


Abstract
This study aimed to evaluate prosthetic complications, implant survival rates, and marginal bone loss in implant-supported monolithic restorations compared to metal-ceramic restorations. The study was registered in PROSPERO (CRD420251022336) and conducted following the Cochrane Handbook for Systematic Reviews of Interventions and PRISMA guidelines. A systematic search was conducted in the electronic databases MEDLINE/PubMed, Web of Science, Scopus, Embase, and ProQuest for articles published up to December 2024. The inclusion criteria comprised studies evaluating only randomized clinical trials that evaluated implant-supported monolithic restorations directly compared to metal-ceramic restorations, considering any type of ceramic material and regardless of the fixation system (screw-retained or cemented), with a minimum follow-up of one year. A meta-analysis was performed using RevMan 5.4 software, and the risk of bias and certainty of evidence were assessed using the RoB 2.0 and GRADE tools, respectively. A total of six studies were included, all of which exclusively evaluated monolithic zirconia single crowns over follow-up periods ranging from 1 to 3 years. None of the included studies evaluated fixed partial dentures or restorative materials other than monolithic zirconia. In total, 267 patients (mean age range: 18–57 years) were analyzed, with a total of 174 implant-supported monolithic zirconia crowns and 165 metal-ceramic single crowns in the posterior region (premolars and molars). The meta-analysis revealed that implant-supported monolithic zirconia single crowns exhibited significantly fewer prosthetic complications compared to metal-ceramic single crowns (p < 0.0001; Risk Ratio [RR]: 0.26; Confidence Interval [CI]: 0.14–0.47). However, no statistically significant differences were observed between implant-supported monolithic zirconia and metal-ceramic single crowns regarding implant survival rates (p = 0.36; RR: 1.66; CI: 0.56–4.94) or marginal bone loss (p = 0.15; Mean Difference [MD]: −0.05; CI: −0.11–0.02). The risk of bias assessment indicated that four studies had a low risk of bias. However, the certainty of evidence was classified as low for prosthetic complications and implant survival rates and very low for marginal bone loss. Within the limitations of this review, it can be concluded that implant-supported monolithic zirconia single crowns can be considered a favorable treatment option as they show comparable implant survival and bone stability to metal-ceramic crowns, with a potential reduction in short-term prosthetic complications such as screw loosening and ceramic chipping. However, due to the limited number of studies included and low certainty of evidence, further long-term research is still needed to confirm their clinical performance over time.
1. Introduction
Dental implants are now a widely accepted and highly successful treatment option for partially or fully edentulous patients, offering substantial benefits to clinicians and patients [1]. Metal-ceramic implant-supported restorations have long been considered a reliable and well-established approach [1,2] primarily due to their high mechanical strength and survival rates, which are important for the longevity of rehabilitative treatments [3,4]. However, metal-ceramic restorations have certain limitations, including constraints associated with manual fabrication methods and suboptimal esthetics properties, which may affect patient acceptance [5].
Recent advancements in digital technologies and the development of novel restorative materials for implant-supported prostheses have significantly expanded treatment possibilities, particularly through CAD/CAM systems [5,6,7]. Ceramic restorations have emerged as a well-established alternative to metal-ceramic restorations due to their superior esthetics, lower bacterial adhesion, reduced gingival discolorations, and shorter processing times with CAD/CAM systems [5]. These restorations can be fabricated using either monolithic or veneered restorations, both of which are viable options for implant-supported single crowns [8]. However, the layering technique presents challenges, including a higher risk of complications related to the core–veneer bond, variations in cooling rates after veneer firings, mismatches in the coefficient of thermal expansion, and the intrinsic properties of the veneering ceramic [2].
To overcome these issues, monolithic zirconia has emerged as a preferred material over veneered restorations due to its reduced risk of technical complications [7]. Monolithic restorations fabricated with CAD/CAM systems also offer advantages such as reduced clinical and laboratory processing time [9], contributing to their increasing popularity in recent years. A recent systematic review assessing the performance of monolithic restorations in implant-supported single crowns concluded that they represent a viable and safe treatment option, with favorable short-term survival rates and a low incidence of prosthetic complications. However, this study exclusively analyzed the prognostics of monolithic restorations without direct comparison. The authors emphasized the need for further research, particularly comparing monolithic and metal-ceramic restorations to provide a more comprehensive understanding of their clinical performance [2].
Therefore, although monolithic restorations are currently considered an excellent treatment option, direct comparisons with well-established materials such as metal-ceramic restorations remain necessary. This systematic review and meta-analysis aimed to evaluate the prosthetic complications, survival rates, and bone loss associated with monolithic implant-supported restorations compared to metal-ceramic implant-supported restorations. The research hypothesis was that no significant differences would be observed between these two types of implant-supported restorations in terms of complications, survival rates, and bone loss.
2. Materials and Methods
2.1. Protocol and Registration
The review was conducted following the Cochrane Handbook or Systematic Reviews of Interventions and in compliance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA). The review protocol was developed and registered in the open-access database PROSPERO (CRD420251022336).
2.2. Eligibility Criteria
The focused question was formulated using the population, intervention, comparison, outcome, and study design (PICOS) framework as follows: “Do monolithic implant-supported restorations exhibit similar rates of prosthetic complications, survival, and marginal bone loss compared to metal-ceramic implant-supported restorations?”. According to the PICO question, the population consisted of patients rehabilitated with implant-supported single crowns or fixed partial dentures. The intervention was defined as monolithic ceramic restorations, while the control group comprised metal-ceramic restorations. The primary outcome was prosthetic complications rates, while secondary outcomes included prosthesis survival rate and marginal bone loss. Only randomized controlled trials (RCTs) were considered for eligibility.
The inclusion criteria were as follows: the comparative evaluation of monolithic and metal-ceramic implant-supported restorations conducted within the same study, considering any type of ceramic material for monolithic crowns, regardless of the retention system (screw-retained or cemented), with a minimum follow-up of one year. In vitro studies, computational studies, case reports, and studies evaluating only monolithic implant-supported restorations without a control group were excluded. No restrictions were applied regarding the publication date or language.
2.3. Search Strategy
A systematic search was conducted across electronic databases, including PubMed/MEDLINE, Web of Science, Scopus, and Embase, as well as ProQuest for grey literature, retrieving articles published up to December 2024. Two independent reviewers (C.A.A.L. and L.C.d.M.F.) performed the search using the electronic website Rayyan QCRI to assist in article selection. The advanced search strategy for each database, including the keywords used, is provided in Supplemental File S1. The initial selection was based on title and abstract screening. Studies deemed eligible underwent full-text analysis and were then included or excluded according to eligibility criteria. Additionally, a manual search of the reference lists of selected studies and other relevant publications was performed to identify potential articles not retrieved in the initial database search.
2.4. Data Extraction
One reviewer (L.C.d.M.F.) extracted data from the selected studies using a standardized pilot form in Microsoft Word (Office 365; version 2407). The extracted data included study authors, year of publication, number of patients, clinical parameters, restorative materials, marginal bone loss, prosthetic complications, survival rates, and follow-up period. A second author (D.S.F.) verified the tabulated data to ensure accuracy and prevent potential errors during the extraction process.
2.5. Data Synthesis
A meta-analysis was performed by one reviewer (C.A.A.L.) using the Mantel–Haenzel and inverse variance methods. Dichotomous outcomes, including prosthetic complications and survival rates, were assessed using the risk ratio (RR). Meanwhile, marginal bone loss, considered a continuous outcome, was evaluated using the mean difference (MD) in millimeters. Statistical significance was set at p < 0.05. When significant heterogeneity was detected (p < 0.10), a random-effects model was adopted; otherwise, a fixed-effects model was used [10]. The meta-analysis was conducted using RevMan 5.4 (Cochrane Group).
2.6. Risk of Bias
The Risk of Bias 2 (RoB 2) tool, a standardized instrument specifically designed for randomized controlled trials, was employed to evaluate potential sources of bias in the included studies. This tool systematically assesses five key domains: randomization process, deviations from intended interventions, missing outcome data, outcome measurement, and a selection of reported results. Each domain was analyzed using signaling questions designed to identify methodological factors relevant to bias risk. Based on these responses, an algorithm generated an overall risk-of-bias judgment for each study, classifying it as low risk, some concerns, or high risk. The use of RoB 2 ensured a transparent and standardized assessment of the methodological validity of the included studies [11].
2.7. Certainty of Evidence
Certainty of evidence was assessed using the Grading of Recommendations Assessment, Development, and Evaluation (GRADE) framework. This methodology evaluates the reliability of evidence for each outcome by considering factors such as study design, inconsistency, indirectness, imprecision, and potential publication bias. Based on these criteria, the certainty of evidence for each outcome was classified into one of four levels: high, moderate, low, or very low. To summarize the findings, GRADEpro GDT software (https://gdt.gradepro.org/app/) accessed on 23 November 2024 was used to generate summary of findings tables [12].
3. Results
3.1. Study Selection
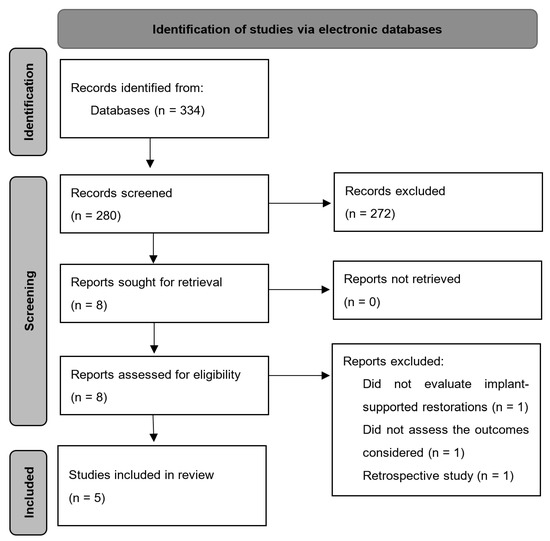
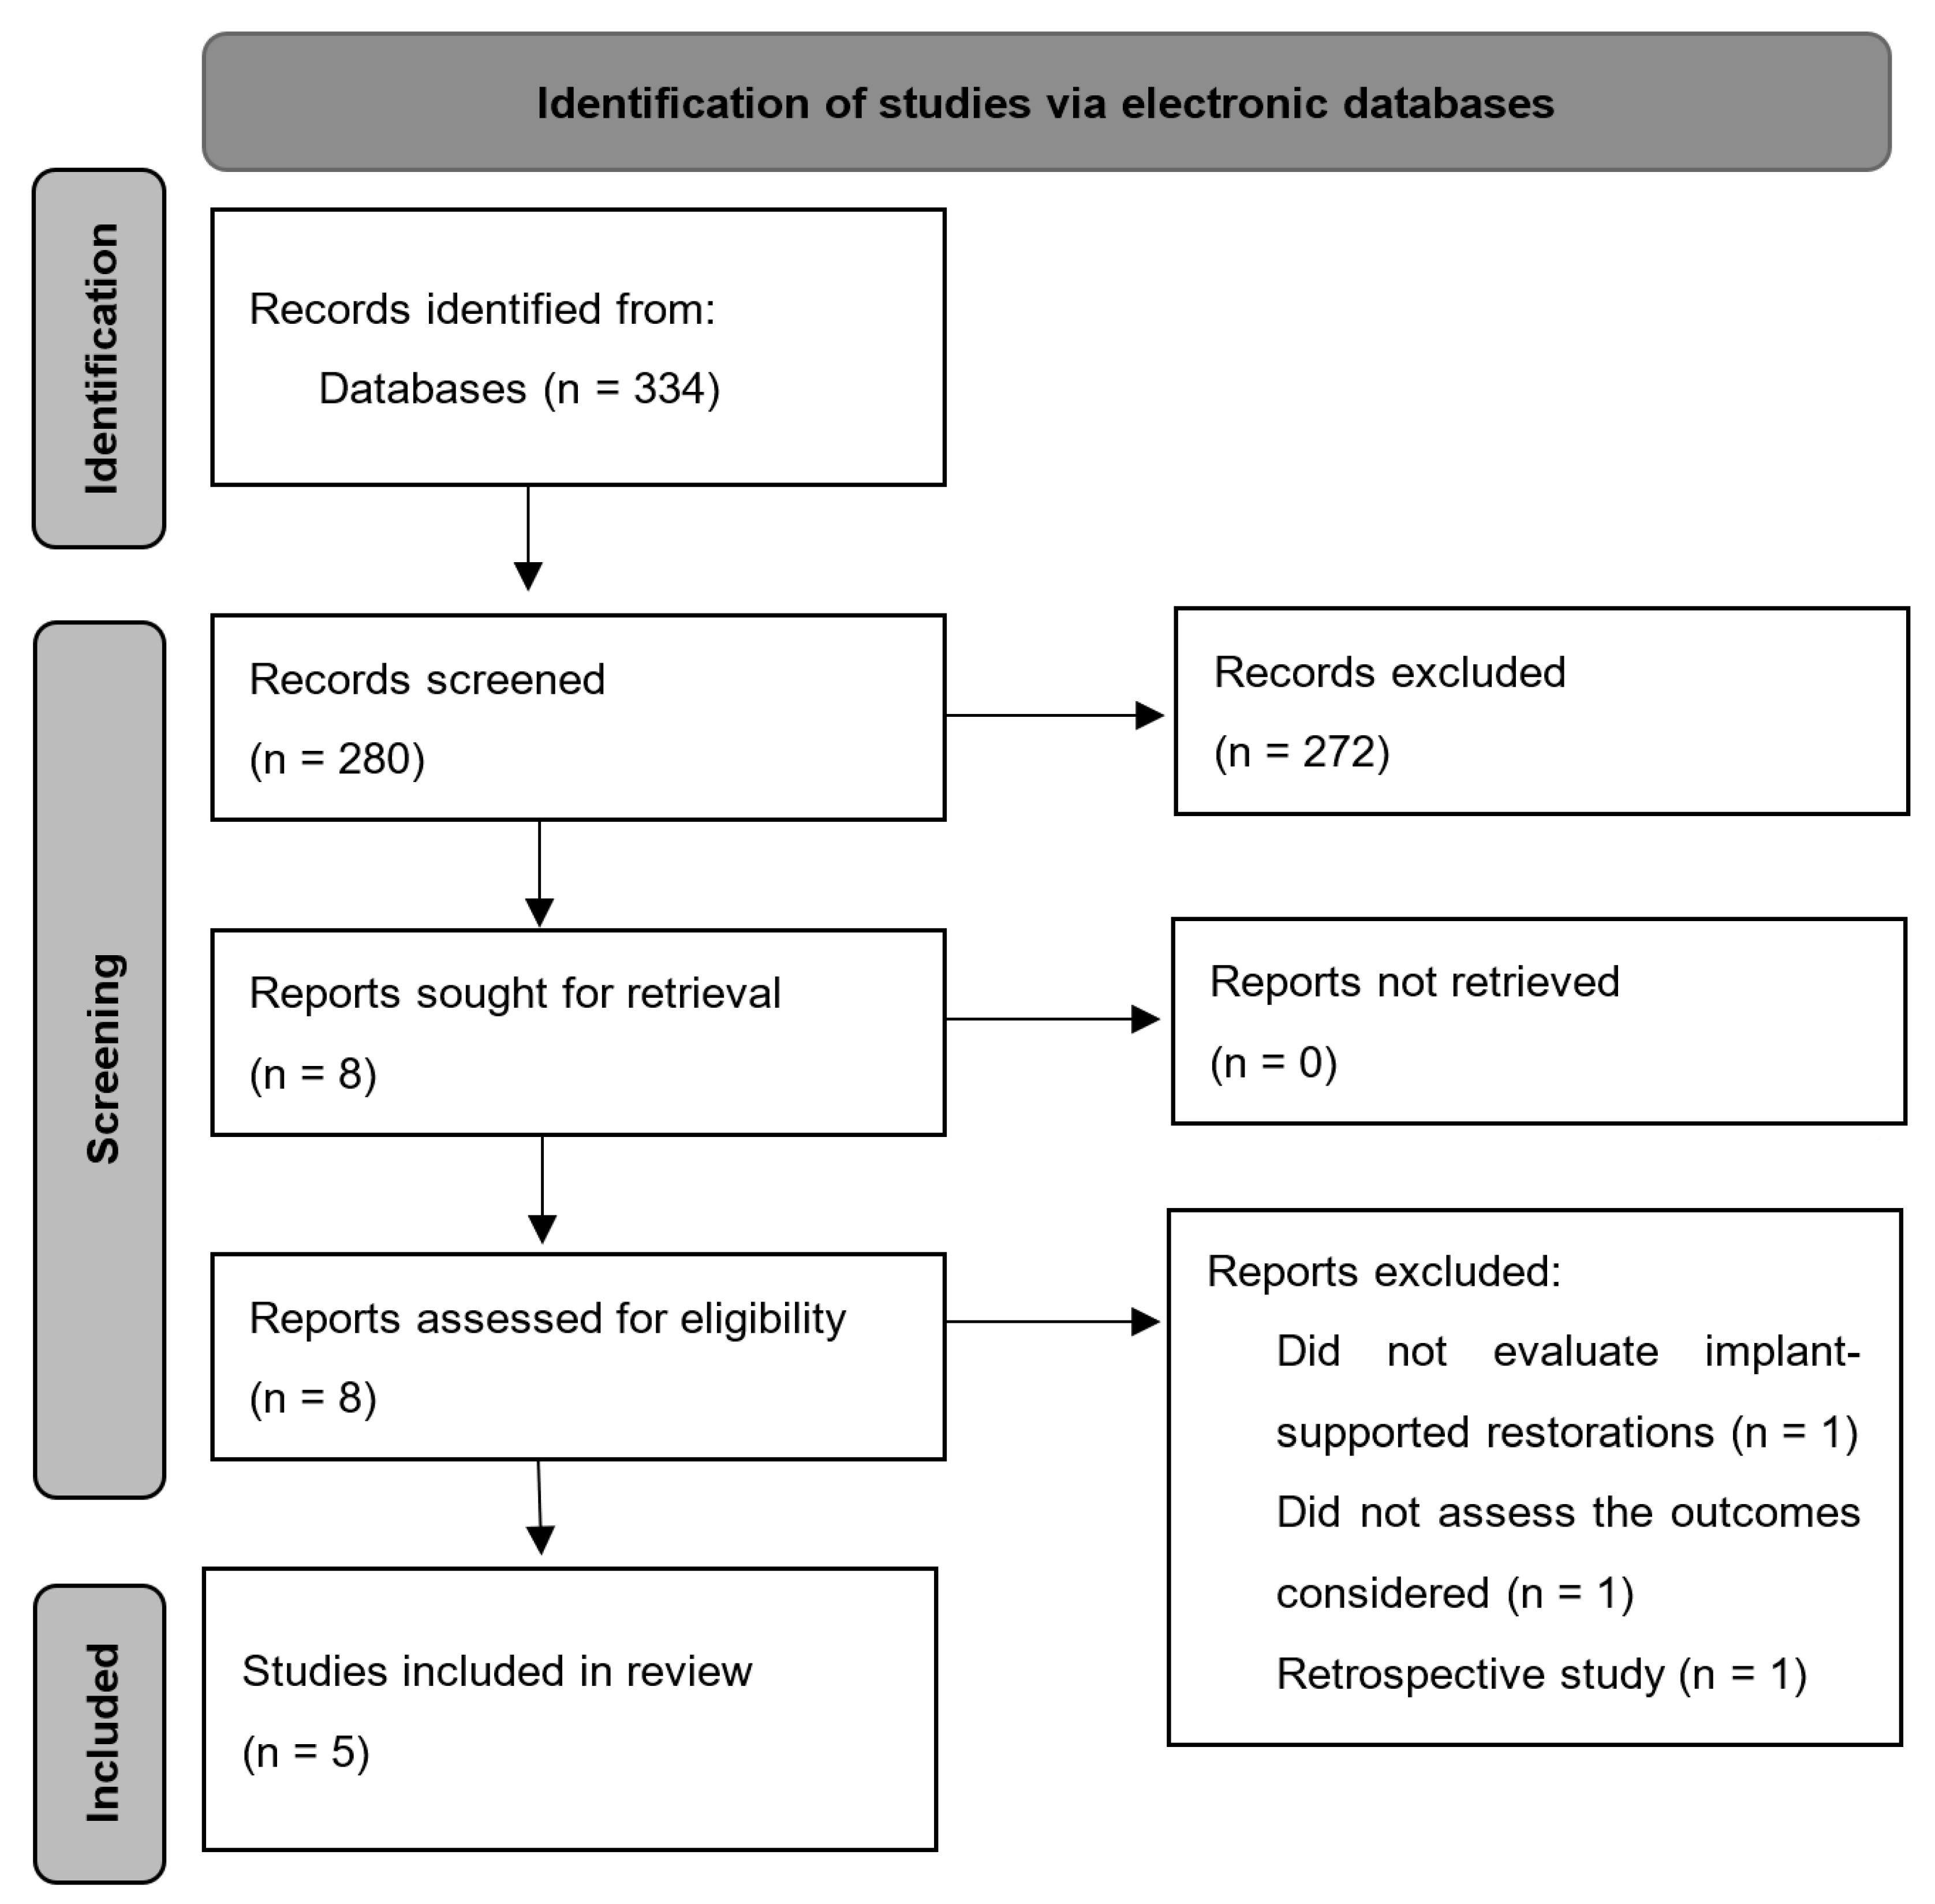
The electronic database search identified a total of 334 studies, with 54 sourced from Scopus, 30 from Web of Science, 105 from PubMed, 137 from Embase, and 8 from ProQuest. After removing 54 duplicate studies, 280 studies remained for title and abstract screening. Of these, based on pre-established eligibility criteria, eight articles were deemed eligible for full-text reading. Of these, five studies were included in this systematic review and meta-analysis. Three articles were excluded: one because it did not evaluate implant-supported restorations [13], one because it did not assess the outcomes considered in this systematic review [14], and one because it was a retrospective study [3]. The entire selection process is illustrated in Figure 1.
Figure 1.
Flow diagram illustrating the search strategy.
3.2. Characteristics of Included Studies
A total of six studies were included in this systematic review [4,15,16,17,18,19], all published between 2018 and 2025. The included studies exclusively evaluated monolithic zirconia single crowns, with no assessment of fixed partial dentures or other restorative materials. In total, 267 patients, with a mean age ranged from 18 to 57 years, were analyzed, encompassing 174 implant-supported monolithic zirconia and 165 metal-ceramic single crowns in the posterior region (premolars and molars). Various implant systems were used in the included studies, with three studies evaluating internal connection implants [4,15,16,19] and two studies evaluating external connection implants [17,18]. Regarding prosthesis retention, four studies exclusively examined screw-retained restorations [16,17,18,19], one study focused solely on cement-retained restorations [15], and one study included both [4] (Table 1).
Table 1.
Characteristics of included studies (n = 5).
3.3. Meta-Analysis
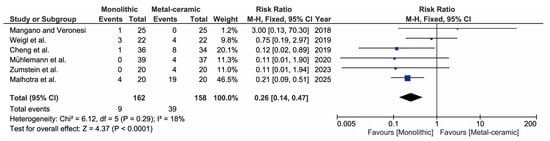
In a quantitative analysis of complication rates, monolithic zirconia single crowns exhibited significantly fewer complications than metal-ceramic single crowns (p < 0.0001; RR: 0.26; Confidence Interval [CI]: 0.14 to 0.47). No significant heterogeneity was detected in the analysis (p = 0.29; I2 = 18%) (Figure 2). Among the reported complications, metal-ceramic prostheses demonstrated a high incidence of screw loosening [16,19], loss of retention [4,16], abutment fracture [19], and chipping or fracture of the veneering material [4,16,17,19].
Figure 2.
Forest plot of prosthetic complications. Article references (from top to bottom): [4,15,16,17,18,19]. The position of the black diamond represents the estimated effect size, while its width indicates the precision of the estimate. The size of each blue square reflects the weight of the corresponding study in the analysis.
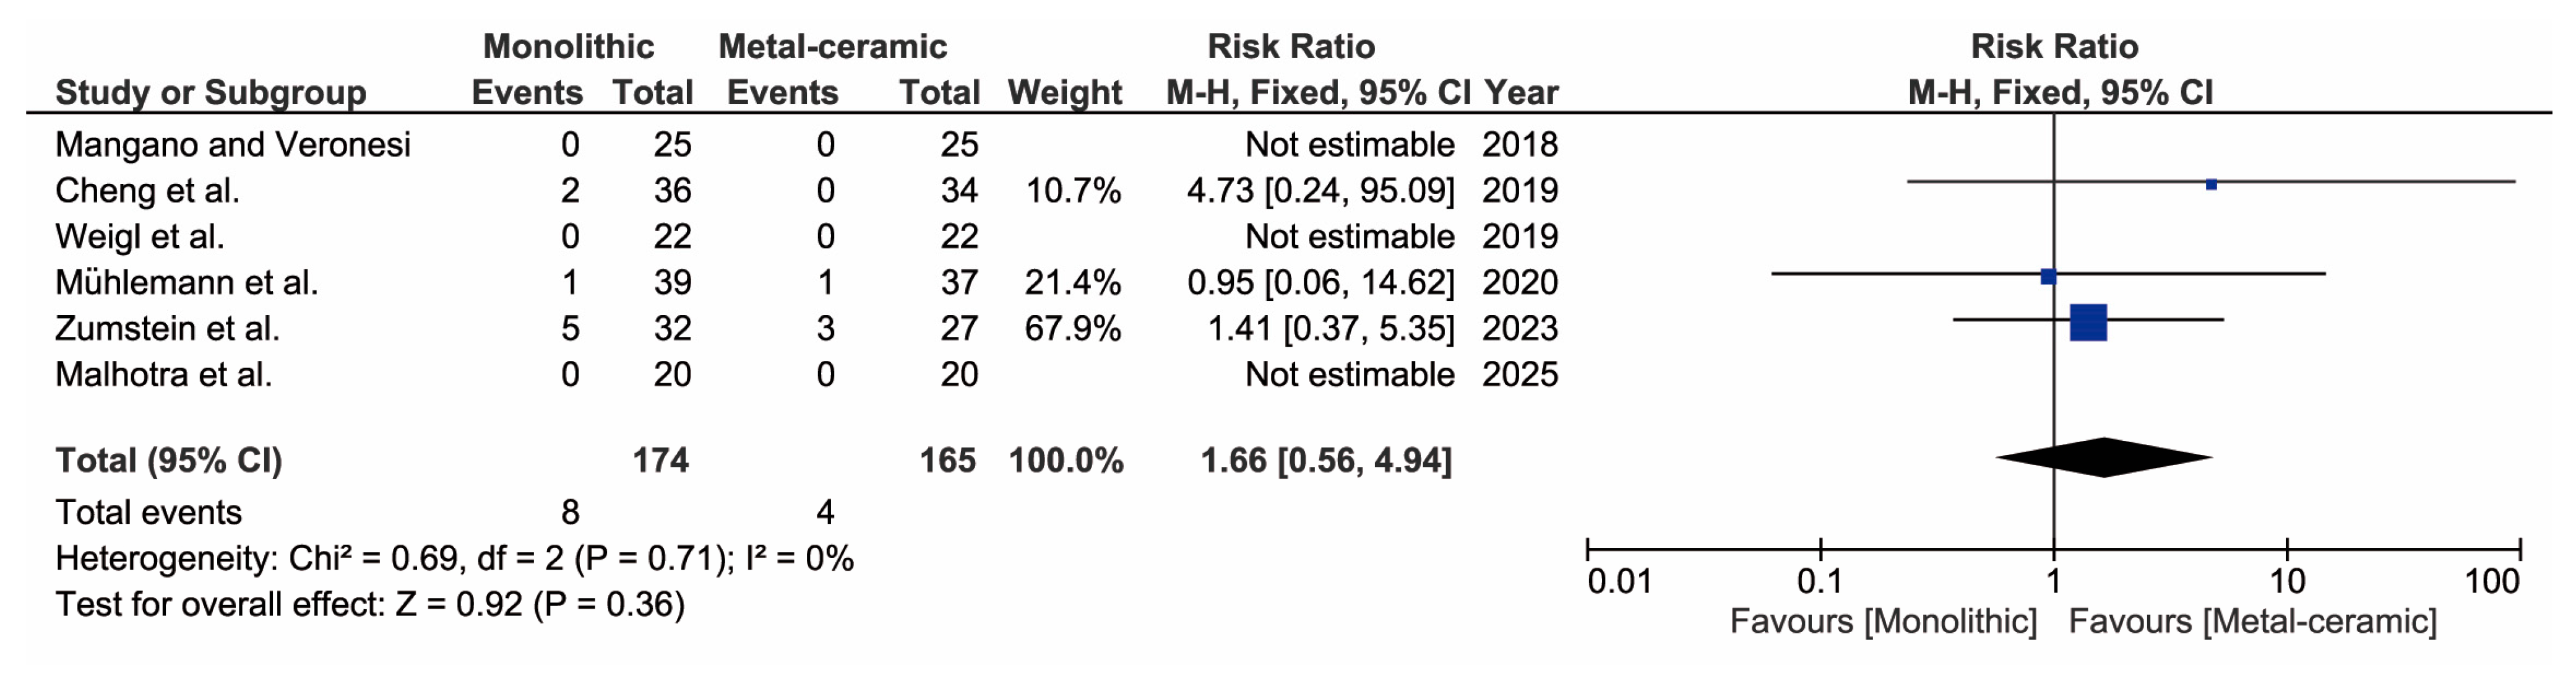
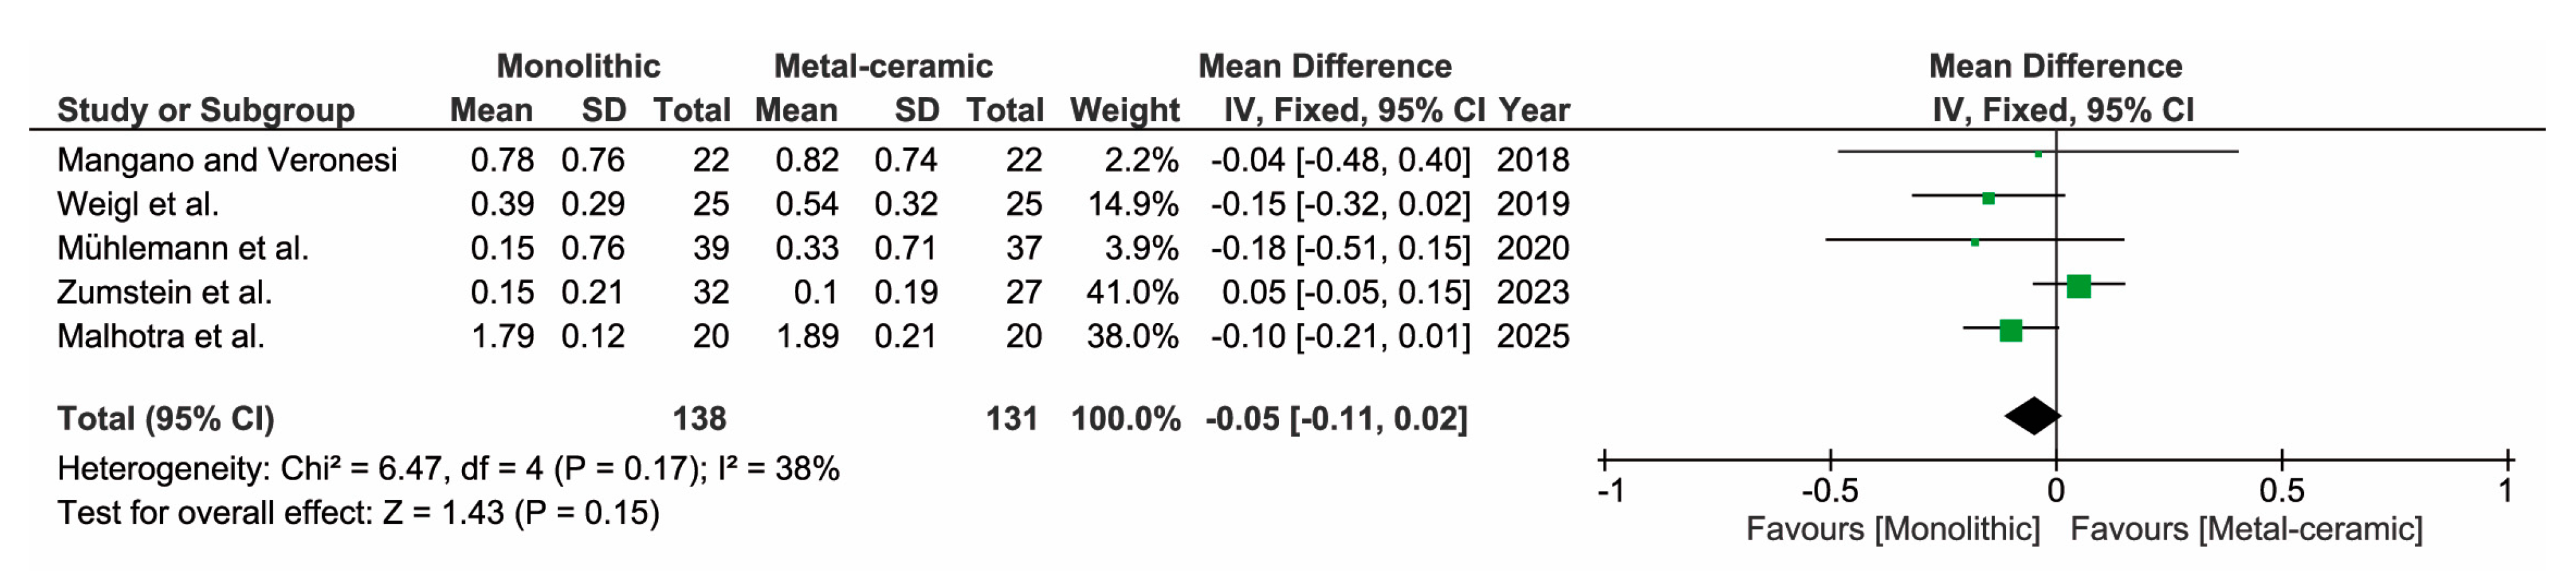
Implant survival rates of monolithic zirconia versus metal-ceramic implant-supported single crowns were not significantly influenced by the restorative material (p = 0.36; RR: 1.66; CI: 0.56 to 4.94). No significant heterogeneity was observed in this analysis (p = 0.71; I2 = 0%) (Figure 3). Additionally, three studies [4,15,19] reported no failures. Similarly, no significant influence of the restorative material on marginal bone loss in implant-supported single crowns was observed (p = 0.15; MD: −0.05; CI: −0.11 to 0.02). Although an increase in heterogeneity values was noted, it remained non-significant (p = 0.17; I2 = 38%) (Figure 4).
Figure 3.
Forest plot of implant survival rates. Article references (from top to bottom): [4,15,16,17,18,19]. The position of the black diamond represents the estimated effect size, while its width indicates the precision of the estimate. The size of each blue square reflects the weight of the corresponding study in the analysis.
Figure 4.
Forest plot of marginal bone loss. Article references (from top to bottom): [4,15,17,18,19]. The position of the black diamond represents the estimated effect size, while its width indicates the precision of the estimate. The size of each green square reflects the weight of the corresponding study in the analysis.
3.4. Risk of Bias
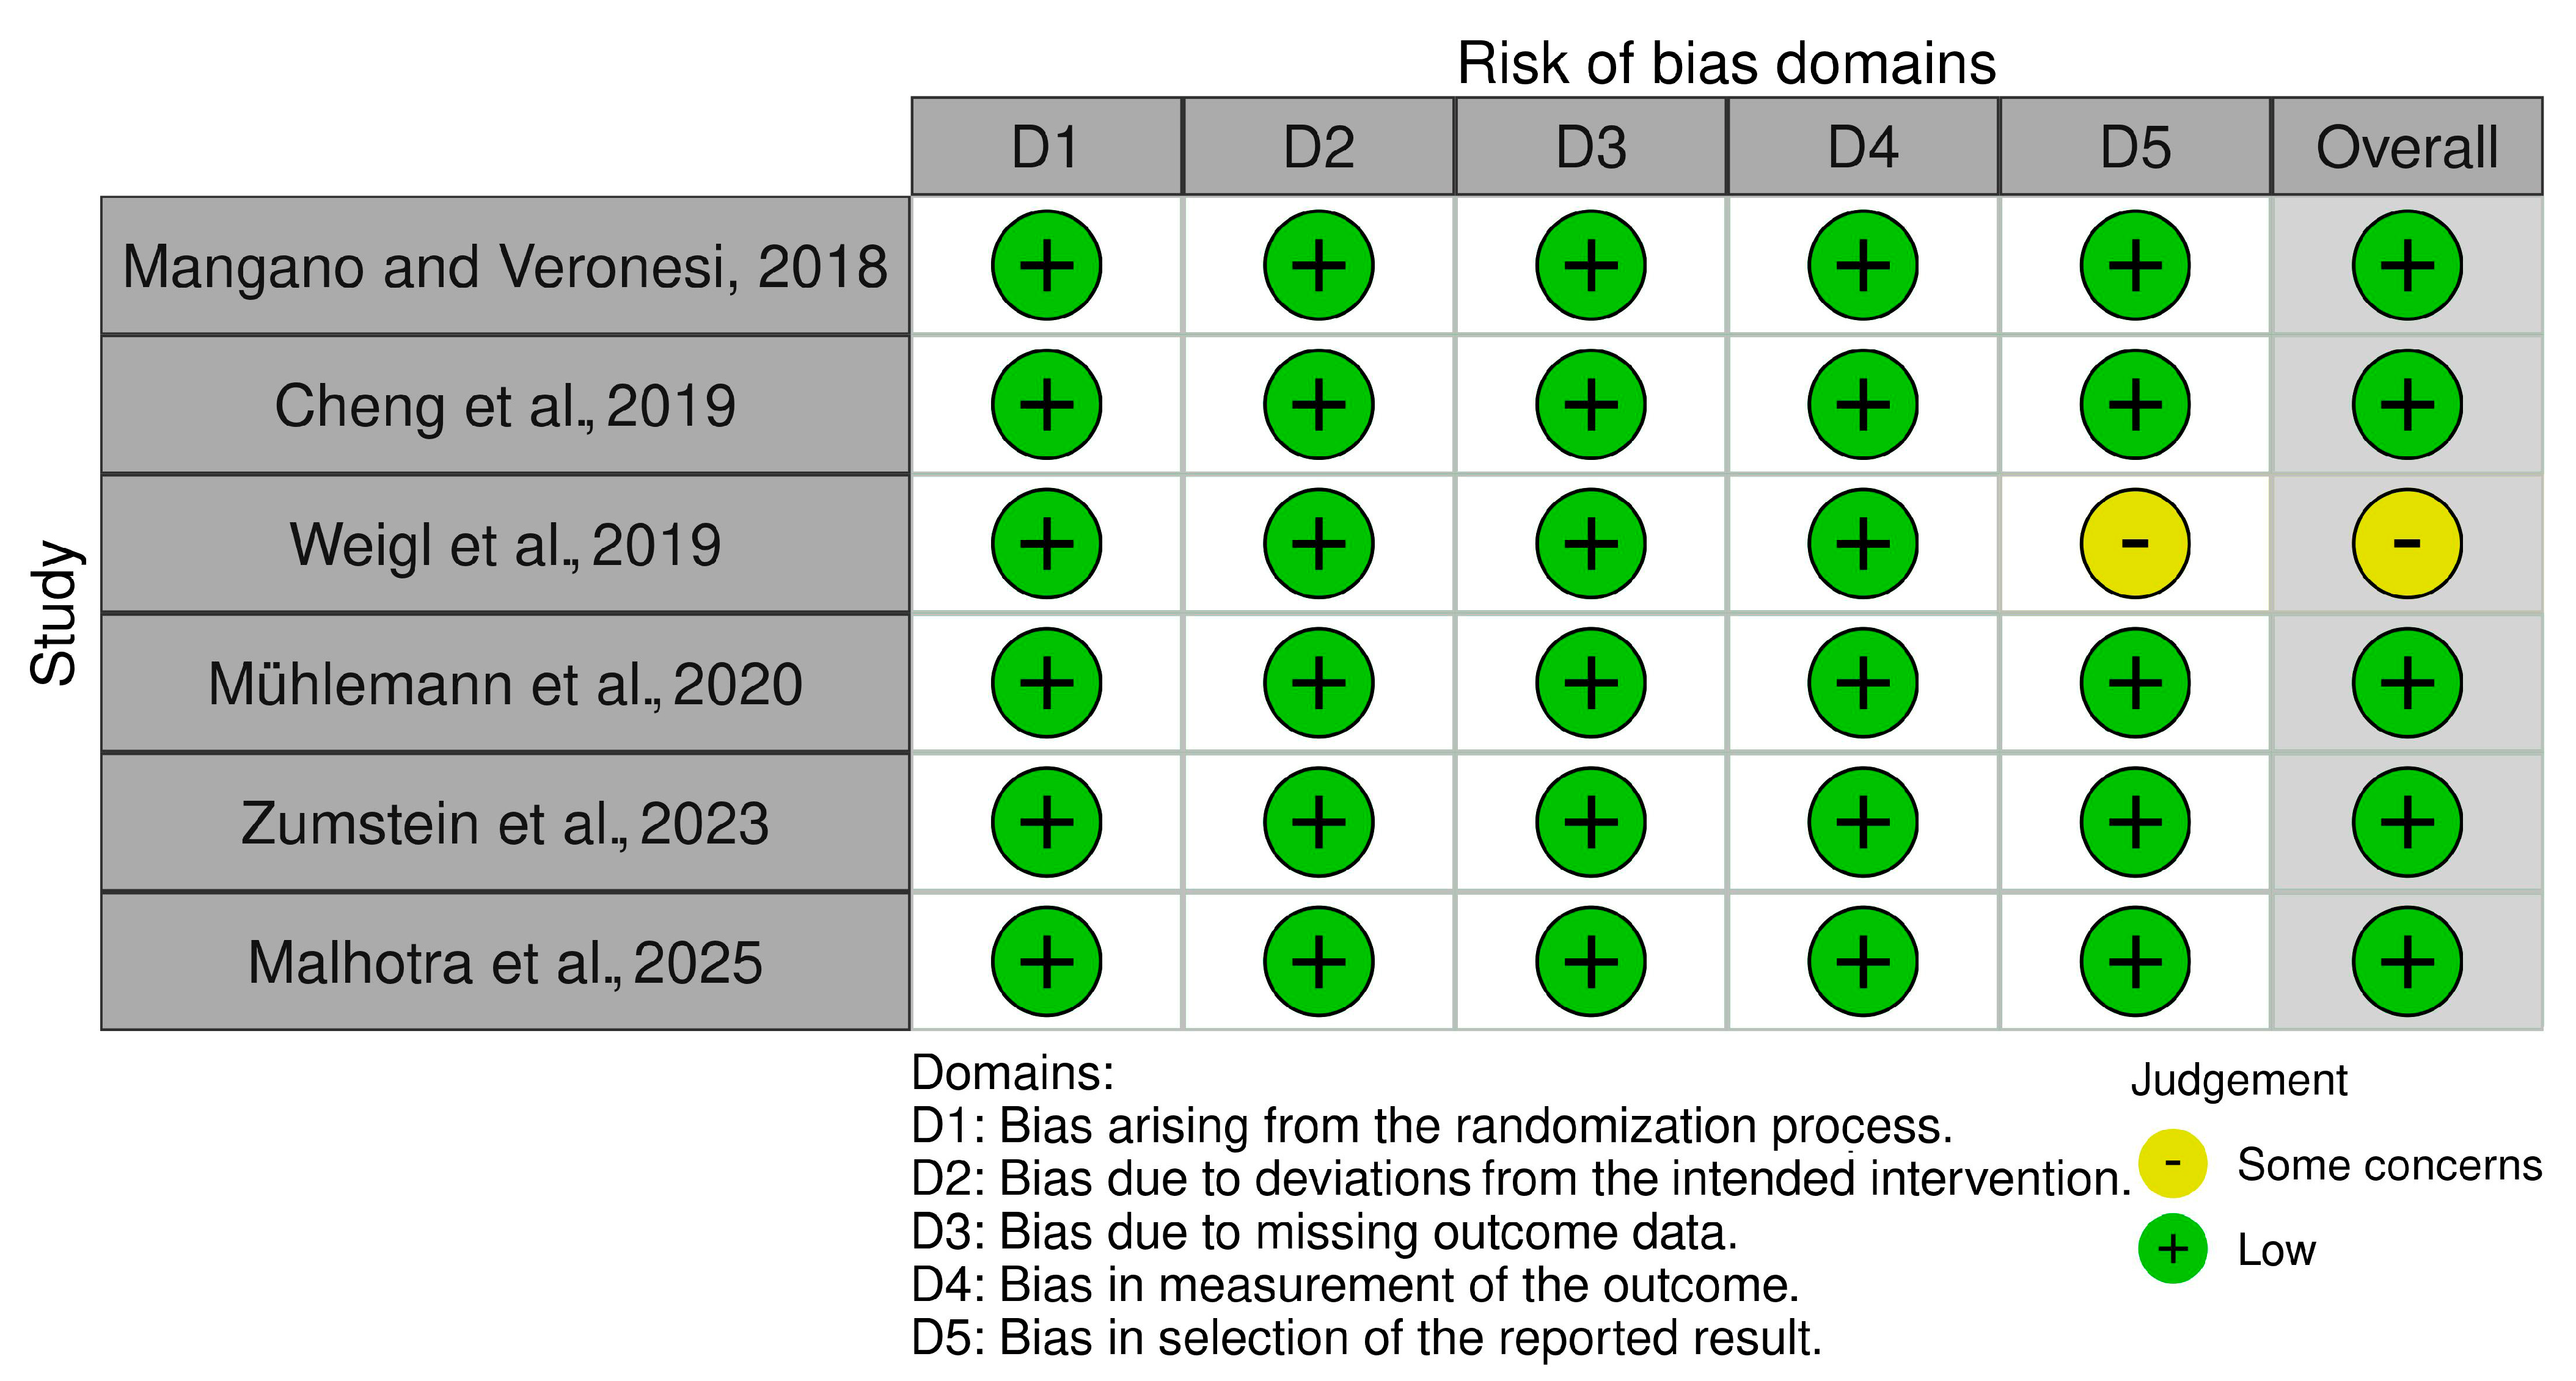
Regarding the risk of bias assessment, four studies [15,16,17,18,19] were classified as having a low risk of bias as they adequately reported all assessed domains. Conversely, one study [4] was classified as having “some concerns” due to potential reporting bias in the study outcomes (Figure 5).
Figure 5.
Risk of bias of included studies using RoB 2.0 tool. Article references (from top to bottom): [4,15,16,17,18,19].
3.5. Certainty of Evidence
The certainty of evidence was rated as low for prosthetic complications and implant survival rates, and very low for marginal bone loss. All three outcomes were downgraded by two levels due to the small optimal information size as only five studies were included. Additionally, marginal bone loss was downgraded by one more level due to high heterogeneity, contributing to inconsistency of the analysis. No upgrades were applied for large effects, plausible confounding factors, or dose–response gradients (Table 2).
Table 2.
Certainty of evidence of outcomes evaluated.
4. Discussion
The hypothesis partially failed to be rejected as no differences were observed between restorative materials regarding implant survival rates and marginal bone loss; however, implant-supported monolithic single crowns exhibited a lower incidence of complications compared to metal-ceramic single crowns.
The lower incidence of chipping in monolithic zirconia single crowns may be attributed to the absence of layered interfaces. This structural characteristic helps prevent failures and crack propagation, reducing complications in the restorative material [2]. The included studies reported a higher incidence of chipping in metal-ceramic restorations [4,16,17,18,19]. Veneered ceramic restorations are influenced by technique-sensitive procedures, where bonding between copings and veneering ceramics, as well as residual stress generation during ceramic cooling, can compromise interface restoration [20,21,22]. Laboratory studies have also recommended monolithic ceramic materials to minimize failure rates [23,24]. Another important factor contributing to these results is that all included studies evaluated monolithic zirconia single crowns. Zirconia materials exhibit high resistance to chipping and fracture [4,25], and their use in monolithic form may provide greater durability compared to bilayer restorations [4].
Screw loosening was another frequently observed complication. Cheng et al. [16] reported that monolithic zirconia single crowns had a significantly lower screw loosening rate (2.9%) compared to metal-ceramic single crowns (14.7%) after one year of follow-up. Several factors may explain this discrepancy between restorative materials, including the fixation systems. In this study, only one screw-retained monolithic zirconia single crown exhibited screw loosening (9.1%), whereas screw-retained metal-ceramic single crowns had a significantly higher rate (45.5%). In contrast, none of the cemented restorations, regardless of the restorative material, presented screw loosening [16], suggesting that this complication is less frequent in cemented restorations [5].
Another possible explanation is that the manual fabrication process of metal-ceramic restorations may contribute to increased marginal misfit in implant-supported prostheses, leading to stress accumulation around the screw and consequently causing its loosening or fracture [26]. Additionally, the study that reported a higher incidence of screw loosening [16] evaluated restorative materials on implants with an internal octagonal connection, whereas most other studies analyzed implants with an internal conical connection, which may have influenced the increased screw in their findings [27]. These factors suggest that the incidence of screw loosening may be more influenced by fixation systems, prosthetic fabrication method, and implant connection design than by the type of restorative material. Given the limited number of studies included in this systematic review, further research is recommended to reassess these findings.
Regarding overall clinical performance, both crown types demonstrated high success rates and marginal bone stability, regardless of the restorative material. These findings align with biomechanical studies suggesting that the choice of restorative material has minimal influence on stress distribution in bone tissue or implants [28,29]. However, the short follow-up periods in the included studies may account for the absence of significant differences in these outcomes. Most of the included studies had a follow-up period of only one year. This represents a limitation as one year is relatively short for assessing long-term parameters. Therefore, these findings should be interpreted with caution, and further studies with longer follow-up periods are recommended.
Digitally manufactured monolithic crowns using CAD/CAM technology may improve efficiency in terms of treatment time and cost, benefiting both clinical and laboratory workflows. The optimization of laboratory time enhances the advantages of digital workflows. Additionally, digital case documentation allows for modifications and remakes without the need for a new scan, which is particularly beneficial in cases requiring retreatment [15]. However, despite longer production times and higher costs, metal-ceramic crowns continue to demonstrate high clinical reliability [15].
A relevant concern is the durability and resistance of implant-supported monolithic zirconia single crowns, particularly in bruxism patients, who are at a higher risk of chipping. Cheng et al. [16] rehabilitated 11 patients diagnosed with bruxism, with six receiving implant-supported monolithic single crowns and five receiving metal-ceramic single crowns. They reported that screw loosening occurred predominantly in the bruxism group, suggesting that parafunctional overloads contribute to increased stress in implants and prosthetic components, thereby elevating the likelihood of prosthetic complications. These findings align with a biomechanical study showing that parafunctional loads negatively affect the prosthetic components of implant-supported prostheses [30].
Despite the findings of this systematic review, the choice between implant-supported monolithic zirconia and metal-ceramic single crowns should be tailored to individual patient needs, considering factors such as occlusion, esthetics, and periodontal history. This highlights the importance of a personalized treatment approach [4]. One of the included studies evaluated patient satisfaction and reported similar outcomes for both crown types, suggesting that strength and functionality are often prioritized over esthetics. However, it is important to note that this study focused exclusively on single crowns in the posterior region, where esthetic concerns may be of lesser importance to patients [17]. Therefore, studies assessing anterior restorations are essential.
This study has certain limitations that should be considered when interpreting the results. The primary limitation is the short follow-up period of the included studies as a longer observation time is often necessary for a comprehensive evaluation of prosthetic outcomes. Among the six included studies, only two [18,19] reported follow-up periods longer than one year; however, these were limited to 2 and 3 years, which are still considered insufficient for a thorough assessment of prosthetic parameters, especially given that some studies recommend follow-up periods longer than 5 years [31]. Additionally, the limited number of included studies may affect the reliability of effect estimates and hinder subgroup analyses, such as the evaluation of fixation systems (cemented vs. screw-retained) and implant–abutment connection types. This should be acknowledged as a limitation as previous systematic reviews have demonstrated that differences in retention systems [32], abutment types [33], and implant connection designs [27] can influence clinical outcomes, underscoring the importance of these variables in the evaluation of implant-supported restorations. Another limitation is that only single implant-supported crowns were analyzed, which restricts the generalizability of results for implant-supported fixed partial dentures. Therefore, well-designed long-term clinical studies are needed to further assess the influence of implant-supported monolithic crowns compared to metal-ceramic crowns.
5. Conclusions
Within the limitations of this systematic review and meta-analysis, it can be concluded that implant-supported monolithic zirconia single crowns demonstrate implant survival rates and peri-implant bone stability comparable to metal-ceramic single crowns. However, their use may help reduce short-term prosthetic complications, such as screw loosening and chipping of the restorative material. Nonetheless, long-term studies are necessary to evaluate the durability and clinical performance of these crowns over time.
Supplementary Materials
The following supporting information can be downloaded at https://www.mdpi.com/article/10.3390/ceramics8020063/s1, Supplementary File S1: Search strategies in different databases.
Author Contributions
L.C.d.M.F.: acquisition analysis, interpretation of data for the work, drafting the work, and final approval of the version; D.S.F.: acquisition analysis, reviewing it critically for important intellectual content; and final approval of the version; B.N.F.: drafting the work and final approval of the version; I.d.C.: acquisition analysis, reviewing it critically for important intellectual content, and final approval of the version; J.S.M.: reviewing it critically for important intellectual content and final approval of the version; C.A.A.L.: conceptualization, supervision, drafting the work, and final approval of the version. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Pjetursson, B.E.; Valente, N.A.; Strasding, M.; Zwahlen, M.; Liu, S.; Sailer, I. A systematic review of the survival and complication rates of zirconia-ceramic and metal-ceramic single crowns. Clin. Oral Implant. Res. 2018, 29 (Suppl. S16), 199–214. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lemos, C.A.A.; Verri, F.R.; de Luna Gomes, J.M.; Santiago Junior, J.F.; Miyashita, E.; Mendonca, G.; Pellizzer, E.P. Survival and prosthetic complications of monolithic ceramic implant-supported single crowns and fixed partial dentures: A systematic review with meta-analysis. J. Prosthet. Dent. 2024, 132, 1237–1249. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shen, X.T.; Li, J.Y.; Luo, X.; Feng, Y.; Gai, L.T.; He, F.M. Peri-implant marginal bone changes with implant-supported metal-ceramic or monolithic zirconia single crowns: A retrospective clinical study of 1 to 5 years. J. Prosthet. Dent. 2022, 128, 368–374. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weigl, P.; Saarepera, K.; Hinrikus, K.; Wu, Y.; Trimpou, G.; Lorenz, J. Screw-retained monolithic zirconia vs. cemented porcelain-fused-to-metal implant crowns: A prospective randomized clinical trial in split-mouth design. Clin. Oral Investig. 2019, 23, 1067–1075. [Google Scholar] [CrossRef] [Scilit]
- Lemos, C.A.A.; Verri, F.R.; Gomes, J.M.L.; de Souza Batista, V.E.; Cruz, R.S.; Oliveira, H.; Pellizzer, E.P. Ceramic versus metal-ceramic implant-supported prostheses: A systematic review and meta-analysis. J. Prosthet. Dent. 2019, 121, 879–886.e4. [Google Scholar] [CrossRef] [Scilit]
- Derksen, W.; Joda, T.; Chantler, J.; Fehmer, V.; Gallucci, G.O.; Gierthmuehlen, P.C.; Ioannidis, A.; Karasan, D.; Lanis, A.; Pala, K.; et al. Group 2 ITI Consensus Report: Technological developments in implant prosthetics. Clin. Oral Implant. Res. 2023, 34 (Suppl. S26), 104–111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pjetursson, B.E.; Sailer, I.; Merino-Higuera, E.; Spies, B.C.; Burkhardt, F.; Karasan, D. Systematic review evaluating the influence of the prosthetic material and prosthetic design on the clinical outcomes of implant-supported multi-unit fixed dental prosthesis in the posterior area. Clin. Oral Implant. Res. 2023, 34 (Suppl. S26), 86–103. [Google Scholar] [CrossRef] [Scilit]
- Pjetursson, B.E.; Fehmer, V.; Sailer, I. EAO Position Paper: Material Selection for Implant-Supported Restorations. Int. J. Prosthodont. 2022, 35, 7–16. [Google Scholar] [CrossRef] [Scilit]
- Mühlemann, S.; Kraus, R.D.; Hämmerle, C.H.F.; Thoma, D.S. Is the use of digital technologies for the fabrication of implant-supported reconstructions more efficient and/or more effective than conventional techniques: A systematic review. Clin. Oral Implant. Res. 2018, 29 (Suppl. S18), 184–195. [Google Scholar] [CrossRef] [Scilit]
- Egger, M.; Smith, G.D.; Phillips, A.N. Meta-analysis: Principles and procedures. BMJ 1997, 315, 1533–1537. [Google Scholar] [CrossRef] [Scilit]
- Sterne, J.A.C.; Savovic, J.; Page, M.J.; Elbers, R.G.; Blencowe, N.S.; Boutron, I.; Cates, C.J.; Cheng, H.Y.; Corbett, M.S.; Eldridge, S.M.; et al. RoB 2: A revised tool for assessing risk of bias in randomised trials. BMJ 2019, 366, l4898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guyatt, G.; Oxman, A.D.; Akl, E.A.; Kunz, R.; Vist, G.; Brozek, J.; Norris, S.; Falck-Ytter, Y.; Glasziou, P.; DeBeer, H.; et al. GRADE guidelines: 1. Introduction-GRADE evidence profiles and summary of findings tables. J. Clin. Epidemiol. 2011, 64, 383–394. [Google Scholar] [CrossRef] [Scilit]
- Batson, E.R.; Cooper, L.F.; Duqum, I.; Mendonça, G. Clinical outcomes of three different crown systems with CAD/CAM technology. J. Prosthet. Dent. 2014, 112, 770–777. [Google Scholar] [CrossRef] [Scilit]
- Alarcón-Sánchez, M.A.; Castro-Alarcón, N.; Sandoval-Guevara, D.; Vázquez-Villamar, M.; Fernández-Acosta, K.; Méndez-Gómez, M.Y.; Parra-Rojas, I.; Romero-Castro, N.S. Analysis of subgingival microbiota and IL-1β, TNF-α and CX3CL1 levels in gingival crevicular fluid of fixed dental prostheses. Dent. Mater. J. 2024, 43, 235–246. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mangano, F.; Veronesi, G. Digital versus Analog Procedures for the Prosthetic Restoration of Single Implants: A Randomized Controlled Trial with 1 Year of Follow-Up. Biomed. Res. Int. 2018, 2018, 5325032. [Google Scholar] [CrossRef] [Scilit]
- Cheng, C.W.; Chien, C.H.; Chen, C.J.; Papaspyridakos, P. Randomized Controlled Clinical Trial to Compare Posterior Implant-Supported Modified Monolithic Zirconia and Metal-Ceramic Single Crowns: One-Year Results. J. Prosthodont. 2019, 28, 15–21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mühlemann, S.; Lakha, T.; Jung, R.E.; Hämmerle, C.H.F.; Benic, G.I. Prosthetic outcomes and clinical performance of CAD-CAM monolithic zirconia versus porcelain-fused-to-metal implant crowns in the molar region: 1-year results of a RCT. Clin. Oral Implant. Res. 2020, 31, 856–864. [Google Scholar] [CrossRef] [Scilit]
- Zumstein, K.; Waller, T.; Hämmerle, C.H.F.; Jung, R.E.; Benic, G.; Mühlemann, S. Clinical performance of monolithic zirconia crowns on titanium-zirconium reduced-diameter implants in the molar area: Interim data at three years of a randomized controlled trial. Clin. Oral Implant. Res. 2023, 34, 1354–1362. [Google Scholar] [CrossRef] [Scilit]
- Malhotra, T.; Kumar Yadav, B.; Singh Phukela, S.; Bhardwaj, A.; Khandait, M.; Nagpal, A.; Shetty, O. A Comparative Evaluation of Prosthetic and Biologic Outcomes as Influenced by Two Different Implant Restorative Materials: A Prospective, Split-Mouth Study. Int. J. Prosthodont. 2025, 38, 35–45. [Google Scholar]
- Zhang, Y.; Kelly, J.R. Dental Ceramics for Restoration and Metal Veneering. Dent. Clin. N. Am. 2017, 61, 797–819. [Google Scholar] [CrossRef] [Scilit]
- Lee, J.T.; Lee, H.J.; Park, S.Y.; Kim, H.Y.; Yeo, I.S. Consecutive unsplinted implant-supported restorations to replace lost multiple adjacent posterior teeth: A 4-year prospective cohort study. Acta Odontol. Scand. 2015, 73, 461–466. [Google Scholar] [CrossRef] [Scilit]
- Esquivel-Upshaw, J.F.; Clark, A.E.; Shuster, J.J.; Anusavice, K.J. Randomized clinical trial of implant-supported ceramic-ceramic and metal-ceramic fixed dental prostheses: Preliminary results. J. Prosthodont. 2014, 23, 73–82. [Google Scholar] [CrossRef] [Scilit]
- Lopez-Suarez, C.; Tobar, C.; Sola-Ruiz, M.F.; Pelaez, J.; Suarez, M.J. Effect of Thermomechanical and Static Loading on the Load to Fracture of Metal-Ceramic, Monolithic, and Veneered Zirconia Posterior Fixed Partial Dentures. J. Prosthodont. 2019, 28, 171–178. [Google Scholar] [CrossRef] [Scilit]
- López-Suárez, C.; Castillo-Oyagüe, R.; Rodríguez-Alonso, V.; Lynch, C.D.; Suárez-García, M.J. Fracture load of metal-ceramic, monolithic, and bi-layered zirconia-based posterior fixed dental prostheses after thermo-mechanical cycling. J. Dent. 2018, 73, 97–104. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coray, R.; Zeltner, M.; Ozcan, M. Fracture strength of implant abutments after fatigue testing: A systematic review and a meta-analysis. J. Mech. Behav. Biomed. Mater. 2016, 62, 333–346. [Google Scholar] [CrossRef] [Scilit]
- Mello, C.C.; Santiago Junior, J.F.; Lemos, C.A.A.; Galhano, G.A.; Evangelisti, E.; Scotti, R.; Verri, F.R.; Pellizzer, E.P. Evaluation of the accuracy and stress distribution of 3-unit implant supported prostheses obtained by different manufacturing methods. Mater. Sci. Eng. C Mater. Biol. Appl. 2019, 102, 66–74. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rodrigues, V.V.M.; Fae, D.S.; Rosa, C.; Bento, V.A.A.; Lacerda, M.; Pellizzer, E.P.; Lemos, C.A.A. Is the clinical performance of internal conical connection better than internal non-conical connection for implant-supported restorations? A systematic review with meta-analysis of randomized controlled trials. J. Prosthodont. 2023, 32, 382–391. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lemos, C.A.A.; Verri, F.R.; Noritomi, P.Y.; de Souza Batista, V.E.; Cruz, R.S.; de Luna Gomes, J.M.; de Oliveira Limírio, J.P.J.; Pellizzer, E.P. Biomechanical Evaluation of Different Implant-Abutment Connections, Retention Systems, and Restorative Materials in the Implant-Supported Single Crowns Using 3D Finite Element Analysis. J. Oral Implantol. 2022, 48, 194–201. [Google Scholar] [CrossRef] [Scilit]
- Santiago Junior, J.F.; Pellizzer, E.P.; Verri, F.R.; de Carvalho, P.S. Stress analysis in bone tissue around single implants with different diameters and veneering materials: A 3-D finite element study. Mater. Sci. Eng. C Mater. Biol. Appl. 2013, 33, 4700–4714. [Google Scholar] [CrossRef] [Scilit]
- Borges Radaelli, M.T.; Idogava, H.T.; Spazzin, A.O.; Noritomi, P.Y.; Boscato, N. Parafunctional loading and occlusal device on stress distribution around implants: A 3D finite element analysis. J. Prosthet. Dent. 2018, 120, 565–572. [Google Scholar] [CrossRef] [Scilit]
- de Luna Gomes, J.M.; Lemos, C.A.A.; Santiago Junior, J.F.; de Moraes, S.L.D.; Goiato, M.C.; Pellizzer, E.P. Optimal number of implants for complete-arch implant-supported prostheses with a follow-up of at least 5 years: A systematic review and meta-analysis. J. Prosthet. Dent. 2019, 121, 766–774.e3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lemos, C.A.; de Souza Batista, V.E.; Almeida, D.A.; Santiago Júnior, J.F.; Verri, F.R.; Pellizzer, E.P. Evaluation of cement-retained versus screw-retained implant-supported restorations for marginal bone loss: A systematic review and meta-analysis. J. Prosthet. Dent. 2016, 115, 419–427. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Canullo, L.; Pesce, P.; Patini, R.; Antonacci, D.; Tommasato, G. What Are the Effects of Different Abutment Morphologies on Peri-implant Hard and Soft Tissue Behavior? A Systematic Review and Meta-Analysis. Int. J. Prosthodont. 2020, 33, 297–306. [Google Scholar] [CrossRef]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).