Relationship Between Scheimpflug-Based Ocular Biomechanics and Myopic Maculopathy

 , , ,
Abstract
1. Introduction
2. Materials and Methods
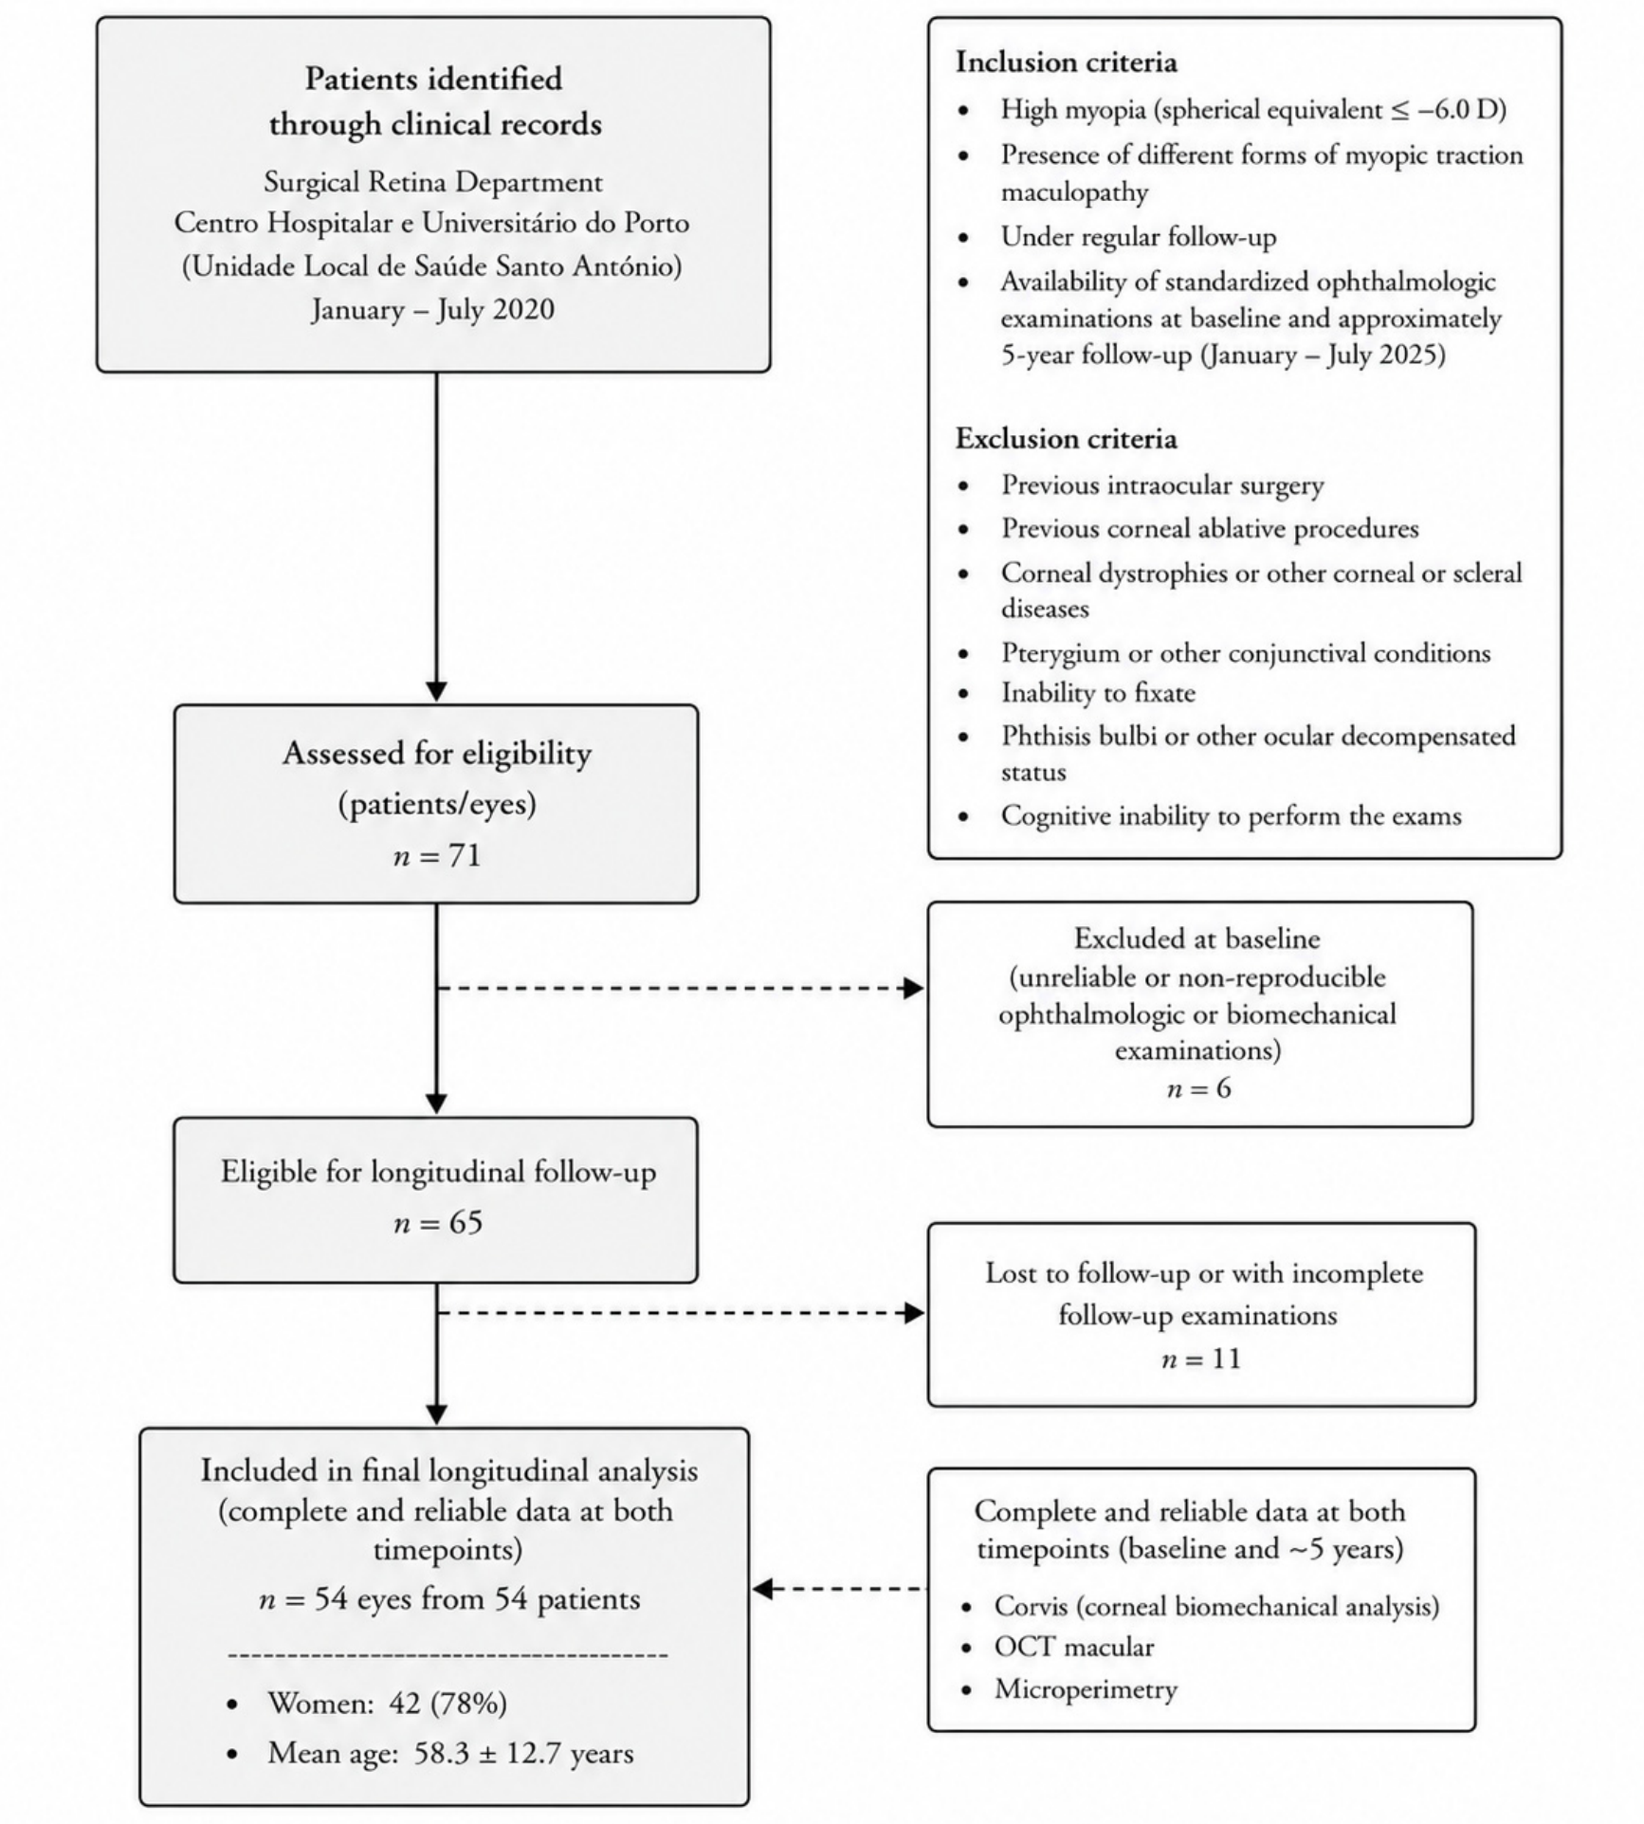
2.1. Design and Study Population
2.2. Demographic and Clinical Data
2.3. Ocular Biomechanical and Biometric Data
2.4. Characterization of Macular Structure
2.5. Macular Microperimetry Assessment
2.6. Study Steps
- General analysis (baseline characterization): anatomical, biomechanical, and functional characterization of the study cohort at baseline was performed.
- Four independent comparative analyses were conducted to assess differences in baseline ocular biomechanical parameters according to macular structural status. Specifically, comparisons were performed between:
- Eyes with retinal splitting/foveoschisis (foveoschisis group, n = 19) and those without this alteration;
- Eyes with fibrotic and/or atrophic changes of the outer retina (atrophy/fibrosis group, n = 33) and those without this alteration;
- Eyes with anterior vitreomacular traction (VMT group, n = 9) and those without this alteration;
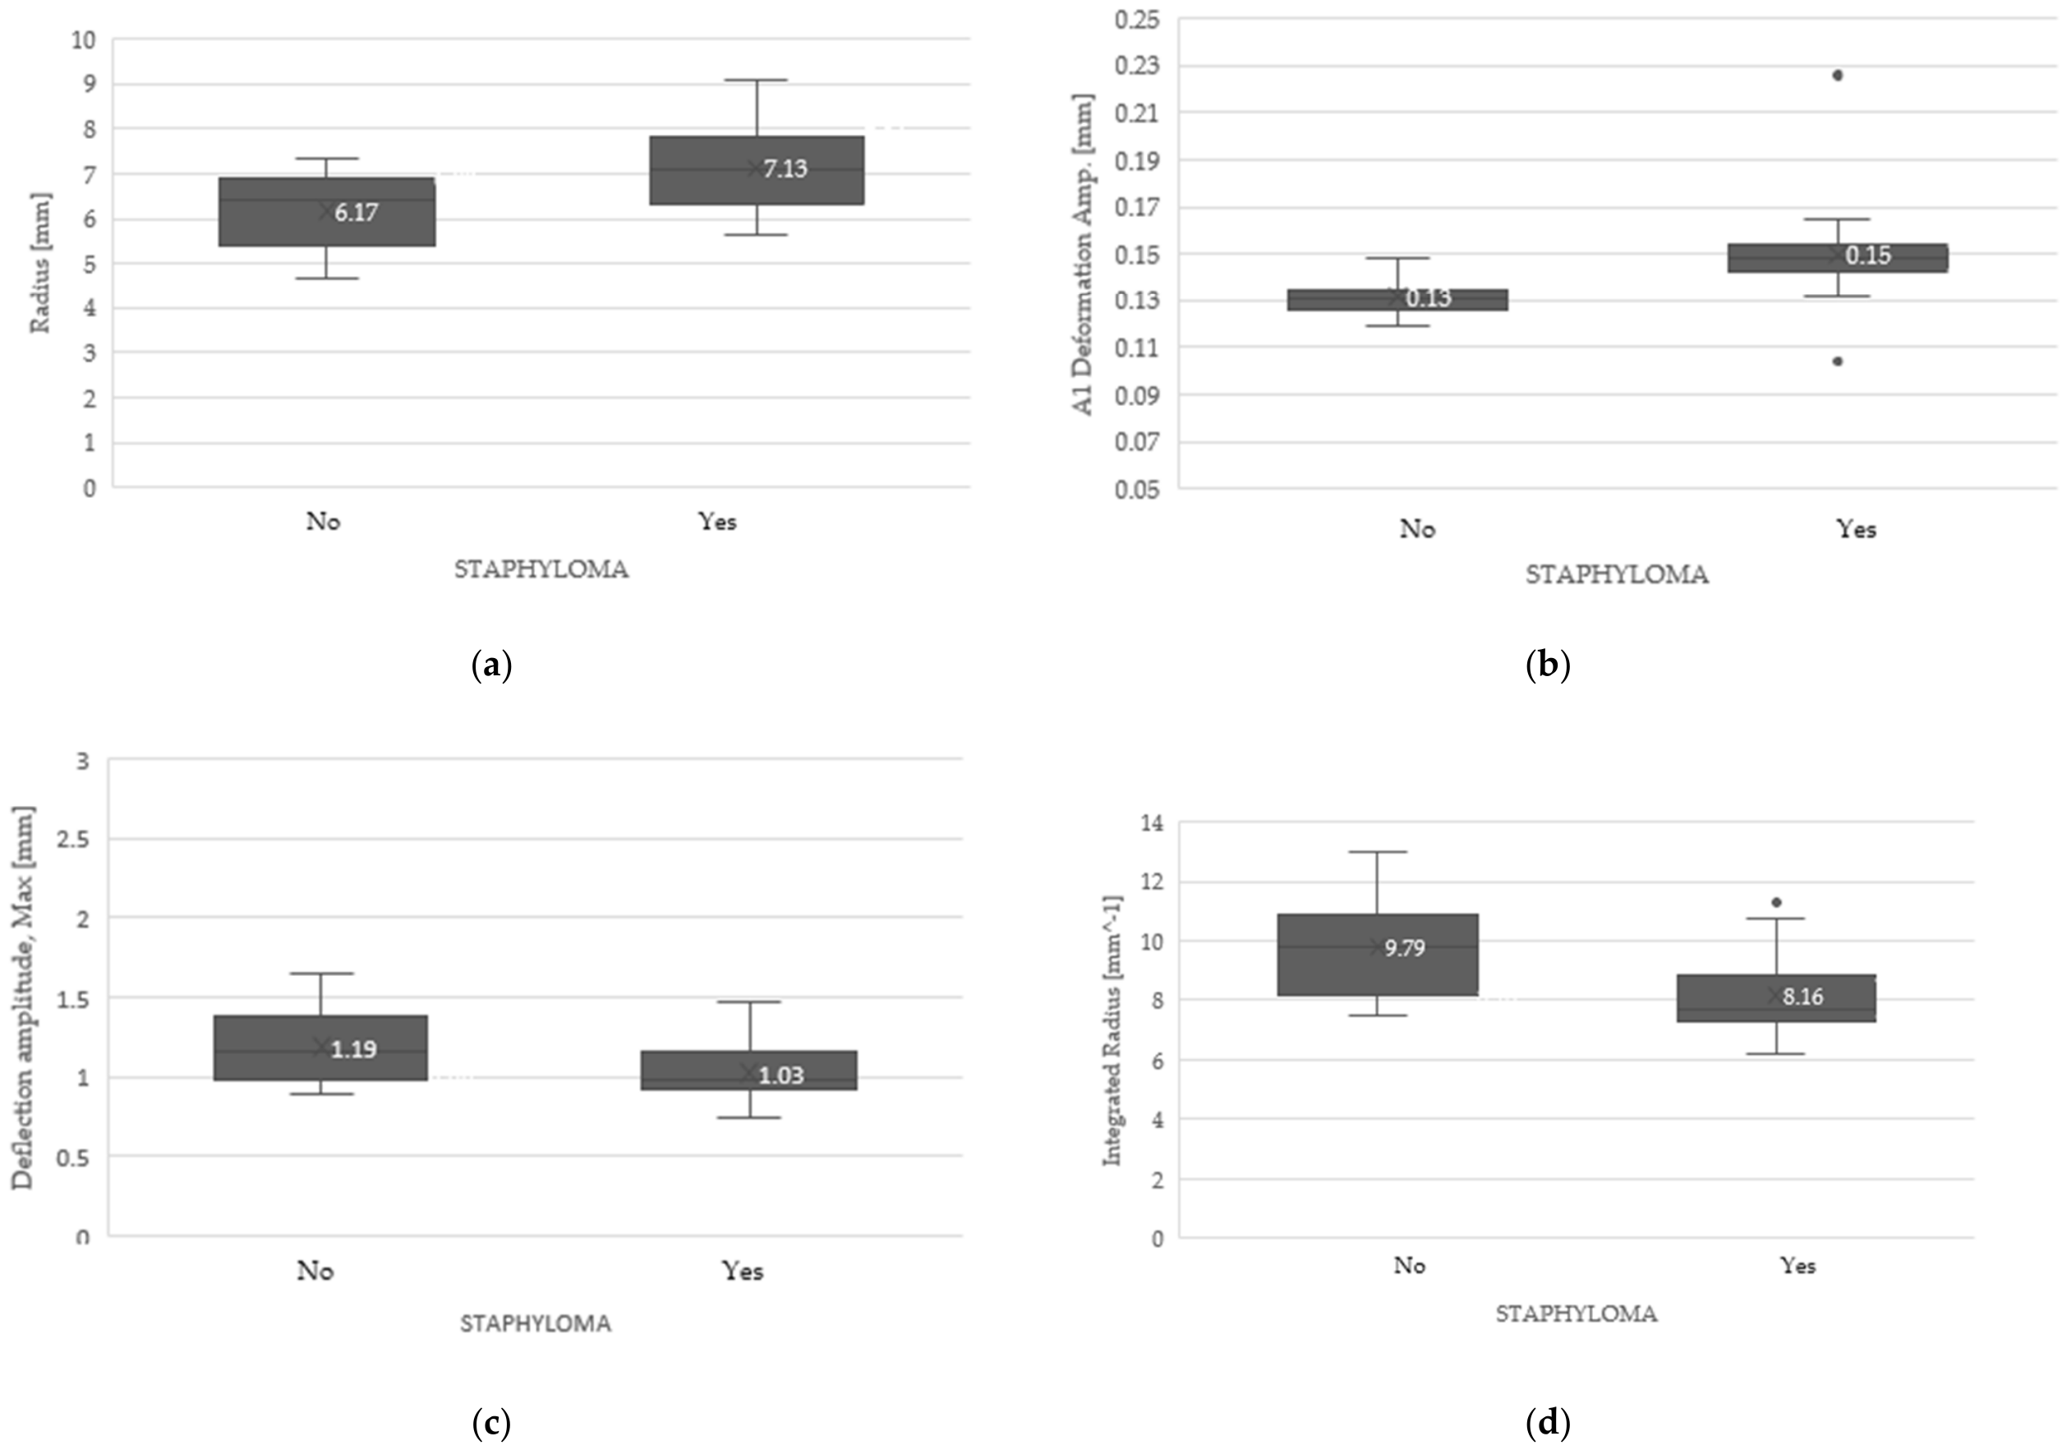
- Eyes with posterior pole staphyloma (staphyloma group, n = 31) and those without this alteration.
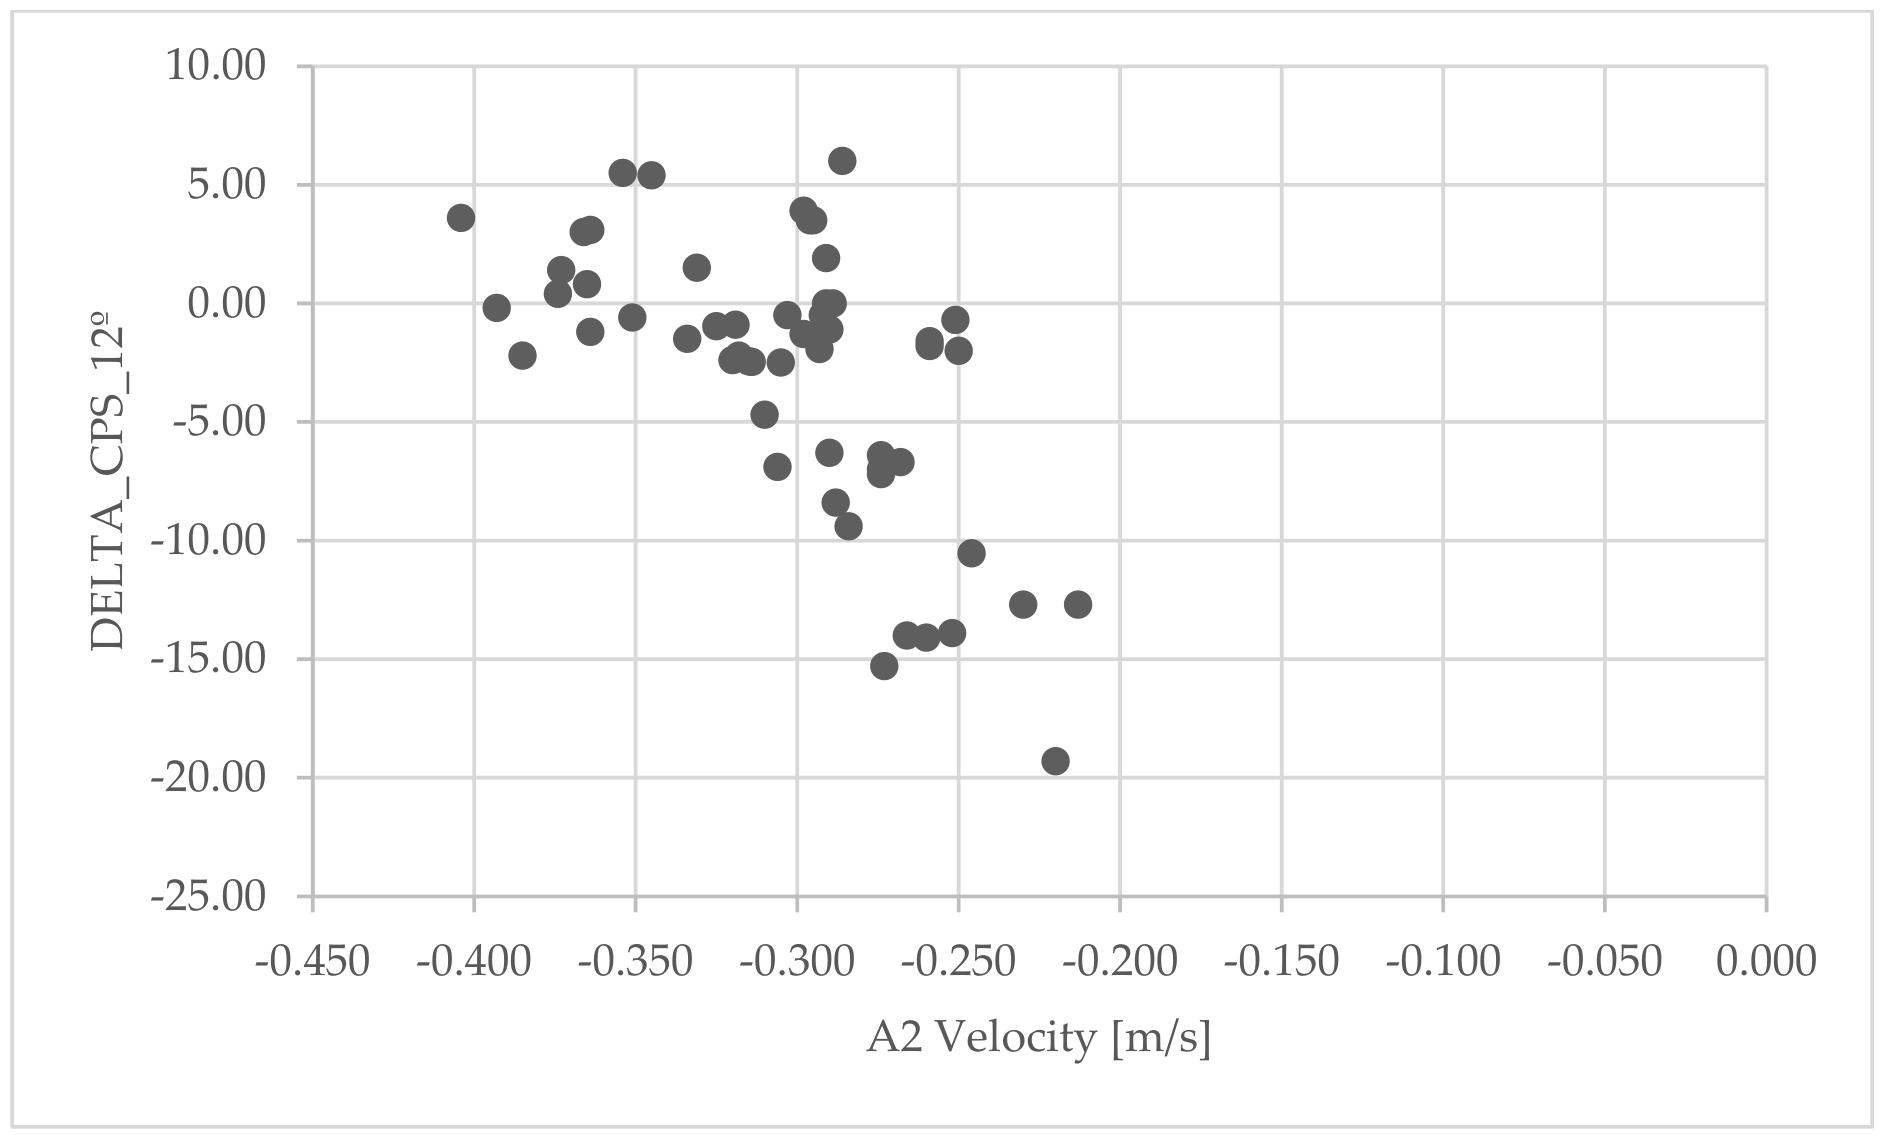
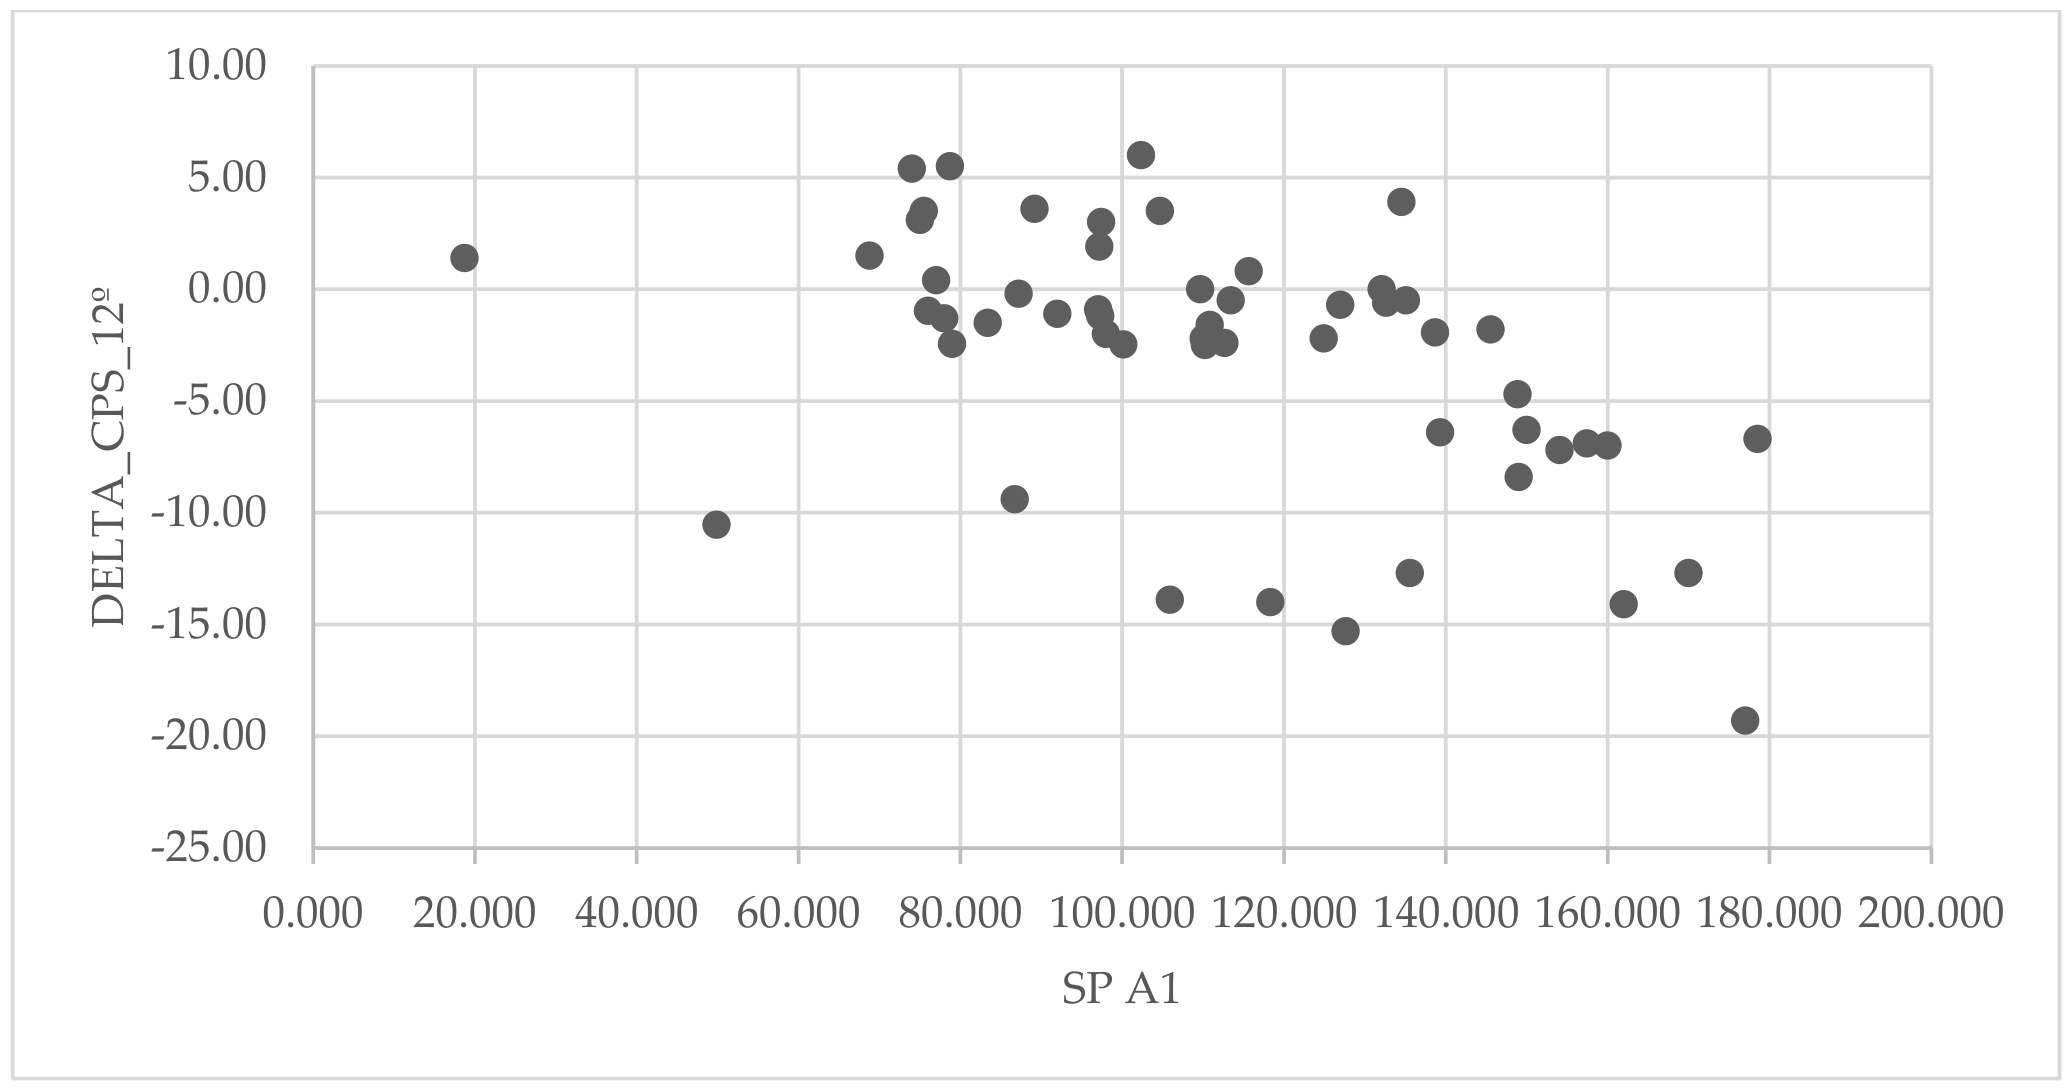
- Correlation analysis: Univariable correlation analyses were performed to investigate the correlations between baseline ocular biomechanical parameters and longitudinal changes in macular microperimetric functional outcomes over the follow-up period, considering the entire study cohort.
- Additionally, multivariable linear regression models were developed to identify independent associations between baseline biomechanical parameters and ΔCPS 12°. Candidate predictors included baseline biomechanical parameters that showed significant or near-significant associations in univariable analyses (p < 0.10) and/or were considered clinically relevant. A stepwise selection procedure was applied (entry p < 0.05, removal p > 0.10) to derive the final models. To reduce the risk of multicollinearity, correlations between predictors were assessed, and variance inflation factors (VIF) were calculated, with a predefined threshold of VIF > 5 indicating collinearity. In such cases, only one of the correlated variables was retained based on clinical relevance. Given the limited sample size (n = 54), the number of predictors included in each final model was restricted to maintain an appropriate ratio between sample size and model complexity. Potential confounding by baseline age, SE, CFT and CT was assessed.
2.7. Statistical Analysis
3. Results
3.1. Subgroup Analysis
3.2. Correlation Analysys
4. Discussion
4.1. Ocular Biomechanical Profiles Across High-Myopia Subgroups
4.2. Correlations Between Baseline Biomechanics and Longitudinal Functional Changes
4.3. Limitations and Future Perspectives
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
Abbreviations
| BCEA | Bivariate Contour Ellipse Area |
| CFT | Central foveal thickness |
| CPS | Central point sensitivity |
| CT | Choroidal thickness |
| F2 | Fixation within 2 central degrees |
| F4 | Fixation within 4 central degrees |
| FS | Foveoschisis |
| HM | High myopia |
| IOP | Intraocular pressure |
| MH | Macular hole |
| MP-3 | Microperimeter MP-3 |
| MTM | Myopic traction maculopathy |
| OCT | Optical coherence tomography |
| PM | Pathologic myopia |
| PS | Posterior staphyloma |
| SD | Standard deviation |
| SD-OCT | Spectral-domain optical coherence tomography |
| SE | Spherical equivalent |
| VMT | Vitreomacular traction |
| WEM | Whole eye movement |
References
- Flitcroft, D.I.; He, M.; Jonas, J.B.; Jong, M.; Naidoo, K.; Ohno-Matsui, K.; Rahi, J.; Resnikoff, S.; Vitale, S.; Yannuzzi, L. IMI—Defining and Classifying Myopia: A Proposed Set of Standards for Clinical and Epidemiologic Studies. Investig. Ophthalmol. Vis. Sci. 2019, 60, M20–M30. [Google Scholar]
- Ohno-Matsui, K.; Lai, T.Y.; Lai, C.C.; Cheung, C.M. Updates of pathologic myopia. Prog. Retin. Eye Res. 2016, 52, 156–187. [Google Scholar] [CrossRef] [Scilit]
- Ruiz-Medrano, J.; Montero, J.A.; Flores-Moreno, I.; Arias, L.; Garcia-Layana, A.; Ruiz-Moreno, J.M. Myopic maculopathy: Current status and proposal for a new classification and grading system (ATN). Prog. Retin. Eye Res. 2019, 69, 80–115. [Google Scholar] [CrossRef] [Scilit]
- Holden, B.A.; Fricke, T.R.; Wilson, D.A.; Jong, M.; Naidoo, K.S.; Sankaridurg, P.; Wong, T.Y.; Naduvilath, T.J.; Resnikoff, S. Global Prevalence of Myopia and High Myopia and Temporal Trends from 2000 through 2050. Ophthalmology 2016, 123, 1036–1042. [Google Scholar] [CrossRef] [Scilit]
- Iwase, A.; Araie, M.; Tomidokoro, A.; Yamamoto, T.; Shimizu, H.; Kitazawa, Y. Prevalence and Causes of Low Vision and Blindness in a Japanese Adult Population: The Tajimi Study. Ophthalmology 2006, 113, 1354–1362.e1. [Google Scholar] [CrossRef] [Scilit]
- Wong, Y.-L.; Sabanayagam, C.; Ding, Y.; Wong, C.-W.; Yeo, A.C.-H.; Cheung, Y.-B.; Cheung, G.; Chia, A.; Ohno-Matsui, K.; Wong, T.-Y.; et al. Prevalence, Risk Factors, and Impact of Myopic Macular Degeneration on Visual Impairment and Functioning Among Adults in Singapore. Investig. Ophthalmol. Vis. Sci. 2018, 59, 4603–4613. [Google Scholar] [CrossRef] [Scilit]
- Xu, L.; Cui, T.; Yang, H.; Hu, A.; Ma, K.; Zheng, Y.; Sun, B.; Li, J.; Fan, G.; Jonas, J.B. Prevalence of Visual Impairment among Adults in China: The Beijing Eye Study. Am. J. Ophthalmol. 2006, 141, 591–593. [Google Scholar] [CrossRef] [Scilit]
- Cotter, S.A.; Varma, R.; Ying-Lai, M.; Azen, S.P.; Klein, R. Causes of Low Vision and Blindness in Adult Latinos: The Los Angeles Latino Eye Study. Ophthalmology 2006, 113, 1574–1582. [Google Scholar] [CrossRef] [Scilit]
- Cedrone, C.; Nucci, C.; Scuderi, G.; Ricci, F.; Cerulli, A.; Culasso, F. Prevalence of blindness and low vision in an Italian population: A comparison with other European studies. Eye 2006, 20, 661–667. [Google Scholar] [CrossRef] [Scilit]
- Klaver, C.C.W.; Wolfs, R.C.W.; Vingerling, J.R.; Hofman, A.; de Jong, P.T.V.M. Age-Specific Prevalence and Causes of Blindness and Visual Impairment in an Older Population: The Rotterdam Study. Arch. Ophthalmol. 1998, 116, 653–658. [Google Scholar] [CrossRef] [Scilit]
- Panozzo, G.; Mercanti, A. Optical Coherence Tomography Findings in Myopic Traction Maculopathy. Arch. Ophthalmol. 2004, 122, 1455–1460. [Google Scholar] [CrossRef] [Scilit]
- Wu, P.C.; Chen, Y.J.; Chen, Y.H.; Chen, C.H.; Shin, S.J.; Tsai, C.L.; Kuo, H.K. Factors associated with foveoschisis and foveal detachment without macular hole in high myopia. Eye 2009, 23, 356–361. [Google Scholar] [CrossRef] [Scilit]
- Johnson, M.W. Myopic traction maculopathy: Pathogenic mechanisms and surgical treatment. Retina 2012, 32, S205–S210. [Google Scholar] [CrossRef] [Scilit]
- Zhang, R.; Xue, J.; Zheng, M.; Cao, X.; Li, C.; Wu, C. Progression of Myopic Maculopathy Based on the ATN Classification System. Ophthalmologica 2024, 247, 65–72. [Google Scholar] [CrossRef] [Scilit]
- Sun, Y.; Guo, Y.; Pang, R.; Peng, J.; Cao, K.; Wang, N. Corneal biomechanical properties and potential influencing factors in varying degrees of myopia. Sci. Rep. 2024, 14, 20626. [Google Scholar] [CrossRef] [Scilit]
- Shen, M.; Fan, F.; Xue, A.; Wang, J.; Zhou, X.; Lu, F. Biomechanical properties of the cornea in high myopia. Vis. Res. 2008, 48, 2167–2171. [Google Scholar] [CrossRef] [Scilit]
- Liu, M.-X.; Zhu, K.-Y.; Li, D.-L.; Dong, X.-X.; Liang, G.; Grzybowski, A.; Pan, C.-W. Corneal Biomechanical Characteristics in Myopes and Emmetropes Measured by Corvis ST: A Meta-Analysis. Am. J. Ophthalmol. 2024, 264, 154–161. [Google Scholar] [CrossRef] [Scilit]
- Yu, A.Y.; Shao, H.; Pan, A.; Wang, Q.; Huang, Z.; Song, B.; McAlinden, C.; Huang, J.; Chen, S. Corneal biomechanical properties in myopic eyes evaluated via Scheimpflug imaging. BMC Ophthalmol. 2020, 20, 279. [Google Scholar] [CrossRef] [Scilit]
- Yii, F.; Strang, N.; Bernabeu, M.O.; Dhillon, B.; MacGillivray, T. Corneal biomechanics are not exclusively compromised in high myopia. Ophthalmic Physiol. Opt. 2024, 44, 977–986. [Google Scholar] [CrossRef] [Scilit]
- Del Buey, M.A.; Lavilla, L.; Ascaso, F.J.; Lanchares, E.; Huerva, V.; Cristobal, J.A. Assessment of corneal biomechanical properties and intraocular pressure in myopic spanish healthy population. J. Ophthalmol. 2014, 2014, 905129. [Google Scholar] [CrossRef] [Scilit]
- He, M.; Wang, W.; Ding, H.; Zhong, X. Corneal Biomechanical Properties in High Myopia Measured by Dynamic Scheimpflug Imaging Technology. Optom. Vis. Sci. 2017, 94, 1074–1080. [Google Scholar] [CrossRef] [Scilit]
- Chen, L.; Huang, Y.; Zhang, X.; Shi, Y.; Gao, Z.; Sun, B.; Shen, Y.; Sun, L.; Cao, Y.; Zhang, Q.; et al. Corneal Biomechanical Properties Demonstrate Anisotropy and Correlate With Axial Length in Myopic Eyes. Investig. Ophthalmol. Vis. Sci. 2023, 64, 27. [Google Scholar]
- Baptista, P.M.; Ambrosio, R.; Oliveira, L.; Meneres, P.; Beirao, J.M. Corneal Biomechanical Assessment with Ultra-High-Speed Scheimpflug Imaging During Non-Contact Tonometry: A Prospective Review. Clin. Ophthalmol. 2021, 15, 1409–1423. [Google Scholar] [CrossRef] [Scilit]
- Roberts, C.J.; Mahmoud, A.M.; Bons, J.P.; Hossain, A.; Elsheikh, A.; Vinciguerra, R.; Vinciguerra, P.; Ambrosio, R., Jr. Introduction of Two Novel Stiffness Parameters and Interpretation of Air Puff-Induced Biomechanical Deformation Parameters With a Dynamic Scheimpflug Analyzer. J. Refract. Surg. 2017, 33, 266–273. [Google Scholar] [CrossRef] [Scilit]
- Vinciguerra, R.; Ambrósio, R.; Elsheikh, A.; Roberts, C.J.; Lopes, B.; Morenghi, E.; Azzolini, C.; Vinciguerra, P. Detection of Keratoconus With a New Biomechanical Index. J. Refract. Surg. 2016, 32, 803–810. [Google Scholar] [CrossRef] [Scilit]
- Jędzierowska, M.; Koprowski, R. Novel dynamic corneal response parameters in a practice use: A critical review. Biomed. Eng. Online 2019, 18, 17. [Google Scholar] [CrossRef] [Scilit]
- Yang, Y.; Chu, Z.; Cheng, L.; Cheng, H.; Ren, Q. Potential dynamic corneal response parameters for myopia: Relationships between axial length with whole eye movement at the first and second applanations and the highest concavity. BMC Ophthalmol. 2024, 24, 382. [Google Scholar] [CrossRef] [Scilit]
- Mettai, M.; Daoud, I.; Mesli, F.; Kenouche, S.; Melkemi, N.; Kherachi, R.; Belkadi, A. Molecular docking/dynamics simulations, MEP analysis, bioisosteric replacement and ADME/T prediction for identification of dual targets inhibitors of Parkinson’s disease with novel scaffold. In Silico Pharmacol. 2023, 11, 3. [Google Scholar]
- Esporcatte, L.P.G.; Salomao, M.Q.; Lopes, B.T.; Vinciguerra, P.; Vinciguerra, R.; Roberts, C.; Elsheikh, A.; Dawson, D.G.; Ambrosio, R., Jr. Biomechanical diagnostics of the cornea. Eye Vis. 2020, 7, 9. [Google Scholar] [CrossRef] [Scilit]
- Wilson, A.; Marshall, J. A review of corneal biomechanics: Mechanisms for measurement and the implications for refractive surgery. Indian J. Ophthalmol. 2020, 68, 2679–2690. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tahsini, V.; Jimenez-Garcia, M.; Makarem, A.; Elsheikh, A.; Buchler, P.; Kling, S.; Rozema, J.J. Regional corneal biomechanics assessment as a function of age using Strain-Stress Index maps. Ophthalmic Physiol. Opt. 2025, 45, 1773–1779. [Google Scholar] [CrossRef] [Scilit]
- Yashiro, K.; Aoki, S.; Kitamoto, K.; Arai, T.; Azuma, K.; Inoue, T.; Asaoka, R.; Obata, R. Biomechanical Properties Measured With Dynamic Scheimpflug Analyzer in Myopic Maculopathy. Am. J. Ophthalmol. 2025, 276, 92–98. [Google Scholar] [CrossRef] [Scilit]
- Aoki, S.; Asaoka, R.; Fujino, Y.; Nakakura, S.; Murata, H.; Kiuchi, Y. Comparing corneal biomechanic changes among solo cataract surgery, microhook ab interno trabeculotomy and iStent implantation. Sci. Rep. 2023, 13, 19148. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ohno-Matsui, K.; Jonas, J.B. Posterior staphyloma in pathologic myopia. Prog. Retin. Eye Res. 2019, 70, 99–109. [Google Scholar] [CrossRef] [Scilit] [PubMed]




| Parameter | Abbreviation | Explanation | Anatomical Unit Movement | Theoretical Meaning of Higer Values |
|---|---|---|---|---|
| cIOP [mmHg] | cIOP | Corvis-derived intraocular pressure | Non applied | Non applied |
| cPachy [µm] | cCCT | Corvis-derived central corneal thickness | Non applied | Non applied |
| 1st generation parameters | ||||
| Deformation Amp. Max [mm] | MaxDefoA | Corneal deformation amplitude during MaxDT, expressed as the sum of corneal deflection amplitude and MaxWEM | Ocular deformation | Less rigid behavior |
| A1 Time [ms] | A1T | Time from the beginning of measurement to the first applanation moment | Corneal deflection | More rigid behavior |
| A1 Velocity [m/s] | A1V | Velocity of the corneal apex during the first applanation | Corneal deflection | Less rigid behavior |
| A2 Time [ms] | A2T | Time from the beginning of measurement to the second applanation moment | Corneal deflection | Less rigid behavior |
| A2 Velocity [m/s] | A2V | Velocity of the corneal apex during the second applanation | Corneal deflection | Less rigid behavior |
| HC Time [ms] | HCT | Time from the beginning of measurement to the moment of reaching the highest concavity (HC) | Corneal deflection | Less rigid behavior |
| Peak Dist. [mm] | HCPD | Distance between the corneal peaks at the HC | Corneal deflection | Less rigid behavior |
| Radius [mm] | HCR | Radius of corneal curvature during the HC | Corneal deflection | More rigid behavior |
| A1 Deformation Amp. [mm] | A1DefoA | Corneal deformation amplitude during A1, expressed as the sum of corneal deflection amplitude and MaxWEM | Ocular deformation | Less rigid behavior |
| HC Deformation Amp. [mm] | HCDefoA | Corneal deformation amplitude during HC, expressed as the sum of corneal deflection amplitude and MaxWEM | Ocular deformation | Less rigid behavior |
| A2 Deformation Amp. [mm] | A2DefoA | Corneal deformation amplitude during A2, expressed as the sum of corneal deflection amplitude and MaxWEM | Ocular deformation | Less rigid behavior |
| A1 Deflection Length [mm] | A1DL | Horizontal length of the flattened cornea at the A1 | Corneal deflection | More rigid behavior |
| HC Deflection Length [mm] | HCDL | Horizontal length of the flattened cornea at the HC | Corneal deflection | More rigid behavior |
| A2 Deflection Length [mm] | A2DL | Horizontal length of the flattened cornea at the A2 | Corneal deflection | More rigid behavior |
| A1 Deflection Amp. [mm] | A1DA | Corneal deflection amplitude during A1, determined as the displacement of the corneal apex in relation to the initial state without MaxWEM quantification | Corneal deflection | Less rigid behavior |
| HC Deflection Amp. [mm] | HCDA | Corneal deflection amplitude during HC, determined as the displacement of the corneal apex in relation to the initial state without MaxWEM quantification | Corneal deflection | Less rigid behavior |
| A2 Deflection Amp. [mm] | A2DA | Corneal deflection amplitude during A2, determined as the displacement of the corneal apex in relation to the initial state without MaxWEM quantification | Corneal deflection | Less rigid behavior |
| Deflection Amp. Max [mm] | MaxDA | Corneal deflection amplitude during MaxDT | Corneal deflection | Less rigid behavior |
| Deflection Amp. Max [ms] | MaxDT | Moment of the maximum corneal deflection during the oscillatory phase near HC | Corneal deflection | Less rigid behavior |
| Whole Eye Movement Max [mm] | MaxWEM | Amplitude of the maximum whole eye movement | Ocular deformation | More energy to posterior pole |
| Whole Eye Movement Max [ms] | MaxWEMT | Time at which the highest amplitude of the maximum whole eye movement (near A2) occurs | Ocular deformation | Less energy to posterior pole |
| A1 Deflection Area [mm2] | A1DArea | Deflection area in A1 | Corneal deflection | Less rigid behavior |
| HC Deflection Area [mm2] | HCDArea | Deflection area in HC | Corneal deflection | Less rigid behavior |
| A2 Deflection Area [mm2] | A2DArea | Deflection area in A2 | Corneal deflection | Less rigid behavior |
| A1 dArc Length [mm] | A1dArcL | Delta arc length of the corneal surface in A1 | Corneal deflection | Less rigid behavior |
| HC dArc Length [mm] | HCdArcL | Delta arc length of the corneal surface in HC | Corneal deflection | Less rigid behavior |
| A2 dArc Length [mm] | A2dArcL | Delta arc length of the corneal surface in A2 | Corneal deflection | Less rigid behavior |
| dArcLengthMax [mm] | MaxdArcL | Delta arc length of the corneal surface in MaxDT | Corneal deflection | Less rigid behavior |
| 2nd generation parameters | ||||
| Max Inverse Radius [mm−1] | MIR | 1/HCR | Corneal deflection | Less rigid behavior |
| DA Ratio Max (2 mm) | DARM2 | Ápex MaxDA/MaxDA at 2 mm from the ápex | Corneal deflection | Less rigid behavior |
| PachySlope [µm] | PqS | Peripheric (8 mm horizontal) pachymetry/Ápex pachymetry | Non applied | Non applied |
| DA Ratio Max (1 mm) | DARM1 | Ápex MaxDA/MaxDA at 1 mm from the ápex | Corneal deflection | Less rigid behavior |
| Ambrosio Relational Thickness (8 mm) | ARTh | Ambrosio relational thickness within the horizontal 8 mm cornea of the image | Non applied | Non applied |
| Biomechanically Corrected IOP | bIOP | IOP adjusted for biomechanical parameters | Non applied | Non applied |
| Integrated Radius [mm−1] | IR | Area under the curve of the 1/HCR function | Corneal deflection | Less rigid behavior |
| Stiffness parameter in A1 | SP-A1 | Air-puff pressure–bIOP/A1DA | Ocular deformation | More rigid behavior |
| Corvis biomechanical index | CBI | Exponential function score determined through a logistic regression analysis of 6 parameters (SP-A1, DARM1, DARM2, ARTh, A1V and MaxDefoA) and adjusted for IOP and CCT to describe ectasia risk | Corneal deflection | Less rigid behavior |
| Tomographic and Biomechanical Index | TBI | Algorithm including tomographic and biomechanical parameters for the discrimination of eyes with corneal ectasia susceptibility | Corneal deflection | Less rigid behavior |
| Stress–Strain Index | SS-I | Finite element modeling algorithm for the estimation of the non-linear in vivo biomechanical behavior in corneas with normal topography | Ocular deformation | More rigid behavior |
| Parameter | All Samples (N = 54) | Schisis | Atrophy/Fibrosis | VMT | Posterior Staphyloma | ||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Yes (n = 19) | No (n = 35) | p | Yes (n = 33) | No (n = 21) | p | Yes (n = 9) | No (n = 45) | p | Yes (n = 31) | No (n = 23) | p | ||
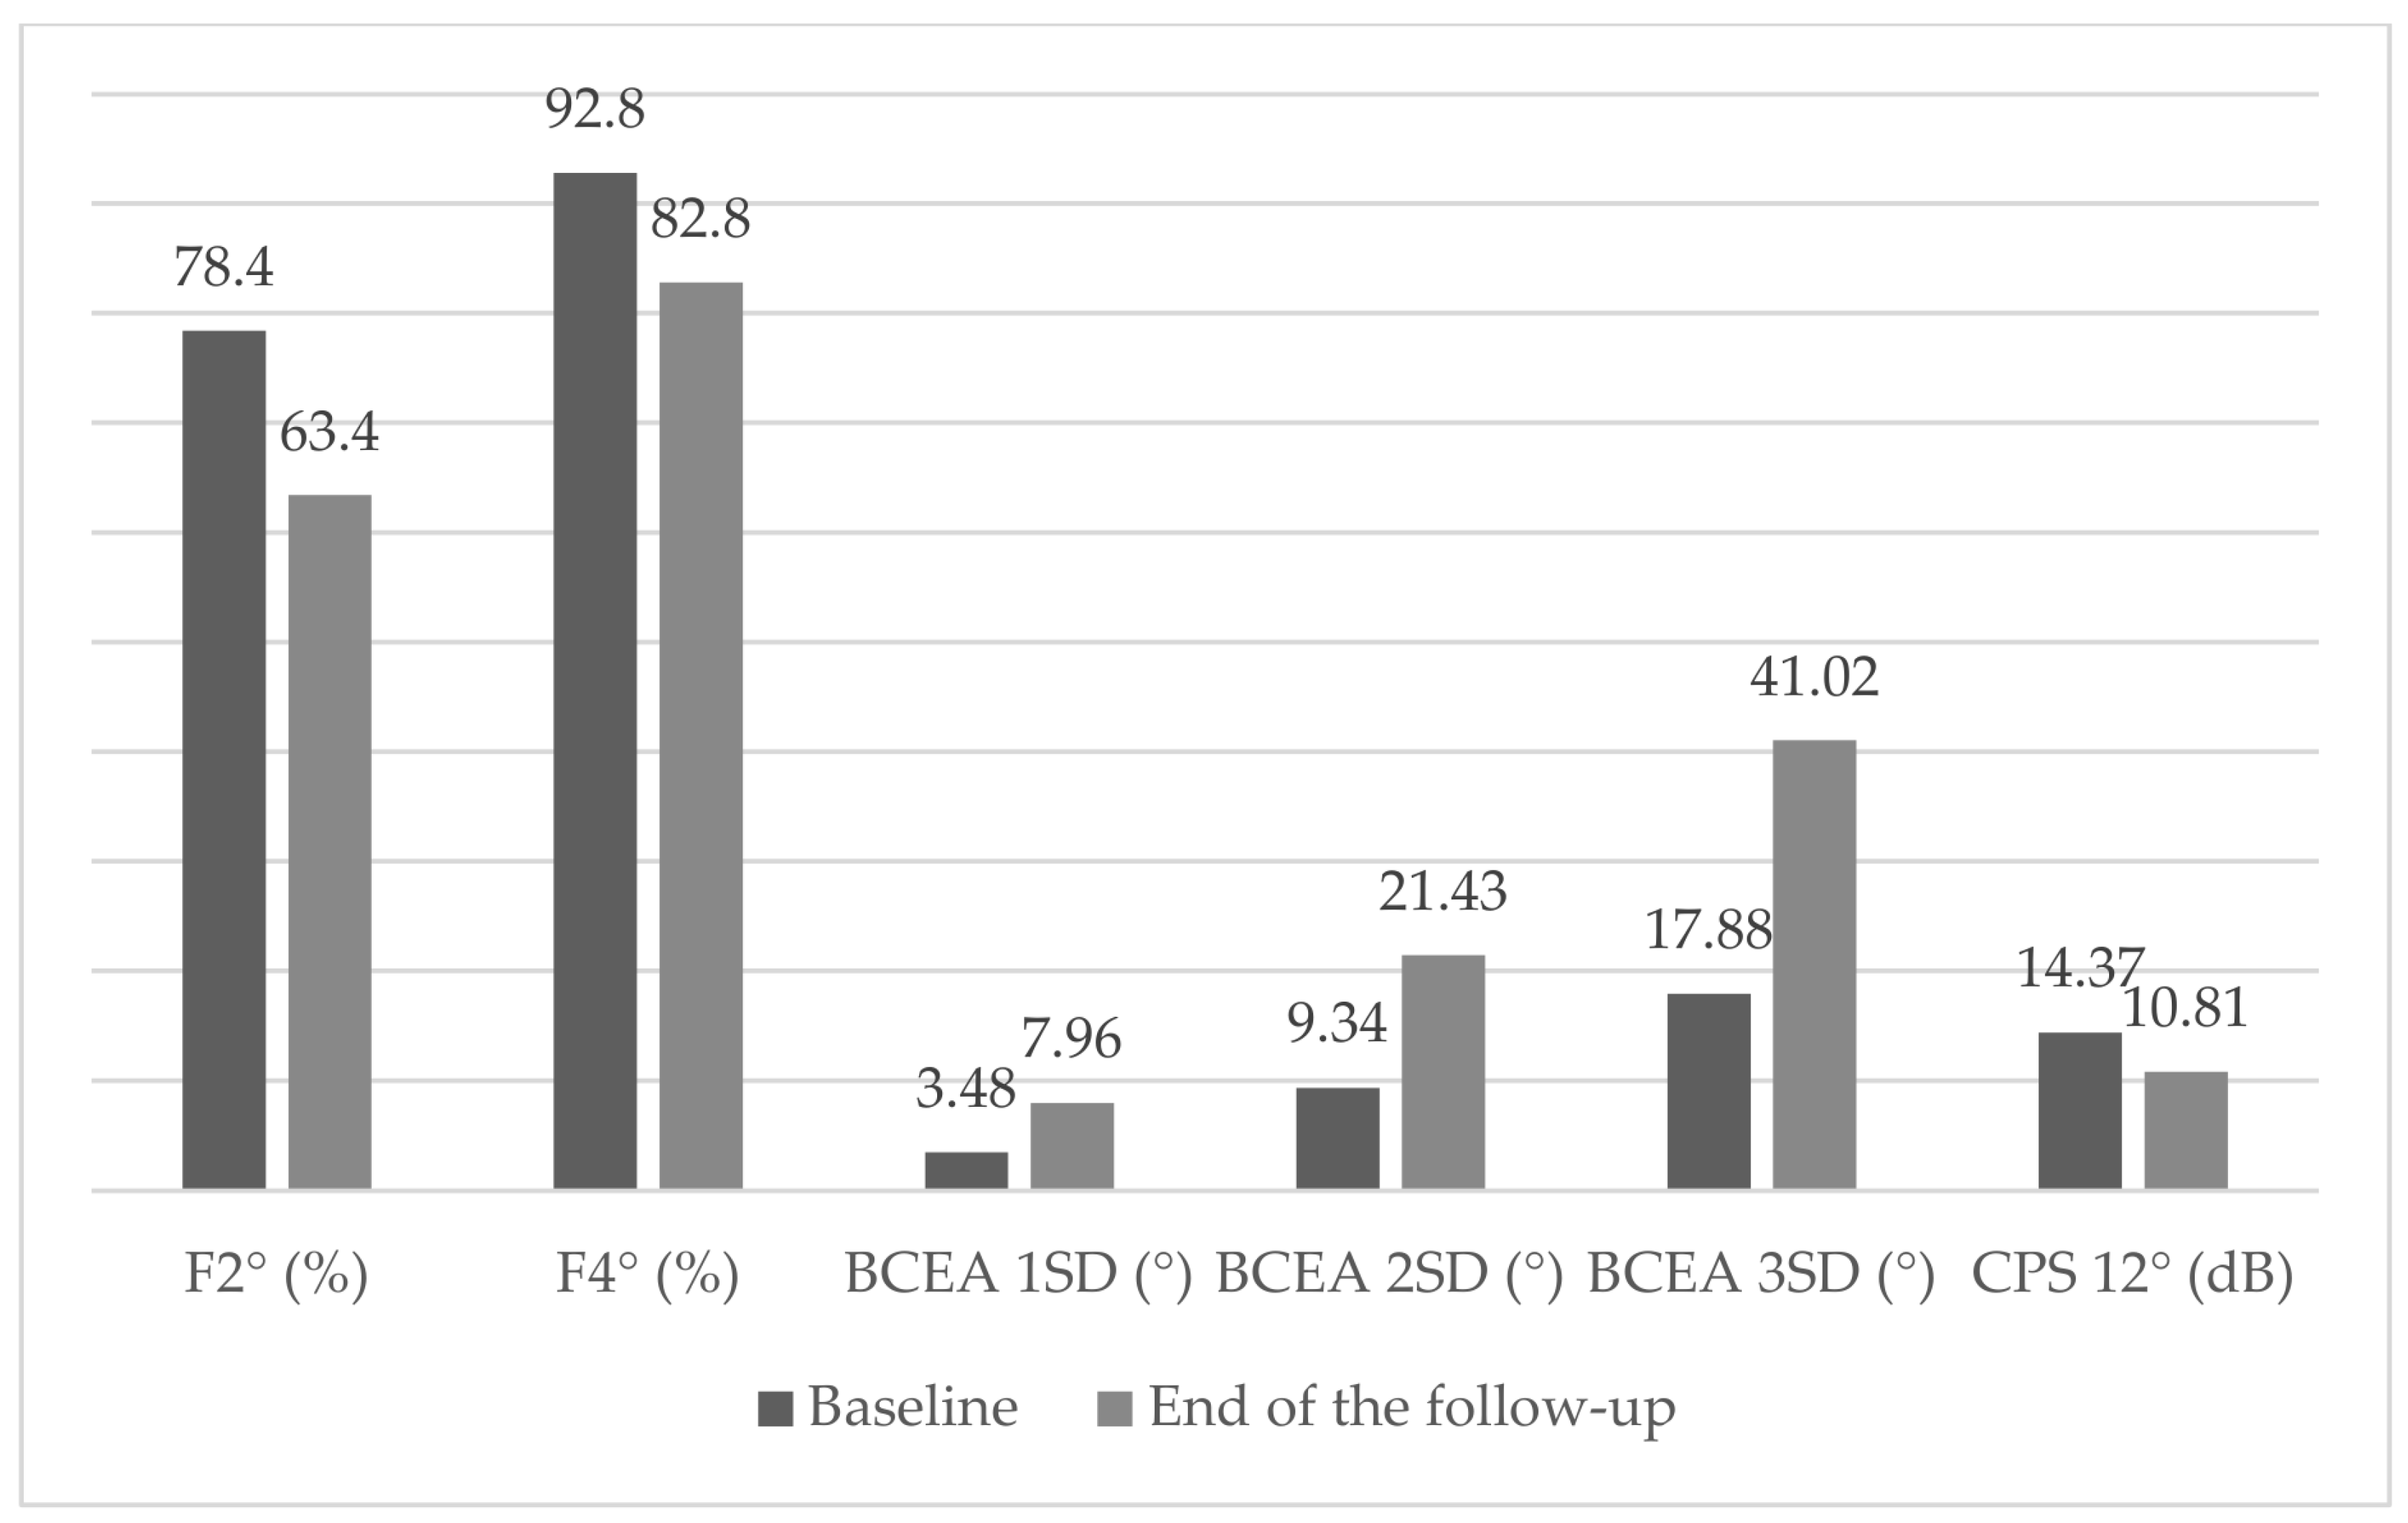
| Age (years) | 58.3 ± 12.7 | 63.0 ± 11.5 | 55.2 ± 13.1 | 0.147 | 60.9 ± 11.7 | 53.1 ± 13.3 | 0.134 | 66.7 ± 10.2 | 56.2 ± 12.4 | 0.212 | 59.2 ± 13.4 | 56.3 ± 11.7 | 0.317 |
| Absolute SE (D) | 15.5 ± 6.6 | 14.9 ± 7.6 | 16.20 ± 5.9 | 0.608 | 16.80 ± 7.2 | 10.8 ± 7.2 | 0.245 | 10.4 ± 11.6 | 10.1 ± 7.9 | 0.191 | 10.4 ± 9.5 | 9.8 ± 7.1 | 0.269 |
| Anatomical data | |||||||||||||
| CFT (μm) | 216.7 ± 142.1 | 280.6 ± 194 | 177.6 ± 80 | 0.1 | 192.1 ± 157 | 264.5 ± 92.9 | 0.088 | 329.8 ± 261.2 | 191.9 ± 87.2 | 0.447 | 231.9 ± 169.1 | 191.9 ± 79.1 | 0.482 |
| CT (μm) | 49.10 ± 55.1 | 38.30 ± 19.8 | 67.0 ± 35.0 | 0.283 | 32.7 ± 23.9 | 80.9 ± 80.7 | 0.027 * | 34.1 ± 22.8 | 52.4 ± 39.6 | 0.585 | 49.2 ± 35.3 | 49.9 ± 43.6 | 0.486 |
| Microperimetric data | |||||||||||||
| CPS 12° (dB) | 14.37 ± 9.1 | 13.7 ± 9.1 | 14.8 ± 9.3 | 0.973 | 11.2 ± 8.8 | 20.9 ± 6.0 | <0.001 * | 12.8 ± 8.4 | 14.5 ± 9.4 | 0.283 | 12.2 ± 9.1 | 17.73 ± 8.4 | 0.394 |
| F2° (%) | 78.4 ± 23.5 | 76.7 ± 26.2 | 79.5 ± 21.8 | 0.903 | 76.6 ± 25.4 | 81.9 ± 19.2 | 0.725 | 62.0 ± 27.9 | 81.8 ± 21.3 | 0.332 | 77.93 ± 23.9 | 94.1 ± 10.2 | 0.102 |
| F4° (%) | 92.8 ± 13.5 | 90.5 ± 17.9 | 94.4 ± 9.3 | 0.593 | 91.7 ± 15.4 | 95.1 ± 8.0 | 0.591 | 87.6 ± 12.6 | 93.9 ± 13.6 | 0.04 * | 92.0 ± 15.3 | 94.1 ± 10.23 | 0.466 |
| BCEA 1SD (°) | 3.48 ± 5.8 | 2.2 ± 1.7 | 2.6 ± 2.8 | 0.858 | 4.0 ± 6.8 | 2.4 ± 2.3 | 0.842 | 5.3 ± 4.1 | 2.7 ± 3.26 | 0.081 | 3.0 ± 6.9 | 7.7 ± 8.7 | 0.544 |
| BCEA 2SD (°) | 9.34 ± 15.6 | 12.6 ± 11.1 | 7.1 ± 7.60 | 0.858 | 10.8 ± 18.3 | 6.4 ± 6.1 | 0.833 | 14.18 ± 11.1 | 7.3 ± 8.79 | 0.368 | 10.4 ± 18.7 | 14.7 ± 16.7 | 0.566 |
| BCEA 3SD (°) | 17.88 ± 29.7 | 11.1 ± 42.8 | 13.5 ± 14.5 | 0.526 | 20.7 ± 35.1 | 12.1 ± 11.7 | 0.824 | 27.1 ± 21.2 | 12.4 ± 9.37 | 0.205 | 19.9 ± 35.8 | 17.7 ± 8.4 | 0.439 |
| (a) | ||||||||||
| Foveoschisis | Atrophy/Fibrosis | |||||||||
| Yes (n = 19) | No (n = 35) | p | Yes (n = 33) | No (n = 21) | p | |||||
| Mean | SD | Mean | SD | Mean | SD | Mean | SD | |||
| Pachy [µm] | 519.000 | 39.569 | 535.179 | 37.221 | 0.191 | 529.200 | 32.835 | 530.308 | 50.501 | 0.932 |
| Def, Amp, Max [mm] | 1.175 | 0.130 | 1.171 | 0.181 | 0.935 | 1.190 | 0.176 | 1.132 | 0.126 | 0.290 |
| A1 Time [ms] | 7.923 | 0.413 | 7.967 | 0.452 | 0.754 | 7.922 | 0.424 | 8.021 | 0.467 | 0.497 |
| A1 Velocity [m/s] | 0.134 | 0.019 | 0.128 | 0.027 | 0.450 | 0.134 | 0.019 | 0.122 | 0.033 | 0.113 |
| A2 Time [ms] | 21.781 | 0.383 | 21.768 | 0.571 | 0.936 | 21.792 | 0.472 | 21.729 | 0.595 | 0.713 |
| A2 Velocity [m/s] | −0.301 | 0.042 | −0.311 | 0.047 | 0.486 | −0.310 | 0.047 | −0.302 | 0.040 | 0.576 |
| HC Time [ms] | 17.278 | 0.478 | 17.224 | 0.737 | 0.799 | 17.132 | 0.723 | 17.498 | 0.354 | 0.032 * |
| Peak Dist, [mm] | 5.322 | 0.290 | 5.341 | 0.411 | 0.881 | 5.372 | 0.386 | 5.246 | 0.325 | 0.310 |
| Radius [mm] | 6.990 | 1.046 | 6.686 | 0.954 | 0.341 | 6.861 | 0.937 | 6.633 | 1.113 | 0.493 |
| A1 Deformation Amp, [mm] | 0.145 | 0.013 | 0.143 | 0.021 | 0.678 | 0.146 | 0.018 | 0.137 | 0.017 | 0.136 |
| HC Deformation Amp, [mm] | 1.175 | 0.130 | 1.171 | 0.181 | 0.935 | 1.190 | 0.176 | 1.132 | 0.126 | 0.290 |
| A2 Deformation Amp, [mm] | 0.371 | 0.049 | 0.333 | 0.044 | 0.014 * | 0.350 | 0.048 | 0.341 | 0.052 | 0.618 |
| A1 Deflection Length [mm] | 2.317 | 0.217 | 2.327 | 0.172 | 0.876 | 2.336 | 0.169 | 2.289 | 0.235 | 0.489 |
| HC Deflection Length [mm] | 6.937 | 0.558 | 6.797 | 0.625 | 0.475 | 6.915 | 0.616 | 6.677 | 0.541 | 0.249 |
| A2 Deflection Length [mm] | 3.392 | 1.076 | 2.631 | 0.626 | 0.007 * | 2.974 | 0.947 | 2.753 | 0.737 | 0.474 |
| A1 Deflection Amp, [mm] | 0.094 | 0.011 | 0.109 | 0.107 | 0.598 | 0.094 | 0.008 | 0.126 | 0.059 | 0.487 |
| HC Deflection Amp, [mm] | 1.034 | 0.144 | 1.051 | 0.220 | 0.783 | 1.049 | 0.187 | 1.037 | 0.220 | 0.854 |
| A2 Deflection Amp, [mm] | 0.115 | 0.017 | 0.128 | 0.099 | 0.634 | 0.109 | 0.014 | 0.155 | 0.140 | 0.265 |
| Deflection Amp, Max [mm] | 1.050 | 0.140 | 1.104 | 0.240 | 0.358 | 1.083 | 0.202 | 1.089 | 0.238 | 0.934 |
| Deflection Amp, Max [ms] | 16.143 | 0.518 | 16.087 | 0.933 | 0.802 | 16.178 | 0.768 | 15.940 | 0.899 | 0.381 |
| Whole Eye Movement Max [mm] | 0.262 | 0.052 | 0.239 | 0.076 | 0.306 | 0.255 | 0.065 | 0.230 | 0.078 | 0.277 |
| Whole Eye Movement Max [ms] | 22.102 | 0.571 | 21.259 | 4.199 | 0.446 | 22.092 | 0.901 | 20.311 | 1.022 | 0.309 |
| A1 Deflection Area [mm2] | 0.182 | 0.027 | 0.204 | 0.236 | 0.724 | 0.177 | 0.028 | 0.240 | 0.348 | 0.522 |
| HC Deflection Area [mm2] | 3.958 | 0.719 | 3.943 | 1.020 | 0.961 | 4.061 | 0.977 | 3.689 | 0.732 | 0.226 |
| A2 Deflection Area [mm2] | 0.276 | 0.069 | 0.294 | 0.267 | 0.801 | 0.249 | 0.060 | 0.374 | 0.374 | 0.250 |
| A1 DArc Length [mm] | −0.019 | 0.005 | −0.020 | 0.029 | 0.838 | −0.018 | 0.003 | −0.022 | 0.043 | 0.758 |
| HC DArc Length [mm] | −0.149 | 0.030 | −0.113 | 0.104 | 0.206 | −0.144 | 0.034 | −0.082 | 0.144 | 0.151 |
| A2 DArc Length [mm] | −0.025 | 0.009 | −0.028 | 0.022 | 0.658 | −0.024 | 0.006 | −0.033 | 0.031 | 0.303 |
| DArcLengthMax [mm] | −0.168 | 0.026 | −0.170 | 0.051 | 0.880 | −0.167 | 0.043 | −0.174 | 0.048 | 0.648 |
| Max Inverse Radius [mm−1] | 0.182 | 0.025 | 0.211 | 0.087 | 0.206 | 0.189 | 0.041 | 0.229 | 0.114 | 0.244 |
| DA Ratio Max (2 mm) | 4.014 | 0.364 | 4.609 | 2.677 | 0.399 | 4.060 | 0.555 | 5.189 | 3.855 | 0.314 |
| PachySlope [µm] | 43.190 | 24.215 | 37.891 | 27.645 | 0.536 | 34.890 | 19.260 | 50.930 | 36.547 | 0.156 |
| DA Ratio Max (1 mm) | 1.516 | 0.053 | 1.571 | 0.244 | 0.397 | 1.517 | 0.057 | 1.632 | 0.350 | 0.260 |
| ARTh | 488.963 | 265.053 | 629.380 | 369.792 | 0.201 | 581.876 | 318.455 | 576.986 | 400.736 | 0.969 |
| bIOP | 15.253 | 3.013 | 15.562 | 2.971 | 0.752 | 15.132 | 3.021 | 16.131 | 2.788 | 0.320 |
| Integrated Radius [mm−1] | 8.418 | 1.663 | 8.901 | 1.699 | 0.376 | 8.625 | 1.579 | 8.980 | 1.947 | 0.531 |
| SP A1 | 115.040 | 24.809 | 110.507 | 32.812 | 0.647 | 115.519 | 23.875 | 104.479 | 40.715 | 0.289 |
| CBI | 0.380 | 0.333 | 0.422 | 0.399 | 0.741 | 0.365 | 0.323 | 0.506 | 0.469 | 0.377 |
| TBI | 6.273 | 0.670 | 6.321 | 0.850 | 0.857 | 6.343 | 0.670 | 6.189 | 1.033 | 0.669 |
| SSI | 0.986 | 0.281 | 0.827 | 0.196 | 0.035 * | 0.905 | 0.258 | 0.830 | 0.184 | 0.289 |
| (b) | ||||||||||
| Vitreomacular Traction | Staphyloma | |||||||||
| Yes (n = 9) | No (n = 45) | p | Yes (n = 31) | No (n = 23) | p | |||||
| Mean | SD | Mean | SD | Mean | SD | Mean | SD | |||
| Pachy [µm] | 532.750 | 32.539 | 528.800 | 39.989 | 0.796 | 537.536 | 38.373 | 514.600 | 34.834 | 0.061 |
| Def, Amp, Max [mm] | 1.174 | 0.141 | 1.172 | 0.170 | 0.97 | 1.146 | 0.160 | 1.220 | 0.164 | 0.163 |
| A1 Time [ms] | 8.042 | 0.496 | 7.931 | 0.424 | 0.519 | 8.032 | 0.474 | 7.802 | 0.308 | 0.098 |
| A1 Velocity [m/s] | 0.128 | 0.029 | 0.131 | 0.024 | 0.787 | 0.132 | 0.021 | 0.128 | 0.030 | 0.608 |
| A2 Time [ms] | 21.678 | 0.425 | 21.795 | 0.527 | 0.560 | 21.670 | 0.488 | 21.958 | 0.502 | 0.076 |
| A2 Velocity [m/s] | −0.298 | 0.055 | −0.310 | 0.043 | 0.516 | −0.306 | 0.045 | −0.311 | 0.046 | 0.752 |
| HC Time [ms] | 17.389 | 0.607 | 17.210 | 0.666 | 0.489 | 17.093 | 0.634 | 17.523 | 0.611 | 0.038 |
| Peak Dist, [mm] | 5.334 | 0.371 | 5.334 | 0.375 | 0.998 | 5.293 | 0.388 | 5.410 | 0.333 | 0.329 |
| Radius [mm] | 6.889 | 1.243 | 6.770 | 0.937 | 0.763 | 7.126 | 0.896 | 6.168 | 0.850 | 0.002 * |
| A1 Deformation Amp, [mm] | 0.145 | 0.014 | 0.143 | 0.019 | 0.802 | 0.150 | 0.019 | 0.132 | 0.008 | 0.001 * |
| HC Deformation Amp, [mm] | 1.174 | 0.141 | 1.172 | 0.170 | 0.970 | 1.146 | 0.160 | 1.220 | 0.164 | 0.163 |
| A2 Deformation Amp, [mm] | 0.372 | 0.045 | 0.341 | 0.049 | 0.105 | 0.341 | 0.051 | 0.358 | 0.043 | 0.261 |
| A1 Deflection Length [mm] | 2.298 | 0.219 | 2.329 | 0.183 | 0.694 | 2.369 | 0.178 | 2.225 | 0.173 | 0.019 * |
| HC Deflection Length [mm] | 6.837 | 0.673 | 6.849 | 0.594 | 0.963 | 6.873 | 0.571 | 6.796 | 0.671 | 0.698 |
| A2 Deflection Length [mm] | 3.350 | 1.453 | 2.819 | 0.722 | 0.151 | 2.920 | 0.943 | 2.890 | 0.802 | 0.921 |
| A1 Deflection Amp, [mm] | 0.165 | 0.190 | 0.090 | 0.027 | 0.302 | 0.097 | 0.009 | 0.116 | 0.148 | 0.618 |
| HC Deflection Amp, [mm] | 1.098 | 0.271 | 1.033 | 0.176 | 0.406 | 1.013 | 0.180 | 1.105 | 0.215 | 0.144 |
| A2 Deflection Amp, [mm] | 0.175 | 0.175 | 0.111 | 0.023 | 0.341 | 0.113 | 0.016 | 0.143 | 0.132 | 0.392 |
| Deflection Amp, Max [mm] | 1.116 | 0.267 | 1.078 | 0.199 | 0.650 | 1.028 | 0.175 | 1.192 | 0.235 | 0.013 * |
| Deflection Amp, Max [ms] | 15.722 | 0.760 | 16.194 | 0.801 | 0.137 | 16.044 | 0.681 | 16.223 | 1.016 | 0.494 |
| Whole Eye Movement Max [mm] | 0.246 | 0.087 | 0.248 | 0.066 | 0.950 | 0.243 | 0.069 | 0.255 | 0.070 | 0.580 |
| Whole Eye Movement Max [ms] | 19.649 | 0.783 | 21.989 | 0.906 | 0.424 | 21.984 | 0.837 | 20.751 | 0.694 | 0.418 |
| A1 Deflection Area [mm2] | 0.330 | 0.019 | 0.165 | 0.056 | 0.305 | 0.183 | 0.027 | 0.220 | 0.325 | 0.666 |
| HC Deflection Area [mm2] | 3.901 | 0.859 | 3.959 | 0.942 | 0.874 | 3.899 | 0.966 | 4.041 | 0.843 | 0.635 |
| A2 Deflection Area [mm2] | 0.311 | 0.205 | 0.282 | 0.222 | 0.736 | 0.254 | 0.064 | 0.348 | 0.352 | 0.319 |
| A1 DArc Length [mm] | −0.035 | 0.046 | −0.016 | 0.013 | 0.295 | −0.019 | 0.004 | −0.020 | 0.040 | 0.922 |
| HC DArc Length [mm] | −0.108 | 0.122 | −0.130 | 0.079 | 0.534 | −0.152 | 0.031 | −0.076 | 0.130 | 0.041 * |
| A2 DArc Length [mm] | −0.030 | 0.021 | −0.026 | 0.018 | 0.558 | −0.025 | 0.007 | −0.030 | 0.029 | 0.530 |
| DArcLengthMax [mm] | −0.189 | 0.057 | −0.165 | 0.040 | 0.168 | −0.169 | 0.041 | −0.169 | 0.051 | 0.999 |
| Max InverseRadius [mm−1] | 0.208 | 0.099 | 0.199 | 0.067 | 0.772 | 0.175 | 0.020 | 0.249 | 0.105 | 0.016 * |
| DA Ratio Max (2 mm) | 5.800 | 4.867 | 4.082 | 0.635 | 0.352 | 3.912 | 0.477 | 5.316 | 3.519 | 0.146 |
| PachySlope [µm] | 38.140 | 12.900 | 40.105 | 28.661 | 0.852 | 34.154 | 23.374 | 50.164 | 29.111 | 0.079 |
| DA Ratio Max (1 mm) | 1.575 | 0.108 | 1.547 | 0.217 | 0.729 | 1.502 | 0.059 | 1.646 | 0.315 | 0.101 |
| ARTh | 443.206 | 202.008 | 611.755 | 359.642 | 0.088 | 614.132 | 348.878 | 517.425 | 326.301 | 0.381 |
| bIOP | 15.638 | 3.684 | 15.403 | 2.813 | 0.843 | 15.842 | 3.425 | 14.767 | 1.782 | 0.194 |
| Integrated Radius [mm−1] | 8.218 | 1.261 | 8.850 | 1.759 | 0.344 | 8.164 | 1.428 | 9.794 | 1.646 | 0.002 * |
| SP A1 | 105.129 | 45.899 | 113.976 | 25.017 | 0.460 | 118.152 | 26.701 | 101.165 | 33.050 | 0.086 |
| CBI | 0.399 | 0.339 | 0.407 | 0.383 | 0.957 | 0.351 | 0.312 | 0.498 | 0.451 | 0.294 |
| TBI | 6.319 | 0.410 | 6.297 | 0.840 | 0.948 | 6.408 | 0.753 | 6.104 | 0.797 | 0.257 |
| SSI | 0.949 | 0.190 | 0.867 | 0.248 | 0.389 | 0.917 | 0.245 | 0.818 | 0.220 | 0.202 |
| Δ_F2° | Δ_F4° | Δ_BCEA_1SD | Δ_BCEA_2SD | Δ_BCEA_3SD | Δ_CPS_12° | |||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Mean | SD | Mean | SD | Mean | SD | Mean | SD | Mean | SD | Mean | SD | |
| −15.0 | 38.319 | −10.03 | 12.493 | 4.480 | 6.719 | 12.089 | 18.056 | 23.143 | 34.568 | −3.559 | 6.417 | |
| Pearson Correlations | ||||||||||||
| r | p | r | p | r | p | r | p | r | p | r | p | |
| IOP [mmHg] | 0.347 | 0.060 * | 0.178 | 0.338 | −0.116 | 0.534 | −0.116 | 0.534 | −0.116 | 0.534 | −0.457 | 0.011 * |
| Pachy [µm] | 0.162 | 0.391 | 0.056 | 0.764 | −0.005 | 0.978 | −0.004 | 0.982 | −0.005 | 0.978 | −0.175 | 0.356 |
| Def. Amp. Max [mm] | −0.298 | 0.110 | −0.219 | 0.237 | 0.121 | 0.518 | 0.120 | 0.519 | 0.120 | 0.519 | 0.379 | 0.039 * |
| A1 Time [ms] | 0.338 | 0.068 * | 0.196 | 0.291 | −0.122 | 0.512 | −0.122 | 0.513 | −0.122 | 0.512 | −0.453 | 0.012 * |
| A1 Velocity [m/s] | −0.385 * | 0.036 * | −0.266 | 0.148 | 0.175 | 0.346 | 0.175 | 0.347 | 0.175 | 0.346 | 0.359 | 0.051 * |
| A2 Time [ms] | −0.277 | 0.138 | −0.106 | 0.577 | 0.040 | 0.835 | 0.041 | 0.832 | 0.041 | 0.832 | 0.456 | 0.013 * |
| A2 Velocity [m/s] | −0.157 | 0.407 | −0.139 | 0.465 | 0.121 | 0.524 | 0.122 | 0.520 | 0.122 | 0.520 | −0.529 | 0.003 * |
| HC Time [ms] | −0.246 | 0.189 | −0.006 | 0.973 | 0.033 | 0.860 | 0.032 | 0.863 | 0.033 | 0.862 | −0.010 | 0.960 |
| Peak Dist. [mm] | −0.151 | 0.424 | −0.142 | 0.446 | 0.012 | 0.948 | 0.012 | 0.948 | 0.012 | 0.949 | 0.404 | 0.027 * |
| Radius [mm] | 0.039 | 0.836 | −0.202 | 0.276 | 0.283 | 0.123 | 0.283 | 0.123 | 0.283 | 0.122 | −0.245 | 0.191 |
| A1 Deformation Amp. [mm] | 0.154 | 0.417 | −0.138 | 0.458 | 0.295 | 0.107 | 0.296 | 0.106 | 0.296 | 0.106 | −0.128 | 0.500 |
| HC Deformation Amp. [mm] | −0.298 | 0.110 | −0.219 | 0.237 | 0.121 | 0.518 | 0.120 | 0.519 | 0.120 | 0.519 | 0.379 | 0.039 * |
| A2 Deformation Amp. [mm] | −0.369 * | 0.045 * | −0.242 | 0.197 | 0.327 | 0.078 | 0.327 | 0.078 | 0.328 | 0.077 | −0.038 | 0.844 |
| A1 Deflection Length [mm] | −0.431 * | 0.017 * | 0.261 | 0.156 | −0.066 | 0.725 | −0.066 | 0.725 | −0.065 | 0.728 | 0.078 | 0.681 |
| HC Deflection Length [mm] | −0.036 | 0.848 | −0.163 | 0.382 | 0.113 | 0.544 | 0.113 | 0.545 | 0.113 | 0.544 | 0.482 | 0.007 * |
| A2 Deflection Length [mm] | −0.125 | 0.511 | −0.384 | 0.036 * | 0.375 | 0.041 * | 0.374 | 0.042 * | 0.374 | 0.042 * | 0.081 | 0.675 |
| A1 Deflection Amp. [mm] | −0.129 | 0.496 | −0.018 | 0.924 | 0.215 | 0.245 | 0.215 | 0.246 | 0.215 | 0.244 | −0.041 | 0.832 |
| HC Deflection Amp. [mm] | −0.257 | 0.170 | −0.146 | 0.433 | 0.021 | 0.909 | 0.021 | 0.910 | 0.021 | 0.910 | 0.423 | 0.020 * |
| A2 Deflection Amp. [mm] | −0.091 | 0.632 | −0.061 | 0.750 | 0.324 | 0.080 | 0.323 | 0.082 | 0.324 | 0.081 | 0.209 | 0.276 |
| Deflection Amp. Max [mm] | −0.267 | 0.154 | −0.160 | 0.391 | 0.040 | 0.829 | 0.040 | 0.830 | 0.040 | 0.830 | 0.424 | 0.019 * |
| Deflection Amp. Max [ms] | −0.134 | 0.479 | −0.127 | 0.495 | 0.121 | 0.517 | 0.121 | 0.517 | 0.121 | 0.517 | −0.004 | 0.984 |
| Whole Eye Movement Max [mm] | −0.369 * | 0.045 * | −0.256 | 0.165 | 0.325 | 0.074 * | 0.326 | 0.073 | 0.326 | 0.073 | −0.125 | 0.511 |
| Whole Eye Movement Max [ms] | −0.318 | 0.087 * | −0.071 | 0.704 | 0.095 | 0.612 | 0.096 | 0.609 | 0.096 | 0.608 | 0.062 | 0.744 |
| A1 Deflection Area [mm2] | 0.354 | 0.055 * | 0.156 | 0.403 | −0.013 | 0.945 | −0.013 | 0.946 | −0.012 | 0.949 | −0.047 | 0.806 |
| HC Deflection Area [mm2] | −0.213 | 0.259 | −0.157 | 0.399 | 0.037 | 0.844 | 0.037 | 0.844 | 0.037 | 0.844 | 0.434 | 0.017 * |
| A2 Deflection Area [mm2] | 0.272 | 0.146 | −0.028 | 0.885 | 0.222 | 0.238 | 0.221 | 0.241 | 0.222 | 0.238 | 0.312 | 0.099 * |
| A1 dArc Length [mm] | 0.073 | 0.702 | −0.120 | 0.521 | −0.048 | 0.800 | −0.046 | 0.805 | −0.047 | 0.802 | 0.084 | 0.658 |
| HC dArc Length [mm] | 0.188 | 0.321 | 0.385 | 0.032 * | −0.380 | 0.035 * | −0.380 | 0.035 * | −0.380 | 0.035 * | −0.443 | 0.014 * |
| A2 dArc Length [mm] | −0.010 | 0.958 | 0.178 | 0.348 | −0.368 | 0.045 * | −0.367 | 0.046 * | −0.368 | 0.045 * | −0.172 | 0.371 |
| dArcLengthMax [mm] | 0.284 | 0.129 | 0.429 | 0.016 * | −0.406 | 0.023 * | −0.406 | 0.023 * | −0.406 | 0.023 * | −0.441 | 0.015 * |
| Max InverseRadius [mm−1] | −0.116 | 0.543 | 0.277 | 0.131 | −0.367 | 0.042 * | −0.368 | 0.042 * | −0.368 | 0.042 * | 0.188 | 0.321 |
| DA Ratio Max (2 mm) | −0.356 | 0.053 | −0.092 | 0.621 | −0.110 | 0.555 | −0.110 | 0.555 | −0.110 | 0.556 | 0.128 | 0.502 |
| PachySlope [µm] | 0.084 | 0.658 | 0.169 | 0.364 | −0.255 | 0.165 | −0.255 | 0.166 | −0.255 | 0.166 | 0.249 | 0.185 |
| DA Ratio Max (1 mm) | −0.489 | 0.006 * | −0.274 | 0.135 | 0.043 | 0.820 | 0.043 | 0.820 | 0.043 | 0.820 | 0.021 | 0.912 |
| ARTh | 0.304 | 0.102 | 0.268 | 0.146 | −0.287 | 0.118 | −0.287 | 0.117 | −0.288 | 0.116 | −0.225 | 0.232 |
| bIOP | 0.399 | 0.029 * | 0.228 | 0.217 | −0.203 | 0.273 | −0.204 | 0.272 | −0.204 | 0.272 | −0.501 | 0.005 * |
| Integrated Radius [mm−1] | −0.197 | 0.298 | 0.051 | 0.784 | −0.090 | 0.629 | −0.090 | 0.630 | −0.090 | 0.630 | 0.282 | 0.131 |
| SP A1 | 0.224 | 0.235 | 0.038 | 0.837 | −0.030 | 0.872 | −0.030 | 0.873 | −0.031 | 0.870 | −0.377 | 0.040 * |
| CBI | −0.147 | 0.456 | 0.056 | 0.773 | −0.066 | 0.733 | −0.066 | 0.734 | −0.066 | 0.735 | 0.331 | 0.085 |
| TBI | 0.133 | 0.499 | 0.022 | 0.908 | −0.025 | 0.898 | −0.025 | 0.896 | −0.026 | 0.894 | −0.178 | 0.365 |
| SSI | −0.086 | 0.651 | −0.210 | 0.256 | 0.411 | 0.022 * | 0.411 | 0.021 * | 0.412 | 0.021 * | −0.079 | 0.678 |
| Variable | β Coefficient | p-Value |
|---|---|---|
| Age | 0.284 | 0.007 * |
| SE | 0.223 | 0.047 * |
| Central Foveal Thickness | −0.011 | 0.056 |
| Choroidal Thickness | 0.070 | 0.001 * |
| A2 Velocity [m/s] | −85.29 | 0.003 * |
| A1 Velocity [m/s] | −239.98 | 0.004 * |
| HC Deflection Length [mm] | 5.80 | 0.029 * |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Vieira, B.C.; Rodrigues, D.; Heitor, J.; Coelho, J.; Sousa, P.; Lume, M.; Meireles, A.; Ambrósio, R., Jr.; Menéres, P.; Beirão, J.M.; et al. Relationship Between Scheimpflug-Based Ocular Biomechanics and Myopic Maculopathy. Bioengineering 2026, 13, 658. https://doi.org/10.3390/bioengineering13060658
Vieira BC, Rodrigues D, Heitor J, Coelho J, Sousa P, Lume M, Meireles A, Ambrósio R Jr., Menéres P, Beirão JM, et al. Relationship Between Scheimpflug-Based Ocular Biomechanics and Myopic Maculopathy. Bioengineering. 2026; 13(6):658. https://doi.org/10.3390/bioengineering13060658
Chicago/Turabian StyleVieira, Beatriz Costa, Diogo Rodrigues, João Heitor, João Coelho, Paulo Sousa, Miguel Lume, Angelina Meireles, Renato Ambrósio, Jr., Pedro Menéres, João Melo Beirão, and et al. 2026. "Relationship Between Scheimpflug-Based Ocular Biomechanics and Myopic Maculopathy" Bioengineering 13, no. 6: 658. https://doi.org/10.3390/bioengineering13060658
APA StyleVieira, B. C., Rodrigues, D., Heitor, J., Coelho, J., Sousa, P., Lume, M., Meireles, A., Ambrósio, R., Jr., Menéres, P., Beirão, J. M., & Baptista, P. M. (2026). Relationship Between Scheimpflug-Based Ocular Biomechanics and Myopic Maculopathy. Bioengineering, 13(6), 658. https://doi.org/10.3390/bioengineering13060658