


Abstract
Treatment of aircraft with insecticide in a procedure referred to as ‘disinsection’ is recommended to prevent the conveyance of arthropod vectors internationally and to mitigate the globalization of vector-borne infectious diseases. However, the full spectrum of human-based outcomes related to disinsection of conveyances has not been recently synthesized. A systematic review was conducted to evaluate the human safety and toxicity of insecticides used during the process of disinsecting international aircraft, marine vessels, rail, and ground transportation of mosquitoes. The systematic review was conducted according to the PRISMA guidelines and was registered in PROSPERO (CRD42024543998). The certainty of the evidence was rated, and key primary outcomes, including human health effects of conveyance disinsection, were synthesized. A total of 21 studies that described human health effects of conveyance disinsection and reported outcomes of safety, toxicity, and tolerability were included, and were of generally limited quality and high risk of bias, with low to very low certainty of estimates of effect. No high-quality studies investigating the safety, toxicity, or tolerability of disinsection were identified. Human health effects, including morbidity, including work days lost, adverse events including hospitalization, objective measures of insecticide toxicity, detectable and elevated urinary metabolites, and subjective reporting of symptoms consistent with acute insecticide poisoning, were reported by the small number of uncontrolled observational studies and public health surveillance reports included. Given the reports of significant morbidity, adverse events, and toxicity putatively attributable to aircraft disinsection, well-designed studies in exposed populations investigating the full range of human health impacts of disinsection on passengers and crew are urgently needed.
Keywords:
aircraft; disinsection; insecticide; marine vessel; occupational health; pesticide; safety; tolerability; toxicity 1. Introduction
Aircraft ‘disinsection’ is a “procedure whereby health measures are taken to control or kill the insect vectors of human disease present in baggage, cargo, containers, conveyances, goods and postal parcels (International Health Regulations [IHR], Part I, article 1)” [1] to prevent international dispersal of mosquitoes and the diseases they vector. In practice, this process necessitates the application of aerosolized or liquid insecticides such a permethrin or d-phenothrin by ground crew and/or flight attendants to cabin surfaces and within cabin air. According to the IHR, disinsection should “be carried out so as to avoid injury and, as far as possible, discomfort to persons” (IHR, Part IV, article 22, Section 3) [1]; however, large-scale syntheses of human studies demonstrating the safety of disinsection procedures in highly exposed individuals, such as flight attendants and ground crew, are absent from the medical literature.
The first edition of the World Health Organization’s (WHO) comprehensive publication on aircraft disinsection methods and procedures, building on ad hoc earlier publications over the past several decades, was published in 2021 [2] and then updated in 2023 [3]. The updated document provides newer guidance on how to apply insecticides and the equipment used therein (Supplementary Table S1), type of spray specifications (i.e., aerosol vs. residual), updated tables for calculating amounts of aerosol spray required, newer protocols for pre-boarding and pre-departure cabin treatment, and the International Civil Aviation Organization (ICAO) certification requirements for the disinsection procedures. Many countries have developed specific aircraft disinsection regulations, which can be found in Supplementary Table S2. Moreover, marine conveyance disinsection regulations also exist, and countries requiring such procedures aboard marine vessels can be found in Supplementary Table S3.
Vehicles, including marine vessels, rail and ground transportation, and aircraft, contribute to the globalization of vector-borne infections, including arboviruses (e.g., dengue, chikungunya, Zika) and malaria through the conveyance of infected persons along with the mosquito and other vectors capable of pathogen transmission. Consequently, conveyance disinsection through the use of insecticides, including aerosol sprays, has been used to eliminate arthropod vectors of public health importance, including mosquitoes. However, despite the widespread use of disinsection, comprehensive guidance documents regarding the safety and toxicity of such procedures to human health are largely unavailable. As such, we undertook a systematic review to synthesize the literature around the human health effects of conveyance disinsection and report our findings herein. We also identify areas warranting future concerted research efforts.
2. Methods
A systematic review of conveyance disinsection was commissioned by the WHO [4] in accordance with the PICO framework below (Table 1). As a main outcome beyond effectiveness, the systematic review synthesizes the safety, toxicity and tolerability of mosquito disinsection of any areas of international conveyances, including the passenger chambers, cargo areas, and cargoes, of aircraft, marine vessels, and rail and ground transport vehicles, to prevent or reduce the spread of competent vectors of human disease via international travel (Table 1).
Table 1.
PICO (population, intervention, comparator, outcome framework) for the systematic review of disinsection safety, toxicity, and tolerability.
The systematic review was conducted according to the Preferred Reporting Items for Systematic Reviews and Meta-Analysis (PRISMA) guidelines [6] and registered with the International Prospective Register of Systematic Reviews (PROSPERO) database (CRD42024543998).
Inclusion criteria: All papers reporting on mosquito disinsection of any areas of any international conveyance, including aircraft, marine vessels, ground, and rail transport, according to the insecticide used (including but not limited to the most commonly used and historical insecticides such as DDT, d-phenothrin, and permethrin), and method of application were included. All of the following methodologies were included: systematic reviews, randomized controlled trials (RCTs), cohort studies, cross-sectional studies, case–control studies, case-series, and case reports (n ≥ 1). Studies with alternative methodological designs (e.g., conference abstracts) were also included, so long as they reported primary data.
Exclusion criteria: We excluded in vitro and animal studies as well as those that did not allow ascertainment and/or assessment of our pre-defined safety, toxicity, and tolerability outcomes (e.g., mathematical modeling studies). Studies that were carried out in models replicating conveyance interiors but which did not fully reproduce the conveyance environment (e.g., non-pressurized structure instead of an actual aircraft cabin; upholstery sections impregnated with insecticide in a laboratory rather than actual residual disinsection of an aircraft, etc.).
Outcomes: The PICO statement above describes the outcomes of relevance to the safety, toxicity, and tolerability systematic review (Table 1). The primary outcome addressed in the systematic review and from which the Summary of Findings tables were generated includes disinsection safety and toxicity, with proportionate and absolute human adverse events, objective measures of biological toxicity, levels of pyrethroids and their metabolites in human tissues and effluents, and objective and subjective measures of tolerability, morbidity, and mortality as the main outcomes of interest.
Search strategy: Electronic databases including PubMed, Embase, Medline, Scopus, LILACS, and CINAHL were searched from inception to 31 May 2025 without language restriction as previously described [4] using combinations of search terms related to disinsection, insecticides (e.g., DDT, permethrin, etc.), types of conveyance (e.g., airplane, ship, train, lorry, etc.), transportation sector (e.g., aviation, shipping, rail, ground transportation), relevant occupational hazards (e.g., flight attendant, crew, etc.), mosquitoes, and relevant vector-borne diseases disseminated via international conveyances (e.g., malaria, dengue, Zika, etc.). The exact search terms employed, as previously reported [4] were: (disinsection OR insecticide OR d-phenothrin OR permethrin OR deet OR spraying OR “mosquito control”) AND (travel OR airport OR airplane OR plane OR aviation OR aircraft OR airline OR air-cans OR truck OR bus OR cargo OR rail OR train OR tram OR marine OR ship OR boat OR lorry OR vessel OR submarine OR space OR spacecraft OR rocketship OR spaceship OR “marine vehicle” OR “marine vessel” OR “cruise ship” OR “water taxi” OR ferry OR barge OR “passenger chamber” OR “cargo area” OR “land transport vehicles”) AND (neurotoxicity OR crew OR passengers OR “flight attendant” OR “occupational exposure” OR insect OR mosquito OR malaria OR “airport malaria” OR dengue OR chikungunya OR zika).
Literature not appearing in the six targeted databases, including conference proceedings, dissertations, and other documents existing in the public domain, was captured by searching databases such as OpenGrey and the Grey Literature Report. A hand search of the bibliographies of key papers was executed to capture applicable literature not otherwise captured. The online platform Covidence was used for overall study management, deduplication, title, abstract, and full-text screening. Articles were double-screened independently by two reviewers, with discrepancies resolved via discussion and/or by a third arbitrator.
Two independent reviewers conducted the data extraction, which was validated by the study lead according to the Grading of Recommendations, Assessment, Development, and Evaluation (GRADE) framework [7,8,9]. Articles not written in English were screened and extracted by reviewers speaking the relevant language (e.g., French, Spanish) or were translated into English using Google Translate (Google, Mountain View, CA, USA). Non-English language full-texts sent to the study team by the University of Toronto’s interlibrary loan system as image files were saved as PDF files and then processed through optical character recognition software [10,11,12] in order to facilitate Google translation. Any discrepancies that arose were resolved by conversation between reviewers, and any disagreements were adjudicated by a tertiary author. Following data extraction, standard “study characteristics” tables were created, and then data were synthesized in aggregate both quantitatively and qualitatively, where applicable. Standard “Summary of Findings” tables were then generated using GRADEpro GDT (Cochrane, Oxford, UK and McMaster University, Hamilton, ON, Canada, 2025). If outcomes were reported inconsistently or when different types of data were collected and reported across studies, preventing numerical synthesis, narrative synthesis was conducted and represented in text format only.
Data Analysis: Sample sizes, means with standard deviations, mean differences, and/or medians with ranges and interquartile ranges were reported for continuous variables. Frequencies and proportions with 95% confidence intervals were reported for dichotomous or categorical variables (such as the presence of adverse event, for example) when provided. We planned to collect continuous outcomes (mean difference), and dichotomous outcomes (relative risk, and odds ratio) when available, and reported them in Summary of Findings tables if and when the study producing primary data included a comparator group, using a standardized measure of treatment difference. Summary estimates of both continuous and dichotomous outcomes were pooled for each combination of disinsection exposure (including insecticide used and application method) and safety outcome (e.g., biological toxicity, objective morbidity, subjective tolerability, etc.). The level of significance was set at a 5% alpha level for summary estimates of outcomes measured against a comparator. Statistical analyses were executed using GRADEpro GDT (Cochrane, Oxford, UK and McMaster University, Hamilton, ON, Canada, 2025), GraphPad PRISM v.9.0 (GraphPad, La Jolla, CA, USA), and Review Manager (RevMan, computer program, version 5.3. Copenhagen: The Nordic Cochrane Centre, The Cochrane Collaboration, 2014).
Included studies were examined for key health equity factors represented by the acronym PROGRESS, which includes place of residence; race or ethnicity; occupation; gender and sex; religion; education; socioeconomic status; social capital or resources; and additional relevant stratifiers such as sexual orientation, marital status, and gestational status, as previously reported [13]. We also included other health equity and human rights stratifiers signified by the acronym CANDALS—citizenship; ability; neurotypicality or neurodiversity; disability; age; literacy and/or fluency in a universal language of aviation; and size, body mass index (BMI) or body habitus, as described previously [14]. Studies were reviewed for any description of and/or data stratification by the PROGRESS-CANDALS factors.
Risk of Bias and Certainty of Evidence: Forms to score risk of bias (ROB) were adapted in accordance with standard critical appraisal tools developed by the Joanna Briggs Institute, were designed, and populated independently and simultaneously by two reviewers to execute the bias assessment [15]. Ascertainment of methodological quality followed the GRADE framework by scoring each included study a ‘quality grade’ of high, moderate, low, or very low, based on the ascertained level of bias [7,8,9]. Discussion resolved discrepancies, and in the case of non-agreement, a tertiary arbitrator was engaged. Outcomes either inadequately or not fully reported, or assessments obtained only subjectively (such as by self-report of adverse event, for example) meant that risk for reporting and/or information/outcome bias, respectively, were present. Assessments of bias were aggregated, and an overall ROB score was ascertained for each study. The aggregate bias risk was rendered according to the degree (i.e., adequate or not) of allocation, concealment, blinding, attrition, and completeness of reporting, where noted and applicable to the study design, by one reviewer and then validated by a second reviewer. The software RevMan (version 5.3), Copenhagen: The Nordic Cochrane Centre, The Cochrane Collaboration, 2014, was used to generate heatmaps of study quality.
Further GRADE measures such as outcome inconsistency, indirectness, and imprecision, along with degree of publication bias and likely confounding, effect size, and relevant dose–response gradients were noted, where applicable, when evaluating certainty of evidence. Overall, ROB was considered in conjunction with these additional GRADE measures to generate one final, consolidated certainty of evidence GRADE score, according to each reported safety, toxicity, and tolerability outcome, whether objective or subjective in nature.
Sources of expected effect heterogeneity likely to affect the safety outcomes included but were not limited to: specifications of the insecticide applied (including type, formulation and concentration, such as 2% permethrin vs. 2% d-phenothrin, for example); whether or not the air filtration system of the conveyance was operational during application of insecticide and, if so, the number of air exchanges per unit time on the conveyance; model of the particular conveyance having insecticide applied (e.g., specific models of aircraft, type of marine vessel, etc.); climate-related measures including ambient temperature, humidity, UV index, cabin pressure, and altitude during insecticide application; and the precise time of travel during which insecticide application occurred (e.g., at pre-embarkation vs. taxiing vs. time of descent). The disinsection process constitutes a multistep sequence with variability inherent to individuals applying insecticide, and is, therefore, a “complex intervention”. Individuals of diverse height, strength, and stride cadence are expected to apply insecticides nonuniformly and, therefore, generate potential effect heterogeneity. The extent and rate of insecticide dispersion are most likely influenced by climatic and ambient conveyance factors, including but not limited to operation of the air conditioner, as is recommended by authoritative guidance [16]. Each of these types of factors was considered and extracted in as granular a form as was reported by the primary study and subsequently noted in the Study Characteristics tables. A lack of such granularity was indicated in the limitations of data generalizability and external validity section of the descriptive text.
3. Results
3.1. Literature Search
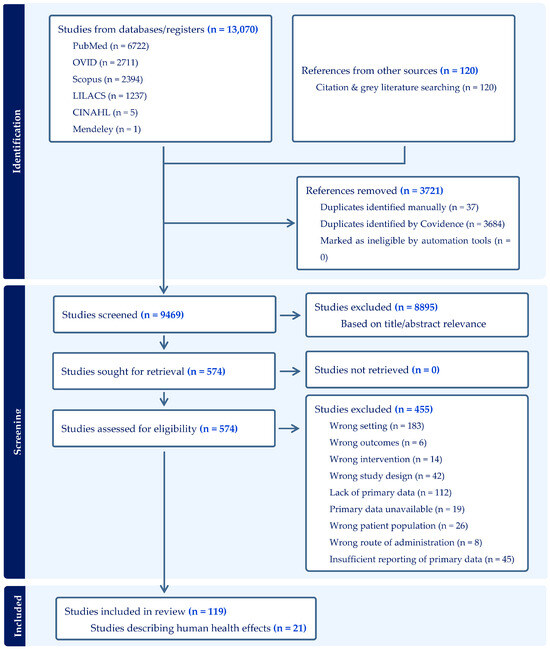
Of the 9469 unique articles identified in the search, 574 moved through to full-text screening, after which 455 were excluded for not fulfilling inclusion criteria (Figure 1). This review forms part of a broader systematic review series evaluating the disinsection of vehicular conveyances across multiple domains, including efficacy, human health effects, and epidemiological outcomes. Of 119 unique included articles or studies identified across the entire systematic review series, 21 reported primary human health effects, including toxicity, subjective tolerability, morbidity, and/or mortality. These publications are the focus of this specific systematic review and will be exclusively discussed herein.
Figure 1.
PRISMA flow diagram of literature examined for inclusion in the systematic review of safety, toxicity, and tolerability of international conveyance mosquito disinsection.
3.2. Included Studies
Table 2 pertains to studies reporting the safety, toxicity, and tolerability of aircraft disinsection in humans with primary reported outcomes of morbidity, adverse events, objective measures of toxicity, and subjective measures of tolerability.
Safety and Toxicity of Disinsection
A total of 21 studies evaluating the human safety, toxicity, and/or tolerability of aircraft mosquito disinsection fulfilled inclusion criteria (Table 2), of which 11 were experimental trials without human control arms [17,18,19,20,21,22,23,24,25,26,27], 1 was a case–control study with a comparator arm of unexposed Arizona residents [28], 1 was a cohort study with both exposed and unexposed flight attendants [29], 5 were case series [30,31,32,33,34], 1 was a case report [35], and 2 were review articles reporting primary data [36,37].
Of 21 studies evaluating or reporting on human safety, toxicity, and tolerability of aircraft disinsection of mosquitoes, 3 studies reported significant chronic morbidity [28,32,34], 3 studies reported specific adverse events and health safety effects [32,34,35], 12 studies reported objective signs and/or biological markers of exposure and/or toxicity [17,25,26,27,28,29,30,31,37], 11 studies reported on subjective symptoms in those exposed [18,20,26,28,30,32,33,34,35,36,37], and 8 studies reported on subjective tolerability with or without subjective symptoms [19,20,21,23,24,34,36,37].
3.3. Summary of Methodological Quality and Risk of Bias Assessment
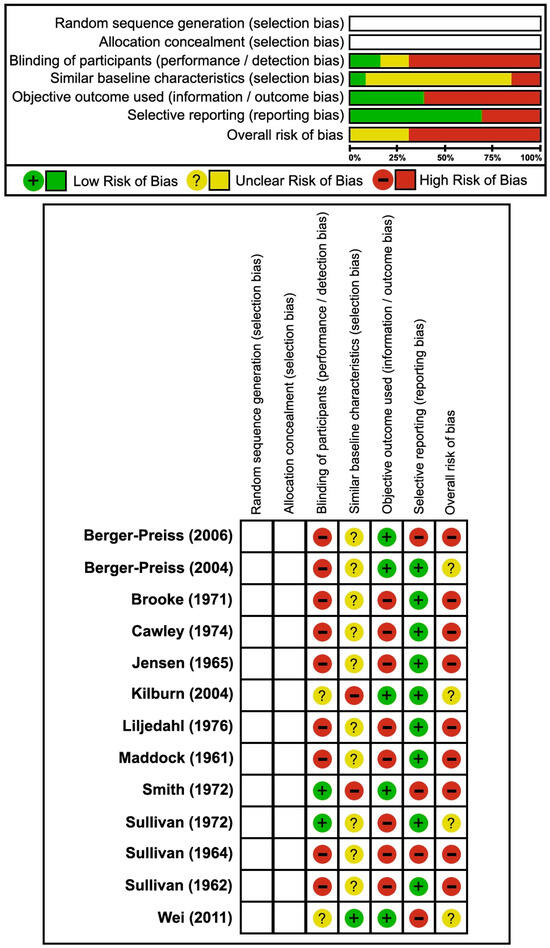
Of the 21 studies included in this review, only 13 provided sufficient methodological information to permit structured risk-of-bias assessment, as the remaining eight were case reports or case series that lacked the data necessary for domain-level evaluation. Overall, aircraft disinsection studies reporting human safety, toxicity, and tolerability were of low quality and high risk of bias (Figure 2, Table 3), with only two human studies reporting an unexposed human comparator or control arm [28,29]. Only one study [29] of aircraft disinsection evaluating safety or toxicity in humans adhered to standard study design or reporting of methodological rigor including: approval by institutional review boards or research ethics committees governing human subjects considerations in research; description or notation of recruitment process, eligibility assessment, and informed consent of participants; study protocol registration; a statement of independence of investigators from stakeholders and disclosures of funding; and collection and reporting of objective biological, behavioral, or psychological metrics corroborating subjectively reported tolerability, and more notably, intolerability. Despite this, although all included studies implemented disinsection as an intervention, none incorporated randomization or allocation concealment procedures consistent with formal interventional trial methodology. Therefore, two domains under “Selection Bias” in Figure 2 were intentionally left blank to illustrate this absence. Collectively, studies of human safety, toxicity, and/or tolerability of aircraft mosquito disinsection were either at serious risk of bias for morbidity outcomes [28,32,34] or very serious risk of bias for safety, toxicity, and tolerability outcomes [19,26,27,28,30,31,32,33,34,35], with estimated health effects of very low certainty according to GRADE assessment.
Figure 2.
Risk of bias assessment for studies reporting the safety, toxicity, and tolerability of conveyance disinsection. Studies cited: [17,18,19,20,21,22,23,24,25,26,27,28,29].
Table 2.
Characteristics of studies examining the safety and toxicity conveyance disinsection that were included in the systematic review.
Table 3.
Summary of Findings: Safety, Toxicity, and Tolerability of Conveyance Disinsection.
3.4. Quantitative and Qualitative Synthesis
Summary of Findings—Safety and Toxicity
The Summary of Findings Table 3 provides a quantitative synthesis of aircraft disinsection safety, toxicity, and tolerability. Where age and/or sex were reported [27,28,29,31,34,35], participants were mostly in young to middle adulthood, with men outnumbering women at a ratio of 1.75 to 1. Participants also largely represented those employed by the aviation industry as flight attendants, crew, pilots, technicians, or engineers [18,19,20,21,22,24,28,29,30,31,32,33,34,36], authors of the studies themselves [17,18,20,25,26], and passengers [21,22,23,24,30,34,35,36].
Among studies reporting attributable morbidity in just over one-third of exposed participants [28,32,34], notable findings included 8 individuals (19%) reporting early retirement due to symptoms related to disinsection, 8 individuals (19%) reporting long-term disability related to disinsection, 14 individuals (70%) reporting hospitalization, and an estimated 78 work days lost due to disinsection (Table 3).
Among studies reporting specific adverse events attributable to aircraft mosquito disinsection in more than 50% of exposed participants [32,34,35], notable findings included 1 case of anaphylaxis, 1 case of blood-cell disorder, and 14 cases of seizure (Table 3).
Among studies reporting objective evidence of toxicity attributable to aircraft mosquito disinsection in almost two-thirds of exposed participants [17,25,26,27,28,29,31,32,33,34,35], notable findings included detectable serum and/or urinary metabolites of insecticides (15/15 tested) [29,31]; epileptic encephalogram (5%); impaired cardiovascular function (15%); and impaired pulmonary function (24%). Additionally, objective signs of insecticide toxicity included conjunctivitis (19%); lip edema (25%); skin erythema (12.5%); and anemia (48.5%) (Table 3). One study with a comparator arm of unexposed controls [28] noted that exposed flight attendants had a significantly higher number of neurocognitive abnormalities on objective and validated testing compared to unexposed controls (mean 2.8 versus 1.2, respectively), and one cohort study of flight attendants both exposed and unexposed to disinsection demonstrated significantly elevated urinary concentrations of pyrethroid metabolites in those flying disinsected routes compared to those not [29]. Moreover, the urinary concentration of pyrethroid metabolites in the unexposed flight attendants (ie, those not flying routes that were disinsected) did not differ from that of the general population [29]. The flights conferring the highest urinary metabolites of pyrethroids in exposed flight attendants were those to and from Australia [29].
Among studies reporting subjective symptoms attributable to aircraft mosquito disinsection in 97% of exposed participants [18,20,26,28,30,32,33,34,35], notable findings included reports of systemic symptoms including fever (10%) and myalgia (5%); dermatologic symptoms such as rash (44%) and hair loss (36%); neurologic symptoms (53%) such as numbness, impaired concentration, loss of consciousness, headache, and impaired memory; respiratory symptoms (74%) such as shortness of breath; cardiovascular symptoms (42%); gastrointestinal symptoms (29%) such as nausea and diarrhea; and finally other localizing symptoms such as epistaxis (33%) and ocular symptoms (62%) (Table 3). Among 38 eligible participants in one study, 100% had symptoms consistent with insecticide poisoning [30]. In the one study with a comparator arm of unexposed controls, the mean frequency of 35 specific symptoms was almost twice that of unexposed controls [28].
Among studies reporting subjective tolerability in the absence of specific symptoms [19,20,21,23,24,34,36,37], malodour was reported by 14% of participants (Table 3).
Given the absence of studies with comparator arms across standardized methodologies, pooled summary estimates of safety and toxicity, such as relative risks and odds ratios, could not be calculated.
3.5. Health Equity and Human Rights Considerations
The body of main and supporting literature related to human safety and toxicity of disinsection reported very few of the PROGRESS-CANDALS factors and did not stratify the occurrence of specific outcomes according to such factors. In general, only a handful of studies or reports investigating the human health effects of disinsection, including safety, toxicity, and tolerability, reported the sex [27,31,34,35] and/or age [27,28,29,31,35] breakdowns of their participants. Given that women are more likely to be employed as flight attendants, studies of flight attendants in particular skewed more to female participants. A greater number of studies or reports of human health effects noted participants’ occupations as flight attendants, pilots, and crew [19,20,21,22,24,28,29,30,32,33,34,36] or technicians and engineers [18,31], as such employment engendered occupational exposure to disinsection. However, no studies stratified their findings according to PROGRESS-CANDALS factors as none were designed a priori or powered for such subgroup analyses.
4. Discussion
The systematic review identified that high-quality studies evaluating the safety, toxicity, and tolerability of aircraft disinsection were unidentifiable through our search strategy, and if such data exist, they are absent from the published medical literature and grey literature that is publicly available. Moreover, reports of health equity and human rights considerations of disinsection were absent from the included literature as well. Given that women of childbearing age are over-represented amongst cohorts of flight attendants, the reporting of health and safety outcomes according to sex and pregnancy status is of paramount importance. Of particular concern is the breadth and quality of evidence surrounding human health impacts, as no high-quality studies investigating the safety, toxicity, or tolerability of disinsection were identified. Rather, the literature base describing human health effects of disinsection comprises very limited post hoc public health surveillance, small cohort studies, one unmatched case–control study, case series, and case reports. Despite this, multiple countries have national-level regulations regarding aircraft and marine vessel disinsection using aerosolized and liquid formulations of insecticides such as permethrin and phenothrin (Supplementary Tables S2 and S3).
Experimental trials that commented on safety and tolerability in humans were primarily designed to test the insecticidal efficacy of disinsection, and standard human subject considerations and measures of methodological rigor in clinical research were largely ignored or not reported. The highest quality cohort study (which reasonably adhered to acceptable standards of methodological rigor) of flight attendants noted demonstrable elevations of urinary pyrethroid metabolites in those flying disinsected routes compared to those who did not. That particular study did not extend its findings to either subjective or objective measures of human toxicity; as such, the implications of elevated urinary pyrethroid concentrations in this context remain unknown. The scant safety and toxicity literature base has a high risk of bias; however, given the reports of significant morbidity, adverse events, and toxicity putatively and objectively attributable to aircraft disinsection, well-designed clinical and occupational health studies investigating the full range of human health impacts of disinsection on passengers and crew are urgently needed.
Current guidance on methodological components to include in studies of disinsection efficacy [16] are process process-oriented, and we could identify no corollary guidelines for assessing the safety and toxicity of aircraft or other conveyance disinsection. The long history of insecticide approval for use aboard aircraft and in many other occupational and household contexts is almost certainly underpinned by human safety and toxicity data that were unavailable publicly and unidentifiable by our search strategy. Making such reports available not just to regulatory agencies responsible for adjudicating safety, but to all stakeholders, including the public, in a comprehensive and organized manner, is a matter of urgency.
Based on the types and quality of safety and toxicity reports included, the human health effects of aircraft disinsection procedures are unknown. What literature does exist is concerning for a potential safety signal and, as a matter of urgency, is establishing safety and toxicity specifically of aircraft and marine vessel disinsection through methodologically rigorous, prospective, registered, IRB-approved, sufficiently powered, placebo-controlled (i.e., sham disinsection) human trials with adequate post-exposure follow-up. Reported outcomes in such trials should focus on the safety and toxicity of insecticides across the human lifespan and across the range of exposures one would expect to encounter both occupationally and as a passenger, and should include both subjective and objective measures of safety. Furthermore, a specific focus of safety and toxicity outcomes in the most vulnerable of potentially exposed individuals—including children, pregnant women and women of childbearing age, and those marginalized according to PROGRESS+ factors—should be prioritized, and studies should be sufficiently powered to report their outcomes accordingly.
5. Conclusions
The full spectrum of human-based outcomes related to aircraft disinsection remains incompletely understood, and accrual of primary data through high-quality research is an urgent research agenda. Additionally, there is a severe paucity of synthesized information regarding the safety and toxicity of marine, rail, and land conveyance disinsection, which are also utilized in national and regional-level vector-management systems globally. Given the potential hazards associated with insecticide exposure, particularly among those most vulnerable, such as pregnant women and children, capturing the full range of human health effects of disinsection procedures is critically important.
Current literature is limited almost entirely to small cohort studies, unmatched case–control studies, case series, and case reports, with an absence of standardized methodology, comparator groups, and ethics or institutional review board approval. As such, the human health effects of aircraft disinsection procedures remain unknown, acknowledging the inherent limitations of this systematic review given the quality and design of available studies. To address these limitations, methodologically rigorous, prospective, registered, IRB-approved, and sufficiently powered trials with both subjective and objective measures of safety and toxicity, and adequate post-exposure follow-up, are urgently needed. Comparator trials employing sham disinsection versus standard operating procedures should be pursued. Future research should also prioritize vulnerable populations, including children, pregnant women, and those marginalized according to PROGRESS+ factors, to ensure that safety and toxicity outcomes are representative and equitable.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/toxics13110965/s1, Table S1: WHO-recommended aircraft cabin disinsection procedures, Table S2: Countries and territories with Aircraft Disinsection Regulations, Table S3: Disinsection Regulations for Marine/Submarine Conveyances. References [38,39,40,41,42,43,44] are included in the Supplementary Material.
Author Contributions
Conceptualization, A.K.B.; Methodology, M.K., G.D.H., S.Z.A., C.M., A.R.-J., J.H., A.A. and A.K.B.; Software, A.K.B., M.K.; Validation, M.K., G.D.H., S.Z.A., C.M., A.R.-J., J.H., A.A. and A.K.B.; Formal Analysis, M.K., G.D.H., S.Z.A., C.M., A.R.-J., J.H., A.A., A.K.B.; Investigation, M.K., G.D.H., S.Z.A., C.M., A.R.-J., J.H., A.A., A.K.B.; Resources, A.K.B.; Data Curation, M.K., G.D.H., S.Z.A., C.M., A.R.-J., J.H., A.A. and A.K.B.; Evidence Synthesis—Table Creation and Editing, M.K., G.D.H., S.Z.A., C.M., A.R.-J., J.H., A.A. and A.K.B.; Writing—Original Draft Preparation, A.K.B.; Writing—Review and Editing, M.K., G.D.H., S.Z.A., C.M., A.R.-J., J.H., A.A. and A.K.B.; Visualization, M.K., G.D.H., S.Z.A., C.M., A.R.-J., J.H., A.A. and A.K.B.; Supervision, A.K.B.; Project Administration, A.K.B.; Funding Acquisition, A.K.B. All authors have read and agreed to the published version of the manuscript.
Funding
This study was commissioned and paid for by the World Health Organization (WHO). Andrea Boggild is supported as a Clinician Scientist by the Department of Medicine at the University Health Network. Michael Klowak and Greg Hawley are supported by Ontario Graduate Scholarships and the Institute of Medical Science at the University of Toronto.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Copyright in the original work on which this article is based belongs to WHO. The authors have been given permission to publish this article. The author(s) alone is/are responsible for the views expressed in the publication, which do not necessarily represent the views, decisions, or policies of the World Health Organization.
Data Availability Statement
All available data are contained in the manuscript.
Acknowledgments
The authors would like to thank Mika Kawano, Richard John Brown, and Ninglan Wang of the WHO for helpful discussion and critical feedback.
Conflicts of Interest
The authors have no conflicts to declare.
References
- World Health Organization. International Health Regulations (2005), 3rd ed.; World Health Organization: Geneva, Switzerland, 2016. Available online: https://apps.who.int/iris/handle/10665/246107 (accessed on 2 November 2025).
- World Health Organization. WHO Aircraft Disinsection Methods and Procedures; World Health Organization: Geneva, Switzerland, 2021. Available online: https://iris.who.int/handle/10665/339863 (accessed on 2 November 2025).
- World Health Organization. WHO Aircraft Disinsection Methods and Procedures, 2nd ed.; World Health Organization: Geneva, Switzerland, 2023. Available online: https://iris.who.int/handle/10665/374318 (accessed on 2 November 2025).
- WHO. Effectiveness of Disinsection of Conveyances to Prevent or Reduce the Spread of Mosquito Vectors via International Travel: Evidence Review; World Health Organization: Geneva, Switzerland, 2025. [CrossRef] [Scilit]
- World Health Organization. Aircraft Disinsection Insecticides; Environmental Health Criteria 243; World Health Organization: Geneva, Switzerland, 2013. Available online: https://iris.who.int/handle/10665/100023 (accessed on 2 November 2025).
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Guyatt, G.H.; Oxman, A.D.; Vist, G.E.; Kunz, R.; Falck-Ytter, Y.; Alonso-Coello, P.; Schünemann, H.J. GRADE: An emerging consensus on rating quality of evidence and strength of recommendations. BMJ 2008, 336, 924–926. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guyatt, G.; Oxman, A.D.; Akl, E.A.; Kunz, R.; Vist, G.; Brozek, J.; Norris, S.; Falck-Ytter, Y.; Glasziou, P.; deBeer, H.; et al. GRADE guidelines: 1. Introduction-GRADE evidence profiles and summary of findings tables. J. Clin. Epidemiol. 2011, 64, 383–394. [Google Scholar] [CrossRef] [Scilit]
- Atkins, D.; Best, D.; Briss, P.A.; Eccles, M.; Falck-Ytter, Y.; Flottorp, S.; Guyatt, G.H.; Harbour, R.T.; Haugh, M.C.; Henry, D.; et al. Grading quality of evidence and strength of recommendations. BMJ 2004, 328, 1490–1494. [Google Scholar] [CrossRef] [Scilit]
- OCR Space. OCRSpace: Online OCR. 2023. Available online: https://ocr.space/ (accessed on 2 November 2025).
- Deep L. Deep L Translator. 2024. Available online: https://www.deepl.com/translator (accessed on 2 November 2025).
- OpenAI. PDF Translator (GPT-4). 2024. Available online: https://chatgpt.com/g/g-DTk1KpYjg-pdf-translator (accessed on 2 November 2025).
- WHO. Handbook on Health Inequality Monitoring; World Health Organization: Geneva, Switzerland, 2013. Available online: https://www.who.int/docs/default-source/gho-documents/health-equity/handbook-on-health-inequality-monitoring/handbook-on-health-inequality-monitoring.pdf (accessed on 2 November 2025).
- WHO. Evidence to Recommendations: Methods Used for Assessing Health Equity and Human Rights Considerations in COVID-19 and Aviation; Interim guidance, 23 December 2020; World Health Organization: Geneva, Switzerland, 2020. Available online: https://apps.who.int/iris/bitstream/handle/10665/338056/WHO-2019-nCoV-Aviation-evidence_equity-2020.1-eng.pdf?sequence=1&isAllowed=y (accessed on 1 February 2021).
- Joanna Briggs Institute. Checklist for Systematic Reviews and Research Syntheses. Available online: https://jbi.global/critical-appraisal-tools (accessed on 6 November 2025).
- WHO. Guidelines for Testing the Efficacy of Insecticide Products Used in Aircraft; World Health Organization: Geneva, Switzerland, 2012. Available online: https://www.who.int/publications/i/item/9789241503235 (accessed on 2 November 2025).
- Berger-Preiss, E.; Koch, W.; Gerling, S.; Kock, H.; Klasen, J.; Hoffmann, G.; Appel, K.E. Aircraft disinsection: Exposure assessment and evaluation of a new pre-embarkation method. Int. J. Hyg. Environ. Health 2006, 209, 41–56. [Google Scholar] [CrossRef] [Scilit]
- Brooke, J.P.; Evans, M. Disinsection of aircraft with pressure packs containing the pyrethroids, resmethrin and bioresmethrin. Pestic. Sci. 1971, 2, 133–137. [Google Scholar] [CrossRef] [Scilit]
- Cawley, B.M.; Sullivan, W.N.; Schechter, M.S.; McGuire, J.U. Desirability of three synthetic pyrethroid aerosols for aircraft disinsection. Bull. World Health Organ. 1974, 51, 537–540. [Google Scholar] [PubMed]
- Liljedahl, L.A.; Retzer, H.J.; Sullivan, W.N.; Schechter, M.S.; Cawley, B.M.; Morgan, N.O.; Amyx, C.M.; Schiefer, B.A.; Gerberg, E.J.; Pal, R. Aircraft disinsection: The physical and insecticidal characteristics of (+) phenothrin applied by aerosol at ‘blocks away’. Bull. World Health Organ. 1976, 54, 391–396. [Google Scholar]
- Sullivan, W.N.; Keiding, J.; Wright, J.W. Studies on aircraft disinsection at ‘blocks away’. Bull. World Health Organ. 1962, 27, 263–273. [Google Scholar]
- Sullivan, W.N.; Azurin, J.C.; Wright, J.W.; Gratz, N.G. Studies on aircraft disinsection at “blocks away” in tropical areas. Bull. World Health Organ. 1964, 30, 113–118. [Google Scholar]
- Sullivan, W.N.; Pal, R.; Wright, J.W.; Azurin, J.C.; Okamoto, R.; McGuire, J.U.; Waters, R.M. Worldwide studies on aircraft disinsection at “blocks away”. Bull. World Health Organ. 1972, 46, 485–491. [Google Scholar]
- Jensen, J.A.; Flury, V.P.; Schoof, H.F. Dichlorvos vapour disinsection of aircraft. Bull. World Health Organ. 1965, 32, 175–180. [Google Scholar]
- Berger-Preiss, E.; Koch, W.; Behnke, W.; Gerling, S.; Kock, H.; Elflein, L.; Appel, K.E. In-flight spraying in aircrafts: Determination of the exposure scenario. Int. J. Hyg. Environ. Health 2004, 207, 419–430. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maddock, D.R.; Sedlak, V.A.; Schoof, H.F. Preliminary tests with DDVP vapor for aircraft disinsection. Public Health Rep. 1961, 76, 777–780. [Google Scholar] [CrossRef] [Scilit]
- Smith, P.W.; Mertens, H.; Lewis, M.F.; Funkhouser, G.E.; Higgins, E.A.; Crane, C.R.; Sanders, D.C.; Endecott, B.R.; Flux, M. Toxicology of dichlorvos at operational aircraft cabin altitudes. Aerosp. Med. 1972, 43, 473–478. [Google Scholar]
- Kilburn, K.H. Effects of onboard insecticide use on airline flight attendants. Arch. Environ. Health Int. J. 2004, 59, 284–291. [Google Scholar] [CrossRef] [Scilit]
- Wei, B.; Mohan, K.R.; Weisel, C.P. Exposure of flight attendants to pyrethroid insecticides on commercial flights: Urinary metabolite levels and implications. Int. J. Hyg. Environ. Health 2012, 215, 465–473. [Google Scholar] [CrossRef] [Scilit]
- Bonta, D.M.; Davis, G. Occupational Illness Among Flight Attendants Due to Aircraft Disinsection; State of California Health and Human Services Agency, Department of Health Services: Oakland, CA, USA, 2003.
- Edmundson, W.F.; Davies, J.E.; Cranmer, M. DDT and DDE in blood and DDA in urine of men exposed to 3 percent DDT aerosol. Public Health Rep. 1970, 85, 457–463. [Google Scholar] [CrossRef] [Scilit]
- Przyborowski, T.; Rychard, J.; Tyrakowski, M. Dieldrin insecticide as a cause of an outbreak of intoxication on board of a ship. Prz. Epidemiol. 1962, 16, 315–320. [Google Scholar]
- Sutton, P.M.; Vergara, X.; Beckman, J.; Nicas, M.; Das, R. Pesticide illness among flight attendants due to aircraft disinsection. Am. J. Ind. Med. 2007, 50, 345–356. [Google Scholar] [CrossRef] [Scilit]
- Woodyard, C. Fliers Fume Over Planes Treated with Pesticides. USA Today. 9 October 2001. Available online: https://www.perrysanderslaw.com/fliers-fume-over-planes-treated-with-pesticides/ (accessed on 2 November 2025).
- Vanden Driessche, K.S.; Sow, A.; Van Gompel, A.; Vandeurzen, K. Anaphylaxis in an airplane after insecticide spraying. J. Travel Med. 2010, 17, 427–429. [Google Scholar] [CrossRef] [Scilit]
- Bitelli, M. Disinfection of airplanes. Minerva. Med. 1969, 60, 3672–3681. [Google Scholar]
- de Tavel, F. Measures to be taken to prevent the transmission of Aedes aegypti by sea and air. Bull. World Health Organ. 1967, 36, 639–644. [Google Scholar]
- Aircraft Disinsection Requirements | US Department of Transportation. Available online: https://www.transportation.gov/airconsumer/spray (accessed on 3 October 2024).
- Air Canada. Health and Travel Tips. Available online: https://www.aircanada.com/ca/en/aco/home/plan/peace-of-mind/travel-tips.html#/ (accessed on 3 October 2024).
- Subiakto, Y. Aviation Medicine Capacity on Facing Biological Threat in Indonesia Airports. Infect. Dis. Rep. 2020, 12, 8738. [Google Scholar] [CrossRef] [Scilit]
- Health Canada. ARCHIVED—Ship Sanitation Certificate Program. Available online: https://www.canada.ca/en/health-canada/services/healthy-living/travel-health/general-advice/ship-sanitation-certificate-program-health-canada.html (accessed on 3 October 2024).
- The Swedish Club. China: Yellow Fever Prevention Measures. Available online: https://www.swedishclub.com/news/loss-prevention/china-yellow-fever-prevention-measures/ (accessed on 3 October 2024).
- The Swedish Club. Zika Virus: South Korea Requires Self-Disinfection Certificates for Vessels. Available online: https://www.swedishclub.com/news/loss-prevention/zika-virus-south-korea-requires-self-disinfection-certificates-for-vessels/ (accessed on 3 October 2024).
- Interim Guidance on Maritime Transport and Zika Virus Disease. Available online: https://www.shipsan.eu/Portals/0/docs/MaritimeZika_EUSHIPSAN_UPDATE_13.4.2016.pdf (accessed on 3 October 2024).

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).