


Abstract
Background/goal: Hypertrophic pachymeningitis is a rare chronic inflammatory disorder characterized by marked fibrous thickening of the cerebral and/or spinal dura mater. This condition has largely been reported in adults, but there are very few reports in children. Methods: We describe a 14-year-old boy with idiopathic hypertrophic pachymeningitis, who presented with deteriorating vision on a background of severe headache. We evaluated pediatric cases of hypertrophic pachymeningitis and compared treatments and their relation to outcomes. Results: There are only eleven pediatric cases of hypertrophic pachymeningitis reported in the literature. In the patients treated with steroids either at presentation or subsequent relapses, a good response was reported. In the cases with delayed initiation of steroid treatment, this was often related to an incomplete recovery. In our patient, this delay may have contributed to his poor visual outcome. Conclusions: Early initiation of steroid treatment in children with idiopathic hypertrophic pachymeningitis may improve outcomes.
1. Introduction
Hypertrophic pachymeningitis is a rare inflammatory disorder characterized by localized or diffuse thickening of the cranial or spinal dura mater, resulting in progressive neurological deficits. The etiology of the pachymeningitis is thought to be immune in nature or secondary to other possible causes of dural reaction, such as infectious conditions (neurosyphilis, tuberculosis, fungal infections, syphilis, Lyme’s disease); collagen vascular disorders (granulomatosis with polyangiitis, rheumatoid arthritis, systemic lupus erythematosus, mixed connective tissue disease); neoplasia (dural carcinomatosis, meningioma en plaque, lymphoma) and miscellaneous disorders such as sarcoidosis, mucopolysaccharidosis, intracranial hypotension syndrome and intrathecal drug administration [1,2]. IgG4-related hypertrophic pachymeningitis (IgG4-RHP), a recently described entity, is an increasingly recognized manifestation of IgG4-related disease, a fibroinflammatory condition that can affect virtually any organ [3]. The present report describes a 14-year-old boy with idiopatic hypertrophic pachymeningitis, the course of his illness, his response to treatment and a comparison to the other cases reported in literature.
2. Case Study
A previously healthy 14-year-old boy presented with a several-week history of deteriorating vision on a background of experiencing headaches 9 months prior, which worsened over recent months. He reported double vision and progressive loss of vision in the right eye over the few weeks prior to presentation. There were no other constitutional symptoms like fever, night sweats or weight loss. The patient reported a non-specific insect bite 3 months prior, and there was no history of recent foreign travel.
The key finding on clinical examination was a fulminant right optic neuritis, where he could only perceive light, alongside right sided 4th and 6th cranial nerve palsy. There was no evidence of uveal disease. He had a full neurological examination, which did not reveal any abnormality. His systemic examination was normal and in particular there was no evidence of lymphadenopathy, organomegaly or cutaneous features of connective tissue disease.
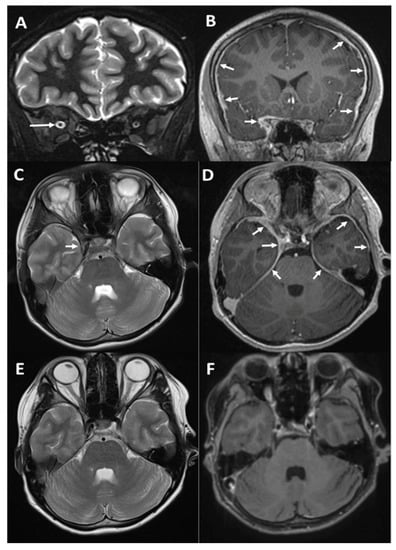
Magnetic resonance imaging (MRI) identified widespread dural (pachymeningeal) thickening with contiguous involvement of the cavernous sinus on the right side (Figure 1) with no evidence of brain parenchymal or white matter involvement.
Figure 1.
MRI findings in our patient. Top row (A,B): Coronal STIR image at presentation showing mild congestion of the right orbit with a dilated optic nerve sheath but normal signal of the optic nerve ((A), long arrow); coronal post-contrast T1w (T1 weighted) image showing diffuse dural thickening extending to the right cavernous sinus and optic canal, where it surrounds the optic nerve ((B), small arrows). Middle row (C,D): Axial T2w (C) and post-contrast T1w (D) images showing normal brain appearances but diffuse bilateral dural thickening with subtle corresponding low signal on T2. Bottom row ((E,F)): Follow-up imaging after a month showing resolution of the dural enhancement, though there is still some evidence of right 6th cranial nerve palsy (note the adducted right globe).
Following consultation with the infectious diseases and rheumatology team, investigations were initiated which did not reveal an infective or immune etiology for the presumed pachymeningitis (Table 1).
Table 1.
Investigations excluding infectious and immune etiology of pachymeningitis in our case.
High-dose pulsed intravenous methylprednisolone 30 mg/kg/day was administered for 3 consecutive days and his vision began to improve (counting fingers), along with a vast improvement in his headaches. He was converted to 60 mg prednisolone orally daily. Although dural biopsy was considered, a marked improvement in his imaging (Figure 1) to a near resolution of the lesion did not present us with a biopsy target. Similarly, systemic imaging with a whole-body MRI also failed to identify a potential lesion to biopsy or any underlying systemic process.
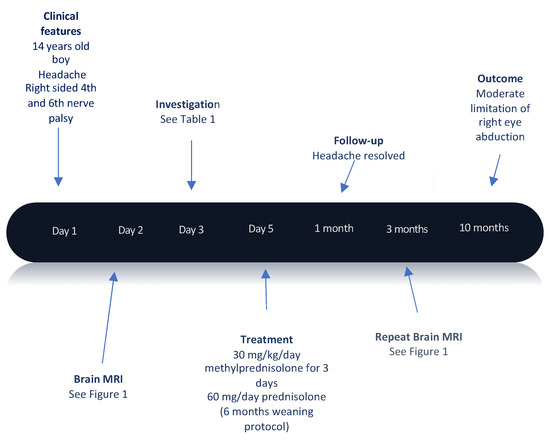
He was reviewed in the outpatient clinic a month after discharge and was doing well. His headaches had resolved completely (timeline detailed in Figure 2). Ophthalmology assessment revealed an ongoing reduction of vision in the right eye with a central visual acuity of LogMAR 1.52 (2/60) and remaining limitation of abduction in the right eye to the mid-line. His optical coherence tomography showed retinal nerve fiber layer thinning in the right eye and a stable, normal retinal nerve fiber layer in the left eye.
Figure 2.
Timeline of our patient’s history.
At 3 months from symptom presentation, while on a slow steroid taper (10 mg daily, 6 months weaning protocol), repeat imaging continues to demonstrate no active dural disease. At latest follow-up (10 months), he remains well clinically and his visual acuity has improved to LogMAR 0.50 (6/19) in the right eye. His eye movements also continue to improve, with only 25% limitation of right abduction and he has no esotropia or double vision when looking straight ahead. He continues to have a mild right relative afferent pupillary defect and a pale right optic disc.
3. Discussion
Hypertrophic pachymeningitis was first described by Charcot and Joffroy in 1869 [4]. It is a rare chronic inflammatory disorder characterized by marked thickening of the cerebral and/or spinal dura matter. It has been described in association with infection, trauma, tumors and immune-mediated disease such as granulomatosis with polyangiitis, neurosarcoidosis or IgG4 related disease [1,2,3,5]. In cases when no causative factors can be identified, the condition is referred to as ‘idiopathic” [6].
The thickened dura causes progressive neurological impairment. Chronic headache and multiple cranial neuropathies are the most common clinical manifestations [5,6]. These may include ataxia, facial pain, cranial nerve involvement and neuro-ophthalmic complications such as papilledema and various neurological deficits [1,2].
The diagnostic workup should include serology tests for VZV, Mycoplasma pneumoniae, Haemophilus influenzae type B, HTLV1(Human T-cell lymphotropic virus type 1), HHV6(Human Herpes Virus 6), Enterovirus, Borrelia burgdorferi, CMV(cytomegalovirus), HIV(Human Immunodeficiency Virus), syphilis, EBV(Epstein-Barr Virus) and, in endemic areas, tuberculosis tests (Quantiferon tests and/or Mantoux skin testing). Moreover, an autoimmune screening is recommended, including neuronal surface antibody research and a complete CSF (Cerebral Spinal Fluid) exam.
The definitive diagnosis is based on MRI or brain biopsy of the thickened dura mater, which reveals interstitial fibrosis and inflammatory cell infiltration.
This condition has largely been reported in adults, but there are very few reports in children. We performed a review of the literature (Medline 1990–present) using the search terms (hypertrophic pachymeningitis) AND (paediatric OR pediatric OR children OR childhood). Twelve cases referring to children (<18 years old) were identified and the full manuscripts were available for review [7,8,9,10,11,12,13,14,15,16,17,18].
Among the twelve pediatric cases of hypertrophic pachymeningitis reported in the literature, three cases developed in association with tuberculosis [10,11,17], one was PR3-ANCA-associated [13], two developed in association with IgG4-RD [16,18] and six were regarded as idiopathic [7,8,9,12,14,15]. The clinical features, MRI findings, biopsy results, treatment and outcomes are summarized in Table 2.
Table 2.
Clinical data of 13 patients with hypertrophic pachymeningitis.
In the patients treated with steroids either at presentation or subsequent relapses, a good response to steroids was reported (6 events; Case 2 relapse (R) 1; Case 3 presentation (P) and R1; Case 5 P; Case 7 R1; Case 9 P; Case 12 P and R1).
However, the course of the disease was chronic and relapsing in six of the 13 cases, necessitating more aggressive immune therapy such as methotrexate, cyclophosphamide, intraventricular cytarabine, azathriopine or rituximab (Cases 2, 3, 6, 7, 9 and 12).
Of the two patients (Cases 1 and 2) treated conservatively, one patient relapsed, who then responded to steroids (Case 2). Overall, all but one case (Case 6), had a satisfactory outcome (mRS 0–2). Residual visual deficits occurred in two cases and hypoglossal palsy in one case (Cases 3, 5 and 9); one chronically deteriorated neurologically into a chronic vegetative state (Case 6).
Although immunotherapy-responsive, the delay in initiating steroid treatment in our patient may have contributed to his poor visual outcome. In the reported cases with a lag in initiating steroid treatment, this was often related to an incomplete recovery (Case 2 initiating 21 months later at relapse; Case 3 6 months from prior episode managed as viral meningitis; Case 6 10 weeks).
In conclusion, idiopathic hypertrophic pachymeningitis can present in children and should be considered in cases of pachymeningitis and negative findings from diagnostic evaluation.
Early initiation of steroid treatment may improve the outcome.
Author Contributions
E.R. and M.L. performed the literature review, derived the key messages of the manuscript, wrote and revised all versions of manuscripts. A.E.R., V.S. and A.S. reviewed the relevant specialty-specific data and revised all versions of the manuscripts. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Informed Consent Statement
Patent and family have consented to clinical history and investigations being presented in this publication.
Data Availability Statement
Authors will be happy to share anonymized clinical data additional to those provided in manuscript uopn request.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Dash, G.K.; Thomas, B. Clinico-radiological spectrum and outcome in idiopathic hypertrophic pachymeningitis. J. Neurol. Sci. 2015, 350, 51–60. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kupersmith, M.J.; Martin, V. Idiopathic hypertrophic pachymeningitis. Neurology 2004, 62, 686–694. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Melenotte, C.; Seguier, J. Clinical presentation, treatment and outcome of IgG4-related pachymeningitis: From a national case registry and literature review. Semin. Arthritis Rheum. 2019, 49, 430–437. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Charcot, J.M.; Joffroy, A. Deux cas d’atrphie musculaire progressive avec lesions de la substance grise et des faisceaux anterolateraux de la moelle epiniere (in French). Arch. Physiol. Norm. Pathol. 1869, 2, 354–367, 629–649, 744–746. [Google Scholar]
- Hahn, L.D.; Fulbright, R. Hypertrohic pachymeningitis. J. Neurolog. Sci. 2016, 367, 278–283. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Riku, S.; Kato, S. Idiopathic hypertrophic pachymeningitis. Neuropathology 2003, 23, 335–344. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Asano, T.; Hayashida, M. Hypertrophic cranial pachymeningitis in a patient with aplastic anemia. Ann. Hematol. 1998, 77, 279–282. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Toorn, R.; Esser, M. Idiopathic hypertrophic cranial pachymeningitis causing progressive polyneuropathies in a child. Eur. J. Paediatr. Neurol. 2008, 12, 144–147. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aburahma, S.K.; Anabtawi, A.G. Idiopathic hypertrophic pachymeningitis in a child with hydrocephalus. Pediatr. Neurol. 2009, 40, 457–460. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karimi, A.; Tabatabaei, S.R. Tuberculous pachymeningitis in a young child with spinal involvement: A case report. Arch. Pediatr. Infect. Dis. 2013, 1, 36–39. [Google Scholar] [CrossRef] [Scilit]
- Sharma, P.K.; Saikia, B. Pachymeningitis in a young child responded to antitubercular therapy: A case report. J. Child Neurol. 2014, 29, 92–95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsuchida, K.; Fukumura, S. Rapidly progressive fatal idiopathic hypertrophic pachymeningitis with brainstem involvement in a child. Childs Nerv. Syst. 2018, 34, 1795–1798. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matsumoto, K.; Akiyama, M. Adolescent PR3-ANCA-positive hypertrophic pachymeningitis. A case report and review of the literature. Medicine 2018, 97, 17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brand, B.; Somers, D. Diplopia with dural fibrotic thickening. Semin. Pediatr. Neurol. 2018, 26, 83–87. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsieh, D.T.; Faux, B.M. Headache and hypoglossal nerve palsy in a child with idiopathic hypertrophic pachymeningitis. Headache 2019, 59, 1390–1391. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nambirajan, A.; Sharma, M. Large dural-based mass with bony hyperostosis in a 16-year-old male: IgG4-related disease mimicking lymphoplasmacyte-rich meningioma. Childs Nerv. Syst. 2019, 35, 1423–1427. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharawat, I.K.; Saini, A.G. “Encased brain” in hypertrophic pachymeningitis. Childs Nerv. Syst. 2019, 35, 585–587. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vakrakou, G.; Evangelopoulos, M. Recurrent myelitis and asymptomatic hypophysitis in IgG4-related disease: Case-based review. Rheumatol. Int. 2020, 40, 337–343. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2020 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).