


Abstract
Background/Objectives: Contemporary health systems continue to face persistent challenges in financing, equity, and governance, particularly under conditions of limited resources, workforce shortages, and demographic pressures. While the World Health Organization calls for strengthening social participation to achieve universal health coverage, evidence suggests that such participation often remains largely symbolic. Existing global examples of social participation in health are limited either by their short duration of implementation or by their limited scope. In contrast, the experience of former Yugoslavia (1945–1991) represents a distinctive case. In the early post-war period, health reforms were directed towards the development of a decentralised, self-managed health system that emphasised universal coverage, participatory governance, social solidarity, and local autonomy. The trajectory of these reforms was further shaped by global economic and political pressures, including neoliberal trends, international debt, and the oil crises, which constrained resources and exposed systemic vulnerabilities. The so-called Yugoslav Experiment may offer an alternative to existing market-oriented and, at times, inefficient health systems. This review aims to synthesise evidence on the governance, financing, organisation, and outcomes of Yugoslavia’s self-managed health system and to evaluate its relevance to contemporary debates on health system resilience, decentralisation, participatory governance, equity, and sustainability. It examines power relations, stakeholder interests, and resource allocation, and assesses the lessons that the Yugoslav experience offers for contemporary debates on participatory governance and the sustainability of healthcare systems, while identifying areas of convergence, debate, and gaps in the existing scholarship. Methods: We conducted a systematic narrative review of peer-reviewed articles, book chapters, conference papers, and commentaries published in English or Bosnian–Croatian–Montenegrin–Serbian that covered the period 1945–1991. Scopus, PubMed, and EBSCOhost (including CINAHL Plus with full text, Medline and PsychInfo) were searched on 19 January 2026. Studies were included if they addressed health system reform, self-management, governance, financing, or institutional continuity. Contextual studies of selected services—primary care, mental health, reproductive health, and vaccination—were included only if they illuminated reform trajectories. Data synthesis focused on reform phases, institutional transformations, financing arrangements, governance mechanisms, and power relations, with particular attention to continuity, path dependence, and critical junctures. Given the heterogeneous and predominantly historical, analytical, and policy-oriented nature of the literature, we did not apply conventional study-design-specific risk-of-bias tools. Instead, we used an overarching framework to classify and contextualise the included evidence according to five dimensions: source type, nature of contribution, evidentiary role, temporal context, and health-system domain. The protocol was not registered. The study was financed by the Provincial Secretariat for Higher Education and Scientific Research, Autonomous Province of Vojvodina, Republic of Serbia. Results: The database searches yielded 265 records, of which 193 were selected for title and abstract screening after removing 72 duplicates. At this stage, 133 publications were excluded because they did not meet the eligibility criteria and 60 publications were selected for full-text review. Application of the predefined inclusion and exclusion criteria resulted in 22 eligible publications. An additional 18 studies were identified through citation chaining and targeted Google Scholar searches. Twenty-two publications were coded as primary studies, directly examining health system reform, governance, or self-management, while 18 were classified as contextual studies addressing specialty areas. The analysis identified key reforms that followed the social participation, i.e., ‘self-management’, approach, which expanded primary care, preventive services, and local participation. It revealed institutional changes, as well as the role of power and health financing in health reforms aimed at strengthening social participation. Nonetheless, challenges—including bureaucratic and managerial elitism, unequal professional authority, resource scarcity, and tensions between market-oriented policies and social solidarity—were amplified by global economic forces and neoliberal trends, ultimately contributing to the system’s collapse by the late 1980s. This review was limited by its search strategy, the exclusion of grey literature, the potential omission or inaccessibility of relevant studies, and its focus on selected aspects of health reform, namely post-war recovery and self-management. Conclusions: The Yugoslav experience illustrates both the promise and the fragility of socially oriented, participatory health systems, demonstrating how international political alignments and global economic pressures can profoundly shape domestic health reform trajectories. Lessons from this case remain relevant to contemporary efforts to strengthen social participation for universal health coverage through designing sustainable, resilient, equitable, and socially accountable health systems under complex global conditions.
1. Introduction
The last three and a half decades have represented a period of profound health reforms at the global level. The end of the Cold War and the collapse of the Eastern European bloc triggered extensive reform processes across Central and Eastern Europe in the early 1990s, but also globally [1]. Rapid globalisation, together with international initiatives aimed at combating HIV, tuberculosis, malaria, and other major diseases, generated new demands for adaptation within national health systems. At the same time, comprehensive reform programmes promoted by international financial institutions, particularly the World Bank and the International Monetary Fund, had a significant influence on health policy design and implementation in many countries [2,3].
Ten years ago, the World Health Organization acknowledged that functional health systems delivering high-quality services to the population are a key priority for governments, and that achieving this requires permanent, well-structured, and dynamic processes, underpinned by genuine consensus between the demand for and supply of services, as well as among governments, service providers, and the population, through robust, evidence-informed policy dialogue [4]. Social participation is defined as “empowering people, communities, and civil society through inclusive participation in decision-making processes that affect health, across the policy cycle and at all levels of the system” [5]. The COVID-19 pandemic further highlighted the fundamental importance of social participation in fostering trust in governments and public institutions, demonstrating that regular and institutionalised dialogue, in which people feel heard, are empowered to express their views, and are able to influence decisions, strengthens trust, supports effective COVID-19 responses, and advances the right to health [6].
Three main areas of scholarly interest in participatory governance and healthcare have been identified: the relationship between community participation and the improvement and tailoring of healthcare services; the involvement of patients and their families in therapeutic practices; and comparative analyses of case studies focusing on participatory governance in healthcare policymaking [7]. Although valuable studies have examined experiences of participatory governance in healthcare in countries including Brazil [8], Thailand [9], South Korea [10], and elsewhere [5,6], their findings are often limited in two respects: either the implementation period was relatively short, or social participation was confined to only certain aspects of healthcare. Furthermore, almost all of these studies focus on the participation of patients and citizens, while only rarely addressing the participation of healthcare workers in decision-making and the management of health institutions and health systems.
Although the available studies mainly discuss social participation for health from the early 1990s onwards, this phenomenon has a much longer history. In former Yugoslavia, it existed for nearly forty years before the country dissolved in 1991, in a specific form known as (workers’) self-management. While it was initially introduced in industrial complexes, it spread to health institutions in the early 1950s. Over the following decades, it evolved continuously and represented a form of social experiment, sometimes called ‘Yugoslav experiment’ [11].
In its mature phase during the 1970s, it included a complex framework of social participation and participatory governance, participatory decision-making processes, and transformed health institutions to ensure the direct participation of each worker in decision-making, as well as the involvement of the local community. The long duration of this specific type of social participation in health, together with the many avant-garde approaches that were introduced, allowed it to be monitored, measured, and evaluated. It attracted widespread interest among Western and local scholars concerned with participatory democracy and worker involvement [11,12,13,14,15,16]. Yugoslavia’s openness towards the West and its sustained economic growth encouraged researchers to study not only its healthcare system but also broader aspects of its society. Self-management was frequently cited as a key factor underlying the country’s perceived successes [15,16].
This systematic narrative review aims to synthesise evidence on the governance, financing, organisation, and outcomes of Yugoslavia’s self-managed health system and to evaluate its relevance to contemporary debates on health system resilience, decentralisation, participatory governance, equity, and sustainability. It examines power relations, stakeholder interests, and resource allocation and assesses the lessons that the Yugoslav experience offers for contemporary debates on participatory governance and the sustainability of healthcare systems, while identifying areas of convergence, debate, and gaps in the existing scholarship.
2. Materials and Methods
2.1. Setting
Yugoslavia was formed in 1918 from territories previously under Austro-Hungarian, Ottoman, and, until the end of the 18th century, Venetian rule for centuries, with Serbia and Montenegro having been internationally recognised as independent in 1878. Prolonged foreign domination left the new state economically underdeveloped, predominantly agrarian, and characterised by high mortality and illiteracy rates. The interwar period was marked by economic, political, and ethnic tensions.
The Second World War resulted in an estimated 1.7 million deaths, around 250,000 orphans, and destruction of nearly one-third of all buildings [17]. Yugoslav partisans, led by the Communist Party, assumed power in 1944–1945. Following the 1948 break with the Soviet Union, Yugoslavia pursued an independent socialist path, later establishing a system of workers’ self-management. Economic crises in the 1970s contributed to growing political instability and rising nationalism, culminating in the country’s dissolution in 1991, with conflicts continuing into the early 2000s.
2.2. Methodological Approach
The decision to adopt a systematic narrative review was deliberate and informed by the nature of the research question and the characteristics of the available literature. Our aim was to systematically identify, evaluate, and synthesise the existing evidence while allowing for an interpretive narrative synthesis, given the heterogeneity of the included studies in terms of study designs, populations, and the concepts and outcomes examined. This heterogeneity limited the suitability of a conventional systematic review with quantitative synthesis.
A scoping review was not considered appropriate because the purpose of this study extended beyond identifying and describing the range and characteristics of the existing literature. Instead, our aim was to synthesise and interpret the findings in relation to our specific research question. Similarly, a historical review was not considered appropriate because tracing the development of the topic over time was not the primary objective. Therefore, a systematic narrative approach provided the most appropriate framework for maintaining a systematic and transparent search and study-selection process, while accommodating the heterogeneous nature of the evidence and enabling an integrated narrative synthesis.
2.3. Search Strategy
A systematic narrative review was conducted in line with PRISMA 2020 guidelines [18] (Appendix D, Table A2). Scopus, PubMed, and EBSCOhost (including CINAHL Plus with full text, Medline and PsychInfo) were searched on 19 January 2026 using combinations of terms related to Yugoslavia, health, and reform:
“Yugoslavia” AND “health” AND (“reform” OR “crisis” OR “recovery” OR “socialism” OR “self-management”)
The search strategy was piloted prior to conducting the final searches. The strategy was assessed to determine whether it retrieved meaningful and relevant results and was also tested against a set of known relevant studies to confirm that these studies were identified. The pilot confirmed that the search strategy was appropriate, and therefore no modifications were considered necessary before conducting the final searches.
No date restrictions were applied; searches included all records up to 19 January 2026. Results were exported to Rayyan for records management.
Additional sources were identified through screening reference lists of included studies and the first ten pages of Google Scholar results to capture literature not indexed in the primary databases. Search terms and inclusion criteria were designed to capture both studies explicitly addressing health system reform and those providing contextual insights into governance, financing, professional roles, or sector-specific services.
2.4. Eligibility Criteria
Included publications were peer-reviewed journal articles, book chapters, conference papers, editorials, commentaries, viewpoints, and letters. Abstracts had to be available in English or Bosnian–Croatian–Montenegrin–Serbian. Studies were eligible if they explicitly discussed health system reform or provided relevant contextual information on healthcare organisation, governance, financing, or professional roles, covering fully or partially the period 1945–1991.
Excluded publications included those with unavailable full texts or in ineligible languages, studies focusing exclusively on periods outside 1945–1991 without meaningful overlap, or studies not providing substantive discussion of health systems, healthcare organisation, or institutional context. Non-peer-reviewed sources, such as dissertations, theses, news articles, interviews, as well as protocols and book reviews, were also excluded.
2.5. Screening and Data Extraction
All search results were imported into Rayyan, and duplicates were removed. Titles and abstracts were independently screened by two researchers, with disagreements resolved through discussion or consultation with a third reviewer. Full texts were obtained for studies meeting inclusion criteria at the title/abstract stage. Two researchers independently reviewed the full texts to ensure coverage of reform phases, self-management, governance, financing, and institutional context. Any discrepancies between the reviewers were discussed to reach a consensus. When consensus could not be achieved, a third author was consulted to facilitate resolution of the disagreement.
Data were extracted into Excel, capturing bibliographic information, temporal context, system component, source type, evidentiary role (classified as primary or contextual), nature of contribution (empirical, historical, etc.), health-system domain, institutional structures, financing arrangements, governance mechanisms, key actors and their interactions, and indicators of continuity, path dependence, or critical junctures.
2.6. Evidence Classification and Appraisal
Given the heterogeneous and predominantly historical, analytical, and policy-oriented nature of the literature, we did not apply conventional study-design-specific risk-of-bias tools. Instead, we used an overarching framework to classify and contextualise the included evidence according to five dimensions: source type, nature of the contribution, evidentiary role, temporal context, and health-system domain.
Studies were classified according to their evidentiary role as either primary or contextual. Primary studies were those that directly addressed health system reform, self-management, or governance under socialism. Contextual studies were eligible if they either provided in-depth analysis of specific services or specialties—including mental health, reproductive health, vaccines, or primary care—relevant to understanding reform trajectories, institutional continuity, or legacies of self-management, or provided background information on health system reform between 1945 and 1991.
The temporal context of each publication was also considered. Foundational studies covering pre-1945 developments were included when they informed postwar reform design, ideology, or institutional structures. Studies covering the post-1991 period were included when they provided insights into the legacy of self-management, institutional continuity, or adaptation of governance, financing, and service delivery arrangements.
The source type (e.g., journal article, book chapter, or conference paper) and nature of contribution (e.g., historical, review, empirical, analytical, or other) were recorded to distinguish the different forms and evidentiary bases of the literature. The health-system domain addressed by each publication was also recorded. These dimensions were used to contextualise the contribution of each source and to avoid treating heterogeneous forms of evidence as equivalent during the narrative synthesis.
2.7. Data Synthesis and Analysis
Data synthesis focused on mapping reform phases and critical junctures, examining institutional changes in organisation, financing, governance, and service delivery, and analysing power relations, interests, and conflicts among key actors. Primary studies formed the basis of the analysis of self-management, institutional reforms, and governance, while contextual studies complemented this analysis by highlighting sectoral, regional, and political influences.
Although the protocol was not prospectively registered, an internal protocol was developed and adhered to throughout the study.
3. Results
3.1. Overview of Included Publications
The database searches yielded 265 records, of which 193 were selected for screening titles and abstracts after removing 72 duplicates. At this stage, 133 publications were excluded because they did not meet the eligibility criteria and 60 publications were selected for full-text review. Applying predefined inclusion and exclusion criteria resulted in 22 eligible publications. An additional 18 studies were identified through citation chaining and targeted Google Scholar searches. In total, 40 publications were included in the final analysis (Figure 1; Appendix A; Appendix B).
Figure 1.
PRISMA Flow Diagram.
The temporal distribution of publications shows that relevant literature has become increasingly available over time. More than half (52.5%, n = 21) were published since 2000, while 42.5% (n = 17) appeared between 1970 and 1999. Two publications date from the early 1950s.
3.2. Geographic Distribution
Based on the corresponding or first author’s affiliation, the majority of publications originated from the United States (27.5%, n = 11), the United Kingdom (20%, n = 8), and Yugoslavia (12.5%, n = 5) or its successor states (Serbia, n = 4; Croatia, n = 1; Slovenia, n = 1). The remaining publications came from Australia, Canada, Denmark, Germany, New Zealand, Spain, and the Netherlands.
3.3. Publication Characteristics
Most publications were journal articles (85%, n = 34), with the remainder being book chapters (15%, n = 6; Appendix C, Table A1). Considering the nature of the contribution, 24 publications were historical (including eight combined articles—e.g., analytical or empirical with a historical overview), eight empirical, whereas other publications were theoretical articles, analytical articles, viewpoints or reports. Historical studies analysed reform trajectories and institutional development using secondary sources. Empirical studies drew on primary data—such as surveys, interviews, or secondary data —administrative records—often focusing on service organisation or governance.
Regarding the evidentiary role, 22 publications were coded as primary, directly examining health system reform, governance, or self-management, while 18 were contextual, addressing specialty areas (e.g., psychiatry, reproductive health, or vaccines) or focused primarily on developments before 1945 or after 1991.
By tracing constitutional, legislative, and institutional developments across the postwar period and situating them within the broader political trajectory of the socialist state, we identified distinct reform phases corresponding to critical political junctures. Drawing on extracted data from the included studies, we mapped health sector transformations, highlighting structural innovations—such as self-management councils and communal insurance associations—and the socio-political dynamics that shaped their implementation (Table 1).
Table 1.
Phases of Health Reform in Socialist Yugoslavia.
3.4. Wartime Period (1941–1945)
A formative wartime period (1941–1945) saw partisan medical units operating not only in liberated territories but also alongside combat forces, providing basic services and laying the foundation for postwar reform [21]. These units organised rudimentary clinics and mobile care, establishing professional networks that later underpinned postwar healthcare institutions. Despite severe resource scarcity and infrastructure destruction, partisan medicine emphasised collective responsibility, community engagement, and preventive practices. These experiences shaped postwar expectations regarding state responsibility, workforce mobilisation, and emergency health provision, influencing the institutional logic of the socialist health system [22,23].
3.5. Centralised Administrative Management (1945–1952: Administrative Socialism)
The first postwar phase was dominated by centralised, Soviet-inspired administration, with financing reliant on state budgets and health workers employed directly by the state [24,25,26,27,28]. Early reformers drew heavily on the interwar work of Andrija Štampar, whose vision of rural health, prevention, and social medicine guided post-1945 strategies [27,28]. Physicians, often assigned to rural or underserved areas, prioritised training and institution-building despite harsh living and working conditions [26,29,30]. Widespread outbreaks of infectious disease and profound psychological distress highlighted the scale of postwar health needs [31].
Following the 1948 Tito–Stalin split, Yugoslavia gradually moved away from Soviet-style command planning towards a distinct Yugoslav model combining socialism with decentralisation and worker participation [16,32]. While the state retained strong control, this period established the institutional and ideological groundwork for the decentralisation reforms of the 1950s and 1960s, particularly in healthcare financing and governance [16,33].
3.6. Early Self-Management (1953–1960: Administrative Market Socialism)
From as early as 1949, and more widely from 1953 onwards, self-management principles were introduced, initially in enterprises and progressively extended to the health sector [12,13,16,22]. Federal health planning evolved into a hybrid system, combining central guidance with increasing republic- and local-level authority, as annual and five-year plans devolved operational responsibilities to communes and institutions [13,32]. Social insurance began covering patient costs, and primary health centres (domovi zdravlja) were established to expand access and strengthen preventive services [34,35]. These centres provided universal coverage, addressed priority health problems, and cared for vulnerable groups through multidisciplinary teams embedded in local communities [36].
Workers’ councils became primary mechanisms for employee influence, holding authority to select managers from approved lists, set internal pay scales, determine hiring procedures, and allocate surpluses between wages and investment. While management guided most decisions, workers played a significant role in welfare, employment, and compensation matters [32]. Decentralised responsibility allowed communities and local governments to influence service provision, expanding the role of primary care physicians and preventive work [37]. Participatory bodies—such as workers’ councils, tenant councils, and assemblies of social service users and providers—broadened citizen and worker engagement in decision-making [38]. Challenges persisted, including limited expertise in health promotion, low professional status of primary care staff, weak citizen participation, and the continued dominance of curative, hospital-based medicine.
3.7. Formalised Self-Management (1961–1973: Market Socialism)
The main principles of the 1968 Law on Health Care and Health Service introduced elements of primary healthcare nearly a decade before the Alma Ata Conference [39,40]. During the 1960s and early 1970s, self-management principles were formalised within healthcare institutions, with expanded autonomy and financing increasingly reliant on workers’ and farmers’ insurance funds rather than state budgets [16,34,38]. Centrally planned state budgets were gradually replaced by “social plans,” giving enterprises greater autonomy over income, resource allocation, and market participation. While this encouraged efficiency, it also generated unemployment, emigration, and tensions between management and workers [32].
Health and other service institutions adopted a form of social self-management, with governance shared between employees and external representatives, including consumers, while budgets and staffing remained subject to oversight by councils and general assemblies [16,38].
Commune-level oversight and bicameral assemblies further institutionalised fiscal and administrative decentralisation. Efficiency gains were reported in some areas, yet tensions persisted between professional authority and worker councils, particularly regarding investment priorities and service organisation. Preventive care, mental health initiatives, and reproductive health programmes expanded during this period [24,41,42].
3.8. Constitutional Reforms and SMIC/BOAL Era (1974–1988: Contractual Socialism)
Following the 1974 Constitution and the Law on Associated Labour, Basic Organisations of Associated Labour (BOALs) and Health Self-Management Interest Communities (SMICs) became central governance units in the health sector [14,16]. BOALs enabled employees to participate formally in staffing, budgets, and service delivery decisions, while SMICs coordinated financing and planning across multiple institutions at the regional level. These reforms aimed to strengthen self-management and reduce reliance on market mechanisms, but they also increased institutional complexity. Economic stagnation, rising social inequalities, and growing nationalist tensions further strained coordination and equity [43,44].
Self-management during this period empowered local actors but also produced fragmentation and bureaucratic overload, particularly during fiscal crises [16]. Decentralised bargaining weakened coherent planning and reduced the capacity of social services to respond to macroeconomic shocks. The mid-1980s also saw institutional innovation and organisational experimentation, with management innovations introduced alongside worker-council governance [45].
3.9. Collapse Period (1989–1991)
The final phase corresponded with the disintegration of the Yugoslav federation. Political collapse, economic crises, and rising nationalism disrupted health system governance, financing, and service delivery. Worker councils, SMICs, and BOALs lost cohesion, budgets fell into deficit, and inter-republic coordination deteriorated, culminating in the near-total breakdown of previously established self-management mechanisms. The period exposed the vulnerability of decentralised institutions to political and economic shocks [11,23].
3.10. Forms of Institutional Change in Healthcare
Between 1945 and the 1980s, Yugoslav healthcare underwent major institutional changes. Initially, policymakers prioritised establishing a universal, centralised system of care [23,29]. Early legislation, such as the 1945 Law on Implementation of Social Insurance, centralised financing through the Central Institute for Social Insurance and initially prioritised industrial workers before extending coverage to the general population, reflecting socialist commitments to universal coverage [27,32].
The government emphasised preventive medicine and public health, targeting disease outbreaks such as typhus, malaria, dysentery, diphtheria, and tuberculosis, while promoting hygiene and health education to transform the largely rural society [21,27,33,36,38].
The 1950s and 1960s saw the establishment of community-oriented primary care centres (Dom zdravlja), staffed by multidisciplinary teams including general practitioners, paediatricians, gynaecologists, and nurses, with clearly defined preventive and consultative functions [31,33,46]. While these centres formed the foundation of primary care, preventive services remained underdeveloped, and primary care physicians often faced low prestige and poor remuneration relative to specialists [37]. Reproductive and family health services evolved progressively, culminating in the 1974 constitutional guarantee of reproductive choice [22].
A major institutional change was the introduction of workers’ self-management alongside wider economic reforms [8,11,23]. Hospitals and health centres were theoretically granted autonomy from the state and managed through worker councils and community representatives, responsible for budgeting, staffing, and planning local services [47]. Employees participated in assemblies approving budgets and selecting directors, reflecting the ideal of democratic workplace participation [8,23]. However, self-management frequently generated bureaucracy, inefficiency, and fragmentation, as local facilities pursued their own priorities, while technical managers and state representatives increasingly dominated decision-making [25,44].
Despite these challenges, Yugoslavia’s health system represents a unique attempt to combine central planning, socialised medicine, and localised self-management, combining universal coverage with worker and community involvement. Reforms extended to preventive medicine, mental health, reproductive rights, and primary care, showing how socialist goals and practical constraints shaped institutional change, including the perceived broader role of GPs in the community [12,23,31,41,48,49,50]. Coordination, resource allocation, and professional hierarchies remained challenges.
3.11. Health Financing
Healthcare was primarily financed through social insurance contributions, supplemented by state transfers, business donations, and user fees [28,34,35,42]. From the 1960s, decentralisation and self-management increased local influence over budgeting, service provision, and insurance coverage [12,51]. Contributions were collected at district or communal levels, and providers negotiated budgets with local social insurance bodies [40,42]. Small business owners and self-employed professionals contributed voluntarily, while specialised enterprise clinics created a parallel system bypassing community health centres, contributing to weaker general practice and preventive care [34].
The formal establishment of SMICs in health financing occurred after the 1974 Constitution, institutionalising local self-management and granting responsibility for administering insurance funds, negotiating services, and overseeing local healthcare delivery [28,35]. Decentralisation had mixed effects: regional life expectancy disparities declined, but inequalities in infant mortality increased [52]. Cost-sharing measures introduced in 1978 had limited impact on overall spending and tended to exacerbate inequities [44]. Solidarity mechanisms supported poorer regions and agricultural populations, gradually extending basic and hospital care to farmers by the 1980s [28,35]. As authority shifted between federal, republican, and local institutions, financing bodies gained or lost autonomy accordingly [12,16,38,51].
3.12. Power Relations
In the immediate postwar period, power was concentrated in the federal state, with the Central Institute for Social Insurance controlling financing and resources, leaving little autonomy to republics, municipalities, or local health institutions [24,25,33]. Health planning followed centralised Five-Year Plans, with limited decision-making power for communes and workers [13,37].
From 1953 through the 1960s, authority gradually shifted to republic and local levels. Social management bodies were created in health facilities and Social Insurance Institutes, though powers remained limited, and federal oversight continued [16]. Representation was uneven, with male experts overrepresented and workers and women underrepresented, limiting democratisation [16]. Federal authorities intervened when expenditures were deemed excessive, showing continued federal influence [16,42].
Between 1961 and 1974, the self-management system expanded, with communal insurance associations becoming principal financiers of health services. Federal authorities retained capacity for ad hoc intervention, while trade unions, local political elites, and enterprise representatives increased participation, though experts and elites maintained significant power [16]. Republican bureaucracies expanded authority amid Communist Party divisions, while municipal assemblies and communal organisations established control over local resources [12,16].
After the 1974 Constitution, decentralisation was institutionalised through SMICs and BOALs. SMICs oversaw municipal health financing and were governed by councils representing providers and consumers, while BOALs introduced worker self-management within enterprises and social services, allowing autonomous contract negotiation [14,40,44]. Consumer participation was strengthened through health parliaments, in which workers and citizens influenced budgeting, capital projects, and operational decisions [40].
3.13. Convergence, Debate, and Gaps
There is broad agreement that Yugoslavia achieved important public health gains under socialist self-management, despite structural and political constraints. Population health improved markedly, driven by reductions in infant and child mortality and infectious diseases, improvements in sanitation, nutrition, and maternal/childcare services [42]. Expansion of infrastructure—hospital beds, medical schools, and insurance coverage—also increased substantially [44].
Scholars largely agree that the Yugoslav model diverged from the Soviet Semashko system, combining decentralised community responsibility with universal coverage, affecting service availability and community engagement. The model represents a unique hybrid: centralised planning with decentralised self-management, market-based incentives with social insurance, and top-down authority with participatory governance [25,42,44].
Debates persist regarding the effectiveness of self-management. While formal structures allowed worker and citizen participation, professional elites and state regulators often dominated strategic decision-making, limiting true democratisation [14,16]. Opinions diverge on efficiency: some argue decentralisation improved responsiveness, while others highlight fragmentation and regional disparities [34,44,52].
Gaps include underexplored roles of gender and social inequality in care access and council participation, uneven development of preventive versus curative services, and limited analysis linking institutional reforms to long-term health outcomes, particularly during political and economic crises.
4. Discussion
Our systematic review presents the main aspects of health reform in Yugoslavia, which was guided by the principles of a specific form of social participation in healthcare—self-management. It represents an avant-garde and unique example of direct democracy in healthcare. During the mature phase of self-management, complex structures of social participation were developed, and healthcare institutions were transformed in an effort to ensure that every employee was included in the decision-making process. While the review identifies the main advantages of this particular approach to social participation, it also highlights its weaknesses. More specifically, it examines institutional change, health financing, the role of power, and the debates surrounding the effectiveness and limitations of self-management.
As stated by Chuong and O’Doherty, unlike consumerist approaches, democratic approaches explicitly address issues of power, emphasising the redistribution of power and a commitment to both individual and collective empowerment [53]. However, established forms of participation have often been largely symbolic and consultative, constrained by their tendency to operate at the micro level—through limited spatial reach and a focus on policy niches—as well as by their failure to adequately address asymmetrical power relations within and beyond participatory forums [7]. Consequently, most measures used to assess social participation involving citizens and policymakers focus primarily on the existence of participation rather than on its quality [54]. Our review found the opposite pattern: the empowerment of healthcare workers and other employees reached such an extent that it weakened healthcare institutions, while social participation at the local and subnational levels almost completely eroded national control over the healthcare system. Although the intention was to ensure that employees assumed full control over their respective units and that local communities took responsibility for healthcare governance within their communities, this often resulted in a lack of solidarity with more vulnerable groups and those with different healthcare needs.
In the immediate post-war period, Yugoslavia faced several challenges that remain relevant for many low-resource health systems today. Emerging from the devastation of the Second World War—during which 11% of Yugoslav citizens lost their lives—and soon confronted with political and economic isolation following the split with the Soviet Union, the country had to reconstruct a severely damaged health system with limited institutional and material resources [17]. This reconstruction occurred under conditions of severe material scarcity, a very limited number of qualified health professionals—often with outdated training—shortages of facilities, equipment, and medicines, and a population that, prior to the war, had been among the poorest in Europe [26,29]. Illiteracy rates exceeded 50%, most of the population lived in rural areas, and subsistence agriculture predominated [42].
However, the foundations of the post-war Yugoslav health system were not created ex nihilo. They drew heavily on interwar reforms led by Andrija Štampar, who promoted decentralised health administration, the establishment of a dense network of health institutions, and a strong focus on rural populations, health education and prevention [28,34]. Although politically sidelined in the 1930s, Štampar returned after the war to play a central role in Yugoslav health policy and in shaping the emerging World Health Organization. His vision—later described by Albrecht as “peasant internationalism”—deeply influenced the normative orientation of Yugoslav health reforms [27].
This approach materialised institutionally through the development of domovi zdravlja (primary health centres), community-based primary care facilities distributed across all territorial units and supported by satellite outpatient stations in smaller settlements, decades before the Declaration of Alma-Ata (acknowledged in 2018 by the Declaration of Astana) [55]. Over time, these centres integrated general practice with maternal and child health, occupational health, basic diagnostics, emergency care, dentistry, pharmacy, and selected specialist services [36,38]. In line with the ideological prioritisation of industrial workers, parallel systems of workers’ health care were also established within large enterprises or linked to health centres [25]. During the early post-war period, when infectious diseases, epidemics, and high infant and child mortality dominated the epidemiological landscape, health authorities emphasised prevention, hygiene, and health education [31]. Health was conceptualised holistically—as physical, mental, and social well-being—reflecting the belief that human beings were not merely biological units, but social and moral actors embedded in collective life [49].
In addition, the initial success of self-government in Yugoslavia was built upon widespread social enthusiasm rooted in the anti-fascist partisan resistance during the Second World War [26]. For many citizens, the end of the war represented both national liberation and the possibility of constructing a different social order, forged through mass mobilisation involving multiple Yugoslav peoples and nationalities, explicitly grounded in ideals of social justice and solidarity [31]. Within this movement, a wartime health service developed that was first tested under combat conditions and later expanded in liberated territories. Despite extreme material constraints, it provided care for the wounded and organised civilian health services, including epidemic control and health education [40,56]. These wartime experiences shaped post-war expectations regarding state responsibility for health, collective action, and the social role of medicine. These lessons may be relevant to countries currently experiencing the large-scale destruction of their healthcare systems (e.g., Ukraine and Palestine) or the collapse of both healthcare systems and wider society (e.g., Sudan).
The fact that Yugoslavia was largely liberated by its own population, rather than through external military imposition, is crucial to understanding its post-war trajectory [42]. This historical specificity, together with the 1948 conflict with the Soviet Union, created conditions for a sharp political reorientation. While the short-lived post-war centralisation modelled on Soviet administrative socialism achieved some success in emergency reconstruction, it also generated widespread dissatisfaction among civilians and former fighters [22]. The experience of importing rigid ideological models and “ready-made” solutions likely contributed to Yugoslavia’s decision to pursue an alternative path. This alternative trajectory later became known as self-management socialism. It emphasised decentralisation, reduced state control, and broader participation in decision-making. In the post-Cold War period, beginning in the 1990s, health system reforms in post-conflict and fragile settings were largely driven by attempts to replicate health systems from Western countries. These reforms often overlooked the recipient countries’ existing achievements and rarely resulted in sustainable health systems and programmes that were not dependent on foreign aid. By contrast, the Yugoslav experience demonstrated that an efficient health system can be built by strengthening previously established foundations, adapting reforms to local circumstances, and recognising that there is no single model for a sustainable health system.
Yugoslav self-management evolved through repeated reforms and institutional experiments. It was a continuous process of reform, often experimental, involving governance mechanisms introduced without clear empirical evidence of their effectiveness. The underlying rationale rested on an optimistic belief in the maturation of social consciousness: that educated, empowered, and formally autonomous citizens would govern according to principles of solidarity and the common good [41]. These assumptions were deeply rooted in Marxist theories, the legacy of the wartime resistance, interwar labour movements, and the strong post-war role of trade unions. Solidarity thus became a core ideological reference point—domestically and internationally—shaping Yugoslavia’s support for decolonisation movements and its leadership role within the Non-Aligned Movement.
After the initial post-war reconstruction phase, health reforms focused mainly on two areas: financing and institutional governance. From the early 1950s, the federal state gradually retreated from direct financing and decision-making. Budgetary funding was replaced by compulsory social insurance contributions paid primarily by workers, and over time, formal control over these funds was transferred—at least nominally—to the workers themselves. At the local level, health policy and resource allocation were debated within health parliaments and, later, self-managing communities of interest, bringing together representatives of service users and providers [12,16]. Health institutions were formally governed by workers’ councils, responsible for contracting services and managing internal affairs.
Over time, policymakers increasingly recognised that health-sector development depended on broader economic conditions, and that industrial growth was prioritised through partial marketisation. This shift disadvantaged the service sector, including health care [14,44]. Health workers were often paid less than industrial workers, resources remained limited, and post-war enthusiasm gradually eroded [15]. Professional prestige and informal authority—especially within hospitals—became compensatory mechanisms, reinforcing urban concentration and contributing to persistent rural–urban disparities. Decentralisation of education further produced a cohort of locally educated professionals facing limited employment opportunities, while labour market pressures and rationalisation fostered migration and social dissatisfaction [57].
Market-oriented reforms also facilitated the emergence of a managerial–bureaucratic elite composed of enterprise managers, bankers, and administrators [14,58]. Although workers’ councils formally governed institutions, real negotiations increasingly occurred between managers, financial institutions, and state officials. In response to rising social tensions and nationalism, the Yugoslav leadership introduced a new wave of reforms culminating in the 1974 Constitution and the 1976 Law on Associated Labour. These reforms intensified decentralisation and participatory governance through the fragmentation of large enterprises into basic organisations of associated labour and the strengthening of local communities and self-managing interest communities. The explicit aim was to weaken emerging elites and deepen direct participation [14,16].
In practice, however, these measures often weakened managerial capacity without generating corresponding responsibility among workers [32]. Expectations of solidarity between profitable and loss-making units were frequently unmet, and strikes became more common. These reforms coincided with economic stagnation, global neoliberal shifts, mounting external debt, IMF conditionality, and geopolitical instability. The oil crisis of 1979 and broader crises within socialist Europe further constrained reform capacity [32]. Yet perhaps the most prominent challenges observed in the mature phase of self-management were the weakening of healthcare institutions and the almost complete erosion of national control over the healthcare system. Potential reasons for weakened institutions might have been the lack of a sense of ownership and accountability. According to Muller, shared governance should involve employees actively participating in decision-making and problem-solving, while taking responsibility and accountability for the outcomes of their decisions. Authority should be delegated to the lowest appropriate level, enabling individuals to take ownership of both successful and unsuccessful outcomes and remain accountable for their professional and organisational responsibilities [59].
On the other hand, achieving the desired level of central control of the health system is equally difficult. Even beyond health systems, an additional layer of power and control may be challenging (e.g., the contemporary role of the United Nations, WHO, or EU bodies). As noted by Rechel et al., decentralisation aims to make services more responsive to local needs and market pressures, but it cannot resolve all the tensions involved [60]. Local, person-centred decision-making can create tensions between regional fairness, responsiveness to local preferences and the efficiency benefits of economies of scale [60].
The Yugoslav experience teaches us the same lesson as the one we learnt recently during the COVID-19 pandemic: while, as a global society, we have not yet found a solution for global solidarity, the same applies to a nation—namely, the lack of solidarity between regions and administrative units. Therefore, a fundamental shift in the way we perceive society should be a prerequisite for substantial healthcare reform. Such a shift is impossible under the neoliberal, market-oriented ideology, the same ideology that destroyed Yugoslav self-management.
Atuire et al. note that efforts to advance equity-driven global health are declining and are increasingly being replaced by a transactional model shaped by geopolitical competition, conditional partnerships and a retreat from multilateralism [61]. This approach prioritises exchange, leverage and strategic interests over shared commitments to improving health for all. In this context, the survival of global health as a meaningful ethical and political endeavour is at stake. They acknowledge that “solidarity is not only a moral aspiration but also the only viable organising principle capable of drawing and sustaining collective commitment in an actively fragmenting, yet deeply interdependent, world” [61].
Tong et al. propose six strategies to enhance solidarity: a. international agreements should be greatly strengthened, and treaties and other agreements defining shared stewardship should be actively pursued; b. public health and other professionals should understand the importance of solidarity and health professionals, in particular, as stakeholders, can play a significant role in advocating for taking action to make changes and can ally themselves with other thought leaders, such as cultural and religious leaders, to emphasise solidarity; c. we should endeavour to reduce inequities within societies because the challenges need to be addressed collectively, at local, regional, national and global levels; d. trust between people and institutions, as an index of solidarity, should be cultivated and respected, and tracked as a key social indicator, and this requires controlling the spread of disinformation and countering its effects; e. we must overcome key obstacles in achieving global solidarity—geopolitical, economic, behavioural and others; the principles of mutual understanding, mutual respect and mutual support should be upheld, and collaboration and cooperation from the interpersonal to the international scales are essential; and f. we should promote a transition towards a more integral and inclusive model of development, one grounded in solidarity and responsibility [62]. While the initial main aim of these strategies is to propose actions to increase solidarity within the public health field in the context of the Anthropocene, it is equally applicable to solidarity more broadly, which is a prerequisite for effective and sustainable self-management.
Rather than leading to the “withering away” of the state, decentralisation in Yugoslavia contributed to the consolidation of republican and local political–economic elites. Competition replaced solidarity, federal institutions were increasingly perceived as adversaries, and nationalist mobilisation intensified [42]. By the late 1980s, these dynamics had become irreversible.
Classically, four forms of decentralisation that differ in the extent of authority transferred can be identified: deconcentration and delegation retain ultimate authority at the centre, while devolution grants legally independent local bodies substantial self-governing powers; dispersal involves placing central administrators locally without transferring significant authority or responsibility [63,64]. In the case of Yugoslavia, however, we need to emphasise two types of decentralisation. The first type is ‘health system governance decentralisation’ (devolution) which was reflected, on the one hand, in the very high level of autonomy enjoyed by the Yugoslav republics, provinces and local communities, on the other, in the establishment of SMICs, i.e., decentralisation to the level of a citizen. The second type is governance decentralisation within a healthcare setting (BOALs in the case of Yugoslavia). Health system governance decentralisation, in the sense of transferring greater power to ‘lower’ administrative levels (sub-national and local), has been much more extensively explored in both high-income countries and low- and middle-income countries. However, empirical evidence on whether decentralisation leads to improved health system performance remains inconclusive and controversial [65].
This Yugoslav approach, with SMICs, was not unique. Particularly in Latin America, similar efforts to promote broader participation among society and local communities can be found, for example, in Brazil and Cuba [66,67,68]. However, comparable initiatives have also been documented in other regions [69]. The main challenges associated with health governance decentralisation largely remain the same as those observed in Yugoslavia. Oliveira et al. found that decentralising health policies to municipalities can improve responsiveness and information exchange, but that its effects vary depending on socioeconomic conditions, funding, and implementation [70]. While it may promote equity when resources are distributed fairly, it can also increase costs and widen disparities, particularly disadvantaging municipalities with fewer resources. Devolution can enable local governments to tailor health systems to the needs of their populations, but it also creates differences between jurisdictions, effectively producing ‘mini’ health systems with varying levels of service provision and access [71]. This fragmentation can exacerbate existing inequalities, particularly where jurisdictions have unequal resources, making need-based resource allocation essential for maintaining equity [71].
The other form of decentralisation—within institutions—is much less explored. Even when the decentralisation of institutional governance is considered, it mainly concerns increasing healthcare institutions’ autonomy and providing them with greater direct managerial control [60]. Similarly, in the WHO’s efforts to improve participatory governance, such participation seems to remain limited to public forums and hearings, consultative meetings and discussions, and fixed seats in administrative bodies [5]. There appear to be no efforts to include healthcare workers and other staff within healthcare institutions in decision-making processes beyond purely consultative mechanisms, despite the United Nations General Assembly’s Political Declaration of the High-Level Meeting on Universal Health Coverage recognising the role of health and care workers in participatory and inclusive approaches to health governance [72]. Participatory approaches are mentioned in point 104 of the Declaration’s 109 points. This makes the ‘Yugoslav experiment’ perhaps unique in having involved each employee in decision-making within their institution.
However, this approach was echoed in Muller’s model of participative management in a healthcare organisation [59], in which participatory management is seen as a process involving collaborative decision-making and problem-solving, shared ownership and accountability among all stakeholders in the healthcare system, organisational transformation and empowerment, and effective communication within the healthcare organisation. Muller makes a point that is fully applicable to the ‘Yugoslav experiment’: “The implementation of participative management in a health care organisation poses a tremendous challenge for the health service managers. Change is never effected without difficulties, but the potential for personal, professional and organisational growth is unlimited and very worthwhile” [59].
While early literature largely celebrated Yugoslav reforms, international scholarship grew increasingly critical from the late 1970s onwards. Post-dissolution analyses often shifted towards largely unqualified condemnation. Notably, despite decades of subsequent reform, the institutional foundations of Yugoslav health systems remain largely intact across successor states, and few comparable institutional alternatives have subsequently developed.
The experience of Yugoslavia contributes to the ongoing debates on social participation for health by providing unique evidence of comprehensive social participation at the national (macro), republican and provincial (meso), and local (micro) levels over a period of nearly four decades. It may inform initiatives, including those led by the WHO [5,6], aimed at promoting social participation for health as a prerequisite for sustainable health systems. However, it also offers valuable lessons on the limitations of social participation.
Based on the Yugoslav experience, we may summarise the key lessons for the internationalisation of this unique experience in participatory governance for health:
- Decentralisation within the health system, from the central to the sub-national and local levels: This approach has already been well conceptualised, but ambiguities remain due to tensions between the need for greater participation and the need for greater efficiency [73]. Its success depends on local specificities and adequate support during the transition of power and decision-making authority. A lack of support, including financial support and capacity-building, may lead to failure, which can then be used as an argument against decentralisation and in favour of subsequent re-centralisation [74].
- Decentralisation of institutional governance, giving greater autonomy to health institutions in decision-making: The same limitations as those described for system-level decentralisation apply here [60].
- Decentralisation of governance within a health institution: The aim is to ensure that each employee, including health workers and other staff, participates in decision-making. The Yugoslav experience of BOALs may be further explored as a potential model, together with Muller’s model, which provides practical steps for establishing participatory management in health [59].
- Society and community involvement in health governance: This involvement includes both overall participation in health-system management at the local and other levels (drawing on the Yugoslav experience with SMICs and similar examples from Brazil and other countries), as well as involvement in the management of healthcare institutions, both directly (through participation in decision-making, i.e., within BOAL-equivalent managing bodies) and indirectly (through SMICs-equivalents). It should be noted that this approach would require a strategic shift away from the currently prevalent practice in which “community participation” is understood mainly as the participation of civil society organisations and representatives of the most vulnerable groups and/or patients.
This study has several limitations. The systematic literature review relied on specific search terms, which limited the analysis to studies that included these terms in titles or abstracts; relevant publications may have been missed. Grey literature was not included, which could have provided additional insights. Many studies were published several decades ago, and some were inaccessible due to availability or access restrictions. Finally, this analysis focused on selected aspects of health reform—specifically post-war recovery and self-management—while other aspects were beyond the scope of this study.
5. Conclusions
The Yugoslav experience with social participation for health represents one of the few attempts to reform health care through detatisation, decentralisation, depoliticisation, and democratisation, underpinned by participatory governance and solidarity. Despite structural limitations, the literature documents substantial improvements in population health, particularly during the early phases of reform. However, throughout its existence, the system remained constrained by competing economic priorities rooted in market-oriented development. The unresolved tension between these logics is widely regarded as contributing to the emergence of managerial elites and the gradual erosion of solidarity.
Several analytical lessons can be drawn from this experience. Mechanisms to limit elite capture must be built into reforms from the outset without undermining effective governance. Decentralisation must involve the genuine transfer of decision-making authority, rather than merely redistributing centres of power. Participatory governance should be paired with accountability. Finally, reforms that do not explicitly prioritise solidarity risk reproducing inequitable outcomes. The Yugoslav case therefore remains a grounded reference point for contemporary debates on sustainable social participation for health.
Author Contributions
Conceptualisation, P.D., S.R., J.D.M., D.P. and L.M.; methodology, P.D.; software, P.D., S.R. and J.D.M.; validation, P.D.; formal analysis, P.D.; investigation, P.D., S.R., J.D.M.; resources, P.D. and S.R.; data curation, P.D.; writing—original draft preparation, P.D.; writing—review and editing, P.D., S.R., J.D.M., D.P. and L.M.; visualisation, P.D.; supervision, P.D.; project administration, P.D.; funding acquisition, P.D. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by Provincial Secretariat for Higher Education and Scientific Research, Autonomous Province of Vojvodina, Republic of Serbia, grant number 003897441 2025 09418 003 000 000 001 04 004.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analysed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflicts of interest.
Appendix A
List of publications included in systematic review analysis
- Albrecht, N. Peasant internationalism: Understanding social medicine beyond socialism. Eur. J. Hist. Med. Health 2025, 82(1), 13–42. https://doi.org/10.1163/26667711-bja10053.
- Antić, A. The pedagogy of workers’ self-management: Terror, therapy, and reform communism in Yugoslavia after the Tito–Stalin split. J. Soc. Hist. 2016, 50(1), 179–203. https://doi.org/10.1093/jsh/shw013.
- Bartlett, W.; Božikov, J.; Rechel, B. Health reforms in South East Europe: An introduction. In Health Reforms in South East Europe; Bartlett, W.; Božikov, J.; Rechel, B., Eds.; Palgrave Macmillan: London, UK, 2012; pp. 3–28. https://doi.org/10.1057/9781137264770_1
- Beaven, D.W. Diabetes services in Yugoslavia. Br. Med. J. 1983, 287(6396), 894–895. https://doi.org/10.1136/bmj.287.6396.894.
- Bogdan, B. Cold War entanglements and abortion technology: Writing Yugoslavia into the global history of vacuum aspiration, 1964–1974. Aust. J. Polit. Hist. 2018, 64(3), 407–421. https://doi.org/10.1111/ajph.12486.
- Bogdan, B. Vračare: Village wise women, reproductive health, and Yugoslavia’s early socialist modernisation project. J. Aging Stud. 2023, 64, 101084. https://doi.org/10.1016/j.jaging.2022.101084.
- Brujić, M. In Torlak we (would) trust: Domestic vaccine production in contemporary Serbia. Med. Humanit. 2022, 48(3), e11. https://doi.org/10.1136/medhum-2021-012212.
- De Miguel, J.M. Policies and politics of the health reforms in southern European countries: A sociological critique. Soc. Sci. Med. 1977, 11(6–7), 379–393. https://doi.org/10.1016/0037-7856(77)90101-9.
- Drobnič, S.; Son, K. The welfare state in Yugoslavia and its successor states: The case of family policy. In The Generosity of Social Policies in Socialist and Post-Socialist States: Global Dynamics of Social Policy; Heinrich, A.; Kaminska, M.E.; Pleines, H.; ten Brink, T., Eds.; Springer: Cham, Switzerland, 2025; pp. 93–118. https://doi.org/10.1007/978-3-031-87733-9_5.
- Durlević, Z. Razvoj zdravstvene delatnosti u drugoj Jugoslaviji od 1944. do 1991. godine. Naučni Časopis Urgentne Medicine HALO 194 2013, 19(2), 78–89. (In Serbian).
- Estrin, S. Yugoslavia: The case of self-managing market socialism. J. Econ. Perspect. 1991, 5(4), 187–194. https://doi.org/10.1257/jep.5.4.187
- Grielen, S.J.; Boerma, W.G.W.; Groenewegen, P.P. Unity or diversity? Task profiles of general practitioners in Central and Eastern Europe. Eur. J. Public Health 2000, 10(4), 249–254. https://doi.org/10.1093/eurpub/10.4.249.
- Hill, E.; Jankovic, S. Revitalizing health promotion: A case study from Serbia. Promot. Educ. 2006, 13(4), 243–247. https://doi.org/10.1177/175797590601300403.
- Himmelstein, D.U.; Lang, S.; Woolhandler, S. The Yugoslav health system: Public ownership and local control. J. Public Health Policy 1984, 5(3), 423–431.
- Kessler, H.H. Medicine in Yugoslavia. JAMA 1951, 147(16), 1564–1567. https://doi.org/10.1001/jama.1951.73670330011013.
- Kunitz, S.J. Health care and workers’ self-management in Yugoslavia. Int. J. Health Serv. 1979, 9(3), 521–537. https://doi.org/10.2190/9240-YUX2-VX2H-RU0L.
- Kunitz, S.J. The recruitment, training, and distribution of physicians in Yugoslavia. Int. J. Health Serv. 1980, 10(4), 587–609. https://doi.org/10.2190/0Q25-HLXU-KGRE-2C5N.
- Kunitz, S.J. What Yugoslavia means: Progress, nationalism, and health. Health Transit. Rev. 1996, 6(Suppl.), 253–272.
- Kunitz, S.J. The making and breaking of Yugoslavia and its impact on health. Am. J. Public Health 2004, 94(11), 1894–1904. https://doi.org/10.2105/AJPH.94.11.1894.
- Liotta, P.H. Paradigm lost: Yugoslav self-management and the economics of disaster. Balkanologie 2001, 5(1–2). https://doi.org/10.4000/balkanologie.681.
- Mastilica, M. Health and social inequities in Yugoslavia. Soc. Sci. Med. 1990, 31(3), 405–412. https://doi.org/10.1016/0277-9536(90)90287-3.
- Milanović, V. Humanism and medicine. Soc. Sci. Med. 1987, 25(1), 35–41. https://doi.org/10.1016/0277-9536(87)90201-2.
- Milenkovitch, D.D. The case of Yugoslavia. Am. Econ. Rev. 1977, 67(1), 55–60.
- Mowlem, R. Medicine in Yugoslavia. Br. Med. J. 1950, 1(4661), 1072–1073.
- Novosel, M.; Kohn, R. Physician and society: A study of people’s perception of the social role of physicians in a region of Yugoslavia. Soc. Sci. Med. 1979, 13, 73–80. https://doi.org/10.1016/0271-7123(79)90010-5.
- Parmelee, D.E. Whither the state in Yugoslav health care? Soc. Sci. Med. 1985, 21(7), 719–728. https://doi.org/10.1016/0277-9536(85)90116-9.
- Parmelee, D.E.; Henderson, G.; Cohen, M.S. Medicine under socialism: Some observations on Yugoslavia and China. Soc. Sci. Med. 1982, 16(15), 1389–1396. https://doi.org/10.1016/0277-9536(82)90133-2.
- Popić, T.; Perišić, N. Former Yugoslavia. In Health Politics in Europe: A Handbook; Immergut, E.M.; Anderson, K.M.; Devitt, C.; Popić, T., Eds.; Oxford University Press: Oxford, UK, 2021; pp. 901–907. https://doi.org/10.1093/oso/9780198860525.003.0040.
- Popić, T. Slovenia. In Health Reforms in Post-Communist Eastern Europe; Popić, T., Ed.; Springer: Cham, Switzerland, 2023; pp. 59–104. https://doi.org/10.1007/978-3-031-15497-3_3.
- Romano, J. Pukovnik pregled lekara, farmaceuta, studenata medicine i farmacije učesnika NOR-a i poginulih u ratu, učešće i doprinos bolničarki u NOV i POJ 1941–1945. In Sanitetska služba u Narodnooslobodilačkom ratu 1941–1945, Vol. IV; Vojnoizdavački i novinski centar: Beograd, Serbia, 1989. (In Serbian).
- Sarić, M.; Rodwin, V.G. The once and future health system in the former Yugoslavia: Myths and realities. J. Public Health Policy 1993, 14(2), 220–237. https://doi.org/10.2307/3342966.
- Savelli, M. Peace and happiness await us: Psychotherapy in Yugoslavia, 1945–1985. Hist. Hum. Sci. 2018, 31(4), 38–57. https://doi.org/10.1177/0952695118773951.
- Savelli, M. Socialism, society, and the struggle against mental illness: Preventative psychiatry in post-war Yugoslavia. In Preventing Mental Illness: Mental Health in Historical Perspective; Kritsotaki, D.; Long, V.; Smith, M., Eds.; Springer: Cham, Switzerland, 2019; pp. 131–150. https://doi.org/10.1007/978-3-319-98699-9_6.
- Savelli, M. The afterlives of mental hygiene: Psychiatrizing society in socialist Yugoslavia. Soc. Hist. Med. 2024, 37(2), 364–386. https://doi.org/10.1093/shm/hkac067.
- Simić, I. The curious case of Aleksandar Milivojević: The Donja Toponica Hospital and mental health in socialist Yugoslavia. Soc. Hist. Med. 2020, 33(4), 1350–1362. https://doi.org/10.1093/shm/hkz033.
- Simić, S.; Santrić Milićević, M.; Matejić, B.; Marinković, J.; Adams, O. Do we have primary health care reform? The story of the Republic of Serbia. Health Policy 2010, 96, 160–169. https://doi.org/10.1016/j.healthpol.2010.01.015.
- Švab, I. Primary health care reform in Slovenia: First results. Soc. Sci. Med. 1995, 41(1), 141–144. https://doi.org/10.1016/0277-9536(94)00323-L.
- Spasenoska, D. Dynamics of life expectancy change during the transition to democracy in the ex-Yugoslav countries. Espace Popul. Soc. 2022, 2-3. https://doi.org/10.4000/eps.12945.
- Vukmanović, C. Decentralized socialism: Medical care in Yugoslavia. Int. J. Health Serv. 1972, 2(1), 35–44. https://doi.org/10.2190/Q611-5JHT-6691-N1CU.
- Zrinščak, S. Zdravstvena politika Hrvatske: U vrtlogu reformi i suvremenih društvenih izazova. Rev. Soc. Polit. 2007, 14(2), 193–220. (In Croatian). https://doi.org/10.3935/rsp.v14i2.697.
Appendix B
List of publications excluded from the analysis (not retrieved or do not meet the inclusion criteria)
- Belson, D.L. Self-managed health care in Yugoslavia. Health Care Manage Rev. 1977, 2(1), 71–75. https://doi.org/10.1097/00004010-197700210-00012.
- Bjegovic-Mikanovic, V.; Vukovic, D.; Terzic-Supic, Z.; Santric-Milicevic, M.S.; Laaser, U. Strategic orientation of public health in transition: An overview of South Eastern Europe. J. Public Health Policy 2007, 28(1), 94–101. https://doi.org/10.1057/palgrave.jphp.3200121.
- Blaskovich, J.N. Organizational structure of American medical practice: Health care crisis and reform. Croat. Med. J. 1994, 35(3), 137–142.
- Boerma, W.G.W. Profiles of General Practice in Europe: An International Study of Variation in the Tasks of General Practitioners. Doctoral Thesis, Maastricht University, Maastricht, The Netherlands, 17 September 2003. https://doi.org/10.26481/dis.20030917wb
- Bojanin, S. A mental hygienic approach to adolescent age (Serbocroatian). Anali Zavoda za mentalno zdravlje 1973, 5(4), 105–116.
- Bundy, A.M. There Was a Man of UNRRA: Internationalism, Humanitarianism, and the Early Cold War in Europe, 1943–1947. Doctoral Thesis, The Ohio State University, Columbus, OH, USA, 2017. Available online: https://etd.ohiolink.edu/acprod/odb_etd/ws/send_file/send?accession=osu1492608585636304&disposition=inline (accessed on 20 January 2026).
- Cesen, M.; Drnovsek, VM. The process of health legislation reform in the Republic of Slovenia. Eur. J. Health Law 2000, 7(1), 73–84. https://doi.org/10.1163/15718090020523061.
- Clark, C. Government spending, policy outputs, and policy outcomes: Health policy in Yugoslavia. Environ. Plann. C Gov. Policy 1990, 8(2), 123–138. https://doi.org/10.1068/c080123
- Čatić, T.; Tabakovic, V.; Vuk, S.M.; Bejtovic, H.; Kopanja, D.; Samardzic, D.; Skrbo, A.; Mačić, I. Historical developments of Bosnia and Herzegovina pharmaceutical industry—The past and the future perspectives of domestic manufacturing. Mater. Sociomed. 2022, 34(3), 228–235. https://doi.org/10.5455/msm.2022.34.228-235.
- Čavoški, J. And after Tito… no one. Yugoslavia and the crisis of the Non-Aligned Movement during the early 1980s. Istorija 20. Veka 2024, 42(1), 233–256. https://doi.org/10.29362/ist20veka.2024.1.cav.233-256.
- Dugac, Ž. Croatian Medical Association, Andrija Štampar and public health politics in the Kingdom of Serbs, Croats and Slovenians (Kingdom of Yugoslavia). Liječnički Vjesnik 2005, 127(5-6), 151–157.
- Dugac, Ž. Building an original and internationally standardized public health system in the Kingdom of Yugoslavia. Acta Historica Medicinae, Stomatologiae, Pharmaciae, Medicinae Veterinariae 2024, 43(1), 51–64. https://doi.org/10.5937/acthist43-52883.
- Dugački, V.; Regan, K. Povijest zdravstvene skrbi i razvoja zdravstvenih ustanova na hrvatskom prostoru. Studia Lexicographica 2019, 13(25), 35–74. https://doi.org/10.33604/sl.13.25.2.
- Echols, J.M. Racial and ethnic inequality: The comparative impact of socialism. Comp. Polit. Stud. 1981, 13(4), 403–444. https://doi.org/10.1177/001041408101300403.
- Ensor, T.; Thompson, R. Health insurance as a catalyst to change in former communist countries? Health Policy 1998, 43(3), 203–218. https://doi.org/10.1016/s0168-8510(97)00098-5
- Ferhadbegović, S. Past and Present Health Crises: How Yugoslavia Managed the Smallpox Epidemic of 1972. Cultures of History Forum 2020. Available online: https://www.cultures-of-history.uni-jena.de/focus/kleio-in-pandemia/past-and-present-health-crises-how-yugoslavia-managed-the-smallpox-epidemic-of-1972/ (accessed on 19 January 2026)
- Gajić-Stevanović, M.; Stevanović, I. Overview of changes in the health sector and its financing in the Republic of Serbia in the period 2004–2020. Serbian Dental Journal 2023, 70(2), 93–101. https://doi.org/10.2298/SGS2302095G.
- Geisthövel, A. Exploring state socialist governmentality: Eastern European examples from medicine and health care. Hist. Human Sci. 2026, 39(2), 3–20. https://doi.org/10.1177/09526951251385887.
- Healy, J.; McKee, M. Implementing hospital reform in central and eastern Europe. Health Policy 2002, 61(1), 1–19. https://doi.org/10.1016/s0168-8510(01)00213-5
- Ibrahim, KM.; Yassin, K.M.; Khan, S.; Laaser, U. Decline in the child health indicators: Assessing the impact of war in five South-Eastern European countries. Period. Biol. 2003, 105(1), 37–43.
- Iacob, B.C. Malariology and decolonization: Eastern European experts from the League of Nations to the World Health Organization. J. Glob. Hist. 2022, 17(2), 233–253. https://doi.org/10.1017/S1740022822000067.
- Jakovljevic, M.M.; Arsenijevic, J.; Pavlova, M.; Verhaeghe, N.; Laaser, U.; Groot, W. Within the triangle of healthcare legacies: Comparing the performance of South-Eastern European health systems. J. Med. Econ. 2017, 20(5), 483–492. https://doi.org/10.1080/13696998.2016.1277228.
- Jakovljevic, M. Resource allocation strategies in Southeastern European health policy. Eur. J. Health Econ. 2013, 14(2), 153–159. https://doi.org/10.1007/s10198-012-0439-y.
- Karge, H. Transnational knowledge into Yugoslav practices? The legacy of the Second World War on social welfare policy in Yugoslavia. Comparativ 2010, 20(5), 75–86.
- Klančar, D.; Švab, I. Primary care principles and community health centers in the countries of former Yugoslavia. Health Policy 2014, 118(2), 166–172. https://doi.org/10.1016/j.healthpol.2014.08.014.
- Klančar, D. Primary Health Care Organisation in the Countries in the Area of Yugoslavia.Doctoral dissertation, University of Ljubljana, Ljubljana, Slovenia, 2021. (In Slovenian)
- Komadina, D. Integration of consumers and providers of health services. World Hosp. 1976, 12(1), 40–43.
- Kostić, M.; Vuković, D. Regression of hard-won advances in socialized medicine: The emergence of the private sector in health care in Serbia. Health Hum. Rights. 2025, 27(2), 229–242.
- Kronja, T. Ethical problems of health and health workers. Liječnički Vjesnik 1969, 91(6), 581–588.
- Kutzin, J.; Jakab, M.; Cashin, C. Lessons from health financing reform in central and eastern Europe and the former Soviet Union. Health Econ. Policy Law 2010, 5, 135–147. https://doi.org/10.1017/S1744133110000010.
- Mardesić D, Gjurić G, Jezerinac Z. Sistematsko traganje za nasljednim metaboličkim bolestima u svijetu i u nas [Screening for inborn errors of metabolism in the newborn population abroad and in our country (author’s transl)]. Lijec Vjesn. 1979, 101(12):746–750.
- McCarthy, M. Serbia rebuilds and reforms its health-care system. The Lancet 2007, 369(9559), 360. https://doi.org/10.1016/S0140-6736(07)60173-1.
- Miller, N. Return engagement: Intellectuals and nationalism in Tito’s Yugoslavia. In State Collapse in South-Eastern Europe: New Perspectives on Yugoslavia’s Disintegration; Cohen, L.J., Dragović-Soso, J., Eds.; Purdue University Press: West Lafayette, IN, USA, 2008; pp. 179–200.
- Miller, R.F. Social, economic and political dilemmas of reform in Yugoslavia. Politics 1989, 24(1), 92–107. https://doi.org/10.1080/00323268908402081.
- Mladenović, D.; Simić, S. All Health Care System Reforms in Former and Present Yugoslavia. In Osnove za reformu sistema zdravstvene zaštite u Republici Srbiji; Centar za proučavanje alternativa: Beograd, Serbia, 2001; pp. 33–45.
- Nikolic, B. Historical and modern development of healthcare in Čazma. Radovi Zavoda za Znanstvenoistraživački i Umjetnički Rad u Bjelovaru 2019, 13, 107–114. https://doi.org/10.21857/MNLQGC036Y.
- Nolimal, D. Some reflections on alcohol public policy in Yugoslavia. Socijalna Psihijatrija 1989, 17(1), 67–82.
- Orešković, S. Health system reorganization in Croatia in the light of major reform tendencies in OECD countries. Croat. Med. J. 1995, 36(1), 47–54.
- Ovseiko, P.V. The Politics of Health Care Reform in Central and Eastern Europe: The Case of the Czech Republic. Doctoral Thesis, University of Oxford, Oxford, UK, 2009. https://doi.org/10.5287/ora-nb98kn0p4.
- Parmelee, D.E. Yugoslavia: Health Care under Self-Managing Socialism. In Success and Crisis in National Health Systems: A Comparative Approach; Field, M.G., Ed.; Routledge: New York, NY, USA, London, UK, 1989; pp. 165–191.
- Pavlínek, P.; Pickles, J. Part II: Nature, risk and the legacies of state socialism. In Environmental Transitions: Transformation and Ecological Defense in Central and Eastern Europe; Routledge: London/New York, 2000; pp. 37–154.
- Pašić, N. The political articulation and aggregation of plural interests in self-management systems. Wilson Center Fellowship Report, 1986.
- Skubic Ermenc, K.; Bembič, B. Slovenia: Segmentation and Sectoral Disparities. In Skill Formation in Central and Eastern Europe: A Search for Patterns and Directions of Development; Tūtlys, V., Markowitsch, J., Pavlin, S., Winterton, J., Eds.; Peter Lang: Berlin, Germany, 2022; pp. 243–264.
- Perlmutter, F.D. Citizen participation in Yugoslavia. Social Work 1974, 19(2), 226–232. https://doi.org/10.1093/sw/19.2.226.
- Popovic, B.; Skribic, M.; Kohn, R. Yugoslavia’s autonomous health institutions. Their role within the constitutional and sociopolitical framework in the Republic of Croatia. International Journal of Health Services 1973, 3(2), 213–221. https://doi.org/10.2190/BPBP-4KED-TW3H-F7P4.
- Prica, V.P. The response of Yugoslav architects on the health challenges and crisis 1918–1941. Istorija 20. Veka 2023, 41(1), 45–66. https://doi.org/10.29362/ist20veka.2023.1.put.45-66.
- Radovanović, M. Desirable ways of reforming the health care system in Yugoslavia. Med. Pregl. 1994, 47(3-4), 77–78.
- Rajić, Z.; Gorski, B. Zagreb hospitals at a turning point: A comprehensive analysis and reorganization proposals with a key role for the University Hospital in Novi Zagreb Croat. Med. J. 1994, 35(4), 203–213.
- Rechel, B.; McKee, M. Health reform in central and eastern Europe and the former Soviet Union. The Lancet 2009, 374, 1186–1195. https://doi.org/10.1016/S0140-6736(09)61334-9
- Rusinow, D. Understanding the Yugoslav reforms. The World Today 1967, 23(2), 71–79.
- Souliotis, K.; Economou, C.; Tountas, Y. Health care reforms in the ex-socialist South-Eastern European countries. J. Soc. Soc. Policy 2005, 4(1), 63–76.
- Spasić, I. Yugoslavia as a place for living a normal life: Memories of ordinary people in Serbia. Sociologija 2012, 54(4), 577–594. https://doi.org/10.2298/SOC1204577S.
- Spaskovska, L. Constructing the “City of International Solidarity”: Non-Aligned internationalism, the United Nations and visions of development, modernism and solidarity, 1955–1975. Journal of World History 2020, 31(1), 137–164.
- Stanimirović, N. (2021). Self-managing the brotherhood and unity: Understanding Tito’s approach to nationalism.Master’s thesis, Budapest, Hungary, Central European University.
- Stojanović, R. The sources of contradiction in self-managing socialism. Zbornik Radova 1989, 23(1–3), 125–131.
- Tavanxhi, N.; Burazeri, G.; Laaser, U. Southeastern Europe, health systems of. In International Encyclopedia of Public Health; Heggenhougen, H.K., Ed.; Academic Press: Oxford, UK, 2008; pp. 137–147. https://doi.org/10.1016/B978-012373960-5.00308-7.
- Toth, M. Group practice in Yugoslavia. International Dental Journal 1986, 36(2), 102–105.
- Uvalić, M. The rise and fall of market socialism in Yugoslavia. 2019.
- Vlahović, Z.; Radojković, D. Healthcare in Serbia in transition period. EPMA J. 2010, 1(4), 601–606. https://doi.org/10.1007/s13167-010-0055-9.
- Živković, M.; Bjegović, V.; Simić, S.; Marinković, J. Laboratory testing in primary health care in Belgrade. International Journal for Quality in Health Care 1994, 6(1), 97–102. https://doi.org/10.1093/intqhc/6.1.97.
Appendix C
Table A1.
Characteristics of included publications (n = 40).
Appendix D
Table A2.
PRISMA Checklist.
References
- Rechel, B.; McKee, M. Health reform in central and eastern Europe and the former Soviet Union. Lancet 2009, 374, 1186–1195. [Google Scholar] [CrossRef] [Scilit]
- Campbell Page, E. (Ed.) Supporting Health Reform in Eastern Europe; OED Precis No. 223; World Bank: Washington, DC, USA, 2002; Available online: http://documents.worldbank.org/curated/en/514921468770969786 (accessed on 7 July 2026).
- Kaminska, M.E.; Druga, E.; Stupele, L.; Malinar, A. Changing the healthcare financing paradigm: Domestic actors and international organizations in the agenda setting for diffusion of social health insurance in post-communist Central and Eastern Europe. Soc. Policy Adm. 2021, 55, 1066–1081. [Google Scholar] [CrossRef] [Scilit]
- Schmets, G.; Rajan, D.; Kadandale, S. (Eds.) Strate Gizing National Health in the 21st Century: A Handbook; World Health Organization: Geneva, Switzerland, 2016; Available online: https://www.who.int/publications/i/item/9789241549745 (accessed on 4 August 2026).
- World Health Organization. Social Participation for Universal Health Coverage: Technical Paper; World Health Organization: Geneva, Switzerland, 2023; Available online: https://www.who.int/publications/i/item/9789240085923 (accessed on 4 August 2026).
- World Health Organization. Voice, Agency, Empowerment—Handbook on Social Participation for Universal Health Coverage; World Health Organization: Geneva, Switzerland, 2021; Available online: https://iris.who.int/server/api/core/bitstreams/f7980b68-6ce9-4091-b7e2-b32ebafdecea/content (accessed on 5 August 2026).
- Esposto, E.; Moini, G. Participatory governance and healthcare. Opportunities and perils. In Urban Health. AIMETA 2019; Green Energy and Technology; Battisti, A., Marceca, M., Iorio, S., Eds.; Springer: Cham, Switzerland, 2020; pp. 9–18. [Google Scholar] [CrossRef] [Scilit]
- Mayka, L. The origins of strong institutional design: Policy reform and participatory institutions in Brazil’s health sector. Comp. Politics 2019, 51, 275–294. [Google Scholar] [CrossRef] [Scilit]
- Marshall, A.I.; Kantamaturapoj, K.; Kiewnin, K.; Chotchoungchatchai, S.; Patcharanarumol, W.; Tangcharoensathien, V. Participatory and responsive governance in universal health coverage: An analysis of legislative provisions in Thailand. BMJ Glob. Health 2021, 6, e004117. [Google Scholar] [CrossRef] [Scilit]
- Oh, J.; Ko, Y.; Alley, A.B.; Kwon, S. Participation of the lay public in decision-making for benefit coverage of national health insurance in South Korea. Health Syst. Reform. 2015, 1, 62–71. [Google Scholar] [CrossRef] [Scilit]
- Rusinow, D. The Yugoslav Experiment 1948–1974; University of California Press: Berkeley, CA, USA; Los Angeles, CA, USA, 1977. [Google Scholar]
- Vukmanović, C. Decentralized socialism: Medical care in Yugoslavia. Int. J. Health Serv. 1972, 2, 35–44. [Google Scholar] [CrossRef] [Scilit]
- De Miguel, J.M. Policies and politics of the health reforms in southern European countries: A sociological critique. Soc. Sci. Med. 1977, 11, 379–393. [Google Scholar] [CrossRef] [Scilit]
- Milenkovitch, D. The case of Yugoslavia. Am. Econ. Rev. 1977, 67, 55–60. [Google Scholar] [CrossRef] [Scilit]
- Kunitz, S.J. Health care and workers’ self-management in Yugoslavia. Int. J. Health Serv. 1979, 9, 521–537. [Google Scholar] [CrossRef] [Scilit]
- Parmelee, D.E. Whither the state in Yugoslav health care? Soc. Sci. Med. 1985, 21, 719–728. [Google Scholar] [CrossRef] [Scilit]
- Drobnič, S.; Son, K. The welfare state in Yugoslavia and its successor states: The case of family policy. In The Generosity of Social Policies in Socialist and Post-Socialist States: Global Dynamics of Social Policy; Heinrich, A., Kaminska, M.E., Pleines, H., ten Brink, T., Eds.; Springer: Cham, Switzerland, 2025; pp. 93–118. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Mencinger, J. The Yugoslav Economic Systems and Their Efficiency. Econ. Anal. Work. Manag. 1986, 20, 31–43. [Google Scholar]
- Mencinger, J. The Yugoslav Economy Systemic Changes, 1945–1986. Carl Beck Pap. Russ. East Eur. Stud. 1989, 707, 1–32. [Google Scholar] [CrossRef] [Scilit]
- Romano, J. Pregled lekara, farmaceuta, studenata medicine i farmacije učesnika NOR-a i poginulih u ratu, učešće i doprinos bolničarki u NOV i POJ 1941–1945. In Sanitetska Služba u Narodnooslobodilačkom Ratu 1941–1945; Vojnoizdavački i Novinski Centar: Beograd, Serbia, 1989; Volume IV. (In Serbian) [Google Scholar]
- Antić, A. The pedagogy of workers’ self-management: Terror, therapy, and reform communism in Yugoslavia after the Tito–Stalin split. J. Soc. Hist. 2016, 50, 179–203. [Google Scholar] [CrossRef] [Scilit]
- Savelli, M. Peace and happiness await us: Psychotherapy in Yugoslavia, 1945–1985. Hist. Hum. Sci. 2018, 31, 38–57. [Google Scholar] [CrossRef] [Scilit]
- Bogdan, B. Cold War entanglements and abortion technology: Writing Yugoslavia into the global history of vacuum aspiration, 1964–1974. Aust. J. Politics Hist. 2018, 64, 407–421. [Google Scholar] [CrossRef] [Scilit]
- Popić, T. Slovenia. In Health Reforms in Post-Communist Eastern Europe; Springer: Cham, Switzerland, 2023; pp. 59–104. [Google Scholar] [CrossRef] [Scilit]
- Kessler, H.H. Medicine in Yugoslavia. JAMA 1951, 147, 1564–1567. [Google Scholar] [CrossRef] [Scilit]
- Albrecht, N. Peasant internationalism: Understanding social medicine beyond socialism. Eur. J. Hist. Med. Health 2025, 82, 13–42. [Google Scholar] [CrossRef] [Scilit]
- Zrinščak, S. Zdravstvena politika Hrvatske: U vrtlogu reformi i suvremenih društvenih izazova. Rev. Soc. Polit. 2007, 14, 193–220. (In Croatian) [Google Scholar] [CrossRef] [Scilit]
- Mowlem, R. Medicine in Yugoslavia. Br. Med. J. 1950, 1, 1072–1073. [Google Scholar] [CrossRef] [Scilit]
- Bogdan, B. Vračare: Village wise women, reproductive health, and Yugoslavia’s early socialist modernisation project. J. Aging Stud. 2023, 64, 101084. [Google Scholar] [CrossRef] [Scilit]
- Savelli, M. Socialism, society, and the struggle against mental illness: Preventative psychiatry in post-war Yugoslavia. In Preventing Mental Illness; Kritsotaki, D., Long, V., Smith, M., Eds.; Springer: Cham, Switzerland, 2019; pp. 131–150. [Google Scholar] [CrossRef] [Scilit]
- Estrin, S. Yugoslavia: The case of self-managing market socialism. J. Econ. Perspect. 1991, 5, 187–194. [Google Scholar] [CrossRef] [Scilit]
- Durlević, Z. Razvoj zdravstvene delatnosti u drugoj Jugoslaviji od 1944. do 1991. godine. Naučni Časopis Urgent. Med. HALO 194 2013, 19, 78–89. (In Serbian) [Google Scholar]
- Bartlett, W.; Božikov, J.; Rechel, B. (Eds.) Health reforms in South-East Europe: An introduction. In Health Reforms in South-East Europe; Palgrave Macmillan: London, UK, 2012; pp. 3–28. [Google Scholar] [CrossRef] [Scilit]
- Popić, T.; Perišić, N. Former Yugoslavia. In Health Politics in Europe: A Handbook; Immergut, E.M., Anderson, K.M., Devitt, C., Popić, T., Eds.; Oxford University Press: Oxford, UK, 2021; pp. 901–907. [Google Scholar] [CrossRef] [Scilit]
- Švab, I. Primary health care reform in Slovenia: First results. Soc. Sci. Med. 1995, 41, 141–144. [Google Scholar] [CrossRef] [Scilit]
- Grielen, S.J.; Boerma, W.G.W.; Groenewegen, P.P. Unity or diversity? Task profiles of general practitioners in Central and Eastern Europe. Eur. J. Public Health 2000, 10, 249–254. [Google Scholar] [CrossRef] [Scilit]
- Parmelee, D.E.; Henderson, G.; Cohen, M.S. Medicine under socialism: Some observations on Yugoslavia and China. Soc. Sci. Med. 1982, 16, 1389–1396. [Google Scholar] [CrossRef] [Scilit]
- Hill, E.; Jankovic, S. Revitalizing health promotion: A case study from Serbia. Promot. Educ. 2006, 13, 243–247. [Google Scholar] [CrossRef] [Scilit]
- Himmelstein, D.U.; Lang, S.; Woolhandler, S. The Yugoslav health system: Public ownership and local control. J. Public Health Policy 1984, 5, 423–431. [Google Scholar] [CrossRef] [Scilit]
- Savelli, M. The afterlives of mental hygiene: Psychiatrizing society in socialist Yugoslavia. Soc. Hist. Med. 2024, 37, 364–386. [Google Scholar] [CrossRef] [Scilit]
- Kunitz, S.J. What Yugoslavia means: Progress, nationalism, and health. Health Transit. Rev. 1996, 6, 253–272. [Google Scholar]
- Spasenoska, D. Dynamics of life expectancy change during the transition to democracy in the ex-Yugoslav countries. Espace Popul. Soc. 2022, 2–3. [Google Scholar] [CrossRef] [Scilit]
- Sarić, M.; Rodwin, V.G. The once and future health system in the former Yugoslavia: Myths and realities. J. Public Health Policy 1993, 14, 220–237. [Google Scholar] [CrossRef] [Scilit]
- Brujić, M. In Torlak we (would) trust: Domestic vaccine production in contemporary Serbia. Med. Humanit. 2022, 48, e11. [Google Scholar] [CrossRef] [Scilit]
- Kunitz, S.J. The recruitment, training, and distribution of physicians in Yugoslavia. Int. J. Health Serv. 1980, 10, 587–609. [Google Scholar] [CrossRef] [Scilit]
- Beaven, D.W. Diabetes services in Yugoslavia. Br. Med. J. 1983, 287, 894–895. [Google Scholar] [CrossRef] [Scilit][Green Version]
- Simić, S.; Santrić Milićević, M.; Matejić, B.; Marinkovic, J.; Adams, O. Do we have primary health care reform? The story of the Republic of Serbia. Health Policy 2010, 96, 160–169. [Google Scholar] [CrossRef] [Scilit]
- Simić, I. The curious case of Aleksandar Milivojević: The Donja Toponica Hospital and mental health in socialist Yugoslavia. Soc. Hist. Med. 2020, 33, 1350–1362. [Google Scholar] [CrossRef] [Scilit]
- Novosel, M.; Kohn, R. Physician and society: A study of people’s perception of the social role of physicians in a region of Yugoslavia. Soc. Sci. Med. 1979, 13, 73–80. [Google Scholar] [CrossRef] [Scilit]
- Liotta, P.H. Paradigm lost: Yugoslav self-management and the economics of disaster. Balkanologie 2001, 5. [Google Scholar] [CrossRef] [Scilit]
- Mastilica, M. Health and social inequities in Yugoslavia. Soc. Sci. Med. 1990, 31, 405–412. [Google Scholar] [CrossRef] [Scilit]
- Chuong, K.H.; O’Doherty, K.C. Participatory governance in health research: Patients and publics as stewards of health research systems. In The Cambridge Handbook of Health Research Regulation; Laurie, G., Dove, E., Ganguli-Mitra, A., McMillan, C., Postan, E., Sethi, N., Sorbie, A., Eds.; Cambridge University Press: Cambridge, UK, 2021; pp. 121–129. [Google Scholar] [CrossRef] [Scilit]
- Gupta, P.; Rouffy-Ly, B.; Rohrer-Herold, K.; Koch, K.; Rao, N.; Poulussen, C.; Brearley, L.; Abou-Taleb, H.; Rajan, D. Assessing the interactions of people and policy-makers in social participation for health: An inventory of participatory governance measures from a rapid systematic literature review. Int. J. Equity Health 2023, 22, 240. [Google Scholar] [CrossRef] [Scilit]
- Galea, S.; Kruk, M.E. Forty years after Alma-Ata: At the intersection of primary care and population health. Milbank Q. 2019, 97, 383–386. [Google Scholar] [CrossRef] [Scilit]
- Nikoliš, G. Uvod. Sanitetska Služba u Narodnooslovodilačkom Ratu Jugoslavije 1941–1945; Vojnoizdavački i Vojni Centar: Belgrade, Serbia, 1989; Volume I, (In Serbo-Croatian). [Google Scholar]
- Kunitz, S.J. The making and breaking of Yugoslavia and its impact on health. Am. J. Public Health 2004, 94, 1894–1904. [Google Scholar] [CrossRef] [Scilit]
- Milanović, V. Humanism and medicine. Soc. Sci. Med. 1987, 25, 35–41. [Google Scholar] [CrossRef] [Scilit]
- Muller, M. Participative management in health care services. Curationis 1995, 18, 15–21. [Google Scholar] [CrossRef] [Scilit]
- Rechel, B.; Duran, A.; Saltman, R. What Is the Experience of Decentralized Hospital Governance in Europe? 10 Case Studies from Western Europe on Institutional and Accountability Arrangements; European Observatory on Health Systems and Policies: Copenhagen, Denmark, 2018; Available online: https://iris.who.int/server/api/core/bitstreams/15ae69c4-6823-4554-bf70-b37aa8edec84/content (accessed on 27 August 2026).
- Atuire, C.; Spasenoska, D.; Natukunda, J.; Orth, Z.; Giri, A.; Afful, A.; Akintola, S.; Andrews, D.; Arguedas Ramírez, G.; Asamoaning, A.; et al. Solidarity is essential in a more transactional global health era. Nat. Health 2026. [Google Scholar] [CrossRef] [Scilit]
- Tong, S.; Samet, J.M.; Steffen, W.; Kinney, P.L.; Frumkin, H. Solidarity for the Anthropocene. Environ. Res. 2023, 235, 116716. [Google Scholar] [CrossRef] [Scilit]
- Mills, A.; Vaughan, J.P.; Smith, D.L.; Tabibzadeh, I.; World Health Organization. Health System Decentralization: Concepts, Issues and Country Experience; World Health Organization: Geneva, Switzerland, 1990; Available online: https://iris.who.int/handle/10665/39053 (accessed on 6 August 2026).
- Farid Uddin, K. Decentralization and governance. In Global Encyclopedia of Public Administration, Public Policy, and Governance; Farazmand, A., Ed.; Springer: Cham, Switzerland, 2018; pp. 2955–2961. [Google Scholar] [CrossRef] [Scilit]
- Mahmood, S.; Sequeira, R.; Siddiqui, M.M.U.; Herkenhoff, M.B.A.; Ferreira, P.P.; Fernandes, A.C.; Sousa, P. Decentralization of the health system—Experiences from Pakistan, Portugal and Brazil. Health Res. Policy Syst. 2024, 22, 61. [Google Scholar] [CrossRef] [Scilit]
- Engstrom, E.M.; Silva, V.C. Participative management in Primary Health Care: An essay on an experience in a vulnerable urban territory. Saúde Debate 2022, 46, 120–130. [Google Scholar] [CrossRef] [Scilit]
- Soares, C.S.A.; Neto, J.E.B.; da Silva, A.C.F. Public health systems in Brazil and Portugal: Organization and challenges. In International Conference on Information Systems and Medicine, ICISMED 2025; Gal-dames, I.S., Vázquez-Justo, E., Abreu, A., Carvalho, J.V., Eds.; Springer: Cham, Switzerland, 2026; Volume 2. [Google Scholar] [CrossRef] [Scilit]
- Matta, S.; Bishai, D.; Más Bermejo, P. Cuba’s progress on primary health care since the Alma-Ata Conference. In Achieving Health for All: Primary Health Care in Action; Schleiff, M., Bishai, D., Eds.; Johns Hopkins University Press: Baltimore, MD, USA, 2020; pp. 298–318. Available online: https://muse.jhu.edu/pub/1/oa_edited_volume/chapter/2715642 (accessed on 6 August 2026).
- Ben Mesmia, H.; Rajan, D.; Bouhafa Chtioui, R.; Koch, K.; Jaouadi, I.; Aboutaleb, H.; De Courcelles, S.; Atmani, L.; Pujos, B.; Mtiraoui, A. The Tunisian Experience of Participatory Health Governance: The Societal Dialogue for Health (A Qualitative Study). Health Res. Policy Syst. 2023, 21, 84. [Google Scholar] [CrossRef] [Scilit]
- Oliveira, R.; Santinha, G.; Sá Marques, T. The impacts of health decentralization on equity, efficiency, and effectiveness: A scoping review. Sustainability 2024, 16, 386. [Google Scholar] [CrossRef] [Scilit]
- Sapkota, S.; Dhakal, A.; Rushton, S.; van Teijlingen, E.; Marahatta, S.B.; Balen, J.; Lee, A.C. The impact of decentralisation on health systems: A systematic review of reviews. BMJ Glob. Health 2023, 8, e013317. [Google Scholar] [CrossRef] [Scilit]
- United Nations General Assembly. Political Declaration of the High-Level Meeting on Universal Health Coverage: Universal Health Coverage: Expanding our Ambition for Health and Well-Being in a Post-COVID World; Resolution A/RES/78/4; United Nations: New York, NY, USA, 2023; Available online: https://docs.un.org/en/A/RES/78/4 (accessed on 27 August 2026).
- Nelson, M.A. Decentralization and trust: Institutional design for effective governance. Int. Tax Public Financ. 2026. [Google Scholar] [CrossRef] [Scilit]
- Duric, P. From Optimization to Decentralization of Healthcare. Peoples Dispatch, 18 November 2022. Available online: https://peoplesdispatch.org/2022/11/18/from-optimization-to-decentralization-of-healthcare/ (accessed on 27 August 2026).
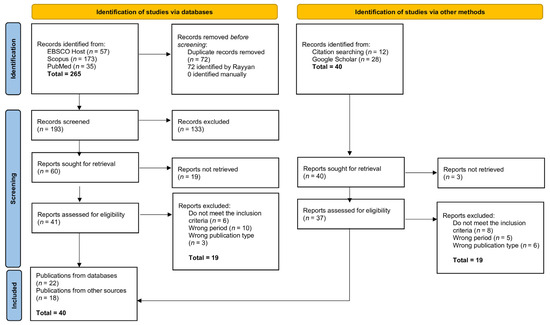
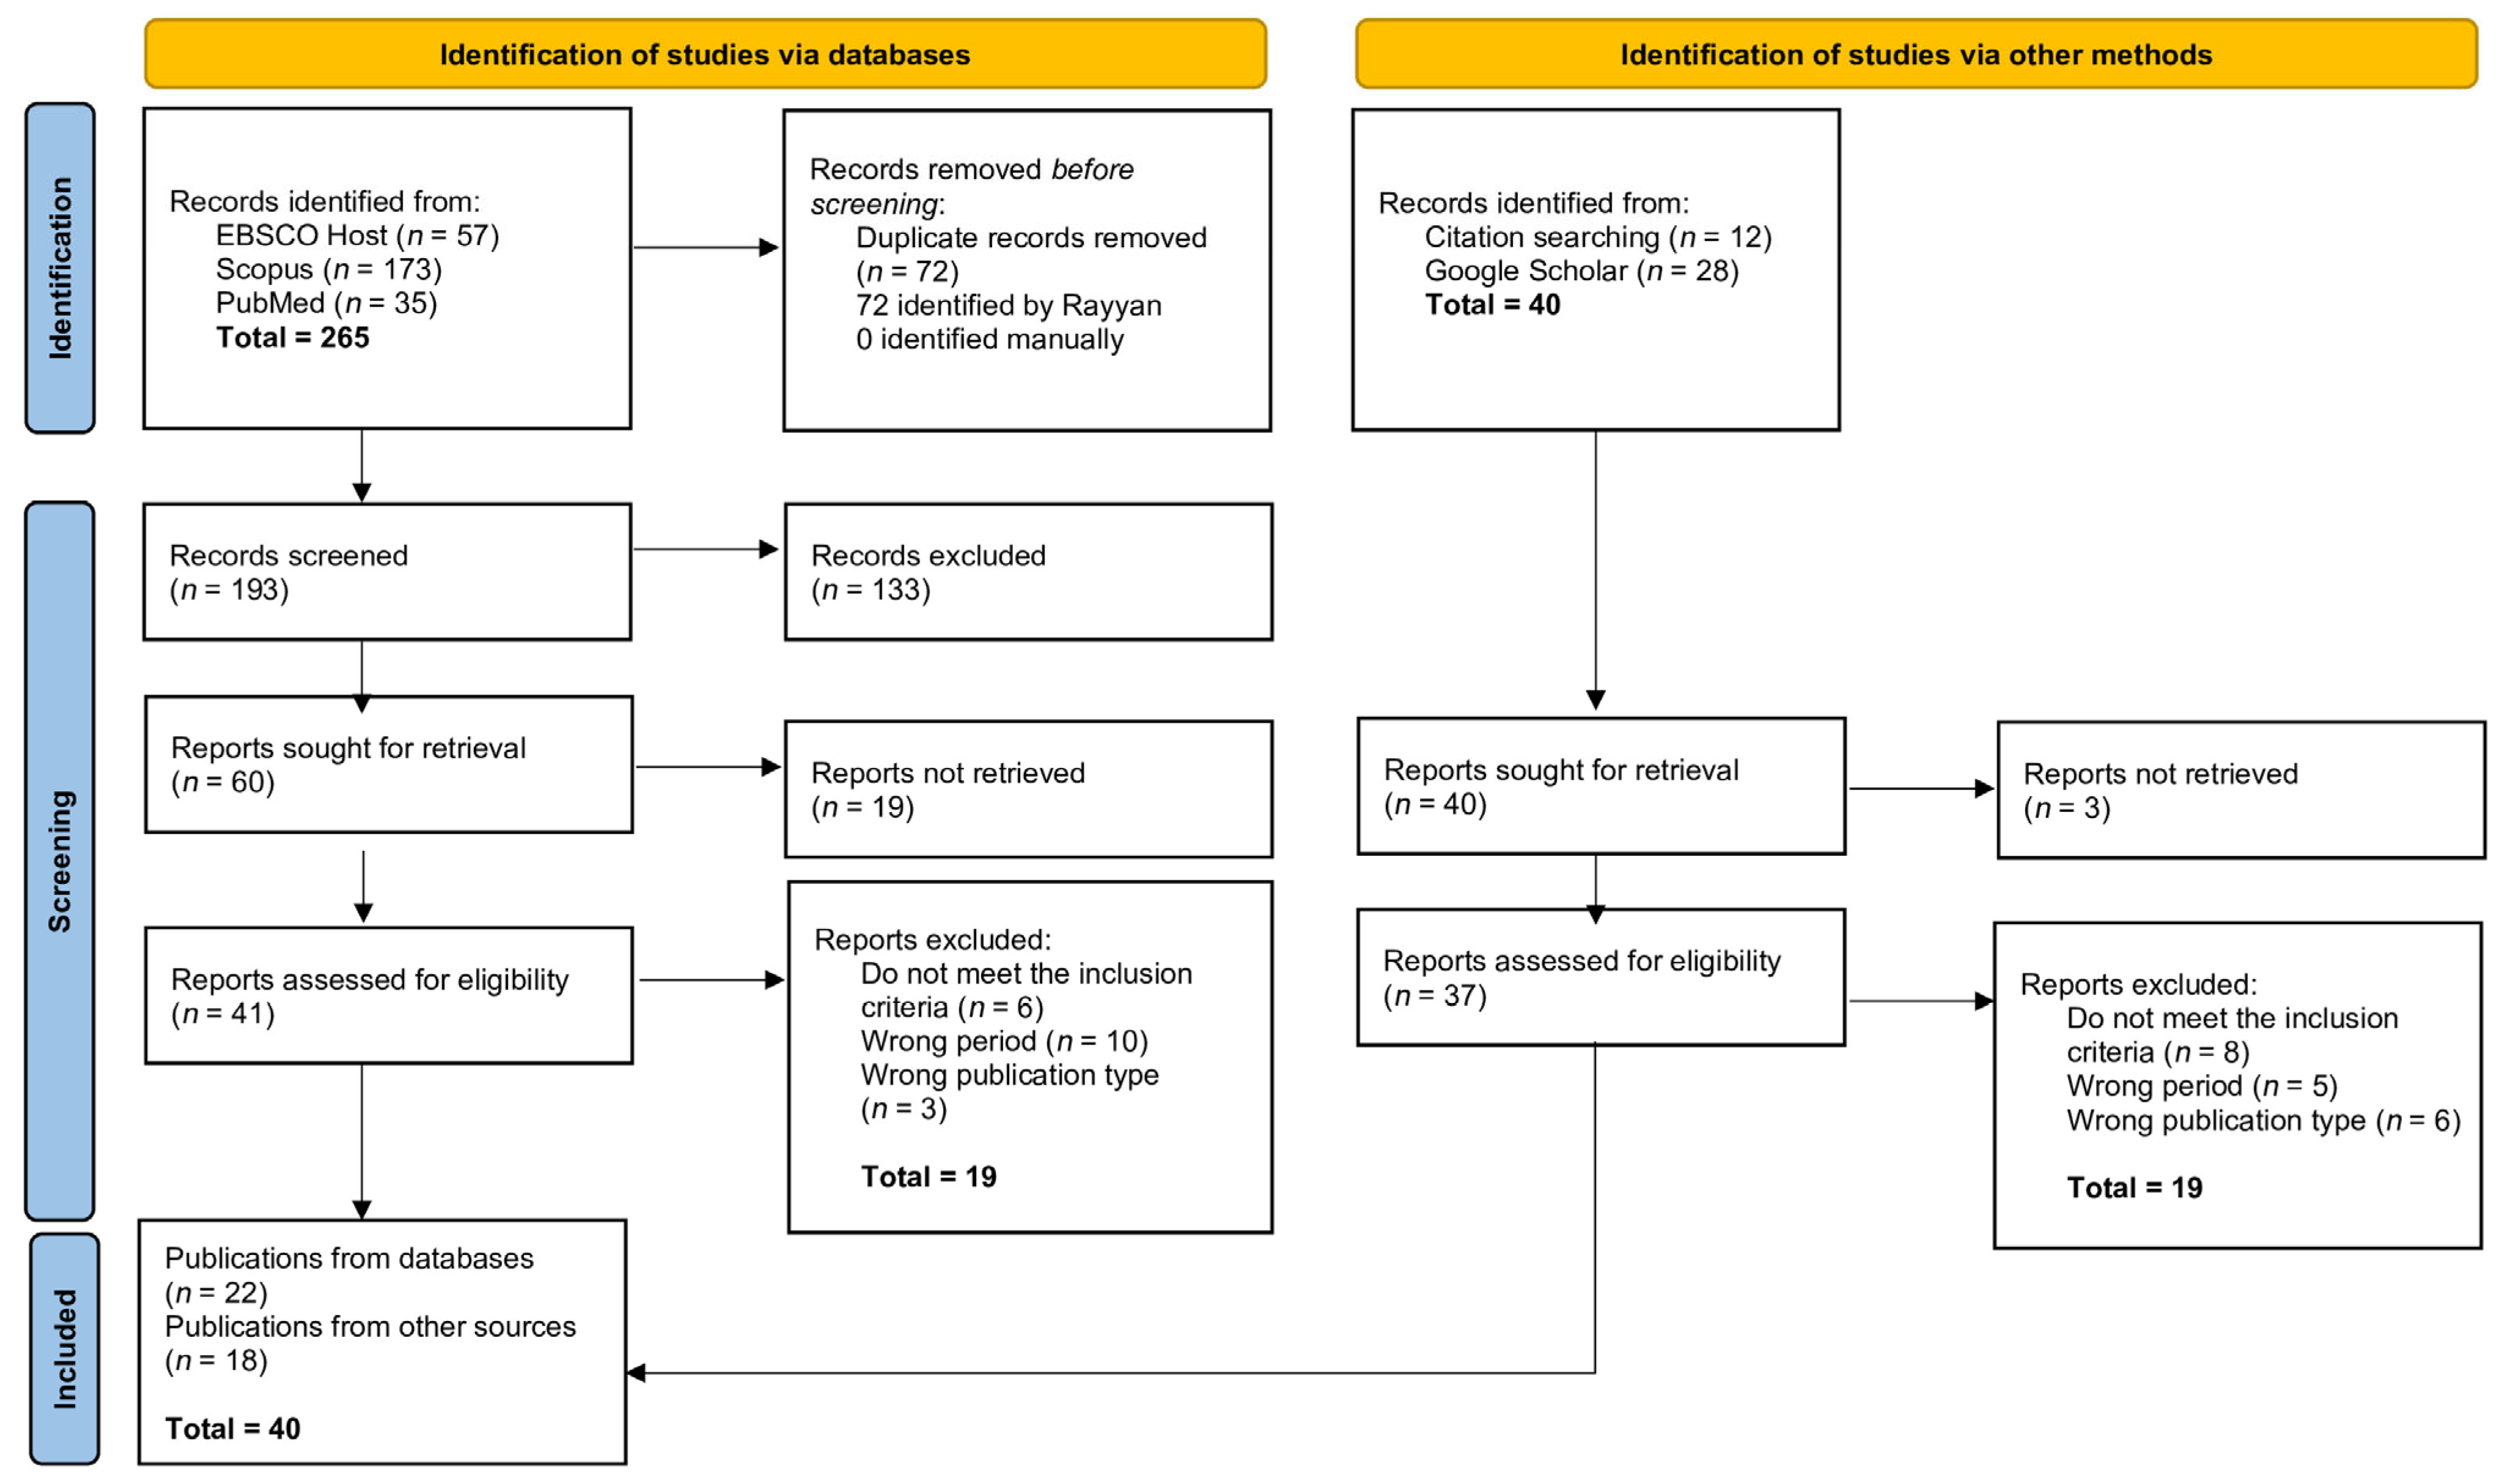

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.