


Abstract
Medicines are the most used health technology in Long-Term Care. The prevalence of potentially inappropriate medicines amongst Long-Term Care patients is high. Pharmacists, assisted by prescribing-assessment tools, can play an important role in optimizing medication use at this level of care. Through a modified RAND/UCLA Appropriateness Method, 13 long-term care and hospital pharmacists assessed as ‘appropriate’, ‘uncertain’, or ‘inappropriate’ a collection of commonly used prescribing-assessment tools as to its suitability in assisting pharmacy practice in institutional long-term care settings. A qualitative analysis of written or transcribed comments of participants was pursued to identify relevant characteristics of prescribing-assessment tools and potential hinders in their use. From 24 different tools, pharmacists classified 9 as ‘appropriate’ for pharmacy practice targeted to long-term care patients, while 3 were classified as ‘inappropriate’. The tools feature most appreciated by study participants was the indication of alternatives to potentially inappropriate medication. Lack of time and/or pharmacists and limited access to clinical information seems to be the most relevant hinders for prescribing-assessment tools used in daily practice.
1. Introduction
Long-Term Care (LTC) encompasses a range of healthcare, personal care, and other supportive services targeted to patients whose capacity for self-care is limited over an extended period [1,2]. In Portugal, the National Network for Long-Term Integrated Care represents the country’s response to the growing demand for this level of care. Structurally, the National Network for Long-Term Integrated Care (NLTIC) comprehends Home and Community-Based Services (outpatient settings) and Skilled Nursing Homes (inpatient settings). Pharmacists’ intervention in NLTIC outpatient settings is absent. National Network for Long-Term Integrated inpatient settings is divided into ‘Convalescence units’, ‘Medium Term & Rehabilitation units’, and ‘Long-Term & Maintenance units’ [3]. Although not explicitly targeted to care for aged people, LTC populations are often elderly patients. In 2020, 84% of NLTIC’s patients were aged 65 or over, aligned with the worldwide demographic ageing trend [4]. As extensively reported, the ageing process is highly associated with multimorbidity and, consequently, with augmented use of medications [5,6,7]. Older populations are more susceptible to Adverse Drug Events (ADEs) given the age-related pharmacokinetics and pharmacodynamics changes, adding to elders’ usual under-representation in clinical trials. All previous reasons might explain the high prevalence of Potentially Inappropriate Medication (PIM) in older patients [8,9]. A recent systematic review identified a prevalence of inappropriate medication use among the elderly ranging from 11.5% to 62.5% [10]. In LTC facilities, the prevalence of inappropriate medication is also high [11,12,13]. Consequently, the quality of prescribing in LTC populations is of utmost importance, being a complex and challenging process. Potentially Inappropriate Prescribing (PIP) has been associated with negative health outcomes and economic losses [14,15]. Potentially Inappropriate Prescribing concept encompasses the following practices: (i) misprescribing, i.e., the prescription of a medication that could potentially lead to a significant risk of ADEs, due to erroneous posology or route of administration or due to increased risk of drug-drug or drug-disease interaction; (ii) underprescribing or Potential Prescribing Omission (PPO), i.e., the omission of a medication that is clinically indicated for disease treatment or prevention; (iii) overprescribing, i.e., the prescription of medications for which no clear clinical indication exists [16,17]. Different methods have been developed and implemented focused on inappropriate prescribing prevention, such as education, medication reconciliation, and prescribing-assessment tools [18]. Over the last three decades, several criteria and screening tools have been developed to assist clinicians in identifying and preventing PIP. These tools can be explicit (i.e., criteria-based) or implicit (i.e., judgement-based) [19,20]. Amongst the healthcare professionals capable of using such instruments are pharmacists. Pharmacists’ practice encompasses several medicine-related interventions, from medicines management to establishing, assessing, or monitoring treatment plans. Through a set of clinical and patient-oriented activities and collaboration with other healthcare professionals, pharmacists can reduce PIP also in LTC settings [21,22].
Long-Term Care conceptualization and delivery vary from country to country, hampering scientific reporting and standardized utilization of Potentially Inappropriate Prescribing (PIP) assessment tools [23,24]. In Portugal, no common or generally accepted guidelines regarding therapy optimization are known in LTC. The existing heterogeneity of medication prescribing practices, the wide range of supporting instruments available, and the LTC population heterogeneous health status turns challenging to identify the most suitable Prescribing-Assessment Tools (PATs). This study aimed to identify the most suitable Prescribing-Assessment Tools useful for LTC pharmacy practice. An additional goal was to map key characteristics of Prescribing-Assessment Tools from the pharmacist-user perspective and potential hinders for their use.
2. Materials and Methods
This study followed a consensus-building methodology to select the most appropriate tools for pharmacy practice in LTC settings, adjusted to patients’ characteristics and pharmacists’ activities in this level of care.
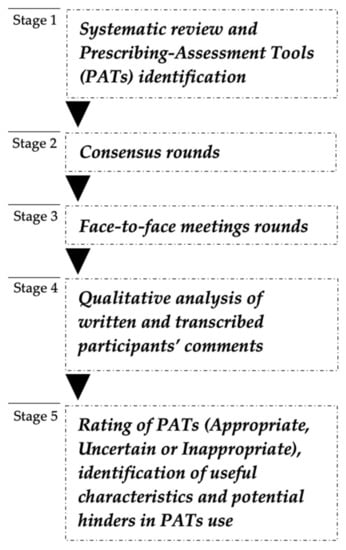
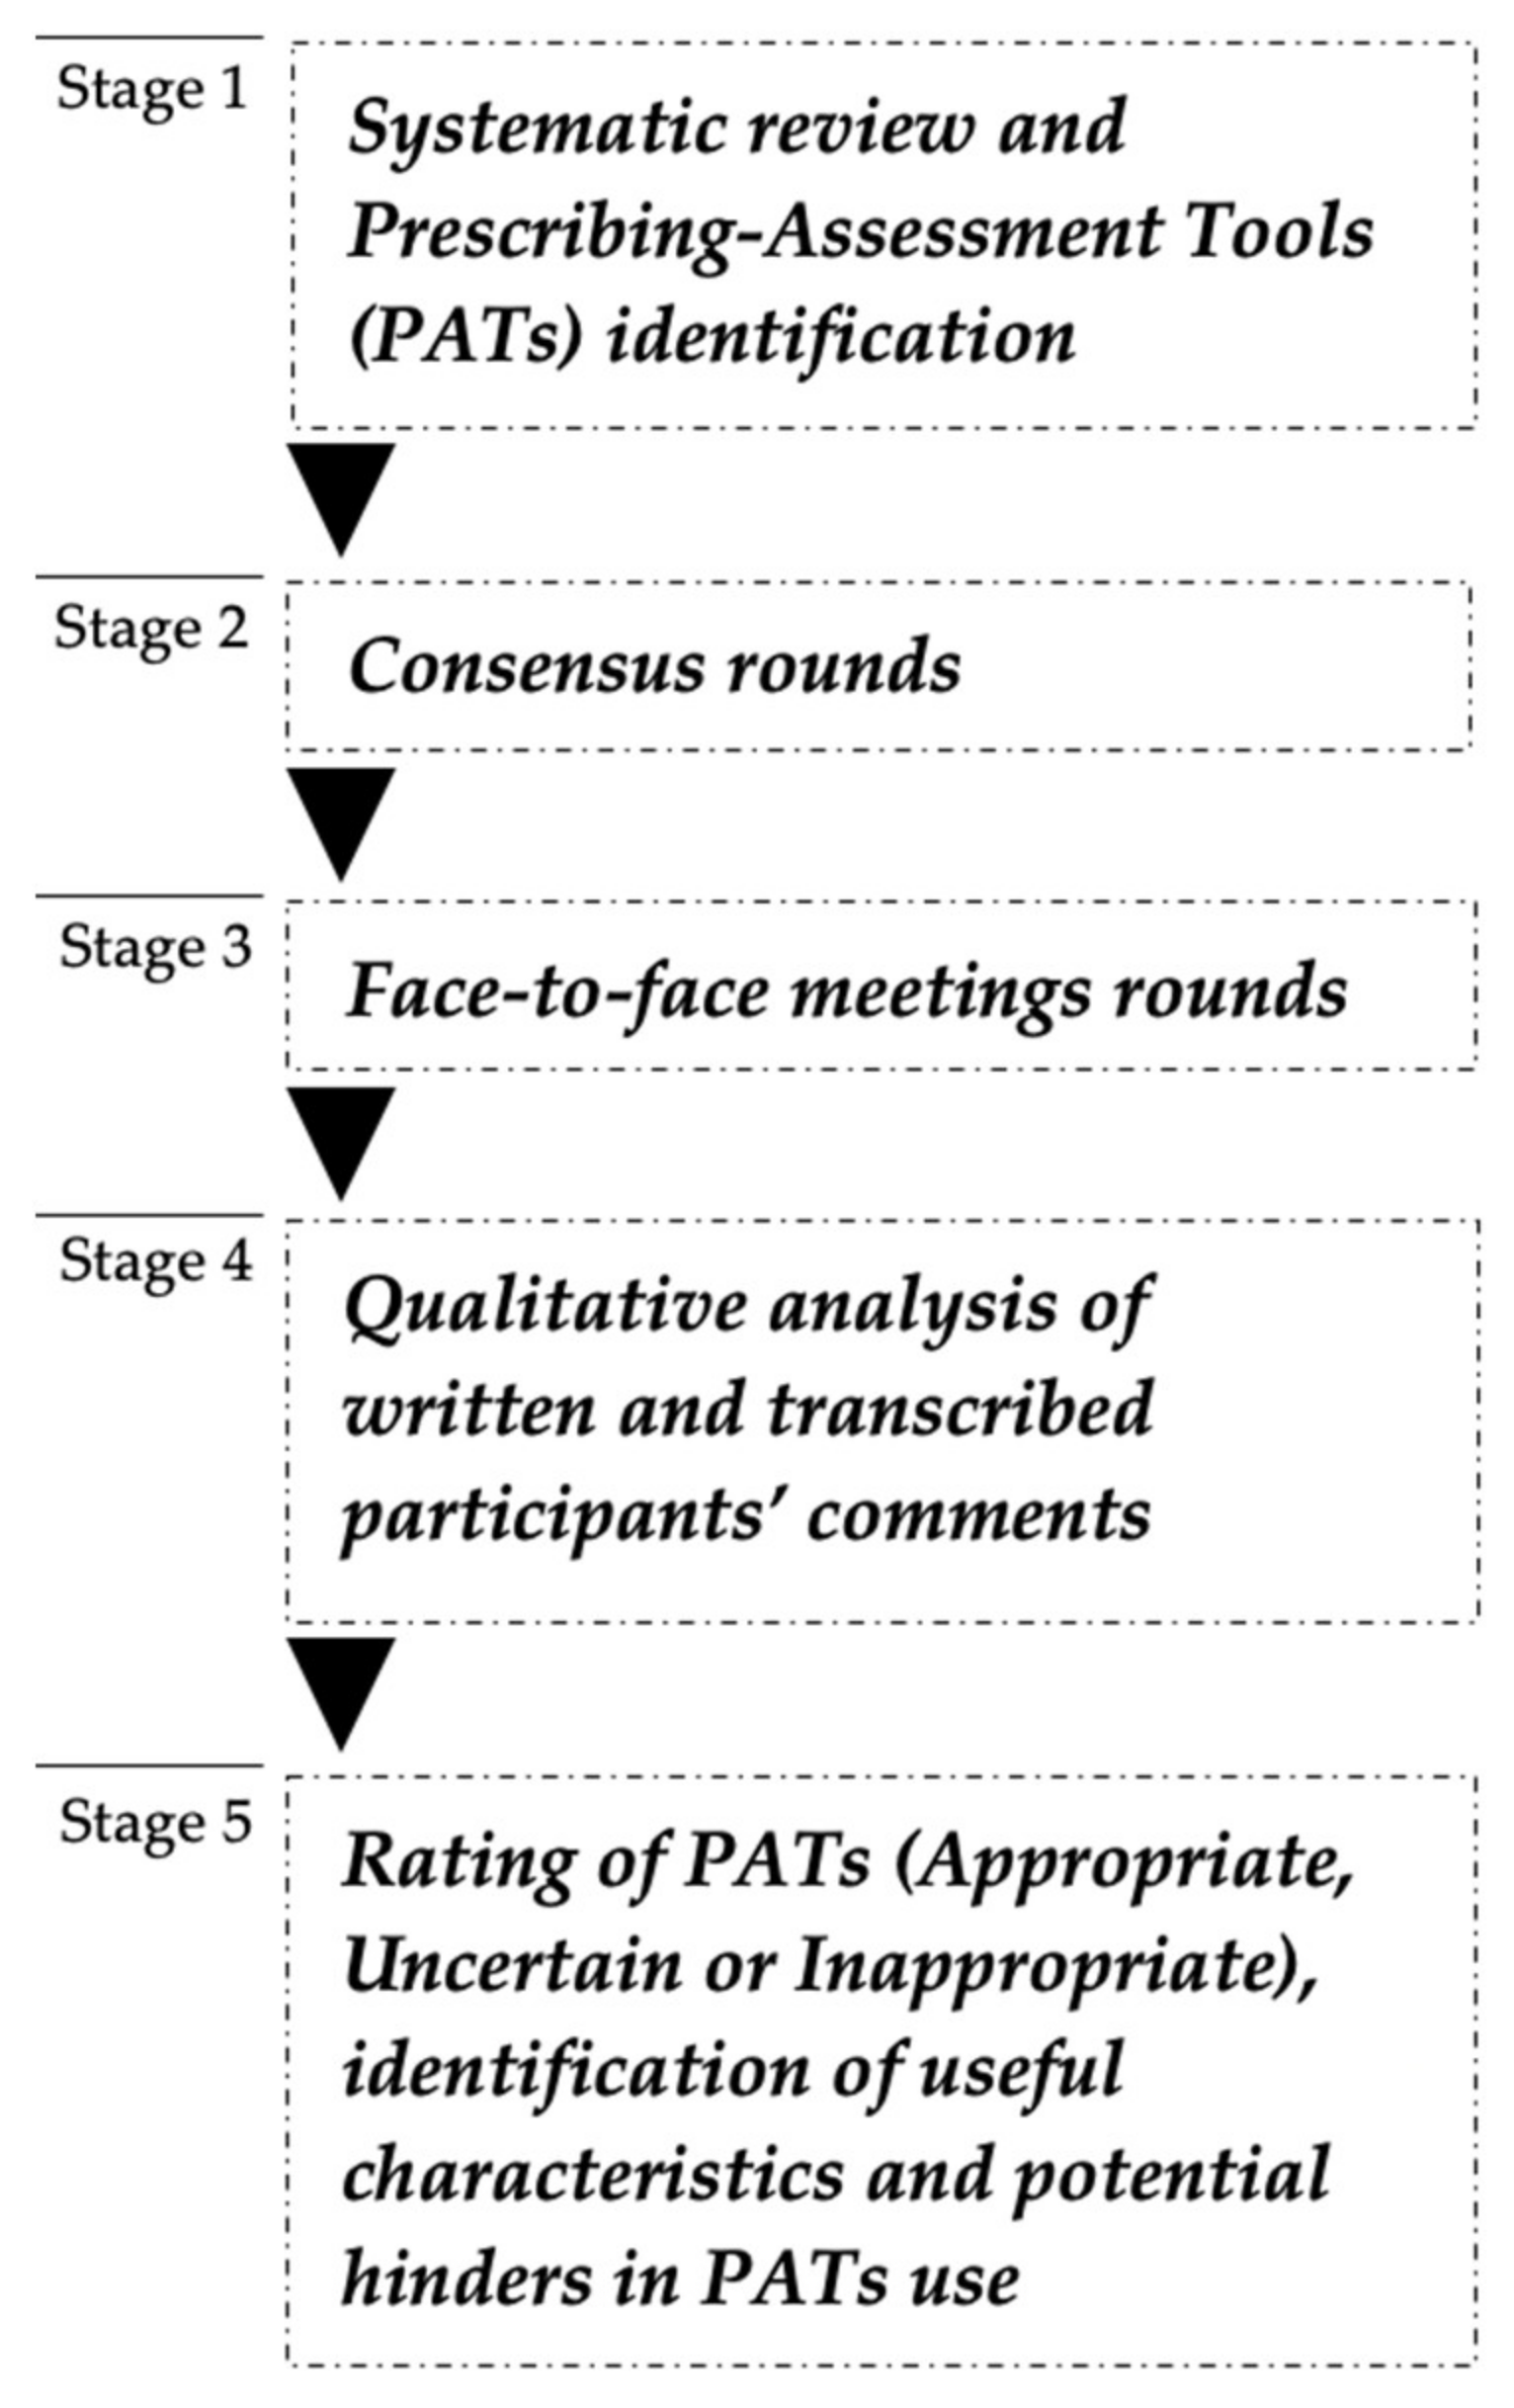
The methodological approach is summarized in Figure 1.
Figure 1.
Study methodology flowchart.
Consensus methods can be defined as a set of facilitation techniques designed to explore the level of consensus among a group of experts by synthesizing and clarifying expert opinions. In healthcare research, four consensus methods are frequently used: Delphi, Nominal Group technique, Consensus Development Conference, and RAND/UCLA Appropriateness Method (RAM) [25,26]. RAM is accomplished from a list of predetermined items [27]. For this reason, RAM suits our objectives once Prescribing-Assessment Tools are already developed and published in the scientific literature. Generically, RAM methodology can be described in four main steps: (i) literature review; (ii) panel rating round to review the evidence gathered from literature (without any interactions between panelists, the silent round); (iii) face-to-face meeting aimed at discussing group’s ratings, followed by individual opportunities for re-ratings; (iv) final classification of evidence as “appropriate”, “uncertain” or “inappropriate” (according to panelists median scores) and discussion [27]. A pilot phase was undertaken to anticipate potential hinders in applying this method, particularly for the meeting step (e.g., time and other constraints). At this point, a RAM modification was assumed to strengthen a qualitative perspective on PATs use, inspired by a mixed-methods approach. Instead of a single round, two silent rounds with all panelists were conducted to obtain PATs quantitative appraisal before the face-to-face meeting.
2.1. Literature Review and Prescribing-Assessment Tools Identification
Prescribing-Assessment Tools were identified in studies reporting pharmacist-led interventions in institutional LTC settings from published primary sources summarized in a recent systematic review, published elsewhere (Figure 1) [28]. Additionally, a manual search of relevant references from the retrieved papers was undertaken.
2.2. Prescribing-Assessment Tools Independent Rating
Panelists’ enrollment was made following a purposive sampling technique (Table 1). Panelists were LTC pharmacists exclusively dedicated to at least one of the three types of RNCCI inpatient settings (‘Convalescence units’, ‘Medium Term & Rehabilitation units’, and ‘Long-Term & Maintenance units’) or hospital pharmacists. Referral of patients to the National Network for Long-Term Integrated Care is made mainly through hospital settings; therefore, the intervention of hospital pharmacists in the transition of patients to LTC occurs. Community pharmacists are not involved in the transition of care; thus, they were not recruited. The final PATs collection was mailed to institutional addresses of each pharmacist for judgment and private rating, as described next.
Table 1.
Panelists’ demographic characteristics.
Panelists were asked to rate each PAT regarding its suitability for LTC pharmacy practice (How appropriate could this PAT be in providing care to LTC patients?), using a 9-points Likert scale (1—totally inappropriate; 9—totally appropriate), and to comment on their ratings. Ratings of 1–3, 4–6 and 7–9 were classified as Inappropriate (I), Uncertain (B), and Appropriate (A), respectively. After each round, the group median rate, Disagreement Index (DI) and comments supporting ratings were anonymously shared with all panelists, who were allowed to change their ratings before the second round and face-to-face meeting.
Disagreement Index is an indicator of consensus and for its calculation, the following equation was used: DI = IPR/IPRAS (IPR, Inter-Percentile Range; IPRAS, Inter-Percentile Range Adjusted for Symmetry), considering the following: (i) IPR = 70th–30th percentile; (ii) IPR Central Point (IPRCP = (70th + 30th percentile)/2; (iii) Asymmetry Index (AI) = (5–IPRCP); (iv) IPRAS = 2,5 + (AI × 1,5) [27]. A DI value less than or equal to 1 signals agreement between panelists [29].
2.3. Face-to-Face Meetings
Live remote meetings were held with panelists after the two silent rounds to reach a consensus. An earlier pilot panel, meeting online with 3 LTC pharmacists, took 3 h and 15 min to its end. Thus, to assure that all participants could express their evaluation of all PATs, including qualitative accounts, within an acceptable timeframe, it was necessary to convene three groups of 3–5 panelists. All panels aimed to reach an agreement on assessing PATs as Appropriate, Uncertain and Inappropriate, regarding their usefulness for LTC pharmacy practice. In case panelists disagreed, that panel’s rating was considered as Uncertain (B). For final consensus as Inappropriate (If), Uncertain (Bf), and Appropriate (Af), a thumb rule was followed: for PATs with at least two panels’ rating aligned with the 2nd round overall rating and a DI equal or below 1, final consensus as If, Bf or Af was considered accordingly to the overall group’s rating. If the two panels’ ratings were not aligned with the overall group’s rating, the PAT was classified as Uncertain (B) use for LTC pharmacy practice.
2.4. Analysis of Panellists’ Accounts and Final Classification
To inform reasons for ratings and consensus and explore PATs’ characteristics identified as more suitable for pharmacist LTC practice, a record of comments (written during the private rating and transcribed from face-to-face meetings) was performed. The panelists’ accounts were interpreted, organized, and synthesized into two main themes (positive features and usage hinders) without pursuing a detailed qualitative analytical approach.
3. Results
3.1. Literature Review
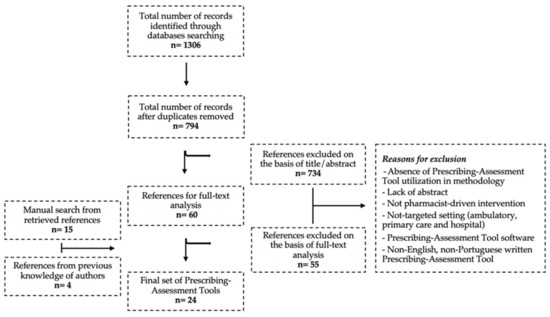
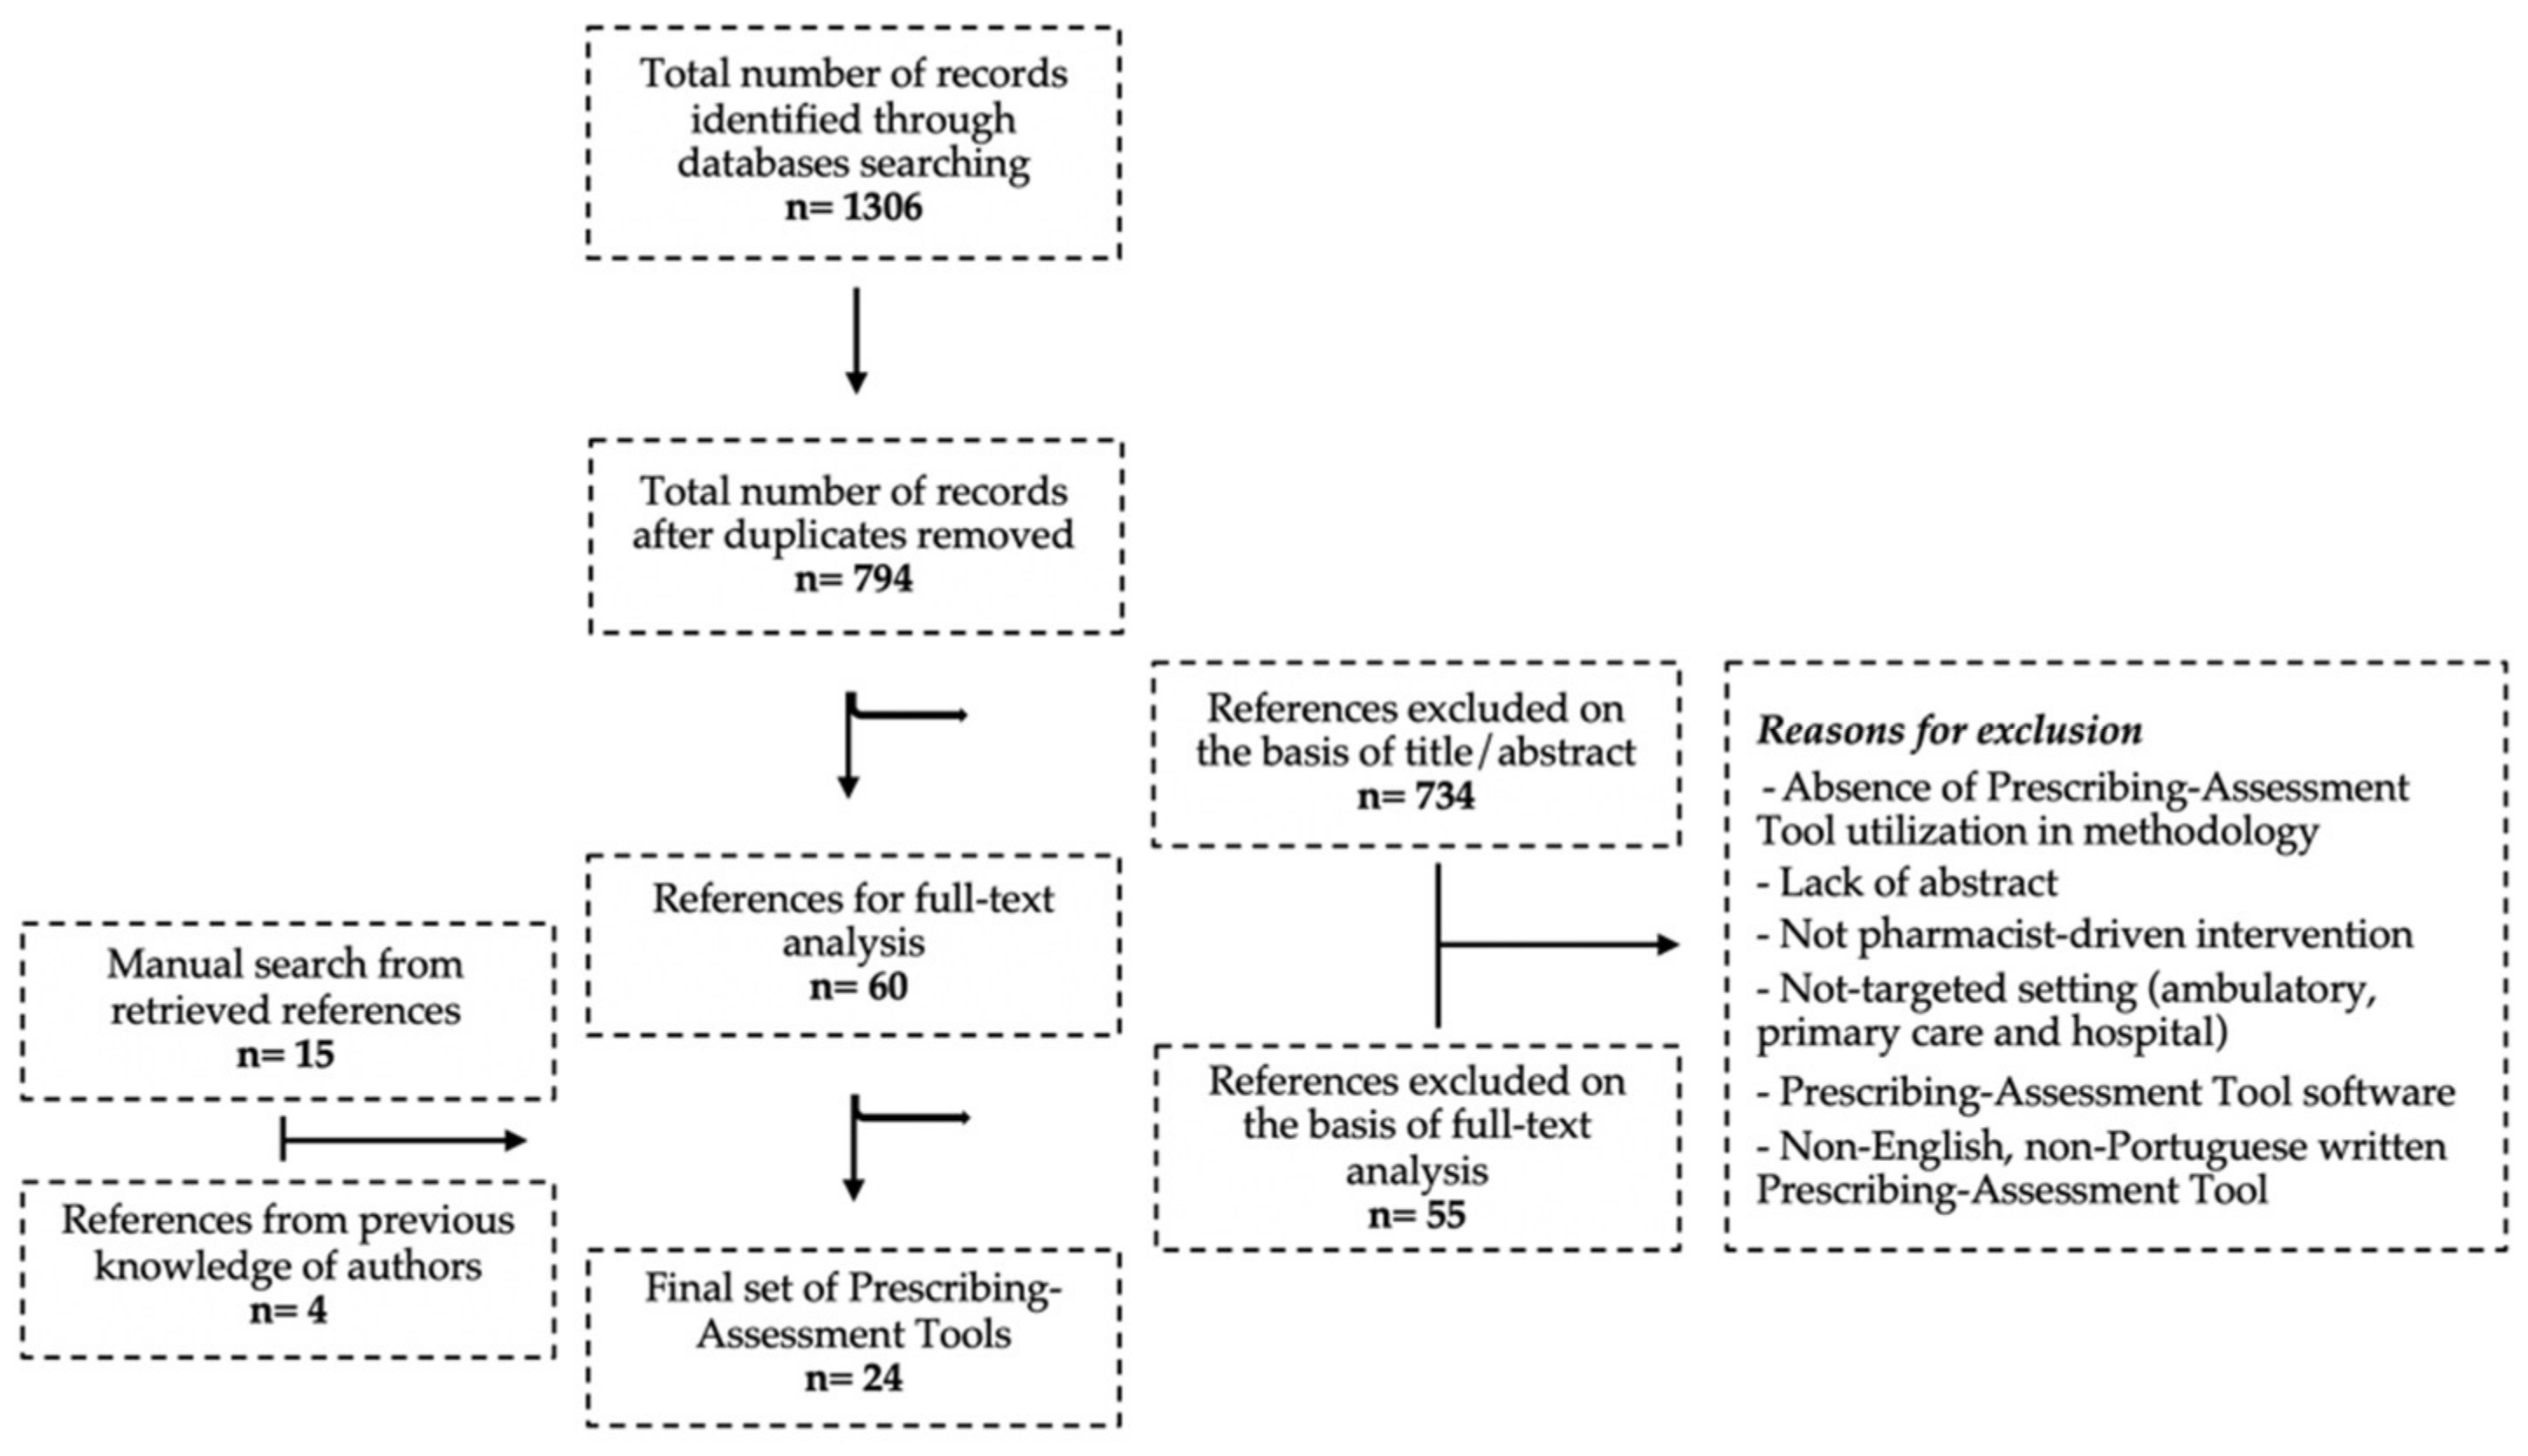
The literature review process (Figure 2) retrieved 24 PATs (Supplementary Table S1). These were organized into different practice areas, namely: (i) anticholinergic and sedative medicines usage: ARS [30] and DBI [31]; (ii) hemorrhagic risk: ATRIA [32], CHA2DS2VASc [33], HAS-BLED [34] and HEMORR2HAGES [35]; (iii) antibiotics usage: Loeb [36]; iv) medication complexity: MRCI [37,38] and Mrs. GRACE [39]; (v) comprehensive implicit assessment of prescribing: MAI [40] and PAI [41]; (vi) comprehensive, explicit assessment of prescribing: Beers criteria [42]; NORGEP [43]; STOPP/START [44]; FORTA [45,46]; Winit-Watjanas criteria [47]; Rancourts criteria [48]; Poudels criteria [49]; McLeods criteria [50]; Laroches criteria [51]; Australian Prescribing Indicators Tool [52] (vii) medicines usage in dementia: APID [53], Holmes criteria [54] and Krogers criteria [55].
Figure 2.
Flowchart of literature review and Prescribing-Assessment Tools identification.
3.2. Panellists’ Characteristics
Participants’ characteristics are described in Table 1. Participants enrolled included pharmacists working in Long-Term Care Facilities (LTCFs) or hospitals from four Regional Health Authorities (RHAs) catchment areas (out of 5 RAHs in mainland Portugal).
Three meetings with three panelists each were organized. The face-to-face panels were formed by participants 1, 2, 3 (panel 1–LTC pharmacists), 4, 5, 6 (panel 2–LTC pharmacists), 10, 11, 13 (panel 3–Hospital pharmacists), i.e., a dropout rate of 30% was verified (participants 7, 8 and 9).
3.3. RAM Rounds, Face-to-Face Meetings and Final Consensus
For 14 PATs, consensus was reached in all components, i.e., overall group rating (with DI ≤ 1) was aligned with the three panels ratings. For instance, in the case of ATRIA, the second-round rating was 7 (A)–with a DI of 0.164–and panels’ 1, 2, and 3 ratings were A; thus, the final consensus was set as Af (Appropriate). For 10 PATs, one panel rating was not aligned with the rest of the ratings. For instance, in the case of DBI, the overall group’s rating was C (Inappropriate) with a DI of 0.438; panels’ 1 and 2 ratings were C, while panel’s 3 rating was B; thus, the final decision was Cf (Inappropriate). For all PATs, DI at the second round was lower than 1. If this rule could not be followed, a PAT was rated for Uncertain (Bf) usefulness in LTC pharmacy practice. Results are summarized in Table 2.
Table 2.
Prescribing-Assessment Tools ratings, representative quotations and final consensus.
3.4. Relevant Characteristics of PATs
Several characteristics of interest emerged from comments and face-to-face meetings qualitative analysis (Table 3).
Table 3.
Prescribing-Assessment Tools’ useful characteristics and representative quotations.
Four main groups of potential determinants hindering the use of PATs have also been identified through qualitative analysis (Table 4).
Table 4.
Potential determinants hindering Prescribing-Assessment Tool use.
4. Discussion
This study aimed at identifying useful Prescribing-Assessment Tools for LTC pharmacy practice and, additionally, to map its most relevant characteristics and potential hinders.
LTC pharmacy practice varies regarding the population served and patients’ characteristics (e.g., units exclusively dedicated to cognitive disorders) and pharmacist presence (on-site vs. periodic visits [4,56]. For these reasons, identifying PATs that might be useful for all LTC pharmacists and in the transition of care of LTC patients (hospital-LTC facility) may be difficult. Nevertheless, the RAND methodology allowed to reach a consensus on the most suitable tools for LTC pharmacy practice and mapped its most valuable characteristics. The number and diversity of enrolled participants (e.g., varying years of experience) enriched the discussion and strengthened the potential to translate conclusions into practice. This study is the first to use the RAND approach in LTC pharmacy practice research to the best of our knowledge.
Inappropriate prescribing has been studied and published in the scientific literature for many decades; thus, tools addressing this topic have a considerable number. Kaufmann et al. systematic review identified 46 PATs, of which 6 (13%) were initially developed for LTC use [20]. Similarly, Masnoon et al. identified 42 tools for assessment of the appropriateness of prescribing [19]. To address the apparent scarcity of PATs specifically designed for LTC, we have decided to identify PATs previously used in the LTC context [28]. Additionally, we tried to reduce the set of PATs for panelists’ assessment to avoid loss of richness during meeting discussions.
The 24 PATs were grouped into seven areas: anticholinergic and sedative medicines; hemorrhagic risk; antibiotics; medication complexity; dementia; comprehensive assessment of prescribing (implicit or explicit).
Participants reported anticholinergic and sedative medicines usage and hemorrhagic risk as relevant in the LTC pharmacy context. Scoring systems estimating the risk of bleeding in patients on anticoagulation, such as HAS-BLED and ATRIA, were classified as “Appropriate”, while CHA2DS2VASc and HEMORR2HAGES were classified as “Uncertain”. The difference in classification here seemed to be based on the nature and availability of the data needed to calculate the risk, like CYP 2C9 polymorphisms or previous diagnoses, often not available during the transition of care (e.g., history of alcohol abuse).
Pharmacists working in LTC facilities or hospitals expectably disagree on antibiotic use, knowing antibiotics’ range and use differ in both settings. In RNCCI facilities, antibiotic use is often empirical (i.e., not assisted by antibiogram), while some antibiotics are exclusive of hospital use. In the rating of this particular PAT, hospital and LTC pharmacy practice differences were highlighted, with hospital pharmacists’ panel rating it as “Inappropriate” and both LTC pharmacists’ panels as “Appropriate”. Nevertheless, if considering only LTC practice and excluding transition of care, Loeb’s criteria seem appropriate.
Pharmacists identified some strengths on PATs for medication complexity, yet its usefulness seemed limited. Both MRCI and MRS.GRACE were rated as “Uncertain” for their usefulness for LTC pharmacy practice, mainly given its length (i.e., too time-consuming). However, participants consider these tools as potentially useful at post-discharge moments and to ease medicines administration burden by nurses [57,58].
Prescribing-Assessment Tools targeted to medicines optimization in dementia (APID, Holmes’s criteria, and Kroger’s criteria) were all classified as “Uncertain”. The usefulness of these PATs seems to considerable differ based on pharmacists’ experiences with delivering care to patients with dementia or not. Further research on PATs in dementia is recommended, mainly due to the high prevalence of dementia and cognitive disorders amongst LTC patients [59,60].
Prescribing-Assessment Tools not targeted to a disease/syndrome or a medicines group comprised 50% of all PATs assessed (n = 12 out of 24). PATs used for a comprehensive assessment of prescribing were divided into explicit and implicit. Explicit criteria represent the larger group (n = 10), with Beers’, Laroche’s, and Poudel’s criteria, FORTA and STOPP/START being classified as “Appropriate” for LTC pharmacy practice. Medication Appropriateness Index (implicit PAT) was also assessed as “Appropriate” by participants.
Explicit criteria (including ARS, ATRIA and HAS-BLED) represent 90% of all PATs classified as “Appropriate” (n = 8 out of 9), aligned with healthcare professionals’ preferences reported in the scientific literature [61,62].
Agreement on the rating was reached for all PATs, and the combination of silent ratings and face-to-face discussion allows us to say that the 9 PATs rated as “Appropriate [30,32,34,40,42,44,45,49,51] have the potential to be suitable for LTC pharmacy practice” and during the transition of care of LTC patients. All the 9 PATs address misprescribing, underprescribing and overprescribing practices included in the Potentially Inappropriate Prescribing concept.
In what concerns to helpful characteristics of PATs, the indication of alternatives to PIM seems to be one of the most relevant characteristics along with an organization by medicine, followed by the indication of recommended dose and duration of treatment. However, regarding PAT’s organization (by medicine vs. by disease), further research is needed to explore more clearly participants’ divide: “I prefer a tool that evaluates [medication] by pharmacotherapeutic group and not so much by pathology because when I’m evaluating a prescription, I evaluate medicine by medicine” (P10) vs. “I prefer a disease-oriented PAT” (P11). On the other hand, lack of time and staff (pharmacists) and limited availability or access to clinical information seems to be the most relevant hinders for PATs use in daily practice.
Some limitations of the study can be mentioned: (i) with exception to Beer’s and MRCI, all PATs are not translated to Portuguese language or no previous validation or adaptation to Portuguese LTC context or medicines use, which may have had an impact on panelists’ assessment; (ii) around 40% of PATs under evaluation are targeted to aged people, and LTC is not exclusively targeted to aged people, although, in 2020, 83% of patients assisted in Portuguese LTC network were 65 years old or over [4]; (iii) other published PATs were not included in the final PATs set for analysis once the methodological strategy; (iv) given the heterogeneity of LTC worldwide and that participants work exclusively in Portugal, application of conclusions in international contexts may be hampered.
5. Conclusions
Nine Prescribing-Assessment Tools seem to be suitable in assisting clinical pharmacists’ activities targeted to LTC patients. Except for one (MAI), all PATs identified are explicit criteria (ARS, ATRIA, HAS-BLED, Beers’, FORTA, Laroche’s, Poudel’s, and STOPP/START criteria). These Prescribing-Assessment Tools seem to have the potential to be helpful for LTC patients during the transition of care. Three Prescribing-Assessment Tools were classified as Inappropriate for LTC pharmacy practice (DBI, Australian Prescribing Indicators, and NORGEP). Half of Prescribing-Assessment Tools were classified as “Uncertain”, yet further studies should investigate their relevance in particular areas and circumstances of LTC pharmacy practice (e.g., medication regimen complexity or dementia). Explicit criteria gathered the preference of participants, in line with preferences reported in scientific literature. Some important design characteristics of Prescribing-Assessment Tools seem to be related to convenient features of these tools, such as indicating alternatives to Potentially Inappropriate Medication. Future research should investigate the impact of these PATs in relevant endpoints and outcomes for LTC patients (e.g., mortality, hospitalization).
Supplementary Materials
The following are available online at https://www.mdpi.com/article/10.3390/pharmacy9040194/s1, Table S1: Summary of the identified Prescribing-Assessment Tools.
Author Contributions
Conceptualization: J.R.G., B.L.S., M.J.L., A.M.C.; Methodology: J.R.G.; Data collection: J.R.G., A.M.C.; Analysis: J.R.G., B.L.S., M.J.L., A.M.C.; Draft preparation: J.R.G.; Review and editing: J.R.G., B.L.S., A.M.C.; Supervision: B.L.S., M.J.L., A.M.C. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted according to the guidelines of the Declaration of Helsinki and approved by the Committee of Research involving Human Beings of the Faculty of Pharmacy of the University of Lisbon (no. 02/2020).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Conflicts of Interest
The authors declare no conflict of interest.
References
- World Health Organization. Towards an International Consensus on Policy for Long-Term Care of the Ageing. WHO. 2000. Available online: https://apps.who.int/iris/handle/10665/66339 (accessed on 3 August 2021).
- OECD. A Good Life in Old Age? Monitoring and Improving Quality in Long-Term Care. OECD; June 2013 (OECD Health Policy Studies). Available online: https://www.oecd-ilibrary.org/social-issues-migration-health/a-good-life-in-old-age_9789264194564-en (accessed on 5 August 2021).
- Lopes, H.; Mateus, C.; Hernández-Quevedo, C. Ten Years after the Creation of the Portuguese National Network for Long-Term Care in 2006: Achievements and Challenges. Health Policy 2018, 122, 210–216. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saúde, M.D. Monitorização da Rede Nacional de Cuidados Continuados Integrados (RNCCI)—2020. 2020. Available online: http://www.acss.min-saude.pt/wp-content/uploads/2021/08/Relatorio-de-Monitorização-da-RNCCI-Anual-2020-VF.pdf (accessed on 4 August 2021).
- Nobili, A.; Garattini, S.; Mannucci, P.M. Multiple Diseases and Polypharmacy in the Elderly: Challenges for the Internist of the Third Millennium. J. Comorbidity 2011, 1, 28–44. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nunes, B.P.; Flores, T.R.; Mielke, G.; Thumé, E.; Facchini, L.A. Multimorbidity and mortality in older adults: A systematic review and meta-analysis. Arch. Gerontol. Geriatr. 2016, 67, 130–138. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khezrian, M.; McNeil, C.J.; Murray, A.; Myint, P.K. An overview of prevalence, determinants and health outcomes of polypharmacy. Ther. Adv. Drug Saf. 2020, 11. [Google Scholar] [CrossRef] [Scilit]
- Gray, S.L.; Marcum, Z.A.; Schmader, K.E.; Hanlon, J.T. Update on Medication Use Quality and Safety in Older Adults, 2017. J. Am. Geriatr. Soc. 2018, 66, 2254–2258. [Google Scholar] [CrossRef] [Scilit]
- McLean, A.J.; le Couteur, D.G. Aging biology and geriatric clinical pharmacology. Pharmacol. Rev. 2004, 56, 163–184. [Google Scholar] [CrossRef] [Scilit]
- Guaraldo, L.; Cano, F.G.; Damasceno, G.S.; Rozenfeld, S. Inappropriate medication use among the elderly: A systematic review of administrative databases. BMC Geriatr. 2011, 11, 79. [Google Scholar] [CrossRef] [Scilit]
- Avorn, J.; Gurwitz, J.H. Drug Use in the Nursing Home. 1995. Available online: http://annals.org/ (accessed on 3 August 2021).
- Qassemi, S.; Pagès, A.; Rouch, L.; Bismuth, S.; Stillmunkes, A.; Lapeyre-Mestre, M.; McCambridge, C.; Cool, C.; Cestac, P. Potentially Inappropriate Drug Prescribing in French Nursing Home Residents: An Observational Study. Pharmacy 2020, 8, 133. [Google Scholar] [CrossRef] [Scilit]
- Storms, H.; Marquet, K.; Aertgeerts, B.; Claes, N. Prevalence of inappropriate medication use in residential long-term care facilities for the elderly: A systematic review. Eur. J. Gen. Pract. 2017, 23, 69–77. [Google Scholar] [CrossRef] [Scilit]
- Spinewine, A.; Schmader, K.E.; Barber, N.; Hughes, C.; Lapane, K.L.; Swine, C.; Hanlon, J.T. Appropriate prescribing in elderly people: How well can it be measured and optimised? Lancet 2007, 370, 173–184. [Google Scholar] [CrossRef] [Scilit]
- Cahir, C.; Bennett, K.; Teljeur, C.; Fahey, T. Potentially inappropriate prescribing and adverse health outcomes in community dwelling older patients. Br. J. Clin. Pharmacol. 2014, 77, 201–210. [Google Scholar] [CrossRef] [Scilit]
- Rankin, A.; Cadogan, C.A.; Patterson, S.M.; Kerse, N.; Cardwell, C.R.; Bradley, M.C.; Ryan, C.; Hughes, C. Interventions to improve the appropriate use of polypharmacy for older people. Cochrane Database Syst. Rev. 2018, 9. [Google Scholar] [CrossRef] [Scilit]
- O’connor, M.N.; Gallagher, P.; O’mahony, D. Inappropriate Prescribing Criteria, Detection and Prevention. Drugs Aging 2012, 29, 437–452. [Google Scholar] [CrossRef] [Scilit]
- O’Mahony, D.; Gallagher, P.F.; Lavan, A.H. Methods to reduce prescribing errors in elderly patients with multimorbidity. Clin. Interv. Aging 2016, 11, 857–866. [Google Scholar] [CrossRef] [Scilit]
- Masnoon, N.; Shakib, S.; Ellett, L.K.; Caughey, G. Tools for Assessment of the Appropriateness of Prescribing and Association with Patient-Related Outcomes: A Systematic Review. Drugs Aging 2018, 35, 43–60. [Google Scholar] [CrossRef] [Scilit]
- Kaufmann, C.P.; Tremp, R.; Hersberger, K.E.; Lampert, M.L. Inappropriate prescribing: A systematic overview of published assessment tools. Eur. J. Clin. Pharmacol. 2013, 70, 1–11. [Google Scholar] [CrossRef] [Scilit]
- Scahill, S.; Atif, M.; Babar, Z. Defining pharmacy and its practice: A conceptual model for an international audience. Integr. Pharm. Res. Pract. 2017, 6, 121–129. [Google Scholar] [CrossRef] [Scilit]
- Wiedenmayer, K.; Summers, R.S.; Mackie, C.A.; Gous, A.G.S.; Everard, M.; Tromp, D. Developing Pharmacy Practice: A Focus on Patient Care, 1st ed.; World Health Organization (International Pharmaceutical Federation): Hague, The Netherlands, 2006; Available online: https://apps.who.int/iris/bitstream/handle/10665/69399/WHO_PSM_PAR_2006.5_eng.pdf?sequence=1&isAllowed=y (accessed on 1 November 2021).
- Sanford, A.M.; Orrell, M.; Tolson, D.; Abbatecola, A.M.; Arai, H.; Bauer, J.M.; Cruz-Jentoft, A.J.; Dong, B.; Ga, H.; Goel, A.; et al. An International Definition for “Nursing Home”. J. Am. Med. Dir. Assoc. 2015, 16, 181–184. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization—Regional Office for Europe. Integrated Care Models: An Overview Working Document. 2016. Available online: http://www.euro.who.int/pubrequest (accessed on 3 August 2021).
- Campbell, S.M.; Cantrill, J.A. Consensus methods in prescribing research. J. Clin. Pharm. Ther. 2001, 26, 5–14. [Google Scholar] [CrossRef] [Scilit]
- Humphrey-Murto, S.; Varpio, L.; Wood, T.J.; Gonsalves, C.; Ufholz, L.A.; Mascioli, K.; Wang, C.; Foth, T. The Use of the Delphi and Other Consensus Group Methods in Medical Education Research: A Review. Acad. Med. 2017, 92, 1491–1498. [Google Scholar] [CrossRef] [Scilit]
- Fitch, K.; Bernstein, S.; Aguilar, M.; Burnand, B. The Rand/UCLA Appropriateness Method User’s Manual; RAND: Santa Monica, CA, USA, 2001. [Google Scholar]
- Gonçalves, J.R.; Ramalhinho, I.; Sleath, B.L.; Lopes, M.J.; Cavaco, A.M. Probing pharmacists’ interventions in Long-Term Care: A systematic review. Eur. Geriatr. Med. 2021, 12, 673–693. [Google Scholar] [CrossRef] [Scilit]
- Din, S.; Kent, A.; Pollok, R.C.; Meade, S.; Kennedy, N.A.; Arnott, I.; Beattie, R.M.; Chua, F.; Cooney, R.; Dart, R.J.; et al. Adaptations to the British Society of Gastroenterology guidelines on the management of acute severe UC in the context of the COVID-19 pandemic: A RAND appropriateness panel. Gut 2020, 69, 1769–1777. [Google Scholar] [CrossRef] [Scilit]
- Rudolph, J.L.; Salow, M.J.; Angelini, M.C.; McGlinchey, R.E. The Anticholinergic Risk Scale and Anticholinergic Adverse Effects in Older Persons. Arch. Intern. Med. 2008, 168, 508–513. [Google Scholar] [CrossRef] [Scilit]
- Hilmer, S.N.; Mager, D.E.; Simonsick, E.M.; Cao, Y.; Ling, S.M.; Windham, B.G.; Harris, T.B.; Hanlon, J.T.; Rubin, S.M.; Shorr, R.I.; et al. A Drug Burden Index to Define the Functional Burden of Medications in Older People. Arch. Intern. Med. 2007, 167, 781–787. [Google Scholar] [CrossRef] [Scilit]
- Fang, M.C.; Go, A.S.; Chang, Y.; Borowsky, L.H.; Pomernacki, N.K.; Udaltsova, N.; Singer, D.E. A New Risk Scheme to Predict Warfarin-Associated Hemorrhage: The ATRIA (Anticoagulation and Risk Factors in Atrial Fibrillation) Study. J. Am. Coll. Cardiol. 2011, 58, 395–401. [Google Scholar] [CrossRef] [Scilit]
- Lip, G.Y.; Nieuwlaat, R.; Pisters, R.; Lane, D.A.; Crijns, H.J. Refining clinical risk stratification for predicting stroke and thromboembolism in atrial fibrillation using a novel risk factor-based approach: The Euro Heart Survey on atrial fibrillation. Chest 2010, 137, 263–272. [Google Scholar] [CrossRef] [Scilit]
- Pisters, R.; Lane, D.A.; Nieuwlaat, R.; De Vos, C.B.; Crijns, H.J.; Lip, G.Y. A novel user-friendly score (HAS-BLED) to assess 1-year risk of major bleeding in patients with atrial fibrillation: The euro heart survey. Chest 2010, 138, 1093–1100. [Google Scholar] [CrossRef] [Scilit]
- Gage, B.F.; Yan, Y.; Milligan, P.; Waterman, A.; Culverhouse, R.; Rich, M.W.; Radford, M. Clinical classification schemes for predicting hemorrhage: Results from the National Registry of Atrial Fibrillation (NRAF). Am. Heart J. 2006, 151, 713–719. [Google Scholar] [CrossRef] [Scilit]
- Loeb, M.; Bentley, D.W.; Bradley, S.; Crossley, K.; Garibaldi, R.; Gantz, N.; McGeer, A.; Muder, R.R.; Mylotte, J.; Nicolle, L.E.; et al. Development of Minimum Criteria for the Initiation of Antibiotics in Residents of Long-Term–Care Facilities: Results of a Consensus Conference. Infect. Control. Hosp. Epidemiol. 2001, 22, 120–124. [Google Scholar] [CrossRef] [Scilit]
- George, J.; Phun, Y.-T.; Bailey, M.J.; Kong, D.C.; Stewart, K. Development and Validation of the Medication Regimen Complexity Index. Ann. Pharmacother. 2004, 38, 1369–1376. [Google Scholar] [CrossRef] [Scilit]
- Melchiors, A.C.; Correr, C.J.; Fernández-Llimos, F. Translation and Validation into Portuguese Language of the Medication Regimen Complexity Index. Arq Bras Cardiol. 2007, 89, 210–218. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, E.Y.; Sluggett, J.; Ilomaki, J.; Hilmer, S.; Corlis, M.; Picton, L.J.; Dean, L.; Alderman, C.P.; Farinola, N.; Gailer, J.; et al. Development and validation of the Medication Regimen Simplification Guide for Residential Aged CarE (MRS GRACE). Clin. Interv. Aging 2018, 13, 975–986. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hanlon, J.T.; Schmader, K.E.; Samsa, G.P.; Weinberger, M.; Uttech, K.M.; Lewis, I.K.; Cohen, H.J.; Feussner, J.R. A method for assessing drug therapy appropriateness. J. Clin. Epidemiol. 1992, 45, 1045–1051. [Google Scholar] [CrossRef] [Scilit]
- Tully, M.P.; Javed, N.; Cantrill, J.A. Development and Face Validity of Explicit indicators of Appropriateness of Long Term Prescribing. Pharm. World Sci. 2005, 27, 407–413. [Google Scholar] [CrossRef] [Scilit]
- Fick, D.M.; Semla, T.P.; Steinman, M.; Beizer, J.; Brandt, N.; Dombrowski, R.; DuBeau, C.E.; Pezzullo, L.; Epplin, J.J.; Flanagan, N. American Geriatrics Society 2019 Updated AGS Beers Criteria® for Potentially Inappropriate Medication Use in Older Adults. J. Am. Geriatr. Soc. 2019, 67, 674–694. [Google Scholar]
- Rognstad, S.; Brekke, M.; Fetveit, A.; Spigset, O.; Wyller, T.B.; Straand, J. The Norwegian General Practice (NORGEP) criteria for assessing potentially inappropriate prescriptions to elderly patients. Scand. J. Prim. Health Care 2009, 27, 153–159. [Google Scholar] [CrossRef] [Scilit]
- O’Mahony, D.; O’Sullivan, D.; Byrne, S.; O’Connor, M.N.; Ryan, C.; Gallagher, P. STOPP/START criteria for potentially inappropriate prescribing in older people: Version 2. Age Ageing 2015, 44, 213–218. [Google Scholar] [CrossRef] [Scilit]
- Kuhn-Thiel, A.M.; Weiß, C.; Wehling, M. Consensus Validation of the FORTA (Fit fOR The Aged) List: A Clinical Tool for Increasing the Appropriateness of Pharmacotherapy in the Elderly. Drugs Aging 2014, 31, 131–140. [Google Scholar] [CrossRef] [Scilit]
- Wehling, M. Arzneimitteltherapie im alter: Zu viel und zu wenig, was tun? Ein neues bewertungssystem: Fit for the aged (FORTA). Dtsch. Med. Wochenschr. 2008, 133, 2289–2291. [Google Scholar] [CrossRef] [Scilit]
- Winit-Watjana, W.; Sakulrat, P.; Kespichayawattana, J. Criteria for high-risk medication use in Thai older patients. Arch. Gerontol. Geriatr. 2008, 47, 35–51. [Google Scholar] [CrossRef] [Scilit]
- Rancourt, C.; Moisan, J.; Baillargeon, L.; Verreault, R.; Laurin, D.; Grégoire, J.-P. Potentially inappropriate prescriptions for older patients in long-term care. BMC Geriatr. 2004, 4, 9. [Google Scholar] [CrossRef] [Scilit]
- Poudel, A.; Ballokova, A.; Hubbard, R.; Gray, L.C.; Mitchell, C.A.; Nissen, L.M.; Scott, I. Algorithm of medication review in frail older people: Focus on minimizing the use of high-risk medications. Geriatr. Gerontol. Int. 2016, 16, 1002–1013. [Google Scholar] [CrossRef] [Scilit]
- McLeod, P.J.; Huang, A.R.; Tamblyn, R.M.; Gayton, D.C. Defining inappropriate practices in prescribing for elderly people: A national consensus panel. Can. Med. Assoc. J. 1997, 156, 385–391. [Google Scholar]
- Laroche, M.-L.; Charmes, J.-P.; Merle, L. Potentially inappropriate medications in the elderly: A French consensus panel list. Eur. J. Clin. Pharmacol. 2007, 63, 725–731. [Google Scholar] [CrossRef] [Scilit]
- Basger, B.J.; Chen, T.F.; Moles, R.J. Inappropriate Medication Use and Prescribing Indicators in Elderly Australians Development of a Prescribing Indicators Tool. Drugs Aging 2008, 25, 777–793. [Google Scholar] [CrossRef] [Scilit]
- Van der Spek, K.; Gerritsen, D.L.; Smalbrugge, M.; Nelissen-Vrancken, M.H.; Wetzels, R.B.; Smeets, C.H.; Zuidema, S.U.; Koopmans, R.T. A reliable and valid index was developed to measure appropriate psychotropic drug use in dementia. J. Clin. Epidemiol. 2015, 68, 903–912. [Google Scholar] [CrossRef] [Scilit]
- Holmes, H.M.; Sachs, G.A.; Shega, J.W.; Hougham, G.; Hayley, D.C.; Dale, W. Integrating Palliative Medicine into the Care of Persons with Advanced Dementia: Identifying Appropriate Medication Use. J. Am. Geriatr. Soc. 2008, 56, 1306–1311. [Google Scholar] [CrossRef] [Scilit]
- Kröger, E.; Wilchesky, M.; Marcotte, M.; Voyer, P.; Morin, M.; Champoux, N.; Monette, J.; Aubin, M.; Durand, P.J.; Verreault, R.; et al. Medication Use Among Nursing Home Residents With Severe Dementia: Identifying Categories of Appropriateness and Elements of a Successful Intervention. J. Am. Med. Dir. Assoc. 2015, 16, 629.e1–629.e17. [Google Scholar] [CrossRef] [Scilit]
- INFARMED. Deliberação 09/CD/2010. 2010. Available online: https://www.infarmed.pt/docu-428ments/15786/1219415/delib_09_CD_2010_Uni%25E3o_Miseric%25F3rdias%2520Portuguesas.pdf/4bb6580c-ec1a-4b6a-b2d4-4298cc1dddbb0a0 (accessed on 1 December 2021).
- Thomson, M.S.; Gruneir, A.; Lee, M.; Baril, J.; Field, T.S.; Gurwitz, J.H.; Rochon, P.A. Nursing Time Devoted to Medication Administration in Long-Term Care: Clinical, Safety, and Resource Implications. J. Am. Geriatr. Soc. 2009, 57, 266–272. [Google Scholar] [CrossRef] [Scilit]
- Alves-Conceição, V.; da Silva, D.T.; de Santana, V.L.; dos Santos, E.G.; Santos, L.M.C.; de Lyra, D.P. Evaluation of pharmacotherapy complexity in residents of long-term care facilities: A cross-sectional descriptive study. BMC Pharmacol Toxicol. 2017, 18, 59. [Google Scholar] [CrossRef] [Scilit]
- Fagundes, D.F.; Costa, M.T.; Alves, B.B.D.S.; Benício, M.M.S.; Vieira, L.P.; Carneiro, L.S.F.; Nascimento, O.J.M.; Junior, R.S.M. Prevalence of dementia in long-term care institutions: A meta-analysis. J. Bras. Psiquiatr. 2021, 70, 59–67. [Google Scholar] [CrossRef] [Scilit]
- Helvik, A.S.; Engedal, K.; Benth, J.Š.; Selbæk, G. Prevalence and Severity of Dementia in Nursing Home Residents. Dement. Geriatr. Cogn. Disord. 2015, 40, 166–177. [Google Scholar] [CrossRef] [Scilit]
- Curtin, D.; Gallagher, P.F.; O’Mahony, D. Explicit criteria as clinical tools to minimize inappropriate medication use and its consequences. Ther. Adv. Drug Saf. 2019, 10. [Google Scholar] [CrossRef] [Scilit]
- Chang, C.-B.; Chan, D.-C. Comparison of Published Explicit Criteria for Potentially Inappropriate Medications in Older Adults. Drugs Aging 2010, 27, 947–957. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).