


Abstract
Healthcare workforce planning continues to face entrenched challenges arising from the complex adaptive nature of health systems and the ongoing misalignment between workforce capabilities and system purpose. This paper introduces a conceptual meta-system framework grounded in systems and complexity thinking, positioning patient-centred care as the core system purpose and the guiding principle for workforce design. Drawing on the vortex model to visualise the nested layers of a health system—from individual care to national policy—the framework integrates interdependent domains, including system-level workforce needs. By synthesising global examples and varied planning strategies, the paper critiques the limitations of traditional linear forecasting and advocates for whole-system, needs-based approaches that embed dynamic feedback and stakeholder collaboration. It underscores the importance of strong partnerships between education and practice and highlights the role of adaptive leadership in aligning workforce planning with organisational purpose. Rather than offering prescriptive solutions, the framework serves as a catalyst for critical reflection, encouraging policymakers and healthcare leaders to tailor workforce strategies to their specific contexts. Ultimately, this conceptual approach seeks to enhance system resilience, improve health outcomes, and reduce future care demands through genuine alignment between workforce planning and the evolving needs of patients and health systems.
1. Introduction
Yogi Berra famously said, “If you don’t know where you are going, you’ll end up somewhere else.” This statement perfectly captures the challenges of managing complex problems, those that arise within organisations and simultaneously are influenced by external stakeholders. In Russell Ackoff’s words: “Managers are not confronted with problems that are independent of each other, but with dynamic situations that consist of complex systems of changing problems that interact with each other” [1].
Healthcare systems function as complex adaptive systems (CAS) [2,3]—dynamic networks of diverse, interdependent agents (patients, professionals, organisations, and policies) whose interactions are nonlinear, unpredictable, and constantly adapting to internal and external influences. In CAS, collective behaviour emerges from the interactions of its parts rather than the behaviour of any single part. Outcomes—such as care quality, efficiency, or workforce well-being—cannot be traced simply to linear interventions, rather, they arise through feedback, self-organisation, and adaptation inherent in the system’s dynamic interactions.
Effectiveness depends on clarity of purpose, defining: Why are we here? and What do we want to achieve? [4,5,6,7]. Recent health systems research findings showed that ambiguity in the system’s purpose invariably leads to fragmentation and policy misalignment [7,8].
Workforce planning failures often arise from the disconnect between system purpose and workforce capability, compounded by insufficient attention to the distinctive characteristics of local operating environments [9,10,11,12]. Applying systems and complexity thinking—an approach that examines a system’s structure, boundaries, and dynamic interactions—enables policymakers and leaders to recognise nonlinearity, feedback, and contextual variability that conventional planning frameworks frequently overlook [13,14,15,16].
Organisational research emphasises that a shared understanding of purpose and strategic alignment are key drivers of an organisation’s design and effectiveness [5,6,7]. Poor system function results from poor design; hence, meaningful improvement invariably requires system redesign [7].
This paper examines the complexities of healthcare workforce planning, a multifaceted challenge shaped by interdependencies both within and beyond the boundaries of the healthcare system [9,10,11,12].
2. Systems and Complexity Thinking to Guide Multi-Stakeholder Design
The paper approaches workforce planning through a complex adaptive systems lens. It posits that the healthcare system is a dynamic, interconnected organisation whose effectiveness depends fundamentally on its core purpose—to deliver care that meets patients’ needs [7,17,18].
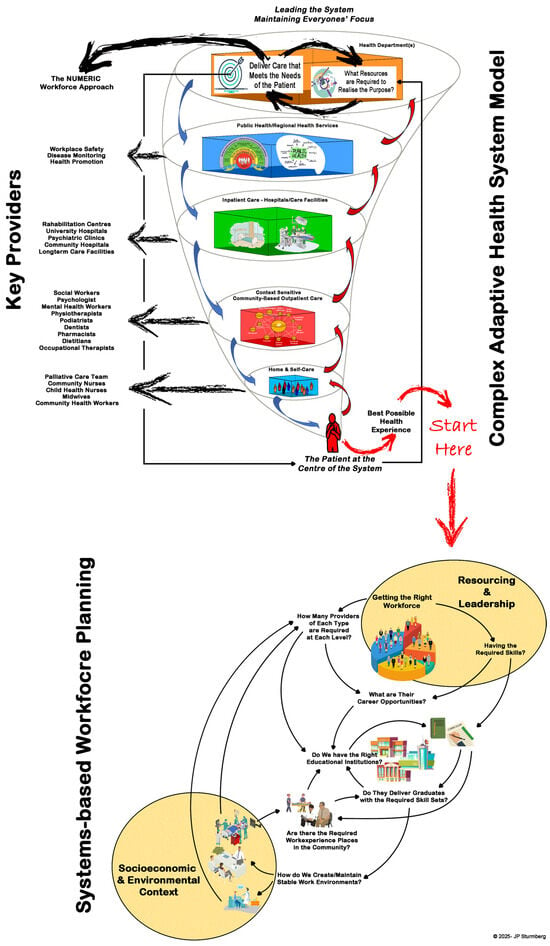
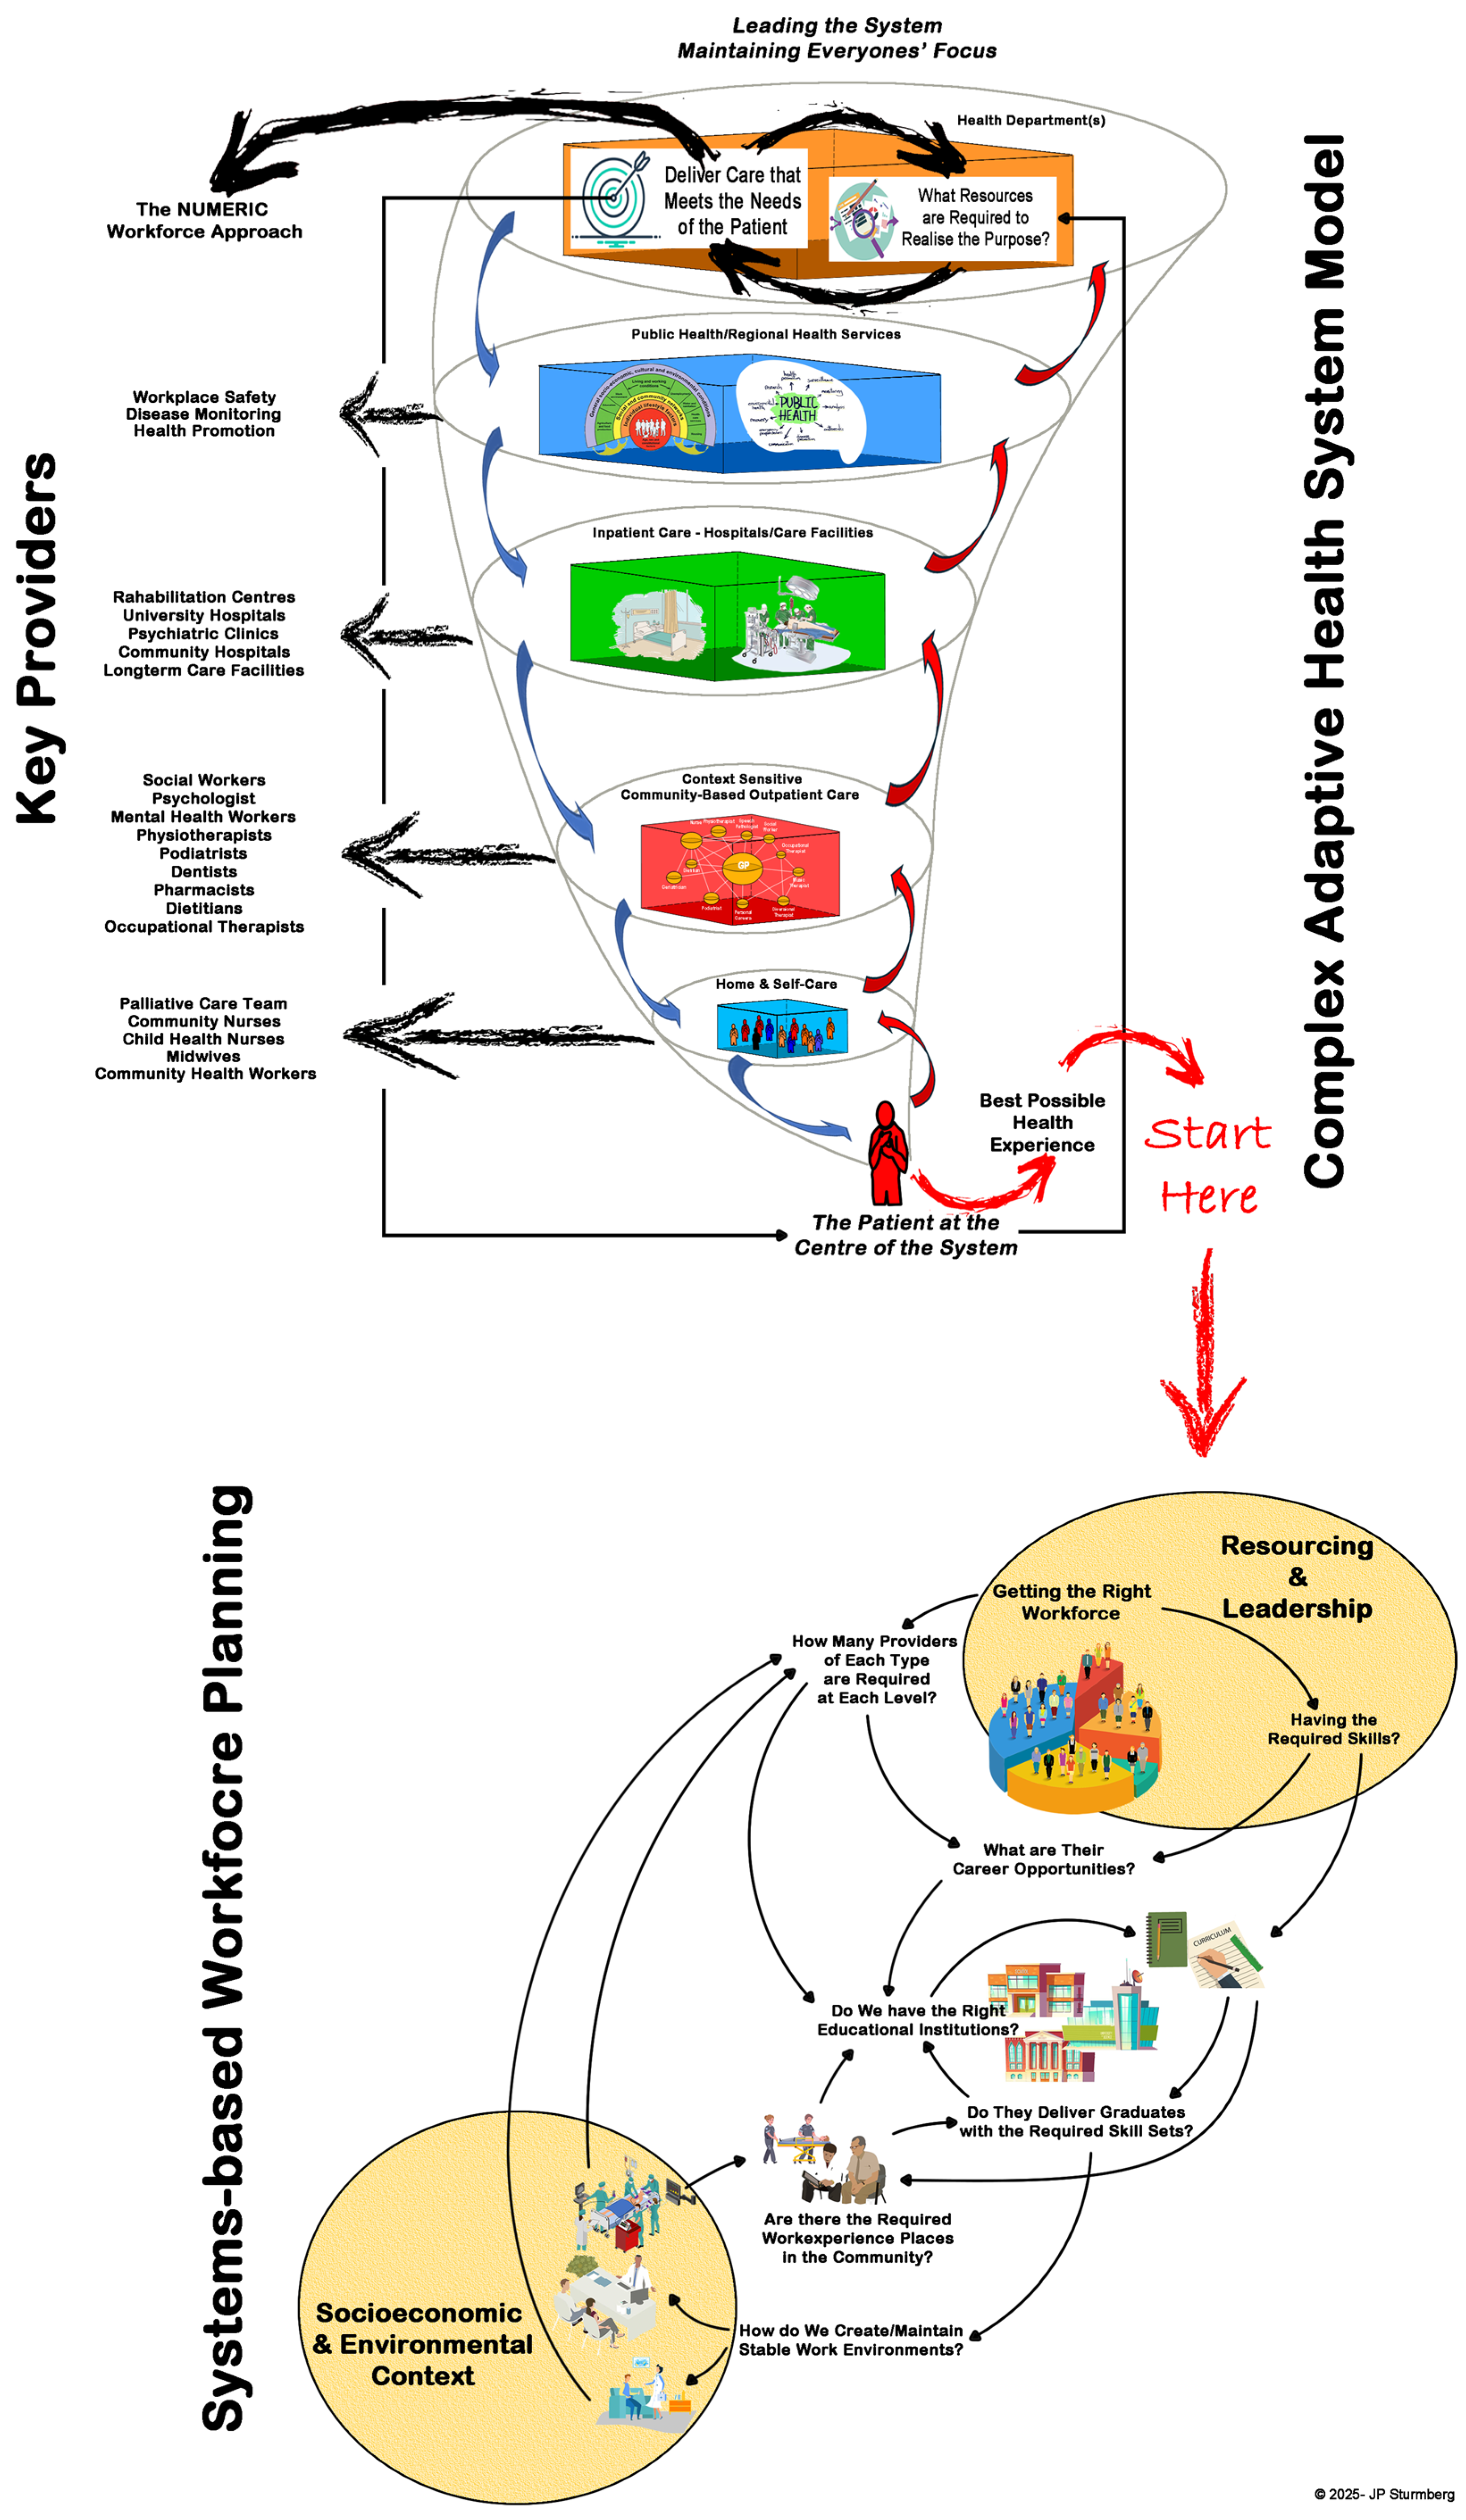
It further posits that the vortex metaphor offers a useful visualisation of a “nested system”, centered on the patient and expanding upwards through functional layers from primary care, to secondary and tertiary care, community care, regional care, and finally national care policy (Figure 1 top) [3].
Figure 1.
The vortex model of the healthcare system as the starting point for systemic workforce planning.
And lastly, it posits that designing an efficient, resilient health system depends on multi-stakeholder participatory model building [19], which brings together patients, clinicians and allied health professionals, administrators, community representatives, industry, and policymakers. Such collaboration forms the foundation for co-creating context-sensitive effective, efficient and resilient health system models [19,20,21,22].
Visualisation–Deepening System Understanding
Mapping structural relationships across a system’s organisational layers is fundamental to system and complexity thinking. By “seeing” the system, stakeholders can gain a nuanced understanding of the structural relationships and dynamic interactions amongst its components. This approach is crucial for recognising nonlinear behaviours driven by feedback loops that give rise to emergent outcomes, i.e., the rise in novel patterns, properties, or behaviours that cannot be predicted by analysing individual components in isolation.
Dissolving dysfunctions perpetuated by feedback requires systems and complexity thinking—solutions must eliminate the immediate issue of concern and simultaneously improve the function of contributing domains [23].
3. Workforce Planning “Beyond Bumps on Seats”
Although current workforce planning strategies often claim to be “adaptive”, most remain constrained by an internal organisational focus, with scenario planning being a notable exception (Table 1). This inward orientation could be characterised as “bumps on seats” over purpose—counting bodies rather than aligning workforce planning with an organisation’s core purpose. In healthcare, that purpose lies foremost in understanding patients’ care needs within their contextual operating/living environments.
Table 1.
What Organisations Are Doing Now (as outlined by various workforce management organisations).
A whole-of-system perspective transcends previous workforce research which has typically focused narrowly on issues arising at subsystem levels. Examples include expanding services at a maternity care clinic on additional time demands [24] (Figure 2), specific workplace settings like general practice [25] (Figure 3), or national health system reform [26] (Figure 4).
Focusing on patients’ care needs demands a nuanced approach that addresses complexities amongst provider roles, skills, and the inherent dynamics at every organisational level. While a systems-based perspective entails strong partnerships between education and practice [10], it also necessitates an adaptive leadership style [27,28] to create conditions that attract, develop, and retain skilled providers committed to maintain their focus on realising the system’s purpose.
Figure 2.
Integrating HIV, syphilis, malaria and anaemia point-of-care testing (POCT) for antenatal care at dispensaries in western Kenya: discrete-event simulation modelling of operational impact (modified from [24] under Creative Commons Attribution 4.0 licence).
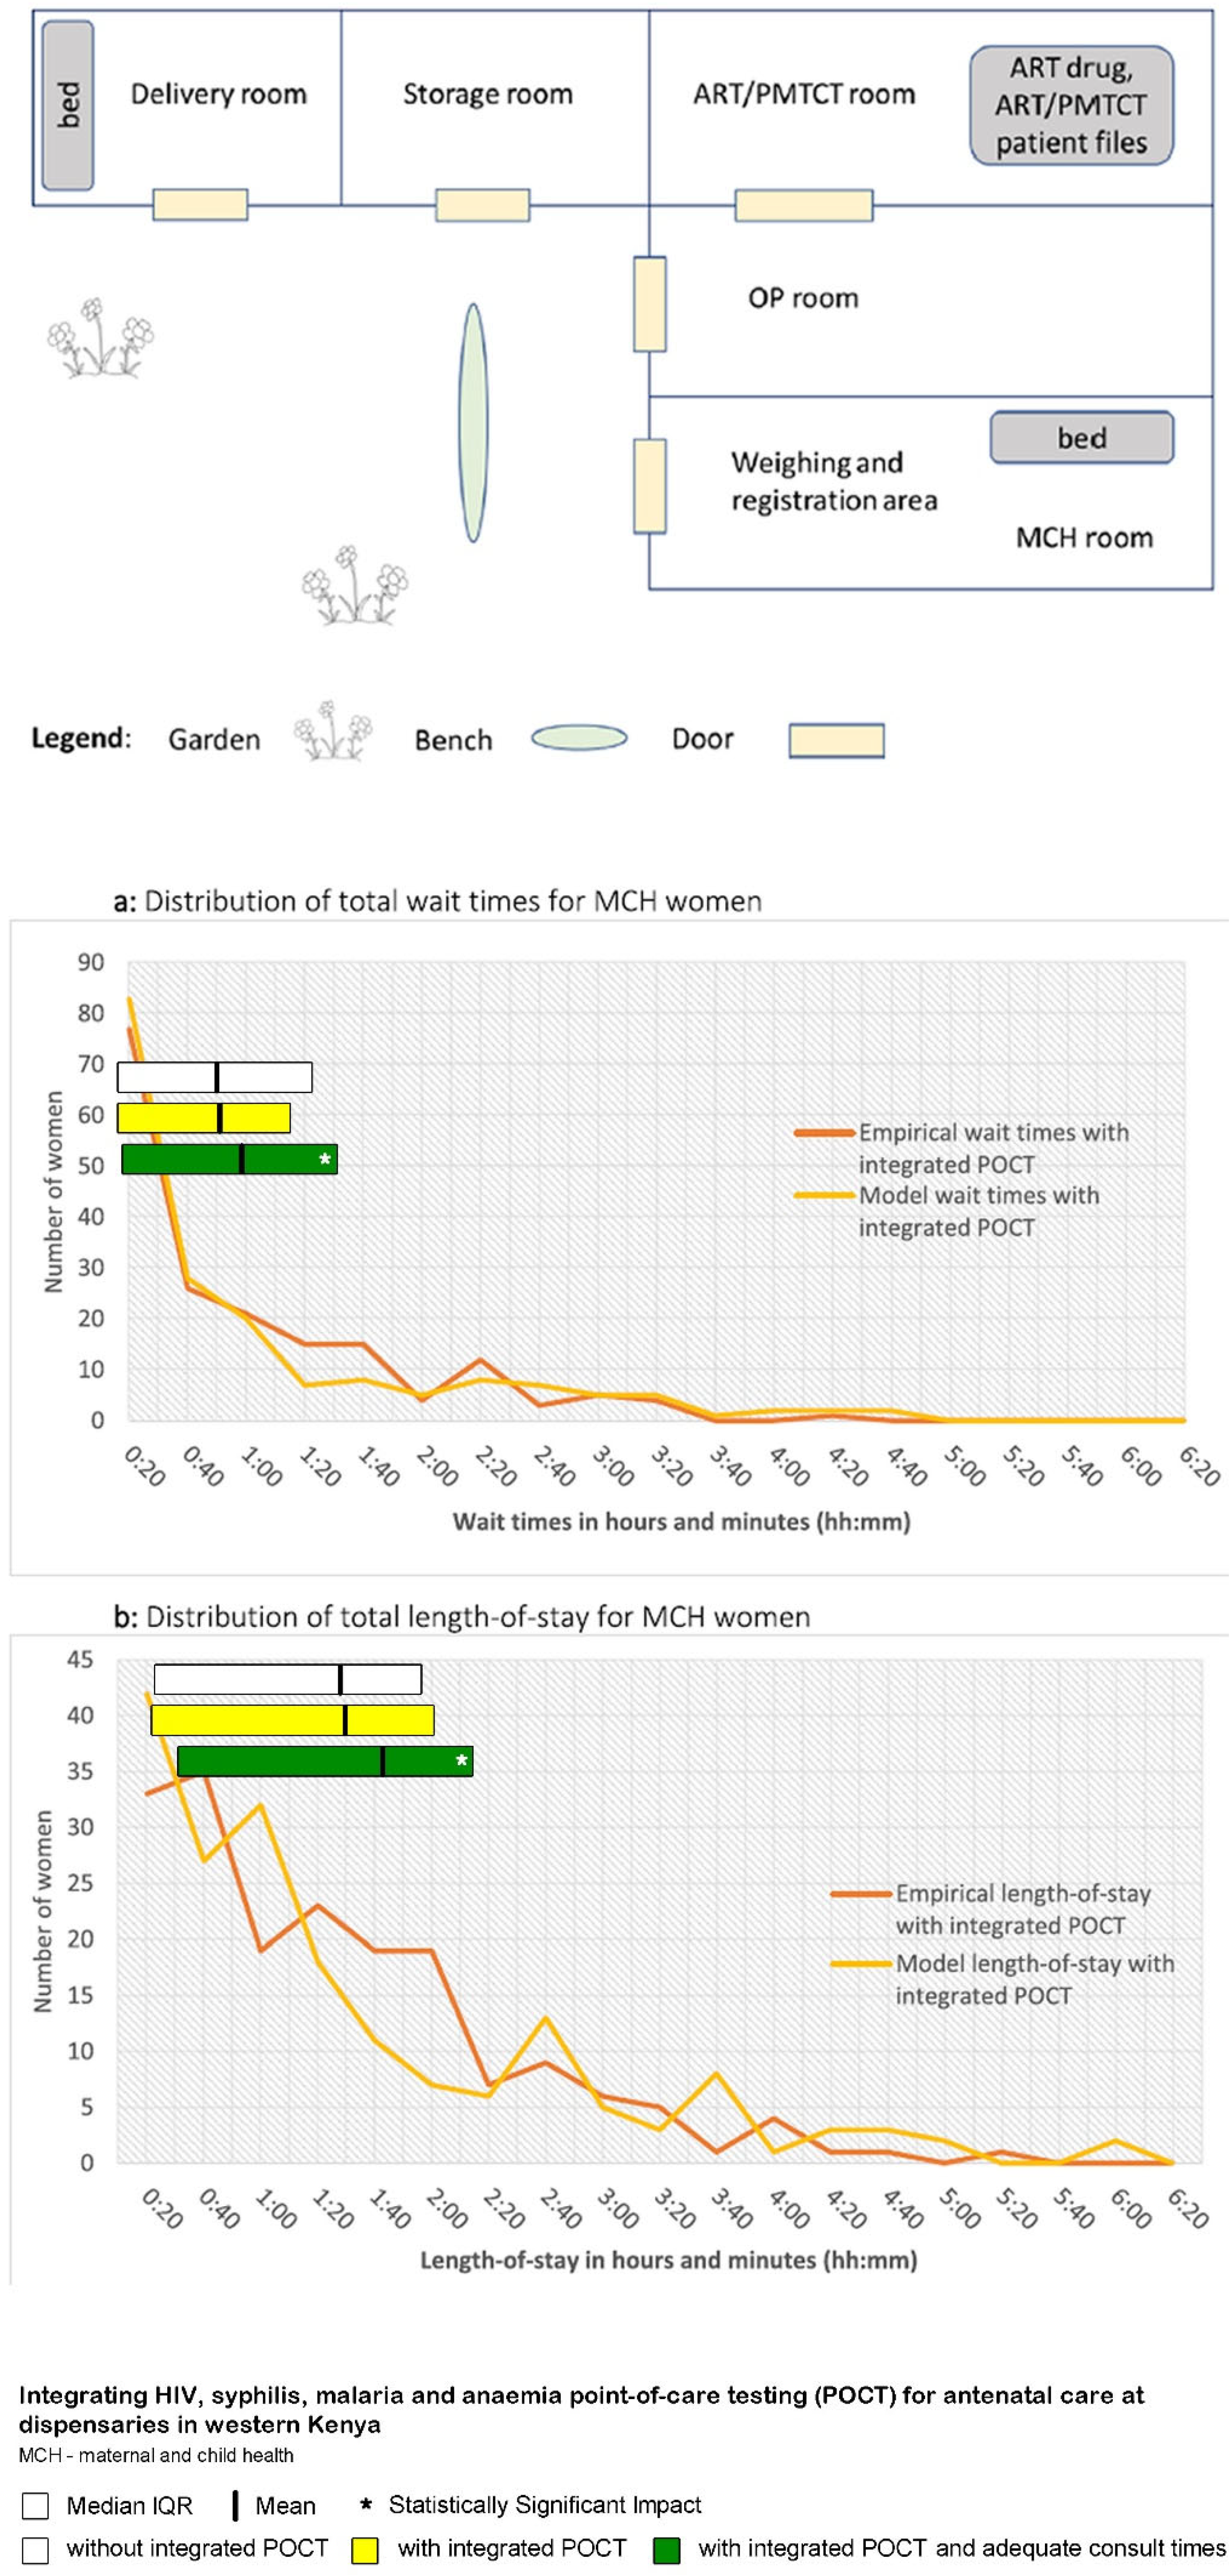
The study asked: How does providing four point-of-care tests for ANC affect nurse utilisation and wait times for women seeking maternal and child health services in western Kenya?
Integrating POCT had minimal pragmatic effects on patients or staff—waiting time increased by a mean of 2 min, or 9 min when associated with an adequate length of ante-natal consultation. Increase in mean length of stay at the clinic was 2 min, or 16 min when associated with an adequate length of ante-natal consultation. Overall, introducing POCT had minimal impact on the nurses’ overall workload.
Figure 3.
General practice work and workforce. Interdependencies between demand, supply and quality [25].
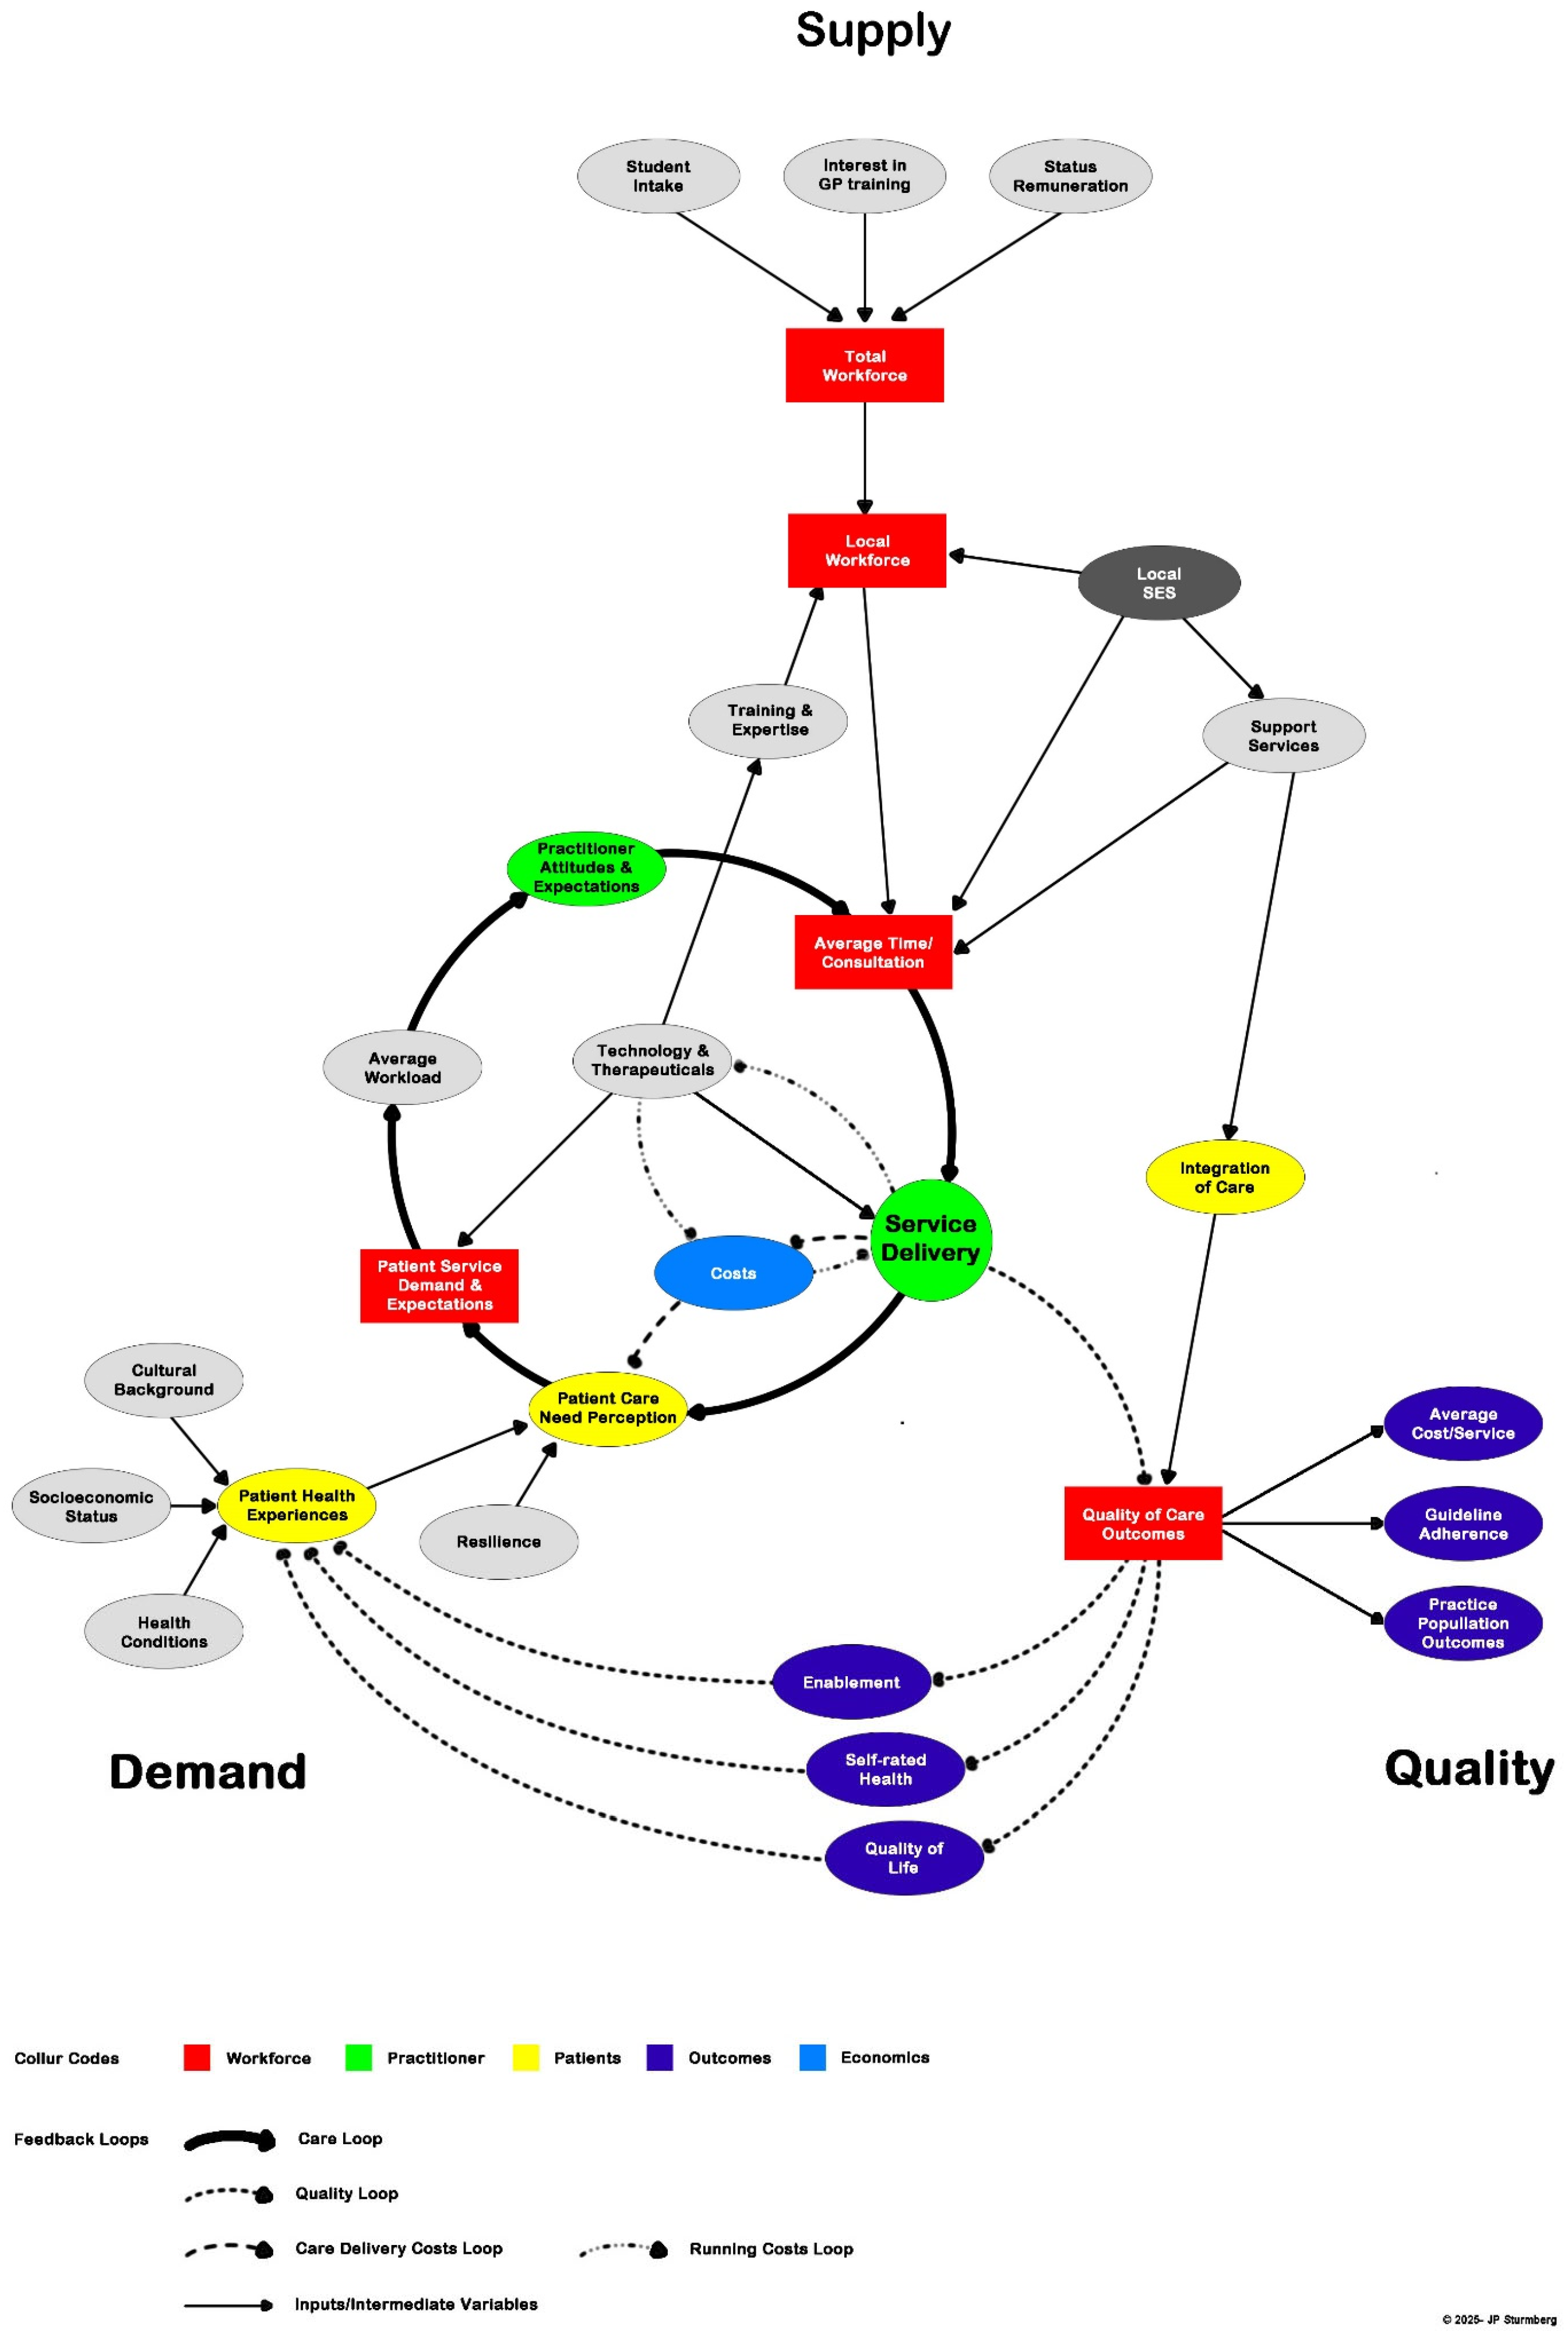
The study asked: How does the nature of general practice work affect people and their health outcomes and experiences?
The interdependencies of general practice work arise from three areas: “patient demands”, “provider supply” and “quality-of-care outcomes”—the thick central loop describes general practice care: service delivery influences patient care need perceptions and generates patient demand and expectations. The level of actual demand determines the average workload; workload has an impact on practitioners’ attitudes and expectations (burn-out), which affect—contingent on local circumstances—the length of consultations, which in turn has an impact on service delivery.
A related loop shows the impact of service delivery on the quality-of-care and patient-related outcomes, which in turn has an additional impact on patient care needs and perceptions.
Note: Agents contributing to the key variables are in grey ovals, e.g., the “total general practice workforce” depends on policies of “student intake”, “interest in general practice training” and the “status and relative remuneration differential” with specialist medical practitioners, while patient factors like “health conditions”, “SES status” and “cultural background” shape patients’ health experiences, which in turn are modified by the “quality-of-care” outcomes. Changes to such variables have a significant impact on the demand for care and the work demand of practitioners.
Figure 4.
System dynamics modelling of health workforce planning to address future challenges of Thailand’s Universal Health Coverage (modified from [26] under Creative Commons Attribution 4.0 licence).
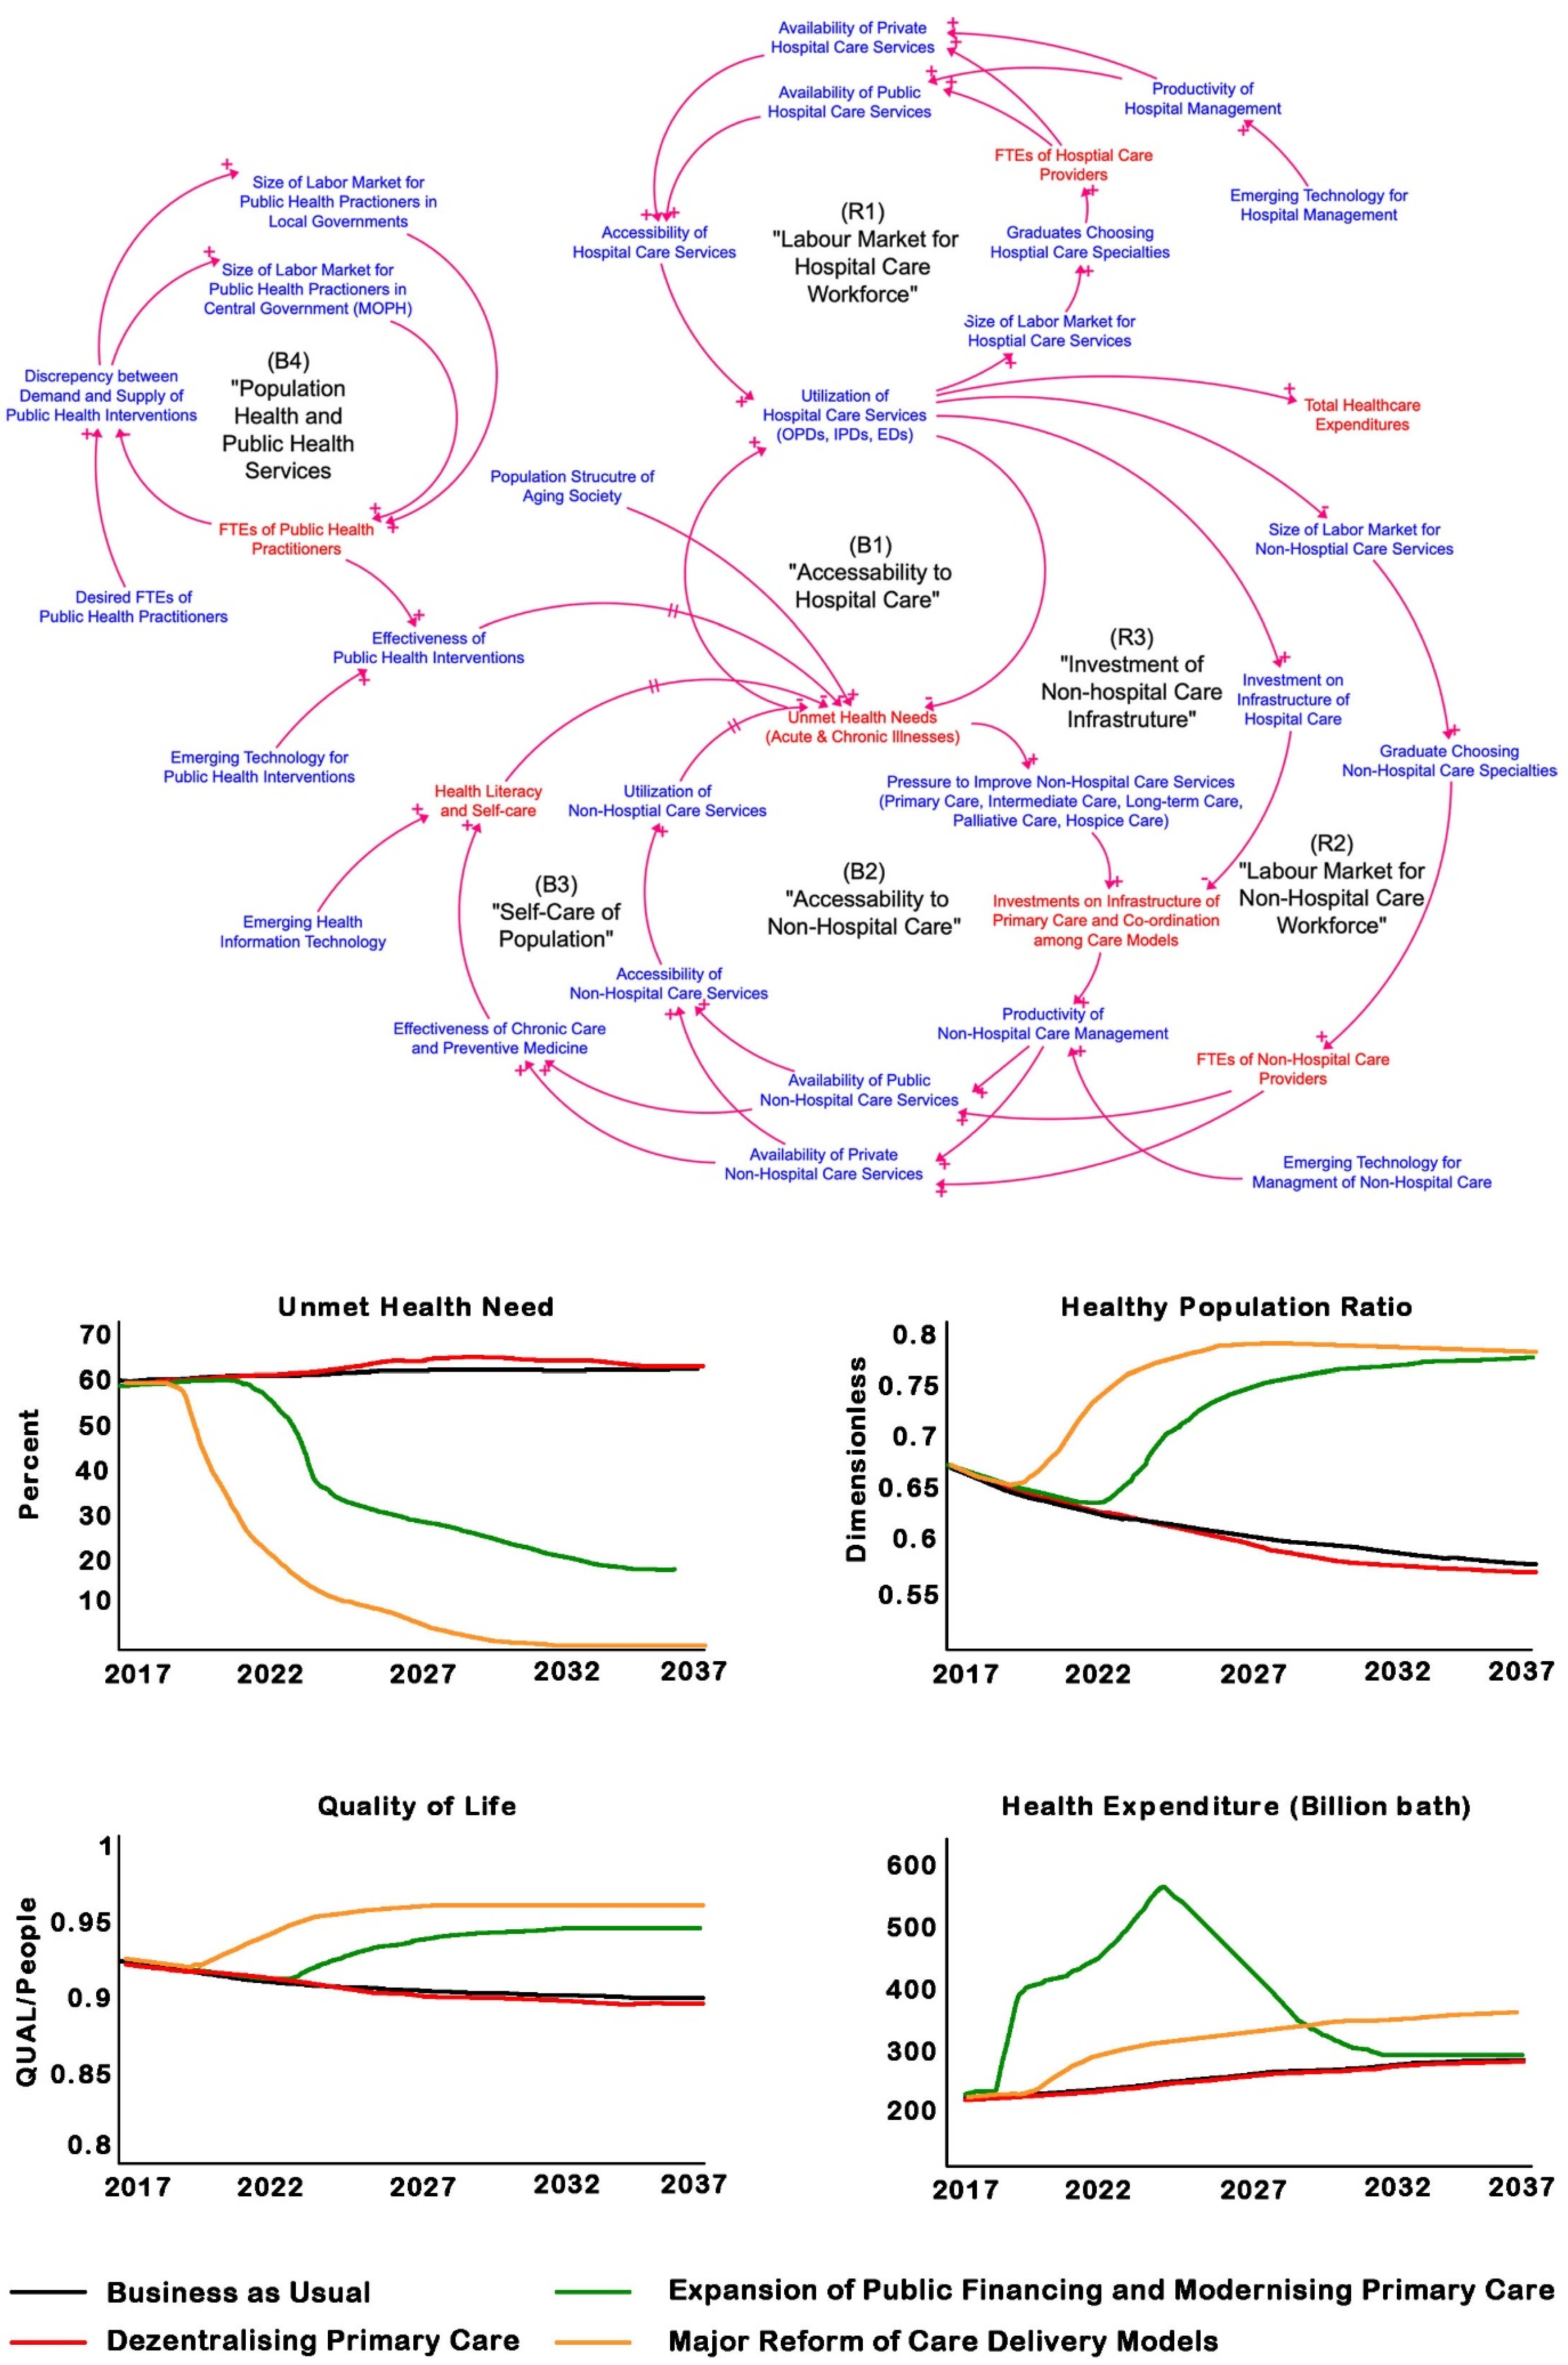
The study asked: What are the potential consequences of three policy changes on “unmet health needs”, “population health”, “quality of life” and “health expenditure”?
The Major Reform of Care Delivery Models—with a major focus on increasing non-hospital workforce, has the greatest impact on reducing “unmet health needs”, increasing “population health” and “quality of life”, at a modest but constantly rising “health expenditure”.
Systems-based workforce planning must therefore focus on the following key interconnected and interdependent domains:
- Understanding System Levels and Workforce Needs
- Each level of the health system must be analysed for its unique structure and function, identifying both the types of providers needed and the specific skill sets required.
- Determining optimal workforce size involves assessing not only the time required to deliver care but also the dynamic interactions among providers within and across system levels.
- Effective care delivery hinges on access to essential resources, which must be incorporated into workforce planning.
- Influences on Workforce Recruitment and Retention
- Attracting and retaining the necessary workforce is shaped by factors such as remuneration and career opportunities, which influence whether individuals choose to pursue and remain in specific health professions.
- The appeal of a health career is closely tied to the perceived value of the work, available career pathways, and the support provided during education and training.
- The Role of Education and Training
- Most health professional education occurs outside the direct purview of the health system, yet producing graduates with the right skills requires close collaboration between educational institutions and healthcare professionals.
- Effective curriculum co-design and guaranteed access to work experience placements are essential. The availability and quality of these placements depend on the practicing workforce’s capacity to teach and serve as positive role models, which in turn reinforces the attractiveness of the profession.
- Leadership and System Alignment
- Adaptive leadership is crucial for navigating the complexities of workforce planning and “optimal” care delivery. Leaders must ensure planning aligns with the overarching purpose of the health system.
- Responsibilities include ensuring necessary resources, fostering desirable workplace conditions, collaborating with education providers, and empowering staff to coordinate care, especially regarding the social determinants of health, to achieve “best possible” patient outcomes.
The bottom section of Figure 1 illustrates the interdependencies inherent in a systemic health workforce planning approach that embodies these core principles—patient needs inform workforce skills and numbers, which in turn guide health education strategies, including the integration of workplace exposure and experiences. Context-responsive education nurtures the development of a skilled and motivated workforce capable of adapting to emerging clinical challenges. This systems-based planning approach relies equally on adaptive leadership and adequate resourcing.
This approach represents a meta-cognitive process, that is more likely “to get it right” in Ackoff’s sense, seeking to dissolve rather than merely solve a problem [1]—addressing the workforce crisis while simultaneously enhancing the performance across related domains.
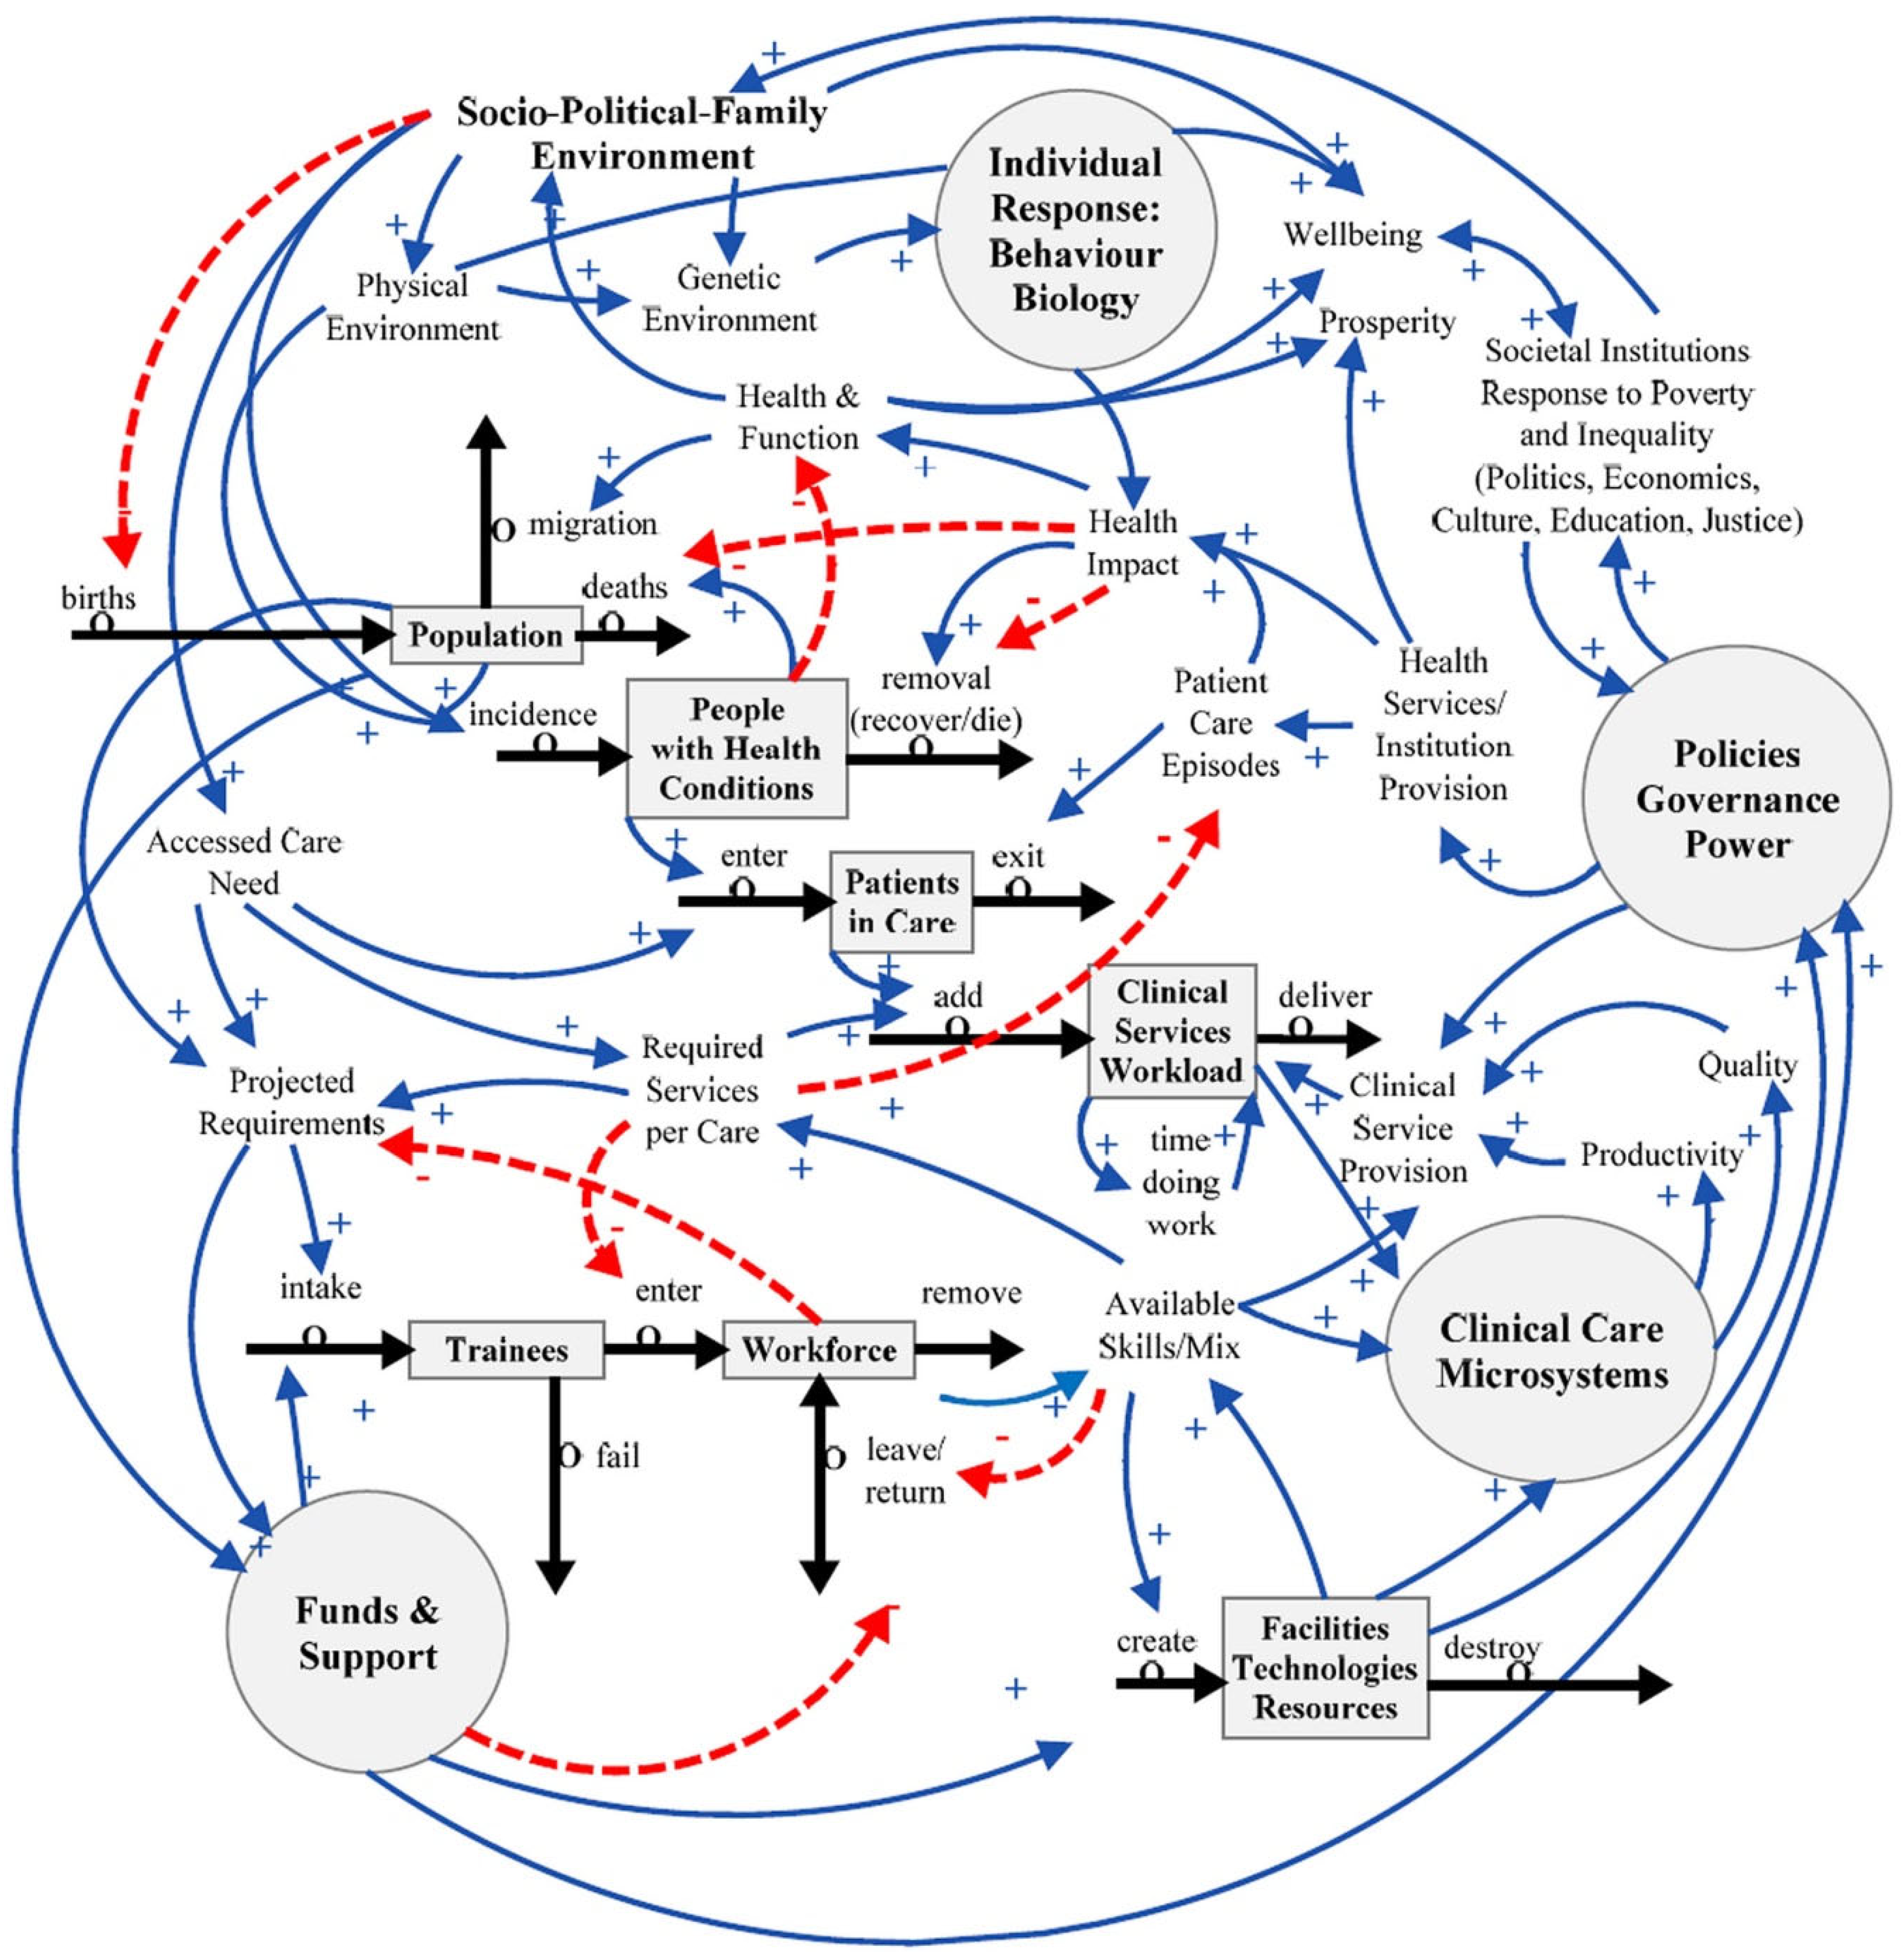
Masnik and McDonnell [29] first outlined a systemic approach to workforce modelling (Figure 5) that captured many dimensions articulated in the health vortex model.
Figure 5.
A model linking clinical workforce skill mix planning to health and healthcare dynamics (reproduced from [29] under Creative Commons Attribution 2.0 licence).
The study asked: How to best manage the appropriate skills mix of personnel in the clinical workforce given the dynamic complexities between health and healthcare?
Dynamic modelling can provide leadership the ability for informed and co-ordinated planning in a real-world context.
Despite the clear advantages of a whole-of-system framework, practical challenges remain. Data fragmentation and siloed information systems often hinder the development of a comprehensive view of workforce needs and trends. Power imbalances among stakeholders can marginalise important perspectives, leading to solutions that may not fully address the needs of the entire system. Furthermore, the diversity of local contexts means that strategies succeeding in one context may not be transferable to another, or put differently, there is seldom a “one size fits all” answer.
By embracing a systems-thinking approach—focused on feedback, adaptability, and context-specific solutions—healthcare organisations can strengthen workforce planning, bolster resilience, and ultimately advance patient care.
4. Discussion
Siloed, linear approaches to workforce planning continue to be promoted [30], yet have come under increasing scrutiny, e.g., Rees et. al. call for a shift from linear forecasting to a normative backcasting approach [31]. Sutten et al., based on an extensive literature review, conclude that workforce planning would greatly benefit from adopting a whole-system, needs-based approach that accounts for demographic trends, epidemiology, and evolving service requirements [32], Table 2 contrasts various workforce planning approaches, highlighting their respective focuses, strengths and limitations.
Table 2.
Comparing Different Workforce Planning Approaches.
While linear forecasting methods rely on historical trends and straightforward projections, applying systems and complexity thinking to healthcare workforce planning—centered on patients’ care needs—offers significant advantages for “getting it right” [33]. By mapping the structure and dynamics of the healthcare system, systems and complexity thinking approaches reduce uncertainty and foster a shared understanding amongst all stakeholders of how their actions and decisions interact. Such alignment is essential for building resilience (an emerging system property) within the system enabling coordinated efforts and a unified direction among clinicians, administrators, educators, and policymakers. Systems thinking promotes holistic problem-solving [14,15,16], encourages adaptive leadership [27], and supports designing workforce strategies that are flexible, context-sensitive, and aligned with the evolving needs of patients and the broader system [34,35,36,37,38].
A defining feature of systems thinking is its focus on feedback mechanisms. Organisations that recognise both stabilising and reinforcing feedback loops can adapt their strategies to evolving circumstances. This context-sensitive adaptation is crucial for maintaining resilience—being an emergent system property—as it enables the system to respond flexibly to new challenges, prevent stagnation, and avoid the escalation of problems. In doing so, systems thinking nurtures a culture of continuous improvement and informed decision-making [39].
The framework outlined here is not intended as a prescriptive solution, but rather as a conceptual catalyst for debate and reflection “amongst people with a problem” [40]. Its purpose is to encourage stakeholders to critically examine their current workforce planning practices within the complex realities they face, recognising that lasting solutions in healthcare workforce planning are rarely universal and must instead be adapted thoughtfully to the specific needs and context of each setting.
This paper offers the first meta-system perspective on workforce planning, viewing the healthcare system as an integrated whole that acknowledges the interconnectedness of its multiple layers, domains, and dynamics. This approach aims to facilitate the design of policies and strategies capable of addressing these complex, interdependent elements simultaneously. The outcomes of such a systemic workforce planning framework are emergent, arising from a top-down and bottom-up purpose-driven perspective on the health system centred on meeting patients’ needs that simultaneously enables the achievement of best possible health outcomes. Effectively meeting patient needs not only enhances quality of care and improves health experiences but also reduces future care demands [41,42,43].
5. Conclusions
Effective healthcare workforce planning requires a shift from the widely adopted linear forecasting approach to embracing a systems and complexity thinking framework. The nested vortex model provides a clear visualisation of the multi-layered system structures and dynamic interactions within health systems, which is vital for workforce design that aligns with these complexities. Achieving meaningful and sustainable outcomes depends on inclusive stakeholder engagement, acknowledging feedback loops, and fostering adaptive leadership. Together, these elements enable strategic interventions that build system resilience and deliver adaptive high-quality, patient-centered care in constantly evolving environments. As this conceptual meta-system framework has not yet been practically implemented, its real-world effectiveness and adaptability present a valuable opportunity for healthcare leaders and policymakers to pilot, refine, and rigorously evaluate its application across diverse community settings.
Funding
This research received no external funding.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The author declares no conflicts of interest.
References
- Ackoff, R.L. Redesigning the Future: A Systems Approach to Societal Problems; John Wiley & Sons: New York, NY, USA, 1974. [Google Scholar]
- Anderson, R.A.; McDaniel, R.R. Managing Health Care Organizations: Where Professionalism Meets Complexity Science. Health Care Manag. Rev. 2000, 25, 83–92. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sturmberg, J.; O’Halloran, D.; Martin, C. Understanding health system reform—A complex adaptive systems perspective. J. Eval. Clin. Pract. 2012, 18, 202–208. [Google Scholar] [CrossRef] [Scilit]
- Sinek, S. Start with Why: How Great Leaders Inspire Everyone to Take Action; Portfolio: New York, NY, USA, 2009. [Google Scholar]
- Collins, J.C.; Porras, J.I. Built to Last: Successful Habits of Visionary Companies; Random House: London, UK, 2000. [Google Scholar]
- Ackoff, R.L.; Magidson, J.; Addison, H.J. Idealized Design: Creating an Organization’s Future; Wharton School Publishing: Upper Saddle River, NJ, USA, 2006. [Google Scholar]
- Sturmberg, J.P. Health System Redesign: How to Make Health Care Person-Centered, Equitable, and Sustainable; Springer: Cham, Switzerland, 2018. [Google Scholar]
- Braithwaite, J. Changing how we think about healthcare improvement. BMJ 2018, 361, k2014. [Google Scholar] [CrossRef] [Scilit]
- Kuhlmann, E.; Lotta, G.; Dussault, G.; Falkenbach, M.; Correia, T. The workforce crisis in healthcare: Moving the debate to bridge evidence and policy. Int. J. Health Policy Manag. 2024, 39, 607–613. [Google Scholar] [CrossRef] [Scilit]
- Sturmberg, J.P.; Gainsford, L.; Goodwin, N.; Pond, D. Systemic failures in nursing home care—A scoping study. J. Eval. Clin. Pract. 2024, 30, 484–496. [Google Scholar] [CrossRef] [Scilit]
- Correia, T.; Kuhlmann, E.; Lotta, G.; Beja, A.; Morais, R.; Zapata, T.; Campbell, J. Turning the global health and care workforce crisis into action: The pathway to effective evidence-based policy and implementation. Int. J. Health Plan. Manag. 2025, 40, 224–233. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baumann, B. Workforce Planning Inefficiencies Created by Siloed Enterprise Systems. 2025. Available online: https://www.panorama-consulting.com/workforce-planning-inefficiencies-created-by-siloed-erp-systems/ (accessed on 27 October 2025).
- Meadows, D.H. Thinking in Systems: A Primer; Wright, D., Ed.; Chelsea Green Publishing Company: White River Junction, VT, USA, 2009. [Google Scholar]
- Haynes, A.; Garvey, K.; Davidson, S.; Milat, A. What Can Policy-Makers Get Out of Systems Thinking? Policy Partners’ Experiences of a Systems-Focused Research Collaboration in Preventive Health. Int. J. Health Policy Manag. 2020, 9, 65–76. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sturmberg, J.P. Without Systems and Complexity Thinking There Is no Progress—Or Why Bureaucracy Needs to Become Curious; Comment on “What Can Policy-Makers Get out of Systems Thinking? Policy Partners’ Experiences of a Systems-Focused Research Collaboration in Preventive Health”. Int. J. Health Policy Manag. 2020, 11, 409–413. [Google Scholar] [CrossRef] [Scilit]
- Khan, S. Overcoming Barriers to Applying Systems Thinking Mental Models in Policy-Making Comment on “What Can Policy-Makers Get Out of Systems Thinking? Policy Partners’ Experiences of a Systems-Focused Research Collaboration in Preventive Health”. Int. J. Health Policy Manag. 2021, 10, 281–283. [Google Scholar] [CrossRef] [Scilit]
- Mayo, W.J. The necessity of cooperation in medicine. Mayo Clin. 1910, 2, 557–566. [Google Scholar] [CrossRef] [Scilit]
- Berry, L.; Seltman, K. Management Lessons from Mayo Clinic: Inside One of the World’s Most Admired Service Organizations; McGraw-Hill: New York, NY, USA, 2008. [Google Scholar]
- Estrada-Magbanua, W.M.; Huang, T.T.; Lounsbury, D.W.; Zito, P.; Iftikhar, P.; El-Bassel, N.; Gilbert, L.; Wu, E.; Lee, B.Y.; Mateu-Gelabert, P.; et al. Application of group model building in implementation research: A systematic review of the public health and healthcare literature. PLoS ONE 2023, 18, e0284765. [Google Scholar] [CrossRef] [Scilit]
- Siokou, C.; Morgan, R.; Shiell, A. Group model building: A participatory approach to understanding and acting on systems. Public. Health Res. Pract. 2014, 25, e2511404. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khayal, I.S.; Campbell, A.M.; Farid, A.M. Enhancing the adaptability of healthcare delivery as a complex system. Procedia Comput. Sci. 2025, 268, 113–121. [Google Scholar] [CrossRef] [Scilit]
- McBeth, R.; Sandberg, C.; Varewny, V.; Piggott, B.; Ajani, A.; Auger, S.; Campbell-Scherer, D.; Dong, K.; Hyshka, E.; Srinivasan, C.; et al. Co-creating health system innovation with people who use drugs. Harm Reduct. J. 2025, 22, 176. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ackoff, R.L. Re-Creating the Corporation: A Design of Organizations for the 21st Century; Oxford University Press: Cary, NC, USA, 1999. [Google Scholar]
- Young, N.; Taetgmeyer, M.; Zulaika, G.; Aol, G.; Desai, M.; Ter Kuile, F.; Langley, I. Integrating HIV, syphilis, malaria and anaemia point-of-care testing (POCT) for antenatal care at dispensaries in western Kenya: Discrete-event simulation modelling of operational impact. BMC Public Health 2019, 19, 1629. [Google Scholar] [CrossRef] [Scilit]
- Sturmberg, J.P.; M O’Halloran, D.; McDonnell, G.; M Martin, C. General practice work and workforce. Aust. J. Gen. Pract. 2018, 47, 507–513. [Google Scholar] [CrossRef] [Scilit]
- Leerapan, B.; Teekasap, P.; Urwannachotima, N.; Jaichuen, W.; Chiangchaisakulthai, K.; Udomaksorn, K.; Meeyai, A.; Noree, T.; Sawaengdee, K. System dynamics modelling of health workforce planning to address future challenges of Thailand’s Universal Health Coverage. Human. Resour. Health 2021, 19, 31. [Google Scholar] [CrossRef] [Scilit]
- Uhl-Bien, M.; Arena, M. Complexity leadership: Enabling people and organizations for adaptability. Organ. Dyn. 2017, 46, 9–20. [Google Scholar] [CrossRef] [Scilit]
- Khan, S.; Vandermorris, A.; Shepherd, J.; Begun, J.W.; Lanham, H.J.; Uhl-Bien, M.; Berta, W. Embracing uncertainty, managing complexity: Applying complexity thinking principles to transformation efforts in healthcare systems. BMC Health Serv. Res. 2018, 18, 192. [Google Scholar] [CrossRef] [Scilit]
- Masnick, K.; McDonnell, G. A model linking clinical workforce skill mix planning to health and health care dynamics. Hum. Resour. Health 2010, 8, 11. [Google Scholar] [CrossRef] [Scilit]
- Zhu, Z.; Zheng, W.; Tang, N.; Zhong, W. Review of Manpower Management in Healthcare System: Strategies, Challenges, and Innovations. J. Multidiscip. Healthc. 2024, 17, 5341–5351. [Google Scholar] [CrossRef] [Scilit]
- Rees, G.H.; Willis, G.; Scotter, C. Health workforce planning should be strategy or policy-driven: From linear forecasts to normative futures. Health Policy 2025, 161, 105440. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sutton, C.; Prowse, J.; McVey, L.; Elshehaly, M.; Neagu, D.; Montague, J.; Alvarado, N.; Tissiman, C.; O’Connell, K.; Eyers, E.; et al. Strategic workforce planning in health and social care—An international perspective: A scoping review. Health Policy 2023, 132, 104827. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sturmberg, J.P.; O’Halloran, D.M.; Martin, C.M. People at the centre of complex adaptive health systems reform. Med. J. Aust. 2010, 193, 474–478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barasa, E.; Mbau, R.; Gilson, L. What Is Resilience and How Can It Be Nurtured? A Systematic Review of Empirical Literature on Organizational Resilience. Int. J. Health Policy Manag. 2018, 7, 491–503. [Google Scholar] [CrossRef] [Scilit]
- Forsgren, L.; Tediosi, F.; Blanchet, K.; Saulnier, D.D. Health systems resilience in practice: A scoping review to identify strategies for building resilience. BMC Health Serv. Res. 2022, 22, 1173. [Google Scholar] [CrossRef] [Scilit]
- Sturmberg, J.; Ridde, V.; Brown, G.; Paul, E. Health System Resilience—The Foundation For Pandemic Preparedness. Health Aff. Forefr. 2023. [Google Scholar] [CrossRef] [Scilit]
- Asfoor, D.A.; Tabche, C.; Zidjali, M.A.; Mataria, A.; Saikat, S.; Rawaf, S. Concept analysis of health system resilience. Health Policy Policy Syst. 2024, 22, 43. [Google Scholar] [CrossRef] [Scilit]
- Chamberlain, S. Workforce Planning Within a System. 2017. Available online: https://recipeforworkforceplanning.hee.nhs.uk/Portals/0/HEWM_Cookbooks/Workforce%20Planning%20within%20a%20System%20Guidance%20Document.pdf?ver=2017-02-24-143230-873 (accessed on 9 November 2025).
- Linnéusson, G.; Andersson, T.; Kjellsdotter, A.; Holmén, M. Using systems thinking to increase understanding of the innovation system of healthcare organisations. J. Health Organ. Manag. 2022, 36, 179–195. [Google Scholar] [CrossRef] [Scilit]
- Heifetz, R. Leadership Without Easy Answers; Harvard University Press: Cambridge, MA, USA, 1994. [Google Scholar]
- Bertakis, K.D.; Azari, R. Patient-Centered Care is Associated with Decreased Health Care Utilization. J. Am. Board Fam. Med. 2011, 24, 229–239. [Google Scholar] [CrossRef] [Scilit]
- Nkhoma, K.B.; Cook, A.; Giusti, A.; Farrant, L.; Petrus, R.; Petersen, I.; Gwyther, L.; Venkatapuram, S.; Harding, R. A systematic review of impact of person-centred interventions for serious physical illness in terms of outcomes and costs. BMJ Open 2022, 12, e054386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yu, C.; Xian, Y.; Jing, T.; Bai, M.; Li, X.; Li, J.; Liang, H.; Yu, G.; Zhang, Z. More patient-centered care, better healthcare: The association between patient-centered care and healthcare outcomes in inpatients. Front. Public Health 2023, 11, 1148277. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the author. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).