


Abstract
Fever is one of the most common causes of medical evaluation of children, and early discrimination between viral and bacterial infection is essential to reduce inappropriate prescriptions. This study aims to systematically review the effects of point-of-care tests (POCTs) and rapid tests for respiratory tract infections on changing antibiotic prescription rate, length of stay, duration of therapy, and healthcare costs. Embase, MEDLINE, and Cochrane Library databases were systematically searched. All randomized control trials and non-randomized observational studies meeting inclusion criteria were evaluated using the NIH assessment tool. A meta-analysis was performed to assess the effects of rapid influenza diagnostic tests and film-array respiratory panel implementation on selected outcomes. From a total of 6440 studies, 57 were eligible for the review. The analysis was stratified by setting and POCT/rapid test type. The most frequent POCTs or rapid tests implemented were the Rapid Influenza Diagnostic Test and film-array and for those types of test a separate meta-analysis assessed a significant reduction in antibiotic prescription and an improvement in oseltamivir prescription. Implementing POCTs and rapid tests to discriminate between viral and bacterial infections for respiratory pathogens is valuable for improving appropriate antimicrobial prescriptions. However, more studies are needed to assess these findings in pediatric settings.
1. Introduction
Fever in children is one of the most common causes of medical evaluation in the emergency department (ED) or primary care practices and one of the possible complications in children hospitalized for other reasons [1]. Early recognition of severe infections in acutely ill children is crucial for improving their outcomes. Many physicians prescribe antibiotics, especially broad-spectrum antibiotics, for children with fever while waiting for blood tests and microbiological results to avoid the risk of severe infectious complications. However, it has been demonstrated that up to 50% of antibiotic prescriptions are unnecessary or inappropriate [2], and many children receive broad-spectrum antibiotics for viral infections [3]. This unnecessary use of antibiotics leads to increased antibiotic resistance and healthcare costs. For these reasons, discriminating between viral and bacterial infections is essential.
In 2007, the Infectious Disease Society of America (IDSA), alarmed by the increasing antimicrobial resistance rate compared to a reduction in newly available antibiotics, introduced the concept of Antimicrobial Stewardship Programs (ASP), defined as a collection of proactive strategies to improve the antibiotic prescription [2]. An integral part of ASPs is represented by diagnostic stewardship, coordinated guidance, and intervention to improve the appropriate use of microbiological diagnostics, which could help discriminate between viral and bacterial infection and guide therapeutic decisions [4]. Indeed, diagnostic tools are required to be accurate and available in a short period of time to modify decisions effectively and have an impact on the choice of treatment, as well as adequately cost saving.
Rapid tests are designed to give a diagnostic response with a shorter turnaround time than standard analysis (sample culture, serology, etc.). In addition, microbiological point-of-care tests (POCTs) are rapid tests designed to provide a quicker response at the bedside [5]. Indeed, rapid tests and POCTs could reduce inappropriate antibiotic prescriptions and length of stay, improve patient outcomes, and even allow cost savings due to earlier appropriate medical decisions. Many studies have been published on the usability of rapid tests and POCTs for implementing the diagnostic workup in many different settings, especially in adult populations. However, their use is not currently the standard of care for evaluating febrile children.
The primary aim of this review is to summarize the current state of evidence on the impact of rapid tests and POCTs for respiratory tract infections in pediatric settings (ED, inpatient, and outpatient) on changing the antimicrobial prescriptions rate (both antibiotic and oseltamivir), duration of therapy, length of stay, and healthcare costs in high and low–middle income countries.
2. Results
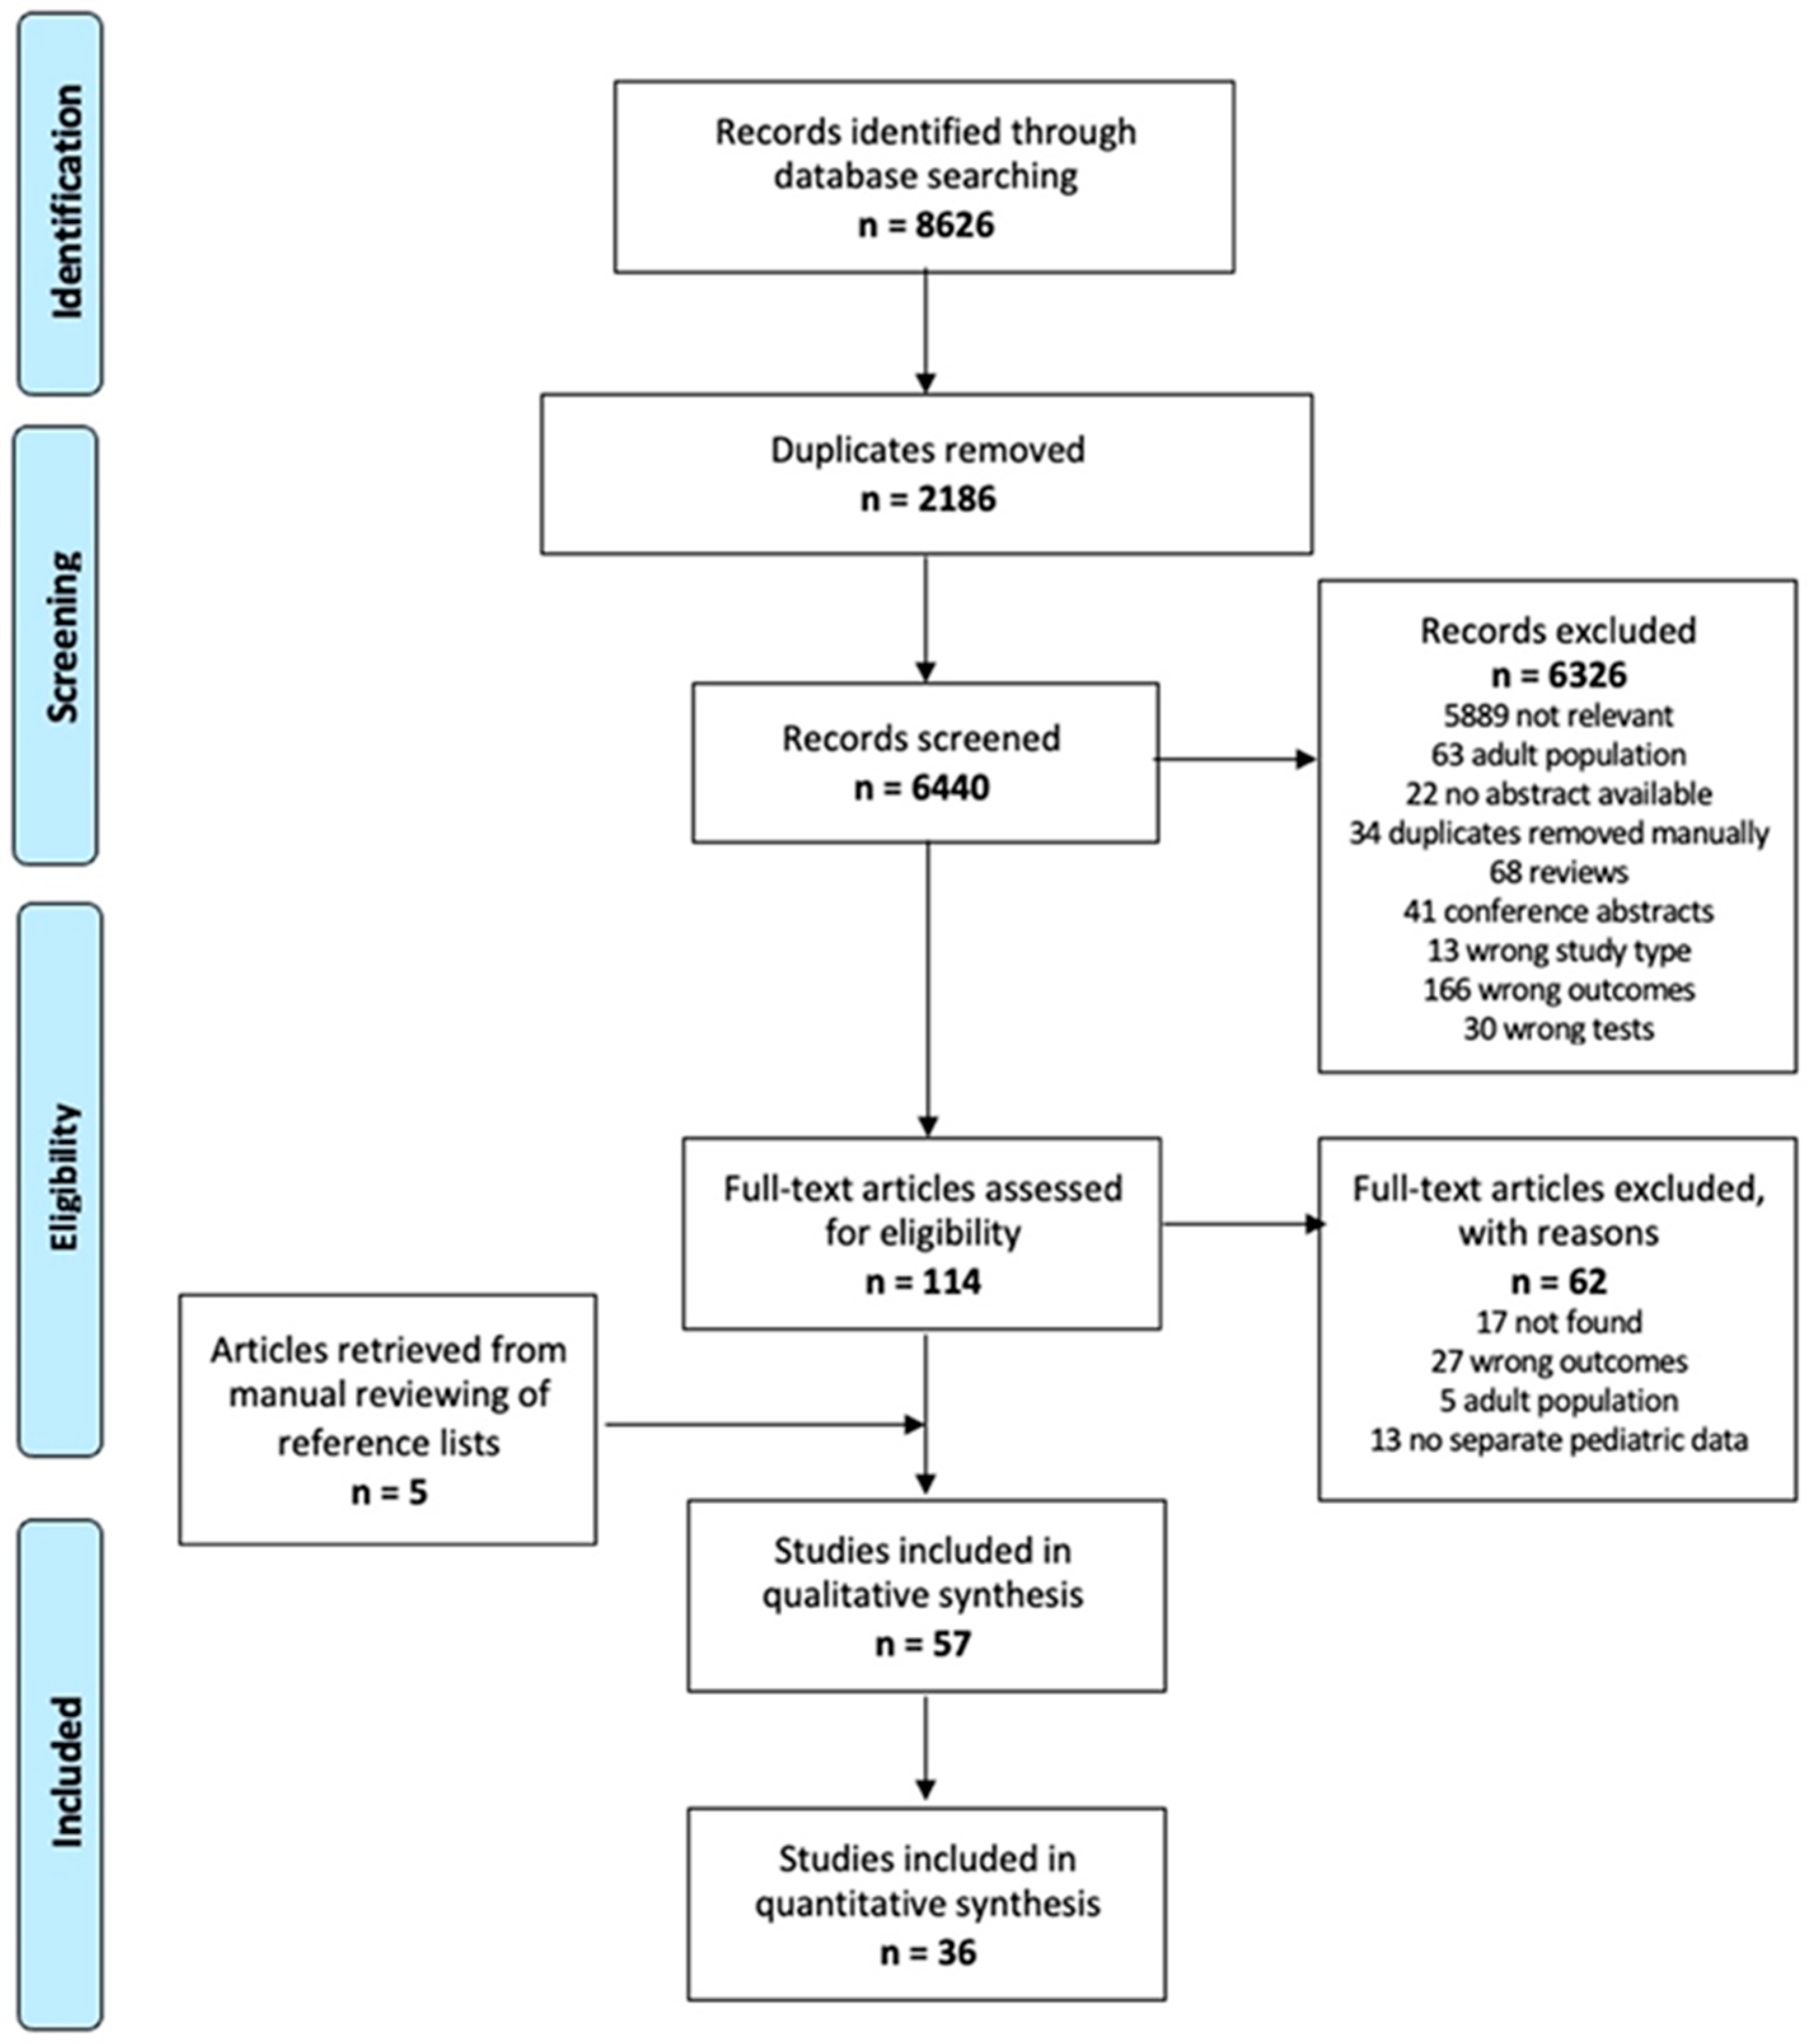
A total of 6440 studies were retrieved from the database search, excluding duplicates. After title and abstract screening, 114 were eligible for full-text reading and 52 were included in this review. In addition, five studies were added from the manual reviewing of reference lists for a total of 57 papers. The selection process is summarized in Figure 1 [6].
Figure 1.
Flowchart of the study selection process (PRISMA).
The title, authors, publication year, study design, country, study period, setting, number of patients included, type of rapid test or POCT, and types of outcomes considered are summarized in Table 1. The results of each study for the different outcomes are reported in Table 2.
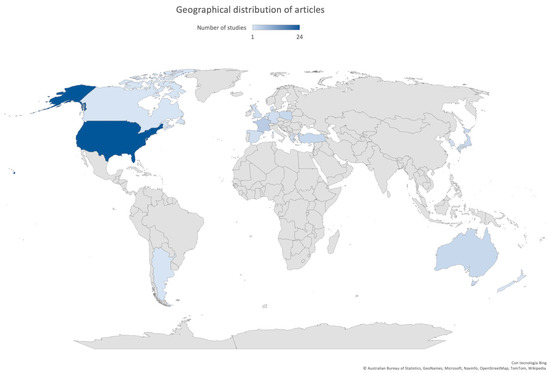
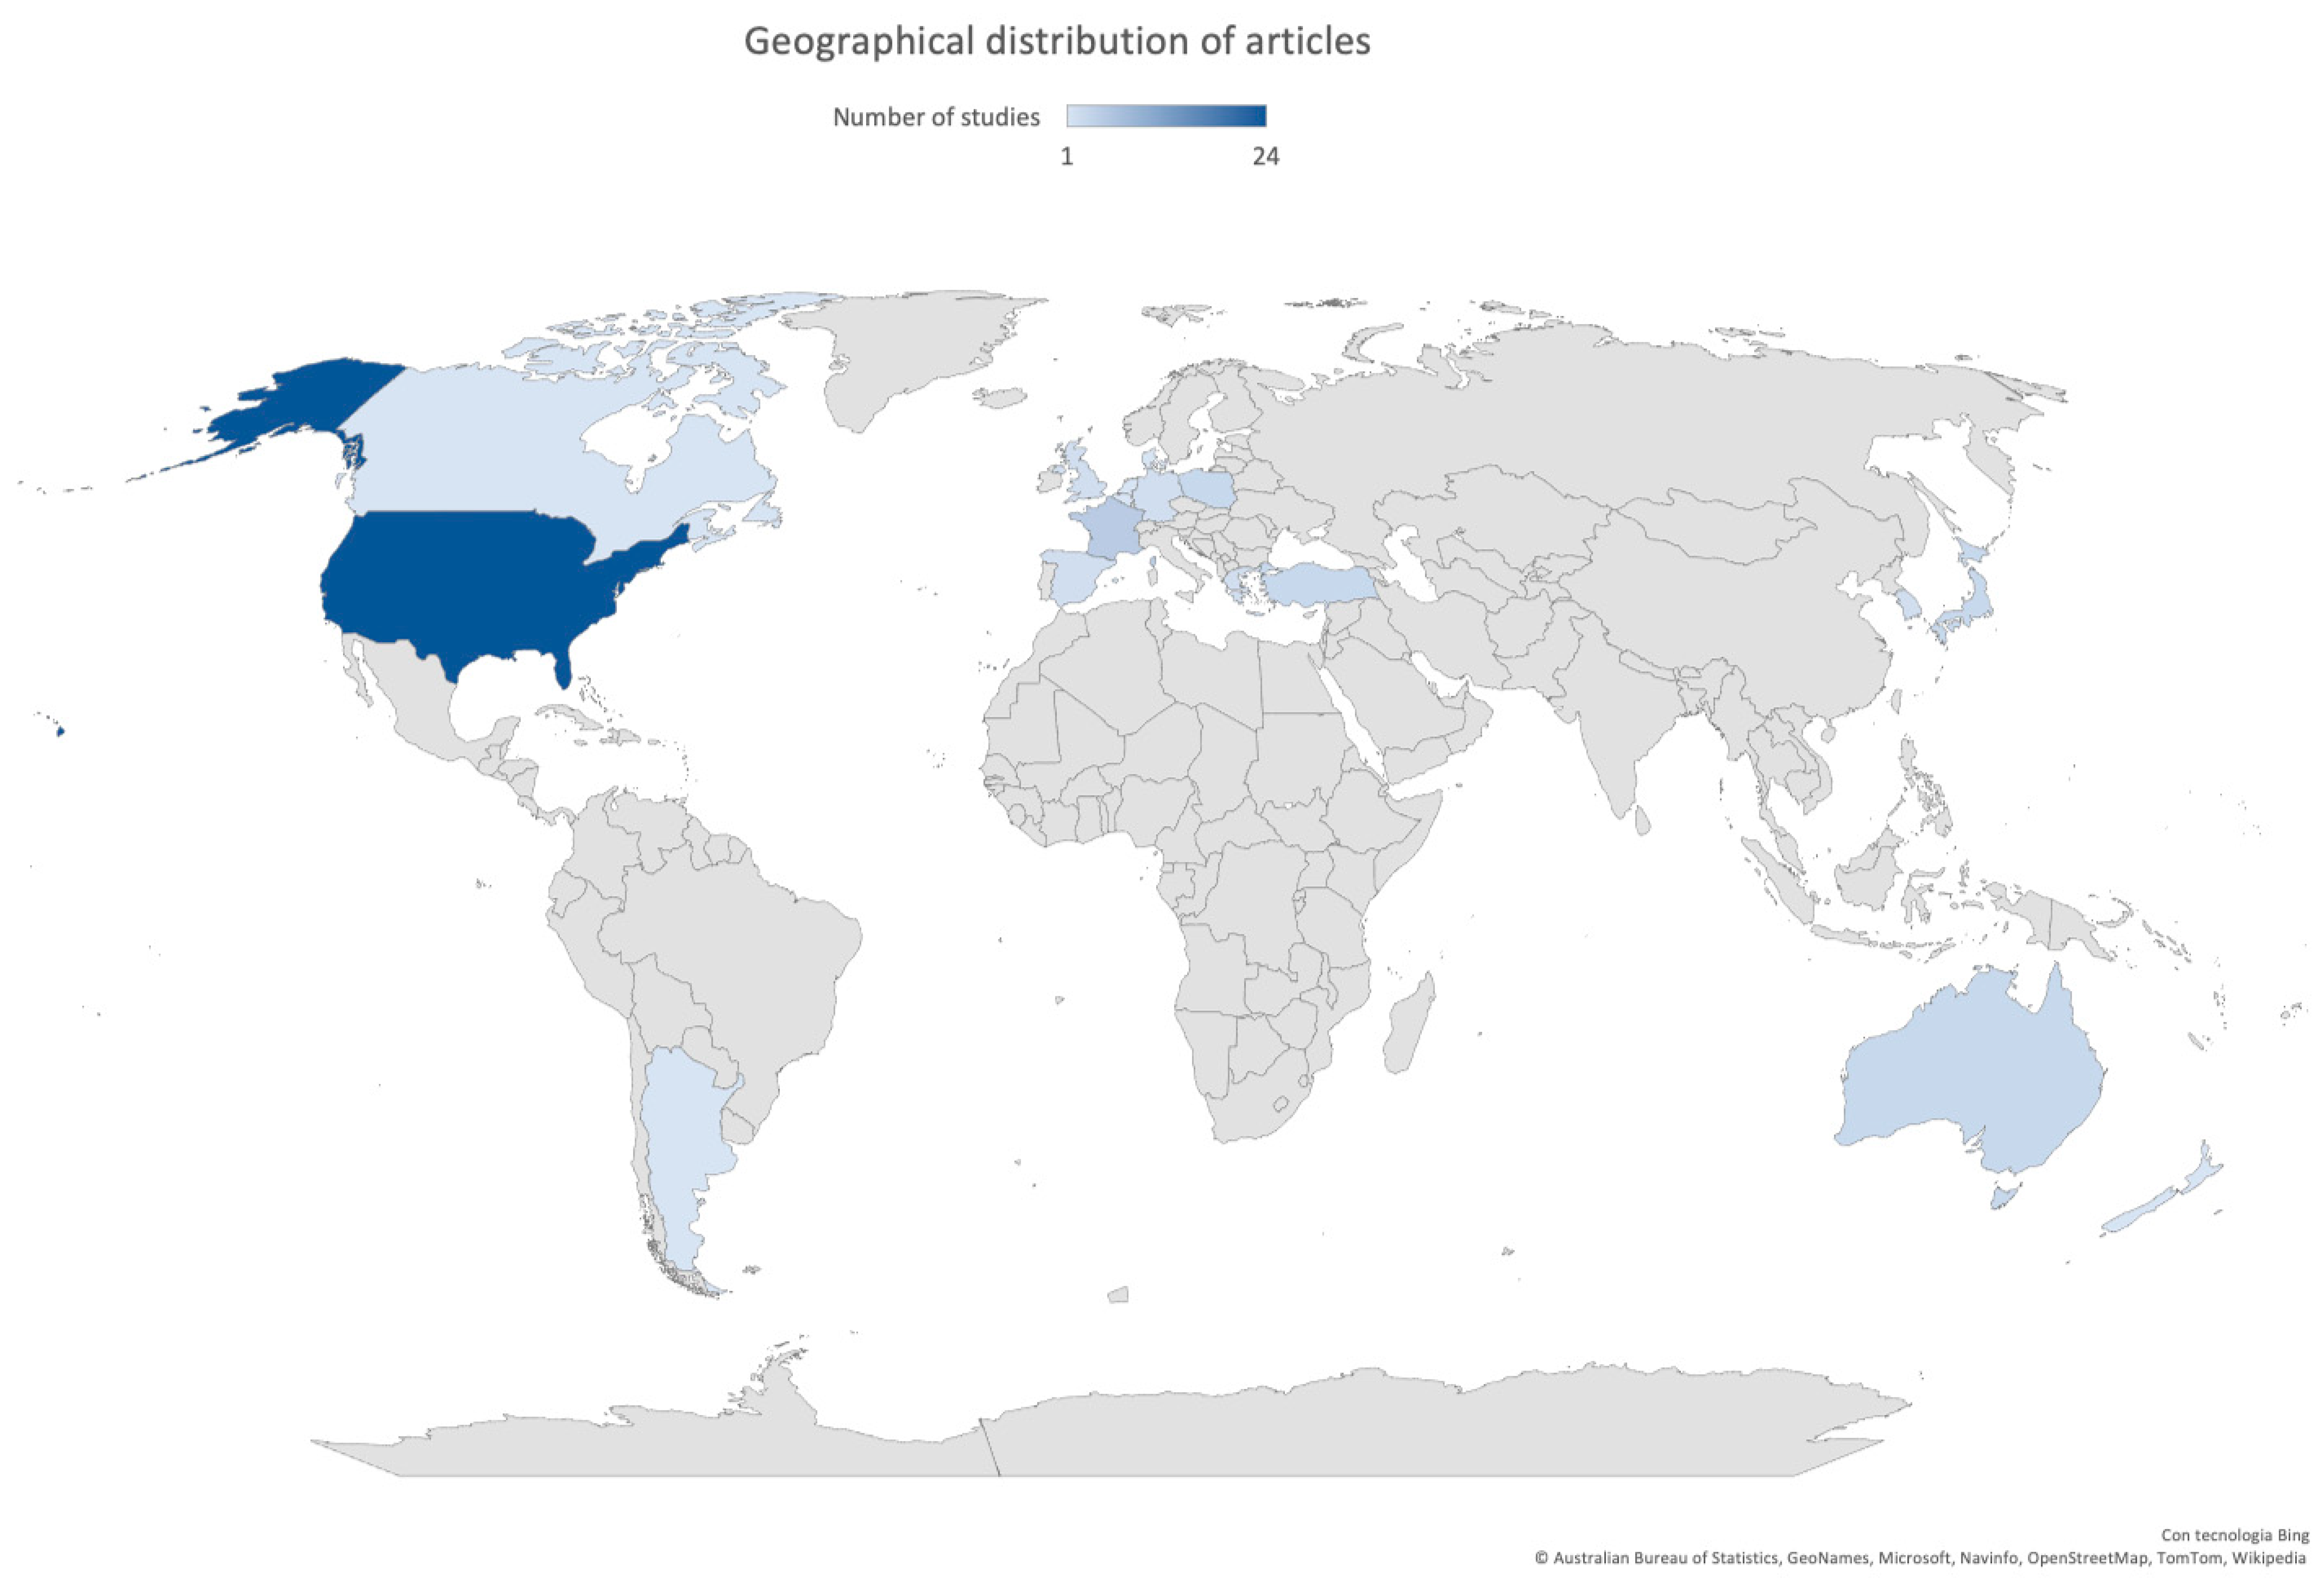
Most of the studies were published after 2007 (47/57, 82.5%), with 18 studies (10/57, 17.5%) between 2020 and 2021. Fifty-three studies (53/57, 93.0%) were conducted in high-income countries [7], and almost 80% of these articles described the implementation of a rapid test or POCT in North America (25/57, 43.9%) or Europe (19/57, 33.3%). Only eight studies (8/57, 14.0%) were conducted in Asia. The geographical distribution of articles is shown in Figure 2.
Figure 2.
Geographical distribution of articles included in this review.
Thirteen studies were multicenter: more than half were set in Europe (8/13, 61.5%) and the other 5 in North America (5/13, 38.5%).
The distribution of studies according to their design was: 8 randomized controlled trials (14.0%), 27 observational studies, including retrospective or prospective observational studies and control–case studies (47.4%), 22 quasi-experimental studies including before and after studies and interrupted time series studies (38.6%)
The most frequent rapid tests or POCTs implemented were the Rapid Influenza Diagnostic Test (RIDT) (22/57, 38.6%) and Film Array–Respiratory Panel (FA-RP) (22/57, 38.5%), followed by Strep A rapid tests (7/57, 12.3%) and others testing Respiratory Syncytial Virus (RSV) or the combination of RSV and influenza. Only one study focused on the implementation of a rapid PCR test for Mycoplasma pneumoniae.
Table 1.
Characteristics of studies included in the review.
Table 2.
Outcomes of the studies included in the review.
2.1. Implementation Setting
More than three-quarters of the studies described the implementation of rapid tests or POCTs in a hospital setting (46/57, 80.7%). More than half were exclusively conducted in the ED (29/46, 63.0%), and 14 studies (14/46, 30.4%) referred only to hospital wards. Three studies (3/46, 6.52%) described the implementation of rapid tests or POCTs both in ED and hospital wards. Nine studies (9/57, 15.8%) were conducted in the outpatient setting and two studies both in the outpatient and ED settings.
The implementation of different rapid tests and POCTs according to different settings is summarized in Table 1.
2.1.1. Hospital Setting: Inpatient—Emergency Department
Most of the studies on the implementation of FA-RP were conducted in a hospital setting (20/22, 90.9%), 7 studies in the ED (7/20, 35.0%) and 10 studies in different hospital wards (10/20, 50.0%); 3 studies were conducted both in the ED and hospital wards (3/20, 15.0%). More than half of the studies on the implementation of RIDT were conducted in a hospital setting (16/22, 72.7%), almost all in the ED (14/16, 87.5%). Rapid tests for RSV, Mycoplasma, or rapid tests combined for RSV and influenza were implemented only in the hospital setting (three studies about the RSV rapid test, three studies for the combined test, one study about Mycoplasma). Almost all the studies on the implementation of rapid tests or POCTs in hospital wards were conducted in high-income countries.
2.1.2. Outpatient—Primary Care
The most implemented POCT in the outpatient setting was RIDT (5/9, 55.6%), followed by Strep A test (3/9, 33.3%). Only one study described the implementation of FA-RP in the outpatient setting.
Almost all the studies about POCTs in outpatient settings were conducted in Europe (7/9, 77.8%), and only two in the USA (2/9, 22.2%).
2.2. Implementation of Rapid Tests or POCTs and Outcomes
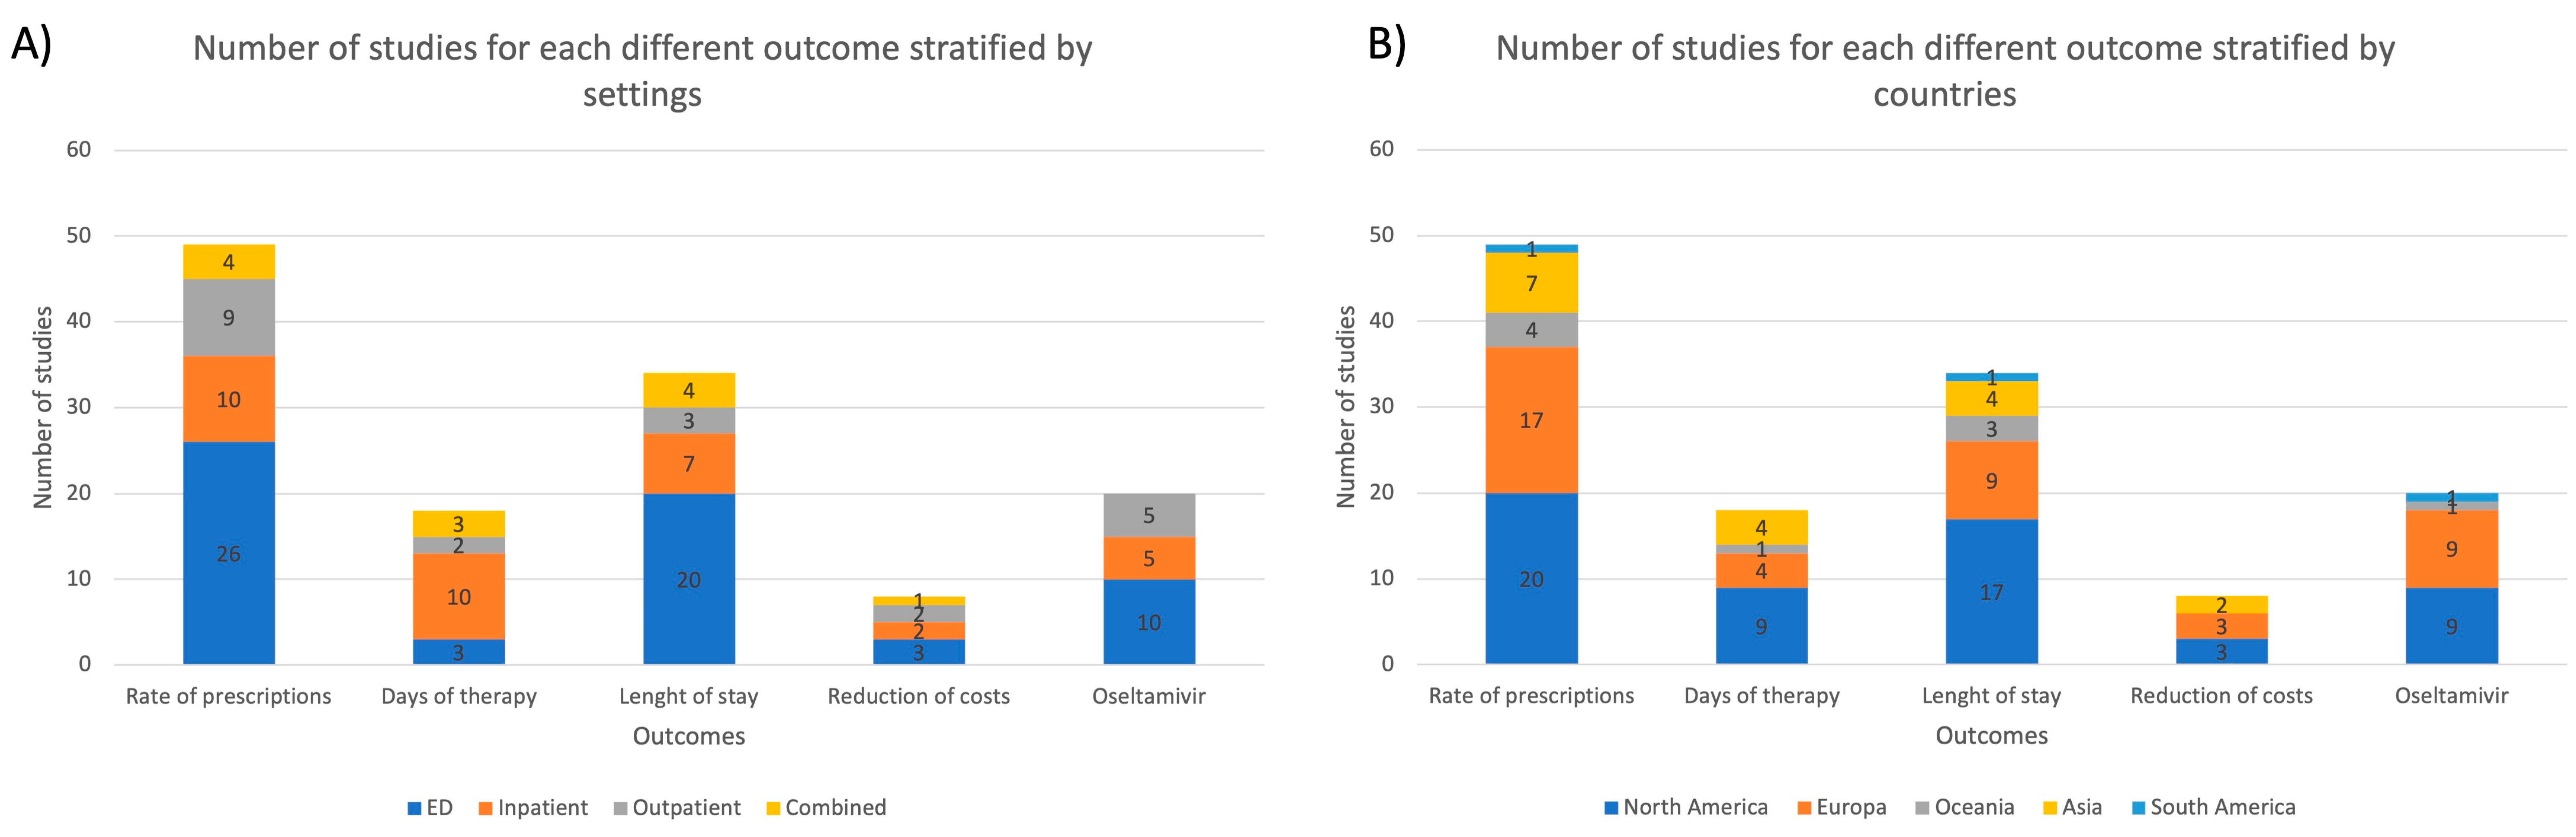
In Figure 3, the distribution of studies for each outcome is reported, stratified for setting and country.
Figure 3.
The number of studies for each different outcome stratified by (A) settings; (B) countries; ED = emergency department.
Considering the studies’ variety, separate meta-analyses for primary and secondary outcomes were conducted for the two types of rapid tests/POCTs with the most consistent data: film-array respiratory panel FA-RP and RIDT, including a total of 15 articles and 21 articles, respectively.
2.2.1. Antibiotics Prescription
More than three-quarters of the studies reported as their main outcome the change in antibiotics prescription after rapid tests or POCT implementation (49/57, 86.0%), with almost two-thirds (32/49, 65.3%) assessing a statistically significant reduction.
All the articles that focused on the change in antibiotic prescription after the introduction of the Strep A test reported a significant reduction in the antibiotic use, both in inpatient and outpatient settings.
On the contrary, the two articles about the implementation of a rapid test for RSV showed no difference in the antibiotic prescriptions between patients testing positive and those testing negative, both in the ED and hospital wards. One of the studies on the rapid test for RSV combined with influenza reported a statistically significant reduction in antibiotic use in children with a positive test, while another showed a slight reduction in antibiotic prescription. The study about the implementation of a rapid PCR for Mycoplasma pneumoniae showed increased appropriateness in prescribing antibiotics for atypical pathogens in those patients testing positive.
Separate meta-analyses for FA-RP and RIDT are reported in Figure 4 and Figure 5, and subgroup analyses are reported in Supplementary Material. It was not possible to conduct the pre-planned metanalysis by age groups due to the lack of data.
Figure 4.
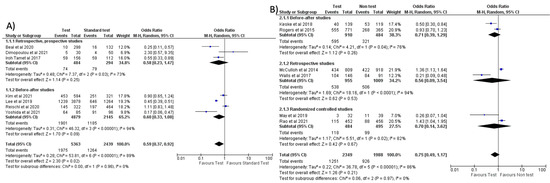
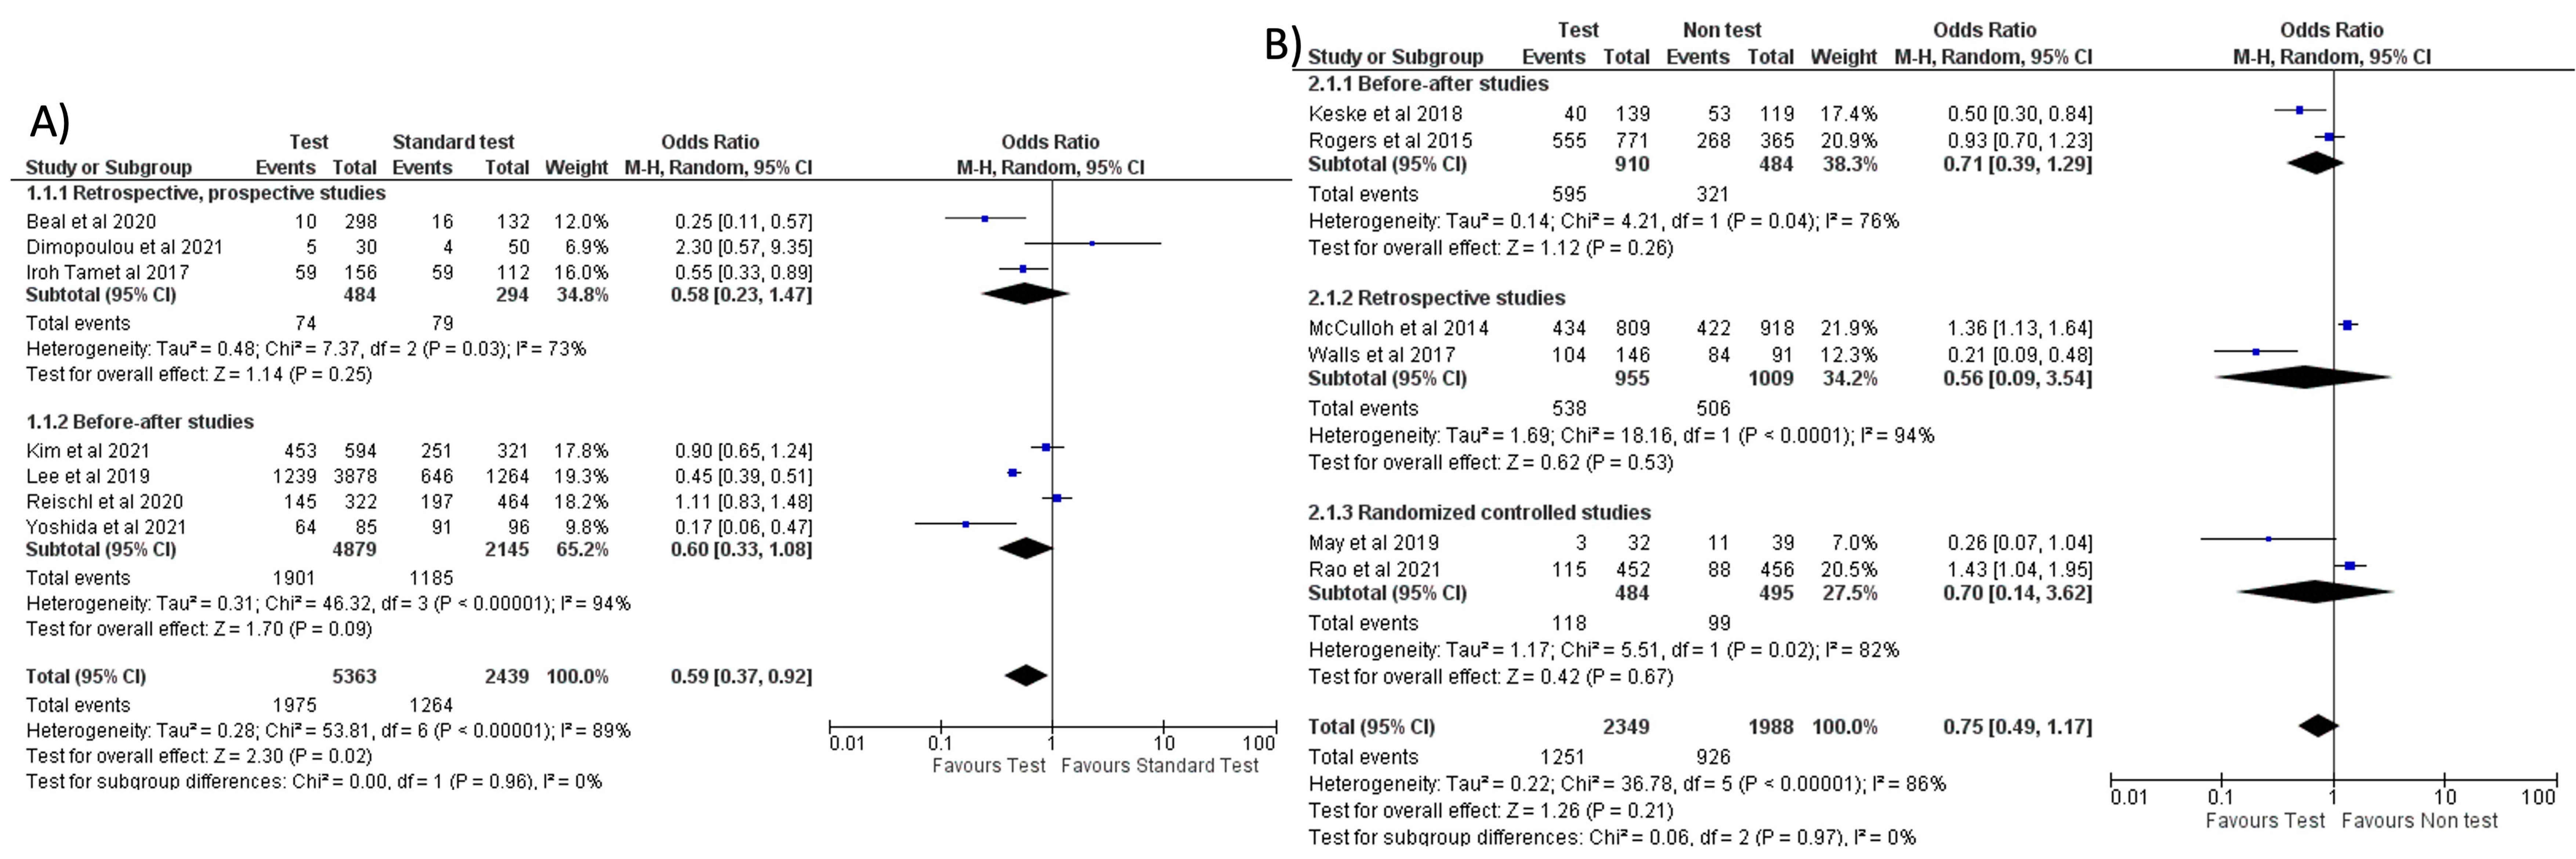
Forest plot of prescription of antibiotics after implementation of FA-RP: (A) FA-RP vs. standard test; (B) FA-RP versus clinical diagnosis.
Figure 5.
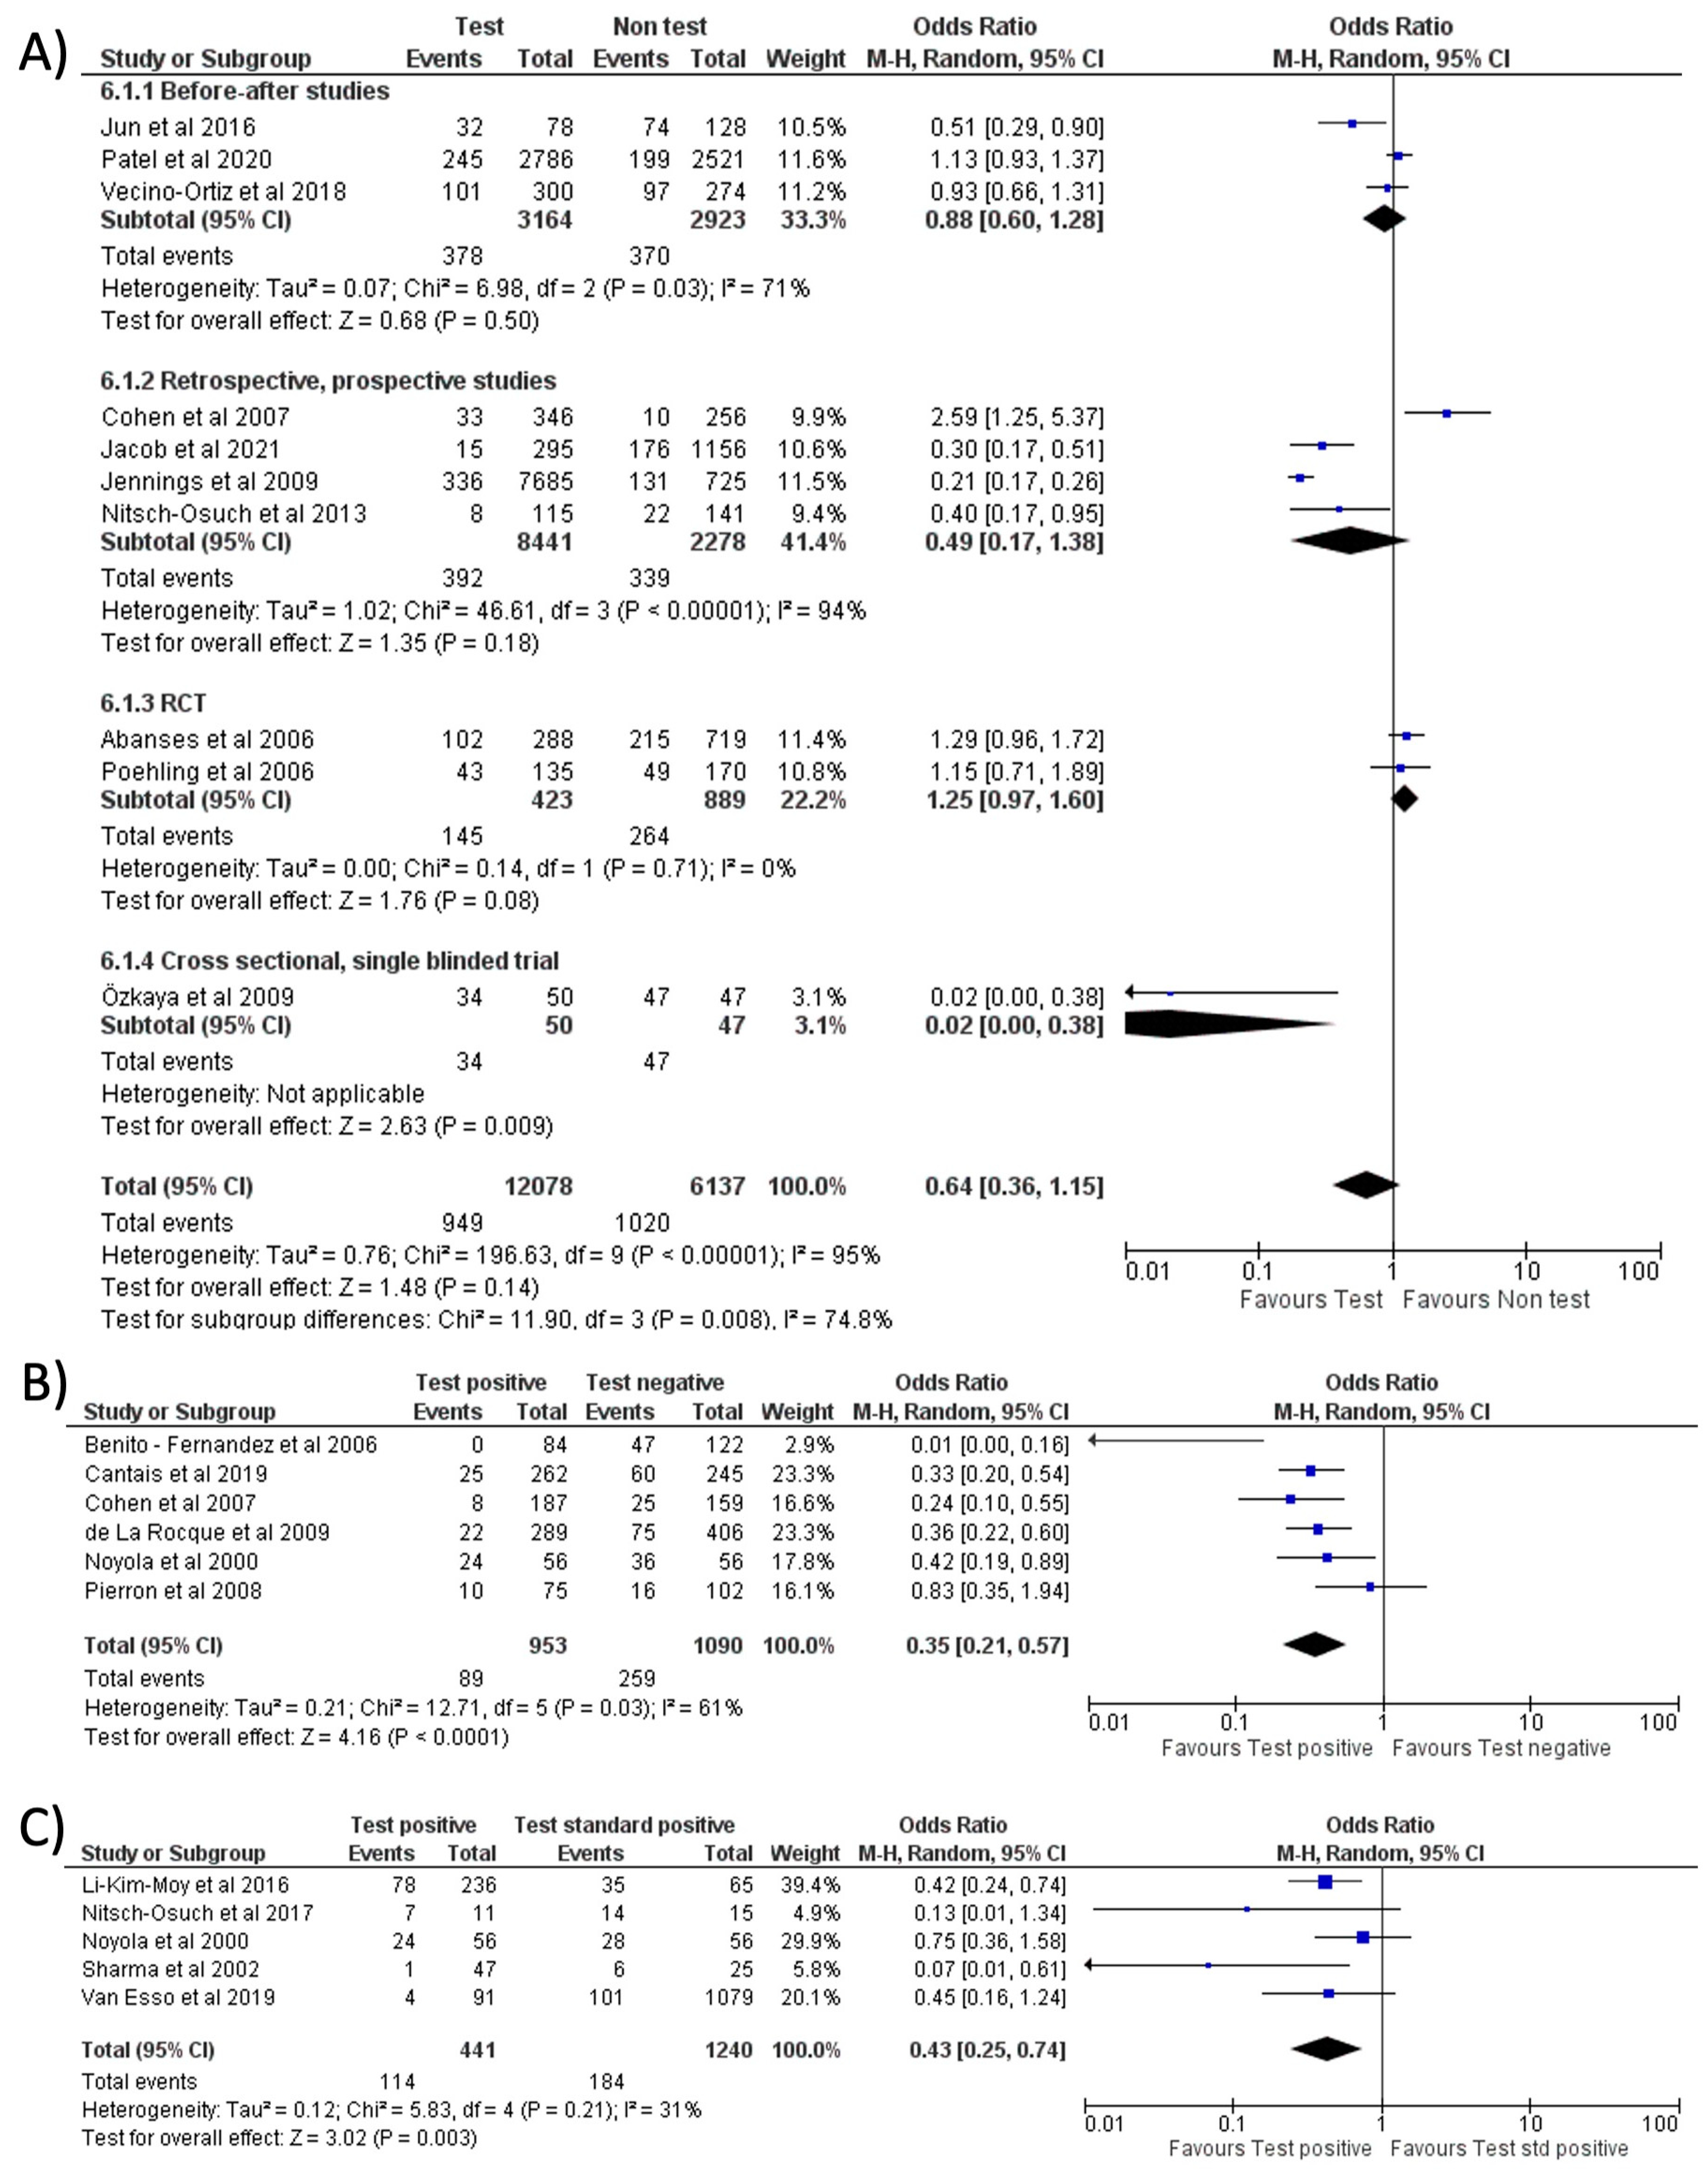
Forest plot of prescription of antibiotics after implementation of RIDT: (A) RIDT vs. clinical diagnosis; (B) RIDT positive versus RIDT negative; (C) RIDT positive vs. standard of care positive.
When comparing the use of FA-RP vs. standard test, an overall reduction in antibiotic prescriptions was noted (OR = 0.59, 95% CI 0.37–0.92, p = 0.02) [32,33,37,40,41,46,51], however, with a high heterogeneity (I2) of 89% (Figure 4A). In a subgroup analysis stratified by countries, this reduction was more significant in the studies conducted in the US compared to Europe and East Asia (see Figure S1A). However, when comparing FA-RP vs. clinical diagnosis [30,36,38,42,47,49], prescription rate did not significantly decrease (OR = 0.75, 95% CI 0.49–1.17, p = 0.21; I2 = 86%) (Figure 4B). A subgroup analysis stratified for different types of study is shown in Figure S1B,C.
No significant reduction in antibiotic prescription (OR = 0.64, 95% CI 0.36–1.15, p = 0.14; I2 = 95%) was noted when comparing the use of RIDT vs. clinical diagnosis (Figure 5A) [9,10,13,17,18,21,24,25,26,28]. One of the studies (Ozkaya et al.) seems to have a more evident reduction in antibiotic prescribing compared to the other studies. This study, conducted in Turkey, involved only 97 children and all the patients not tested with the rapid antigen detection test received antibiotic therapy. We evaluated this study as “fair” and it had a low weight in our metanalysis.
However, when stratified by geographical location (continent, nation, or single state based on the number of articles included in the analysis), a trend toward fewer prescriptions emerged in Europe and East Asia with respect to the US (see Figure S2A).
Comparing a positive result of RIDT vs. a negative result, a significant reduction in the prescriptions rate was noted (OR = 0.35, 95% CI 0.21–0.57, p < 0.0001; I2 = 61%) (Figure 5B) [12,15,22,23,28,29]. A positive RIDT was also associated with a significant reduction in antibiotics prescriptions with respect to a positive standard test [8,12,19,20,27] (OR = 0.43, 95% CI 0.25–0.74, p = 0.003; I2 = 31%) (Figure 5C). This evidence seemed stronger in Europe than in the US (see Figure S2B). A subgroup analysis stratified for different types of study is shown in Figure S3.
2.2.2. Oseltamivir Prescription
Twenty studies (20/57, 35.1%) also reported the change in antiviral prescriptions (oseltamivir). A significant increase in oseltamivir prescription with POCT emerged from 60.0% of the studies (12/20), including one study focused on the implementation of the rapid test for RSV combined with influenza.
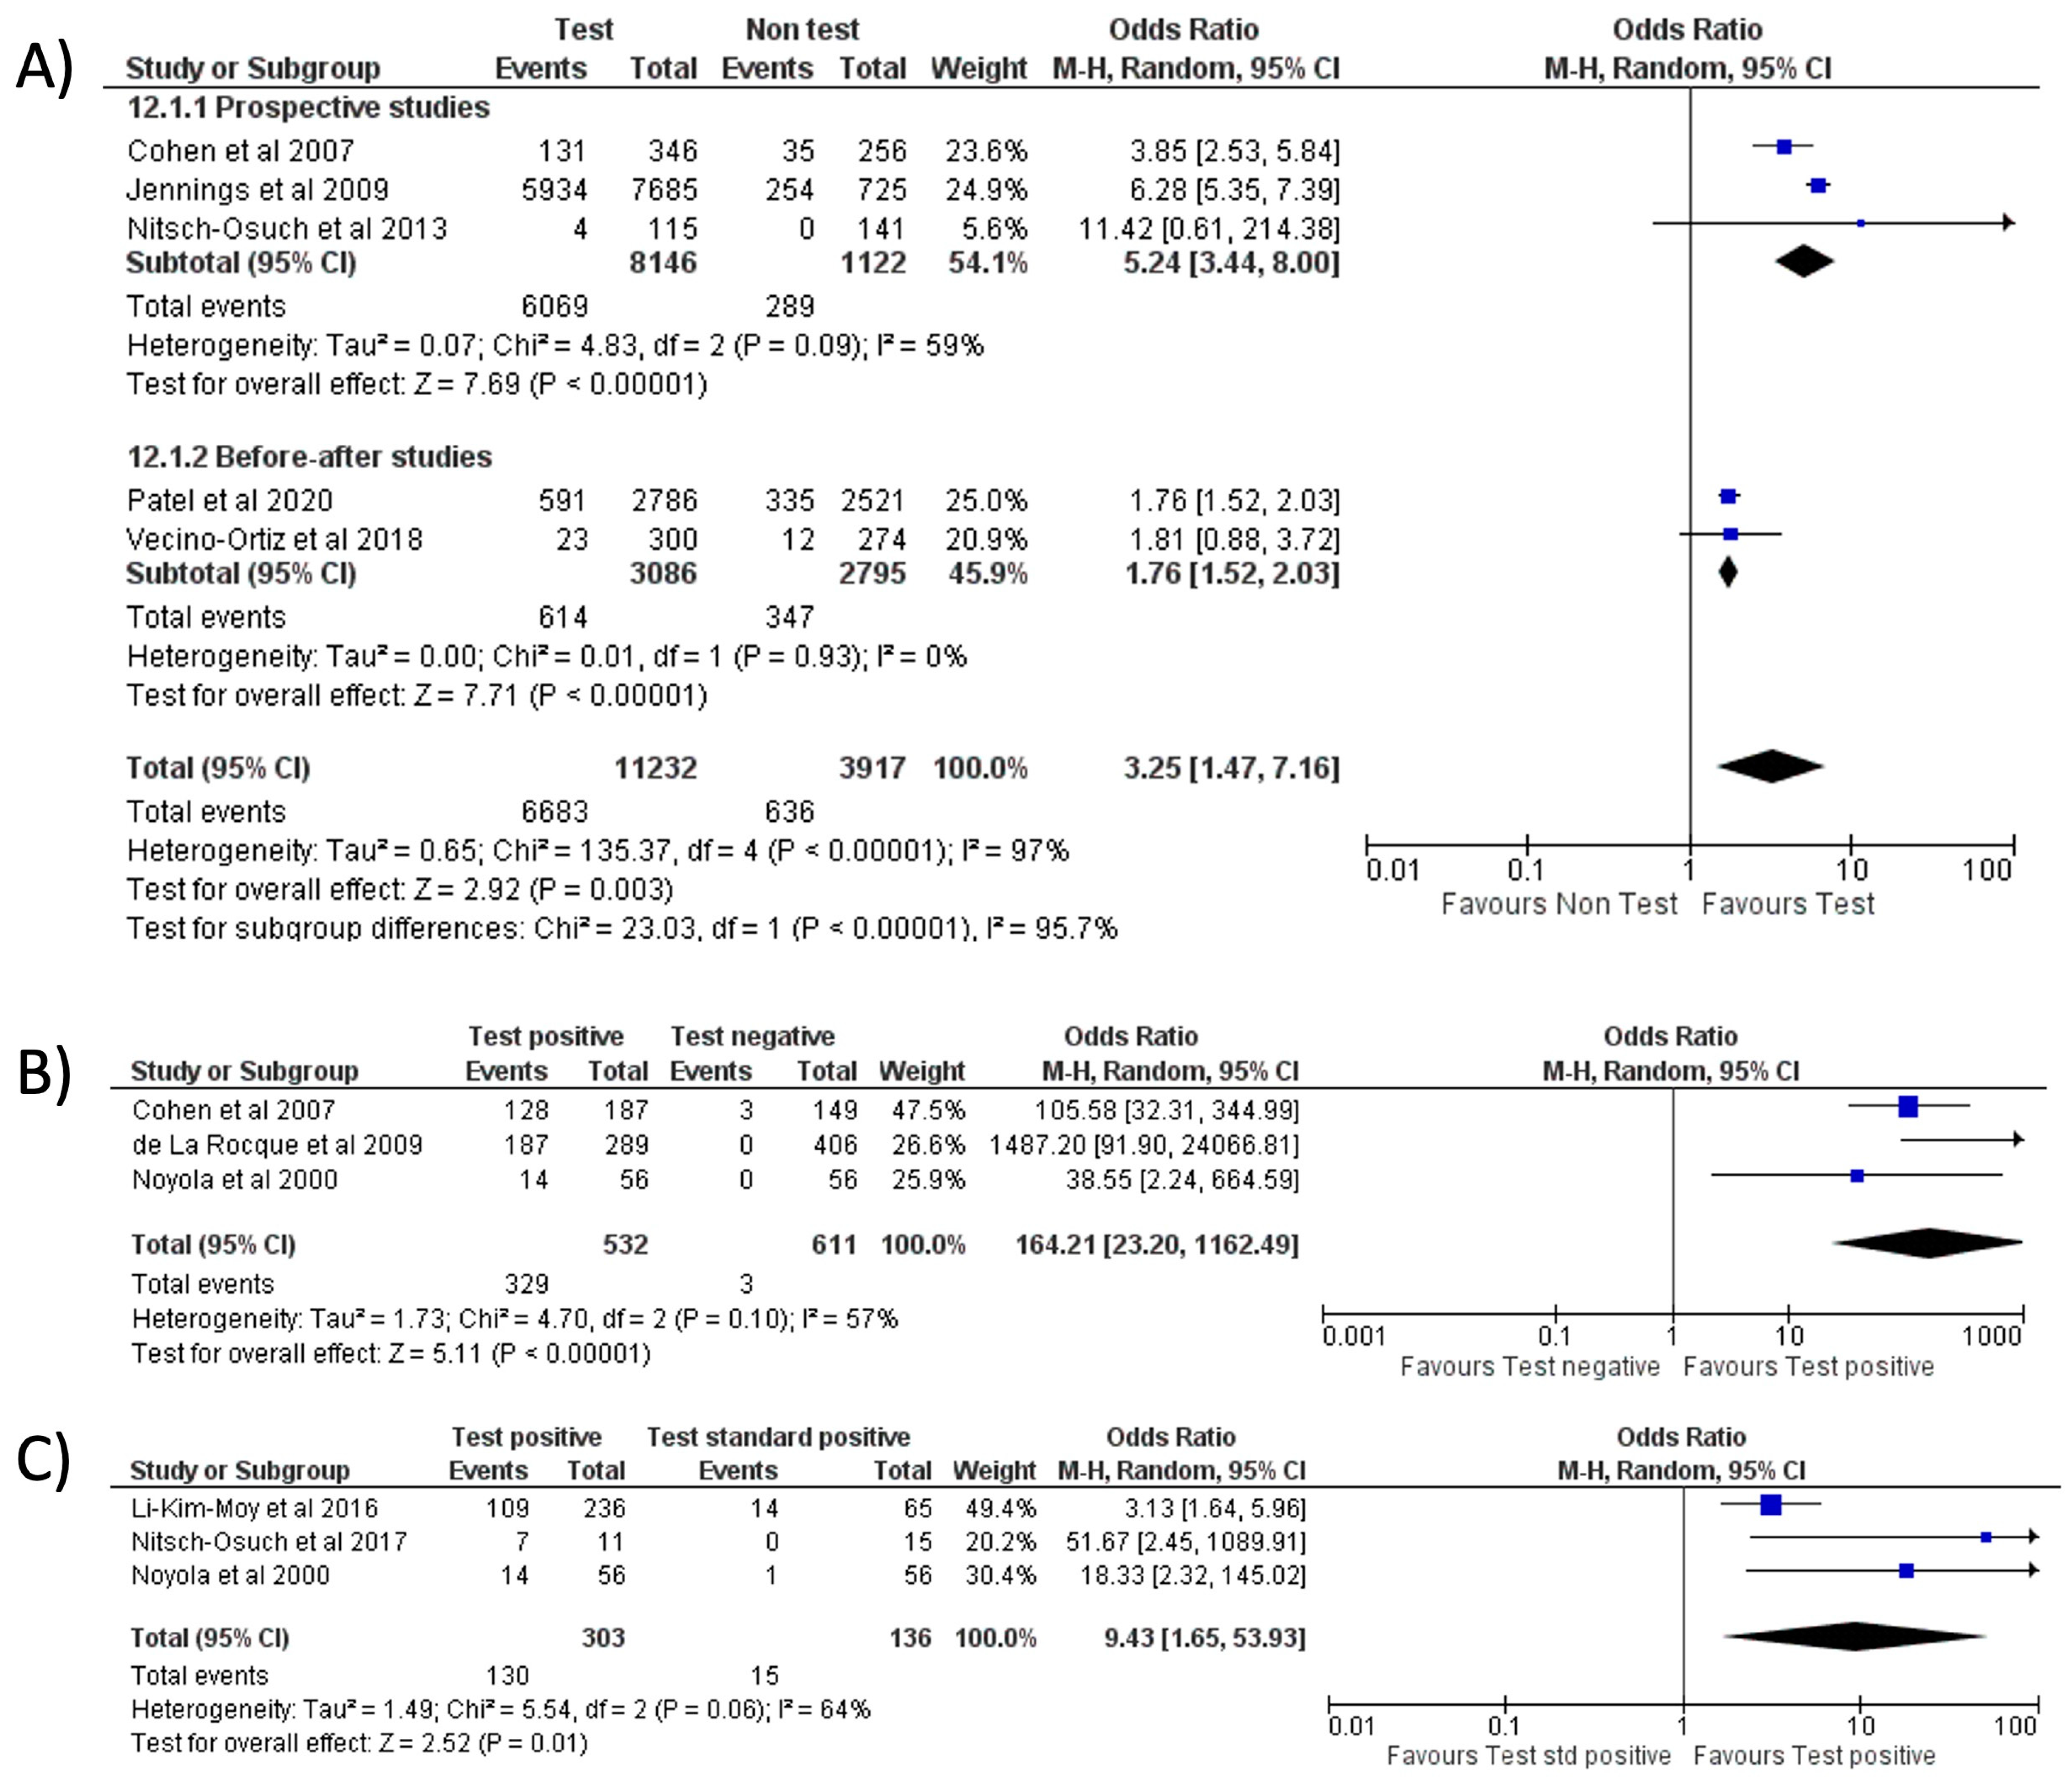
Separate meta-analyses stratified by FA-RP and RIDT are reported in Figure 6 and Figure 7. Subgroup analyses are reported in Figure S4.
Figure 6.
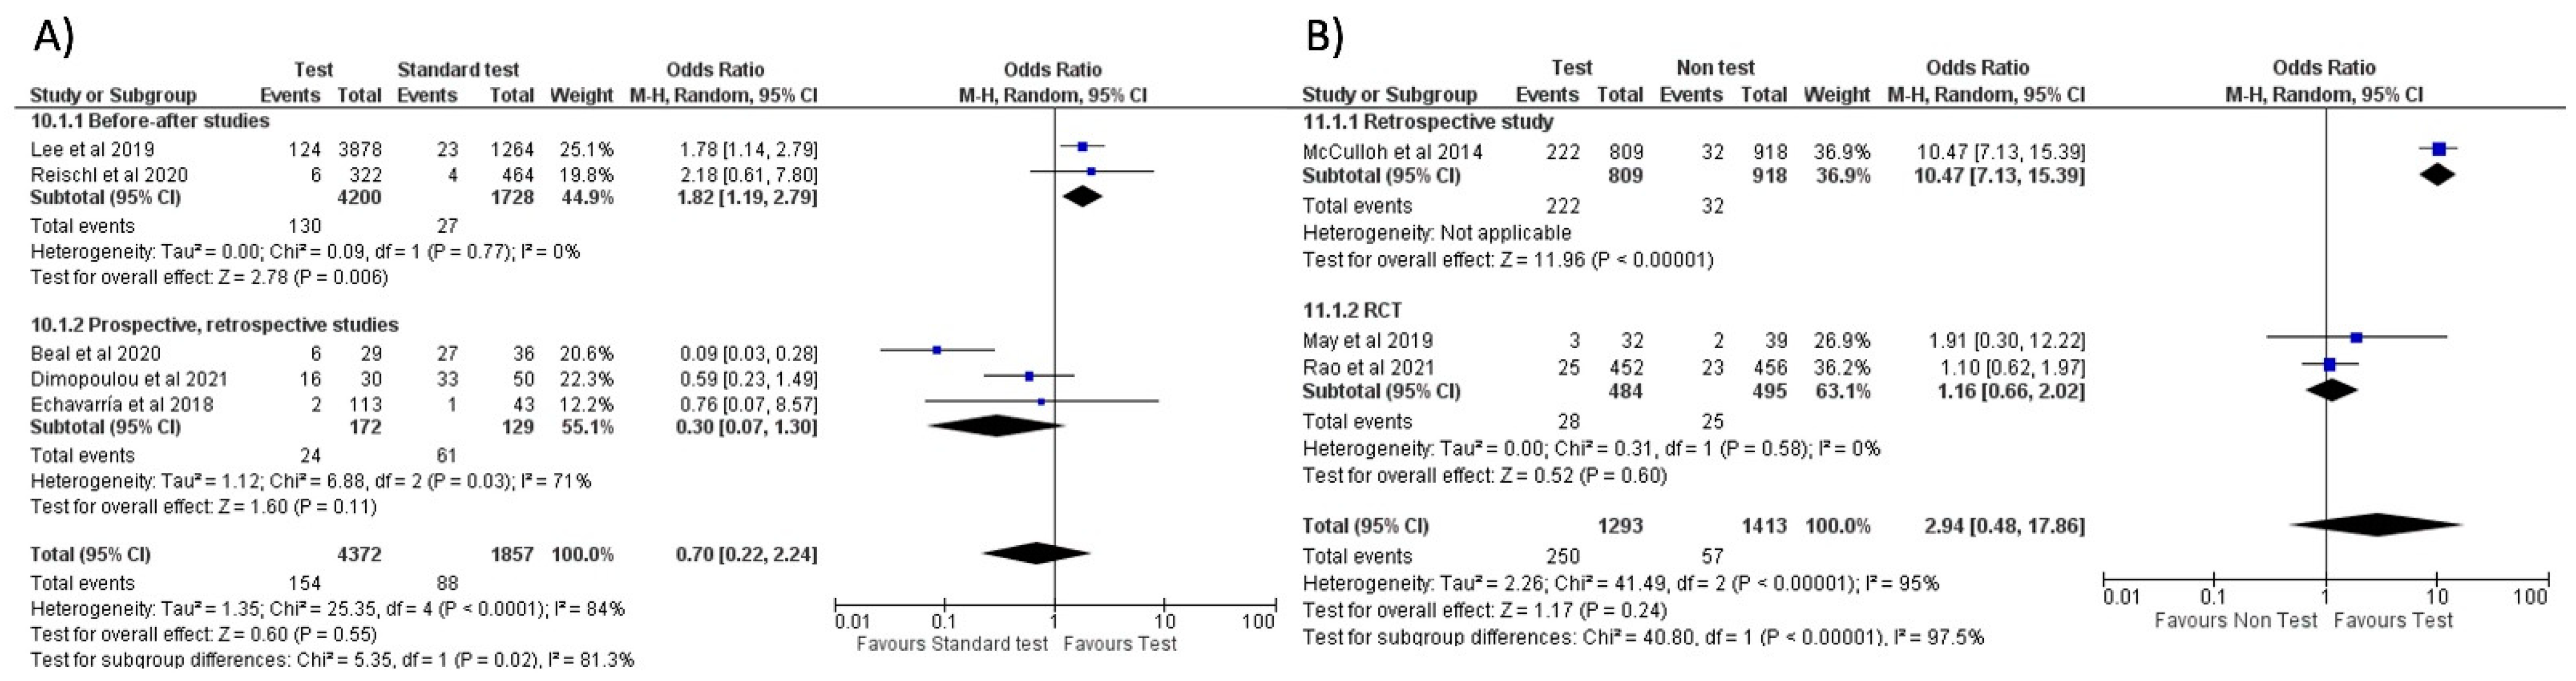
Forest plot of prescription of oseltamivir after implementation of FA-RP: (A) FA-RP vs. standard of care; (B) FA-RP vs. clinical diagnosis.
Figure 7.
Forest plot of prescription of oseltamivir after implementation of RIDT: (A) RIDT vs. clinical diagnosis; (B) RIDT positive vs. RIDT negative; (C) RIDT positive vs. standard of care positive.
No significant difference in oseltamivir prescription was noted when comparing FA-RP to the standard test (OR = 0.70, 95% CI 0.22–2.24, p = 0.55; I2 = 84%) (Figure 6A) [32,33,46,48,51], which is confirmed in the sub-group analysis stratified by country (Europe and the US, see Figure S4A). When comparing the use of FA-RP vs. clinical diagnosis of influenza [38,47,49], there was an increased trend in prescriptions but without a significant difference (OR = 2.94, 95% CI 0.48–17.86, p = 0.24; I2 = 95%) (Figure 6B).
With respect to RIDT, all comparisons from the meta-analysis highlighted a significant increase in oseltamivir prescriptions: the use of RIDT vs. clinical diagnosis [9,21,25,26,28] tripled the odds of having prescribed oseltamivir (OR = 3.25, 95% CI 1.47–7.16, p = 0.003; I2 = 97%) (Figure 7A), while a more conclusive association emerged when comparing a positive RIDT result vs. negative (OR = 164.21, 95% CI 23.20–1162.49, p < 0.001; I2 = 57%) (Figure 7B) [12,28,29] and when evaluating a positive RIDT vs. a positive standard test (OR = 9.43, 95% CI 1.65–53.93, p = 0.01; I2 = 64%) (Figure 7C) [8,12,19].
2.2.3. Length of Stay
Thirty-four studies (34/57, 59.6%) evaluated the length of stay in relation to rapid tests or POCTs, with most of the studies conducted in the hospital setting (20/34 and 7/34 in ED other hospital wards, respectively). Almost half of the studies (16/34, 47.1%) reported a significant reduction in the length of stay with POCTs.
Data were not available from RIDT and FA-RP studies to conduct a meta-analysis.
2.2.4. Days of Therapy
Eighteen different studies (18/57, 31.6%), mostly conducted in the hospital wards (15/18, 83.3%), evaluated a potential change in days of therapy (DOT) related to rapid tests or POCT implementation.
In 61.1% of the studies a reduction in DOT was noted (11/18, 61%).
A meta-analysis was possible only for three observational studies [31,33,41], which compared the use of FA-RP vs. standard tests for the duration of therapy in inpatients. No significant difference was found (see Figure S4B). Data from RIDT studies were not available to conduct a meta-analysis for this outcome.
2.2.5. Healthcare Cost
The reduction of healthcare costs was less frequent analyzed; only eight studies, mostly conducted in the ED and hospital wards (6/8, 75.0%), reported data about costs (8/57, 14.0%). In only three studies (3/8, 37.5%) a significant reduction in costs was noted. No meta-analysis was conducted for this outcome.
2.3. Quality Assessment of Studies
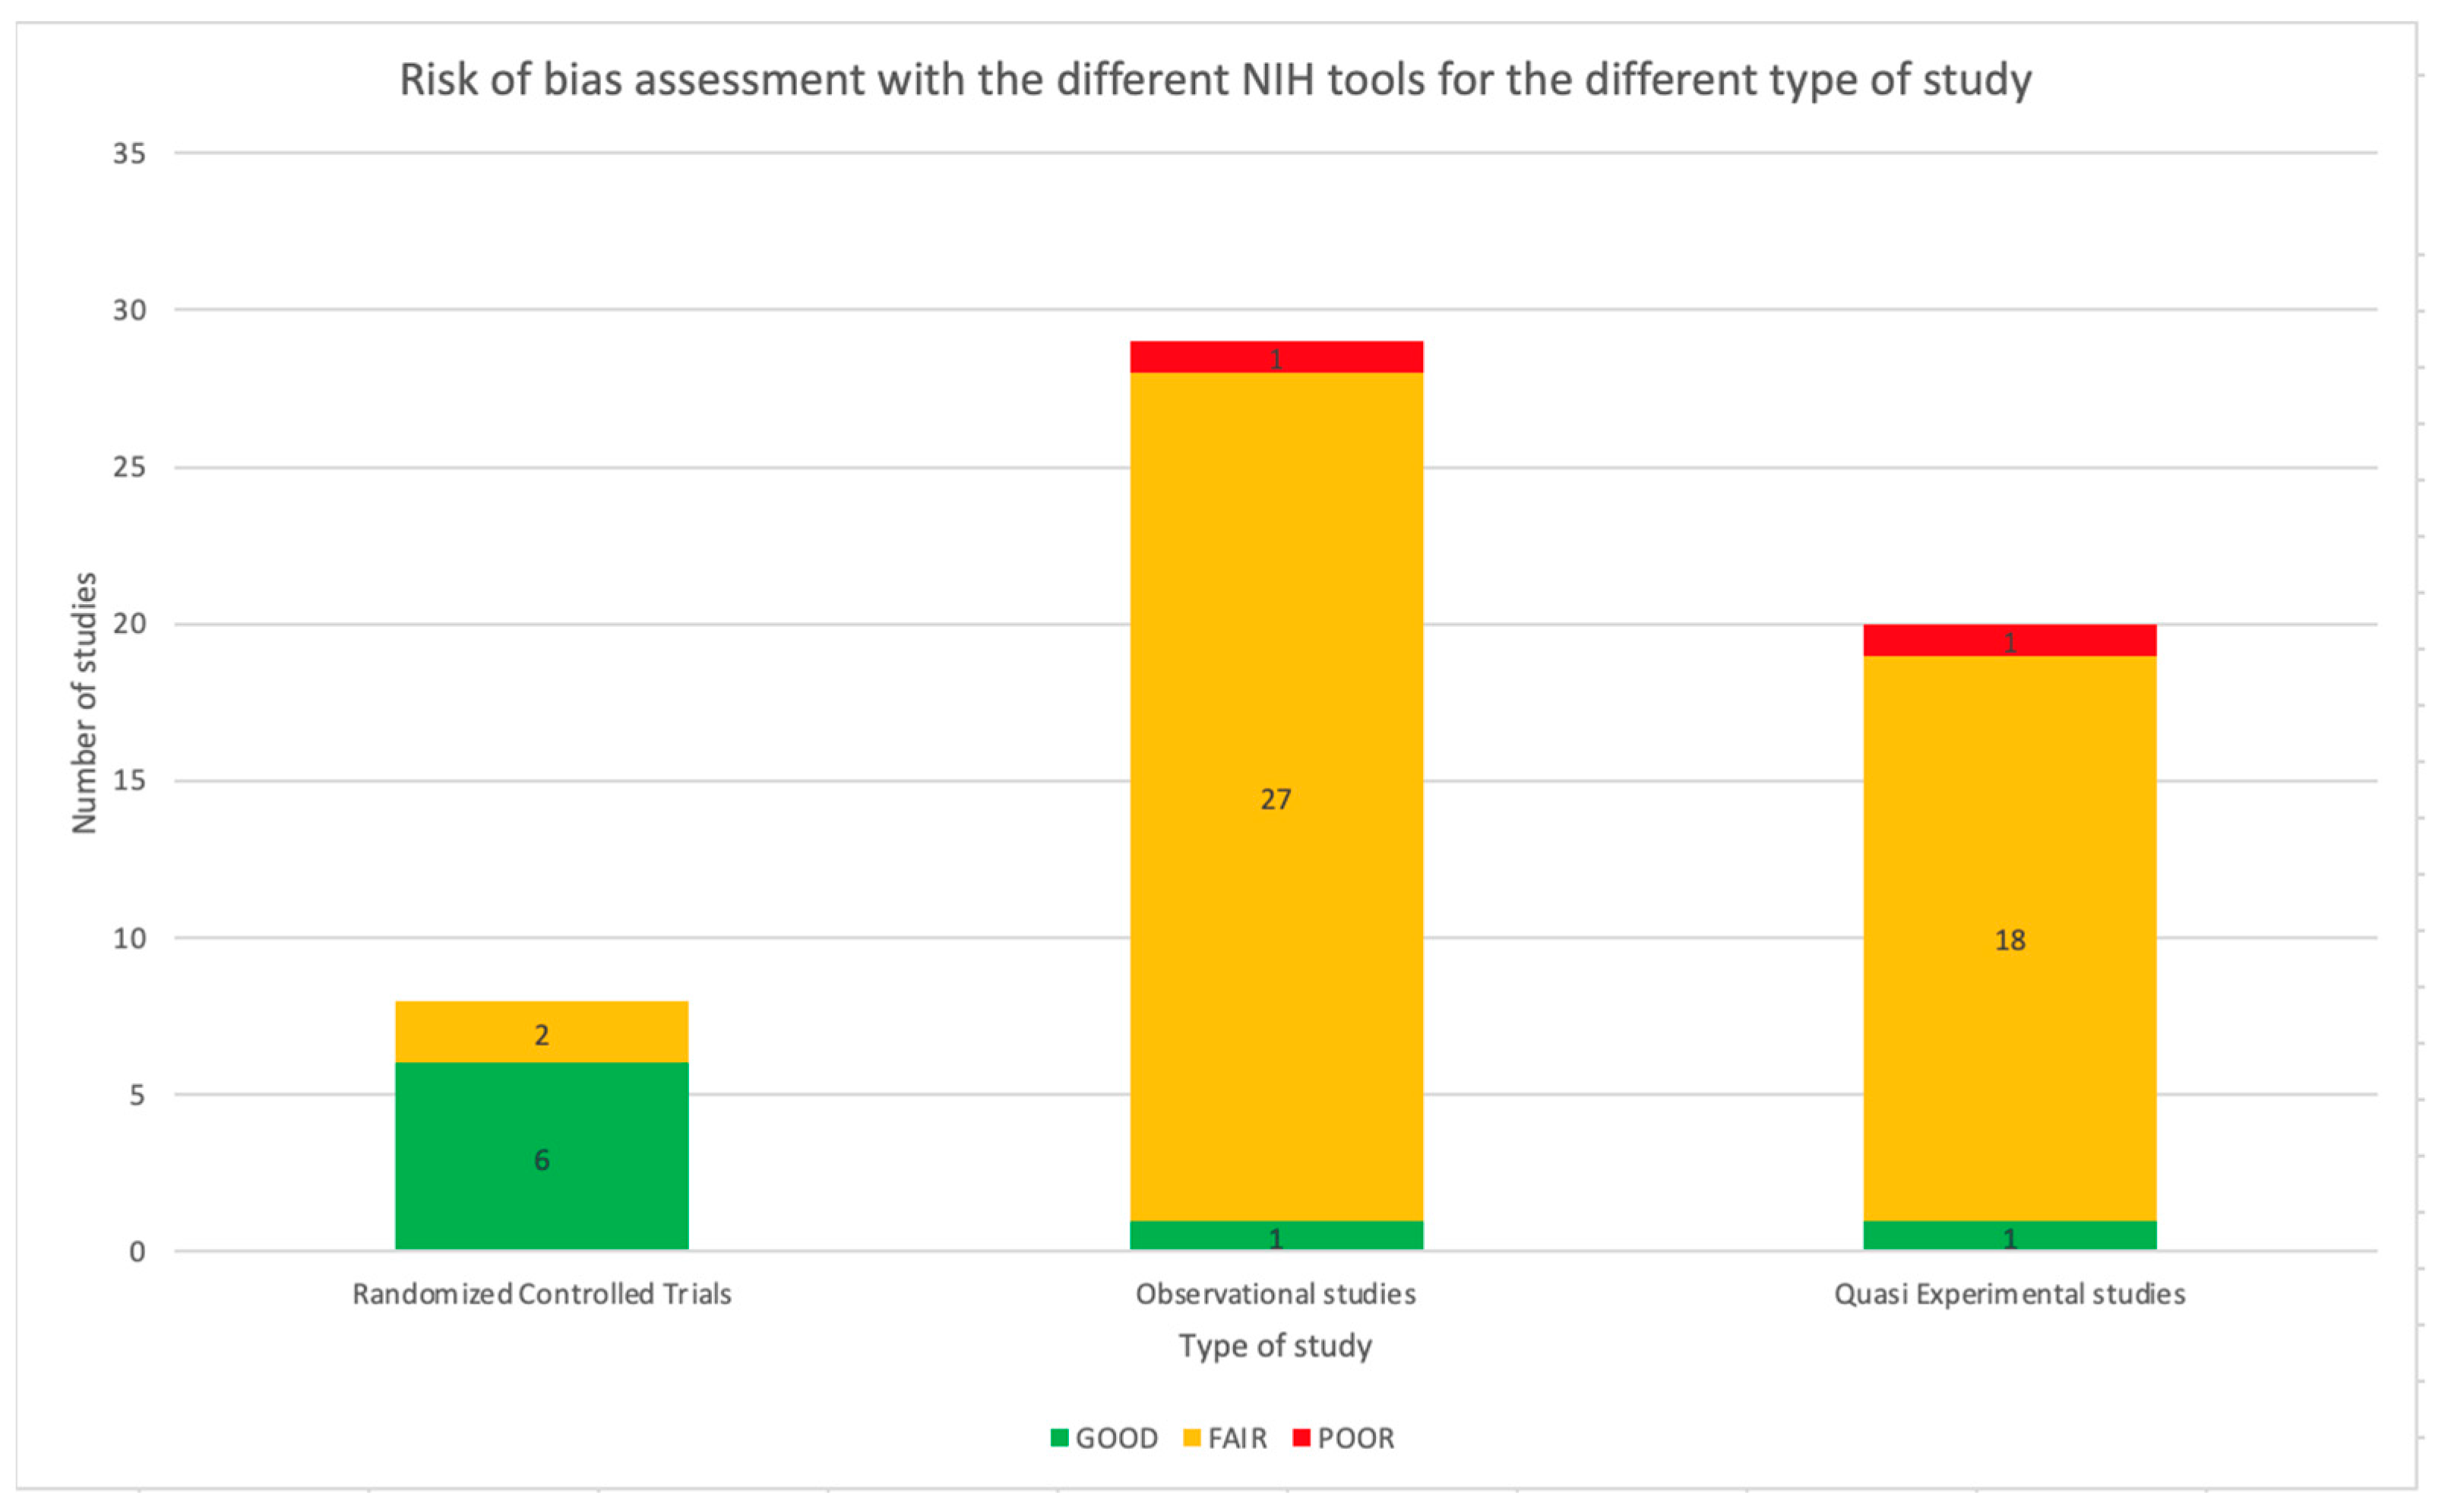
The NIH Quality Assessment Tool was applied to all 57 studies. As reported in Table 1, 47 studies (82.5%) were assessed as fair, two as poor, and eight as good using a specific tool based on the type of study. Referring to RCT, 75.0% of the studies were considered good (6/8). The remaining two studies were assessed as fair. Considering the observational studies, meant as cohort studies, prospective and retrospective studies, most of the papers were considered as fair (27/29, 93.1%) and one as poor (1/29, 3.4%). Only one study was assessed as good (1/29, 3.4%). Most of the before and after studies were considered fair (18/19, 94.7%), while the other study was assessed as poor (1/19, 5.3%). Figure 8 shows the distribution of the quality assessment for the different types of studies. The complete quality assessment of each study is reported in Tables S1–S4 in the Supplementary Material.
Figure 8.
Risk of bias assessment with the different NIH tools for the different types of studies.
3. Discussion
Rapid tests and POCTs are important tools to help clinicians discriminate the risk of infection and differentiate between viral and bacterial pathogens. Many rapid tests and POCTs are available nowadays, ranging from quick lab tests to microbiological arrays to even ultrasound bedside imaging protocols.
Advances in technology and recent innovations have allowed diagnostics to enlarge their scope, increase accuracy, minimize the time required for results and, above all, reduce their costs. This leads to the actual usage and applicability of these tests in routine diagnostic evaluation in adults [65]. When efficiently implemented into the diagnostic process, the most valuable characteristic of rapid tests is the shorter time to results, leading to more rapid clinical decisions than the standard test.
Respiratory, gastrointestinal, blood, and cerebrospinal fluid (CSF) arrays have been recently developed and evaluated for the diagnostic workup of outpatient, inpatient, and ED settings also in children, with no univocal interpretation of their utility. Despite these doubts, the potential of the new technologies and new diagnostics is still considered of great value [66].
Indeed, the chance to discriminate the presence of infection with more rapid tests is essential for developing institutional programs to enhance antimicrobial stewardship. As predictable, almost 80% of studies on rapid test implementation were performed after 2007. A further increase occurred during the last two years of the COVID-19 pandemic, with a quarter of studies conducted from 2019 to 2021 since differentiating between viral and bacterial infections has become more crucial [67].
Although rapid tests and POCTs have already been proven valuable and feasible in the adult population, both in outpatient and hospital settings [68,69], studies in children are still lacking.
To our knowledge, this is the first systematic review evaluating rapid tests and POCTs in pediatric settings worldwide and their impact on antimicrobial prescription, healthcare costs, and patient outcomes.
A wide heterogeneity in the use of rapid tests for febrile children with respiratory tract infections emerged. More than 75% of studies reported the implementation of POCTs in hospital settings. In outpatient and primary care practice, Strep A rapid test and influenza tests were the most commonly used POCTs. This is not surprising considering the need for a nearby laboratory to perform other tests such as FA-RP that require different procedures for the analysis of the sample (immunofluorescence, array, molecular probe, etc.). In contrast, the rapid antigen tests represent a quicker (15–30 min) tool that can be undertaken at the bedside. Nevertheless, their use still seems not as widespread compared to the in-hospital setting, and this could also be related to the costs of the POCT and the lack of diagnostic stewardship programs that involve general practitioners and pediatricians working in primary care practices.
Almost 80% of studies on rapid test or POCT usage have been performed in Europe and North America, with only a few in East Asia and none in Africa. Due to their simplicity and quick response, there is wide potential in the implementation of POCTs in low- and middle-income countries and in remote or resource-poor settings with no laboratory infrastructure. However, the simple availability of rapid or easy tests does not ensure their implementation [70,71]. As reported by Pai et al. [72], there are considerable barriers to the widespread use of POCTs at primary levels of the healthcare system, which could be related to the lack of training of physicians or of economic resources to buy them. Nevertheless, it is important to highlight that we did not consider for our review many POCTs that could be more useful in low- and middle-income countries than in high-income countries, such as HIV, HCV, malaria, and tuberculosis POCTs.
Rapid differentiation of respiratory infection in non-critically ill children is essential to positively affect the rate of antibiotic prescriptions. This outcome was assessed for the out-patient setting in 86% of all studies worldwide (80%, 89.5%, and 87.5% of studies in North America, Europe, and Asia, respectively). Regardless of setting, country, and type of test, prescriptions rate seems to be positively affected in 65.3% of cases by rapid tests or POCTs implementation.
More evidence on rapid tests and POCTs for respiratory pathogens in improving both antibacterial and antiviral prescriptions results from the meta-analysis of RIDT and FA-RP.
Different results are reported comparing a positive RIDT result with a negative one or comparing the use of RIDT, regardless of the results, to the clinical diagnosis. In the first case, assessing influenza virus as causative of the clinical presentation of the patients, leads to a reduction in antibiotic prescription. Instead, in the second case, the reduction in antibiotic prescription seems to be less significant. This could be related to different reasons, probably depending on physicians’ prescribing attitudes and intrinsic study limitations.
Even if no definite statement can be made, it is interesting to notice that the trend towards fewer prescriptions is stronger in Europe than in the USA. IDSA guidelines for influenza strengthen the efficacy of an empirical antibacterial therapy to be started in case of deterioration or failure to improve in patients with this diagnosis, especially those with comorbidities [73,74]. Moreover, in the US, antimicrobial stewardship programs have been widespread for longer, so the impact of rapid tests and POCTs in further reducing antibiotics may appear less significant.
Similar results can be extracted from studies evaluating FA-RP, confirming an overall reduction in antibiotic prescriptions. However, as displayed for RIDT, when comparing FA-RP to clinical diagnosis, the evidence for this outcome becomes less strong, despite results from two RCTs assessed as good through the NIH quality assessment rate. Unlike RIDT, this trend appears more significant in the US than in Europe, maybe because the prescription of antibiotics in Europe remains higher for respiratory non-influenza viruses for fear of possible bacterial co-infections [75,76,77]. For example, British guidelines for community-acquired pneumonia (CAP) suggest that all children with a clear clinical diagnosis of CAP should receive antibiotics as bacterial and viral pathogens cannot reliably be distinguished from each other, especially with persistent symptoms [78].
Interestingly, the two studies on the implementation of the rapid test for RSV showed no significant difference in the antibiotic prescription between those testing positive and those negative, suggesting that factors others than the specific etiology determined the decision about prescription. In the study of Thibeault [52], factors associated independently with the cessation of intravenous antibiotics in the case of a positive test for RSV were the age > 3 months and the absence of pneumonia. This is probable due to the fact that young infants are more likely to have severe outcomes than older ones and that the risk of bacterial coinfection could be perceived greater by physicians in case of presence of pneumonia. This is in line with what was found by a Spanish study based on a mail questionnaire, showing that the fear of complications from infections is one of the factors related to the prescribing of antibiotics by general practitioners even if not necessary. Indeed, many physicians agreed that when in doubt as to whether a patient had a bacterial infection, it was better to prescribe a broad-spectrum antibiotic [79,80].
It is important to highlight this point, because it is known that the implementation of these tests alone is often not enough to change antimicrobial prescription patterns [81].
Unfortunately, only six studies included in this review specified whether an antimicrobial stewardship program (ASP) was implemented at the same time of the introduction of the point of care test and in only one the introduction of a rapid test was concomitant with the implementation of an ASP. The implementation of educational interventions combined with the introduction of rapid tests could further improve the antibiotic prescription, as it is also emphasized by a review published in 2018 to ensure rational use of antibiotics [82].
The meta-analysis highlighted as the strongest evidence the improvement of oseltamivir prescription from overall use of RIDT. According to the IDSA guideline on managing seasonal influenza, oseltamivir should be prescribed to patients at high risk of complications from influenza. Regarding children, it is recommended for children aged < 5 years and especially aged < 2 years, children with hematological disease (including sickle cell disease), metabolic disease (diabetes, obesity), immunosuppression, and children and adolescents through 18 years who are receiving aspirin and who might be at risk of Reye Syndrome [73].
Analysis for FA-RP shows a trend toward a more appropriate prescription of antivirals, despite a significant difference. It could be related to the usefulness of this test for detecting a broad spectrum of pathogens rather than influenza only; therefore, this outcome can be limited by less a pre-test probability for clinical, seasonal, or epidemiological reasons.
Unfortunately, no significant data could be extrapolated from RIDT and FA-RP studies for meta-analysis regarding secondary outcomes considered in this review (DOTs, LOS, and healthcare costs). A trend in reduction of DOTs was only evaluated from three studies of FA-RP without a significant difference.
Almost half of the studies in our review reported an overall significant reduction of LOS using the rapid tests, particularly in ED, due to faster clinical decisions. Nevertheless, it is difficult to assess this outcome in hospitalized children because of other possible confounders (e.g., severity of symptoms, comorbidities, complications). For such patients, a decline in the duration of treatment seems to be more relevant. Interestingly, three-quarters of the studies reporting DOTs and LOS as outcomes were conducted in Europe (4/18, 22.2% and 9/34, 26.5%, respectively) and North America (9/18, 50.0% and 17/34, 50.0%, respectively).
The effects of rapid tests and POCTs on healthcare costs have been assessed in only one-third of studies, almost all conducted in hospital settings, with a positive correlation in terms of cost-saving. Whereas other outcomes (rate of prescriptions, LOS, or DOTs) can be easily measured, healthcare cost evaluation involves a more complex analysis to be performed by the authors. Thus, although rapid tests and POCTs should theoretically be cost-saving tools, less evidence emerged from this review that cannot be transferred to outpatient settings.
Finally, considerations can be made from the quality assessment of studies. Most RCTs have been assessed as good using the standardized NIH tool. Only two studies were considered fair, mainly due to an overall drop-out rate higher than 20% and an included population that had not reached the pre-planned sample size. In none of the studies, participants, providers, or people assessing the outcomes were blinded to the intervention. The majority of the observational and before and after studies have been judged as fair. Most of the studies did not have a pre-planned sample size calculation; therefore, it was not possible to assess the statistical power of the studies. Indeed, no studies reported the blinding of the outcome assessors and not all the potentially confounding variables were always measured and adjusted statistically.
It would be desirable that before and after studies, with preplanned sample size calculation or blinded, randomized, clinical trials would be proposed and conducted both in high and low–middle income countries.
Limitations
The limitations of this study are primarily related to the vast heterogeneity of studies focused on the use of rapid tests and POCTs in pediatric settings. Beyond the type of rapid tests evaluated, another source of variability was due to different brand names used for testing, which involves non-uniform reliability of tests in terms of sensitivity, specificity, and positive or negative predictive value. The authors also did not consider different pre-test probability related to the type of infection for most cases. Moreover, the majority of studies analyzed for this review were set in high-income countries, thus, results and conclusions cannot be broadened to low-resources countries.
All of this was also exacerbated by different modalities for outcome assessment which complicated the comparison between studies.
4. Materials and Methods
4.1. Study Design and Search Strategy
This systematic review is based on the Preferred Reporting Items for Systematic Reviews and Meta-analyses (PRISMA) guidelines [83]. Embase, MEDLINE, and Cochrane Library databases were systematically searched, combining terms for “children”, “rapid test”, “Point of care test”, and “Outcome Assessment”, with restrictions on dates from 1 January 2000, to 11 September 2021. The full strategy is provided in Supplementary Material File S1.
The review protocol was registered at the PROSPERO International Prospective Register of Systematic Reviews: Registration Number CRD 42022345124.
4.2. Inclusion Criteria and Outcomes
Studies evaluating the effect of the implementation of rapid tests and POCTs for respiratory tract infections that included patients younger than 21 years, both in outpatient or in-hospital settings, were considered for full-text review. Even if the child age is usually considered until 14 years old, we decided to include children until 21 years old because some centers accept these younger adults in the Pediatric Emergency Department.
POCTs were considered those tests for which the sample was analyzed near the patient itself, for example, the Rapid Influenza Diagnostic Test (RIDT) and Strep A test. Instead, rapid tests were those tests for which the sample was collected and then sent to a laboratory that analyzed it and gave results in few hours, for example, the film-array test or PCR for respiratory virus.
Randomized controlled trials, controlled and non-controlled before and after studies, controlled and non-controlled interrupted time series, and cohort studies conducted in all income level countries were included. The primary outcome considered for the final review was the change in the rate of antimicrobial prescriptions (antibacterial and/or antiviral); secondary outcomes included days of therapy (DOTs), length of stay (LOS), and healthcare costs.
4.3. Exclusion Criteria
Review, case series, notes and letters, conference abstracts, and opinion articles were excluded. Papers on both adults and children were also excluded if extraction of pediatric data was not possible. Papers on rapid tests and POCTs for HIV, malaria, tuberculosis, hepatitis B or C virus, parasites, or sexually transmitted infections were also excluded. Studies validating rapid tests’ or POCTs’ diagnostic accuracy or only with epidemiological analysis were excluded. Papers on rapid tests on blood, stool, or cerebrospinal fluid were excluded.
4.4. Study Selection
In line with the PRISMA guidelines for systemic reviews, titles and abstracts identified through an electronic database were independently screened by three reviewers (GB, AG, MM), and any references which did not meet the inclusion criteria were excluded. For all remaining references, three reviewers obtained full-text copies and independently examined them in detail to determine whether they met all the inclusion criteria for the review. Discussion with a fourth reviewer (DD) resolved any disagreement regarding study selection.
4.5. Data Collection
Data were extracted using a standardized data collection form. The following data from each included paper were extracted, where reported: study characteristics (authors, year of publication, study design, study location, multicenter involvement, country); patient characteristics (age, care setting, inclusion and exclusion criteria); type of rapid test or POCT; main results with accuracy measures; outcomes (e.g., rate of antibiotic and antiviral prescription, days of therapy); patient care (e.g., length of stay); economic outcomes.
The income level of each country was defined according to the World Bank List of economies published in July 2021 [7].
4.6. Risk of Bias in Individual Studies
Three reviewers independently rated the quality of the included studies using the National Institutes of Health (NIH) Quality Assessment Tool [84]. Based on the type of study, a different NIH tool was used. The overall assessment was good, fair, or poor. The tools with 14 questions were classified as poor if the score was between 0 and 5, fair if between 6 and 10, and good if between 11 and 14. The tools with 12 questions were classified as poor if the score was between 0 and 4, fair if between 5 and 8, and good if between 9 and 12.
4.7. Statistical Analysis
When sufficient outcome data were available, we performed meta-analyses. The effect of the intervention was evaluated using the dichotomized measure of odds ratio (OR) and a mean difference (MD) value when different outcome measurements were present for continuous outcomes, along with 95% confidence intervals (CI). Heterogeneity between study-specific estimates was tested using chi-squared statistics and measured with the I2 index (a measure of the percentage variation across the studies caused by heterogeneity) and the Cochran’s Q test [85,86]. A pooled estimate was obtained by fitting the DerSimonian and Laird random-effects model [87], which takes into account both the sampling variance within the studies and the variation in the underlying effect across studies. Separated analyses were performed depending on the study design, observational or randomized controlled studies. Furthermore, subgroup analyses were planned (1) by age group (e.g., less than 5 years or 18 years) and (2) geographical locations (e.g., USA or European countries). All tests were considered significant statistically, for p < 0.05. The analyses were performed using Review Manager Version 5.4 (Cochrane Collaboration, London, UK).
5. Conclusions
The findings of this systematic review seem to support the implementation of rapid tests and POCTs as a valuable tool to improve antimicrobial prescribing, both reducing unnecessary antibiotics administration and the duration of therapy and increasing appropriate oseltamivir usage. Furthermore, even if it was not possible to perform a metanalysis, the use of rapid tests also seems to be useful in reducing turnaround time and length of stay, particularly in hospital settings.
However, more well-designed studies are still needed to reliably assess the implementation of rapid tests and POCTs in pediatric settings, both in high and low-middle income countries, in order to improve patients’ outcomes and reduce unnecessary prescriptions and healthcare costs.
It is also advocated that implementation of rapid tests should be constantly combined within well-structured antimicrobial stewardship programs, as recommended by international societies for infection and antibiotic resistance control, to improve antimicrobial prescription further.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/antibiotics11091192/s1, Supplementary Material File S1: Search strategy; Figure S1: Forest plot of prescription of antibiotics after implementation of FA-RP; Figure S2: Forest plot of prescription of antibiotics after implementation of RIDT; Figure S3: Forest plot of prescription of antibiotics after implementation of RIDT; Figure S4: Forest plot (A) of prescription of oseltamivir after implementation of FA-RP versus standard test stratified for different countries; (B) of days of therapy after implementation of FA-RP versus standard test; Table Supplementary: NIH assessment tools.
Author Contributions
D.D., G.B. and A.G. conceived the idea. G.B., A.G. and M.M. conducted the assessments of the titles, abstracts, and full texts independently. D.D., E.B., G.B., A.G., M.M. and S.R. discussed study selection and study details and decided which studies were to be included in the review. G.B., A.G. and M.M. performed the numerical calculations and the assessment of bias. A.B., A.C. performed statistical analysis. G.B., A.G. and M.M. wrote the manuscript with input from all authors. D.D. and E.B. supervised and revised the manuscript. C.G. and L.D.D. revised the manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This study was supported by grants from the Italian Ministry of the Education, University and Research (‘PRIN’ 2017, project 2017728JPK. Modelling Effectiveness, Cost-effectiveness, and Promoting Health Care Value in the Real World: the MOTIVE Project).
Conflicts of Interest
The authors declare no conflict of interest.
References
- Sands, R.; Shanmugavadivel, D.; Stephenson, T.; Wood, D. Medical problems presenting to paediatric emergency departments: 10 Years on. Emerg. Med. J. 2012, 29, 379–382. [Google Scholar] [CrossRef] [Scilit]
- Dellit, T.H.; Owens, R.C.; McGowan, J.E.; Gerding, D.N.; Weinstein, R.A.; Burke, J.P.; Huskins, W.C.; Paterson, D.L.; Fishman, N.O.; Carpenter, C.F.; et al. Infectious Diseases Society of America and the Society for Healthcare Epidemiology of America Guidelines for Developing an Institutional Program to Enhance Antimicrobial Stewardship. Clin. Infect. Dis. 2007, 44, 159–177. [Google Scholar]
- Hecker, M.T.; Aron, D.C.; Patel, N.P.; Lehmann, M.K.; Donskey, C.J. Unnecessary Use of Antimicrobials in Hospitalized Patients. Arch. Intern. Med. 2003, 163, 972–978. [Google Scholar] [CrossRef] [Scilit]
- Messacar, K.; Gaensbauer, J.T.; Birkholz, M.; Palmer, C.; Todd, J.K.; Tyler, K.L.; Dominguez, S.R. Impact of FilmArray meningitis encephalitis panel on HSV testing and empiric acyclovir use in children beyond the neonatal period. Diagn. Microbiol. Infect. Dis. 2020, 97, 115085. [Google Scholar] [CrossRef] [Scilit]
- Samuel, L. Point-of-Care Testing in Microbiology. Clin. Lab. Med. 2020, 40, 483–494. [Google Scholar] [CrossRef] [Scilit]
- Moher, D.; Liberati, A.; Tetzlaff, J.; Altman, D.G.; PRISMA Group. Preferred reporting items for systematic reviews and meta-analyses: The PRISMA statement. PLoS Med. 2009, 6, e1000097. [Google Scholar] [CrossRef] [Scilit]
- New World Bank Country Classifications by Income Level: 2021–2022. Available online: https://blogs.worldbank.org/opendata/new-world-bank-country-classifications-income-level-2021-2022 (accessed on 22 February 2022).
- Nitsch-Osuch, A.; Kuchar, E.; Gołębiak, I.; Kanecki, K.; Tarka, P.; Brydak, L.B. Rapid influenza diagnostic tests improve suitability of antiviral treatment in hospitalized children. Adv. Exp. Med. Biol. 2017, 968, 1–6. [Google Scholar]
- Vecino-Ortiz, A.I.; Goldenberg, S.D.; Douthwaite, S.T.; Cheng, C.-Y.; Glover, R.E.; Mak, C.; Adams, E.J. Impact of a multiplex PCR point-of-care test for influenza A/B and respiratory syncytial virus on an acute pediatric hospital ward. Diagn. Microbiol. Infect. Dis. 2018, 91, 331–335. [Google Scholar] [CrossRef] [Scilit]
- Abanses, J.C.; Dowd, M.D.; Simon, S.D.; Sharma, V. Impact of rapid influenza testing at triage on management of febrile infants and young children. Pediatr. Emerg. Care 2006, 22, 145–149. [Google Scholar] [CrossRef] [Scilit]
- Diallo, D.; Hochart, A.; Lagree, M.; Dervaux, B.; Martinot, A.; Dubos, F. Impact of the Sofia® Influenza A+B FIA rapid diagnostic test in a pediatric emergency department. Arch. Pediatr. 2019, 26, 6–11. [Google Scholar]
- Noyola, D.E.; Demmler, G.J. Effect of rapid diagnosis on management of influenza A infections. Pediatr. Infect. Dis. J. 2000, 19, 303–307. [Google Scholar] [CrossRef] [Scilit]
- Özkaya, E.; Cambaz, N.; Çoşkun, Y.; Mete, F.; Geyik, M.; Samanci, N. The effect of rapid diagnostic testing for influenza on the reduction of antibiotic use in paediatric emergency department. Acta Paediatr. Int. J. Paediatr. 2009, 98, 1589–1592. [Google Scholar] [CrossRef] [Scilit]
- Bonner, A.B.; Monroe, K.W.; Talley, L.I.; Klasner, A.E.; Kimberlin, D.W. Impact of the Rapid Diagnosis of Influenza on Physician Decision-Making and Patient Management in the Pediatric Emergency Department: Results of a Randomized, Prospective, Controlled Trial. Pediatrics 2003, 112, 363–367. [Google Scholar] [CrossRef] [Scilit]
- Cantais, A.; Mory, O.; Plat, A.; Bourmaud, A.; Giraud, A.; Costille, M.; Pozzetto, B.; Pillet, S. Impact of bedside diagnosis of influenza in the paediatric emergency ward. Clin. Microbiol. Infect. 2018, 25, 898–903. [Google Scholar]
- Iyer, S.B.; Gerber, M.A.; Pomerantz, W.J.; Mortensen, J.E.; Ruddy, R.M. Effect of Point-of-care Influenza Testing on Management of Febrile Children. Acad. Emerg. Med. 2006, 13, 1259–1268. [Google Scholar]
- Jacob, R.; White, B.; McCaskill, M.E. Does location of rapid influenza diagnostic testing influence treatment time and ancillary testing in a paediatric emergency department? EMA-Emerg. Med. Australas. 2021, 33, 88–93. [Google Scholar] [CrossRef] [Scilit]
- Jun, S.H.; Kim, J.Y.; Yoon, Y.H.; Lim, C.S.; Ch, H.J.; Choi, S.H. The effect of the rapid antigen test for influenza on clinical practice in the emergency department: A comparison of periods before and after the 2009 H1N1 influenza pandemic. Signa Vitae 2016, 11, 74–89. [Google Scholar]
- Li-Kim-Moy, J.; Dastouri, F.; Rashid, H.; Khandaker, G.; Kesson, A.; McCaskill, M.; Wood, N.; Jones, C.; Zurynski, Y.; Macartney, K.; et al. Utility of early influenza diagnosis through point-of-care testing in children presenting to an emergency department. J. Paediatr. Child Health 2016, 52, 422–429. [Google Scholar]
- Sharma, V.; Dowd, M.D.; Slaughter, A.J.; Simon, S.D. Effect of rapid diagnosis of influenza virus type A on the emergency department management of febrile infants and toddlers. Arch. Pediatr. Adolesc. Med. 2002, 156, 41–43. [Google Scholar] [CrossRef] [Scilit]
- Patel, P.; Laurich, V.M.; Smith, S.; Sturm, J. Point-of-care influenza testing in the pediatric emergency department. Pediatr. Emerg. Care 2020, 36, 515–518. [Google Scholar] [CrossRef] [Scilit]
- Pierron, S.; Haas, H.; Berlioz, M.; Ollier, L.; Albertini, M. Impact of rapid influenza test during influenza epidemic in all febrile children less than 6 years old in a pediatric emergency departmentl. Arch. Pediatr. Organe Off. Soc. Fr. Pediatr. 2008, 15, 1283–1288. [Google Scholar] [CrossRef] [Scilit]
- Benito-Fernández, J.; Vázquez-Ronco, M.A.; Morteruel-Aizkuren, E.; Mintegui-Raso, S.; Sánchez-Etxaniz, J.; Fernández-Landaluce, A. Impact of rapid viral testing for influenza A and B viruses on management of febrile infants without signs of focal infection. Pediatr. Infect. Dis. J. 2006, 25, 1153–1157. [Google Scholar] [CrossRef] [Scilit]
- Poehling, K.A.; Zhu, Y.; Tang, Y.W.; Edwards, K. Accuracy and impact of a point-of-care rapid influenza test in young children with respiratory illnesses. Arch. Pediatr. Adolesc. Med. 2006, 160, 713–718. [Google Scholar] [CrossRef] [Scilit]
- Jennings, L.C.; Skopnik, H.; Burckhardt, I.; Hribar, I.; del Piero, L.; Deichmann, K.A. Effect of rapid influenza testing on the clinical management of paediatric influenza. Influenza Other Respi. Viruses 2009, 3, 91–98. [Google Scholar] [CrossRef] [Scilit]
- Nitsch-Osuch, A.; Stefańska, I.; Kuchar, E.; Brydak, L.B.; Pirogowicz, I.; Życińska, K.; Wardyn, K. Influence of rapid influenza test on clinical management of children younger than five with febrile respiratory tract infections. Adv. Exp. Med. Biol. 2013, 755, 237–241. [Google Scholar] [PubMed]
- van Esso, D.L.; Valente, A.M.; Vilà, M.; Casanovas, J.M.; de Quixano, M.; Rodrigo, C.; Anton, A.; Pumarola, T. Rapid Influenza Testing in Infants and Children Younger than 6 Years in Primary Care: Impact on Antibiotic Treatment and Use of Health Services. Pediatr. Infect. Dis. J. 2019, 38, E187–E189. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cohen, R.; Thollot, F.; Lécuyer, A.; Koskas, M.; Touitou, R.; Boucherat, M.; D’Athis, P.; Corrard, F.; Pecking, M.; de La Rocque, F. Impact des tests de diagnostic rapide en ville dans la prise en charge des enfants en période de grippe. Arch. Pediatr. 2007, 14, 926–931. [Google Scholar] [CrossRef] [Scilit]
- de La Rocque, F.; Lecuyer, A.; Wollner, C.; d’Athis, P.; Pecking, M.; Thollot, F.; Cohen, R. Impact des tests de diagnostic rapide de la grippe dans la prise en charge des enfants en période d’épidémie en pédiatrie de ville. Arch. Pediatr. 2009, 16, 288–293. [Google Scholar] [CrossRef] [Scilit]
- Keske, Ş.; Ergönül, Ö.; Tutucu, F.; Karaaslan, D.; Palaoğlu, E.; Can, F. The rapid diagnosis of viral respiratory tract infections and its impact on antimicrobial stewardship programs. Eur. J. Clin. Microbiol. Infect. Dis. 2018, 37, 779–783. [Google Scholar] [CrossRef] [Scilit]
- Kitano, T.; Nishikawa, H.; Suzuki, R.; Onaka, M.; Nishiyama, A.; Kitagawa, D.; Oka, M.; Masuo, K.; Yoshida, S. The impact analysis of a multiplex PCR respiratory panel for hospitalized pediatric respiratory infections in Japan. J. Infect. Chemother. 2019, 26, 82–85. [Google Scholar] [CrossRef] [Scilit]
- Lee, B.R.; Hassan, F.; Anne, M.; Selvarangan, R. Impact of multiplex molecular assay turn-around-time on antibiotic utilization and clinical management of hospitalized children with acute respiratory tract infections. J. Clin. Virol. 2018, 110, 11–16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reischl, A.T.; Schreiner, D.; Poplawska, K.; Kidszun, A.; Zepp, F.; Gröndahl, B.; Gehring, S. The clinical impact of PCR-based point-of-care diagnostic in respiratory tract infections in children. J. Clin. Lab. Anal. 2020, 34, e23203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schulert, G.S.; Lu, Z.; Wingo, T.; Tang, Y.W.; Saville, B.R.; Hain, P.D. Role of a respiratory viral panel in the clinical management of pediatric inpatients. Pediatr. Infect. Dis. J. 2013, 32, 467–472. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Subramony, A.; Zachariah, P.; Krones, A.; Whittier, S.; Saiman, L. Impact of multiplex polymerase chain reaction testing for respiratory pathogens on healthcare resource utilization for pediatric inpatients. J. Pediatr. 2016, 173, 196–201.e2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Walls, T.; Stark, E.; Pattemore, P.; Jennings, L. Missed opportunities for antimicrobial stewardship in pre-school children admitted to hospital with lower respiratory tract infection. J. Paediatr. Child Health 2017, 53, 569–571. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yoshida, K.; Hatachi, T.; Okamoto, Y.; Aoki, Y.; Kyogoku, M.; Miyashita, K.M.; Inata, Y.; Shimizu, Y.; Fujiwara, F.; Takeuchi, M. Application of Multiplex Polymerase Chain Reaction for Pathogen Identification and Antibiotic Use in Children With Respiratory Infections in a PICU. Pediatr. Crit. Care Med. 2021, 22, e644–e648. [Google Scholar] [CrossRef] [Scilit]
- McCulloh, R.J.; Andrea, S.; Reinert, S.; Chapin, K. Potential utility of multiplex amplification respiratory viral panel testing in the management of acute respiratory infection in children: A retrospective analysis. J. Pediatr. Infect. Dis. Soc. 2014, 3, 146–153. [Google Scholar] [CrossRef] [Scilit]
- McFall, C.; Salimnia, H.; Lephart, P.; Thomas, R.; McGrath, E. Impact of Early Multiplex FilmArray Respiratory Pathogen Panel (RPP) Assay on Hospital Length of Stay in Pediatric Patients Younger Than 3 Months Admitted for Fever or Sepsis Workup. Clin. Pediatr. 2018, 57, 1224–1226. [Google Scholar] [CrossRef] [Scilit]
- Tam, P.Y.I.; Zhang, L.; Cohen, Z. Impact of a transition from respiratory virus shell vial to multiplex PCR on clinical outcomes and cost in hospitalized children. Children 2017, 4, 3. [Google Scholar]
- Kim, Y.K.; Lee, J.H.; Kim, S.Y.; Ahn, J.Y.; Choi, K.H.; Lee, Y.H.; Jang, K.M.; Hau, Y.S.; Lee, J.M. Rapid Molecular Tests for Detecting Respiratory Pathogens Reduced the Use of Antibiotics in Children. Antibiotics 2021, 10, 283. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rogers, B.B.; Shankar, P.; Jerris, R.C.; Kotzbauer, D.; Anderson, E.J.; Watson, J.R.; O’Brien, L.A.; Uwindatwa, F.; McNamara, K.; Bost, J.E. Impact of a Rapid Respiratory Panel Test on Patient Outcomes. Arch. Pathol. Lab. Med. 2014, 139, 636–641. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Busson, L.; Bartiaux, M.; Brahim, S.; Konopnicki, D.; Dauby, N.; Gérard, M. Contribution of the FilmArray Respiratory Panel in the management of adult and pediatric patients attending the emergency room during 2015–2016 influenza epidemics: An interventional study. Int. J. Infect. Dis. 2019, 83, 32–39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Byington, C.L.; Castillo, H.; Gerber, K.; Daly, J.A.; Brimley, L.A.; Adams, S.; Christenson, J.C.; Pavia, A.T. The Effect of Rapid Respiratory Viral Diagnostic Testing on Antibiotic Use in a Children’s Hospital. Arch. Pediatr. Adolesc. Med. 2002, 156, 1230–1234. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Crook, J.; Xu, M.; Slaughter, J.C.; Willis, J.; Browning, W.; Estrada, C.; Gay, J.; Thomas, G.; Benton, A.; Quinn, C.; et al. Impact of clinical guidance and rapid molecular pathogen detection on evaluation and outcomes of febrile or hypothermic infants. Infect. Control Hosp. Epidemiol. 2020, 41, 1285–1291. [Google Scholar] [CrossRef] [Scilit]
- Dimopoulou, D.; Vourli, S.; Douros, K.; Pournaras, S.; Papaevangelou, V. Use of point-of-care molecular tests reduces hospitalization and oseltamivir administration in children presenting with influenza-like illness. J. Med. Virol. 2021, 93, 3944–3948. [Google Scholar] [CrossRef] [Scilit]
- Rao, S.; Lamb, M.M.; Moss, A.; Mistry, R.D.; Grice, K.; Ahmed, W.; Santos-Cantu, D.; Kitchen, E.; Patel, C.; Ferrari, I. Effect of Rapid Respiratory Virus Testing on Antibiotic Prescribing among Children Presenting to the Emergency Department with Acute Respiratory Illness: A Randomized Clinical Trial. JAMA Netw. Open 2021, 4, e2111836. [Google Scholar] [CrossRef] [Scilit]
- Echavarría, M.; Marcone, D.; Querci, M.; Seoane, A.; Ypas, M.; Videla, C.; O’Farrell, C.; Vidaurreta, S.; Ekstrom, J.; Carballal, G. Clinical impact of rapid molecular detection of respiratory pathogens in patients with acute respiratory infection. J. Clin. Virol. 2018, 108, 90–95. [Google Scholar] [CrossRef] [Scilit]
- May, L.; Tatro, G.; Poltavskiy, E.; Mooso, B.; Hon, S.; Bang, H.; Polage, C. Rapid Multiplex Testing for Upper Respiratory Pathogens in the Emergency Department: A Randomized Controlled Trial. Open Forum Infect. Dis. 2019, 6, ofz481. [Google Scholar] [CrossRef] [Scilit]
- Wishaupt, J.O.; Russcher, A.; Smeets, L.C.; Versteegh, F.G.A.; Hartwig, N.G. Clinical Impact of RT-PCR for Pediatric Acute Respiratory Infections: A Controlled Clinical Trial. Pediatrics 2011, 128, e1113–e1120. [Google Scholar] [CrossRef] [Scilit]
- Beal, S.G.; Posa, M.; Gaffar, M.; Reppucci, J.; Mack, J.A.; Gurka, M.J.; Rand, K.; Houck, H.; Kelly, M.N. Performance and Impact of a CLIA-waived, Point-of-care Respiratory PCR Panel in a Pediatric Clinic. Pediatr. Infect. Dis. J. 2020, 39, 188–191. [Google Scholar] [CrossRef] [Scilit]
- Thibeault, R.; Gilca, R.; Côté, S.; de Serres, G.; Boivin, G.; Déry, E.P. Antibiotic use in children is not influenced by the result of rapid antigen detection test for the respiratory syncytial virus. J. Clin. Virol. 2007, 39, 169–174. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schnell, J.; Schroeder, L.; Sinclair, K.; Patel, L.; Dowd, D. The Effect of Early Knowledge of Respiratory Syncytial Virus Positivity on Medical Decision Making and Throughput Time within the Pediatric Emergency Department. Pediatr. Emerg. Care 2020, 36, 134–137. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Callaghan, K.; Jones, K. Rapid testing for respiratory viruses: Impact on antibiotic use and time to patient discharge. Infect. Dis. Health 2019, 24, 147–151. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mitchell, S.L.; Chang, Y.C.; Feemster, K.; Cárdenas, A.M. Implementation of a rapid influenza A/B and RSV direct molecular assay improves emergency department oseltamivir use in paediatric patients. J. Med. Microbiol. 2018, 67, 358–363. [Google Scholar] [CrossRef] [Scilit]
- Schneider, U.V.; Holm MK, A.; Bang, D.; Petersen, R.F.; Mortensen, S.; Trebbien, R.; Lisby, J.G. Point-of-care tests for influenza A and B viruses and RSV in emergency departments-indications, impact on patient management and possible gains by syndromic respiratory testing, Capital Region, Denmark, 2018. Eurosurveillance 2020, 25, 1900430. [Google Scholar]
- Hayashi, D.; Akashi, Y.; Suzuki, H.; Shiigai, M.; Kanemoto, K.; Notake, S.; Ishiodori, T.; Ishikawa, H.; Imai, H. Implementation of Point-of-Care Molecular Diagnostics for Mycoplasma pneumoniae Ensures the Correct Antimicrobial Prescription for Pediatric Pneumonia Patients. Tohoku J. Exp. Med. 2018, 246, 225–231. [Google Scholar] [CrossRef] [Scilit]
- Ayanruoh, S.; Waseem, M.; Quee, F.; Humphrey, A.; Reynolds, T. Impact of rapid streptococcal test on antibiotic use in a pediatric emergency department. Pediatr. Emerg. Care 2009, 25, 748–750. [Google Scholar] [CrossRef] [Scilit]
- Bird, C.; Winzor, G.; Lemon, K.; Moffat, A.; Newton, T.; Gray, J. A Pragmatic Study to Evaluate the Use of a Rapid Diagnostic Test to Detect Group A Streptococcal Pharyngitis in Children with the Aim of Reducing Antibiotic Use in a UK Emergency Department. Pediatr. Emerg. Care 2021, 37, E249–E251. [Google Scholar] [CrossRef] [Scilit]
- Halverson, K.A.; Milner, D. Implementation of Point-of-Care Testing in the Emergency Department. Point Care J. Near-Patient Test. Technol. 2011, 10, 116–119. [Google Scholar] [CrossRef] [Scilit]
- Kose, E.; Kose, S.S.; Akca, D.; Yildiz, K.; Elmas, C.; Baris, M.; Anil, M. The Effect of Rapid Antigen Detection Test on Antibiotic Prescription Decision of Clinicians and Reducing Antibiotic Costs in Children with Acute Pharyngitis. J. Trop. Pediatr. 2016, 62, 308–315. [Google Scholar] [CrossRef] [Scilit]
- Małecki, M.; Mazur, A.; Sobolewski, M.; Binkowska-Bury, M.; Marć, M.; Januszewicz, P. Rapid strip tests as a decision-making tool about antibiotic treatment in children–A prospective study. Pediatr. Polska 2017, 92, 149–155. [Google Scholar] [CrossRef] [Scilit]
- Maltezou, H.C.; Tsagris, V.; Antoniadou, A.; Galani, L.; Douros, C.; Katsarolis, I.; Maragos, A.; Raftopoulos, V.; Biskini, P.; Kanellakopoulou, K.; et al. Evaluation of a rapid antigen detection test in the diagnosis of streptococcal pharyngitis in children and its impact on antibiotic prescription. J. Antimicrob. Chemother. 2008, 62, 1407–1412. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rao, A.; Berg, B.; Quezada, T.; Fader, R.; Walker, K.; Tang, S.; Cowen, U.; Duncan, D.; Sickler, J. Diagnosis and antibiotic treatment of group a streptococcal pharyngitis in children in a primary care setting: Impact of point-of-care polymerase chain reaction. BMC Pediatr. 2019, 19, 24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sullivan, K.V. Advances in Diagnostic Testing that Impact Infection Prevention and Antimicrobial Stewardship Programs. Curr. Infect. Dis. Rep. 2019, 21, 6. [Google Scholar] [CrossRef] [Scilit]
- Martínez-González, N.A.; Keizer, E.; Plate, A.; Coenen, S.; Valeri, F.; Verbakel, J.Y.J.; Rosemann, T.; Neuner-Jehle, S.; Senn, O. Point-of-care c-reactive protein testing to reduce antibiotic prescribing for respiratory tract infections in primary care: Systematic review and meta-analysis of randomised controlled trials. Antibiotics 2020, 9, 610. [Google Scholar] [CrossRef] [Scilit]
- Lippi, G.; Nocini, R.; Mattiuzzi, C.; Henry, B.M. FebriDx for rapid screening of patients with suspected COVID-19 upon hospital admission: Systematic literature review and meta-analysis. J. Hosp. Infect. 2022, 123, 61–66. [Google Scholar] [CrossRef] [Scilit]
- Egilmezer, E.; Walker, G.J.; Bakthavathsalam, P.; Peterson, J.R.; Gooding, J.J.; Rawlinson, W.; Stelzer-Braid, S. Systematic review of the impact of point-of-care testing for influenza on the outcomes of patients with acute respiratory tract infection. Rev. Med Virol. 2018, 28, e1995. [Google Scholar] [CrossRef] [Scilit]
- Marrie, T.J.; Lau, C.Y.; Wheeler, S.L.; Wong, C.J.; Vandervoort, M.K.; Feagan, B.G. A controlled trial of a critical pathway for treatment of community-acquired pneumonia. CAPITAL Study Investigators. Community-Acquired Pneumonia Intervention Trial Assessing Levofloxacin. JAMA 2000, 283, 749–755. [Google Scholar] [CrossRef] [Scilit]
- Asiimwe, C.; Kyabayinze, D.; Kyalisiima, Z.; Nabakooza, J.; Bajabaite, M.; Counihan, H.; Tibenderana, J.K. Early experiences on the feasibility, acceptability, and use of malaria rapid diagnostic tests at peripheral health centres in Uganda-insights into some barriers and facilitators. Implement. Sci. 2012, 7, 5. [Google Scholar] [CrossRef] [Scilit]
- Schito, M.; Peter, T.F.; Cavanaugh, S.; Piatek, A.S.; Young, G.J.; Alexander, H.; Coggin, W.; Domingo, G.; Ellenberger, D.; Ermantraut, E.; et al. Opportunities and Challenges for Cost-Efficient Implementation of New Point-of-Care Diagnostics for HIV and Tuberculosis. J. Infect. Dis. 2012, 205, S169–S180. [Google Scholar] [CrossRef] [Scilit]
- Pai, N.P.; Vadnais, C.; Denkinger, C.; Engel, N.; Pai, M. Point-of-Care Testing for Infectious Diseases: Diversity, Complexity, and Barriers in Low- and Middle-Income Countries. PLoS Med. 2012, 9, e1001306. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Uyeki, T.M.; Bernstein, H.H.; Bradley, J.S.; Englund, J.A.; File, T.M., Jr.; Fry, A.M.; Gravenstein, S.; Hayden, F.G.; Harper, S.A.; Hirshon, J.M.; et al. Clinical Practice Guidelines by the Infectious Diseases Society of America: 2018 Update on Diagnosis, Treatment, Chemoprophylaxis, and Institutional Outbreak Management of Seasonal Influenza. Clin. Infect. Dis. IDSA Guidel. 2019, 30, 97–98. [Google Scholar]
- Tse, J.; Near, A.M.; Cheng, M.; Karichu, J.; Lee, B.; Chang, S.N. Outpatient Antibiotic and Antiviral Utilization Patterns in Patients Tested for Respiratory Pathogens in the United States: A Real-World Database Study. Antibiotics 2022, 11, 1058. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheysson, F.; Brun-Buisson, C.; Opatowski, L.; Le Fouler, L.; Caserio-Schönemann, C.; Pontais, I.; Guillemot, D.; Watier, L. Outpatient antibiotic use attributable to viral acute lower respiratory tract infections during the cold season in France, 2010–2017. Int. J. Antimicrob. Agents 2021, 57, 106339. [Google Scholar] [CrossRef] [Scilit]
- Thompson, P.L.; Spyridis, N.; Sharland, M.; Gilbert, R.; Saxena, S.; Long, P.; Johnson, A.P.; Wong, I.C.K. Changes in clinical indications for community antibiotic prescribing for children in the UK from 1996 to 2006: Will the new NICE prescribing guidance on upper respiratory tract infections just be ignored? Arch. Dis. Child. 2009, 94, 337–340. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fitzpatrick, T.; Malcolm, W.; McMenamin, J.; Reynolds, A.; Guttmann, A.; Hardelid, P. Community-Based Antibiotic Prescribing Attributable to Respiratory Syncytial Virus and Other Common Respiratory Viruses in Young Children: A Population-Based Time-series Study of Scottish Children. Clin. Infect. Dis. 2021, 72, 2144–2153. [Google Scholar] [PubMed]
- Harris, M.; Clark, J.; Coote, N.; Fletcher, P.; Harnden, A.; Mckean, M.; Thomson, A.; on behalf of British Thoracic Society Standards of Care Committee. British Thoracic Society guidelines for the management of community acquired pneumonia in children: Update 2011. Thorax 2011, 66 (Suppl. S2), ii1–ii23. [Google Scholar] [CrossRef] [Scilit]
- Gonzalez-Gonzalez, C.; López-Vázquez, P.M.; Vazquez-Lago, J.; Piñeiro-Lamas, M.; Herdeiro, M.T.; Arzamendi, P.C.; Figueiras, A.; GREPHEPI Group. Effect of Physicians’ Attitudes and Knowledge on the Quality of Antibiotic Prescription: A Cohort Study. PLoS ONE 2015, 10, e0141820. [Google Scholar]
- Borg, M.A.; Camilleri, L. Broad-spectrum antibiotic use in Europe: More evidence of cultural influences on prescribing behaviour. J. Antimicrob. Chemother. 2019, 74, 3379–3383. [Google Scholar] [CrossRef] [Scilit]
- Zeitler, K.; Narayanan, N. The Present and Future State of Antimicrobial Stewardship and Rapid Diagnostic Testing: Can One Ideally Succeed Without the Other? Curr. Treat. Options Infect. Dis. 2019, 11, 177–187. [Google Scholar] [CrossRef] [Scilit]
- Machowska, A.; Lundborg, C.S. Drivers of irrational use of antibiotics in Europe. Int. J. Environ. Res. Public Health 2019, 16, 27. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; Moher, D.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. PRISMA 2020 explanation and elaboration: Updated guidance and exemplars for reporting systematic reviews. BMJ 2021, 372, n160. [Google Scholar] [CrossRef]
- NIH Tool for Bias Assessment. Available online: https://www.nhlbi.nih.gov/health-topics/study-quality-assessment-tools (accessed on 3 February 2022).
- Higgins, J.P.T.; Thompson, S.G. Quantifying heterogeneity in a meta-analysis. Stat. Med. 2002, 21, 1539–1558. [Google Scholar] [CrossRef] [Scilit]
- Cochran, W.G. The Combination of Estimates from Different Experiments. Biometrics 1954, 10, 101–129. [Google Scholar] [CrossRef] [Scilit]
- Der Simonian, N.; Lair, R. Meta-analysis in clinical trials. Control. Clin. Trials 1986, 7, 177–188. [Google Scholar] [CrossRef] [Scilit]




Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).