


Abstract
Background: In the era of antibiotic resistance, an antibiotic-sparing approach presents an interesting alternative treatment of uncomplicated cystitis in women. Our aim is to perform a systematic review and meta-analysis to compare the effectiveness and safety profile of a medical device containing xyloglucan, hibiscus and propolis (XHP) in women with uncomplicated cystitis. Methods: Relevant databases were searched using methods recommended by the Preferred Reporting Items for Systematic Reviews and Meta-Analysis guidelines. The primary endpoint was clinical or microbiological success, defined as the complete (cure) and/or non-complete (improvement) resolution of symptoms at the end of treatment, or microbiological resolutions. Results: After screening 21 articles, three studies were included, recruiting a total of 178 patients. All three studies used placebo as comparator. A statistically significant difference was found in terms of clinical or microbiological resolution between the medical device and the comparator (3 RCTs, 178 patients, OR: 0.13; 95% CI: 0.05–0.33; p < 0.0001). No clinically significant adverse effects have been reported. Conclusion: A medical device containing xyloglucan, hibiscus and propolis is superior to comparator regimens in terms of clinical effectiveness in adult women with microbiologically confirmed or clinical suspicion of uncomplicated cystitis and is associated with a high patient compliance.
1. Introduction
The prevalence of recurrent uncomplicated urinary tract infections (rUTIs) in women accounts for about 27% and the impact of those on patients’ quality of life is high [1,2]. In particular, suffering from recurrent urinary tract infection has a detrimental influence on patient quality of life, in terms of the level of stress and anxiety [2]. In addition, its management is still under discussion and there is not a consensus [3,4]. The need for an antibiotics-sparing approach, due to the worldwide emergency of antibiotic resistance, and the recent interest in the role of non-antibiotic oral supplements increased the interest among physicians and researchers in the use of medical devices containing phytotherapy and nutraceuticals compounds. On the basis of this considerations, here we focused our attention on a medical device containing xyloglucan, hibiscus and propolis (XHP) in the management of women affected by rUTIs. Recently Cai et al. demonstrated in a prospective clinical trial the clinical and microbiological efficacy of XHP in improving quality of life in women affected by rUTIs, reducing symptomatic episode and the use of antibiotics [5]. This study has been based on the encouraging results from previous published RCTs [6,7,8]. In this sense, the use of XHP seems an interesting tool for use in everyday clinical practice for improving antimicrobial stewardship. Considering this background information and considering the lack of a general consensus about the management of rUTIs, we aimed to compare the effectiveness and safety profile of XHP in women with uncomplicated cystitis, by performing a systematic review and meta-analysis of relevant randomized controlled trials.
Research Questions
We put forth two research queries:
- Is XHP able to obtain significant pre-clinical data in order to justify its clinical use in the management of patients affected by uncomplicated cystitis?
- Is XHP able to obtain a clinical and/or microbiological cure in women affected by uncomplicated cystitis?
2. Results
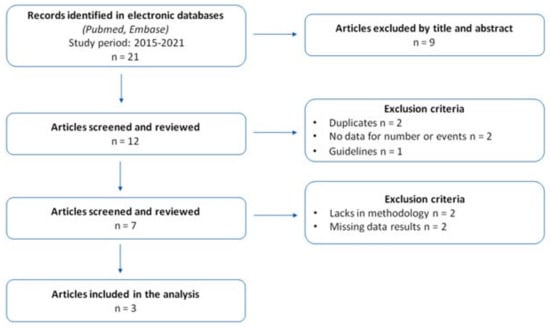
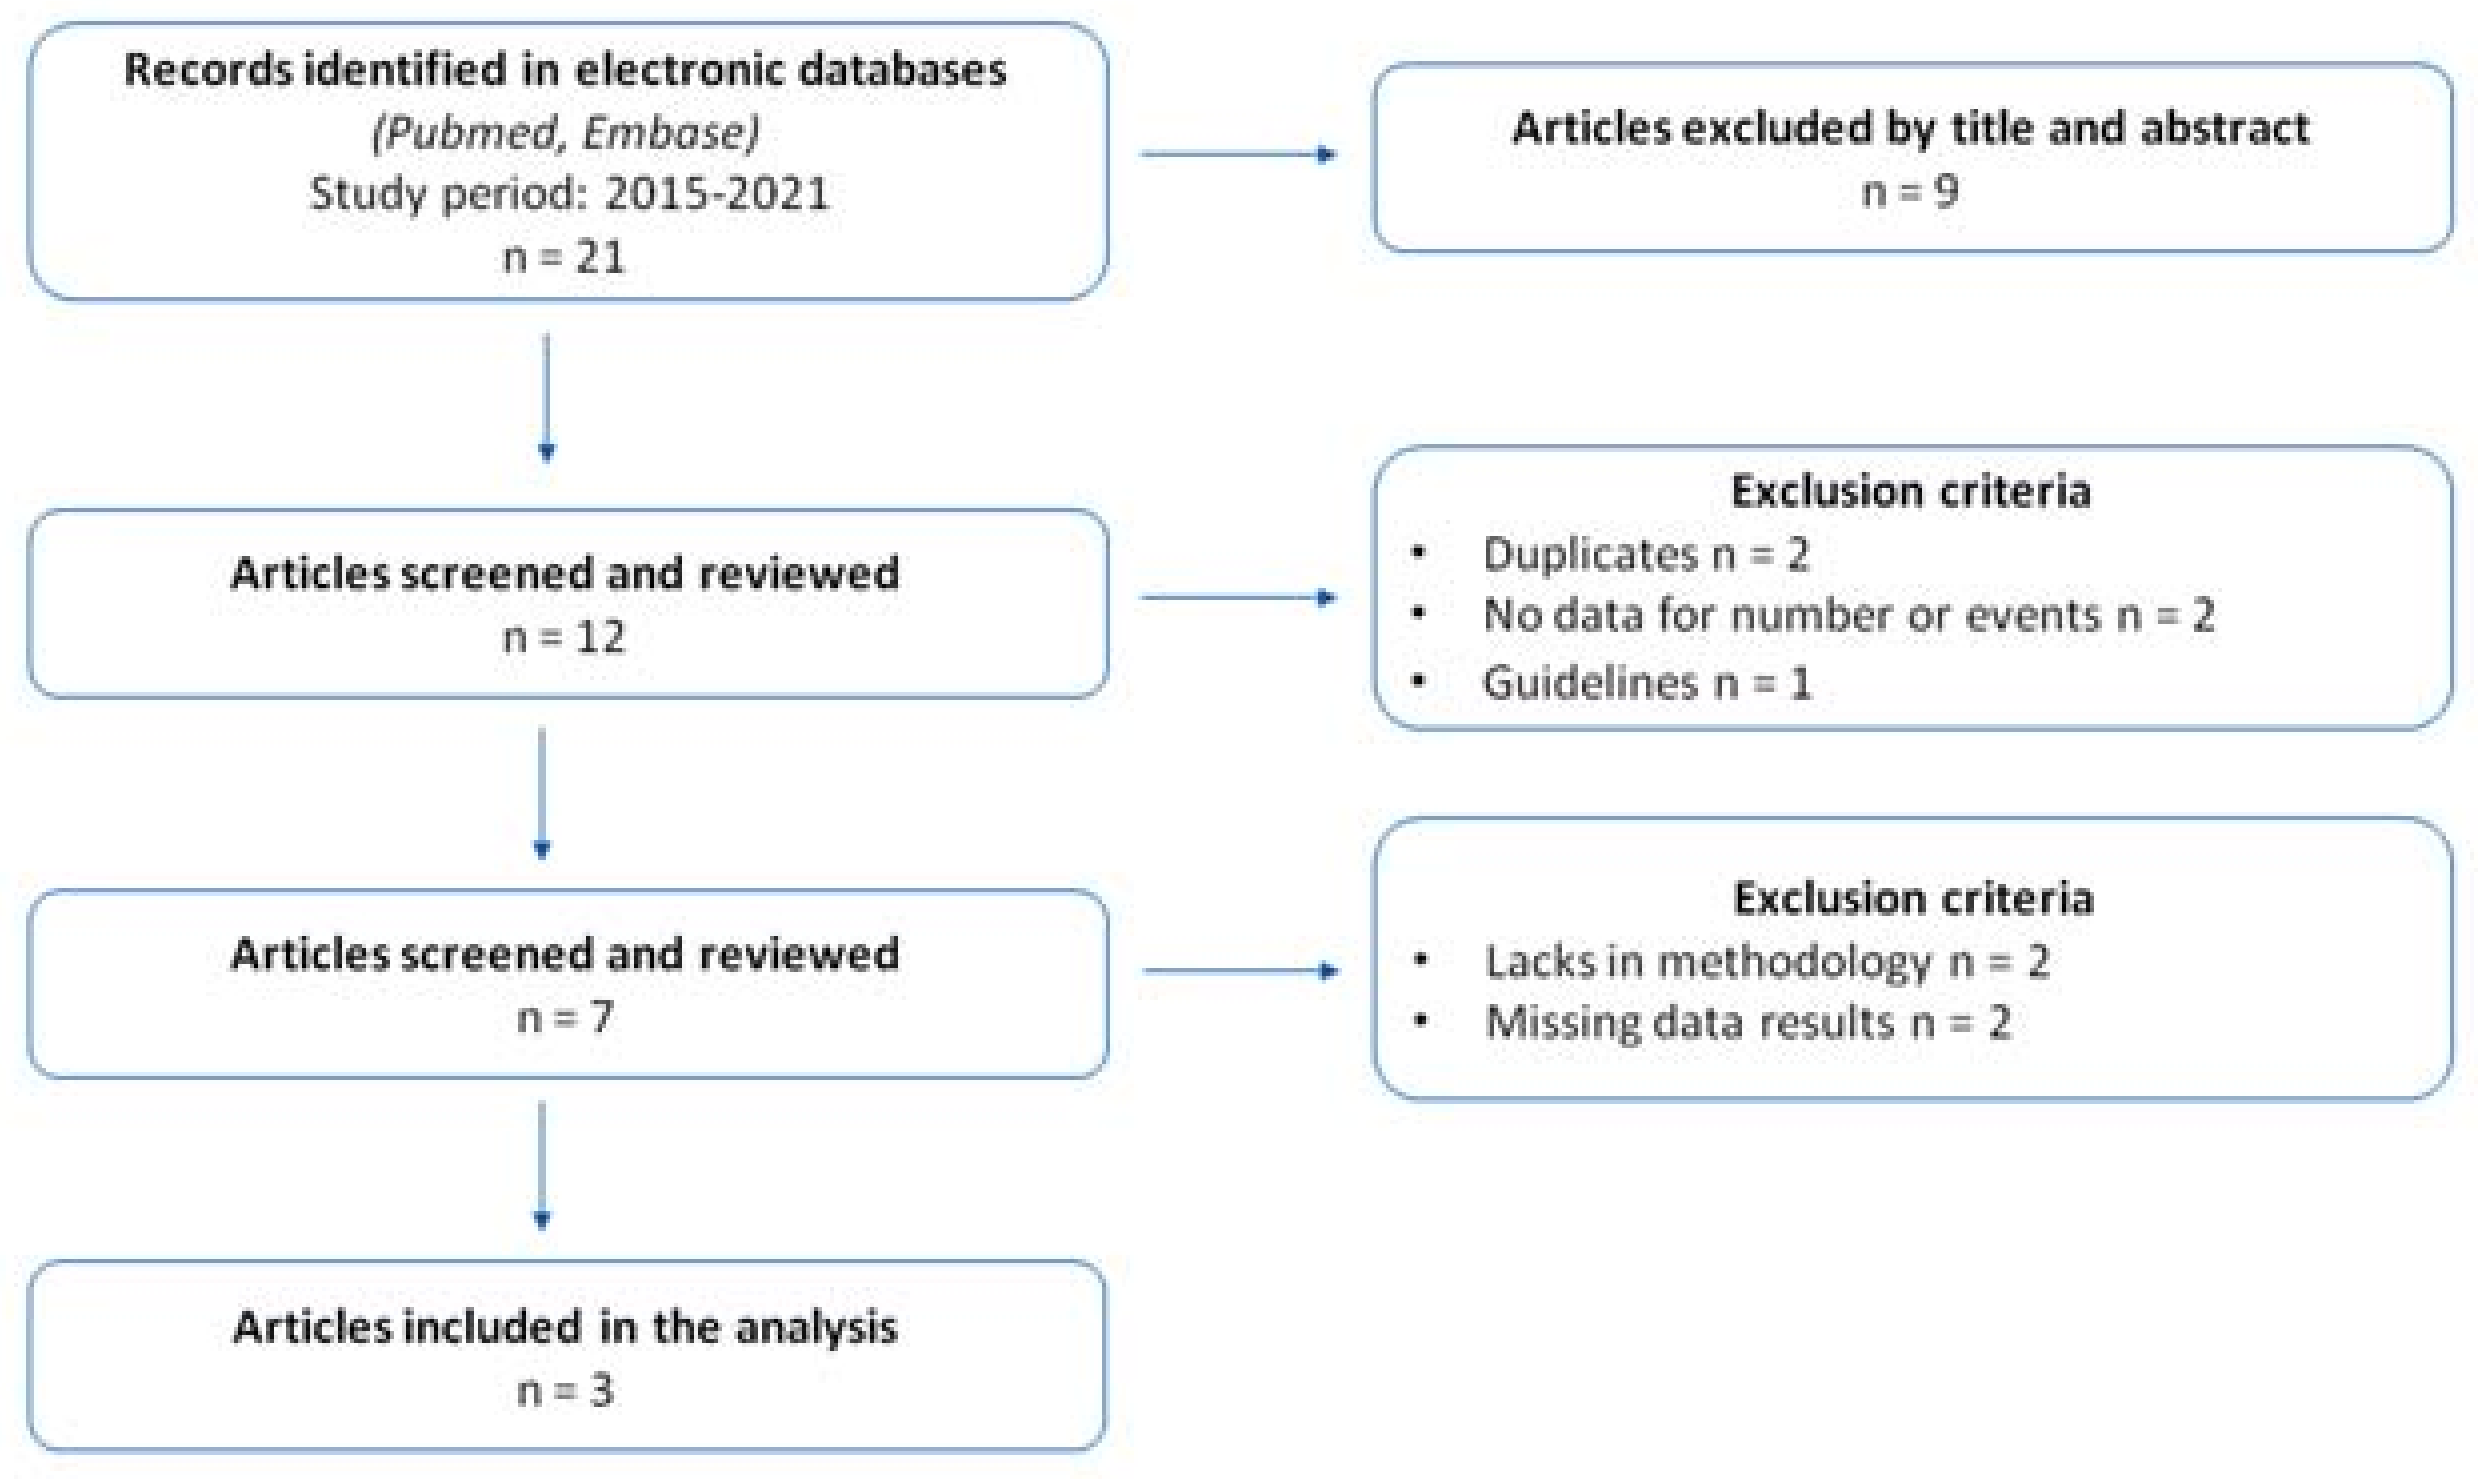
Our research produced 21 potentially relevant articles. After the screening, three pre-clinical studies and four clinical trials were considered. All the papers were published after 2015. The detailed selection process of the included trials has been displayed in Figure 1.
Figure 1.
The figure shows the papers’ selection process according to PRISMA recommendations.
2.1. Pre-Clinical and Non-Randomized Clinical Studies
Three pre-clinical studies were included: one in vitro study and two animal model studies. One prospective non-randomized clinical study has been included in the systematic review but not in the meta-analysis. Table 1 shows characteristics of all of the pre-clinical and non-randomized clinical studies.
Table 1.
The table shows all characteristics of all pre-clinical and non-randomized clinical studies. List of abbreviations used in table: MD = medical device; RGHP = reticulated-gelatin hibiscus and propolis; RG = reticulated gelatin (RGHP); SRR = symptomatic recurrence reduction; UTI = urinary tract infection; rUTI = recurrent urinary tract infection; XGHP = xyloglucan–gelose–hibiscus–propolis; AEs = adverse effects; EC = Escherichia coli; XHP = xyloglucan–hibiscus–propolis; XG = xyloglucan–gelose; UT = urinary tract; MPO = myeloperoxidase assay; HSP = H. sabdariffa and propolis.
2.2. RCTs
2.2.1. Evidence Synthesis, Study Characteristics and Quality Assessment Results
Three RCTs were considered eligible to be included in the meta-analysis, recruiting a total of 178 patients. One study was performed with a combination of xyloglucan, hibiscus and propolis, and two studies were performed with a combination of an equivalent mucoprotectant (reticulated gelatin), hibiscus and propolis. The Jadad score was 4 for two papers and 5 for one paper. One paper also includes an account of all patients, and for this reason, the trialists assigned the score of 5. The risk of publication bias and small-study effects has been evaluated with funnel plot analysis. The characteristics of all RCTs included in the systematic review and meta-analysis are described in Table 2.
Table 2.
The table shows all characteristics of all included RCTs in the systematic review and meta-analysis.
2.2.2. Characteristics of Studies Included in the Meta-Analysis
In two studies, the medical device is used in the management of acute uncomplicated cystitis treatment as adjuvant therapy in association with an antimicrobial agent. In one study, the medical device is used in the management of acute uncomplicated cystitis treatment alone. In two studies, the medical device is used in association with an antimicrobial agent and used for 2 months. On the other hand, in one study, the medical device is used only for 5 days in acute setting. The follow-up period ranges from 11 days to 2 months.
2.2.3. Clinical Cure
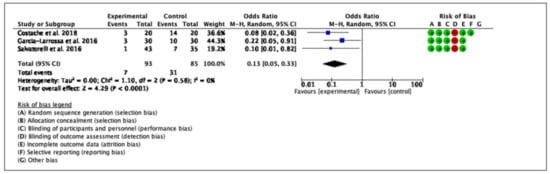
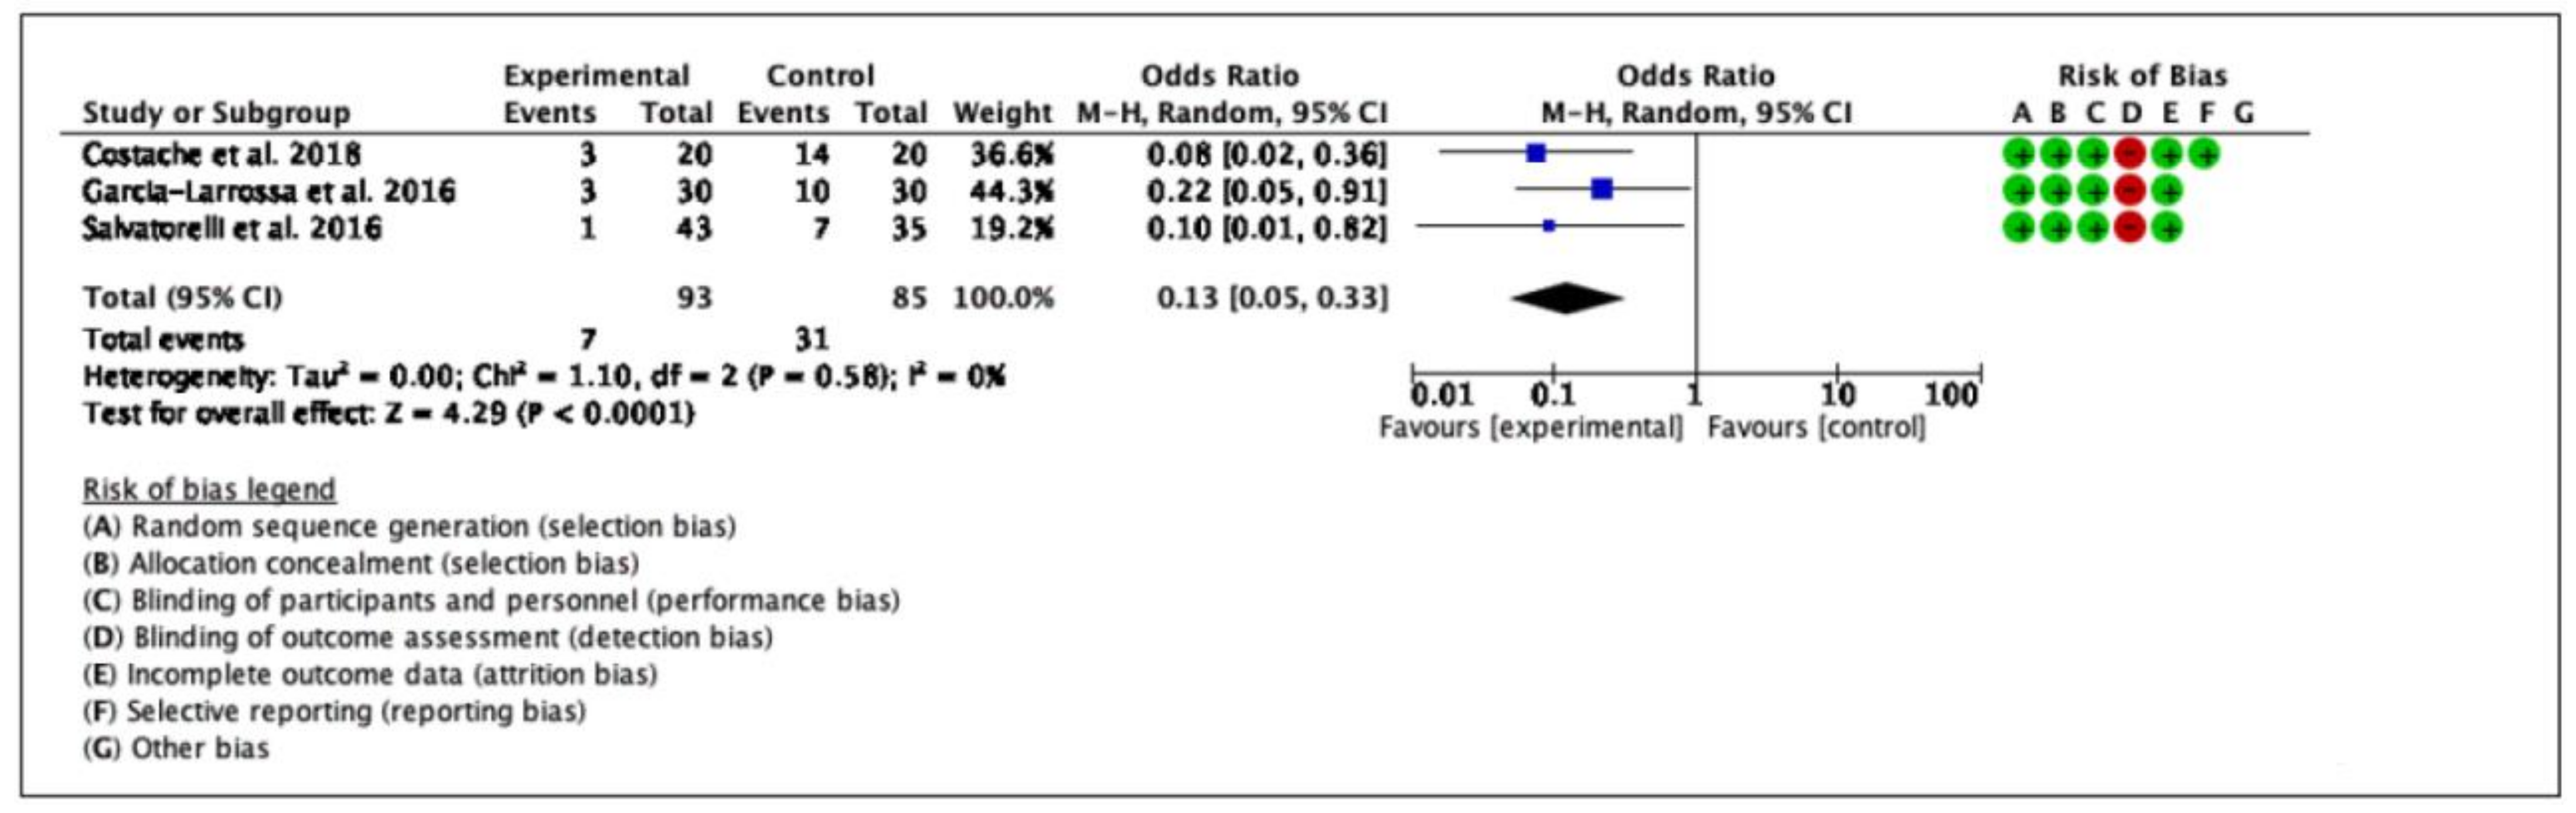
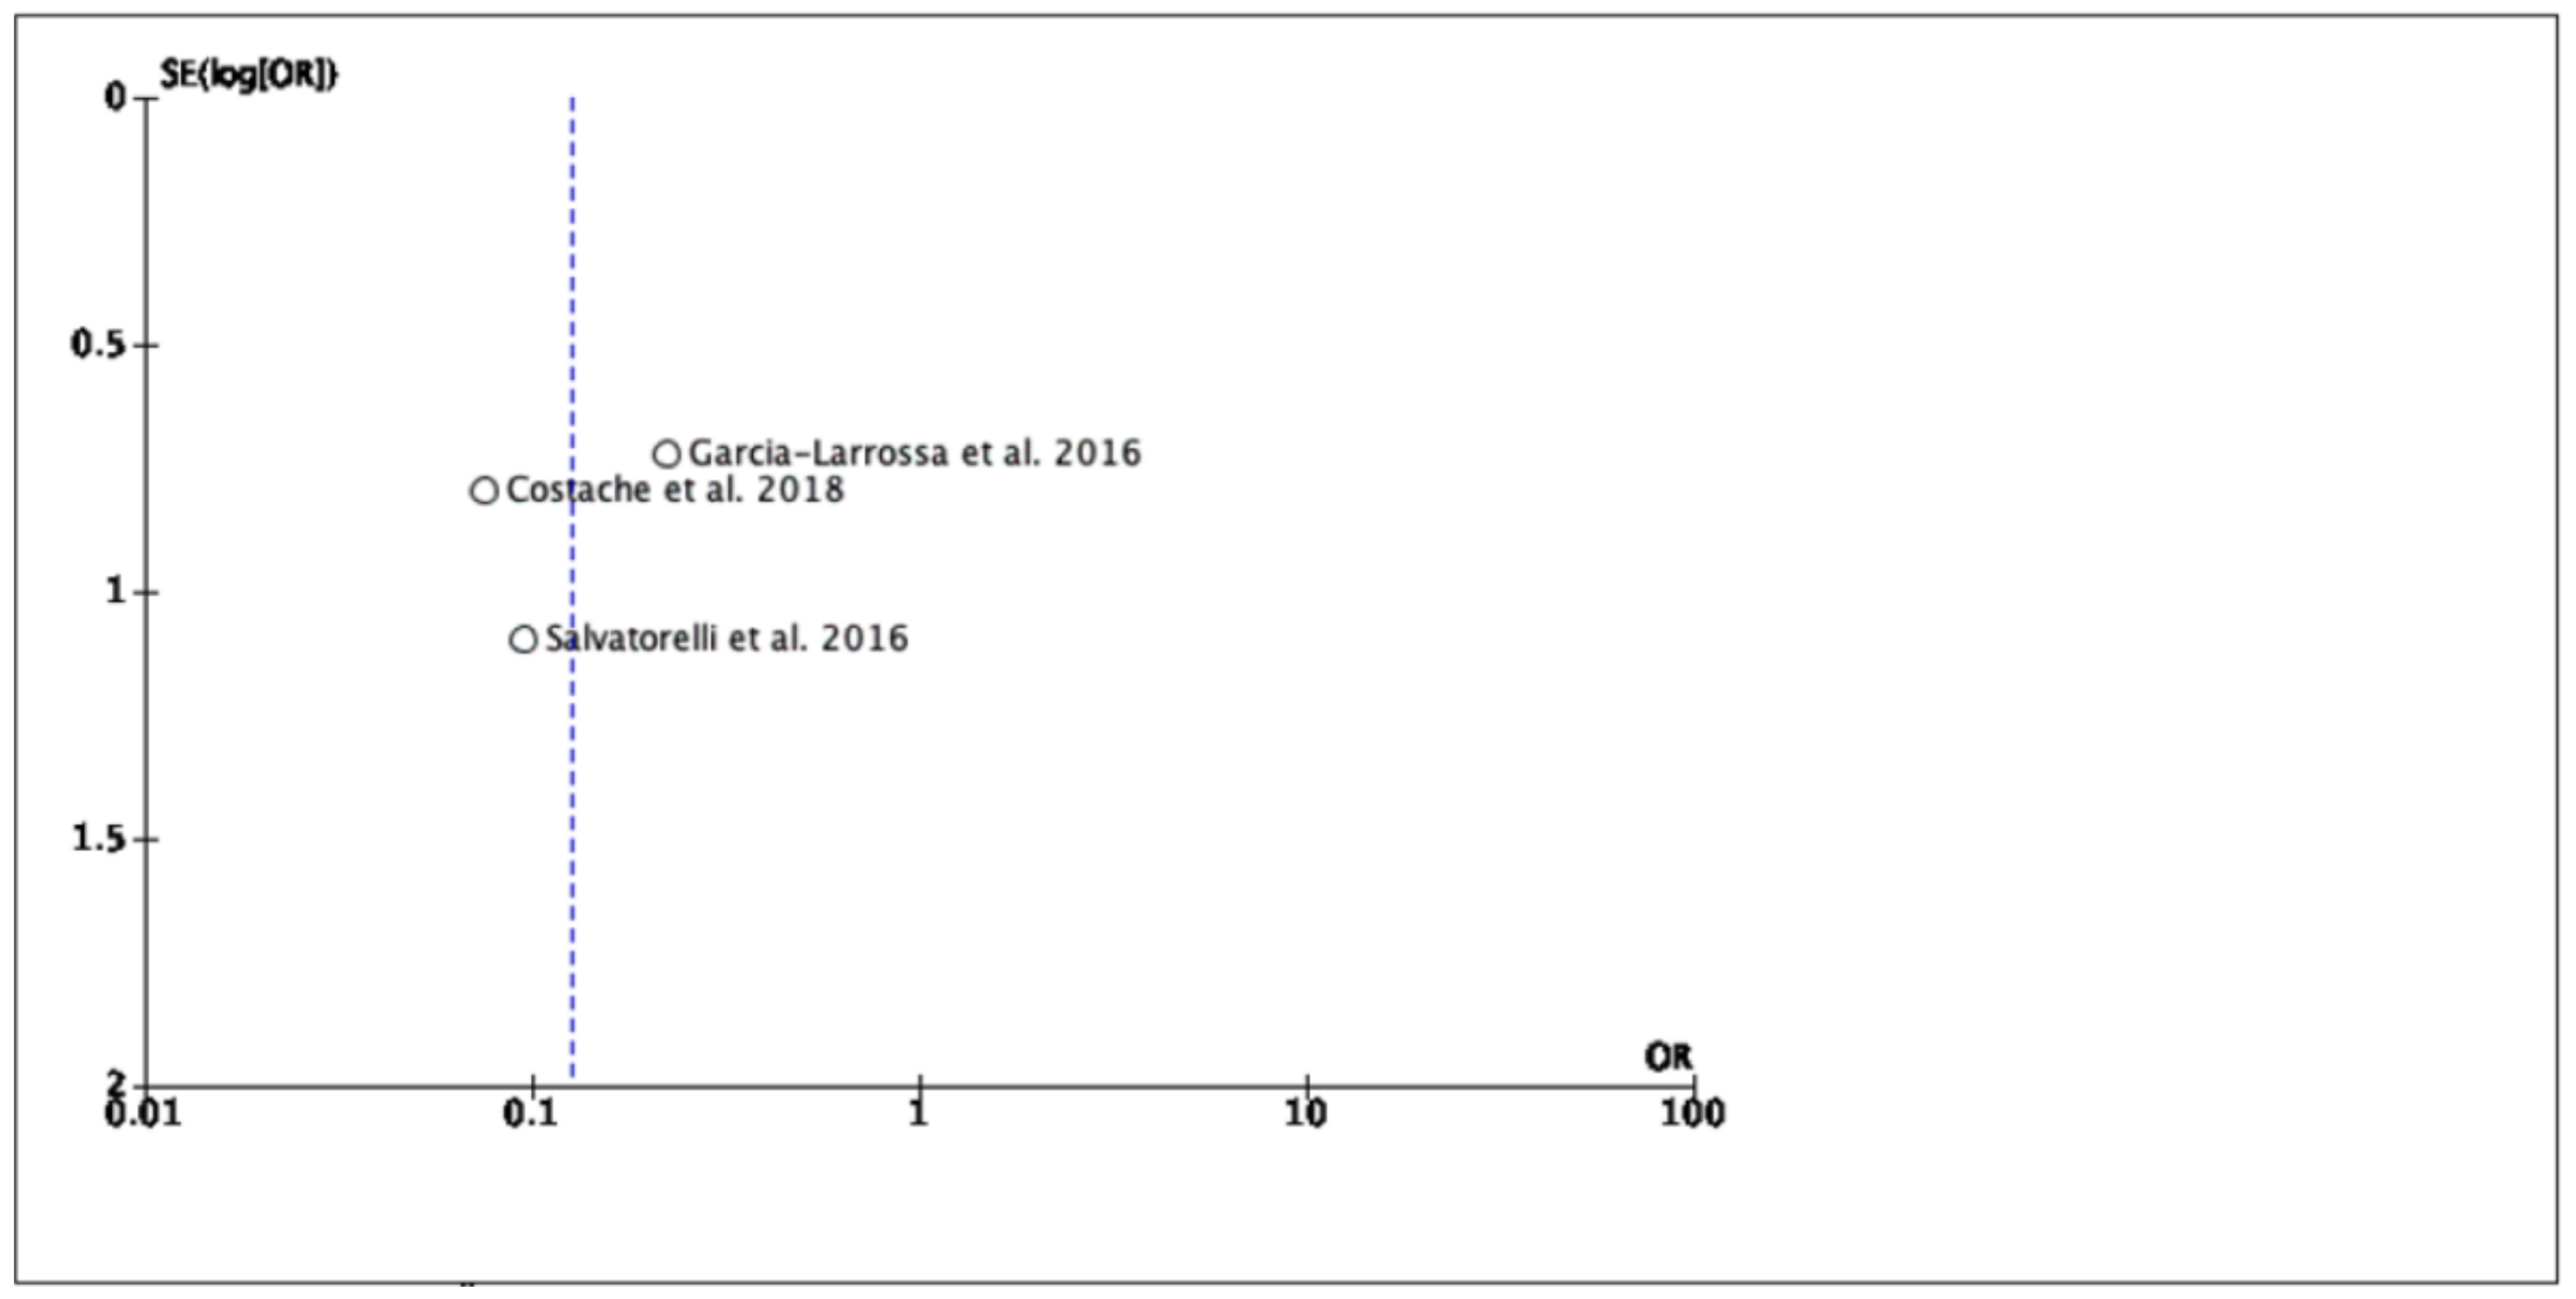
We considered all three RCTs for the evaluation of a clinical cure. A statistically significant difference has been found in terms of clinical resolution between the medical device and the comparator (3 RCTs, 178 patients, OR: 0.13; 95% CI: 0.05–0.33; p < 0.0001). Figure 2 shows the clinical success (improvement/cure) in women with cystitis who were treated with the medical device compared to other antibiotic agents. Funnel plots were generated to analyze publication bias and small-study effects. The funnel plots analysis did not suggest the exclusion of any study (Figure 3).
Figure 2.
The figure shows a forest plot of the effects of the medical device on women with cystitis in terms of clinical success (improvement/cure).
Figure 3.
The figure shows the funnel plot for publication bias analysis.
2.2.4. Safety Outcomes
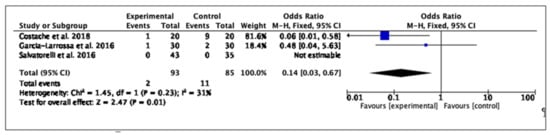
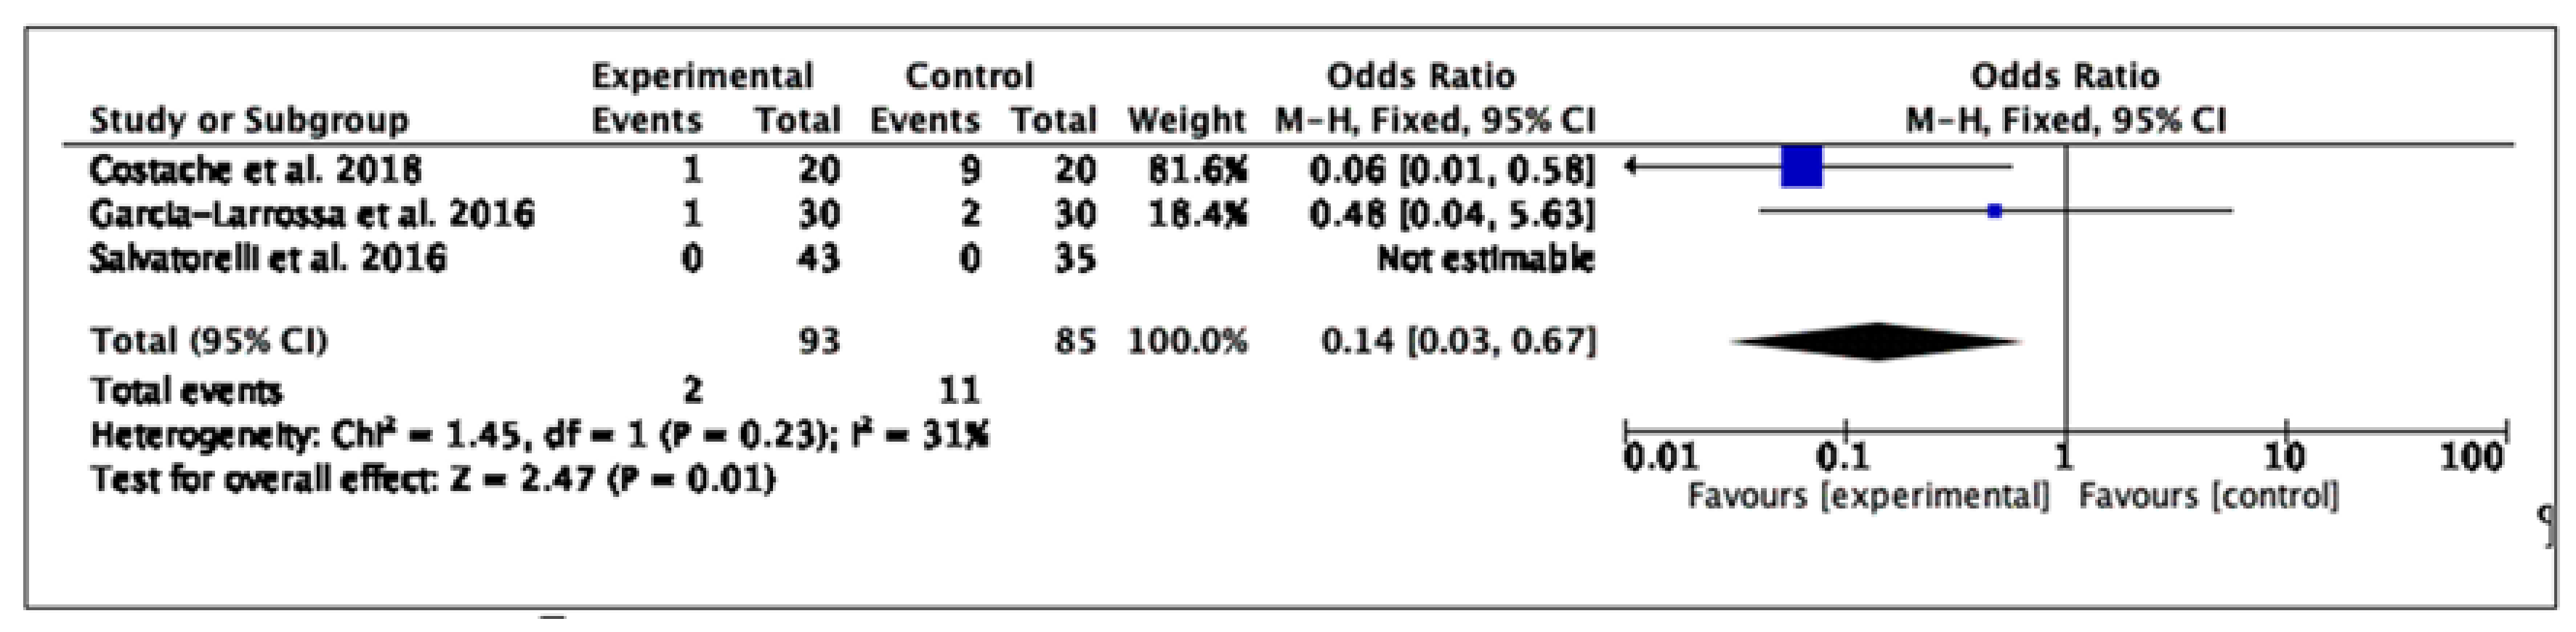
No significant difference has been found in terms of adverse effects (3 RCTs, 178 patients, OR: 0.14; 95% CI: 0.03–0.67; p = 0.001) (Figure 4). The most common reported adverse effects were of the gastrointestinal type (abdominal pain, diarrhea). In one study, the high prevalence of adverse effects is related to the antimicrobial agents and not to the placebo. No study withdrawal due to adverse events occurred in either of the compared treatment groups in the three trials that provided relevant data.
Figure 4.
The figure shows a forest plot of the effects of the medical device on women with cystitis in terms of adverse effects.
3. Discussion
3.1. Main Findings
Here, we demonstrated that the medical device containing xyloglucan, hibiscus and propolis is superior to comparator regimens in terms of clinical effectiveness in adult women with microbiologically confirmed or clinical suspicion of uncomplicated cystitis and is associated with a high patient compliance.
3.2. Evidence and Implications for Clinical Practice
In recent years, the use of phytotherapy and nutraceuticals-based medications has gained popularity among non-antibiotic prophylaxis of rUTIs in urological practice [9]. Nowadays, the progressive introduction of phytotherapy and nutraceuticals drugs for the management of symptomatic UTI recurrences represents a reasonable, cost-effective alternative to obviate the massive and reckless use of antibiotics [10]. Xyloglucan, hibiscus and propolis as well as hibiscus and propolis combinations have recently emerged as alternative non-antibiotic approaches in the management of women affected by acute uncomplicated cystitis and rUTIs [5,6,7,8]. The clinical efficacy of XHP on uncomplicated cystitis both in the acute phase and for the prevention of recurrence is due to the following properties:
- —
- Mechanical barrier protection (mucoprotectant effect) on intestinal cell mucosa.
- —
- Environmental changes in urine (mild decrease of pH) that prevent bacteria proliferation in the urinary tract.
These properties are related to the components in the medical device. Xyloglucan, extracted from the seeds of the tamarind tree (Tamarindus indica), is a ‘mucosal protector’ with the capability to produce a defensive barrier on human epithelial tissues. In vitro studies highlighted how xyloglucan could be efficacious for the management of UTIs by lowering the intestinal reservoirs of uropathogens colonizing the lower intestinal tract, as well as by interfering in the process by which microorganisms contact uroepithelial cell receptors [11,12,13,14].
On the other hand, Hibiscus sabdariffa and propolis have been shown to modify the urine environment, preventing bacteria proliferation and colonization of the urinary tract [15,16].
Several studies have already presented the effects of different mucoprotectant-containing products in women at increased risk for UTIs [5,8]. Herein, we undertook this systematic review and meta-analysis to evaluate the available evidence on medical devices containing a mucoprotectant, hibiscus and propolis, in the management of rUTIs. In this scenario, we selected trials that focused on the efficacy and safety profile of these medications in the prophylaxis of symptomatic recurrences and for improving UTI-related urinary symptoms. Indeed, we included in the selection process all ‘in vitro’ or ‘in vivo’ studies on rat models which evaluated the mechanism of action of mucoprotectants on intestinal epithelial cells [11,12,13,17]. Despite the limited available literature, the results of our study suggest that XHP may represent a promising, non-antibiotic approach to the management of acute UTI and rUTIs. To our knowledge, this is the first meta-analysis to focus on a novel combination of nutraceutical agents as a therapeutical option to manage UTIs. Three RCTs were considered eligible, considering a decrease in symptomatic UTI as the primary endpoint [6,7,8]. The series were comparable in terms of the number of patients considered and the secondary endpoints considered (safety profile or urinary symptoms improvement). Only one study reported the drop-out rate (24%), while only one series required either an active UTI or history of UTI at study entry, although varying criteria and validated tools to define rUTIs were used. Despite the concept of ‘culture-negative’ UTI having emerged, which recognizes the demonstrated effect of antibiotics to resolve UTI symptoms in women who did not demonstrate a culture growth of uropathogens or who had low colony-count infections, it is common in clinical practice to initiate treatment without or before culture results are available, creating a significant bias [18]. In all clinical series, the medical device was adequately tolerated, resulting in excellent compliance, as negligible side effects were registered [19]. Moreover, it showed remarkable results since patients reported a notable clinical improvement of urinary symptoms at 6 months ranging between 19.4–85% [5,6,8].
3.3. Study Strengths and Limitations
This meta-analysis is not free from limitations. Firstly, the small observational timeframes and the lack of validated tools for estimating urinary symptoms may represent an intrinsic bias. Furthermore, the restricted number and gender of patients enrolled should be considered a limitation. Moreover, in several series, only patients with an active UTI and unknown history were enrolled and the subsequent UTI was considered a recurrent UTI. Notwithstanding these limitations, our meta-analysis suggests that XHP may represent a potential non-pharmacologic approach for women affected by uncomplicated UTI. Longer-term follow-up and further multicentric series would be necessary to definitively establish the long-term benefits of XHP.
4. Materials and Methods
4.1. Research Strategy and Literature Search
From September 2020 to April 2021, two independent reviewers (T.C., I.T.) performed the research in PubMed database, Cochrane CENTRAL and Scopus. All disagreements between the two reviewers were resolved by a supervisor (T.B.J.). All references cited in relevant articles were also reviewed and analyzed. The search strategy used was ‘(xyloglucan,) AND (hibiscus) AND (propolis) AND (urinary tract infection OR cystitis)’. As filters, we used: clinical trial, humans, female, English language and adult. Titles and abstracts were used to screen for initial study inclusion. Full-text review was used where abstracts were insufficient to determine if the study met inclusion or exclusion criteria. Two authors independently performed all data abstraction, including evaluation of the study characteristics, risk of bias and outcome measures, with independent verification performed by the senior author. The limited number of studies collected did not require any other authors. The study has been performed in line with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA), the recommendations of the European Association of Urology Guidelines office for conducting systematic reviews and meta-analysis and previous studies [4,20,21]. All selected pre-clinical and clinical trials were used for the systematic review. On the other hand, only clinical trials have been used for the meta-analysis.
4.2. Selection Criteria for Study Inclusion in Meta-Analysis and Data Extraction
In this meta-analysis, we included all RCTs involving female patients aged >19 years with microbiologically confirmed or clinical suspicion of uncomplicated cystitis, who were randomized to receive treatment with a medical device containing xyloglucan (or an equivalent mucoprotectant substance), hibiscus and propolis or placebo or other comparator. In line with EAU guidelines, we defined uncomplicated cystitis as acute, sporadic or recurrent cystitis limited to non-pregnant, premenopausal women with no known relevant anatomical and functional abnormalities within the urinary tract or comorbidities [4]. We excluded all male patients and patients with complicated UTIs, defined as reported in the EAU guidelines [4]. We consider for this meta-analysis only studies written in English languages. Abstracts presented at scientific conferences were not considered. Data extraction, risk of bias (RoB) assessment using the Cochrane RoB Tool and quality assessment using the Grading of Recommendations, Assessment, Development and Education (GRADE) [22] approach have been performed by two reviewers (T.C., I.T.) working independently, as described in our previous study [23].
4.3. Main Outcomes Measures
The primary endpoint was clinical or microbiological success, defined as the complete (cure) and/or non-complete (improvement) resolution of symptoms at the end of treatment, or microbiological resolutions, in line with the trialists’ definition. Microbiological success (eradication) was defined as the presence of a negative urine culture at the end of treatment [23]. Secondary endpoints included the presence of adverse events, which was defined as any adverse event that was reported at any time during the study period [23].
4.4. Statistical Considerations
After extraction, data were pooled to conduct a meta-analysis. Outcomes for continuous variables were expressed as mean difference (MD) with 95% confidence intervals (CI). To analyze dichotomous data, we calculated crude (unadjusted) odds ratios (OR) and log odds ratios. The inverse variance method was used for the combination of the results. Meta-analysis and forest plot diagrams were designed using a random effect model since the sample sizes of the selected studies were different. The ‘trim and fill’ missing study imputation approach was applied to funnel plots, and adjusted overall effect sizes were calculated according to Duval and Tweedie [24]. The software that has been used was the Review Manager (RevMan) Version 5.4 (The Cochrane Collaboration, The Nordic Cochrane Center, Copenhagen 2014). Variations among the studies were calculated using the chi-square test. In addition, I2 was evaluated to indicate the proportion of inconsistency between the selected studies that could not be attributed to chance. Separate analyses regarding all the clinical and microbiological outcomes were performed to compare fosfomycin with each of the different types of antibiotic agent. Finally, the Jadad criteria were used to assess the methodological quality of each of the included trials [25]. The risk of bias was performed by using the Newcastle–Ottawa Scale [26].
5. Conclusions
A medical device containing xyloglucan, hibiscus and propolis is superior to comparator regimens in terms of clinical effectiveness in adult women with microbiologically confirmed or clinical suspicion of uncomplicated cystitis and is associated with a high patient compliance. XHP, in this sense, may represent a novel starting grid to expand the armamentarium for uncomplicated UTIs.
Author Contributions
Conceptualization, T.C. and A.G.-L.; methodology, U.A.; software, T.C.; formal analysis, T.C., S.M. and I.T.; data curation, T.C. and U.A.; writing—original draft preparation, T.C., P.V. and M.R.; writing—review and editing, G.L.; supervision, A.P., V.M. and T.E.B.J. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Conflicts of Interest
The authors declare the following conflict of interest: Tommaso Cai received a travel and speaker grant from the Noventure-Ferrer Company, but it was not related to this manuscript.
References
- Silverman, J.A.; Schreiber, H.L.; Hooton, T.M.; Hultgren, S.J. From physiology to pharmacy: Developments in the pathogenesis and treatment of recurrent urinary tract infections. Curr. Urol. Rep. 2013, 14, 448–456. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cai, T.; Tamanini, I.; Kulchavenya, E.; Perepanova, T.; Köves, B.; Wagenlehner, F.M.E.; Tandogdu, Z.; Bonkat, G.; Bartoletti, R.; Bjerklund Johansen, T.E. The role of nutraceuticals and phytotherapy in the management of urinary tract infections: What we need to know? Arch. Ital. Urol. Androl. 2017, 89, 1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cai, T.; Cocci, A.; Tiscione, D.; Puglisi, M.; Di Maida, F.; Malossini, G.; Verze, P.; Palmieri, A.; Mirone, V.; Bjerklund Johansen, T.E. L-Methionine associated with Hibiscus sabdariffa and Boswellia serrata extracts are not inferior to antibiotic treatment for symptoms relief in patients affected by recurrent uncomplicated urinary tract infections: Focus on antibiotic-sparing approach. Arch. Ital. Urol. Androl. 2018, 90, 97–100. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bonkat, G.; Bartoletti, R.; Bruyère, F.; Cai, T.; Geerlings, S.E.; Köves, B.; Schubert, S.; Wagenlehner, F. EAU Guidelines on Urological Infections. Available online: https://uroweb.org/guideline/urological-infections/ (accessed on 14 September 2021).
- Cai, T.; Tamanini, I.; Cocci, A.; Di Maida, F.; Caciagli, P.; Migno, S.; Mereu, L.; Tateo, S.; Malossini, G.; Palmieri, A.; et al. Xyloglucan, hibiscus and propolis to reduce symptoms and antibiotics use in recurrent UTIs: A prospective study. Future Microbiol. 2019, 14, 1013–1021. [Google Scholar] [CrossRef] [Scilit]
- Costache, R.C.; Novac, B.; Bardan, T.R.; Agapie, D.N.; Edu, A. Xyloglucan + gelose combination versus placebo as adjuvant therapy to first-line antimicrobials for uncomplicated urinary tract infection in adults. Urol. Int. 2019, 102, 468–475. [Google Scholar] [CrossRef] [Scilit]
- Garcia-Larrosa, A.; Alexe, O. Efficacy and Safety of a Medical Device versus Placebo in the Early Treatment of Patients with Symptoms of Urinary Tract Infection: A Randomized Controlled Trial. Clin. Microbiol. 2016, 5, 1. [Google Scholar] [CrossRef]
- Salvatorelli, N.; Garcia-Larrosa, A.; Allegrini, A.; Pavone, D. A New Approach to the Treatment of Uncomplicated Cystitis: Results of a Randomized Placebo-Controlled Clinical Trial. Urol. Int. 2016, 97, 347–351. [Google Scholar] [CrossRef] [Scilit]
- Wagenlehner, F.M.E.; Bjerklund Johansen, T.E.; Cai, T.; Koves, B.; Kranz, J.; Pilatz, A.; Tandogdu, Z. Epidemiology, definition and treatment of complicated urinary tract infections. Nat. Rev. Urol. 2020, 17, 586–600. [Google Scholar] [CrossRef] [Scilit]
- Sihra, N.; Goodman, A.; Zakri, R.; Sahai, A.; Malde, S. Nonantibiotic prevention and management of recurrent urinary tract infection. Nat. Rev. Urol. 2018, 15, 750–776. [Google Scholar] [CrossRef] [Scilit]
- De Servi, B.; Ranzini, F.; Piqué, N. Effect of Utipro(®) (containing gelatin-xyloglucan) against Escherichia coli invasion of intestinal epithelial cells: Results of an in vitro study. Future Microbiol. 2016, 11, 651–658. [Google Scholar] [CrossRef] [Scilit]
- Olier, M.; Sekkal, S.; Harkat, C.; Eutamene, H.; Theodorou, V. Evaluation of reticulated gelatin-hibiscus-propolis against intestinal commensal species commonly associated with urinary tract infections. Future Microbiol. 2017, 12, 505–513. [Google Scholar] [CrossRef] [Scilit]
- Fraile, B.; Alcover, J.; Royuela, M.; Rodríguez, D.; Chaves, C.; Palacios, R.; Piqué, N. Xyloglucan, hibiscus and propolis for the prevention of urinary tract infections: Results of in vitro studies. Future Microbiol. 2017, 12, 721–731. [Google Scholar] [CrossRef] [Scilit]
- Beerepoot, M.; Geerlings, S. Non-antibiotic prophylaxis for urinary tract infections. Pathogens 2016, 5, 36. [Google Scholar] [CrossRef] [Scilit]
- Alshami, I.; Alharbi, A.E. Hibiscus sabdariffa extract inhibits in vitro biofilm formation capacity of Candida albicans isolated from recurrent urinary tract infections. Asian Pac. J. Trop. Biomed. 2014, 4, 104–108. [Google Scholar] [CrossRef] [Scilit]
- Lavigne, J.P.; Vitrac, X.; Bernard, L.; Bruyère, F.; Sotto, A. Propolis can potentialise the anti-adhesion activity of proanthocyanidins on uropathogenic Escherichia coli in the prevention of recurrent urinary tract infections. BMC Res. Notes 2011, 4, 522. [Google Scholar] [CrossRef] [Scilit]
- Esposito, E.; Campolo, M.; Casili, G.; Lanza, M.; Franco, D.; Filippone, A.; Peritore, A.F.; Cuzzocrea, S. Protective effects of xyloglucan in association with the polysaccharide gelose in an experimental model of gastroenteritis and urinary tract infections. Int. J. Mol. Sci. 2018, 19, 1844. [Google Scholar] [CrossRef] [Scilit]
- Betschart, C.; Albrich, W.C.; Brandner, S.; Faltin, D.; Kuhn, A.; Surbek, D.; Geissbuehler, V. Guideline of the Swiss Society of Gynaecology and Obstetrics (SSGO) on acute and recurrent urinary tract infections in women, including pregnancy. Swiss Med. Wkly. 2020, 150, w20236. [Google Scholar] [CrossRef] [Scilit]
- Cai, T.; Konstantinidis, C.; Ward, S. A non-pharmacological approach to the treatment of urinary tract infections: Case reports with Utipro® Plus. Drugs Context. 2021, 10, 2021-2-2. [Google Scholar] [CrossRef] [Scilit]
- Moher, D.; Liberati, A.; Tetzlaff, J.; Altman, D.G.; Group, P. Preferred reporting items for systematic reviews and meta-analyses: The PRISMA statement. Ann. Intern. Med. 2009, 151, 264–269. [Google Scholar] [CrossRef]
- Köves, B.; Cai, T.; Veeratterapillay, R.; Pickard, R.; Seisen, T.; Lam, T.B.; Yuan, C.Y.; Bruyere, F.; Wagenlehner, F.; Bartoletti, R.; et al. Benefits and Harms of Treatment of Asymptomatic Bacteriuria: A Systematic Review and Meta-analysis by the European Association of Urology Urological Infection Guidelines Panel. Eur. Urol. 2017, 72, 865–868. [Google Scholar] [CrossRef] [Scilit]
- Available online: https://www.erim.eur.nl/fileadmin/erim_content/images/metaessentials/Metaanalyze_dichotomous_data.pdf (accessed on 14 September 2021).
- Cai, T.; Tamanini, I.; Tascini, C.; Köves, B.; Bonkat, G.; Gacci, M.; Novelli, A.; Horcajada, J.P.; Bjerklund Johansen, T.E.; Zanel, G. Fosfomycin Trometamol versus Comparator Antibiotics for the Treatment of Acute Uncomplicated Urinary Tract Infections in Women: A Systematic Review and Meta-Analysis. J. Urol. 2020, 203, 570–578. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Duval, S.; Tweedie, R. Trim and fill: A simple funnel-plot-based method of testing and adjusting for publication bias in meta-analysis. Biometrics 2000, 56, 455–463. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jadad, A.R.; Moore, R.A.; Carroll, D.; Jenkinson, C.; Reynolds, D.J.; Gavaghan, D.J.; McQuay, H.J. Assessing the quality of reports of randomized clinical trials: Is blinding necessary? Control. Clin. Trials 1996, 17, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Wells, G.A.; Shea, B.; O’Connell, D.; Peterson, J.; Welch, V.; Losos, M.; Tugwell, P. The Newcastle-Ottawa Scale (NOS) for Assessing the Quality of Nonrandomized Studies in Meta-Analyses, 2011. Available online: http://www.ohri.ca/programs/clinical_epidemiology/oxford.asp (accessed on 14 September 2021).

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).