


Abstract
This multidisciplinary series is aimed at offering readers many opportunities to appreciate how a clinical and ethical approach to pregnancy has changed in patients with kidney diseases and with related conditions, including diabetes, hypertension, and immunologic diseases. Furthermore, this series aims to focus on the fact that many issues remain unreslved, that there are enormous gaps in knowledge, and that the bioethical approach needs to integrated in the clinical practice, which would allow for a deeper appreciation of different cultural and religious backgrounds. Much still needs to be done to allow women suffering from all stages of chronic kidney disease (CKD) and those with predisposed conditions, so that they may experience safe pregnancies, starting from an increased awareness of the importance of CKD, even in its early stages, to the detection of risk factors. Women who have experienced preeclampsia or acute kidney injury in pregnancy need to have follow-up checks. The role of urinary infections, kidney stones, and urinary malformations is not fully acknowledged, nor have univocal control schedules and treatment schemas yet been defined for the different kidney diseases. In this regard, the fight for equitable treatment for all women with acute or chronic kidney disease in pregnancy and for the widespread prevention of adverse pregnancy-related and long-term outcomes is ultimately a battle for equitable healthcare.
Pregnancy in dialysis patients is the tip of an iceberg. When, in 1970, professor Confortini reported on the first full-term pregnancy in a patient on haemodialysis, few, if any, nephrologists expected that, some 50 years later, hundreds of women would have conceived and given birth while on haemodialysis [1,2].
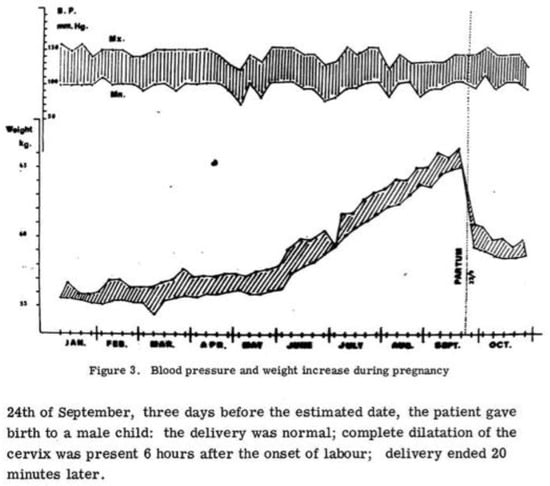
It is worth reading Confortini’s paper, which is available online, with its commentary and its handmade graphs that may make us smile today, but at the same time, show us the enormous advances that have been made in medicine, communications, and overall research tools (Figure 1). The World Wide Web did not exist and its revolutionary use in medicine was still to come, but innovation did not wait for the Internet.
Figure 1.
Weight gain during pregnancy on dialysis, from Confortini et al. [1] (Reproduced with permission from ERA-EDTA).
Today, the chance that a woman on dialysis will have a baby remains about 1:100 lower than a woman in the general population. In addition, the babies are often born pre-term and are small for their gestational age [2,3,4].
Great advances have been made, but can more be done?
The importance of the lessons that have been learned from these ‘extreme’ cases are not limited to obstetric nephrology, but affect the overall management of dialysis. Advances in dialysis have led to advances in obstetric nephrology, and conversely, advances in obstetric nephrology have improved our understanding of the physiology (or non-physiology) of dialysis and of the level of depuration that can be achieved with renal replacement therapy [5].
These exchanges are very important in nephrology. The field of what is now often called ‘obstetric nephrology’ is almost, by definition, a multidisciplinary one, involving not only nephrologists, obstetricians, and neonatologists, but also many other specialties and competences.
Professor Confortini was not a nephrologist. He belonged to the generation of surgeons who, in the early years of dialysis, in Italy, were often responsible for the care of dialysis patients. He was also one of the first people in this country to perform arterio-venous Cimino-Brescia fistula for hemodialysis.
Reading his paper encourages us to reflect on the importance of being open-minded beyond the ‘usual’ competence of our chosen specialty. His paper still conveys not only his enthusiasm “We think it is worthwhile to report what may be the first case of a female patient undergoing regular dialysis treatment, conceiving, and bringing to full term a perfectly normal pregnancy, and giving birth to a viable and healthy child”, but also his respect for the mother’s wishes. This was a concept that was not widely accepted in the overall paternalistic approach to medicine in early the Seventies, especially in Southern European countries [1].
The paper goes on, “In January 1970 the patient conceived. She did not allow termination of pregnancy, and, because of her excellent clinical condition, perfect mental balance, and her expressed wishes, we decided to try bringing the pregnancy to its full term” [1]. The innovative character of this statement will be better appreciated if we compare it with an article on pregnancy with kidney diseases, which appeared in The Lancet at about the same time, and began by stating that, “Children of women with renal disease used to be born dangerously or not at all—not at all if their doctors had their way” [6].
We hope this multidisciplinary series will offer readers many opportunities to appreciate how ‘doctors’ ways’ have changed, while not losing sight of the fact that many issues remain unsolved, that there are enormous gaps in knowledge in all clinical fields, and that the bioethical approach needs to integrated in the clinical practice, allowing for a deeper appreciation of different cultural and religious backgrounds.
Much has to be done to allow women with all stages of chronic kidney disease (CKD) to experience safe pregnancies, starting from an increased awareness of the importance of CKD even in its early stages, to the detection of risk factors, and to the follow-up checks for women who have experienced preeclampsia or acute kidney injury in pregnancy. The role of urinary infections, kidney stones, and urinary malformations is not fully acknowledged, nor have univocal control schedules and treatment schemas yet been defined for the different kidney diseases.
If the lists of what we would like to know are long (Table 1, Table 2 and Table 3), the lists of what we would like to make available might be even longer, and they should be adapted to different settings of care, as it is too early to talk about intensive daily dialysis in a setting where no treatment for acute kidney failure is yet available.
Table 1.
Some bioethical questions waiting for answers regarding pregnant women with chronic kidney disease (CKD) and related diseases.
Table 2.
Some clinical questions waiting for answers regarding pregnant women with CKD. BP—blood pressure.
Table 3.
Some clinical questions waiting for answers regarding pregnant women with acute kidney involvement or other diseases potentially involving the kidney.
In this regard, it should be kept in mind that the fight for equitable treatment for all women with acute or chronic kidney disease in pregnancy, and for the widespread prevention of adverse pregnancy-related and long-term outcomes, is ultimately a battle for overall equitable healthcare.
This editorial is dedicated to all of the women with a chronic disease who have fought and are fighting to live a full life, and to those who are attempting overcome unexpected barriers, as well as to those who have given up or have been overwhelmed by the difficulties that they have encountered.
Bringing hope should be a part of all treatments.
We know that avoiding unnecessary pregnancy-related deaths is possible, just as we know that this will require a multidisciplinary commitment [7].
Giving birth when suffering from disease is often seen as a life sentence, understanding physiology through pathology, and improving knowledge on kidney diseases are all fascinating challenges. If this series will to add just a little bit to any one of them, our goal will be met.
Funding
This research received no external funding.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Confortini, P.; Galanti, G.; Ancona, G.; Giongio, A.; Bruschi, E.; Lorenzini, E. Full-term pregnancy and successful delivery in a patient on chronic hemodialysis. Proc. Eur. Dial. Transplant. Assoc. 1971, 8, 74–80, (The full text is available on line at the following link, last accessed 10 May 2018: http://www.era-edta.org/proceedings/vol8/V8_09.pdf). [Google Scholar]
- Piccoli, G.B.; Minelli, F.; Versino, E.; Cabiddu, G.; Attini, R.; Vigotti, F.N.; Rolfo, A.; Giuffrida, D.; Colombi, N.; Pani, A.; et al. Pregnancy in dialysis patients in the new millennium: a systematic review and meta-regression analysis correlating dialysis schedules and pregnancy outcomes. Nephrol. Dial. Transplant. 2016, 31, 1915–1934. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Piccoli, G.B.; Alrukhaimi, M.; Liu, Z.H.; Zakharova, E.; Levin, A.; World Kidney Day Steering Committee. What we do and do not know about women and kidney diseases; questions unanswered and answers unquestioned: reflection on World Kidney Day and International Woman’s Day. BMC Nephrol. 2018, 19, 66. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shahir, A.K.; Briggs, N.; Katsoulis, J.; Levidiotis, V. An observational outcomes study from 1966–2008, examining pregnancy and neonatal outcomes from dialysed women using data from the ANZDATA Registry. Nephrology (Carlton) 2013, 18, 276–284. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hladunewich, M.A.; Hou, S.; Odutayo, A.; Cornelism, T.; Pierratos, A.; Goldstein, M.; Tennankore, K.; Keunen, J.; Hui, D.; Chan, C.T. Intensive hemodialysis associates with improved pregnancy outcomes: a Canadian and United States cohort comparison. J. Am. Soc. Nephrol. 2014, 25, 1103–1109. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Editorial. Pregnancy and renal disease. Lancet 1975, 25, 801–802. [Google Scholar]
- Tunçalp, Ӧ.; Were, W.M.; MacLennan, C.; Oladapo, O.T.; Gülmezoglu, A.M.; Bahl, R.; Daelmans, B.; Mathai, M.; Say, L.; Kristensen, F.; et al. Quality of care for pregnant women and newborns—The WHO vision. BJOG 2015, 122, 1045–1049. [Google Scholar] [CrossRef] [Scilit] [PubMed]

© 2018 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).