


Current Evidence on the Relationship Between Perioperative Hypothermia and Surgical Site Infection: A Scoping Review
 , ,
Abstract
1. Introduction
2. Methods
2.1. Research Question
2.2. Elegibility Criteria
- (1)
- fixed temperature thresholds (generally <36 °C, but with a range of <35 to <35.5 °C),
- (2)
- time-dependent definitions based on the duration of exposure below a given threshold, and
- (3)
- composite or continuous measures, such as cumulative heat load or area under the temperature curve.
2.3. Information Sources and Search Strategy
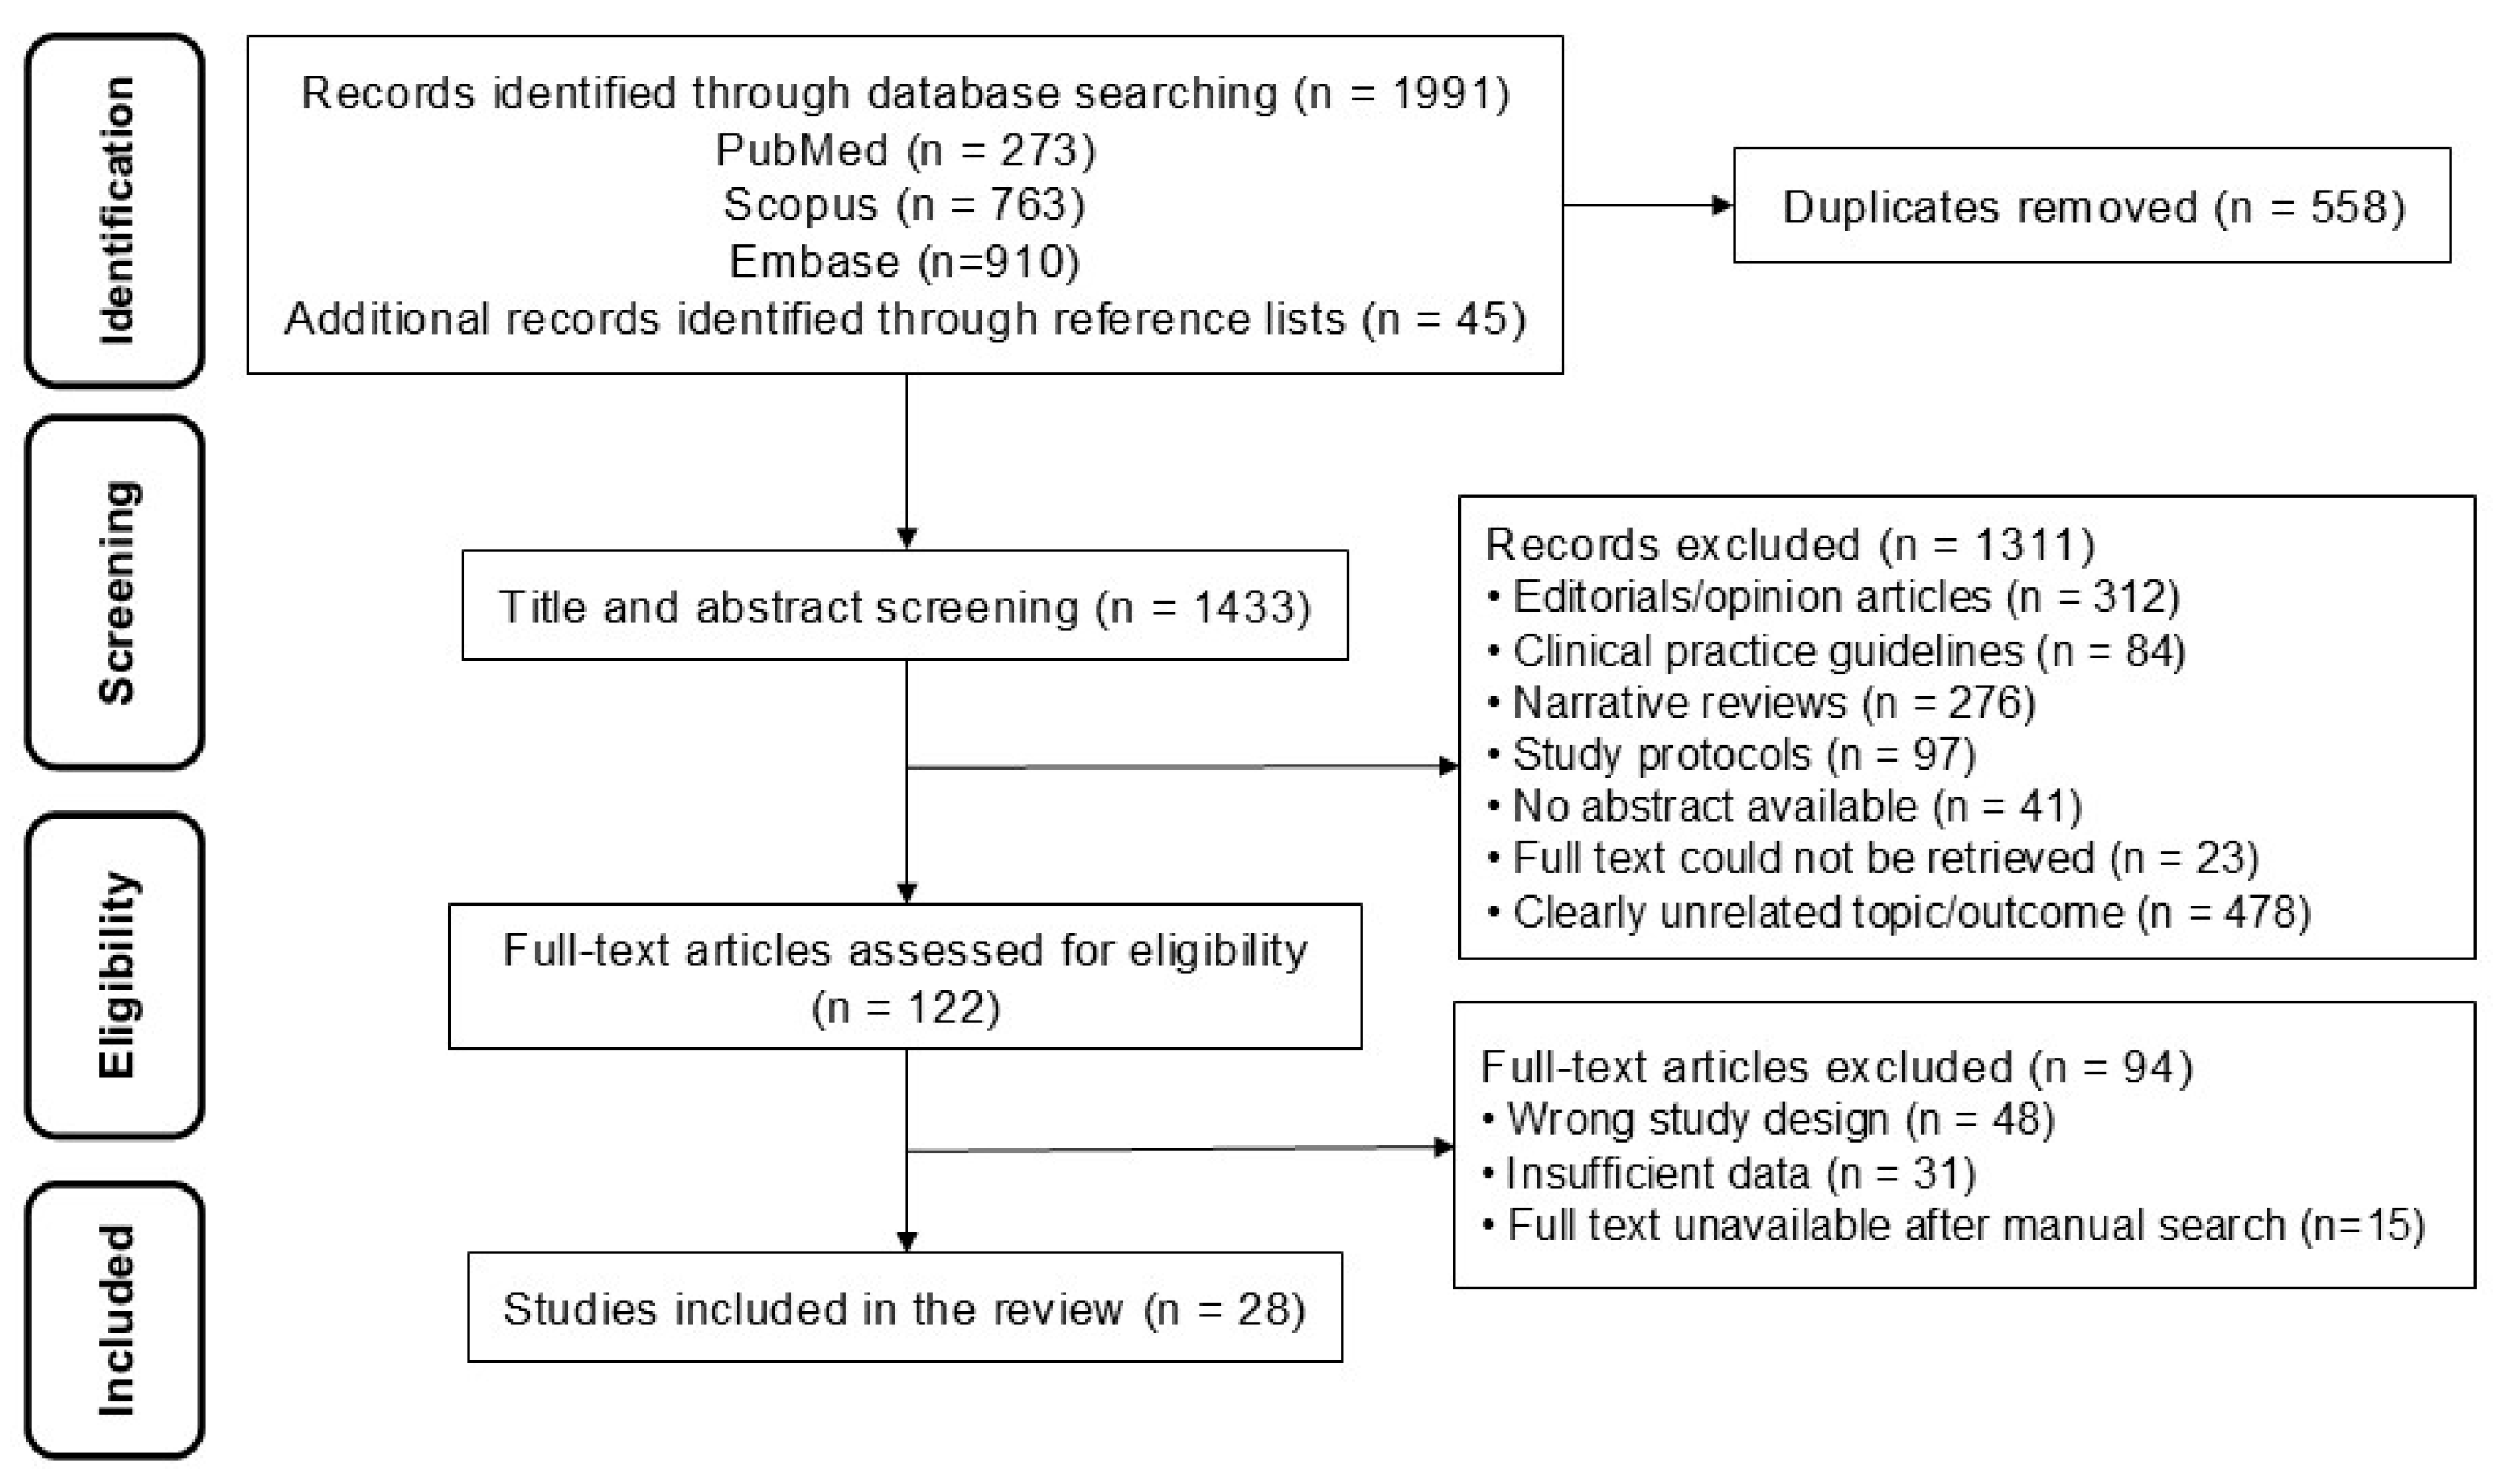
2.4. Study Selection Process
2.5. Data Extraction
3. Results
Heterogeneity in the Definition and Measurement of Perioperative Hypothermia
4. Discussion
Limitations
5. Conclusions
Supplementary Materials
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
References
- Chen, R.; Du, Y.; Chen, L.; Bai, Y.; Zhang, Y.; Yu, T.; Li, H.; Wang, G. The impact of perioperative hypothermia on surgical site infection risk: A meta-analysis. BMC Anesthesiol. 2025, 25, 443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bu, N.; Zhao, E.; Gao, Y.; Zhao, S.; Bo, W.; Kong, Z.; Wang, Q.; Gao, W. Association between perioperative hypothermia and surgical site infection: A meta-analysis. Medicine 2019, 98, e14392. [Google Scholar] [CrossRef] [Scilit]
- Brown, M.J.; Curry, T.B.; Hyder, J.A.; Berbari, E.F.; Truty, M.J.; Schroeder, D.R.; Hanson, A.C.; Kor, D.J. Intraoperative Hypothermia and Surgical Site Infections in Patients with Class I/Clean Wounds: A Case-Control Study. J. Am. Coll. Surg. 2017, 224, 160–171. [Google Scholar] [CrossRef] [Scilit]
- Wang, H.; Xu, P.; Luo, J.; Jiang, Q. The Risk Assessment Tools for Intraoperative Hypothermia in Adults: A Scope Review. Nurs. Open 2026, 13, e70416. [Google Scholar] [CrossRef] [Scilit]
- Pietrzyk, B.; Mikolajczyk, J.; Joniec, A.; Fajferek, T.; Kaczara, S. The Role of Thermal Immunomodulation in Postoperative Wound Repair with a Focus on Hepatic Surgery. Int. J. Mol. Sci. 2026, 27, 1473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yan, L.; Yao, L.; Zhao, Q.; Xiao, M.; Li, Y.; Min, S. Risk Prediction Models for Inadvertent Intraoperative Hypothermia: A Systematic Review. J. Perianesth. Nurs. 2021, 36, 724–729. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Read, T.E.; Brozovich, M.; Caushaj, P.F. Perioperative hypothermia during colectomy: When do patients get cold? Tech. Coloproctol. 2018, 22, 343–346. [Google Scholar] [CrossRef] [Scilit]
- Carpenter, L.; Baysinger, C.L. Maintaining perioperative normothermia in the patient undergoing cesarean delivery. Obstet. Gynecol. Surv. 2012, 67, 436–446. [Google Scholar] [CrossRef] [Scilit]
- Matos, J.R.; McSwain, J.R.; Wolf, B.J.; Doty, J.W.; Wilson, S.H. Examination of intra-operative core temperature in joint arthroplasty: A single-institution prospective observational study. Int. Orthop. 2018, 42, 2513–2519. [Google Scholar] [CrossRef] [Scilit]
- Stamos, M.J. Lessons Learned in Intraoperative Hypothermia: Coming in from the Cold. JAMA Surg. 2015, 150, 575–576. [Google Scholar] [CrossRef] [Scilit]
- Arksey, H.; O’Malley, L. Scoping studies: Towards a methodological framework. Int. J. Soc. Res. Methodol. 2005, 8, 19–32. [Google Scholar] [CrossRef] [Scilit]
- Levac, D.; Colquhoun, H.; O’Brien, K.K. Scoping studies: Advancing the methodology. Implement. Sci. 2010, 5, 69. [Google Scholar] [CrossRef] [Scilit]
- Aromataris, E.; Munn, Z. JBI Manual for Evidence Synthesis; JBI: Philadelphia, PA, USA, 2020. [Google Scholar]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467. [Google Scholar] [CrossRef] [Scilit]
- Ouzzani, M.; Hammady, H.; Fedorowicz, Z.; Elmagarmid, A. Rayyan—A web and mobile app for systematic reviews. Syst. Rev. 2016, 5, 210. [Google Scholar] [CrossRef] [Scilit]
- Grudniewicz, A.; Nelson, M.; Kuluski, K.; Lui, V.; Cunningham, H.V.; Nie, J.X.; Colquhoun, H.; Wodchis, W.P.; Taylor, S.; Loganathan, M.; et al. Treatment goal setting for complex patients: Protocol for a scoping review. BMJ Open 2016, 6, e011869. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yilmaz Eker, P.; Yildiz, E. The Effect of Inadvertent Perioperative Hypothermia on Surgical-Site Infection in Bariatric Surgery Patients. Bariatr. Surg. Pract. Patient Care 2023, 18, 121–127. [Google Scholar] [CrossRef] [Scilit]
- Walters, M.J.; Tanios, M.; Koyuncu, O.; Mao, G.; Valente, M.A.; Sessler, D.I. Intraoperative core temperature and infectious complications after colorectal surgery: A registry analysis. J. Clin. Anesth. 2020, 63, 109758. [Google Scholar] [CrossRef] [Scilit]
- Zeba, S.; Surbatovic, M.; Stanojevic, I.; Radakovic, S.; Djordjevic, D.; Udovicic, I.; Rondovic, G.; Vojvodic, D. The effects of intraoperative hypothermia on cytokine profile: A randomized pilot study. J. Clin. Anesth. 2020, 63, 109779. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, Y.-D.; Zhang, W.-Y.; Xie, G.-H.; Ye, H.; Chu, L.-H.; Guo, Y.-Q.; Lou, Y.; Fang, X.-M. Inadvertent perioperative hypothermia and surgical site infections after liver resection. Hepatobiliary Pancreat. Dis. Int. 2024, 23, 579–585. [Google Scholar] [CrossRef] [Scilit]
- Pang, Q.Y.; Yang, Y.J.; Feng, Y.M.; Sun, S.F.; Liu, H.L. Relationship between intraoperative hypothermia and hyperthermia with postoperative pulmonary infection and surgical site infection in major non-cardiac surgery. Front. Med. 2024, 11, 1408342. [Google Scholar] [CrossRef] [Scilit]
- Abugri, B.O.; Matsusaki, T.; Ren, W.; Morimatsu, H. Intraoperative Hypothermia Is Not Associated with Surgical Site Infections after Total Hip or Knee Arthroplasty. Acta Medica Okayama 2022, 76, 651–660. [Google Scholar] [CrossRef]
- Baucom, R.B.; Phillips, S.E.; Ehrenfeld, J.M.; Muldoon, R.L.; Poulose, B.K.; Herline, A.J.; Wise, P.E.; Geiger, T.M. Association of Perioperative Hypothermia During Colectomy with Surgical Site Infection. JAMA Surg. 2015, 150, 570–575. [Google Scholar] [CrossRef] [Scilit]
- Siddiqiui, T.; Pal, K.I.; Shaukat, F.; Mubashir, H.; Ali, A.A.; Malik, M.J.A.; Shahzad, N. Association Between Perioperative Hypothermia and Surgical Site Infection After Elective Abdominal Surgery: A Prospective Cohort Study. Cureus 2020, 12, e11145. [Google Scholar] [CrossRef] [Scilit]
- Ribeiro, J.C.; Bellusse, G.C.; Martins de Freitas, I.C.; Galvão, C.M. Effect of perioperative hypothermia on surgical site infection in abdominal surgery: A prospective cohort study. Int. J. Nurs. Pract. 2021, 27, e12934. [Google Scholar] [CrossRef] [Scilit]
- Tsuchida, T.; Takesue, Y.; Ichiki, K.; Uede, T.; Nakajima, K.; Ikeuchi, H.; Uchino, M. Influence of Peri-Operative Hypothermia on Surgical Site Infection in Prolonged Gastroenterological Surgery. Surg. Infect. 2016, 17, 570–576. [Google Scholar] [CrossRef] [Scilit]
- Frisch, N.B.; Pepper, A.M.; Jildeh, T.R.; Shaw, J.; Guthrie, T.; Silverton, C. Intraoperative Hypothermia During Surgical Fixation of Hip Fractures. Orthopedics 2016, 39, e1170–e1177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Andersen, E.S.; Chishom, T.A.; Rankin, J.; Juan, H.Y.; Coots, L.; Mountziaris, P.M. Impact of Intraoperative Hypothermia on Incidence of Infection in Implant-Based Breast Reconstruction. Plast. Reconstr. Surg. 2024, 153, 35–44. [Google Scholar] [CrossRef] [Scilit]
- Ziolkowski, N.; Rogers, A.; Xiong, W.; Hong, B.; Patel, S.; Trull, B.; Jeschke, M. The impact of operative time and hypothermia in acute burn surgery. Burns 2017, 43, 1673–1681. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fahim, M.; Dijksman, L.M.; Biesma, D.H.; Noordzij, P.G.; Smits, A.B. Effect of Intra-Operative Hypothermia on Post-Operative Morbidity in Patients with Colorectal Cancer. Surg. Infect. 2021, 22, 803–809. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eng, O.S.; Raoof, M.; O’LEary, M.P.; Lew, M.W.; Wakabayashi, M.T.; Paz, I.B.; Melstrom, L.G.; Lee, B. Hypothermia Is Associated with Surgical Site Infection in Cytoreductive Surgery with Hyperthermic Intra-Peritoneal Chemotherapy. Surg. Infect. 2018, 19, 618–621. [Google Scholar] [CrossRef] [Scilit]
- Flores-Maldonado, A.; Medina-Escobedo, C.E.; Ríos-Rodríguez, H.M.; Fernández-Domínguez, R. Mild perioperative hypothermia and the risk of wound infection. Arch. Med. Res. 2001, 32, 227–231. [Google Scholar] [CrossRef] [Scilit]
- Seamon, M.J.; Wobb, J.; Gaughan, J.P.; Kulp, H.; Kamel, I.; Dempsey, D.T. The effects of intraoperative hypothermia on surgical site infection: An analysis of 524 trauma laparotomies. Ann. Surg. 2012, 255, 789–795. [Google Scholar] [CrossRef] [Scilit]
- Liedl, H.J.C.; Lazenby, K.A.; Arimoto, R.S.; Singh, A.; Strelzow, J.A. Normothermia to Decrease Surgical Site Infection Risk: Silver Bullet or Fool’s Gold? A Retrospective Cohort Study. JAAOS Glob. Res. Rev. 2024, 8, e23.00227. [Google Scholar] [CrossRef] [Scilit]
- Kim, S.H.; Cha, Y.; Seok, S.Y.; Cho, J.H.; Kim, B.-Y.; Lee, H.-J.; Kim, G.-O. Relationship Between Types of Warming Devices and Surgical Site Infection in Patients Who Underwent Posterior Fusion Surgery Based on National Data. Neurospine 2023, 20, 1328–1336. [Google Scholar] [CrossRef] [Scilit]
- Walz, J.M.; Paterson, C.A.; Seligowski, J.M.; Heard, S.O. Surgical site infection following bowel surgery: A retrospective analysis of 1446 patients. Arch. Surg. 2006, 141, 1014–1018. [Google Scholar] [CrossRef] [Scilit]
- Anannamcharoen, S.; Vachirasrisirikul, S.; Boonya-Assadorn, C. Incisional surgical site infection in colorectal surgery patients. J. Med. Assoc. Thai 2012, 95, 42–47. [Google Scholar]
- Kurz, A.; Sessler, D.I.; Lenhardt, R. Perioperative normothermia to reduce the incidence of surgical-wound infection and shorten hospitalization. Study of Wound Infection and Temperature Group. N. Engl. J. Med. 1996, 334, 1209–1215. [Google Scholar] [CrossRef] [Scilit]
- Shao, L.; Pang, N.; Yan, P.; Jia, F.; Sun, Q.; Ma, W.; Yang, Y. Control of body temperature and immune function in patients undergoing open surgery for gastric cancer. Bosn. J. Basic Med. Sci. 2018, 18, 289–296. [Google Scholar] [CrossRef] [Scilit]
- Kawaraguchi, Y.; Kawaguchi, M.; Inoue, S.; Sakamoto, T.; Kitaguchi, K.; Furuya, H.; Sakaki, T. Effect of deliberate mild hypothermia on the incidence of surgical-wound infection and duration of hospitalization in neurosurgical patients. Masui 1999, 48, 232–237. [Google Scholar]
- Beilin, B.; Shavit, Y.; Razumovsky, J.; Wolloch, Y.; Zeidel, A.; Bessler, H. Effects of mild perioperative hypothermia on cellular immune responses. Anesthesiology 1998, 89, 1133–1140. [Google Scholar] [CrossRef] [Scilit]
- Jildeh, T.R.; Okoroha, K.R.; Marshall, N.E.; Amato, C.; Trafton, H.; Muh, S.J.; Kolowich, P. The effect of intraoperative hypothermia on shoulder arthroplasty. Orthopedics 2018, 41, e523–e528. [Google Scholar] [CrossRef] [Scilit]
- Mohib, Y.; Zahid, M.; Ashraf, I.; Noordin, S. Does hypothermia really contributes to infection in hip and knee arthroplasty? A tertiary care experience. Int. J. Surg. Open 2017, 8, 15–17. [Google Scholar] [CrossRef] [Scilit]
- Todd, M.M.; Hindman, B.J.; Clarke, W.R.; Torner, J.C. Intraoperative Hypothermia for Aneurysm Surgery Trial (IHAST) Investigators. Mild intraoperative hypothermia during surgery for intracranial aneurysm. N. Engl. J. Med. 2005, 352, 135–145. [Google Scholar] [CrossRef] [Scilit]

| Author | Authors’ Country | Study Design | Objective | Results | Limitations |
|---|---|---|---|---|---|
| Yilmaz Eker, et al. [17] | Turkey | Prospective cohort | To determine whether unnoticed perioperative hypothermia affects the risk of surgical site infection in patients undergoing bariatric surgery. | The presence of perioperative hypothermia following bariatric surgery was associated with an increased incidence of surgical site infections (p = 0.001). | Lack of randomization. Variation in how temperature was measured and managed. |
| Walters, MJ, et al. [18] | United States | Retrospective cohort | To assess whether there is a relationship between the average intraoperative core temperature and the risk of serious infections (local or systemic) in adults undergoing colorectal surgery under general anesthesia | When the average temperature was ≤35.4 °C, each 0.5 °C decrease was associated with a higher probability of severe infection (OR = 1.38; p = 0.045). | Single-center study. Small sample size. |
| Zeba, S, et al. [19] | Serbia | Randomized clinical trial | To assess how intraoperative hypothermia affects the cytokine profile (inflammatory markers) in surgical patients. | Intraoperative warming attenuated the increased and sustained proinflammatory response, which is potentially harmful, present in the unwarmed controls (p < 0.01). | Single-center study. Small sample size. |
| Zhou YD, et al. [20] | China | Retrospective cohort | To assess whether unnoticed perioperative hypothermia is associated with an increased incidence of surgical site infections following liver resection. | No significant association was found between hypothermia and SSI following liver resection: high exposure to hypothermia (OR = 1.25; 95% CI: 0.84–1.87; p = 0.266), moderate exposure (OR = 1.00; 95% CI: 0.65–1.53; p = 0.999), and low exposure (OR = 1.11; 95% CI: 0.73–1.65; p = 0.628). | Non-standardized temperature measurement and thermal management. Clinical variation in real-world practice. |
| Pang QY, et al. [21] | China | Retrospective cohort | Association between intraoperative hypothermia and hyperthermia with postoperative pulmonary infection and surgical site infection in major non-cardiac surgery. | Intraoperative hypothermia and hyperthermia were found to be associated with an increased risk of postoperative pulmonary infection related to the duration of exposure (hypothermia > 90 min: aOR = 1.425; 95% CI: 1.131–1.796; hyperthermia > 75 min: aOR = 1.395; 95% CI: 1.208–1.612), AUC for hypothermia (aOR 1.390) and hyperthermia (aOR 2.045), and with surgical site infection also associated with duration (hypothermia > 195 min: aOR = 2.900; 95% CI: 1.703–4.937; hyperthermia > 75 min: aOR = 1.395; 95% CI: 1.208–1.612), AUC for hypothermia (aOR 2.665) and hyperthermia (aOR 2.619) in major non-cardiac surgery. | Variability in temperature measurement. Limited generalizability if it is a single-center study. |
| Abugri BO, et al. [22] | Japan | Retrospective cohort | Association between Surgical Site Infection and Intraoperative Hypothermia in Total Hip and Knee Arthroplasties. | Intraoperative hypothermia occurred in 18.8% of patients and was not associated with SSI in adults undergoing total hip and knee arthroplasty. In contrast, temperatures > 36 °C were associated with an increased risk of SSI (OR = 3.6; 95% CI: 1.367–9.475; p = 0.009). | Single-center study. |
| Baucom RB, et al. [23] | United States | Retrospective cohort | To determine whether intraoperative hypothermia in patients undergoing segmental colectomy is associated with postoperative surgical site infection | Patients undergoing segmental colectomy who experienced a period of intraoperative hypothermia were no more likely to develop a surgical site infection than those who were normothermic (OR = 1.17; 95% CI, 0.76–1.81; p = 0.48). | Single-center study. Specific colorectal surgery. Does not evaluate deeper hypothermia (<35 °C). |
| Siddiqiui T, et al. [24] | United States | Prospective cohort | To determine the association between hypothermia and surgical site infection in elective abdominal surgery. | No statistically significant association was found between hypothermia and surgical site infection, with a similar SSI rate in patients with and without hypothermia (10% vs. 10.8%; p = 0.867). | Observational study Small sample size |
| Ribeiro JC, et al. [25] | Brasil | Prospective cohort | To determine the independent association between perioperative hypothermia and the incidence of surgical site infection in patients undergoing abdominal surgery. | Perioperative hypothermia was an independent risk factor for surgical site infection (RR = 1.89) | Single-center study |
| Tsuchida T, et al. [26] | United States | Retrospective cohort | To determine whether unintentional perioperative hypothermia is associated with an increased risk of postoperative infection. | Severe hypothermia and delayed hypothermia were associated with a higher incidence of surgical site infection and organ/space infection; however, they were not identified as independent risk factors for SSI in the multivariate analysis (severe hypothermia: OR = 1.24; 95% CI: 0.56–2.77; late-onset hypothermia: OR = 0.71; 95% CI: 0.46–1.01). | Small sample size |
| Frisch NB, et al. [27] | United States | Retrospective cohort | To evaluate the effect of intraoperative hypothermia on complications and clinical outcomes in patients with hip fractures undergoing surgical treatment. | Intraoperative hypothermia was associated with an increased rate of deep surgical site infection (OR = 3.30; 95% CI: 1.19–9.14; p = 0.022); in addition, a lower body mass index (p = 0.004) and older age (p = 0.005) were identified as risk factors for hypothermia. | Small sample size |
| Andersen ES, et al. [28] | United States | Retrospective cohort | To analyze the association between intraoperative hypothermia, as a modifiable risk factor, and the occurrence of postoperative surgical site infection in patients undergoing immediate breast reconstruction with implants following mastectomy. | Intraoperative hypothermia is a significant risk factor for postoperative infection in breast reconstruction with implants following mastectomy (OR = 2.567; 95% CI: 1.367–4.818; p < 0.05), and delayed wound healing (OR = 2.023; 95% CI: 1.053–3.884; p < 0.05); therefore, maintaining adequate normothermia during the procedure may promote better clinical outcomes and reduce healing complications. | Observational study. Small sample size. |
| Ziolkowski N, et al. [29] | Canada | Retrospective cohort | To evaluate the association between hypothermia and operative time with postoperative complications in acute burn surgery | In patients with extensive burns, hypothermia predisposed them to infectious complications (RR 1.3; 1.1–1.5; p < 0.0017) and non-infectious complications (RR 1.7; 1.2–2.5; p < 0.0049). Risk stratification revealed that hypothermic patients with extensive burns undergoing prolonged surgery had a higher risk of infectious complications (RR 1.4; 1.1–1.7; p < 0.0068) and non-infectious complications (RR 1.8; 1.1–3.0; p < 0.0132) compared with those without these risk factors. | Observational study Small sample size |
| Fahim M, et al. [30] | United States | Retrospective cohort | To assess whether maintaining normothermia as part of perioperative temperature management strategies is effective in reducing surgical site infections and postoperative complications in patients undergoing colorectal cancer surgery. | Multivariate analysis did not show an association between intraoperative hypothermia and complications, mortality, or readmission, with a surgical site infection rate of 10% at 30 days. | Observational study Small sample size |
| Eng OS, et al. [31] | United States | Retrospective cohort | To investigate the association between perioperative hypothermia and surgical site infections in patients undergoing cytoreductive surgery with hyperthermic intraperitoneal chemotherapy. | Hypothermia is associated with surgical site infections; in the multivariate analysis, the percentage of surgical time spent in hypothermia was the only associated factor (OR 1.04; 95% CI 1.01–1.07; p = 0.008) with surgical site infections within 30 days after surgery. | Single-center study Small sample size |
| Flores-Maldonado A, et al. [32] | Mexico | Prospective cohort | To assess whether mild perioperative hypothermia is associated with surgical site infection in patients undergoing cholecystectomy. | Hypothermia was found to be a significant independent risk factor for infection (RR 6.3; p = 0.01). | Single-center study Small sample size |
| Seamon MJ, et al. [33] | United States | Retrospective cohort | To determine whether intraoperative hypothermia predisposes patients to postoperative surgical site infections following traumatic laparotomy. | Multivariate analysis determined that a single intraoperative temperature measurement below 35 °C independently increased the risk of site infection by 221% for each degree below 35 °C (OR 2.21; 95% CI: 1.24–3.92, p = 0.007). | Single-center study Small sample size |
| Liedl HJC, et al. [34] | United States | Retrospective cohort | To determine the association between perioperative hypothermia and surgical site infection in patients with diabetes mellitus undergoing elective orthopaedic surgery and non-urgent fracture management. | Perioperative hypothermia is not an independent risk factor for surgical site infection; however, in patients with elevated HbA1c, it was associated with an increased risk of SSI (OR 2.39; 95% CI 1.12–5.32; p = 0.022), suggesting an additive effect in the context of poor glycemic control. | Single-center study Small sample size |
| Kim SH, et al. [35] | Republic of Kore | Retrospective cohort | To determine the effect of intraoperative warming devices on surgical site infection rates in patients undergoing posterior lumbar spinal fusion. | The incidence of surgical site infection was higher in patients who underwent forced-air warming than in those who did not undergo active warming (odds ratio [OR], 1.73; p = 0.039), particularly in those over 70 years of age (OR, 4.11; p = 0.014). | They compare warming devices but not the relationship between hypothermia and surgical site infection. |
| Walz JM, et al. [36] | United States | Retrospective cohort | To assess the impact of preoperative antibiotic administration, intraoperative transfusion of blood products, and intraoperative hypothermia on the incidence of surgical site infection in patients undergoing intestinal surgery. | Patients with a lower intraoperative temperature nadir had a lower risk of surgical site infection (p = 0.05; odds ratio, 1.33), although this difference is not statistically significant (35.8 ± 0.8 °C vs. 36.0 ± 0.9 °C, p < 0.05). | It does not evaluate hypothermia as an independent risk factor for surgical site infection. |
| Anannamcharoen S, et al. [37] | Thailand | Prospective cohort | To identify factors that increase the risk of incisional surgical site infection for colorectal surgery. | Postoperative hypothermia was identified as an independent risk factor associated with a higher probability of incisional surgical site infection (OR = 5.6; 95% CI: 1.112–28.482; p = 0.037). | Single-center study Small sample size |
| Kurz A, et al. [38] | United States | Randomized clinical trial | To test the hypothesis that hypothermia increases susceptibility to surgical site infection and prolongs hospital stay in patients undergoing colorectal surgery | The final intraoperative core temperature was 34.7 ± 0.6 °C in the hypothermia group and 36.6 ± 0.5 °C in the normothermia group (p < 0.001). Surgical site infection occurred in 18 of 96 patients (19%) with hypothermia compared with 6 of 104 (6%) with normothermia (p = 0.009). Furthermore, in the hypothermia group, suture removal was delayed by 1 day (p = 0.002) and the hospital stay was prolonged by 2.6 days (20%) (p = 0.01). | Does not evaluate multiple perioperative confounding factors simultaneously. Follow-up focused on immediate postoperative outcomes. |
| Shao L, et al. [39] | Turkey | Prospective cohort | To analyze body temperature, immune function, and wound infection rates in patients undergoing open surgery for gastric cancer. | No intergroup differences were found in infection rates one week after surgery. | Limited sample size Single-center study |
| Kawaraguchi, Y, et al. [40] | Japan | Retrospective cohort | To assess the effect of mild hypothermia on the incidence of surgical site infection and the length of hospital stay in patients undergoing intracranial operation | Surgical site infection was found in 4 of 122 patients (3.3%) in the Hypothermia group, but in none of the 51 patients (0%) in the Normothermia group; however, there were no statistically significant differences in the incidence of surgical site infection or in the length of hospital stay. | Limited sample size |
| Beilin, B, et al. [41] | Israel | Randomized clinical trial | To determine whether mild perioperative hypothermia affects the cellular immune response in patients undergoing abdominal surgery | The results showed that mild perioperative hypothermia suppresses cellular immune function. | It discusses immune suppression but does not directly address the risk of surgical site infection |
| Jildeh TR, et al. [42] | United States | Retrospective cohort | To determine the incidence of intraoperative hypothermia in patients undergoing shoulder arthroplasty and its effect on perioperative complications. | Hypothermia showed no significant association with surgical site infections or any other perioperative complications. The incidence of intraoperative hypothermia was 52.7%, advanced age (p = 0.002), lower body mass index (p = 0.006), the use of interscalene anesthesia (p = 0.004), and a lower white blood cell count (p < 0.001) were associated with a higher incidence of hypothermia. | Single-center study. |
| Mohib Y, et al. [43] | Pakistan | Retrospective cohort | To evaluate the incidence of hypothermia in total hip and knee arthroplasty and its relationship to periprosthetic joint infection. | In patients undergoing joint replacement, the incidence of hypothermia was 11.57% and that of infection was 4.2%; only one patient with hypothermia in the total knee replacement group developed an infection (p = 0.37), while none in the total hip replacement group did so, and the association with diabetes (p = 0.32). Hypothermia was not a risk factor for wound infection following joint replacement. | Limited sample size |
| Todd M et al. [44] | United States (multicenter) | Randomized clinical trial | To evaluate whether intraoperative hypothermia (33 °C) improves neurological outcomes compared with normothermia in patients undergoing surgery for intracranial aneurysm. | No significant differences were observed between groups in overall adverse events or major outcomes. Surgical site infections were not a primary endpoint; however, infection-related outcomes (e.g., bacteremia) were reported, with a slightly higher incidence in the hypothermia group (5% vs. 3%, p = 0.05). | Surgical site infection was not a predefined primary or secondary outcome. The study population was limited to patients with subarachnoid hemorrhage and good neurological grade, which may limit generalizability. |
| Study | Temperature Threshold | Measurement Type | Exposure Metric | SSI Outcome |
|---|---|---|---|---|
| Yilmaz Eker, et al. [17] | <36 °C | Not specified | Dichotomous (yes/no) | Primary |
| Walters, MJ, et al. [18] | ≤35.4 °C | Mean intraoperative | Continuous (per 0.5 °C decrease) | Primary |
| Zeba, S, et al. [19] | Not specified | Not specified | Group comparison (warming vs. control) | Secondary (immune markers) |
| Zhou YD, et al. [20] | <36 °C | Not specified | Categorical exposure levels | Primary |
| Pang QY, et al. [21] | <36 °C/>37.3 °C | Repeated measures | Duration + AUC | Primary |
| Abugri BO, et al. [22] | <36 °C | Not specified | Dichotomous | Primary |
| Baucom RB, et al. [23] | <36 °C | Not specified | Dichotomous (any hypothermia) | Primary |
| Siddiqiui T, et al. [24] | <36 °C | Not specified | Dichotomous | Primary |
| Ribeiro JC, et al. [25] | <36 °C | Repeated measures | Duration (>75 min) | Primary |
| Tsuchida T, et al. [26] | Not specified | Not specified | Severity categories | Primary |
| Frisch NB, et al. [27] | Not specified | Not specified | Dichotomous | Primary |
| Andersen ES, et al. [28] | <35.5 °C | Not specified | Dichotomous + duration | Primary |
| Ziolkowski N, et al. [29] | Not specified | Not specified | Dichotomous + operative time | Primary |
| Fahim M, et al. [30] | Not specified | Not specified | Dichotomous | Primary |
| Eng OS, et al. [31] | <36 °C | Repeated measures | % operative time | Primary |
| Flores-Maldonado A, et al. [32] | <36 °C | Not specified | Dichotomous | Primary |
| Seamon MJ, et al. [33] | <35 °C | Single measurement | Continuous (per degree) | Primary |
| Liedl HJC, et al. [34] | Not specified | Not specified | Dichotomous | Primary |
| Kim SH, et al. [35] | Not applicable | Not specified | Warming strategy (indirect) | Secondary |
| Walz JM, et al. [36] | Not specified | Nadir temperature | Continuous | Secondary |
| Anannamcharoen S, et al. [37] | Not specified | Postoperative | Dichotomous | Primary |
| Kurz A, et al. [38] | ~34.7 °C vs. 36.6 °C | Continuous monitoring | Group comparison | Primary |
| Shao L, et al. [39] | Not specified | Not specified | Group comparison | Primary |
| Kawaraguchi, Y, et al. [40] | Not specified | Not specified | Dichotomous | Primary |
| Beilin, B, et al. [41] | Not specified | Not specified | Immune response | Secondary |
| Jildeh TR, et al. [42] | <36 °C | Not specified | Dichotomous | Primary |
| Mohib Y, et al. [43] | <36 °C | Not specified | Dichotomous | Primary |
| Todd M et al. [44] | 33 °C | Controlled | Group comparison | Secondary |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Ortiz-Tello, A.P.; Ospina-Gomez, S.; Bonilla, N.; Ríos-Barbosa, F.; Tuta-Quintero, E. Current Evidence on the Relationship Between Perioperative Hypothermia and Surgical Site Infection: A Scoping Review. J. Clin. Med. 2026, 15, 4501. https://doi.org/10.3390/jcm15124501
Ortiz-Tello AP, Ospina-Gomez S, Bonilla N, Ríos-Barbosa F, Tuta-Quintero E. Current Evidence on the Relationship Between Perioperative Hypothermia and Surgical Site Infection: A Scoping Review. Journal of Clinical Medicine. 2026; 15(12):4501. https://doi.org/10.3390/jcm15124501
Chicago/Turabian StyleOrtiz-Tello, Angie Paola, Sebastian Ospina-Gomez, Nicole Bonilla, Fernando Ríos-Barbosa, and Eduardo Tuta-Quintero. 2026. "Current Evidence on the Relationship Between Perioperative Hypothermia and Surgical Site Infection: A Scoping Review" Journal of Clinical Medicine 15, no. 12: 4501. https://doi.org/10.3390/jcm15124501
APA StyleOrtiz-Tello, A. P., Ospina-Gomez, S., Bonilla, N., Ríos-Barbosa, F., & Tuta-Quintero, E. (2026). Current Evidence on the Relationship Between Perioperative Hypothermia and Surgical Site Infection: A Scoping Review. Journal of Clinical Medicine, 15(12), 4501. https://doi.org/10.3390/jcm15124501

