


Abstract
Introduction: TAVR remains a complex procedure that may result in serious intraprocedural complications. In many of these circumstances, venoarterial extracorporeal membrane oxygenation (V-A ECMO) helps to manage complications, provides a hemodynamic back-up, and bridges to an emergency open heart surgery. The clinical outcomes of 27 patients who underwent prophylactic implantation of peripheral V-A ECMO (pV-A ECMO) during high-risk transcatheter aortic valve replacement (TAVR) cases are described. Methods: From June 2012 to October 2022, 590 consecutive patients underwent TAVR at our center. Of these, 27 patients (4.5%) underwent TAVR with pV-AECMO because they were deemed very high risk for periprocedural complications and formed the study population. Results: There were no pV-A ECMO, hemodynamic or TAVR implantation complications. Decannulation of the ECMO system was performed in 92.6% of cases at the end of the procedure in the hybrid-operating theatre. The mean duration of pV-A ECMO for procedure support was 51.4 ± 10.3 min. There were no ECMO-related vascular or bleeding complications. Conclusion: This study shows that the prophylactic placement of awake peripheral V-A ECMO provides excellent temporary cardio-circulatory and pulmonary support during very high-risk TAVR procedures.
1. Introduction
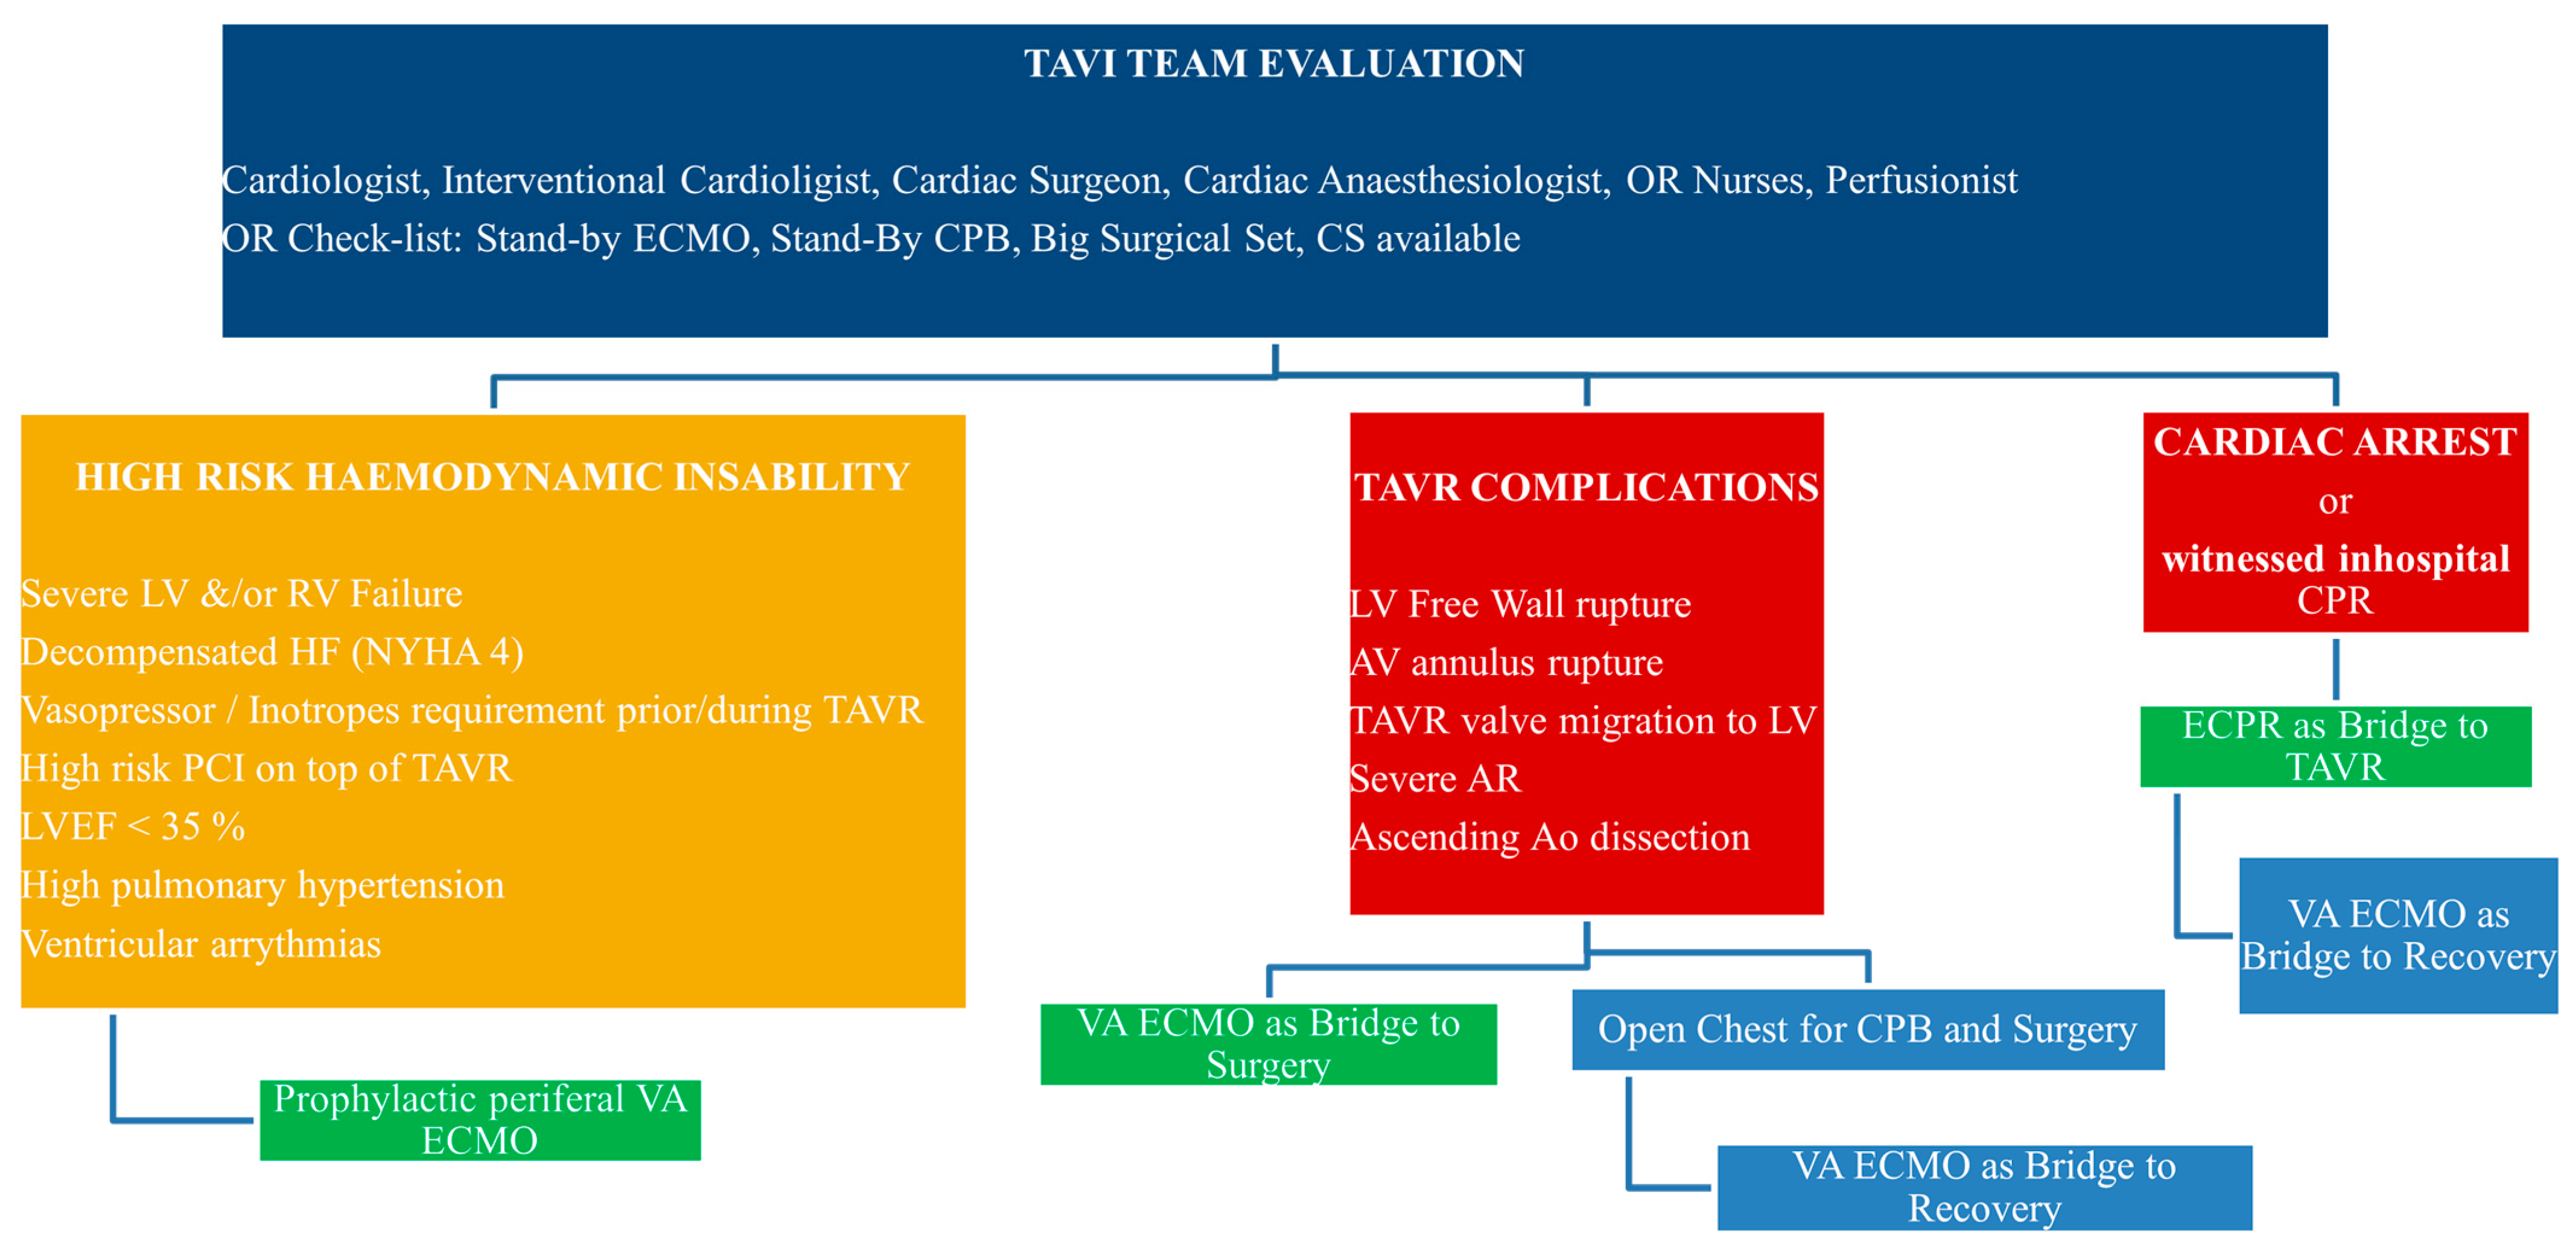
During high-risk transcatheter aortic valve replacement (TAVR) operations, there are several patient and/or procedure-related conditions that predispose to complications. Depressed left ventricular ejection fraction, severe pulmonary artery hypertension, and decompensated or high-grade heart failure constitute high-risk patients. In order to mitigate adverse outcomes in such cases, we implemented an algorithm to be used if such high-risk conditions were present. The strategy prefiguration was described by Raffa GM et al. [1] and summarized in an algorithm of prophylactic and emergency Veno-arterial extracorporeal membrane oxygenation (V-A ECMO) during TAVR for institutions without cardiac surgery on site. Our institution is the reference heart surgery and ECMO center in the country, so we decided to adapt the algorithm to our conditions (Figure 1). Clinical outcomes of 27 patients who underwent prophylactic implantation of peripheral V-A ECMO (pV-A ECMO) during high-risk TAVR cases are described.
Figure 1.
The algorithm of prophylactic and emergency veno-arterial extracorporeal membrane oxygenation for high-risk TAVR procedures with cardiac surgery on site. AV—Aortic Valve; CPB—Cardio Pulmonary Bypass; CS—Cardiac Surgeon; ECPR—Extracorporeal Cardio-Pulmonary Resuscitation; HF—Heart Failure; LVEF—Left Ventricular Ejection Fraction; NYHA—New-York Heart Association; OR—Operating Room; PCI—Percutaneous Intervention; RV—Right Ventricle; TAVR—Transcatheter Aortic Valve Replacement.
2. Materials and Methods
From June 2012 to October 2022, 590 consecutive patients underwent TAVR at our center. Of these, 27 patients (4.5%) underwent TAVR with pV-A ECMO because they were deemed very high risk for periprocedural complications and formed the study population (Table 1). TAVR valves used included balloon-expandable Sapien XT™ (Edwards Lifesciences, Irvine, CA, USA), Myval™ (Meril Life Sciences Pvt. Ltd., Vapi, Gujarat, India), and self-expandable EvolutR™ (Medtronic, Irvine, CA, USA).
Table 1.
Baseline clinical characteristics.
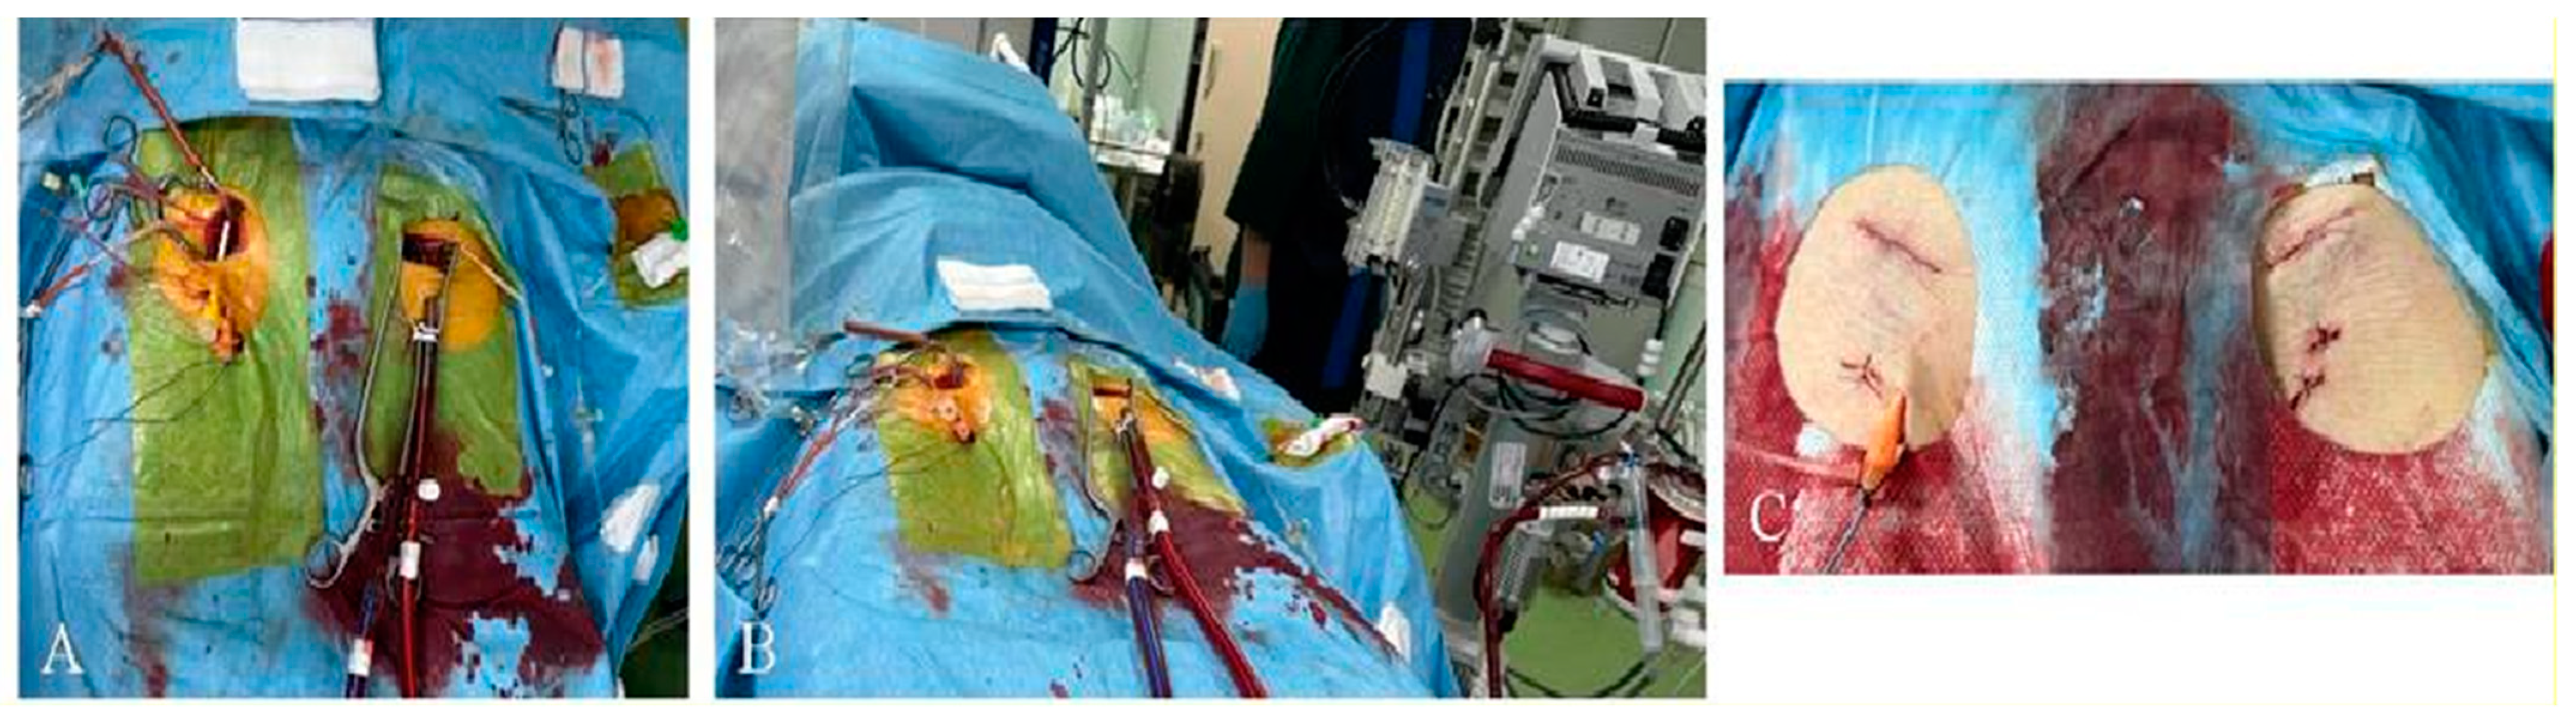
All TAVR operations and pV-A ECMO implantation (Stockert, Sorin Group Deutschland GMBH, München, Germany, and Deltasrtream MDC, Medos/Xenios, Xenios AG, Heilbronn, Germany) were performed via surgically assisted transfemoral approaches under monitored conscious sedation and local anaesthesia. The veno-arterial cannulation was performed via a mini cut-down open technique (Figure 2). Arterial and venous cannulae (Medtronic Bio-MedicusTM, Tijuana, Baja, California, Mexico) were selected according to the patient’s biometric parameters. Blood is drained from the right atrium and the inferior vena cava, oxygenated and decarboxylated in the ECMO device and returned to the iliac artery.
Figure 2.
Mini-cutdown open technique for V-AECMO and TAVR cannulation. (A,B) intraprocedural view of running V-A ECMO; (C) final view of accesses for ECMO and TAVR.
The pV-A ECMO was initiated in the operating theater prior to TAVR in all cases. The ECMO setting at the start of the procedure were: priming with 800 milliliters of balanced electrolyte isotonic solution (Sterofundin, B.BRAUN MELSUNGEN, AG, Germany). The initial pump speed was 1 L per minute. After vascular access is achieved, the circuit is connected to cannulae and flow is initiated at a low flow rate, increased incrementally to the target rate over a short time. Gas flow rates were set in relation to blood flow. The ECMO flow with a minimum of 1200 milliliters per minute and gas sweep rates were adjusted in each case to maintain target mean arterial pressure ≥ 70 mmHg and normocapnia, to maintain spontaneous breathing. During rapid pacing for balloon valvuloplasty, deployment and post-dilatation of the transcatheter heart valve, the pump was running stable speed.
3. Results
There were no pV-A ECMO, hemodynamic or TAVR implantation complications. Decannulation of the ECMO system was performed in 92.6% of cases at the end of the procedure in the hybrid-operating theatre. The mean duration of pV-A ECMO for procedure support was 51.4 ± 10.3 min. There were no ECMO-related vascular or bleeding complications (Table 2). There were no hospital mortality and morbidity in terms of bleeding, vascular complications, stroke, myocardial damage, renal insufficiency and thrombosis. Device success was achieved in all cases. Transprosthetic gradients during ECMO support were not measured due to a great risk of bias caused by mechanical circulatory support.
Table 2.
Prophylactic V-A ECMO characteristics and clinical course details.
4. Discussion
Despite advancements in technology, TAVR remains a complex procedure that may result in serious intraprocedural complications, which can occur in up to 7.6% of TAVR operations [2]. In many of these circumstances, V-A ECMO can bridge the patients to emergency repair of structural damages by open heart surgery.
The use of Mechanical Circulatory Support (MCS) to manage complications and to provide a hemodynamic backup will increase the indications for TAVR [3,4].
Peripheral V-A ECMO is the most appropriate, short-term MCS device to support high-risk TAVR procedures [1]. From the technical standpoint, peripheral V-A ECMO only requires the insertion of arterial and venous cannulae over guidewires already present in the femoral vessels. In the scientific literature, there is a lack of differentiation between TAVR and ECMO-related vascular access complications. Despite non-specified data, vascular complications and bleeding occurred in a relatively small cohort of ECMO patients, reaching 16% [1]. In our series, all TAVR operations and pV-AE CMO implantation were performed via surgically assisted transfemoral approaches using a mini-cutdown open technique. There were no ECMO-related vascular or bleeding complications as vascular management was realized ad oculus. In all cases, the tunneling (through counerapertur) technique for cannulae insertion was used (Figure 2). This provides additional stability for cannulae and safe wound closure with minimal risk in case the prolongation of ECMO is needed. In addition, we found this maneuver much safer to control bleeding and other vascular complications when expandable introducers sheathe are used by snaring intraprocedurally, and vascular suturing at the end of the procedure for the TAVR site. Forthcoming decannulation is eased by pre-explored femoral vessels.
Among other MCS devices employed for emergency and elective TAVR procedures, cardiopulmonary bypass (CPB) has been adopted [5,6]. CPB is a feasible option intraprocedurally, but inconvenient and impractical for prolonged support. Other short-term MCS devices, such as Impella and Tandem Heart, have significant technical limitations that are time-consuming and challenging in TAVR procedures, especially in emergency situations [7].
There are currently concerns about the anesthesia management during high-risk TAVR, with the two main strategies—conscious monitored sedation and general anesthesia. The most common scenario for high-risk TAVR is general anesthesia, which was found the preferred strategy since it may assure a more well regulated cardiac and respiratory support [8,9]. In our institution, we found a conscious monitored sedation strategy more rational in the case of prophylactic ECMO institution. This approach carries good clinical outcomes providing (1) hemodynamic stability during balloon pre/post-dilatation; (2) hemodynamic stability during procedures in patients with high central venous pressure, and/or pulmonary capillary wedge pressure, mean pulmonary artery pressure (>50 mmHg) and low cardiac index; (3) hemodynamic stability while left ventricular recovery from rapid pacing; (4) reduces if there is need at all in high vasopressor or inotropes requirements; (5) protects concomitant high-risk intervention (coronary, valvular); (6) makes no rush for intubation in case of ventricular fibrillation; (7) prevents artificial ventilation. Moreover, the shortening of the length of stay may reduce costs [1].
The outcome of pV-A ECMO cases is favorable and patients are weaned off of ECMO support after the relief of aortic stenosis during the operation or the day after. The emergency cases are transferred to the operating theatre for the correction of structural damage (coronary ostia obstruction, annular, or ventricular rupture, aortic dissection, valve migration, apical disruption after transapical cases), which can occur in up to 7.6% of TAVR procedures [2,10]. The post-surgery course would most probably depend on the severity of intraprocedural complications. Post-cardiotomy V-A ECMO in these patients should be considered as a bridge to recovery. Unfortunately, results in this cohort show a much lower survival rate-about 60%. Surgical trauma, cardioplegic heart arrest, inotropic support and mechanical ventilation are additional factors influencing survival V-A ECMO.
In our opinion, open heart surgery should be performed on the same Catheter-Lab table in order to minimize the time for surgical restoration and the risk of multiorgan failure. It makes it crucial for the TAVR team to be composed of all of the experienced individuals: the referring cardiologist, the interventional cardiologist, the cardiac surgeon and anesthesiologist, the perfusionist, the scrub, and/or catheter-lab nurses.
Limitations
The small number of patients and the retrospective nature of the analysis represent the major limitations of our study. It is clear that randomized trials are needed to address the feasibility and safety of pV-A ECMO for high-risk TAVR. Moreover, the influence of TAVR on late outcomes in patients with aortic stenosis at stage 3 and stage 4 of cardiac damage [11] warrants further investigation.
5. Conclusions
Prophylactic placement of awake peripheral V-A ECMO provides excellent temporary cardiocirculatory and pulmonary support during very high-risk TAVR procedures.
Author Contributions
Conceptualization, T.L.; methodology, A.M., S.A., L.F. and Z.N.; validation, Z.N.; formal analysis, T.L. and A.K. (Aigerim Kunakbayeva); investigation, A.M., S.A., R.K., A.K. (Aidyn Kuanyshbek), L.F. and A.S.; writing—original draft, T.L.; writing—review & editing, T.L. and Z.N. All authors have read and agreed to the published version of the manuscript.
Funding
This research is funded by the Science Committee of the Ministry of Education and Science of the Republic of Kazakhstan (Grants № BR10965200, № AP09258870).
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Local Bioethics Committee of the National Research Cardiac Surgery Center (№ 01-74/2021 from 6 October 2020).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The data presented in this study is available upon request from the corresponding author.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Raffa, G.M.; Kowalewski, M.; Meani, P.; Follis, F.; Martucci, G.; Arcadipane, A.; Pilato, M.; Maessen, J.; Lorusso, R. In-hospital outcomes after emergency or prophylactic veno-arterial extracorporeal membrane oxygenation during transcatheter aortic valve implantation: A comprehensive review of the literature. Perfusion 2019, 34, 354–363. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seiffert, M.; Conradi, L.; Baldus, S.; Schirmer, J.; Blankenberg, S.; Reichenspurner, H.; Diemert, P.; Treede, H. Severe intraprocedural complications after transcatheter aortic valve implantation: Calling for a heart team approach. Eur. J. Cardio-Thorac. Surg. 2013, 44, 478–484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Makdisi, G.; Makdisi, P.B.; Wang, I.W. New horizons of nonemergent use of extracorporeal membranous oxygenator support. Ann. Transl. Med. 2016, 4, 76. [Google Scholar] [PubMed]
- Singh, V.; Damluji, A.A.; Mendirichaga, R.; Alfonso, C.E.; Martinez, C.A.; Williams, D.; Heldman, A.W.; De Marchena, E.J.; O’Neill, W.W.; Cohen, M.G. Elective or emergency use of mechanical circulatory support devices during transcatheter aortic valve replacement. J. Interv. Cardiol. 2016, 29, 513–522. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roselli, E.E.; Idrees, J.; Mick, S.; Kapadia, S.; Tuzcu, M.; Svensson, L.G.; Lytle, B.W. Emergency use of cardiopulmonary bypass in complicated transcatheter aortic valve replacement: Importance of a heart team approach. J. Thorac. Cardiovasc. Surg. 2014, 148, 1413–1416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Drews, T.; Pasic, M.; Buz, S.; D’Ancona, G.; Mladenow, A.; Hetzer, R.; Unbehaun, A. Elective femoro-femoral cardiopulmonary bypass during transcatheter aortic valve implantation: A useful tool. J. Thorac. Cardiovasc. Surg. 2013, 145, 757–763. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meani, P.; Gelsomino, S.; Natour, E.; Johnson, D.M.; Rocca, H.P.B.L.; Pappalardo, F.; Bidar, E.; Makhoul, M.; Raffa, G.; Heuts, S.; et al. Modalities and effects of left ventricle unloading on extracorporeal life support: A review of the current literature. Eur. J. Heart Fail. 2017, 19, 84–91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lester, L.; Brady, M.B.; Brown, C.H., 4th. Sedation versus general anesthesia for TAVR: Where do we go from here? J. Cardiothorac. Vasc. Anesth. 2017, 31, 2055–2057. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Konigstein, M.; Ben-Shoshan, J.; Zahler, D.; Flint, N.; Margolis, G.; Granot, Y.; Aviram, G.; Halkin, A.; Keren, G.; Banai, S.; et al. Outcome of patients undergoing TAVR with and without the attendance of ananesthesiologist. Int. J. Cardiol. 2017, 241, 124–127. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tam, D.Y.; Jones, P.M.; Kiaii, B.; Diamantouros, P.; Teefy, P.; Bainbridge, D.; Cleland, A.; Fernandes, P.; Chu, M.W.A. Salvaging catastrophe in transcatheter aortic valve implantation: Rehearsal, preassigned roles, and emergency preparedness. Can. J. Anaesth. 2015, 62, 918–926. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Généreux, P.; Pibarot, P.; Redfors, B.; Mack, M.J.; Makkar, R.R.; Jaber, W.A.; Svensson, L.; Kapadia, S.; Tuzcu, M.; Thourani, V.; et al. Staging classification of aortic stenosis based on the extent of cardiac damage. Eur. Heart J. 2017, 38, 3351–3358. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).