


Abstract
This systematic review assessed the global epidemiology of metallo-β-lactamase (MBL)-producing Acinetobacter clinical isolates and the associated antimicrobial resistance. A total of 475 relevant articles from the Cochrane Library, Google Scholar, PubMed, Scopus, and Web of Science were identified and screened as potentially eligible articles. Data from 85 articles were extracted for the analysis. Most reports on MBL-producing Acinetobacter clinical isolates originated from Asia [68/85 (80%) studies] and Africa [14/85 (16.5%) studies]. There were also scarce reports from Europe and America. The blaVIM (in 31 studies), blaIMP (in 29 studies), and blaNDM (in 21 studies) genes were the most commonly identified genes. In 22 out of 28 (78.6%) studies with comparable data, the proportions of MBL-producing pathogens detected using phenotypic methods were numerically higher than those using genotypic methods. MBL-producing Acinetobacter isolates showed high resistance (up to 100%) to several antibiotic classes, including carbapenems, cephalosporins, fluoroquinolones, and monobactams. However, they showed low resistance to colistin [ranging from 0% (in six studies) to 14.3% (in one study)] and to tigecycline [0% (in three studies)]. No risk of bias assessment was conducted. The findings emphasize the global spread of MBL-producing Acinetobacter and the need for enhanced antimicrobial stewardship, infection control measures, and surveillance.
1. Introduction
Pathogens resistant to antimicrobial agents are increasing worldwide and pose a threat to public health because they cause significant mortality, morbidity, and increased healthcare costs [1]. Many of the most frequently encountered resistant isolates belong to the so-called ‘ESKAPE’ pathogens (Enterococcus faecium, Staphylococcus aureus, Klebsiella pneumoniae, Acinetobacter baumannii, Pseudomonas aeruginosa, and Enterobacterales), for which the treatment options are limited [2,3].
Among these, Acinetobacter baumannii infections are particularly associated with advanced antimicrobial resistance [4]. Such infections are usually healthcare associated, but may also be community acquired [5]. Moreover, patients with Acinetobacter baumannii infections experience high mortality [6], especially when caused by carbapenem-resistant strains [7].
The World Health Organization (WHO) has designated carbapenem-resistant Acinetobacter baumannii as a critical priority pathogen and has called for the development of new therapeutic options to treat these infections [8]. Furthermore, the resistance of Acinetobacter clinical isolates to carbapenems is increasing worldwide, driven by various mechanisms, including the production of β-lactamases [9].
Beta-lactamases inactivate β-lactam antibiotics by hydrolyzing the β-lactam ring. According to the Ambler classification, β-lactamases are divided into four molecular classes: A, B, C, and D [10,11]. Classes A, C, and D have an active serine site, whereas class B [also called metallo-β-lactamases (MBLs)] uses zinc as a cofactor [12,13]. Metal ion chelators like ethylene-diamine-tetra-acetic acid (EDTA) inhibit MBL activity [12], a property utilized in phenotypic tests to detect MBL production [14]. MBLs can hydrolyze almost all β-lactam antibiotics, including carbapenems, with the notable exception of monobactams [15,16].
Previous studies are limited in scope: some examined the regional prevalence of carbapenemase-producing Acinetobacter [17,18,19,20], while others focused specifically on Acinetobacter isolates carrying the blaNDM gene [21]. However, a gap remains in understanding the global epidemiology of MBL-producing Acinetobacter. The therapeutic options for such infections are limited, as these pathogens are often resistant to most antibiotics. Potential therapeutic options include carbapenems (imipenem and meropenem), polymyxins (colistin and polymyxin B), tigecycline, and new β-lactamase inhibitor combinations (sulbactam–durlobactam and aztreonam–avibactam) [22,23,24,25]. Also, there are antibiotics in the pipeline for treating patients with these infections that could potentially be used as alternatives to the available agents, but currently they are under development in clinical trials [26]. Thus, as it is useful to evaluate the global epidemiology of MBL-producing Acinetobacter, this systematic review aims to address the knowledge gap by assessing the data on this clinically important issue.
2. Methods
2.1. Objectives
The objective of this review was to assess the global epidemiology of MBL-producing Acinetobacter clinical isolates and their resistance profiles in regard to various antimicrobial agents.
2.2. Eligibility Criteria
We included all the research articles reporting on Acinetobacter clinical isolates, with no restrictions in terms of the language, publication date, journal, region, patient demographics (adult or pediatric), or setting (inpatient or outpatient). We excluded gray literature (e.g., conference abstracts and industry reports) and any studies analyzing fewer than 5 Acinetobacter isolates.
We included studies that detected MBLs using genotypic methods [polymerase chain reaction (PCR)] and/or phenotypic methods [combined disk test (CDT), double-disk synergy test (DDST), or E-test]. Both CDT and DDST methods use imipenem plus EDTA disks in different settings to test for MBL production, as EDTA inhibits the action of MBLs. Thus, imipenem can act against the growth of MBL-producing strains [27,28]. For the CDT, a zone of inhibition more than 7 mm around the EDTA–imipenem-containing disk is considered a positive result for the production of MBL [27,29]. For the DDST, inhibition between the imipenem and EDTA disks, placed at a 10 mm distance, is a positive result [28,29]. For the E-test, a strip containing imipenem and EDTA is used [30]. We extracted antimicrobial susceptibility data from the studies that used antibiotic diffusion or microdilution methods for antimicrobial susceptibility testing.
2.3. Search Strategy
We searched five databases on 5 February 2025 (the Cochrane Library, Google Scholar, PubMed, Scopus, and Web of Science), using specific search strings (see Supplementary Table S1). Additionally, we screened the reference lists of the included studies for any further relevant articles.
2.4. Selection of Articles
Two investigators (DSK and MZ) conducted the searches. In Google Scholar, only the first 1000 results were accessible, and no bulk export option is available; therefore, we screened the Google Scholar results by title/abstract manually, before deduplication. All the citations from the Cochrane Library, PubMed, Scopus, and Web of Science were exported into Zotero version 7.0.11 (citation management software). These, combined with the Google Scholar selections, were deduplicated using the SR Accelerator tool. Two reviewers (DSK and MZ) independently screened the articles first based on the title and/or abstract and then by reviewing the full text. Any disagreements were resolved by consensus, during scientific meetings with a senior author (MEF).
2.5. Data Extraction
Two investigators (DSK and MZ) independently extracted and tabulated the key data from each study, including first author and publication year; study location (continent and country); patient population characteristics (e.g., age group, inpatient vs. outpatient); hospital/department setting; specimen type from which Acinetobacter isolates were obtained; identified Acinetobacter species; and the MBL genes tested. The main text was translated, using a web software program, if the studies were in a language other than English. For each study, we evaluated the proportion of Acinetobacter isolates that were MBL producers, as determined by genotypic and/or phenotypic methods. The studies were grouped based on the continent and country where the isolates were detected. If multiple data points were provided in a study regarding the isolation of MBL-producing Acinetobacter isolates, they were all extracted and presented separately (e.g., per isolation period). We also noted the proportion of MBL-producing isolates that were non-susceptible to various antibiotics, when such antimicrobial susceptibility data were available.
2.6. Adherence to the PRISMA Guidelines
This systematic review complies with the most recent “Preferred Reporting Items for Systematic Reviews and Meta-Analyses” (PRISMA) guidelines, and any omission is explicitly reported in the discussion section of this study. The study research protocol was not registered in a database. The PRISMA checklists for the abstract and full-text review are provided in Supplementary Tables S2 and S3, respectively.
3. Results
Identification of Relevant Articles
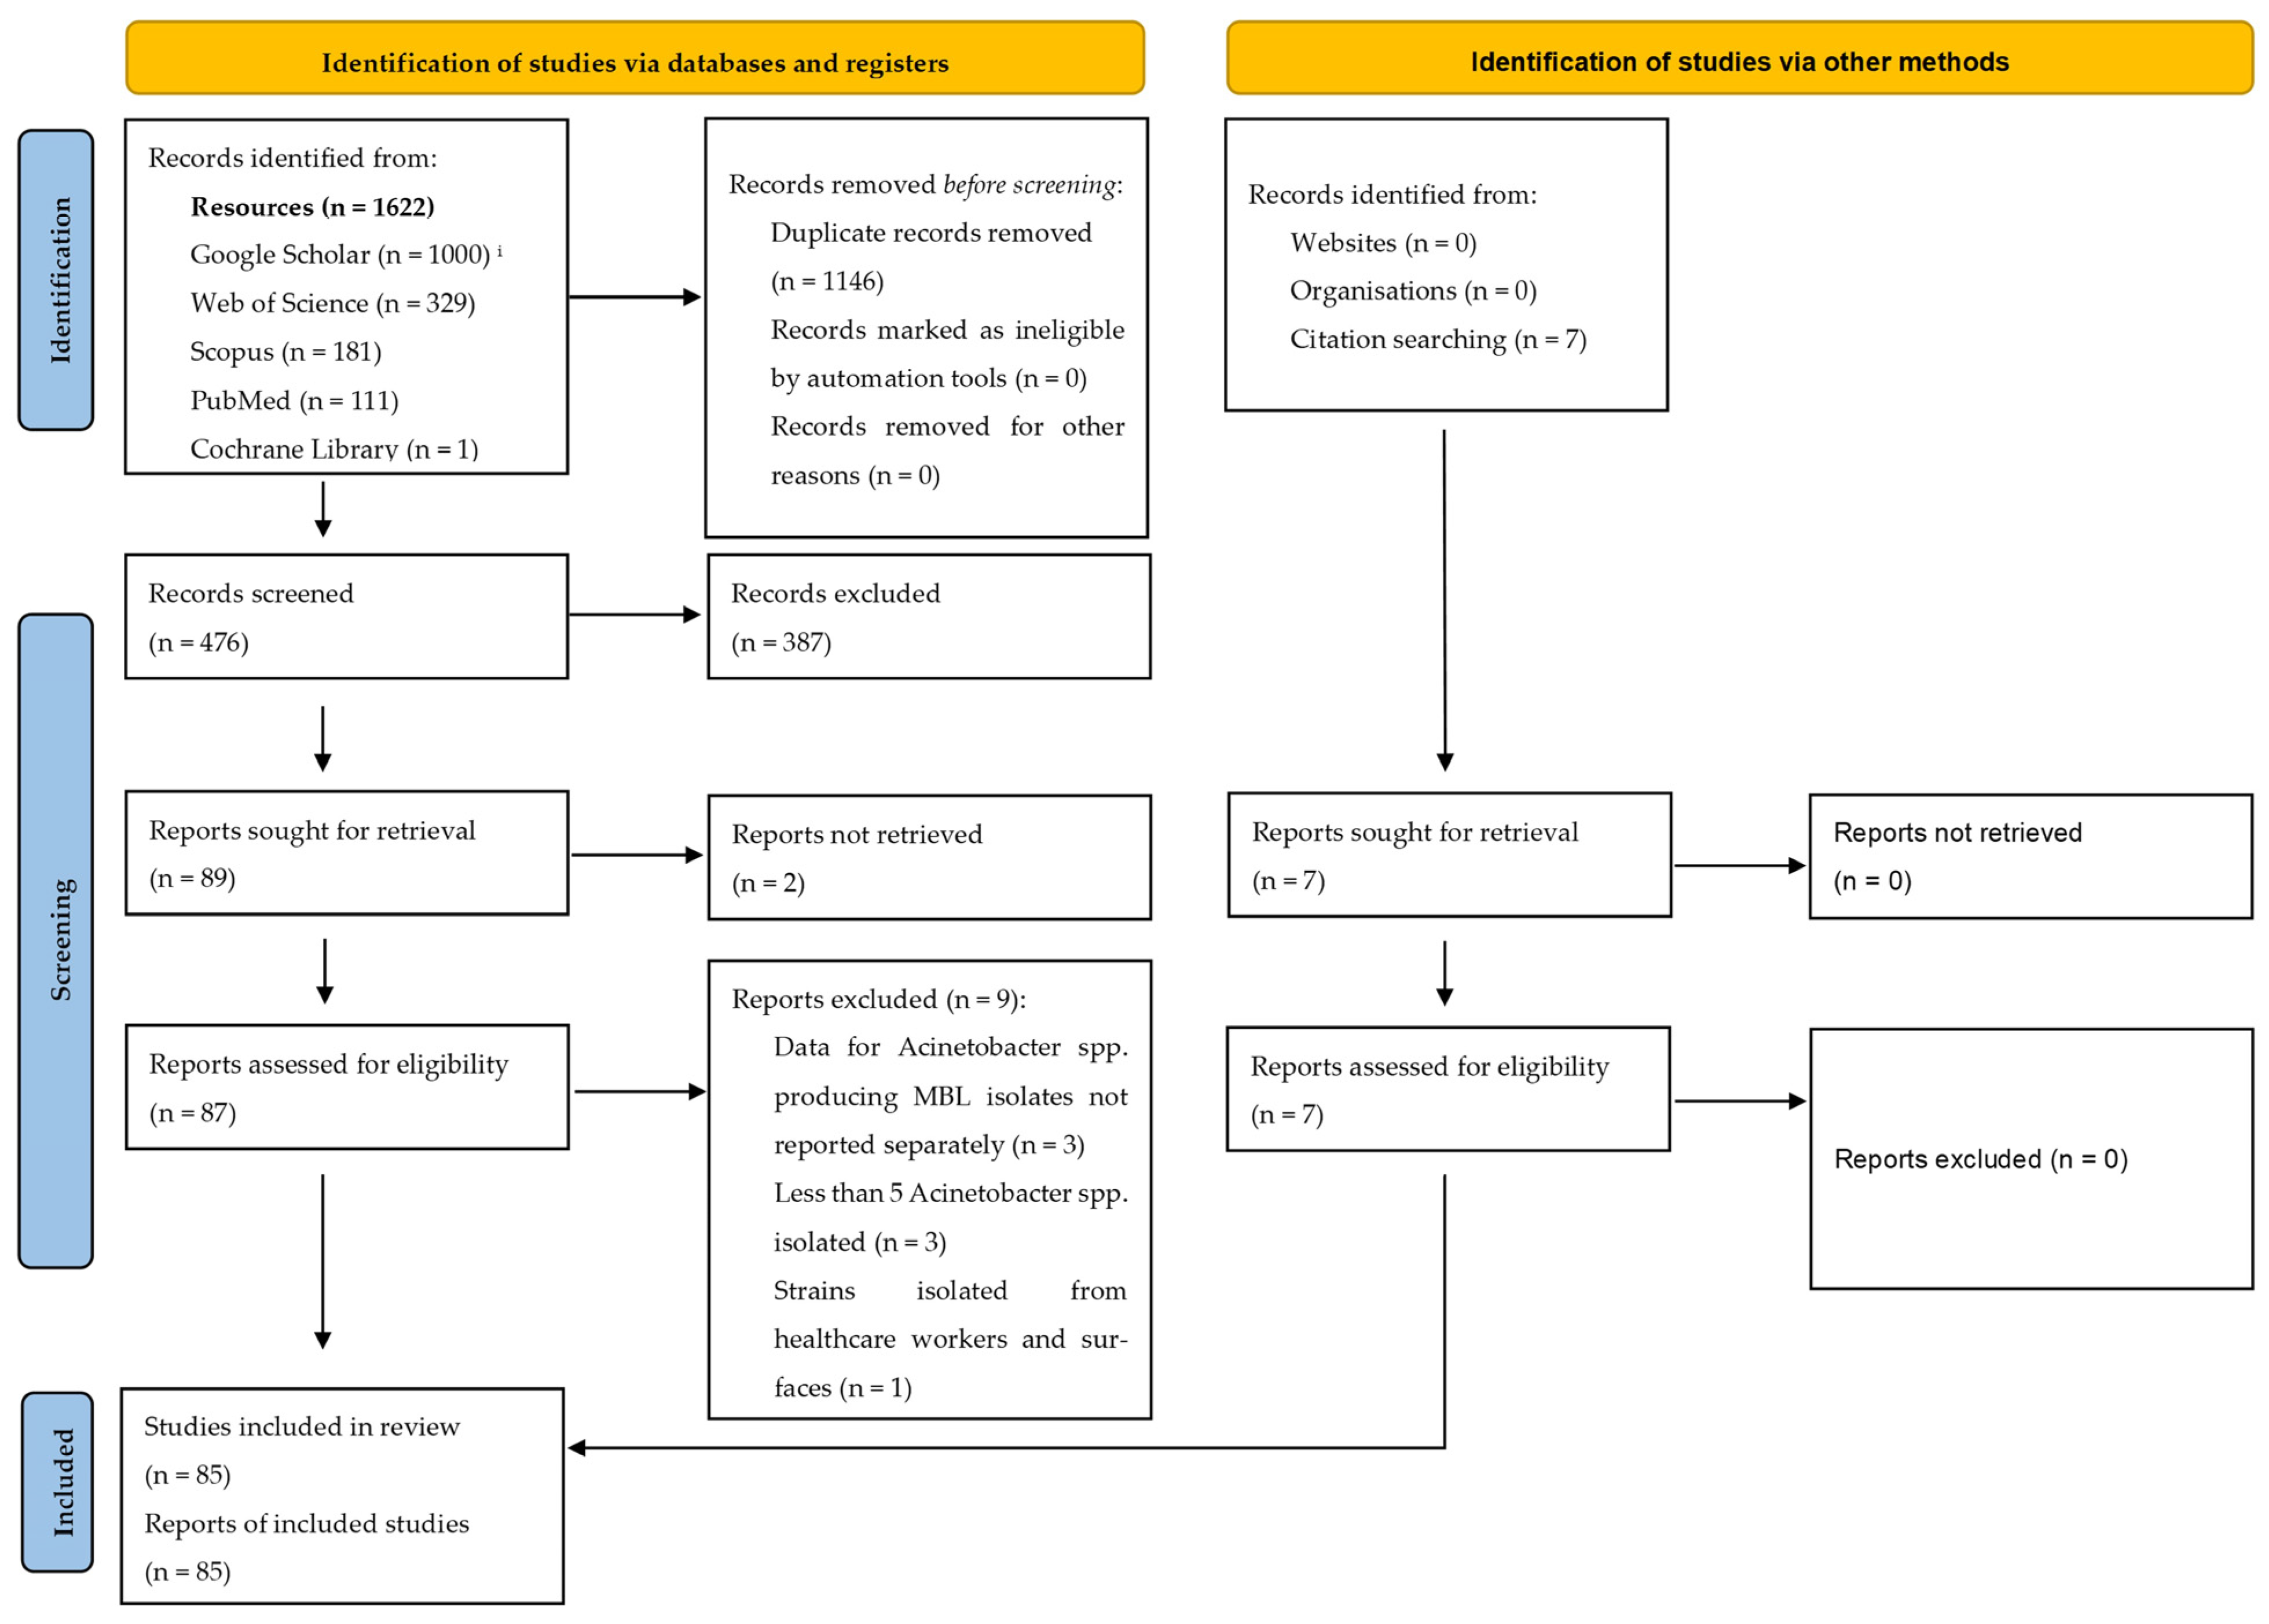
Figure 1 presents a PRISMA flow diagram on the identification, selection, and inclusion of articles included in this systematic review. In total, our searches yielded 73 articles from Google Scholar and 622 from the other sources. After removing duplicates, 475 articles remained for screening. Ultimately, 85 studies met the inclusion criteria and were included in our analysis, and nine articles were excluded after a full-text evaluation (Figure 1). Three studies did not present data specifically for MBL production in Acinetobacter isolates, three studies reported the isolation of less than five Acinetobacter pathogens, one study reported the isolation of pathogens from surfaces and healthcare workers, one study was a dissertation, and one study was a conference abstract. Sixty-eight of the included studies originated from Asia [31,32,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,57,58,59,60,61,62,63,64,65,66,67,68,69,70,71,72,73,74,75,76,77,78,79,80,81,82,83,84,85,86,87,88,89,90,91,92,93,94,95,96,97,98], fourteen from Africa [99,100,101,102,103,104,105,106,107,108,109,110,111,112], two from America [113,114], and one from Europe [115].
Figure 1.
“Preferred Reporting Items for Systematic Reviews and Meta-Analyses” (PRISMA) flow diagram for identification, screening, and inclusion of articles. i Even though 16,300 results were retrieved with the Google Scholar search, only the first 1000 results could be accessed. Source: Page MJ, et al. BMJ 2021;372:n71. doi: 10.1136/bmj.n71 [116]. This work is licensed under CC BY 4.0. To view a copy of this license, visit https://creativecommons.org/licenses/by/4.0/ (accessed on 6 February 2025).
Table 1 presents the proportions of MBL-producing Acinetobacter isolates identified using genotypic and phenotypic methods, sorted by continent and country. In summary, 68 studies reported clinical Acinetobacter strains isolated from patients in countries in Asia (26 in India, 14 in Iran, 9 in Nepal, 5 in Iraq, 5 in Pakistan, 2 in Japan, 1 in Bangladesh, China, Lebanon, Malaysia, Saudi Arabia, South Korea, Taiwan), 14 in Africa (7 in Egypt, 1 in Algeria, Ghana, Libya, Morocco, South Africa, Sudan, Uganda), 2 in America (1 in Canada and the USA, 1 in Colombia), and 1 in Europe (1 in Romania). Seventy-eight studies included clinical isolates from hospitalized patients, six from both hospitalized patients and outpatients, and only one from outpatients [76]. The isolates were obtained from a variety of clinical specimens, most frequently respiratory sources (e.g., sputum and other respiratory secretions) [in 64 of 76 (84.2%) studies with available relevant data], blood [in 56/76 (73.7%)], and urine [in 50/76 (65.8%)]. Wound swabs were the next most common [in 34/76 (44.7%)], followed by cerebrospinal fluid [in 18/76 (23.7%)], pleural fluid [in 9/76 (11.8%)], burn wound samples [in 3/76 (3.9%)], and other sources.
Table 1.
Proportion of phenotypic and genotypic detection of MBLs in various Acinetobacter species.
In the 85 included studies, the most commonly identified Acinetobacter species were Acinetobacter baumannii [in 63/85 (74.1%)], followed by Acinetobacter baumannii–calcoaceticus complex [in 6/85 (7.1%)], and Acinetobacter hemolyticus [in 5/85 (5.9%)]. Other Acinetobacter species were also reported in 12 studies. However, 18/85 (21.2%) studies did not specify the isolated Acinetobacter species.
Forty-seven of the 85 studies included in our analysis (55.3%) employed genotypic methods (PCR) to detect MBL genes. In total, blaVIM was tested in 31 studies, blaIMP in 29, blaNDM in 21, blaSPM in 7, blaGIM in 7, blaSIM in 5, and blaDIM in 1 study. In Africa, 10/13 (76.9%) studies tested for blaNDM, 6/13 (46.2%) for blaVIM, and 5/13 (38.5%) for blaIMP. However, in Asia, 23/31 (74.2%) studies tested for blaIMP, 22/31 (71%) for blaVIM, and 11/31 (35.5%) for blaNDM. In America, two studies tested for blaVIM, and 1/2 (50%) studies tested for blaNDM, blaVIM, and blaIMP. In Europe, the one relevant study tested for blaVIM. Only 8 of the 85 studies (9%) included in our analysis reported data on clones of Acinetobacter baumannii isolates.
Seventy of the 85 studies (82.4%) employed phenotypic tests (CDT, DDST, and/or E-test) for MBL detection. Notably, six studies used modified versions of these tests [52,77,79,80,109,117]. Thirty-two studies (37.6%) used both genotypic and phenotypic methods. In four of those thirty-two studies [55,59,79,112], the data were not directly comparable because the number of isolates tested using each method differed. Thus, 28 studies had directly comparable results between genotypic and phenotypic detection and were analyzed for concordance.
In 22 of the 28 studies (78.6%), phenotypic methods detected a higher proportion of MBL-producing Acinetobacter isolates than genotypic methods. Of those twenty-two studies, eight relied solely on the CDT for phenotypic testing [50,62,65,72,73,102,103,107], six used only the E-test [63,67,68,98,111,117], and three used only the DDST [53,57,64] method. One study used all the CDT, DDST, and E-test methods [100], and two studies used both CDT and E-test methods [51,61]. In one of the last studies, the E-test method had a lower proportion of phenotypic MBL-production detection [117/172 (68.0%)] than the genotypic method [139/172 (80.8%)] in contrast to the CDT method [144/172 (83.7%)] [51]. Also, one study used a modified CDT method, with an increase of more than 10 mm in the zone of inhibition for a positive result [80], and one used the EDTA-modified carbapenem inactivation method [117].
In 4/28 (14.3%) studies, the proportion of MBL-producing Acinetobacter detected was higher using genotypic than phenotypic methods. Among these four studies, two used only the DDST method [39,94], one used only the CDT method [101], and one used both CDT and DDST methods [69]. Finally, in 2/28 (7.1%) studies, the proportion of MBL-producing Acinetobacter detected was equal using the genotypic and phenotypic methods. One study used the CDT [31] and one used the DDST phenotypic method [99].
Table 2 presents data on the antimicrobial resistance of the studied clinical isolates. Among the 33 studies that reported antimicrobial susceptibility data for MBL-producing Acinetobacter, the resistance rates were as high as 100% in regard to most of the tested antibiotics, including carbapenems, cephalosporins, and fluoroquinolones. In five studies, MBL-producing pathogens showed resistance to monobactams too. Notably, in six of seven studies (85.7%) that evaluated colistin (six using antibiotic diffusion methods [34,36,55,66,71,84] and one using the agar dilution method [101]), no colistin resistance was detected among the MBL-producing isolates [34,36,55,66,71,84]. In the remaining study, colistin resistance was 14.3% (6 of 42 MBL-producing isolates) [101]. In addition, in all three studies that evaluated tigecycline, no tigecycline resistance was detected [34,44,87].
Table 2.
Proportion of the studied resistant MBL-producing Acinetobacter clinical isolates to various antimicrobial agents.
4. Discussion
The objective of this study was the assessment of the global epidemiology of MBL-producing Acinetobacter isolates and their resistance to various antimicrobial agents. Our main finding confirms that these isolates have now spread worldwide, with most reported cases coming from Asia and Africa. In most studies, MBL-producing Acinetobacter isolates were 100% resistant to most of the tested antibiotics, including all carbapenems. Interestingly, although MBLs do not hydrolyze monobactams, the studies that tested for aztreonam susceptibility showed high resistance to this agent. This finding implies that these isolates were co-producing other types of lactamases (such as extended-spectrum β-lactamases), thus making them resistant to aztreonam, a monobactam antibiotic.
Colistin was the only agent that retained activity against the majority of these isolates (as most studies reported 0% resistance to colistin). However, all six studies that reported 0% resistance to colistin used disk diffusion methods for antimicrobial susceptibility testing. According to the joint Clinical and Laboratory Standards Institute (CLSI)/European Committee on Antimicrobial Susceptibility Testing (EUCAST) guidelines on colistin susceptibility testing, broth and agar microdilution methods are recommended over diffusion methods [118]. Thus, colistin resistance could be underestimated in these studies, with more false-susceptible pathogens reported, and the 0% percentage of resistance to colistin could have been higher if microdilution methods had been used.
In most studies with comparable data (78.6%), MBL-producing Acinetobacter was more frequently detected using phenotypic methods, specifically the CDT, followed by the DDST and E-test methods. This finding indicates that the genes encoding MBLs in the isolates from these studies possibly differed from those included in the PCR assay. The fact that the CDT detected more MBL-producing isolates compared to the other phenotypic methods is in keeping with results from previous studies demonstrating that this method is more sensitive than the DDST or E-test in regard to identifying MBL-producing pathogens [119,120,121]. Moreover, in Africa, most studies tested for the presence of the blaNDM, whereas in Asia most studies tested for blaIMP and blaVIM, highlighting the different prevalence of MBL genes between these geographical regions. Only a small proportion of studies reported data on the clones of Acinetobacter baumannii isolates.
Data from the included studies were heterogeneous, as patients were in different settings (ICU, other clinical departments, or outpatients) and had various infections. Also, the sources of isolation varied from study to study. These limitations made the analyses and synthesis of the data in the subgroups challenging and, thus, only a descriptive evaluation was conducted.
Antimicrobial resistance (AMR) is a growing global threat in regard to the treatment of infectious diseases. In response to rising AMR, standardized definitions for multidrug-resistant (MDR), extensively drug-resistant (XDR), and pandrug-resistant (PDR) bacteria have been adopted [122]. Briefly, MDR organisms are non-susceptible to ≥1 agent in at least three antibiotic categories, XDR organisms are resistant to all but one or two available categories, and PDR organisms are resistant to all categories [122].
Gram-negative bacteria have emerged as the most problematic causes of MDR/XDR/PDR infections from a public health perspective. In particular, Acinetobacter baumannii, once dismissed as a harmless colonizer, is now understood to cause severe infections. Numerous studies have demonstrated that Acinetobacter baumannii infections lead to considerable morbidity, prolonged hospital stays, higher healthcare costs, and attributable mortality [6,123]. Today, the need for immediate interventions and targeted research initiatives related to Acinetobacter baumannii infections is more urgent than ever. There is an urgent need for immediate interventions and targeted research to address Acinetobacter baumannii infections. Developing new antimicrobials, implementing personalized therapeutic approaches, and strengthening infection prevention and control programs are all crucial strategies to stem this crisis.
The global spread of MDR, XDR, and PDR Acinetobacter baumannii infections, including those caused by MBL-producing isolates, is not solely a consequence of antibiotic misuse and overuse, due to a lack of adherence to antimicrobial stewardship policies. Multiple factors, including inadequate infection control in hospitals and transmission via contaminated medical devices, also drive the spread [124]. Additionally, the genetic flexibility of Acinetobacter baumannii enables it to acquire and maintain resistance genes, complicating efforts to eradicate the bacteria [125]. The increasing use of invasive medical procedures, exposure to disinfectants, and heavy metals, further promote the persistence of resistant strains. Particularly concerning is the spread of MBL-producing strains, facilitated by horizontal gene transfer, plasmids, and resistance islands [125].
Extensive antibiotic resistance dramatically limits treatment options, making the management of patients with MDR Acinetobacter infections extremely challenging. The remaining therapeutic choices, such as polymyxins, tigecycline, and sulbactam, come with significant drawbacks, including nephrotoxicity, gastrointestinal disturbances, and limited effectiveness in certain cases [124,126,127,128]. Also, there are limited data on the clinical use of new antibiotics (cefiderocol and sulbactam–durlobactam) that may have activity against MDR Acinetobacter isolates. Cefiderocol was demonstrated to have considerable antimicrobial activity against Gram-negative bacterial isolates, including Acinetobacter baumannii [129]. Although higher mortality was observed in patients who received cefiderocol in a randomized controlled clinical trial for Acinetobacter baumannii infection, subsequent observational studies suggested better clinical outcomes in patients with Acinetobacter baumannii infection treated with this new siderophore, cephalosporin [130,131,132]. In addition, a non-inferiority randomized controlled trial comparing sulbactam–durlobactam with colistin (both combined with imipenem–cilastatin) in patients with carbapenem-resistant Acinetobacter baumannii infection showed promising results for this new combination of two β-lactamase inhibitors [133,134]. Notably, sulbactam may have activity against Acinetobacter baumannii isolates and has been used in high doses for patients with such infections [135]. This underscores the complexity of managing such infections, highlighting the urgent need for stricter surveillance, enhanced infection control programs, and the development of new therapeutic strategies [126].
Our analysis has several limitations. First, most of the included studies were from single hospitals or limited geographic areas rather than broad multicenter surveillance efforts, which may limit the generalizability of their findings. Second, there was inconsistency in the phenotypic MBL detection methods used among the studies, some used modified tests with different zone diameter cut-offs, which complicates direct comparisons of the MBL rates. Third, our analysis did not include data on some of the newest antimicrobials (e.g., recently developed β-lactam/β-lactamase inhibitor combinations), since most of the included studies were published before those agents became available. In addition, we did not perform a formal quality assessment of the included studies, sensitivity analyses, statistical methods to assess the heterogeneity of the studies, and publication bias (e.g., a tendency to report outbreaks or unusually resistant cases), which might have influenced the literature available. These factors should be kept in mind when interpreting our results.
5. Conclusions
The assessed data show that MBL-producing Acinetobacter strains that cause infections have spread globally. These isolates are associated with advanced antimicrobial resistance and pose a critical therapeutic challenge, with important consequences for global public health. These findings underscore the urgent need for a multifaceted approach, including enhanced antimicrobial stewardship, strengthened infection control measures, and sustained global surveillance, to mitigate the spread of MBL-producing Acinetobacter isolates.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/pathogens14060557/s1, Table S1: Search strings for each resource; Table S2: “Preferred Reporting Items for Systematic Reviews and Meta-Analyses” (PRISMA) checklist for the abstract; Table S3: “Preferred Reporting Items for Systematic Reviews and Meta-Analyses” (PRISMA) checklist for the full-text review.
Author Contributions
M.E.F. had the idea for the article. All authors contributed to the methodology used in the article. D.S.K. and M.Z. conducted the literature search, data extraction, and tabulation. M.E.F., D.S.K. and M.Z. contributed to the first version of the manuscript. C.F. and G.S.T. revised the manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The data used in the conduction of this study are available upon request.
Conflicts of Interest
The authors declare that there are no conflicts of interest.
Abbreviations
| AMR | Antimicrobial resistance |
| CDT | Combined disk test |
| CLSI | Clinical and Laboratory Standards Institute |
| DDST | Double-disk synergy test |
| EDTA | Ethylene-diamine-tetra-acetic acid |
| EUCAST | European Committee on Antimicrobial Susceptibility Testing |
| MBL | Metallo-β-lactamase |
| MDR | Multidrug resistant |
| PCR | Polymerase chain reaction |
| PDR | Pandrug resistant |
| PRISMA | Preferred Reporting Items for Systematic Reviews and Meta-Analyses |
| WHO | World Health Organization |
| XDR | Extensively drug resistant |
References
- Oliveira, M.; Antunes, W.; Mota, S.; Madureira-Carvalho, Á.; Dinis-Oliveira, R.J.; Dias da Silva, D. An Overview of the Recent Advances in Antimicrobial Resistance. Microorganisms 2024, 12, 1920. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salam, M.A.; Al-Amin, M.Y.; Salam, M.T.; Pawar, J.S.; Akhter, N.; Rabaan, A.A.; Alqumber, M.A.A. Antimicrobial Resistance: A Growing Serious Threat for Global Public Health. Healthcare 2023, 11, 1946. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Miller, W.R.; Arias, C.A. ESKAPE pathogens: Antimicrobial resistance, epidemiology, clinical impact and therapeutics. Nat. Rev. Microbiol. 2024, 22, 598–616. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- De Oliveira, D.M.P.; Forde, B.M.; Kidd, T.J.; Harris, P.N.A.; Schembri, M.A.; Beatson, S.A.; Paterson, D.L.; Walker, M.J. Antimicrobial Resistance in ESKAPE Pathogens. Clin. Microbiol. Rev. 2020, 33, e00181-19. [Google Scholar] [CrossRef] [Scilit]
- Falagas, M.E.; Karveli, E.A.; Kelesidis, I.; Kelesidis, T. Community-acquired Acinetobacter infections. Eur. J. Clin. Microbiol. Infect. Dis. 2007, 26, 857–868. [Google Scholar] [CrossRef] [Scilit]
- Falagas, M.E.; Rafailidis, P.I. Attributable mortality of Acinetobacter baumannii: No longer a controversial issue. Crit. Care Lond. Engl. 2007, 11, 134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lemos, E.V.; de la Hoz, F.P.; Einarson, T.R.; McGhan, W.F.; Quevedo, E.; Castañeda, C.; Kawai, K. Carbapenem resistance and mortality in patients with Acinetobacter baumannii infection: Systematic review and meta-analysis. Clin. Microbiol. Infect. Infect. Dis. 2014, 20, 416–423. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. WHO Bacterial Priority Pathogens List, 2024: Bacterial Pathogens of Public Health Importance, to Guide Research, Development and Strategies to Prevent and Control Antimicrobial Resistance; World Health Organization: Geneva, Switzerland, 2024; Available online: https://iris.who.int/handle/10665/376776 (accessed on 6 February 2025).
- Wong, D.; Nielsen, T.B.; Bonomo, R.A.; Pantapalangkoor, P.; Luna, B.; Spellberg, B. Clinical and Pathophysiological Overview of Acinetobacter Infections: A Century of Challenges. Clin. Microbiol. Rev. 2017, 30, 409–447. [Google Scholar] [CrossRef] [Scilit]
- Ambler, R.P.; Baddiley, J.; Abraham, E.P. The structure of β-lactamases. Philos. Trans. R. Soc. Lond. B Biol. Sci. 1997, 289, 321–331. [Google Scholar] [CrossRef] [Scilit]
- Bush, K. Past and Present Perspectives on β-Lactamases. Antimicrob. Agents Chemother. 2018, 62, e01076-18. [Google Scholar] [CrossRef] [Scilit]
- Nagshetty, K.; Shilpa, B.M.; Patil, S.A.; Shivannavar, C.T.; Manjula, N.G. An Overview of Extended Spectrum Beta Lactamases and Metallo Beta Lactamases. Adv. Microbiol. 2021, 11, 37–62. [Google Scholar] [CrossRef]
- Samaha-Kfoury, J.N.; Araj, G.F. Recent developments in β lactamases and extended spectrum β lactamases. BMJ 2003, 327, 1209–1213. [Google Scholar] [CrossRef] [Scilit]
- Franklin, C.; Liolios, L.; Peleg, A.Y. Phenotypic Detection of Carbapenem-Susceptible Metallo-β-Lactamase-Producing Gram-Negative Bacilli in the Clinical Laboratory. J. Clin. Microbiol. 2006, 44, 3139–3144. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bebrone, C. Metallo-beta-lactamases (classification, activity, genetic organization, structure, zinc coordination) and their superfamily. Biochem. Pharmacol. 2007, 74, 1686–1701. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palzkill, T. Metallo-β-lactamase structure and function. Ann. N. Y. Acad. Sci. 2013, 1277, 91–104. [Google Scholar] [CrossRef] [Scilit]
- Yu, H.; Ezpeleta-Lobato, G.; Han, X.; Carmona-Cartaya, Y.; Quiñones-Pérez, D. Carbapenamase-Producing Acinetobacter baumannii in China, Latin America and the Caribbean. MEDICC Rev. 2022, 24, 59–69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kindu, M.; Derseh, L.; Gelaw, B.; Moges, F. Carbapenemase-Producing Non-Glucose-Fermenting Gram-Negative Bacilli in Africa, Pseudomonas aeruginosa and Acinetobacter baumannii: A Systematic Review and Meta-Analysis. Int. J. Microbiol. 2020, 2020, 9461901. [Google Scholar] [CrossRef] [Scilit]
- Hsu, L.-Y.; Apisarnthanarak, A.; Khan, E.; Suwantarat, N.; Ghafur, A.; Tambyah, P.A. Carbapenem-Resistant Acinetobacter baumannii and Enterobacteriaceae in South and Southeast Asia. Clin. Microbiol. Rev. 2017, 30, 1–22. [Google Scholar] [CrossRef] [Scilit]
- Djahmi, N.; Dunyach-Remy, C.; Pantel, A.; Dekhil, M.; Sotto, A.; Lavigne, J.-P. Epidemiology of carbapenemase-producing Enterobacteriaceae and Acinetobacter baumannii in Mediterranean countries. BioMed Res. Int. 2014, 2014, 305784. [Google Scholar] [CrossRef] [Scilit]
- Hajikhani, B.; Sameni, F.; Ghazanfari, K.; Abdolali, B.; Yazdanparast, A.; Asarehzadegan Dezfuli, A.; Nasiri, M.J.; Goudarzi, M.; Dadashi, M. Prevalence of blaNDM-producing Acinetobacter baumannii strains isolated from clinical samples around the world; a systematic review. Gene Rep. 2023, 30, 101728. [Google Scholar] [CrossRef] [Scilit]
- Vardakas, K.Z.; Mavroudis, A.D.; Georgiou, M.; Falagas, M.E. Intravenous colistin combination antimicrobial treatment vs. monotherapy: A systematic review and meta-analysis. Int. J. Antimicrob. Agents 2018, 51, 535–547. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kwa, A.L.; Falagas, M.E.; Michalopoulos, A.; Tam, V.H. Benefits of aerosolized colistin for ventilator-associated pneumonia: Absence of proof versus proof of absence? Clin. Infect. Dis. Off. Publ. Infect. Dis. Soc. Am. 2011, 52, 1278–1279; author reply 1279–1280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Falagas, M.E.; Kyriakidou, M.; Voulgaris, G.L.; Vokos, F.; Politi, S.; Kechagias, K.S. Clinical use of intravenous polymyxin B for the treatment of patients with multidrug-resistant Gram-negative bacterial infections: An evaluation of the current evidence. J. Glob. Antimicrob. Resist. 2021, 24, 342–359. [Google Scholar] [CrossRef] [Scilit]
- Falagas, M.E.; Vardakas, K.Z.; Tsiveriotis, K.P.; Triarides, N.A.; Tansarli, G.S. Effectiveness and safety of high-dose tigecycline-containing regimens for the treatment of severe bacterial infections. Int. J. Antimicrob. Agents 2014, 44, 1–7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Katsarou, A.; Stathopoulos, P.; Tzvetanova, I.D.; Asimotou, C.-M.; Falagas, M.E. β-Lactam/β-Lactamase Inhibitor Combination Antibiotics Under Development. Pathogens 2025, 14, 168. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yong, D.; Lee, K.; Yum, J.H.; Shin, H.B.; Rossolini, G.M.; Chong, Y. Imipenem-EDTA Disk Method for Differentiation of Metallo-β-Lactamase-Producing Clinical Isolates of Pseudomonas spp. and Acinetobacter spp. J. Clin. Microbiol. 2002, 40, 3798–3801. [Google Scholar] [CrossRef] [Scilit]
- Lee, K.; Chong, Y.; Shin, H.B.; Kim, Y.A.; Yong, D.; Yum, J.H. Modified Hodge and EDTA-disk synergy tests to screen metallo-β-lactamase-producing strains of Pseudomonas and Acinetobactet species. Clin. Microbiol. Infect. 2001, 7, 88–91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shivaprasad, A.; Antony, B.; Shenoy, P. Comparative Evaluation of Four Phenotypic Tests for Detection of Metallo-β-Lactamase and Carbapenemase Production in Acinetobacter baumannii. J. Clin. Diagn. Res. JCDR 2014, 8, DC05–DC08. [Google Scholar] [CrossRef] [Scilit]
- Behera, B.; Mathur, P.; Das, A.; Kapil, A.; Sharma, V. An evaluation of four different phenotypic techniques for detection of metallo-beta-lactamase producing Pseudomonas aeruginosa. Indian J. Med. Microbiol. 2008, 26, 233–237. [Google Scholar] [CrossRef] [Scilit]
- Rakhi, N.N.; Alam, A.S.M.R.U.; Sultana, M.; Rahaman, M.M.; Hossain, M.A. Diversity of carbapenemases in clinical isolates: The emergence of blaVIM-5 in Bangladesh. J. Infect. Chemother. 2019, 25, 444–451. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.J.; Pan, C.Z.; Zhao, Z.W.; Zhao, Z.X.; Chen, H.L.; Lu, W.B. Effects of a combination of amlodipine and imipenem on 42 clinical isolates of Acinetobacter baumannii obtained from a teaching hospital in Guangzhou, China. BMC Infect. Dis. 2013, 13, 548. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ahir, H.R.; Patel, P.H.; Berry, R.A.; Parmar, R.; Soni, S.T.; Shah, P.K.; Vegad, M.M.; Patil, S. Prevalence of metallo-β-lactamases producing Pseudomonas and Acinetobacter species in tertiary care teaching hospital, Gujarat. Int. J. Microbiol. Res. 2012, 4, 322–325. [Google Scholar] [CrossRef] [Scilit]
- Archana Rao, K.; Aradita, C.; Lakshminarayana, S. Detection of metallo-beta-lactamase (MBL) producing Pseudomonas aeruginosa and Acinetobacter spp. from a Tertiary Care Hospital. J. Res. Appl. Basic Med Sci. 2024, 10, 72–79. [Google Scholar] [CrossRef] [Scilit]
- Banerjee Molay, C.B.L. Prevalence of ESBL and MBL in Acinetobacter Species Isolated from Clinical Samples in Tertiary Care Hospital. Int. J. Sci. Res. IJSR 2015, 4, 1183–1186. [Google Scholar]
- Binnani, A.; Bishnoi, B.R.; Meena, S.; Singh, D. Study of Prevalence and Antimicrobial Susceptibility Pattern of Matello-Beta-Lactamase Producing Acinetobacter spp. Isolated at a Tertiary Care Institute in North West Region of Rajasthan. Int. J. Curr. Microbiol. Appl. Sci. 2018, 7, 2521–2526. [Google Scholar] [CrossRef] [Scilit]
- De, A.S.; Kumar, S.H.; Baveja, S.M. Prevalence of metallo-β-lactamase producing Pseudomonas aeruginosa and Acinetobacter species in intensive care areas in a tertiary care hospital. Indian J. Crit. Care Med. Peer-Rev. Off. Publ. Indian Soc. Crit. Care Med. 2010, 14, 217–219. [Google Scholar] [CrossRef] [Scilit]
- Gautam, D.; Dolma, K.G.; Khandelwal, B.; Goyal, R.K.; Mitsuwan, W.; Pereira, M.d.L.G.; Klangbud, W.K.; Gupta, M.; Wilairatana, P.; Siyadatpanah, A.; et al. Acinetobacter baumannii in suspected bacterial infections: Association between multidrug resistance, virulence genes, & biofilm production. Indian J. Med. Res. 2023, 158, 439. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Girija, S.A.; Jayaseelan, V.P.; Arumugam, P. Prevalence of VIM- and GIM-producing Acinetobacter baumannii from patients with severe urinary tract infection. Acta Microbiol. Immunol. Hung. 2018, 65, 539–550. [Google Scholar] [CrossRef] [Scilit]
- Goel, N.; Punia, P.; Chaudhary, U. Prevalence of ESBL, MBL and Amp C producing XDR Acinetobacter isolates from lower respiratory tract specimens. Int. J. Contemp. Med. Res. 2017, 4, 2091–2095. [Google Scholar]
- Hodiwala, A.; Dhoke, R.; Urhekar, A. Incidence of metallo-betalactamase producing pseudomonas, acinetobacter & enterobacterial isolates in hospitalised patients. Int. J. Pharamcy Biol. Sci. 2013, 3, 79–83. [Google Scholar]
- Jena, J.; Sahoo, R.K.; Subudhi, E.; Debata, N. Prevalence of ESBL, MBL and Ampc-b-lactamases producing multidrug resistance gram negative bacteria in a tertiary care hospital. J. Pure Appl. Microbiol. 2014, 8, 4099–4105. [Google Scholar]
- Jethwa, D.K.; Vegad, M. Phenotypic Detection & Prevalence of Metallo-β-lactamases in Acinetobacter spp. in Clinical Isolates at Tertiary Care Hospital. Med. Sci. 2013, 2, 270–271. [Google Scholar]
- John, S.; Balagurunathan, R. Metallo beta lactamase producing Pseudomonas aeruginosa and Acinetobacter baumannii. Indian J. Med. Microbiol. 2011, 29, 302–304. [Google Scholar] [CrossRef] [Scilit]
- Kaur, A.; Gupta, V.; Chhina, D. Prevalence of metalo- β-lactamase-producing (MBL) Acinetobacter species in a tertiary care hospital. Iran. J. Microbiol. 2014, 6, 22–25. [Google Scholar] [PubMed]
- Kaur, A.; Singh, S. Prevalence of Extended Spectrum Betalactamase (ESBL) and Metallobetalactamase (MBL) Producing Pseudomonas aeruginosa and Acinetobacter baumannii Isolated from Various Clinical Samples. J. Pathog. 2018, 2018, 6845985. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, E.; Usha, K.; Ramana, B.; Chaudhury, A.; GOPAL, D. Prevalence of various β-lactamase (ESBL, AmpC and MBL) producing multidrug-resistant clinical isolates of Acinetobacter spp. in a tertiary care hospital. Asian J. Pharm. Clin. Res. 2013, 6, 28–31. [Google Scholar]
- Pandya, Y.; Singh, S.; Badodariya, D.; Shethwala, N. Metallo-β-Lactamase Producing Clinical Isolates Of Acinetobacter Baumannii And Pseudomonas Aeruginosa In A Teaching Hospital Of Rural Gujarat-India.: Metallo-β-Lactamase Producing Clinical Isolates Of Acinetobacter Baumannii And Pseudomonas Aeruginosa. Natl. J. Integr. Res. Med. 2016, 7, 29–33. [Google Scholar]
- Patil, H.V.; Mohite, S.T.; Patil, V.C. Metallo-beta-lactamase-producing multidrug-resistant acinetobacter isolates in patients with ventilator-associated pneumonia. J. Nat. Sci. Biol. Med. 2021, 12, 64. [Google Scholar] [CrossRef] [Scilit]
- Rynga, D.; Shariff, M.; Deb, M. Phenotypic and molecular characterization of clinical isolates of Acinetobacter baumannii isolated from Delhi, India. Ann. Clin. Microbiol. Antimicrob. 2015, 14, 40. [Google Scholar] [CrossRef] [Scilit]
- Saikia, S.; Gogoi, I.; Oloo, A.; Sharma, M.; Puzari, M.; Chetia, P. Co-production of metallo-β-lactamase and OXA-type β-lactamases in carbapenem-resistant Acinetobacter baumannii clinical isolates in North East India. World J. Microbiol. Biotechnol. 2024, 40, 167. [Google Scholar] [CrossRef] [Scilit]
- Singla, P.; Sikka, R.; Deep, A.; Chaudhary, U. Phenotypic detection and prevalence of metallo β-lactamases (MBLs) in carbapenem resistant isolates of acinetobacter species at a tertiary care hospital in north India. Int. J. Pharm. Med. Bio Sci. 2013, 2, 85–91. [Google Scholar]
- Sinha, N.; Agarwal, J.; Srivastava, S.; Singh, M. Analysis of carbapenem-resistant Acinetobacter from a tertiary care setting in North India. Indian J. Med. Microbiol. 2013, 31, 60–63. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sugumaran, S.; Devi, S.U. Prevalence of Metallo-Beta-Lactamase Producers among Non-Fermenting Gram Negative Bacilli. IOSR J. Dent. Med. Sci. 2019, 18, 32–41. [Google Scholar] [CrossRef]
- Thakar, V.H.; Chakraborthy, A.; Modak, M.; Krunal, L. Detection of Metallo-β-lactamase production amongst Acinetobacter species from a tertiary care hospital. J. Acad. Clin. Microbiol. 2021, 23, 63–68. [Google Scholar] [CrossRef] [Scilit]
- Tripathi, P.; Gajbhiye, S. Prevalence of multidrug resistance, ESBL and MBL production in Acinetobacter spp. Int. J. Recent. Trends Sci. Technol. 2013, 6, 139–143. [Google Scholar]
- Uma Karthika, R.; Srinivasa Rao, R.; Sahoo, S.; Shashikala, P.; Kanungo, R.; Jayachandran, S.; Prashanth, K. Phenotypic and genotypic assays for detecting the prevalence of metallo-beta-lactamases in clinical isolates of Acinetobacter baumannii from a South Indian tertiary care hospital. J. Med. Microbiol. 2009, 58, 430–435. [Google Scholar] [CrossRef] [Scilit]
- Vamsi, K.S.; Moorthy, S.R.; Murali, T.; Hemiliamma, M.; Reddy, Y.; Reddy, B.; Kumar, J.S. Phenotypic Methods for the Detection of Metallo-Beta-Lactamase Production by Gram-negative Bacterial Isolates from Hospitalized Patients in A Tertiary Care Hospital in India. J. Pure Appl. Microbiol. 2021, 15, 2019–2026. [Google Scholar] [CrossRef] [Scilit]
- Aghamiri, S.; Amirmozafari, N.; Fallah Mehrabadi, J.; Fouladtan, B.; Hanafi Abdar, M. Antibiotic resistance patterns and a survey of metallo-β-lactamase genes including bla-IMP and bla-VIM types in Acinetobacter baumannii isolated from hospital patients in Tehran. Chemotherapy 2016, 61, 275–280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jahantigh, M.; Javadi, R.; Bameri, Z.; Dehvari, A. Evaluation of Antibiotic Susceptibility, Carbapenemase and Metallobetalactamase-producing Strains of Acinetobacter baumannii Isolated from Hospitalized Patients in Zahedan During 2019–2022. Int. J. Infect. 2024, 10, e143968. [Google Scholar] [CrossRef] [Scilit]
- Khaledi, M.; Shahini Shams Abadi, M.; Validi, M.; Zamanzad, B.; Vafapour, R.; Gholipour, A. Phenotypic and genotypic detection of metallo-β-lactamases in A. baumanii isolates obtained from clinical samples in Shahrekord, southwest Iran. BMC Res. Notes 2019, 12, 597. [Google Scholar] [CrossRef] [Scilit]
- Maspi, H.; Mahmoodzadeh Hosseini, H.; Amin, M.; Imani Fooladi, A.A. High prevalence of extensively drug-resistant and metallo beta-lactamase-producing clinical Acinetobacter baumannii in Iran. Microb. Pathog. 2016, 98, 155–159. [Google Scholar] [CrossRef] [Scilit]
- Moghadam, M.; Motamedifar, M.; Sarvari, J.; Ebrahim-Saraie, H.S.; Same, M.M.; Moghadam, F. Emergence of multidrug resistance and metallo-beta-lactamase producing Acinetobacter baumannii isolated from patients in Shiraz, Iran. Ann. Med. Health Sci. Res. 2016, 6, 162–167. [Google Scholar] [PubMed]
- Moulana, Z.; Babazadeh, A.; Eslamdost, Z.; Shokri, M.; Ebrahimpour, S. Phenotypic and genotypic detection of metallo-beta-lactamases in Carbapenem resistant Acinetobacter baumannii. Casp. J. Intern. Med. 2020, 11, 171–176. [Google Scholar] [CrossRef] [Scilit]
- Noori, M.; Karimi, A.; Fallah, F.; Hashemi, A.; Alimehr, S.; Goudarzi, H.; Aghamohammad, S. High Prevalence of Metallo-beta-lactamase Producing Acinetobacter. Arch. Pediatr. 2014, 2, e15439. [Google Scholar]
- Owlia, P.; Azimi, L.; Gholami, A.; Asghari, B.; Lari, A.R. ESBL- and MBL-mediated resistance in Acinetobacter baumannii: A global threat to burn patients. Infez. Med. 2012, 20, 182–187. [Google Scholar] [PubMed]
- Peymani, A.; Nahaei, M.-R.; Farajnia, S.; Hasani, A.; Mirsalehian, A.; Sohrabi, N.; Abbasi, L. High prevalence of metallo-beta-lactamase-producing acinetobacter baumannii in a teaching hospital in Tabriz, Iran. Jpn. J. Infect. Dis. 2011, 64, 69–71. [Google Scholar] [CrossRef] [Scilit]
- Ranjbar, R.; Farahani, A. Study of genetic diversity, biofilm formation, and detection of Carbapenemase, MBL, ESBL, and tetracycline resistance genes in multidrug-resistant Acinetobacter baumannii isolated from burn wound infections in Iran. Antimicrob. Resist. Infect. Control 2019, 8, 172. [Google Scholar] [CrossRef] [Scilit]
- Rezaei, A.; Fazeli, H.; Halaji, M.; Moghadampour, M.; Faghri, J. Prevalence of metallo-beta-lactamase producing Acinetobacter baumannii isolated from intensive care unit in tertiary care hospitals. Ann. Ig. Med. Prev. E Comunita 2018, 30, 330–336. [Google Scholar] [CrossRef] [Scilit]
- Safari, M.; Saidijam, M.; Bahador, A.; Jafari, R.; Alikhani, M.Y. High prevalence of multidrug resistance and metallo-beta-lactamase (MbetaL) producing Acinetobacter baumannii isolated from patients in ICU wards, Hamadan, Iran. J. Res. Health Sci. 2013, 3, 162–167. [Google Scholar]
- Soltani, B.; Heidari, H.; Ebrahim-Saraie, H.S.; Hadi, N.; Mardaneh, J.; Motamedifar, M. Molecular characteristics of multiple and extensive drug-resistant Acinetobacter baumannii isolates obtained from hospitalized patients in Southwestern Iran. Infez. Med. Riv. Period. Eziologia Epidemiol. Diagn. Clin. E Ter. Patol. Infett. 2018, 26, 67–76. [Google Scholar]
- Vala, M.H.; Hallajzadeh, M.; Hashemi, A.; Goudarzi, H.; Tarhani, M.; Tabrizi, M.S.; Bazmi, F. Detection of Ambler class A, B and D ß-lactamases among Pseudomonas aeruginosa and Acinetobacter baumannii clinical isolates from burn patients. Ann. Burns Fire Disasters 2014, 27, 8. [Google Scholar]
- Al Marjani, M.; Al-Ammar, M.; Kadhem, E. Occurrence of ESBL and MBL genes in Pseudomonas aeruginosa and Acinetobacter baumannii isolated from Baghdad, Iraq. Int. J. Curr. Res. 2013, 5, 2482–2486. [Google Scholar]
- Anoar, K.A.; Ali, F.A.; Omer, S.A. Detection of metallo beta-lactamase enzyme in some gram negative bacteria isolated from burn patients in sulaimani city, Iraq. Eur. Sci. J. 2014, 10, 485–496. [Google Scholar]
- Numan, S.; Al-Saedi, F.; Burhan, I. Prevalence of Extended Spectrum Betalactamase and Metallobetalactamase Producing Acinetobacter baumannii Isolated from Different Infections in Baghdad City of Iraq. Int. J. Drug Deliv. Technol. 2022, 12, 1742–1747. [Google Scholar] [CrossRef] [Scilit]
- Radhi, S.H.; Al-Charrakh, A.H. Occurrence of MBLs and Carbapenemases among MDR and XDR Acinetobacter baumannii Isolated from Hospitals in Iraq. Indian J. Public Health Res. Dev. 2019, 10, 668. [Google Scholar] [CrossRef] [Scilit]
- Smail, S.B.; Al-Otrachi, K.I. Phenotypic Characterization of Extended-Spectrum Beta-Lactamases and Metallo-Beta-Lactamase of Multi Drug Resistant Acinetobacter baumannii Causing Nosocomial Infections in Erbil City. Al-Mustansiriyah J. Sci. 2019, 30, 51–56. [Google Scholar] [CrossRef] [Scilit]
- Kishii, K.; Kikuchi, K.; Yoshida, A.; Okuzumi, K.; Uetera, Y.; Yasuhara, H.; Moriya, K. Antimicrobial susceptibility profile of Acinetobacter species isolated from blood cultures in two Japanese university hospitals. Microbiol. Immunol. 2014, 58, 142–146. [Google Scholar] [CrossRef] [Scilit]
- Yamamoto, M.; Nagao, M.; Matsumura, Y.; Hotta, G.; Matsushima, A.; Ito, Y.; Takakura, S.; Ichiyama, S. Regional dissemination of Acinetobacter species harbouring metallo-β-lactamase genes in Japan. Clin. Microbiol. Infect. Infect. Dis. 2013, 19, 729–736. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hajjar Soudeiha, M.; Dahdouh, E.; Daoud, Z.; Sarkis, D.K. Phenotypic and genotypic detection of β-lactamases in Acinetobacter spp. isolates recovered from Lebanese patients over a 1-year period. J. Glob. Antimicrob. Resist. 2018, 12, 107–112. [Google Scholar] [CrossRef] [Scilit]
- Maziz, M.N.H.; Chakravarthi, S. ESBL and MBL detection in clinical isolates of Acinetobacter species. MAHSA Int. J. Health Med. 2021, 1, 21–28. [Google Scholar]
- Koirala, A.; Agrahari, G.; Dahal, N.; Ghimire, P. ESBL and MBL mediated resistance in clinical isolates of nonfermentating Gram negative bacilli (NFGNB) in Nepal. J. Microb. Antimicrob. Agents 2017, 3, 18–24. [Google Scholar]
- Kumari, M.; Bhattarai, N.R.; Rai, K.; Pandit, T.K.; Khanal, B. Multidrug-Resistant Acinetobacter: Detection of ESBL, MBL, blaNDM-1 Genotype, and Biofilm Formation at a Tertiary Care Hospital in Eastern Nepal. Int. J. Microbiol. 2022, 2022, 8168000. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mishra, S.K.; Acharya, J.; Kattel, H.P.; Koirala, J.; Rijal, B.P.; Pokhrel, B.M. Metallo-beta-lactamase producing gram-negative bacterial isolates. J. Nepal Health Res. Counc. 2012, 10, 208–213. [Google Scholar] [PubMed]
- Pandey, R.; Mishra, S.K.; Shrestha, A. Characterisation of ESKAPE Pathogens with Special Reference to Multidrug Resistance and Biofilm Production in a Nepalese Hospital. Infect. Drug Resist. 2021, 14, 2201–2212. [Google Scholar] [CrossRef] [Scilit]
- Pathak, P.; Jaishi, N.; Yadav, B.K.; Shah, P.K. Prevalence of extended spectrum beta lactamases (ESBL) and metallo beta lactamases (MBL) mediated resistance in gram negative bacterial pathogens. Tribhuvan Univ. J. Microbiol. 2017, 4, 49–54. [Google Scholar] [CrossRef] [Scilit]
- Sakuma, M.; Tohya, M.; Hishinuma, T.; Sherchand, J.B.; Kirikae, T.; Tada, T. Molecular epidemiology of multidrug-resistant Acinetobacter baumannii isolates from a hospital in Nepal. J. Glob. Antimicrob. Resist. 2024, 38, 363–367. [Google Scholar] [CrossRef] [Scilit]
- Shrestha, S.; Tada, T.; Shrestha, B.; Ohara, H.; Kirikae, T.; Rijal, B.; Pokhrel, B.; Sherchand, J. Phenotypic characterization of multidrug-resistant Acinetobacter baumannii with special reference to metallo-β-lactamase production from the hospitalized patients in a tertiary care hospital in Nepal. J. Inst. Med. Nepal 2015, 37, 3–10. [Google Scholar] [CrossRef] [Scilit]
- Thapa, P.; Bhandari, D.; Shrestha, D.; Parajuli, H.; Chaudhary, P.; Amatya, J.; Amatya, R. A hospital based surveillance of metallo-beta-lactamase producing gram negative bacteria in Nepal by imipenem-EDTA disk method. BMC Res. Notes 2017, 10, 322. [Google Scholar] [CrossRef] [Scilit]
- Yadav, S.K.; Bhujel, R.; Hamal, P.; Mishra, S.K.; Sharma, S.; Sherchand, J.B. Burden of Multidrug-Resistant Acinetobacter baumannii Infection in Hospitalized Patients in a Tertiary Care Hospital of Nepal. Infect. Drug Resist. 2020, 13, 725–732. [Google Scholar] [CrossRef] [Scilit]
- Anwar, M.; Ejaz, H.; Zafar, A.; Hamid, H. Phenotypic Detection of Metallo-Beta-Lactamases in Carbapenem Resistant Acinetobacter baumannii Isolated from Pediatric Patients in Pakistan. J. Pathog. 2016, 2016, 8603964. [Google Scholar] [CrossRef] [Scilit]
- Hasan, B.; Perveen, K.; Olsen, B.; Zahra, R. Emergence of carbapenem-resistant Acinetobacter baumannii in hospitals in Pakistan. J. Med. Microbiol. 2014, 63, 50–55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Irfan, S.; Zafar, A.; Guhar, D.; Ahsan, T.; Hasan, R. Metallo-β-Lactamase-Producing Clinical Isolates Of Acinetobacter Species And Pseudomonas Aeruginosa From Intensive Care Unit Patients Of A Tertiary Care Hospital. Indian J. Med. Microbiol. 2008, 26, 243–245. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rashid, F.; Masood, R.; Faiz, M. Prevalence of New Delhi metallo beta-lactamase (NDM) producing Gram-negative bacteria from different tertiary care hospitals in Lahore, Pakistan. Pak. J. Zool. 2020, 52, 1209. [Google Scholar] [CrossRef] [Scilit]
- Sajjad, A.; Malik, M.; Javed, I.; Mushtaq, S.; Imran, F.; Jameel, R. Detection of metallo beta lactamase production in imipenem resistant gram negative bacilli non fermenters isolated in a Tertiary Care Hospital. Prof. Med. J. 2019, 26, 2080–2084. [Google Scholar] [CrossRef] [Scilit]
- Shah, M.W.; Yasir, M.; Farman, M.; Jiman-Fatani, A.A.; Almasaudi, S.B.; Alawi, M.; El-Hossary, D.; Azhar, E.I. Antimicrobial Susceptibility and Molecular Characterization of Clinical Strains of Acinetobacter baumannii in Western Saudi Arabia. Microb. Drug Resist. 2019, 25, 1297–1305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sung, J.Y.; Koo, S.H.; Kim, S.; Kwon, G.C. Emergence of Acinetobacter pittii harboring New Delhi metallo-β-lactamase genes in Daejeon, Korea. Ann. Lab. Med. 2015, 35, 531. [Google Scholar] [CrossRef] [Scilit]
- Lee, M.-F.; Peng, C.-F.; Hsu, H.-J.; Chen, Y.-H. Molecular characterisation of the metallo-β-lactamase genes in imipenem-resistant Gram-negative bacteria from a university hospital in southern Taiwan. Int. J. Antimicrob. Agents 2008, 32, 475–480. [Google Scholar] [CrossRef] [Scilit]
- Mesli, E.; Berrazeg, M.; Drissi, M.; Bekkhoucha, S.N.; Rolain, J.-M. Prevalence of carbapenemase-encoding genes including New Delhi metallo-β-lactamase in Acinetobacter species, Algeria. Int. J. Infect. Dis. 2013, 17, e739–e743. [Google Scholar] [CrossRef] [Scilit]
- Abd El-Glil, R. New Delhi Metallo-β-lactamase 1 (NDM-1) producing Acinetobacter baumannii in Egyptian hospitals. Int. J. Adv. Res. 2015, 3, 470–478. [Google Scholar]
- Elbrolosy, A.M.; Labeeb, A.Z.; Hassan, D.M. New Delhi metallo-β-lactamase-producing Acinetobacter isolates among late-onset VAP patients: Multidrug-resistant pathogen and poor outcome. Infect. Drug Resist. 2019, 12, 373–384. [Google Scholar] [CrossRef] [Scilit]
- El-Din, R.A.A.; El-Bassat, H.; El-Bedewy, M.; El-Mohamady, H. Prevalence of metallo-β-lactamases producers among carbapenem-resistant Acinetobacter baumannii strains isolated from diabetic foot ulcers. Afr. J. Microbiol. Res. 2014, 8, 1580–1585. [Google Scholar] [CrossRef] [Scilit]
- Fattouh, M.; El-Din, A. Emergence of carbapenem-resistant Acinetobacter baumannii in the intensive care unit in Sohag University Hospital, Egypt. Int. J. Curr. Microbiol. Appl. Sci. 2014, 3, 732–744. [Google Scholar]
- Fouad, M.; Attia, A.S.; Tawakkol, W.M.; Hashem, A.M. Emergence of carbapenem-resistant Acinetobacter baumannii harboring the OXA-23 carbapenemase in intensive care units of Egyptian hospitals. Int. J. Infect. Dis. IJID Off. Publ. Int. Soc. Infect. Dis. 2013, 17, e1252–e1254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hassan, R.M.; Salem, S.T.; Hassan, S.I.M.; Hegab, A.S.; Elkholy, Y.S. Molecular characterization of carbapenem-resistant Acinetobacter baumannii clinical isolates from Egyptian patients. PLoS ONE 2021, 16, e0251508. [Google Scholar] [CrossRef] [Scilit]
- Wasfi, R.; Rasslan, F.; Hassan, S.S.; Ashour, H.M.; Abd El-Rahman, O.A. Co-Existence of carbapenemase-encoding genes in Acinetobacter baumannii from cancer patients. Infect. Dis. Ther. 2021, 10, 291–305. [Google Scholar] [CrossRef] [Scilit]
- Olu-Taiwo, M.A.; Opintan, J.A.; Codjoe, F.S.; Obeng Forson, A. Metallo-Beta-Lactamase-Producing Acinetobacter spp. from Clinical Isolates at a Tertiary Care Hospital in Ghana. BioMed Res. Int. 2020, 2020, 3852419. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mathlouthi, N.; El Salabi, A.A.; Ben Jomàa-Jemili, M.; Bakour, S.; Al-Bayssari, C.; Zorgani, A.A.; Kraiema, A.; Elahmer, O.; Okdah, L.; Rolain, J.-M.; et al. Early detection of metallo-β-lactamase NDM-1- and OXA-23 carbapenemase-producing Acinetobacter baumannii in Libyan hospitals. Int. J. Antimicrob. Agents 2016, 48, 46–50. [Google Scholar] [CrossRef] [Scilit]
- Kabbaj, H.; Seffar, M.; Belefquih, B.; Akka, D.; Handor, N.; Amor, M.; Alaoui, A.E. Prevalence of metallo-β-Lactamases Producing Acinetobacter baumannii in a Moroccan Hospital. Int. Sch. Res. Not. 2013, 2013, 154921. [Google Scholar] [CrossRef] [Scilit]
- Nogbou, N.-D.; Phofa, D.T.; Nchabeleng, M.; Musyoki, A.M. Investigating multi-drug resistant Acinetobacter baumannii isolates at a tertiary hospital in Pretoria, South Africa. Indian J. Med. Microbiol. 2021, 39, 218–223. [Google Scholar] [CrossRef] [Scilit]
- Elbadawi, H.S.; Elhag, K.M.; Mahgoub, E.; Altayb, H.N.; Ntoumi, F.; Elton, L.; McHugh, T.D.; Tembo, J.; Ippolito, G.; Osman, A.Y.; et al. Detection and characterization of carbapenem resistant Gram-negative bacilli isolates recovered from hospitalized patients at Soba University Hospital, Sudan. BMC Microbiol. 2021, 21, 136. [Google Scholar] [CrossRef] [Scilit]
- Kateete, D.P.; Nakanjako, R.; Namugenyi, J.; Erume, J.; Joloba, M.L.; Najjuka, C.F. Carbapenem resistant Pseudomonas aeruginosa and Acinetobacter baumannii at Mulago Hospital in Kampala, Uganda (2007–2009). SpringerPlus 2016, 5, 1308. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Takemura, M.; Wise, M.G.; Hackel, M.A.; Sahm, D.F.; Yamano, Y. In vitro activity of cefiderocol against MBL-producing Gram-negative bacteria collected in North America and Europe in five consecutive annual multinational SIDERO-WT surveillance studies (2014–2019). J. Antimicrob. Chemother. 2023, 78, 2019–2027. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hernández Gómez, C.; Blanco, V.M.; Motoa, G.; Correa, A.; Maya, J.J.; de la Cadena Vivas, E.; Perenguez, M.; Rojas, L.; Hernández, A.; Vallejo, M.; et al. Evolución de la resistencia antimicrobiana de bacilos Gram negativos en unidades de cuidados intensivos en Colombia. Bioméd. Rev. Inst. Nac. Salud 2014, 34, 91–100. [Google Scholar] [CrossRef] [Scilit]
- Mereuţă, A.I.; Bădescu, A.C.; Dorneanu, O.S.; Iancu, L.S.; Tuchiluş, C.G. Spread of VIM-2 metallo-beta-lactamase in Pseudomonas aeruginosa and Acinetobacter baumannii clinical isolates from Iaşi, Romania. Rev. Romana Med. Lab. 2013, 21, 423–430. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumari, M.; Verma, S.; Venkatesh, V.; Gupta, P.; Tripathi, P.; Agarwal, A.; Siddiqui, S.S.; Arshad, Z.; Prakash, V. Emergence of blaNDM-1 and blaVIM producing Gram-negative bacilli in ventilator-associated pneumonia at AMR Surveillance Regional Reference Laboratory in India. PLoS ONE 2021, 16, e0256308. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matuschek, E.; Ahman, J.; Webster, C.; Kahlmeter, G. Antimicrobial susceptibility testing of colistin—Evaluation of seven commercial MIC products against standard broth microdilution for Escherichia coli, Klebsiella pneumoniae, Pseudomonas aeruginosa, and Acinetobacter spp. Clin. Microbiol. Infect. 2018, 24, 865–870. [Google Scholar] [CrossRef] [Scilit]
- Galani, I.; Rekatsina, P.D.; Hatzaki, D.; Plachouras, D.; Souli, M.; Giamarellou, H. Evaluation of different laboratory tests for the detection of metallo-β-lactamase production in Enterobacteriaceae. J. Antimicrob. Chemother. 2008, 61, 548–553. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Daef, E.A.; Mohamed, I.S.; Ahmed, A.S.; Elsherbiny, N.M.; Sayed, I.M. Evaluation of different phenotypic assays for the detection of metallo-β-lactamase production in carbapenem susceptible and resistant Acinetobacter baumannii isolates. J. Am. Sci. 2012, 8, 292–299. [Google Scholar]
- Pandya, N.P.; Nirav, P.; Pandya, S.B.P. Evaluation of various methods for detection of metallo-β-lactamase (mbl) production in gram negative bacilli. Int. J. Biol. Med. Res. 2011, 2, 775–777. [Google Scholar]
- Magiorakos, A.-P.; Srinivasan, A.; Carey, R.B.; Carmeli, Y.; Falagas, M.E.; Giske, C.G.; Harbarth, S.; Hindler, J.F.; Kahlmeter, G.; Olsson-Liljequist, B.; et al. Multidrug-resistant, extensively drug-resistant and pandrug-resistant bacteria: An international expert proposal for interim standard definitions for acquired resistance. Clin. Microbiol. Infect. 2012, 18, 268–281. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Falagas, M.E.; Bliziotis, I.A.; Siempos, I.I. Attributable mortality of Acinetobacter baumannii infections in critically ill patients: A systematic review of matched cohort and case-control studies. Crit. Care Lond. Engl. 2006, 10, R48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Falagas, M.E.; Kopterides, P. Risk factors for the isolation of multi-drug-resistant Acinetobacter baumannii and Pseudomonas aeruginosa: A systematic review of the literature. J. Hosp. Infect. 2006, 64, 7–15. [Google Scholar] [CrossRef] [Scilit]
- Poirel, L.; Bonnin, R.A.; Nordmann, P. Genetic basis of antibiotic resistance in pathogenic Acinetobacter species. IUBMB Life 2011, 63, 1061–1067. [Google Scholar] [CrossRef] [Scilit]
- Jain, R.; Danziger, L.H. Multidrug-resistant Acinetobacter infections: An emerging challenge to clinicians. Ann. Pharmacother. 2004, 38, 1449–1459. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karageorgopoulos, D.E.; Kelesidis, T.; Kelesidis, I.; Falagas, M.E. Tigecycline for the treatment of multidrug-resistant (including carbapenem-resistant) Acinetobacter infections: A review of the scientific evidence. J. Antimicrob. Chemother. 2008, 62, 45–55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Poulikakos, P.; Tansarli, G.S.; Falagas, M.E. Combination antibiotic treatment versus monotherapy for multidrug-resistant, extensively drug-resistant, and pandrug-resistant Acinetobacter infections: A systematic review. Eur. J. Clin. Microbiol. Infect. Dis. 2014, 33, 1675–1685. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Falagas, M.E.; Skalidis, T.; Vardakas, K.Z.; Legakis, N.J.; Hellenic Cefiderocol Study Group. Activity of cefiderocol (S-649266) against carbapenem-resistant Gram-negative bacteria collected from inpatients in Greek hospitals. J. Antimicrob. Chemother. 2017, 72, 1704–1708. [Google Scholar] [CrossRef] [Scilit]
- Oliva, A.; Liguori, L.; Covino, S.; Petrucci, F.; Cogliati-Dezza, F.; Curtolo, A.; Savelloni, G.; Comi, M.; Sacco, F.; Ceccarelli, G.; et al. Clinical effectiveness of cefiderocol for the treatment of bloodstream infections due to carbapenem-resistant Acinetobacter baumannii during the COVID-19 era: A single center, observational study. Eur. J. Clin. Microbiol. Infect. Dis. 2024, 43, 1149–1160. [Google Scholar] [CrossRef] [Scilit]
- Calò, F.; Onorato, L.; De Luca, I.; Macera, M.; Monari, C.; Durante-Mangoni, E.; Massa, A.; Gentile, I.; Di Caprio, G.; Pagliano, P.; et al. Outcome of patients with carbapenem-resistant Acinetobacter baumannii infections treated with cefiderocol: A multicenter observational study. J. Infect. Public Health 2023, 16, 1485–1491. [Google Scholar] [CrossRef] [Scilit]
- Bassetti, M.; Echols, R.; Matsunaga, Y.; Ariyasu, M.; Doi, Y.; Ferrer, R.; Lodise, T.P.; Naas, T.; Niki, Y.; Paterson, D.L.; et al. Efficacy and safety of cefiderocol or best available therapy for the treatment of serious infections caused by carbapenem-resistant Gram-negative bacteria (CREDIBLE-CR): A randomised, open-label, multicentre, pathogen-focused, descriptive, phase 3 trial. Lancet Infect. Dis. 2021, 21, 226–240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sargianou, M.; Stathopoulos, P.; Vrysis, C.; Tzvetanova, I.D.; Falagas, M.E. New β-Lactam/β-Lactamase Inhibitor Combination Antibiotics. Pathogens 2025, 14, 307. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaye, K.S.; Shorr, A.F.; Wunderink, R.G.; Du, B.; Poirier, G.E.; Rana, K.; Miller, A.; Lewis, D.; O’Donnell, J.; Chen, L.; et al. Efficacy and safety of sulbactam-durlobactam versus colistin for the treatment of patients with serious infections caused by Acinetobacter baumannii-calcoaceticus complex: A multicentre, randomised, active-controlled, phase 3, non-inferiority clinical trial (ATTACK). Lancet Infect. Dis. 2023, 23, 1072–1084. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rafailidis, P.I.; Ioannidou, E.N.; Falagas, M.E. Ampicillin/sulbactam: Current status in severe bacterial infections. Drugs 2007, 67, 1829–1849. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).