Natural Versus Vaccine-Induced Immunity Against HPV: A Comparative Review of Antibody Response and Cancer Prevention


 ,
 ,

Abstract
1. Introduction
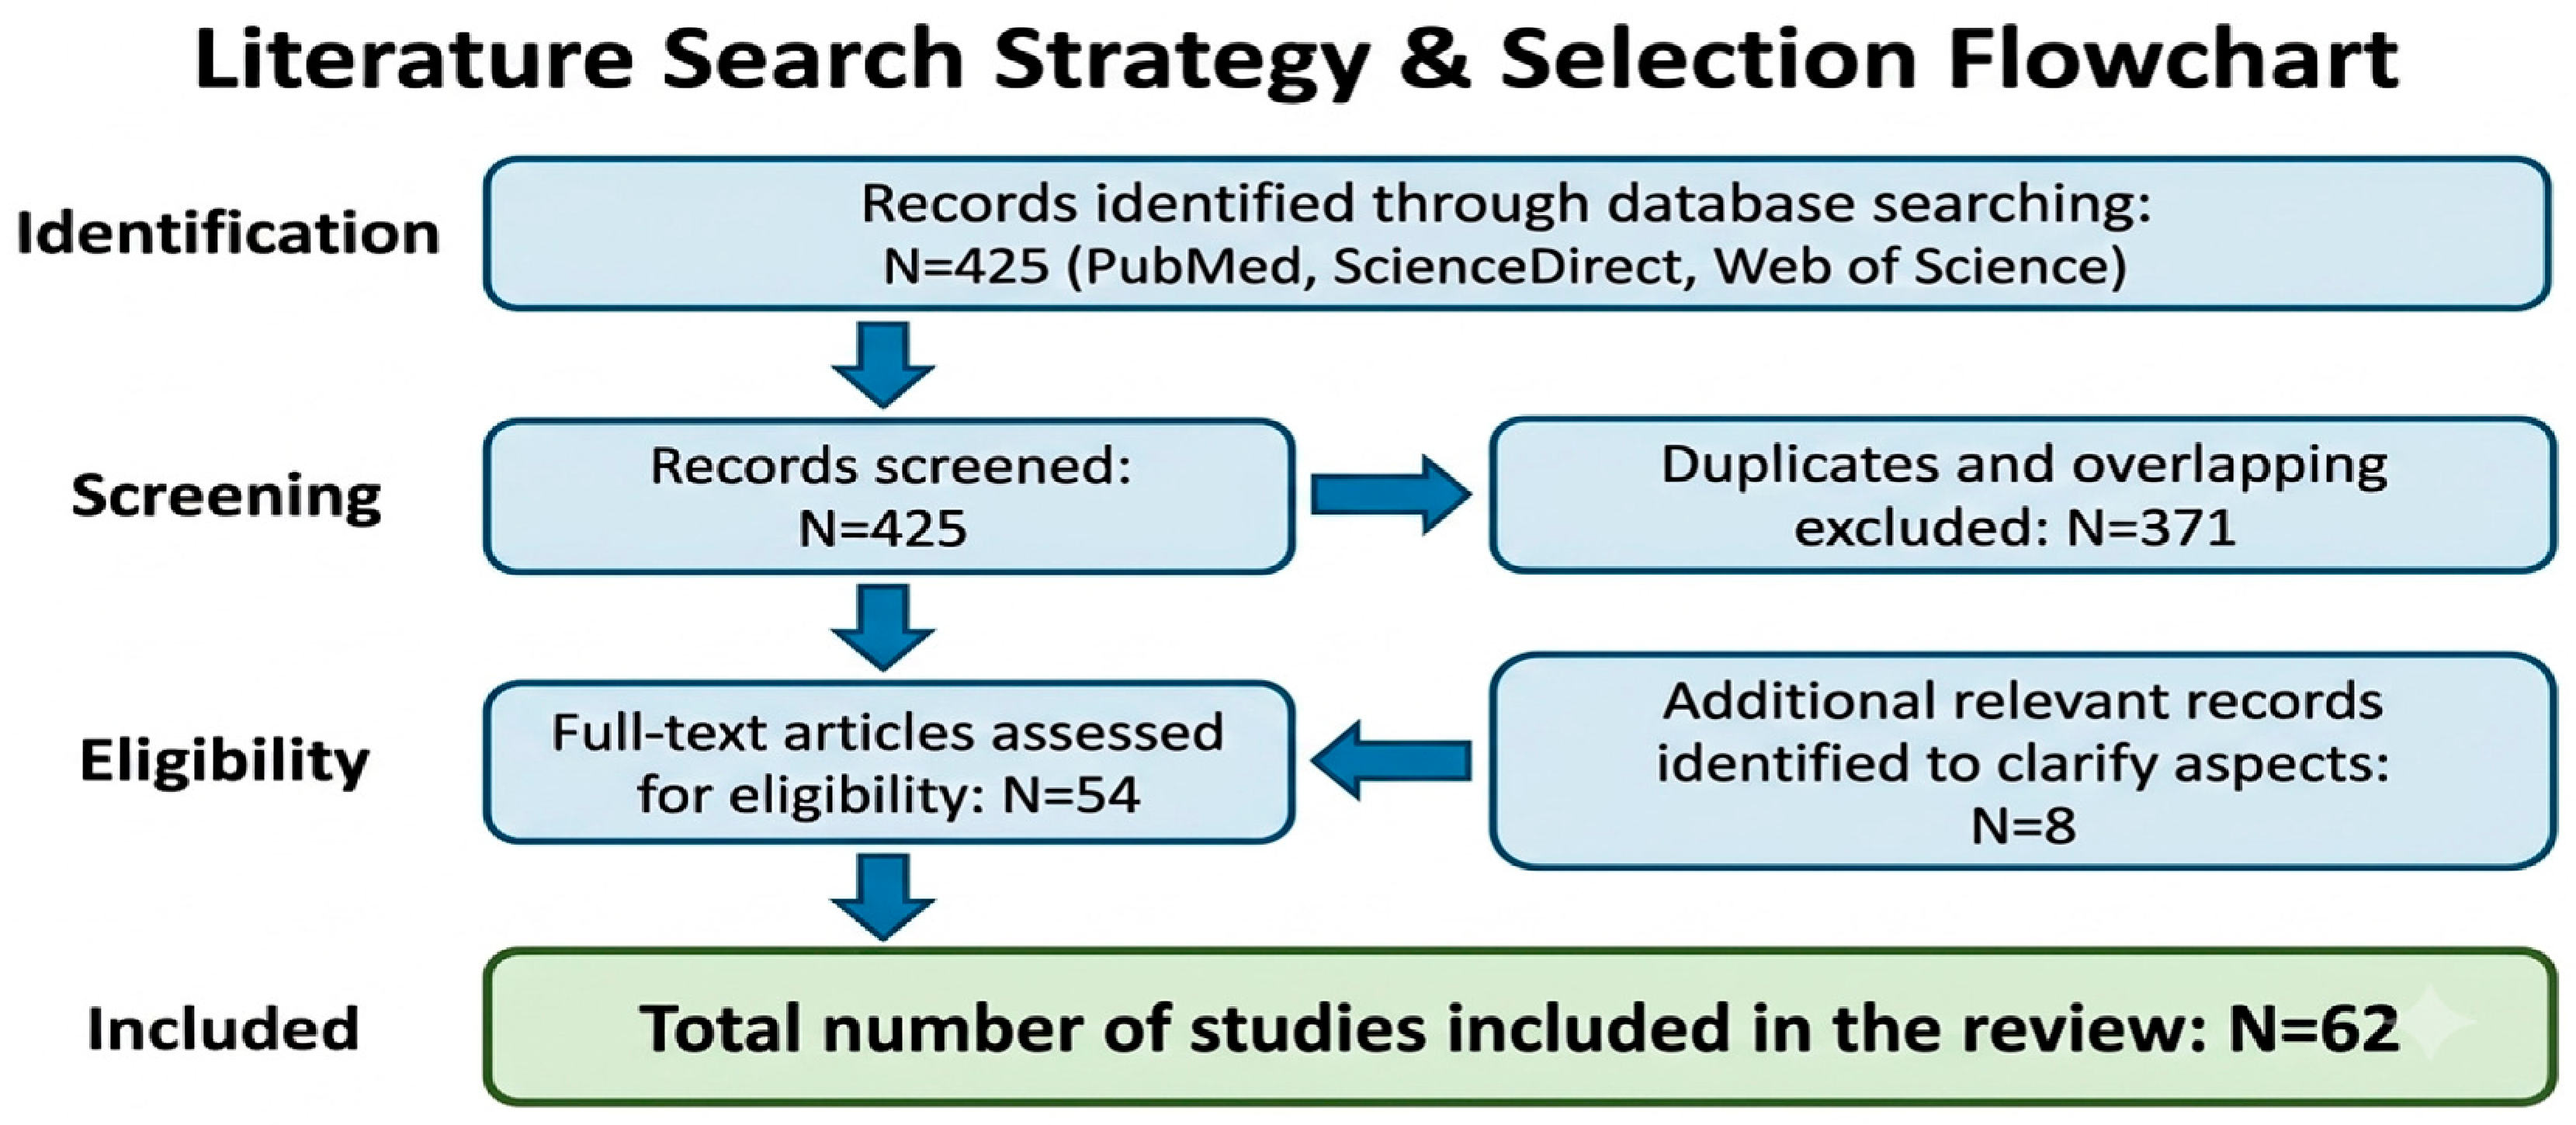
2. Materials and Methods
3. Results
3.1. Natural Immunity After HPV Infection
Seroprevalence and Protection: Evidence from International Studies
- A.
- A large stage three study [7] followed seroconversion for HPV 16/18 in two cohorts of unvaccinated women over the period of four years. Of the 10,752 women screened for HPV-16 antibodies, only 18% (1935 women) were positive for the neutralising IgG. In the HPV-18 cohort (11,169 women), 15% (1675 cases) showed neutralizing IgG seropositivity [7]. However, clinical outcomes underlined the limited protective value of natural immunity: 1607 lesions progressed toward malignancy (mostly HPV-16 related), with 37% incidence of newly acquired infections, 30% persistent infections lasting over two years, and 43% squamous cell atypia [7]. These results indicate that naturally acquired antibodies are insufficient to prevent disease progression, particularly for HPV-16.
- B.
- A Dutch cohort study [36], which involved several thousand women near menopause, assessed the relation between naturally acquired HPV antibodies and protection against subsequent infections. Although women with detectable antibodies were expected to be less vulnerable to new HPV infections, the data did not show a statistically significant difference. However, those same antibodies did appear to offer better protection against persistent infections, which are more likely to lead to malignant changes [36]. In this cohort, 30% of participants had detectable anti-HPV 16/18 antibodies, yet only 9.95% of them reported an HPV infection history [36]. These results indicate that although natural immunity may help limit long-term viral persistence, it does not reliably prevent initial infection.
- C.
- In a cohort of 978 unvaccinated women from China [37], researchers measured levels of anti-HPV 16/18 antibodies—both neutralizing IgG and total IgG (including binding, non-neutralizing antibodies). With high statistical significance (p < 0.05) and strong data correlation (k between 0.52 and 0.38), their results underline that neutralizing IgG antibodies are the most important markers of protection against persistent HPV infections [37].
- D.
- E.
- Important data are provided by two studies conducted in China. The first study [39] followed women with and without HPV infection through periodic cytological examinations and serum antibody measurements. Among HPV-positive women, infection was most often caused by a single strain, with coinfections being rare (although one case of simultaneous infection with HPV types 16, 18, 33, and 45 was documented) [39]. Antibody titres were significantly higher in HPV-positive women, particularly in those with lesions (e.g., four women with CIN III). Interestingly, 45% of women without demonstrable infection also had detectable anti-HPV antibodies, predominantly against types 16 and 18 [39].
- F.
- The second study [40] used a similar approach, measuring antibodies and performing cytological evaluation in 1897 women with CIN. The most notable finding was the higher prevalence of antibodies against non-high-risk HPV types, which may explain the relatively limited protection observed after natural infection. It is important to note that these studies measured total antibodies, not specifically neutralizing antibodies [40].
- G.
- Another important aspect of HPV immunity is the possibility of antibody transfer through the placental barrier. A 2022 Finnish study [41] analyzed serum samples from 276 mother–infant pairs, from right after birth to the 36-month mark. They measured antibodies for the 6, 11, 16, 18, and 45 HPV strains, and identified two distinct pathways in which they evolve. The first reflects passive maternal transmission: at birth, 40–62% of newborns had detectable anti-HPV antibodies, a finding strongly correlated with maternal seropositivity (p < 0.001) [41]. These passively acquired antibodies declined steadily, becoming negligible by 8–10 months, consistent with the natural fading of maternal immunity as antibodies were metabolized. The second pathway points to independent early contact. By 36 months, 53% of children born to seronegative mothers had developed anti-HPV antibodies, most likely through early environmental contact with the virus via fomites or caregivers [41]. The results indicate that maternal immune antibodies provide only short-term passive protection, while early postnatal exposure can independently induce antibody responses in children.
- H.
- Natural immunity against HPV is weak and often inconsistent [7,42]. The cellular immune response plays a central role, yet seroconversion is inefficient, and neutralizing antibody titers remain low. Studies regularly emphasize the importance of IgG neutralising antibodies (especially anti-L1) as a protective marker. Yet the absence of an international standard for cut-off values complicates standardisation. Passive transmission across the placental barrier offers temporary protection; however, initial exposure to HPV maintains its status as a genuine public health concern. This evidence emphasizes the limited and unreliable nature of natural immunity, supporting the need for vaccination as the primary strategy for durable protection.
3.2. Acquired Immunity After Vaccination
3.2.1. Types of HPV Vaccines
3.2.2. Cross-Reactivity
3.2.3. Immune Response After Vaccination
3.2.4. Degree of Protection and Antibody Kinetics
Protective Role of IgA Antibodies
Post-Infection Vaccination Utility
4. Vaccine Immunogenicity
5. Immune Response in Mixed Cohorts
6. Immune Memory
7. Vaccination and Local Lesions
8. Vaccination in HPV-Positive Women
9. HPV Vaccine and Respiratory Papillomatosis
10. Interactions and Risks
11. Discussion
12. Conclusions and Future Perspectives
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
Abbreviations
| APCs | Antigen-presenting cells |
| CI/Cl | Confidence Interval (mentioned as 95% CI or Cl = 95%) |
| CIN | Cervical intraepithelial neoplasia (mentioned in the text as CIN III or CIN2+) |
| DNA | Deoxyribonucleic acid |
| GMC | Geometric Mean Concentration |
| GMT | Geometric Mean Titer (found in the antibody tables) |
| HPV | Human Papillomavirus |
| HSIL | High-grade squamous intraepithelial lesions |
| IgA, IgG, IgM | Immunoglobulin A, G, and M (types of antibodies) |
| IU/mL | International Units per milliliter |
| LEEP | Loop electrosurgical excision procedure (mentioned in the text as “LEEPconization”) |
| LSIL | Low-grade squamous intraepithelial lesions |
| LU/mL | Local units per milliliter |
| MHC | Major histocompatibility complex (e.g., MHC I and MHC II) |
| MU/mL | Merck Units per milliliter |
| NK (cells) | Natural killer cells |
| RRP | Recurrent respiratory papillomatosis |
| VLPs | Virus-like particles |
References
- Hirth, J. Disparities in HPV Vaccination Rates and HPV Prevalence in the United States: A Review of the Literature. Hum. Vaccines Immunother. 2019, 15, 146–155. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Milano, G.; Guarducci, G.; Nante, N.; Montomoli, E.; Manini, I. Human Papillomavirus Epidemiology and Prevention: Is There Still a Gender Gap? Vaccines 2023, 11, 1060. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Forslund, O.; Miriam Elfström, K.; Lamin, H.; Dillner, J. HPV-mRNA and HPV-DNA Detection in Samples Taken up to Seven Years before Severe Dysplasia of Cervix Uteri. Int. J. Cancer 2019, 144, 1073–1081. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jamdar, F.; Farzaneh, F.; Navidpour, F.; Younesi, S.; Balvayeh, P.; Hosseini, M.; Ghodssi-Ghasemabadi, R. Prevalence of Human Papillomavirus Infection among Iranian Women Using COBAS HPV DNA Testing. Infect. Agents Cancer 2018, 13, 6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roy, V.; Jung, W.; Linde, C.; Coates, E.; Ledgerwood, J.; Costner, P.; Yamshchikov, G.; Streeck, H.; Juelg, B.; Lauffenburger, D.A.; et al. Differences in HPV-Specific Antibody Fc-Effector Functions Following Gardasil® and Cervarix® Vaccination. npj Vaccines 2023, 8, 39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, R.; Liu, Z.; Sun, T.; Zhu, L. Cervicovaginal Microbiome, High-Risk HPV Infection and Cervical Cancer: Mechanisms and Therapeutic Potential. Microbiol. Res. 2024, 287, 127857. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kiamba, E.W.; Goodier, M.R.; Clarke, E. Immune Responses to Human Papillomavirus Infection and Vaccination. Front. Immunol. 2025, 16, 1591297. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Di Spirito, F.; Pantaleo, G.; Di Palo, M.P.; Amato, A.; Raimondo, A.; Amato, M. Oral Human Papillomavirus Benign Lesions and HPV-Related Cancer in Healthy Children: A Systematic Review. Cancers 2023, 15, 1096. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wei, F.; Georges, D.; Man, I.; Baussano, I.; Clifford, G.M. Causal Attribution of Human Papillomavirus Genotypes to Invasive Cervical Cancer Worldwide: A Systematic Analysis of the Global Literature. Lancet 2024, 404, 435–444. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shi, R.; Qi, W.; Wang, Z.; Cai, J.; Zhao, M.; Wang, Z. High-Risk Human Papillomavirus Genotype Distribution and Attribution to Cervical Lesions in a Shanxi Province Screening Population. Sci. Rep. 2025, 15, 28217. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mirabello, L.; Clarke, M.; Nelson, C.; Dean, M.; Wentzensen, N.; Yeager, M.; Cullen, M.; Boland, J.; Schiffman, M.; Burk, R. The Intersection of HPV Epidemiology, Genomics and Mechanistic Studies of HPV-Mediated Carcinogenesis. Viruses 2018, 10, 80. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Santacroce, L.; Di Cosola, M.; Bottalico, L.; Topi, S.; Charitos, I.A.; Ballini, A.; Inchingolo, F.; Cazzolla, A.P.; Dipalma, G. Focus on HPV Infection and the Molecular Mechanisms of Oral Carcinogenesis. Viruses 2021, 13, 559. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Sanjosé, S.; Brotons, M.; Pavón, M.A. The Natural History of Human Papillomavirus Infection. Best Pract. Res. Clin. Obstet. Gynaecol. 2018, 47, 2–13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beachler, D.C.; Pinto, L.A.; Kemp, T.J.; Nyitray, A.G.; Hildesheim, A.; Viscidi, R.; Schussler, J.; Kreimer, A.R.; Giuliano, A.R. An Examination of HPV16 Natural Immunity in Men Who Have Sex with Men (MSM) in the HPV in Men (HIM) Study. Cancer Epidemiol. Biomark. Prev. 2018, 27, 496–502. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Franceschi, S.; Baussano, I. Naturally Acquired Immunity Against Human Papillomavirus (HPV): Why It Matters in the HPV Vaccine Era. J. Infect. Dis. 2014, 210, 507–509. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rosillon, D.; Baril, L.; Del Rosario-Raymundo, M.R.; Wheeler, C.M.; Skinner, S.R.; Garland, S.M.; Salmeron, J.; Lazcano-Ponce, E.; Vallejos, C.S.; Stoney, T.; et al. Risk of Newly Detected Infections and Cervical Abnormalities in Adult Women Seropositive or Seronegative for Naturally Acquired HPV-16/18 Antibodies. Cancer Med. 2019, 8, 4938–4953. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yao, X.; Chu, K.; Zhao, J.; Hu, Y.; Lin, Z.; Lin, B.; Chen, Q.; Li, Y.; Zhang, Q.; Fang, M.; et al. Comparison of HPV Neutralizing and IgG Antibodies in Unvaccinated Female Adolescents. Future Microbiol. 2022, 17, 1207–1215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morais, S.; Wissing, M.D.; Khosrow-Khavar, F.; Burchell, A.N.; Tellier, P.P.; Coutlee, F.; Waterboer, T.; El-Zein, M.; Franco, E.L. Serologic Response to Human Papillomavirus Genotypes among Unvaccinated Women: Findings from the HITCH Cohort Study. J. Infect. Dis. 2023, 227, 1173–1184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Syrjänen, S.; Waterboer, T.; Rintala, M.; Pawlita, M.; Syrjänen, K.; Louvanto, K.; Grenman, S. Maternal HPV-Antibodies and Seroconversion to HPV in Children during the First 3 Years of Life. Sci. Rep. 2022, 12, 2227. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Porras, C.; Tsang, S.H.; Herrero, R.; Guillén, D.; Darragh, T.M.; Stoler, M.H.; Hildesheim, A.; Wagner, S.; Boland, J.; Lowy, D.R.; et al. Efficacy of the Bivalent HPV Vaccine against HPV 16/18-Associated Precancer: Long-Term Follow-up Results from the Costa Rica Vaccine Trial. Lancet Oncol. 2020, 21, 1643–1652. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Watson-Jones, D.; Changalucha, J.; Whitworth, H.; Mutani, P.; Indangasi, J.; Hashim, R.; Kamala Dip, B.; Songoro, T.B.; Mbwanji, G.; Mmbando, D.; et al. Immunogenicity and Safety of One-Dose Human Papillomavirus Vaccine Compared with Two or Three Doses in Tanzanian Girls (DoRIS): An Open-Label, Randomised, Non-Inferiority Trial. Lancet Glob. Health 2022, 10, e1473–e1484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hoes, J.; King, A.J.; Berkhof, J.; de Melker, H.E. High Vaccine Effectiveness Persists for Ten Years after HPV16/18 Vaccination among Young Dutch Women. Vaccine 2023, 41, 285–289. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pruski, D.; Łagiedo-żelazowska, M.; Millert-Kalińska, S.; Sikora, J.; Jach, R.; Przybylski, M. Immunity after HPV Vaccination in Patients after Sexual Initiation. Vaccines 2022, 10, 728. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Panwar, K.; Yokoya, K.; Checchi, M.; Anderson, A.; Tonge, S.; Borrow, R.; Soldan, K.; Beddows, S. Serosurveillance to Support HPV Vaccination in England. Open Forum Infect. Dis. 2025, 12, ofaf218. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Steinberg, J.; Panicker, G.; Unger, E.R.; Blake, I.; Lewis, R.M.; Geis, J.; Bruden, D.; Fischer, M.; Markowitz, L.E.; Bruce, M.G. Immunogenicity and Duration of Antibodies after Vaccination with a Two-Dose Series of the Nine-Valent Human Papillomavirus Vaccine among Alaska Native Children: A Prospective Cohort Study. BMC Infect. Dis. 2025, 25, 640. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Souza, G.; Tewari, S.R.; Troy, T.; Waterboer, T.; Struijk, L.; Castillo, R.; Wright, H.; Shen, M.; Miles, B.; Johansson, M.; et al. Prevalence of Oral and Blood Oncogenic Human Papillomavirus Biomarkers among an Enriched Screening Population: Baseline Results of the MOUTH Study. Cancer 2023, 129, 2373–2384. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Restrepo, J.; Herrera, T.; Samakoses, R.; Reina, J.C.; Pitisuttithum, P.; Ulied, A.; Bekker, L.-G.; Moreira, E.D.; Olsson, S.-E.; Block, S.L.; et al. Ten-Year Follow-up of 9-Valent Human Papillomavirus Vaccine: Immunogenicity, Effectiveness, and Safety. Pediatrics 2023, 152, e2022060993. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maldonado, I.; Plata, M.; Gonzalez, M.; Correa, A.; Nossa, C.; Giuliano, A.R.; Joura, E.A.; Ferenczy, A.; Ronnett, B.M.; Stoler, M.H.; et al. Effectiveness, Immunogenicity, and Safety of the Quadrivalent HPV Vaccine in Women and Men Aged 27–45 Years. Hum. Vaccines Immunother. 2022, 18, 2078626. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barnabas, R.V.; Brown, E.R.; Onono, M.A.; Bukusi, E.A.; Njoroge, B.; Winer, R.L.; Galloway, D.A.; Pinder, L.F.; Donnell, D.; Wakhungu, I.; et al. Efficacy of single-dose HPV vaccination among young African women. NEJM Evid. 2022, 1, EVIDoa2100056. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pruski, D.; Millert-Kalińska, S.; Łagiedo, M.; Sikora, J.; Jach, R.; Przybylski, M. Effect of HPV Vaccination on Virus Disappearance in Cervical Samples of a Cohort of HPV-Positive Polish Patients. J. Clin. Med. 2023, 12, 7592. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kitano, T.; Schwartz, K.L.; Abdulnoor, M.; Garfield, H.; Booran, N.K.; Avitzur, Y.; Teoh, C.W.; Hébert, D.; Allen, U. Immunogenicity of a Quadrivalent Human Papillomavirus Vaccine in Pediatric Kidney and Liver Transplant Recipients. Pediatr. Transplant. 2023, 27, e14476. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weissert, R.; Mehta, T.; Kammeyer, R.; Xie, C.; Li, A.; Hu, Y.; Li, J.; Chen, X.; Jiang, Y. Case Report: Anti-GAD65 Antibody-Associated Autoimmune Encephalitis Following HPV Vaccination. Front. Neurol. 2022, 13, 1017086. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Costa, A.P.F.; Gonçalves, A.K.; Machado, P.R.L.; de Souza, L.B.F.C.; Sarmento, A.; Cobucci, R.N.O.; Giraldo, P.C.; Witkin, S.S. Immune Response to Human Papillomavirus One Year after Prophylactic Vaccination with AS04-Adjuvanted HPV-16/18 Vaccine: HPV-Specific IgG and IgA Antibodies in the Circulation and the Cervix. Asian Pac. J. Cancer Prev. 2018, 19, 2313–2317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Murillo, R.; Ordóñez- Reyes, C. Human Papillomavirus (HPV) Vaccination: From Clinical Studies to Immunization Programs. Int. J. Gynecol. Cancer 2019, 29, 1317–1326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsang, S.H.; Sampson, J.N.; Schussler, J.; Porras, C.; Wagner, S.; Boland, J.; Cortes, B.; Lowy, D.R.; Schiller, J.T.; Schiffman, M.; et al. Durability of Cross-Protection by Different Schedules of the Bivalent HPV Vaccine: The CVT Trial. JNCI J. Natl. Cancer Inst. 2020, 112, 1030–1037. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheng, L.; Wang, Y.; Du, J. Human Papillomavirus Vaccines: An Updated Review. Vaccines 2020, 8, 391. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tang, Y.; Zhang, A.X.J.; Chen, G.; Wu, Y.; Gu, W. Prognostic and Therapeutic TILs of Cervical Cancer—Current Advances and Future Perspectives. Mol. Ther. Oncolytics 2021, 22, 410–430. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tessandier, N.; Elie, B.; Boué, V.; Selinger, C.; Rahmoun, M.; Bernat, C.; Grasset, S.; Groc, S.; Bedin, A.S.; Beneteau, T.; et al. Viral and Immune Dynamics of Genital Human Papillomavirus Infections in Young Women with High Temporal Resolution. PLoS Biol. 2025, 23, e3002949. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joura, E.A.; Giuliano, A.R.; Iversen, O.-E.; Bouchard, C.; Mao, C.; Mehlsen, J.; Moreira, E.D.; Ngan, Y.; Petersen, L.K.; Lazcano-Ponce, E.; et al. A 9-Valent HPV Vaccine against Infection and Intraepithelial Neoplasia in Women. N. Engl. J. Med. 2015, 372, 711–723. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quang, C.; Anderson, J.; Russell, F.M.; Reyburn, R.; Ratu, T.; Tuivaga, E.; Devi, R.; Frazer, I.H.; Garland, S.M.; Wines, B.; et al. Systems Serology Analysis Shows IgG1 and IgG3 Memory Responses Six Years after One Dose of Quadrivalent HPV Vaccine. Nat. Commun. 2025, 16, 2130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weiland, T.; Zgubic, J.; Brcic, L.; Thurnher, D. Detection of Antibody Subclasses IgA, IgM and IgG against HPV L1 in HPV-Positive Oropharyngeal Squamous Cell Carcinoma Patients: A Pilot Study. Eur. Arch. Oto-Rhino-Laryngol. 2024, 281, 2637–2644. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sauvageau, C.; Panicker, G.; Unger, E.R.; De Serres, G.; Schiller, J.; Ouakki, M.; Gilca, V. Priming Effect of Bivalent and Quadrivalent Vaccine for HPV 31/33/45/52: An Exploratory Analysis from Two Clinical Trials. Hum. Vaccines Immunother. 2020, 16, 590–594. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, S.; Deng, Y.; Lepp, T.; Ask, L.S.; Sparen, P.; Clements, M.; Dillner, J.; Lei, J. Extended Follow-up of Invasive Cervical Cancer Risk after Quadrivalent HPV Vaccination: Nationwide, Register Based Study. BMJ 2026, 392, e087326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schiffman, M.; Doorbar, J.; Wentzensen, N.; de Sanjosé, S.; Fakhry, C.; Monk, B.J.; Stanley, M.A.; Franceschi, S. Carcinogenic Human Papillomavirus Infection. N. Engl. J. Med. 2016, 2, 16086. [Google Scholar] [CrossRef] [Scilit]
- Schiller, J.T.; Lowy, D.R. Understanding and Learning from the Success of Prophylactic Human Papillomavirus Vaccines. Nat. Rev. Microbiol. 2012, 10, 681–692. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pasmans, H.; Berkowska, M.A.; Diks, A.M.; de Mooij, B.; Groenland, R.J.; de Rond, L.; Nicolaie, M.A.; van der Burg, S.H.; van Dongen, J.J.M.; van der Klis, F.R.M.; et al. Characterization of the Early Cellular Immune Response Induced by HPV Vaccines. Front. Immunol. 2022, 13, 863164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Centers for Disease Control and Prevention (CDC). HPV Vaccination Considerations: Safety and Effectiveness Data. Available online: https://www.cdc.gov/hpv/hcp/vaccination-considerations/safety-and-effectiveness-data.html (accessed on 7 July 2026).
- Cortés, B.; Ocampo, R.; Porras, C.; Liu, D.; Gail, M.H.; Sierra, M.S.; Herrero, R.; Lowy, D.R.; Carvajal, L.J.; Kemp, T.J.; et al. Human Papillomavirus (HPV) Type 16 and Type 18 Antibody Concentrations after a Single Dose of Bivalent HPV Vaccine in Girls Aged 9–14 Years Compared with Three Doses of Quadrivalent HPV Vaccine in Women Aged 18–25 Years in Costa Rica (PRIMAVERA): A Non-Randomised, Open-Label, Immunobridging, Non-Inferiority Trial. Lancet Infect. Dis. 2025, 25, 1314–1324. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joshi, S.; Anantharaman, D.; Muwonge, R.; Bhatla, N.; Panicker, G.; Butt, J.; Rani Reddy Poli, U.; Malvi, S.G.; Esmy, P.O.; Lucas, E.; et al. Evaluation of Immune Response to Single Dose of Quadrivalent HPV Vaccine at 10-Year Post-Vaccination. Vaccine 2023, 41, 236–245. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kreimer, A.R.; Porras, C.; Liu, D.; Hildesheim, A.; Carvajal, L.J.; Ocampo, R.; Romero, B.; Gail, M.H.; Cortes, B.; Sierra, M.S.; et al. Noninferiority of One HPV Vaccine Dose to Two Doses. N. Engl. J. Med. 2025, 393, 2421–2433. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scherpenisse, M.; Mollers, M.; Schepp, R.M.; Meijer, C.J.L.M.; de Melker, H.E.; Berbers, G.A.M.; van der Klis, F.R.M. Detection of Systemic and Mucosal HPV-Specific IgG and IgA Antibodies in Adolescent Girls One and Two Years after HPV Vaccination. Hum. Vaccines Immunother. 2013, 9, 314–321. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Handisurya, A.; Schellenbacher, C.; Haitel, A.; Senger, T.; Kirnbauer, R. Human Papillomavirus Vaccination Induces Neutralising Antibodies in Oral Mucosal Fluids. Br. J. Cancer 2016, 114, 409–416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, Z.; Li, X.; Zhang, B. Assessment of the Ability of HPV Vaccines to Induce Neutralizing Antibodies Based on Pseudovirus-Based Neutralization Assay. Front. Public Health 2025, 13, 1636491. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Middeldorp, M.; Duijster, J.W.; van de Kassteele, J.; van der Klis, F.R.M.; de Melker, H.E. Immune Response Following a Two-Dose Schedule of Bivalent HPV Vaccination among Girls and Boys. Front. Immunol. 2024, 15, 1327770. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guzun, N.; Ouakki, M.; Panicker, G.; Ionescu, I.G.; Mayrand, M.H.; Unger, E.R.; Sauvageau, C. Immune Response after One Dose of HPV Vaccine among Girls and Boys and the Impact of a Second Dose given after 3 or More Years. Vaccine 2025, 62, 127475. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guevara, A.; Cabello, R.; Woelber, L.; Moreira, E.D.; Joura, E.; Reich, O.; Shields, C.; Ellison, M.C.; Joshi, A.; Luxembourg, A. Antibody Persistence and Evidence of Immune Memory at 5 Years Following Administration of the 9-Valent HPV Vaccine. Vaccine 2017, 35, 5050–5057. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ewaisha, R.; Ruffin, M.T.; Williams, S.; Chung, Y.; DeGraffinreid, C.R.; Paskett, E.D.; Reiter, P.L.; Qiu, J.; Brenner, D.E.; Anderson, K.S. Serum Profiling of the Antibody Response to HPV in Women with or without Abnormal Cervical Cytology Undergoing Cervical Cancer Screening. Front. Immunol. 2025, 16, 1612761. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mauz, P.S.; Schäfer, F.A.; Iftner, T.; Gonser, P. HPV Vaccination as Preventive Approach for Recurrent Respiratory Papillomatosis—A 22-Year Retrospective Clinical Analysis. BMC Infect. Dis. 2018, 18, 343. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smahelova, J.; Hamsikova, E.; Ludvikova, V.; Vydrova, J.; Traboulsi, J.; Vencalek, O.; Lukeš, P.; Tachezy, R. Outcomes After Human Papillomavirus Vaccination in Patients With Recurrent Respiratory Papillomatosis. JAMA Otolaryngol.-Head Neck Surg. 2022, 148, 654. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lehtinen, M.; van Damme, P.; Beddows, S.; Pinto, L.A.; Mariz, F.; Gray, P.; Dillner, J. Scientific Approaches to Defining HPV Vaccine-Induced Protective Immunity. Int. J. Cancer 2025, 156, 1848–1857. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Herrin, D.M.; Coates, E.E.; Costner, P.J.; Kemp, T.J.; Nason, M.C.; Saharia, K.K.; Pan, Y.; Sarwar, U.N.; Holman, L.; Yamshchikov, G.; et al. Comparison of Adaptive and Innate Immune Responses Induced by Licensed Vaccines for Human Papillomavirus. Hum. Vaccines Immunother. 2014, 10, 3446–3454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tian, T.; Fu, L.; Lin, Y.-F.; Zou, H. Potential Role of Naturally Acquired Immunity against HPV in the Control of HPV Related Diseases. Lancet Reg. Health West. Pac. 2021, 13, 100220. [Google Scholar] [CrossRef] [Scilit] [PubMed]



| Author [Reference] | Year | Geographical Location | Methods/Cohort Size | Main Focus of the Study |
|---|---|---|---|---|
| Rosillon et al. [16] | 2019 | Netherlands | Cohort study, thousands of women near menopause | Natural immunity and protection against persistent infection |
| Yao et al. [17] | 2022 | China | Serological analysis, 978 unvaccinated women | Natural neutralizing vs. total IgG antibodies |
| Morais et al. [18] | 2023 | Canada | Seroprevalence assessment, 222 unvaccinated women | Baseline natural immunity and antibody types |
| Syrjänen et al. [19] | 2022 | Finland | Longitudinal serum analysis, 276 mother–infant pairs | Placental antibody transfer and early postnatal exposure |
| Porras et al. [20] | 2020 | Costa Rica | Large-scale trial, 7466 women, 10-year follow-up | Bivalent vaccine efficacy (1, 2, or 3 doses) |
| Watson-Jones et al. [21] | 2022 | Tanzania | Randomized trial, 950 participants, 2-year follow-up | Dose-sparing (1, 2, 3 doses) nonavalent vs. bivalent |
| Hoes et al. [22] | 2023 | Netherlands | Longitudinal monitoring (10 years), women aged 14–27 | Bivalent vaccine efficacy against persistent infections |
| Pruski et al. [23] | 2022 | Poland | Clinical assessment, 60 women (12 HPV+), 6-month follow-up | Nonavalent vaccine administration post-infection |
| Panwar et al. [24] | 2025 | United Kingdom | Comparative serosurveillance, 727 individuals | Immunogenicity of bivalent vs. quadrivalent vaccine |
| Steinberg et al. [25] | 2025 | USA (Alaska) | Prospective mixed cohort, 227 participants, 3-year follow-up | 2-dose nonavalent vaccine immunogenicity |
| D’Souza et al. [26] | 2023 | USA | Cross-sectional study, 1108 mixed-person cohort | Vaccine protection in high-sexual-exposure populations |
| Restrepo et al. [27] | 2023 | Multi-continental | Long-term follow-up (126 months), 1272 participants | Nonavalent vaccine impact on local lesions/persistence |
| Maldonado et al. [28] | 2022 | Canada, USA, Colombia | 10-year follow-up, 3253 participants (men and women) | Quadrivalent vaccine efficacy on genital lesions |
| Barnabas et al. [29] | 2022 | Kenya | Randomized trial, 2275 women, 6-month follow-up | Single-dose nonavalent/bivalent vs. control vaccine |
| Pruski et al. [30] | 2023 | Poland | Prospective study, 60 HPV+ patients | 9-valent vaccine combined with LEEP-conization |
| Smahelova et al. [31] | 2022 | Czechia | Clinical tracking (up to 5 years), 50 individuals with RRP | Quadrivalent vaccine for respiratory papillomatosis |
| Kitano et al. [32] | 2023 | Canada | Immunological assessment, 33 transplant/immunosuppressed | Quadrivalent vaccine immunogenicity in transplant recipients |
| HPV Type | Seropositivity Rate (%) | Notes |
|---|---|---|
| HPV 6 | 15.7 | Highest seropositivity rate among tested types |
| HPV 16 | 10.2 | Higher than HPV 18 |
| HPV 18 | — | Lower than HPV 16 (exact % not specified) |
| HPV 33 | 1.6 | Low seropositivity |
| HPV 58 | 3.1 | Low seropositivity |
| Antibody Type | Relative Abundance | Role in Malignancy Prevention |
|---|---|---|
| IgG anti-L1 | Most prevalent | Structural protein not directly linked to malignancy prevention |
| IgG anti-E7 | Moderate | Considered effective in preventing lesion malignancy |
| IgG anti-E6 | Rare | Also effective in preventing lesion malignancy |
| PROTECTION AND CROSS-REACTIVITY BY DOSE | 0 DOSES | 1 DOSE | 2 DOSES | 3 DOSES |
|---|---|---|---|---|
| HPV-6 | / | LOW | MODERATE | HIGH |
| HPV-11 | / | LOW | MODERATE | HIGH |
| HPV-16 | LOWEST | LOW | MODERATE | HIGH |
| HPV-18 | LOWEST | LOW | MODERATE | HIGH |
| HPV-31 | / | LOWEST | LOW | MODERATE |
| HPV-33 | / | LOWEST | LOW | MODERATE |
| HPV-45 | / | LOWEST | LOW | MODERATE |
| HPV-52 | / | LOWEST | LOW | MODERATE |
| HPV-58 | / | LOWEST | LOW | MODERATE |
| FOLLOW UP | NEUTRALISING ANTIBODY | NONAVALENT VACCINE | QUADRIVALENT VACCINE | BIVALENT VACCINE | p | |||
|---|---|---|---|---|---|---|---|---|
| MEAN | GMT | MEAN | GMT | MEAN | GMT | |||
| 1 MONTH | HPV-16 | 13,486 | 9545 | 8225 | 8222 | 8705 | 8702 | 0.5082 |
| HPV-18 | 7132 | 4583 | 4450 | 4449 | 7715 | 7685 | 0.0896 | |
| 6 MONTHS | HPV-16 | 4626 | 3580 | 7680 | 7612 | 10,129 | 9849 | <0.0001 |
| HPV-18 | 8737 | 7740 | 4360 | 4267 | 8357 | 8138 | 0.0004 | |
| 12 MONTHS | HPV-16 | 6359 | 4638 | 6812 | 4758 | 0.2482 | ||
| HPV-18 | 11,388 | 7181 | 4010 | 2271 | 0.0006 | |||
| HPV STRAIN | 6 Months After First Dose (N = 205) | 1 Month After Second Dose (N = 197) | 1 Year After Second Dose (N = 172) | 3 Years After Second Dose (N = 145) | ||||
|---|---|---|---|---|---|---|---|---|
| Seropositivity | GMC (UI/mL) | Seropositivity | GMC (UI/mL) | Seropositivity | GMC (UI/mL) | Seropositivity | GMC (UI/mL) | |
| 6 | 99% | 59 | 100% | 4535 | 100% | 469 | 100% | 220 |
| 11 | 99% | 42 | 100% | 3727 | 100% | 374 | 100% | 171 |
| 16 | >99% | 22 | 100% | 1781 | 100% | 219 | 100% | 94 |
| 18 | 94% | 13 | 100% | 635 | 96% | 62 | 96% | 27 |
| 31 | 99% | 26 | 100% | 1554 | 98% | 176 | 99% | 88 |
| 33 | 98% | 36 | 100% | 2540 | 99% | 274 | 100% | 123 |
| 45 | 85% | 8 | 100% | 462 | 95% | 45 | 92% | 25 |
| 52 | 99% | 96 | 100% | 2960 | 99% | 368 | 100% | 184 |
| 58 | 99% | 93 | 100% | 3483 | 100% | 435 | 100% | 207 |
| HPV TYPE | WOMEN | MEN | ||
|---|---|---|---|---|
| 1 Month After Dose 2 | 3 Years After Dose 2 | 1 Month After Dose 2 | 3 Years After Dose 2 | |
| HPV-16 | 6000 LU/mL | 482 LU/mL | 9069 LU/mL | Significantly higher |
| HPV-18 | 6606 LU/mL | 159 LU/mL | 4215 LU/mL | Significantly higher |
| STUDY GROUP | SEROPOSITIVITY RATE | ANTIBODY CONCENTRATION (MU/mL) |
|---|---|---|
| Control (N = 16) | 100% | 638.8–4391.6 |
| Liver transplant (N = 10) | 100% | 569.3–3097.3 |
| Kidney transplant (N = 7) | 50–75% | 8.6–42.4 |
| Feature | Naturally Acquired Immunity | Vaccine-Induced Immunity |
|---|---|---|
| Primary Immune Response | Dominated by cellular responses; slow, highly variable, and often incomplete seroconversion. | Coordinated robust humoral and cellular responses (activation of memory T and B cells); rapid and nearly 100% seroconversion. |
| Antibody Levels | Low and weak neutralizing antibody titers (typically 100–500 mMU/mL). | Significantly higher neutralizing IgG antibody titers (exceeding 3000–10,000 mMU/mL). |
| Duration of Protection | Short-lived; memory B-cell responses are suboptimal, leading to high reinfection rates (20–50%). | Highly durable; antibody levels stabilize into a long-term plateau, persisting for ≥15 years without the need for boosters. |
| Scope of Protection | Strictly type-specific (protects only against the infecting strain). | Broad protection against targeted high-risk and low-risk strains, with proven cross-protection against genetically related non-vaccine strains. |
| Clinical Efficacy | Unreliable; frequently insufficient to prevent initial infection, persistent infection, or progression to malignancy. | Consistently superior; provides 90–100% protection against high-grade lesions (e.g., CIN2+) and significantly reduces viral persistence even in already infected individuals. |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Ghilencea, B.; Moroianu, B.I.; Năstac, A.-I.; Bostan, I.-S.; Panaitescu, A.; Mehedințu, C.; Gică, N. Natural Versus Vaccine-Induced Immunity Against HPV: A Comparative Review of Antibody Response and Cancer Prevention. Antibodies 2026, 15, 61. https://doi.org/10.3390/antib15040061
Ghilencea B, Moroianu BI, Năstac A-I, Bostan I-S, Panaitescu A, Mehedințu C, Gică N. Natural Versus Vaccine-Induced Immunity Against HPV: A Comparative Review of Antibody Response and Cancer Prevention. Antibodies. 2026; 15(4):61. https://doi.org/10.3390/antib15040061
Chicago/Turabian StyleGhilencea, Bogdan, Bianca Ilinca Moroianu, Ancuța-Iuliana Năstac, Ioana-Stefania Bostan, Anca Panaitescu, Claudia Mehedințu, and Nicolae Gică. 2026. "Natural Versus Vaccine-Induced Immunity Against HPV: A Comparative Review of Antibody Response and Cancer Prevention" Antibodies 15, no. 4: 61. https://doi.org/10.3390/antib15040061
APA StyleGhilencea, B., Moroianu, B. I., Năstac, A.-I., Bostan, I.-S., Panaitescu, A., Mehedințu, C., & Gică, N. (2026). Natural Versus Vaccine-Induced Immunity Against HPV: A Comparative Review of Antibody Response and Cancer Prevention. Antibodies, 15(4), 61. https://doi.org/10.3390/antib15040061