


Simple Summary
Systemic mastocytosis (SM) is a clonal mast cell (MC) neoplasm driven by somatically acquired activating mutations in the KIT receptor tyrosine kinase (CD117), resulting in pathological accumulation of morphologically atypical MCs in extracutaneous organs. The KIT D816V substitution is detectable in over 95% of cases by high-sensitivity next-generation sequencing (NGS) or allele-specific PCR. The development of type I KIT inhibitors with selectivity for the D816V-mutant conformation has fundamentally restructured the therapeutic field of advanced SM. This review provides a thorough synthesis of SM pathobiology, WHO-defined diagnostic and classification criteria, validated prognostic tools, and the developing landscape of KIT-directed and combination therapies, with direct translational relevance for specialist practitioners managing this heterogeneous myeloid neoplasm.
Abstract
Background: Systemic mastocytosis (SM) is a clonal mast cell (MC) neoplasm driven by somatically acquired activating mutations in the KIT receptor tyrosine kinase (CD117), resulting in pathological accumulation of morphologically atypical MCs in extracutaneous organs. The KIT D816V substitution is detectable in over 95% of cases by high-sensitivity next-generation sequencing (NGS) or allele-specific PCR. This gain-of-function variant confers ligand-independent receptor autophosphorylation, leading to constitutive activation of downstream signaling cascades that promote MC progenitor survival, clonal expansion, and resistance to apoptosis. Co-occurring somatic mutations in TET2, SRSF2, ASXL1, CBL, and RUNX1, increasingly identified in the context of clonal hematopoiesis of indeterminate potential, are associated with more aggressive phenotypes and independently confer adverse prognostic impact. Results: The 2022 WHO classification delineates indolent forms from advanced-phase SM, aggressive SM, SM with an associated hematologic neoplasm (SM-AHN), and MC leukemia, which produce progressive end-organ damage through both neoplastic tissue infiltration and uncontrolled mediator release. Formal diagnosis requires integration of histological criteria (multifocal bone marrow MC aggregates of ≥15 cells), immunophenotypic aberrancies (CD25, CD2, and/or CD30 coexpression on MCs by flow cytometry or immunohistochemistry), biochemical markers (baseline serum tryptase ≥ 20 ng/mL), and molecular confirmation of KIT D816V or equivalent pathogenic KIT mutation. The development of type I KIT inhibitors with selectivity for the D816V-mutant conformation has fundamentally restructured the therapeutic field of advanced SM. Conclusions: This review provides a thorough synthesis of SM pathobiology, WHO-defined diagnostic and classification criteria, validated prognostic tools, and the developing landscape of KIT-directed and combination therapies, with direct translational relevance for specialist practitioners managing this heterogeneous myeloid neoplasm.
1. Introduction
Mastocytosis is a neoplastic disorder characterized by clonal mast cell (MC) accumulation in one or more organs. It is classified as cutaneous mastocytosis (CM), which is limited to the skin; systemic mastocytosis (SM), which involves extracutaneous organs with or without skin involvement; or the rare mast cell sarcoma (MSC) [1]. While both SM and mast cell activation syndrome (MCAS) present with overlapping symptoms due to mast cell mediator release, SM is a distinct clinical entity [2]. Idiopathic MCAS derives from hyperactivation of non-clonal mast cells and lacks the defining histopathological and molecular features of SM [3]. SM encompasses a heterogeneous clinical and biological spectrum rather than a single disease. Indolent SM (ISM) is the most prevalent form in adults and is associated with a near-normal prognosis. In contrast, aggressive SM (ASM), SM with associated hematological neoplasm (SM-AHN), and mast cell leukemia (MCL) are associated with increased morbidity and mortality [4]. A comprehensive understanding of the molecular basis, diagnostic modalities, subclassification, and therapeutic strategies is vital for specialist clinicians. Clonality in SM is established at the molecular and immunophenotypic level, typically by detecting a somatic activating KIT mutation (most often D816V) in lesional mast cells and/or by demonstrating an aberrant, disease-restricted mast cell immunophenotype (CD25 and/or CD2 co-expression) by flow cytometry or immunohistochemistry; X-chromosome inactivation (HUMARA) assays were used historically to demonstrate mast cell monoclonality before molecular methods became standard.
2. Pathophysiology
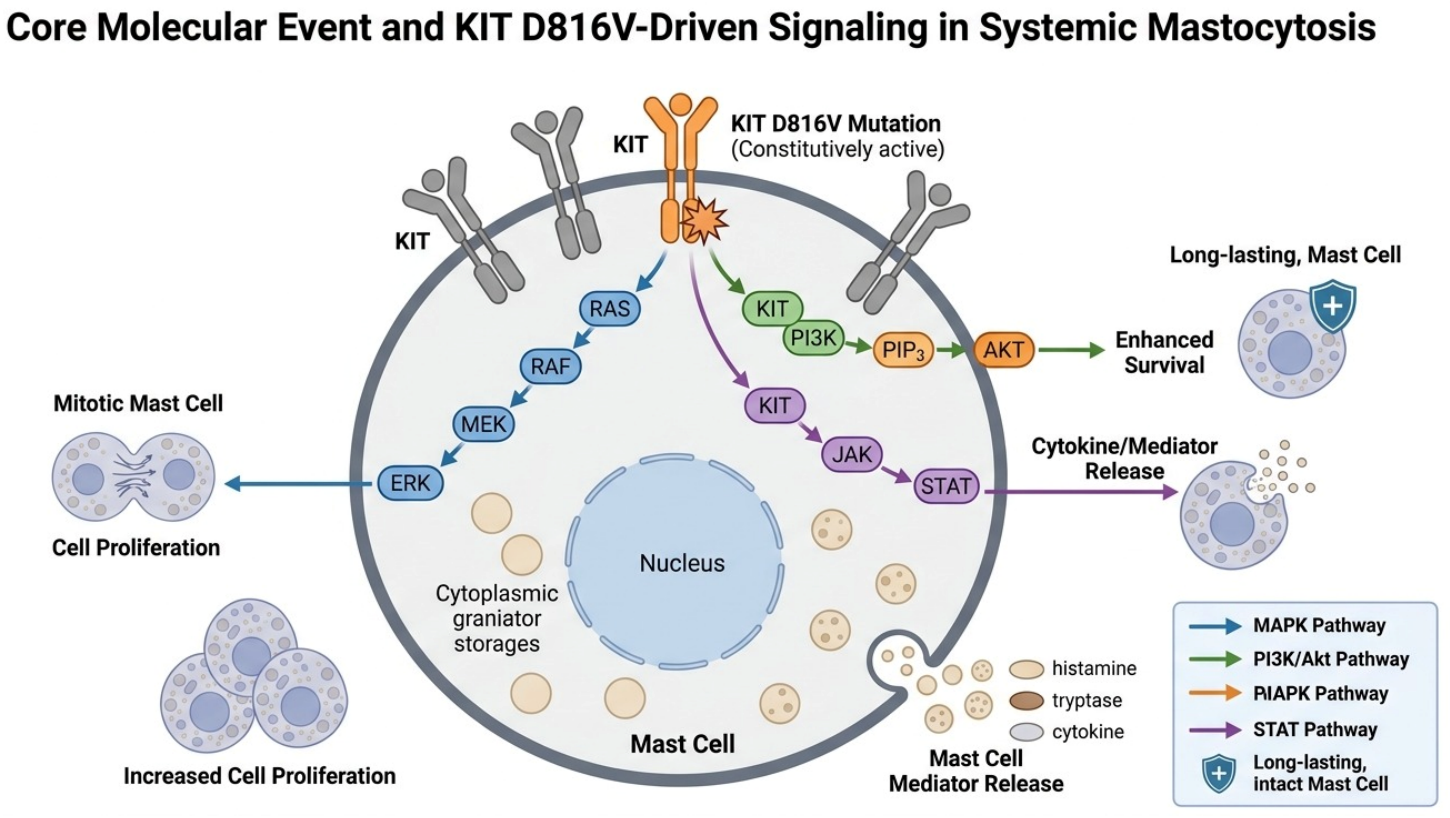
The central molecular event in SM is a somatic gain-of-function mutation in the KIT gene. KIT encodes the KIT receptor tyrosine kinase, also known as CD117 or stem cell factor receptor (Figure 1) [5]. KIT is the focus of SM pathobiology both because activating KIT mutations are the most frequent molecular abnormality in SM, present in over 90% of patients, and because KIT D816V was the first molecular lesion identified in SM and has since been shown to be necessary and sufficient to drive ligand-independent mast cell proliferation and survival, making it the central, disease-defining oncogenic driver rather than merely the most common incidental finding.
Figure 1.
Core Molecular Event and KIT D816V-Driven Signaling in Systemic Mastocytosis.
Under physiological conditions, stem cell factor (SCF) binds to KIT, activating the receptor and downstream signaling through the JAK/STAT, MAPK/ERK, PI3K/AKT, and PLCγ pathways. These pathways regulate mast cell proliferation, survival, and migration, each with a partially distinct contribution: JAK/STAT signaling drives proliferation and pro-survival gene transcription; MAPK/ERK signaling promotes proliferation and cytokine production; PI3K/AKT signaling supports survival by inhibiting apoptosis; and PLCγ signaling regulates degranulation and calcium-dependent mediator release. Over 90% of patients with mastocytosis harbor a KIT gene mutation, with the D816V substitution in exon 17 present in 85–90% of adults [6]. This mutation leads to ligand-independent receptor activation. The D816V substitution lies within the KIT activation loop (exon 17) and destabilizes the autoinhibited conformation of the kinase domain, locking the receptor in an active, ligand-independent state; this conformational shift alters the ATP-binding pocket relative to wild-type KIT. Consequently, first-generation tyrosine kinase inhibitors (TKIs) such as imatinib, which require the inactive conformation for high-affinity binding, are ineffective because they cannot bind the altered protein conformation, whereas type I inhibitors such as avapritinib and bezuclastinib were rationally designed to accommodate the active-state conformation. Constitutive KIT signaling promotes expansion of clonal mast cells, which accumulate in the bone marrow, liver, spleen, gastrointestinal tract, and other extracutaneous organs. This accumulation results in the release of vasoactive, proinflammatory, and fibrogenic mediators, including histamine, prostaglandin D2, heparin, tryptase, leukotrienes, and cytokines such as IL-6 and TNF, which together produce the systemic manifestations of SM [7,8].
Under normal physiological conditions, mast cells are tissue-resident innate immune cells that arise from bone marrow progenitors and mature locally in the skin, gastrointestinal tract, respiratory mucosa, and other organs. They contribute to host defense against parasites and certain bacteria, participate in IgE-mediated allergic responses, and play recognized roles in tissue remodeling, angiogenesis, and wound healing through the coordinated release of preformed and newly synthesized mediators. In SM, this normal physiological repertoire of mediator release is preserved but becomes pathologically amplified and dysregulated as a consequence of clonal mast cell expansion, explaining why SM manifests principally as an exaggeration of otherwise physiological mast-cell-driven processes.
Chronic and episodic release of mast cell mediators results in a broad spectrum of symptoms, some of which are debilitating [9]. Cutaneous manifestations, primarily attributable to histamine, include pruritus, urticaria, flushing, and angioedema. Gastrointestinal symptoms, such as abdominal cramping, nausea, vomiting, and diarrhea, arise from the actions of histamine and prostaglandins on the gut mucosa. Cardiovascular instability, presenting as presyncope, tachycardia, and anaphylaxis, is mediated by vasodilatory and anaphylactogenic substances. Neurocognitive symptoms, including cognitive impairment, poor concentration, and headaches, are also recognized, although their basic mechanisms remain incompletely understood.
In advanced stages, mast cell infiltration of organs leads to structural damage that is independent of mediator-related symptoms [10]. Complications may include cytopenias due to bone marrow infiltration, hepatosplenomegaly, portal hypertension, and osteoporosis. Bone involvement results from both direct mast cell invasion and the inhibitory effects of heparin on osteoblast function. While all SM subtypes negatively affect quality of life, advanced disease has the greatest impact.
3. Clinical Presentation and Differential Diagnosis
Before comparing age-related presentations, it is important to distinguish clearly between cutaneous mastocytosis (CM) and systemic mastocytosis (SM). CM is confined to the skin, with no histological or molecular evidence of extracutaneous mast cell infiltration, and it predominates in children. SM, by definition, requires demonstration of clonal mast cell involvement in one or more extracutaneous organs (most often the bone marrow) fulfilling the WHO/ICC diagnostic criteria detailed in Section 4, and it predominates in adults. Because Table 1 compares the typical mastocytosis phenotype across age groups, it necessarily contrasts predominantly cutaneous pediatric-onset disease with predominantly systemic adult-onset disease, rather than CM versus SM within a single age group.
Table 1.
Pediatric- vs. Adult-Onset Mastocytosis.
SM in adults and children is a different entity (Table 1) [11].
In adults, indolent SM (ISM) is the most common form. It is chronic and does not resolve. In adults, small monomorphic maculopapules, known as urticaria pigmentosa, are present in over 80% of cases on the thighs and trunk [11]. The Darier sign—whealing and erythema after stroking the lesion—is usually present. Serum tryptase is usually above 20 µg/L in most adults, and KIT D816V is found in 85–90% of cases [6]. Pediatric mastocytosis is very different. Cutaneous mastocytosis is most common and usually does not involve systemic organs. The disease frequently resolves spontaneously before adulthood, an observation attributed to the predominantly non-D816V, often non-KIT-restricted mutational profile of pediatric skin mast cells, a lower overall mast cell burden confined to the skin, and a presumed self-limited proliferative process during childhood rather than a persistent clonal bone marrow-derived neoplasm as seen in adult SM. Skin lesions are polymorphic and may affect the head and extremities. Tryptase is usually under 20 µg/L. KIT mutations are less common and more varied. Anaphylaxis occurs in under 10% of children, which is much lower than in adults (about 50%) [12].
SM presents with episodic and multisystem symptoms. This results in a wide differential diagnosis, and clinicians must consider other mast cell disorders, such as monoclonal and idiopathic MCAS, as well as systemic anaphylaxis from other causes [13]. Other conditions can have similar symptoms (Table 2).
Table 2.
Differential Diagnosis.
A complete assessment is required to differentiate SM from other conditions presenting with similar symptoms. Diagnostic assessment should include measurement of serum tryptase, skin biopsy when indicated, and bone marrow examination.
4. Diagnostic Approach
SM should be suspected in adults presenting with recurrent mast cell mediator release symptoms or anaphylaxis of unexplained etiology, particularly in the setting of a persistently elevated baseline serum tryptase [14]. Adult-onset urticaria pigmentosa confirmed on skin biopsy constitutes an independent indication for further investigation. A baseline serum tryptase ≥ 20 ng/mL, in the absence of chronic renal impairment or concomitant myeloid neoplasm, both of which can independently elevate tryptase, warrants bone marrow evaluation to exclude SM. It is important to note, however, that tryptase thresholds carry imperfect sensitivity: approximately 15% of SM patients present with levels below 20 ng/mL, and up to 10% have values within the normal reference range, underscoring the need for integrating clinical, histological, and molecular criteria rather than relying on biomarker thresholds alone. Hereditary alpha-tryptasemia (HαT), caused by germline duplications or multiplications of the TPSAB1 gene encoding α-tryptase, is the most frequent cause of a persistently elevated baseline serum tryptase in the general population and must be considered whenever tryptase is elevated, independent of SM [14]. Because HaT can raise baseline tryptase irrespective of mast cell burden and may co-occur with SM, assessment of the underlying TPSAB1 genotype improves the sensitivity and specificity of tryptase-based diagnostic thresholds and is recommended when an elevated tryptase does not otherwise fit the clinical picture.
The WHO 5th Edition [15] and the International Consensus Classification (ICC) [16] define SM diagnosis using major and minor criteria (Table 3). WHO diagnosis requires one major plus at least one minor criterion. ICC requires one major or three or more minor criteria. The ≥15 mast cell aggregate threshold for the major criterion and the associated minor criteria thresholds were empirically derived and iteratively refined through consensus by the WHO and ECNM working groups on the basis of comparative histopathological and outcome data distinguishing SM from reactive mast cell hyperplasia and from CM [15,17]; they are not derived from a single index study but represent an evolving consensus standard periodically re-validated as diagnostic experience accumulates.
Table 3.
Diagnostic Criteria for Systemic Mastocytosis.
When SM is suspected, several steps are needed. These include bone marrow biopsy with MC immunophenotyping and molecular testing for KIT D816V. Additional KIT sequencing is done if required. In KIT D816V-negative patients with eosinophilia, screen for the FIP1L1::PDGFRA fusion.
Real-world diagnosis is often complicated by atypical presentations that do not fit the classic profile. A meaningful minority of patients with confirmed SM have a normal baseline serum tryptase, particularly in BMM and in some ISM cases with low mast cell burden, so a normal tryptase does not exclude SM in a patient with a compatible clinical picture. Similarly, mast cells can show an atypical immunophenotype (e.g., weak or absent CD25 expression) in a subset of patients, and bone marrow mast cell aggregates can be sparse or spindle-shaped rather than the classic round, atypical morphology, increasing the risk of a false-negative biopsy if an experienced hematopathologist is not involved. In such atypical cases, repeat or multisite bone marrow sampling, sensitive allele-specific KIT D816V PCR performed on peripheral blood or bone marrow, and correlation with clinical mediator-release symptoms and imaging are recommended before SM can be confidently excluded.
5. Disease Classification and Subtyping
Accurate subclassification is essential (Table 4) [17]. It determines prognosis and guides treatment. SM is either non-advanced or advanced based on B- and C-findings. B-findings indicate worsening SM, but no organ damage yet. They include a high mast cell burden, signs of myeloproliferation and/or myelodysplasia in a non-mast-cell lineage not fulfilling criteria for an associated hematologic neoplasm (AHN), enlarged liver, enlarged spleen, or swollen lymph nodes. C-findings mean SM has caused organ damage. These signs include low blood counts due to mast cell infiltration of the bone marrow, an enlarged and poorly functioning liver, difficulty absorbing nutrients, bone breakdown with fractures, or a very large spleen that lowers blood cell counts.
Table 4.
Identifying Systemic Mastocytosis Subtypes.
Differentiating between non-advanced and advanced SM is critical for guiding treatment decisions. Patients with ISM or SSM are initially managed with antimediator therapy, and, more recently, selective KIT inhibition has been introduced for symptom control. In contrast, patients with advanced SM require cytoreductive therapy to reduce mast cell burden.
6. Therapies for Systemic Mastocytosis
For many patients with indolent SM, symptom-directed antimediator therapy (Section 13) provides adequate long-term disease control, and pharmacologic cytoreduction is not required. The discussion that follows focuses on KIT-directed targeted therapies, which are the mainstay for advanced SM and are increasingly used in indolent or smoldering SM when symptoms remain uncontrolled despite optimized antimediator treatment.
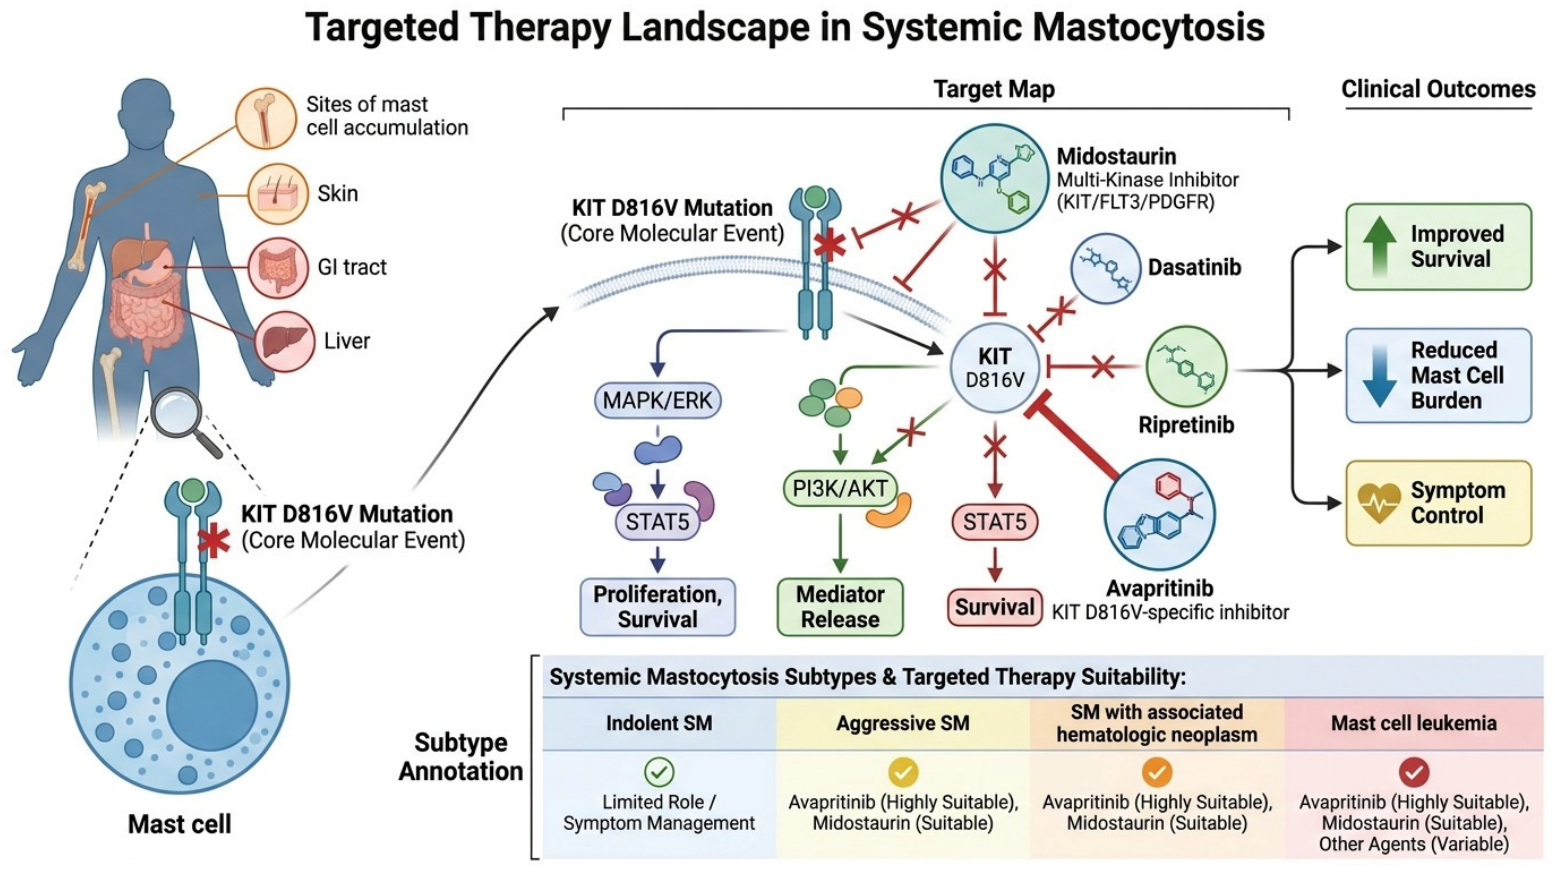
The therapeutic field of systemic mastocytosis (SM) has been fundamentally transformed by the molecular characterization of the KIT D816V somatic mutation, which is present in over 90% of cases and constitutively activates KIT signaling, driving neoplastic mast cell proliferation and survival [18] (Figure 1). This discovery established the rationale for selective kinase inhibition as the central therapeutic strategy in advanced SM (Figure 2) (Table 5).
Figure 2.
Targeted Therapy in Systemic Mastocytosis.
Table 5.
KIT-Targeted Tyrosine Kinase Inhibitors in Systemic Mastocytosis.
7. Midostaurin
Midostaurin (PKC412) was the first targeted agent globally approved for advanced SM, including aggressive SM (ASM), SM with associated hematologic neoplasm (SM-AHN), and mast cell leukemia (MCL) [36,37]. As a multikinase inhibitor active against KIT D816V, FLT3, PDGFR, and VEGFR, midostaurin demonstrated meaningful reductions in mast cell burden, serum tryptase levels, splenomegaly, and symptom severity in the pivotal CPKC412D2201 trial, achieving an overall response rate of approximately 60% in advanced SM [20]. Its approval represented a paradigm shift from purely cytoreductive or symptomatic approaches toward mutation-targeted therapy [38]. In the pivotal open-label CPKC412D2201 trial, 116 patients with advanced SM (aggressive SM, SM-AHN, and MCL) received midostaurin 100 mg twice daily; the overall response rate by prespecified criteria was approximately 60%, with responses observed across all three advanced subtypes, and median overall survival exceeded two years in responders [20]. The most common adverse events were low-grade gastrointestinal toxicities—nausea, vomiting, and diarrhea—occurring in the majority of patients and generally manageable with antiemetics and dose modification; myelosuppression and hepatotoxicity were also reported and required monitoring [20,38]. Ten-year median follow-up confirmed durable responses in a subset of patients without new safety signals [37]. Unlike avapritinib, midostaurin is a multikinase inhibitor with only modest selectivity for KIT D816V, which underlies its broader off-target toxicity profile but does not require the REMS-type monitoring associated with more potent, selective type I inhibitors.
8. Imatinib
Imatinib retains a narrow but defined role in the rare subset of SM patients lacking the KIT D816V mutation, particularly those harboring wild-type KIT or transmembrane/juxtamembrane domain mutations, where it can achieve meaningful responses [19]. It has no meaningful activity against KIT D816V and is not appropriate for most SM patients.
9. Avapritinib
Avapritinib is a selective, potent inhibitor of KIT D816V (and PDGFRA D842V) that has changed the treatment framework for SM [39]. Unlike imatinib, avapritinib was specifically designed to bind the activated conformation of the mutant KIT kinase domain, overcoming the structural barrier to inhibition posed by the D816V substitution. In advanced SM, avapritinib showed strong responses in the phase II PATHFINDER trial [21,22]. Across all advanced SM subtypes, it produced sustained reductions in mast cell burden, serum tryptase, and KIT D816V variant allele frequency (VAF), with overall response rates well above prior standards of care.
The pivotal phase II/III PIONEER trial (N = 212) evaluated avapritinib 25 mg daily versus placebo in patients with ISM and moderate-to-severe symptom burden (Total Symptom Score ≥ 28) despite two or more antimediator drugs [23]. Key findings at 24 weeks included Total Symptom Score reduction of ≥50%: 25% of avapritinib-treated patients vs. 10% with placebo (p = 0.005); serum tryptase reduction ≥ 50%: 54% vs. 0% (p < 0.001); KIT D816V VAF reduction ≥50%: 68% vs. 6% (p < 0.001); and bone marrow mast cell burden reduction ≥50%: 53% vs. 23% (p < 0.001). Avapritinib also produced meaningful reductions in skin lesion area across multiple body regions at 24 weeks, with mean reductions ranging from approximately 31% to 57%, compared with minimal change with placebo. Long-term data from the PIONEER open-label extension (data cutoff: September 2024) demonstrate durable and deepening benefit: the mean Total Symptom Score change from baseline was −17.51 at Week 96 and −20.07 at Week 144 [24]. Improvements were seen across gastrointestinal, skin, and neurocognitive symptom domains, with parallel improvements in mastocytosis-specific quality-of-life scores.
Avapritinib is generally well tolerated in ISM at the approved 25 mg daily dose [23,24]. The most common adverse reactions (≥10% incidence in ISM) are periorbital/eye edema, dizziness, peripheral edema, and flushing. In advanced SM at higher doses, edema, diarrhea, nausea, and fatigue/asthenia are more prominent (≥20% incidence). Key warnings and precautions include intracranial hemorrhage, observed in 2.9% of patients with GIST or advanced SM in clinical trials; no events occurred in ISM patients in PIONEER. Fatal events were reported in <1% of trial participants overall. Cognitive effects are dose-dependent and generally reversible on withholding or reducing the drug. Patients should be advised to avoid direct UV exposure. Embryofetal toxicity: effective contraception is mandatory. Per guidelines, cladribine and tyrosine kinase inhibitors are not recommended during pregnancy.
10. Investigational KIT Inhibitors
Two additional selective KIT inhibitors are in advanced clinical development and show notable promise.
The SUMMIT clinical trial is a multi-part, randomized, double-blind, placebo-controlled Phase 2 study evaluating bezuclastinib in patients with indolent or smoldering systemic mastocytosis whose symptoms remain uncontrolled by best supportive care [31,32]. Treatment with a 100 mg dose demonstrated rapid, clinically meaningful, and durable reductions in overall patient symptom severity [31,32]. These improvements were measured by the validated Mastocytosis Symptom Severity Daily Diary (MS2D2) scale. Patients experienced significant and deep reductions in standard diagnostic markers of mast cell burden [32]. This includes dramatic drops in serum tryptase levels, bone marrow mast cell burden, and KIT D816V variant allele frequency (VAF). The APEX clinical trial is an open-label, registration-directed Phase 2 study targeting life-threatening subtypes of SM, including aggressive SM (ASM), SM with an associated hematologic neoplasm (SM-AHN), and mast cell leukemia (MCL) [33,34]. Long-term data from the trial demonstrated a 24-month progression-free survival (PFS) rate of 82% alongside objective reductions in total disease burden [33,34]. Most treatment-emergent adverse events were low-grade, highly manageable, and reversible. Common mild side effects included hair color changes, alterations in taste (dysgeusia), nausea, and transient elevations in liver enzymes. Unlike older-generation TKIs, bezuclastinib distinguishes itself through precise structural engineering [35]. It avoids off-target inhibition of closely related kinases such as PDGFRα, PDGFRβ, and CSF1R. Sparing these pathways markedly decreases the likelihood of toxicities like severe edema, pleural effusions, and bleeding events. Bezuclastinib was designed specifically not to cross the blood–brain barrier [35]. This low central nervous system penetration successfully eliminates the severe cognitive impairments and intracranial hemorrhage risks associated with alternative agents like avapritinib.
Elenestinib (BLU-263) is a novel, investigational, oral, next-generation tyrosine kinase inhibitor that potently and selectively inhibits KIT D816V with limited central nervous system penetration and pharmacokinetics that support once-daily dosing [25,26,27]. HARBOR is a randomized, double-blind, placebo-controlled, Phase 2/3 study comparing the efficacy and safety of elenestinib + symptom-directed therapy (SDT) with placebo + SDT in participants with ISM whose symptoms are not adequately controlled by SDT [29,30]. Part 1 was a double-blind, placebo-controlled, dose-finding study that enrolled adult patients with centrally confirmed ISM per WHO criteria and moderate-to-severe symptoms, defined as an ISM Symptom Assessment Form (ISM-SAF) total symptom score (TSS) of at least 28. Patients were randomly assigned to receive placebo plus best supportive care (BSC), elenestinib at 25 mg/day plus BSC, elenestinib at 50 mg/day plus BSC, or elenestinib at 100 mg/day plus BSC. The primary endpoints of Part 1 were safety and pharmacokinetics/pharmacodynamics. Elenestinib at all tested doses demonstrated beneficial effects on disease-related symptoms and biomarkers of mast cell burden in a large, maturing cohort of patients with ISM and moderate-to-severe symptom burden. Key eligibility criteria for Part 2 include an ISM diagnosis and ISM-SAF TSS ≥ 28 at screening. Endpoints include mean change in ISM-SAF TSS from baseline to Week 48 (primary endpoint), achievement of controlled disease (defined as mild TSS), changes in serum tryptase, KIT D816V variant allele fraction, bone mineral density, anaphylaxis rate, and safety. Part 2 of HARBOR is ongoing and will deliver the definitive randomized efficacy data, with a particular focus on symptom burden, mast cell biomarkers, bone density, and anaphylaxis reduction [29,30].
Comparative structural selectivity. Avapritinib and bezuclastinib both potently inhibit KIT D816V but differ meaningfully in their kinase selectivity and pharmacologic consequences. Avapritinib is a type I inhibitor that also retains substantial activity against PDGFRA D842V and wild-type KIT/PDGFR family members, and it is brain-penetrant; this broader activity and CNS exposure likely contribute to its efficacy across advanced SM subtypes but are also mechanistically linked to its principal toxicities, including intracranial hemorrhage risk and cognitive effects. Bezuclastinib was engineered for greater structural selectivity for mutant KIT D816V over closely related kinases such as PDGFRα, PDGFRβ, and CSF1R and was designed to have low CNS penetration; this narrower off-target profile is associated with a lower observed incidence of edema, effusions, bleeding, and cognitive adverse events in early trials, though cross-trial comparisons are limited by differing patient populations and endpoints, and head-to-head data are not yet available.
11. Emerging and Combined Strategies
The recognition that SM frequently co-occurs with clonal hematologic neoplasms—and that additional somatic mutations (TET2, SRSF2, ASXL1, RUNX1) confer prognostic significance and may mediate resistance—has prompted interest in combination regimens [30,40]. Trials exploring avapritinib or bezuclastinib in combination with venetoclax, azacitidine, or ruxolitinib are ongoing, aiming at deeper and more durable eradication of the neoplastic clone [41,42]. Allogeneic stem cell transplantation remains the only potentially curative modality in eligible patients with aggressive SM or SM-AHN, though its role is being reassessed in the era of highly effective KIT inhibitors [43].
Co-occurring somatic mutations. Beyond KIT D816V, mutations in TET2, SRSF2, ASXL1, CBL, and RUNX1—genes classically associated with clonal hematopoiesis and myeloid neoplasms—are detected in a substantial proportion of patients with SM, particularly SM-AHN and other advanced subtypes, and are markedly less frequent in ISM. TET2 and SRSF2 mutations are the most common of this group, and while individually associated with a modest prognostic effect, their co-occurrence with ASXL1 and/or RUNX1 mutations (the so-called S/A/R/T genotype when combined with SRSF2) identifies a subset of patients with shorter overall and progression-free survival independent of the SM subtype itself. Mechanistically, these mutations are thought to arise in a hematopoietic progenitor upstream of or independent from the KIT D816V-mutant mast cell clone, contributing to myelodysplastic and myeloproliferative features of SM-AHN and potentially to resistance to KIT-selective inhibition, which targets the mast cell compartment but does not eradicate a co-occurring myeloid clone. Screening for these mutations by targeted next-generation sequencing myeloid panels at diagnosis is therefore recommended in suspected advanced SM to refine prognosis and to identify patients who may benefit from combination strategies or earlier consideration of allogeneic transplantation.
12. Cytoreductive Therapy: The Pre-Targeted Era
Prior to the advent of selective KIT inhibitors, cytoreductive therapy for advanced SM relied on agents offering limited and often short-lived clinical benefit at the cost of significant toxicity [44]. Interferon-α (with or without corticosteroids) and cladribine (2-CdA) were the mainstays, achieving partial responses in some patients—primarily reductions in splenomegaly, mast cell burden, and symptom severity—but rarely inducing deep molecular remission. Hydroxyurea provided modest cytoreduction in slower-proliferating disease. These agents remain relevant in specific scenarios: rapid debulking requirements, resource-constrained settings, or intolerance to approved targeted therapies, but they have been largely supplanted by molecularly targeted approaches in eligible patients.
13. Stepwise Antimediator Therapy
Regardless of SM subtype, symptomatic management of mast cell mediator release forms the essential foundation of treatment and should be initiated in all patients before escalating to cytoreductive or targeted approaches (Table 6) [45,46,47,48].
Table 6.
Treatment for Mast Cell Mediator-Related Symptoms.
First-line antimediator therapy centers on combined H1 antihistamines (cetirizine, loratadine, hydroxyzine) and H2 antihistamines (famotidine, ranitidine) to control cutaneous manifestations, urticaria, flushing, pruritus, and gastrointestinal symptoms, including cramping, nausea, and diarrhea. Second-line agents address refractory or multisystem symptoms: cromolyn sodium stabilizes mast cell degranulation along the gut mucosa and reduces systemic mediator burden; proton pump inhibitors manage acid hypersecretion and upper GI complications; and leukotriene receptor antagonists (montelukast) provide additional control of bronchospasm and flushing refractory to antihistamine monotherapy. Prevention and management of anaphylaxis are critical priorities for all SM patients. All patients must always carry two epinephrine auto-injectors, given the unforeseeable and potentially fatal nature of anaphylactic events. Venom immunotherapy is indicated where Hymenoptera sensitization is identified. In refractory or recurrent anaphylaxis, omalizumab (anti-IgE, off-label) has demonstrated success in reducing anaphylactic episodes and mediator-related symptom burden, particularly in patients with elevated baseline IgE or concomitant allergic sensitization. Corticosteroids, systemic or topical, may provide benefit in refractory cutaneous disease, malabsorption syndromes, and ascites refractory to other measures, though chronic use is limited by well-established adverse effects. Bisphosphonates (zoledronic acid preferred) and vitamin D/calcium supplementation address osteoporosis driven by heparin and tryptase release from infiltrating mast cells.
14. Expert Opinion
Systemic mastocytosis is a complex mast cell neoplasm that requires a strong index of suspicion for timely diagnosis and appropriate referral to dedicated centers. The heterogeneity of clinical presentations, ranging from indolent to aggressive forms, confirms the importance of a multidisciplinary approach to management. Treatment remains adapted to disease burden and symptom profile. Antimediator therapies address symptomatic relief, while cytoreductive strategies target the underlying neoplastic process. The identification of KIT mutations, particularly KIT D816V, as central drivers of SM pathophysiology has paved the path for a new generation of precision therapies. Selective KIT inhibitors represent a significant advance in the field of treatment, offering the opportunity to modify the disease course rather than merely manage symptoms. Given the chronicity of the disease and the complexity of its management, patients with SM often require concurrent and evolving treatment regimens. Clear, ongoing communication between patients and care providers is therefore not a secondary consideration but a keystone of quality care. Making sure that patients understand their condition, therapeutic options, and the rationale for therapy modifications directly contributes to adherence and outcomes. As the therapeutic armamentarium continues to expand, early referral to expert centers and incorporation of emerging targeted agents will be critical to improving prognosis and quality of life for people living with systemic mastocytosis.
The diagnostic workup should adhere to WHO criteria, incorporating bone marrow biopsy with immunohistochemistry (CD117, CD25, CD2 expression), KIT D816V mutational analysis in peripheral blood and bone marrow, and serum tryptase measurement, recognizing that a baseline tryptase ≥ 20 ng/mL is itself one of the four minor diagnostic criteria and a surrogate marker of mast cell burden. Once diagnosis is confirmed, categorization into ISM, smoldering SM (SSM), SM with an associated hematologic neoplasm (SM-AHN), aggressive SM (ASM), or mast cell leukemia (MCL) is critical to determine prognosis and treatment intensity and should be performed in centers with documented expertise in mast cell diseases.
From a clinical management standpoint, referral to a specialized center is not simply recommended but strongly advocated by current international guidelines, including those from the European Competence Network on Mastocytosis (ECNM) and the American Initiative in Mast Cell Diseases (AIM) [11,15]. This is particularly relevant given data from patient surveys, which indicate that diagnostic responsibility is distributed across multiple specialties: hematology/oncology in approximately 32–34% of cases and allergy/immunology in 18–20% [9], highlighting the fragmented and often delayed diagnostic journey patients experience. At the specialized center level, a structured multidisciplinary team should include hematologists, allergists/immunologists, dermatologists, gastroenterologists, endocrinologists, and psychiatrists, each involved in the management of the distinct but interconnected comorbidities that define the clinical complexity of SM.
Mediator-related symptoms, including flushing, urticaria, pruritus, abdominal cramping, diarrhea, and episodic hypotension, are present in most SM patients and represent a main cause of impaired quality of life. Bone disease represents another frequently underdiagnosed comorbidity that requires systematic evaluation and active management [49]. SM-associated osteoporosis is driven by the direct osteolytic effects of mast cell mediators, including histamine, heparin, and various cytokines, and is further potentiated by modifiable risk factors such as vitamin D deficiency, obesity, sedentary lifestyle, and prolonged corticosteroid use. A baseline DXA scan is mandatory in all SM patients at diagnosis, with follow-up assessments guided by clinical risk stratification. Vitamin D supplementation should be initiated in all patients with a deficiency. For patients with high-risk osteopenia (T score approaching −2) or overt osteoporosis (T score ≤ −2), bisphosphonate therapy constitutes the standard of care; in cases refractory to bisphosphonates, a RANK inhibitor (denosumab) represents a valid alternative. Low-dose interferon-alpha (IFN-α) may be considered in selected patients with severe SM-related bone disease unresponsive to conventional therapies. Weight management, dietary optimization, and individualized physical activity programs should be integrated into the management of all SM patients with obesity or sedentary behavior, covering both osteoporosis risk and general metabolic health.
Psychiatric comorbidities, particularly depression and anxiety, are highly prevalent in SM and are substantially underrecognized in routine clinical practice. The chronic variability of anaphylaxis, the persistent burden of mediator symptoms, and the mental health impact of living with a rare and often misunderstood disease contribute to considerable mental health morbidity. Formal psychiatric evaluation and antidepressant therapy should be considered early in the clinical course, with integration of psychiatric support into the MDT framework. Similarly, hepatosplenomegaly and lymphadenopathy, when present, require gastroenterological and hematological assessment, with imaging and, where appropriate, liver biopsy, given the possibility to signal more advanced or aggressive disease.
The systematic assessment of symptom burden and health-related quality of life (HRQoL) using validated patient-reported outcome measures is a clinical imperative, not an optional add-on. The Mastocytosis Quality of Life Questionnaire (MQLQ) and the Mastocytosis Symptom Assessment Form (MSAF) provide structured, reproducible frameworks for covering the full spectrum of SM-related morbidity across domains, including skin symptoms, mediator release episodes, fatigue, and psychological health [49,50]. These instruments should be administered at baseline and at regular follow-up intervals, as longitudinal trends in scores inform treatment escalation decisions and serve as objective metrics for evaluating therapeutic response, including response to novel targeted therapies such as midostaurin and avapritinib in advanced SM.
Finally, shared decision-making must be recognized as an integral clinical competency in SM management. The complexity of treatment choices demands that clinicians actively involve patients, transparently communicate the benefits and harms of available options, and anchor decisions in individual patient values and preferences. Living well with SM requires not only pharmacological expertise but also a sustained partnership between the patient and a coordinated, compassionate, and knowledgeable multidisciplinary team.
15. Conclusions
Systemic mastocytosis has evolved from a poorly understood clinical curiosity into a molecularly defined myeloid neoplasm with a clear central driver, KIT D816V, and an increasingly precise diagnostic and therapeutic framework. The 2022 WHO and ICC classifications now allow clinicians to integrate histological, immunophenotypic, biochemical, and molecular criteria into a reproducible diagnosis and to stratify patients into non-advanced and advanced subtypes that carry markedly different prognoses and treatment intensities. This precision has been matched on the therapeutic side: the field has progressed from non-selective cytoreductive agents and the multikinase inhibitor midostaurin toward rationally designed, selective type I KIT D816V inhibitors—avapritinib and the next-generation agents bezuclastinib and elenestinib—that achieve deeper and more durable disease control with more favorable safety profiles. At the same time, symptom-directed antimediator therapy remains the foundation of care for most patients with indolent disease, and recognition of co-occurring myeloid mutations (TET2, SRSF2, ASXL1, RUNX1) is reshaping how advanced SM and SM-AHN are risk-stratified and treated, including growing interest in rational combination regimens and, in eligible patients, allogeneic stem cell transplantation. Important gaps remain: diagnosis is still missed or delayed in patients with atypical presentations (normal tryptase, atypical immunophenotype, or coexisting hereditary alpha-tryptasemia), head-to-head comparisons between the newer KIT inhibitors are lacking, and the long-term impact of clonal co-mutations on resistance to KIT-selective therapy is not yet fully defined. Addressing these gaps will require continued collaboration between hematologists, allergists, dermatologists, and pathologists, ideally within the expert-center networks (ECNM, AIM) that already coordinate much of the clinical and translational research in this field. For the practicing clinician, the essential takeaway is that systemic mastocytosis is now a treatable, molecularly targetable disease, and that early recognition, accurate subclassification, and timely referral are what translate this scientific progress into better outcomes for patients.
Author Contributions
Conceptualization, C.A. and M.M.; methodology, C.A., M.P., and M.M.; writing—original draft preparation, C.A., M.P. and M.M.; writing—review and editing, C.A., M.B.G., G.P. (Gaetana Porto), G.P. (Giorgia Policastro), E.B., G.U., L.G., M.P. and M.M.; visualization, C.A. and M.M.; supervision, M.M.; project administration, M.P. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
| 2-CdA | cladribine |
| AE | adverse event |
| AIM | American Initiative in Mast Cell Diseases |
| AML | acute myeloid leukemia |
| ASM | aggressive systemic mastocytosis |
| AHN | associated hematologic neoplasm |
| AdvSM | advanced systemic mastocytosis |
| BID | twice daily |
| BM | bone marrow |
| BMM | bone marrow mastocytosis |
| BSC | best supportive care |
| CBL | Casitas B-lineage lymphoma proto-oncogene |
| CHIP | clonal hematopoiesis of indeterminate potential |
| CM | cutaneous mastocytosis |
| CNS | central nervous system |
| CR | complete remission |
| DXA | dual-energy X-ray absorptiometry |
| ECNM | European Competence Network on Mastocytosis |
| FLT3 | FMS-like tyrosine kinase 3 |
| HRQoL | health-related quality of life |
| HαT | hereditary alpha-tryptasemia |
| IBD | inflammatory bowel disease |
| IBS | irritable bowel syndrome |
| ICC | International Consensus Classification |
| IFN-α | interferon-alpha |
| ISM | indolent systemic mastocytosis |
| ISM-SAF | Indolent Systemic Mastocytosis Symptom Assessment Form |
| LABA | long-acting beta-agonist |
| MC | mast cell |
| MCAS | mast cell activation syndrome |
| MCL | mast cell leukemia |
| MDT | multidisciplinary team |
| MDS | myelodysplastic syndrome |
| mIWG | modified International Working Group |
| MPN | myeloproliferative neoplasm |
| MQLQ | Mastocytosis Quality of Life Questionnaire |
| MSC | mast cell sarcoma |
| MSAF | Mastocytosis Symptom Assessment Form |
| NGS | next-generation sequencing |
| NonAdvSM | non-advanced systemic mastocytosis |
| ORR | overall response rate |
| OS | overall survival |
| PCR | polymerase chain reaction |
| PDGFR | platelet-derived growth factor receptor |
| QD | once daily |
| QoL | quality of life |
| RANK | receptor activator of nuclear factor kappa-B |
| SCF | stem cell factor |
| SDM | shared decision-making |
| SDT | symptom-directed therapy |
| SM | systemic mastocytosis |
| SM-AHN | systemic mastocytosis with associated hematologic neoplasm |
| SSM | smoldering systemic mastocytosis |
| TEAE | treatment-emergent adverse event |
| TPSAB1 | tryptase alpha/beta 1 gene |
| TSS | total symptom score |
| VAF | variant allele frequency |
| VEGFR | vascular endothelial growth factor receptor |
| WHO | World Health Organization |
References
- Akin, C.; Siebenhaar, F.; Wechsler, J.B.; Youngblood, B.A.; Maurer, M. Detecting Changes in Mast Cell Numbers Versus Activation in Human Disease: A Roadblock for Current Biomarkers? J. Allergy Clin. Immunol. Pract. 2024, 12, 1727–1737. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hamilton, M.J. Nonclonal Mast Cell Activation Syndrome: A Growing Body of Evidence. Immunol. Allergy Clin. N. Am. 2018, 38, 469–481. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Leru, P.M. Evaluation and Classification of Mast Cell Disorders: A Difficult to Manage Pathology in Clinical Practice. Cureus 2022, 14, e22177. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Leru, P.M.; Anton, V.F.; Ureche, C.; Zurac, S.; Bratu, O.; Neagoe, C.D. Mast cell activation syndromes—Evaluation of current diagnostic criteria and laboratory tools in clinical practice (Review). Exp. Ther. Med. 2020, 20, 2348–2351. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- van der Weide, H.Y.; van Westerloo, D.J.; van den Bergh, W.M. Critical care management of systemic mastocytosis: When every wasp is a killer bee. Crit. Care 2015, 19, 238. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Cilloni, D.; Maffeo, B.; Savi, A.; Danzero, A.C.; Bonuomo, V.; Fava, C. Detection of KIT Mutations in Systemic Mastocytosis: How, When, and Why. Int. J. Mol. Sci. 2024, 25, 10885. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Komi, D.E.A.; Rambasek, T.; Wöhrl, S. Mastocytosis: From a Molecular Point of View. Clin. Rev. Allergy Immunol. 2018, 54, 397–411. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Valent, P.; Hartmann, K.; Stefanzl, G.; Filik, Y.; Bauer, K.; Degenfeld-Schonburg, L.; Gleixner, K.V.; Siebenhaar, F.; Niedoszytko, M.; Sperr, W.R.; et al. Systemic Mastocytosis, KIT and the Effects of KIT Tyrosine Kinase Inhibitors on Mast Cell and Basophil Activation. Curr. Allergy Asthma Rep. 2026, 26, 10. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Triggiani, M.; Hobart, J.; Alvarez-Twose, I.; Livideanu, C.B.; Ruëff, F.; Barete, S.; Bonadonna, P.; Bouillet, L.; Butt, N.M.; Drummond, M.; et al. Patient-Reported Outcomes and Provider Perceptions of Systemic Mastocytosis: Results From the PRISM Study. Clin. Exp. Allergy 2025, 55, 784–794. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nallamilli, S.; O’Neill, A.; Wilson, A.; Sekhar, M.; Lambert, J. Systemic mastocytosis: Variable manifestations can lead to a challenging diagnostic process. BMJ Case Rep. 2019, 12, e229967. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Hartmann, K.; Escribano, L.; Grattan, C.; Brockow, K.; Carter, M.C.; Alvarez-Twose, I.; Matito, A.; Broesby-Olsen, S.; Siebenhaar, F.; Lange, M.; et al. Cutaneous manifestations in patients with mastocytosis: Consensus report of the European Competence Network on Mastocytosis; the American Academy of Allergy, Asthma & Immunology; and the European Academy of Allergology and Clinical Immunology. J. Allergy Clin. Immunol. 2016, 137, 35–45. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lange, M.; Hartmann, K.; Carter, M.C.; Siebenhaar, F.; Alvarez-Twose, I.; Torrado, I.; Brockow, K.; Renke, J.; Irga-Jaworska, N.; Plata-Nazar, K.; et al. Molecular Background, Clinical Features and Management of Pediatric Mastocytosis: Status 2021. Int. J. Mol. Sci. 2021, 22, 2586. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Weiler, C.R. Mast Cell Activation Syndrome: Tools for Diagnosis and Differential Diagnosis. J. Allergy Clin. Immunol. Pract. 2020, 8, 498–506. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Crupi, F.; Caroprese, J.; Mannelli, F. Defining “Normal” basal serum tryptase levels: A context-dependent approach to improve diagnostics in systemic mastocytosis. Front. Allergy 2025, 6, 1592001. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- NCCN. Clinical Practice Guidelines in Oncology: Systemic Mastocytosis. v.1.2026. Systemic Mastocytosis—Guidelines Detail. Available online: https://www.nccn.org/guidelines/guidelines-detail?category=1&id=1490 (accessed on 1 July 2026).
- Arber, D.A.; Orazi, A.; Hasserjian, R.P.; Borowitz, M.J.; Calvo, K.R.; Kvasnicka, H.M.; Wang, S.A.; Bagg, A.; Barbui, T.; Branford, S.; et al. International Consensus Classification of Myeloid Neoplasms and Acute Leukemias: Integrating morphologic, clinical, and genomic data. Blood 2022, 140, 1200–1228. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Valent, P.; Akin, C.; Hartmann, K.; Alvarez-Twose, I.; Brockow, K.; Hermine, O.; Niedoszytko, M.; Schwaab, J.; Lyons, J.J.; Carter, M.C.; et al. Updated Diagnostic Criteria and Classification of Mast Cell Disorders: A Consensus Proposal. HemaSphere 2021, 5, e646. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Monaldi, C.; De Santis, S.; Mancini, M.; Bruno, S.; Cavo, M.; Soverini, S. Systemic Mastocytosis: Molecular Landscape and Implications for Treatment. Mediterr. J. Hematol. Infect. Dis. 2021, 13, e2021046. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Vega-Ruiz, A.; Cortes, J.E.; Sever, M.; Manshouri, T.; Quintás-Cardama, A.; Luthra, R.; Kantarjian, H.M.; Verstovsek, S. Phase II study of imatinib mesylate as therapy for patients with systemic mastocytosis. Leuk. Res. 2009, 33, 1481–1484. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Gotlib, J.; Kluin-Nelemans, H.C.; George, T.I.; Akin, C.; Sotlar, K.; Hermine, O.; Awan, F.T.; Hexner, E.; Mauro, M.J.; Sternberg, D.W.; et al. Efficacy and Safety of Midostaurin in Advanced Systemic Mastocytosis. N. Engl. J. Med. 2016, 374, 2530–2541. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gotlib, J.; Reiter, A.; Radia, D.H.; Deininger, M.W.; George, T.I.; Panse, J.; Vannucchi, A.M.; Platzbecker, U.; Alvarez-Twose, I.; Mital, A.; et al. Efficacy and safety of avapritinib in advanced systemic mastocytosis: Interim analysis of the phase 2 PATHFINDER trial. Nat. Med. 2021, 27, 2192–2199. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Gotlib, J.; Reiter, A.; Radia, D.H.; Álvarez-Twose, I.; Deininger, M.W.; George, T.I.; Panse, J.; Mital, A.; Pettit, K.M.; Vannucchi, A.M.; et al. Efficacy and safety of avapritinib in advanced systemic mastocytosis: 4-year follow-up of the PATHFINDER study. Blood Adv. 2026, 10, 3676–3689. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gotlib, J.; Castells, M.; Elberink, H.O.; Siebenhaar, F.; Hartmann, K.; Broesby-Olsen, S.; George, T.I.; Panse, J.; Alvarez-Twose, I.; Radia, D.H.; et al. Avapritinib versus Placebo in Indolent Systemic Mastocytosis. NEJM Evid. 2023, 2, EVIDoa2200339. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tashi, T.; Oude Elberink, H.; Akin, C.; Castells, M.; Panse, J.; Radia, D.; Siebenhaar, F.; Bulai Livideanu, C.; Hartmann, K.; Broesby-Olsen, S.; et al. Avapritinib achieves deep and durable symptom control with a well-tolerated safety profile in ism: Long-term outcomes from pioneer. Blood 2025, 146, 2024. [Google Scholar] [CrossRef] [Scilit]
- Farmer, I.; Radia, D.H. Systemic Mastocytosis: State of the Art. Curr. Hematol. Malig. Rep. 2024, 19, 197–207. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Costa, A.; Scalzulli, E.; Carmosino, I.; Capriata, M.; Ielo, C.; Masucci, C.; Passucci, M.; Martelli, M.; Breccia, M. Systemic mastocytosis: 2023 update on diagnosis and management in adults. Expert Opin. Emerg. Drugs 2023, 28, 153–165. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Costanzo, G.; Marzio, V.; Cavaglià, E.; Paoletti, G.; Heffler, E. New treatments for systemic mastocytosis in 2025. Curr. Opin. Allergy Clin. Immunol. 2025, 25, 277–292. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tashi, T.; Hermine, O.; Castells, M.; Guilarte, M.; Sabato, V.; Maurer, M.; Panse, J.; Alvarez-Twose, I.; Cabral, R.; Bird, R.; et al. Elenestinib, an Investigational, Next Generation KIT D816V Inhibitor, Reduces Mast Cell Burden, Improves Symptoms, and Has a Favorable Safety Profile in Patients with Indolent Systemic Mastocytosis: Analysis of the Harbor Trial. Blood 2023, 142, 76. [Google Scholar] [CrossRef] [Scilit]
- Phase 2/3 Harbor Study of Elenestinib in ISM: A Trial-in-Progress Update of Novel Endpoints and Biomarkers Aimed at Evaluating Disease Modification. Available online: https://library.ehaweb.org/eha/2025/eha2025-congress/4162181/ivan.alvarez-twose.phase.2.3.harbor.study.of.elenestinib.in.ism.a.html?f=listing%3D3%2Abrowseby%3D8%2Asortby%3D1%2Amedia%3D1 (accessed on 1 July 2026).
- Jawhar, M.; Schwaab, J.; Meggendorfer, M.; Naumann, N.; Horny, H.P.; Sotlar, K.; Haferlach, T.; Schmitt, K.; Fabarius, A.; Valent, P.; et al. The clinical and molecular diversity of mast cell leukemia with or without associated hematologic neoplasm. Haematologica 2017, 102, 1035–1043. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- A Study to Evaluate the Efficacy and Safety of CGT9486 Versus Placebo in Patients With Indolent or Smoldering Systemic Mastocytosis. Available online: https://clinicaltrials.gov/study/NCT05186753 (accessed on 1 July 2026).
- Rein, L.; Boggs, N.; Bose, P.; Modena, B.; Sabato, V.; Hartmann, K.; Akin, C.; George, T.; Yi, C.A.; Oude Elberink, H.; et al. Efficacy and safety results from the primary analysis of the pivotal summit trial: Bezuclastinib in adults with non-advanced systemic mastocytosis. Blood 2025, 146, 80. [Google Scholar] [CrossRef] [Scilit]
- DeAngelo, D.J.; Pullarkat, V.; Piris-Villaespesa, M.; George, T.I.; Patel, J.L.; Ustun, C.; Bose, P.; Heaney, M.L.; Pilla, A.; Massaro, M.; et al. P1049: A Phase 2 Study of Bezuclastinib (CGT9486), a Novel, Highly Selective, Potent Kit D816V Inhibitor, in Adults with Advanced Systemic Mastocytosis (APEX): Methods, Baseline Data, and Early Insights. HemaSphere 2022, 6, 939–940. [Google Scholar] [CrossRef] [Scilit] [PubMed Central]
- DeAngelo, D.J.; Gotlib, J.; Pullarkat, V.; Vachhani, P.; Tashi, T.; Lee, S.; Schiller, G.J.; Hunter, A.M.; Piris-Villaespesa, M.; Pomares, H.; et al. Apex Part 1: Updated Assessment of Bezuclastinib (CGT9486), a Selective KIT D816V Tyrosine Kinase Inhibitor, in Patients with Advanced Systemic Mastocytosis (AdvSM). Blood 2024, 144, 659. [Google Scholar] [CrossRef] [Scilit]
- Carpio-Escalona, L.V.; Prieto-García, A.; Morales-Cabeza, C.; Guilarte, M.; Matito, A.; Torrado, I.; Vega-Castro, A.; González-de-Olano, D. Tyrosine Kinase Inhibitors for the Treatment of Mast Cell Diseases: Review and Update. J. Investig. Allergol. Clin. Immunol. 2025, 35, 328–340. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Valent, P.; Akin, C.; Hartmann, K.; George, T.I.; Sotlar, K.; Peter, B.; Gleixner, K.V.; Blatt, K.; Sperr, W.R.; Manley, P.W.; et al. Midostaurin: A magic bullet that blocks mast cell expansion and activation. Ann. Oncol. 2017, 28, 2367–2376. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DeAngelo, D.J.; George, T.I.; Linder, A.; Langford, C.; Perkins, C.; Ma, J.; Westervelt, P.; Merker, J.D.; Berube, C.; Coutre, S.; et al. Efficacy and safety of midostaurin in patients with advanced systemic mastocytosis: 10-year median follow-up of a phase II trial. Leukemia 2018, 32, 470–478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kasamon, Y.L.; Ko, C.W.; Subramaniam, S.; Ma, L.; Yang, Y.; Nie, L.; Shord, S.; Przepiorka, D.; Farrell, A.T.; McKee, A.E.; et al. FDA Approval Summary: Midostaurin for the Treatment of Advanced Systemic Mastocytosis. Oncologist 2018, 23, 1511–1519. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Evans, E.K.; Gardino, A.K.; Kim, J.L.; Hodous, B.L.; Shutes, A.; Davis, A.; Zhu, X.J.; Schmidt-Kittler, O.; Wilson, D.; Wilson, K.; et al. A precision therapy against cancers driven by KIT/PDGFRA mutations. Sci. Transl. Med. 2017, 9, eaao1690. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Veitch, S.; Radia, D.H. Recent Advances in the Therapeutic Management of Advanced Systemic Mastocytosis. Diagnostics 2023, 14, 80. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Rahmani, N.E.; Ramachandra, N.; Sahu, S.; Gitego, N.; Lopez, A.; Pradhan, K.; Bhagat, T.D.; Gordon-Mitchell, S.; Pena, B.R.; Kazemi, M.; et al. ASXL1 mutations are associated with distinct epigenomic alterations that lead to sensitivity to venetoclax and azacytidine. Blood Cancer J. 2021, 11, 157. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Avapritinib with Decitabine in Patients with SM-AHN. Available online: https://clinicaltrials.gov/study/NCT06327685 (accessed on 1 July 2026).
- Pardanani, A.; Reichard, K.; Tefferi, A. Advanced systemic mastocytosis-Revised classification, new drugs and how we treat. Br. J. Haematol. 2024, 204, 402–414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lim, K.H.; Pardanani, A.; Butterfield, J.H.; Li, C.Y.; Tefferi, A. Cytoreductive therapy in 108 adults with systemic mastocytosis: Outcome analysis and response prediction during treatment with interferon-alpha, hydroxyurea, imatinib mesylate or 2-chlorodeoxyadenosine. Am. J. Hematol. 2009, 84, 790–794. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tolar, J.; Tope, W.D.; Neglia, J.P. Leukotriene-receptor inhibition for the treatment of systemic mastocytosis. N. Engl. J. Med. 2004, 350, 735–736. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carter, M.C.; Robyn, J.A.; Bressler, P.B.; Walker, J.C.; Shapiro, G.G.; Metcalfe, D.D. Omalizumab for the treatment of unprovoked anaphylaxis in patients with systemic mastocytosis. J. Allergy Clin. Immunol. 2007, 119, 1550–1551. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Worobec, A.S. Treatment of systemic mast cell disorders. Hematol. Oncol. Clin. N. Am. 2000, 14, 659–687. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Laroche, M.; Livideanu, C.; Paul, C.; Cantagrel, A. Interferon alpha and pamidronate in osteoporosis with fracture secondary to mastocytosis. Am. J. Med. 2011, 124, 776–778. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Spolak-Bobryk, N.; Niedoszytko, M.; Jassem, E.; Chełmińska, M.; Lange, M.; Majkowicz, M.; Nedoszytko, B.; Borchet, J. Assessing quality of life in patients with mastocytosis: Development of the disease-specific questionnaire. Postępy Dermatol. Alergol. 2021, 38, 1044–1051. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- van Anrooij, B.; Kluin-Nelemans, J.C.; Safy, M.; Flokstra-de Blok, B.M.; Oude Elberink, J.N. Patient-reported disease-specific quality-of-life and symptom severity in systemic mastocytosis. Allergy 2016, 71, 1585–1593. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.