


Simple Summary
FLT3 and IDH2 mutations are more commonly seen in KMT2A-rearranged acute myeloid leukemia (KMT2Ar AML), whereas NPM1, TP53, and myelodysplasia-related mutations are more commonly seen in KMT2A wild-type AML (KMT2Awt). This genomic landscape study highlights significant genomic differences between KMT2A-arranged and wild-type AML, which may enrich our understanding of the molecular profile and associations between mutations in AML.
Abstract
Background: The KMT2A (MLL1) gene is altered in a variety of hematological malignancies and solid tumors. KMT2A-rearranged (KMT2Ar) AML represents a distinct subtype associated with poor outcomes and high relapse rate despite initial responsiveness to chemotherapy. Methods: A total of 3863 cases of AML peripheral blood samples were analyzed using the FoundationOne Heme combined comprehensive hybrid capture-based DNA and RNA sequencing assay. Results: Of the 3863 AML cases, 521 (13.4%) featured genomic alterations (GAs) in the KMT2A gene, 99.1% of which were large rearrangements (KMT2Ar). A total of 56.9% were males with a median age of 62 years. Of the KMT2Ar cases, there were 43.1% KMT2A duplications, 52.7% fusions, and 4.2% not otherwise specified rearrangements. A total of 0.9% of the KMT2A-altered AML cases were short variant mutations. There were no KMT2A (0%) amplifications or deletions. KMT2Ar cases were associated with increased GA frequencies in FLT3 (27.3% vs. 19.8%; p = 0.0002), KRAS (17.2% vs. 7.8%; p < 0.0001) (overall; 1.1% KRAS G12C), and IDH2 (16.0% vs. 10.4%; p < 0.0001), while KMT2A wild-type AML (KMT2Awt) had significantly increased GA frequencies in RUNX1 (20.7% vs. 15.8%; p = 0.0081), ASXL1 (16.6% vs. 10.5%; p = 0.0003), and TET2 (16.4% vs. 10.1%; p = 0.0002), NPM1 (17.5% vs. 0.2%; p < 0.0001), and TP53 (17.8% vs. 7.9%; p < 0.0001). Conclusions: KMT2A rearrangements are common in AML (13.4% of cases featured KMT2Ar). A total of 99.1% of alterations in KMT2A are large rearrangements, with fusions being the most commonly observed alteration (52.7% of total rearrangements). No amplifications or deletions were seen. This genomic landscape study highlights significant genomic differences between KMT2Ar and KMT2Awt AML patients, which may enrich our understanding of the molecular profile and clusters of mutations in AML.
1. Introduction
Acute myeloid leukemia (AML) encompasses a diverse group of hematologic malignancies, marked by uncontrolled proliferation and clonal expansion of stem and progenitor cells within the bone marrow [1,2]. AML accounts for almost 1.1% of all newly diagnosed cancer cases in the United States, and it is commonly diagnosed at older age, with a median age at diagnosis of 68 years [3,4]. The estimated 5-year overall survival (OS) rate is approximately 32%, although it can vary based on age, with an OS around 50% in younger patients and below 10% in patients over 60 years old [5,6].
The wide range of genomic alterations in AML demonstrates the complexity of this hematologic malignancy [7]. Genomic analysis is a key component in the initial evaluation of AML patients, as it guides treatment decisions through AML subtype classification, prognostication, and risk stratification [8,9]. Comprehensive genomic sequencing of AML conducted by The Cancer Genome Atlas (TCGA), using either whole-genome sequencing or whole-exome sequencing, along with RNA and microRNA sequencing and DNA-methylation analysis, uncovered around 2000 unique somatically mutated genes across a cohort of 200 patients, and at least one driver mutation was identified in nearly all cases of AML [10]. Efforts to characterize the mutational landscape of AML are ongoing and reflected in the initial findings from the Beat AML dataset, which analyzed 672 tumor specimens from 562 patients using whole-exome sequencing, RNA sequencing, and ex vivo drug sensitivity, which identified novel mutational events not previously detected in AML and highlighted predicted drug responses based on specific gene networks [11].
Mutations in epigenetic regulator genes including KMT2A are frequently acquired early in AML and are found in the original clonal population, also known as de novo AML [12,13,14]. Such mutations can survive induction chemotherapy, result in clonal expansion in the bone marrow at remission, and eventually lead to leukemic progression and disease relapse [14]. In contrast, mutations in Nucleophosmin (NPM1) or other signaling molecules such as FLT3 and RAS usually occur in later leukemogenesis [15].
Lysine-specific N-methyltransferase 2A (KMT2A), also known as mixed-lineage leukemia1 (MLL1), is located on chromosome 11q23 and encodes a nuclear protein critical for epigenetic regulation [16]. KMT2A belongs to the Trithorax group (TrxG) proteins and facilitates transcriptional activity by catalyzing histone H3 lysine 4 methylation (H3K4me), a key feature of active gene promoters [17,18]. It is frequently involved in chromosomal translocations that generate fusion genes [19].
KMT2A is specifically associated with hematologic malignancies due to its crucial role in hematopoietic stem cell (HSC) differentiation [20]. KMT2Ar are present in 3–10% of adult AML cases [21]. In general, leukemias with KMT2A rearrangements have poor prognosis, with a progression-free survival (PFS) of 30–40% and an overall survival (OS) below 25% [19]. KMT2A GAs in AML are heterogeneous in nature and diverse and characterized by chemotherapy resistance and high risk of relapse [22]. A 5-year cumulative incidence of relapse (CIR) of 41.5% was reported in pediatric AML patients with mutated KMT2A, while a higher CIR up to 80% was seen in adult patients [21,23].
KMT2A fusion proteins recruit transcription cofactors such as menin, CBX8, TFEb, and DOTL1, which promote transcription elongation [19]. This explains the potential therapeutic effect of menin inhibitors (e.g., Revumenib, Ziftomenib) [24,25] and DOTL1 inhibitors (e.g., Pinometostat) in this adverse disease subtype of AML [21,26,27,28].
The aim of this study is to investigate the major genomic alterations in AML, specifically comparing the different mutations in KMT2Ar and KMT2Awt AML cases. A comprehensive genomic analysis was performed to characterize key mutations in both groups. Our findings highlight distinct molecular profiles associated with KMT2Ar, providing critical insights into the disease mechanisms and the impact of these genomic alterations on prognosis and therapeutic intervention.
2. Methods
2.1. Study Design
The study protocol received approval from the Western Institutional Review Board (Protocol No. 20152817), including a waiver of informed consent and HIPAA authorization. We performed a retrospective analysis of AML patients who underwent comprehensive genomic profiling (CGP) assays. A total of 3863 peripheral blood samples from patients diagnosed with AML between 2019 and 2024 were included, in which all patients underwent comprehensive genomic profiling of peripheral blood samples with the Foundation One Heme assay, a hybrid capture-based DNA and RNA sequencing platform.
Eligibility criteria included patients who were at least 18 years of age, had a confirmed diagnosis of AML, and had undergone next-generation sequencing (NGS). Genomic data were analyzed for base substitutions, short insertions and deletions, copy number changes and rearrangements, and fusions. Patient age and biological sex were extracted from accompanying pathology reports.
The Foundation One Heme assay includes both DNA and RNA sequencing. The DNAseq component detects the entire coding region of 405 genes and selects intronic regions in 31 genes known to be clinically and biologically relevant in cancer. The RNAseq component is focused on 265 genes recurrently rearranged in cancer. This assay is validated to a high accuracy, achieved through high and uniform coverage, with an average median exon depth of 500× (DNA) and average on-target distinct pairs of ~3 M (RNA). The tumor mutational burden (TMB) is defined as the total number of mutations found in the DNA of cancer cells and is reported as the number of mutations seen in a section of DNA per megabase (mut/Mb) (a TMB of 10 mut/Mb or greater was referred to as TMB-high) [29]. Microsatellite stability (MSS) status was determined on at least 1500 loci [30,31]. The Catalogue of Somatic Mutations in Cancer (COSMIC) was used in order to reflect the underlying mechanisms of mutational processes in each case [32].
The FoundationOne Heme assay was utilized for comprehensive genomic profiling as previously described [33], and the sequencing workflow is demonstrated in Figure 1.
Figure 1.
Workflow of the Foundation Heme One assay, illustrating a comprehensive combined DNA and RNA genomic analysis in clinical specimens and the coverage distribution of all exons.
Patients were categorized into two cohorts for comparative analysis based on their genomic profiling results: patients diagnosed with KMT2A rearrangements (KMT2Ar) and those without KMT2A rearrangements, also referred to as KMT2A wild-type AML (KMT2Awt).
2.2. Outcome Definitions
The primary aim of this study was to characterize the genomic landscape of AML, with emphasis on comparing key genetic alterations between the KMT2Ar and KMT2Awt AML cases. Secondary objectives included assessing the distribution of TMB, and MSS status in these cohorts, as well as examining potential associations between genomic profiles and available clinical characteristics such as patient age, gender, laboratory markers, and treatment response.
The analysis included clinical endpoints and variables such as median age at diagnosis, prevalence of specific genomic alterations, TMB classification (above 10 mutations/Mb and above 20 mutations/Mb), MSS status, and mutational signature patterns referenced from COSMIC.
2.3. Statistical Analyses
The median age of the study population was calculated. Comparisons between the KMT2A-rearranged (KMT2Ar) and KMT2A non-rearranged (KMT2Awt) groups were performed. Univariate analyses of continuous variables were conducted using the t-test, while categorical variables were assessed using the chi-square test or Fisher’s exact test, as appropriate. Continuous data are presented as means with standard deviations (±SD), and categorical data are reported as counts and percentages. To account for multiple comparisons and control the false discovery rate, Fisher’s exact test results were adjusted using the Benjamini–Hochberg procedure, which ranks individual p-values and applies a progressively stricter significance threshold as the number of tests increases. A two-sided p-value < 0.05 was considered statistically significant.
3. Results
A total of 3863 AML cases were included in the analysis. Based on KMT2A genomic alterations, cases were stratified into two subgroups: 521 (13.5%) cases of KMT2A-rearranged, in which 99.1% of the GAs were large rearrangements, and 3342 (86.5%) cases of KMT2A non-rearranged (wild-type).
There were no significant differences between the KMT2Ar and KMT2Awt cohorts with respect to sex or age (mean age: 52.8 vs. 53.7 years; p = NS, or median age: 61 vs. 62 years; p = NS) (Table 1).
Table 1.
Baseline characteristics comparison between KMT2A-rearranged vs. KMT2A wild-type AML patients. ns: not statistically significant.
Within the KMT2Ar subgroup, alteration types were distributed as follows: 43.1% duplications, 52.7% fusions, and 4.2% rearrangements not otherwise specified (NOS). Short variant mutations accounted only for 0.9% of KMT2A-altered cases, and no KMT2A amplifications or deletions were observed.
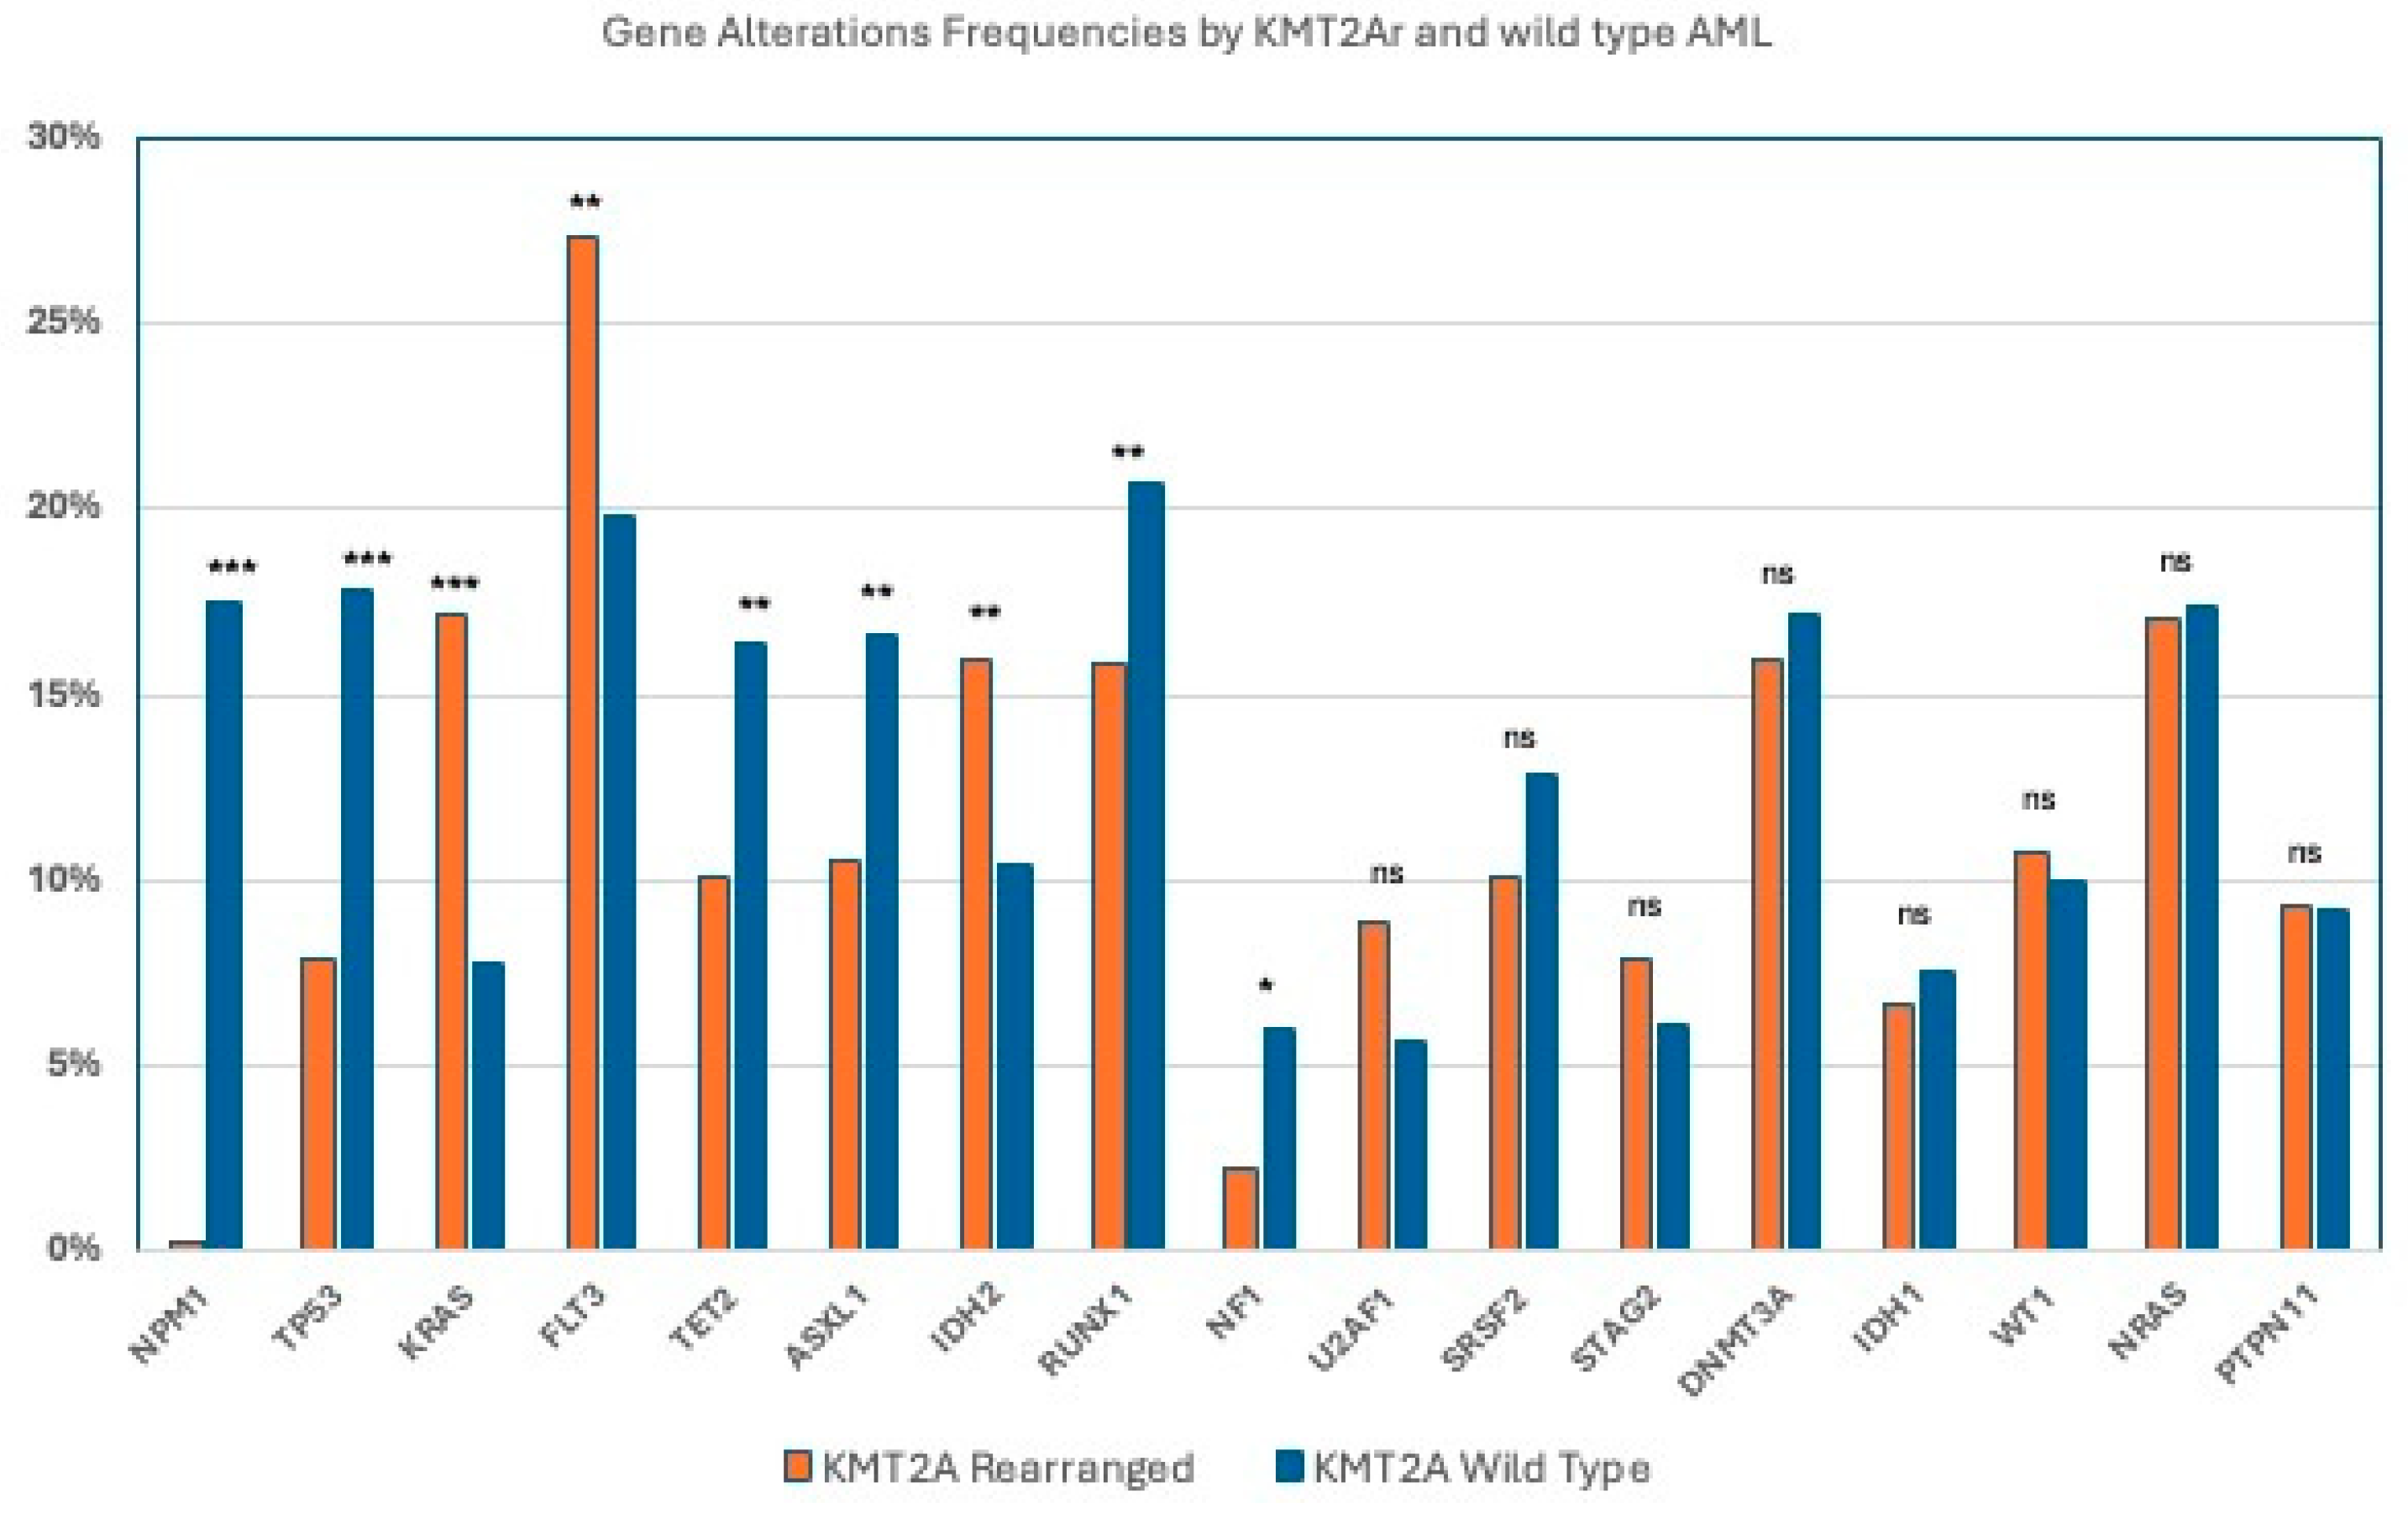
When comparing the genomic landscape between KMT2Ar and KMT2Awt AML cases, several significant differences were observed and are demonstrated in Table 2 and Figure 2. The KMT2Ar cases demonstrated significantly higher frequencies of GAs in FLT3 (27.3% vs. 19.8%; p = 0.0001), KRAS (17.2% vs. 7.8%; p < 0.0001), and IDH2 (16.0% vs. 10.4%; p < 0.0001).
Table 2.
Genomic analysis comparison between KMT2A-rearranged AML vs. KMT2A wild-type AML patients. ns: not statistically significant.
Figure 2.
Gene alteration frequencies between KMT2A-rearranged and KMT2A wild-type AML Cases. *: p < 0.05. **: p < 0.001. ***: p < 0.0001. ns: not statistically significant.
In contrast, the KMT2Awt cases demonstrated significantly higher frequencies of GAs observed in RUNX1 (20.7% vs. 15.8%; p = 0.0081), ASXL1 (16.6% vs. 10.5%; p = 0.0003), TET2 (16.4% vs. 10.1%; p = 0.0002), NPM1 (17.5% vs. 0.2%; p = <0.0001), and NF1 (6% vs. 2.2%; p = 0.001). TP53 mutations were significantly increased in KMT2Awt (17.8% vs. 7.9%; p = <0.0001)
No significant differences were observed between the two groups in the prevalence of GAs in NRAS (17.4% vs. 17%), DNMT3A (16.0% vs. 17.2%), WT1 (10.7% vs. 10%), SRSF2 (10.1% vs. 12.8%; p = NS), PTPN11 (9.3% vs. 9.2%; p = NS), U2AF1 (8.9% vs. 5.7%; p = NS), STAG2 (7.9% vs. 6.1%; p = NS), or IDH1 (6.7% vs. 7.6%; p = NS).
With respect to mutational burden, the median tumor mutational burden (TMB) was similar between the KMT2Ar and KMT2Awt cohorts at 0.8 mutations/Mb, with only 0.2% of cases in either group exhibiting a TMB greater than 10 mutations/Mb. Furthermore, all cases (100%) in both groups were microsatellite-stable (MSS).
4. Discussion
Recently, AML with KMT2Ar has been widely studied, as it is highly characterized by adverse outcomes due to treatment failure, high relapse rate, and early mortality [34]. The t(9;11) (p21.3;q23.3) translocation resulting in the KMT2A-MLLT3 fusion is the most frequent KMT2A rearrangement seen in adults with AML, although over 80 different fusion partners have been identified [35].
KMT2Ar results in fusion proteins that drive leukemia by activating HOX genes and their cofactor Meis1, which are both critical for leukemogenesis [36]. Menin serves as an essential scaffolding protein that facilitates the binding of KMT2A complex to HOX gene promoters, playing an important role in pathogenesis [37]. The disruption of the menin-KMT2A interaction can restore normal gene expression, promote differentiation, and exert an antileukemic effect. Similarly, AML with NPM1 mutations depends on the menin–KMT2A interaction, and thus the efficacy of menin inhibitors is studied in AML with NPM1 mutation and KMT2A rearrangement [38].
Despite the use of intensive chemotherapy and hematopoietic stem cell transplants (HSCTs), patients with KMT2Ar AML still have unfavorable prognosis and show limited responses to treatment [39]. Additionally, therapy-related KMT2Ar AML has worse OS compared to de novo KMT2Ra AML [23]. Of the chemotherapeutic agents linked to therapy-related AML, topoisomerase II inhibitors (such as daunorubicin) are closely linked to KMT2Ar AML and typically lead to disease onset after a short latency period [40].
Menin inhibitors are emerging therapeutic agents under clinical investigation in NPM1-mutated and KMT2Ar AML, with a promising effect on the transcriptional network driving leukemogenesis [24]. Revumenib is a menin inhibitor that received its first FDA approval in the United States in November 2024 for the treatment of relapsed/refractory KMT2Ar AML [28,41,42]. Ongoing clinical trials are evaluating integrating menin inhibitors into upfront standard induction/consolidation therapy. [43] Other menin inhibitors such as Ziftomenib [25] and Bleximenib [44] are being studied in addition to the possible combination therapies with venetoclax, hypomethylating agents, PARP inhibitors, all-trans-retinoic acid (ATRA), and other common treatment options in AML [45].
In our study, the percentage of KMT2Ar in AML is 13.5%, which is slightly higher than the reported rate of 3–10% in the literature [21]. This could be attributed to the retrospective study design which included samples at diagnosis and variable times throughout the course of treatment. There was no significant difference based on sex between KMT2Ar and KMT2Awt groups, which aligns with the published data [46,47]. Similarly, there was no significant difference based on age between the two groups. Interestingly, a large proportion of our patient samples (43.1%) had duplications as GAs in KMT2A, which is higher than the reported cases (3–11%) [48,49,50,51]; this could be potentially explained by our assay using combined DNA and RNA sequencing in comparison to other studies utilizing DNA-based testing only. Short variant mutations are very rare (0.9%) in KMT2A AML compared to rearrangements and duplications, and the latter aligns with the available data [52].
Importantly, genomic alterations, which serve as potential targets for treatment, show higher frequency in KMT2Ar cases compared to KMT2wt. These include GAs in FLT3 and IDH2. Additionally, GAs in KRAS, including KRAS G12C mutations, were more frequently seen in KMT2Ar AML, which has more clinical implications in solid malignancies like non-small-cell lung cancer. [53] KMT2Ar is the primary initiating event and key driver in KMT2Ar AML, while the effect of additional mutations on prognosis and clinical outcomes is under investigation [54,55]. In a study by Issa et al., RAS and FLT3 mutations in KMT2Ar AML did not have a significant implication on prognosis except when ≥2 mutations were present [23]. However, a recent study by Wu et al. showed that KMT2Ar AML patients harboring KRAS mutations had significantly worse 2-year OS and higher 2-year cumulative incidence of relapse (CIR) compared to those with wild-type KRAS, while NRAS and FLT3 mutations were not significantly associated with differences in OS or CIR [56]. Studies suggest that KMT2A rearrangement creates a cellular environment favorable for the acquisition and maintenance of KRAS mutations, which have a synergistic leukemogenesis effect [57,58]. In preclinical studies, it has been demonstrated that FLT ITD and NRAS mutations accelerate KMT2A leukemia onset, possibly by providing stimulatory factors [58,59].
On the other hand, we found a significantly lower frequency of GAs in RUNX1, ASXL1, TET2 and NF1 in KMT2Ar compared with KMT2Awt cases. Mutations in genes like ASXL1 and TET2 are often mutated in the elderly and are associated with clonal hematopoietic expansion, with a high risk of developing hematologic malignancies [60].
There was also no significant difference in the prevalence of GAs in NRAS, DNMT3A, WT1, SRSF2, PTPN11, U2AF1, STAG2, or IDH1 between both groups. Other studies also demonstrated a low prevalence of these mutations in KMT2Ar AML [23,55]. NPM1 mutation was exclusively observed in KMT2Awt (17.5% vs. 0.2%; p < 0.0001), suggesting that in patients with KMT2Ar AML, the chances of identifying NPM1 are extremely low, at <0.5%.
TP53 mutations represent a significant challenge in AML and MDS due to their resistance and high rates of relapse with conventional chemotherapy [61,62,63,64]. The rate of TP53 mutations in our study was significantly higher in patients with KMT2Awt compared to KMT2Ar AML (17.8% vs. 7.9%; p < 0.0001), which correlates with the literature [63].
Regarding mutational burden, we reported a similar TMB of 0.8 mutations/Mb between the KMT2Ar and KMT2Awt cohorts, with only 0.2% of cases in either group exhibiting a TMB greater than 10 mutations/Mb. All cases in both groups were microsatellite-stable (MSS). The median TMB identified in the literature is equally low, with 0.5 mutations per patient in KMT2Ar and 2 mutations per patient in KMT2Anr [23]. Unlike solid tumors, in which TMB and/or MSS status have been validated as biomarkers and have clinical implications regarding responsiveness to immunotherapy [65], testing in AML patients is not routinely performed, and there is no available data about MSS and TMB testing in KMT2Ar AML.
The main limitation of this study was the lack of data on clinical outcomes in this studied population.
5. Conclusions
KMT2A rearrangements are common in AML (13.4% of cases featured KMT2Ar). A total of 99.1% of alterations in KMT2A are large rearrangements, with fusions being the most commonly observed alteration (52.7% of total rearrangements). No amplifications or deletions were seen. FLT3 and IDH2 mutations are more commonly seen in KMT2Ar AML, whereas NPM1, TP53, and myelodysplasia-related mutations are more commonly seen in KMT2Awt. This genomic landscape study highlights significant genomic differences between KMT2Ar and KMT2Awt AML patients, which may enrich our understanding of the molecular profile and clusters of mutations in AML.
Author Contributions
Conceptualization, O.B., M.M., N.S.N., A.P., A.R.M., A.G., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G.; Methodology, O.B., M.M., N.S.N., A.R.M., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G.; Software, O.B., M.M., N.S.N., A.P., A.R.M., A.G., J.S.R., C.H. and C.M.; Validation, O.B., M.M., N.S.N., A.P., A.R.M., A.G., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G.; Formal analysis, O.B., J.S.R., C.H. and C.M.; Investigation, O.B., M.M., N.S.N., A.P., A.R.M., A.G., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G. Resources, O.B., M.M., N.S.N., A.P., A.R.M., A.G., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G.; Data curation, O.B., M.M., N.S.N., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G.; Writing—original draft preparation, O.B., M.M., N.S.N., A.P., A.R.M., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G.; Writing—review and editing, O.B., M.M., N.S.N., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G.; Visualization, O.B., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G.; Supervision, O.B., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G.; Project administration, O.B., M.M., N.S.N., J.S.R., C.H., C.M., Z.Z., G.K.-S., T.G. and K.B.G. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the Western Institutional Review Board (Protocol No. 20152817, 7 January 2016).
Informed Consent Statement
Waiver of informed consent and an HIPAA waiver of authorization were obtained from the Western Institutional Review Board.
Data Availability Statement
The raw data supporting the conclusions of this article will be made available by the authors on request.
Conflicts of Interest
Authors Chelsea Marcus, Caleb Ho, and Jeffrey S. Ross were employed by the company Foundation Medicine and are equity holders in Roche Holdings. Author Jeffrey S. Ross is an equity holder in Tango Therapeutics. The remaining authors declare that the research was conducted in the absence of any commercial or financial relationships that could be construed as a potential conflict of interest.
References
- Kurzer, J.H.; Weinberg, O.K. Updates in molecular genetics of acute myeloid leukemia. Semin. Diagn. Pathol. 2023, 40, 140–151. [Google Scholar] [CrossRef] [Scilit]
- Shimony, S.; Stahl, M.; Stone, R.M. Acute Myeloid Leukemia: 2025 Update on Diagnosis, Risk-Stratification, and Management. Am. J. Hematol. 2025, 100, 860–891. [Google Scholar] [CrossRef] [Scilit]
- Juliusson, G.; Antunovic, P.; Derolf, A.; Lehmann, S.; Möllgård, L.; Stockelberg, D.; Tidefelt, U.; Wahlin, A.; Höglund, M. Age and acute myeloid leukemia: Real world data on decision to treat and outcomes from the Swedish Acute Leukemia Registry. Blood 2009, 113, 4179–4187. [Google Scholar] [CrossRef] [Scilit]
- Penney, S.W.; Watson, N.L.; Brooks, D.I.; Whiteway, S.L.; Warwick, A.B.; Zanetti, R.C.; Vasta, L.M. Innovative Algorithm for Incidence of Leukemia and Lymphoma in the U.S. Military Health Care System. Mil. Med. 2025, 190, e1184–e1189. [Google Scholar] [CrossRef] [Scilit]
- Sasaki, K.; Ravandi, F.; Kadia, T.M.; DiNardo, C.D.; Short, N.J.; Borthakur, G.; Jabbour, E.; Kantarjian, H.M. De novo acute myeloid leukemia: A population-based study of outcome in the United States based on the Surveillance, Epidemiology, and End Results (SEER) database, 1980 to 2017. Cancer 2021, 127, 2049–2061. [Google Scholar] [CrossRef] [Scilit]
- Jia, Z.Y.; Abulimiti, M.; Wu, Y.; Ma, L.N.; Li, X.Y.; Wang, J. A novel perspective on survival prediction for AML patients: Integration of machine learning in SEER database applications. Heliyon 2025, 11, e42030. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Snaith, O.; Poveda-Rogers, C.; Laczko, D.; Yang, G.; Morrissette, J.J.D. Cytogenetics and genomics of acute myeloid leukemia. Best. Pract. Res. Clin. Haematol. 2024, 37, 101533. [Google Scholar] [CrossRef] [Scilit]
- Akkari, Y.M.N.; Baughn, L.B.; Dubuc, A.M.; Smith, A.C.; Mallo, M.; Dal Cin, P.; Diez Campelo, M.; Gallego, M.S.; Granada Font, I.; Haase, D.T.; et al. Guiding the global evolution of cytogenetic testing for hematologic malignancies. Blood 2022, 139, 2273–2284. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yahya, D.; Stoyanova, M.; Hachmeriyan, M.; Levkova, M. Genomic Evaluation of AML-Main Techniques and Novel Approaches. J. Clin. Med. 2025, 14, 5685. [Google Scholar] [CrossRef] [Scilit]
- Ley, T.J.; Miller, C.; Ding, L.; Raphael, B.J.; Mungall, A.J.; Robertson, A.; Hoadley, K.; Triche, T.J., Jr.; Laird, P.W.; Baty, J.D.; et al. Genomic and epigenomic landscapes of adult de novo acute myeloid leukemia. N. Engl. J. Med. 2013, 368, 2059–2074. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tyner, J.W.; Tognon, C.E.; Bottomly, D.; Wilmot, B.; Kurtz, S.E.; Savage, S.L.; Long, N.; Schultz, A.R.; Traer, E.; Abel, M.; et al. Functional genomic landscape of acute myeloid leukaemia. Nature 2018, 562, 526–531. [Google Scholar] [CrossRef] [Scilit]
- Bullinger, L.; Döhner, K.; Döhner, H. Genomics of Acute Myeloid Leukemia Diagnosis and Pathways. J. Clin. Oncol. 2017, 35, 934–946. [Google Scholar] [CrossRef] [Scilit]
- Zjablovskaja, P.; Florian, M.C. Acute Myeloid Leukemia: Aging and Epigenetics. Cancers 2019, 12, 103. [Google Scholar] [CrossRef] [Scilit]
- Milan, T.; Celton, M.; Lagacé, K.; Roques, É.; Safa-Tahar-Henni, S.; Bresson, E.; Bergeron, A.; Hebert, J.; Meshinchi, S.; Cellot, S.; et al. Epigenetic changes in human model KMT2A leukemias highlight early events during leukemogenesis. Haematologica 2022, 107, 86–99. [Google Scholar] [CrossRef] [Scilit]
- Martignoles, J.A.; Delhommeau, F.; Hirsch, P. Genetic Hierarchy of Acute Myeloid Leukemia: From Clonal Hematopoiesis to Molecular Residual Disease. Int. J. Mol. Sci. 2018, 19, 3850. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meyer, C.; Larghero, P.; Lopes, B.A.; Marschalek, R. The KMT2A/MLL consensus gene structure: A comprehensive update for research and diagnostic implications. Leukemia 2024, 38, 1403–1406. [Google Scholar] [CrossRef] [Scilit]
- Schuettengruber, B.; Martinez, A.M.; Iovino, N.; Cavalli, G. Trithorax group proteins: Switching genes on and keeping them active. Nat. Rev. Mol. Cell Biol. 2011, 12, 799–814. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van, H.T.; Xie, G.; Dong, P.; Liu, Z.; Ge, K. KMT2 Family of H3K4 Methyltransferases: Enzymatic Activity-dependent and -independent Functions. J. Mol. Biol. 2024, 436, 168453. [Google Scholar] [CrossRef] [Scilit]
- Guarnera, L.; D’Addona, M.; Bravo-Perez, C.; Visconte, V. KMT2A Rearrangements in Leukemias: Molecular Aspects and Therapeutic Perspectives. Int. J. Mol. Sci. 2024, 25, 9023. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rao, R.C.; Dou, Y. Hijacked in cancer: The KMT2 (MLL) family of methyltransferases. Nat. Rev. Cancer 2015, 15, 334–346. [Google Scholar] [CrossRef] [Scilit]
- Zehtabcheh, S.; Soleimani Samarkhazan, H.; Asadi, M.; Zabihi, M.; Parkhideh, S.; Mohammadi, M.H. Insights into KMT2A rearrangements in acute myeloid leukemia: From molecular characteristics to targeted therapies. Biomark. Res. 2025, 13, 73. [Google Scholar] [CrossRef] [Scilit]
- Meyer, C.; Larghero, P.; Almeida Lopes, B.; Burmeister, T.; Gröger, D.; Sutton, R.; Venn, N.C.; Cazzaniga, G.; Corral Abascal, L.; Tsaur, G.; et al. The KMT2A recombinome of acute leukemias in 2023. Leukemia 2023, 37, 988–1005. [Google Scholar] [CrossRef] [Scilit]
- Issa, G.C.; Zarka, J.; Sasaki, K.; Qiao, W.; Pak, D.; Ning, J.; Short, N.J.; Haddad, F.; Tang, Z.; Patel, K.P.; et al. Predictors of outcomes in adults with acute myeloid leukemia and KMT2A rearrangements. Blood Cancer J. 2021, 11, 162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Issa, G.C.; Aldoss, I.; DiPersio, J.; Cuglievan, B.; Stone, R.; Arellano, M.; Thirman, M.J.; Patel, M.R.; Dickens, D.S.; Shenoy, S.; et al. The menin inhibitor revumenib in KMT2A-rearranged or NPM1-mutant leukaemia. Nature 2023, 615, 920–924. [Google Scholar] [CrossRef] [Scilit]
- Daigle, S.R.; Olhava, E.J.; Therkelsen, C.A.; Basavapathruni, A.; Jin, L.; Boriack-Sjodin, P.A.; Allain, C.J.; Klaus, C.R.; Raimondi, A.; Scott, M.P.; et al. Potent inhibition of DOT1L as treatment of MLL-fusion leukemia. Blood 2013, 122, 1017–1025. [Google Scholar] [CrossRef] [Scilit]
- Issa, G.C.; Aldoss, I.; Thirman, M.J.; DiPersio, J.; Arellano, M.; Blachly, J.S.; Mannis, G.N.; Perl, A.; Dickens, D.S.; McMahon, C.M.; et al. Menin Inhibition With Revumenib for KMT2A-Rearranged Relapsed or Refractory Acute Leukemia (AUGMENT-101). J. Clin. Oncol. 2025, 43, 75–84. [Google Scholar] [CrossRef] [Scilit]
- Chalmers, Z.R.; Connelly, C.F.; Fabrizio, D.; Gay, L.; Ali, S.M.; Ennis, R.; Schrock, A.; Campbell, B.; Shlien, A.; Chmielecki, J.; et al. Analysis of 100,000 human cancer genomes reveals the landscape of tumor mutational burden. Genome Med. 2017, 9, 34. [Google Scholar] [CrossRef] [Scilit]
- Moore, J.A.; Chen, K.T.; Madison, R.; Newberg, J.Y.; Fleischmann, Z.; Wang, S.; Sharaf, R.; Murugesan, K.; Fendler, B.J.; Hughes, J.; et al. Pan-Cancer Analysis of Copy-Number Features Identifies Recurrent Signatures and a Homologous Recombination Deficiency Biomarker to Predict Poly (ADP-Ribose) Polymerase Inhibitor Response. JCO Precis. Oncol. 2023, 7, e2300093. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Trabucco, S.E.; Gowen, K.; Maund, S.L.; Sanford, E.; Fabrizio, D.A.; Hall, M.J.; Yakirevich, E.; Gregg, J.P.; Stephens, P.J.; Frampton, G.M.; et al. A Novel Next-Generation Sequencing Approach to Detecting Microsatellite Instability and Pan-Tumor Characterization of 1000 Microsatellite Instability-High Cases in 67,000 Patient Samples. J. Mol. Diagn. 2019, 21, 1053–1066. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alexandrov, L.B.; Kim, J.; Haradhvala, N.J.; Huang, M.N.; Tian Ng, A.W.; Wu, Y.; Boot, A.; Covington, K.R.; Gordenin, D.A.; Bergstrom, E.N.; et al. The repertoire of mutational signatures in human cancer. Nature 2020, 578, 94–101. [Google Scholar] [CrossRef] [Scilit]
- He, J.; Abdel-Wahab, O.; Nahas, M.K.; Wang, K.; Rampal, R.K.; Intlekofer, A.M.; Patel, J.; Krivstov, A.; Frampton, G.M.; Young, L.E.; et al. Integrated genomic DNA/RNA profiling of hematologic malignancies in the clinical setting. Blood 2016, 127, 3004–3014. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nguyen, D.; Kantarjian, H.M.; Short, N.J.; Qiao, W.; Ning, J.; Cuglievan, B.; Daver, N.G.; DiNardo, C.D.; Jabbour, E.J.; Kadia, T.M.; et al. Early mortality in acute myeloid leukemia with KMT2A rearrangement is associated with high risk of bleeding and disseminated intravascular coagulation. Cancer 2023, 129, 1856–1865. [Google Scholar] [CrossRef] [Scilit]
- Meyer, C.; Burmeister, T.; Gröger, D.; Tsaur, G.; Fechina, L.; Renneville, A.; Sutton, R.; Venn, N.C.; Emerenciano, M.; Pombo-de-Oliveira, M.S.; et al. The MLL recombinome of acute leukemias in 2017. Leukemia 2018, 32, 273–284. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fiskus, W.; Boettcher, S.; Daver, N.; Mill, C.P.; Sasaki, K.; Birdwell, C.E.; Davis, J.A.; Takahashi, K.; Kadia, T.M.; DiNardo, C.D.; et al. Effective Menin inhibitor-based combinations against AML with MLL rearrangement or NPM1 mutation (NPM1c). Blood Cancer J. 2022, 12, 5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, Y.; Zhou, B.; Mao, F.; Xu, J.; Miao, H.; Zou, Z.; Phuc Khoa, L.T.; Jang, Y.; Cai, S.; Witkin, M.; et al. HOXA9 Reprograms the Enhancer Landscape to Promote Leukemogenesis. Cancer Cell 2018, 34, 643–658.e5. [Google Scholar] [CrossRef] [Scilit]
- Swaminathan, M.; Bourgeois, W.; Armstrong, S.A.; Wang, E.S. Menin Inhibitors in Acute Myeloid Leukemia-What Does the Future Hold? Cancer J. 2022, 28, 62–66. [Google Scholar] [CrossRef] [Scilit]
- Yin, L.; Wan, L.; Zhang, Y.; Hua, S.; Shao, X. Recent Developments and Evolving Therapeutic Strategies in KMT2A-Rearranged Acute Leukemia. Cancer Med. 2024, 13, e70326. [Google Scholar] [CrossRef] [Scilit]
- Super, H.J.; McCabe, N.R.; Thirman, M.J.; Larson, R.A.; Le Beau, M.M.; Pedersen-Bjergaard, J.; Philip, P.; Diaz, M.O.; Rowley, J.D. Rearrangements of the MLL gene in therapy-related acute myeloid leukemia in patients previously treated with agents targeting DNA-topoisomerase II. Blood 1993, 82, 3705–3711. [Google Scholar] [CrossRef] [Scilit]
- Candoni, A.; Coppola, G. A 2024 Update on Menin Inhibitors. A New Class of Target Agents against KMT2A-Rearranged and NPM1-Mutated Acute Myeloid Leukemia. Hematol. Rep. 2024, 16, 244–254. [Google Scholar] [CrossRef] [Scilit]
- Syed, Y.Y. Revumenib: First Approval. Drugs 2025, 85, 577–583. [Google Scholar] [CrossRef] [Scilit]
- Lynch, E.J.; Faro, S.J.E.; Lindstrom, A.M.; Sethi, N.A.; Wang, W.Y.; Seligson, N.D. Revumenib for Relapsed or Refractory Acute Leukemia With a KMT2A Translocation. Ann. Pharmacother. 2025, 59, 1108–1118. [Google Scholar] [CrossRef] [Scilit]
- Othman, J.; Potter, N.; Freeman, S.D.; McCarthy, N.; Jovanovic, J.; Runglall, M.; Canham, J.; Thomas, I.; Johnson, S.; Gilkes, A.; et al. Induction chemotherapy and molecular MRD influence outcomes in KMT2A-rearranged AML. Blood 2025, 146, 1862–1867. [Google Scholar] [CrossRef] [Scilit]
- Wang, E.S.; Issa, G.C.; Erba, H.P.; Altman, J.K.; Montesinos, P.; DeBotton, S.; Walter, R.B.; Pettit, K.; Savona, M.R.; Shah, M.V.; et al. Ziftomenib in relapsed or refractory acute myeloid leukaemia (KOMET-001): A multicentre, open-label, multi-cohort, phase 1 trial. Lancet Oncol. 2024, 25, 1310–1324. [Google Scholar] [CrossRef] [Scilit]
- Kwon, M.C.; Thuring, J.W.; Querolle, O.; Dai, X.; Verhulst, T.; Pande, V.; Marien, A.; Goffin, D.; Wenge, D.V.; Yue, H.; et al. Preclinical efficacy of the potent, selective menin-KMT2A inhibitor JNJ-75276617 (bleximenib) in KMT2A- and NPM1-altered leukemias. Blood 2024, 144, 1206–1220. [Google Scholar] [CrossRef] [Scilit]
- Zeidner, J.F.; Lin, T.L.; Welkie, R.L.; Curran, E.; Koenig, K.; Stock, W.; Madanat, Y.F.; Swords, R.; Baer, M.R.; Blum, W.; et al. Azacitidine, Venetoclax, and Revumenib for Newly Diagnosed NPM1-Mutated or KMT2A-Rearranged AML. J. Clin. Oncol. 2025, 43, 2606–2615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hoffmeister, L.M.; Orhan, E.; Walter, C.; Niktoreh, N.; Hanenberg, H.; von Neuhoff, N.; Reinhardt, D.; Schneider, M. Impact of KMT2A Rearrangement and CSPG4 Expression in Pediatric Acute Myeloid Leukemia. Cancers 2021, 13, 4817. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al Jadir, R.Q.; Abdulameer, S.A.; Alalsaidissa, J.N.; AlJabban, A. Lysine (K)-specific methyltransferase 2A (KMT2A) rearrangements among Iraqi de novo acute myeloid leukemia. Iraqi J. Hematol. 2024, 13, 269–274. [Google Scholar] [CrossRef] [Scilit]
- Hinai, A.; Pratcorona, M.; Grob, T.; Kavelaars, F.G.; Bussaglia, E.; Sanders, M.A.; Nomdedeu, J.; Valk, P.J.M. The Landscape of KMT2A-PTD AML: Concurrent Mutations, Gene Expression Signatures, and Clinical Outcome. Hemasphere 2019, 3, e181. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xie, D.H.; Chen, W.M.; Hao, Y.; Wang, X.; Li, L.D.; Li, J.Y.; Li, Z.Y.; Jiang, H.; Jiang, Q.; Huang, X.J.; et al. The Characteristics and Outcomes of Adult Acute Myeloid Leukemia Patients With KMT2A-Partial Tandem Duplication. Int. J. Lab. Hematol. 2025, 47, 1119–1127. [Google Scholar] [CrossRef] [Scilit]
- Wei, Q.; Hu, S.; Xu, J.; Loghavi, S.; Daver, N.; Toruner, G.A.; Wang, W.; Medeiros, L.J.; Tang, G. Detection of KMT2A Partial Tandem Duplication by Optical Genome Mapping in Myeloid Neoplasms: Associated Cytogenetics, Gene Mutations, Treatment Responses, and Patient Outcomes. Cancers 2024, 16, 4193. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seto, A.; Downs, G.; King, O.; Salehi-Rad, S.; Baptista, A.; Chin, K.; Grenier, S.; Nwachukwu, B.; Tierens, A.; Minden, M.D.; et al. Genomic Characterization of Partial Tandem Duplication Involving the KMT2A Gene in Adult Acute Myeloid Leukemia. Cancers 2024, 16, 1693. [Google Scholar] [CrossRef] [Scilit]
- Bawwab, A.; Nurse, D.P.; El-Asmar, J.; Abu-Farsakh, Y.; Albliwi, M.; Hanna, J.; Rauf, A.; Batah, H.; Abuamsha, H.; Zabor, E.C.; et al. Comprehensive Analysis of KMT2A Alterations in Acute Myeloid Leukemia and Their Impact on Survival and Response Rates; A Single Center Experience. Blood 2024, 144, 4249. [Google Scholar] [CrossRef] [Scilit]
- Yaeger, R.; Weiss, J.; Pelster, M.S.; Spira, A.I.; Barve, M.; Ou, S.I.; Leal, T.A.; Bekaii-Saab, T.S.; Paweletz, C.P.; Heavey, G.A.; et al. Adagrasib with or without Cetuximab in Colorectal Cancer with Mutated KRAS G12C. N. Engl. J. Med. 2023, 388, 44–54. [Google Scholar] [CrossRef] [Scilit]
- Lavallée, V.P.; Baccelli, I.; Krosl, J.; Wilhelm, B.; Barabé, F.; Gendron, P.; Boucher, G.; Lemieux, S.; Marinier, A.; Meloche, S.; et al. The transcriptomic landscape and directed chemical interrogation of MLL-rearranged acute myeloid leukemias. Nat. Genet. 2015, 47, 1030–1037. [Google Scholar] [CrossRef] [Scilit]
- Bill, M.; Mrózek, K.; Kohlschmidt, J.; Eisfeld, A.K.; Walker, C.J.; Nicolet, D.; Papaioannou, D.; Blachly, J.S.; Orwick, S.; Carroll, A.J.; et al. Mutational landscape and clinical outcome of patients with de novo acute myeloid leukemia and rearrangements involving 11q23/KMT2A. Proc. Natl. Acad. Sci. USA 2020, 117, 26340–26346. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, Y.; Yuan, X.; Lai, X.; Liu, L.; Liang, Y.; Yang, L.; Zhu, P.; Shi, J.; Yu, J.; Zhao, Y.; et al. KRAS mutation status critically determines the clinical outcome of patients with KMT2A-rearranged acute myeloid leukemia. Cancer 2025, 131, e35941. [Google Scholar] [CrossRef] [Scilit]
- Yuen, K.Y.; Liu, Y.; Zhou, Y.Z.; Wang, Y.; Zhou, D.H.; Fang, J.P.; Xu, L.H. Mutational landscape and clinical outcome of pediatric acute myeloid leukemia with 11q23/KMT2A rearrangements. Cancer Med. 2023, 12, 1418–1430. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hyrenius-Wittsten, A.; Pilheden, M.; Sturesson, H.; Hansson, J.; Walsh, M.P.; Song, G.; Kazi, J.U.; Liu, J.; Ramakrishan, R.; Garcia-Ruiz, C.; et al. De novo activating mutations drive clonal evolution and enhance clonal fitness in KMT2A-rearranged leukemia. Nat. Commun. 2018, 9, 1770. [Google Scholar] [CrossRef] [Scilit]
- Miao, H.; Kim, E.; Chen, D.; Purohit, T.; Kempinska, K.; Ropa, J.; Klossowski, S.; Trotman, W.; Danet-Desnoyers, G.; Cierpicki, T.; et al. Combinatorial treatment with menin and FLT3 inhibitors induces complete remission in AML models with activating FLT3 mutations. Blood 2020, 136, 2958–2963. [Google Scholar] [CrossRef] [Scilit]
- Genovese, G.; Kähler, A.K.; Handsaker, R.E.; Lindberg, J.; Rose, S.A.; Bakhoum, S.F.; Chambert, K.; Mick, E.; Neale, B.M.; Fromer, M.; et al. Clonal hematopoiesis and blood-cancer risk inferred from blood DNA sequence. N. Engl. J. Med. 2014, 371, 2477–2487. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tashakori, M.; Kadia, T.; Loghavi, S.; Daver, N.; Kanagal-Shamanna, R.; Pierce, S.; Sui, D.; Wei, P.; Khodakarami, F.; Tang, Z.; et al. TP53 copy number and protein expression inform mutation status across risk categories in acute myeloid leukemia. Blood 2022, 140, 58–72. [Google Scholar] [CrossRef] [Scilit]
- Sallman, D.A.; Stahl, M. TP53-mutated acute myeloid leukemia: How can we improve outcomes? Blood 2025, 145, 2828–2833. [Google Scholar] [CrossRef] [Scilit]
- Sahasrabudhe, K.D.; Mims, A.S. Novel investigational approaches for high-risk genetic subsets of AML: TP53, KMT2A, FLT3. Hematol. Am. Soc. Hematol. Educ. Program 2022, 2022, 15–22. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ali, A.M.; Salih, G.F. Molecular and clinical significance of FLT3, NPM1, DNMT3A and TP53 mutations in acute myeloid leukemia patients. Mol. Biol. Rep. 2023, 50, 8035–8048. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sahajpal, N.S.; Mondal, A.K.; Ananth, S.; Njau, A.; Ahluwalia, P.; Jones, K.; Ahluwalia, M.; Okechukwu, N.; Savage, N.M.; Kota, V.; et al. Clinical performance and utility of a comprehensive next-generation sequencing DNA panel for the simultaneous analysis of variants, TMB and MSI for myeloid neoplasms. PLoS ONE 2020, 15, e0240976. [Google Scholar] [CrossRef] [Scilit] [PubMed]



Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.