


Simple Summary
The number of cancer survivors has increased dramatically in the past several decades. Research indicates that health behaviors, including having a healthy diet and engaging in regular exercise, may improve the treatment outcomes and quality of life of cancer survivors. Behavioral interventions using web and mobile technology may be feasible and acceptable approaches to modify physical activity and dietary behaviors. This review summarizes the feasibility, acceptability and estimated effects of physical activity and dietary interventions using web and mobile technology from the published studies.
Abstract
Background: Technology-based interventions are increasingly used to improve physical activity (PA) and diet. Methods: We conducted a systematic review of randomized controlled trials (RCTs) published up to August 2021 that tested mobile health (mHealth) PA and/or dietary interventions among cancer survivors and reported on the feasibility, satisfaction, behavioral change, and/or quality of life (QOL) outcomes. Results: In total, 61 articles were identified on PubMed, and 23 of those met the inclusion criteria. The most common cancers were breast (n = 1000), prostate (n = 713), and colorectal (n = 650). Participants were predominantly White (median: 84%, interquartile range (IQR): 20%) and college-educated (58%). The interventions varied, but the most common combination of components (six studies) was a website/mobile app with an activity tracker and coaching. In terms of duration, 70% (n = 16) of the interventions lasted 12 weeks. The median total tracker wear was 87% of the study days (IQR: 6%) and the median text-message reply rate was 73% (IQR 4%). Most participants (median: 87%; IQR: 16%) were satisfied with at least one intervention component. Eleven out of 18 studies examining behavioral change reported significant between-group differences and six out of 11 studies examining QoL reported significant improvements. Conclusions: mHealth interventions are a promising approach to improving the PA and diets of cancer survivors. Research in racially/ethnically and socioeconomically diverse populations is needed.
1. Introduction
As of January 2022, it was estimated that there were 18 million cancer survivors in the United States (US), and the prevalence of cancer in the US is projected to approach 26 million by 2040 [1]. Early detection and improvement in treatments have led to improved survival rates for cancer. Cancer survivors often deal with physical effects of cancer and its treatments, such as fatigue and pain, as well as psychological effects of cancer, ranging from fear of recurrence to anxiety and depression. Research indicates that health behaviors, including a healthy diet and regular physical activity, are associated with better treatment outcomes, quality of life (QoL), and overall survival in people with cancer [2,3,4,5,6]. In 2022, the American Cancer Society (ACS) updated its nutrition and physical activity guidelines for cancer survivors. These guidelines include being physically active and maintaining a healthy eating pattern that is high in vegetables, fruits, and whole grains and low in red and processed meats, sugar-sweetened beverages, highly processed foods, and refined grain products [7]. Similarly, the World Cancer Research Fund/American Institute for Cancer Research updated their expert report on diet, nutrition, physical activity, and cancer in 2018. In this report, the emphasis of their recommendations shifted toward an integrated pattern of behaviors [8]. Despite the known benefits of a healthy diet and physical activity, adherence to these recommendations is low among cancer survivors [9].
Mobile health (mHealth) is defined by the World Health Organization (WHO) as ‘medical and public health practices supported by a mobile device, such as mobile phone, patient monitoring devices, personal digital assistants and other wireless devices’ [10]. mHealth is becoming increasingly common in healthcare and represents a promising approach for increasing physical activity and modifying dietary behaviors. mHealth tools include, but are not limited to, websites, email, mobile applications (apps), text messaging, and wearable activity trackers. These tools can support goal setting, self-monitoring, and instruction, as well as provide feedback on physical activity and diet change [11]. A growing body of research has incorporated mHealth into lifestyle interventions to increase physical activity and modify dietary behaviors among different populations [12,13,14]. The purpose of this article is to summarize published studies reporting on mHealth physical activity and/or dietary interventions among cancer survivors.
2. Methods
This systematic review is registered in Open Science (Registration DOI: 10.17605/OSF.IO/8EYC2) and was performed in accordance with the Preferred Reporting Items for Systematic Review and Meta-Analysis (PRISMA) guidelines [15].
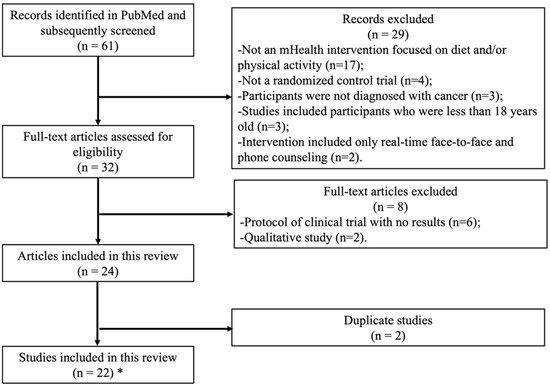
In this review, we summarize findings from recent (in the past ~5 years) randomized controlled trials (RCTs) with mHealth interventions focused on healthy diet and/or physical activity promotion in cancer survivors, defined as any person who has been diagnosed with cancer [16]. We define an mHealth intervention as one that includes a website/mobile app, text messages, and/or activity trackers. Given how quickly mHealth technology changes, we used 2016 as the earliest cut-off date for our search. As shown in Figure 1, we used the following search terms to identify relevant titles and abstracts in PubMed: mHealth intervention (digital OR website OR text message OR app OR Fitbit OR “wearable device” OR tracker), cancer patients or cancer survivors, dietary and/or physical activity (lifestyle OR behavioral OR physical activity OR exercise OR diet OR nutrition), and intervention. We selected “clinical trial” as the article type in the PubMed search filters. A single author (LW) reviewed titles and abstracts of papers published from 1 January 2016 to 13 August 2021 and written in English that examined an mHealth intervention among adult cancer survivors (aged 18 or over) to determine eligibility (n = 61).
Figure 1.
Flow chart of study selection. Search terms: (“2016/01/01”[Date—Publication]: “2021/08/13/”[Date—Publication]) AND (digital [tiab] OR website [tiab] OR text message [tiab] OR app [tiab] OR Fitbit [tiab] OR “wearable device”[tiab] OR tracker [tiab]) AND (lifestyle [tiab] OR behavioral [tiab] OR physical activity [tiab] OR exercise [tiab] OR diet [tiab] OR nutrition) AND (intervention [tiab]) AND (cancer [tiab]) AND (survivors OR patients). * One article that was suggested by the reviewer but was not found by our search criteria, though it did meet the inclusion criteria, was added. The total number of studies included in this review was 23.
To be included, studies were required to meet the following criteria: a randomized control trial with adult participants (aged 18 or over) testing an mHealth physical activity and/or dietary intervention. Studies were excluded if only real-time telephone calls and/or video calls and/or non-automated text messaging were used as the intervention. One of the advantages of a mHealth intervention is reduced person-time required per patient (from staff or other interventionists). Therefore, we included an inclusion criterion that some aspect was not executed in real-time by a human. If the intervention included only direct coaching by phone, the intervention did not meet our definition of a digital health intervention and was excluded.
The results of the search and reasons for ineligibility can be found in Figure 1. Information from the titles and abstracts was used to determine whether the papers met our eligibility criteria. The most common reason for exclusion was an intervention that was not targeted at physical activity and/or dietary behavioral change or was not an mHealth intervention (n = 17). We also excluded studies with participants who were not diagnosed with cancer (n = 3), studies that were not randomized controlled trials (n = 4), and articles that included participants who were less than 18 years old (n = 3). Lastly, to focus on scalable mHealth interventions, we excluded two articles reporting interventions that included only real-time telephone calls, video calls, and/or non-automated text messaging (e.g., direct text messaging with a human). Of the remaining 32 articles that were determined eligible for a full-text review, 24 articles (22 studies, including two studies with different portions of their results each reported in two separate articles) were deemed eligible for this review (Furthermore, one article that was suggested by the reviewer but was not found by our search criteria, yet did meet the inclusion criteria, was added. The total number of studies included in this review, therefore, was 23).
Predefined data-extraction tables were used to summarize the study design and participant characteristics (Table 1), intervention characteristics and findings of behavioral change (Table 2), and findings concerning the feasibility of and satisfaction with the intervention (Table 3). A narrative approach was used to synthesize a study of the characteristics and key findings of the included evidence [17].
The quality of the study design was assessed by a trained reviewer (LW) for each study using a scoring system adapted from a review of eHealth interventions [18,19,20]. A score was assigned to each study based on the following nine methodological characteristics: individual randomization, use of a control group for comparison, testing a single technology, use of pre-/posttest design, participant retention, equivalence of baseline groups, handling missing data, sample size calculation, and validity of measures. The range of possible scores was 0–100%. Studies were not excluded based on their quality scores.
Table 1.
Randomized controlled trials of mHealth interventions focused on a healthy diet and physical activity among cancer survivors (2016–2021).
Table 2.
Combination of mHealth intervention tools used in randomized controlled trials among cancer survivors to promote physical activity and/or dietary change, and associations with change in physical activity, diet, and/or quality of life, sorted by outcome measure.
Table 3.
Adherence to and acceptance of mHealth behavioral interventions tested in randomized controlled trials among cancer survivors.
3. Results
3.1. Demographic Characteristics
Table 1 summarizes each study included in this review. Across the 23 unique studies, 2538 participants were enrolled, 54% of whom were female (n = 1359). Most studies (n = 16 described in 18 articles) included breast cancer, prostate cancer, and/or colorectal cancer survivors [23,25,26,27,28,29,31,33,34,35,36,37,38,39,41,42,43,44]. Besides these 16 studies, four studies included survivors of breast cancer and other cancer types (gynecologic cancer, testicular cancer, gastrointestinal cancer, lung cancer, osteosarcoma, and other rare cancers) [22,30,40,45], one included survivors of colorectal cancer and gynecologic cancer [32], one study included survivors of breast cancer, colorectal cancer, and other cancer types (endometrial cancer, bladder cancer, kidney cancer) [21], and one study included survivors of leukemia and lymphoma [24]. The most prevalent type of cancer diagnosis was breast cancer (n = 1000), followed by prostate cancer (n = 713) and colorectal cancer (n = 650). There were 175 participants diagnosed with other cancers (gynecologic cancer, testicular cancer, gastrointestinal cancer, leukemia, lymphoma, bladder cancer, kidney cancer, lung cancer, osteosarcoma, and others). Participants in 18 of the 23 studies had completed their primary cancer treatment before enrollment.
The sample sizes of the 23 studies varied from 20 to 492 participants. Eighteen out of the 23 studies had a sample size less than 100. The mean age of participants across studies was 59.1 years (reported in 20 studies); the lowest and highest within-study mean age were 33.6 [40] and 71.6 years [22], respectively. Twelve of the 23 studies reported race/ethnicity [22,23,27,28,30,32,35,36,38,39,42,43]. In these 12 studies, participants were predominantly White [median: 84%, interquartile range (IQR): 20%]. Among the 15 studies [22,23,28,29,30,32,35,36,38,39,41,42,43,44,45] that reported information on the education of their participants, more than half (58%) of the participants were college-educated. Among the 10 studies [21,23,28,29,30,38,39,42,43,44] that reported participants’ work status, 49% of participants worked full- or part-time.
3.2. Intervention Details
Of the 23 unique studies, 15 focused on physical activity only, two studies focused on diet only, and six studies targeted both physical activity and dietary change. Table 2 shows that, across the 23 interventions, 19 used websites/mobile apps, 15 included wearable activity trackers, 13 included in-person/telephone/video call/email coaching by study staff, and eight sent automated short message service (SMS) text messages to their participants. The most common combination of tools was a web/mobile app intervention with a wearable activity tracker and coaching by group session, email, or phone video call (n = 6) [22,26,27,31,32,42,43], followed by five studies that examined a web/mobile app intervention alone (n = 5) [21,29,40,44,45]. Across the eight studies that used text messages as one of the intervention tools, the frequency of text messages varied from once weekly to once daily. Four studies included text messages that asked for a reply.
Most studies used usual care and/or information concerning a healthy diet and/or physical activity as their comparator (control) intervention (n = 14). Six studies had waitlist controls where participants in the control group had the option to receive a delayed intervention [21,25,28,31,39,41]. Four studies [22,24,30,39] had Fitbit-only controls. The duration of the intervention ranged from 4 weeks to 6 months; the most common duration was 12 weeks (n = 16). Retention in the studies ranged from 32% to 100%, with a mean retention of 86%. The lowest retention, 32%, was reported by Short et al. from a study that tested a 12-week web-only intervention, aiming to examine different delivery schedules of physical activity advice modules among breast cancer survivors [44]. Studies with an intervention that included a wearable activity tracker had the highest mean retention rate (91%), and studies with an intervention that included a website/app only had the lowest (72%).
3.3. Feasibility and Acceptability
Feasibility (adherence) was reported in 19 out of the 23 studies (Table 3). It was defined differently across studies, including as website/mobile app usage, the wear time of wearable activity trackers, and/or response rates to text messages. Among the 19 studies that included a website/mobile app, six studies [21,23,28,31,44] with 12-week interventions reported the median number of days participants visited the website/mobile app; these numbers varied from 2% to 15% of the 84 study days. One study by Finlay et al. measured website usage by the number of physical activity logs completed across one control and two intervention arms [29]. A higher number of completed weekly physical activity logs was observed in the intervention arm (mean: 2.6 ± 1.3) that received an intervention content module weekly for four weeks than in the intervention arm (mean: 1.5 ± 1.4) that had access to all the intervention modules at any time and in any order. Adherence to wearable activity trackers was reported in eight studies [22,24,30,32,35,38,39,43] out of 15 that included wearable activity trackers. Adherence levels were generally high, with a median 87% (IQR: 6%) of study days wearing the devices. All four studies that included interactive text messages reported the text message response rate [28,34,35,38]. Overall, participants were responsive, with the median reply level being to 73% (IQR: 4%) of the text messages that asked for a reply.
Acceptability was measured in 17 out of the 23 studies (Table 3). It was mainly measured by semi-structured interviews or surveys to assess the participants’ perceptions of, and satisfaction with, the overall intervention, wearable activity trackers, text messages, and/or website/mobile app. Among the 12 studies that measured satisfaction, most participants were satisfied or very satisfied with at least one of the intervention components (median 87%, IQR: 16%). In five studies, participants perceived wearable activity trackers to be helpful and important for physical activity [22,27,30,39,43]. Four [28,30,35,38] out of the eight studies that sent regular text messages to participants assessed the participants’ satisfaction with the text messages, and 73% to 90% of the participants in these four studies were satisfied with the text messages and/or agreed that text messages motivated them to be physically active. In the studies by Ormel et al. [40] and Van Blarigan et al. [38], more than three-quarters of the participants in the intervention group (79% and 88%, respectively) said they would continue to use the mobile app or wear the Fitbit after the study ended. In Valle et al.’s study, all 24 participants in the intervention group would recommend the program with an in-person individual coaching session providing information on weight gain and the use of a wireless scale, along with the wireless scale itself, 24 weekly email-delivered behavioral lessons, and an optional activity tracker [43].
3.4. Behavioral Change
A change in physical activity and/or dietary behaviors was estimated in 18 of the 23 studies. As shown in Table 2, 16 studies estimated the change in physical activity [21,22,24,27,29,30,32,34,36,38,39,40,41,42,43,44], five studies reported the change in the diet [24,28,39,43,45], and two studies reported the change in a lifestyle score based on both physical activity and diet [23,35].
Among the 16 studies that reported physical activity change [21,22,24,27,29,30,32,34,36,38,39,40,41,42,43,44], six reported an intervention arm having demonstrated an increase in step counts [22,27] and physical activity time, ranging from 45 to 345 min per week [22,27,32,34,36,40]. Two studies reported that the intervention arm maintained a weekly MVPA from pre- to post-intervention [30,41]. These improvements were significantly different from the control arms. The intervention components in the eight studies with significant between-group differences in physical activity varied. Three studies included a web/mobile app with a wearable activity tracker and coaching [22,27,32]. Four studies used at least two of these tools in their intervention (wearable activity tracker + coaching + text messages [30]/website + wearable activity tracker [41]/wearable activity tracker + coaching [36]/coaching + text message [34]). One study tested an intervention with a mobile app only [40].
Five studies reported a dietary change [24,28,39,43,45]. One testing a web-based dietary intervention with daily text messages among colorectal cancer survivors found significantly greater improvement in whole grain consumption, measured using dietary records collected with the National Cancer Institute’s Automated Self-Administered Dietary Assessment Tool (ASA-24) [46] in the intervention arm at the end of the 12-week intervention compared to the control arm [28]. This improvement was maintained at a 24-week follow-up. The other four studies observed no change in diet measured by a self-administered nutrition questionnaire that was developed by Gnagnarella et al. [45]. food frequency questionnaires [47] at clinic visits, automated self-administered 24-hour dietary recalls (ASA-24) [46], or 24-h diet recalls administered by the research assistant using the Sparkpeople.com food diary tool [39]. Of those four, one study tested a web-based intervention with online nutrition information among cancer patients who were not receiving enteral nutrition, parenteral nutrition, or palliative care, and not reporting significant weight loss in the last 6 months [45]. One tested an mHealth intervention with a 30-min telephone session, a wearable activity tracker, a dietary tracker, and coaching on goal-setting and feedback by email or text messages [24]. The other two were weight-management programs among African American breast cancer survivors. One tested a program with an individual coaching session, a wireless scale, 24 weekly email-delivered behavioral lessons, and an optional activity tracker [43]. The other estimated the effect of a program with an interactive website, a wearable activity tracker, and text messages [39].
Significant improvement was reported by both studies that measured physical activity and dietary change using a composite lifestyle score [23,25]. These two studies targeted both physical activity and dietary change among prostate cancer survivors. One of the studies used a web-based intervention with a wearable activity tracker, text messages, and optional telephone coaching [23]. The other used a web-based intervention with a wearable activity tracker and text messages [35].
3.5. Quality of Life
Among the 11 studies that examined changes in QoL, six studies observed improvements (Table 2) [25,26,31,33,41,45]. One study with a web-based intervention with wearable activity trackers and coaching that targeted both diet and physical activity found significantly greater improvement in the overall QoL score measured by the European Organization for Research and Treatment of Cancer’s Quality of Life Questionnaire-C30 (EORTC QLQ-C30) in the intervention arm at the end of the 12-week intervention compared to the control arm [31]. Another study with a web-based intervention, a wearable activity tracker, and coaching on physical activity reported significantly greater improvement in physical and mental health measured by the SF-36 Health Survey [26]. Greater mental health improvement was also observed in one study using a mobile app and coaching in an intervention focused on physical activity, measured by the SF-36 Health Survey [33]. A study with a web-based physical activity intervention and wearable activity trackers reported greater improvement in both physical functioning measured by the EORTC QLQ-C30 and fatigue measured by Checklist for Individual Strength (CIS) [41]. Greater role functioning improvement, measured by the EORTC QLQ-C30, was observed in one study with a dietary intervention that included text messages and coaching [45]. Lastly, improvements in sleep quality, including less waking after sleep onset and a reduced number of awakenings, were observed in one study with a wearable activity tracker, one face-to-face session, and five telephone-delivered behavioral counseling sessions [25].
4. Assessment of Risk of Bias
The study design quality score for each study is presented in Table 4. The mean study design quality score was 75%. All included studies were randomized studies with control groups. Behavior/QoL outcomes were assessed both pre- and post-intervention, and validated measurement of outcomes was used in all studies. Retention was above 80% for all but three studies [29,44,45]. Thirteen out of 23 studies reported a sample size calculation. Fourteen out of 23 studies conducted the data analysis with consideration of the impact of the missing data. Eight out of 23 studies conducted a test to confirm the balance of baseline characteristics between the study groups. However, only seven out of 23 studies were designed to test the effectiveness of an isolated piece of technology [21,22,29,34,39,40,45]; all other studies were designed to test the effectiveness of a combination of intervention tools.
Table 4.
Summary of risk of bias among randomized controlled trials testing mHealth behavioral interventions in cancer survivors.
5. Discussion
The results of the 23 studies (25 publications) reviewed here provide evidence of the feasibility and acceptability of using mHealth interventions to promote behavioral change (diet and/or physical activity) among cancer survivors. Among the 23 studies, most focused on physical activity (n = 15) or targeted both physical activity and the diet (n = 6), while only two studies focused on the diet alone. More studies with interventions focused specifically on the diet are needed to assess the feasibility and acceptability, and improve the effectiveness, of mHealth dietary interventions. Additionally, only four out of the 23 studies evaluated 6-month interventions; the duration of the rest of the studies ranged from 4–16 weeks. Thus, the feasibility, adherence, and acceptability of these interventions over a longer period are unknown.
Text messaging was commonly used as part of mHealth interventions, in combination with other components. Most of the text messages focused on providing tailored health promotion information and behavioral prompts. Personalized text messages with dietary behavior or physical activity information and reminders can motivate and support a change of behavior. Text messages that solicit a reply may increase participants’ engagement [20]. However, there is a lack of consensus or conclusive evidence from this review regarding the optimal frequency and timing of text messages.
Wearable activity trackers, alone or in combination with other mHealth tools, were a feasible method to increase physical activity. Wearable activity trackers provide objective measures of physical activity and exercise [48]. They can also prompt behavioral change in real-time, assist users to self-monitor their physical activity, and provide automated feedback and rewards. These are behavioral change techniques associated with positive physical activity changes [49]. Adherence to wearing activity trackers was high, suggesting these devices are feasible and acceptable to participants. However, there was no standardized method for reporting wearable activity tracker outcomes, including adherence, validity, and physical activity measures [50]. The heterogeneous reporting of methods and results among studies using wearable physical activity trackers makes it difficult to compare findings across studies.
All included studies evaluated short-term (6 months or less) effects of mHealth interventions in relatively small sample sizes. The longer-term effects of mHealth interventions on maintaining physical activity and/or dietary behavioral change are unknown [51]. Tools such as websites/mobile apps, text messages, and wearable activity trackers in mHealth interventions may be useful for providing ongoing monitoring and support to cancer survivors, but studies with longer intervention and follow-up periods are needed to assess whether participants maintain engagement with mHealth interventions over time.
Of the 23 included studies, only one focused on the older population (≥65 years) [22]. This group carries a severe and disproportionate burden of cancer since two-thirds of cancer survivors are aged 65 or older in the US [1]. Additionally, in this review, most of the participants identified as White across the 12 studies that reported race/ethnicity, and more than half of the participants had at least a college/university degree across the 15 studies that reported education information. The lack of racial/ethnic and socioeconomic diversity in published studies is a limitation. mHealth interventions hold promise for improving health among underserved populations through low-cost approaches since they can be largely automated and disseminate information effectively. However, access and technology literacy are potential barriers. Data from the Pew Research Center showed that, as of 2020, 85% of Americans own a smartphone [52]. While overall smartphone ownership is high, it varies based on age, household income, and educational attainment. Bommakanti et al. [53] reported that patients who were older, male, less educated, and/or had a lower annual income were less likely to own smartphones, and thus could miss out on mHealth interventions requiring personal smartphone ownership. Patients might also be unwilling or unable to engage with mHealth interventions due to low smartphone literacy. On the other hand, a review from Armaou et al. [54] supported the effectiveness of web-based interventions to improve health in racial/ethnic minority and historically underserved communities. Studies have shown that linguistic and cultural tailoring can improve the effectiveness of health promotion interventions in minority or underserved populations [55,56]. Overall, more research is needed to assess the feasibility and acceptability of mHealth interventions in underrepresented populations. These interventions need to be tailored to the language and sociocultural characteristics of the target population.
Our review was limited in that all studies were identified through one database (PubMed). We also restricted our literature search to articles written in English. Therefore, relevant studies published in other databases or languages may have been missed. We did not exclude studies based on their quality scores. However, all included studies met at least five of the nine criteria. Additionally, as with other systematic reviews of published literature, there is the possibility of publication bias. In particular, four studies [23,28,30,38] listed QoL as one of their secondary or exploratory endpoints on clinicaltrial.gov, but had not yet reported results in the peer-reviewed literature at the time of our search. Of them, two studies reported their results on QoL in separate papers [57,58] published after our search date.
6. Conclusions
Our results show that mHealth interventions are a promising approach to improving physical activity and dietary behaviors in cancer survivors. To better establish the optimal types and combination of mHealth interventions for cancer survivors, alternative study designs, as described by the Multiphase Optimization Strategy framework, may be useful [59]. Additionally, studies with larger sample sizes, longer study periods, and more racially/ethnically and socioeconomically diverse study populations are needed.
Author Contributions
Conceptualization, L.W. and E.L.V.B.; methodology, L.W.; data curation, L.W.; writing—original draft preparation, L.W.; writing—review and editing, all authors. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
All included studies involving human participants were in accordance with the 1964 Helsinki Declaration and its later amendments or comparable ethical standards and were reviewed and approved by the relevant Medical Ethics committee/Institutional Review Broads.
Informed Consent Statement
Informed consent was obtained from all participants in all included studies.
Data Availability Statement
Data are available from the authors upon request.
Conflicts of Interest
The authors declare no conflict of interest.
References
- American Cancer Society. Cancer Treatment & Survivorship Facts & Figures 2022–2024; American Cancer Society: Atlanta, GA, USA, 2022. [Google Scholar]
- Balhareth, A.; Aldossary, M.Y.; McNamara, D. Impact of physical activity and diet on colorectal cancer survivors’ quality of life: A systematic review. World J. Surg. Oncol. 2019, 17, 153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bourke, L.; Smith, D.; Steed, L.; Hooper, R.; Carter, A.; Catto, J.; Albertsen, P.C.; Tombal, B.; Payne, H.A.; Rosario, D.J. Exercise for Men with Prostate Cancer: A Systematic Review and Meta-analysis. Eur. Urol. 2016, 69, 693–703. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mehra, K.; Berkowitz, A.; Sanft, T. Diet, Physical Activity, and Body Weight in Cancer Survivorship. Med. Clin. N. Am. 2017, 101, 1151–1165. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grosso, G.; Bella, F.; Godos, J.; Sciacca, S.; Del Rio, D.; Ray, S.; Galvano, F.; Giovannucci, E.L. Possible role of diet in cancer: Systematic review and multiple meta-analyses of dietary patterns, lifestyle factors, and cancer risk. Nutr. Rev. 2017, 75, 405–419. [Google Scholar] [CrossRef] [Scilit]
- Schmitz, K.H.; Courneya, K.S.; Matthews, C.; Demark-Wahnefried, W.; Galvão, D.A.; Pinto, B.M.; Irwin, M.L.; Wolin, K.Y.; Segal, R.J.; Lucia, A.; et al. American College of Sports Medicine roundtable on exercise guidelines for cancer survivors. Med. Sci. Sports Exerc. 2010, 42, 1409–1426. [Google Scholar] [CrossRef] [Scilit]
- Rock, C.L.; Thomson, C.A.; Sullivan, K.R.; Howe, C.L.; Kushi, L.H.; Caan, B.J.; Neuhouser, M.L.; Bandera, E.V.; Wang, Y.; Robien, K.; et al. American Cancer Society nutrition and physical activity guideline for cancer survivors. CA Cancer J. Clin. 2022, 72, 230–262. [Google Scholar] [CrossRef] [Scilit]
- Clinton, S.K.; Giovannucci, E.L.; Hursting, S.D. The World Cancer Research Fund/American Institute for Cancer Research Third Expert Report on Diet, Nutrition, Physical Activity, and Cancer: Impact and Future Directions. J. Nutr. 2020, 150, 663–671. [Google Scholar] [CrossRef] [Scilit]
- Hyland, K.A.; Jacobs, J.M.; Lennes, I.T.; Pirl, W.F.; Park, E.R. Are cancer survivors following the national comprehensive cancer network health behavior guidelines? An assessment of patients attending a cancer survivorship clinic. J. Psychosoc. Oncol. 2018, 36, 64–81. [Google Scholar] [CrossRef] [Scilit]
- WHO Global Observatory for eHealth. mHealth: New Horizons for Health through Mobile Technologies: Second Global Survey on eHealth. Published Online 2011. Available online: https://apps.who.int/iris/handle/10665/44607 (accessed on 2 June 2022).
- Michie, S.; Ashford, S.; Sniehotta, F.F.; Dombrowski, S.U.; Bishop, A.; French, D.P. A refined taxonomy of behaviour change techniques to help people change their physical activity and healthy eating behaviours: The CALO-RE taxonomy. Psychol. Health 2011, 26, 1479–1498. [Google Scholar] [CrossRef] [Scilit]
- Ringeval, M.; Wagner, G.; Denford, J.; Paré, G.; Kitsiou, S. Fitbit-Based Interventions for Healthy Lifestyle Outcomes: Systematic Review and Meta-Analysis. J. Med. Internet Res. 2020, 22, e23954. [Google Scholar] [CrossRef] [Scilit]
- Smith, D.M.; Duque, L.; Huffman, J.C.; Healy, B.C.; Celano, C.M. Text Message Interventions for Physical Activity: A Systematic Review and Meta-analysis. Am. J. Prev. Med. 2020, 58, 142–151. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Villinger, K.; Wahl, D.R.; Boeing, H.; Schupp, H.T.; Renner, B. The effectiveness of app-based mobile interventions on nutrition behaviours and nutrition-related health outcomes: A systematic review and meta-analysis. Obes. Rev. 2019, 20, 1465–1484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. Syst. Rev. 2021, 10, 89. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Miller, K.D.; Nogueira, L.; Devasia, T.; Mariotto, A.B.; Yabroff, K.R.; Jemal, A.; Kramer, J.; Siegel, R.L. Cancer treatment and survivorship statistics, 2022. CA Cancer J. Clin. 2022. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Popay, J.; Roberts, H.; Sowden, A.; Petticrew, M.; Arai, L.; Rodgers, M.; Britten, N.; Roen, K.; Duffy, S. Guidance on the Conduct of Narrative Synthesis in Systematic Reviews; Academia: San Francisco, CA, USA, 2006. [Google Scholar]
- Norman, G.J.; Zabinski, M.F.; Adams, M.A.; Rosenberg, D.E.; Yaroch, A.L.; Atienza, A.A. A Review of eHealth Interventions for Physical Activity and Dietary Behavior Change. Am. J. Prev. Med. 2007, 33, 336–345. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cole-Lewis, H.; Kershaw, T. Text Messaging as a Tool for Behavior Change in Disease Prevention and Management. Epidemiol Rev. 2010, 32, 56–69. [Google Scholar] [CrossRef] [Scilit]
- Shaw, R.; Bosworth, H. Short message service (SMS) text messaging as an intervention medium for weight loss: A literature review. Health Inform. J. 2012, 18, 235–250. [Google Scholar] [CrossRef] [Scilit]
- Rees-Punia, E.; Leach, C.R.; Westmaas, J.L.; Dempsey, L.F.; Roberts, A.M.; Nocera, J.R.; Patel, A.V. Pilot Randomized Controlled Trial of Feasibility, Acceptability, and Preliminary Efficacy of a Web-Based Physical Activity and Sedentary Time Intervention for Survivors of Physical Inactivity-Related Cancers. Int. J. Behav. Med. 2022, 29, 220–229. [Google Scholar] [CrossRef] [Scilit]
- Pinto, B.M.; Kindred, M.; Franco, R.; Simmons, V.; Hardin, J. A “novel” multi-component approach to promote physical activity among older cancer survivors: A pilot randomized controlled trial. Acta. Oncol. 2021, 60, 968–975. [Google Scholar] [CrossRef] [Scilit]
- Chan, J.M.; Van Blarigan, E.L.; Langlais, C.S.; Zhao, S.; Ramsdill, J.W.; Daniel, K.; Macaire, G.; Wang, E.; Paich, K.; Kessler, E.R.; et al. Feasibility and Acceptability of a Remotely Delivered, Web-Based Behavioral Intervention for Men With Prostate Cancer: Four-Arm Randomized Controlled Pilot Trial. J. Med. Internet Res. 2020, 22, e19238. [Google Scholar] [CrossRef] [Scilit]
- Chow, E.J.; Doody, D.R.; Di, C.; Armenian, S.H.; Baker, K.S.; Bricker, J.B.; Gopal, A.K.; Hagen, A.M.; Ketterl, T.G.; Lee, S.J.; et al. Feasibility of a behavioral intervention using mobile health applications to reduce cardiovascular risk factors in cancer survivors: A pilot randomized controlled trial. J. Cancer Surviv. 2020, 15, 554–563. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nguyen, N.H.; Vallance, J.K.; Buman, M.P.; Moore, M.M.; Reeves, M.M.; Rosenberg, D.E.; Boyle, T.; Milton, S.; Friedenreich, C.M.; English, D.R.; et al. Effects of a wearable technology-based physical activity intervention on sleep quality in breast cancer survivors: The ACTIVATE Trial. J. Cancer Surviv. 2021, 15, 273–280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rastogi, S.; Tevaarwerk, A.J.; Sesto, M.; Van Remortel, B.; Date, P.; Gangnon, R.; Thraen-Borowski, K.; Cadmus-Bertram, L. Effect of a technology-supported physical activity intervention on health-related quality of life, sleep, and processes of behavior change in cancer survivors: A randomized controlled trial. Psychooncology 2020, 29, 1917–1926. [Google Scholar] [CrossRef] [Scilit]
- Cadmus-Bertram, L.; Tevaarwerk, A.J.; Sesto, M.E.; Gangnon, R.; Van Remortel, B.; Date, P. Building a physical activity intervention into clinical care for breast and colorectal cancer survivors in Wisconsin: A randomized controlled pilot trial. J. Cancer Surviv. 2019, 13, 593–602. [Google Scholar] [CrossRef] [Scilit]
- Van Blarigan, E.L.; Kenfield, S.A.; Chan, J.M.; Van Loon, K.; Paciorek, A.; Zhang, L.; Chan, H.; Savoie, M.B.; Bocobo, A.G.; Liu, V.N.; et al. Feasibility and Acceptability of a Web-Based Dietary Intervention with Text Messages for Colorectal Cancer: A Randomized Pilot Trial. Cancer Epidemiol. Biomark. Prev. 2020, 29, 752–760. [Google Scholar] [CrossRef] [Scilit]
- Finlay, A.; Evans, H.; Vincent, A.; Wittert, G.; Vandelanotte, C.; Short, C.E. Optimising Web-Based Computer-Tailored Physical Activity Interventions for Prostate Cancer Survivors: A Randomised Controlled Trial Examining the Impact of Website Architecture on User Engagement. Int. J. Environ. Res. Public Health 2020, 17, 7920. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gell, N.M.; Grover, K.W.; Savard, L.; Dittus, K. Outcomes of a text message, Fitbit, and coaching intervention on physical activity maintenance among cancer survivors: A randomized control pilot trial. J. Cancer Surviv. 2020, 14, 80–88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mohamad, H.; Ntessalen, M.; Craig, L.C.A.; Clark, J.; Fielding, S.; N’Dow, J.; Heys, S.D.; McNeill, G. A self-help diet and physical activity intervention with dietetic support for weight management in men treated for prostate cancer: Pilot study of the Prostate Cancer Weight Management (PRO-MAN) randomised controlled trial. Br. J. Nutr. 2019, 122, 592–600. [Google Scholar] [CrossRef] [Scilit]
- Maxwell-Smith, C.; Hince, D.; Cohen, P.; Bulsara, M.K.; Boyle, T.; Platell, C.; Tan, P.; Levitt, M.; Salama, P.; Tan, J.; et al. A randomized controlled trial of WATAAP to promote physical activity in colorectal and endometrial cancer survivors. Psychooncology 2019, 28, 1420–1429. [Google Scholar] [CrossRef] [Scilit]
- Dong, X.; Yi, X.; Gao, D.; Gao, Z.; Huang, S.; Chao, M.; Chen, W.; Ding, M. The effects of the combined exercise intervention based on internet and social media software (CEIBISMS) on quality of life, muscle strength and cardiorespiratory capacity in Chinese postoperative breast cancer patients:a randomized controlled trial. Health Qual. Life Outcomes 2019, 17, 109. [Google Scholar] [CrossRef] [Scilit]
- Gomersall, S.R.; Skinner, T.L.; Winkler, E.; Healy, G.N.; Eakin, E.; Fjeldsoe, B. Feasibility, acceptability and efficacy of a text message-enhanced clinical exercise rehabilitation intervention for increasing “whole-of-day” activity in people living with and beyond cancer. BMC Public Health 2019, 19 (Suppl. S2). [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kenfield, S.A.; Van Blarigan, E.L.; Ameli, N.; Lavaki, E.; Cedars, B.; Paciorek, A.T.; Monroy, C.; Tantum, L.K.; Newton, R.U.; Signorell, C.; et al. Feasibility, Acceptability, and Behavioral Outcomes from a Technology-enhanced Behavioral Change Intervention (Prostate 8): A Pilot Randomized Controlled Trial in Men with Prostate Cancer. Eur. Urol. 2019, 75, 950–958. [Google Scholar] [CrossRef] [Scilit]
- Mcneil, J.; Brenner, D.R.; Stone, C.R.; O’Reilly, R.; Ruan, Y.; Vallance, J.K.; Courneya, K.S.; Thorpe, K.; Klein, D.J.; Friedenreich, C.M. Activity Tracker to Prescribe Various Exercise Intensities in Breast Cancer Survivors. Med. Sci. Sports Exerc. 2019, 51, 930–940. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McNeil, J.; Fahim, M.; Stone, C.R.; O’Reilly, R.; Courneya, K.S.; Friedenreich, C.M. Adherence to a lower versus higher intensity physical activity intervention in the Breast Cancer & Physical Activity Level (BC-PAL) Trial. J. Cancer Surviv. 2022, 16, 353–365. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Blarigan, E.L.; Chan, H.; Van Loon, K.; Kenfield, S.A.; Chan, J.; Mitchell, E.; Zhang, L.; Paciorek, A.; Joseph, G.; Laffan, A.; et al. Self-monitoring and reminder text messages to increase physical activity in colorectal cancer survivors (Smart Pace): A pilot randomized controlled trial. BMC Cancer 2019, 19, 218. [Google Scholar] [CrossRef] [Scilit]
- Ferrante, J.M.; Devine, K.A.; Bator, A.; Rodgers, A.; Ohman-Strickland, P.A.; Bandera, E.V.; Hwang, K. Feasibility and potential efficacy of commercial mHealth/eHealth tools for weight loss in African American breast cancer survivors: Pilot randomized controlled trial. Transl. Behav. Med. 2018, 10, 938–948. [Google Scholar] [CrossRef] [Scilit]
- Ormel, H.L.; van der Schoot, G.G.F.; Westerink, N.D.L.; Sluiter, W.J.; Gietema, J.A.; Walenkamp, A.M.E. Self-monitoring physical activity with a smartphone application in cancer patients: A randomized feasibility study (SMART-trial). Support Care Cancer 2018, 26, 3915–3923. [Google Scholar] [CrossRef] [Scilit]
- Golsteijn, R.H.J.; Bolman, C.; Volders, E.; Peels, D.A.; de Vries, H.; Lechner, L. Short-term efficacy of a computer-tailored physical activity intervention for prostate and colorectal cancer patients and survivors: A randomized controlled trial. Int. J. Behav. Nutr. Phys. Act. 2018, 15, 106. [Google Scholar] [CrossRef] [Scilit]
- Mayer, D.K.; Landucci, G.; Awoyinka, L.; Atwood, A.K.; Carmack, C.L.; Demark-Wahnefried, W.; McTavish, F.; Gustafson, D.H. SurvivorCHESS To Increase Physical Activity In Colon Cancer Survivors: Can We Get Them Moving? J. Cancer Surviv. 2018, 12, 82–94. [Google Scholar] [CrossRef] [Scilit]
- Valle, C.G.; Deal, A.M.; Tate, D.F. Preventing weight gain in African American breast cancer survivors using smart scales and activity trackers: A randomized controlled pilot study. J. Cancer Surviv. 2017, 11, 133–148. [Google Scholar] [CrossRef] [Scilit]
- Short, C.E.; Rebar, A.; James, E.L.; Duncan, M.J.; Courneya, K.S.; Plotnikoff, R.; Crutzen, R.; Vandelanotte, C. How do different delivery schedules of tailored web-based physical activity advice for breast cancer survivors influence intervention use and efficacy? J. Cancer Surviv. 2017, 11, 80–91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gnagnarella, P.; Misotti, A.M.; Santoro, L.; Akoumianakis, D.; Del Campo, L.; De Lorenzo, F.; Lombardo, C.; Milolidakis, G.; Sullivan, R.; McVie, J.G. Nutritional Online Information for Cancer Patients: A Randomized Trial of an Internet Communication Plus Social Media Intervention. J. Cancer Educ. 2016, 31, 472–480. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- ASA24® Dietary Assessment Tool|EGRP/DCCPS/NCI/NIH. Available online: https://epi.grants.cancer.gov/asa24/ (accessed on 25 July 2022).
- Patterson, R.E.; Kristal, A.R.; Tinker, L.F.; Carter, R.A.; Bolton, M.P.; Agurs-Collins, T. Measurement Characteristics of the Women’s Health Initiative Food Frequency Questionnaire. Ann. Epidemiol. 1999, 9, 178–187. [Google Scholar] [CrossRef] [Scilit]
- Chiauzzi, E.; Rodarte, C.; DasMahapatra, P. Patient-centered activity monitoring in the self-management of chronic health conditions. BMC Med. 2015, 13, 77. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Olander, E.K.; Fletcher, H.; Williams, S.; Atkinson, L.; Turner, A.; French, D.P. What are the most effective techniques in changing obese individuals’ physical activity self-efficacy and behaviour: A systematic review and meta-analysis. Int. J. Behav. Nutr. Phys. Act. 2013, 10, 1–15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chan, A.; Chan, D.; Lee, H.; Ng, C.C.; Yeo, A.H.L. Reporting adherence, validity and physical activity measures of wearable activity trackers in medical research: A systematic review. Int. J. Med. Inform. 2022, 160, 104696. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Middleton, K.R.; Anton, S.D.; Perri, M.G. Long-Term Adherence to Health Behavior Change. Am. J. Lifestyle Med. 2013, 7, 395–404. [Google Scholar] [CrossRef] [Scilit]
- NW 1615 L. St, Washington S 800, Inquiries D 20036 U 419 4300|M 857 8562|F 419 4372|M. Demographics of Mobile Device Ownership and Adoption in the United States. Pew Research Center: Internet, Science & Tech. Available online: https://www.pewresearch.org/internet/fact-sheet/mobile/ (accessed on 17 February 2022).
- Bommakanti, K.K.; Smith, L.L.; Liu, L.; Do, D.; Cuevas-Mota, J.; Collins, K.; Munoz, F.; Rodwell, T.C.; Garfein, R.S. Requiring smartphone ownership for mHealth interventions: Who could be left out? BMC Public Health 2020, 20, 81. [Google Scholar] [CrossRef] [Scilit]
- Armaou, M.; Araviaki, E.; Musikanski, L. eHealth and mHealth Interventions for Ethnic Minority and Historically Underserved Populations in Developed Countries: An Umbrella Review. Int. J. Com. WB 2020, 3, 193–221. [Google Scholar] [CrossRef] [Scilit]
- Mendoza-Vasconez, A.S.; Linke, S.; Muñoz, M.; Pekmezi, D.; Ainsworth, C.; Cano, M.; Williams, V.; Marcus, B.H.; Larsen, B.A. Promoting Physical Activity Among Underserved Populations. Curr. Sports Med. Rep. 2016, 15, 290–297. [Google Scholar] [CrossRef] [Scilit]
- Lagisetty, P.A.; Priyadarshini, S.; Terrell, S.; Hamati, M.; Landgraf, J.; Chopra, V.; Heisler, M. Culturally Targeted Strategies for Diabetes Prevention in Minority Populations: A Systematic Review and Framework. Diabetes Educ. 2017, 43, 54–77. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Langlais, C.S.; Chen, Y.-H.; Van Blarigan, E.L.; Kenfield, S.A.; Kessler, E.R.; Daniel, K.; Ramsdill, J.W.; Beer, T.M.; Graff, R.E.; Paich, K.; et al. Quality of Life of Prostate Cancer Survivors Participating in a Remotely Delivered Web-Based Behavioral Intervention Pilot Randomized Trial. Integr. Cancer Ther. 2022, 21, 15347354211063500. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chan, H.; Van Loon, K.; Kenfield, S.A.; Chan, J.M.; Mitchell, E.; Zhang, L.; Paciorek, A.; Joseph, G.; Laffan, A.; Atreya, C.; et al. Quality of life of colorectal cancer survivors participating in a pilot randomized controlled trial of physical activity trackers and daily text messages. Support Care Cancer 2022, 30, 4557–4564. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Collins, L.M.; Strayhorn, J.C.; Vanness, D.J. One view of the next decade of research on behavioral and biobehavioral approaches to cancer prevention and control: Intervention optimization. Transl. Behav. Med. 2021, 11, 1998–2008. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).