


Abstract
Background/objectives: The nutrition care process (NCP) is an evidence-based practice framework used in Medical Nutrition Therapy for the prevention, treatment, and management of non-communicable chronic health conditions. This review aimed to explore available artificial intelligence (AI)-integrated technologies across the NCP in dietetic primary care, their uses, and their impacts on the NCP and patient outcomes. Method: Six databases were searched: MEDLINE, Embase, PsycINFO, Scopus, IEEE, and ACM digital library. Eligible studies were published between January 2007 and August 2024 and included human adult studies, AI-integrated technologies in the dietetic primary care setting, and patient-related outcomes. Extracted details focused on participant characteristics, dietitian involvement, and the type of AI system and its application in the NCP. Results: Ninety-seven studies were included. Three different AI systems (image or audio recognition, chatbots, and recommendation systems) were found. These were implemented in web-based or smartphone applications, wearable sensor systems, smart utensils, and software. Most AI-integrated technologies could be incorporated into one or more NCP stages. Seventy-nine studies reported user- or patient-related outcomes, with mixed findings, but all highlighted efficiencies of using AI. Higher patient engagement was observed with Chatbots. Seventeen studies raised concerns encompassing ethics and patient safety. Conclusions: AI systems show promise as a clinical support tool across most stages of the NCP. Whilst they have varying degrees of accuracy, AI demonstrates potential in improving efficiency, supporting personalised nutrition, and enhancing chronic disease management outcomes. Integrating AI education into dietetic training and professional development will be essential to ensure safe and effective use in practice.
1. Introduction
Non-communicable diseases (NCDs) currently account for approximately 74% of global deaths [1]. Poor diet and metabolic factors substantially elevate the risk of NCDs, including cardiovascular disease, colorectal cancer, and obesity-related conditions [1]. Modern food systems contribute to poorer diets characterised by energy-dense and nutrient-poor ultra-processed foods (typically containing added sugars, salt and/or saturated fats, food additives, and potential contaminants from packaging material) [2,3]. Registered Dietitians or Accredited Practising Dietitians are the only qualified healthcare professionals recognised to provide Medical Nutrition Therapy (MNT) to prevent, treat, or manage NCDs. MNT applies evidence-based practice (EBP) by following the nutrition care process (NCP) framework [4,5]. This is a standardised clinical framework that entails: 1. Nutrition Assessment (and reassessment) (including anthropometric, biochemical, clinical data collection, and interpretation), 2. Nutrition Diagnosis, 3. Nutrition Intervention, and 4. Monitoring and Evaluation (Figure 1) [4]. The NCP model is adaptable to patient progress, enabling dietitians to revisit prior stages as new clinical information emerges to support timely prevention or management of chronic conditions, particularly in primary healthcare [4,6]. Effectiveness of MNT in primary care is contingent on the dietitians’ ability to deliver tailored nutritional guidance and the patient’s active engagement in implementing and adhering to clinical recommendations.
Figure 1.
The nutrition care process model (adapted from the Academy of Nutrition and Dietetics) [4].
Primary care is the first point of contact with healthcare services for individuals within the community for the prevention, treatment, and management of health conditions. Common primary care providers include family medicine or general practitioners, nurses, allied health professionals, and pharmacies [7]. Primary care dietitians navigate an ongoing challenge to balancing workflow efficiency with clinical effectiveness to meet patient needs and expectations [8]. The rising prevalence of chronic health conditions strains the efficiency and reach of the traditional NCP provided by dietitians, thus underscoring the importance of new technological innovations in dietetics. The evolving landscape of artificial intelligence (AI) has become an area of growing interest in nutrition [9]. AI relies on machine learning algorithms to build systems capable of analysing large datasets to detect patterns or relationships to inform predictions and outputs [9,10]. Through cycles of trial and error, AI systems can mimic human cognitive processes, including stimulus recognition, problem solving, and decision-making [9]. Leveraging machine learning and deep learning capabilities of AI could transform the ways in which dietitians engage with each stage of the NCP, from synthesising nutrition assessment data, tailoring interventions, and predicting patient nutrition-related outcomes [9,11].
Use of digital technologies and devices as a tool to assist in the NCP is not new to healthcare. Technologies such as wearable devices, sensors, interactive platforms, and mobile-based or mobile health (mHealth) applications (apps), alongside web-based tools, have become more commonplace and effective in supporting dietitians in clinical practice [11,12,13]. To date, the most notable contributions of AI embedded technology include assisting with detailed data collection in NCD management (e.g., dietary patterns, nutrient breakdowns, health monitoring), as well as screening tools (e.g., refeeding syndrome risk) [9,11,12,14]. These innovations bring notable efficiencies, such as accurate nutritional diagnosis with more streamlined patient data; greater time allocations to delivering nutritional interventions; and the encouragement of active patient involvement to facilitate patient-driven care [14,15]. There will be projected growth in clinical efficiencies as AI models continue to evolve.
While AI is a promising tool to supplement dietetic clinical practice, concerns surrounding ethical frameworks and privacy are controversial topics that need to be addressed [9,15]. These include biases of ingrained AI algorithms stemming from low-quality training datasets representative of certain genders, ethnicities, or socioeconomic groups. In turn, inappropriate recommendations or advice can be generated for underrepresented populations, which can ultimately be detrimental to patient health and safety [9]. Concerns over data privacy will continually need to be addressed through regulations and security measures built into AI-integrated technologies to ensure sensitive patient data remain protected [9].
To our knowledge, the prior literature has generally offered a broad picture of prospective AI-integrated technologies in nutrition. This review provides a refined focus on primary care—the fundamental setting for managing and treating NCDs through clinicians engaging with patients to guide behavioural changes. By synthesising the latest evidence, this scoping review aims to provide a comprehensive overview of how AI-integrated technologies can be integrated into dietetic practice to assist in NCP delivery and its impact on patient outcomes.
2. Materials and Methods
This review was registered with the Open Science Framework (https://osf.io/2dwyh, accessed on 5 August 2025). The scoping review process was conducted in accordance with the Joanna Briggs Institute Manual (Chapter 10) Scoping Reviews outline [16]. The review process and reporting were aligned with Preferred Reporting Items for Systematic and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR) to ensure consistency and adherence to best practice [17].
2.1. Search Strategy
A preliminary pilot search of MEDLINE and IEEE was undertaken to identify articles relevant to the topic. Keywords contained in the titles, abstracts, and medical subject headings (MeSH) of articles were used to generate a search strategy which was adapted across six electronic databases: MEDLINE, Embase, PsycINFO, Scopus, IEEE, and ACM digital library. These databases were searched for peer-reviewed, original literature published from 1 January 2007 to 20 August 2024, a period during which research on the use of AI was rapidly evolving. Keywords and subject headings (including MeSH) were guided by the Population, Concept, and Context (PCC) Framework (Table 1). Key search terms included artificial intelligence, machine learning, deep learning, image recognition, generative AI, chatbots, medication nutrition therapy, nutrition care process (NCP), nutritionist/dietitian, private practice, and related synonyms. The final searches for each database are included in the Supplementary Materials (Tables S1–S5).
Table 1.
Inclusion and exclusion criteria incorporating the Population Concept Context framework. This table was applied throughout all stages of screening.
2.2. Source of Evidence Selection
All citations were exported into EndNote 21 citation management software (Clarivate Analytics, Philadelphia, PA, USA), and duplicate records were removed. Citations were then imported into Covidence 2024 software (Veritas Health Innovation, Melbourne, Australia) for screening.
Titles and abstracts were dual screened separately by two independent reviewers (K.N. and S.M.) to minimise bias. The same two reviewers (K.N. and S.M.) conducted a full-text review to identify articles eligible for inclusion in the review. The same review criteria (Table 1) were consistently applied across all stages of screening. For any articles that were excluded, a reason was documented and reported in a PRISMA-ScR flow diagram (Figure 2). Discrepancies at each screening stage were discussed between the two reviewers (K.N. and S.M.), and an additional reviewer (J.C./V.C./M.A.F.) was consulted to reach a consensus.
Figure 2.
PRISMA flow diagram for scoping review study selection.
2.3. Data Extraction
Data from relevant studies were extracted by two reviewers (K.N. and S.M.) to ensure accuracy and completeness. An Excel spreadsheet was utilised as the main data extraction and collation tool. Extraction of data was guided by areas of interest that would address the research aim as outlined in Table 2.
Table 2.
Details of interest that were extracted from included studies during the data extraction process.
2.4. Data Analysis and Presentation
Main findings addressing the scoping review’s objectives were collated and presented in tabular form and diagrams, with an accompanying narrative synthesis in Section 3.
3. Results
3.1. Findings from Search Strategy
The search retrieved 5863 records (Figure 2). After the removal of duplicates, 5539 studies underwent title–abstract screening, where a further 4948 studies were excluded. Full-text screening was conducted for 591 studies, in which only 97 studies were eligible.
3.2. Characteristics of Included Studies
From the 97 studies, 34 were descriptive studies, 7 were mixed methods studies, ad 56 were classified as aalytical studies (experimental, observational, or randomised controlled trials (RCTs)). In total, 11 were RCTs, and 6 were pilot studies. First authors had academic backgrounds in informatics or computer science (n = 23), various fields of engineering (n = 19), nutrition science and dietetics (n = 19), medicine (n = 18), biological and life sciences (n = 5), public health (n = 4), and economics (n = 1). The included papers were predominantly published from the following countries: United States of America (n = 23), Switzerland (n = 8), Taiwan (n = 6), Australia (n = 5), Germany (n = 5), Japan (n = 5) and Italy (n = 5). The remaining publications were from a variety of other countries (n = 40) (Supplementary Table S6)
Chronic medical conditions of focus included weight management (overweight or obesity) (n = 13), diabetes mellitus (type 1, type 2, and prediabetes) (n = 12), gastrointestinal (n = 7), renal (n = 3), cardiovascular (n = 1), metabolic Syndrome (n = 3), elderly nutrition (particularly malnutrition) (n = 3), two or more comorbid medical conditions (n = 2), and others (includes cancer, neurological, and food allergies) (n = 3). The remaining studies focused on healthy participants (n = 35) or did not specify a specific medical condition (n = 18) (Table 3). There were varying sample sizes (range: 1–123,787) and age ranges (range: 18–91 years old) amongst the participants in the included studies (Supplementary Table S6). Approximately two-thirds (68%) of the studies included dietitian, nutritionist, or nutrition expert involvement (n = 66), whilst the remainder did not (n = 31).
Table 3.
Summary of the characteristics and outcomes of included studies (n = 97).
The AI-integrated technologies explored could be classified under three categories: image or audio recognition (n = 53), chatbots (n = 22), and recommendation systems (n = 50). Three-quarters (75%) of the AI-integrated technologies only utilised one form of AI system (n = 73). Whilst with other technologies, they utilised a combination of either two (n = 20) or all three forms (n = 4). These AI-integrated technologies were available via the web (n = 28), smartphone apps (n = 34), a combination of both web and smart phone apps (n = 5), wearable sensor systems (n = 21), smart utensils (n = 2), and system or database development (n = 7) or were not clearly specified by study (n = 3). When further deconstructed by subdomains and specific techniques of AI, digital technologies employed machine learning (n = 31), deep learning (n = 17), natural language processing (inclusive of fuzzy logic, language learning models, and generative pre-trained transformers) (n = 19), and genetic/evolutionary algorithms (n = 3). In some cases, digital technologies utilised more than one subset of AI (n = 10). There are some studies that did not explicitly specify the subset of AI embedded in their technology (n = 17) (Table 4).
Table 4.
Summary of the primary outcome of AI-integrated technologies included in the scoping review. Table includes each technology, its potential application in the stages of NCP, and types of AI.
Sixty-two studies assessed the performance of AI-integrated technologies using evaluation metrics. More notable assessment metrics included accuracy (n = 27), precision (n = 8), recall (n = 7), F1 scores (the harmonic means between precision and recall) (n = 6), and user experience (n = 6) (Table 4).
3.3. AI Involvement in the Stages of the Nutrition Care Process (NCP)
The results relating to the application of AI-integrated technologies in dietetic primary care can be further grouped in accordance with the four main elements of the NCP cycle: assessment, diagnosis, intervention, and monitoring and evaluation [4,5]. Across the 97 studies, the functions of AI-integrated technologies could be incorporated into at least one (n = 31), two (n = 41), three (n = 15), or all four (n = 10) stages of the NCP (Figure 3). Table 4 summarises the different AI-integrated technologies and their application in the NCP model’s stages.
Figure 3.
Distribution of included studies (n = 97) based on AI-integrated technology’s potential contribution to the stage(s) of the nutrition care process (NCP). The NCP is a standardised cyclical framework that entails the following: 1. nutrition assessment (and reassessment) (including anthropometric, biochemical, clinical data collection, and interpretation); 2. nutrition diagnosis; 3. nutrition intervention; 4. monitoring and evaluation [4]. Legend in the diagram outlines the clusters of different NCP stages that AI-integrated technologies can support. Bold lines indicate involvement at that NCP stage. Dotted lines indicate that a certain NCP stage is not involved within the cluster.
3.3.1. Nutrition Assessment
Eight studies focused on the use of smartphone apps and wearable sensor technologies (e.g., glasses, in-ear microphones) to capture images or audio files and detect or identify participant food intake to aid automated diet histories [20,30,35,70,74,86,87,105]. Wearable sensors employed classifier algorithms to label instances and types of food consumed by participants. The common inputs for these algorithms included food images, audio files (e.g., chewing sounds), or electromyography (EMG: measure of electrical activity from nerve stimulation of muscles). For instance, a study by Papapanagiotou and colleagues (2021) explored the use of commercially available Samsung Galaxy earbuds to record audio to input into machine learning and deep learning algorithms, determine bite weight estimation, and record food intake occasions for participants [87]. A notable study by Papathanail and colleagues (2022) explored a deep learning convoluted neural network system which could take inputs from apps collecting diet history and calculate an adherence score with respect to the Mediterranean diet’s guidelines [90]. Similarly, AI-integrated technologies developed based on data mapping and machine learning models have been able to yield patient dietary intake profiles that are comparable to validated standards, such as ASA24 reports [34,79].
3.3.2. Nutrition Diagnosis
One study focused on technology that could specifically support dietitians in reaching nutrition diagnoses in the NCP [32]. This study proposed and evaluated a web-based nutrition expert diagnosis system which provided recommendations to assist clinical dietitians in reaching a more informed diagnosis. The nutrition diagnosis expert system was programmed with a specific set of fifty different nutritional diagnosis rules. This system relied on a dietitian’s input of dietary assessment data to specifically produce a nutrition diagnosis report addressing protein energy malnutrition. The AI-integrated technology was more efficient and achieved 100% accuracy, outperforming a human dietitian who served as the standard of comparison.
Another two studies [98,102] also proposed technologies that had the potential to assist with the diagnosis, intervention, and monitoring and evaluation stages. Recommendation systems and image recognition AI algorithms formed the basis of both innovations, using personalised dietary data analysis and patient diagnosis to develop meal recommendations to meet daily macronutrient needs [102] or support obesity management [98].
3.3.3. Nutrition Intervention
Among the studies, four studies solely focused on assisting the provision of nutrition interventions employed chatbots [19,83,91,92], eight used recommender systems [26,31,53,57,62,76,88,113], and three employed a combination of both types of AI systems [28,49,60]. In terms of dietetic interventions, the benefits of AI technology encompass providing more personalised and precise nutrition interventions [18,24,26,27,44,56,57,60,88,92,93,94,102,107,113] that are more tailored to specific chronic disease populations’ needs [18,24,44,57,60,88,92,93,107], assisting with brainstorming a greater variety of actionable recommendations to suit patient needs in order to support increased adherence [26,56,57,60,62,75,88,92,93,94,102,113] and utilising data-driven insights to predict patient outcomes for more tailored interventions [18,40,54]. AI-integrated technologies also have the capacity to empower patients to take an active role in chronic disease management through increasing engagement and self-awareness and building relevant nutritional knowledge and skills to support self-efficacy [28,38,43,44,45,46,52,60,61,64,66,75,91,93,94,95,96,98,99,101]. The chatbots employed in these studies were generally easily accessible to the public via the internet (e.g., ChatGPT versions 3.0, 3.5, and 4.0, Bard AI, and Bing Chat). In other cases, innovations that assisted with interventions had embedded recommender systems within a digital web platform or smartphone app interface for users to interact with. These systems generally provide recommendations to patients for menu or recipe ideas, with considerations of evidence-based guidelines for their chronic disease management and personal taste and cuisine preferences. For instance, a 2024 study combined both patient profile data (e.g., anthropometric values, past medical history) to formulate nutrient requirements to guide ChatGPT’s output of culturally tailored and accurate meal plans for chronic disease patients [88].
The integration of food recognition coupled with recommender systems also unlocks the potential for AI-integrated technologies to assist with both nutrition intervention alongside monitoring and evaluation. For instance, studies that focused on mobile apps generally had food recognition and recommender systems to underpin app functionalities to target specific clinical conditions (e.g., liver disease, irritable bowel syndrome (IBS) and low fermentable oligosaccharides, disaccharides, monosaccharides, and polyols (FODMAP)) [52,64,93]. In turn, this would increase patient dietary awareness and reinforce nutrition education for the intervention phase. Similarly, smart utensils were a new AI-integrated technological innovation explored by Nakaoka and colleagues (2021). Sensor-based chopsticks could be used to assist in providing patients with real-time feedback on the healthiness category of food consumed (i.e., whether food was healthy or not) and the rate of food consumption, which, in turn, actively reinforces the application of real-time nutrition education [81].
Anthropometric parameters were examined across twenty studies [18,23,25,26,38,40,45,46,50,63,64,69,75,82,85,94,98,99,108,109]. A number of these studies reported weight loss outcomes for metabolic health conditions such as obesity [18,45,75,82], type 2 diabetes mellitus [18,45,63,69,99,108], and Non-alcoholic fatty liver disease (NAFLD) [64]. Of these weight loss studies, three also reported a concurrent reduction in waist circumference in participants [45,75,108]. De Marchi and colleagues (2022) observed successful weight stabilisation, with the prevention of further weight loss in amyotrophic lateral sclerosis patients who engaged with an eHealth Chatbot platform compared to the control group that experienced a 3 kg weight loss over 6 months [38]. For significant weight management-focused studies, AI-integrated technology provided users with real-time interactions via chatbots [38,75] and food intake tracking [23,45,50,63,64,69,82] and recommended advice or meal ideas [63,69,82]. Five studies explored how AI systems could assist with data-driven insights to predict an individual’s weight trajectory and provide accompanying meal recommendations [18,94,98]. Health professionals gauged weight management program engagement and efficacy [40] and nutrition support for malnutrition in aging populations [109].
Biochemical and microbiological outcomes changes in participants’ biomarkers or as data integrated within AI-integrated technologies were reported across fifteen studies [24,26,44,45,56,57,60,63,64,69,82,85,99,107,108]. A study conducted by Kiriakedis and colleagues (2024) observed that ChatGPT (Version 4.0) exhibited poor performance in detecting and advising on abnormal urinalysis calcium and citrate levels, as it was unable to address 30% of the abnormalities presented. However, it exhibited strong performance for interpreting urinalysis biomarkers within normal levels [60]. Six studies highlighted overall improvements in glycaemic control [44,45,63,69,99,108]. Of these, four studies specified reductions in HbA1c levels using AI-based smartphone apps [63,69,99,108]. Kwon and colleagues (2024) observed significant improvements with respect to liver function test biomarkers (AST, ALT, and ɣ-GT) in non-alcoholic fatty liver disease patients as they developed health-related self-management skills over 6 months with the assistance of a nutrition advisor integrated in the SMART-liver app [64]. A key study unveiled that engagement with a generative pretrained transformer for dietary guidance significantly reduced the proportion of haemodialysis patients with hyperkaliemia from 39.8% to 25% [56]. Three studies exploring precision nutrition highlighted alterations in patient gut microbiome populations [24,57,107]. Two studies reported that greater favourable changes to microbiota occurred with increased adherence to the personalised diet, as opposed to the conventional Mediterranean [24] and low-FODMAP diets [107]. Similarly, Karakan and colleagues (2022) asserted that a personalised diet tailored for the gut microbiome of each IBS case led to increases in Faecalibacterium genus, Bacteroides, putatively probiotic genus, and Propionibacterium populations [57].
Clinical symptom-related outcomes were explored in fourteen studies [26,27,28,33,45,54,57,64,75,85,93,94,99,107]. The studies centred around patients with IBS and diarrhoea-predominant IBS (IBS-D) (n = 2) [54,57] and all IBS subtypes [93,107]. Of these, one study reported improved symptom management for participants receiving the AI-assisted personalised diet for all IBS subtypes compared to the FODMAP diet, which was only effective in the management of symptoms for IBC-C and IBS-D subtypes [107]. Across these studies, it was observed that 81% of participants with IBS/IBD had symptom improvements at week 5 [54], while another study reported a change in the categorisation of IBS symptoms from severe to moderate over 6 weeks [57], both of which utilised AI recommender systems. Buchan and colleagues (2024) unveiled significant improvements in quality of life and symptom management for 82% and 88% of cancer patients, respectively, after interaction with INA, a virtual assistant platform [27]. A study on type 2 diabetic patients using Twin Precision Nutrition observed significant improvements in metabolic health markers (e.g., Hba1C, weight, HOMA-IR), with most patients ceasing the use of medications (including insulin, metformin, DPP-4 inhibitors, and liraglutide) [99]. However, one study noted reduced confidence with diabetes management after using web-based diabetes nutrition care platforms that meal preparation and planning [28].
Sixty studies reported diet quality-, nutrient-, and food intake-related observations [20,21,22,27,28,29,30,33,35,37,38,41,43,44,45,46,49,50,52,53,55,56,57,58,59,60,61,62,64,66,68,70,71,74,75,76,77,78,79,80,82,83,84,85,86,88,89,90,91,92,93,94,95,96,97,98,99,100,101,102,103,104,105,106,110,113]. For more patient-focused studies, nine studies explored alterations to dietary intake and behaviours. Of these, two studies helped with improving participant confidence in core food preparation skills, such as meal planning [28] and meal preparation and cooking [43]. Many study participants were receptive to AI-integrated technologies, which was observed through an uncovered increase in tendency to select healthier choices [45,46,96,101] and more regulated portion sizes [46,101] and improvements in food intake patterns (e.g., reduced snacking) [33,96]. More specifically, two studies on participants interacting with Paola (an AI virtual chatbot on the Slack communication platform) observed improvements in the selection of foods, leading to greater dietary compliance with prescribed diets, such as the Mediterranean diet [37,75].
Alternatively, some studies focused on evaluating the quality-of-food-related outputs from AI systems [29,49,56,61,71,76,79,80,83,89,90,92,94,104,106,110]. For studies that focused on AI system recommendations, some utilised healthcare professionals or experts’ responses as a standard of comparison, including clinical diabetes educators [29], dietitian clinical judgements and recommendations [61,71,76,104], Mediterranean diet adherence scores by dietitians [90,110], and nutrition experts [94]. Alternatively, studies also compared AI outputs to recognised dietary standards for the keto diet [104], allergy diets [83], Mayo Clinic Renal Handbook [56,92], National Dietary Reference Intakes (USDA DRI) [49], and various international clinical guidelines for management of NCDs [80,91]. For some studies exploring AI’s capabilities with respect to macronutrient estimation, the AI system outputs were compared to validated tools such as the ASA-24 [79], dietitians carrying out 24 h dietary recalls [89], and nutritionists [106]. Studies on wearable devices commented on performances in detecting important stimuli indicative of eating occasions, such as sound patterns [20,21,22,30,68,86], movements associated with fluid intake [22,58,59], and food intake gestures [30,41,58,59,97].
3.3.4. Monitoring and Evaluation
Eight studies solely focused on patient monitoring and evaluation, which mostly incorporated food recognition technologies, some recommender systems, and the reduced involvement of chatbots. Of these AI-integrated technologies, they were predominantly embedded in smart device-based apps and platforms (n = 6) [36,37,50,65,69,84], and the remaining AI-integrated technologies explored were wearable devices (n = 2) [21,51].
Fifteen studies monitored patient adherence. Of these studies, greater levels of engagement and retention and lower dropout rates were observed in studies which implemented Chatbots in their platform (n = 4) [27,38,63,75], AI biochemical data-driven personalised nutrition (n = 2) [54,107], meal recommendation apps (n = 2) [26,43], and apps with a health behaviour coach feature (n = 4) [46,63,64,75]. Lower engagement and adherence were seen with respect to dietary support apps or web-based platforms (n = 4) [26,28,55,102] and food recognition systems (n = 1) [89]. Changes in perception or interest in health outcomes over time (n = 2) [26,55], use in older or chronically ill populations (n = 1) [28], compliance with instructions (n = 1) [89], and the necessity for regular reminders and support follow-through during intervention delivery (n = 1) [102] were some of the factors contributing to reduced engagement with AI-integrated technologies.
3.3.5. All Stages of the NCP
Ten studies explored AI-integrated technological innovations with the potential to support all four stages of the NCP (Table 4) [38,54,66,79,80,94,99,101,104,109]. Most of these digital technologies utilised recommender systems [54,66,80,94,99,101,104,109]. For instance, a Personal Intelligent Nutrition (PIN) system designed to automate patient health assessments and meal plans received 88.7% agreement from nutrition experts for weight and body fat percentage recommendations and was commended by experts due to its ability to identify nutrients of concern and the meal plans that address them [94].
Two studies explored recommender systems paired with image or audio recognition in the form of nutritional intake platforms [66], which could aggregate user-reported data and external sources to provide seamless accessibility to nutritional care, and technology-assisted dietary assessment mobile apps that improved the user’s diet quality and eating behaviours [101]. De Marchi and colleagues’ (2022) e-Health chatbot app encouraged patient adherence with respect to registering dietary intake, and they supported dietitians in prescribing a personalised caloric dietary plan [38].This resulted in weight stabilisation in amyotrophic lateral sclerosis patients, with only 3 kg weight loss over 6 months compared to the baseline in the control group [38]. Only Sun and colleagues (2023) utilised all three forms of AI systems (food recognition, chatbots, and recommender systems) to propose an AI nutritionist program based on ChatGPT and a generative pre-trained transformer to provide easy and affordable access to dietetic care and all stages of the NCP [104].
3.4. Efficiencies of AI-Integrated Technology Use
Ninety-three studies [18,19,20,21,22,23,24,25,26,27,29,30,31,32,34,35,36,37,38,39,40,41,42,43,44,45,46,47,49,50,51,52,53,54,55,56,57,58,59,60,61,62,63,64,65,66,67,69,70,71,72,73,74,75,76,77,78,79,80,81,82,84,85,86,88,89,90,91,92,93,94,95,96,97,98,99,100,101,102,103,104,105,106,107,108,109,110,111,112,113,114,115] commented on potential efficiencies in utilising AI-integrated technologies compared to traditional methods of dietetic care. Another notable benefit for both dietitians and patients was the reduced burden in collecting and analysing food intake records for dietary assessment (n = 25) [18,20,22,33,34,53,55,59,66,70,72,73,74,75,78,79,81,82,90,97,100,106,110,111,114] and monitoring and evaluation (n = 29) [18,22,35,38,39,41,47,48,51,55,56,57,58,63,64,65,66,67,70,78,81,84,85,86,90,101,108,111,114].
More specifically, for dietitians, AI-integrated technologies could potentially improve the flow of consultations by supporting clinicians in summing up all relevant data to support decision-making processes for nutrition assessment and delivering tailored nutrition interventions (n = 20) [23,32,53,54,55,56,59,60,69,76,78,79,80,88,94,102,109,110,111,114]. Through the patient perspective, benefits of implementing AI-integrated technologies included easier access, use, and interaction across smart devices (e.g., smartphones, iPads or tablets) (n = 21) [19,25,27,31,43,46,48,55,60,61,71,80,82,91,93,95,98,101,103,104] and relevant nutrition-related information or feedback on demand (n = 14) [25,52,55,62,82,88,90,91,92,93,95,96,98,111]. AI-integrated technologies were also cited to be cost-effective (n = 13) [19,55,56,59,61,77,80,82,85,91,102,104,108] for accessing nutrition care and managing chronic health conditions to minimise long-term healthcare costs. In more regional or rural areas or locations, there are limited healthcare resources (e.g., healthcare professionals), and AI-integrated technologies assisted in extending dietetic care to individuals who needed it (n = 10) [27,31,45,60,71,76,91,95,102,104].
3.5. Limitations and Safety Concerns with AI-Integrated Technology Use
Among the six studies (Table 5) [19,27,72,80,83,104] that mentioned patient safety, two studies touched on the provision of warnings and disclaimers with ChatGPT responses [19,80], and four studies encouraged further verification via seeking professional advice [80,91,92,104].
Table 5.
Ethical considerations (privacy and data) (n = 11) and safety (nutrition practice) (n = 6) themes explored in studies in the scoping review.
Studies also emphasised that, depending on how the user phrased their prompts (n = 4) [19,49,80,104], the time and date of prompt entry (n = 2) [60,80], and the complexity of the cases (e.g., presence of multiple chronic conditions or food allergies) (n = 3) [27,61,91], chatbot systems could potentially provide inconsistent or misleading responses. Therefore, it was highlighted that individuals without prior nutrition knowledge were vulnerable to nutritional misinformation (n = 7) [19,25,60,61,71,80,91]. For instance, a study utilised ChatGPT to generate allergen-specific menu and food recommendations, which incorrectly integrated almond milk into a nut-free allergy diet [83]. Furthermore, concerns were highlighted regarding how virtual assistants may be limited in being able to safely offer additional guidance for more complex patient cases with multiple chronic medical conditions, food intolerances, or allergies [27], and discrepancies were observed between chatbot food item recommendations and best practice guidelines for specific diets [104]. Professional oversight by dietitians was integrated across some studies to mitigate these safety concerns [27,83,104]. Lin and colleagues (2020) advised that employing recognised nutritional guidelines (i.e., European Food Safety Authority (EFSA)) into AI systems would further assist and guide a more accurate and robust learning recommendation system [72]. Some authors emphasised that refining these AI-integrated technologies should be a collaborative task between dietitians, nutrition experts, or other healthcare professionals to ensure appropriateness for clinical use (n = 5) [70,71,80,83,90].
Across the AI-integrated technologies explored, some were still in the preliminary stages of prototype development and were only trained either using smaller datasets or a specific set of clinical nutrition guidelines (n = 22) [24,28,33,34,35,37,49,52,54,56,65,69,71,77,88,92,95,100,109,111,113]. In turn, some studies suggested that their AI systems undergo further refinement with larger datasets to address low varieties in certain food groups or mixed-food selections and recommendations (n = 8) [34,46,55,56,62,89,94,98], to include different cuisines (n = 4) [26,56,104,106], to cover more nutrition-specific diets (n = 2) [18,62], and to account for dietary supplements (n = 1) [79]. Studies also noted factors such as user self-desirability bias (n = 1) [29] and user confidence (n = 1) [110], alongside underreporting (n = 1) [79] or omissions (n = 1) [27] by AI systems requiring self-reported outcomes.
More specifically, for wearable sensor systems, studies highlighted limiting factors, including poor performance in deciphering food attributes and intake (n = 6) [20,21,47,68,70,86], fluid intake detection (n = 5) [36,39,47,59,86], and prototype design impacting the user and their comfort (n = 5) [22,51,68,73,86], or they were more sensitive to interference by surrounding factors (n = 5) [72,78,87,97,112]. Additional barriers to user engagement included the presence of technical jargon (n = 3) [25,46,60] and poor design of interactive features (e.g., generic message outputs) (n = 3) [26,50,92] in relation to the user interface. Other prominent barriers cited include access to the appropriate technology (e.g., specific smart device, internet access) (n = 3) [45,48,64], poor technological literacy (n = 2) [70,75], and elderly populations (n = 2) [33,85].
3.6. Ethical Considerations
Eleven studies commented on ethical considerations relating to patient privacy in AI-integrated technologies (Table 5) [19,25,36,50,56,85,92,97,99,105,108,111]. Two studies explored alternative privacy-preserving designs for wearable devices. These included the use of depth cameras [36] and the repositioning of camera angles [97] to minimise the collection of unnecessary surrounding images. Further studies on wearable sensor systems highlighted the potential of sharing unwanted images or other sensitive information, such as GPS location, with third parties (e.g., annotator, human observer) to assist in training AI systems for image recognition functions [31,50]. One study had sharing-based authorisation, whereby patients could grant healthcare professionals access to their wearable device’s data [111]. Additionally, one study raised concerns with respect to the anonymity and privacy of the user when utilising a health chatbot to provide information-based support and answers [25].
Three studies explained that participants’ data would be transmitted and stored in a security system to protect them [85,99,108]. These included incorporating layers of security to control users’ and administrators’ access, restricting the collection of personal identification information [85] and providing a secure transmission pathway [99,108]. Two studies raised the importance of the development of standardised ethical guidelines on patient autonomy and informed consent [56,92]. In contrast, an additional three studies advocated for the importance of warnings and disclaimers for potential AI errors that could compromise patient safety [19,27,80]; hence, they advocated for the value of healthcare professional oversight to mitigate this risk [19,27,72,80,83,104,116].
4. Discussion
Embedding AI-integrated technologies into the NCP presents a promising opportunity to address rising healthcare demands driven by the growing prevalence of chronic health conditions [8,15]. The salient findings include the following: (i) three main AI systems (image or audio recognition, chatbots, and recommendation systems) being employed; (ii) AI technologies could be integrated into one or more stages of the NCP to aid dietitians with workflow and patient outcomes; and (iii) AI-integrated technologies potentially enhance patient outcomes for chronic disease management through strengthening patient engagement and targeting drivers of behavioural change. Nevertheless, AI-integrated technologies are not a replacement for dietetic expertise, given their susceptibility to errors which can impact patient safety and ethical concerns.
4.1. Nutrition Assessment
The AI-integrated technologies in our review have largely targeted the nutrition assessment component of the NCP. Numerous studies have reported that AI-integrated technologies are a solution for alleviating the burden for both patients and dietitians in collecting data for dietary assessments, as this constitutes a significant proportion of initial consultations [71]. AI food and audio recognition systems are time-efficient and seamless for recording food intake and calculating the corresponding nutrient composition [117]. Prerecorded dietary intake can be more readily evaluated during dietary assessments and diagnosis stages, thus allowing more time to be allocated to targeted nutrition education and behavioural counselling. Such types of AI systems have mostly been embedded in wearable sensor systems (e.g., necklaces, wristbands, glasses) and utensils or incorporated in smartphone or web-based apps. These systems have demonstrated the ability to accurately detect food intake (e.g., solid foods) [22,41,59]. Additionally, AI addresses the shortfalls of conventional dietary assessment methods (e.g., using 24 h recalls for diet history), which are susceptible to biases relating to memory, measurement, and under-reporting due to social desirability [118]. However, the accuracy of wearable or sensor-based AI-integrated technologies remains inconclusive, as many examples included in this review were in the preliminary stages of development and may have only been tested in laboratories (e.g., [20,22,30,34,48]). Further development of AI-driven image and audio recognition systems requires fine-tuning to address detection inaccuracies, such as fluid intake and identifying variable food attributes (irregular shape, lower weight, and soft foods), to better capture and reflect an individual’s daily dietary variability.
AI food recognition algorithms have expanded beyond use in nutrition research and become increasingly integrated into commercially available apps (e.g., MyFitnessPal) [70]. AI algorithms can leverage food composition and nutrient databases to enhance the accuracy and efficiency of individual dietary intake analyses [8,12]. For instance, the Keenoa app demonstrated strong comparative validity relative to conventional methods for recording dietary intake and nutrient estimation [55,78]. Participants preferred app-based food intake recording over more traditional methods (three-day food diary and ASA-24) due to reduced self-burden with increased ease and convenience for food logging [55,78]. However, dietitian oversight is still required to appraise the app’s nutritional assessment, override errors, and manually enter more complex food items (e.g., dietary supplements) [55,78]. While these AI-integrated technologies may exhibit greater accuracy, adaptability, and efficiency, their degree of performance and their reliability have limitations. They are inherently dependent on the quality and comprehensiveness of their underlying databases. Therefore, it is crucial to dedicate additional efforts to optimising nutrition databases, expanding them to include cultural foods, cooking styles, and branded pre-packaged items [70]. AI integration automates dietary data collection and analysis, streamlining the assessment process. Consequently, dietitians can focus on building rapport and trust with patients to better implement motivational interviewing and behavioural counselling techniques [8].
4.2. Nutrition Diagnosis
Nutritional diagnoses are essential for guiding appropriate, targeted interventions. Although this review uncovered only one suitable AI diagnostic system for primary care, AI-integrated technologies have been widely explored for acute inpatient settings. For instance, a trial on machine learning models using electronic medical record (EMR) admission data (e.g., biochemical tests, anthropometry, disease severity scores, nutrition assessments) has been designed to predict malnutrition diagnoses in accordance with the Global Leadership Initiative on Malnutrition (GLIM) diagnostic framework [119]. Similar studies may serve as examples for where AI algorithms can be adapted for primary care clinical data. However, the development of a truly representative diagnostic tool is a challenge as nutrition-related diseases arise from a complex interplay of health and lifestyle factors. In primary care, patients present with a variety of more unique and complex chronic conditions (e.g., multiple complex comorbidities, allergies, and intolerances). Based on this review, there is limited evidence for the accuracy of AI-integrated technologies in formulating nutritional diagnoses for various clinical conditions [32]. Instead, this review provides insight into how AI systems can support dietitians by presenting data aligned with the most relevant clinical diagnostic tools, frameworks, and guidelines. This approach streamlines the process of identifying a list of potential diagnoses. Dietitians can select the most appropriate diagnosis while considering the patient’s social, socioeconomic, and environmental context. Through informed clinical decision-making, dietitians retain professional autonomy within an increasingly AI-integrated healthcare environment. In the diagnostic domain, AI-integrated tools are supportive adjuncts, offering data-driven insights that align with clinical practice guidelines.
4.3. Nutrition Intervention
AI has created new opportunities to advance precision nutrition by leveraging patient-specific data, including genetic, metabolic, and physiological parameters and gut microbiota profiles [9,15,88,120]. Personalised diet programs like ZOE have gained interest for delivering tailored nutrition advice based on multiple biochemical inputs (blood lipids, blood glucose profile, and gut microbiome) collected using convenient at-home test kits [121]. In the 18-week ZOE Measuring Efficacy Through Outcomes of Diet (METHOD) RCT, ZOE was more effective in improving the markers of cardiometabolic health (body weight, waist circumference, HbA1c, and triglycerides) compared to generalised dietary advice (United States Dietary Guidelines for Americans 2020–2025) [122]. Precision nutrition intervention participants received personalised food scores in conjunction with generalised nutrition and lifestyle education remotely via the ZOE app. Tailored recommendations from ZOE’s algorithm (2022) considered various factors, including food characteristics, biochemical data from at-home collection kits, cardiovascular disease risk, and past medical history [122]. Similarly, this was echoed in this review, where precision nutrition yielded significant clinical improvements for patients over more conventional dietary pattern prescriptions (e.g., Mediterranean diet, low-FODMAP) [57,99,120]. However, like ZOE, AI-driven precision nutrition remains largely confined to clinical trials and higher socioeconomic groups, limiting its accessibility and equitable reach among the general population [120]. Rapid advancements in precision nutrition have warranted its spotlight in the NIH 2020–2030 Strategic Plan for Nutrition Research. This plan further advocates for the use of AI and machine learning to more effectively integrate genetic, microbiome, behavioural, and environmental data to generate individualised dietary recommendations [123]. The Australian Academy of Science’s decadal plan also recognises precision nutrition as one of the four pillars of nutrition science, elucidating its potential to tailor dietary guidance in accordance with an individual’s biology, culture, and context [124]. With continual refinement, AI systems will become better equipped to deliver more precise and effective recommendations for the wide variety and complex, multifactorial nature of NCDs treated in primary care [15,88].
This review also examines AI-integrated apps that offer greater accessibility to the population than precision nutrition. Our findings highlight that these technologies support patients in improving patient dietary intake and health outcomes, with predominantly positive implications for weight loss [23,63,69,82], gain [18] and stabilisation (e.g., in patients with amyotrophic lateral sclerosis) [38]. Further software refinement and up-scaling trials will enable some of these innovations to extend their reach and ease of access to dietetic care in regional, rural, and underserved areas with constraints in healthcare professional availability [91,104]. mHealth apps commonly integrating one aspect or a combination of image recognition, chatbots, and recommender systems better enabled users to receive real-time feedback. For instance, the eTRIP weight management program integrated an adjunct mHealth app with personalised reminders, chatbots providing real-time feedback, and food logging with image recognition [33]. Additionally, the integration of an appealing and user-friendly interface enhances engagement and adherence to dietary recommendations [33]. This builds upon Salas-Grove and colleagues’ (2023) review, reinforcing that mHealth nutrition apps with self-monitoring tools, personalised feedback, goal setting, educational content, reminders, prompts, and social support features (e.g., connection with peers or healthcare providers) pave the way for sustained behaviour change and, in turn, improve health outcomes in chronic disease populations [125]. AI-integrated technologies could be a cost-effective method of reducing the long-term economic burdens of chronic conditions, enabling individuals to seek necessary healthcare guidance for effective self-management rather than a reliance on later-stage medical treatments [126].
Generative AI chatbots such as ChatGPT are a publicly accessible tool that could be valuable as a complementary aid for patients beyond or outside clinical consultations; however, they are not a replacement for dietitians or clinical advice. Caution should be exercised as chatbots have been observed to mislead users on their credibility and accuracy, as factually incorrect outputs have been generated in a confident manner (known as “hallucinations”) [80]. When supporting intervention delivery, chatbot use requires oversight by a dietitian to assess the quality of outputs. AI chatbots may unlock the potential to design personalised educational materials or appropriate food recommendations to better tailor diets to patient preferences (e.g., taste, cuisine preference) [8]. When used in conjunction with clinician counselling, adjunct chatbot interaction enhances nutrition interventions through targeted nutrition education and recommendations (e.g., diet-compliant meal plans). This approach not only reinforces dietary prescriptions beyond consultations but may improve patient receptiveness to behavioural changes and adherence. A similar case was explored with respect to physiotherapy, elucidating the current limitations of publicly accessible AI. The study examined ChatGPT’s ability to offer advice in accordance with clinical guidelines, but it lacked nuanced clinical reasoning for more complex patient presentations and, thus, should only be used as a supplementary tool [127]. Hence, further research efforts may explore designing patient-facing chatbots based on evidence-based guidelines, and recommendations would ensure greater degrees of patient safety and efficacy rather than relying on publicly accessible AI chatbots. Mistakes in healthcare lead to detrimental harm, and clinical experience and expertise are crucial safeguards for addressing patient-specific concerns, monitoring clinical progress, and ensuring patient safety by clarifying misinformation [70,80,91,92,116].
4.4. Monitoring and Evaluation
A key component mediating the effectiveness of the prevention and management of chronic health conditions is patient engagement and adherence to prescribed interventions [128]. Our findings indicate that a prominent overlap occurs in the AI-integrated technologies designed to target the NCP stages of nutrition intervention, monitoring and evaluation, and dietary assessment (recording food intake). Various AI-integrated technologies, ranging from virtual health chatbots to smartphone apps designed for diet management, are tools that have been shown to facilitate higher levels of patient engagement [120,129]. Greater levels of patient satisfaction, engagement, and adherence were observed with AI-integrated technologies featuring chatbots [27]. This review offers a glimpse into the features that facilitate positive user experiences, which include app interfaces that are well-tailored to the needs, interests, and lifestyle of the user. For instance, the HealthAware advice desktop platform was designed to target office workers. Through active engagement with HealthAware, a majority (>50%) of users developed greater awareness of their current dietary patterns (e.g., snacking or selecting unhealthy food choices) and were more receptive to healthier dietary recommendations suggested by HealthAware. AI’s ability to reflect real-time analytics, optimising goal setting and tracking, facilitates patient engagement [75]. Additional AI-driven features, including reminders and nudges, sustain motivation and prevent behavioural relapse, targeting the user’s adherence and sense of accountability [33,81,102,125].
From a dietitian’s perspective, the emergence of generalist clinical AI systems capable of addressing three or more domains of the NCP will have broad implications. These include AI-integrated technologies designed with image or audio recognition and recommender systems that streamline the collection of dietary intake data and summarise it in relation to patient progress and goals. For instance, the clinical decision support system (CDSS) minimised the time required for clinicians to analyse patient self-reported dietary intake data via an app and offered clinicians dietary recommendations based on patient input data [29]. In turn, AI can bridge critical gaps limiting patient-centred care and would be very beneficial during follow-up consultations where time is more limited.
4.5. Additional Practical Implications
4.5.1. Healthcare Professionals
Balancing clinician benefits, professional identity, and risk of deskilling are essential as AI becomes increasingly integrated in healthcare. Aspiring and current dietitians must develop a thorough awareness of the strengths, limitations, and risks of AI-integrated technology use. This is important as healthcare registration and accreditation bodies emphasise that healthcare professionals are responsible and accountable for the use of AI-integrated technologies in clinical practice and patient care. Key future learning initiatives include embedding course content regarding practical, safe, and ethical use of AI-integrated technologies in clinical practice into university health and medicine curricula (e.g., healthcare ethics, exposure in clinical rotations/placement or simulation clinics), professional development courses, or onboarding modules in healthcare workplaces [130]. In the technology acceptance model, training is a critical factor mediating perceived usefulness and increasing receptiveness through shifting mindsets and attitudes towards AI integration in healthcare [131,132]. Training initiatives to enhance dietitians’ self-efficacy in using mHealth tools may adopt a two-phase model comprising an initial education workshop followed by a supervised integration phase [130,133]. Rather than deskilling, AI’s growing presence presents an opportunity to upskill dietitians as their expertise and identity evolve, while still preserving professional autonomy.
Furthermore, EBP provides a clinical decision-making framework that integrates the best available research evidence and clinical experience and patients’ contextual values [134]. Limited time outside patient care and financial constraints are significant barriers to dietitians’ ability to remain up to date with the latest clinical research for EBP [135,136]. AI-integrated clinical technologies are a practical solution, enabling dietitians to efficiently strengthen their clinical dietetic knowledge. AI chatbots can improve accessibility, facilitate the synthesis of large research databases to enhance confidence in knowledge translation, and apply emerging evidence in practice. Clinician-facing AI-integrated technologies such as the 2023 Mayo Clinic Platform Accelerate Program, OpenEvidence, have been evaluated using primary care cases (hypertension, hyperlipidaemia, type 2 diabetes mellitus, depression, and obesity) to deliver pertinent outputs that support a physician’s clinical judgement in medical decision-making rather than replacing it [137]. OpenEvidence’s design promotes transparency in its outputs by incorporating reputable journal citations (e.g., New England Journal of Medicine, Journal of American Medical Association). This fosters clinician trust and reinforces a collaborative clinician–AI working environment in which clinicians retain autonomy to act on or reassess AI-generated recommendations. For dietitians, adapting a similar system could enhance point-of-care support, especially given the breadth of clinical presentations in primary care.
4.5.2. Reimbursement Models
The emergence of AI-integrated technologies presents both opportunities and challenges for achieving equitable access to healthcare, particularly dietetic services. Compared to larger healthcare precincts (e.g., metropolitan), there is an underutilisation of AI-integrated clinical technologies in smaller, regional, or rural health services. This imbalance is driven by differing capacities and resource availability (e.g., workforce shortages, financial constraints, and infrastructure). Instead, AI-integrated technologies should be regarded as a cost-effective solution to address these shortcomings [45,91]. Generalist AI-integrated technologies currently being trialled in medicine are capable of engaging multi-step integrated analysis and thus present a promising opportunity to ensure that healthcare services can be equally accessible regardless of location [138]. Similarly, this review highlights potential generalist AI-integrated technologies that can support all stages of the NCP.
However, outside of certain medical specialties (such as radiology and pathology), the deployment of AI-integrated technologies has generally been slower [139,140]. A primary barrier for its slower adoption in healthcare stems from uncertainty with respect to evidence supporting the accuracy, value, and utility of AI-integrated technologies. Implementation requires considerable costs for primary care organisations: for example, purchasing software licenses, adequate professional training, digital infrastructure adjustments, and continual maintenance and monitoring. Current reimbursement models in primary care (a fee-for-service payment of discrete definable medical services and episodes of patient care) are not reflective of the capabilities of AI and the evolving roles of healthcare professionals [138]. Additionally, given the ongoing development of AI-integrated technologies, it would be limiting for dietitians to restrict their use to a single tool or a select few. A proposed revised government-funded healthcare model (e.g., Medicare, National Healthcare System) articulates three guiding principles: 1. bundling AI services with complementary services; 2. setting a separate reference fee or transitional add-on payment for AI-enabled services; 3. regular re-evaluation of Medicare fees to reflect cost fluctuations and the associated value of clinical work [141]. Future planning for widespread AI integration should draw on the successes and challenges experienced during the global transition from paper-based patient records to EMR systems.
4.5.3. Patient Safety, Efficacy, and Evaluation Tools
A lack of consensus exists on how AI-integrated technologies could be evaluated for patient safety and efficacy and the identification of accountable stakeholders. There are multiple means of evaluation, yet no standardised benchmark, tool, or reporting guidelines exist. For instance, the current evaluation metrics used include consumer (patient or clinician) usability ratings and business operation key performance indicators (e.g., time efficiency, patient turnover rates). Whilst these metrics have largely highlighted the positive impacts of AI-integrated technologies, some reveal safety concerns, including advice that may be harmful or that conflicts with nutritional guidelines. This underscores the need for a thorough investigation into current evaluation approaches. Governing regulatory bodies such as the Food and Drug Administration (US) and Therapeutic Goods Administration (Australia) oversee the clearances of medical devices fit for consumer use. Although certain types of AI-integrated technologies fall within existing regulatory frameworks, others may fall outside their scope and be overlooked, posing a risk to patient safety. Future efforts should focus on developing standardised criteria or frameworks for AI-integrated healthcare technologies. These frameworks should be able to provide the following: 1. clear definitions of the intervention and context of use; 2. specify and explain the mechanisms underlying the AI system; 3. capture relevant health outcomes and infer the effect or causality of the AI-integrated technology [139].
RCTs are the gold standard for inferring causality. However, RCTs may not be feasible due to limitations (e.g., increased time requirements, funding). Only a small fraction of AI-integrated technologies were evaluated using this type of study design (Supplementary Table S6). Instead, for primary care settings, cohort observational data (e.g., based on wearable sensor data) and quasi-experimental designs may be more practical with some additional considerations (e.g., training participants to accurately collect data, additional statistical expertise for data cleaning) [139].
For quality evaluation, ongoing efforts are underway to adapt and extend pre-existing tools, statements, and guidelines, including APPRAISE-AI, CONSORT-AI, TRIPOD + AI, and the MARS tool [139,142,143,144,145]. All these efforts can contribute to consumer safety certifications and mandated labelling processes which currently apply to products such as medications, foods, and medical devices. Product specifications should include a clear overview of designs, intended use, and performance (reliability, safety, compliance, and monitoring), enabling end-users to be better informed.
4.5.4. AI-Integrated Technology Development
In this review, some studies on AI-integrated technologies were in stages of prototype refinement and preliminary testing, accounting for differences in relative performance. A lack of a standardised framework for protocol development, training, and testing with respect to AI-integrated technologies targeted for the healthcare industry may lead to poorly designed systems [129]. Various studies indicated differences in foundational AI algorithms and models, the quality of training datasets (sample sizes and representativeness), and mechanisms. Absence of design transparency poses difficulty for peer-reviewed assessments of AI output quality and reproducibility. In cases where dataset quality is overlooked, AI algorithmic biases can continue to perpetuate pre-existing healthcare disparities (e.g., variation in health condition diagnoses across different sociodemographic groups), especially when deployed on a system-wide scale [146]. Clinician involvement in the development of AI-integrated technologies is often limited, yet it is critically important [126,129,147]. Only two-thirds (68%) of the studies in this review reported dietitian, nutritionist, or nutrition expert involvement. Dietitians bring a nuanced understanding of clinical nutrition, clinical workflows, and real-world constraints [120,129,147]. Clinicians contribute significantly to patient-facing care. Thus, they are well positioned to advocate for patient feedback, which can be under-represented in digital healthcare development. Moving forward, all stakeholders play pivotal roles in successful integration and quality improvement cycles as AI-integrated technologies continue to evolve.
Early responses by the World Health Organisation included the launch of the “Ethics and Governance of AI for Health” (2021) manual. Internationally, countries have adjusted and reviewed patient privacy legislations, such as HIPAA (United States of America); GDPR (Europe); DCB0129, DTAC, DSPT, Cyber Essentials, and the Data Protection Act (United Kingdom); PIPEDA (Canada); Australian Privacy Principles (Australia); and Information Privacy Principles (New Zealand) [126]. In this review, there were particular concerns regarding patient privacy, confidentiality of patient data that are collected and analysed by apps, web-based tools, and wearable sensor systems or used to train AI systems, and secure data storage (Table 5). To mediate this, the correct authorisation of access should be practiced, and patient data should be encrypted and anonymised [111,129]. However, there are other concerns as anonymised patient data can be nullified due to the ability of new algorithms to reidentify data [129]. Therefore, it is crucial that regulatory frameworks and legislation are continually revised in accordance with the rapidly evolving AI-integrated technology landscape.
4.6. Strengths and Limitations
Our review offers a novel focus on primary care settings. Primary care plays a critical role in relieving the burden on emergency medicine and inpatient care, especially with the growing prevalence of chronic NCDs as the current population ages. This differs from more recent reviews, which generally provided more generalised insight into AI-integrated technologies for nutrition research or acute care clinical practice (e.g., [9,14,129,148,149,150]).
The scoping review design was selected to capture the breadth and diversity of the literature on how AI-integrated technologies contribute to the NCP rather than assessing AI’s effectiveness. Following established frameworks [17,151], two independent reviewers conducted a comprehensive search across six health and technology databases. Through this approach, key healthcare ethical considerations were highlighted for future action through a collaborative effort by research, policy, and technology development stakeholders.
However, as this is a scoping review, the included studies have not undergone a quality and bias assessment. Precautions should be exercised when interpreting individual study results due to the potential risk of bias within study methodologies and designs. Future research endeavours should consider a systematic review to assess study quality or a meta-analysis to enable statistical inferences to be derived for addressing the effectiveness of AI-integrated technologies with respect to patient health and behavioural outcomes. This can strengthen our understanding of the feasibility of implementing AI-integrated technologies in the NCP.
Furthermore, some AI-integrated technologies found in this review were only in preliminary stages of development, and thus, individual findings may not be conclusive and generalisable. Across numerous studies, small sample sizes and the recruitment of specific populations were emphasised as limiting factors that impact the generalisability and conclusiveness of findings. Therefore, any transition and implementation of AI-integrated technologies demand thorough reassessment and reporting to ensure compatibility, safety, and appropriateness for clinical use. Additionally, our targeted focus on primary care excluded AI-integrated technologies that could streamline dietitians’ administrative workflow beyond patient consultations (e.g., billing, letter transcripts, EMR documentation). A significant proportion of a clinician’s patient care activities beyond consultations is often overlooked, thus warranting additional exploration of how AI-integrated technologies can also transform this space [152].
This review also does not explore AI-integrated technologies for inpatient clinical dietetics. Given the differences between acute inpatient care vs primary care, such as length of patient interactions (e.g., short vs. long term) and breadth of clinical presentations (e.g., malnutrition screening, refeeding syndrome risk, parenteral or enteral nutrition support vs. chronic disease management), this topic would be more suited as a separate avenue for future exploration. AI integration into inpatient clinical dietetics is also a concurrently evolving research field that addresses common dietetic presentations unique to critical care and hospital admissions. Notable AI-integrated technologies have addressed muscle mass evaluation, malnutrition screening, prediction of enteral nutrition needs and feed tolerance, and the risk of refeeding syndrome in intensive care unit patients by integrating diverse data streams from the EMR [9,153]. Nevertheless, concerns around interoperability and patient privacy continue to be echoed. Last of all, this scoping review was constrained to English-only articles, which may have impacted the breadth of the literature survey and the data analysed. It is recommended that future research incorporate studies published in other languages to uncover other potential AI-integrated technologies that may emerge.
5. Conclusions
AI-integrated technologies enhance how primary care dietitians engage with all stages of the NCP. AI-integration in wearables, sensors, apps, web-based tools, and software are revolutionising dietary tracking and monitoring and personalised nutrition interventions. For clinicians, AI-integrated technologies support summative data analysis and clinical decision-making particularly in nutrition assessment and diagnosis stages, allowing more time to engage patients in nutrition education and behavioural counselling. This shift facilitates improvements in adherence to recommended dietary patterns and clinical markers that promote better long-term health outcomes. Challenges that arise include implementing professional development initiatives to upskill dietitians and protect professional autonomy; revising current reimbursement models; ensuring ongoing clinician oversight for patient safety; and establishing standardised technology development frameworks and validation tools alongside new regulatory and legal standards. Addressing these concerns requires a multidisciplinary approach (including AI technology developers, clinicians, researchers, and patients). This actively promotes a collaborative and expanding clinician–AI ecosystem built on trust, transparency, and acceptance. AI-integrated technologies offer transformative potential in advancing primary care dietetics and optimising chronic disease management.
Supplementary Materials
The following supporting information can be downloaded at https://www.mdpi.com/article/10.3390/nu17223515/s1, Table S1: Title and abstract search for IEEE Database; Table S2: Search terms for the ACM Library; Table S3: Search terms for Scopus; Table S4: Medline (Ovid) Search; Table S5: Embase (Ovid) Search; Table S6: Summary of the characteristics of the included studies (n = 97). Studies organised based on the study’s chronic medical condition of focus.
Author Contributions
Conceptualization, J.C., V.C. and M.A.-F.; methodology, K.N., S.M., A.Y., H.Y.C., X.L., M.A.-F. and V.C.; formal analysis, K.N. and S.M.; investigation, K.N. and S.M.; data curation, K.N. and S.M.; writing—original draft preparation, K.N. and S.M.; writing—review and editing, K.N., S.M., J.C., V.C. and M.A.-F.; visualization, K.N. and S.M.; supervision, J.C., V.C. and M.A.-F.; project administration, J.C. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in the study are included in the article/Supplementary Materials; further inquiries can be directed to the corresponding author.
Acknowledgments
This project was carried out by the University of Sydney as a partial fulfilment of the requirements of the Master of Nutrition and Dietetics by the first two authors, Kaitlyn Ngo and Simone Mekhail.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- World Health Organisation. Noncommunicable Diseases. Available online: https://www.who.int/news-room/fact-sheets/detail/noncommunicable-diseases (accessed on 14 September 2025).
- Lane, M.M.; Gamage, E.; Du, S.; Ashtree, D.N.; McGuinness, A.J.; Gauci, S.; Baker, P.; Lawrence, M.; Rebholz, C.M.; Srour, B.; et al. Ultra-processed food exposure and adverse health outcomes: Umbrella review of epidemiological meta-analyses. BMJ 2024, 384, e077310. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, X.; Yon, D.K.; Nguyen, T.T.; Tanisawa, K.; Son, K.; Zhang, L.; Shu, J.; Peng, W.; Yang, Y.; Branca, F.; et al. Dietary and other lifestyle factors and their influence on non-communicable diseases in the Western Pacific region. Lancet Reg. Health West. Pac. 2024, 43, 100842. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Swan, W.I.; Vivanti, A.; Hakel-Smith, N.A.; Hotson, B.; Orrevall, Y.; Trostler, N.; Beck Howarter, K.; Papoutsakis, C. Nutrition Care Process and Model Update: Toward Realizing People-Centered Care and Outcomes Management. J. Acad. Nutr. Diet. 2017, 117, 2003–2014. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mitchell, L.J.; Ball, L.E.; Ross, L.J.; Barnes, K.A.; Williams, L.T. Effectiveness of Dietetic Consultations in Primary Health Care: A Systematic Review of Randomized Controlled Trials. J. Acad. Nutr. Diet. 2017, 117, 1941–1962. [Google Scholar] [CrossRef] [Scilit]
- Reynolds, R.; Dennis, S.; Hasan, I.; Slewa, J.; Chen, W.; Tian, D.; Bobba, S.; Zwar, N. A systematic review of chronic disease management interventions in primary care. BMC Fam. Pract. 2018, 19, 11. [Google Scholar] [CrossRef] [Scilit]
- Australian Government Department of Health, Disability and Ageing. About Primary Care. Available online: https://www.health.gov.au/topics/primary-care/about (accessed on 14 September 2025).
- O’Connor, R.; Slater, K.; Ball, L.; Jones, A.; Mitchell, L.; Rollo, M.E.; Williams, L.T. The tension between efficiency and effectiveness: A study of dietetic practice in primary care. J. Hum. Nutr. Diet. 2019, 32, 259–266. [Google Scholar] [CrossRef] [Scilit]
- Bond, A.; McCay, K.; Lal, S. Artificial intelligence & clinical nutrition: What the future might have in store. Clin. Nutr. ESPEN 2023, 57, 542–549. [Google Scholar] [CrossRef] [Scilit]
- Korteling, J.E.; van de Boer-Visschedijk, G.C.; Blankendaal, R.A.M.; Boonekamp, R.C.; Eikelboom, A.R. Human- versus Artificial Intelligence. Front. Artif. Intell. 2021, 4, 622364. [Google Scholar] [CrossRef] [Scilit]
- Liang, Y.; Xiao, R.; Huang, F.; Lin, Q.; Guo, J.; Zeng, W.; Dong, J. AI nutritionist: Intelligent software as the next generation pioneer of precision nutrition. Comput. Biol. Med. 2024, 178, 108711. [Google Scholar] [CrossRef] [Scilit]
- Chen, J.; Gemming, L.; Hanning, R.; Allman-Farinelli, M. Smartphone apps and the nutrition care process: Current perspectives and future considerations. Patient Educ. Couns. 2018, 101, 750–757. [Google Scholar] [CrossRef] [Scilit]
- Salinari, A.; Machì, M.; Armas Diaz, Y.; Cianciosi, D.; Qi, Z.; Yang, B.; Ferreiro Cotorruelo, M.S.; Villar, S.G.; Dzul Lopez, L.A.; Battino, M.; et al. The Application of Digital Technologies and Artificial Intelligence in Healthcare: An Overview on Nutrition Assessment. Diseases 2023, 11, 97. [Google Scholar] [CrossRef] [Scilit]
- Kelly, J.T.; Collins, P.F.; McCamley, J.; Ball, L.; Roberts, S.; Campbell, K.L. Digital disruption of dietetics: Are we ready? J. Hum. Nutr. Diet. 2021, 34, 134–146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singer, P.; Robinson, E.; Raphaeli, O. The future of artificial intelligence in clinical nutrition. Curr. Opin. Clin. Nutr. Metab. Care 2024, 27, 200–206. [Google Scholar] [CrossRef] [Scilit]
- Peters, M.D.; Godfrey, C.; McInerney, P.; Munn, Z.; Tricco, A.C.; Khalil, H. Scoping Reviews (2020). In JBI Manual for Evidence Synthesis; JBI: Adeleide, Australia, 2024. [Google Scholar] [CrossRef] [Scilit]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abeltino, A.; Bianchetti, G.; Serantoni, C.; Ardito, C.F.; Malta, D.; De Spirito, M.; Maulucci, G. Personalized Metabolic Avatar: A Data Driven Model of Metabolism for Weight Variation Forecasting and Diet Plan Evaluation. Nutrients 2022, 14, 3520. [Google Scholar] [CrossRef] [Scilit]
- Agne, I.; Gedrich, K. Personalized dietary recommendations for obese individuals—A comparison of ChatGPT and the Food4Me algorithm. Clin. Nutr. Open Sci. 2024, 56, 192–201. [Google Scholar] [CrossRef] [Scilit]
- Amft, O.; Kusserow, M.; Troster, G. Automatic Identification of Temporal Sequences in Chewing Sounds. In Proceedings of the 2007 IEEE International Conference on Bioinformatics and Biomedicine (BIBM 2007), Silicon Valley, CA, USA, 2–4 November 2007; pp. 194–201. [Google Scholar]
- Amft, O.; Kusserow, M.; Troster, G. Bite Weight Prediction from Acoustic Recognition of Chewing. IEEE Trans. Biomed. Eng. 2009, 56, 1663–1672. [Google Scholar] [CrossRef] [Scilit]
- Amft, O.; Troster, G. Recognition of dietary activity events using on-body sensors. Artif. Intell. Med. 2008, 42, 121–136. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ben Neriah, D.; Geliebter, A. Weight Loss Following Use of a Smartphone Food Photo Feature: Retrospective Cohort Study. JMIR mHealth uHealth 2019, 7, e11917. [Google Scholar] [CrossRef] [Scilit]
- Ben-Yacov, O.; Godneva, A.; Rein, M.; Shilo, S.; Lotan-Pompan, M.; Weinberger, A.; Segal, E. Gut microbiome modulates the effects of a personalised postprandial-targeting (PPT) diet on cardiometabolic markers: A diet intervention in pre-diabetes. Gut 2023, 72, 1486–1496. [Google Scholar] [CrossRef] [Scilit]
- Beyeler, M.; Légeret, C.; Kiwitz, F.; van der Horst, K. Usability and Overall Perception of a Health Bot for Nutrition-Related Questions for Patients Receiving Bariatric Care: Mixed Methods Study. JMIR Hum. Factors 2023, 10, e47913. [Google Scholar] [CrossRef] [Scilit]
- Bohn, T.; Ferrini, K.; Stahl, C. LIFANA—Toward developing a meal recommender system as a dietary support app for the elderly. Int. J. Vitam. Nutr. Res. 2024, 94, 221–238. [Google Scholar] [CrossRef] [Scilit]
- Buchan, M.L.; Goel, K.; Schneider, C.K.; Steullet, V.; Bratton, S.; Basch, E. National Implementation of an Artificial Intelligence-Based Virtual Dietitian for Patients with Cancer. JCO Clin. Cancer Inform. 2024, 8, e2400085. [Google Scholar] [CrossRef] [Scilit]
- Bul, K.; Holliday, N.; Bhuiyan, M.R.A.; Clark, C.C.T.; Allen, J.; Wark, P.A. Usability and Preliminary Efficacy of an Artificial Intelligence-Driven Platform Supporting Dietary Management in Diabetes: Mixed Methods Study. JMIR Hum. Factors 2023, 10, e43959. [Google Scholar] [CrossRef] [Scilit]
- Burgermaster, M.; Son, J.H.; Davidson, P.G.; Smaldone, A.M.; Kuperman, G.; Feller, D.J.; Burt, K.G.; Levine, M.E.; Albers, D.J.; Weng, C.; et al. A new approach to integrating patient-generated data with expert knowledge for personalized goal setting: A pilot study. Int. J. Med. Inform. 2020, 139, 104158. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, J.; Wang, X.; Li, J.; Chernyshov, G.; Huang, Y.; Kunze, K.; Huang, J.; Starner, T.; Zhang, Q. First Bite/Chew: Distinguish different types of food by first biting/chewing and the corresponding hand movement. In Proceedings of the CHI EA ‘23: Extended Abstracts of the 2023 CHI Conference on Human Factors in Computing Systems, Hamburg, Germany, 19 April 2023; p. 138. [Google Scholar]
- Chen, R.C.; Ting, Y.H.; Chen, J.K.; Lo, Y.W. The nutrients of chronic diet recommended based on domain ontology and decision tree. In Proceedings of the 2015 Conference on Technologies and Applications of Artificial Intelligence (TAAI), Tainan, Taiwan, 20–22 November 2015; pp. 289–295. [Google Scholar]
- Chen, Y.; Hsu, C.Y.; Liu, L.; Yang, S. Constructing a nutrition diagnosis expert system. Expert Syst. Appl. 2012, 39, 2132–2156. [Google Scholar] [CrossRef] [Scilit]
- Chew, H.S.J.; Chew, N.W.S.; Loong, S.S.E.; Lim, S.L.; Tam, W.S.W.; Chin, Y.H.; Chao, A.M.; Dimitriadis, G.K.; Gao, Y.; So, J.B.Y.; et al. Effectiveness of an artificial intelligence-assisted app for improving eating behaviors: Mixed methods evaluation. J. Med. Internet Res. 2024, 26, e46036. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chin, E.L.; Simmons, G.; Bouzid, Y.Y.; Kan, A.; Burnett, D.J.; Tagkopoulos, I.; Lemay, D.G. Nutrient Estimation from 24-Hour Food Recalls Using Machine Learning and Database Mapping: A Case Study with Lactose. Nutrients 2019, 11, 3045. [Google Scholar] [CrossRef] [Scilit]
- Chotwanvirat, P.; Prachansuwan, A.; Sridonpai, P.; Kriengsinyos, W. Automated Artificial Intelligence-Based Thai Food Dietary Assessment System: Development and Validation. Curr. Dev. Nutr. 2024, 8, 102154. [Google Scholar] [CrossRef] [Scilit]
- Cohen, R.; Fernie, G.; Fekr, A.R. Contactless Drink Intake Monitoring Using Depth Data. IEEE Access 2023, 11, 12218–12225. [Google Scholar] [CrossRef] [Scilit]
- Davis, C.R.; Murphy, K.J.; Curtis, R.G.; Maher, C.A. A Process Evaluation Examining the Performance, Adherence, and Acceptability of a Physical Activity and Diet Artificial Intelligence Virtual Health Assistant. Int. J. Environ. Res. Public Health 2020, 17, 9137. [Google Scholar] [CrossRef] [Scilit]
- De Marchi, F.; Serioli, M.; Collo, A.; Belotti, E.G.; Alloatti, F.; Biroli, G.; Bolioli, A.; Cantello, R.; Riso, S.; Mazzini, L. A Telehealth Intervention for Nutritional Counseling in Amyotrophic Lateral Sclerosis Patients. J. Clin. Med. 2022, 11, 4286. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Farooq, M.; Sazonov, E. A Novel Wearable Device for Food Intake and Physical Activity Recognition. Sensors 2016, 16, 1067. [Google Scholar] [CrossRef] [Scilit]
- Fernandes, G.J.; Choi, A.; Schauer, J.M.; Pfammatter, A.F.; Spring, B.J.; Darwiche, A.; Alshurafa, N.I. An Explainable Artificial Intelligence Software Tool for Weight Management Experts (PRIMO): Mixed Methods Study. J. Med. Internet Res. 2023, 25, e42047. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fontana, J.M.; Farooq, M.; Sazonov, E. Automatic ingestion monitor: A novel wearable device for monitoring of ingestive behavior. IEEE Trans. Bio-Med. Eng. 2014, 61, 1772–1779. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fontana, J.M.; Sazonov, E.S. A robust classification scheme for detection of food intake through non-invasive monitoring of chewing. In Proceedings of the Annual International Conference of the IEEE Engineering in Medicine and Biology Society, San Diego, CA, USA, 28 August–1 September 2012; pp. 4891–4894. [Google Scholar]
- Garcia, M.B. Plan-Cook-Eat: A Meal Planner App with Optimal Macronutrient Distribution of Calories Based on Personal Total Daily Energy Expenditure. In Proceedings of the 2019 IEEE 11th International Conference on Humanoid, Nanotechnology, Information Technology, Communication and Control, Environment, and Management (HNICEM), Laoag, Philippines, 29 November–1 December 2019; pp. 1–5. [Google Scholar]
- Gonzalez-Flo, E.; Kheirabadi, E.; Rodriguez-Caso, C.; Macia, J. Evolutionary algorithm for the optimization of meal intake and insulin administration in patients with type 2 diabetes. Front. Physiol. 2023, 14, 1149698. [Google Scholar] [CrossRef] [Scilit]
- Hansel, B.; Giral, P.; Gambotti, L.; Lafourcade, A.; Peres, G.; Filipecki, C.; Kadouch, D.; Hartemann, A.; Oppert, J.M.; Bruckert, E.; et al. A Fully Automated Web-Based Program Improves Lifestyle Habits and HbA1c in Patients with Type 2 Diabetes and Abdominal Obesity: Randomized Trial of Patient E-Coaching Nutritional Support (The ANODE Study). J. Med. Internet Res. 2017, 19, e360. [Google Scholar] [CrossRef] [Scilit]
- Hauptmann, H.; Leipold, N.; Madenach, M.; Wintergerst, M.; Lurz, M.; Groh, G.; Bohm, M.; Gedrich, K.; Krcmar, H. Effects and challenges of using a nutrition assistance system: Results of a long-term mixed-method study. User Model. User Adapt. Interact. 2022, 32, 923–975. [Google Scholar] [CrossRef] [Scilit]
- Heremans, E.R.M.; Chen, A.S.; Wang, X.; Cheng, J.; Xu, F.; Martinez, A.E.; Lazaridis, G.; Van Huffel, S.; Chen, J.D.Z. Artificial Neural Network-Based Automatic Detection of Food Intake for Neuromodulation in Treating Obesity and Diabetes. Obes. Surg. 2020, 30, 2547–2557. [Google Scholar] [CrossRef] [Scilit]
- Hezarjaribi, N.; Mazrouee, S.; Ghasemzadeh, H. Speech2Health: A Mobile Framework for Monitoring Dietary Composition from Spoken Data. IEEE J. Biomed. Health Inform. 2018, 22, 252–264. [Google Scholar] [CrossRef] [Scilit]
- Hieronimus, B.; Hammann, S.; Podszun, M.C. Can the AI tools ChatGPT and Bard generate energy, macro- and micro-nutrient sufficient meal plans for different dietary patterns? Nutr. Res. 2024, 128, 105–114. [Google Scholar] [CrossRef] [Scilit]
- Holmes, S.; Moorhead, A.; Bond, R.; Zheng, H.; Coates, V.; McTear, M. WeightMentor, bespoke chatbot for weight loss maintenance: Needs assessment & Development. In Proceedings of the 2019 IEEE International Conference on Bioinformatics and Biomedicine (BIBM), San Diego, CA, USA, 18–21 November 2019; pp. 2845–2851. [Google Scholar]
- Hossain, D.; Imtiaz, M.H.; Ghosh, T.; Bhaskar, V.; Sazonov, E. Real-Time Food Intake Monitoring Using Wearable Egocentric Camera. In Proceedings of the 2020 42nd Annual International Conference of the IEEE Engineering in Medicine & Biology Society (EMBC), Montréal, QC, Canada, 20–24 July 2020; pp. 4191–4195. [Google Scholar]
- Hsiao, M.; Yeh, Y.F.; Hsueh, P.Y.; Lee, S. Intelligent Nutrition Service for Personalized Dietary Guidelines and Lifestyle Intervention. In Proceedings of the 2011 International Joint Conference on Service Sciences, Taipei, Taiwan, 25–27 May 2011; pp. 11–16. [Google Scholar]
- Hsu, C.Y.; Huang, L.C.; Chen, T.M.; Chen, L.F.; Chao, J.C.J. A web-based decision support system for dietary analysis and recommendations. Telemed. e-Health 2011, 17, 68–75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jactel, S.N.; Olson, J.M.; Wolin, K.Y.; Brown, J.; Pathipati, M.P.; Jagiella, V.J.; Korzenik, J.R. Efficacy of a Digital Personalized Elimination Diet for the Self-Management of Irritable Bowel Syndrome and Comorbid Irritable Bowel Syndrome and Inflammatory Bowel Disease. Clin. Transl. Gastroenterol. 2023, 14, e00545. [Google Scholar] [CrossRef] [Scilit]
- Ji, Y.; Plourde, H.; Bouzo, V.; Kilgour, R.D.; Cohen, T.R. Validity and usability of a smartphone image-based dietary assessment app compared to 3-day food diaries in assessing dietary intake among Canadian adults: Randomized controlled trial. JMIR mHealth uHealth 2020, 8, e16953. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jin, H.; Lin, Q.; Lu, J.; Hu, C.; Lu, B.; Jiang, N.; Wu, S.; Li, X. Evaluating the Effectiveness of a Generative Pre-trained Transformers-Based Dietary Recommendation System in Managing Potassium Intake for Hemodialysis Patients. J. Ren. Nutr. 2024, 34, 539–545. [Google Scholar] [CrossRef] [Scilit]
- Karakan, T.; Gundogdu, A.; Alagozlu, H.; Ekmen, N.; Ozgul, S.; Tunali, V.; Hora, M.; Beyazgul, D.; Nalbantoglu, O.U. Artificial intelligence-based personalized diet: A pilot clinical study for irritable bowel syndrome. Gut Microbes 2022, 14, 2138672. [Google Scholar] [CrossRef] [Scilit]
- Karmakar, A.; Nishida, M.; Nishimura, M. Eating and Drinking Behavior Recognition Using Multimodal Fusion. In Proceedings of the 2023 IEEE 12th Global Conference on Consumer Electronics (GCCE), Nara, Japan, 10–13 October 2023; pp. 210–213. [Google Scholar]
- Khan, M.T.; Ghaffarzadegan, S.; Feng, Z.; Hasan, T. A Fabric-based Inexpensive Wearable Neckband for Accurate and Reliable Dietary Activity Monitoring. In Proceedings of the 2022 25th International Conference on Computer and Information Technology (ICCIT), Chittagong, Bangladesh, 17–19 December 2022; pp. 994–997. [Google Scholar]
- Kiriakedis, S.; Duty, B.; Chase, T.; Wusirika, R.; Metzler, I. Using ChatGPT-4 to Analyze 24-Hour Urine Results and Generate Custom Dietary Recommendations for Nephrolithiasis. J. Endourol. 2024, 38, 719–724. [Google Scholar] [CrossRef] [Scilit]
- Kirk, D.; Van Eijnatten, E.; Camps, G. Comparison of Answers between ChatGPT and Human Dieticians to Common Nutrition Questions. J. Nutr. Metab. 2023, 2023, 5548684. [Google Scholar] [CrossRef] [Scilit]
- Kobayashi, A.; Mori, S.; Hashimoto, A.; Katsuragi, T.; Kawamura, T. Functional Food Knowledge Graph-based Recipe Recommendation System Focused on Lifestyle-Related Diseases. In Proceedings of the 2024 IEEE 18th International Conference on Semantic Computing (ICSC), Laguna Hills, CA, USA, 5–7 February 2024; pp. 261–268. [Google Scholar] [CrossRef] [Scilit]
- Krishnakumar, A.; Verma, R.; Chawla, R.; Sosale, A.; Saboo, B.; Joshi, S.; Shaikh, M.; Shah, A.; Kolwankar, S.; Mattoo, V. Evaluating glycemic control in patients of South Asian origin with type 2 diabetes using a digital therapeutic platform: Analysis of real-world data. J. Med. Internet Res. 2021, 23, e17908. [Google Scholar] [CrossRef] [Scilit]
- Kwon, O.Y.; Lee, M.K.; Lee, H.W.; Kim, H.; Lee, J.S.; Jang, Y. Mobile App-Based Lifestyle Coaching Intervention for Patients with Nonalcoholic Fatty Liver Disease: Randomized Controlled Trial. J. Med. Internet Res. 2024, 26, e49839. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lázaro, J.P.; Fides, A.; Navarro, A.; Guillén, S. Ambient Assisted Nutritional Advisor for elderly people living at home. In Proceedings of the Annual International Conference of the IEEE Engineering in Medicine and Biology Society, Buenos Aires, Argentina, 31 August–4 September 2010; pp. 198–203. [Google Scholar]
- Lee, H.A.; Liu, C.Y.; Hsu, C.Y. Precision Nutrition Management in Continuous Care: Leveraging AI for User-Reported Dietary Data Analysis. Stud. Health Technol. Inform. 2024, 315, 256–261. [Google Scholar] [CrossRef] [Scilit]
- Lee, J.; Paudyal, P.; Banerjee, A.; Gupta, S.K.S. FIT-EVE&ADAM: Estimation of Velocity & Energy for Automated Diet Activity Monitoring. In Proceedings of the 16th IEEE International Conference on Machine Learning and Applications, Cancún, Mexico, 21 December 2017; pp. 1071–1074. [Google Scholar]
- Lee, K.S. Joint Audio-Ultrasound Food Recognition for Noisy Environments. IEEE J. Biomed. Health Inform. 2020, 24, 1477–1489. [Google Scholar] [CrossRef] [Scilit]
- Lee, Y.B.; Kim, G.; Jun, J.E.; Park, H.; Lee, W.J.; Hwang, Y.C.; Kim, J.H. An Integrated Digital Health Care Platform for Diabetes Management with AI-Based Dietary Management: 48-Week Results from a Randomized Controlled Trial. Diabetes Care 2023, 46, 959–966. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Yin, A.; Choi, H.Y.; Chan, V.; Allman-Farinelli, M.; Chen, J. Evaluating the Quality and Comparative Validity of Manual Food Logging and Artificial Intelligence-Enabled Food Image Recognition in Apps for Nutrition Care. Nutrients 2024, 16, 2573. [Google Scholar] [CrossRef] [Scilit]
- Liao, L.L.; Chang, L.C.; Lai, I.J. Assessing the Quality of ChatGPT’s Dietary Advice for College Students from Dietitians’ Perspectives. Nutrients 2024, 16, 1939. [Google Scholar] [CrossRef] [Scilit]
- Lin, Z.; Xie, Y.; Guo, X.; Ren, Y.; Chen, Y.; Wang, C. WiEat: Fine-grained Device-free Eating Monitoring Leveraging Wi-Fi Signals. In Proceedings of the 2020 29th International Conference on Computer Communications and Networks (ICCCN), Honolulu, HI, USA, 3–6 August 2020; pp. 1–9. [Google Scholar]
- Liu, M.; Zhou, B.; Rey, V.F.; Bian, S.; Lukowicz, P. iEat: Automatic wearable dietary monitoring with bio-impedance sensing. Sci. Rep. 2024, 14, 17873. [Google Scholar] [CrossRef] [Scilit]
- Lozano, C.P.; Canty, E.N.; Saha, S.; Broyles, S.T.; Beyl, R.A.; Apolzan, J.W.; Martin, C.K. Validity of an Artificial Intelligence-Based Application to Identify Foods and Estimate Energy Intake Among Adults: A Pilot Study. Curr. Dev. Nutr. 2023, 7, 102009. [Google Scholar] [CrossRef] [Scilit]
- Maher, C.A.; Davis, C.R.; Curtis, R.G.; Short, C.E.; Murphy, K.J. A Physical Activity and Diet Program Delivered by Artificially Intelligent Virtual Health Coach: Proof-of-Concept Study. JMIR mHealth uHealth 2020, 8, e17558. [Google Scholar] [CrossRef] [Scilit]
- Marashi-Hosseini, L.; Jafarirad, S.; Hadianfard, A.M. A fuzzy based dietary clinical decision support system for patients with multiple chronic conditions (MCCs). Sci. Rep. 2023, 13, 12166. [Google Scholar] [CrossRef] [Scilit]
- Martino, F.D.; Delmastro, F.; Dolciotti, C. Malnutrition Risk Assessment in Frail Older Adults using m-Health and Machine Learning. In Proceedings of the ICC 2021—IEEE International Conference on Communications, Online, 14–23 June 2021; pp. 1–6. [Google Scholar]
- Mertes, G.; Ding, L.; Chen, W.; Hallez, H.; Jia, J.; Vanrumste, B. Measuring and Localizing Individual Bites Using a Sensor Augmented Plate During Unrestricted Eating for the Aging Population. IEEE J. Biomed. Health Inform. 2020, 24, 1509–1518. [Google Scholar] [CrossRef] [Scilit]
- Moyen, A.; Rappaport, A.I.; Fleurent-Gregoire, C.; Tessier, A.J.; Brazeau, A.S.; Chevalier, S. Relative Validation of an Artificial Intelligence-Enhanced, Image-Assisted Mobile App for Dietary Assessment in Adults: Randomized Crossover Study. J. Med. Internet Res. 2022, 24, e40449. [Google Scholar] [CrossRef] [Scilit]
- Naja, F.; Taktouk, M.; Matbouli, D.; Khaleel, S.; Maher, A.; Uzun, B.; Alameddine, M.; Nasreddine, L. Artificial intelligence chatbots for the nutrition management of diabetes and the metabolic syndrome. Eur. J. Clin. Nutr. 2024, 78, 887–896. [Google Scholar] [CrossRef] [Scilit]
- Nakaoka, R.; Nakamura, Y.; Matsuda, Y.; Misaki, S.; Yasumoto, K. eat2pic: Food-tech Design as a Healthy Nudge with Smart Chopsticks and Canvas. In Proceedings of the 2021 IEEE International Conference on Pervasive Computing and Communications Workshops and other Affiliated Events (PerCom Workshops), Kassel, Germany, 22–26 March 2021; pp. 389–391. [Google Scholar]
- Nakata, Y.; Sasai, H.; Gosho, M.; Kobayashi, H.; Shi, Y.; Ohigashi, T.; Mizuno, S.; Murayama, C.; Kobayashi, S.; Sasaki, Y. A Smartphone Healthcare Application, CALO mama Plus, to Promote Weight Loss: A Randomized Controlled Trial. Nutrients 2022, 14, 4608. [Google Scholar] [CrossRef] [Scilit]
- Niszczota, P.; Rybicka, I. The credibility of dietary advice formulated by ChatGPT: Robo-diets for people with food allergies. Nutrition 2023, 112, 112076. [Google Scholar] [CrossRef] [Scilit]
- Ocay, A.B.; Fernandez, J.M.; Palaoag, T.D. NutriTrack: Android-based food recognition app for nutrition awareness. In Proceedings of the 2017 3rd IEEE International Conference on Computer and Communications (ICCC), Chengdu, China, 13–16 December 2017; pp. 2099–2104. [Google Scholar]
- Oh, S.W.; Kim, K.K.; Kim, S.S.; Park, S.K.; Park, S. Effect of an Integrative Mobile Health Intervention in Patients with Hypertension and Diabetes: Crossover Study. JMIR mHealth uHealth 2022, 10, e27192. [Google Scholar] [CrossRef] [Scilit]
- Papapanagiotou, V.; Diou, C.; Zhou, L.; van den Boer, J.; Mars, M.; Delopoulos, A. A Novel Chewing Detection System Based on PPG, Audio, and Accelerometry. IEEE J. Biomed. Health Inform. 2017, 21, 607–618. [Google Scholar] [CrossRef] [Scilit]
- Papapanagiotou, V.; Ganotakis, S.; Delopoulos, A. Bite-Weight Estimation Using Commercial Ear Buds. In Proceedings of the Annual International Conference of the IEEE Engineering in Medicine and Biology Society, Online, 1–5 November 2021; pp. 7182–7185. [Google Scholar]
- Papastratis, I.; Konstantinidis, D.; Daras, P.; Dimitropoulos, K. AI nutrition recommendation using a deep generative model and ChatGPT. Sci. Rep. 2024, 14, 14620. [Google Scholar] [CrossRef] [Scilit]
- Papathanail, I.; Abdur Rahman, L.; Brigato, L.; Bez, N.S.; Vasiloglou, M.F.; van der Horst, K.; Mougiakakou, S. The Nutritional Content of Meal Images in Free-Living Conditions-Automatic Assessment with goFOODTM. Nutrients 2023, 15, 3835. [Google Scholar] [CrossRef] [Scilit]
- Papathanail, I.; Vasiloglou, M.F.; Stathopoulou, T.; Ghosh, A.; Baumann, M.; Faeh, D.; Mougiakakou, S. A feasibility study to assess Mediterranean Diet adherence using an AI-powered system. Sci. Rep. 2022, 12, 17008. [Google Scholar] [CrossRef] [Scilit]
- Ponzo, V.; Goitre, I.; Favaro, E.; Merlo, F.D.; Mancino, M.V.; Riso, S.; Bo, S. Is ChatGPT an Effective Tool for Providing Dietary Advice? Nutrients 2024, 16, 469. [Google Scholar] [CrossRef] [Scilit]
- Qarajeh, A.; Tangpanithandee, S.; Thongprayoon, C.; Suppadungsuk, S.; Krisanapan, P.; Aiumtrakul, N.; Garcia Valencia, O.A.; Miao, J.; Qureshi, F.; Cheungpasitporn, W. AI-Powered Renal Diet Support: Performance of ChatGPT, Bard AI, and Bing Chat. Clin. Pract. 2023, 13, 1160–1172. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rafferty, A.J.; Hall, R.; Johnston, C.S. A Novel Mobile App (Heali) for Disease Treatment in Participants with Irritable Bowel Syndrome: Randomized Controlled Pilot Trial. J. Med. Internet Res. 2021, 23, e24134. [Google Scholar] [CrossRef] [Scilit]
- Salloum, G.; Semaan, E.; Tekli, J. PIN Prototype for Intelligent Nutrition Assessment and Meal Planning. In Proceedings of the 2018 IEEE International Conference on Cognitive Computing (ICCC), San Francisco, CA, USA, 2–7 July 2018; pp. 110–113. [Google Scholar]
- Samaan, J.S.; Issokson, K.; Feldman, E.; Fasulo, C.; Ng, W.H.; Rajeev, N.; Hollander, B.; Yeo, Y.H.; Vasiliauskas, E. Artificial Intelligence and Patient Education: Examining the Accuracy and Reproducibility of Responses to Nutrition Questions Related to Inflammatory Bowel Disease by GPT-4. medRxiv 2023. [Google Scholar] [CrossRef] [Scilit]
- Sano, A.; Johns, P.; Czerwinski, M. HealthAware: An advice system for stress, sleep, diet and exercise. In Proceedings of the 2015 International Conference on Affective Computing and Intelligent Interaction (ACII), Xi’an, China, 21–24 September 2015; pp. 546–552. [Google Scholar]
- Schiboni, G.; Wasner, F.; Amft, O. A Privacy-Preserving Wearable Camera Setup for Dietary Event Spotting in Free-Living. In Proceedings of the 2018 IEEE International Conference on Pervasive Computing and Communications Workshops (PerCom Workshops), Athens, Greece, 19–23 March 2018; pp. 872–877. [Google Scholar]
- Sefa-Yeboah, S.M.; Osei Annor, K.; Koomson, V.J.; Saalia, F.K.; Steiner-Asiedu, M.; Mills, G.A. Development of a Mobile Application Platform for Self-Management of Obesity Using Artificial Intelligence Techniques. Int. J. Telemed. Appl. 2021, 2021, 6624057. [Google Scholar] [CrossRef] [Scilit]
- Shamanna, P.; Saboo, B.; Damodharan, S.; Mohammed, J.; Mohamed, M.; Poon, T.; Kleinman, N.; Thajudeen, M. Reducing HbA1c in Type 2 Diabetes Using Digital Twin Technology-Enabled Precision Nutrition: A Retrospective Analysis. Diabetes Ther. 2020, 11, 2703–2714. [Google Scholar] [CrossRef] [Scilit]
- Shao, Z.; Fang, S.; Mao, R.; He, J.; Wright, J.L.; Kerr, D.A.; Boushey, C.J.; Zhu, F. Towards Learning Food Portion from Monocular Images with Cross-Domain Feature Adaptation. In Proceedings of the 2021 IEEE 23rd International Workshop on Multimedia Signal Processing (MMSP), Tampere, Finland, 6–8 October 2021; pp. 1–6. [Google Scholar]
- Shoneye, C.L.; Dhaliwal, S.S.; Pollard, C.M.; Boushey, C.J.; Delp, E.J.; Harray, A.J.; Howat, P.A.; Hutchesson, M.J.; Rollo, M.E.; Zhu, F.; et al. Image-Based Dietary Assessment and Tailored Feedback Using Mobile Technology: Mediating Behavior Change in Young Adults. Nutrients 2019, 11, 435. [Google Scholar] [CrossRef] [Scilit]
- Silva, V.C.; Gorgulho, B.; Marchioni, D.M.; Alvim, S.M.; Giatti, L.; de Araujo, T.A.; Alonso, A.C.; Santos, I.D.S.; Lotufo, P.A.; Bensenor, I.M. Recommender System Based on Collaborative Filtering for Personalized Dietary Advice: A Cross-Sectional Analysis of the ELSA-Brasil Study. Int. J. Environ. Res. Public Health 2022, 19, 14934. [Google Scholar] [CrossRef] [Scilit]
- Sowah, R.A.; Bampoe-Addo, A.A.; Armoo, S.K.; Saalia, F.K.; Gatsi, F.; Sarkodie-Mensah, B. Design and Development of Diabetes Management System Using Machine Learning. Int. J. Telemed. Appl. 2020, 2020, 8870141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, H.; Zhang, K.; Lan, W.; Gu, Q.; Jiang, G.; Yang, X.; Qin, W.; Han, D. An AI Dietitian for Type 2 Diabetes Mellitus Management Based on Large Language and Image Recognition Models: Preclinical Concept Validation Study. J. Med. Internet Res. 2023, 25, e51300. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, M.; Burke, L.E.; Baranowski, T.; Fernstrom, J.D.; Zhang, H.; Chen, H.C.; Bai, Y.; Li, Y.; Li, C.; Yue, Y.; et al. An exploratory study on a chest-worn computer for evaluation of diet, physical activity and lifestyle. J. Healthc. Eng. 2015, 6, 1–22. [Google Scholar] [CrossRef] [Scilit]
- Thames, Q.; Karpur, A.; Norris, W.; Xia, F.; Panait, L.; Weyand, T.; Sim, J. Nutrition5k: Towards Automatic Nutritional Understanding of Generic Food. In Proceedings of the 2021 IEEE/CVF Conference on Computer Vision and Pattern Recognition (CVPR), Online, 19–25 June 2021; pp. 8899–8907. [Google Scholar]
- Tunali, V.; Arslan, N.C.; Ermis, B.H.; Hakim, G.D.; Gundogdu, A.; Hora, M.; Nalbantoglu, O.U. A Multicenter Randomized Controlled Trial of Microbiome-Based Artificial Intelligence-Assisted Personalized Diet Vs Low Fodmap Diet: A Novel Approach for the Management of Irritable Bowel Syndrome. Am. J. Gastroenterol. 2024, 119, 1901–1912. [Google Scholar] [CrossRef] [Scilit]
- Turnin, M.C.; Gourdy, P.; Martini, J.; Buisson, J.C.; Chauchard, M.C.; Delaunay, J.; Schirr-Bonnans, S.; Taoui, S.; Poncet, M.F.; Cosma, V.; et al. Impact of a Remote Monitoring Programme Including Lifestyle Education Software in Type 2 Diabetes: Results of the Educ@dom Randomised Multicentre Study. Diabetes Ther. 2021, 12, 2059–2075. [Google Scholar] [CrossRef] [Scilit]
- Valero-Ramon, Z.; Fernandez-Llatas, C.; Martinez-Millana, A.; Traver, V. A Dynamic Behavioral Approach to Nutritional Assessment using Process Mining. In Proceedings of the 2019 IEEE 32nd International Symposium on Computer-Based Medical Systems (CBMS), Córdoba, Spain, 5–7 June 2019; pp. 398–404. [Google Scholar]
- Vasiloglou, M.F.; Lu, Y.; Stathopoulou, T.; Papathanail, I.; Fah, D.; Ghosh, A.; Baumann, M.; Mougiakakou, S. Assessing Mediterranean Diet Adherence with the Smartphone: The Medipiatto Project. Nutrients 2020, 12, 3763. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Walker, W.P.; Bhatia, D.K. Automated Ingestion Detection for a Health Monitoring System. IEEE J. Biomed. Health Inform. 2014, 18, 682–692. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, C.; Kumar, T.S.; Raedt, W.D.; Camps, G.; Hallez, H.; Vanrumste, B. Eat-Radar: Continuous Fine-Grained Intake Gesture Detection Using FMCW Radar and 3D Temporal Convolutional Network with Attention. IEEE J. Biomed. Health Inform. 2024, 28, 1000–1011. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, X.; Li, Z.; Wu, H. Personalized Recommendation Method of “Carbohydrate-Protein” Supplement Based on Machine Learning and Enumeration Method. IEEE Access 2023, 11, 100573–100586. [Google Scholar] [CrossRef] [Scilit]
- Zhang, L.; Huang, S.; Das, A.; Do, E.; Glantz, N.; Bevier, W.; Santiago, R.; Kerr, D.; Gutierrez-Osuna, R.; Mortazavi, B.J. Joint Embedding of Food Photographs and Blood Glucose for Improved Calorie Estimation. In Proceedings of the 2023 IEEE EMBS International Conference on Biomedical and Health Informatics (BHI), Pittsburgh, PA, USA, 15–18 October 2023; pp. 1–4. [Google Scholar]
- Chew, H.S.J.; Ang, W.H.D.; Lau, Y. The potential of artificial intelligence in enhancing adult weight loss: A scoping review. Public Health Nutr. 2021, 24, 1993–2020. [Google Scholar] [CrossRef] [Scilit]
- Mennella, C.; Maniscalco, U.; De Pietro, G.; Esposito, M. Ethical and regulatory challenges of AI technologies in healthcare: A narrative review. Heliyon 2024, 10, e26297. [Google Scholar] [CrossRef] [Scilit]
- Shonkoff, E.; Cara, K.C.; Pei, X.A.; Chung, M.; Kamath, S.; Panetta, K.; Hennessy, E. AI-based digital image dietary assessment methods compared to humans and ground truth: A systematic review. Ann. Med. 2023, 55, 2273497. [Google Scholar] [CrossRef] [Scilit]
- Bailey, R.L. Overview of dietary assessment methods for measuring intakes of foods, beverages, and dietary supplements in research studies. Curr. Opin. Biotechnol. 2021, 70, 91–96. [Google Scholar] [CrossRef] [Scilit]
- Ma, W.; Cai, B.; Wang, Y.; Wang, L.; Sun, M.W.; Lu, C.D.; Jiang, H. Artificial intelligence driven malnutrition diagnostic model for patients with acute abdomen based on GLIM criteria: A cross-sectional research protocol. BMJ Open 2024, 14, e077734. [Google Scholar] [CrossRef] [Scilit]
- Abeltino, A.; Riente, A.; Bianchetti, G.; Serantoni, C.; De Spirito, M.; Capezzone, S.; Esposito, R.; Maulucci, G. Digital applications for diet monitoring, planning, and precision nutrition for citizens and professionals: A state of the art. Nutr. Rev. 2025, 83, e574–e601. [Google Scholar] [CrossRef] [Scilit]
- ZOE Limited. ZOE. Available online: https://zoe.com/en-gb/faqs (accessed on 17 September 2025).
- Bermingham, K.M.; Linenberg, I.; Polidori, L.; Asnicar, F.; Arrè, A.; Wolf, J.; Badri, F.; Bernard, H.; Capdevila, J.; Bulsiewicz, W.J.; et al. Effects of a personalized nutrition program on cardiometabolic health: A randomized controlled trial. Nat. Med. 2024, 30, 1888–1897. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- National Institute of Health. National Institute of Health: Office of Nutrition Research; National Institute of Health: Bethesda, MD, USA, 2025; p. 24. [Google Scholar]
- Truby, H.; Allman-Farinelli, M.; Beck, E.J.; Beckett, E.L.; Bondonno, C.; Dordevic, A.L.; Livingstone, K.M.; Willcox, J.; Wilkinson, S.A. Advancing the decadal plan for the science of nutrition: Progressing a framework for implementation. Nutr. Diet. 2024, 81, 133–148. [Google Scholar] [CrossRef] [Scilit]
- Salas-Groves, E.; Galyean, S.; Alcorn, M.; Childress, A. Behavior Change Effectiveness Using Nutrition Apps in People with Chronic Diseases: Scoping Review. JMIR mHealth uHealth 2023, 11, e41235. [Google Scholar] [CrossRef] [Scilit]
- Detopoulou, P.; Voulgaridou, G.; Moschos, P.; Levidi, D.; Anastasiou, T.; Dedes, V.; Diplari, E.M.; Fourfouri, N.; Giaginis, C.; Panoutsopoulos, G.I.; et al. Artificial intelligence, nutrition, and ethical issues: A mini-review. Clin. Nutr. Open Sci. 2023, 50, 46–56. [Google Scholar] [CrossRef] [Scilit]
- Safran, E.; Yildirim, S. A cross-sectional study on ChatGPT’s alignment with clinical practice guidelines in musculoskeletal rehabilitation. BMC Musculoskelet. Disord. 2025, 26, 411. [Google Scholar] [CrossRef] [Scilit]
- Desroches, S.; Lapointe, A.; Ratté, S.; Gravel, K.; Légaré, F.; Turcotte, S.; Desroches, S. Interventions to enhance adherence to dietary advice for preventing and managing chronic diseases in adults. Cochrane Database Syst. Rev. 2013, 2013, CD008722. [Google Scholar] [CrossRef] [Scilit]
- Atwal, K. Artificial intelligence in clinical nutrition and dietetics: A brief overview of current evidence. Nutr. Clin. Pract. 2024, 39, 736–742. [Google Scholar] [CrossRef] [Scilit]
- Schubert, T.; Oosterlinck, T.; Stevens, R.D.; Maxwell, P.H.; van der Schaar, M. AI education for clinicians. eClinicalMedicine 2025, 79, 102968. [Google Scholar] [CrossRef] [Scilit]
- Tetik, G.; Türkeli, S.; Pinar, S.; Tarim, M. Health information systems with technology acceptance model approach: A systematic review. Int. J. Med. Inform. 2024, 190, 105556. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ibrahim, F.; Münscher, J.C.; Daseking, M.; Telle, N.T. The technology acceptance model and adopter type analysis in the context of artificial intelligence. Front. Artif. Intell. 2025, 7, 1496518. [Google Scholar] [CrossRef] [Scilit]
- Chen, J.; Allman-Farinelli, M. Impact of Training and Integration of Apps into Dietetic Practice on Dietitians’ Self-Efficacy with Using Mobile Health Apps and Patient Satisfaction. JMIR mHealth uHealth 2019, 7, e12349. [Google Scholar] [CrossRef] [Scilit]
- Nilsen, P.; Sundemo, D.; Heintz, F.; Neher, M.; Nygren, J.; Svedberg, P.; Petersson, L. Towards evidence-based practice 2.0: Leveraging artificial intelligence in healthcare. Front. Health Serv. 2024, 4, 1368030. [Google Scholar] [CrossRef] [Scilit]
- Barrimore, S.E.; Cameron, A.E.; Young, A.M.; Hickman, I.J.; Campbell, K.L. Translating Research into Practice: How Confident Are Allied Health Clinicians? J. Allied. Health 2020, 49, 258–262. [Google Scholar]
- Young, A.M.; Olenski, S.; Wilkinson, S.A.; Campbell, K.; Barnes, R.; Cameron, A.; Hickman, I. Knowledge Translation in Dietetics: A Survey of Dietitians’ Awareness and Confidence. Can. J. Diet. Pract. Res. 2020, 81, 49–53. [Google Scholar] [CrossRef] [Scilit]
- Hurt, R.T.; Stephenson, C.R.; Gilman, E.A.; Aakre, C.A.; Croghan, I.T.; Mundi, M.S.; Ghosh, K.; Edakkanambeth, V.J. The Use of an Artificial Intelligence Platform Open Evidence to Augment Clinical Decision-Making for Primary Care Physicians. J. Prim. Care Community Health 2025, 16, 21501319251332215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mahajan, A.; Powell, D. Generalist medical AI reimbursement challenges and opportunities. npj Digit. Med. 2025, 8, 125. [Google Scholar] [CrossRef] [Scilit]
- Angus, D.C.; Khera, R.; Lieu, T.; Liu, V.; Ahmad, F.S.; Anderson, B.; Bhavani, S.V.; Bindman, A.; Brennan, T.; Celi, L.A.; et al. AI, Health, and Health Care Today and Tomorrow: The JAMA Summit Report on Artificial Intelligence. JAMA 2025. [Google Scholar] [CrossRef] [Scilit]
- Popover, J.L.; Wallace, S.P.; Feldman, J.; Chastain, G.; Kalathia, C.; Imam, A.; Almasri, M.; Toomey, P.G. Artificial Intelligence in Medicine: A Specialty-Level Overview of Emerging AI Trends. JSLS 2025, 29, e2025.00041. [Google Scholar] [CrossRef] [Scilit]
- Zink, A.; Chernew, M.E.; Neprash, H.T. How Should Medicare Pay for Artificial Intelligence? JAMA Intern. Med. 2024, 184, 863–864. [Google Scholar] [CrossRef] [Scilit]
- Stoyanov, S.R.; Hides, L.; Kavanagh, D.J.; Zelenko, O.; Tjondronegoro, D.; Mani, M. Mobile App Rating Scale: A New Tool for Assessing the Quality of Health Mobile Apps. JMIR mHealth uHealth 2015, 3, e27. [Google Scholar] [CrossRef] [Scilit]
- Liu, X.; Cruz Rivera, S.; Moher, D.; Calvert, M.J.; Denniston, A.K.; Chan, A.W.; Darzi, A.; Holmes, C.; Yau, C.; Ashrafian, H.; et al. Reporting guidelines for clinical trial reports for interventions involving artificial intelligence: The CONSORT-AI extension. Nat. Med. 2020, 26, 1364–1374. [Google Scholar] [CrossRef] [Scilit]
- Collins, G.S.; Moons, K.G.M.; Dhiman, P.; Riley, R.D.; Beam, A.L.; Van Calster, B.; Ghassemi, M.; Liu, X.; Reitsma, J.B.; van Smeden, M.; et al. TRIPOD+AI statement: Updated guidance for reporting clinical prediction models that use regression or machine learning methods. BMJ 2024, 385, e078378. [Google Scholar] [CrossRef] [Scilit]
- Kwong, J.C.C.; Khondker, A.; Lajkosz, K.; McDermott, M.B.A.; Frigola, X.B.; McCradden, M.D.; Mamdani, M.; Kulkarni, G.S.; Johnson, A.E.W. APPRAISE-AI Tool for Quantitative Evaluation of AI Studies for Clinical Decision Support. JAMA Netw. Open 2023, 6, e2335377. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hanna, M.G.; Pantanowitz, L.; Jackson, B.; Palmer, O.; Visweswaran, S.; Pantanowitz, J.; Deebajah, M.; Rashidi, H.H. Ethical and Bias Considerations in Artificial Intelligence/Machine Learning. Mod. Pathol. 2025, 38, 100686. [Google Scholar] [CrossRef] [Scilit]
- Perivolaris, A.; Adams-McGavin, C.; Madan, Y.; Kishibe, T.; Antoniou, T.; Mamdani, M.; Jung, J.J. Quality of interaction between clinicians and artificial intelligence systems. A systematic review. Future Heal. J. 2024, 11, 100172. [Google Scholar] [CrossRef] [Scilit]
- Sosa-Holwerda, A.; Park, O.H.; Albracht-Schulte, K.; Niraula, S.; Thompson, L.; Oldewage-Theron, W. The Role of Artificial Intelligence in Nutrition Research: A Scoping Review. Nutrients 2024, 16, 2066. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Theodore Armand, T.P.; Nfor, K.A.; Kim, J.I.; Kim, H.C. Applications of Artificial Intelligence, Machine Learning, and Deep Learning in Nutrition: A Systematic Review. Nutrients 2024, 16, 1073. [Google Scholar] [CrossRef] [Scilit]
- Phalle, A.; Gokhale, D. Navigating next-gen nutrition care using artificial intelligence-assisted dietary assessment tools-a scoping review of potential applications. Front. Nutr. 2025, 12, 1518466. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aromataris, E.; Lockwood, C.; Porritt, K.; Pilla, B.; Jordan, Z. JBI Manual for Evidence Synthesis; JBI: Adelaide, Australia, 2024. [Google Scholar] [CrossRef] [Scilit]
- Cant, R.P. Public Health Nutrition: The Accord of Dietitian Providers in Managing Medicare Chronic Care Outpatients in Australia. Int. J. Environ. Res. Public Health 2010, 7, 1841–1854. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kassem, H.; Beevi, A.A.; Basheer, S.; Lutfi, G.; Cheikh Ismail, L.; Papandreou, D. Investigation and Assessment of AI’s Role in Nutrition-An Updated Narrative Review of the Evidence. Nutrients 2025, 17, 190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
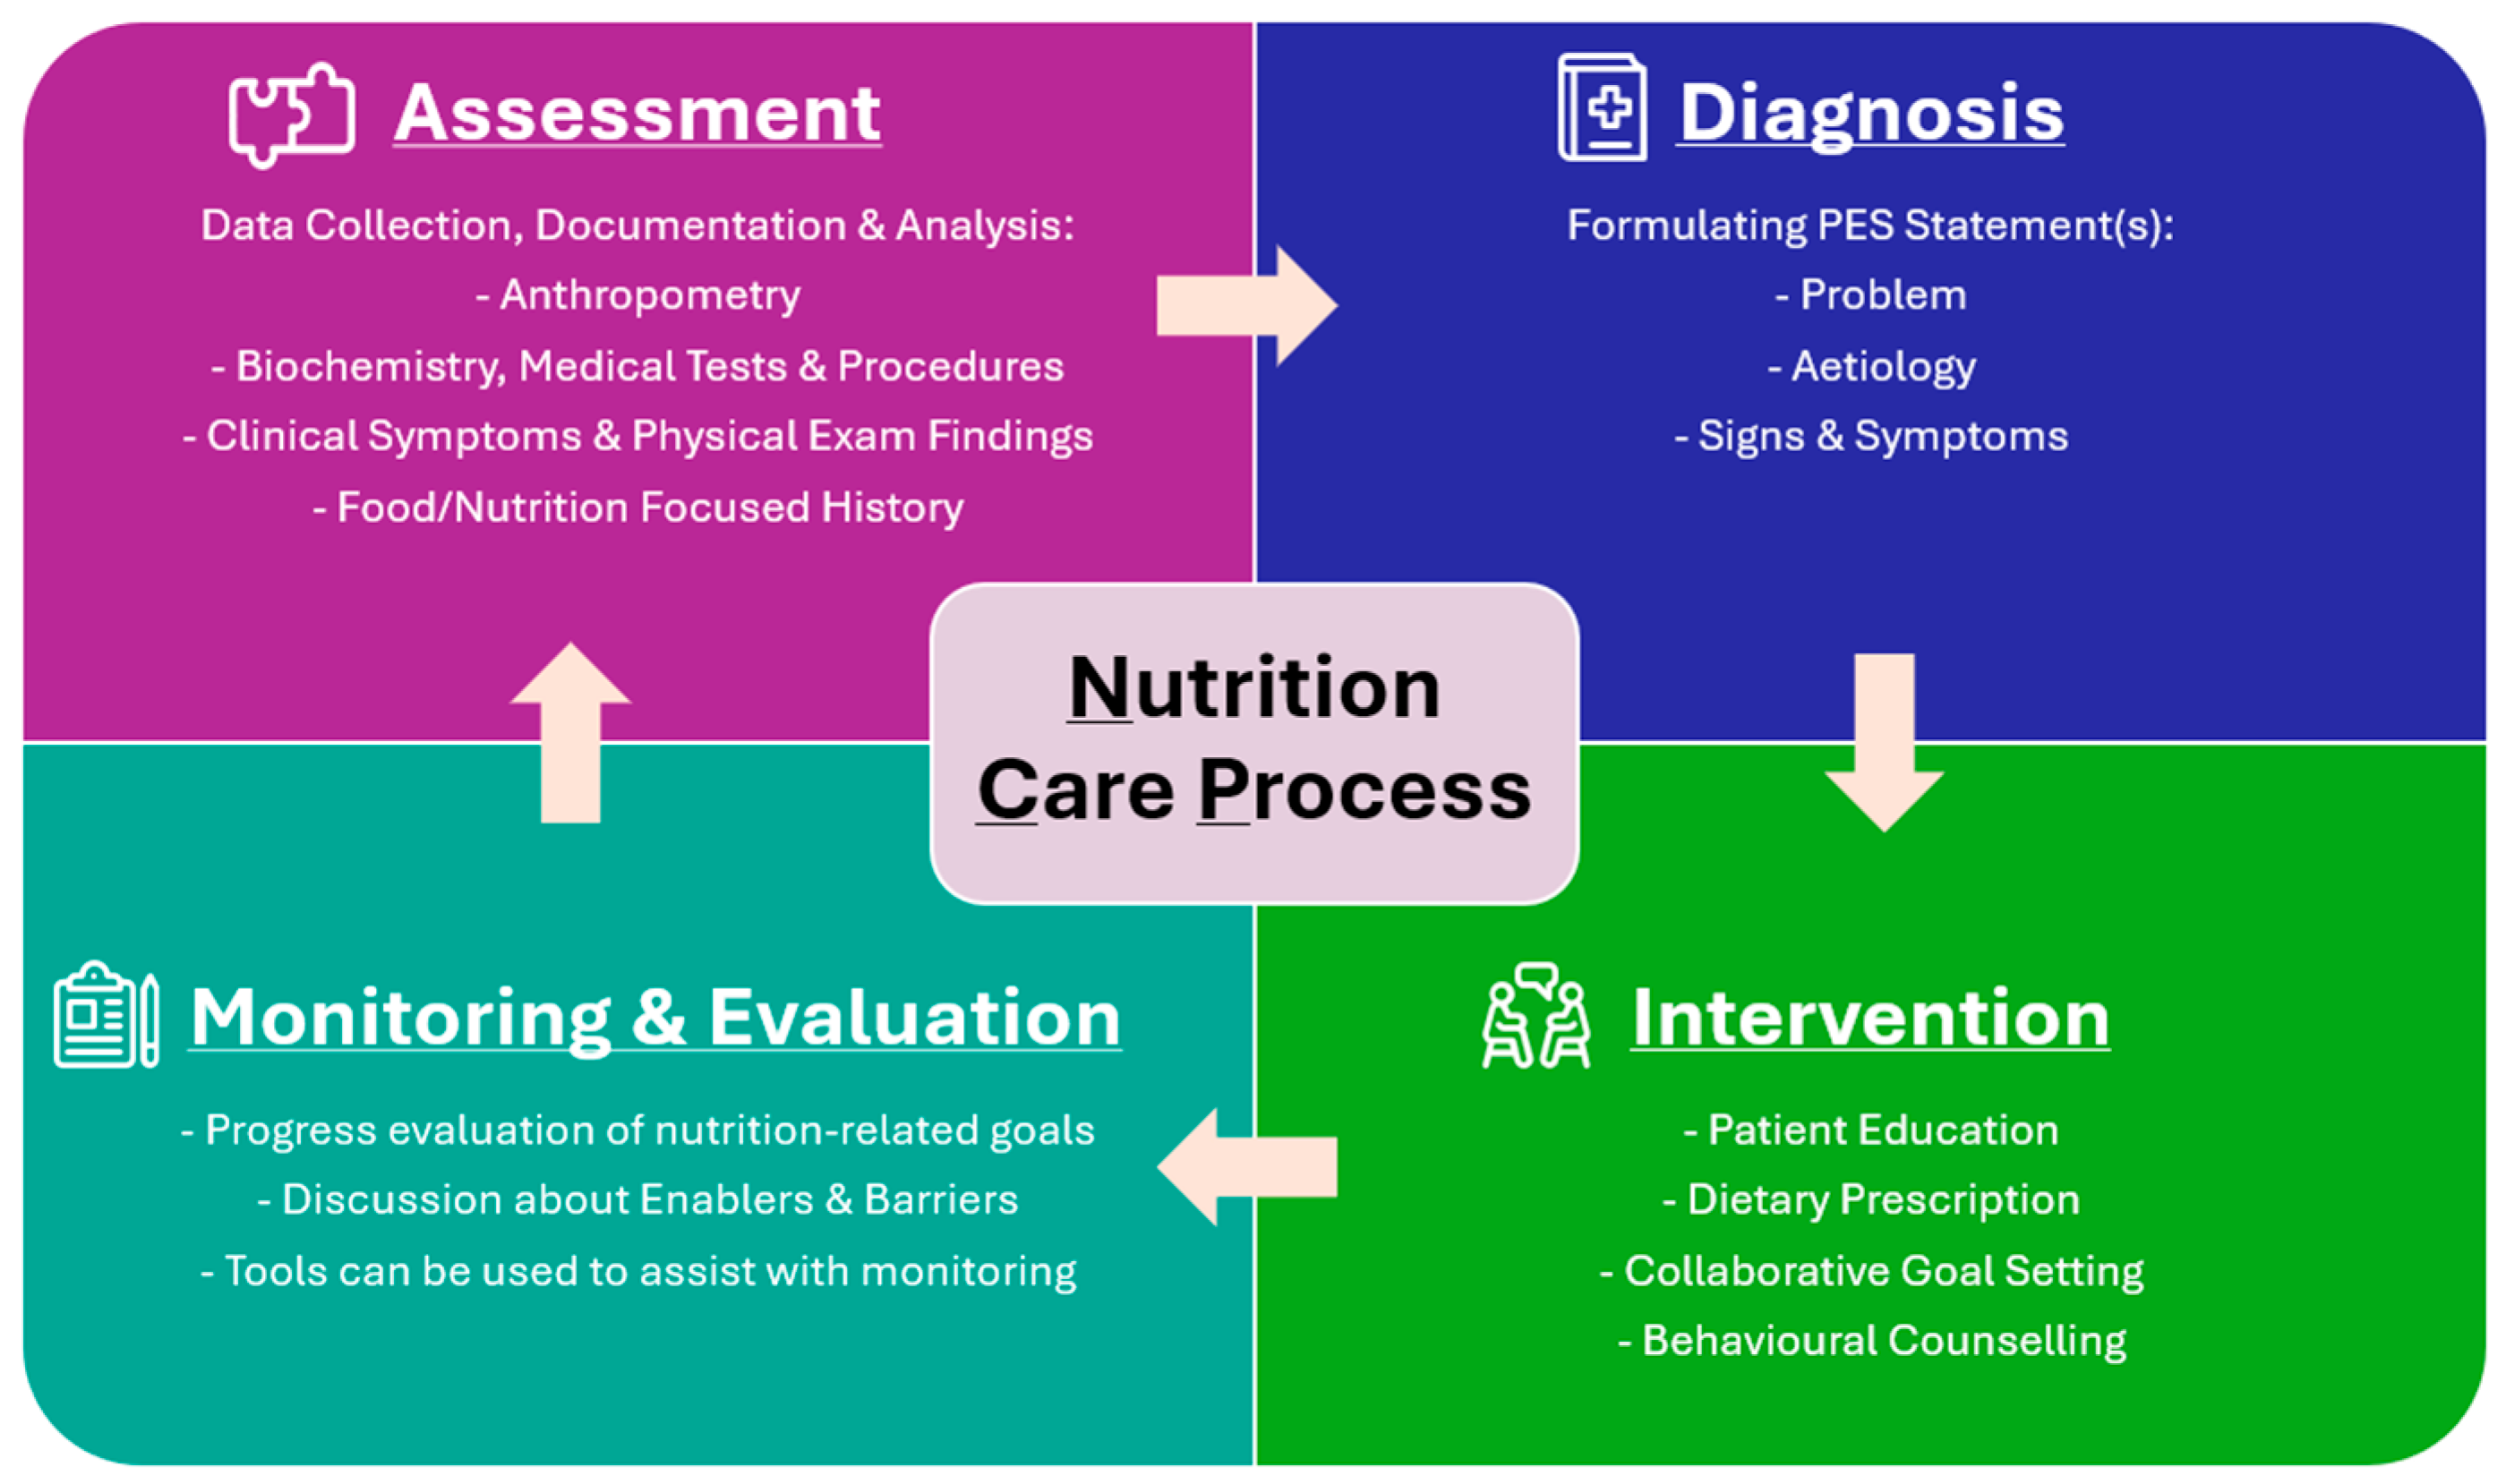
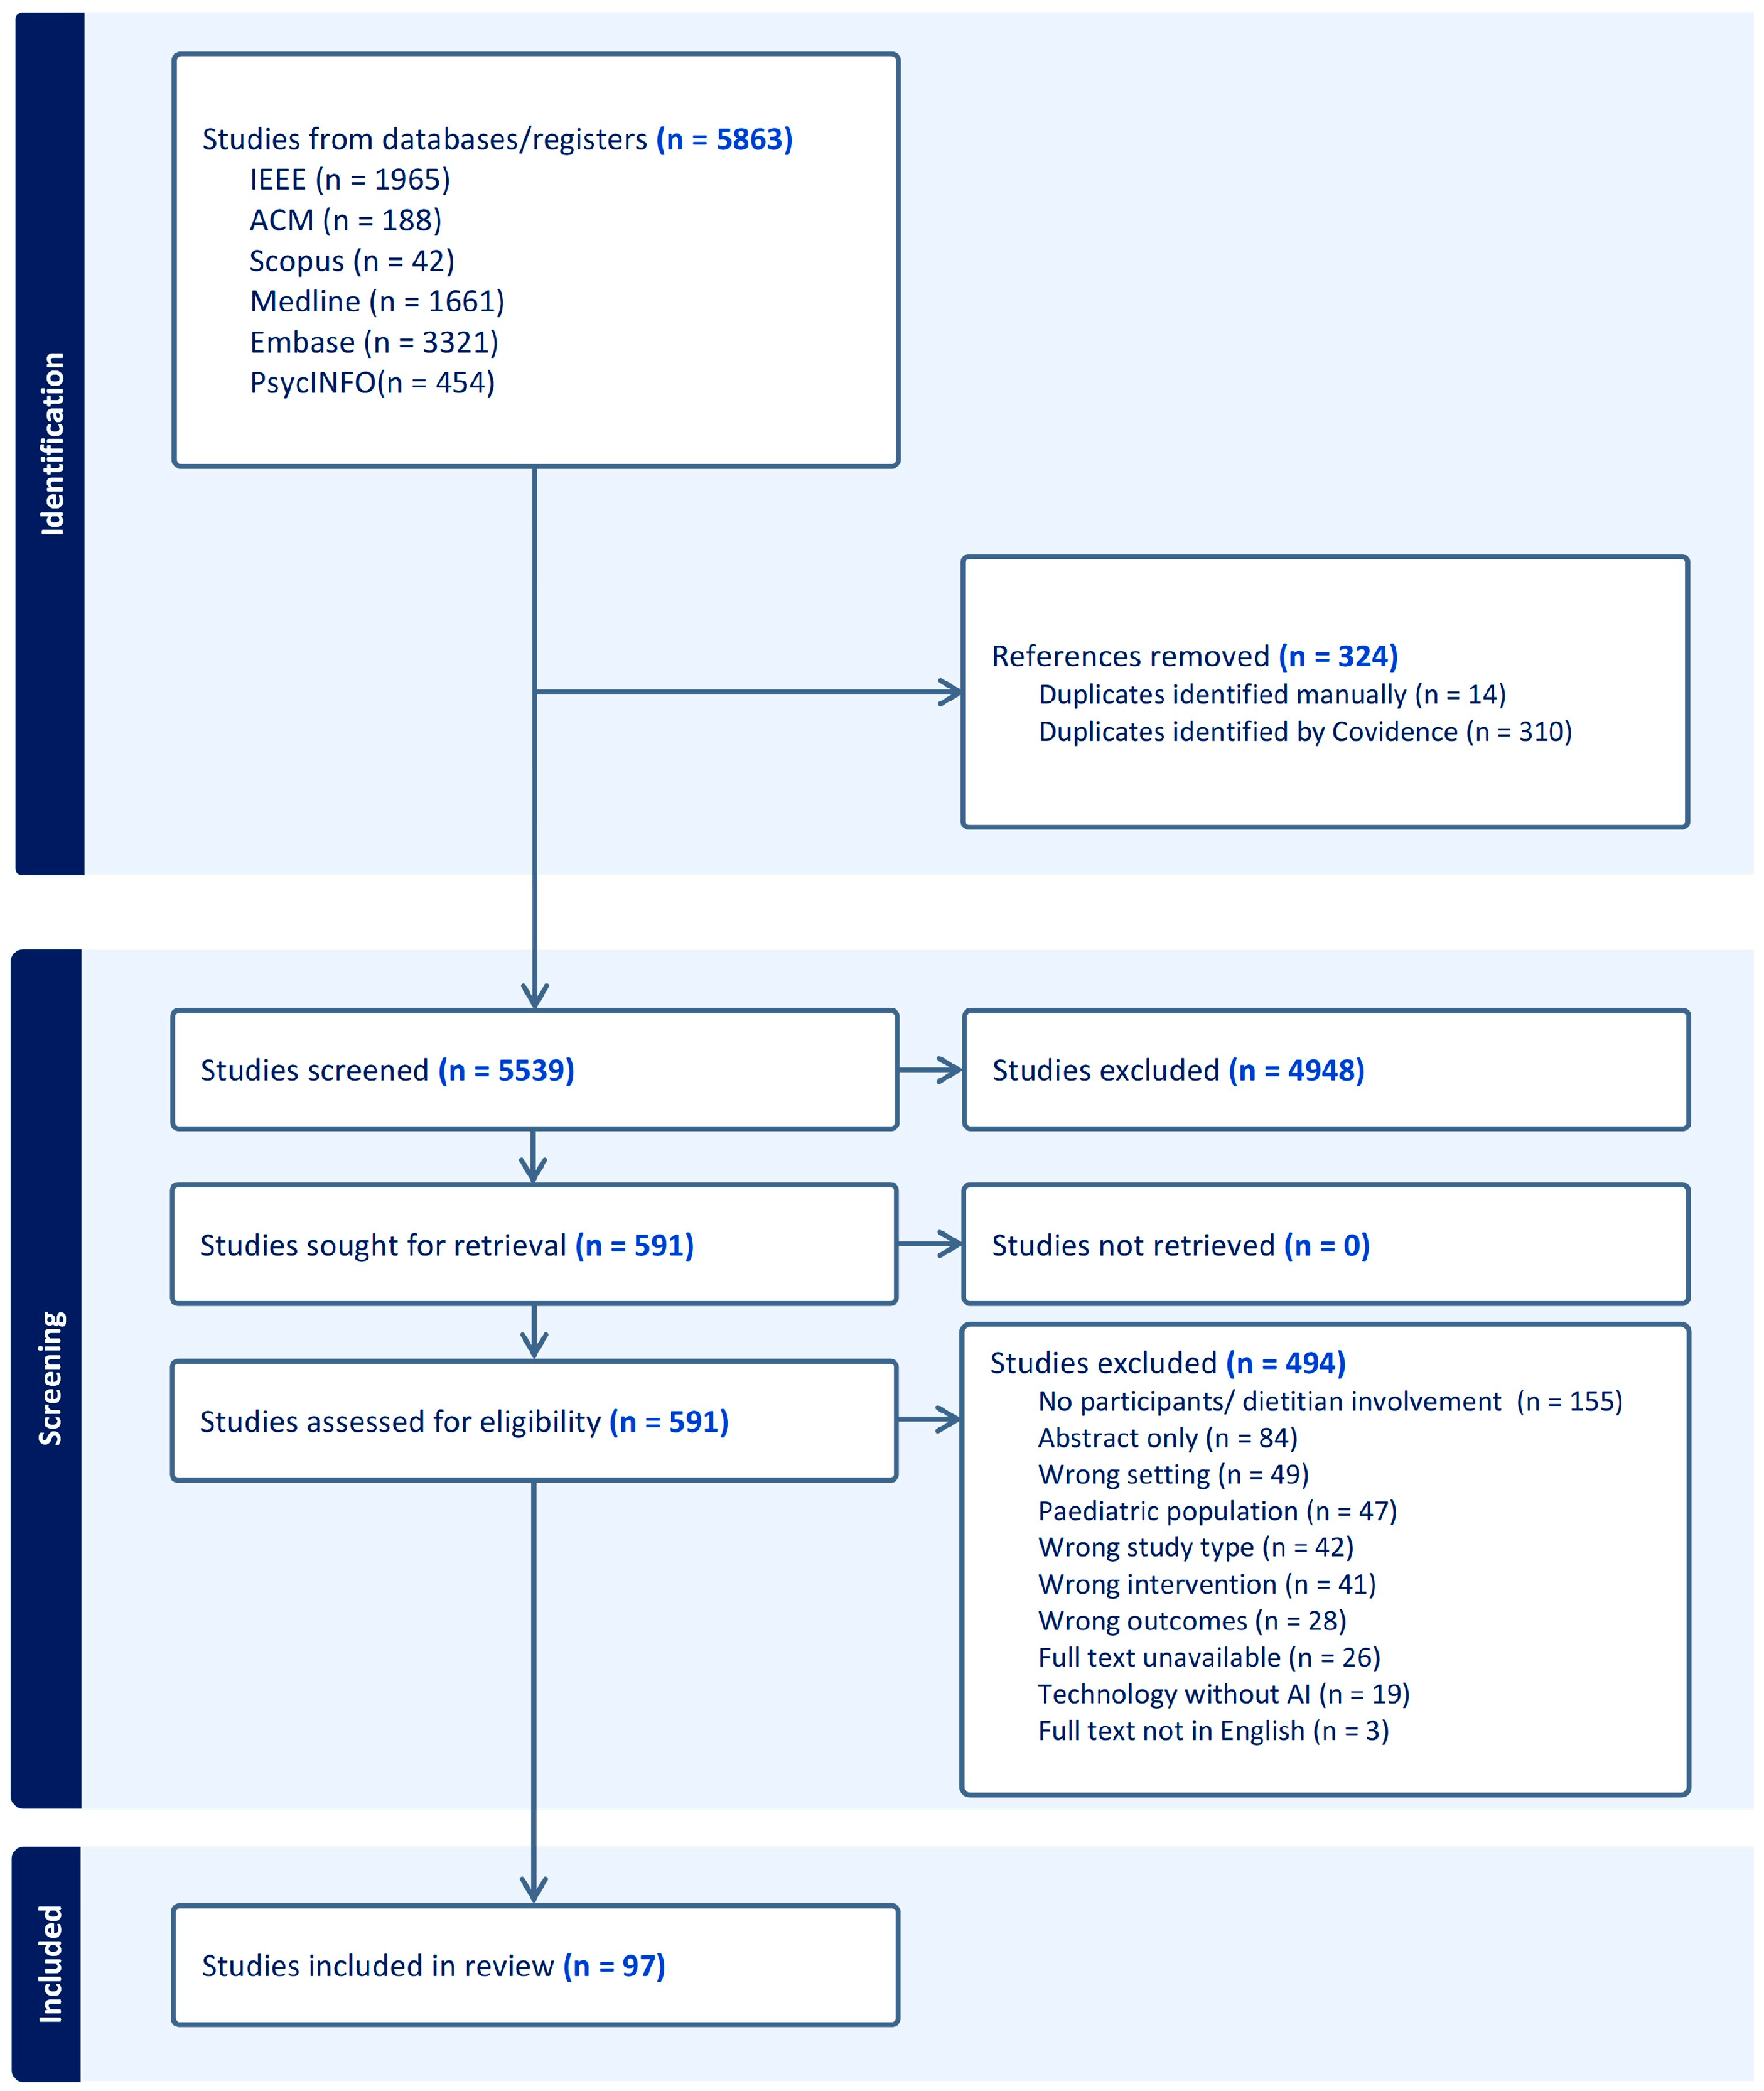
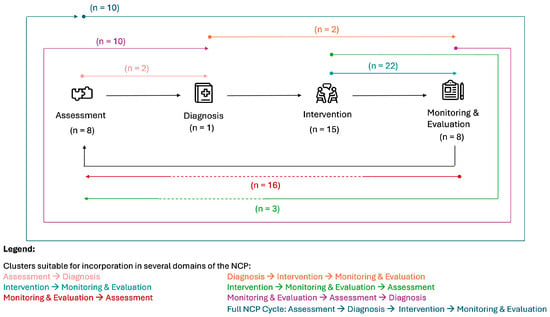
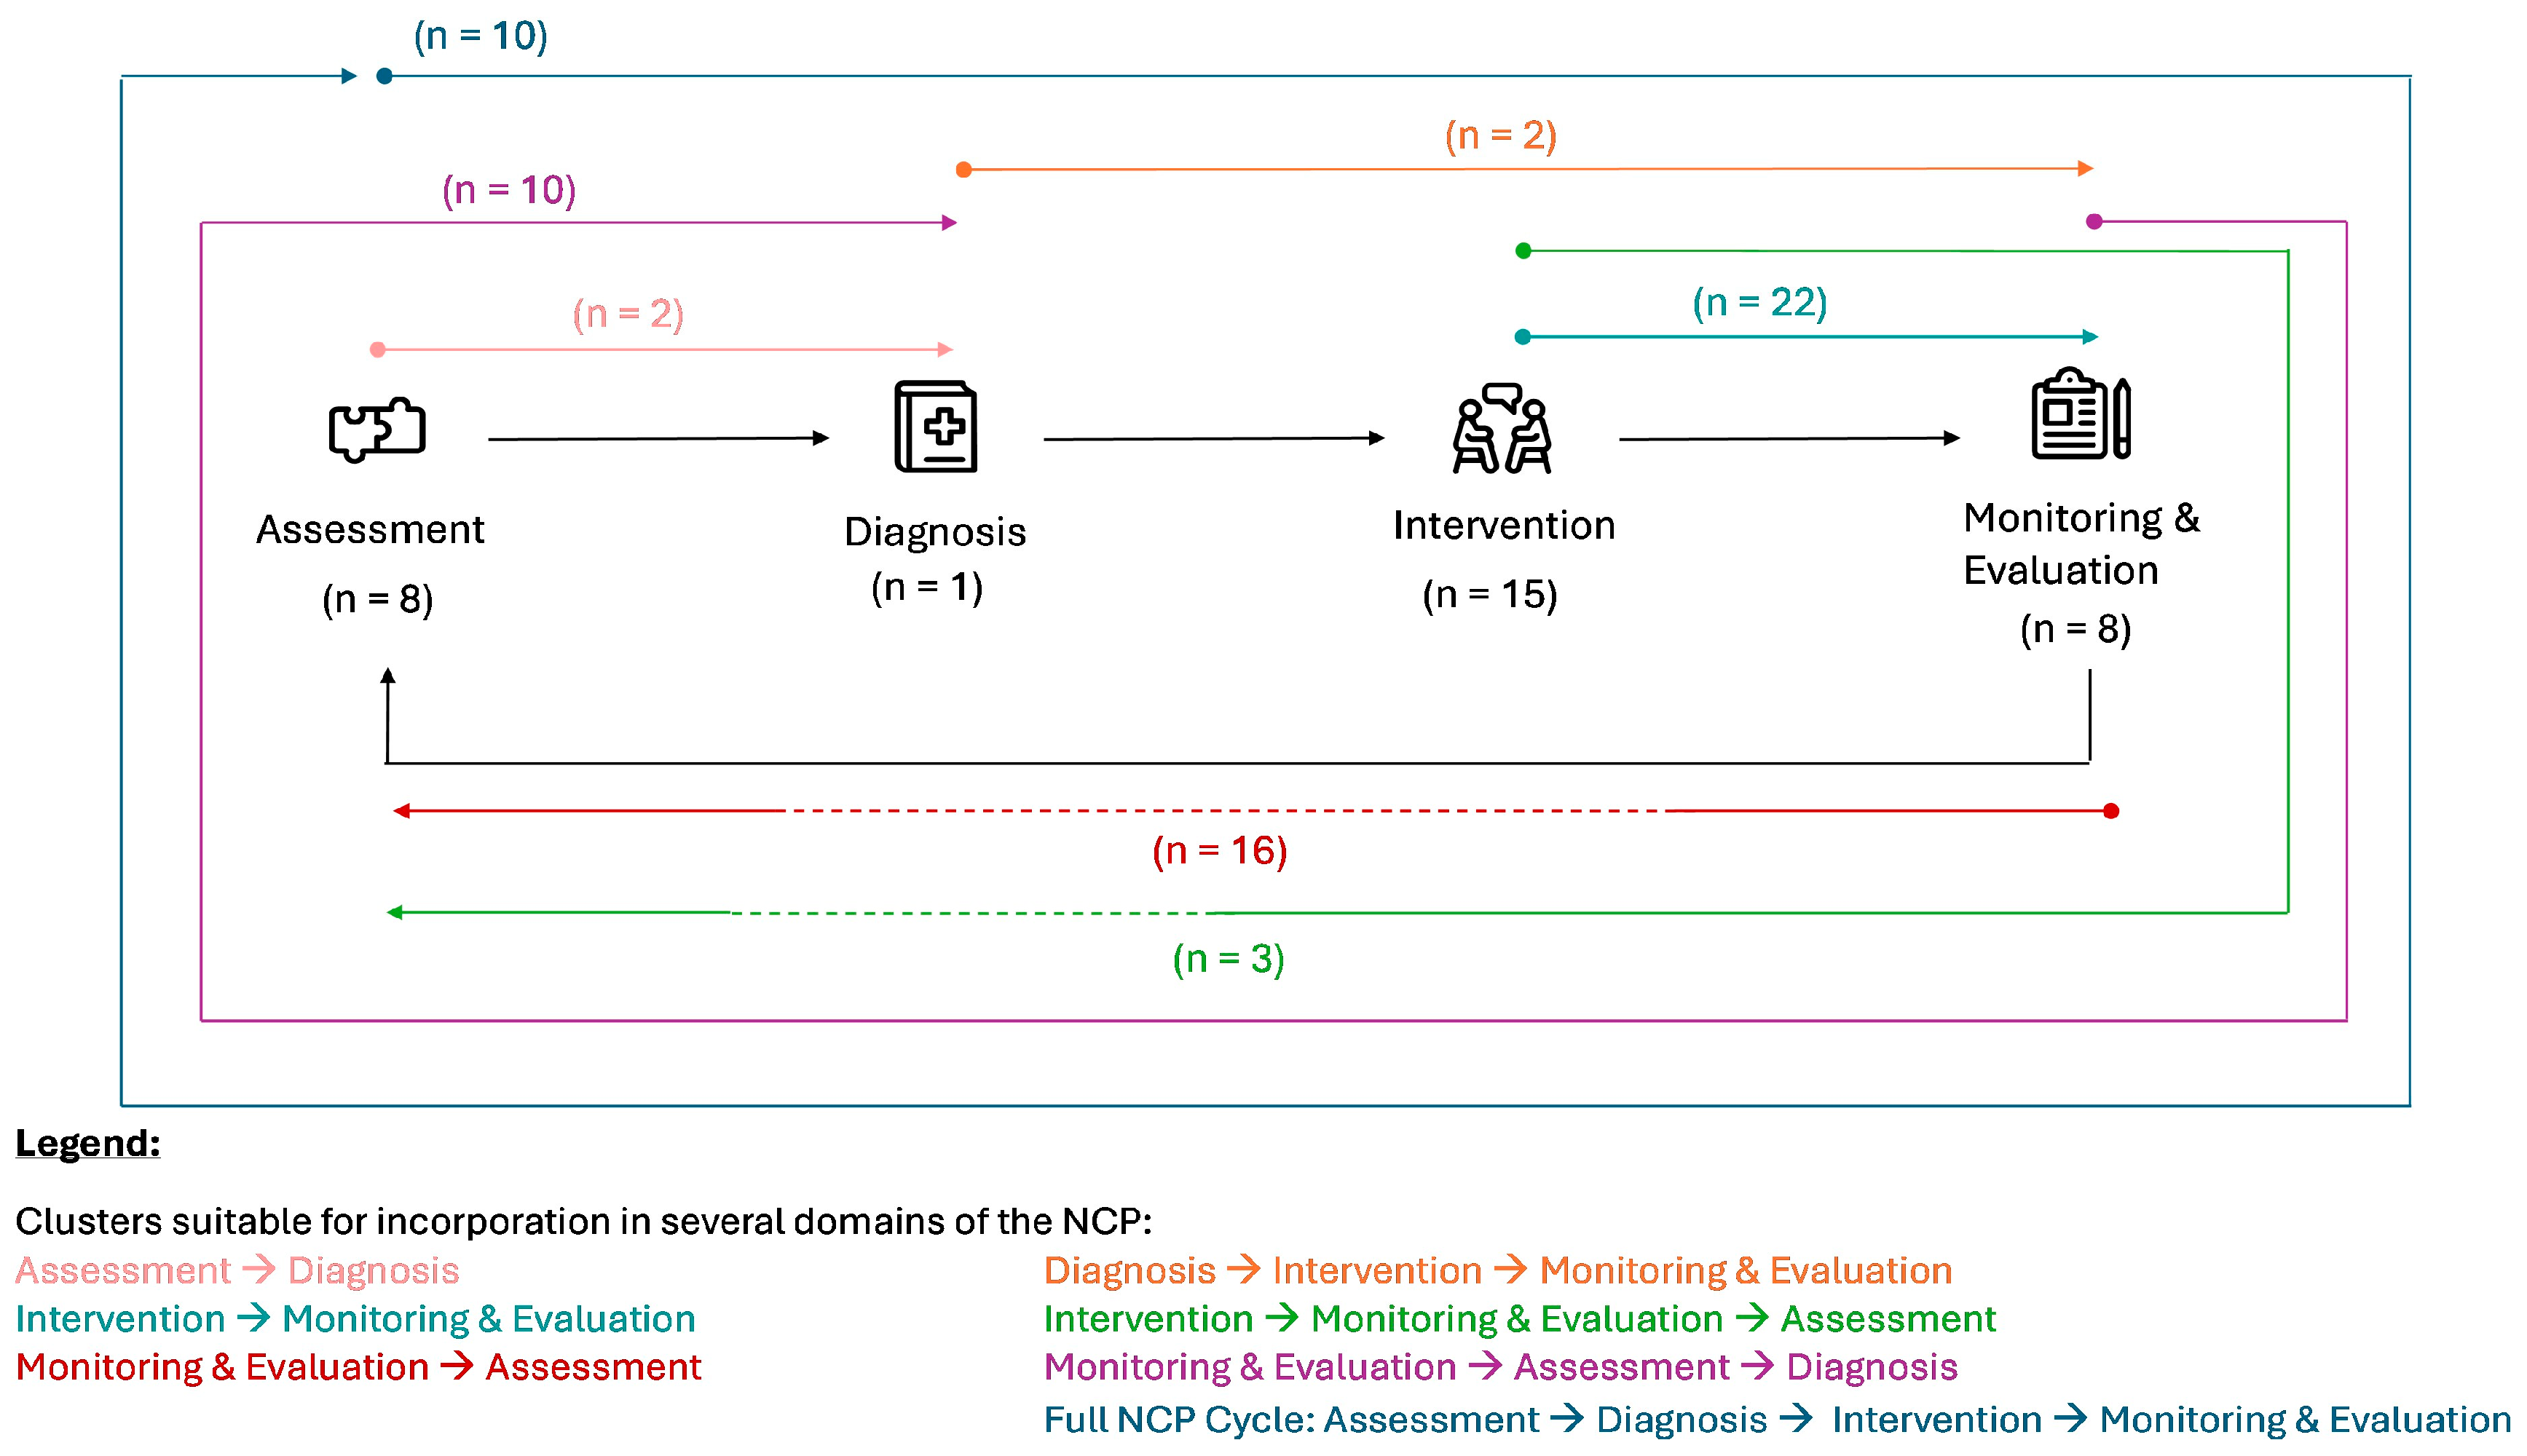

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).