


Abstract
Background: The gold-standard techniques for measuring insulin sensitivity and secretion are well established. However, they may be perceived as invasive and expensive for use in dietary intervention studies. Thus, surrogate markers have been proposed as alternative markers for insulin sensitivity and secretion. This systematic review aimed to identify markers of insulin sensitivity and secretion in response to dietary intervention and assess their suitability as surrogates for the gold-standard methodology. Methods: Three databases, PubMed, Scopus, and Cochrane were searched, intervention studies and randomised controlled trials reporting data on dietary intake, a gold standard of analysis of insulin sensitivity (either euglycaemic-hyperinsulinaemic clamp or intravenous glucose tolerance test and secretion (acute insulin response to glucose), as well as surrogate markers for insulin sensitivity (either fasting insulin, area under the curve oral glucose tolerance tests and HOMA-IR) and insulin secretion (disposition index), were selected. Results: We identified thirty-five studies that were eligible for inclusion. We found insufficient evidence to predict insulin sensitivity and secretion with surrogate markers when compared to gold standards in nutritional intervention studies. Conclusions: Future research is needed to investigate if surrogate measures of insulin sensitivity and secretion can be repeatable and reproducible in the same way as gold standards.
1. Introduction
Type 2 Diabetes (T2D) is a chronic, lifestyle-related disease characterised by elevated circulating glucose levels. The International Diabetes Federation (IDF) has estimated that 624 million adults, aged 20–79 years old, will have T2D by 2040 [1]. Currently, T2D comprises 90% of all diabetes cases worldwide and is a major cause of blindness, kidney failure, heart attacks, stroke, and lower limb amputations [2].
Insulin resistance and diminished insulin secretion are key characteristics of the progression to type 2 diabetes [3], and are often used as outcomes in intervention trials aimed at preventing the development of type 2 diabetes. The assessment of insulin sensitivity and secretion is vital for the early identification of people at risk of developing diabetes as well as for implementing interventions to prevent or delay the pathological progression of the disease.
The classical test to assess insulin sensitivity is the euglycaemic-hyperinsulinaemic clamp (EHC) [4]. During the EHC, insulin concentration is elevated to a standardised level by infusing insulin at a constant rate for 2–3 h. Hyperinsulinaemia stimulates glucose utilisation and suppresses glucose production. Glucose concentration is kept constant at a fixed value (typically ~5 mmol/L) utilising a variable glucose infusion. The variable glucose infusion is adjusted based on frequent glucose measurements, according to an algorithm. Insulin sensitivity is determined from the mean glucose infusion rate at the end of the test when the glucose infusion rate has stabilised (the steady-state period). Under these conditions, the rate of glucose infusion is nearly equal to the rate of glucose utilisation at the standardised insulin and glucose levels, as glucose production is strongly suppressed [5]. Therefore, the rate of glucose infusion, the simplest index of the glucose clamp, is approximately equal to the rate of glucose utilisation.
Another assessment of insulin sensitivity is the intravenous glucose tolerance test (IVGTT) [6]. In this test, glucose is injected intravenously (typically 300 mg/kg), and glucose and insulin concentrations are measured for 3–4 h. The time course of glucose and insulin is analysed with a simplified model of glucose metabolism (the minimal model) to obtain an index of insulin sensitivity denoted as SI. In an important variant of the protocol [7,8,9] a bolus injection of insulin (180–300 pmol/kg) or a brief insulin infusion, given 20 min after glucose injection is performed to increase insulin concentration. The IVGTT is experimentally simpler than the EHC. Data analysis, however, requires specialised software and expertise [10].
For insulin secretion, defining a reference method is more problematic than for insulin sensitivity. Standardisation of the glucose levels is only possible with intravenous glucose infusion.
The reference methods with intravenous glucose infusion are the hyperglycaemic clamp (HC) and the first phase insulin secretion of IVGTT or acute insulin response to glucose (AIRg). IVGTT also provides an estimate of insulin sensitivity, as detailed previously.
AIRg is characterised by an abrupt rise in plasma insulin levels over three to five minutes followed by a decline. The classical index of first-phase insulin secretion is the incremental area under the insulin or C-peptide curve in the first eight-ten minutes. AIRg is a good predictor of diabetes [11].
The main problem with EHC, IVGTT, and AIRg is that, even though they are considered gold standard techniques, they may be perceived as invasive, impractical, and expensive for use in dietary intervention studies. All these methods imply problems for the patients. Therefore, surrogate markers provide indirect estimates; for example, insulin (or C-peptide) and glucose measurements in blood samples taken in the fasting state or after a glucose challenge or a standardised meal.
Surrogate markers for insulin sensitivity and secretion are based on established principles of glucose kinetics and insulin-mediated glucose disposal, and most have been developed from or validated against the euglycaemic-hyperinsulinaemic clamp [12].
Surrogate measures are divided into two families: the oral glucose tolerance test (OGTT) indices and the fasting indices. The OGTT’s surrogate measures are e.g., the Stumvoll Index and the Matsuda Index. During OGTT, blood glucose and insulin levels are assessed in a fasted state (t = 0) and usually at three different time slots (t = 30, 60, and 120 min) after the consumption of a standard oral glucose load of 75 g [13]. The fasting surrogate measures include the homeostatic model assessment for insulin resistance (HOMA-IR), the quantitative insulin sensitivity check index (QUICKI), and fasting insulin.
HOMA-IR was originally derived from a mathematical model of glucose homeostasis [14], as the product of fasting glucose and insulin and a scaling factor to yield a value of 100% in individuals with normal insulin sensitivity. QUICKI is calculated from fasting glucose and insulin concentrations and is mathematically equivalent to the inverse of the logarithm of HOMA-IR plus a constant [15]. Fasting insulin has been considered the most feasible way of measuring insulin resistance [16]; however, one main disadvantage of the method is the lack of accuracy or precision of available insulin assays [17].
Surrogate markers of AIRg are HOMA-beta and the disposition index (DI)—the latter taking the level of insulin sensitivity into account. The analysis of the relationship between insulin secretion parameters and insulin sensitivity has led to the concept that the two variables are hyperbolically related [18]. The product of the insulin secretion and insulin sensitivity parameters, which is constant along the hyperbola representing the normal relationship, has been proposed as an index of beta-cell function properly corrected for insulin sensitivity. This index has been denoted as the “Disposition Index”.
The advantage of surrogate markers is the less complex and invasive nature of the participant phenotyping. There have been several highly cited and extensive reviews in the past on surrogate markers of insulin sensitivity [19,20,21,22] and insulin secretion [23,24,25,26]. The overall conclusion of the reviews was that surrogate markers are useful for large epidemiological studies and that they are appropriate when the investigators are aware of their limitations.
The novelty and importance of this systematic review focus on the use of surrogate markers in nutritional intervention studies, when compared with gold standards, which have not been previously reviewed. Moreover, the use of these measures among individuals without diabetes has not been extensively reviewed. This is of importance because of the need for sensitive markers to evaluate the efficacy of trials aiming to prevent the development of diabetes. The present review investigates surrogate markers of insulin sensitivity and secretion compared to gold-standard methods, in response to a dietary intervention, which will aid the design of future whole dietary patterns, food and food bioactive interventions studies that target insulin sensitivity and secretion.
2. Materials and Methods
2.1. Search Strategy and Selection Criteria
2.1.1. Inclusion Criteria
Eligible studies were English-language reports of all dietary intervention trials and their influence on insulin sensitivity and secretion markers as evaluated by both a gold standard method and a surrogate marker.
For insulin sensitivity, the gold standard methods were the EHC (M-value unit) and IVGTT (Si unit). For insulin secretion, AIRg was used as the gold standard. The surrogate markers of insulin sensitivity were either HOMA-IR, fasting insulin, or the area under the curve oral glucose tolerance test (AUC OGTT). For insulin secretion, the disposition index (DI) was used as a surrogate marker.
Studies were limited to those that included only nondiabetic populations with no restriction on age. However, participants could have treated hypercholesterolemia, treated hypertension, had prediabetes, or been obese if they were considered otherwise healthy. The search strategy used can be seen on Table 1.
Table 1.
Search strings.
2.1.2. Information Sources
Searches were performed between the 18 of February 2016 and the 21 of June 2017. We systematically searched for title articles in PubMed, Scopus, and Cochrane databases.
2.1.3. Selection Process
The titles and abstracts of studies identified by the search were screened by two reviewers and ineligible studies were excluded. The abstracts of all potentially relevant studies were obtained and assessed independently for eligibility by two independent reviewers who completed an abstract review form. Any disagreement was resolved by discussion.
2.2. Data Items
2.2.1. Types of Studies
Randomised controlled trials, including crossover and parallel arm studies, and longitudinal randomised studies were included for this review. PRISMA guidelines were used to conduct the study and report this project.
2.2.2. Types of Intervention
“Dietary interventions” refer to all interventions with either change in total diet or one or more specific foods or dietary components. Exotic plants were not considered in this review as they can be seen as pharmacological rather than nutritional interventions. Studies measuring meal effects such as challenge tests were also excluded. The dietary intervention of the studies had to be at least 1 week in duration and included studies of a combined dietary and physical activity intervention. All included interventions had a control group.
2.3. Data Extraction and Quality Assessment
Relevant data were extracted by the lead author and subsequently reviewed by one of the co-authors for accuracy. The information extracted from the surrogate and reference markers of insulin sensitivity and secretion were measurement units, number of intervention arms, number of control arms, baseline measurements, end of study measurements, and change mean.
The quality of the studies was evaluated using a risk of bias assessment (Cochrane) with criteria that included the following: random sequence generation, allocation concealment, blinding of participants and personnel, incomplete outcome data, selective reporting, and other sources of bias.
2.4. Data Synthesis and Analysis
Correlation is the most popular method used to compare the efficacy of surrogate markers with gold standards as it can give information regarding the power of a relationship between two variables [27]. However, either Spearman or Pearson correlations rely on the assumption of a bivariate normal distribution.
Thus, Lin’s concordance correlation coefficient (LCCC) has been proposed as an analysis method. Lin measures bivariate pairs of observations relative to a “gold standard” test or measurement. Lin calculates the degree to which two sets of data descend along a line of x = y when plotted as opposed to another [28].
LCCC is analogous to Bland and Altman’s concept of the line of the agreement [29]. This concept is especially useful when two variables are measured on different scales. Consequently, Bland and Altman proposed that the extent of agreement could be investigated by plotting the differences between the pairs of measurements on the vertical axis, against the mean of each pair on the horizontal axis.
To compare studies with different units of measurement, the responses were expressed as % change from the baseline/starting value. The percentage change (PC) in response to each treatment, either using the surrogate or gold standard method, was calculated as (Value–Value1)/Value1) × 100) for both the intervention and the control group. This equation quantified the change from one value to another and expressed the change as an increase or decrease.
Once the proportional changes were obtained, we compared EHC (M-value), IVGTT (Si), and AIRg with each surrogate marker using Lin’s concordance correlation coefficient, with 95% confidence intervals. The correlations were conducted on the mean values from each trial rather than individual participant data. Data were analysed using Stata 17 software (StataCorp. 2021. Stata Statistical Software: Release 17. College Station, TX, USA: StataCorp LLC).
For interpreting Lin’s concordance correlation coefficient results, McBride’s descriptive scale for values was used [30]. An agreement was defined as a concordance correlation coefficient of >0.99.
Data were assessed for normality using the Shapiro–Wilk test, which revealed non-normal distributions. Robvis tool was used to present the results of the risk of bias assessment [31] (Supplementary Materials).
3. Results
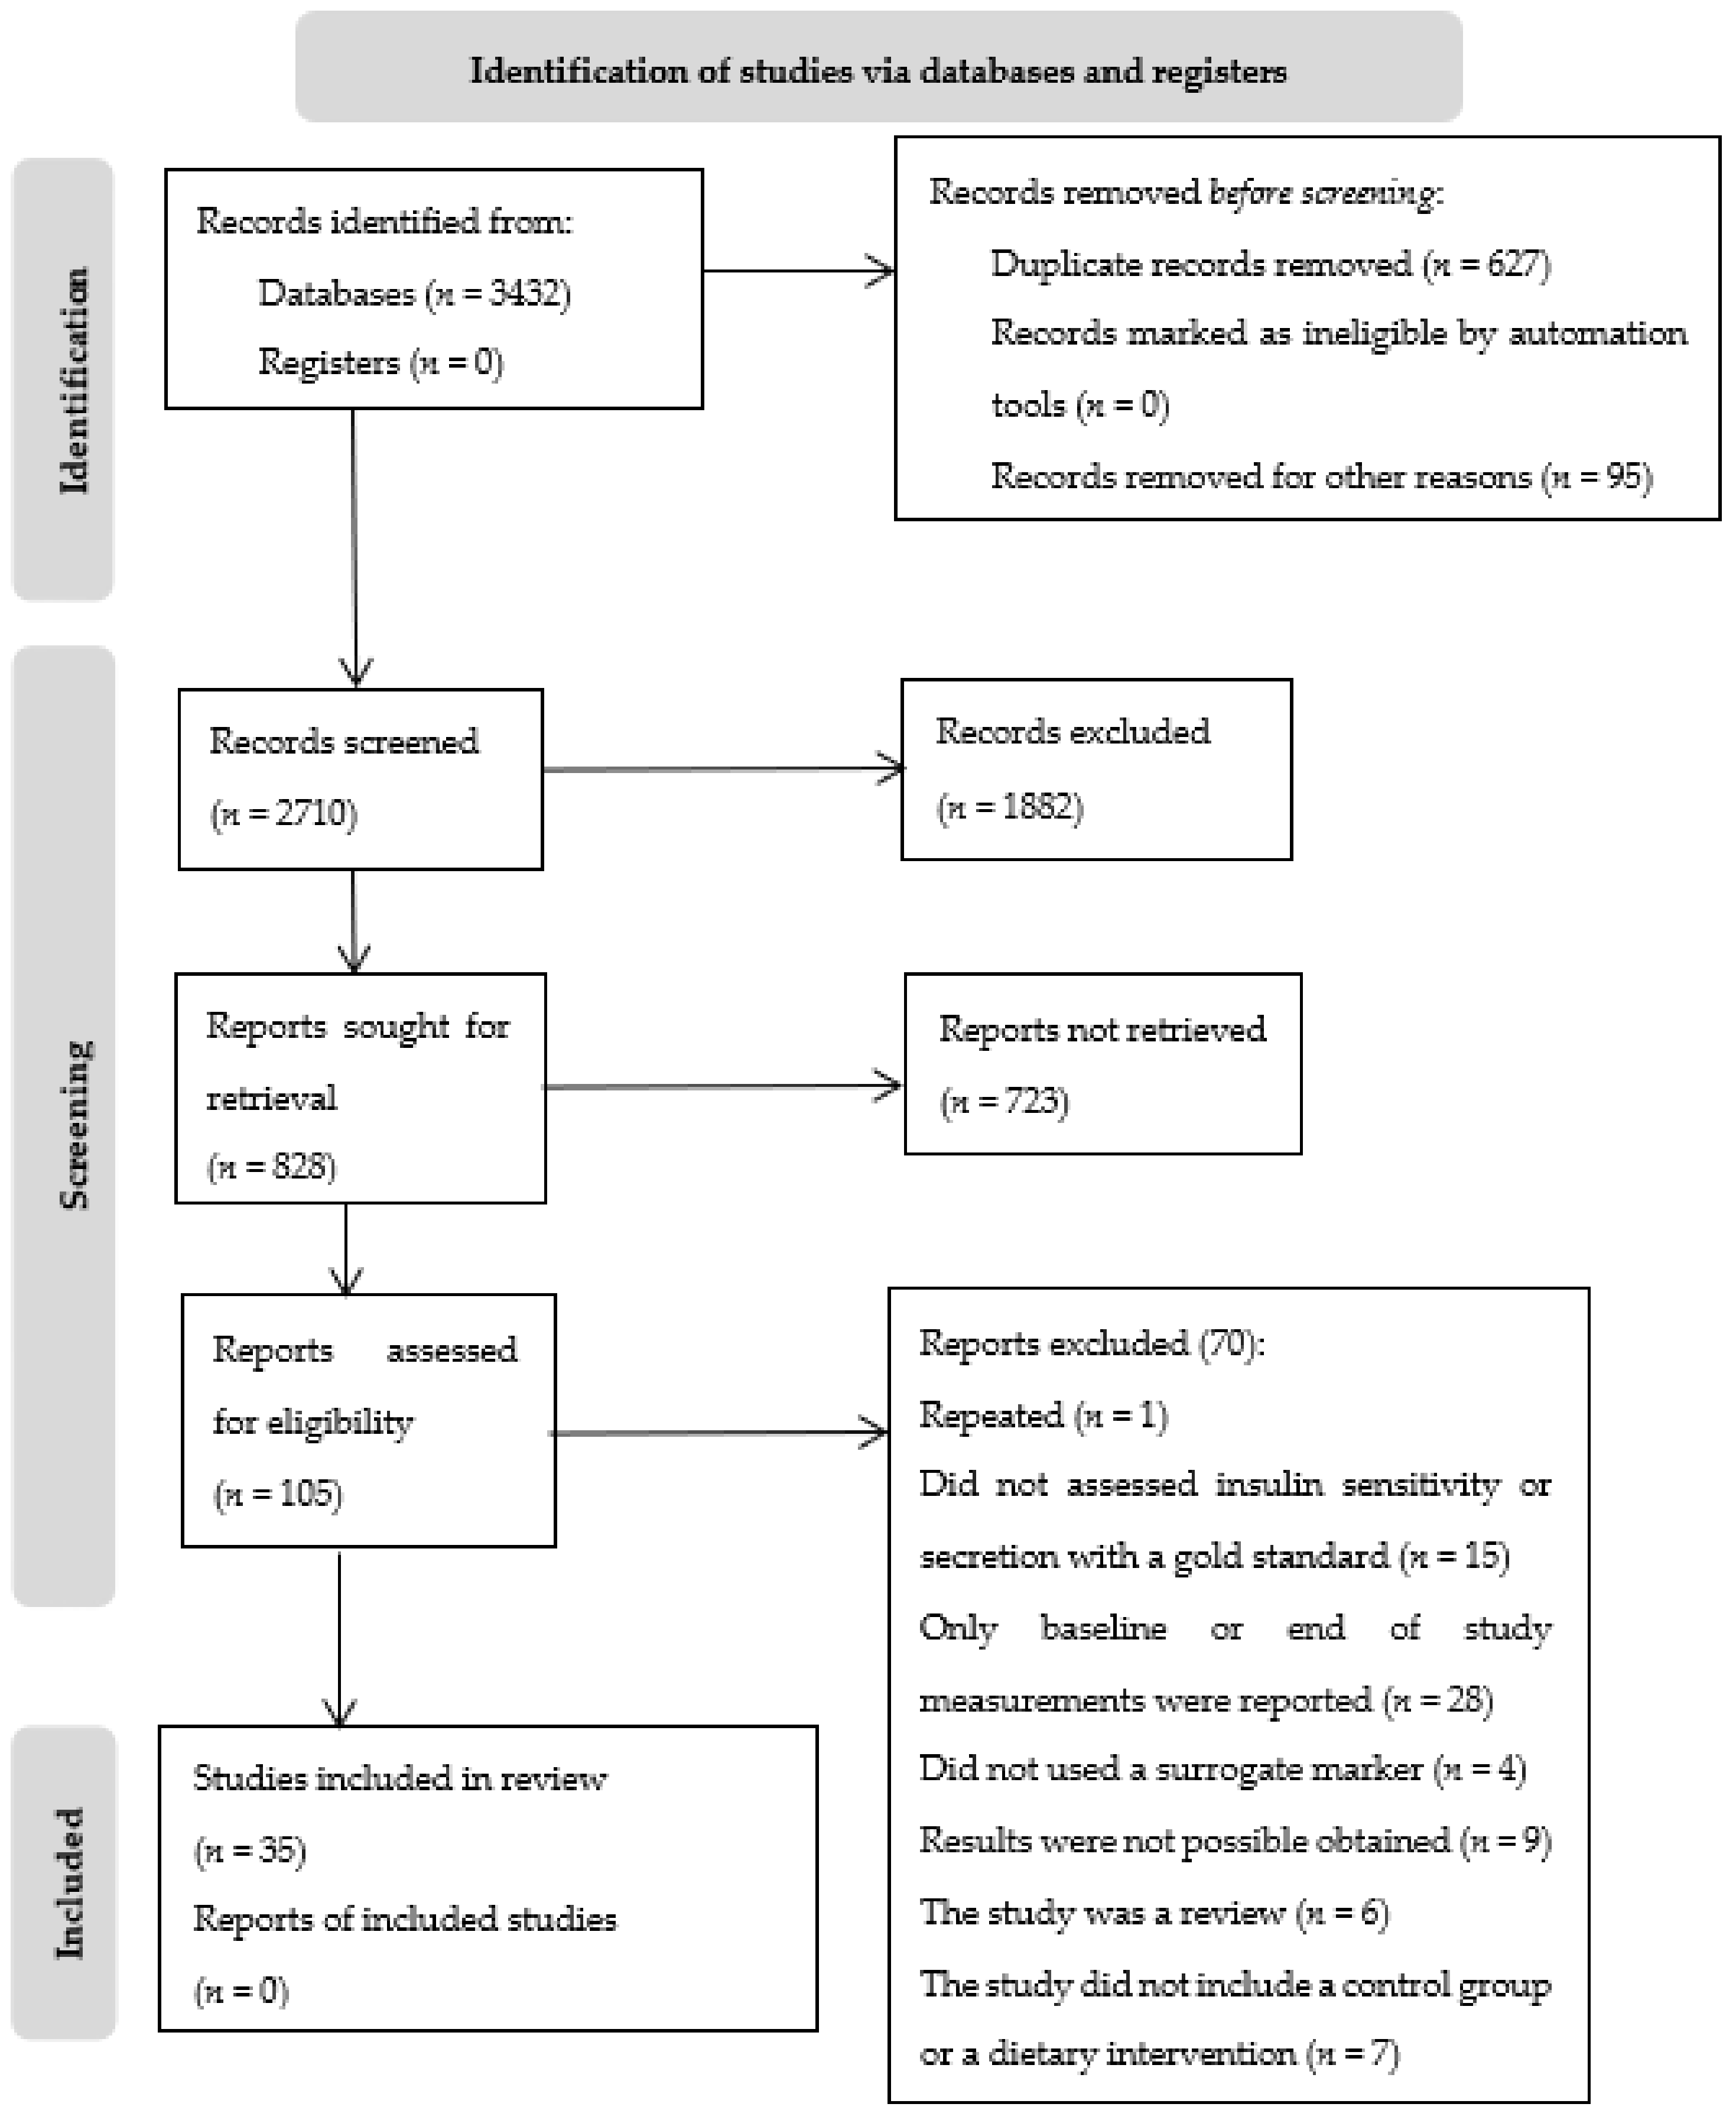
A total of thirty-five articles met the inclusion criteria. A PRISMA flow chart describing the selection process is represented in Figure 1.
Figure 1.
PRISMA flow diagram of study selection for systematic review.
From the represented articles, a total of 2047 individuals (aged between 15 to 75 years of age) were involved in the primary analyses. Each article provided two study arms: control and intervention. Only the intervention arm data was used.
Among the thirty-five articles, the majority were conducted in Europe (twenty-one), four from Australia and New Zealand, and ten from North America. The studied population was mainly adults (including young, middle-aged, and older ones). Two articles were performed on Latino and minority adolescents.
The basic details of each article, as well as the characteristics of the study participants included in this systematic review, are presented in Table 2 and Table 3.
Insulin sensitivity levels were significantly modified after the nutritional intervention in three studies measured using the EHC and the surrogate marker of fasting insulin [32,33,34] as well as AUC OGTT and fasting insulin [35], Table S1, Supplementary Materials (p ≤ 0.05).
Using IVGTT and fasting insulin, five studies demonstrated a change in insulin sensitivity as compared with baseline [36,37,38,39,40], Table S2 Supplementary Materials (p ≤ 0.05). No change in insulin secretion was detected after the nutritional treatment in AIRg and DI, Table S3 Supplementary Materials (p > 0.05).
The detailed results of the risk of bias assessment using the Robvis tool are presented in the Supplementary Materials (Figures S1 and S2). Nonetheless, twenty-four out of the thirty-five studies showed no information regarding allocation concealment and random sequence generation.
Analysis of the results of proportional change with LCCC, using the difference between baseline data and after the nutritional intervention of all studies, established a lack of agreement between the gold standards and the surrogate markers (<0.99) Table 4.
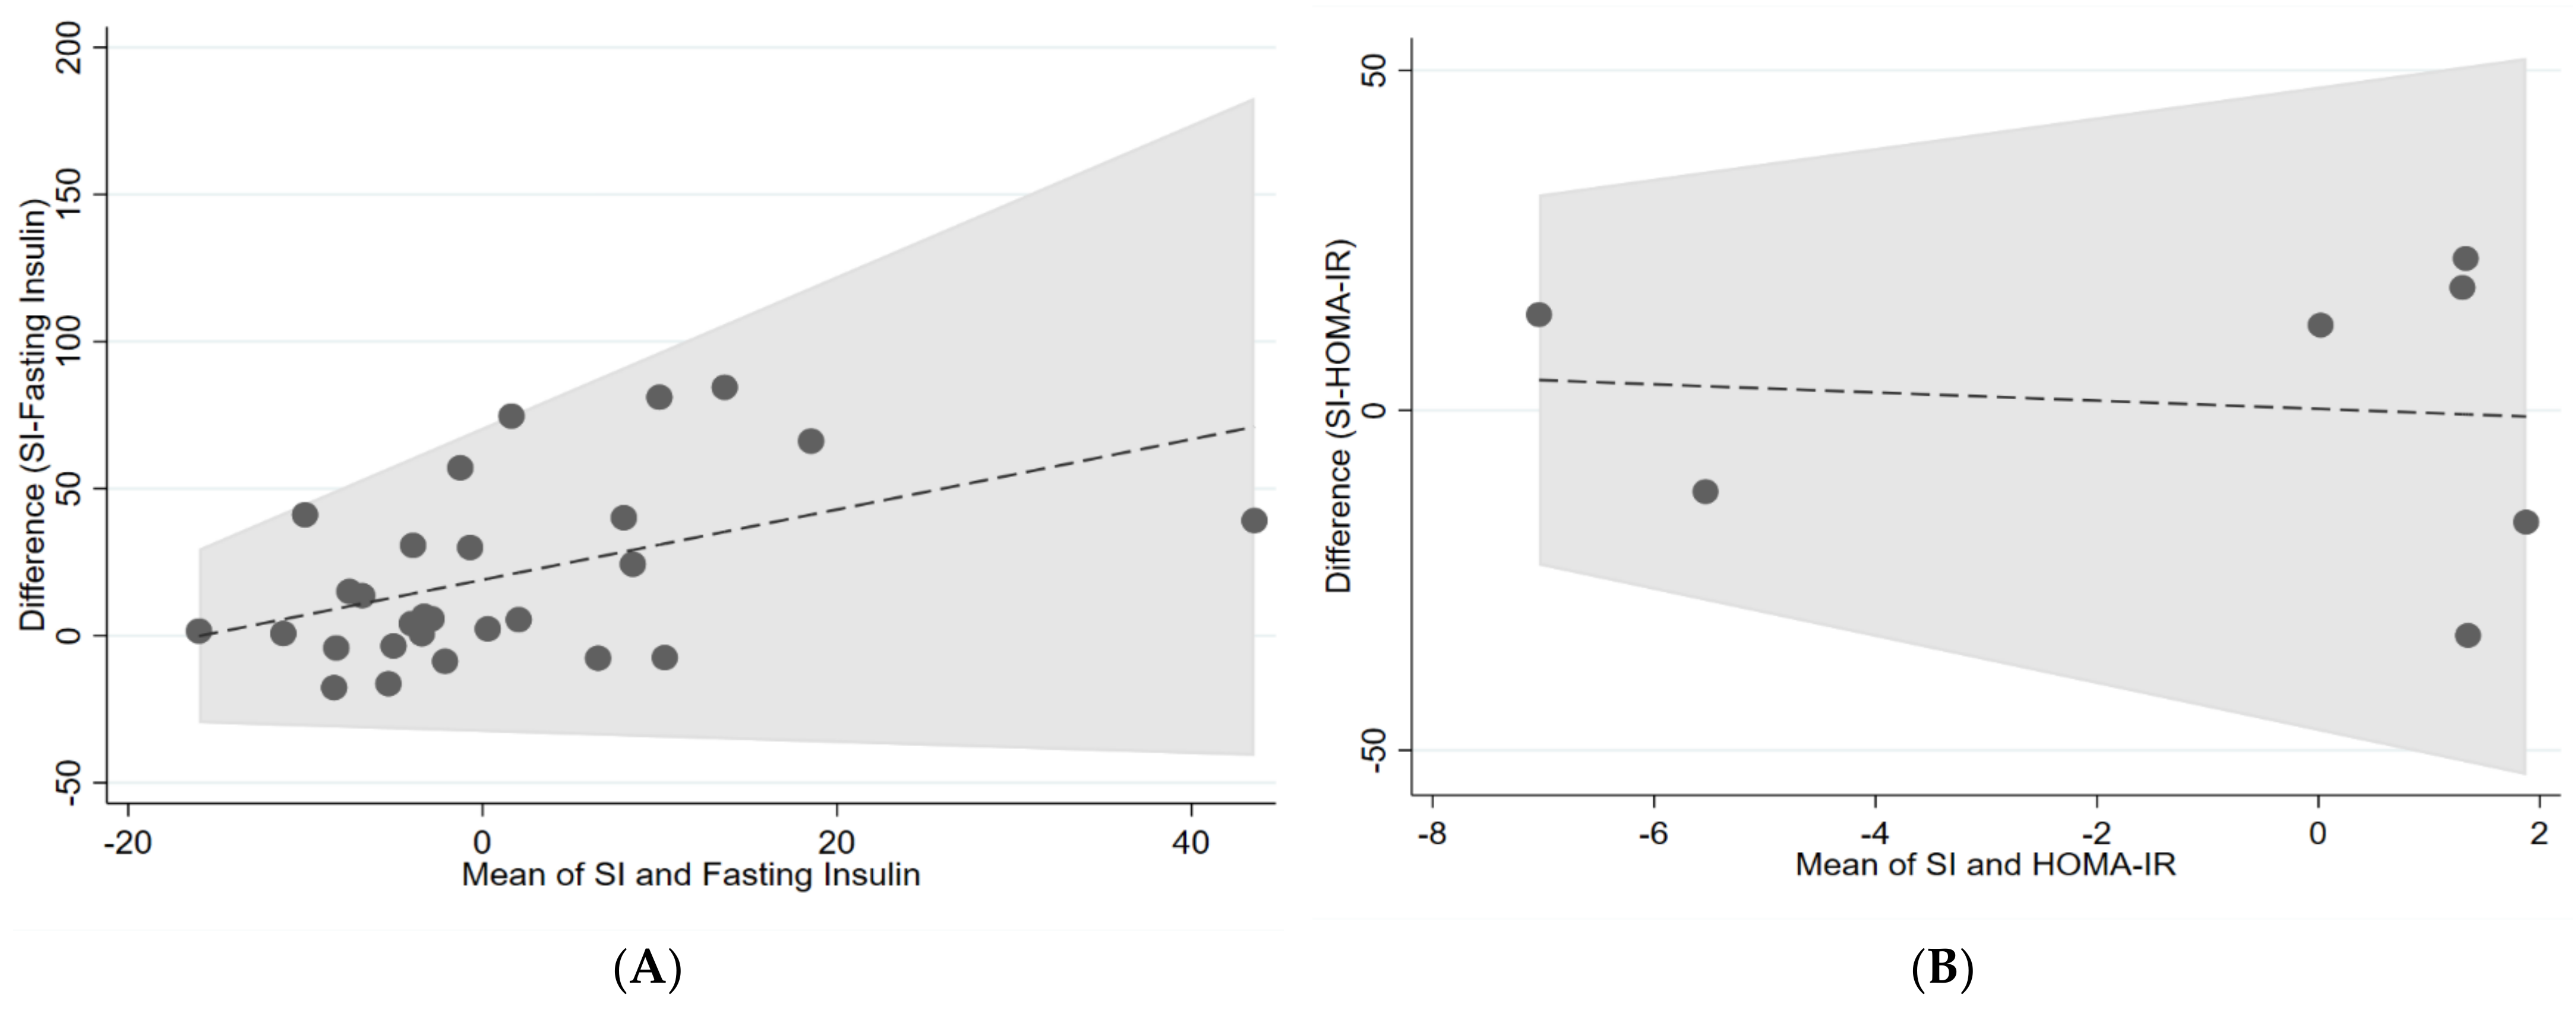
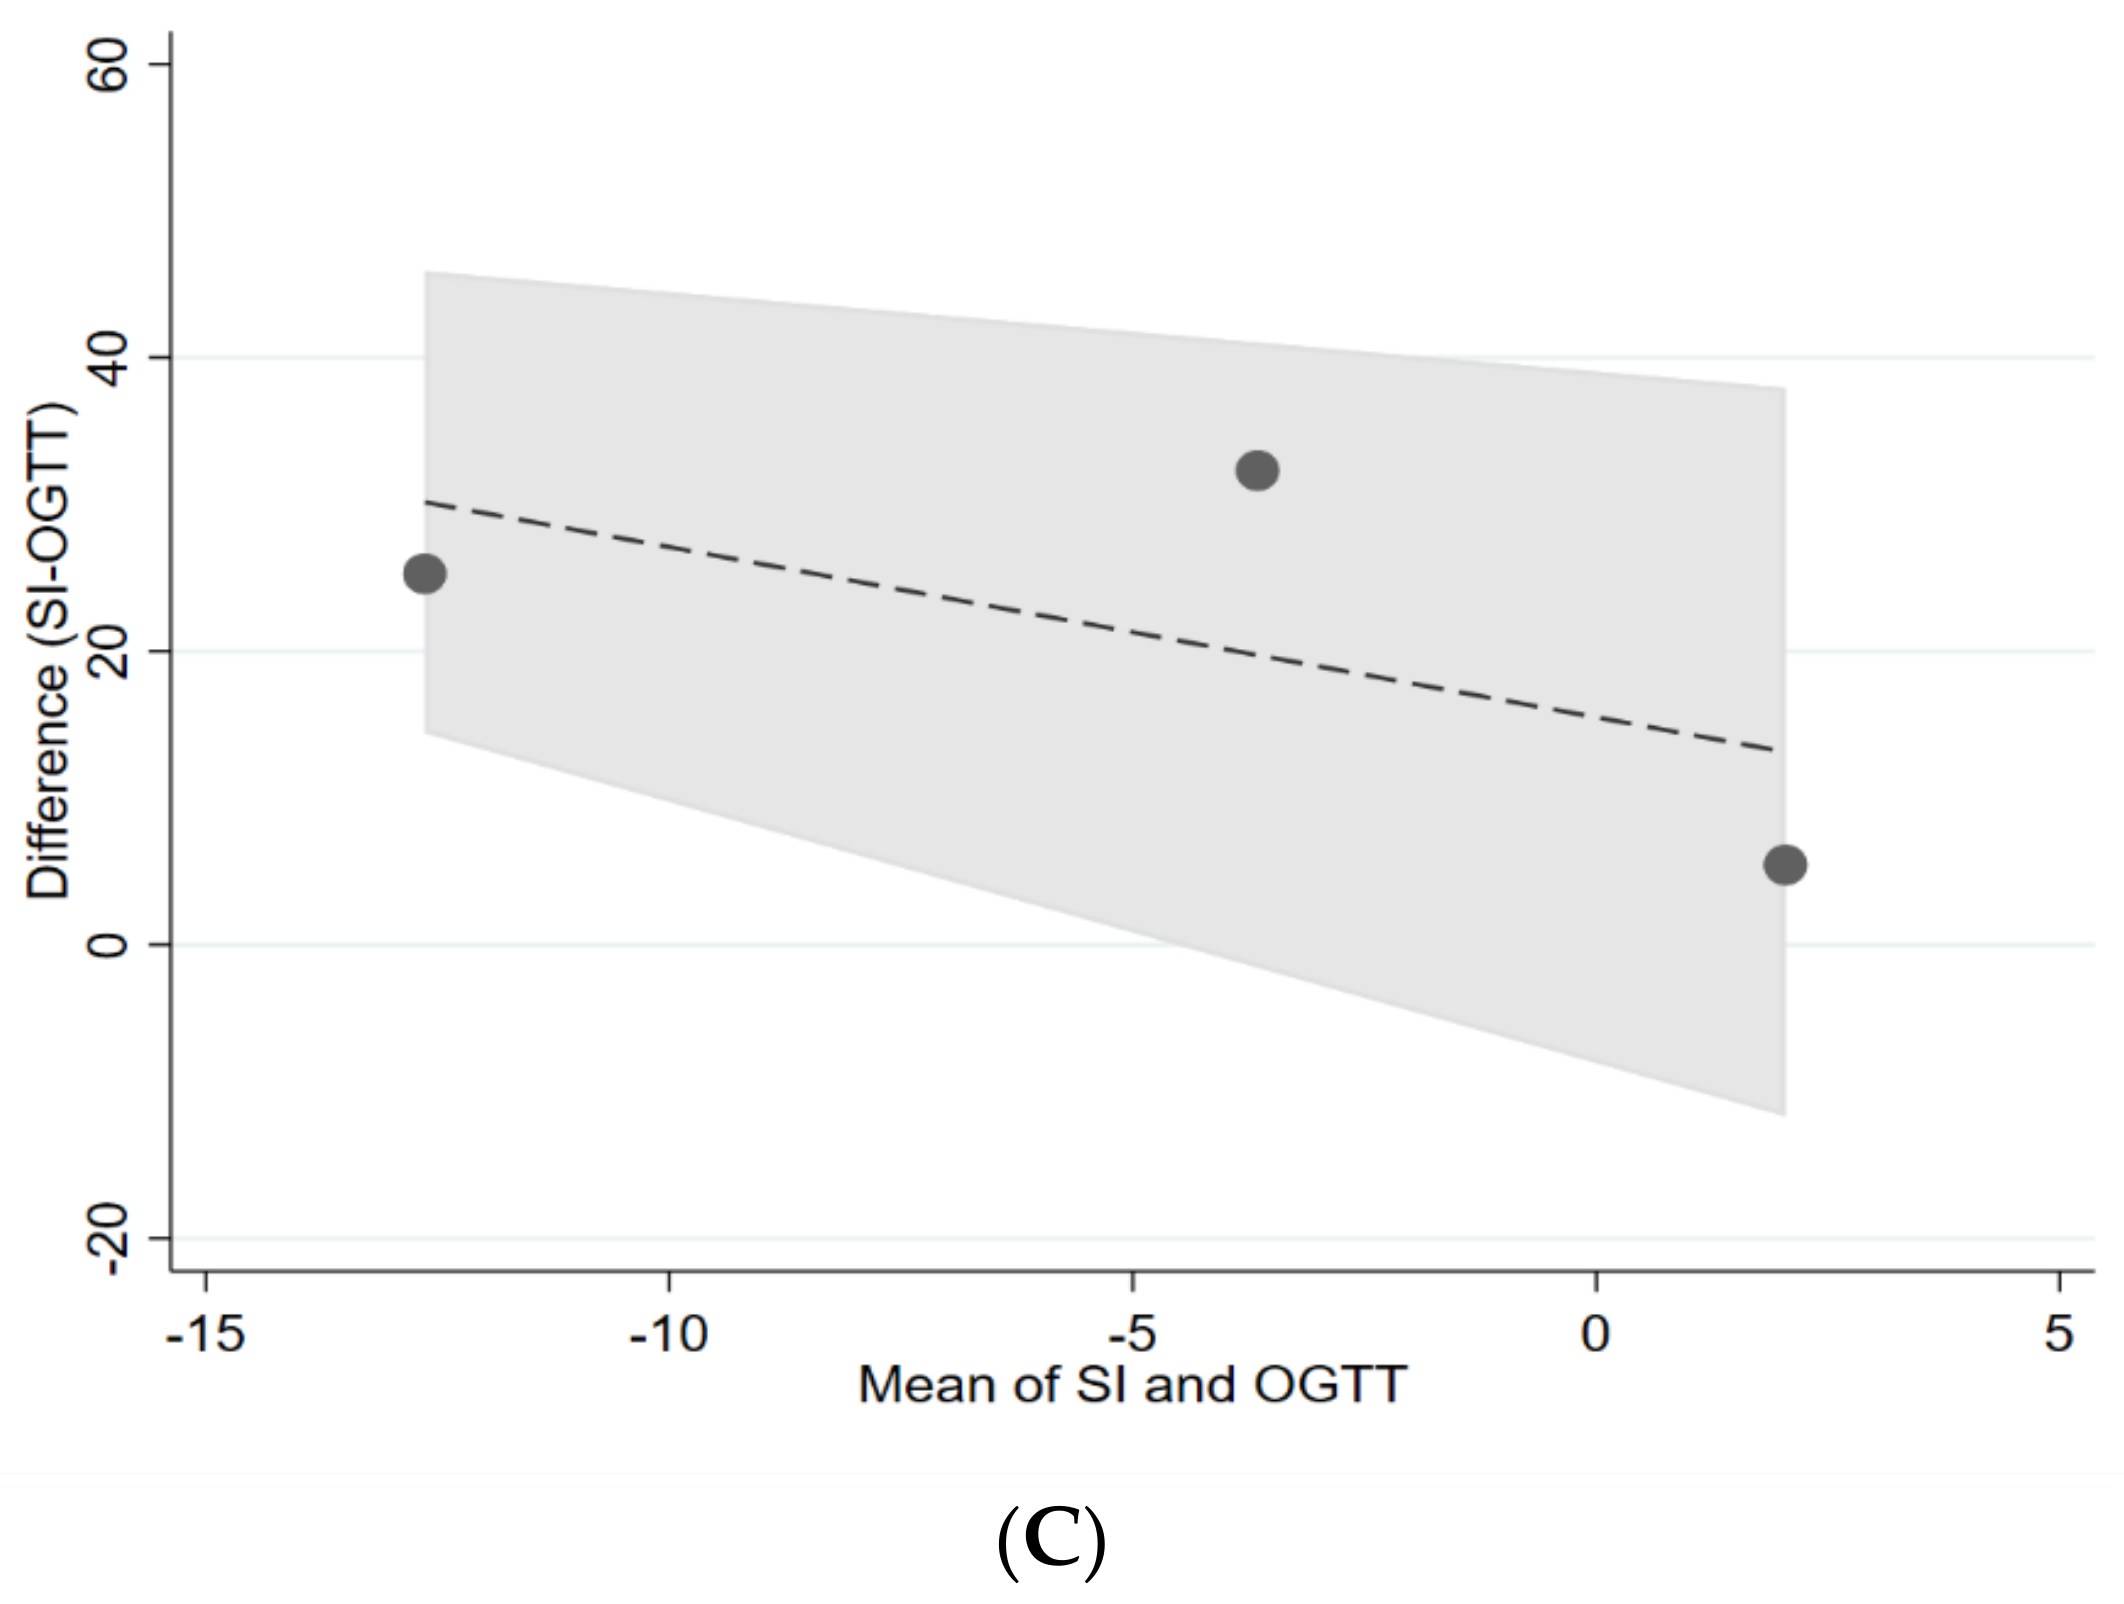
Figure 2, Figure 3 and Figure 4 show the visualisation of Bland and Altman’s plot relationship between paired (gold standards and surrogate markers) differences and their average. We found no agreement between the markers.
Table 2.
Euglycaemic hyperinsulinaemic clamp trials description.
Table 3.
IVGTT and AIRg trials description.
Table 4.
Lin’s concordance correlation coefficient (LCCC) between gold standards and surrogate markers using proportional change data.
Figure 2.
Bland–Altman plots between of AIRg vs. DI (insulin secretion). The central dashed line represents the mean difference between measures represented as log values. The area in grey represents the 95% confidence intervals. AIRg = acute insulin response to glucose, DI = disposition index.
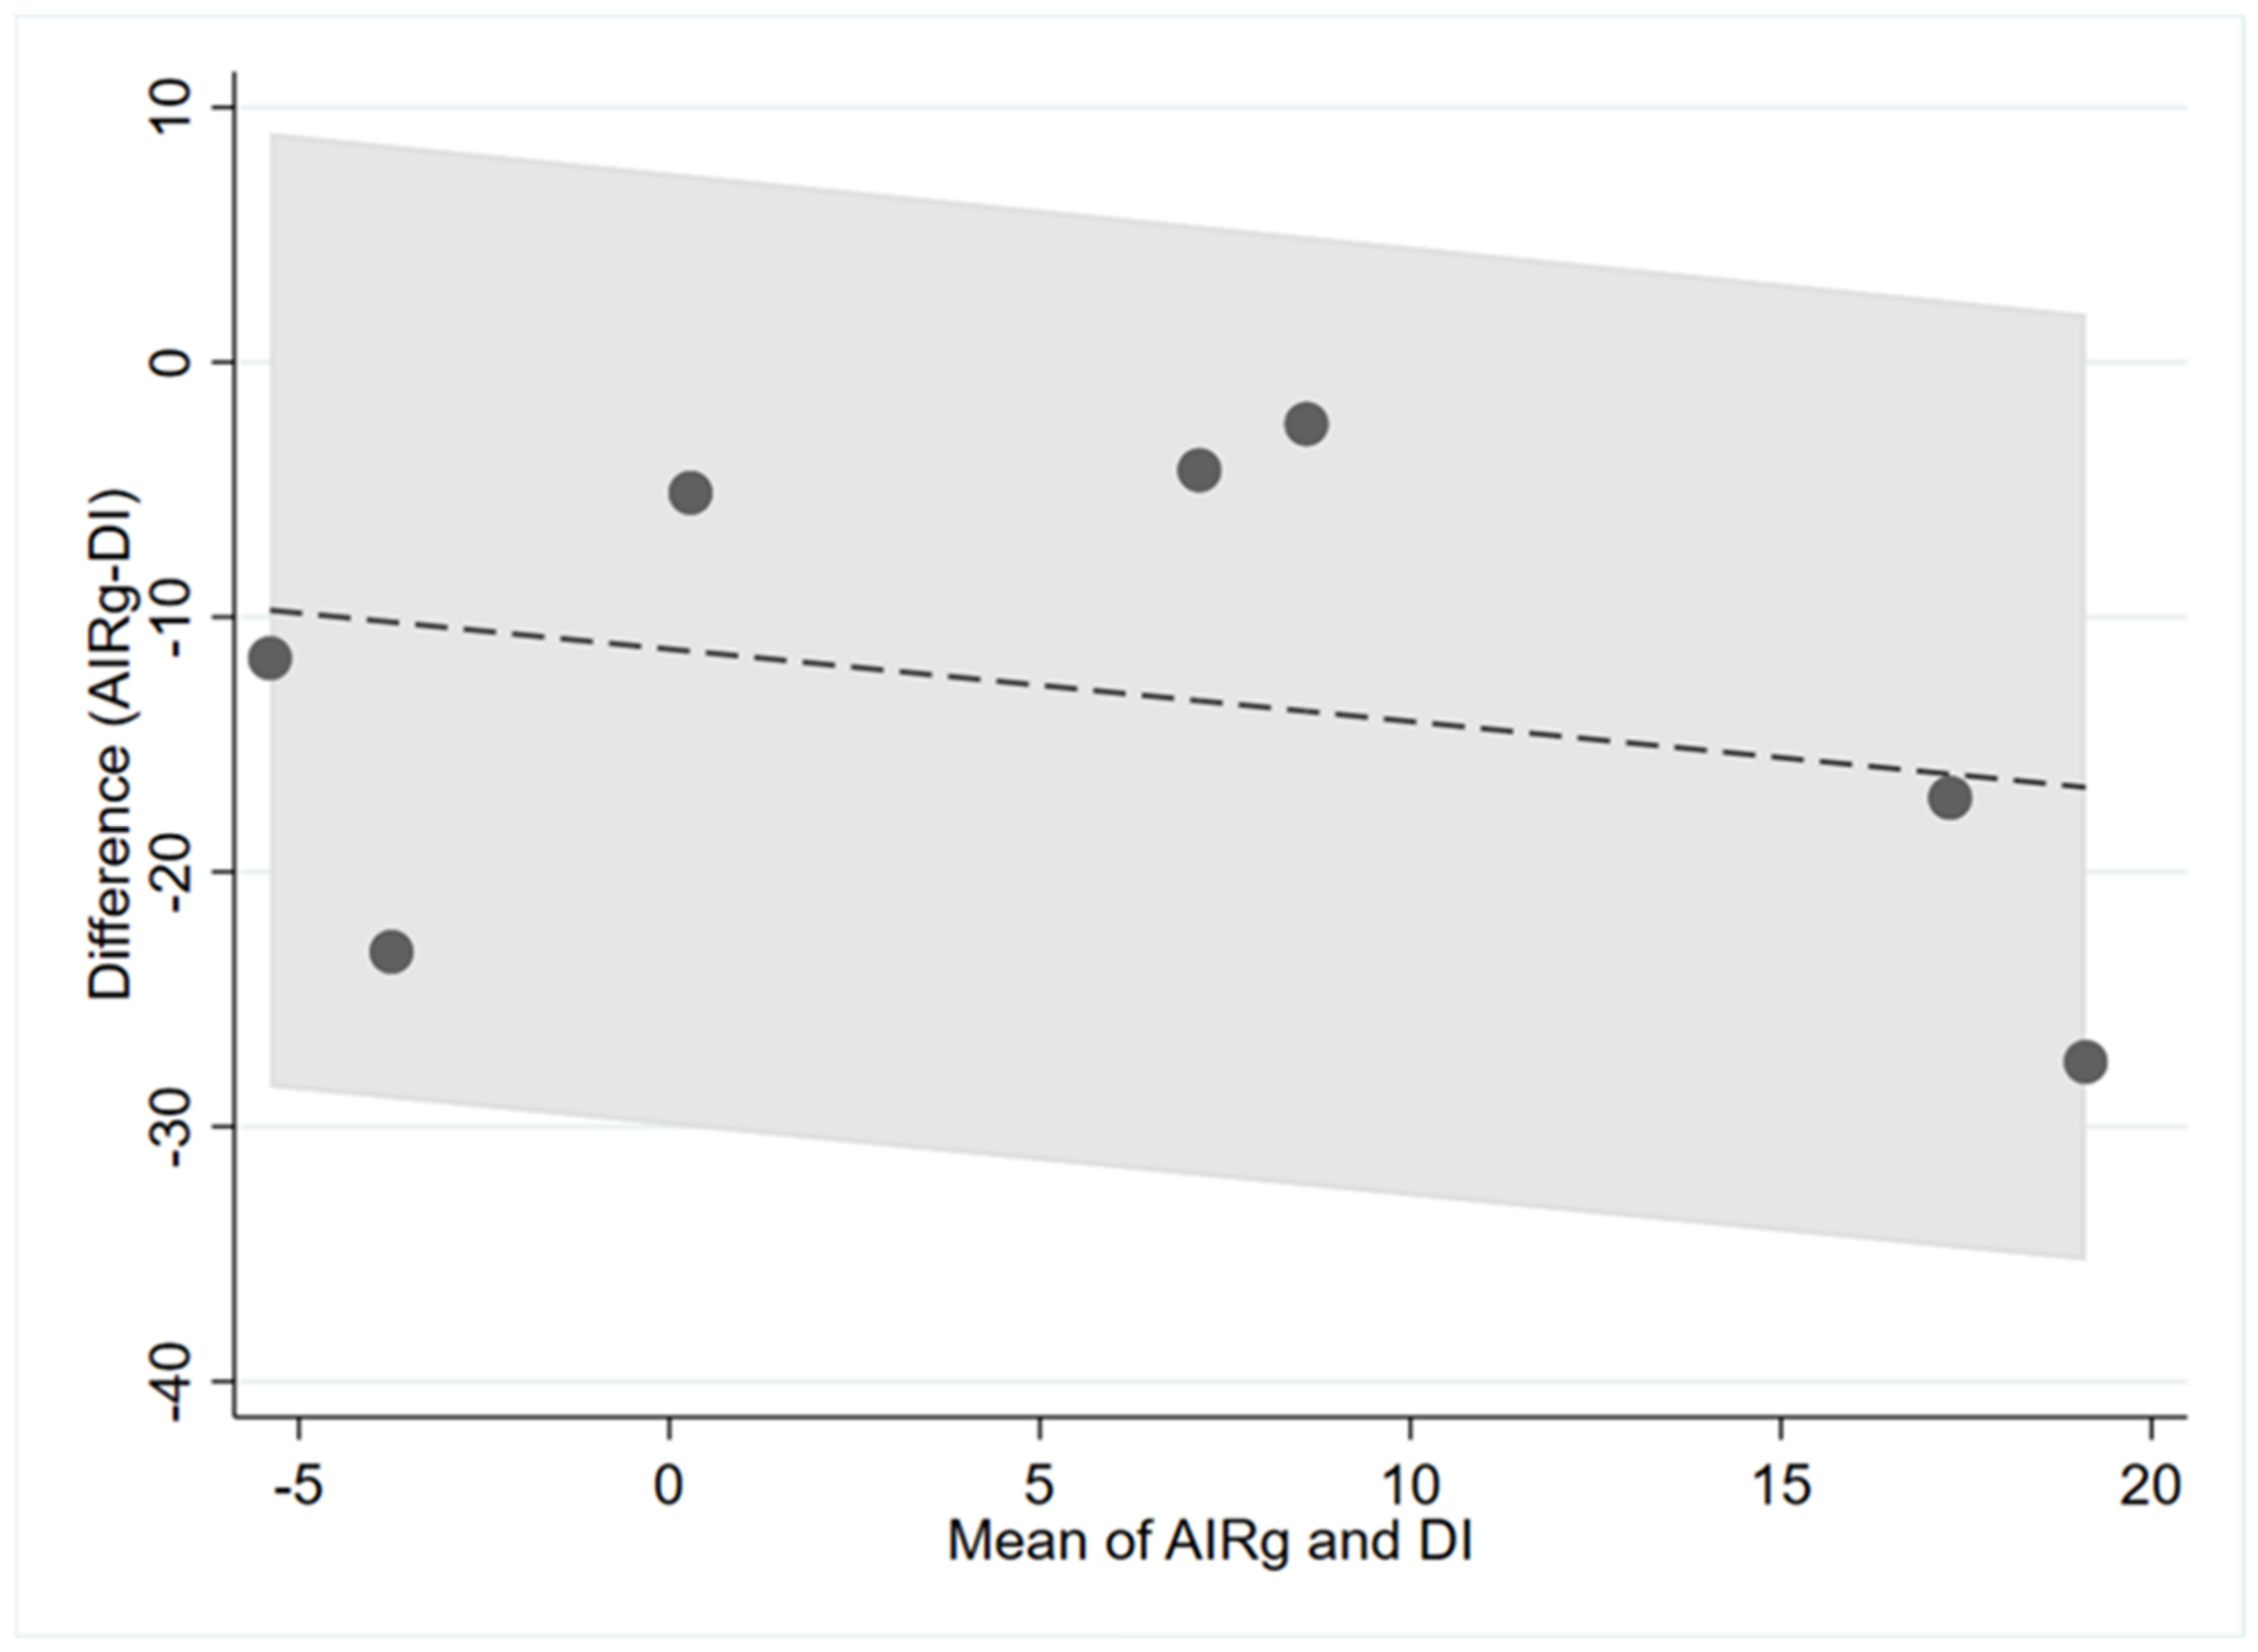
Figure 3.
Bland–Altman plots of (A) clamp vs. fasting insulin, (B) clamp vs. HOMA-IR, (C) clamp vs. OGTT. The central dashed line represents the mean difference between measures represented as log values. The area in grey represents the 95% confidence intervals. HOMA-IR = homeostatic model assessment for insulin resistance, OGTT = oral glucose tolerance test.
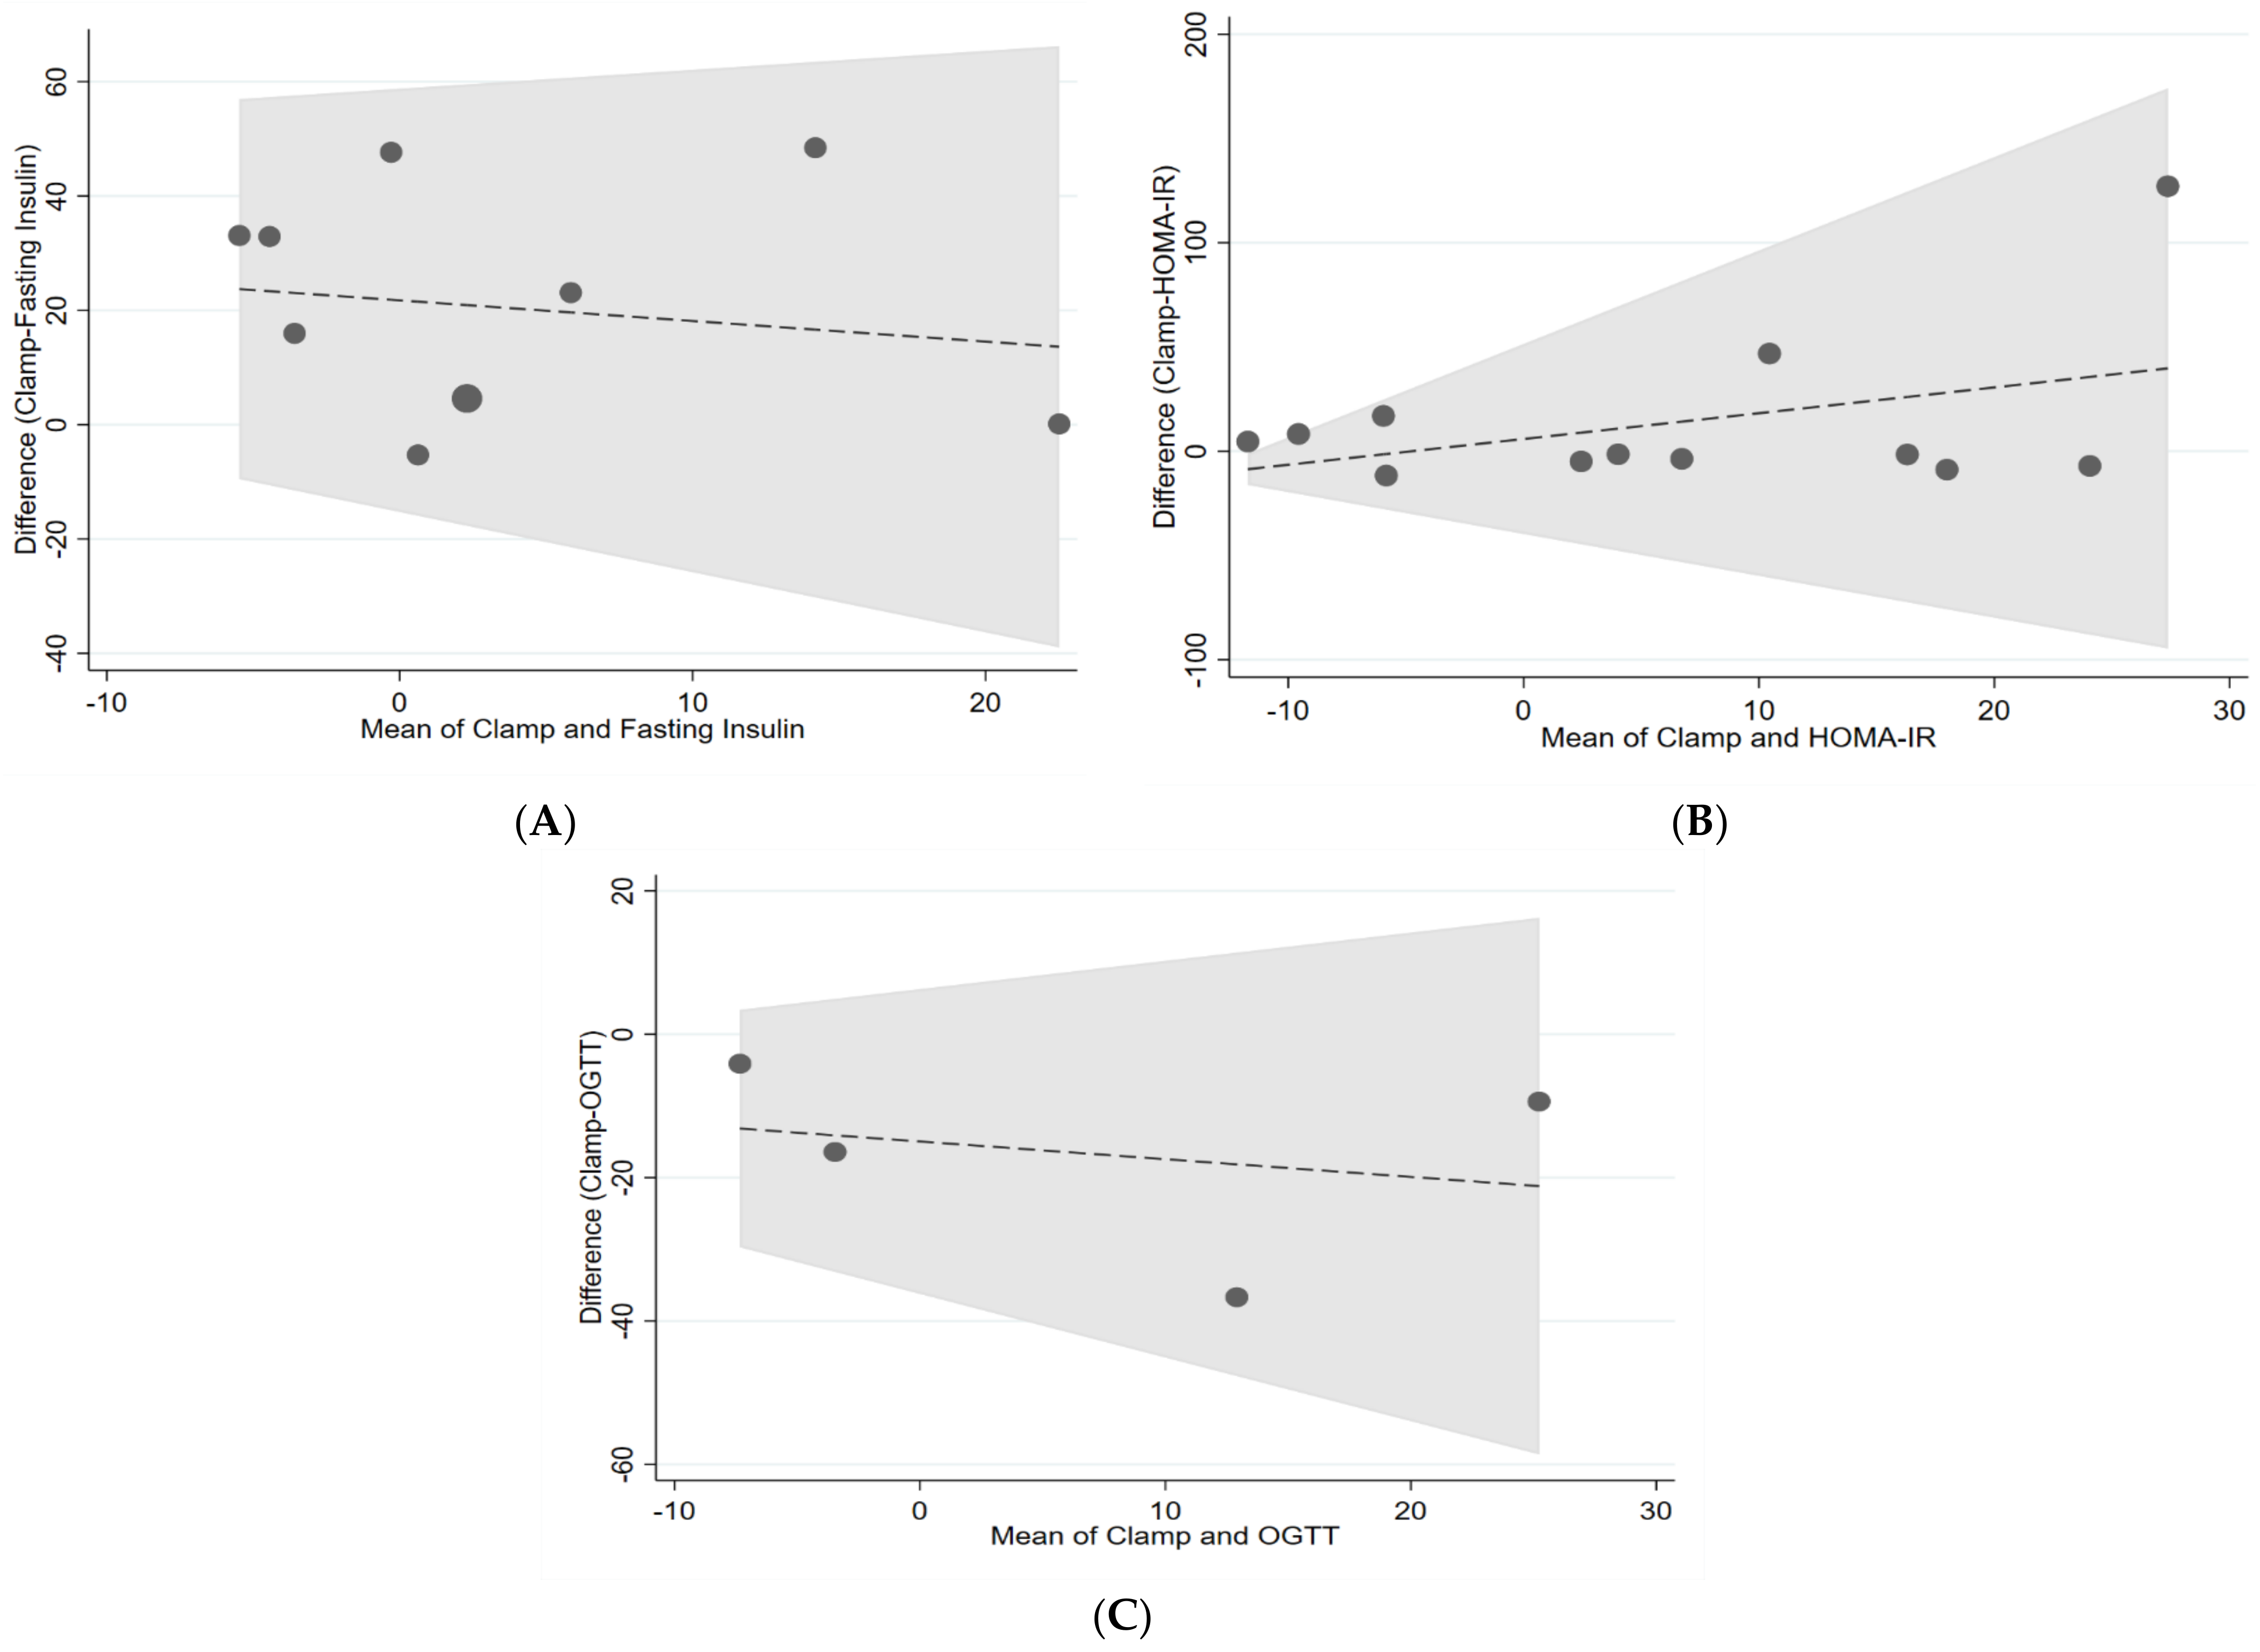
Figure 4.
Bland–Altman plots of (A) SI vs. fasting insulin, (B) SI vs. HOMA-IR, (C) SI vs. OGTT. The central dashed line represents the mean difference between measures represented as log values. The area in grey represents the 95% confidence intervals. HOMA-IR = homeostatic model assessment for insulin resistance, OGTT = oral glucose tolerance test.
4. Discussion
The worldwide rapidly increasing prevalence and burden of type 2 diabetes amplifies the need and urgency for testing and innovative strategies to prevent the development of the disease.
Earlier identification and acceptance of efficacy markers for diabetes risk (or the recognition of gaps in evidence needed for their acceptance) will lead to an earlier and wider endorsement of their use and can speed the testing and development of potentially promising strategies to counteract the disease.
Dietary interventions are modifiable factors that may be more effective than pharmacological agents in preventing the onset of diabetes [67]. Furthermore, the dietary composition may influence insulin sensitivity and secretion [68,69,70].
In this systematic literature review, we identified studies using surrogate markers of insulin sensitivity and secretion and its correlation with gold standards in a population without diabetes using dietary interventions. The use of surrogate markers for the assessment of insulin sensitivity and secretion has been proposed to evaluate large population-based epidemiological investigations to save costs and to obtain data in quick time.
Nonetheless, even though the use of surrogate markers to assess insulin sensitivity and secretion have the potential to decrease costs and minimise participant burden and risk [17], their utility appears to be limited, at least in this review.
One problem that some surrogate markers have, more specifically fasting insulin, HOMA-IR, and AUC OGTT, is that they can be unreliable in certain populations such as the elderly and those with uncontrolled diabetes [20,71]. In this review, the study made by Hayes (2006) used elderly subjects.
Another fasting insulin limitation is that it lacks standardisation of the insulin essay procedure [17]. AUC OGTT provides information regarding glucose tolerance but not insulin resistance [17]. Whereas HOMA-IR and disposition index, evaluate hepatic insulin resistance more than peripheral insulin sensitivity which was our target [20,72].
Our study differs from previously published data, which found a correlation between QUICKI or the OGGT-based indices (Stumvoll, OGIS, Matsuda, and Gutt) with the hyperinsulinaemic-euglycaemic clamp to assess insulin sensitivity [12]. However, the investigators of that study analysed their data using a correlation coefficient method. This method is considered an incorrect measure of reproducibility or repeatability as it measures the correlation between variables but not the agreement between them [73].
The evaluation of the trials involved in our research used different units for the surrogate markers. Thus, the different evaluation parameters made it challenging to integrate the outcomes. However, we decided that the best way to compare the effectiveness of the surrogate markers with the gold standards was with a proportional change formula, analysed using Lin’s concordance correlation coefficient, which is also an index of reliability.
We expected to see an agreement between the surrogate measures and the gold standards with the Bland–Altman plots; however, this was not the case.
Advantages and Disadvantages
One of the main strengths of this study was that the population analysed was diverse, as it included all sexes and ages and some of the participants presented a condition that can lead to type 2 diabetes or any other cardiovascular disease. This study was a general comparison instead of focusing on a specific population.
On the contrary, some might consider this a disadvantage because the analysed participants were not a heterogenic population. Two studies conducted on adolescents were included in this review [39,66].
Another strength was the meticulous selection strategy that identified all the accessible trials with our requested characteristics. So far, no other systematic review or meta-analysis has examined the effect of dietary treatment on insulin sensitivity and surrogate markers.
All the studies included in this review are high-quality trials according to the risk assessment. Nonetheless, some studies showed no information regarding allocation concealment and random sequence generation. This, however, did not influence our results.
5. Conclusions
There is insufficient evidence to evaluate the effects of nutritional intervention studies on insulin sensitivity or secretion with surrogate markers when compared to a euglycemic-hyperinsulinaemic clamp, IVGTT or AIRg.
Future research is needed to investigate if surrogate measures of insulin sensitivity and secretion can be repeatable and reproducible in the same way as the gold standards using nutritional intervention studies.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/nu14102036/s1, Figure S1: Risk of bias assessment, Euglycaemic hyperinsulinaemic clamp; Figure S2: Risk of Bias Assessment, IVGTT, and AIRg. Table S1: Results of the Euglycaemic-hyperinsulinaemic clamp trials and the surrogate markers, Table S2: Results of the Intravenous Glucose Tolerance Test trials and the surrogate markers, Table S3: Results of the AIRg trials and DI (surrogate marker).
Author Contributions
Conceptualisation., I.M. and K.F.; data curation, L.V.R. and I.M.; writing-background, L.V.R. and I.M.; writing—methods and results, L.V.R., M.A. and K.F.; analysis and interpretation of results, L.V.R. and I.M.; writing—original draft preparation, I.M., M.A. and K.F.; writing-discussion, L.V.R.; writing—abstract/conclusion, L.V.R.; review and editing, I.M., K.F. and M.A. All authors have read and agreed to the published version of the manuscript.
Funding
This work was conducted by an expert group of the European branch of the International Life Sciences Institute (ILSI Europe). The research question addressed in this publication and potential contributing experts in the field were identified by the Obesity and Diabetes Task Force. The composition of the task force is listed on the ILSI Europe website at https://ilsi.eu/task-forces/nutrition/obesity-and-diabetes/ (accessed on 2 April 2022). Registration number: CRD42017037411. According to ILSI Europe policies, the EG is composed of at least 50% of external non-industry members. Once the expert group was formed, the research project was handed over to them to independently refine the research question. Consequently, the expert group carried out the work, that is, collecting/analysing data/information and writing the scientific paper independently of other activities of the task force. The research report is the result of a scientific evaluation in line with ILSI Europe’s framework to provide a pre-competitive setting for public-private partnerships. ILSI Europe (Adam Coventry) facilitated scientific meetings and coordinated the overall project management and administrative tasks relating to the completion of this work. For further information about ILSI Europe, please email info@ilsieurope.be or call +3227710014. The opinions expressed herein, and the conclusions of this publication are those of the authors and do not necessarily represent the views of ILSI Europe nor those of its member companies. Experts are not paid for the time spent on this work; however, the non-industry members within the expert group were offered support for travel and accommodation costs from the Obesity and Diabetes Task Force to attend meetings to discuss the manuscript. The authors declare that they have no known competing financial interests or personal relationships that could have appeared to influence the work reported in this paper.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The datasets generated and/or analysed during the current study have been made available online.
Acknowledgments
We would like to thank Andrea Venn (University of Nottingham) for providing insightful thoughts and observations.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Federation, I.D. IDF Diabetes Atlas, 10th ed.; International Diabetes Federation: Brussels, Belgium, 2021. [Google Scholar]
- Blindness, G.B.D. Vision Impairment C, Vision Loss Expert Group of the Global Burden of Disease S. Causes of blindness and vision impairment in 2020 and trends over 30 years, and prevalence of avoidable blindness in relation to VISION 2020: The Right to Sight: An analysis for the Global Burden of Disease Study. Lancet Glob. Health 2021, 9, e144–e160. [Google Scholar] [CrossRef] [Scilit]
- Tabák, A.G.; Jokela, M.; Akbaraly, T.N.; Brunner, E.J.; Kivimäki, M.; Witte, D.R. Trajectories of glycaemia, insulin sensitivity, and insulin secretion before diagnosis of type 2 diabetes: An analysis from the Whitehall II study. Lancet 2009, 373, 2215–2221. [Google Scholar] [CrossRef] [Scilit]
- DeFronzo, R.A.; Tobin, J.D.; Andres, R. Glucose clamp technique: A method for quantifying insulin secretion and resistance. Am. J. Physiol. 1979, 237, E214–E223. [Google Scholar] [CrossRef] [Scilit]
- Molina, J.M.; Baron, A.D.; Edelman, S.V.; Brechtel, G.; Wallace, P.; Olefsky, J.M. Use of a variable tracer infusion method to determine glucose turnover in humans. Am. J. Physiol. 1990, 258, E16–E23. [Google Scholar] [CrossRef] [Scilit]
- Bergman, R.N.; Phillips, L.S.; Cobelli, C. Physiologic evaluation of factors controlling glucose tolerance in man: Measurement of insulin sensitivity and beta-cell glucose sensitivity from the response to intravenous glucose. J. Clin. Investig. 1981, 68, 1456–1467. [Google Scholar] [CrossRef] [Scilit]
- Beard, J.C.; Bergman, R.N.; Ward, W.K.; Porte, D., Jr. The insulin sensitivity index in nondiabetic man. Correlation between clamp-derived and IVGTT-derived values. Diabetes 1986, 35, 362–369. [Google Scholar] [CrossRef] [Scilit]
- Finegood, D.T.; Hramiak, I.M.; Dupre, J. A modified protocol for estimation of insulin sensitivity with the minimal model of glucose kinetics in patients with insulin-dependent diabetes. J. Clin. Endocrinol. Metab. 1990, 70, 1538–1549. [Google Scholar] [CrossRef] [Scilit]
- Welch, S.; Gebhart, S.S.; Bergman, R.N.; Phillips, L.S. Minimal model analysis of intravenous glucose tolerance test-derived insulin sensitivity in diabetic subjects. J. Clin. Endocrinol. Metab. 1990, 71, 1508–1518. [Google Scholar] [CrossRef] [Scilit]
- Boston, R.C.; Stefanovski, D.; Moate, P.J.; Sumner, A.E.; Watanabe, R.M.; Bergman, R.N. MINMOD Millennium: A computer program to calculate glucose effectiveness and insulin sensitivity from the frequently sampled intravenous glucose tolerance test. Diabetes Technol. Ther. 2003, 5, 1003–1015. [Google Scholar] [CrossRef] [Scilit]
- Bunt, J.C.; Krakoff, J.; Ortega, E.; Knowler, W.C.; Bogardus, C. Acute insulin response is an independent predictor of type 2 diabetes mellitus in individuals with both normal fasting and 2-h plasma glucose concentrations. Diabetes Metab. Res. Rev. 2007, 23, 304–310. [Google Scholar] [CrossRef] [Scilit]
- Otten, J.; Ahrén, B.; Olsson, T. Surrogate measures of insulin sensitivity vs. the hyperinsulinaemic-euglycaemic clamp: A meta-analysis. Diabetologia 2014, 57, 1781–1788. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dalla Man, C.; Campioni, M.; Polonsky, K.S.; Basu, R.; Rizza, R.A.; Toffolo, G.; Cobelli, C. Two-hour seven-sample oral glucose tolerance test and meal protocol: Minimal model assessment of beta-cell responsivity and insulin sensitivity in nondiabetic individuals. Diabetes 2005, 54, 3265–3273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matthews, D.R.; Hosker, J.P.; Rudenski, A.S.; Naylor, B.A.; Treacher, D.F.; Turner, R.C. Homeostasis model assessment: Insulin resistance and beta-cell function from fasting plasma glucose and insulin concentrations in man. Diabetologia 1985, 28, 412–419. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Katz, A.; Nambi, S.S.; Mather, K.; Baron, A.D.; Follmann, D.A.; Sullivan, G.; Quon, M.J. Quantitative insulin sensitivity check index: A simple, accurate method for assessing insulin sensitivity in humans. J. Clin. Endocrinol. Metab. 2000, 85, 2402–2410. [Google Scholar] [CrossRef] [PubMed]
- Thomas, G.N.; Critchley, J.A.; Tomlinson, B.; Anderson, P.J.; Lee, Z.S.; Chan, J.C. Obesity, independent of insulin resistance, is a major determinant of blood pressure in normoglycemic Hong Kong Chinese. Metabolism 2000, 49, 1523–1528. [Google Scholar] [CrossRef] [Scilit]
- Singh, B.; Saxena, A. Surrogate markers of insulin resistance: A review. World J. Diabetes 2010, 1, 36–47. [Google Scholar] [CrossRef] [Scilit]
- Kahn, S.E.; Prigeon, R.L.; McCulloch, D.K.; Boyko, E.J.; Bergman, R.N.; Schwartz, M.W.; Neifing, J.L.; Ward, W.K.; Beard, J.C.; Palmer, J.P.; et al. Quantification of the relationship between insulin sensitivity and beta-cell function in human subjects. Evidence for a hyperbolic function. Diabetes 1993, 42, 1663–1672. [Google Scholar] [CrossRef] [Scilit]
- Antuna-Puente, B.; Disse, E.; Rabasa-Lhoret, R.; Laville, M.; Capeau, J.; Bastard, J.P. How can we measure insulin sensitivity/resistance? Diabetes Metab. 2011, 37, 179–188. [Google Scholar] [CrossRef] [Scilit]
- Borai, A.; Livingstone, C.; Kaddam, I.; Ferns, G. Selection of the appropriate method for the assessment of insulin resistance. BMC Med. Res. Methodol. 2011, 11, 158. [Google Scholar] [CrossRef] [Scilit]
- Ferrannini, E.; Mari, A. How to measure insulin sensitivity. J. Hypertens. 1998, 16, 895–906. [Google Scholar] [CrossRef] [Scilit]
- Wallace, T.M.; Matthews, D.R. The assessment of insulin resistance in man. Diabet. Med. 2002, 19, 527–534. [Google Scholar] [CrossRef] [Scilit]
- Cobelli, C.; Toffolo, G.M.; Dalla Man, C.; Campioni, M.; Denti, P.; Caumo, A.; Butler, P.; Rizza, R. Assessment of beta-cell function in humans, simultaneously with insulin sensitivity and hepatic extraction, from intravenous and oral glucose tests. Am. J. Physiol. Endocrinol. Metab. 2007, 293, E1–E15. [Google Scholar] [CrossRef] [Scilit]
- Cersosimo, E.; Solis-Herrera, C.; Trautmann, M.E.; Malloy, J.; Triplitt, C.L. Assessment of pancreatic β-cell function: Review of methods and clinical applications. Curr. Diabetes Rev. 2014, 10, 2–42. [Google Scholar] [CrossRef] [Scilit]
- Hannon, T.S.; Kahn, S.E.; Utzschneider, K.M.; Buchanan, T.A.; Nadeau, K.J.; Zeitler, P.S.; Ehrmann, D.A.; Arslanian, S.A.; Caprio, S.; Edelstein, S.L.; et al. Review of methods for measuring β-cell function: Design considerations from the Restoring Insulin Secretion (RISE) Consortium. Diabetes Obes. Metab. 2018, 20, 14–24. [Google Scholar] [CrossRef] [Scilit]
- Pacini, G.; Mari, A. Methods for clinical assessment of insulin sensitivity and beta-cell function. Best Pract. Res. Clin. Endocrinol. Metab. 2003, 17, 305–322. [Google Scholar] [CrossRef] [Scilit]
- Rudvik, A.; Månsson, M. Evaluation of surrogate measures of insulin sensitivity–correlation with gold standard is not enough. BMC Med. Res. Methodol. 2018, 18, 64. [Google Scholar] [CrossRef] [Scilit]
- Lin, L.I. A concordance correlation coefficient to evalu.u.uate reproducibility. Biometrics 1989, 45, 255–268. [Google Scholar] [CrossRef] [Scilit]
- Bland, J.M.; Altman, D.G. Statistical methods for assessing agreement between two methods of clinical measurement. Lancet 1986, 1, 307–310. [Google Scholar] [CrossRef] [Scilit]
- McBride, G. A Proposal for Strength-of-Agreement Criteria for Lin’s Concordance Correlation Coefficient; National Institute of Water & Atmospheric Research: Hamilton, New Zealand, 2005; pp. 307–310. [Google Scholar]
- Sterne, J.A.C.; Savović, J.; Page, M.J.; Elbers, R.G.; Blencowe, N.S.; Boutron, I.; Cates, C.J.; Cheng, H.Y.; Corbett, M.S.; Eldridge, S.M.; et al. RoB 2: A revised tool for assessing risk of bias in randomised trials. Bmj 2019, 366, l4898. [Google Scholar] [CrossRef] [Scilit]
- Bogdanski, P.; Szulinska, M.; Suliburska, J.; Pupek-Musialik, D.; Jablecka, A.; Witmanowski, H. Supplementation with L-arginine favorably influences plasminogen activator inhibitor type 1 concentration in obese patients. A randomized, double blind trial. J. Endocrinol. Invest. 2013, 36, 221–226. [Google Scholar] [CrossRef] [Scilit]
- Sánchez, M.; de la Sierra, A.; Coca, A.; Poch, E.; Giner, V.; Urbano-Márquez, A. Oral calcium supplementation reduces intraplatelet free calcium concentration and insulin resistance in essential hypertensive patients. Hypertension 1997, 29, 531–536. [Google Scholar] [CrossRef] [Scilit]
- Lê, K.A.; Ith, M.; Kreis, R.; Faeh, D.; Bortolotti, M.; Tran, C.; Boesch, C.; Tappy, L. Fructose overconsumption causes dyslipidemia and ectopic lipid deposition in healthy subjects with and without a family history of type 2 diabetes. Am. J. Clin. Nutr. 2009, 89, 1760–1765. [Google Scholar] [CrossRef] [Scilit]
- Ryan, A.S.; Ortmeyer, H.K.; Sorkin, J.D. Exercise with calorie restriction improves insulin sensitivity and glycogen synthase activity in obese postmenopausal women with impaired glucose tolerance. Am. J. Physiol. Endocrinol. Metab. 2012, 302, E145–E152. [Google Scholar] [CrossRef] [Scilit]
- Ard, J.D.; Grambow, S.C.; Liu, D.; Slentz, C.A.; Kraus, W.E.; Svetkey, L.P. The effect of the PREMIER interventions on insulin sensitivity. Diabetes Care 2004, 27, 340–347. [Google Scholar] [CrossRef] [Scilit]
- Larson-Meyer, D.E.; Heilbronn, L.K.; Redman, L.M.; Newcomer, B.R.; Frisard, M.I.; Anton, S.; Smith, S.R.; Alfonso, A.; Ravussin, E. Effect of calorie restriction with or without exercise on insulin sensitivity, beta-cell function, fat cell size, and ectopic lipid in overweight subjects. Diabetes Care 2006, 29, 1337–1344. [Google Scholar] [CrossRef] [Scilit]
- Paniagua, J.A.; Gallego de la Sacristana, A.; Romero, I.; Vidal-Puig, A.; Latre, J.M.; Sanchez, E.; Perez-Martinez, P.; Lopez-Miranda, J.; Perez-Jimenez, F. Monounsaturated fat-rich diet prevents central body fat distribution and decreases postprandial adiponectin expression induced by a carbohydrate-rich diet in insulin-resistant subjects. Diabetes Care 2007, 30, 1717–1723. [Google Scholar] [CrossRef] [Scilit]
- Davis, J.N.; Ventura, E.E.; Tung, A.; Munevar, M.A.; Hasson, R.E.; Byrd-Williams, C.; Vanni, A.K.; Spruijt-Metz, D.; Weigensberg, M.; Goran, M.I. Effects of a randomized maintenance intervention on adiposity and metabolic risk factors in overweight minority adolescents. Pediatr. Obes. 2012, 7, 16–27. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kien, C.L.; Bunn, J.Y.; Poynter, M.E.; Stevens, R.; Bain, J.; Ikayeva, O.; Fukagawa, N.K.; Champagne, C.M.; Crain, K.I.; Koves, T.R.; et al. A lipidomics analysis of the relationship between dietary fatty acid composition and insulin sensitivity in young adults. Diabetes 2013, 62, 1054–1063. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chachay, V.S.; Macdonald, G.A.; Martin, J.H.; Whitehead, J.P.; O’Moore-Sullivan, T.M.; Lee, P.; Franklin, M.; Klein, K.; Taylor, P.J.; Ferguson, M.; et al. Resveratrol does not benefit patients with nonalcoholic fatty liver disease. Clin. Gastroenterol. Hepatol. 2014, 12, 2092–2103.e6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Derosa, G.; Cicero, A.F.; Fogari, E.; D’Angelo, A.; Bonaventura, A.; Romano, D.; Maffioli, P. Effects of n-3 PUFAs on postprandial variation of metalloproteinases, and inflammatory and insulin resistance parameters in dyslipidemic patients: Evaluation with euglycemic clamp and oral fat load. J. Clin. Lipidol. 2012, 6, 553–564. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grimnes, G.; Figenschau, Y.; Almås, B.; Jorde, R. Vitamin D, insulin secretion, sensitivity, and lipids: Results from a case-control study and a randomized controlled trial using hyperglycemic clamp technique. Diabetes 2011, 60, 2748–2757. [Google Scholar] [CrossRef] [Scilit]
- Hays, N.P.; Starling, R.D.; Sullivan, D.H.; Fluckey, J.D.; Coker, R.H.; Evans, W.J. Comparison of insulin sensitivity assessment indices with euglycemic-hyperinsulinemic clamp data after a dietary and exercise intervention in older adults. Metabolism 2006, 55, 525–532. [Google Scholar] [CrossRef] [Scilit]
- Hokayem, M.; Blond, E.; Vidal, H.; Lambert, K.; Meugnier, E.; Feillet-Coudray, C.; Coudray, C.; Pesenti, S.; Luyton, C.; Lambert-Porcheron, S.; et al. Grape polyphenols prevent fructose-induced oxidative stress and insulin resistance in first-degree relatives of type 2 diabetic patients. Diabetes Care 2013, 36, 1454–1461. [Google Scholar] [CrossRef] [Scilit]
- Johnston, K.L.; Thomas, E.L.; Bell, J.D.; Frost, G.S.; Robertson, M.D. Resistant starch improves insulin sensitivity in metabolic syndrome. Diabet. Med. 2010, 27, 391–397. [Google Scholar] [CrossRef]
- McAuley, K.A.; Williams, S.M.; Mann, J.I.; Goulding, A.; Chisholm, A.; Wilson, N.; Story, G.; McLay, R.T.; Harper, M.J.; Jones, I.E. Intensive lifestyle changes are necessary to improve insulin sensitivity: A randomized controlled trial. Diabetes Care 2002, 25, 445–452. [Google Scholar] [CrossRef] [Scilit]
- Tardy, A.L.; Lambert-Porcheron, S.; Malpuech-Brugère, C.; Giraudet, C.; Rigaudière, J.P.; Laillet, B.; Leruyet, P.; Peyraud, J.L.; Boirie, Y.; Laville, M.; et al. Dairy and industrial sources of trans fat do not impair peripheral insulin sensitivity in overweight women. Am. J. Clin. Nutr. 2009, 90, 88–94. [Google Scholar] [CrossRef] [Scilit]
- Lagerpusch, M.; Enderle, J.; Later, W.; Eggeling, B.; Pape, D.; Müller, M.J.; Bosy-Westphal, A. Impact of glycaemic index and dietary fibre on insulin sensitivity during the refeeding phase of a weight cycle in young healthy men. Br. J. Nutr. 2013, 109, 1606–1616. [Google Scholar] [CrossRef] [Scilit]
- Lagerpusch, M.; Enderle, J.; Eggeling, B.; Braun, W.; Johannsen, M.; Pape, D.; Müller, M.J.; Bosy-Westphal, A. Carbohydrate quality and quantity affect glucose and lipid metabolism during weight regain in healthy men. J. Nutr. 2013, 143, 1593–1601. [Google Scholar] [CrossRef] [Scilit]
- Guebre-Egziabher, F.; Rabasa-Lhoret, R.; Bonnet, F.; Bastard, J.P.; Desage, M.; Skilton, M.R.; Vidal, H.; Laville, M. Nutritional intervention to reduce the n-6/n-3 fatty acid ratio increases adiponectin concentration and fatty acid oxidation in healthy subjects. Eur. J. Clin. Nutr. 2008, 62, 1287–1293. [Google Scholar] [CrossRef] [Scilit]
- Müller, M.J.; Enderle, J.; Pourhassan, M.; Braun, W.; Eggeling, B.; Lagerpusch, M.; Glüer, C.C.; Kehayias, J.J.; Kiosz, D.; Bosy-Westphal, A. Metabolic adaptation to caloric restriction and subsequent refeeding: The Minnesota Starvation Experiment revisited. Am. J. Clin. Nutr. 2015, 102, 807–819. [Google Scholar] [CrossRef] [Scilit]
- Brøns, C.; Spohr, C.; Storgaard, H.; Dyerberg, J.; Vaag, A. Effect of taurine treatment on insulin secretion and action, and on serum lipid levels in overweight men with a genetic predisposition for type II diabetes mellitus. Eur. J. Clin. Nutr. 2004, 58, 1239–1247. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ryan, M.C.; Itsiopoulos, C.; Thodis, T.; Ward, G.; Trost, N.; Hofferberth, S.; O’Dea, K.; Desmond, P.V.; Johnson, N.A.; Wilson, A.M. The Mediterranean diet improves hepatic steatosis and insulin sensitivity in individuals with non-alcoholic fatty liver disease. J. Hepatol. 2013, 59, 138–143. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alemzadeh, R.; Langley, G.; Upchurch, L.; Smith, P.; Slonim, A.E. Beneficial effect of diazoxide in obese hyperinsulinemic adults. J. Clin. Endocrinol. Metab. 1998, 83, 1911–1915. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Osterberg, K.L.; Boutagy, N.E.; McMillan, R.P.; Stevens, J.R.; Frisard, M.I.; Kavanaugh, J.W.; Davy, B.M.; Davy, K.P.; Hulver, M.W. Probiotic supplementation attenuates increases in body mass and fat mass during high-fat diet in healthy young adults. Obesity 2015, 23, 2364–2370. [Google Scholar] [CrossRef] [Scilit]
- Jans, A.; van Hees, A.M.; Gjelstad, I.M.; Sparks, L.M.; Tierney, A.C.; Risérus, U.; Drevon, C.A.; Schrauwen, P.; Roche, H.M.; Blaak, E.E. Impact of dietary fat quantity and quality on skeletal muscle fatty acid metabolism in subjects with the metabolic syndrome. Metabolism 2012, 61, 1554–1565. [Google Scholar] [CrossRef] [Scilit]
- Davy, B.M.; Davy, K.P.; Ho, R.C.; Beske, S.D.; Davrath, L.R.; Melby, C.L. High-fiber oat cereal compared with wheat cereal consumption favorably alters LDL-cholesterol subclass and particle numbers in middle-aged and older men. Am. J. Clin. Nutr. 2002, 76, 351–358. [Google Scholar] [CrossRef] [Scilit]
- Kolehmainen, M.; Mykkänen, O.; Kirjavainen, P.V.; Leppänen, T.; Moilanen, E.; Adriaens, M.; Laaksonen, D.E.; Hallikainen, M.; Puupponen-Pimiä, R.; Pulkkinen, L.; et al. Bilberries reduce low-grade inflammation in individuals with features of metabolic syndrome. Mol. Nutr. Food Res. 2012, 56, 1501–1510. [Google Scholar] [CrossRef] [Scilit]
- Tierney, A.C.; McMonagle, J.; Shaw, D.I.; Gulseth, H.L.; Helal, O.; Saris, W.H.; Paniagua, J.A.; Gołąbek-Leszczyñska, I.; Defoort, C.; Williams, C.M.; et al. Effects of dietary fat modification on insulin sensitivity and on other risk factors of the metabolic syndrome—LIPGENE: A European randomized dietary intervention study. Int. J. Obes. 2011, 35, 800–809. [Google Scholar] [CrossRef] [Scilit]
- Brady, L.M.; Lovegrove, S.S.; Lesauvage, S.V.; Gower, B.A.; Minihane, A.M.; Williams, C.M.; Lovegrove, J.A. Increased n-6 polyunsaturated fatty acids do not attenuate the effects of long-chain n-3 polyunsaturated fatty acids on insulin sensitivity or triacylglycerol reduction in Indian Asians. Am. J. Clin. Nutr. 2004, 79, 983–991. [Google Scholar] [CrossRef] [Scilit]
- Fava, F.; Gitau, R.; Griffin, B.A.; Gibson, G.R.; Tuohy, K.M.; Lovegrove, J.A. The type and quantity of dietary fat and carbohydrate alter faecal microbiome and short-chain fatty acid excretion in a metabolic syndrome ‘at-risk’ population. Int. J. Obes. 2013, 37, 216–223. [Google Scholar] [CrossRef] [Scilit]
- Giacco, R.; Lappi, J.; Costabile, G.; Kolehmainen, M.; Schwab, U.; Landberg, R.; Uusitupa, M.; Poutanen, K.; Pacini, G.; Rivellese, A.A.; et al. Effects of rye and whole wheat versus refined cereal foods on metabolic risk factors: A randomised controlled two-centre intervention study. Clin. Nutr. 2013, 32, 941–949. [Google Scholar] [CrossRef] [Scilit]
- Juntunen, K.S.; Laaksonen, D.E.; Poutanen, K.S.; Niskanen, L.K.; Mykkänen, H.M. High-fiber rye bread and insulin secretion and sensitivity in healthy postmenopausal women. Am. J. Clin. Nutr. 2003, 77, 385–391. [Google Scholar] [CrossRef] [Scilit]
- Douglas, C.C.; Gower, B.A.; Darnell, B.E.; Ovalle, F.; Oster, R.A.; Azziz, R. Role of diet in the treatment of polycystic ovary syndrome. Fertil. Steril. 2006, 85, 679–688. [Google Scholar] [CrossRef] [Scilit]
- Davis, J.N.; Kelly, L.A.; Lane, C.J.; Ventura, E.E.; Byrd-Williams, C.E.; Alexandar, K.A.; Azen, S.P.; Chou, C.P.; Spruijt-Metz, D.; Weigensberg, M.J.; et al. Randomized control trial to improve adiposity and insulin resistance in overweight Latino adolescents. Obesity 2009, 17, 1542–1548. [Google Scholar] [CrossRef] [Scilit]
- Knowler, W.C.; Barrett-Connor, E.; Fowler, S.E.; Hamman, R.F.; Lachin, J.M.; Walker, E.A.; Nathan, D.M. Reduction in the incidence of type 2 diabetes with lifestyle intervention or metformin. N. Engl. J. Med. 2002, 346, 393–403. [Google Scholar] [CrossRef] [Scilit]
- Astrup, A.; Ryan, L.; Grunwald, G.K.; Storgaard, M.; Saris, W.; Melanson, E.; Hill, J.O. The role of dietary fat in body fatness: Evidence from a preliminary meta-analysis of ad libitum low-fat dietary intervention studies. Br. J. Nutr. 2000, 83 (Suppl. S1), S25–S32. [Google Scholar] [CrossRef] [Scilit]
- Risérus, U.; Willett, W.C.; Hu, F.B. Dietary fats and prevention of type 2 diabetes. Prog. Lipid Res. 2009, 48, 44–51. [Google Scholar] [CrossRef] [Scilit]
- Laaksonen, D.E.; Toppinen, L.K.; Juntunen, K.S.; Autio, K.; Liukkonen, K.H.; Poutanen, K.S.; Niskanen, L.; Mykkänen, H.M. Dietary carbohydrate modification enhances insulin secretion in persons with the metabolic syndrome. Am. J. Clin. Nutr. 2005, 82, 1218–1227. [Google Scholar] [CrossRef] [Scilit]
- Katsuki, A.; Sumida, Y.; Urakawa, H.; Gabazza, E.C.; Murashima, S.; Morioka, K.; Kitagawa, N.; Tanaka, T.; Araki-Sasaki, R.; Hori, Y.; et al. Neither homeostasis model assessment nor quantitative insulin sensitivity check index can predict insulin resistance in elderly patients with poorly controlled type 2 diabetes mellitus. J. Clin. Endocrinol. Metab. 2002, 87, 5332–5335. [Google Scholar] [CrossRef] [Scilit]
- Faerch, K.; Brøns, C.; Alibegovic, A.C.; Vaag, A. The disposition index: Adjustment for peripheral vs. hepatic insulin sensitivity? J. Physiol. 2010, 588, 759–764. [Google Scholar] [CrossRef] [Scilit]
- Watson, P.F.; Petrie, A. Method agreement analysis: A review of correct methodology. Theriogenology 2010, 73, 1167–1179. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).