


Abstract
(1) Introduction: Current evidence on managing infants under six months with growth failure or other nutrition-related risk is sparse and low quality. This review aims to inform research priorities to fill this evidence gap, focusing on breastfeeding practices. (2) Methods: We searched PubMed, CINAHL Plus, and Cochrane Library for studies on feeding interventions that aim to restore or improve the volume or quality of breastmilk and breastfeeding when breastfeeding practices are sub-optimal or prematurely stopped. We included studies from both low- and middle-income countries and high-income countries. (3) Results: Forty-seven studies met the inclusion criteria. Most were from high-income countries (n = 35, 74.5%) and included infants who were at risk of growth failure at birth (preterm infants/small for gestational age) and newborns with early growth faltering. Interventions included formula fortification or supplementation (n = 31, 66%), enteral feeds (n = 8, 17%), cup feeding (n = 2, 4.2%), and other (n = 6, 12.8%). Outcomes included anthropometric change (n = 40, 85.1%), reported feeding practices (n = 16, 34%), morbidity (n = 11, 23.4%), and mortality (n = 5, 10.6%). Of 31 studies that assessed formula fortification or supplementation, 30 reported anthropometric changes (n = 17 no effect, n = 9 positive, n = 4 mixed), seven morbidity (n = 3 no effect, n = 2 positive, n = 2 negative), five feeding (n = 2 positive, n = 2 no effect, n = 1 negative), and four mortality (n = 3 no effect, n = 1 negative). Of eight studies that assessed enteral feed interventions, seven reported anthropometric changes (n = 4 positive, n = 3 no effect), five feeding practices (n = 2 positive, n = 2 no effect, n = 1 negative), four morbidity (n = 4 no effect), and one reported mortality (n = 1 no effect). Overall, interventions with positive effects on feeding practices were cup feeding compared to bottle-feeding among preterm; nasogastric tube feed compared to bottle-feeding among low birth weight preterm; and early progressive feeding compared to delayed feeding among extremely low birth weight preterm. Bovine/cow milk feeding and high volume feeding interventions had an unfavourable effect, while electric breast pump and Galactagogue had a mixed effect. Regarding anthropometric outcomes, overall, macronutrient fortified formula, cream supplementation, and fortified human milk formula had a positive effect (weight gain) on preterm infants. Interventions comparing human breastmilk/donor milk with formula had mixed effects. Overall, only human milk compared to formula intervention had a positive effect on morbidity among preterm infants, while none of the interventions had any positive effect on mortality. Bovine/cow milk supplementation had unfavourable effects on both morbidity and mortality. (4) Conclusion: Future research should prioritise low- and middle-income countries, include infants presenting with growth failure in the post-neonatal period and record effects on morbidity and mortality outcomes.
1. Introduction
Early life malnutrition and growth faltering is an important global public health problem [1]. Previously thought to be uncommon, estimates indicate that some 8.5 million infants aged under six months (<6 m) worldwide are wasted (have low weight-for-length, an important anthropometric marker of nutritional risk) [2]. Infants <6 m are not simply small-children; the first six months of life represents a period of rapid maturation and development with unique dietary needs, since infants should ideally be breastfed during this period [3]. The mother or maternal substitute, therefore, plays a critical role in fulfilling the nutritional requirements [4]. Unmet nutritional requirements can have serious implications for growth and survival. The short-term implications include a higher risk of morbidity and mortality, while long-term effects have implications for later health and well-being including the risk of non-communicable diseases [3].
The World Health Organisation (WHO)/United Nations Children’s Fund (UNICEF) global strategy for infant and young child feeding recognises the importance of early initiation of breastfeeding and exclusive breastfeeding (EBF) [5]. However, only 37% of infants <6 m are exclusively breastfed in low- and middle-income countries (LMICs) [6]. Moreover, it is recognised that a significant number of breastfeeding mothers of infants <6 m might face challenges in breastfeeding. Globally, an estimated 15–20% of all births are low birth weight (LBW) [7]. Regarding feeding practices, these infants are often not breastfed and many times not fed at all during the initial hours and days of life [8]. Risk factors for growth failure include both infant and maternal factors. In addition to LBW, sub-optimal feeding practices, congenital abnormalities, and underlying morbidities are common risk factors, while maternal physical and mental conditions are increasingly recognised as other potential causes [9,10]
Many early-life interventions to improve growth among young infants have been tested, ranging from cup feeding to spoon-feeding to the fortification of either human/donor breastmilk or formula [11,12,13,14,15,16,17]. However, currently, especially for infants who are already small or at-risk, there is insufficient data to develop recommendations [14,15,16,18,19,20,21]. In 2011 and 2013, WHO published recommendations on the feeding of LBW infants and management of severe acute malnutrition among infants <6 m, respectively; these recommendations were based on a limited and low or very low quality of evidence [8,22]. Given the importance of early infant feeding practices on morbidity, mortality, and long-term health and well-being, generating high-quality evidence is essential to inform prevention and management of growth failure among young infants.
Through this review, we aim to inform research priorities to prevent and manage growth failure among small and at-risk infants <6 m. The objectives include the following:
- (1)
- to identify and describe feeding interventions with a focus on restoring or improving the volume and quality of breastmilk and breastfeeding when breastfeeding practices are sub-optimal or prematurely stopped, and
- (2)
- to assess the impact of these interventions on feeding practices, anthropometry, morbidity, and mortality status.
2. Materials and Methods
We developed and followed a standard systematic review protocol in accordance with the PRISMA (preferred reporting items for systematic review and meta-analysis protocols) statement [23].
2.1. Eligibility Criteria
Population: We reviewed studies involving infants <6 m who are small or at nutrition-related risk, including those with LBW, and those with weight loss or feeding difficulties.
Intervention: Studies were eligible if they focused on feeding interventions for infants, mothers, or both that aimed at restoring or improving the quality and volume of breastmilk and optimising breastfeeding when breastfeeding practices are sub-optimal or prematurely stopped.
Comparison: Studies reporting any comparison between/with interventions of interest.
Outcomes: Studies reporting on at least one of the following outcomes—feeding practices, anthropometry, morbidity, or mortality—were included.
Study design: We selected studies that included randomised control trials, quasi-experimental, cohort, cross-sectional, and other comparative observational studies.
Context: Studies from both LMICs and high-income countries (HICs) were included.
Exclusion criteria included (1) studies with medical interventions, such as use of antibiotics and micronutrients in addition to human/donor/formula milk fortification; (2) unpublished studies; (3) reviews/systematic reviews; (4) non-human studies; (5) studies not published in English; and (6) studies published in abstract form only, correspondence, letters, case studies, opinion pieces, and protocols.
2.2. Search Strategy
Searches were conducted in three databases: PubMed, CINAHL Plus, and Cochrane Library. We used the following search strategy for PubMed: (“infant” or “newborn” or “newborns” or “neonate” or “neonates” or “low birth weight” or “low birthweight” or “low-birth-weight” or “LBW” or “small for gestational age” or “small-for-gestational-age” or “SGA” or “premature” or “pre-mature” or “preterm” or “pre-term” or “severe acute malnutrition” or “malnutrition” or “SAM” or “wasting” or “wasted” or “foetal growth retardation” or “foetal growth restriction” or “fetal growth restriction” or “fetal growth retardation” or “intrauterine growth restriction” or “intrauterine growth retardation” or “IUGR” or “failure to thrive” or “FTT” or “growth failure” or “growth faltering”) and (“human milk” or “breast milk” or “breastmilk” or “infant formula” or “establishing breastfeeding” or “supplement*” “suck*” or “spoon fe*” or “cup fe*” or “bottle feeding” or “breast milk substitute” or “breast milk fortifier” or “infant feeding practices” or “early weaning” or “relact*” or “complementary food” or “supplementary food”). Similar keywords were used with other selected databases. We limited the evidence to studies published in the English language from Jan 1990 to December 2018 and focusing on the human species.
2.3. Study Selection
All identified records were imported in Eppi Reviewer software (version V.4.8.0.0, EPPI-Centre, UCL Institute of Education, University of London, London, UK). Using a two-stage screening process, two reviewers independently screened all titles and abstracts (first stage), and full texts (second stage); any disagreements were resolved by a third reviewer.
2.4. Data Extraction
Two reviewers independently extracted data using standard data extraction codes developed for this study. A third reviewer checked the coding in Eppi Reviewer. We extracted data on population (including sample size, details of setting, and country), intervention (description), comparison, outcome (description, type of measurement, effect size, and strength of evidence), and study design.
2.5. Analysis
Since the review examines a range of interventions and outcomes, the analyses are presented as a narrative synthesis. However, where the authors had given the magnitude of effect (including statistical uncertainty using confidence intervals) and strength of evidence, it is presented in the results table. We used the following terms for direction of effect: (1) positive evidence of uniformly favourable impacts across one or more outcome measures, analytic samples (full sample or subgroups), and/or studies; (2) negative evidence of uniformly adverse impacts across one or more outcome measures, analytic samples (full sample or subgroups), and/or studies; (3) no effect evidence of uniformly null impacts across one or more outcome measures, analytic samples (full sample or subgroups), and/or studies; and (4) mixed effect evidence of a mix of favourable, null, and/or adverse impacts across one or more outcome measures, analytic samples (full sample or subgroups), and/or studies.
3. Results
3.1. Study Selection
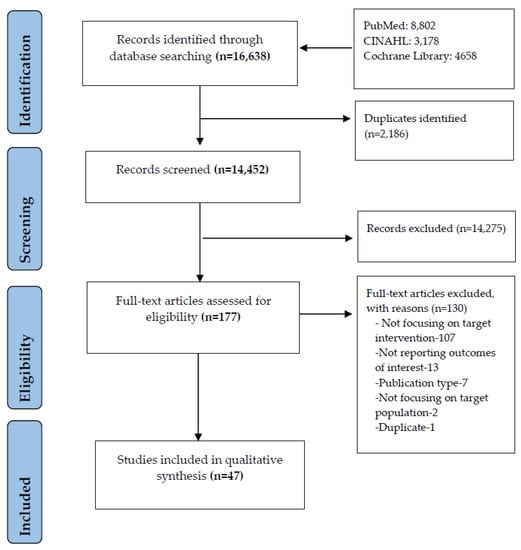
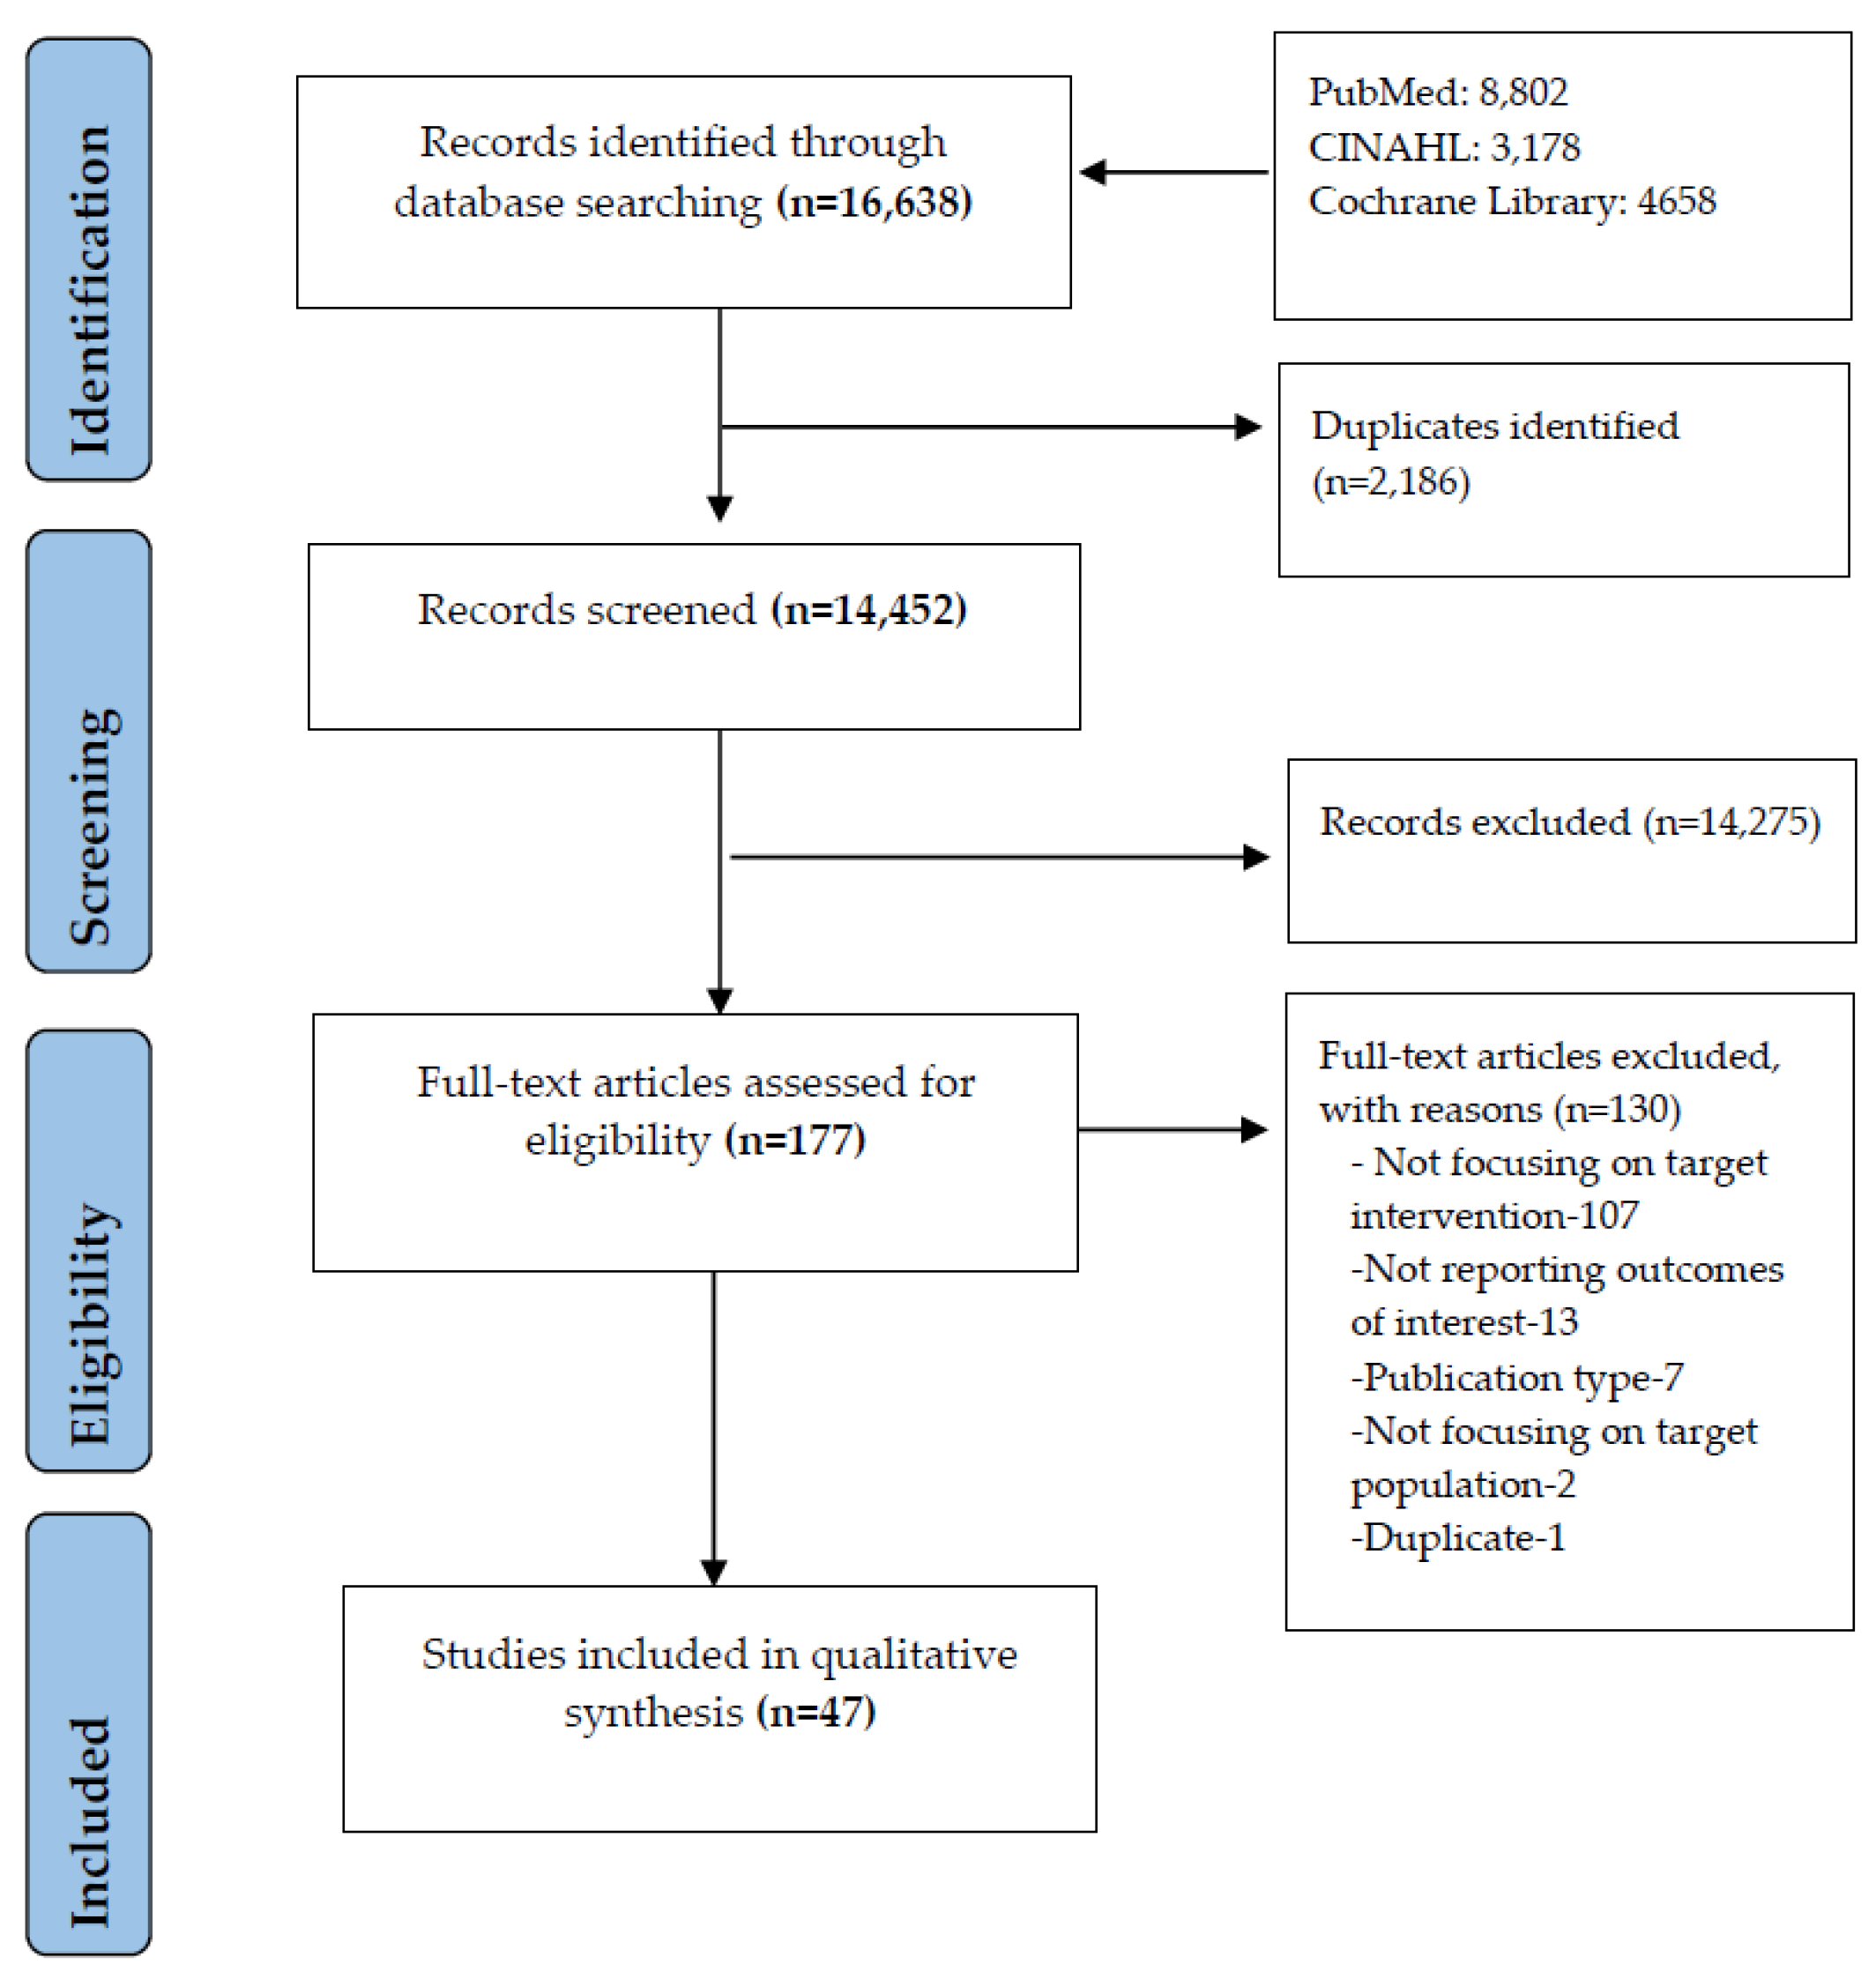
Figure 1 presents the selection process and search results. The search identified 16,638 records. After duplicate removal and initial screening of titles and abstracts, 177 records were eligible for full-text review. Among them, 130 did not meet the inclusion criteria — 107 studies did not focus on targeted interventions, 13 studies did not report outcomes of interest, seven studies were published as protocol/abstract form only/correspondence/opinion, two studies did not focus on the targeted population, and one study was a duplicate. Finally, 47 studies were included in the analysis.
Figure 1.
Flow diagram of included and excluded studies.
3.2. General Characteristics of the Included Studies
Table 1 presents a summary of the descriptive characteristics of the included studies. HICs represented three fourths of the studies (n = 35, 74.5%), with the highest number of studies from the USA (n = 21, 44.7%). Most studies were randomised control trials (RCT) (n = 38, 80.8%), and the sample size of studies ranged from 20 to 642. Regarding population focus, the majority included preterm with LBW/very low birthweight (VLBW)/extremely low birthweight (ELBW) (n = 41, 87.2%), while a few included mothers of preterm (n = 3, 6.4%) and infants with faltering growth (n = 3, 6.4%). We categorised identified interventions into the following groups: formula fortification or supplementation (n = 31, 66%), enteral feeds (n = 8, 17%), cup feeding (n = 2, 4.3%), and other interventions (n = 6, 12.7%). Similarly, identified outcomes were categorised as anthropometry (n = 40, 85.1%), feeding (n = 16, 34%), morbidity (n = 11, 23.4%), and mortality (n = 5, 10.6%).
Table 1.
Characteristics of included studies (n = 47).
Table 2 presents a summary of included reviews. A more detailed summary (intervention components and outcome measures) is presented in Appendix A (Table A1). The subsequent section briefly describes the effect of included studies.
Table 2.
Effect of feeding interventions on feeding practices, anthropometry, morbidity and mortality outcomes (n = 47).
3.3. Synthesis of Results
3.3.1. Cup Feeding
Two studies compared cup feeding with bottle-feeding among preterm infants [24,25]. Abouelfettoh et al. found a higher proportion of infants being breastfed one week post-discharge in the cup feeding group (80% vs. 64%, p = 0.03). Yilmaz et al. also found a significantly higher proportion of infants being exclusively breastfed (at discharge (72 vs. 46, p < 0.0001), 3 m (77 vs. 47, p < 0.0001), and 6 m (57 vs. 42, p < 0.001)) in the cup feeding group. This study also measured weight gain during the first seven days; however, no difference was observed between cup feeding and bottle-feeding (a bottle with a teat or nipple with formula or breast milk).
3.3.2. Formula Fortification or Supplementation
Bovine/Cow Milk Based Formula
Two studies compared bovine/cow milk based formula with fortified human milk. Abrams et al. assessed the effect of a diet consisting of either human milk fortified with a human milk protein-based fortifier (HM) or a diet containing variable amounts of milk containing cow milk-based protein (CM) among VLBW preterm infants [26]. No differences were observed in weight and length change during neonatal intensive care unit stay. Regarding morbidity, the CM group had a higher number of necrotizing enterocolitis (NEC) cases than the HM group (17% vs. 5%, p = 0.002); however, a similar significant effect was not observed in the case of sepsis. In addition, the CM group also had higher mortality compared to the HM group (8% vs. 2%, p = 0.04). Cristofalo et al. compared the effect of bovine milk-based preterm formula with HM fortification [33]. ELBW preterm infants fed with fortified bovine milk had a higher duration of parental nutrition (36 vs. 27 days, p = 0.04) and more cases of NEC (5 vs. 1, p = 0.08) compared to infants fed with HM based formula. However, no significant effect was observed on mortality between the two groups.
Protein Supplementation
Four studies evaluated the effect of protein supplementation on anthropometry [27,29,36,40]. Two studies compared human milk (HM) supplemented with extra protein to HM with standard fortification; the authors reported a mixed effect on anthropometric outcomes [27,29]. Another two studies compared (1) partially hydrolysed whey protein with non-hydrolysed whey casein formula [36], and (2) liquid extensively hydrolysed protein with powdered formula [40]. None of the studies found a statistically significant effect on weight or length gain.
Lactase Fortification
Two studies assessed the effect of lactase fortification on anthropometry [34,37]. Erasmus et al. focused on preterm, while Gathwala et al. studied term small for gestational age (SGA) infants. Erasmus et al. reported no difference in anthropometry at the fourth week between the lactase (Lactaid drops) treated group and untreated fortified HM or preterm formula. In contrast, the study among term SGA infants supplemented with HM fortified with lactase (Lactodex) reported an improvement in weight gain (38.7 vs. 28.7 g/d, p < 0.001) and length gain (1.14 vs. 0.87 cm/wk, p < 0.01) at the fourth week [37].
Fortification with Iron
Two studies compared human milk fortified with iron versus standard fortification among preterm infants [55,70]. Both studies reported no effect on anthropometric outcomes. Willeitner et al. also measured morbidity and mortality outcomes [55]: again, no difference was observed between the intervention and control groups.
Nutrient Fortification
Three studies evaluated the effect of nutrient fortification [32,46,56]. Clarke et al. compared the effect of nutrient-dense formula with the energy-supplemented formula on weight and length gain among infants with growth faltering (range: 2–31 wk) [32]. Another group studied the effect of nutrient-fortified formula (higher protein, calcium, phosphorous, and other vitamins and minerals) with standard formula among VLBW infants [56]. Both studies reported no effect on anthropometric outcomes. In contrast, Morlacchi et al. observed a significant improvement in weight (205.5 vs. 155 g/wk, p = 0.025) and length (1.6 vs. 1.1 cm/wk, p = 0.003) among VLBW preterm infants. Here, the authors compared macronutrient fortification of formula with standard fortification [46].
Cream Supplementation
Hair et al. assessed the effect of HM-derived cream supplement on LBW infants; the other group consisted of mothers’ own milk or donors’ HM derived fortifier [38]. The cream supplemented group had a significantly higher weight (14.0 vs. 12.4, g/kg/d, p = 0.03) and length velocity (1.03 vs. 0.83, cm/wk, p = 0.02) measured at 36 wks post-menstrual age or weaned from fortifier.
Early and Delayed Fortification
Three studies assessed the effect of early and delayed fortification [53,54,71]. Shah et al. compared 20 mL/kg/d HM feeds with 100 mL/kg/d feeds [71], while Tillman et al. compared early (1st feeding) fortification with 50–80 mL/kg/d feeds [54], and Taheri et al. compared early (1st feeding) fortification with 75 mL/kg/d feeds [53]. None of these reported any effect on anthropometry. Shah et al. and Taheri et al. also measured the effect on feeding outcomes; however, none found a significant difference between early and delayed fortification groups. Taheri et al. also recorded morbidity and observed no differences.
Fortified Human Milk
Two studies evaluated the effect of HM fortification on VLBW infants [31,47]. Bhat et al. compared fortified HM with only human milk; the authors reported better weight gain among the intervention group at two months [31]. Morlacchi et al. compared fortified HM with preterm formula; the authors did not observe any difference in weight and length between the two groups at term corrected age [47]. However, infants fed with fortified HM had less fat mass (14.9% vs. 19.2%, p = 0.002) and more fat-free mass (85.1% vs. 80.8%, p = 0.002) compared to the formula-fed group.
Different Formulas
Five studies compared the effect of HM (mother’s own or donor) and formula [41,43,45,48,50]. Three studies focused on ELBW preterm [41,45,50]. Two studies did not observe any effect on anthropometry [41,50], while Manea et al. reported an improvement in weight among infants fed with human breastmilk (120.8 vs. 97.2 g/wk) [45]. Manea et al. and O’Connor et al. also reported lower morbidity among the intervention group [45,50]. Another two studies focused on LBW and VLBW preterm infants [43,48]. Both studies reported no difference in weight and length between intervention and control groups.
One study assessed the effect of liquid and powdered HM fortification [49]. Moya et al. reported a higher weight (1770 vs. 1670 g, p = 0.038) and length gain (41.8 vs. 40.9 cm, p = 0.010) among ELBW preterm fed with liquid HM fortification. However, no difference was observed in morbidity between the two groups.
One study compared different levels of fortification (human milk fortifier-HMF) standard (1.2 g HMF + 30 mL HM), moderate (1.2 g HMF + 25 mL HM), and aggressive (1.2 g HMF + 20 mL HM) [39]. The authors reported no significant differences in weight and length gain between the three groups.
Two studies compared the different compositions of fortifiers [42,51]. Porcelli et al. compared Wyeth Nutritional International’s new HMF (test) with Enfamil HMF (reference); the authors reported an improvement in weight gain (19.7 vs. 16.8 g/kg/d, p = 0.04); however, no effect was observed on length gain [51]. This study also found a positive effect on feeding outcomes; mean human milk intake was higher in test HMF compared to reference HMF. Similarly, Kumar et al. compared Similac liquid HMF with Enfamil liquid HMF [42]; the authors reported better weight gain among infants fed with Similac liquid HMF.
Another two studies compared different formulas [28,44]. Amesz et al. compared post-discharge formula, term formula, and HM fortified formula [28]; the authors did not find any differences in anthropometric outcomes between the three groups. In contrast, Lucas et al. compared follow-on preterm formula with standard term formula [44]; they reported an improvement in both weight and length gain among infants fed with follow-on preterm formula.
Continued EBF and Early Limited Formula
One study compared the effect of early limited formula with continued exclusive breastfeeding among term infants with weight loss within 36 hours of birth [35]. The authors observed a higher proportion of infants being exclusively breastfed at wk 1, 1 m, 2 m, and 3 m among infants fed with early limited formula. Additionally, this group also showed lower weight loss compared to the continued exclusive breastfeeding group (6.8 vs. 8.1%, p = 0.10).
3.3.3. Enteral Feed Interventions
One study compared continuous nasogastric gavage (CNG) with intermittent bolus gavage (IBG) among two groups: VLBW and ELBW preterm [57]. The authors reported no difference between CNG and IBG concerning full enteral feeds and regaining birth weight. Similarly, Mosqueda et al. compared intravenous feeds alone with a small bolus of nasogastric feeding among ELBW preterm [61]; the authors observed no effect on either anthropometry or morbidity. Another study compared nasogastric tube feeding with bottle-feeding among LBW preterm [60]; the authors reported higher chances of breastfeeding at discharge, third day, and three months among infants fed with nasogastric tube compared to bottle-fed infants.
Two studies compared different levels of enteral feeds [58,59]. Bora et al. compared complete enteral feeds (CEF) along with expressed breastmilk with minimal enteral feeds (MEF) along with intravenous feeds [58]. Although no difference was reported for feed intolerance and morbidity between the two groups, infants fed with CEF expended fewer days to regain birth weight compared to the MEF group (10.6 vs. 11.8 days, p = 0.03). Colaizy et al. compared four levels ( <25%, 25–50%, 50–75%, and >75%) of total enteral intake as human milk, donor milk, or mixed feed [59]. Infants fed with >75% enteral feeds were far below the reference median for weight-for-age z score compared to the other three groups (G4: −0.6 vs. G1, G2, G3: −0.1, −0.3, −0.32, p = 0.03).
One study compared high volume feeds (300 mL/kg/d of expressed breastmilk) with standard volume feeds (200 mL/kg/d of expressed breastmilk) [62]. The authors reported a higher number of infants experiencing feed intolerance among the high volume feed group (14 vs. 8, p = 0.07). Additionally, this study found a positive effect on weight gain but no effect on morbidity. Similarly, another study compared early progressive feeding (without trophic feeding) with delayed progressive feeding (after trophic feeding) [52]. The authors reported no difference in anthropometry-, morbidity-, and mortality-related outcomes between the two groups. Interestingly, infants in the delayed progressive feeding group reached full enteral feeding in fewer days (17 vs. 19, p = 0.02). Another study compared proactive feeding regimen (1st day—100, last day—200 mL/kg/d) with standard regimen (1st day—60, last day—170 mL/kg/d) [63]. The authors reported a significantly better (near to median) change in weight (−0.29 vs. −0.48, p = 0.002) and length (−0.19 vs. −0.45, p = 0.011) z scores among proactive feeding group.
3.3.4. Other Interventions
One study evaluated the effect of different concentration of bee honey [64]. Compared to control with no honey, other intervention groups (5 g, 10 g, and 15 g honey) demonstrated weight gain by the second week. Two studies assessed the effect of electric breast pump on mothers of preterm infants [65,69]. One study found no difference in volume of breast milk expressed between intervention (electric breast pump + education) and control group (only education) [65], while another study observed a significantly higher volume of breast milk expressed with electric breast pump compared to hand expression (578 vs. 463 mL, p < 0.01) [69].
One study compared nasogastric feeds with spoon feeds [66]. The authors observed no difference between the two groups when compared for weight gain. One study assessed the effect of suckling and swallowing exercise [67]. The authors compared two intervention groups (non-nutritive suckling exercise/swallowing exercise) with standard care and reported no difference in start to independent oral feeding between the three groups. One study evaluated the effect of Galactagogue provided to mothers of preterm infants [68]. Compared to placebo, Galactagogue group mothers experienced higher breast milk expression at three months (22 vs. 12, p < 0.05); however, this effect was not sustained at six months.
4. Discussion
4.1. Summary of Key Findings
Overall, interventions with positive effect on feeding practices (most commonly assessed by increased duration of breastfeeding) were cup feeding compared to bottle-feeding among preterm; nasogastric tube feed compared to bottle-feeding among LBW preterm; and early progressive feeding compared to delayed feeding among ELBW preterm. Bovine/cow milk feeding and high volume feeding interventions had an unfavourable effects (feeding intolerance and higher parenteral nutrition days), while electric breast pump and Galactagogue had a mixed effect.
Most of the studies reported anthropometric outcomes. Overall, macronutrient fortified formula, cream supplementation, and fortified human milk formula had positive effects (weight gain) on preterm infants. Interventions comparing human breastmilk/donor milk with formula had mixed effects.
Overall, only human milk compared to formula intervention had a positive effect on morbidity among preterm infants, while none of the interventions had any positive effects on mortality. Moreover, bovine/cow milk supplementation had unfavourable effects on morbidity and mortality, respectively.
4.2. This Review’s Findings in Context
Most current evidence is based on limited studies with low to medium study quality [14,15,16,18,19,21]. A review assessing the effect of cup feeding versus other forms of supplemental enteral feeding, for infants unable to fully breastfeed, reported similar findings as observed in our review [11]. However, the authors highlighted the challenge with compliance to cup feeding. Another review examining the effect of formula versus donor human milk for preterm or LBW infants showed better anthropometric outcomes among the formula-fed group [72]. In contrast, our review observed a mixed effect. This difference may be due to the inclusion of all studies in our review, irrespective of study quality. Similar to our findings, a review by Amissah et al. also reported a positive effect on weight with protein supplementation [20]. In decisions around early use of formula milks, it is important to note discussions around risk of allergies that may arise as a result. One recent review focusing on allergies found a risk ratio of 1.75 (95% CI: 1.30–2.27, p = 0.0001) for breastfed infants given cow’s milk formula supplementation in the first few weeks of life against no supplementation given to breastfed infants [73].
We conducted this review with an aim to identify research priorities to prevent and manage growth failure in the first six months of life. The included studies reported a range of populations, interventions, outcomes, and contexts. These are discussed further in the following section.
The population included preterm LBW/VLBW/ELBW, term SGA with LBW, mothers of preterm, and newborns with growth faltering in early days. Interestingly, our search identified a majority of those young infants who are at risk of growth failure at birth. This is indicative of a research gap among other infants under six months where growth failure may manifest or present after birth at different life stages (e.g., early growth failure before 12 wks/3 months or later growth failure-after 12 wks/3 months).
Identified interventions included cup feeding; formula fortification or supplementation with macro and micronutrients; lactase supplementation; bovine/cow milk vs. human milk human milk vs. formula; early vs. delayed feeding; low/high vs. standard feeding; nasogastric tube vs. intravenous feeding; suckling/swallowing exercise vs. standard feeding; nutrient-dense vs. standard feeding; and electric breast pump and Galactagogue.
Reported feeding outcomes included any or exclusive breastfeeding, feed intolerance, days on parenteral nutrition, days to oral feeds, and maternal milk volume. Anthropometric outcomes included-weight/length gain, weight/length velocity, weight-for-age/length-for-age z scores, weight loss, fat mass, fat-free mass, birth weight regain, and weight/length centiles. Similarly, morbidity outcomes included sepsis, NEC, and infection.
Lastly, most (75%) of the evidence is from HICs. However, LMICs have a higher prevalence of growth faltering. This highlights the need for designing and testing further interventions in LMIC settings. Similarly, the majority of the interventions tested were based on inpatient tertiary care hospital settings. These may have limited applicability and could even pose a health risk if applied in a low resource setting without suitable skillset, environmental conditions, and infrastructure. Hence, given the limited health care infrastructure and skillset in LMICs [74,75], future interventions should be suited to and explored in community-based settings. Although some work has been initiated in this area [76], much more still needs to be done to prevent and manage growth faltering among young infants. In rural Rwanda, using a medical-home model, integrated care is provided to at-risk infants through paediatric developmental clinics [77]. Similarly, the C-MAMI (community management of at-risk mothers and infants under six months) tool is being tested in Gambella refugee camps in Ethiopia and in the Rohingya response in Bangladesh [78,79]. Other interventions could include breastfeeding support (supplementary suckling, special breastfeeding support for vulnerable infants, support to mothers to increase confidence, supporting adolescent and working mothers) and non-breastfeeding support (partner, group, and community support).
In addition to the effectiveness of identified feeding interventions, we also extracted information on potential biases. Only one-third of the included studies had sample size more than 100 (50 infants in each arm or more), while nearly a third had sample size below 60 (30 infants each arm or less). This is of concern particularly for studies where authors have also conducted sub-group analysis. Additionally, lost to follow up was a concern in most of the studies, although not formally calculated. Similarly, authors did not report compliance to intervention in many studies. One study reported a challenge with the determination of breastfeeding practices beyond six weeks after discharge [24]. The authors highlighted low education level among mothers as a limiting factor for maternal verbal recall. Similarly, another study emphasised the limitation of determining the duration of full and partial breastfeeding around six months of age [60].
4.3. Strengths and Limitations
We did not formally assess the study quality of each individual study, but despite there being a good number of RCTs in our final sample, overall quality of studies was not always high, a common challenge being small sample size. Additionally, despite many studies reporting on anthropometric change, it is morbidity and mortality that really matters as a key outcome. Even when this was reported, only short-term outcomes were assessed; long term changes may also be relevant, especially given increasing appreciation of links between early life growth and later life risk of non-communicable diseases [80]. In recent years, there has been significant debate about the susceptibility of research to biases of various kinds, one of which includes industry-funded science [81]. Nearly a quarter of studies reported financial support from industry (Supplementary Materials, Table S1), while another 19 studies did not declare whether they received any financial support for the study. Our literature search captured studies published until December 2018.
The review findings should be interpreted considering these limitations. The present review also had several strengths, including the broad scope of the review covering a range of interventions and methodological rigor (double data screening and extraction). Furthermore, this review identified research priorities to prevent and manage growth faltering among a group of young infants that were either excluded or missed in earlier research studies.
5. Conclusions
This review explored ways to manage the feeding of small and at-risk infants in the first six months of life. Whilst finding a large range of interventions, most studies were set in HICs and focused on infants identified around the time of birth with risk factors such as with LBW. Future research needs to do more in LMICs where not only is the problem more common but the consequences more severe. More focus is also needed on infants who present in the post-neonatal period with growth faltering (either new onset or because earlier risk factors like LBW have not previously been noted or acted upon). Although most of the included studies recorded anthropometric outcomes, future research should also record effects on morbidity and mortality outcomes. Ideally, not just in the short term, but also any longer-term impacts.
Supplementary Materials
The following are available online at https://www.mdpi.com/2072-6643/12/7/2044/s1, Table S1: Information on declaration of financial support and conflict of interest.
Author Contributions
Conceptualisation, M.K., R.R., and M.M.; methodology, M.K., M.M., and R.R.; validation, R.R., P.G., and E.T.; formal analysis, R.R. and P.G.; investigation, R.R.; resources, R.R. and M.K.; writing—original draft preparation, R.R.; writing—review and editing, R.R., M.M., and M.K.; visualisation, R.R., M.K., and M.M.; supervision, M.M. and M.K. All authors have read and agreed to the published version of the manuscript.
Acknowledgments
World Health Organisation (WHO) via Emergency Nutrition Network (ENN) funded this research. R.R. was supported by the Department of Science and Technology, Government of India’s DST INSPIRE Faculty Award (IFA13-LSBM 95). This review was commissioned by WHO to feed into a technical consultation ‘research priorities to prevent, identify, and manage young infants with growth failure in the first six months of life’, January 2019, Geneva. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Full summary of the included studies.
Table A1.
Effect of feeding interventions on feeding practices, anthropometry, morbidity, and mortality outcomes (n = 47).

References
- Victora, C.G.; de Onis, M.; Hallal, P.C.; Blössner, M.; Shrimpton, R. Worldwide timing of growth faltering: Revisiting implications for interventions. Pediatric 2010, 125, e473–e480. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kerac, M.; Blencowe, H.; Grijalva-Eternod, C.S.; McGrath, M.; Shoham, J.; Cole, T.J.; Seal, A. Prevalence of wasting among under 6-month-old infants in developing countries and implications of new case definitions using WHO growth standards: A secondary data analysis. Arch. Dis. Child. 2011, 96, 1008–1013. [Google Scholar] [CrossRef] [Scilit]
- Kerac, M.; McGrath, M. Management of acute malnutrition in infants under 6 months of age. In The Biology of the First 1000 Days; CRC Press: Boca Raton, FL, USA, 2018; pp. 207–220. [Google Scholar]
- Management of Acute Malnutrition in Infants (MAMI) Project. 2010. Available online: https://reliefweb.int/sites/reliefweb.int/files/resources/8A7E77D26B35660F492576F70010D7DF-mami-report-complete.pdf (accessed on 16 August 2018).
- Global Strategy for Infant and Young Child Feeding. 2003. Available online: http://apps.who.int/iris/bitstream/handle/10665/42590/9241562218.pdf?sequence=1 (accessed on 16 August 2018).
- Victora, C.G.; Bahl, R.; Barros, A.J.D.; A França, G.V.; Horton, S.; Krasevec, J.; Murch, S.; Sankar, M.J.; Walker, N.; Rollins, N.C. Breastfeeding in the 21st century: Epidemiology, mechanisms, and lifelong effect. Lancet 2016, 387, 475–490. [Google Scholar] [CrossRef] [Scilit]
- Global Nutrition Targets 2025: Low Birth Weight Policy Brief. WHO, 2014. Available online: https://apps.who.int/iris/bitstream/handle/10665/149020/WHO_NMH_NHD_14.5_eng.pdf?ua=1 (accessed on 15 December 2018).
- Guidelines on Optimal Feeding of Low Birth-Weight Infants in Low—And Middle-Income Countries. World Health Organization, 2011. Available online: https://www.who.int/maternal_child_adolescent/documents/9789241548366.pdf?ua=1 (accessed on 10 December 2018).
- Balogun, O.O.; Dagvadorj, A.; Anigo, K.M.; Ota, E.; Sasaki, S. Factors influencing breastfeeding exclusivity during the first 6 months of life in developing countries: A quantitative and qualitative systematic review. Matern. Child. Nutr. 2015, 11, 433–451. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kerac, M.; Frison, S.; Connell, N.; Page, B.; McGrath, M. Informing the management of acute malnutrition in infants aged under 6 months (MAMI): Risk factor analysis using nationally-representative demographic & health survey secondary data. PeerJ 2019, 6, e5848. [Google Scholar] [CrossRef] [Scilit]
- Flint, A.; New, K.; Davies, M.W. Cup feeding versus other forms of supplemental enteral feeding for newborn infants unable to fully breastfeed. Cochrane Database Syst. Rev. 2016, 2016, CD005092. [Google Scholar] [CrossRef] [Scilit]
- Henderson, G.; Anthony, M.Y.; McGuire, W. Formula milk versus maternal breast milk for feeding preterm or low birth weight infants. Cochrane Database Syst. Rev. 2007, 2007, CD002972. [Google Scholar] [CrossRef] [Scilit]
- Collins, C.T.; Gillis, J.; McPhee, A.J.; Suganuma, H.; Makrides, M. Avoidance of bottles during the establishment of breast feeds in preterm infants. Cochrane Database Syst. Rev. 2016, 10, CD005252. [Google Scholar] [CrossRef] [Scilit]
- Young, L.; Embleton, N.D.; McGuire, W. Nutrient-enriched formula versus standard formula for preterm infants following hospital discharge. Cochrane Database Syst. Rev. 2016, 12, CD004696. [Google Scholar] [CrossRef] [Scilit]
- Brown, J.V.; Embleton, N.D.; Harding, J.E.; McGuire, W. Multi-nutrient fortification of human milk for preterm infants. Cochrane Database Syst. Rev. 2016, 2016, CD000343. [Google Scholar] [CrossRef]
- Tan-Dy, C.R.; Ohlsson, A. Lactase treated feeds to promote growth and feeding tolerance in preterm infants. Cochrane Database Syst. Rev. 2013, 2013, CD004591. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greene, Z.; O’Donnell, C.P.; Walshe, M. Oral stimulation for promoting oral feeding in preterm infants. Cochrane Database Syst. Rev. 2016, 9, CD009720. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Premji, S.S.; Chessell, L. Continuous nasogastric milk feeding versus intermittent bolus milk feeding for premature infants less than 1500 grams. Cochrane Database Syst. Rev. 2011, 2011, CD001819. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basuki, F.; Hadiati, D.R.; Turner, T.; McDonald, S.; Hakimi, M. Dilute versus full strength formula in exclusively formula-fed preterm or low birth weight infants. Cochrane Database Syst. Rev. 2013, 2013, CD007263. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amissah, E.A.; Brown, J.; Harding, J.E. Protein supplementation of human milk for promoting growth in preterm infants. Cochrane Database Syst. Rev. 2018, 6, CD000433. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amissah, E.A.; Brown, J.; Harding, J.E. Fat supplementation of human milk for promoting growth in preterm infants. Cochrane Database Syst. Rev. 2018, 6, CD000341. [Google Scholar] [CrossRef] [Scilit]
- Guideline: Updates on the Management of Severe Acute Malnutrition in Infants and Children. World Health Organisation, 2013. Available online: http://apps.who.int/iris/bitstream/handle/10665/95584/9789241506328_eng.pdf?sequence=1 (accessed on 2 September 2018).
- Moher, D.; Liberati, A.; Tetzlaff, J.; Altman, D.G. Preferred reporting items for systematic reviews and meta-analyses. PRISMA Statement 2009, 339, b2535. [Google Scholar] [CrossRef]
- Abouelfettoh, A.M.; Dowling, D.A.; Dabash, A.S.; Elguindy, S.R.; Seoud, I.A. Cup verus bottle feeding for hospitalized late preterm infants in Egypt: A quasi-experimental study. Int. Breastfeed. J. 2008, 3, 27. [Google Scholar] [CrossRef] [Scilit]
- Yilmaz, G.; Caylan, N.; Karacan Can, D.; Bodur, İ.; Gokcay, G. Effect of Cup Feeding and Bottle Feeding on Breastfeeding in Late Preterm Infants: A Randomized Controlled Study. J. Hum. Lact. 2014, 30, 174–179. [Google Scholar] [CrossRef] [Scilit]
- Abrams, S.A.; Schanler, R.J.; Lee, M.L.; Rechtman, D.J. Greater mortality and morbidity in extremely preterm infants fed a diet containing cow milk protein products. Breastfeed. Med. Off. J. Acad. Breastfeed. Med. 2014, 9, 281–295. [Google Scholar] [CrossRef] [Scilit]
- Alan, S.; Atasay, B.; Cakir, U.; Yildiz, D.; Kiliç, A.; Kahvecioglu, D.; Erdeve, O.; Arsan, S. An intention to achieve better postnatal in-hospital-growth for preterm infants: Adjustable protein fortification of human milk. Early Hum. Dev. 2013, 89, 1017–1023. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amesz, E.M.; Schaafsma, A.; Cranendonk, A.; Lafeber, H.N. Optimal growth and lower fat mass in preterm infants fed a protein-enriched postdischarge formula. J. Pediatr. Gastroenterol. Nutr. 2010, 50, 200–207. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arslanoglu, S.; Moro, G.E.; Ziegler, E.E. Adjustable fortification of human milk fed to preterm infants: Does it make a difference? J. Perinatol. Off. J. Calif. Perinat. Assoc. 2006, 26, 614–621. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Berseth, C.L.; Harris, C.L.; Wampler, J.L.; Hoffman, D.R.; Diersen-Schade, D.A. Liquid human milk fortifier significantly improves docosahexaenoic and arachidonic acid status in preterm infants. Prostaglandins Leukot. Essent. Fat. Acids 2014, 91, 97–103. [Google Scholar] [CrossRef] [Scilit]
- Bhat, B.A.; Gupta, B. Effects of human milk fortification on morbidity factors in very low birth weight infants. Ann. Saudi Med. 2001, 21, 292–305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Clarke, S.E.; Evans, S.; Macdonald, A.; Davies, P.; Booth, I.W. Randomized comparison of a nutrient-dense formula with an energy-supplemented formula for infants with faltering growth. J. Hum. Nutr. Diet. 2007, 20, 329–339. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cristofalo, E.A.; Schanler, R.J.; Blanco, C.L.; Sullivan, S.; Trawoeger, R.; Kiechl-Kohlendorfer, U.; Dudell, G.; Rechtman, D.J.; Lee, M.L.; Lucas, A.; et al. Randomized trial of exclusive human milk versus preterm formula diets in extremely premature infants. J. Pediatr. 2013, 163, 1592–1595.e1. [Google Scholar] [CrossRef] [Scilit]
- Erasmus, H.D.; Ludwig-Auser, H.M.; Paterson, P.G.; Sun, D.; Sankaran, K. Enhanced weight gain in preterm infants receiving lactase-treated feeds: A randomized, double-blind, controlled trial. J. Pediatr. 2002, 141, 532–537. [Google Scholar] [CrossRef] [Scilit]
- Flaherman, V.J.; Aby, J.; Burgos, A.E.; Lee, K.A.; Cabana, M.D.; Newman, T.B. Effect of early limited formula on duration and exclusivity of breastfeeding in at-risk infants: An RCT. Pediatrics 2013, 131, 1059–1065. [Google Scholar] [CrossRef] [Scilit]
- Florendo, K.N.; Bellflower, B.; van, Z.; Cooke, R.J. Growth in preterm infants fed either a partially hydrolyzed whey or an intact casein/whey preterm infant formula. J. Perinatol. 2009, 29, 106–111. [Google Scholar] [CrossRef] [Scilit]
- Gathwala, G.; Chawla, M.; Gehlaut, V.S.; Gathwala, G.; Chawla, M.; Gehlaut Veena, S. Fortified human milk in the small for gestational age neonate. Indian J. Pediatr. 2007, 74, 815–818. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hair, A.B.; Blanco, C.L.; Moreira, A.; Hawthorne, K.; Lee, M.L.; Rechtman, D.J.; Abrams, S.A. Randomized trial of human milk cream as a supplement to standard fortification of an exclusive human milk-based diet in infants 750-1250 g birth weight. J. Pediatr. 2014, 165, 915–920. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kanmaz, H.G.; Mutlu, B. Human Milk Fortification with Differing Amounts of Fortifier and Its Association with Growth and Metabolic Responses in Preterm Infants. J. Hum. Lact. 2013, 29, 400–405. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, J.H.; Chan, G.; Schanler, R.; Groh-Wargo, S.; Bloom, B.; Dimmit, R.; Williams, L.; Baggs, G.; Barrett-Reis, B. Growth and Tolerance of Preterm Infants Fed a New Extensively Hydrolyzed Liquid Human Milk Fortifier. J. Pediatr. Gastroenterol. Nutr. 2015, 61, 665–671. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim Eun, J.; Lee Na, M.; Chung, S.-H. A retrospective study on the effects of exclusive donor human milk feeding in a short period after birth on morbidity and growth of preterm infants during hospitalization. Medicine 2017, 96, e7970. [Google Scholar] [CrossRef] [Scilit]
- Kumar, N.; Monga, R.; Sampath, V.; Ehrhart, B. Prospective Comparison of Enfamil and Similac Liquid Human Milk Fortifier on Clinical Outcomes in Premature Infants. Am. J. Perinatol. 2017, 34, 1411–1416. [Google Scholar] [CrossRef] [Scilit]
- Lok, K.Y.W.; Chau, P.H.; Fan, H.S.L.; Chan, K.M.; Chan, B.H.; Fung, G.P.C.; Tarrant, M. Increase in Weight in Low Birth Weight and Very Low Birth Weight Infants Fed Fortified Breast Milk versus Formula Milk: A Retrospective Cohort Study. Nutrients 2017, 9, 520. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lucas, A.; Bishop, N.J.; King, F.J.; Cole, T.J. Randomised trial of nutrition for preterm infants after discharge. Arch. Dis. Child. 1992, 67, 324–327. [Google Scholar] [CrossRef] [Scilit]
- Manea, A.; Boia, M.; Iacob, D.; Dima, M.; Iacob Radu, E. Benefits of early enteral nutrition in extremely low birth weight infants. Singap. Med. J. 2016, 57, 616–618. [Google Scholar] [CrossRef] [Scilit]
- Morlacchi, L.; Mallardi, D.; Giannì, M.L.; Roggero, P.; Amato, O.; Pasqua, P.; Consonni, D.; Mosca, F. Is targeted fortification of human breast milk an optimal nutrition strategy for preterm infants? An interventional study. J. Transl. Med. 2016, 14, 195. [Google Scholar] [CrossRef] [Scilit]
- Morlacchi, L.; Roggero, P.; Giannì, M.L.; Bracco, B.; Porri, D.; Battiato, E.; Menis, C.; Liotto, N.; Mallardi, D.; Mosca, F. Protein use and weight-gain quality in very-low-birth-weight preterm infants fed human milk or formula. Am. J. Clin. Nutr. 2018, 107, 195–200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morley, R.; Lucas, A. Randomized diet in the neonatal period and growth performance until 7.5-8 y of age in preterm children. Am. J. Clin. Nutr. 2000, 71, 822–828. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moya, F.; Sisk, P.M.; Walsh, K.R.; Berseth, C.L. A new liquid human milk fortifier and linear growth in preterm infants. Pediatr 2012, 130, e928–e935. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Connor, D.L.; Gibbins, S.; Kiss, A.; Bando, N.; Brennan-Donnan, J.; Ng, E.; Campbell, D.M.; Vaz, S.; Fusch, C.; Asztalos, E.; et al. Effect of Supplemental Donor Human Milk Compared With Preterm Formula on Neurodevelopment of Very Low-Birth-Weight Infants at 18 Months: A Randomized Clinical Trial. J. Am. Med. Assoc. 2016, 316, 1897–1905. [Google Scholar] [CrossRef] [PubMed]
- Porcelli, P.; Schanler, R.; Greer, F.; Chan, G.; Gross, S.; Mehta, N.; Spear, M.; Kerner, J.; Euler, A.R. Growth in human milk-Fed very low birth weight infants receiving a new human milk fortifier. Ann. Nutr. Metab. 2000, 44, 2–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salas, A.A.; Li, P.; Parks, K.; Lal, C.V.; Martin, C.R.; Carlo, W.A. Early progressive feeding in extremely preterm infants: A randomized trial. Am. J. Clin. Nutr. 2018, 107, 365–370. [Google Scholar] [CrossRef] [Scilit]
- Taheri Peymaneh, A.; Sajjadian, N.; Fargi Marzieh, A.; Shariat, M. Is early breast milk fortification more effective in preterm infants? A clinical trial: Early and late fortification. J. Perinat. Med. 2017, 45, 953–957. [Google Scholar] [CrossRef] [Scilit]
- Tillman, S.; Brandon, D.H.; Silva, S.G. Evaluation of human milk fortification from the time of the first feeding: Effects on infants of less than 31 weeks gestational age. J. Perinatol. Off. J. Calif. Perinat. Assoc. 2012, 32, 525–531. [Google Scholar] [CrossRef] [Scilit]
- Willeitner, A.; Anderson, M.; Lewis, J. Highly Concentrated Preterm Formula as an Alternative to Powdered Human Milk Fortifier: A Randomized Controlled Trial. J. Pediatr. Gastroenterol. Nutr. 2017, 65, 574–578. [Google Scholar] [CrossRef] [Scilit]
- Worrell, L.A.; Thorp, J.W.; Tucker, R.; McKinley, L.T.; Chen, J.; Chng, Y.-M.; Vohr, B.R. The effects of the introduction of a high-nutrient transitional formula on growth and development of very-low-birth-weight infants. J. Perinatol. Off. J. Calif. Perinat. Assoc. 2002, 22, 112–119. [Google Scholar] [CrossRef] [Scilit]
- Akintorin, S.M.; Kamat, M.; Pildes, R.S.; Kling, P.; Andes, S.; Hill, J.; Pyati, S. A prospective randomized trial of feeding methods in very low birth weight infants. Pediatrics 1997, 100, E4. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bora, R.; Murthy, N.B. In resource limited areas complete enteral feed in stable very low birth weight infants (1000–1500 g) started within 24 h of life can improve nutritional outcome. J. Matern. Fetal Neonatal Med. 2017, 30, 2572–2577. [Google Scholar] [CrossRef] [Scilit]
- Colaizy, T.T.; Carlson, S.; Saftlas, A.F.; Morriss, F.H., Jr. Growth in VLBW infants fed predominantly fortified maternal and donor human milk diets: A retrospective cohort study. BMC Pediatr. 2012, 12, 124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kliethermes, P.A.; Cross, M.L.; Lanese, M.G.; Johnson, K.M.; Simon, S.D. Transitioning preterm infants with nasogastric tube supplementation: Increased likelihood of breastfeeding. J. Obs. Gynecol. Neonatal Nurs. 1999, 28, 264–273. [Google Scholar] [CrossRef] [Scilit]
- Mosqueda, E.; Sapiegiene, L.; Glynn, L.; Wilson-Costello, D.; Weiss, M. The early use of minimal enteral nutrition in extremely low birth weight newborns. J. Perinatol. 2008, 28, 264–269. [Google Scholar] [CrossRef] [Scilit]
- Thomas, N.; Cherian, A.; Santhanam, S.; Jana, A.K. A randomized control trial comparing two enteral feeding volumes in very low birth weight babies. J. Trop. Pediatr. 2012, 58, 55–58. [Google Scholar] [CrossRef] [Scilit]
- Zecca, E.; Costa, S.; Barone, G.; Giordano, L.; Zecca, C.; Maggio, L. Proactive enteral nutrition in moderately preterm small for gestational age infants: A randomized clinical trial. J. Pediatr. 2014, 165, 1135–1139.e1. [Google Scholar] [CrossRef] [Scilit]
- Aly, H.; Said, R.N.; Wali, I.E.; Elwakkad, A.; Soliman, Y.S.; Awad, A.R.; Shawky, M.A.; Abu Alam, M.S.; Mohamed, M.A. Medically Graded Honey Supplementation Formula to Preterm Infants as a Prebiotic: A Randomized Controlled Trial. J. Pediatr. Gastroenterol. Nutr. 2017, 64, 966–970. [Google Scholar] [CrossRef] [Scilit]
- Héon, M.; Goulet, C.; Garofalo, C.; Nuyt Anne, M.; Levy, E. An Intervention to Promote Breast Milk Production in Mothers of Preterm Infants. West. J. Nurs. Res. 2016, 38, 529–552. [Google Scholar] [CrossRef] [Scilit]
- Kumar, A.; Dabas, P.; Singh, B. Spoon feeding results in early hospital discharge of low birth weight babies. J. Perinatol. Off. J. Calif. Perinat. Assoc. 2010, 30, 209–217. [Google Scholar] [CrossRef] [Scilit]
- Lau, C.; Smith, E.O. Interventions to improve the oral feeding performance of preterm infants. Acta Paediatr. 2012, 101, e269–e274. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Serrao, F.; Corsello, M.; Romagnoli, C.; D’Andrea, V.; Zecca, E. The Long-Term Efficacy of a Galactagogue Containing Sylimarin-Phosphatidylserine and Galega on Milk Production of Mothers of Preterm Infants. Breastfeed. Med. 2018, 13, 67–69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Slusher, T.; Slusher, I.L.; Biomdo, M.; Bode-Thomas, F.; Curtis, B.A.; Meier, P. Electric breast pump use increases maternal milk volume in African nurseries. J. Trop. Pediatr. 2007, 53, 125–130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Berseth, C.L.; Van Aerde, J.E.; Gross, S.; Stolz, S.I.; Harris, C.L.; Hansen, J.W. Growth, efficacy, and safety of feeding an iron-fortified human milk fortifier. Pediatrics 2004, 114, e699–e706. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shah Sanket, D.; Dereddy, N.; Jones Tamekia, L.; Dhanireddy, R.; Talati Ajay, J. Early versus Delayed Human Milk Fortification in Very Low Birth Weight Infants-A Randomized Controlled Trial. J. Pediatr. 2016, 174, 126–131.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quigley, M.; Embleton, N.D.; McGuire, W. Formula versus donor breast milk for feeding preterm or low birth weight infants. Cochrane Database Syst. Rev. 2018, 6, CD002971. [Google Scholar] [CrossRef] [Scilit]
- Smith, H.A. Formula supplementation and the risk of cow’s milk allergy. Br. J. Midwifery 2012, 20, 345–350. [Google Scholar] [CrossRef] [Scilit]
- Bitton, A.; Ratcliffe, H.L.; Veillard, J.H.; Kress, D.H.; Barkley, S.; Kimball, M.; Secci, F.; Wong, E.; Basu, L.; Taylor, C.; et al. Primary health care as a foundation for strengthening health systems in low-and middle-income countries. J. Gen. Intern. Med. 2017, 32, 566–571. [Google Scholar] [CrossRef] [Scilit]
- Rowe, A.K.; Rowe, S.Y.; Peters, D.H.; Holloway, K.A.; Chalker, J.; Ross-Degnan, D. Effectiveness of strategies to improve health-care provider practices in low-income and middle-income countries: A systematic review. Lancet Glob. Health 2018, 6, e1163–e1175. [Google Scholar] [CrossRef] [Scilit]
- Special Section: Management of at Risk Mothers and Infants under 6 Months (MAMI). 2018. Available online: https://www.ennonline.net/attachments/2989/FEX_58_MAMI_special_section.pdf (accessed on 20 September 2018).
- Beck, K.; Kirk, C.M.; Bradford, J.; Mutaganzwa, C.; Nahimana, E.; Bigirumwami, O. The Paediatric Development Clinic: A model to improve medical, nutritional and developmental outcomes for high-risk children aged under-five in rural Rwanda. Field Exch. 2018, 58, 59. [Google Scholar]
- Kueter, A.M.; Burrell, A.; Butler, S.; Sarwar, M.; Rahaman, H. Piloting the C-MAMI approach in the Rohingya response in Bangladesh. Field Exch. 2018, 58, 51. [Google Scholar]
- Burrell, A.; Barthorp, H. GOAL’s experiences of management of at-risk mothers and infants (MAMI) programming in Ethiopia. Field Exch. 2020, 62, 30. [Google Scholar]
- Mandy, M.; Nyirenda, M. Developmental Origins of Health and Disease: The relevance to developing nations. Int. Health 2018, 10, 66–70. [Google Scholar] [CrossRef] [Scilit]
- Rowe, S.; Alexander, N.; Clydesdale, F.; Applebaum, R.; Atkinson, S.; Black, R.; Dwyer, J.; Hentges, E.; Higley, N.; Lefevre, M.; et al. Funding food science and nutrition research: Financial conflicts and scientific integrity. Nutr. Rev. 2009, 67, 264–272. [Google Scholar] [CrossRef] [Scilit] [PubMed]

© 2020 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).