


Abstract
Background: Transmetatarsal amputation (TMA) is a viable option to avoid major amputation and limb loss in patients with forefoot sepsis, infection, or tissue loss. However, TMAs are associated with a significant incidence of dehiscence, readmission, and reoperation rates ranging from 26% to 63%. To encourage tissue healing, neovascularization, and durable closure, a nonwoven, resorbable, synthetic hybrid-scale fiber matrix whose architecture is similar to native human extracellular matrix was used in an augmented closure technique. We comparatively evaluated clinical outcomes and complication rates in TMA procedures with and without augmented closure. Methods: A retrospective analysis of ten patients who underwent TMA with augmented closure using the synthetic matrix and ten patients who underwent TMA with standard primary closure was conducted. Results: After TMA, 80% of the patients who underwent augmented closure demonstrated complete wound healing compared with 60% of the control group. Patients undergoing augmented closure demonstrated five instances of wound dehiscence and 20% limb loss compared with eight instances of wound dehiscence and 40% limb loss in the control group. After TMA and augmented closure, patients required eight interventional procedures before complete healing compared with patients undergoing standard closure, who required 13 interventional procedures before complete healing. Conclusions: Augmented closure of surgical wounds after TMA using a synthetic hybrid-scale fiber matrix provided a unique means of reducing time to healing (18%), wound dehiscence (29%), number of procedures performed (39%), and rate of limb loss (20%). Augmented closure, therefore, offers a means of improving quality of life and reducing risk for patients undergoing TMA, and potentially reducing total cost of care.
Transmetatarsal amputation (TMA) is a viable option to avoid major amputation and limb loss in patients with forefoot sepsis, infection, or tissue loss [1,2]. Amputation is a major health risk in patients with secondary comorbidities, including diabetes mellitus (DM). Every 17 seconds, a patient is diagnosed as having diabetes in the United States, and one amputation occurs per every 230 Americans with diabetes [3]. Every 30 seconds, a leg is amputated in the world, and 85% of amputees are diabetic patients. The number of amputations has significantly increased in recent years, with a 50% increase from 2009 to 2015, especially in the younger patient population [3]. The 5-year mortality rate in patients with DM after the first ulceration is 40%, and this mortality rate increases to 52% to 80% after a major amputation [4–6]. These increasing trends for amputation and associated risks illustrate the importance of treating lower-extremity wounds and performing TMA to avoid limb loss. A total of 95% of patients with healed TMAs achieved some level of mobility, a rate that is significantly better compared with the mobility of patients who undergo major amputations [7]. However, TMAs are associated with a significant incidence of dehiscence, readmission, and reoperation rates ranging from 26% to 63% 8,9].
Healing TMA wounds and avoiding dehiscence can be challenging, especially for patients with comorbidities such as DM. The current standard of care to close TMAs is primary closure (suture only). However, this method has a high incidence of postoperative infection, wound dehiscence, limb loss, lengthy time to healing, and hospital mortality [2]. Other common complications after TMA are equinovarus deformity of the residual foot and recurrent ulceration [10,11]. The patient’s health status may affect the overall success of treating a TMA wound. Nonhealing TMAs are correlated with the presence of end-stage renal disease [2]. In addition, the literature reported a high complication rate (87.1%) after TMA in patients with diabetes and vasculopathy [2. Landry et al12] reported a 53% TMA healing rate and an 11% patient mortality rate before complete TMA healing, which emphasizes the low healing rate and high mortality associated with the current TMA treatment methods.
Instead of primary closure alone, an alternative method to close wounds after TMAs is an augmented closure approach using a synthetic hybrid-scale fiber matrix. The matrix is composed of synthetic, nonwoven, biocompatible, resorbable hybrid-scale fibers (varying diameters ranging from submicron scale to micro scale) whose structure and architecture are similar to native human extracellular matrix. The synthetic hybrid-scale fiber matrix provides a scaffold for early cell infiltration, accelerates neovascularization and granulation tissue formation, and supports epithelization of the wound bed before fully resorbing via hydrolysis [13].
The primary objective of this study was to comparatively evaluate clinical outcomes and complication rates in TMA procedures with and without augmented closure. The present study is the first known use of the novel technique of augmented closure to treat surgical wounds after TMA. The synthetic hybrid-scale fiber matrix was used with an augmented closure technique in an effort to encourage tissue healing, neovascularization, and durable closure. This is the first study evaluating the safety and efficiency of the synthetic hybrid-scale fiber matrix in the treatment of TMA wounds.
Methods
A retrospective clinical study was conducted at Rush University Medical Center (Oak Park and Chicago, Illinois locations). The control group consisted of ten patients who underwent TMA with standard primary closure before the development of the augmented closure technique. The experimental group consisted of ten consecutive patients who underwent TMA with augmented closure using the synthetic hybrid-scale fiber matrix by the same health-care professional team. The inclusion criteria for the patients were presence of TMA wounds, no known sensitivity to absorbable suture or synthetic wound matrices, and presence of type 2 DM. Patients with Charcot’s foot were excluded from this study. The presence of Charcot's foot significantly affects the healing rate, and in the case of failed wound healing, it is difficult to determine whether the failure was due to treatment inefficiency or to the presence of Charcot’s foot.
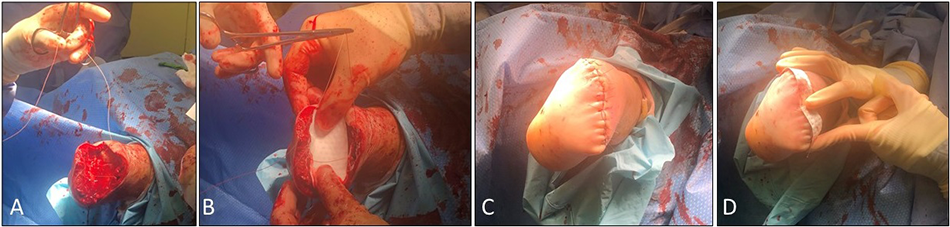
For patients in the experimental group of augmented closure of the wound, after the TMA (Fig. 1A), the synthetic hybrid-scale fiber matrix (Restrata; Acera Surgical Inc, St. Louis, Missouri) was placed in the wound bed deep to the subcutaneous tissue (Fig. 1B) to encourage granulation tissue formation, and the wound was closed using sutures (Fig. 1C). To support suture line healing and avoid wound dehiscence, a thin strip of the synthetic matrix was secured on the suture line using a suture or staple (Fig. 1D). Patients in the control group underwent TMA with primary closure. Casting was not performed in this study; however, nonweightbearing for at least 4 weeks was recommended. Postoperative outcome measures assessed included total number of procedures before healing, time to healing, incidence of wound dehiscence, and incidence of limb loss. Statistical analysis was performed to evaluate healing outcomes in the control and experimental groups.
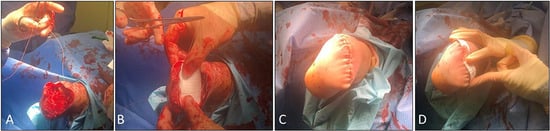
Figure 1.
Augmented closure of a representative transmetatarsal amputation wound using the synthetic hybrid-scale fiber matrix. A, The open wound after the transmetatarsal amputation. B, The synthetic matrix was placed on the wound bed. C, The wound was closed using sutures. D, A thin strip of the synthetic matrix was placed on the suture line.
Results
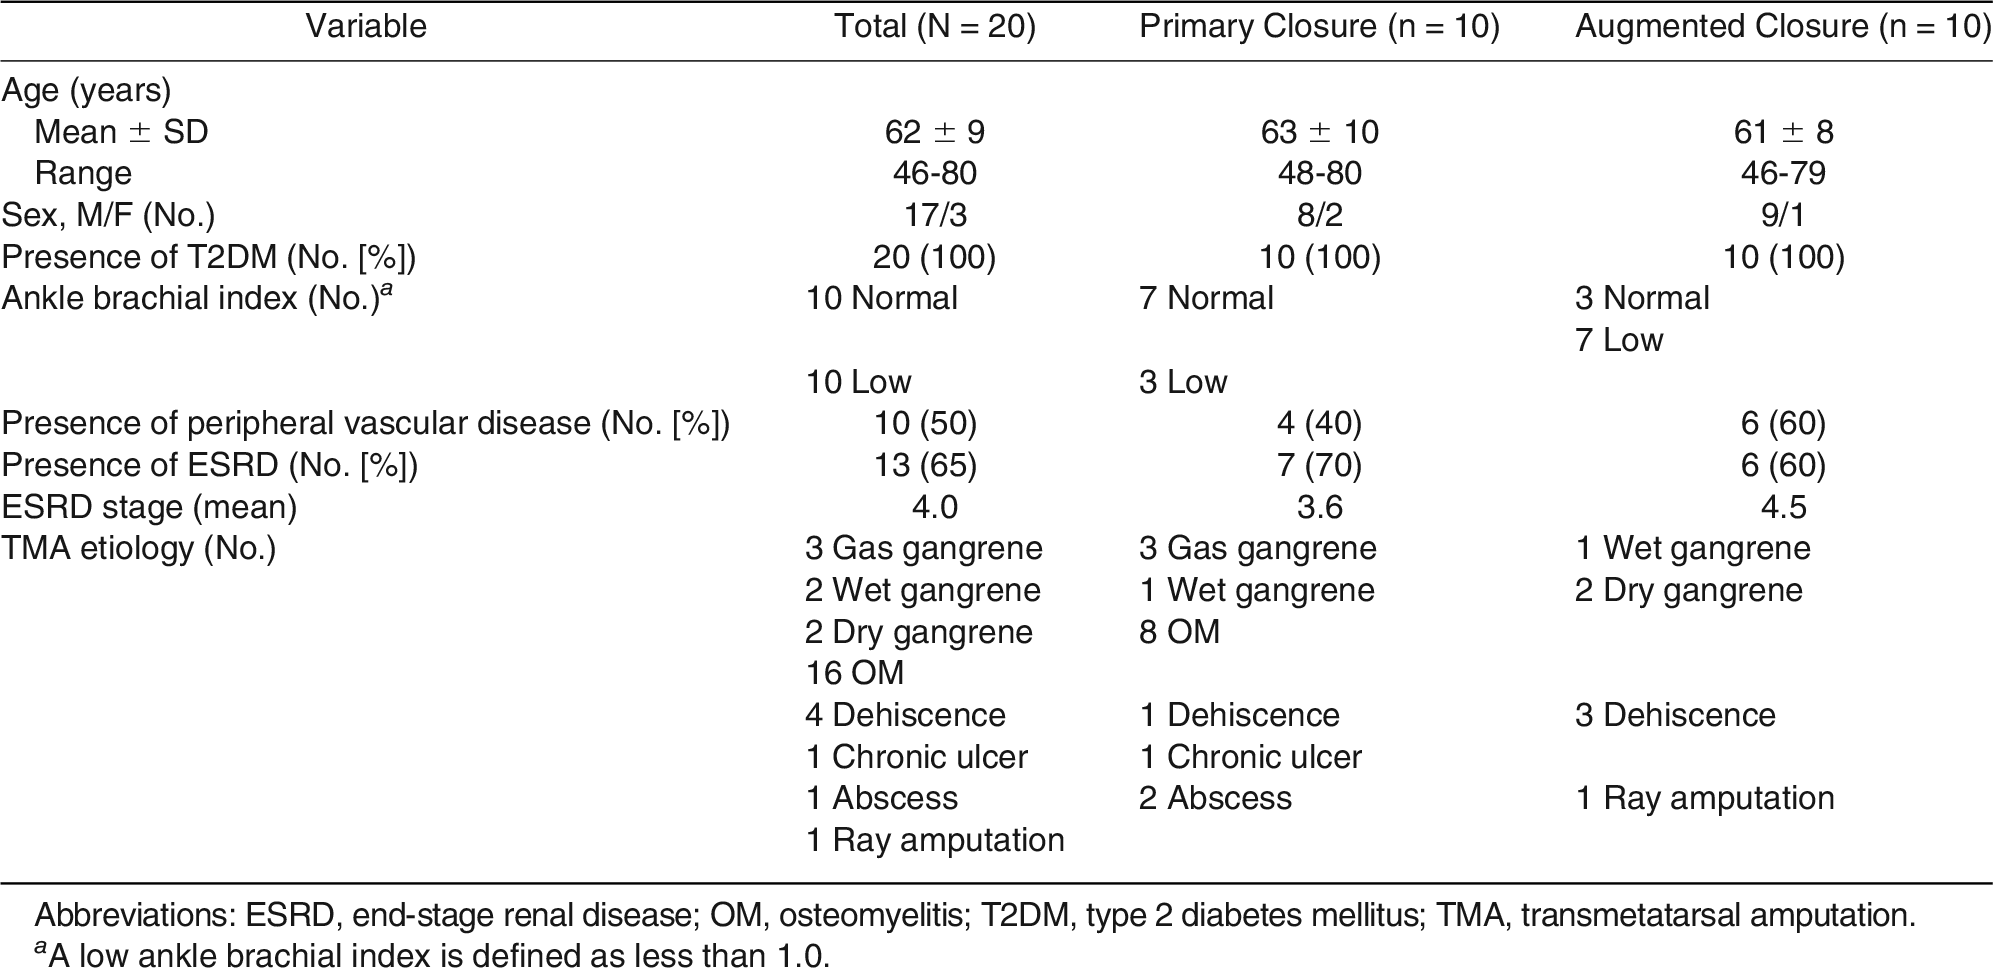
In this study, patients had major comorbidities, including type 2 DM (100%), peripheral vascular disease (50%), and end-stage renal disease (65%). Patient demographics are presented in Table 1.

Table 1.
Patient Demographics
Ten TMA wounds underwent augmented closure using the synthetic hybrid-scale fiber matrix, and routine follow-up was completed to evaluate wound healing and manage wound complications (Table 2). A total of 80% of the patients who underwent augmented closure demonstrated complete wound healing, with a mean ± SD healing period of 70 ± 53 days (Figure 2). In contrast, the healing rate for the control group was lower at 60%, with a mean ± SD healing period of 85 ± 57 days.
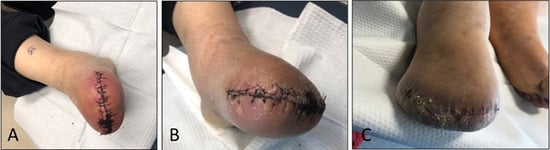
Figure 2.
Healing of a representative transmetatarsal amputation wound 9 days (A), 15 days (B), and 45 days (healed) (C) after augmented closure with the synthetic matrix.
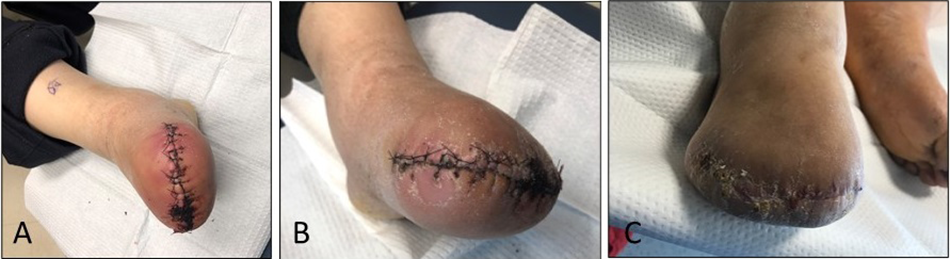
Table 2.
Comparison of Wound-Healing Characteristics Using Augmented Closure and Primary Closure Approaches
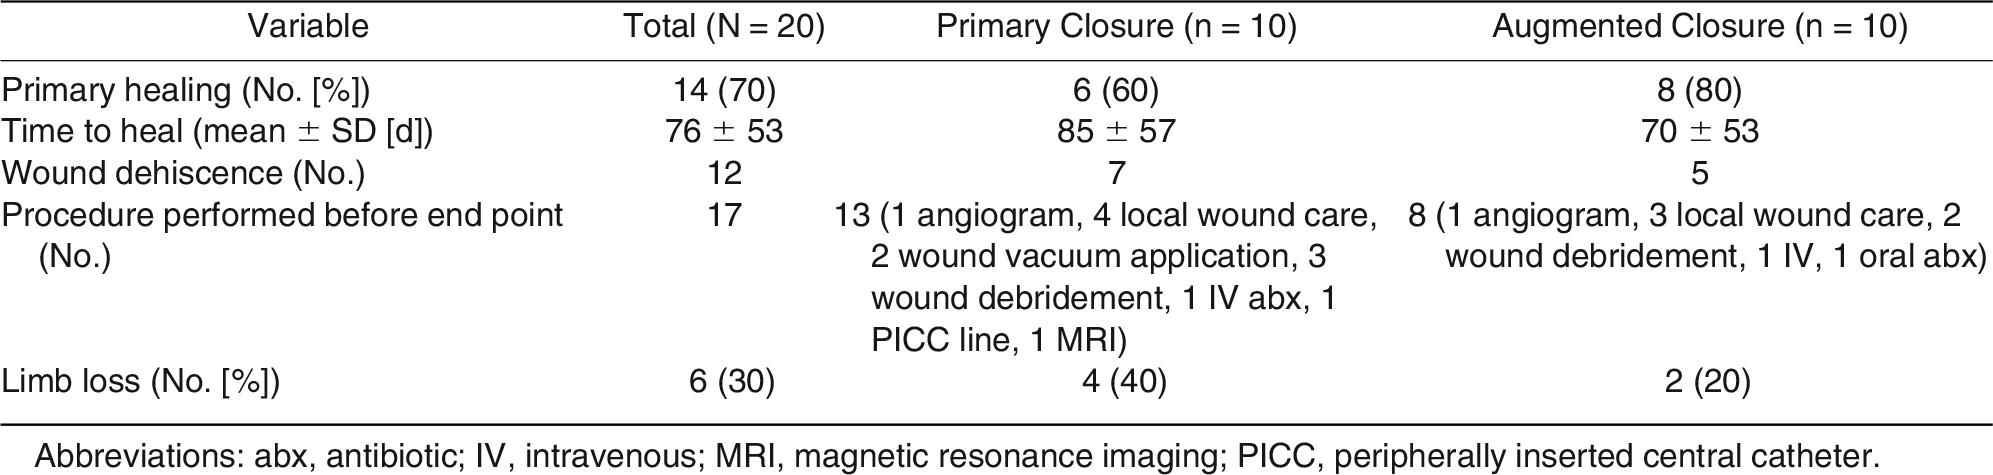
Seven cases of wound dehiscence were reported for TMA wounds closed with suture only and required additional care, and only four of seven dehisced wounds healed. In wounds treated using the synthetic hybrid-scale fiber matrix, five cases of wound dehiscence were observed, and four wounds completely healed with no signs of dehiscence. Only one of five dehisced wounds resulted in amputation.
Patients in the experimental group required eight interventional procedures and patients in the control group required 13 interventional procedures before complete healing (Table 2). Overall, treatment of TMA wounds with augmented closure was more successful, with more proximal amputation required in only 20% of patients, whereas performing the standard closure method on TMA wounds resulted in a 40% proximal amputation rate.
The results of this study showed a trend of lower incidence of limb loss and wound complications after augmented closure with the synthetic hybrid-scale fiber matrix compared with the standard primary closure. However, given the small sample size, the conducted statistical analyses showed no statistically significant difference in healing outcomes between the control and experimental groups.
Discussion
Leland McKittrick first described the TMA to treat gangrene in a patient with a diabetic foot ulcer [14]. This treatment replaced major amputation in many patients to salvage the limb. However, the presence of vascular diseases makes the healing of TMA wounds challenging. Moreover, it has been shown that the healing rate of TMA wounds in patients with peripheral vascular disease decreased when DM was present and resulted in a higher number of amputations [8]. Due to multiple comorbidities of this population, it is challenging to achieve complete wound healing after TMA and avoid limb loss. Patients in this study fall in this difficult-to-heal population diagnosed as having type 2 DM and either peripheral vascular disease or end-stage renal disease and required TMA operation.
It has been previously reported that the average healing period after TMA of the diabetic foot was 84 days [15]. This is consistent with the observation in the present study where the mean ± SD healing duration using the standard primary closure was 85 ± 57 days. In contrast, in this study, the mean ± SD healing period of TMA wounds with augmented closure using the synthetic hybrid-scale fiber matrix was faster at 70 ± 53 days, a reduction of 18% compared with control TMA wounds closed with suture only. Note that the average healing duration of the patients in the primary closure group significantly increased due to a 190-day healing period for one of the patients. Use of the synthetic hybrid-scale fiber matrix contributed to the shorter healing period likely by encouraging faster granulation and neovascularization in the wound bed, consistent with what was reported in an animal study [16]. A shorter healing period has several health-care–related benefits, including shorter patient recovery, quicker mobility gain, and improved quality of life.
Post-TMA complications, including wound dehiscence, infection, and necrosis, are common and create a great burden on the health-care system due to the need for hospital readmission and additional procedures, including wound debridement, vascular intervention, and limb amputation [2], along with additional ongoing care.
In this study, seven cases of wound dehiscence were reported for 10 TMA wounds closed with the suture only. Augmented closure of TMA wounds with the synthetic matrix reduced the complication rate by 29% (five reports). One possible explanation for the lower occurrence of wound dehiscence when performing augmented closure may be use of the synthetic hybrid-scale fiber matrix as a reinforcement for the suture line to ensure lasting wound closure. Moreover, the need for additional procedures before wound healing decreased by 39% when wounds were treated by the synthetic matrix. The reduced rate of wound dehiscence and reduced need for additional care after TMA surgery benefits both the health-care system and patients. These reduced rates decrease the economic burden by avoiding additional procedures and offer patients a shorter healing period with fewer complications and postoperative procedures.
Thomas et al [7] retrospectively reviewed 41 patients who underwent TMA and found the post-TMA healing rate to be 46% and a mortality rate of 17%. The progression of gangrene or cellulitis was reported as the main reason for failed healing and the need for limb amputation. In another retrospective study,12 ]healing and mortality rates of 53% and 11%, respectively, were reported. A similar healing rate (54%) of TMA wounds was reported in a retrospective study including 46 patients.15 Nonhealing TMAs commonly result in major amputations, which add financial burden and lead to patient immobility, poor quality of life, and increased mortality. In comparison, in the control group of the present study, 60% of patients healed and the limb loss rate was 40%, a slightly better healing rate than that reported previously in the literature [7,12,15]. Augmented closure of TMA wound with the synthetic hybrid-scale matrix achieved an 80% healing rate, and only 20% of the patients needed major amputation, a 20% better limb salvage rate compared with patients who underwent primary closure only. When the synthetic hybrid-scale fiber matrix is applied to the wound site, cells infiltrate the porous structure and collagen deposition occurs in the matrix, which progresses to granulation tissue formation, neovascularization of the wound bed, and eventually wound healing and full reepithelialization. A limitation of this study was the lack of randomization process and the small number of enrolled patients in both groups. This limited the ability to achieve a possible statistically significant difference in the experimental group compared with the control group. Moreover, another limitation was that the study was conducted at a single site with one health-care professional team. One potential confounding factor in this study may be the experience of the clinicians. Since the patients in the control group were treated initially, the increased experience level of the clinicians when treating the experimental group may have affected the study outcome. Overall, this report was a pilot study. The positive outcomes observed justify future studies with larger patient populations to further investigate the efficacy of the synthetic hybrid-scale fiber matrix to treat surgical wounds after TMA.
Conclusions
In this study, augmented closure of surgical wounds after TMA using a synthetic hybrid-scale fiber matrix provided a unique means of reducing time to healing (18%), wound dehiscence (29%), number of procedures performed (39%), and limb loss (20%). Therefore, the results suggest that augmented closure may offer a means of improving quality of life and reducing risk for patients undergoing TMA. Overall, augmented closure using the synthetic hybrid-scale matrix is a novel treatment to be included in the clinical approach to TMA wounds.
Financial Disclosure
Acera Surgical, producer of the Restrata graft, provided the grafts used for the study.
Conflict of Interest
Dr. Alexander is a paid consultant for Acera Surgical.
References
- Ammendola M, Sacco R, Butrico L, et al: The care of transmetatarsal amputation in diabetic foot gangrene. Int Wound J 14: 9, 2017.
- Pollard J, Hamilton G, Rush S, et al: Mortality and morbidity after transmetatarsal amputation: retrospective review of 101 cases. J Foot Ankle Surg 45: 91, 2006.
- Fakorede F: Increasing awareness this national diabetes month can save limbs and lives. AJMC Web site. Available at: https://www.ajmc.com/view/increasing-awareness-this-national-diabetes-month-can-save-limbs-and-lives. Published November 29, 2018.
- Thorud J, Plemmons B, Buckley C, et al: Mortality after nontraumatic major amputation among patients with diabetes and peripheral vascular disease: a systematic review. J Foot Ankle Surg 55: 591, 2016.
- Jupiter D, Throud J, Buckley C, et al: The impact of foot ulceration and amputation on mortality in diabetic patients: I. From ulceration to death, a systematic review. Int Wound J 13: 892, 2016.
- Thorud JC, Seidel JL: A closer look at mortality after lower extremity amputation. Podiatry Today 3: 12, 2018.
- Thomas SR, Perkins JM, Magee TR, et al: Transmetatarsal amputation: an 8-year experience. Ann R Coll Surg Engl 83: 164, 2011.
- O'Brien P, Cox M, Shortell C, et al: Risk factors for early failure of surgical amputations: an analysis of 8,878 isolated lower extremity amputation procedures. J Am Coll Surg 216: 836, 2013.
- Hosch J, Quiroga C, Bosma J, et al: Outcomes of transmetatarsal amputations in patients with diabetes mellitus. J Foot Ankle Surg 36: 430, 1997.
- Wallace GF, Stapleton JJ: Transmetatarsal amputations. Clin Podiatr Med Surg 22: 365, 2005.
- Clark GD, Lui E, Cook KD: Tendon balancing in pedal amputations. Clin Podiatr Med Surg 22: 447, 2005.
- Landry G, Silverman D, Liem T, et al: Predictors of healing and functional outcome following transmetatarsal amputations. Arch Surg 146: 1005, 2011.
- MacEwan M, MacEwan S, Kovacs T, et al: What makes the optimal wound healing material? a review of current science and introduction of a synthetic nanofabricated wound care scaffold. Cureus 9: e1736, 2017.
- McKittrick LS, McKittrick JB, Risley TS: Transmetatarsal amputation for infection or gangrene in patients with diabetes mellitus. Ann Surg 130: 826, 1949.
- Dudkiewicz I, Schwarz O, Heim M, et al: Trans-metatarsal amputation in patients with a diabetic foot: reviewing 10 years experience. Foot 19: 201, 2009.
- MacEwan MR, MacEwan S, Wright AP, et al: Comparison of a fully synthetic electrospun matrix to a bi-layered xenograft in healing full thickness cutaneous wounds in a porcine model. Cureus 9: e1614, 2017.
© 2022 American Podiatric Medical Association