

Omission of Axillary Lymph Node Dissection in Breast Cancer Patients with 1–2 Positive Sentinel Lymph Nodes: A Multicenter Real-World Cohort Study in a Chinese Population

 , and
Simple Summary
Abstract
1. Introduction
2. Methods
2.1. Patients and Data Source
2.2. Axillary Surgical Management and Pathological Assessment
2.3. Definition of Nodal Yield and Axillary Tumor Burden
2.4. Adjuvant Radiotherapy
2.5. Outcomes and Follow-Up
2.6. Statistical Analysis
3. Results
3.1. Patients
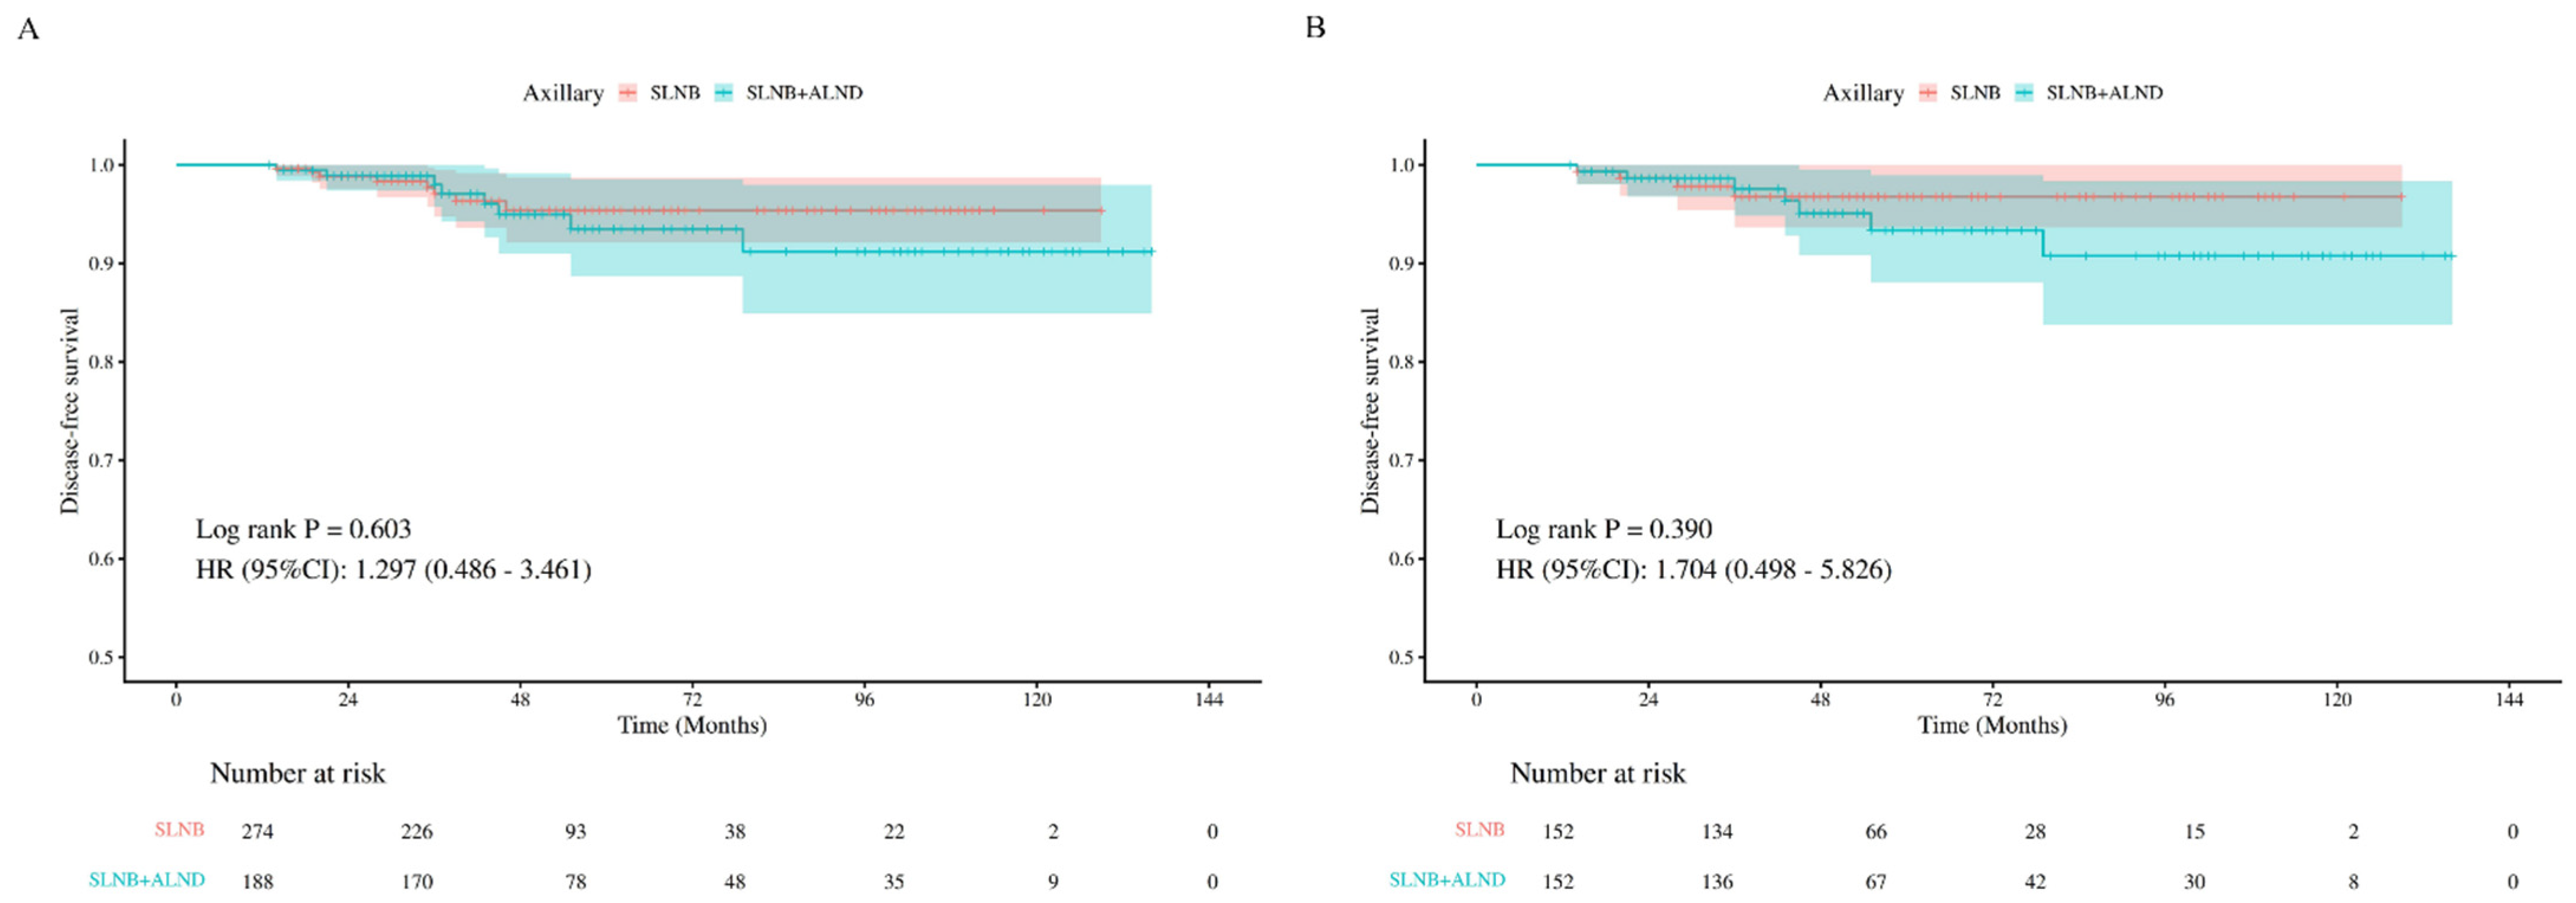
3.2. Survival Analysis
3.3. Factors Influencing Decision-Making
4. Discussion
Supplementary Materials
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
References
- Galimberti, V.; Cole, B.F.; Zurrida, S.; Viale, G.; Luini, A.; Veronesi, P.; Baratella, P.; Chifu, C.; Sargenti, M.; Intra, M.; et al. Axillary dissection versus no axillary dissection in patients with sentinel-node micrometastases (IBCSG 23-01): A phase 3 randomised controlled trial. Lancet Oncol. 2013, 14, 297–305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Galimberti, V.; Cole, B.F.; Viale, G.; Veronesi, P.; Vicini, E.; Intra, M.; Mazzarol, G.; Massarut, S.; Zgajnar, J.; Taffurelli, M.; et al. Axillary dissection versus no axillary dissection in patients with breast cancer and sentinel-node micrometastases (IBCSG 23-01): 10-year follow-up of a randomised, controlled phase 3 trial. Lancet Oncol. 2018, 19, 1385–1393. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Giuliano, A.E.; McCall, L.; Beitsch, P.; Whitworth, P.W.; Blumencranz, P.; Leitch, A.M.; Saha, S.; Hunt, K.K.; Morrow, M.; Ballman, K. Locoregional recurrence after sentinel lymph node dissection with or without axillary dissection in patients with sentinel lymph node metastases: The American College of Surgeons Oncology Group Z0011 randomized trial. Ann. Surg. 2010, 252, 426–433. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lyman, G.H.; Somerfield, M.R.; Bosserman, L.D.; Perkins, C.L.; Weaver, D.L.; Giuliano, A.E. Sentinel Lymph Node Biopsy for Patients with Early-Stage Breast Cancer: American Society of Clinical Oncology Clinical Practice Guideline Update. J. Clin. Oncol. Off. J. Am. Soc. Clin. Oncol. 2017, 35, 561–564. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maramara, T.; Hsieh, M.C.; Janjua, M.; Li, T.; Wu, X.C.; Williams, M.; Shoup, M.; Chu, Q.D. Adherence Rate to Alliance for Clinical Trials in Oncology Z0011 Trial Based on Breast Cancer Subtype. J. Am. Coll. Surg. 2024, 238, 656–667. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peng, Y.; Liu, M.; Li, X.; Tong, F.; Cao, Y.; Liu, P.; Zhou, B.; Liu, H.; Cheng, L.; Guo, J.; et al. Application of the ACOSOG Z0011 criteria to Chinese patients with breast cancer: A prospective study. World J. Surg. Oncol. 2021, 19, 128. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Donker, M.; van Tienhoven, G.; Straver, M.E.; Meijnen, P.; van de Velde, C.J.H.; Mansel, R.E.; Cataliotti, L.; Westenberg, A.H.; Klinkenbijl, J.H.G.; Orzalesi, L.; et al. Radiotherapy or surgery of the axilla after a positive sentinel node in breast cancer (EORTC 10981-22023 AMAROS): A randomised, multicentre, open-label, phase 3 non-inferiority trial. Lancet Oncol. 2014, 15, 1303–1310. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Boniface, J.; Filtenborg, T.T.; Ryden, L.; Szulkin, R.; Reimer, T.; Kuhn, T.; Kontos, M.; Gentilini, O.D.; Olofsson, B.R.; Sund, M.; et al. Omitting Axillary Dissection in Breast Cancer with Sentinel-Node Metastases. N. Engl. J. Med. 2024, 390, 1163–1175. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Appelgren, M.; Sackey, H.; Wengstr, M.Y.; Johansson, K.; Ahlgren, J.; Andersson, Y.; Bergkvist, L.; Frisell, J.; Lundstedt, D.; Rydén, L.; et al. Patient-reported outcomes one year after positive sentinel lymph node biopsy with or without axillary lymph node dissection in the randomized SENOMAC trial. Breast 2022, 63, 16–23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lai, H.W.; Chen, Y.A.; Tam, K.W. Surgical treatments for older breast cancer patients: A systematic review and meta-analysis of real-world evidence. Surgery 2024, 176, 1576–1590. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, K.U.; Somerfield, M.R.; Anne, N.; Brackstone, M.; Conlin, A.K.; Couto, H.L.; Dengel, L.T.; Eisen, A.; Harvey, B.E.; Hawley, J.; et al. Sentinel Lymph Node Biopsy in Early-Stage Breast Cancer: ASCO Guideline Update. J. Clin. Oncol. 2025, 43, 1720–1741. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, X.; Gao, Y.; Yang, X.; Kong, X.; Wang, Z.; Fang, Y.; Wang, J. Omitting ALND Is Not Safe for a Cohort of Early-Stage Breast Cancer Patients with 1-2 SLNs Macro-Metastases and Breast-Conserving Therapy: A Single-Center Retrospective Study. Iran. J. Public Health 2020, 49, 1262–1268. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yu, Y.; Wang, Z.; Wei, Z.; Yu, B.; Shen, P.; Yan, Y.; You, W. Development and validation of nomograms for predicting axillary non-SLN metastases in breast cancer patients with 1–2 positive sentinel lymph node macro-metastases: A retrospective analysis of two independent cohorts. BMC Cancer 2021, 21, 466. [Google Scholar] [CrossRef] [Scilit] [PubMed]

| Variables | Total (n = 462) | SLNB + ALND (n = 188) | SLNB (n = 274) | p |
|---|---|---|---|---|
| Age, n (%) | 0.750 | |||
| ≤50 y | 249 (53.90) | 103 (54.79) | 146 (53.28) | |
| >50 y | 213 (46.10) | 85 (45.21) | 128 (46.72) | |
| BMI, n (%) | 0.259 | |||
| <25 kg/m2 | 335 (72.51) | 131 (69.68) | 204 (74.45) | |
| ≥25 kg/m2 | 127 (27.49) | 57 (30.32) | 70 (25.55) | |
| Grade, n (%) | 0.196 | |||
| I | 26 (5.63) | 15 (7.98) | 11 (4.01) | |
| II | 301 (65.15) | 114 (60.64) | 187 (68.25) | |
| III | 106 (22.94) | 47 (25.00) | 59 (21.53) | |
| Unknow | 29 (6.28) | 12 (6.38) | 17 (6.20) | |
| LVI, n (%) | 0.278 | |||
| Absent | 398 (86.15) | 158 (84.04) | 240 (87.59) | |
| Present | 64 (13.85) | 30 (15.96) | 34 (12.41) | |
| Chemotherapy, n (%) | 0.002 | |||
| No | 61 (13.20) | 14 (7.45) | 47 (17.15) | |
| Yes | 401 (86.80) | 174 (92.55) | 227 (82.85) | |
| NSLNM, n (%) | <0.001 | |||
| Micrometastases | 53 (11.47) | 3 (1.60) | 50 (18.25) | |
| 1 | 333 (72.08) | 139 (73.94) | 194 (70.80) | |
| 2 | 76 (16.45) | 46 (24.47) | 30 (10.95) | |
| PSLNM, n (%) | <0.001 | |||
| ≤1/3 | 321 (69.48) | 102 (54.26) | 219 (79.93) | |
| >1/3 | 141 (30.52) | 86 (45.74) | 55 (20.07) | |
| Ki67, n (%) | 0.855 | |||
| ≤14% | 162 (35.06) | 65 (34.57) | 97 (35.40) | |
| >14% | 300 (64.94) | 123 (65.43) | 177 (64.60) | |
| Molecular Subtype, n (%) | 0.831 | |||
| HR+/HER2− | 403 (87.23) | 163 (86.70) | 240 (87.59) | |
| HER2+ | 49 (10.61) | 20 (10.64) | 29 (10.58) | |
| TNBC | 10 (2.16) | 5 (2.66) | 5 (1.82) | |
| Clinical T stage, n (%) | 0.333 | |||
| T1 | 326 (70.56) | 128 (68.09) | 198 (72.26) | |
| T2 | 136 (29.44) | 60 (31.91) | 76 (27.74) | |
| Anti-HER2 therapy, n (%) | 0.614 | |||
| No | 412 (89.18) | 166 (88.30) | 246 (89.78) | |
| Yes | 50 (10.82) | 22 (11.70) | 28 (10.22) | |
| Endocrine therapy, n (%) | 0.071 | |||
| No | 16 (3.46) | 10 (5.32) | 6 (2.19) | |
| Yes | 446 (96.54) | 178 (94.68) | 268 (97.81) |
| Variables | Univariate | Multivariable | ||||
|---|---|---|---|---|---|---|
| HR | 95% CI | p Value | HR | 95% CI | p Value | |
| Axillary treatment | ||||||
| SLNB | Ref | Ref | ||||
| SLNB + ALND | 1.3 | 0.49~3.46 | 0.604 | 1.32 | 0.42~4.12 | 0.635 |
| BMI | ||||||
| <25 kg/m2 | Ref | Ref | ||||
| ≥25 kg/m2 | 0.65 | 0.18~2.28 | 0.499 | 0.6 | 0.16~2.18 | 0.433 |
| Age | ||||||
| ≤50 y | Ref | Ref | ||||
| >50 y | 0.49 | 0.17~1.42 | 0.133 | 0.56 | 0.19~1.72 | 0.313 |
| Grade | ||||||
| I | Ref | Ref | ||||
| II | 0.43 | 0.05~3.72 | 0.446 | 0.38 | 0.04~3.50 | 0.391 |
| III | 1. 75 | 0.22~12.88 | 0.595 | 1.73 | 0.18~17.13 | 0.637 |
| LVI | ||||||
| Absent | Ref | Ref | ||||
| Present | 3.12 | 1.08~9.06 | 0.036 | 3.19 | 1.01~10.04 | 0.047 |
| No. of positive lymph node | ||||||
| 1 | Ref | Ref | ||||
| 2 | 0.61 | 0.14~2.72 | 0.516 | 0.45 | 0.09~2.18 | 0.321 |
| ≥3 | 2.66 | 0.59~11.9 | 0.201 | 2.59 | 0.43~15.58 | 0.297 |
| Clinical T stage | ||||||
| T1 | Ref | Ref | ||||
| T2 | 0.54 | 0.15~1.91 | 0.341 | 0.31 | 0.08~1.15 | 0.081 |
| Subtype | ||||||
| HR+/HER2− | Ref | Ref | ||||
| Her2+ | 2.05 | 0.58~7.27 | 0.267 | 1.24 | 0.32~4.77 | 0.757 |
| TNBC | 2.29 | 0.29~17.94 | 0.429 | 1.56 | 0.18~13.86 | 0.689 |
| Ki67 | ||||||
| ≤14% | Ref | Ref | ||||
| >14% | 2.55 | 0.73~8.95 | 0.144 | 1.71 | 0.43~6.82 | 0.445 |
| Variables | Univariate | Multivariate | ||
|---|---|---|---|---|
| OR (95% CI) | p | OR (95% CI) | p | |
| Age | ||||
| ≤50 y | 1.00 (Reference) | |||
| >50 y | 1.06 (0.73~1.54) | 0.750 | ||
| BMI | ||||
| <25 kg/m2 | 1.00 (Reference) | |||
| ≥25 kg/m2 | 0.79 (0.52~1.19) | 0.260 | ||
| Clinical T stage | ||||
| T1 | 1.00 (Reference) | |||
| T2 | 0.82 (0.55~1.23) | 0.333 | ||
| NSLNM | ||||
| micrometastases | 1.00 (Reference) | |||
| 1 | 0.08 (0.03~0.27) | <0.001 | 0.08 (0.03~0.28) | <0.001 |
| 2 | 0.04 (0.01~0.14) | <0.001 | 0.08 (0.02~0.31) | <0.001 |
| PSLNM | ||||
| ≤1/3 | 1.00 (Reference) | 1.00 (Reference) | ||
| >1/3 | 0.30 (0.20~0.45) | <0.001 | 0.32 (0.19~0.54) | <0.001 |
| Ki67 | ||||
| <14% | 1.00 (Reference) | |||
| ≥14% | 0.96 (0.65~1.42) | 0.855 | ||
| Subtype | ||||
| HR+/HER2− | 1.00 (Reference) | |||
| HER2+ | 0.98 (0.54~1.80) | 0.960 | ||
| TNBC | 0.68 (0.19~2.38) | 0.546 | ||
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Hong, C.; Chen, J.; Chen, Y.; Li, L.; Du, X.; Chen, D.; Lian, W. Omission of Axillary Lymph Node Dissection in Breast Cancer Patients with 1–2 Positive Sentinel Lymph Nodes: A Multicenter Real-World Cohort Study in a Chinese Population. Curr. Oncol. 2026, 33, 247. https://doi.org/10.3390/curroncol33050247
Hong C, Chen J, Chen Y, Li L, Du X, Chen D, Lian W. Omission of Axillary Lymph Node Dissection in Breast Cancer Patients with 1–2 Positive Sentinel Lymph Nodes: A Multicenter Real-World Cohort Study in a Chinese Population. Current Oncology. 2026; 33(5):247. https://doi.org/10.3390/curroncol33050247
Chicago/Turabian StyleHong, Chengye, Jianhui Chen, Yongwu Chen, Liangqiang Li, Xianqiang Du, Debo Chen, and Weibin Lian. 2026. "Omission of Axillary Lymph Node Dissection in Breast Cancer Patients with 1–2 Positive Sentinel Lymph Nodes: A Multicenter Real-World Cohort Study in a Chinese Population" Current Oncology 33, no. 5: 247. https://doi.org/10.3390/curroncol33050247
APA StyleHong, C., Chen, J., Chen, Y., Li, L., Du, X., Chen, D., & Lian, W. (2026). Omission of Axillary Lymph Node Dissection in Breast Cancer Patients with 1–2 Positive Sentinel Lymph Nodes: A Multicenter Real-World Cohort Study in a Chinese Population. Current Oncology, 33(5), 247. https://doi.org/10.3390/curroncol33050247

