


Abstract
The peritoneum is an unusual site of metastases from lung cancer, and optimal management at the moment remains unclear and mostly based on palliative strategies. Therefore, the aim of the study was to investigate demographic characteristics, management and overall survival of patients with peritoneal metastases from lung cancer (PCLC). A PRISMA-compliant systematic review and pooled analysis was performed searching all English studies published until December 2022. PROSPERO, CRD42022349362. Inclusion criteria were original articles including patients with peritoneal carcinomatosis from lung cancer, specifying at least one outcome of interest. Exclusion criteria were being unable to retrieve patient data from articles, and the same patient series included in different studies. Among 1746 studies imported for screening, twenty-one were included (2783 patients). Mean overall survival was between 0.5 and 5 months after peritoneal carcinomatosis diagnosis and 9 and 21 months from lung cancer diagnosis. In total, 27% of patients underwent first-line or palliative chemotherapy and 7% of them surgery. Management differs significantly among published studies. The literature on PCLC is scarce. Its incidence is low but appears to be substantially rising and is likely to be an underestimation. Prognosis is very poor and therapeutic strategies have been limited and used in a minority of patients. Subcategories of PCLC patients may have an improved prognosis and may benefit from an aggressive oncological approach, including cytoreductive surgery. Further investigation would be needed in this regard.
1. Introduction
Lung cancer (LC) is one of the most common malignancies in the world today. For instance, the American Cancer Society estimated that the statistics for lung cancer in the United States for 2022 were 236,740 new cases and about 130,180 deaths [1].
Metastatic disease is already present at diagnosis in about 40% of patients with the most common sites being bone, liver, brain, and adrenal gland, while gastrointestinal sites are much more uncommon [2,3]. Peritoneal carcinomatosis from lung cancer (PCLC) is indeed a quite rare occurrence, often perceived as a sign of end-life stage, also demonstrated by poor prognostic outcomes [4,5,6]. However, new molecular targets and therapies, and the increasing incidence at earlier stages due to the increased awareness and accuracy of diagnostic methods are now more dutifully raising questions on management and possible treatment [7,8,9,10].
At the moment, the literature is scarce with low-grades of evidence and few patients included, and no published guideline suggesting a specific pathway other than the standard care of lung cancer metastatic disease. Furthermore, no systematic review on the topic exists nor does a pooled analysis of PCLC patients.
Therefore, the aim of this systematic review is to investigate characteristics, management and overall survival of PCLC patients.
2. Materials and Methods
This is a systematic literature review performed in accordance with the current Preferred Reporting Items for Systematic Reviews and Meta-analyses (PRISMA) guidelines [11].
This review was registered in PROSPERO CRD42022349362.
2.1. Search Strategy
Searches were conducted for all English language full-text articles published until December 2022. The following database sources were searched: PubMed (MEDLINE), Cochrane Library, Web of Science.
The following free term combination was used: (peritoneal carcinomatosis), (peritoneal neoplasm), (gastrointestinal metastases), (lung cancer), (lung neoplasia).
Records were screened for relevance based on their title and abstract, and successively the full text of the remaining articles was analysed. Furthermore, the references list of each selected article was analysed to identify additional relevant studies.
2.2. Study Selection
Inclusion criteria were as follows: (1) original articles (retrospective, prospective, randomised clinical trials), case series and report; (2) articles including patients with PC from LC; (3) articles specifying at least one outcome of interest.
Exclusion criteria were as follows: (1) unable to retrieve patient data from articles; (2) meeting abstract; (3) same patient series included in different studies. In the latter case, only the most recent article was included.
2.3. Data Extraction and Synthesis
Two authors (A.F. and L.S.) independently screened each record from full text articles for eligibility, and extracted the data, including quality analysis. Disagreement was resolved by discussion and consensus; if no agreement was reached, a third author was consulted (S.S.).
2.4. Outcome Measures
Primary outcomes were patient management and overall survival from LC diagnosis and PM onset. Patient management included rate of chemotherapy and surgery and specific chemotherapy regimen utilised.
Baseline characteristics analysed were age, sex, ascites, former smoker status, PC incidence in lung cancer, time from LC diagnosis to PC, stage at diagnosis, presence and type of other metastases, tumour histology and mutations.
Additionally, a sub-analysis comparing synchronous versus metachronous PCLC patient characteristics was performed.
2.5. Quality Assessment
Study quality was assessed using Newcastle Ottawa Scale (NOS). NOS is an assessment tool used to measure the quality of non-randomized studies included in systematic reviews. Each article was assessed for 9 parameters, each awarding up to 1 point, with a maximum total score of 9 points [12].
2.6. Statistical Analysis
Categorical data are reported as absolute numbers with percentage; continuous data are reported as median with ranges. Data were pooled and descriptive statistics were produced from the dataset. A pooled analysis was performed where categorical and continuous data were reported as median, range and percentages. There was no comparative statistical analysis.
3. Results
3.1. Systematic Search
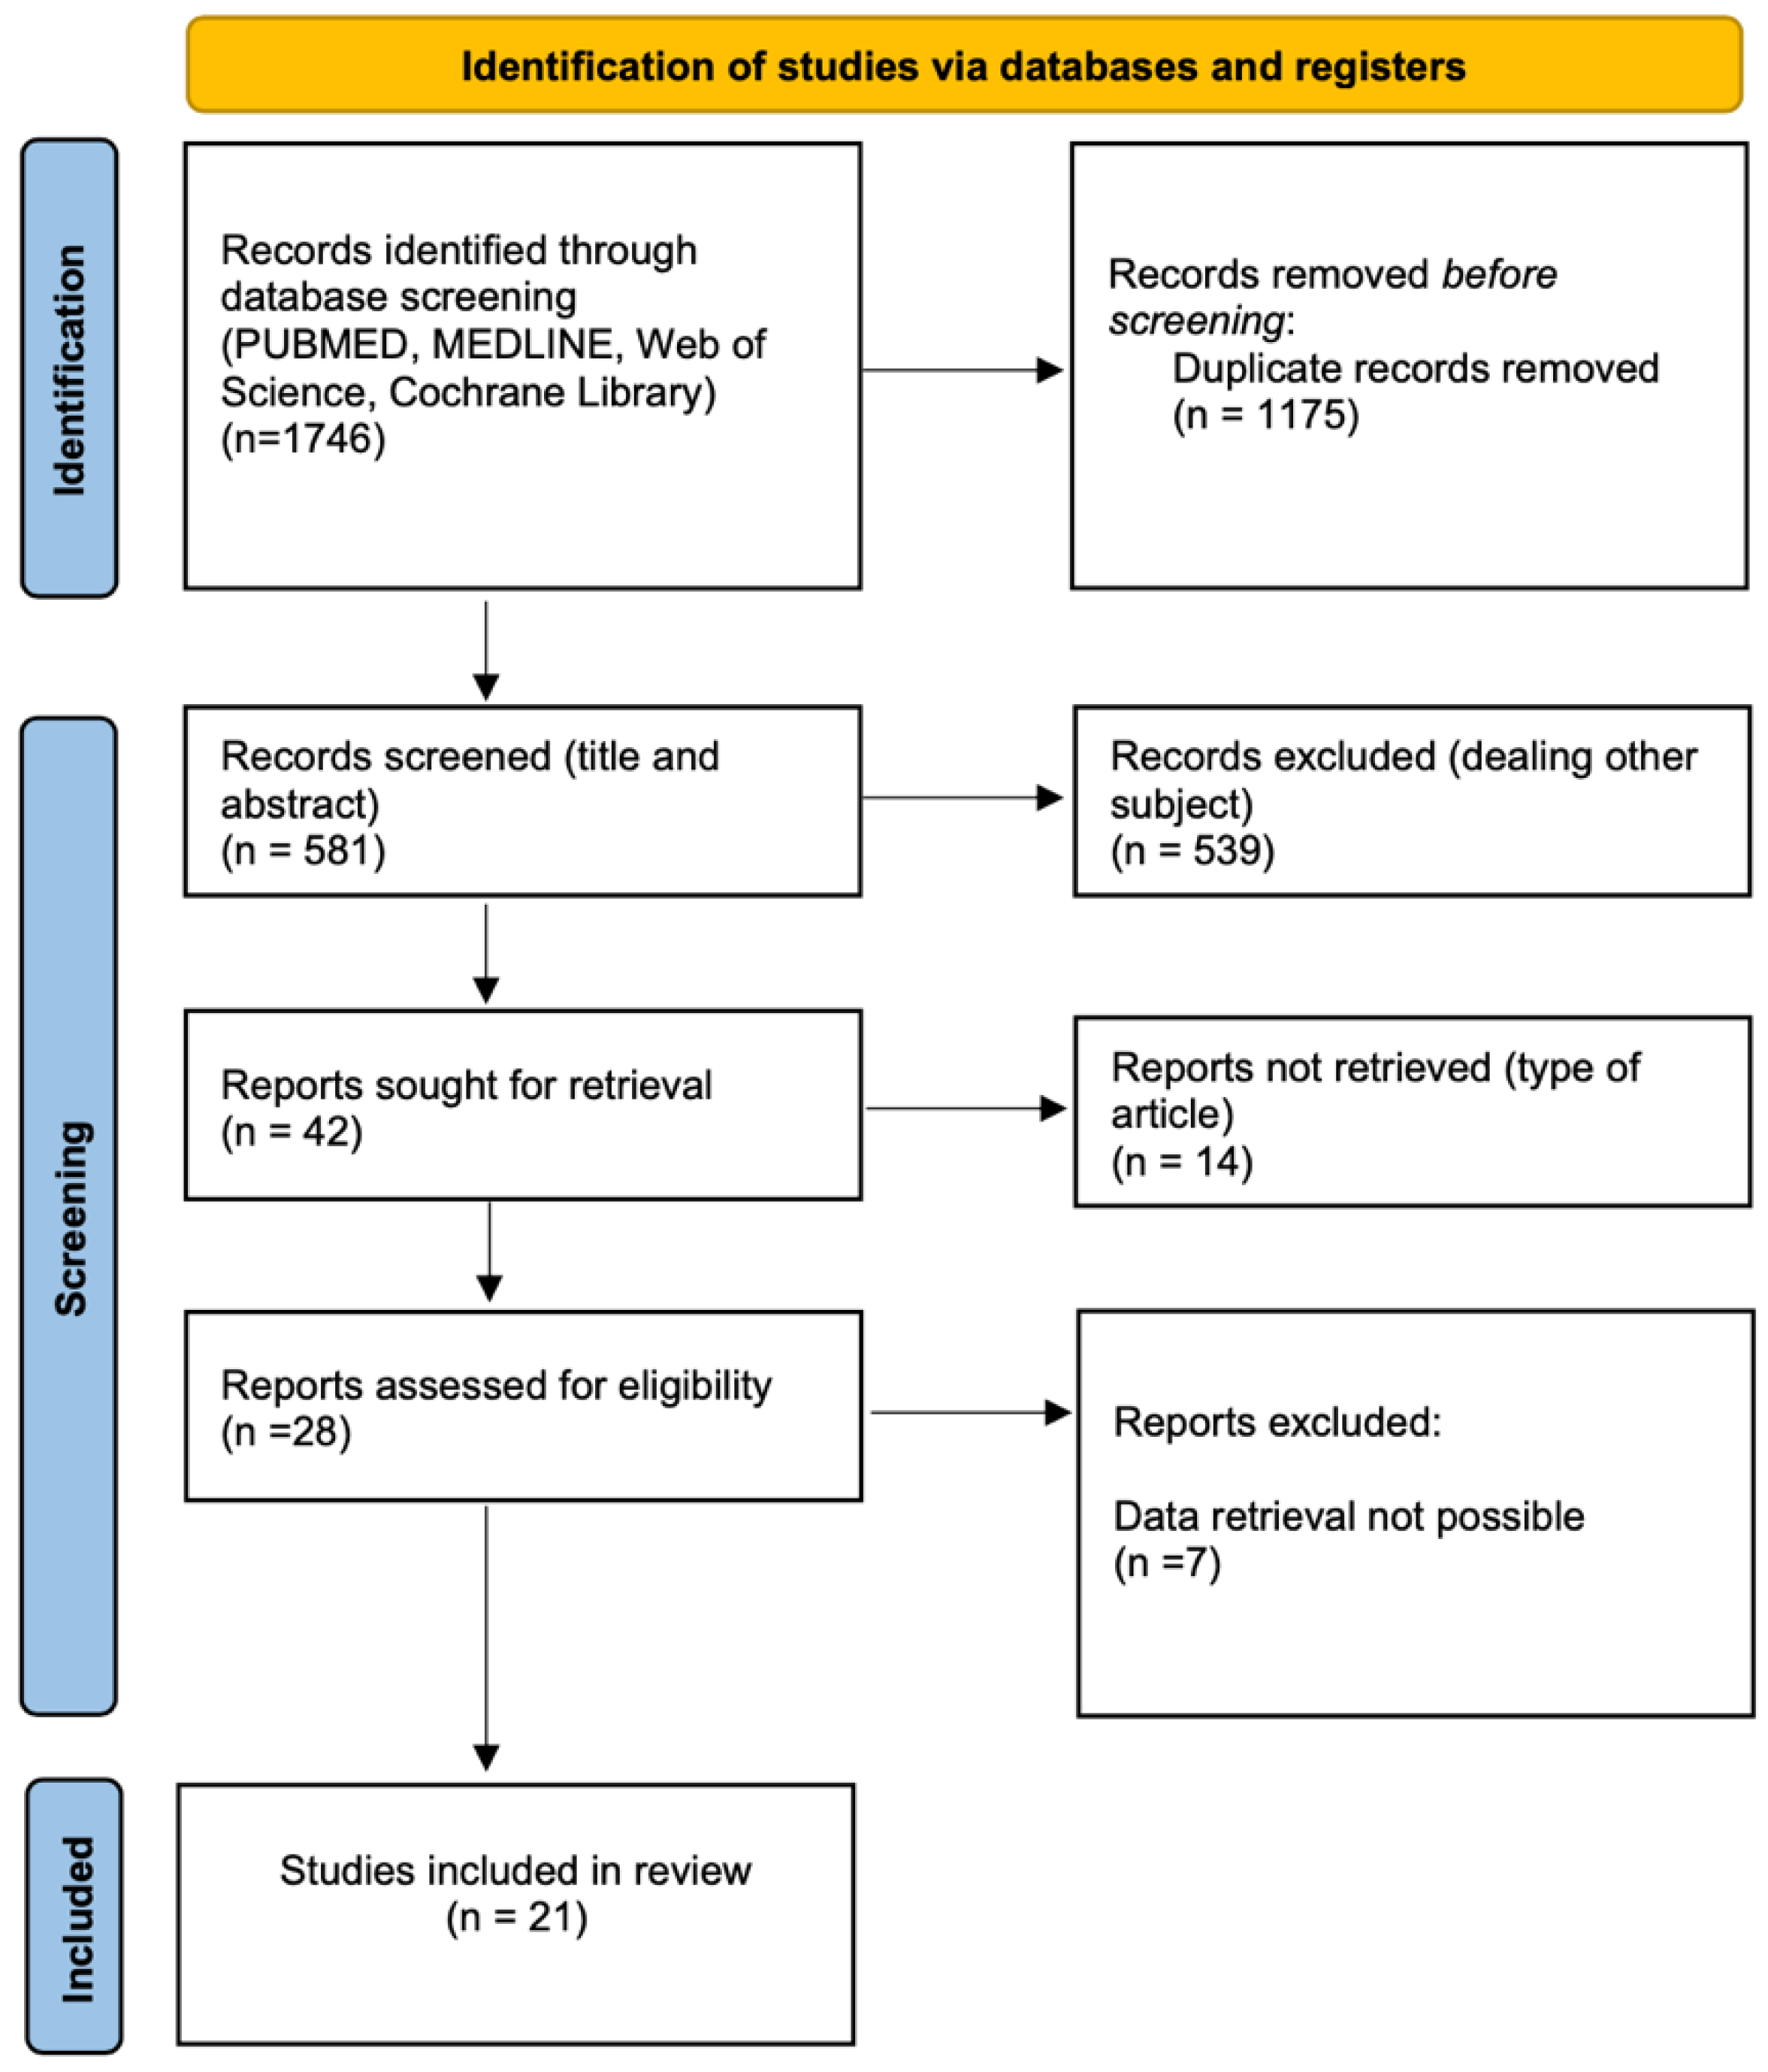
The initial database search identified 1746 articles; 1175 were duplicates, and after screening of title and abstract, 539 dealing with other subjects were excluded. After full-text reading of twenty-eight eligible articles, a further seven were excluded owing to inability to retrieve patient data. Twenty-one studies met the inclusion criteria and were finally selected for the systematic review [13,14,15,16,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33].
The systematic search process is summarised in Figure 1.
Figure 1.
Systematic search process.
3.2. Study Characteristics and Quality Assessment
Articles were published between 2001 and 2022, including seven retrospective, three case series and eleven case reports with a total of 2873 patients. The average NOS score was 7.3.
Characteristics of the studies on PCLC included in the review were summarised in Table 1.
Table 1.
Characteristics of studies included in the review.
3.3. Pooled Analysis
3.3.1. Baseline Characteristics
PCLC occurs mainly in males (57%) and at a median age between 52 and 66 (range: 24–82). Sixty-four percent of patients were former smokers. Among LC, the incidence of PC was 1.5%. Ascites was present in 63% of patients.
Regarding pTNM staging at diagnosis, 0.1% of patients were stage II, 0.3%% were stage III and the vast majority (99.6%) were stage IV. Peritoneum was the sole metastatic site in 13.5% of patients and it was synchronous in 94% of cases while metachronous in 6%. Concurrent metastatic sites were pleura in 29% of patients, liver in 20%, bone in 15%, adrenal glands and contralateral lung in 9%, distant nodes in 4%, pericardium in 2%, and small bowel, colon and eye in 0.5% of patients. Hystology was adenocarcinoma in 46% of patients, non-small-cell lung cancer (NSCLC) in 25% of patients, squamous cell carcinoma in 10% of patients and unspecified in 14%. EGFR mutation was present in 39% of patients, ALK and kRAS in 8%, MET in 3%, ROS in 2% and 40% had no mutations at all.
Baseline characteristics of patients with PC from LC are described in Table 2.
Table 2.
Baseline characteristics of peritoneal carcinosis from lung cancer patients.
3.3.2. PCLC Management and Outcomes
Adjuvant chemotherapy was indicated in 27% of patients in the form of cytotoxic agents in 56% of cases, EGFR/ALK-tyrosine kinase inhibitors in 40%, bevacizumab in 22%, platinum-based agents in 20% and immune-checkpoint inhibitors in 4%.
Recombinant human endostatin, BRAF-tyrosine kinase inhibitors, MEK-tyrosine kinase inhibitors and dendritic cell immunotherapy were indicated in 2% of patients. Surgery was indicated in 7% of cases. The median overall survival (OS) from lung cancer diagnosis was between 9 and 21 months (range: 1–88 months) while from the onset of PC, from 0.5 to 5 months (range 0–78) and 6% of patients were dead at latest follow-up.
PC from LC management and outcomes are summarised in Table 3.
Table 3.
Management and outcomes of peritoneal carcinosis from lung cancer.
3.4. Synchronous and Metachronous PCLC Characteristics Subanalysis
Synchronous and metachronous PCLC patient characteristics are described in Table 4. No comparative analysis was performed due to data paucity.
Table 4.
Synchronous and metachronous PCLC patient characteristics.
4. Discussion
The present study analysed the management and prognosis of patients with PCLC. PCLC appears to be a rare diagnosis; most patients do not receive any form of medical (chemotherapy) or surgical treatment and prognosis is generally very poor.
The pathogenesis of PCLC is not entirely clear, with Patil et al. finding a significant association with malignant pleural effusion, suggesting a possible route of spread, maybe through serosal communication [20]. In fact, in this review, as many as 29% of patients had concurrent pleural disease and this was the most prevalent concomitant site. Nonetheless, this association does not fully explain the pathogenesis, as the majority of PCLC patients never develop pleural disease.
The incidence of PCLC was 1.6% of LC patients and although low, it appears to be rising, as much as three times more than reported by older series, such as Satoh et al. and Flanagan et al. [13,25]. This increase in incidence may simply be the result of improved diagnostic modalities, or it may represent a new trend indicating that we will have to face this situation more often in the future. The latter idea may be supported by autopsy reports which find PCLC in 2% to 16% of cases [29]. In any case, the problem seems to deserve greater attention. This is particularly true when considering that LC is the most common adult cancer, and that the literature in this regard is scarce and provides generally low-quality evidence: this systematic review only found 21 articles on the matter, fourteen of which were case reports or small case series.
The average survival of patients with PCLC ranged between 0.5 and 5.2 months. This is in line with the paper by Niu et al. in which uncommon metastatic sites appear to have worse prognosis [2]. Nonetheless, attempts of PCLC treatment other than supportive management were rare: only 27% of patients received first-line or palliative chemotherapy and only 7% underwent surgery. This may be due to the poor performance status of these patients, but at first glance these numbers look very low and prompt the question of whether we are really doing all we can to help our patients. In particular, there appear to be situations in which the prognosis may be more favourable, and a more “aggressive” oncological management may pay off [25,34].
Patients with isolated PCLC had similar survival rates to patients with isolated “other organ” metastases in a study by Lurvink et al., despite (surprisingly!) significantly lower rates of systemic treatment. In the aforementioned study, these patients had 1- and 2-year OS rates of 22% and 10.5%, respectively [31].
Furthermore, LC may harbour mutations that may be antagonized by new-generation targeted therapy. Currently there are limited data on the specific genomic profile of PCLC. Authors reported EGFR and KRAS mutations, ALK rearrangements and rarely MET mutations. EGFR was the most commonly detected mutation in PCLC (40%) and there are several reports of response to specific tyrosine kinase inhibitors such as gefitinib, afatinib and erlotinib [20,35]. Furthermore, other studies show response to EGFR tyrosine kinase inhibitors without knowledge of their EGFR status [36,37]. Bevacizumab-based treatment may also be an effective treatment strategy for ascites management [29]. On the other hand, immune checkpoint inhibitors that yield good results in specific LC sub-populations seem to fare much worse in patients with PCLC [36,37].
Finally, a proper comparison between metachronous and synchronous PCLC was not possible, even if data may suggest synchronous PCLC to occur at an older age, without other metastases associated. Future studies should investigate this aspect to shed light on different characteristics and prognostic features regarding PCLC timing. Patients with metachronous metastases may have better chances of survival compared with those who had synchronous primary LC and PCLC diagnosis [29]. Unfortunately, most reported PCLC (94%) seem to be synchronous cases; although, this result may have been biased by the fact that the largest study (by far) included in this review focused exclusively on synchronous PCLC [31]. Other favourable prognostic factors seem to be younger age, female sex, and non-smoker status [29,31].
All these subcategories of PCLC may have longer survival times, and further studies should evaluate if they could gain major benefits from earlier diagnosis and adjunctive therapy. A quite good result was reported by Sibio et al., who treated two cases of PCLC with cytoreductive surgery, leading to survivals of 29 and 36 months after surgery, with the latter still being alive [27].
The approach utilised was directly derived from experience in PC from different abdominal (and non-abdominal) primary cancers. Cytoreductive surgery alone was found to be the main contributor to prolonged survival in colorectal cancer, proving the value of elimination gross malignant disease for improving prognosis [38,39,40]. Furthermore, association between cytoreductive surgery and HIPEC or, more recently, PIPAC are established surgical strategies for appendiceal carcinoma, colorectal and gynaecological (particularly ovarian) cancers, and may be considered in hyper-selected cases [4]. On this basis, there may be an argument for the investigation of a more active approach to the care of these patients, in an effort to offer them a chance of longer survival and possibly with a better quality of life. In fact, PCLC may lead to abdominal pain and partial or complete bowel obstruction, which may significantly worsen quality of life and may also deserve surgical treatment. Bowel obstruction is the most frequent clinical presentation in patients with gastrointestinal metastases [4]. Further studies should clarify the possible role of cytoreductive surgery especially when surgery for bowel obstruction seems unavoidable. Nonetheless, these aggressive treatments do have complications and the decision for such a commitment should be taken by a multidisciplinary team after careful consideration of the individual patient situation in terms of performance status and tumour biology (mutations) and distribution (other metastatic sites, peritoneal cancer index—PCI, etc.) [41,42].
Early diagnosis could allow treatment of a less extensive disease (lower PCI) and therefore also be important. In the setting of a growing PCLC incidence, it will be important to be keep a high index of suspicion.
This study has some limitations, the main one being the scarcity and quality of the literature, in addition, another one is the presence of one study reporting on the majority of patients included and reporting on only synchronous PCLC.
Overall, PCLC appears to be a rising diagnosis, with a poor prognosis and limited therapeutical interventions. A more aggressive approach may obtain improved results in some patients and should probably be investigated further in the near future. As the incidence is low, appropriate national or international registries should be encouraged.
5. Conclusions
The literature on PCLC is scarce. Its incidence is low but appears to be substantially rising and is likely to be an underestimation. Prognosis is very poor and therapeutic strategies have been limited and used in a minority of patients. Subcategories of PCLC patients may have an improved prognosis and may benefit from an aggressive oncological approach, including cytoreductive surgery. Further investigation would be needed in this regard.
Author Contributions
Conceptualisation, L.S. and S.S.; methodology, L.S., C.R., A.F., S.S. and L.I.; software, A.F. and G.C.; validation, E.F., G.P., G.C. and L.I.; formal analysis, L.M., S.D.C. and E.F.; investigation, S.D.C. and P.S.; resources, S.S.; data curation, A.F., L.S. and V.U; writing—original draft preparation, L.S, B.S. and G.P.; writing—review and editing, L.S., L.M. and S.S.; visualisation, S.D.C. and S.S.; supervision, S.D.C. and S.S.; project administration, S.S.; funding acquisition, S.S. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted according to the guidelines of the Declaration of Helsinki. Ethical approval was not requested as per local policy on systematic review conducted exclusively on datasets where involved subjects are not identifiable.
Informed Consent Statement
Informed consent was obtained from all the articles involved in this study. However, no patient can be identified in the present study.
Data Availability Statement
All data generated or analysed during this study are included in this published article. The dataset supporting reported results is protected and access availability must be obtained.
Conflicts of Interest
The authors declare no conflict of interest.
References
- American Cancer Society. Cancer Facts & Figures 2023; American Cancer Society: Atlanta, GA, USA, 2023. [Google Scholar]
- Niu, F.-Y.; Zhou, Q.; Yang, J.-J.; Zhong, W.-Z.; Chen, Z.-H.; Deng, W.; He, Y.-Y.; Chen, H.-J.; Zeng, Z.; Ke, E.-E.; et al. Distribution and prognosis of uncommon metastases from non-small cell lung cancer. BMC Cancer 2016, 16, 149. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Di Giorgio, A.; Cardi, M.; Biacchi, D.; Sibio, S.; Accarpio, F.; Ciardi, A.; Cornali, T.; Framarino, M.; Sammartino, P. Depth of colorectal-wall invasion and lymph-node involvement as major outcome factors influencing surgical strategy in patients with advanced and recurrent ovarian cancer with diffuse peritoneal metastases. World J. Surg. Oncol. 2013, 11, 64. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kitai, T. The role of cytoreductive surgery and hyperthermic intraperitoneal chemotherapy in the treatment of peritoneal carcinomatosis: A systematic review including evidence from Japan. Surg. Today 2020, 51, 1085–1098. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- REACCT Collaborative. Characteristics of Early-Onset vs. Late-Onset Colorectal Cancer: A Review. JAMA Surg. 2021, 156, 865–874. [Google Scholar] [CrossRef] [Scilit]
- Jiang, A.; Wang, J.; Liu, N.; Zheng, X.; Li, Y.; Ma, Y.; Zheng, H.; Chen, X.; Fan, C.; Zhang, R.; et al. Integration of Single-Cell RNA Sequencing and Bulk RNA Sequencing Data to Establish and Validate a Prognostic Model for Patients With Lung Adenocarcinoma. Front Genet. 2022, 13, 833797. [Google Scholar] [CrossRef] [Scilit]
- Brinkhof, S.; Groen, H.J.; Siesling, S.S.; Ijzerman, M.J. Resource utilization in lung cancer diagnostic procedures: Current use and budget consequences. PLoS ONE 2017, 12, e0189251. [Google Scholar] [CrossRef] [Scilit]
- Jiang, A.; Chen, X.; Zheng, H.; Liu, N.; Ding, Q.; Li, Y.; Fan, C.; Fu, X.; Liang, X.; Tian, T.; et al. Lipid metabolism-related gene prognostic index (LMRGPI) reveals distinct prognosis and treatment patterns for patients with early-stage pulmonary adenocarcinoma. Int. J. Med. Sci. 2022, 19, 711–728. [Google Scholar] [CrossRef] [Scilit]
- Jiang, A.; Liu, N.; Bai, S.; Wang, J.; Gao, H.; Zheng, X.; Fu, X.; Ren, M.; Zhang, X.; Tian, T.; et al. Identification and validation of an autophagy-related long non-coding RNA signature as a prognostic biomarker for patients with lung adenocarcinoma. J. Thorac. Dis. 2021, 13, 720–734. [Google Scholar] [CrossRef] [Scilit]
- Amelio, I.; Bertolo, R.; Bove, P.; Candi, E.; Chiocchi, M.; Cipriani, C.; Di Daniele, N.; Ganini, C.; Juhl, H.; Mauriello, A.; et al. Cancer predictive studies. Biol. Direct 2020, 15, 18. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Wells, G.A.; Shea, B.; O’Connell, D.; Peterson, J.; Welch, V.; Losos, M.; Tugwell, P. The Newcastle-Ottawa Scale (NOS) for Assessing the Quality of Non-Randomised Studies in Meta-Analyses. Available online: https://www.ohri.ca/programs/clinicalepidemiology/oxford.asp (accessed on 20 December 2022).
- Satoh, H.; Ishikawa, H.; Yamashita, Y.T.; Kurishima, K.; Ohtsuka, M.; Sekizawa, K. Peritoneal carcinomatosis in lung cancer patients. Oncol. Rep. 2001, 8, 1305–1307. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kimura, H.; Iizasa, T.; Ishikawa, A.; Yoshino, M.; Shingyouji, M.; Kimura, M.; Hirata, T.; Odaka, A.; Matsubayasi, K. Eradication of intractable malignant ascites by abdominocentesis, reinfusion of concentrated ascites, and adoptive immunotherapy with dendritic cells and activated killer cells in a patient with recurrent lung cancer: A case report. J. Med. Case Rep. 2008, 2, 372. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- SSu, H.-T.; Tsai, C.-M.; Perng, R.-P. Peritoneal carcinomatosis in lung cancer. Respirology 2008, 13, 465–467. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tanriverdi, O.; Barutca, S.; Meydan, N. Relapse with isolated peritoneal metastasis in lung adenocarcinoma: Case report and review of the literature. Contemp. Oncol. 2012, 16, 586–589. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sereno, M.; Rodríguez-Esteban, I.; Gómez-Raposo, C.; Merino, M.; López-Gómez, M.; Zambrana, F.; Casado, E. Lung cancer and peritoneal carcinomatosis. Oncol. Lett. 2013, 6, 705–708. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bazine, A.; Fetohi, M.; Khmamouch, M.R.; Namad, T.; Ichou, M.; Errihani, H. An Unusual Case of Isolated Peritoneal Metastases from Lung Adenocarcinoma. Case Rep. Oncol. 2014, 7, 600–604. [Google Scholar] [CrossRef] [Scilit]
- Li, B.; Lu, J.C.; He, D.; Wang, J.; Zhou, H.; Shen, L.; Zhang, C.; Duan, C. Rapid onset lung squamous cell carcinoma with prominent peritoneal carcinomatosis and an eosinophilic leukemoid reaction, with coexistence of the BRAF V600E and oncogenic KRAS G12A mutations: A case report. Oncol Lett. 2014, 8, 589–593. [Google Scholar] [CrossRef] [Scilit]
- Patil, T.; Aisner, D.L.; Noonan, S.A.; Bunn, P.A.; Purcell, W.T.; Carr, L.L.; Camidge, D.R.; Doebele, R.C. Malignant pleural disease is highly associated with subsequent peritoneal metastasis in patients with stage IV non-small cell lung cancer independent of oncogene status. Lung Cancer 2016, 96, 27–32. [Google Scholar] [CrossRef] [Scilit]
- Kobayashi, H.; Wakuda, K.; Takahashi, T. Effectiveness of afatinib in lung cancer with paralytic ileus due to peritoneal carcinomatosis. Respirol. Case Rep. 2016, 4, e00197. [Google Scholar] [CrossRef] [Scilit]
- Hanane, K.; Salma, B.; Khadija, B.; Ibrahim, E.; Saber, B.; Hind, M. Peritoneal carcinomatosis, an unusual and only site of metastasis from lung adenocarcinoma. Pan Afr. Med. J. 2016, 23, 60. [Google Scholar] [CrossRef] [Scilit]
- Yang, P.; Li, W.-L.; Zhou, J.-X.; Yang, Y.-B.; Jin, X.-X. Peritoneum as the sole distant metastatic site of lung adenosquamous cell carcinoma: A case report. J. Med. Case Rep. 2017, 11, 274. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kamaleshwaran, K.K.; Joseph, J.; Kalarikal, R.K.; Shinto, A. Image findings of rare case of peritoneal carcinomatosis from non small cell lung cancer and response to erlotinib in F-18 FDG positron emission tomography/computed tomography. Indian J. Nucl. Med. 2017, 32, 140–142. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Flanagan, M.; Solon, J.; Chang, K.; Deady, S.; Moran, B.; Cahill, R.; Shields, C.; Mulsow, J. Peritoneal metastases from extra-abdominal cancer–A population-based study. Eur. J. Surg. Oncol. 2018, 44, 1811–1817. [Google Scholar] [CrossRef] [Scilit]
- Hsu, J.-F.; Lee, Y.-L.; Chang, H.-L.; Wei, P.-J.; Shen, Y.-T.; Lin, C.-M.; Li, C.-Y.; Chong, I.-W.; Yang, C.-J. Clinical efficacy of concurrent bevacizumab for malignant ascites in nonsquamous cell carcinoma of the lung. Asia-Pac. J. Clin. Oncol. 2019, 15, e126–e131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sibio, S.; Sica, G.S.; Di Carlo, S.; Cardi, M.; Di Giorgio, A.; Sollazzo, B.M.; Sammartino, P. Surgical treatment of intraperitoneal metastases from lung cancer: Two case reports and a review of the literature. J. Med. Case Rep. 2019, 13, 262. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kawaguchi, Y.; Hanaoka, J.; Hayashi, H.; Fukuda, Y.; Iihara, H.; Suzuki, A.; Sugiyama, T. Clinical efficacy of osimertinib for a patient with ileus due to peritoneal carcinomatosis. Clin. Case Rep. 2019, 8, 347–350. [Google Scholar] [CrossRef] [Scilit]
- Abbate, M.I.; Cortinovis, D.L.; Tiseo, M.; Vavalà, T.; Cerea, G.; Toschi, L.; Canova, S.; Colonese, F.; Bidoli, P. Peritoneal carcinomatosis in non-small-cell lung cancer: Retrospective multicentric analysis and literature review. Future Oncol. 2019, 15, 989–994. [Google Scholar] [CrossRef] [Scilit]
- Kazakova, V.; Velasco, S.V.A.; Perepletchikov, A.; Lathan, C.S. ROS1-rearranged lung adenocarcinoma with peritoneal carcinomatosis on initial presentation. BMJ Case Rep. 2020, 13, e233864. [Google Scholar] [CrossRef] [Scilit]
- Lurvink, R.J.; Rijken, A.; Bakkers, C.; Aarts, M.J.; Kunst, P.W.A.; van de Borne, B.E.; van Erning, F.N.; de Hingh, I.H.J.T. Synchronous peritoneal metastases from lung cancer: Incidence, associated factors, treatment and survival: A Dutch population-based study. Clin. Exp. Metastasis 2021, 38, 295–303. [Google Scholar] [CrossRef] [Scilit]
- Tani, T.; Nakachi, I.; Ikemura, S.; Ohgino, K.; Kuroda, A.; Terai, H.; Masuzawa, K.; Shinozaki, T.; Ishioka, K.; Funatsu, Y.; et al. Clinical Characteristics and Therapeutic Outcomes of Metastatic Peritoneal Carcinomatosis in Non-Small-Cell Lung Cancer. Cancer Manag. Res. 2021, 13, 7497–7503. [Google Scholar] [CrossRef] [Scilit]
- Yagami, Y.; Nakahara, Y.; Manabe, H.; Yamamoto, H.; Otani, S.; Sato, T.; Igawa, S.; Kubota, M.; Sasaki, J.; Naoki, K. Promising Response to Dabrafenib Plus Trametinib in a Patient with Peritoneal Carcinomatosis from Non Small Lung Cancer Harboring BRAF V600E Mutation. OncoTargets Ther. 2022, 15, 1369–1374. [Google Scholar] [CrossRef] [Scilit]
- Iaculli, E.; Agostini, M.; Biancone, L.; Fiorani, C.; Di Vizia, A.; Montagnese, F.; Sibio, S.; Manzelli, A.; Tesauro, M.; Rufini, A.; et al. C-reactive protein levels in the perioperative period as a predictive marker of endoscopic recurrence after ileo-colonic resection for Crohn’s disease. Cell Death Discov. 2016, 2, 16032. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sibio, S.; Sammartino, P.; Accarpio, F.; Biacchi, D.; Cornali, T.; Cardi, M.; Iafrate, F.; Di Giorgio, A. Metastasis of Pleural Mesothelioma Presenting as Bleeding Colonic Polyp. Ann. Thorac. Surg. 2011, 92, 1898–1901. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aarnink, A.; Fumet, J.D.; Favier, L.; Truntzer, C.; Ghiringhelli, F. Role of pleural and peritoneal metastasis in immune checkpoint inhibitors efficacy patients with non-small cell lung cancer: Real-world data from a large cohort in France. J. Cancer Res. Clin. Oncol. 2020, 146, 2699–2707. [Google Scholar] [CrossRef] [Scilit]
- Onali, S.; Calabrese, E.; Petruzziello, C.; Lolli, E.; Ascolani, P.; Ruffa, A.; Sica, G.; Rossi, A.; Chiaramonte, C.; Pallone, F.; et al. Post-operative recurrence of Crohn’s disease: A prospective study at 5 years. Dig Liver Dis. 2016, 48, 489–494. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quénet, F.; Elias, D.; Roca, L.; Goéré, D.; Ghouti, L.; Pocard, M.; Facy, O.; Arvieux, C.; Lorimier, G.; Pezet, D.; et al. Cytoreductive surgery plus hyperthermic intraperitoneal chemotherapy versus cytoreductive surgery alone for colorectal peritoneal metastases (PRODIGE 7): A multicentre, randomised, open-label, phase 3 trial. Lancet Oncol. 2021, 22, 256–266. [Google Scholar] [CrossRef] [Scilit]
- Di Carlo, S.; Cavallaro, G.; La Rovere, F.; Usai, V.; Siragusa, L.; Izzo, P.; Izzo, L.; Fassari, A.; Izzo, S.; Franceschilli, M.; et al. Synchronous liver and peritoneal metastases from colorectal cancer: Is cytoreductive surgery and hyperthermic intraperitoneal chemotherapy combined with liver resection a feasible option? Front. Surg. 2022, 9, 1006591. [Google Scholar] [CrossRef] [Scilit]
- Sibio, S.; Fiorani, C.; Stolfi, C.; Divizia, A.; Pezzuto, R.; Montagnese, F.; Bagaglini, G.; Sammartino, P.; Sica, G.S. Detection methods and clinical significance of free peritoneal tumor cells found during colorectal cancer surgery. World J. Gastrointest. Surg. 2015, 7, 178–184. [Google Scholar] [CrossRef] [Scilit]
- Di Giorgio, A.; Sammartino, P.; Cardini, C.L.; Al Mansour, M.; Accarpio, F.; Sibio, S.; Di Seri, M. Lung cancer and skeletal muscle metastases. Ann. Thorac. Surg. 2004, 78, 709–711. [Google Scholar] [CrossRef] [Scilit]
- COVIDSurg Collaborative; GlobalSurg Collaborative. SARS-CoV-2 infection and venous thromboembolism after surgery: An international prospective cohort study. Anaesthesia 2022, 77, 28–39. [Google Scholar]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).