


Case description
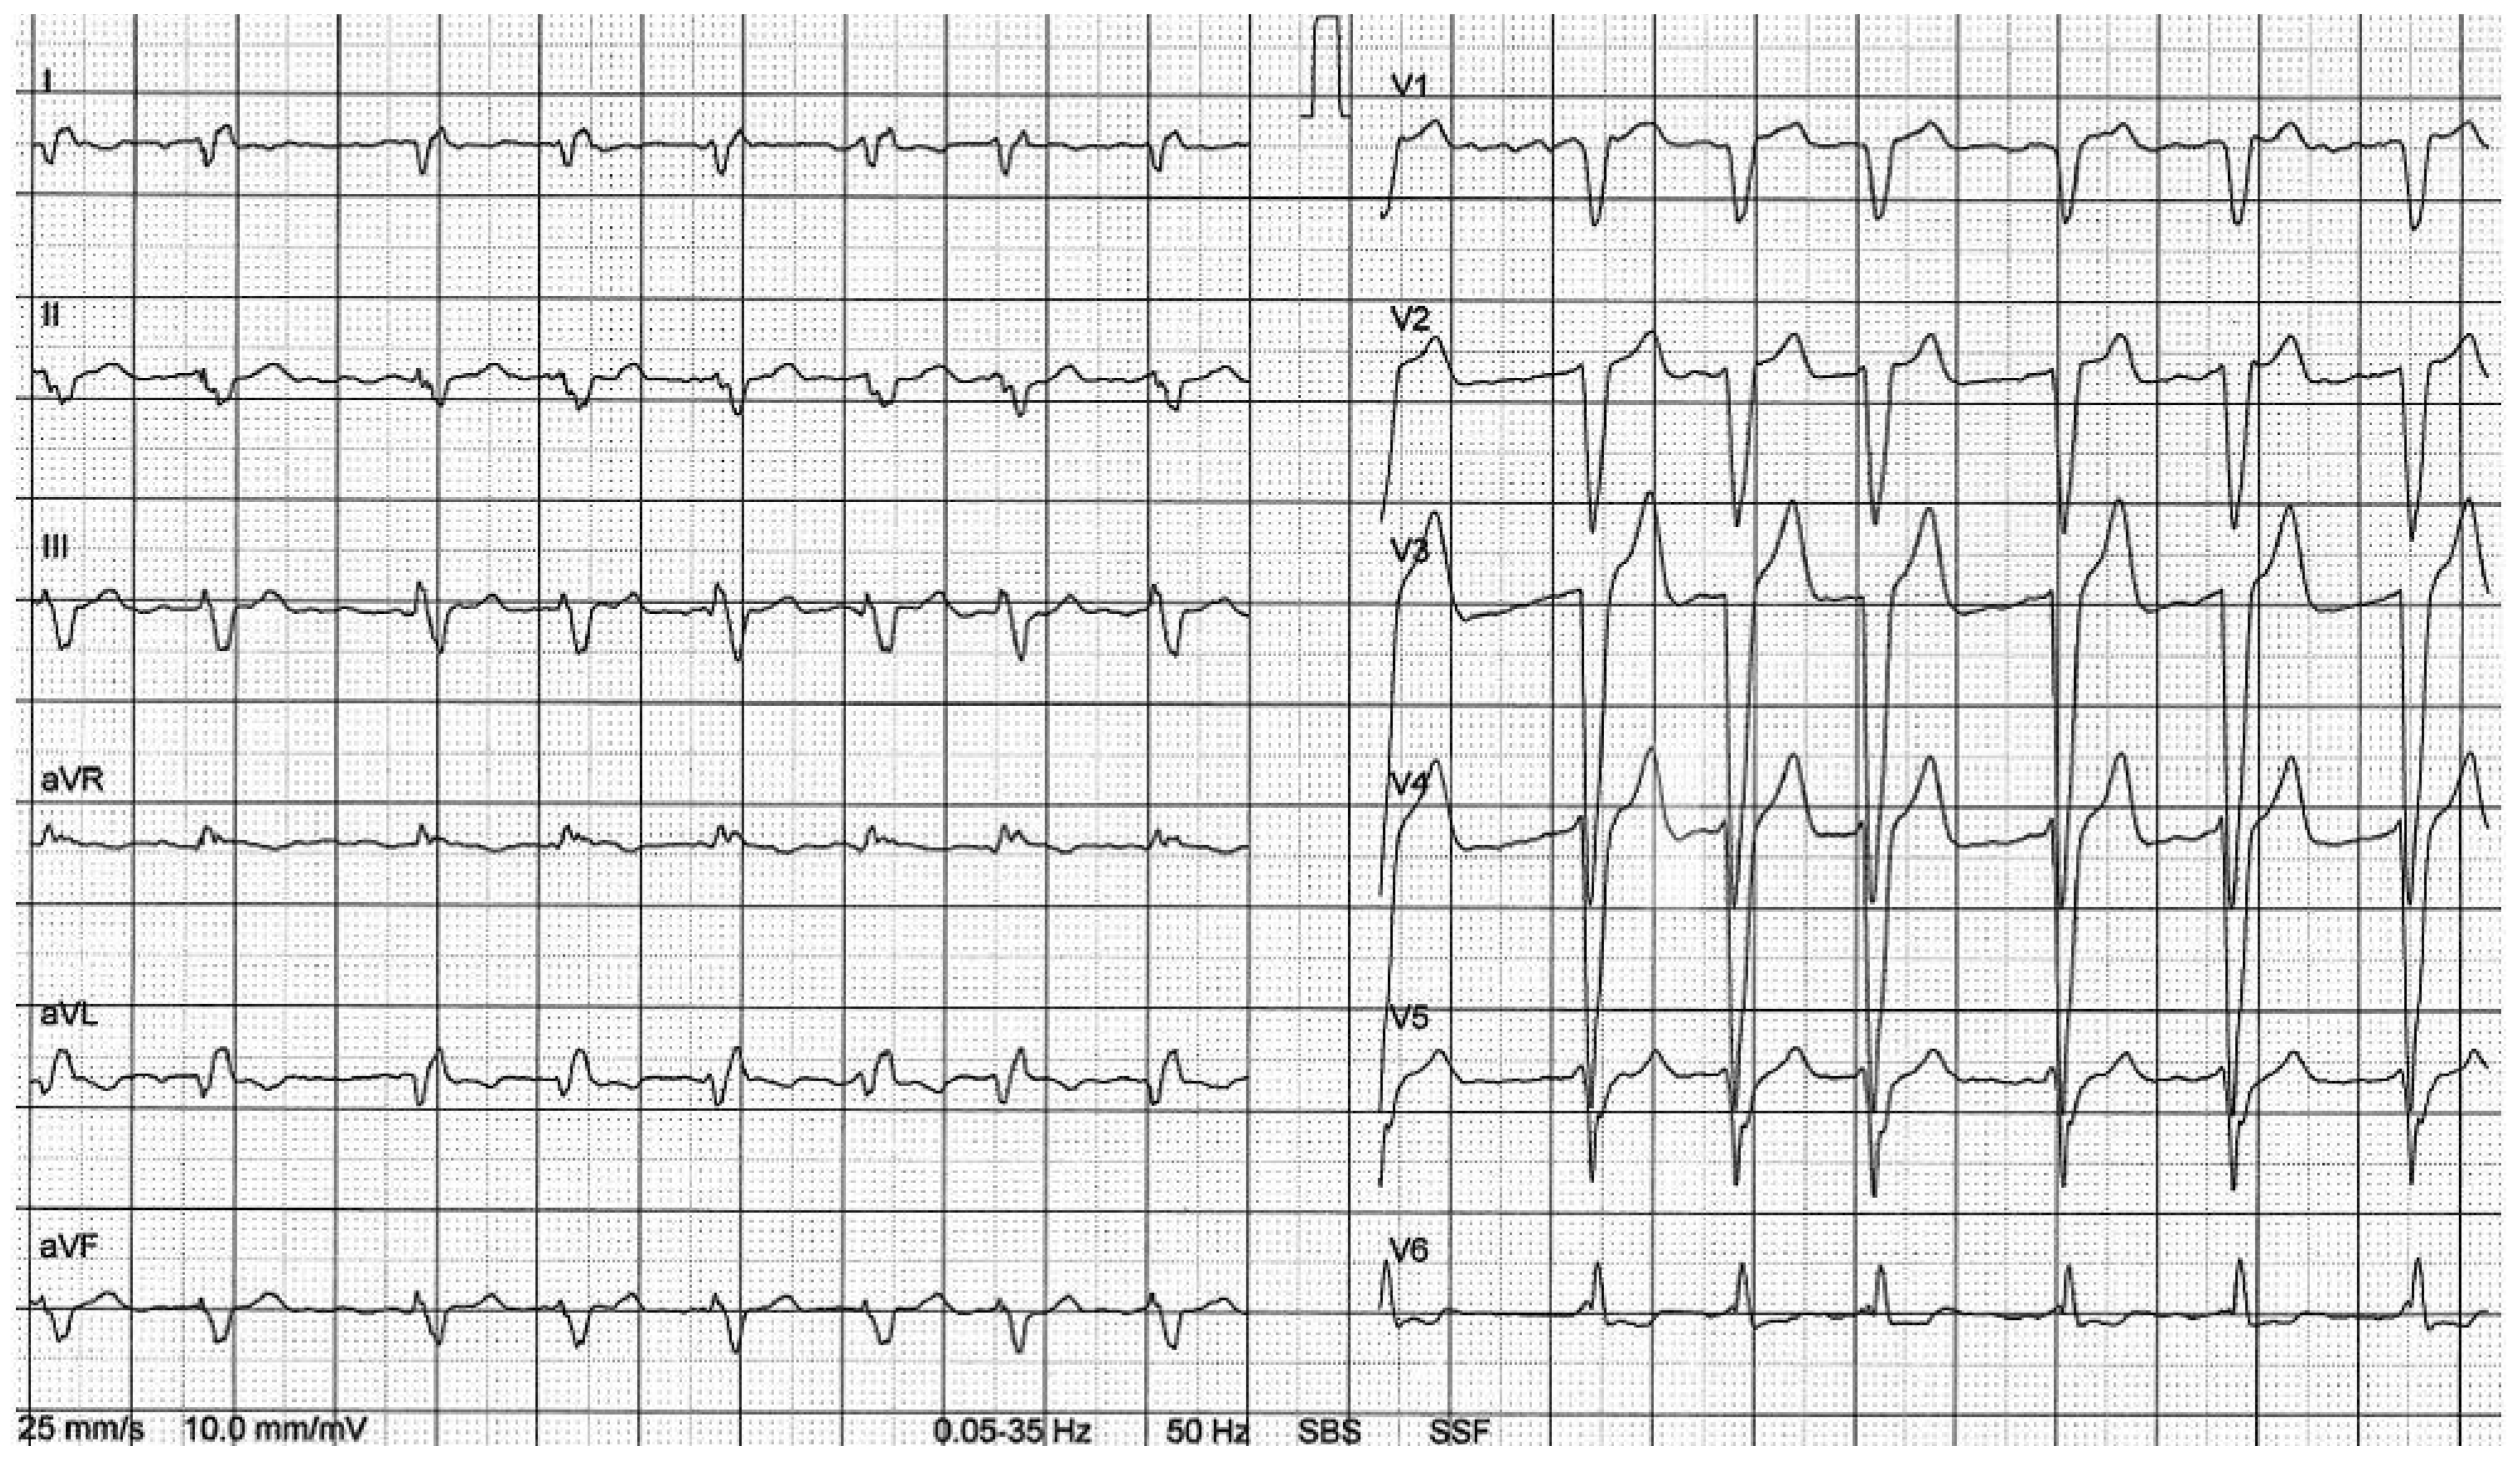
A 79-year-old male was admitted to our outpatient clinic with symptomatic heart failure (HF). The patient reported impaired exercise tolerance with increasing shortness of breath in the previous 4 weeks and a weight gain of 5 kg. The ECG showed new onset atrial fibrillation (AF) with rapid conduction and preexisting left bundle branch block (Figure 1). The patient had a history of coronary artery disease with successful PCI of the LCX after inferolateral myocardial infarction 15 months previously. Medication consisted of acetylsalicylic acid, torasemide, and atorvastatin. Physical examination revealed positive hepatojugular reflux, normal blood pressure (110/85 mm Hg), irregular heart beat (approx. 110 at rest), and right sided pleural effusion. Echocardiography showed severely reduced left ventricular ejection fraction (15–20%) with signs of left ventricular dyssynchrony, moderate mitral regurgitation and severe tricuspid regurgitation.
Figure 1.
Resting ECG.
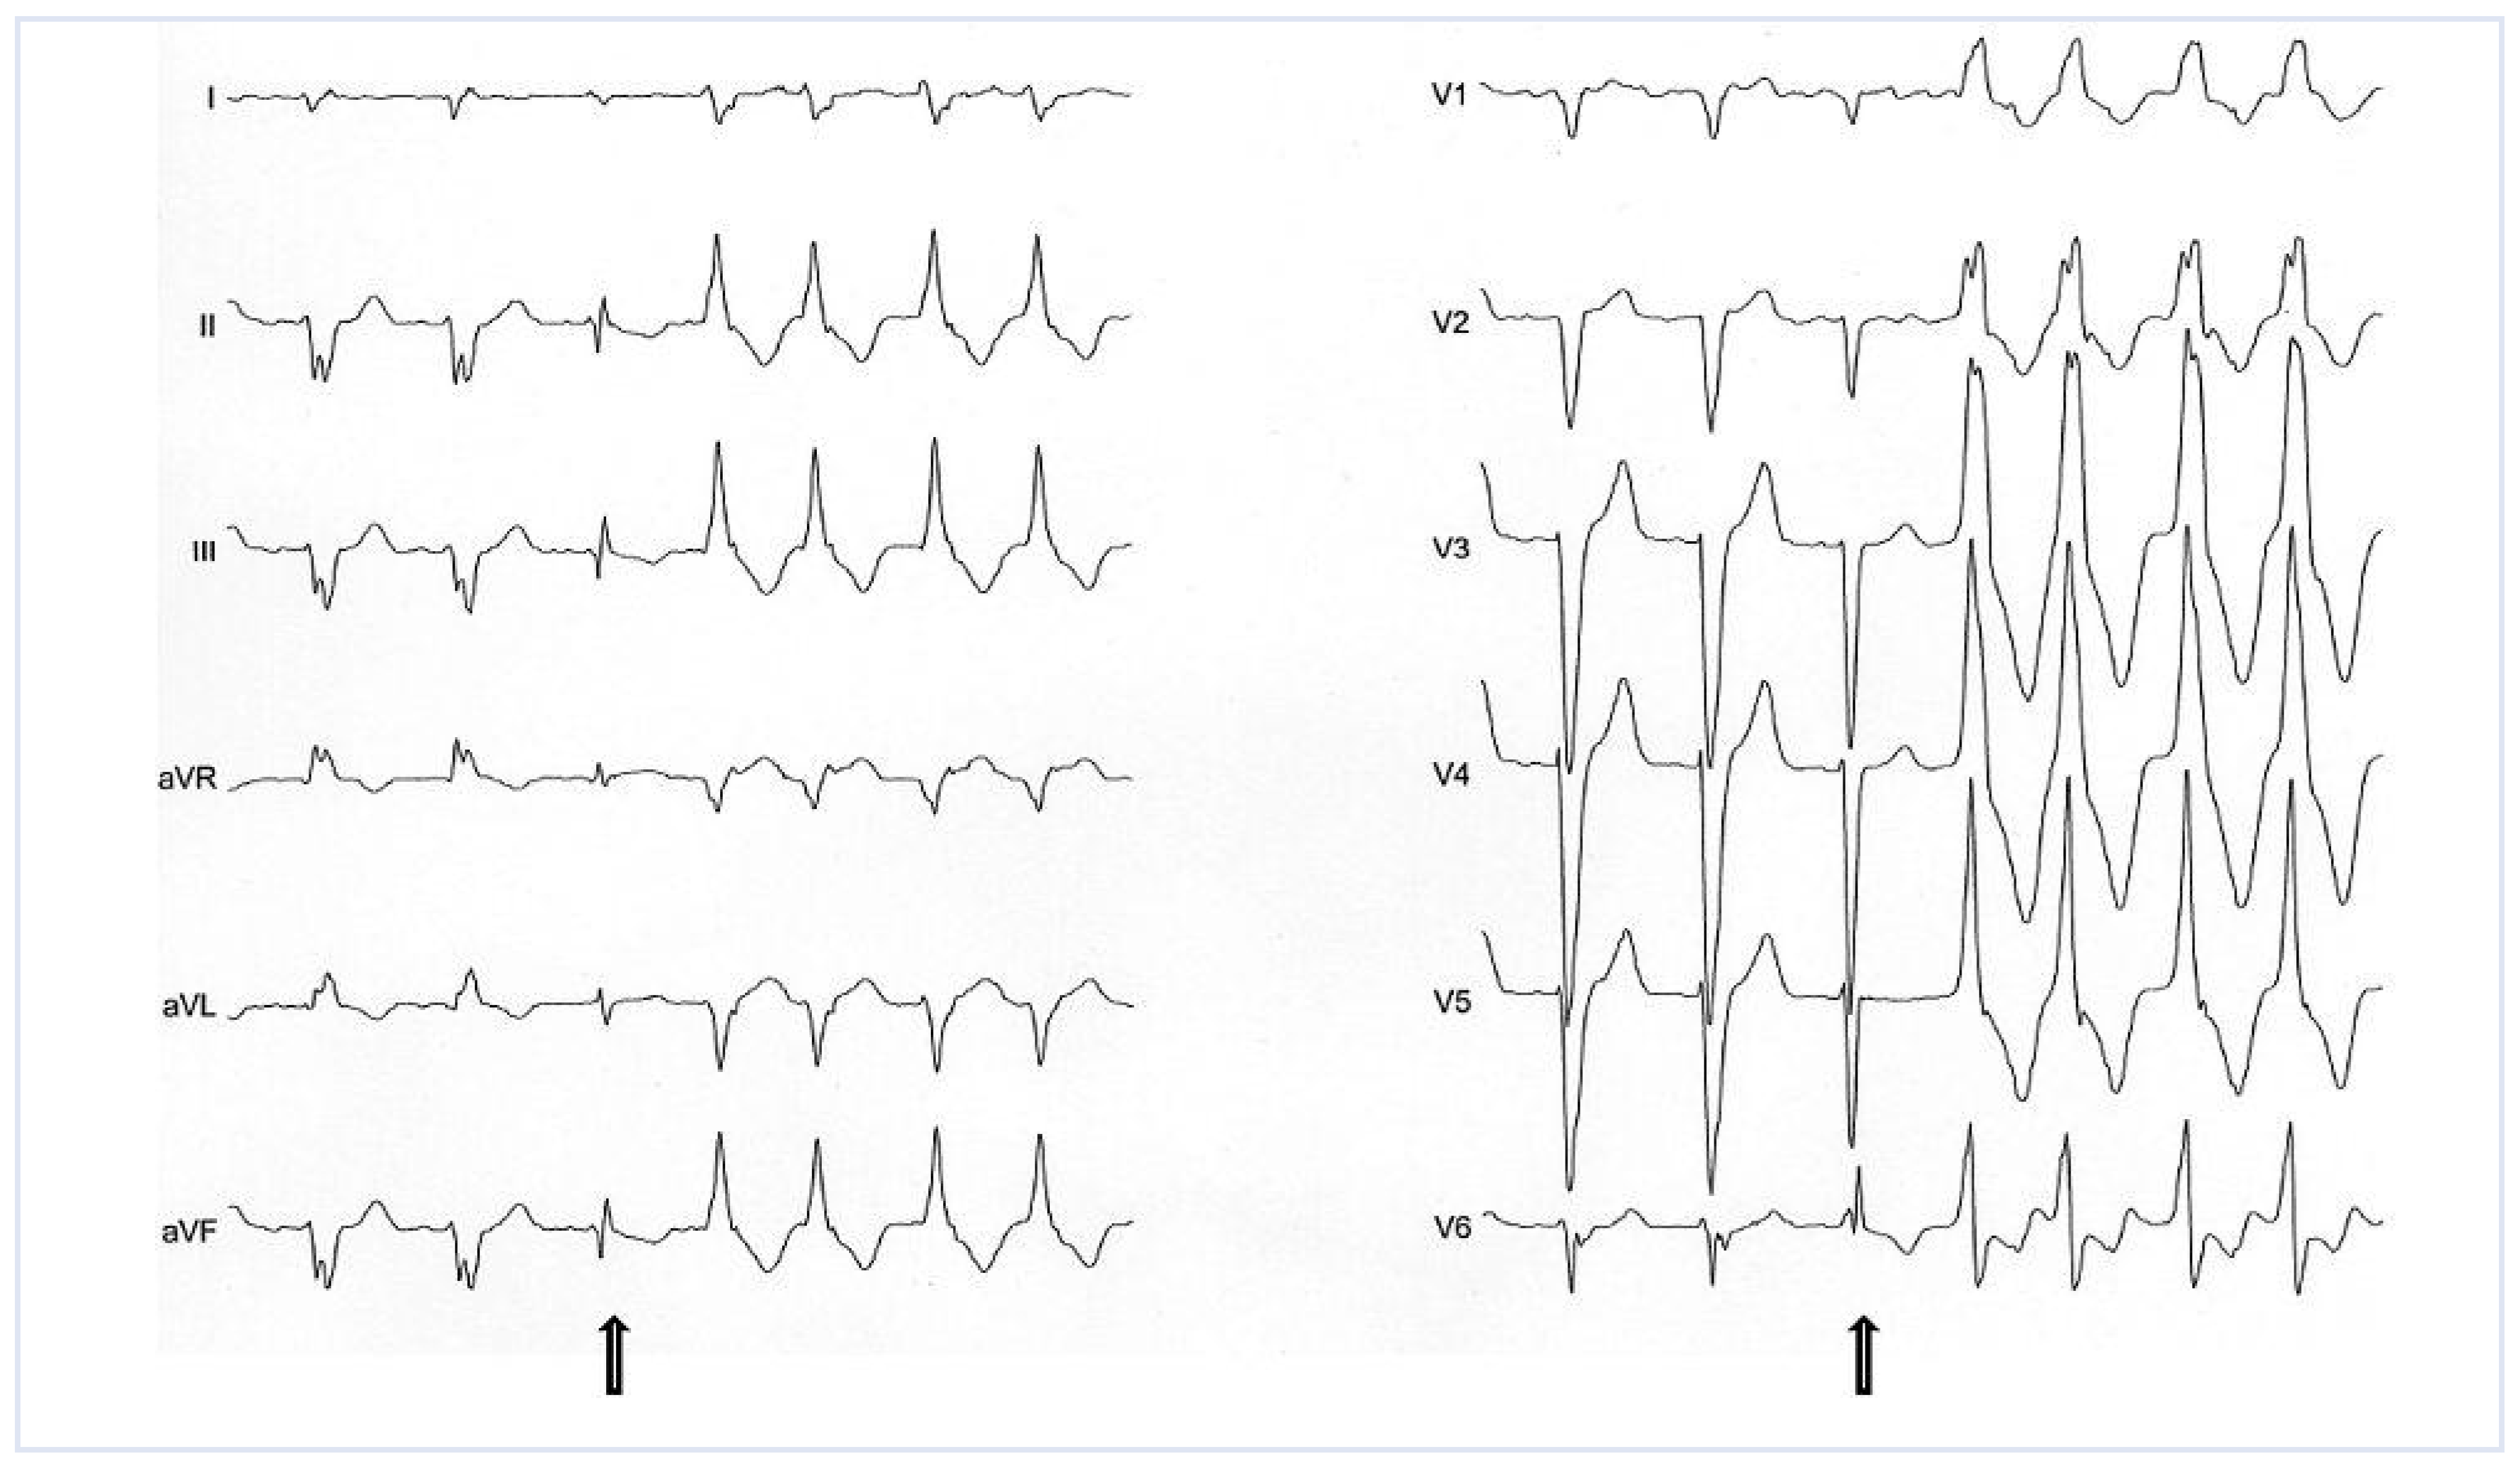
Figure 2.
A sequence of a 24-hour Holter ECG.
Questions
Answers
1. The first two QRS complexes show atrial fibrillation with bundle branch block pattern, which differs slightly from that of the resting ECG (Figure 1—probably due to different lead placement of the Holter electrodes).
The 4th to 7th QRS complexes show a right bundle branch block pattern with inferior axis at a heart rate of 112 bpm, which is slightly irregular (repeated episodes with similar morphology have been observed in the 24-hour ECG with heart rates ranging from 110 to 133 bpm). In consideration of the preexisting conduction abnormalities, a frequency-dependent change in aberration cannot be excluded, although other explanations are more likely. In a patient with severely impaired LVEF and a past history of MI the most important differential diagnosis is non-sustained ventricular tachycardia (VT; also according to the Brugada criteria R/S interval in one precordial lead >100 ms). As an important differential diagnosis, accelerated idioventricular rhythm (AIVR) must be considered. Interestingly, there is no consensus on the upper rate limit for the definition of AIVR; it is usually defined as a heart rate between 100 and 120 bpm [1]. The fact that faster episodes with similar QRS morphology could also be observed would favour VT; however, in view of the irregularity of the tachycardia, we rather assumed AIVR.
2. Interestingly, the 3rd complex shows a narrow QRS complex which contrasts with the broad left bundle branch pattern on the left and the right bundle branch pattern on the right. This feature is consistent with a fusion beat between these two different bundle branch morphologies, leading to fusion-induced resynchronisation of this single beat. Fusion beats are common in AIVR as well as in VTs.
Since NYHA III dyspnoea persisted despite optimised medical therapy, including appropriate rate control, our patient qualified for the implantation of an ICD/CRT device. In this case, the “electrical aim” of resynchronisation would have been to achieve a QRS complex similar to the fusion beat shown in the middle, although it must be admitted that QRS width has proved to be a poor predictor of CRT response [2].
Conflicts of Interest
The authors report no conflict of interest.
References
- Grimm, W.; Hoffmann, J.; Menz, V.; Schmidt, C.; Müller, H.H.; Maisch, B. Significance of accelerated idioventricular rhythm in idiopathic dilated cardiomyopathy. Am J Cardiol. 2000, 85, 899–904, A10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jia, P.; Ramanathan, C.; Ghanem, R.N.; Ryu, K.; Varma, N.; Rudy, Y. Electrocardiographic imaging of cardiac resynchronization therapy in heart failure: observation of variable electrophysiologic responses. Heart Rhythm. 2006, 3, 296–310. [Google Scholar] [CrossRef] [Scilit] [PubMed]
© 2010 by the authors. Attribution-Non-Commercial-NoDerivatives 4.0.