


Abstract
The coronavirus disease 2019 (COVID-19) pandemic has had significant mental health impacts among healthcare workers (HCWs), related to resource scarcity, risky work environments, and poor supports. Understanding the unique challenges experienced by senior doctors and identifying strategies for support will assist doctors facing such crises into the future. A cross-sectional, national, online survey was conducted during the second wave of the Australian COVID-19 pandemic. Inductive content analysis was used to examine data reporting workplace and psychosocial impacts of the pandemic. Of 9518 responses, 1083 senior doctors responded to one or more free-text questions. Of the senior doctors, 752 were women and 973 resided in Victoria. Four themes were identified: (1) work-life challenges; (2) poor workplace safety, support, and culture; (3) poor political leadership, planning and support; and (4) media and community responses. Key issues impacting mental health included supporting staff wellbeing, moral injury related to poorer quality patient care, feeling unheard and undervalued within the workplace, and pandemic ill-preparedness. Senior doctors desired better crisis preparedness, HCW representation, greater leadership, and accessible, authentic psychological wellbeing support services from workplace organisations and government. The pandemic has had significant impacts on senior doctors. The sustainability of the healthcare system requires interventions designed to protect workforce wellbeing.
Keywords:
coronavirus; COVID-19; healthcare workers; frontline; senior doctors; psychosocial; mental health 1. Introduction
It is well recognised that healthcare workers (HCWs) globally experience higher levels of work-related stress and mental illness compared to the general population [1,2,3,4]. Poor mental health outcomes in HCWs are related to heavy workloads, long working hours, high expectations and demands, poor work–life balance, and the emotional challenges of caring for sick and dying patients [5,6]. Doctors in particular are at increased risk of burnout and stress when compared to other occupational groups [7,8,9], with 10% of doctors in Australia reporting previous thoughts of suicide [10].
During crises such as the current coronavirus disease 2019 (COVID-19) pandemic, healthcare services and the health workforce are placed under enormous stress [11,12] with increased workload, altered work practices (including but not limited to adoption of telehealth and use of personal protective equipment (PPE), role changes (such as redeployment to another medical team), inadequate healthcare resources, large volumes of new information, changing health policies and guidelines, and greater risk of infection with COVID-19 [13,14,15,16,17]. Additionally, population-wide challenges have included lockdowns, social restrictions, loss of non-essential services, and reduced income [16,18,19].
Australian and international studies examining the impacts of the COVID-19 pandemic have reported increased fatigue, distress, anxiety, depression, and burnout amongst frontline HCWs [20,21,22]. While quantitative psychosocial effects of the pandemic on HCWs have been described [20,23,24], there has been very little qualitative research examining HCWs’ lived experiences and expectations related to crisis management [14,16]. The Australian COVID-19 Frontline Healthcare Workers Study examined the severity, prevalence, and predictors of mental health issues in Australian HCWs during the pandemic [20]. This article focuses on a sub-set of the data that reports the experiences of senior doctors to provide an understanding of their perspectives and lived experiences of the workplace and psychosocial impacts of the COVID-19 pandemic. Senior doctors have many years of clinical experience, undertake various workplace responsibilities (as clinicians, educators, and leaders), and have additional personal and family commitments. Given their experience and position in the health hierarchy, their experiences as both leaders and clinicians mean they are uniquely placed to deepen our understanding regarding the impacts of the pandemic. In this sub-study we aimed to identify the experiences and challenges faced by senior doctors during the COVID-19 pandemic and draw on their recommendations regarding workplace wellbeing and future crisis preparedness.
2. Materials and Methods
2.1. Australian COVID-19 Frontline Healthcare Workers Study
The full study methodology has been previously published [20]. To summarise, after ethics approval, a cross-sectional, anonymous, national, online survey was conducted during the second wave of the Australian COVID-19 pandemic between the 27th of August and 23rd of October 2020. Survey information was emailed to hospital leaders throughout Victoria and around Australia for dissemination to colleagues. The survey was also shared by 36 professional colleges, societies and associartions, university medical schools, and government health departments across Australia. Participants were those who self-identified as ‘frontline’ HCWs. They were not required to have cared for patients with COVID-19 to participate in the survey. There were no incentives to participate.
All participants provided online consent to participate in this study. Participants completed the online survey via a direct link or via a purpose-built website, and data were collected using REDcap electronic data capture tools [25]. Data collected in the survey questionnaire included: demographics, home life, professional background, work arrangements and changes, workplace leadership, and symptoms of mental illness (both subjectively determined and objectively measured using five validated psychological scales). In addition, four optional free-text questions were included regarding the challenges of the pandemic on mental health and more broadly (Table 1).
Table 1.
Free-text survey questions.
2.2. Senior Doctors Sub-Study
Only responses to the free text questions from participants who identified as senior medical staff working in secondary and tertiary care were included in this sub-study. Senior medical staff refers to senior doctors who have completed postgraduate specialist training and examinations, and who are overall in charge of a patient’s care. Senior doctors are often referred to as consultants or specialists in many countries. Responses from general practitioners are not included in this sub-study. These have been analysed separately due to their different experiences within the primary care sector. Senior doctors who did not provide any responses to the free-text questions were excluded from this qualitative analysis. An inductive qualitative content approach was used to analyse the free-text responses. This approach aims to describe patterns in the data and interpret meaning from the content [26,27]. The responses to each question were first thoroughly read by JT for data immersion. Based on initial reading, a codebook was developed categorising data into three types of responses: personal issues, workplace issues, or broader societal issues. Each response was coded by JT, and an iterative process was undertaken with additions or amendments to the codebook to ensure emerging ideas were coded.
Data were coded until saturation was reached, meaning that no new ideas were emerging from the data [28]. Rigour in ensuring saturation was achieved by coding all responses by participants (n = 716) who had answered three or four of the free-text questions. Subsequently, every 20th response from those who had only answered one or two questions was coded to verify saturation. The remaining responses (n = 351) were not coded as saturation was obtained. Data codes, ideas, and themes were discussed by three researchers (JT, KW and NS) at weekly meetings, with the final themes reached through consensus discussion.
2.3. Ethics
Approval for this study was obtained through the Royal Melbourne Hospital Human Research Ethics Committee (HREC/67074/MH-2020).
3. Findings
3.1. Study Participants
Of 9518 survey participants, 7846 complete responses were received, including 1278 from senior doctors who formed the sample for this sub-study. Free-text responses to at least one of four questions were received from 1083 senior doctors (84.7%) (Table 1). One hundred and ninety-five senior doctors did not provide any responses to the free-text questions. Of the senior doctors, 96.2% were between the ages of 31–64 years, 58.8% were female, 76.1% resided in the state of Victoria, and 86% had more than 10 years of post-graduate experience (Table 2).
Table 2.
Participants’ characteristics (n = 1278).
3.2. Overview of Findings
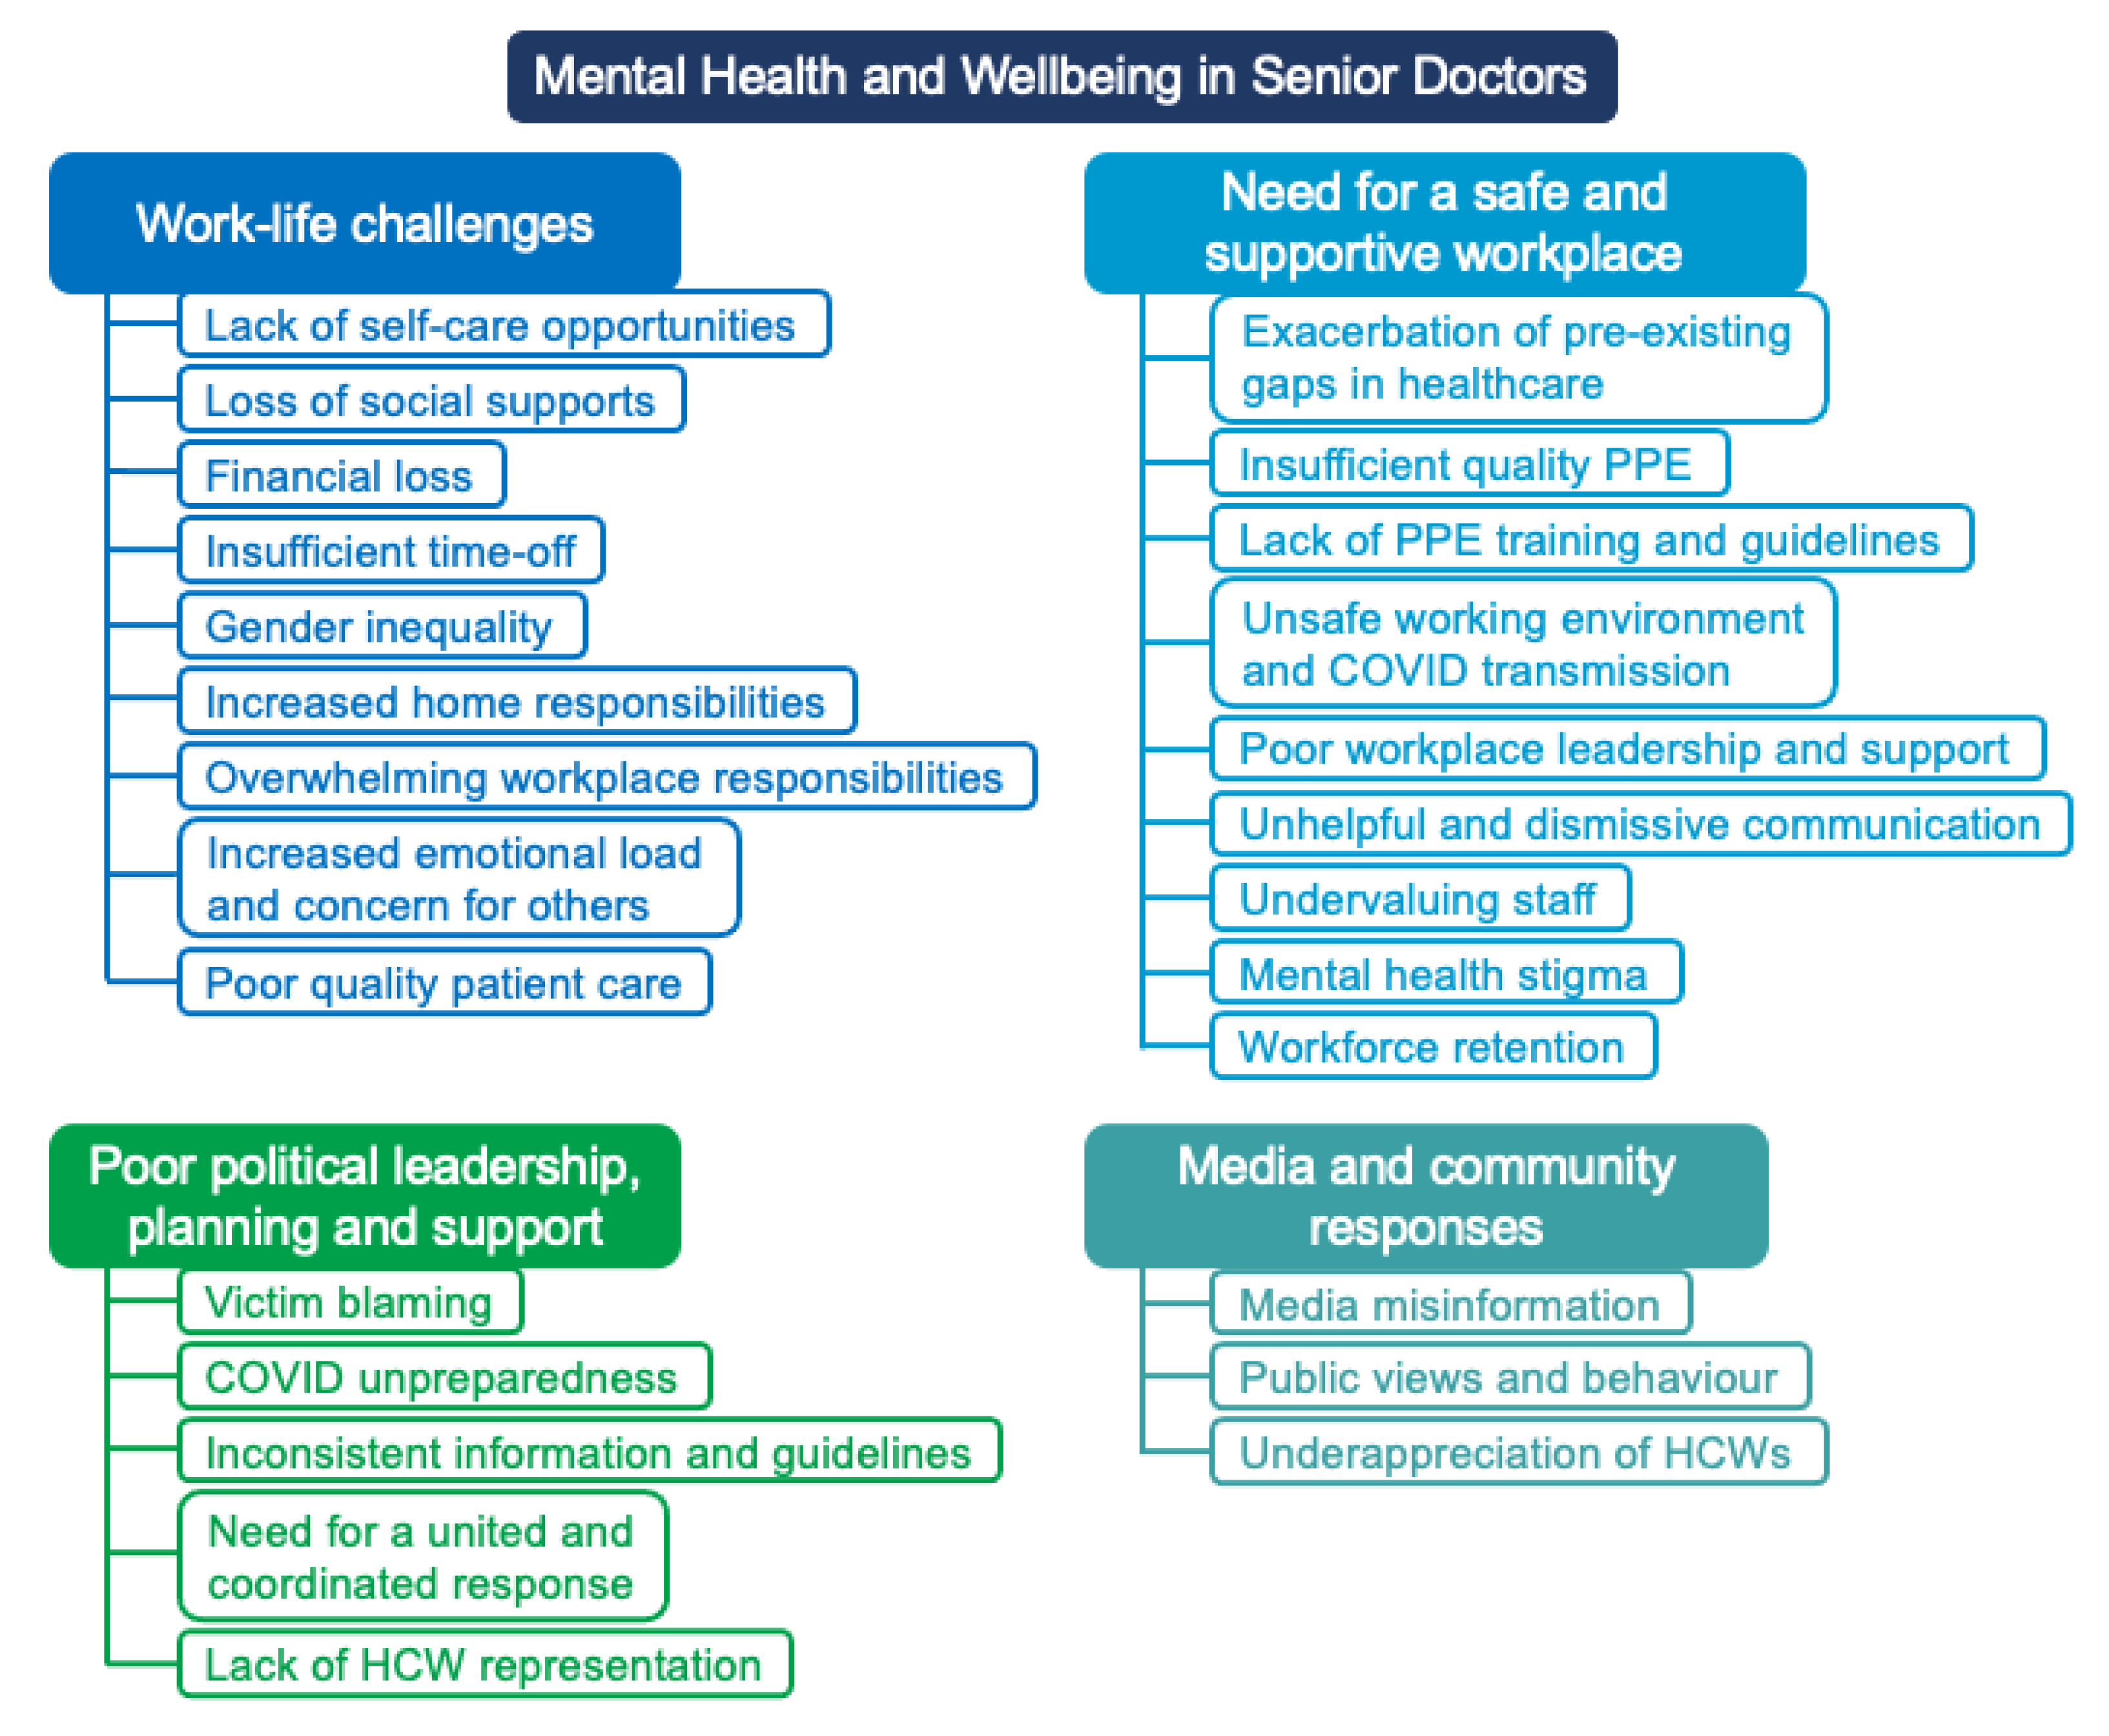
Senior doctors described stress, frustration, and uncertainty during the pandemic, which impacted their mental health. Many senior doctors reported disruptions to their roles and responsibilities at home and in the workplace, leading to substantial strain on their work–life balance and to burnout. Participants also reported feeling their safety was neglected at the workplace, and many felt undervalued by their organisation and the government, with poor leadership at all levels. Community factors, including media misinformation and the views and behaviour of the general public, also contributed to senior doctors feeling frustrated and unappreciated. Four major themes emerged from the data: (1) work-life challenges; (2) poor workplace safety, support, and culture; (3) poor political leadership, planning, and support; and (4) media and community responses (Figure 1).
Figure 1.
Themes: Mental health and wellbeing of Australian senior doctors during the COVID-19 pandemic.
3.3. Theme 1: Work-Life Challenges
Senior medical staff described distress, exhaustion, and burnout associated with work-life challenges and ongoing pandemic uncertainty (Table 3). Disruptions to personal life during the pandemic included a lack of self-care opportunities, inadequate social supports, and financial loss. Many senior doctors also identified the need for more time off to improve physical and mental wellbeing. Female senior doctors also raised issues of gender inequality and described distress related to increased family caring responsibilities, including new homeschooling roles. Senior doctors also felt overwhelmed with increased occupational responsibilities, including additional clinical duties and academic roles. They reported experiencing increased concern and distress associated with supporting the wellbeing of other healthcare workers, such as junior medical staff (JMS), with concerns about the progression of JMS through training during the pandemic. They also wrote about issues relating to quality of patient care associated with the need to rationalise and justify medical interventions, the reduction in access to usual health services, and the adoption of telehealth consultations.
Table 3.
Work–life challenges.
3.4. Theme 2: Poor Workplace Safety, Support, and Culture
Senior doctors reflected on the ongoing issues in the healthcare system including inadequate resources, insufficient workplace support, and poor organisational leadership and communication, which were exacerbated by the COVID-19 pandemic (Table 4). Many participants reported workplace safety as a major challenge during the pandemic due to limited access to PPE, poor quality PPE, inadequate PPE training and guidelines, and unsafe working environments with inadequate space for social distancing and poor ventilation. Senior doctors felt at risk of becoming infected with COVID-19, with significant concerns about transmission to patients, staff, and family members. Senior doctors also believed that workplace leadership and communication during the pandemic were poor, and wrote about feeling unsupported, unheard, and undervalued. Many participants described ongoing mental health stigma in the workplace. Stigma was associated with concerns about consequences to employment and limited access to mental health support services. Worsening mental health coupled with a lack of psychological support raised concerns regarding future workforce retention among senior doctors.
Table 4.
Poor workplace safety, support, and culture.
3.5. Theme 3: Poor Political Leadership, Planning, and Support
Senior doctors described how government departments responded poorly to the increasing COVID-19 case numbers, which included victim blaming of infected HCWs and the slow development and implementation of policies and guidelines (Table 5). They argued that the health system was ill-prepared for this crisis and stressed the importance of developing disaster response plans. To improve future responses, senior doctors described the need for better government planning, a centralised department of health, and better representation of HCWs in organisations and government to facilitate medical policy making.
Table 5.
Poor political leadership, planning, and support.
3.6. Theme 4: Media and Community Responses
Senior doctors were frustrated by the large amount of media misinformation, non-adherence to public health directives by the public, and disruptions within the community (Table 6). Poor efforts from the community to maintain safety left many senior doctors feeling frustrated, concerned for their own health, and underappreciated for the risks they took as HCWs during the pandemic.
Table 6.
Media and community responses.
4. Discussion
To our knowledge, this is the first article describing the in-depth psychological and workplace experiences of Australian senior doctors during the COVID-19 pandemic. Senior doctors represented a unique population with expertise in areas involving workflow and policies in the healthcare system. They provided important perspectives on psychosocial stressors related to workplace issues as hospital leaders and clinicians, as well as on broader societal issues as community members. Key factors that impacted psychological wellbeing in senior doctors included: work–life imbalance related to increased personal and occupational responsibilities, an unsafe and unsupportive workplace, poor political leadership and planning, and poor responses from the community and media. The findings highlight the need to actively support the wellbeing of senior doctors during crises, as a crucial aspect of preparedness planning, enabling workforce retention and the preservation of high-quality patient care. This study underscores the need to destigmatise mental illness and consider innovative approaches to psychological support, as well as strategies to improve access and uptake of these measures long term.
The experiences reported by senior doctors demonstrate broad-ranging personal and workplace impacts of the pandemic, contributing to worsening mental health. Similarly, a recent study of senior specialist doctors in Ireland reported burnout in 77% of doctors, with 64% experiencing adverse effects on their mental health from the COVID-19 pandemic [29]. Another study of mental health amongst obstetricians and gynaecologists in the United Kingdom (UK) during the COVID-19 pandemic showed high rates of major depressive disorder and generalised anxiety disorder in both junior and senior doctors [30]. These findings highlight the importance of identifying strategies that proactively address these concerns.
In addition to increased workplace challenges, senior doctors described many broad stressors during the pandemic. These were often associated with pandemic uncertainty, lockdown restrictions, social isolation, loss of supports, and financial disruption. Other qualitative studies examining psychosocial impacts of the COVID-19 pandemic in frontline healthcare workers in Australia [16], Canada [31], and the UK [32] identified similar personal, professional, and social stressors. These factors have also been recognised in the general adult population, with a recent study demonstrating an association between negative adverse effects on daily life (e.g., loss of work and unemployment) from COVID-19 lockdown restrictions and symptoms of depression or anxiety [33]. Therefore, some of the broader challenges reported by senior doctors in this study, were reflective of population-wide experiences.
Unique to senior doctors is their vital role as leaders in the healthcare workforce. This leadership role involves managing and caring for others—both staff and patients. Senior doctors expressed particular concern for junior doctors, including the impacts on career progression and disruption to training and education. Concerns about maintaining wellbeing and morale of more junior doctors during the COVID-19 pandemic has been reported previously in a qualitative study with doctors in Pakistan, the UK, and the United States of America [34]. These findings showcase the care senior doctors express toward their junior colleagues, which can further add to their emotional load in the workplace.
Concerns regarding the impact of the COVID-19 pandemic on the quality of patient care were highlighted by senior doctors. Having concerns related to the inadequate delivery of patient care while feeling powerless to change the system can be associated with ‘moral injury’, which is an emotional response that occurs following events that contravene a person’s moral values [35]. Moral injury related to patient care and resource scarcity have been identified in HCWs in Australia [14,23] and internationally [36,37,38] during the pandemic, and can contribute to the development of post-traumatic stress, depression and suicide [39]. Conversely, feeling appreciated by the community can be protective against moral injury and adverse mental health outcomes [23]. Importantly, some senior doctors in the current study reported feeling unappreciated by workplace leaders and government. The potential for this to exacerbate the experiences of moral injury and worsen doctors’ mental health is concerning.
Workplace safety, resource scarcity, and poor organisational support were key issues experienced by HCWs [40]. International studies on doctors, nurses, paramedics, allied health professionals, and management staff during the pandemic reported common concerns, which have contributed to mental health symptoms including stress, hypervigilance, fatigue, sleeping difficulties, and difficulties concentrating [41,42]. In addition, reports on HCWs in the National Health Service in the UK have linked feeling undermined and undervalued by their organisation and government with increased burnout, and reduced wellbeing and resilience [43]. As highlighted in our study, this is particularly important for senior doctors who represent leaders in the workplace. Despite their seniority in the medical team hierarchy, many participants still felt that their concerns—namely those regarding safety and provision of PPE—went unheard, leading to feeling undervalued by their organisation. This suggests that even in positions of relative “power”, senior doctors can struggle to implement change in the workplace. Therefore, in support of doctors’ health and wellbeing, the Royal Australian and New Zealand College of Psychiatrists have called for increased access to appropriate PPE for doctors as it represents both a public health and a mental health issue [44]. Similarly, the World Health Professions Alliance called upon governments to prioritise support for frontline HCWs during the COVID-19 crisis [45]. These findings suggest widespread issues regarding organisational and political leadership may have contributed to worsening mental health in senior doctors during the pandemic.
Barriers to accessing care for mental illness in doctors can have long-term mental health and wellbeing sequelae. There have been a range of barriers described including confidentiality concerns, embarrassment, and insufficient time [46]. Nevertheless, the stigma of mental illness, both broadly and in healthcare, remains a significant barrier to accessing mental health support for many doctors [46,47,48]. This stigma is often related to concerns regarding detrimental impacts on career progression and future employment [49], as well as concerns that disclosing mental illness could lead to mandatory reporting, and restrictions on their ability to practise medicine by the Australian Health Practitioner Regulation Agency [50]. To combat this, the Australian Medical Association has called on all jurisdictions to amend the Health Practitioner Regulation National Law, exempting mandatory reporting of doctors experiencing mental illness, similar to the amended model successfully used in Western Australia [51]. For senior doctors, mental health stigma can have severe implications on their ability to work, further exacerbating financial strain during the pandemic, as well as threatening workforce retention. This is further supported by a qualitative study exploring views of senior doctors on mental illness in healthcare in the UK, which also described concerns regarding privacy and confidentiality, and negative career implications [52]. Thus, solutions to improve mental wellbeing in doctors must include actions to reduce the stigma related to mental illness and improve access to psychological support.
4.1. Implications and Future Research
This study documents the significant impacts that the COVID-19 pandemic has had on senior doctors. The risks of moral injury, burnout, and mental health issues in medical leaders within the public and private hospital sectors are important to recognise. The results also highlight important concerns regarding the delivery and quality of patient care, and worsening gender inequality in the workplace during the pandemic. Gender inequality is an important issue in medicine [53] and further research is required to explore its impacts on mental health in senior doctors during the COVID-19 pandemic. Most importantly, our findings emphasise how occupational mental health risk factors can be effectively addressed through appropriate communication, wellbeing support, and the provision of a safe workplace. Senior doctors pointed to the key role they can play as healthcare leaders and clinical experts in future crisis prevention, planning, and management, and the development of policies and guidelines. Strategies that reduce the stigma of mental illness and enhance wellbeing support for all HCWs are essential. The implementation of any new supports and strategies should be supported by research that evaluates the effectiveness of these interventions on mental health. Longitudinal research that documents the continuing psychosocial and workplace impacts of the pandemic on senior doctors is also needed.
4.2. Strengths and Limitations
This study highlights the experiences of senior doctors during a pandemic. The large sample size with a breadth of participants from across Australia enabled an in-depth understanding of the challenges, providing insight to inform future intervention strategies. The senior doctors provided a high volume of detailed responses; a testament to the many issues experienced by this group during the pandemic. Most participants resided in Victoria, the Australian state that experienced the greatest impact from the COVID-19 pandemic during the second wave (in 2020) [54]. Data on broader demographic characteristics such as ethnicity or immigrant status were not collected to reduce the length of the survey and preserve anonymity. However, these data are important, as other reports have documented an increased morbidity and mortality in doctors from ethnic minority backgrounds during the COVID-19 pandemic [55]. The voluntary nature of the survey may have resulted in selection bias and response bias. Respondents experiencing mental health issues may have been more likely to participate in the survey, leading to overreporting. However, this study resonates strongly with the findings from other Australian [20,56,57] and international [21,22] HCW studies.
5. Conclusions
The health and wellbeing of the healthcare workforce is vital to the sustainability of the future healthcare system. This study is one of the first studies reporting the significant impact of COVID-19 pandemic on senior doctors. Better leadership and planning at organisational and government levels, adequate HCW representation, proactive support for mental wellbeing, and reduction in mental health stigma are crucial to ensure workforce retention and reduce negative effects on patient care during future crisis events.
Author Contributions
All authors contributed to this paper. Conceptualization, J.T., K.W. and N.S.; methodology, J.T., K.W. and N.S.; formal analysis, J.T., K.W. and N.S.; writing—original draft preparation, J.T.; writing—review and editing, K.W., M.K., K.H. and N.S.; supervision, K.W. and N.S.; project administration, K.W. and N.S.; funding acquisition, K.W. and N.S. All authors have read and agreed to the published version of the manuscript.
Funding
This research was kindly funded by the Royal Melbourne Hospital Foundation and the Lord Mayor’s Charitable Foundation. Funding bodies had no role in the research activity. All authors were independent from the funders and had access to the study data.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Melbourne Health Human Research Ethics Committee (HREC/67074/MH-2020).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study. Informed consent was obtained prior to completion of the survey. After reading the online participant information sheet, consent was actively provided by completion of a tick box prior to opening the survey questionnaire.
Data Availability Statement
Data available upon reasonable request to the corresponding author.
Acknowledgments
We gratefully acknowledge and thank the Royal Melbourne Hospital Foundation and the Lord Mayor’s Charitable Foundation for financial support for this study. We acknowledge the following people who helped plan and disseminate the survey: Mark Putland, Douglas Johnson, Shyamali Dharmage, Elizabeth Barson, Nicola Atkin, Claire Long, Irene Ng, Anne Holland, Jane Munro, Irani Thevarajan, Cara Moore, Anthony McGillion, and Debra Sandford. We wish to thank the numerous health organisations, universities, professional societies, associations and colleges, and many supportive individuals who assisted in disseminating the survey. We thank the Royal Melbourne Hospital Business Intelligence Unit who provided and hosted the REDCap electronic data capture tools.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Caplan, R.P. Stress, anxiety, and depression in hospital consultants, general practitioners, and senior health service managers. BMJ 1994, 309, 1261–1263. [Google Scholar] [CrossRef] [Scilit]
- Letvak, S.; Ruhm, C.J.; McCoy, T. Depression in hospital-employed nurses. Clin. Nurse Spec. 2012, 26, 177–182. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Imo, U.O. Burnout and psychiatric morbidity among doctors in the UK: A systematic literature review of prevalence and associated factors. BJPsych Bull. 2017, 41, 197–204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- De Cieri, H.; Shea, T.; Cooper, B.; Oldenburg, B. Effects of work-related stressors and mindfulness on mental and physical health among Australian nurses and healthcare workers. J. Nurs. Scholarsh. 2019, 51, 580–589. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Su, J.A.; Weng, H.H.; Tsang, H.Y.; Wu, J.L. Mental health and quality of life among doctors, nurses and other hospital staff. Stress Health J. Int. Soc. Investig. Stress 2009, 25, 423–430. [Google Scholar] [CrossRef] [Scilit]
- Koinis, A.; Giannou, V.; Drantaki, V.; Angelaina, S.; Stratou, E.; Saridi, M. The impact of healthcare workers job environment on their mental-emotional health. Coping strategies: The case of a local general hospital. Health Psychol. Res. 2015, 3, 1984. [Google Scholar] [CrossRef] [Scilit]
- Kumar, S. Burnout and doctors: Prevalence, prevention and intervention. Healthcare 2016, 4, 37. [Google Scholar] [CrossRef] [Scilit]
- Shanafelt, T.D.; Boone, S.; Tan, L.; Dyrbye, L.N.; Sotile, W.; Satele, D.; West, C.P.; Sloan, J.; Oreskovich, M.R. Burnout and satisfaction with work-life balance among US physicians relative to the general US population. Arch. Intern. Med. 2012, 172, 1377–1385. [Google Scholar] [CrossRef] [Scilit]
- McCain, R.S.; McKinley, N.; Dempster, M.; Campbell, W.J.; Kirk, S.J. A study of the relationship between resilience, burnout and coping strategies in doctors. Postgrad. Med. J. 2018, 94, 43–47. [Google Scholar] [CrossRef] [Scilit]
- Wu, F.; Ireland, M.; Hafekost, K.; Lawrence, D. National Mental Health Survey of Doctors and Medical Students; Beyond Blue: Melbourne, Australia, 2013. [Google Scholar]
- Karan, A.; Wadhera, R.K. Healthcare system stress due to COVID-19: Evading an evolving crisis. J. Hosp. Med. 2021, 16, 127. [Google Scholar] [CrossRef] [Scilit]
- Tsamakis, K.; Triantafyllis, A.S.; Tsiptsios, D.; Spartalis, E.; Mueller, C.; Tsamakis, C.; Chaidou, S.; Spandidos, D.A.; Fotis, L.; Economou, M. COVID-19 related stress exacerbates common physical and mental pathologies and affects treatment. Exp. Ther. Med. 2020, 20, 159–162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smallwood, N.; Pascoe, A.; Karimi, L.; Bismark, M.; Willis, K. Occupational Disruptions during the COVID-19 Pandemic and Their Association with Healthcare Workers’ Mental Health. Int. J. Environ. Res. Public Health 2021, 18, 9263. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ananda-Rajah, M.; Veness, B.; Berkovic, D.; Parker, C.; Kelly, G.; Ayton, D. Hearing the voices of Australian healthcare workers during the COVID-19 pandemic. BMJ Lead. 2021, 5, 31–35. [Google Scholar] [CrossRef] [Scilit]
- Adams, J.G.; Walls, R.M. Supporting the health care workforce during the COVID-19 global epidemic. JAMA 2020, 323, 1439–1440. [Google Scholar] [CrossRef] [Scilit]
- Digby, R.; Winton-Brown, T.; Finlayson, F.; Dobson, H.; Bucknall, T. Hospital staff well-being during the first wave of COVID-19: Staff perspectives. Int. J. Ment. Health Nurs. 2021, 30, 440–450. [Google Scholar] [CrossRef] [Scilit]
- Ahmad, F. Canadian clinicians adopting virtual health care during COVID-19 pandemic: Salute to our fast learners. J. Concurr. Disord. 2021, 3, 4–7. [Google Scholar]
- Smallwood, N.; Willis, K. Mental health among healthcare workers during the COVID-19 pandemic. Respirology 2021, 26, 1016. [Google Scholar] [CrossRef] [Scilit]
- Kaye, A.D.; Okeagu, C.N.; Pham, A.D.; Silva, R.A.; Hurley, J.J.; Arron, B.L.; Sarfraz, N.; Lee, H.N.; Ghali, G.E.; Gamble, J.W. Economic impact of COVID-19 pandemic on healthcare facilities and systems: International perspectives. Best. Pract. Res. Clin. Anaesthesiol. 2021, 35, 293–306. [Google Scholar] [CrossRef] [Scilit]
- Smallwood, N.; Karimi, L.; Bismark, M.; Putland, M.; Johnson, D.; Dharmage, S.C.; Barson, E.; Atkin, N.; Long, C.; Ng, I. High levels of psychosocial distress among Australian frontline healthcare workers during the COVID-19 pandemic: A cross-sectional survey. Gen. Psychiatr. 2021, 34, e100577. [Google Scholar] [CrossRef] [Scilit]
- Spoorthy, M.S.; Pratapa, S.K.; Mahant, S. Mental health problems faced by healthcare workers due to the COVID-19 pandemic–A review. Asian J. Psychiatr. 2020, 51, 102119. [Google Scholar] [CrossRef] [Scilit]
- Vizheh, M.; Qorbani, M.; Arzaghi, S.M.; Muhidin, S.; Javanmard, Z.; Esmaeili, M. The mental health of healthcare workers in the COVID-19 pandemic: A systematic review. J. Diabetes Metab. Disord. 2020, 19, 1967–1978. [Google Scholar] [CrossRef] [Scilit]
- Smallwood, N.; Pascoe, A.; Karimi, L.; Willis, K. Moral distress and perceived community views are associated with mental health symptoms in frontline health workers during the COVID-19 pandemic. Int. J. Environ. Res. Public Health 2021, 18, 8723. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pappa, S.; Ntella, V.; Giannakas, T.; Giannakoulis, V.G.; Papoutsi, E.; Katsaounou, P. Prevalence of depression, anxiety, and insomnia among healthcare workers during the COVID-19 pandemic: A systematic review and meta-analysis. Brain. Behav. Immun. 2020, 88, 901–907. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harris, P.A.; Taylor, R.; Thielke, R.; Payne, J.; Gonzalez, N.; Conde, J.G. Research electronic data capture (REDCap)—A metadata-driven methodology and workflow process for providing translational research informatics support. J. Biomed. Inform. 2009, 42, 377–381. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morgan, D.L. Qualitative content analysis: A guide to paths not taken. Qual. Health Res. 1993, 3, 112–121. [Google Scholar] [CrossRef] [Scilit]
- Hsieh, H.-F.; Shannon, S.E. Three approaches to qualitative content analysis. Qual. Health Res. 2005, 15, 1277–1288. [Google Scholar] [CrossRef] [Scilit]
- Saunders, B.; Sim, J.; Kingstone, T.; Baker, S.; Waterfield, J.; Bartlam, B.; Burroughs, H.; Jinks, C. Saturation in qualitative research: Exploring its conceptualization and operationalization. Qual. Quant. 2018, 52, 1893–1907. [Google Scholar] [CrossRef] [Scilit]
- Doherty, A.M.; Colleran, G.C.; Durcan, L.; Irvine, A.D.; Barrett, E. A pilot study of burnout and long covid in senior specialist doctors. Ir. J. Med. Sci. 2021, 191, 133–137. [Google Scholar] [CrossRef] [Scilit]
- Shah, N.; Raheem, A.; Sideris, M.; Velauthar, L.; Saeed, F. Mental health amongst obstetrics and gynaecology doctors during the COVID-19 pandemic: Results of a UK-wide study. Eur. J. Obstet. Gynecol. 2020, 253, 90–94. [Google Scholar] [CrossRef] [Scilit]
- Leigh, J.P.; Kemp, L.G.; de Grood, C.; Brundin-Mather, R.; Stelfox, H.T.; Ng-Kamstra, J.S.; Fiest, K.M. A qualitative study of physician perceptions and experiences of caring for critically ill patients in the context of resource strain during the first wave of the COVID-19 pandemic. BMC Health Serv. Res. 2021, 21, 374. [Google Scholar]
- Aughterson, H.; McKinlay, A.R.; Fancourt, D.; Burton, A. Psychosocial impact on frontline health and social care professionals in the UK during the COVID-19 pandemic: A qualitative interview study. BMJ Open 2021, 11, e047353. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fisher, J.R.; Tran, T.D.; Hammarberg, K.; Sastry, J.; Nguyen, H.; Rowe, H.; Popplestone, S.; Stocker, R.; Stubber, C.; Kirkman, M. Mental health of people in Australia in the first month of COVID-19 restrictions: A national survey. Med. J. Aust. 2020, 213, 458–464. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Urooj, U.; Ansari, A.; Siraj, A.; Khan, S.; Tariq, H. Expectations, fears and perceptions of doctors during COVID-19 pandemic. Pak. J. Med. Sci. 2020, 36, S37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Litz, B.T.; Stein, N.; Delaney, E.; Lebowitz, L.; Nash, W.P.; Silva, C.; Maguen, S. Moral injury and moral repair in war veterans: A preliminary model and intervention strategy. Clin. Psychol. Rev. 2009, 29, 695–706. [Google Scholar] [CrossRef] [Scilit]
- Litam, S.D.A.; Balkin, R.S. Moral injury in health-care workers during COVID-19 pandemic. Traumatology 2021, 27, 14. [Google Scholar] [CrossRef] [Scilit]
- Hines, S.E.; Chin, K.H.; Glick, D.R.; Wickwire, E.M. Trends in moral injury, distress, and resilience factors among healthcare workers at the beginning of the COVID-19 pandemic. Int. J. Environ. Res. Public Health 2021, 18, 488. [Google Scholar] [CrossRef] [Scilit]
- Liberati, E.; Richards, N.; Willars, J.; Scott, D.; Boydell, N.; Parker, J.; Pinfold, V.; Martin, G.; Dixon-Woods, M.; Jones, P.B. A qualitative study of experiences of NHS mental healthcare workers during the COVID-19 pandemic. BMC Psychiatry 2021, 21, 250. [Google Scholar] [CrossRef] [Scilit]
- Williamson, V.; Stevelink, S.A.; Greenberg, N. Occupational moral injury and mental health: Systematic review and meta-analysis. Br. J. Psychiatry 2018, 212, 339–346. [Google Scholar] [CrossRef] [Scilit]
- Vanhaecht, K.; Seys, D.; Bruyneel, L.; Cox, B.; Kaesemans, G.; Cloet, M.; Van Den Broeck, K.; Cools, O.; De Witte, A.; Lowet, K. COVID-19 is having a destructive impact on health-care workers’ mental well-being. Int. J. Qual. Health Care 2021, 33, mzaa158. [Google Scholar] [CrossRef] [Scilit]
- Ahmed, J.; Malik, F.; Arif, T.B.; Majid, Z.; Chaudhary, M.A.; Ahmad, J.; Malik, M.; Khan, T.M.; Khalid, M. Availability of personal protective equipment (PPE) among US and Pakistani doctors in COVID-19 pandemic. Cureus 2020, 12, e8550. [Google Scholar]
- Vindrola-Padros, C.; Andrews, L.; Dowrick, A.; Djellouli, N.; Fillmore, H.; Gonzalez, E.B.; Javadi, D.; Lewis-Jackson, S.; Manby, L.; Mitchinson, L. Perceptions and experiences of healthcare workers during the COVID-19 pandemic in the UK. BMJ Open 2020, 10, e040503. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Best, J. Undermined and undervalued: How the pandemic exacerbated moral injury and burnout in the NHS. BMJ 2021, 374, n1858. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- RANZCP. PPE Remains a Focus for All Healthcare Professionals; RANZCP: Melbourne, Australia, 2020. [Google Scholar]
- WHPA. World Health Professionals Call on Governments to Prioritise Support for Healthcare Workers in the Frontline against Coronavirus; WHPA: Geneva, Switzerland, 2020. [Google Scholar]
- Kay, M.; Mitchell, G.; Clavarino, A.; Doust, J. Doctors as patients: A systematic review of doctors’ health access and the barriers they experience. Br. J. Gen. Pract. 2008, 58, 501–508. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hayes, B.; Prihodova, L.; Walsh, G.; Doyle, F.; Doherty, S. What’s up doc? A national cross-sectional study of psychological wellbeing of hospital doctors in Ireland. BMJ Open 2017, 7, e018023. [Google Scholar] [CrossRef] [Scilit]
- Forbes, M.P.; Iyengar, S.; Kay, M. Barriers to the psychological well-being of Australian junior doctors: A qualitative analysis. BMJ Open 2019, 9, e027558. [Google Scholar] [CrossRef] [Scilit]
- Garelick, A.I. Doctors’ health: Stigma and the professional discomfort in seeking help. Psychiatrist 2012, 36, 81–84. [Google Scholar] [CrossRef] [Scilit]
- Bismark, M.M.; Spittal, M.J.; Plueckhahn, T.M.; Studdert, D.M. Mandatory reports of concerns about the health, performance and conduct of health practitioners. Med. J. Aust. 2014, 201, 399–403. [Google Scholar] [CrossRef] [Scilit]
- AMA. Position Statement: Health and Wellbeing of Doctors and Medical Students; AMA: Barton, Australia, 2020. [Google Scholar]
- Bianchi, E.F.; Bhattacharyya, M.R.; Meakin, R. Exploring senior doctors’ beliefs and attitudes regarding mental illness within the medical profession: A qualitative study. BMJ Open 2016, 6, e012598. [Google Scholar] [CrossRef] [Scilit]
- Halley, M.C.; Mathews, K.S.; Diamond, L.C.; Linos, E.; Sarkar, U.; Mangurian, C.; Sabry, H.; Goyal, M.K.; Olazo, K.; Miller, E.G.; et al. The intersection of work and home challenges faced by physician mothers during the coronavirus disease 2019 pandemic: A mixed-methods analysis. J. Women’s Health 2021, 30, 514–524. [Google Scholar] [CrossRef] [Scilit]
- Coronavirus (COVID-19) at a Glance—23 October 2020. Available online: https://www.health.gov.au/resources/publications/coronavirus-covid-19-at-a-glance-23-october-2020 (accessed on 29 September 2021).
- Mahase, E. COVID-19: UK study aims to understand effects on ethnic minority healthcare workers. BMJ 2021, 372, n23. [Google Scholar] [CrossRef] [Scilit]
- Dobson, H.; Malpas, C.B.; Burrell, A.J.; Gurvich, C.; Chen, L.; Kulkarni, J.; Winton-Brown, T. Burnout and psychological distress amongst Australian healthcare workers during the COVID-19 pandemic. Australas. Psychiatry 2021, 29, 26–30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Holton, S.; Wynter, K.; Trueman, M.; Bruce, S.; Sweeney, S.; Crowe, S.; Dabscheck, A.; Eleftheriou, P.; Booth, S.; Hitch, D. Psychological well-being of Australian hospital clinical staff during the COVID-19 pandemic. Aust. Health Rev. 2020, 45, 297–305. [Google Scholar] [CrossRef] [Scilit] [PubMed]


Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).