
Next-Generation Sequencing in Pulmonary Fibrosis: Translational Promise and Current Clinical Limitations

 , ,
 ,
 and
Abstract
1. Introduction
2. Principles and Technologies of Next-Generation Sequencing
3. Genetics of Pulmonary Fibrosis: Contributions from NGS
3.1. Telomere-Related Genes and the Senescence Paradigm
3.2. Surfactant-Related Genes and Alveolar Type II Epithelial Dysfunction
3.3. Common Susceptibility Loci and the Polygenic Architecture
3.4. Interstitial Lung Abnormalities and Preclinical Genetic Risk
3.5. Missing Heritability and Gene-Environment Interactions
3.6. Ancestry Gaps and the Need for Global Diversity
4. NGS in the Differential Diagnosis of Pulmonary Fibrosis
4.1. NGS as a Tool for Distinguishing Between Overlapping Fibrotic Phenotypes
4.1.1. NGS in Familial Pulmonary Fibrosis (FPF)
4.1.2. NGS in Sporadic and Other Fibrotic ILDs
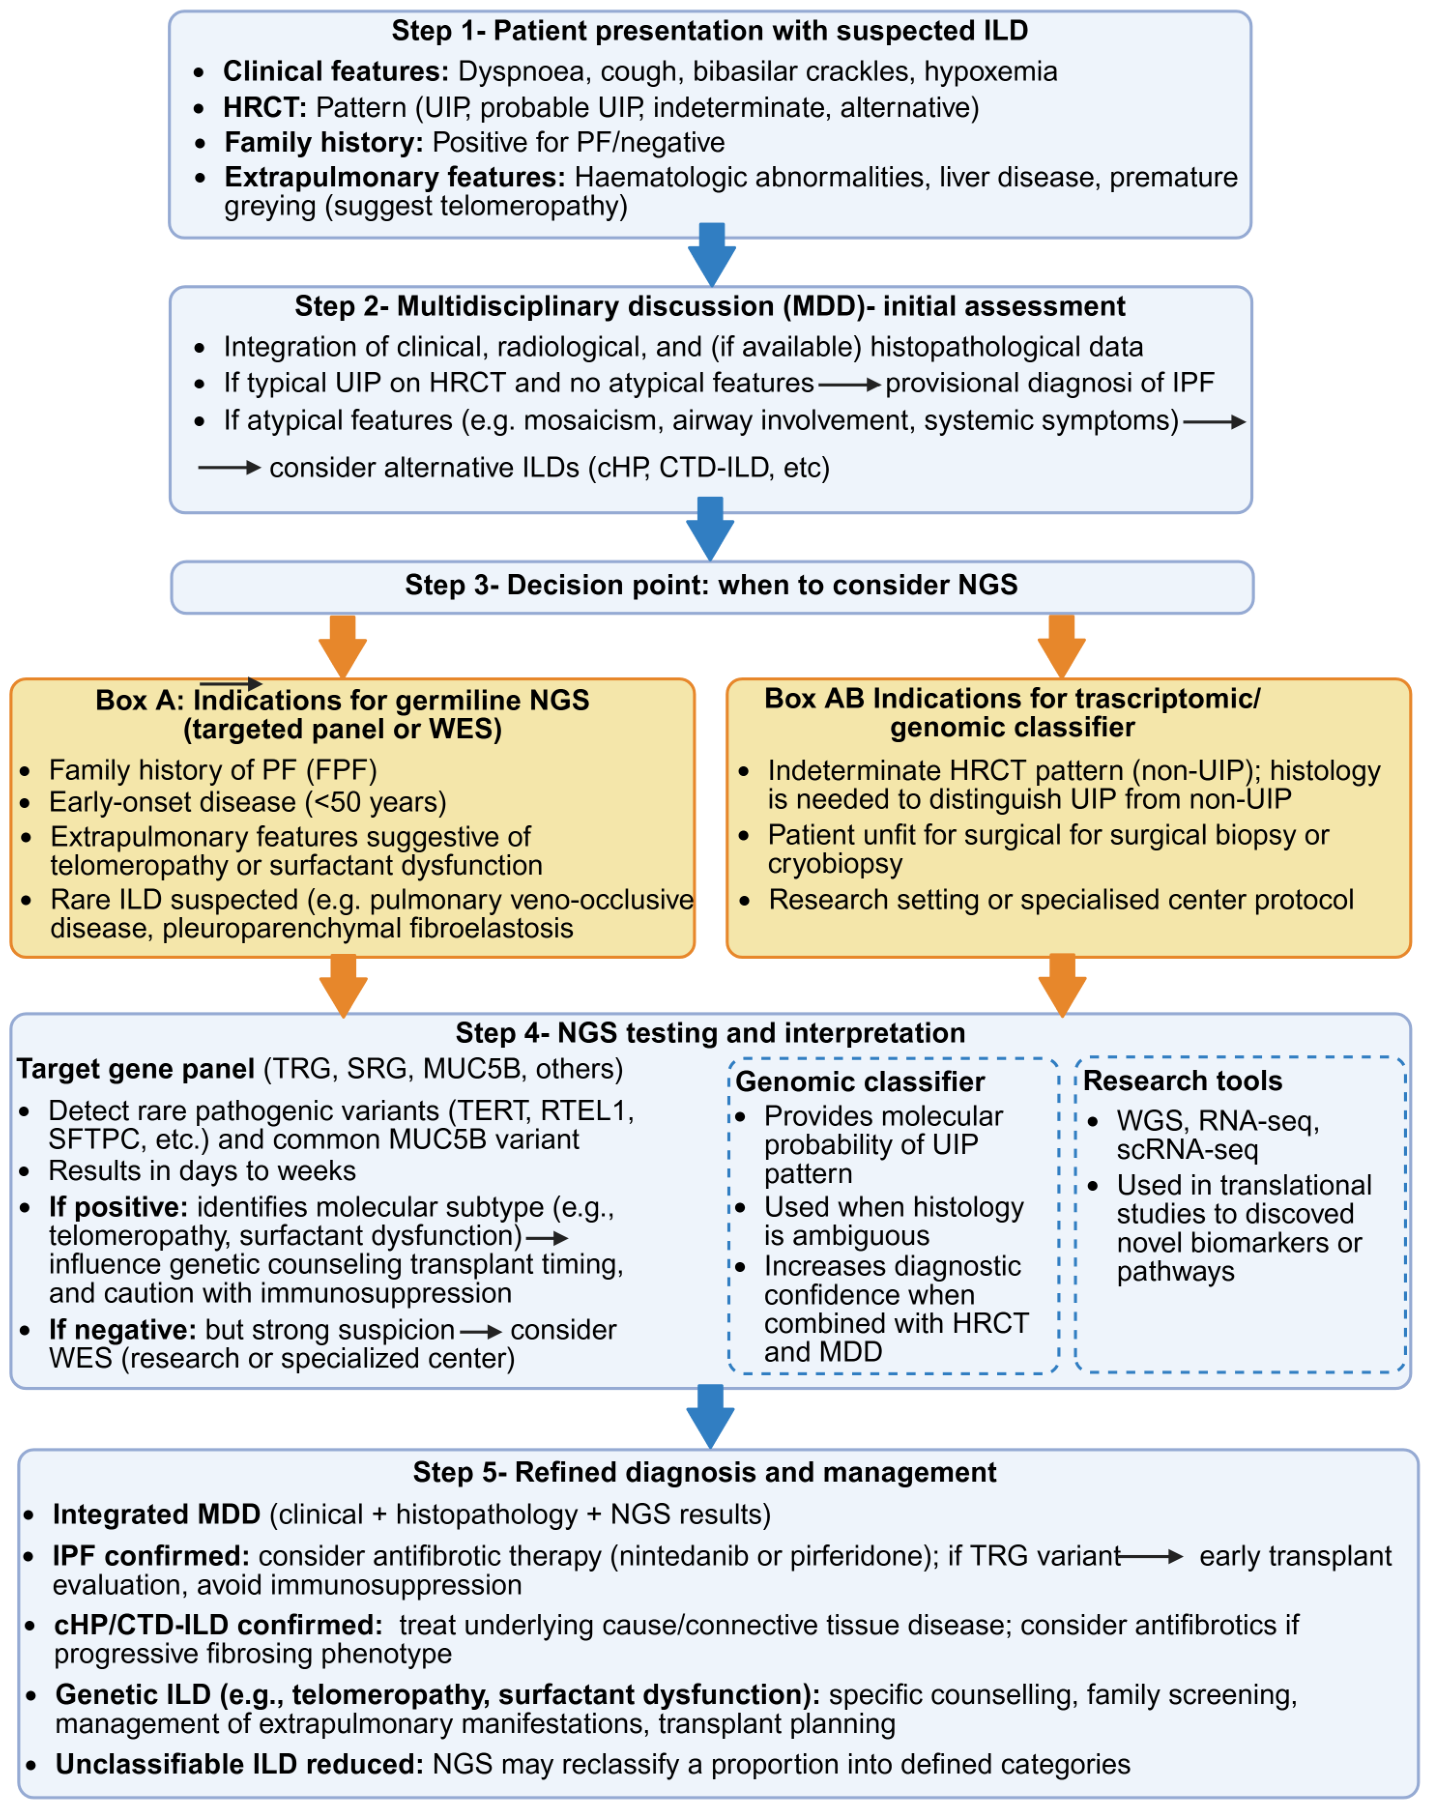
4.2. Integration with Clinical, Radiological, and Histological Data
4.3. Use of Targeted Gene Panels for More Precise Diagnosis
5. Transcriptomics and Biomarker Discovery Through NGS
5.1. RNA-Seq and Gene Expression Profiling in Fibrotic Diseases
5.2. Identification of Key Dysregulated Pathways
5.3. Discovery of Molecular Phenotypes and Potential Biomarkers for Prognosis or Treatment Response
5.4. Pharmacogenomic Insight and Its Limitations
6. Impact of NGS on Therapy and Precision Medicine
7. Translational Potential and Clinical Limitations of NGS in PF
7.1. What NGS Can Currently Offer
- (1)
- Genetic diagnosis in suspected FPF (diagnostic yield 20–30% for telomere variants) [35].
- (2)
- Identification of pathogenic variants in early-onset ILD (<50 years) or with telomere syndrome features.
- (3)
- Guidance for family counselling and early transplant referral in telomere variant carriers.
- (4)
- Definitive diagnosis of rare monogenic ILDs (e.g., EIF2AK4 in pulmonary veno-occlusive disease).
7.2. What NGS Cannot Yet Do
- (1)
- Guide first-line choice between pirfenidone and nintedanib in sporadic IPF (no prospective pharmacogenomic validation).
- (2)
- Replace MDD as diagnostic gold standard.
- (3)
- Provide reliable individual prognostic stratification using common variants (e.g., MUC5B).
- (4)
- Serve as a standalone screening test for ILAs or early IPF.
7.3. Key Clinical Limitations
- (1)
- VUS: Substantial proportion, causing uncertainty and anxiety.
- (2)
- Lack of standardisation: Panels vary widely; no universal panel.
- (3)
- Cost and accessibility: WES/WGS expensive; inconsistent reimbursement.
- (4)
- Genetic counselling gap: Many ILD clinics lack counsellors.
- (5)
- Ancestry bias: Most data from European cohorts.
8. Practical Clinical Relevance: How NGS Informs Diagnosis, Prognosis, and Treatment
8.1. Diagnosis
8.2. Prognosis
8.3. Treatment Implications (Current and Emerging)
8.4. Current Guidelines and Expert Statements
9. Conclusions: Current Limitations and Future Perspectives
Author Contributions
Funding
Data Availability Statement
Conflicts of Interest
References
- Glass, D.S.; Grossfeld, D.; Renna, H.A.; Agarwala, P.; Spiegler, P.; DeLeon, J.; Reiss, A.B. Idiopathic pulmonary fibrosis: Current and future treatment. Clin. Respir. J. 2022, 16, 84–96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Agnano, V.; Perrotta, F.; Fomez, R.; Carrozzo, V.M.; Schiattarella, A.; Sanduzzi Zamparelli, S.; Pagliaro, R.; Bianco, A.; Mariniello, D.F. Pharmacological Treatment of Interstitial Lung Diseases: A Novel Landscape for Inhaled Agents. Pharmaceutics 2024, 16, 1391. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Agnano, V.; Mariniello, D.F.; Pagliaro, R.; Far, M.S.; Schiattarella, A.; Scialò, F.; Stella, G.; Matera, M.G.; Cazzola, M.; Bianco, A.; et al. Sirtuins and Cellular Senescence in Patients with Idiopathic Pulmonary Fibrosis and Systemic Autoimmune Disorders. Drugs 2024, 84, 491–501. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raghu, G.; Collard, H.R.; Egan, J.J.; Martinez, F.J.; Behr, J.; Brown, K.K.; Colby, T.V.; Cordier, J.F.; Flaherty, K.R.; Lasky, J.A.; et al. An official ATS/ERS/JRS/ALAT statement: Idiopathic pulmonary fibrosis: Evidence-based guidelines for diagnosis and management. Am. J. Respir. Crit. Care Med. 2011, 183, 788–824. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Perrotta, F.; Sanduzzi Zamparelli, S.; D’Agnano, V.; Montella, A.; Fomez, R.; Pagliaro, R.; Schiattarella, A.; Cazzola, M.; Bianco, A.; Mariniello, D.F. Genomic Profiling for Predictive Treatment Strategies in Fibrotic Interstitial Lung Disease. Biomedicines 2024, 12, 1384. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, Q.; Zhou, Y.; Cogan, J.D.; Mitchell, D.B.; Sheng, Q.; Zhao, S.; Bai, Y.; Ciombor, K.K.; Sabusap, C.M.; Malabanan, M.M.; et al. The Genetic Landscape of Familial Pulmonary Fibrosis. Am. J. Respir. Crit. Care Med. 2023, 207, 1345–1357. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lawson, W.E.; Grant, S.W.; Ambrosini, V.; Womble, K.E.; Dawson, E.P.; Lane, K.B.; Markin, C.; Renzoni, E.; Lympany, P.; Thomas, A.Q.; et al. Genetic mutations in surfactant protein C are a rare cause of sporadic cases of IPF. Thorax 2004, 59, 977–980. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seibold, M.A.; Wise, A.L.; Speer, M.C.; Steele, M.P.; Brown, K.K.; Loyd, J.E.; Fingerlin, T.E.; Zhang, W.; Gudmundsson, G.; Groshong, S.D.; et al. A common MUC5B promoter polymorphism and pulmonary fibrosis. N. Engl. J. Med. 2011, 364, 1503–1512. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Satam, H.; Joshi, K.; Mangrolia, U.; Waghoo, S.; Zaidi, G.; Rawool, S.; Thakare, R.P.; Banday, S.; Mishra, A.K.; Das, G.; et al. Next-Generation Sequencing Technology: Current Trends and Advancements. Biology 2023, 12, 997, Erratum in Biology 2024, 13, 286. https://doi.org/10.3390/biology12070997. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abbasi, A.; Alexandrov, L.B. Significance and limitations of the use of next-generation sequencing technologies for detecting mutational signatures. DNA Repair 2021, 107, 103200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Redente, E.F.; Song, T.; Javkhlan, N.; Edelman, B.L.; Foster, D.G.; Wilson, J.A.; Chakraborty, S.; Cooley, J.C.; Gaurav, R.; Saguthi, S.; et al. Conditional BCL-2 Expression in Fibroblasts Promotes Persistent Pulmonary Fibrosis which is Reversible by Therapeutic BCL-2 Inhibition. Nat. Commun. 2026, 17, 3317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jaiswal, A.; Kooistra, T.; Pokatayev, V.; Bastos, H.N.; Santos, R.F.; Sarraf, T.R.; Segerstolpe, Å.; Lin, C.; Amir-Zilberstein, L.; Twardus, S.; et al. Spatial transcriptomics reveals altered communities and drivers of aberrant epithelia and pro-fibrotic fibroblasts in interstitial lung diseases. Cell Genom. 2026, 6, 101066. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jin, C.; Chen, Y.; Wang, Y.; Li, J.; Liang, J.; Zheng, S.; Zhang, L.; Li, Q.; Wang, Y.; Ling, F.; et al. Single-cell RNA sequencing reveals special basal cells and fibroblasts in idiopathic pulmonary fibrosis. Sci. Rep. 2024, 14, 15778. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Richards, S.; Aziz, N.; Bale, S.; Bick, D.; Das, S.; Gastier-Foster, J.; Grody, W.W.; Hegde, M.; Lyon, E.; Spector, E.; et al. Standards and guidelines for the interpretation of sequence variants: A joint consensus recommendation of the American College of Medical Genetics and Genomics and the Association for Molecular Pathology. Genet. Med. 2015, 17, 405–424. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brancato, D.; Treccarichi, S.; Bruno, F.; Coniglio, E.; Vinci, M.; Saccone, S.; Calì, F.; Federico, C. NGS Approaches in Clinical Diagnostics: From Workflow to Disease-Specific Applications. Int. J. Mol. Sci. 2025, 26, 9597. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shen, T.; Pajaro-Van de Stadt, S.H.; Yeat, N.C.; Lin, J.C. Clinical applications of next generation sequencing in cancer: From panels, to exomes, to genomes. Front. Genet. 2015, 6, 215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adegunsoye, A.; Newton, C.A.; Oldham, J.M.; Ley, B.; Lee, C.T.; Linderholm, A.L.; Chung, J.H.; Garcia, N.; Zhang, D.; Vij, R.; et al. Telomere length associates with chronological age and mortality across racially diverse pulmonary fibrosis cohorts. Nat. Commun. 2023, 14, 1489. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, H.; Sun, K.; Peng, H.; Wang, Y.; Zhang, L. Emerging roles of noncoding RNAs in idiopathic pulmonary fibrosis. Cell Death Discov. 2024, 10, 443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gill, S.K.; Gomer, R.H. Translational Regulators in Pulmonary Fibrosis: MicroRNAs, Long Non-Coding RNAs, and Transcript Modifications. Cells 2025, 14, 536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, J.W.; Na, H.Y.; Lee, S.; Kim, J.W.; Suh, K.J.; Kim, S.H.; Kim, Y.J.; Lee, K.W.; Lee, J.S.; Kim, J.; et al. Clinical implementation of next-generation sequencing testing and genomically-matched therapy: A real-world data in a tertiary hospital. Sci. Rep. 2025, 15, 2171. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cutting, C.C.; Bowman, W.S.; Dao, N.; Pugashetti, J.V.; Garcia, C.K.; Oldham, J.M.; Newton, C.A. Family History of Pulmonary Fibrosis Predicts Worse Survival in Patients With Interstitial Lung Disease. Chest 2021, 159, 1913–1921. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kropski, J.A.; Pritchett, J.M.; Zoz, D.F.; Crossno, P.F.; Markin, C.; Garnett, E.T.; Degryse, A.L.; Mitchell, D.B.; Polosukhin, V.V.; Rickman, O.B.; et al. Extensive phenotyping of individuals at risk for familial interstitial pneumonia reveals clues to the pathogenesis of interstitial lung disease. Am. J. Respir. Crit. Care Med. 2015, 191, 417–426. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsakiri, K.D.; Cronkhite, J.T.; Kuan, P.J.; Xing, C.; Raghu, G.; Weissler, J.C.; Rosenblatt, R.L.; Shay, J.W.; Garcia, C.K. Adult-Onset Pulmonary Fibrosis Caused by Mutations in Telomerase. Proc. Natl. Acad. Sci. USA 2007, 104, 7552–7557. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Armanios, M.Y.; Chen, J.J.; Cogan, J.D.; Alder, J.K.; Ingersoll, R.G.; Markin, C.; Lawson, W.E.; Xie, M.; Vulto, I.; Phillips, J.A., 3rd; et al. Telomerase mutations in families with idiopathic pulmonary fibrosis. N. Engl. J. Med. 2026, 356, 1317–1326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adegunsoye, A.; Kropski, J.A.; Behr, J.; Blackwell, T.S.; Corte, T.J.; Cottin, V.; Glanville, A.R.; Glassberg, M.K.; Griese, M.; Hunninghake, G.M.; et al. Genetics and Genomics of Pulmonary Fibrosis: Charting the Molecular Landscape and Shaping Precision Medicine. Am. J. Respir. Crit. Care Med. 2024, 210, 401–423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kan, G.; Wang, Z.; Sheng, C.; Chen, G.; Yao, C.; Mao, Y.; Chen, S. Dual Inhibition of DKC1 and MEK1/2 Synergistically Restrains the Growth of Colorectal Cancer Cells. Adv. Sci. 2021, 8, 2004344. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kropski, J.A.; Mitchell, D.B.; Markin, C.; Polosukhin, V.V.; Choi, L.; Johnson, J.E.; Lawson, W.E.; Phillips, J.A., 3rd; Cogan, J.D.; Blackwell, T.S.; et al. A novel dyskerin (DKC1) mutation is associated with familial interstitial pneumonia. Chest 2014, 146, E1–E7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wright, J.R. Immunoregulatory functions of surfactant proteins. Nat. Rev. Immunol. 2005, 5, 58–68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Markart, P.; Ruppert, C.; Wygrecka, M.; Schmidt, R.; Korfei, M.; Harbach, H.; Theruvath, I.; Pison, U.; Seeger, W.; Guenther, A.; et al. Surfactant protein C mutations in sporadic forms of idiopathic interstitial pneumonias. Eur. Respir. J. 2007, 29, 134–137. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fingerlin, T.E.; Murphy, E.; Zhang, W.; Peljto, A.L.; Brown, K.K.; Steele, M.P.; Loyd, J.E.; Cosgrove, G.P.; Lynch, D.; Groshong, S.; et al. Genome-wide association study identifies multiple susceptibility loci for pulmonary fibrosis. Nat. Genet. 2013, 45, 613–620, Erratum in Nat. Genet. 2013, 45, 1409. https://doi.org/10.1038/ng.2609. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maher, T.M.; Nambiar, A.M.; Wells, A.U. The role of precision medicine in interstitial lung disease. Eur. Respir. J. 2022, 60, 2102146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sanduzzi Zamparelli, S.; Sanduzzi Zamparelli, A.; Bocchino, M. The Evolving Concept of the Multidisciplinary Approach in the Diagnosis and Management of Interstitial Lung Diseases. Diagnostics 2023, 13, 2437. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Villeneuve, J.; Tremblay, É.; Gaudreault, N.; Saavedra Armero, V.; Boudreau, D.K.; Li, Z.; Renaut, S.; Dion, G.; Bossé, Y. A Test to Comprehensively Capture the Known Genetic Component of Familial Pulmonary Fibrosis. Am. J. Respir. Cell Mol. Biol. 2024, 70, 437–445. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gigante, A.R.; Tinoco, E.M.; Fonseca, A.; Marques, I.; Sanches, A.; Salgueiro, N.; Nogueira, C.; Campainha, S.; Neves, S. Use of Next-Generation Sequencing to Support the Diagnosis of Familial Interstitial Pneumonia. Genes 2023, 14, 326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Newton, C.A.; Oldham, J.M.; Applegate, C.; Carmichael, N.; Powell, K.; Dilling, D.; Schmidt, S.L.; Scholand, M.B.; Armanios, M.; Garcia, C.K.; et al. Pulmonary Fibrosis Foundation Genetic Testing Work Group. The Role of Genetic Testing in Pulmonary Fibrosis: A Perspective From the Pulmonary Fibrosis Foundation Genetic Testing Work Group. Chest 2022, 162, 394–405. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, C.; Du, Q.; Wang, S.; Zhang, R. A rare compound heterozygous EIF2AK4 mutation in pulmonary veno-occlusive disease. BMC Pulm. Med. 2022, 22, 455. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goos, T.; Verleden, S.E.; De Sadeleer, L.J.; Van Herck, A.; Sacreas, A.; Vanstapel, A.; Kaes, J.; Geudens, V.; Aelbrecht, C.; Ruttens, D.; et al. The MUC5B Promoter Polymorphism is Not Associated With Non-ILD Chronic Respiratory Diseases or Post-transplant Outcome. Transpl. Int. 2022, 35, 10159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mouawad, A.; Chouery, E.; Chebly, A.; Salem, N.; Corbani, S.; Safieddine, M.; Dabar, G. Association of the MUC5B promoter polymorphism with idiopathic pulmonary fibrosis in a lebanese cohort. Front. Genet. 2025, 16, 1544864. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, Q.Q.; Zhang, X.L.; Zhang, S.M.; Tang, S.W.; Min, H.Y.; Yi, L.; Xu, B.; Song, Y. Association Between the MUC5B Promoter Polymorphism rs35705950 and Idiopathic Pulmonary Fibrosis: A Meta-analysis and Trial Sequential Analysis in Caucasian and Asian Populations. Medicine 2015, 94, e1901. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, D.; Guler, S.A.; Shannon, C.P.; Ryerson, C.J.; Tebbutt, S.J. Transcriptomics of interstitial lung disease: A systematic review and meta-analysis. Eur. Respir. J. 2024, 65, 2401070. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adegunsoye, A.; Vij, R.; Noth, I. Integrating Genomics Into Management of Fibrotic Interstitial Lung Disease. Chest 2019, 155, 1026–1040. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Franco, G.; Ba, I.; Nathan, N.; Guerin, C.; Lassus, A.; Kannengiesser, C.; Froidure, A.; Manali, E.; Bunel, V.; Bonniaud, P.; et al. Respifil and OrphaLung. Impact of A Multidisciplinary Team Discussion for Genetic Lung Fibrosis. Respirology 2025, 30, 523–532. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kheir, F.; Uribe Becerra, J.P.; Bissell, B.; Ghazipura, M.; Herman, D.; Hon, S.M.; Hossain, T.; Khor, Y.H.; Knight, S.L.; Kreuter, M.; et al. Use of a Genomic Classifier in Patients with Interstitial Lung Disease: A Systematic Review and Meta-Analysis. Ann. Am. Thorac. Soc. 2022, 19, 827–832. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Glenn, L.M.; Troy, L.K.; Corte, T.J. Novel diagnostic techniques in interstitial lung disease. Front. Med. 2023, 10, 1174443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raghu, G.; Remy-Jardin, M.; Richeldi, L.; Thomson, C.C.; Inoue, Y.; Johkoh, T.; Kreuter, M.; Lynch, D.A.; Maher, T.M.; Martinez, F.J.; et al. Idiopathic Pulmonary Fibrosis (an Update) and Progressive Pulmonary Fibrosis in Adults: An Official ATS/ERS/JRS/ALAT Clinical Practice Guideline. Am. J. Respir. Crit. Care Med. 2022, 205, E18–E47. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raghu, G.; Flaherty, K.R.; Lederer, D.J.; Lynch, D.A.; Colby, T.V.; Myers, J.L.; Groshong, S.D.; Larsen, B.T.; Chung, J.H.; Steele, M.P.; et al. Use of a molecular classifier to identify usual interstitial pneumonia in conventional transbronchial lung biopsy samples: A prospective validation study. Lancet Respir. Med. 2019, 7, 487–496. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kheir, F.; Alkhatib, A.; Berry, G.J.; Daroca, P.; Diethelm, L.; Rampolla, R.; Saito, S.; Smith, D.L.; Weill, D.; Bateman, M.; et al. Using Bronchoscopic Lung Cryobiopsy and a Genomic Classifier in the Multidisciplinary Diagnosis of Diffuse Interstitial Lung Diseases. Chest 2020, 158, 2015–2025. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Churg, A. Hypersensitivity pneumonitis: New concepts and classifications. Mod. Pathol. 2022, 35, 15–27. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, Y.; Tong, Z.; Zhu, X.; Wu, C.; Zhou, Y.; Dong, Z. Deciphering the cellular and molecular landscape of pulmonary fibrosis through single-cell sequencing and machine learning. J. Transl. Med. 2025, 23, 3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ren, F.; Aliper, A.; Chen, J.; Zhao, H.; Rao, S.; Kuppe, C.; Ozerov, I.V.; Zhang, M.; Witte, K.; Kruse, C.; et al. A small-molecule TNIK inhibitor targets fibrosis in preclinical and clinical models. Nat. Biotechnol. 2025, 43, 63–75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Choi, Y.; Lu, J.; Hu, Z.; Pankratz, D.G.; Jiang, H.; Cao, M.; Marchisano, C.; Huiras, J.; Fedorowicz, G.; Wong, M.G.; et al. Analytical performance of Envisia: A genomic classifier for usual interstitial pneumonia. BMC Pulm. Med. 2017, 17, 141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Borie, R.; Kannengiesser, C.; Antoniou, K.; Bonella, F.; Crestani, B.; Fabre, A.; Froidure, A.; Galvin, L.; Griese, M.; Grutters, J.C.; et al. European Respiratory Society statement on familial pulmonary fibrosis. Eur. Respir. J. 2023, 61, 2201383. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Groen, K.; van der Vis, J.J.; van Batenburg, A.A.; Kazemier, K.M.; de Bruijn, M.J.W.; Stadhouders, R.; Arp, P.; Verkerk, A.J.M.H.; Schoemaker, A.E.; de Bie, C.I.; et al. A new variant in the ZCCHC8 gene: Diverse clinical phenotypes and expression in the lung. ERJ Open Res. 2024, 10, 00487–2023. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alrehaili, G.; Kemppainen, J.; Kalra, S.; Pinto, E.; Vairo, F.; Moua, T.; Yi, E.S.; Ferrer, A.; Patnaik, M.M.; Carmona, E.M. Genetic Testing Goes Beyond Imaging and Histological Evaluation in Pleuroparenchymal Fibroelastosis. Lung 2024, 202, 151–156. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khincha, P.P.; Dagnall, C.L.; Hicks, B.; Jones, K.; Aviv, A.; Kimura, M.; Katki, H.; Aubert, G.; Giri, N.; Alter, B.P.; et al. Correlation of Leukocyte Telomere Length Measurement Methods in Patients with Dyskeratosis Congenita and in Their Unaffected Relatives. Int. J. Mol. Sci. 2017, 18, 1765. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Voss, L.A.; Nevel, R.J.; Wambach, J.A.; Nogee, L.M.; Deterding, R.R.; Casey, A.M.; O’Connor, M.G.; Craven, D.I.; Taylor, J.B.; Deutsch, G.H.; et al. Genetic Testing Utilization in the U.S. Registry for Childhood Interstitial and Diffuse Lung Diseases. Pediatr. Pulmonol. 2025, 60, e71073. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chambers, D.C.; Carew, A.M.; Lukowski, S.W.; Powell, J.E. Transcriptomics and single-cell RNA-sequencing. Respirology 2018, 24, 29–36. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mariniello, D.F.; Aronne, L.; Vitale, M.; Schiattarella, A.; Pagliaro, R.; Komici, K. Current challenges and perspectives in lung cancer care during COVID-19 waves. Curr. Opin. Pulm. Med. 2023, 29, 239–247. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marra, A.; D’Agnano, V.; Pagliaro, R.; Perrotta, F.; Di Fiore, I.; D’Orologio, A.; Scialò, F.; Schiattarella, A.; Bianco, A.; Parrella, R. SpO2/FiO2 Correlates with PaO2/FiO2 (P/F) and Radiological Biomarkers of Severity: A Retrospective Study on COVID-19 Pneumonia Patients. Biomedicines 2025, 13, 1072. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mariniello, D.F.; D’Agnano, V.; Cennamo, D.; Conte, S.; Quarcio, G.; Notizia, L.; Pagliaro, R.; Schiattarella, A.; Salvi, R.; Bianco, A.; et al. Comorbidities in COPD: Current and Future Treatment Challenges. J. Clin. Med. 2024, 13, 743. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, Z.; Peng, F.; Zhou, Y. Biomarkers in idiopathic pulmonary fibrosis: Current insight and future direction. Chin. Med. J.—Pulm. Crit. Care Med. 2024, 2, 72–79. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wen, Z.; Liang, W.; Yang, Z.; Liu, J.; Yang, J.; Xu, R.; Lin, K.; Pan, J.; Chen, Z. Genetic insights into idiopathic pulmonary fibrosis: A multi-omics approach to identify potential therapeutic targets. J. Transl. Med. 2025, 23, 337. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nemeth, J.; Schundner, A.; Frick, M. Insights Into Development and Progression of Idiopathic Pulmonary Fibrosis From Single Cell RNA Studies. Front. Med. 2020, 7, 611728. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beisang, D.J.; Smith, K.; Yang, L.; Benyumov, A.; Gilbertsen, A.; Herrera, J.; Lock, E.; Racila, E.; Forster, C.; Sandri, B.J.; et al. Single-cell RNA sequencing reveals that lung mesenchymal progenitor cells in IPF exhibit pathological features early in their differentiation trajectory. Sci. Rep. 2020, 10, 11162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luzina, I.G.; Salcedo, M.V.; Rojas-Peña, M.L.; Wyman, A.E.; Galvin, J.R.; Sachdeva, A.; Clerman, A.; Kim, J.; Franks, T.J.; Britt, E.J.; et al. Transcriptomic evidence of immune activation in macroscopically normal-appearing and scarred lung tissues in idiopathic pulmonary fibrosis. Cell. Immunol. 2018, 325, 1–13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yu, X.; Gu, P.; Huang, Z.; Fang, X.; Jiang, Y.; Luo, Q.; Li, X.; Zhu, X.; Zhan, M.; Wang, J. Reduced expression of BMP3 contributes to the development of pulmonary fibrosis and predicts the unfavorable prognosis in IIP patients. Oncotarget 2017, 9, 80531–80544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sivakumar, P.; Thompson, J.R.; Ammar, R.; Porteous, M.; McCoubrey, C.; Cantu, E., 3rd; Ravi, K.; Zhang, Y.; Luo, Y.; Streltsov, D.; et al. RNA sequencing of transplant-stage idiopathic pulmonary fibrosis lung reveals unique pathway regulation. ERJ Open Res. 2019, 5, 00117–2019. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Petraglia, L.; Komici, K.; Bencivenga, L.; Rengo, G.; Pagliaro, R.; Sciattarella, A.; Ferrara, N.; Bianco, A.; Guerra, G. The association between muscle strength and z scores of pulmonary function. Sci. Rep. 2025, 15, 27662. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McDonough, J.E.; Ahangari, F.; Li, Q.; Jain, S.; Verleden, S.E.; Herazo-Maya, J.; Vukmirovic, M.; DeIuliis, G.; Tzouvelekis, A.; Tanabe, N.; et al. Transcriptional regulatory model of fibrosis progression in the human lung. JCI Insight 2019, 4, e131597. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scialò, F.; Pagliaro, R.; Gelzo, M.; Matera, M.G.; D’Agnano, V.; Zamparelli, S.S.; Castaldo, G.; Cazzola, M.; Bianco, A.; Perrotta, F. Fatty Acids Dysregulation Correlates with Lung Function in Idiopathic Pulmonary Fibrosis. Lung 2025, 203, 99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nigro, E.; D’Agnano, V.; Pagliaro, R.; Mallardo, M.; Bianco, A.; Picone, C.; D’Errico, A.G.; Daniele, A.; Perrotta, F. Exploring the role of serum adiponectin and its holigomerization in fibrotic interstitial lung diseases: Results from a cross-sectional study. BMC Pulm. Med. 2025, 25, 263. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karman, J.; Wang, J.; Bodea, C.; Cao, S.; Levesque, M.C. Lung gene expression and single cell analyses reveal two subsets of idiopathic pulmonary fibrosis (IPF) patients associated with different pathogenic mechanisms. PLoS ONE 2021, 16, e0248889. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, S.; Guo, J.; Kong, Z.; Deng, M.; Da, J.; Lin, X.; Peng, S.; Fu, J.; Luo, T.; Ma, J.; et al. Causal effects of gut microbiota on sepsis and sepsis-related death: Insights from genome-wide Mendelian randomization, single-cell RNA, bulk RNA sequencing, and network pharmacology. J. Transl. Med. 2024, 22, 10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Giriyappagoudar, M.; Vastrad, B.; Horakeri, R.; Vastrad, C. Study on Potential Differentially Expressed Genes in Idiopathic Pulmonary Fibrosis by Bioinformatics and Next-Generation Sequencing Data Analysis. Biomedicines 2023, 11, 3109. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Calabrese, F.; Lunardi, F.; Tauro, V.; Pezzuto, F.; Fortarezza, F.; Vedovelli, L.; Faccioli, E.; Balestro, E.; Schiavon, M.; Esposito, G.; et al. RNA Sequencing of Epithelial Cell/Fibroblastic Foci Sandwich in Idiopathic Pulmonary Fibrosis: New Insights on the Signaling Pathway. Int. J. Mol. Sci. 2022, 23, 3323. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sheu, C.C.; Chang, W.A.; Tsai, M.J.; Liao, S.H.; Chong, I.W.; Kuo, P.L. Bioinformatic analysis of next-generation sequencing data to identify dysregulated genes in fibroblasts of idiopathic pulmonary fibrosis. Int. J. Mol. Med. 2019, 43, 1643–1656. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Di Palma, T.; Filippone, M.G.; Pierantoni, G.M.; Fusco, A.; Soddu, S.; Zannini, M. Pax8 has a critical role in epithelial cell survival and proliferation. Cell Death Dis. 2013, 4, e729. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fagerberg, L.; Hallström, B.M.; Oksvold, P.; Kampf, C.; Djureinovic, D.; Odeberg, J.; Habuka, M.; Tahmasebpoor, S.; Danielsson, A.; Edlund, K.; et al. Analysis of the human tissue-specific expression by genome-wide integration of transcriptomics and antibody-based proteomics. Mol. Cell. Proteom. 2014, 13, 397–406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fang, C.; Huang, H.; Feng, Y.; Zhang, Q.; Wang, N.; Jing, X.; Guo, J.; Ferianc, M.; Xu, Z. Whole-exome sequencing identifies susceptibility genes and pathways for idiopathic pulmonary fibrosis in the Chinese population. Sci. Rep. 2021, 11, 1443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Noth, I.; Zhang, Y.; Ma, S.F.; Flores, C.; Barber, M.; Huang, Y.; Broderick, S.M.; Wade, M.S.; Hysi, P.; Scuirba, J.; et al. Genetic variants associated with idiopathic pulmonary fibrosis susceptibility and mortality: A genome-wide association study. Lancet Respir. Med. 2013, 1, 309–317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Otsubo, K.; Iwama, E.; Ijichi, K.; Kubo, N.; Yoneshima, Y.; Inoue, H.; Tanaka, K.; Osoegawa, A.; Tagawa, T.; Nakanishi, Y.; et al. Paired genetic analysis by next-generation sequencing of lung cancer and associated idiopathic pulmonary fibrosis. Cancer Sci. 2020, 111, 2482–2487. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, Y.; Mizuno, T.; Sridharan, A.; Du, Y.; Guo, M.; Tang, J.; Wikenheiser-Brokamp, K.A.; Perl, A.T.; Funari, V.A.; Gokey, J.J.; et al. Single-cell RNA sequencing identifies diverse roles of epithelial cells in idiopathic pulmonary fibrosis. JCI Insight 2016, 1, e90558. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carraro, G.; Mulay, A.; Yao, C.; Mizuno, T.; Konda, B.; Petrov, M.; Lafkas, D.; Arron, J.R.; Hogaboam, C.M.; Chen, P.; et al. Single-Cell Reconstruction of Human Basal Cell Diversity in Normal and Idiopathic Pulmonary Fibrosis Lungs. Am. J. Respir. Crit. Care Med. 2020, 202, 1540–1550. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reyfman, P.A.; Walter, J.M.; Joshi, N.; Anekalla, K.R.; McQuattie-Pimentel, A.C.; Chiu, S.; Fernandez, R.; Akbarpour, M.; Chen, C.I.; Ren, Z.; et al. Single-Cell Transcriptomic Analysis of Human Lung Provides Insights into the Pathobiology of Pulmonary Fibrosis. Am. J. Respir. Crit. Care Med. 2019, 199, 1517–1536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pardo, A.; Gibson, K.; Cisneros, J.; Richards, T.J.; Yang, Y.; Becerril, C.; Yousem, S.; Herrera, I.; Ruiz, V.; Selman, M.; et al. Up-regulation and profibrotic role of osteopontin in human idiopathic pulmonary fibrosis. PLoS Med. 2005, 2, 0891–0903. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morse, C.; Tabib, T.; Sembrat, J.; Buschur, K.L.; Bittar, H.T.; Valenzi, E.; Jiang, Y.; Kass, D.J.; Gibson, K.; Chen, W.; et al. Proliferating SPP1/MERTK-expressing macrophages in idiopathic pulmonary fibrosis. Eur. Respir. J. 2019, 54, 1802441. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, J.; Jiang, M.; Xiong, A.; Zhang, L.; Luo, L.; Liu, Y.; Liu, S.; Ran, Q.; Wu, D.; Xiong, Y.; et al. Integrated analysis of single-cell and bulk RNA sequencing reveals pro-fibrotic PLA2G7high macrophages in pulmonary fibrosis. Pharmacol. Res. 2022, 182, 106286. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aran, D.; Looney, A.P.; Liu, L.; Wu, E.; Fong, V.; Hsu, A.; Chak, S.; Naikawadi, R.P.; Wolters, P.J.; Abate, A.R.; et al. Reference-based analysis of lung single-cell sequencing reveals a transitional profibrotic macrophage. Nat. Immunol. 2019, 20, 163–172. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Engelbrecht, E.; Kooistra, T.; Burg, N.; Hariri, L.; Nguyen, T.; Brazee, P.; Hla, T.; Gochuico, B.R.; Knipe, R.S. Ectopic Expansion of Pulmonary Vasculature in Fibrotic Lung Disease and Lung Adenocarcinoma Marked by Proangiogenic COL15A1+ Endothelial Cells. Pulm. Circ. 2025, 15, e70102. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Daccord, C.; Maher, T.M. Recent advances in understanding idiopathic pulmonary fibrosis. F1000Research 2016, 5, 1046. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brudon, A.; Legendre, M.; Mageau, A.; Bermudez, J.; Bonniaud, P.; Bouvry, D.; Cadranel, J.; Cazes, A.; Crestani, B.; Dégot, T.; et al. High risk of lung cancer in surfactant-related gene variant carriers. Eur. Respir. J. 2024, 63, 2301809. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fadista, J.; Kraven, L.M.; Karjalainen, J.; Andrews, S.J.; Geller, F.; COVID-19 Host Genetics Initiative; Baillie, J.K.; Wain, L.V.; Jenkins, R.G.; Feenstra, B. Shared genetic etiology between idiopathic pulmonary fibrosis and COVID-19 severity. eBioMedicine 2021, 65, 103277. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van der Vis, J.J.; Snetselaar, R.; Kazemier, K.M.; Ten Klooster, L.; Grutters, J.C.; van Moorsel, C.H. Effect of Muc5b promoter polymorphism on disease predisposition and survival in idiopathic interstitial pneumonias. Respirology 2016, 21, 712–717. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Moorsel, C.H.M.; van der Vis, J.J.; Duckworth, A.; Scotton, C.J.; Benschop, C.; Ellinghaus, D.; Ruven, H.J.T.; Quanjel, M.J.R.; Grutters, J.C. The MUC5B Promoter Polymorphism Associates With Severe COVID-19 in the European Population. Front. Med. 2021, 8, 668024. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McGroder, C.F.; Hansen, S.; Hinckley Stukovsky, K.; Zhang, D.; Nath, P.H.; Salvatore, M.M.; Sonavane, S.K.; Terry, N.; Stowell, J.T.; D’Souza, B.M.; et al. Incidence of interstitial lung abnormalities: The MESA Lung Study. Eur. Respir. J. 2023, 61, 2201950. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moll, M.; Peljto, A.L.; Kim, J.S.; Xu, H.; Debban, C.L.; Chen, X.; Menon, A.; Putman, R.K.; Ghosh, A.J.; Saferali, A.; et al. A Polygenic Risk Score for Idiopathic Pulmonary Fibrosis and Interstitial Lung Abnormalities. Am. J. Respir. Crit. Care Med. 2023, 208, 791–801, Correction in Am. J. Respir. Crit. Care Med. 2024, 209, 1045. https://doi.org/10.1164/rccm.202212-2257OC. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Allen, R.J.; Oldham, J.M.; Jenkins, D.A.; Leavy, O.C.; Guillen-Guio, B.; Melbourne, C.A.; Ma, S.F.; Jou, J.; Kim, J.S. CleanUP-IPF Investigators of the Pulmonary Trials Cooperative; et al. Longitudinal lung function and gas transfer in individuals with idiopathic pulmonary fibrosis: A genome-wide association study. Lancet Respir. Med. 2023, 11, 65–73. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oldham, J.M.; Allen, R.J.; Lorenzo-Salazar, J.M.; Molyneaux, P.L.; Ma, S.F.; Joseph, C.; Kim, J.S.; Guillen-Guio, B.; Hernández-Beeftink, T.; Kropski, J.A.; et al. PCSK6 and Survival in Idiopathic Pulmonary Fibrosis. Am. J. Respir. Crit. Care Med. 2023, 207, 1515–1524. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ruan, P.; Todd, J.L.; Zhao, H.; Liu, Y.; Vinisko, R.; Soellner, J.F.; Schmid, R.; Kaner, R.J.; Luckhardt, T.R.; Neely, M.L. Integrative multi-omics analysis reveals novel idiopathic pulmonary fibrosis endotypes associated with disease progression. Respir. Res. 2023, 24, 141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Herazo-Maya, J.D.; Sun, J.; Molyneaux, P.L.; Li, Q.; Villalba, J.A.; Tzouvelekis, A.; Lynn, H.; Juan-Guardela, B.M.; Risquez, C. Validation of a 52-gene risk profile for outcome prediction in patients with idiopathic pulmonary fibrosis: An international, multicentre, cohort study. Lancet Respir. Med. 2017, 5, 857–868. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhan, S.; Li, S.; Cao, Y.; Liu, D.; Feng, J. Value of bronchoalveolar lavage fluid metagenomic next-generation sequencing in acute exacerbation of fibrosing interstitial lung disease: An individualized treatment protocol based on microbiological evidence. BMC Pulm. Med. 2024, 24, 400. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pagliaro, R.; Aronne, L.; Fomez, R.; Ferri, V.; Montella, A.; Sanduzzi Zamparelli, S.; Bianco, A.; Perrotta, F. High-Flow Nasal Cannula System in Respiratory Failure Associated with Interstitial Lung Diseases: A Systematic Review and Narrative Synthesis. J. Clin. Med. 2024, 13, 2956. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Podolanczuk, A.J.; Kim, J.S.; Cooper, C.B.; Lasky, J.A.; Murray, S.; Oldham, J.M.; Raghu, G.; Flaherty, K.R.; Spino, C.; Noth, I. Design and rationale for the prospective treatment efficacy in IPF using genotype for NAC selection (PRECISIONS) clinical trial. BMC Pulm. Med. 2022, 22, 475. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Doubkova, M.; Kriegova, E.; Littnerova, S.; Schneiderova, P.; Sterclova, M.; Bartos, V.; Plackova, M.; Zurkova, M.; Bittenglova, R.; Lostaková, V.; et al. DSP rs2076295 variants influence nintedanib and pirfenidone outcomes in idiopathic pulmonary fibrosis: A pilot study. Ther. Adv. Respir. Dis. 2021, 15, 17534666211042529. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kubbara, A.; Amundson, W.H.; Herman, A.; Lee, A.M.; Bishop, J.R.; Kim, H.J. Genetic variations in idiopathic pulmonary fibrosis and patient response to pirfenidone. Heliyon 2023, 9, e18573. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sheu, C.C.; Chang, W.A.; Tsai, M.J.; Liao, S.H.; Chong, I.W.; Kuo, P.L. Gene Expression Changes Associated with Nintedanib Treatment in Idiopathic Pulmonary Fibrosis Fibroblasts: A Next-Generation Sequencing and Bioinformatics Study. J. Clin. Med. 2019, 8, 308. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Landi, C.; Carleo, A.; Vantaggiato, L.; Bergantini, L.; D’Alessandro, M.; Cameli, P.; Sebastian, G.; Dotta, F.; Bargagli, E. Common molecular pathways targeted by nintedanib in cancer and IPF: A bioinformatic study. Pulm. Pharmacol. Ther. 2020, 64, 101941. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mikami, S.; Miura, Y.; Kondo, S.; Sakai, K.; Nishimura, H.; Kyoyama, H.; Moriyama, G.; Koyama, N.; Noguchi, H.; Ohkubo, H.; et al. Nintedanib induces gene expression changes in the lung of induced-rheumatoid arthritis-associated interstitial lung disease mice. PLoS ONE 2022, 17, e0270056. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Justet, A.; Klay, D.; Porcher, R.; Cottin, V.; Ahmad, K.; Molina Molina, M.; Nunes, H.; Reynaud-Gaubert, M.; Naccache, J.M.; Manali, E.; et al. Safety and efficacy of pirfenidone and nintedanib in patients with idiopathic pulmonary fibrosis and carrying a telomere-related gene mutation. Eur. Respir. J. 2020, 57, 2003198. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dressen, A.; Abbas, A.R.; Cabanski, C.; Reeder, J.; Ramalingam, T.R.; Neighbors, M.; Bhangale, T.R.; Brauer, M.J.; Hunkapiller, J.; Reeder, J.; et al. Analysis of protein-altering variants in telomerase genes and their association with MUC5B common variant status in patients with idiopathic pulmonary fibrosis: A candidate gene sequencing study. Lancet Respir. Med. 2018, 6, 603–614. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bauer, Y.; Tedrow, J.; de Bernard, S.; Birker-Robaczewska, M.; Gibson, K.F.; Guardela, B.J.; Hess, P.; Klenk, A.; Lindell, K.O.; Poirey, S.; et al. A novel genomic signature with translational significance for human idiopathic pulmonary fibrosis. Am. J. Respir. Cell Mol. Biol. 2015, 52, 217–231. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kwapiszewska, G.; Gungl, A.; Wilhelm, J.; Marsh, L.M.; Thekkekara Puthenparampil, H.; Sinn, K.; Didiasova, M.; Klepetko, W.; Kosanovic, D.; Schermuly, R.T.; et al. Transcriptome profiling reveals the complexity of pirfenidone effects in idiopathic pulmonary fibrosis. Eur. Respir. J. 2018, 52, 1800564. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, X.; Forstner, M.; Rapp, C.K.; Rothenaigner, I.; Li, Y.; Hadian, K.; Griese, M. ABCA3 Deficiency-Variant-Specific Response to Hydroxychloroquine. Int. J. Mol. Sci. 2023, 24, 8179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Birnhuber, A.; Jandl, K.; Biasin, V.; Fließer, E.; Valzano, F.; Marsh, L.M.; Krolczik, C.; Olschewski, A.; Wilhelm, J.; Toller, W.; et al. Pirfenidone exacerbates Th2-driven vasculopathy in a mouse model of systemic sclerosis-associated interstitial lung disease. Eur. Respir. J. 2022, 60, 2102347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McCormack, F.X.; Inoue, Y.; Moss, J.; Singer, L.G.; Strange, C.; Nakata, K.; Barker, A.F.; Chapman, J.T.; Brantly, M.L.; Stocks, J.M. Efficacy and safety of sirolimus in lymphangioleiomyomatosis. N. Engl. J. Med. 2011, 364, 1595–1606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, I.V.; Fingerlin, T.E.; Evans, C.M.; Schwarz, M.I.; Schwartz, D.A. MUC5B and Idiopathic Pulmonary Fibrosis. Ann. Am. Thorac. Soc. 2015, 12, S193–S199. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oldham, J.M.; Ma, S.F.; Martinez, F.J.; Anstrom, K.J.; Raghu, G.; Schwartz, D.A.; Valenzi, E.; Witt, L.; Lee, C.; Vij, R. TOLLIP, MUC5B, and the Response to N-Acetylcysteine among Individuals with Idiopathic Pulmonary Fibrosis. Am. J. Respir. Crit. Care Med. 2015, 192, 1475–1482. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bonella, F.; Spagnolo, P.; Ryerson, C. Current and Future Treatment Landscape for Idiopathic Pulmonary Fibrosis. Drugs 2023, 83, 1581–1593. [Google Scholar] [CrossRef] [Scilit] [PubMed]


| Technology | Detection | Advantages | Limitations | Relative Cost | Diagnostic Yield in PF (Estimated) |
|---|---|---|---|---|---|
| Targeted Gene Panels | Predefined set of genes (e.g., TERT, SFTPC, MUC5B) | Cost-effective; rapid turnaround; high depth of coverage; easier interpretation | Limited to known genes; may miss novel variants | Low ($) | Sporadic: ~5–10%; Familial: ~20–30% |
| Whole-Exome Sequencing (WES) | Protein-coding regions | Broader coverage than panels; can identify novel genes | Higher cost; incidental findings; interpretation challenges | Moderate ($$) | ~10–20% (higher in FPF) |
| Whole-Genome Sequencing (WGS) | Entire genome (coding and non-coding) | Most comprehensive; detects non-coding and structural variants | Highest cost; data storage/analysis complexity | High ($$$) | Similar to WES plus structural variants |
| RNA Sequencing (RNA-seq) | Gene expression levels; splicing; non-coding RNAs | Functional insights; can validate genomic findings; reveals cellular heterogeneity | Requires high-quality RNA; complex analysis; not standardised | Moderate ($$) | Not applicable (research classifier) |
| Single-cell RNA-seq (scRNA-seq) | Gene expression at individual cell resolution | Highest resolution of tissue biology | Very high cost; complex analysis; difficult to standardise | Very high ($$$$) | Not applicable (discovery) |
| Gene/Locus | Protein/Function | Variant Type | Frequency in FPF | Frequency in Sporadic ILD | Associated Phenotype/Syndrome | Clinical Actionability/Notes |
|---|---|---|---|---|---|---|
| Telomere-Related Genes | ||||||
| TERT | Telomerase reverse transcriptase | Rare LoF/dominant negative | ~15–20% | ~1–3% | IPF, short-telomere syndromes (dyskeratosis congenita), hepatic cirrhosis | Inform transplant planning (risk of myelosuppression); genetic counselling |
| TERC | Telomerase RNA component | Rare LoF | ~5–10% | <1% | IPF, short-telomere syndromes | As above; bone marrow failure screening |
| RTEL1 | DNA helicase | Rare LoF | ~2–5% | <1% | IPF, Hoyeraal-Hreidarsson syndrome | Associated with early onset/severe disease |
| PARN | Poly(A)-specific ribonuclease | Rare LoF | ~2–4% | <1% | IPF, short-telomere syndromes | As above |
| TINF2/DKC1 | Shelterin complex/Dyskerin | Rare LoF | <2% | <1% | Dyskeratosis congenita, severe short-telomere syndromes | Usually paediatric onset; rare in adult PF |
| Surfactant-Related Genes | ||||||
| SFTPC | Surfactant protein C | Rare missense/dominant | ~1–2% | <1% | Familial IPF, childhood ILD, adult fibrosis | Associated with atypical imaging (e.g., NSIP, CPFE) |
| SFTPA1/SFTPA2 | Surfactant protein A1/A2 | Rare missense | <1% | <1% | IPF, lung adenocarcinoma | Variants may disrupt innate immunity |
| ABCA3 | ATP-binding cassette transporter | Rare biallelic LoF | <1% | <1% | Childhood ILD, adult PF | Typically severe early onset; rare in adult sporadic PF |
| High-Penetrance Rare Entities | ||||||
| EIF2AK4 | Eukaryotic translation initiation factor | Biallelic LoF | N/A | N/A | Pulmonary veno-occlusive disease (PVOD) | Diagnostic; confirms PVOD; alters transplant urgency |
| Common Susceptibility Loci | ||||||
| MUC5B (rs35705950) | Mucin 5B (promoter variant) | Common SNP (T allele) | ~30–40% (carrier) | ~15–25% (carrier) | IPF, familial PF, chronic HP | Major risk factor; NOT diagnostic (present in healthy controls); useful for risk stratification in research |
| Other GWAS loci (e.g., DSP, FAM13A, TOLLIP, OBFC1) | Various (cell adhesion, telomere maintenance) | Common SNPs | Variable | Variable | Modest risk for IPF/ILD | Currently limited standalone clinical utility; polygenic risk scores unvalidated |
| Technology | Detection | Key Applications in PF/IPF | Advantages | Limitations | Clinical Status |
|---|---|---|---|---|---|
| Targeted Gene Panels | Predefined set of genes (e.g., TERT, SFTPC, MUC5B) | Diagnostic confirmation in suspected FPF; identifying molecular subtypes; prognostic stratification | Cost-effective; rapid turnaround; high depth of coverage; easier interpretation | Limited to known genes; may miss novel or unexpected variants | Clinical use in expert centres for selected cases |
| Whole-Exome Sequencing (WES) | Protein-coding regions of all genes | Discovery of rare variants in known and novel genes; research in FPF; complex cases with negative panel | Broader coverage than panels; can identify novel genes | Higher cost; incidental findings; interpretation challenges | Translational; limited to research or complex cases |
| Whole-Genome Sequencing (WGS) | Entire genome (coding and non-coding) | Comprehensive variant detection; research on structural variants and non-coding regions | Most comprehensive; detects non-coding, structural variants | Highest cost; data storage/analysis; interpretation complexity | Research; not yet for routine clinical use |
| RNA Sequencing (RNA-seq) | Gene expression levels; splicing; non-coding RNAs | Pathway analysis; biomarker discovery; molecular phenotyping | Functional insights; can validate genomic findings; reveals cellular heterogeneity | Requires high-quality RNA; complex analysis; not standardised | Research; developing potential as diagnostic classifier |
| Single-cell RNA-seq (scRNA-seq) | Gene expression at individual cell resolution | Mapping cellular heterogeneity; identifying rare cell populations; understanding fibrotic niche | Highest resolution of tissue biology | Very high cost; complex analysis; difficult to standardise | Research; fundamental for discovery |
| Study | Study Type | Sample Size | Sequencing Platform/Technology | Key Genetic/Transcriptomic Findings | Clinical Relevance | Limitations |
|---|---|---|---|---|---|---|
| [8] | Case–control GWAS | 1610 IPF cases, 2477 controls | SNP microarray | MUC5B promoter variant (rs35705950) confers strong IPF risk (OR ~6–9) | First major common variant; changed understanding of IPF genetics | Non-NGS; European ancestry only |
| [30] | GWAS | 1616 IPF cases, 4683 controls | Illumina arrays | Multiple susceptibility loci (TERT, RTEL1, MUC5B, etc.) | Established polygenic architecture of IPF | Non-NGS; limited functional validation |
| [110] | Candidate gene sequencing | 1226 IPF cases, 1286 controls | Targeted NGS of telomerase genes | Rare protein-altering variants in TERT, TERC, PARN associated with IPF; MUC5B interacts | Showed rare variants contribute to sporadic IPF | Targeted panel only; limited to telomerase genes |
| [6] | Whole-exome sequencing | 1548 FPF cases, 1991 familial controls | WES | Pathogenic variants in telomere-related (27%) and surfactant-related (5%) genes; novel genes (SPATA6, TP63) | Defined genetic landscape of FPF; diagnostic yield quantified | Retrospective; selection bias toward families | |
| [17] | Targeted NGS + telomere length | 1022 PF patients (multi-ethnic) | Targeted panel (telomere/surfactant genes) | Telomere-related variants in 12%; shorter telomeres associated with mortality across races | Demonstrated racial differences in telomere length and outcomes | No WGS; telomere length not directly sequenced |
| [35] | Expert consensus + cohort review | 1067 FPF cases | Various (panel/WES) | Summary of diagnostic yield: ~25–30% in FPF, ~5–10% in sporadic | Provided clinical recommendations for genetic testing | Not a primary research study; consensus-based |
| [97] | GWAS of longitudinal lung function | 2115 IPF cases | GWAS array | PCSK6 and other variants associated with FVC decline and survival | First large-scale GWAS for disease progression | Non-NGS; need functional studies |
| [98] | Exome array + validation | 1482 IPF cases | Exome array (targeted) | PCSK6 variant associated with survival; replicated in multiple cohorts | Potential prognostic biomarker | Not full WES/WGS; mechanism unclear |
| [100] | Transcriptomic (RNA-seq) | 263 IPF patients (discovery + validation) | RNA-seq of peripheral blood | 52-gene signature predictive of transplant-free survival | First validated blood-based prognostic signature for IPF | Single-centre discovery; requires qPCR implementation |
| [99] | Multi-omics (RNA-seq + proteomics) | 114 IPF patients | RNA-seq + proteomics | Identified two molecular endotypes with different progression rates | Demonstrates feasibility of molecular subtyping | Small sample size; validation needed |
| [79] | Whole-exome sequencing | 142 Chinese IPF cases, 255 controls | WES | Novel susceptibility genes (DSP, DYNCIH1, etc.) and pathway enrichment | First WES in Chinese IPF population | Modest sample size; replication needed |
| [33] | Targeted NGS panel | 624 FPF probands | Custom 150-gene panel | Pathogenic variants in 29% of FPF; telomere genes most common | Comprehensive panel for clinical FPF testing | No functional validation; VUS rate not reported |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Pagliaro, R.; Perrotta, F.; Zamparelli, S.S.; Carrozzo, V.M.; Cipriano, A.; Mondoni, M.; Stella, G.M.; Bianco, A.; Scialò, F. Next-Generation Sequencing in Pulmonary Fibrosis: Translational Promise and Current Clinical Limitations. Curr. Issues Mol. Biol. 2026, 48, 721. https://doi.org/10.3390/cimb48070721
Pagliaro R, Perrotta F, Zamparelli SS, Carrozzo VM, Cipriano A, Mondoni M, Stella GM, Bianco A, Scialò F. Next-Generation Sequencing in Pulmonary Fibrosis: Translational Promise and Current Clinical Limitations. Current Issues in Molecular Biology. 2026; 48(7):721. https://doi.org/10.3390/cimb48070721
Chicago/Turabian StylePagliaro, Raffaella, Fabio Perrotta, Stefano Sanduzzi Zamparelli, Valerio Maria Carrozzo, Alfredo Cipriano, Michele Mondoni, Giulia Maria Stella, Andrea Bianco, and Filippo Scialò. 2026. "Next-Generation Sequencing in Pulmonary Fibrosis: Translational Promise and Current Clinical Limitations" Current Issues in Molecular Biology 48, no. 7: 721. https://doi.org/10.3390/cimb48070721
APA StylePagliaro, R., Perrotta, F., Zamparelli, S. S., Carrozzo, V. M., Cipriano, A., Mondoni, M., Stella, G. M., Bianco, A., & Scialò, F. (2026). Next-Generation Sequencing in Pulmonary Fibrosis: Translational Promise and Current Clinical Limitations. Current Issues in Molecular Biology, 48(7), 721. https://doi.org/10.3390/cimb48070721