Shifts in Research Focus on Factors Associated with Burnout Among Nurse Managers Before and During the COVID-19 Pandemic: An Integrative Review


Abstract
1. Introduction
- What is currently known about factors associated with burnout among nurse managers?
- What similarities and differences exist in the focus of research on factors related to burnout among nurse managers before and during the COVID-19 pandemic?
2. Materials and Methods
2.1. Study Design
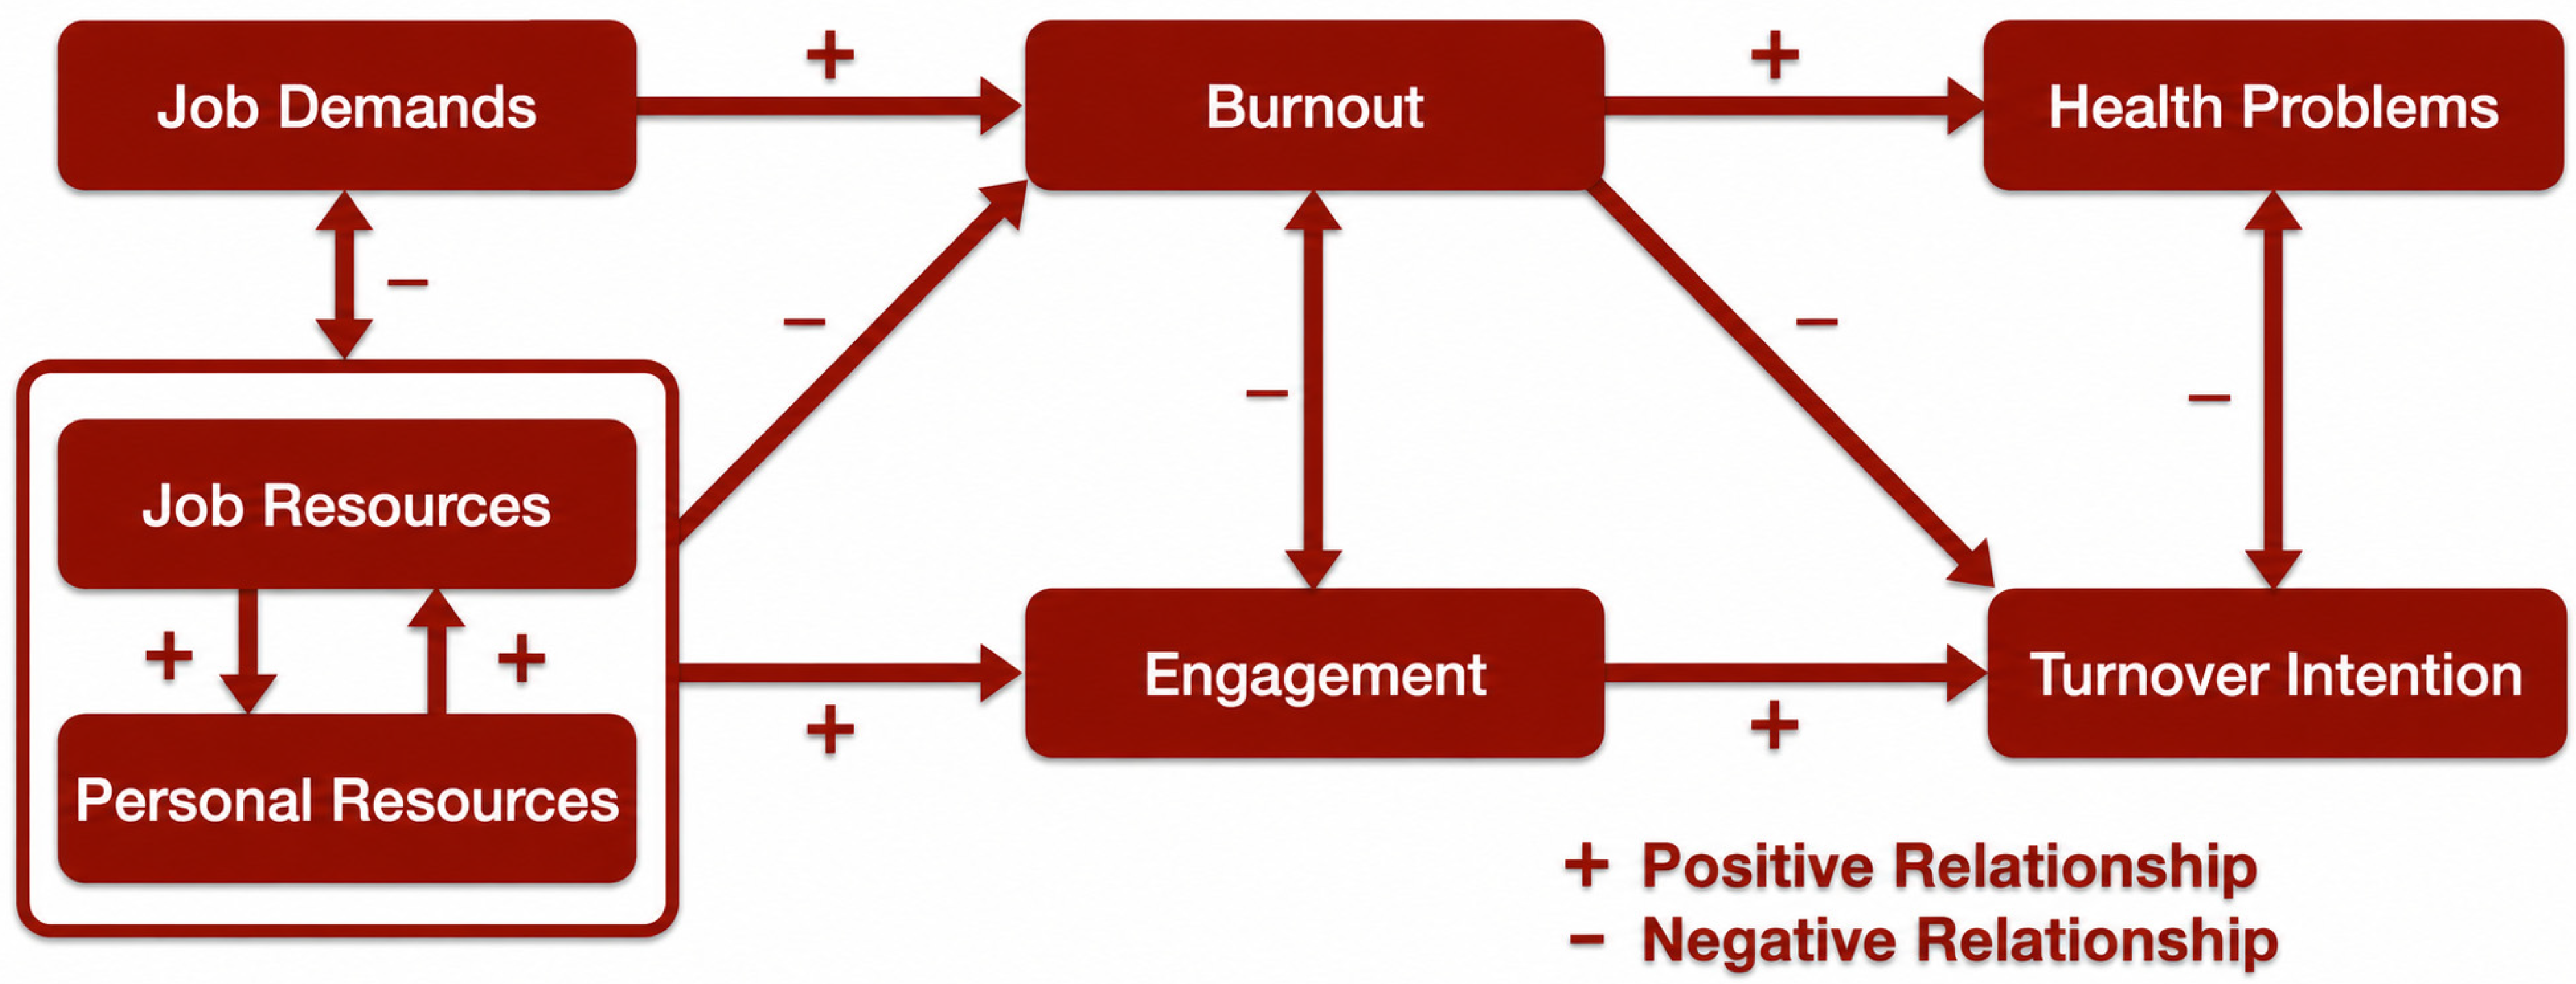
2.2. Theoretical Framework
- Job demands: physical, psychological, social, or organizational aspects of work that require sustained physical or psychological effort [34].
- Job resources: physical, psychological, social, or organizational aspects of work that reduce job demands, promote personal growth and learning, and facilitate the achievement of work goals [34].
2.3. Search Strategy
2.4. Study Selection
- Population: nurse managers.
- Exposure: the COVID-19 pandemic.
- Comparator: pre-pandemic versus pandemic-era conditions.
- Outcome: burnout-related factors, burnout scores, and burnout prevalence.
2.5. Data Extraction and Analysis
3. Results
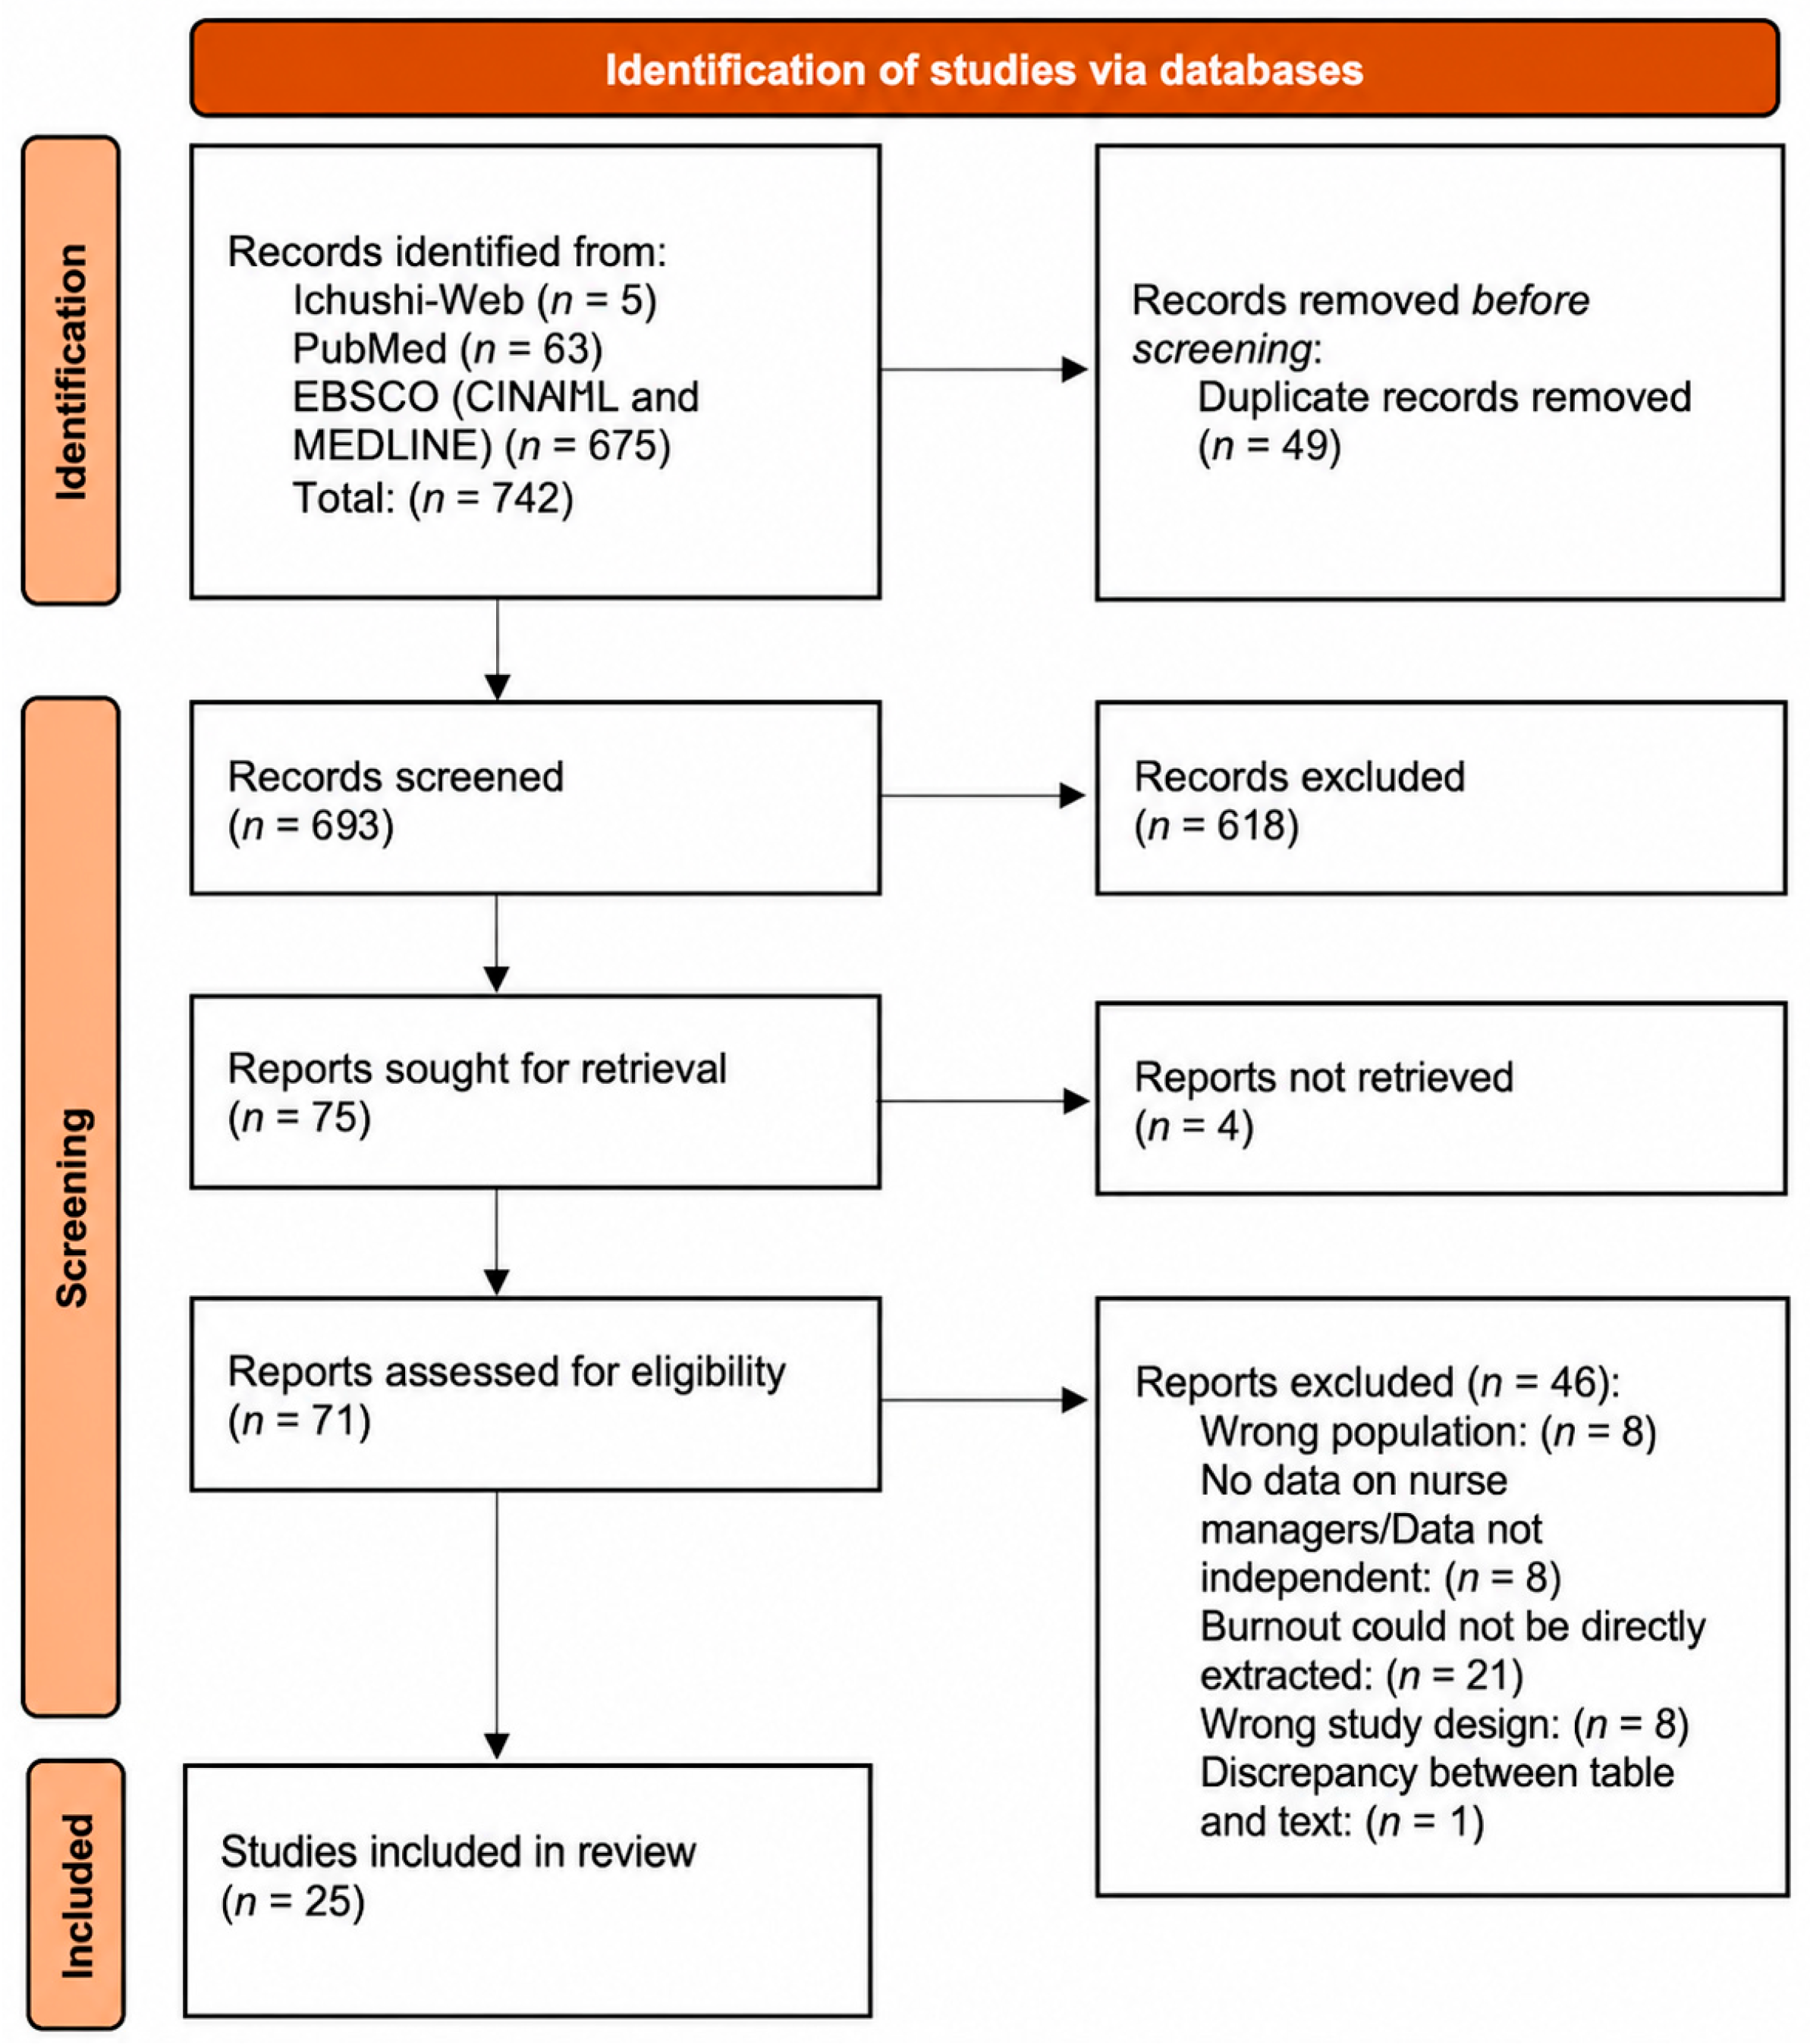
3.1. Results of the Database Search and Study Selection
3.2. Overview of Included Studies
3.3. Organization of Burnout-Associated Factors Based on the JD–R Model
4. Discussion
4.1. Overview of Research on Nurse Manager Burnout
4.2. Burnout-Associated Factors Based on the JD–R Model
4.2.1. Job Demands
4.2.2. Job Resources
4.2.3. Personal Resources
4.3. Practical Implications for Preparing for Future Crisis Situations
4.4. Limitations
5. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
Abbreviations
| BCS | Burnout Characterization Scale |
| CBI | Copenhagen Burnout Inventory |
| CINAHL | Cumulative Index to Nursing and Allied Health Literature |
| COVID-19 | Coronavirus Disease 2019 |
| EBSCO | EBSCOhost (database platform) |
| EID | Emerging Infectious Disease |
| GS | General Survey |
| HSS | Human Services Survey |
| ICD-11 | International Classification of Diseases, 11th Revision |
| ICU | Intensive Care Unit |
| IQR | Interquartile Range |
| JD–R | Job Demands–Resources (model) |
| MBI | Maslach Burnout Inventory |
| MBI-GS | Maslach Burnout Inventory—General Survey |
| MBI-HSS | Maslach Burnout Inventory—Human Services Survey |
| MeSH | Medical Subject Headings |
| MEDLINE | Medical Literature Analysis and Retrieval System Online |
| OLBI | Oldenburg Burnout Inventory |
| OR | Operating Room |
| PA | Pines–Aronson (Burnout) Scale |
| PECO | Population, Exposure, Comparator, Outcome |
| PHEIC | Public Health Emergency of International Concern |
| PRISMA | Preferred Reporting Items for Systematic Reviews and Meta-Analyses |
| ProQOL | Professional Quality of Life Scale |
| RISE | RISE program (psychoeducational group program) |
| SARS-CoV-2 | Severe Acute Respiratory Syndrome Coronavirus 2 |
| SD | Standard Deviation |
| WHO | The World Health Organization |
References
- Serafini, G.; Parmigiani, B.; Amerio, A.; Aguglia, A.; Sher, L.; Amore, M. The psychological impact of COVID-19 on the mental health of the general population. QJM 2020, 113, 531–537. [Google Scholar] [CrossRef] [Scilit]
- Jones, K.E.; Patel, N.G.; Levy, M.A.; Storeygard, A.; Balk, D.; Gittleman, J.L.; Daszak, P. Global trends in emerging infectious diseases. Nature 2008, 451, 990–993. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jamison, D.T.; Summers, L.H.; Chang, A.Y.; Karlsson, O.; Mao, W.; Norheim, O.F.; Ogbuoji, O.; Schäferhoff, M.; Watkins, D.; Adeyi, O.; et al. Global health 2050: The path to halving premature death by mid-century. Lancet 2024, 404, 1561–1614. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. 14.9 Million Excess Deaths Were Associated with the COVID-19 Pandemic in 2020 and 2021. 2022. Available online: https://www.who.int/news/item/05-05-2022-14.9-million-excess-deaths-were-associated-with-the-covid-19-pandemic-in-2020-and-2021 (accessed on 22 November 2025).
- Muller, A.E.; Hafstad, E.V.; Himmels, J.P.W.; Smedslund, G.; Flottorp, S.; Stensland, S.Ø.; Stroobants, S.; Van de Velde, S.; Vist, G.E. The mental health impact of the COVID-19 pandemic on healthcare workers, and interventions to help them: A rapid systematic review. Psychiatry Res. 2020, 293, 113441. [Google Scholar] [CrossRef] [Scilit]
- Luo, M.; Guo, L.; Yu, M.; Jiang, W.; Wang, H. The psychological and mental impact of coronavirus disease 2019 (COVID-19) on medical staff and the general public: A systematic review and meta-analysis. Psychiatry Res. 2020, 291, 113190. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Scherer, N.; Felix, L.; Kuper, H. Prevalence of depression, anxiety and post-traumatic stress disorder in health care workers during the COVID-19 pandemic: A systematic review and meta-analysis. PLoS ONE 2021, 16, e0246454. [Google Scholar] [CrossRef] [Scilit]
- Zhang, W.R.; Wang, K.; Yin, L.; Zhao, W.F.; Xue, Q.; Peng, M.; Min, B.Q.; Tian, Q.; Leng, H.X.; Du, J.L.; et al. Mental health and psychosocial problems of medical health workers during the COVID-19 epidemic in China. Psychother. Psychosom. 2020, 89, 242–250. [Google Scholar] [CrossRef] [Scilit]
- Gross, J.V.; Mohren, J.; Erren, T.C. COVID-19 and healthcare workers: A rapid systematic review into risks and preventive measures. BMJ Open 2021, 11, e042270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mehta, S.; Yarnell, C.; Shah, S.; Dodek, P.; Parsons-Leigh, J.; Maunder, R.; Kayitesi, J.; Eta-Ndu, C.; Priestap, F.; LeBlanc, D.; et al. The impact of the COVID-19 pandemic on intensive care unit workers: A nationwide survey. Can. J. Anesth. 2022, 69, 472–484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nabe-Nielsen, K.; Nilsson, C.J.; Juul-Madsen, M.; Bredal, C.; Hansen, L.O.P.; Hansen, Å.M. COVID-19 risk management at the workplace, fear of infection and fear of transmission among frontline employees. Occup. Environ. Med. 2021, 78, 248–254. [Google Scholar] [CrossRef] [Scilit]
- Boucher, V.G.; Dahl, M.; Lee, J.; Faulkner, G.; Beauchamp, M.R.; Puterman, E. An umbrella review and meta-analysis of 87 meta-analyses examining healthcare workers’ mental health during the COVID-19 pandemic. J. Affect. Disord. 2025, 375, 423–436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Szczerbińska, K.; Barańska, I.; Kijowska, V.; Stodolska, A.; Wójcik, G.; Różańska, A.; Wójkowska-Mach, J. Factors associated with burnout among hospital-based healthcare workers during the COVID-19 pandemic: A cross-sectional CRACoV-HHS study. J. Clin. Nurs. 2024, 33, 304–321. [Google Scholar] [CrossRef] [Scilit]
- Woo, T.; Ho, R.; Tang, A.; Tam, W. Global prevalence of burnout symptoms among nurses: A systematic review and meta-analysis. J. Psychiatr. Res. 2020, 123, 9–20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maniero, C.; Ng, S.M.; Collett, G.; Godec, T.; Siddiqui, I.; Antoniou, S.; Kumar, A.; Janmohamed, A.; Nair, S.; Kotecha, A.; et al. Differential impact of COVID-19 on mental health and burnout. Occup. Med. 2024, 74, 45–52. [Google Scholar] [CrossRef] [Scilit]
- Drake, D.A.; Luna, M.; Georges, J.M.; Steege, L.M.B. Hospital nurse force theory: A perspective of nurse fatigue and patient harm. Adv. Nurs. Sci. 2012, 35, 305–314. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, T.; Ma, M.; Zhu, M.; Liu, Y.; Chen, Q.; Zhang, S.; Deng, J. Challenge or hindrance: Does job stress affect presenteeism among Chinese healthcare workers? J. Occup. Health 2018, 60, 163–171. [Google Scholar] [CrossRef] [Scilit]
- Boytim, J.; Ulrich, B. Factors contributing to perioperative medication errors: A systematic literature review. AORN J. 2018, 107, 91–107. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. Burn-Out an “Occupational Phenomenon”: ICD-11. 2019 (Updated January 2025). Available online: https://www.who.int/standards/classifications/frequently-asked-questions/burn-out-an-occupational-phenomenon (accessed on 2 December 2025).
- Hawsawi, S. Alleviating psychological symptoms in nurses during disease outbreaks: An integrative review. Int. Nurs. Rev. 2022, 69, 470–483. [Google Scholar] [CrossRef] [Scilit]
- Niinihuhta, M.; Häggman-Laitila, A. Relationships between nurse leaders’ leadership styles and nurses’ work-related well-being: A systematic review. Int. J. Nurs. Pract. 2022, 28, e13040. [Google Scholar] [CrossRef] [Scilit]
- Wei, H.; King, A.T.; Jiang, Y.; Sewell, K.A.; Lake, D.M. The impact of nurse leadership styles on nurse burnout. Nurse Lead. 2020, 18, 439–450. [Google Scholar] [CrossRef] [Scilit]
- Japan Academy of Nursing Science. Nursing Administration. Available online: https://www.jans.or.jp/glossary/nursing-administration/ (accessed on 15 June 2025). (In Japanese)
- Membrive-Jiménez, M.J.; Pradas-Hernández, L.; Suleiman-Martos, N.; Vargas-Román, K.; Cañadas-De la Fuente, G.A.; Gomez-Urquiza, J.L.; De la Fuente-Solana, E.I. Burnout in Nursing Managers: A Systematic Review and Meta-Analysis of Related Factors, Levels and Prevalence. Int. J. Environ. Res. Public Health 2020, 17, 3983. [Google Scholar] [CrossRef] [Scilit]
- Van den Broeck, A.; Elst, T.V.; Baillien, E.; Sercu, M.; Schouteden, M.; De Witte, H.; Godderis, L. Job demands, job resources, burnout, work engagement, and their relationships: An analysis across sectors. J. Occup. Environ. Med. 2017, 59, 369–376. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bakker, A.B.; Demerouti, E. Job demands–resources theory. In Wellbeing; Cooper, C.L., Ed.; Wiley Blackwell: Chichester, UK, 2014. [Google Scholar] [CrossRef] [Scilit]
- Bakker, A.B.; Demerouti, E. Multiple levels in job demands–resources theory: Implications for employee well-being and performance. In Handbook of Well-Being; Diener, E., Oishi, S., Tay, L., Eds.; DEF Publishers: Salt Lake City, UT, USA, 2018; Available online: https://www.nobascholar.com (accessed on 15 June 2025).
- World Health Organization. Coronavirus Disease (COVID-19) Pandemic. Available online: https://www.who.int/europe/emergencies/situations/covid-19 (accessed on 21 November 2025).
- Whittemore, R.; Knafl, K. The integrative review: Updated methodology. J. Adv. Nurs. 2005, 52, 546–553. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Knafl, K.; Whittemore, R. Top 10 tips for undertaking synthesis research. Res. Nurs. Health 2017, 40, 189–193. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schaufeli, W.B.; Bakker, A.B. Job demands, job resources, and their relationship with burnout and engagement: A multi-sample study. J. Organ. Behav. 2004, 25, 293–315. [Google Scholar] [CrossRef] [Scilit]
- Schaufeli, W.; Taris, T.W. A critical review of the JD–R model. In Bridging Occupational, Organizational and Public Health; Bauer, G.F., Hämmig, O., Eds.; Springer: Dordrecht, The Netherlands, 2014; pp. 43–68. [Google Scholar] [CrossRef] [Scilit]
- Bakker, A.B.; Demerouti, E. Job demands–resources theory: Taking stock and looking forward. J. Occup. Health Psychol. 2017, 22, 273–285. [Google Scholar] [CrossRef] [Scilit]
- Demerouti, E.; Bakker, A.B.; Nachreiner, F.; Schaufeli, W.B. The job demands–resources model of burnout. J. Appl. Psychol. 2001, 86, 499–512. [Google Scholar] [CrossRef]
- Bakker, A.B.; Demerouti, E. The job demands–resources model: State of the art. J. Manag. Psychol. 2007, 22, 309–328. [Google Scholar] [CrossRef] [Scilit]
- Morgan, R.L.; Whaley, P.; Thayer, K.A.; Schünemann, H.J. Identifying the PECO framework. Environ. Int. 2018, 121, 1027–1031. [Google Scholar] [CrossRef] [Scilit]
- Tomori, K.; Sawada, T.; Ohno, K.; Takahashi, K.; Okita, Y. Reporting guidelines for scoping reviews: PRISMA-ScR. Jpn. Soc. Clin. Occup. Ther. 2020, 7, 70–76. (In Japanese) [Google Scholar]
- Peters, M.D.J.; Godfrey, C.M.; Khalil, H.; McInerney, P.; Parker, D.; Soares, C.B. Guidance for conducting systematic scoping reviews. Int. J. Evid. Based Healthc. 2015, 13, 141–146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Irinyi, T.; Lampek, K.; Németh, A.; Zrínyi, M.; Oláh, A. Discriminating low-, medium-, and high-burnout nurses: Role of organisational and patient-related factors. J. Nurs. Manag. 2019, 27, 1663–1672. [Google Scholar] [CrossRef] [Scilit]
- Kelly, L.A.; Lefton, C.; Fischer, S.A. Nurse leader burnout, satisfaction, and work–life balance. J. Nurs. Adm. 2019, 49, 404–410. [Google Scholar] [CrossRef] [Scilit]
- Nakayama, M.; Katsuki, F. Association between role stress/workload and burnout in nurse managers. Jpn. J. Nurs. Res. 2020, 43, 223–233. [Google Scholar] [CrossRef]
- Cha, W.J.; Kim, S. The effects of job demand and job resources on burnout and work engagement of hospital nurse administrators. Korean J. Occup. Health Nurs. 2020, 29, 262–272. [Google Scholar] [CrossRef]
- Garcia, G.P.A.; Marziale, M.H.P. Satisfaction, stress and burnout of nurse managers and care nurses in primary health care. Rev. Esc. Enferm. USP 2021, 55, e03675. [Google Scholar] [CrossRef] [Scilit]
- Giannouli, V.; Syrmos, N. The flight of Icarus: A preliminary study of the emotional correlates of hubris in gerontological nurses during the SARS-CoV-2 pandemic. Psychiatr. Danub. 2021, 33, S109–S113. [Google Scholar]
- Sadati, A.K.; Heydari, S.T.; Ebrahimzade, N.; Lankarani, K.B. A qualitative study of nursing management in Iran. J. Environ. Public Health 2021, 2021, 1315734. [Google Scholar] [CrossRef] [Scilit]
- Prochnow, J.A.; McGill, R.L.; Pesut, D.J.; Gordon, D.; Deno, F.E.; Becknell, M.D. Challenges and choices: Insights derived from a survey of nurse leader burnout. Nurs. Manag. 2021, 52, 32–40. [Google Scholar] [CrossRef] [Scilit]
- Semerci, R.; Öztürk, G.; Akgün Kostak, M.; Elmas, S.; İhsan Danacı, A.; Musbeg, S. The effect of progressive muscle relaxation exercises on compassion satisfaction, burnout, and compassion fatigue of nurse managers. Perspect. Psychiatr. Care 2021, 57, 1645–1651. [Google Scholar] [CrossRef] [Scilit]
- Galura, S.; Warshawsky, N. A survey of interim nurse managers to understand the role and the impact on nurse and patient outcomes. J. Nurs. Adm. 2022, 52, 42–50. [Google Scholar] [CrossRef] [Scilit]
- Lucas, G.; Colson, S.; Boyer, L.; Gentile, S.; Fond, G. Work environment and mental health in nurse assistants, nurses and health executives: Results from the AMADEUS study. J. Nurs. Manag. 2022, 30, 603–612. [Google Scholar] [CrossRef] [Scilit]
- Luo, D.; Song, Y.; Cai, X.; Li, R.; Bai, Y.; Chen, B.; Liu, Y. Nurse managers’ burnout and organizational support: The serial mediating role of leadership and resilience. J. Nurs. Manag. 2022, 30, 4251–4261. [Google Scholar] [CrossRef] [Scilit]
- Membrive-Jiménez, M.J.; Velando-Soriano, A.; Pradas-Hernandez, L.; Gomez-Urquiza, J.L.; Romero-Béjar, J.L.; Cañadas-De la Fuente, G.A.; De la Fuente-Solana, E.I. Prevalence, levels and related factors of burnout in nurse managers: A multi-centre cross-sectional study. J. Nurs. Manag. 2022, 30, 954–961. [Google Scholar] [CrossRef] [Scilit]
- Montgomery, A.P.; Patrician, P.A. Work environment, resilience, burnout, intent to leave during COVID pandemic among nurse leaders: A cross-sectional study. J. Nurs. Manag. 2022, 30, 2792–2800. [Google Scholar] [CrossRef] [Scilit]
- Pallesen, K.S.; McCormack, B.; Kjerholt, M.; Borre, L.Z.; Rosted, E.; Hølge-Hazelton, B. An investigation of the level of burnout and resilience among hospital-based nurse managers after COVID-19: A cross-sectional questionnaire-based study. J. Nurs. Manag. 2022, 30, 4106–4115. [Google Scholar] [CrossRef] [Scilit]
- Sawyer, A.T.; Harris, S.; Green, J.F.; Du, Y.; Richard, T.; Robinson, P.S.; Celano, P.; Kelly, K.; Bailey, A.K. Clinical leader series: A virtual mental well-being initiative for nurse leaders during the COVID-19 pandemic and beyond. J. Nurs. Adm. 2022, 52, 177–184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sarıbudak, T.P.; Güner, P.; Çepni, B. Effect of a compassion fatigue resiliency program on nurse managers’ professional quality of life, stress, and resilience: A mixed-methods study. J. Nurs. Care Qual. 2023, 38, 126–132. [Google Scholar] [CrossRef] [Scilit]
- Sawyer, A.T.; Tao, H.; Bailey, A.K. The impact of a psychoeducational group program on the mental well-being of unit-based nurse leaders: A randomized controlled trial. Int. J. Environ. Res. Public Health 2023, 20, 6035. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alenezi, L.; Gillespie, G.L.; Smith, C.; Davis, K.G. Gender differences in burnout among US nurse leaders during the COVID-19 pandemic: An online cross-sectional survey study. BMJ Open 2024, 14, e089885. [Google Scholar] [CrossRef] [Scilit]
- Bunch, J.L.; Gedney-Lose, A.; Perkhounkova, Y.; Sharp, B.; Groves, P.S. Nurse managers’ professional quality of life during the COVID-19 pandemic. West. J. Nurs. Res. 2024, 46, 183–191. [Google Scholar] [CrossRef] [Scilit]
- Melnyk, B.M.; Chenot, T.; Hsieh, A.P.; Messinger, J. Supportive workplace wellness cultures and mattering are associated with less burnout and mental health issues in nurse managers. J. Nurs. Adm. 2024, 54, 456–464. [Google Scholar] [CrossRef] [Scilit]
- Zhang, C.; Yang, Z.; Liang, Y.; Feng, Y.; Zhang, X. A qualitative study of head nurses’ experience in China: Forced growth during patient safety incidents. BMC Nurs. 2024, 23, 592. [Google Scholar] [CrossRef] [Scilit]
- Hu, H.; Chang, S.; Tian, G.; Li, Z.; Chang, L.; Zhang, J.; Cheng, C.; Zhang, H.; Cui, P. The impact of perceived stress on job satisfaction among nurse managers: A moderated mediation model of job burnout and psychological capital. BMC Nurs. 2025, 24, 953. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sanabria-Delgado, D.; Barrientos-Trigo, S.; Porcel-Gálvez, A.M. Exploring the long-term impact of emotional exhaustion on frontline nurse managers post-COVID-19: A qualitative study. J. Nurs. Manag. 2025, 2025, 9280686. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Urban, R.W.; Martin, S.D.; Bailey, S.; Rivera, N.; Lim, M.L.C.; Bracco, S. Exploring psychosocial variables and professional well-being in nurse leaders: A predictive correlational study. Worldviews Evid. Based Nurs. 2025, 22, e70054. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maslach, C.; Jackson, S.E. The measurement of experienced burnout. J. Organ. Behav. 1981, 2, 99–113. [Google Scholar] [CrossRef] [Scilit]
- Stamm, B.H. The Concise ProQOL Manual, 2nd ed.; ProQOL.org: Pocatello, ID, USA, 2010. [Google Scholar]
- Bakker, A.B.; Demerouti, E.; Euwema, M.C. Job resources buffer the impact of job demands on burnout. J. Occup. Health Psychol. 2005, 10, 170–180. [Google Scholar] [CrossRef] [Scilit]
- Kristensen, T.S.; Borritz, M.; Villadsen, E.; Christensen, K.B. The Copenhagen Burnout Inventory: A new tool for the assessment of burnout. Work Stress 2005, 19, 192–207. [Google Scholar] [CrossRef] [Scilit]
- Pines, A.; Aronson, E. Career Burnout: Causes and Cures; Free Press: New York, NY, USA, 1988. [Google Scholar]
- Halbesleben, J.R.B.; Demerouti, E. The construct validity of an alternative measure of burnout: Investigating the English translation of the Oldenburg Burnout Inventory. Work Stress 2005, 19, 208–220. [Google Scholar] [CrossRef] [Scilit]
- Hølge-Hazelton, B.; Kjerholt, M.; Rosted, E.; Hansen, S.T.; Borre, L.Z.; McCormack, B. Improving person-centred leadership: A qualitative study of ward managers’ experiences during the COVID-19 crisis. Risk Manag. Healthc. Policy 2021, 14, 1401–1411. [Google Scholar] [CrossRef] [Scilit]
- Munday, R. A Guide to the Nursing Hierarchy; NurseJournal: Charlotte, NC, USA, 2024; Available online: https://nursejournal.org/resources/guide-to-nursing-hierarchy/ (accessed on 24 November 2025).
- Bakker, A.B.; de Vries, J.D. Job demands–resources theory and self-regulation: New explanations and remedies for job burnout. Anxiety Stress Coping 2021, 34, 1–21. [Google Scholar] [CrossRef] [Scilit]
- Lown, B.A.; Manning, C.F. The Schwartz Center Rounds: Evaluation of an interdisciplinary approach to enhancing patient-centered communication, teamwork, and provider support. Acad. Med. 2010, 85, 1073–1081. [Google Scholar] [CrossRef] [Scilit]
- Lefton, C. Strengthening the workforce through meaningful recognition. Nurs. Econ. 2012, 30, 331–338. [Google Scholar]
- McCrae, R.R.; Costa, P.T., Jr.; Ostendorf, F.; Angleitner, A.; Hřebíčková, M.; Avia, M.D.; Sanz, J.; Sánchez-Bernardos, M.L.; Kusdil, M.E.; Woodfield, R.; et al. Nature over nurture: Temperament, personality, and life span development. J. Pers. Soc. Psychol. 2000, 78, 173–186. [Google Scholar] [CrossRef]
- Santos, T.M.; Balsanelli, A.P.; Souza, K.M.J. Randomized crossover clinical trial of a mindfulness-based intervention for nurse leaders: A pilot study. Rev. Lat.-Am. Enferm. 2024, 32, e4101. [Google Scholar] [CrossRef] [Scilit]
- Mohammadi, F.; Vahedi, S.; Alilu, L.; Khameslou, M.A. Effectiveness of an education program based on systems thinking and organizational resilience of nurse managers: A quasi-experimental study. J. Nurs. Adv. Clin. Sci. 2025, 3, 9–16. [Google Scholar] [CrossRef] [Scilit]
- Thompson, W.; McNamara, M. The advanced nurse practitioner in context: Systemic processes. J. Nurs. Scholarsh. 2023, 55, 886–897. [Google Scholar] [CrossRef] [Scilit]



| Database | Search Formula | Filters/Notes |
|---|---|---|
| Ichushi-Web | (Psychological Burnout/TH AND Nurse Manager/TH) | Original research articles only; case reports excluded |
| PubMed | (“Nurse Administrators” [MH] AND “Burnout, Psychological” [MH]) | MeSH terms used |
| EBSCO (CINAHL and MEDLINE) | Burnout AND (Administrator OR Executive OR Manager OR Leader) AND TI nurs * NOT review | Peer-reviewed articles only; MEDLINE records excluded to avoid duplication |
| First Author/Year | Study Design | Country | Participants: (Total, Nurse Manager Positions) | Main Personal Characteristics of Nurse Managers | Burnout Scale | Quality Assessment |
|---|---|---|---|---|---|---|
| Irinyi 2019 [39] | Cross-sectional | Hungary | Total nurses (n = 1201): nurse directors: 2.3%; middle managers: 20.9%; nursing staff: 76.8% | No Data | PA | High |
| Kelly 2019 [40] | Mixed methods | United States | Nurse managers (n = 672) *: nurse directors (n = 100); middle managers (n = 142); first-line managers (n = 430) | F: 89.9%; Nursing experience (Mean ± SD): 17.24 ± 10.26: first-line managers < middle managers < nurse directors | Burnout subscale of ProQOL | High |
| Nakayama 2020 [41] | Cross-sectional | Japan | Total nurses (n = 355), managerial position (n = 261): first-line managers: 22%; assistant first-line managers: 51%; nursing staff (n = 94) | F: 98%; Married: 76%; Have children: 70%; Have someone to consult: 98%; Nursing experience ≥ 15 yrs.: 100% (including staff); Nursing experience 21–30 yrs.: 59% | MBI, Japanese version | High |
| Cha 2020 [42] | Cross-sectional | South Korea | Total nurses (n = 188): nurse directors: 9.6%; middle managers: 14.9%; first-line managers: 14.9%; nursing staff: 60.6% | Administrative department: 100% | MBI-GS | Low: Independent burnout factors for nurse managers were not calculated. |
| Garcia 2021 [43] | Cross-sectional | Brazil | Total nurses (n = 122): Nurse managers: 47.5%; nursing staff: 52.5% | No Data | BCS | High |
| Giannouli 2021 [44] | Pilot | Greece | Clinical leaders (n = 162) | Age (M; Mean ± SD): 48.87 ± 7.32; Age (F; Mean ± SD): 49.23 ± 7.37; Married/cohabiting: 100%; Yrs. of experience (M; Mean ± SD): 20.65 ± 8.44; Yrs. of experience (F; Mean ± SD): 21.45 ± 7.85 | MBI | Low: Insufficient description of variables. No numerical data reported for analysis between burnout and other variables. |
| Sadati 2021 [45] | Qualitative | Iran | Nurse managers (n = 11): nurse directors (n = 1); assistant nurse directors (n = 2); middle managers (n = 6); first-line managers (n = 2) | No Data | Semi-structured interview | High |
| Prochnow 2021 [46] | Mixed methods | United States | Nurse managers (n = 212): nurse directors: 11.2%; middle managers: 35.4%; first-line managers: 33.1%; clinical leaders: 20.3% | Age (Mean): 50.3; F: 91.8%; Married: 82.7%; Hospital employment: 57.7%; Management experience (Mean): 12.9 | Original questionnaire | High |
| Semerci 2021 [47] | Quasi-experimental | Turkey | first-line managers (n = 30) | No Data | Burnout subscale of ProQOL | High |
| Galura 2022 [48] | Cross-sectional | United States | Temporary first-line managers (n = 179) | Age (Mean ± SD): 41.6 ± 6.94; F: 68.0%; Master’s degree: 47.7%; Professional leadership certification: 82%; Management experience (Mean ± SD): 6.28 ± 3.85 | MBI-GS | Low: Factors associated with burnout were not identified. |
| Lucas 2022 [49] | Cross-sectional | France | Healthcare professionals (n = 6935): nurse directors (n = 126) | Age: M ± SD 54.42 ± 6.33; M: 27.8% | MBI, Spanish version | High |
| Luo 2022 [50] | Cross-sectional | China | Nurse managers (n = 458); middle managers and above: 58.3% | Age (Mean ± SD): 42.0 ± 19.8; F: 98.7%; Bachelor’s degree or higher: 84.5%; Nursing experience (Mean ± SD): 20.1 ± 7.0; Management experience ≥ 1 yrs.: 100%; Management experience (Mean ± SD): 7.0 ± 4.8 | MBI-HSS, Chinese version | High |
| Membrive-Jiménez 2022 [51] | Cross-sectional | Spain | middle managers (n = 86) | Age (Mean ± SD): 46.65 ± 7.16; F: 58.1%; Married/In a relationship: 82.6%; Have children: 88.4%; Fixed morning shift: 80.2%; On-call duty: 48.8%; Yrs. as a nurse (Mean ± SD): 281.67 ± 90.192 months; Management experience (Mean ± SD): 128.24 ± 114.41 months; Nursing experience (Mean ± SD): 20.1 ± 7.0 | MBI, Spanish version | High |
| Montgomery 2022 [52] | Cross-sectional | United States | Nurse managers (n = 86): nurse directors: 7.1%; middle managers: 35.7%; first-line managers: 42.9%; clinical leaders: 14.3% | No Data | CBI | High |
| Pallesen 2022 [53] | Cross-sectional | Denmark | First-line managers (n = 31) | Age (Mean): 47.6; F: 97%; No formal management education: 45%; Management experience over 5 yrs.: 52%; Management experience 3–5 yrs.: 19%; Management experience 0–2 yrs.: 29%; Number of employees (Mean): 30.7 | CBI | Low: Small sample size. |
| Sawyer 2022 [54] | Quasi-experimental | United States | Nurse managers (n = 32) *: nurse directors; middle managers; first-line managers; assistant first-line managers | Management experience Before intervention (Median): 5; Management experience After intervention (Median): 9.5; Clinical managers Before intervention: 100%; Clinical managers After intervention: 100% | MBI-GS | Low: Insufficient description of MBI; small sample size. |
| Sarıbudak 2023 [55] | Quasi-experimental | Turkey | First-line managers (n = 16) | Age (Mean ± SD): 32.87 ± 4.47; F: 87.5%; Management experience (Mean ± SD): 10.75 ± 5.61 | Burnout subscale of ProQOL-4, Turkish version | Low: Did not focus on burnout. |
| Sawyer 2023 [56] | Randomized controlled trial | United States | First-line managers (n = 80) | F: Intervention group 82.1%, Control group 92.1%; Married: Intervention group 61.5%, Control group 76.3%; Master’s degree: Intervention group 20.5%, Control group 31.6%; Age (Mean ± SD): Intervention group 43.97 ± 10.60, Control group 44.76 ± 9.24 | Burnout subscale of ProQOL | High |
| Alenezi 2024 [57] | Cross-sectional | United States | Nurse managers (n = 210): nurse directors; middle managers; first-line managers; assistant first-line managers | No Data | CBI | High |
| Bunch 2024 [58] | Cross-sectional | United States | First-line managers (n = 54): first-line managers; assistant first-line managers | Age (Mean ± SD): 39.7 ± 8.7; F: 98.1%; Married/Cohabiting: 84.9%; Have dependent children: 72.2%; Master’s or PhD: 53.7%; Nursing experience (Mean ± SD): 16.3 ± 8.1; Management experience at current institution (Mean ± SD): 5.9 ± 5.8; Weekly work hours at workplace (Mean ± SD): 47.3 ± 6.9; Weekly work hours at home (Mean ± SD): 6.6 ± 8.3 | Burnout subscale of ProQOL-5 | High |
| Melnyk 2024 [59] | Cross-sectional | United States | First-line managers (n = 125): first-line managers: 86.4%; assistant first-line managers: 13.6% | F: 89.6%; Age 40s (Most common): 34.4%; Academic Medical Center/Health System (Most common): 51.2%; Direct reports: 40%; Day shift: 95.2%; Work hours: 8–10 h/day: 70.4% | Original questionnaire, Sensitivity and specificity verified | High |
| Zhang 2024 [60] | Qualitative | China | First-line managers (n = 15) | Clinical department: 100%; F: 80%; Management experience (Mean): 39.67; Age (Mean): 9.07 | Semi-structured interview | High |
| Hu 2025 [61] | Cross-sectional | China | Nurse managers (n = 784); nurse directors; middle managers; first-line managers | ≤36 yrs. (Most common): 27.4%; F: 98.2%; Master’s degree: 3.0%; Married: 95.5%; Management experience ≤ 4 yrs. (Most common): 27.0%; First-line managers (Most common): 79.7%; General hospital: 93.4%; Weekly work hours ≥ 41: 87.6% | MBI, Chinese version | High |
| Sanabria-Delgado 2025 [62] | Qualitative | Spain | First-line managers (n = 12) | Management experience ≥ 12 months: 100%; Unit admitting COVID-19 patients: 100%; Age (Mean): 51.4; Master’s level education: 25%; Management experience (Mean): 11.5 | MBI Semi-structured interview | High |
| Urban 2025 [63] | Cross-sectional | United States | Nurse managers (n = 105): nurse directors; middle managers; first-line managers | No Data | OLBI | High |
| First Author/Year | Main Findings: Burnout-Associated Factors and Scores |
|---|---|
| Irinyi 2019 [39] | Factors associated with higher burnout: Being a manager vs. nursing staff |
| Kelly 2019 [40] | Factors associated with higher burnout: Lack of leadership experience; Low satisfaction with collaboration Factors associated with lower burnout: High overall satisfaction; High satisfaction with work–life balance Factors with no association: Position differences among nurse managers; Perceived evaluation; Perception of collaboration at work Nurse Manager Burnout Scores (Mean ± SD): first-line managers: 23.29 ± 5.7; middle managers: 23.42 ± 5.77; nurse directors: 23.19 ± 5.56; total nurse managers: 23.30 ± 5.69 |
| Nakayama 2020 [41] | Factors associated with higher burnout: Role conflict; Role ambiguity; Underutilization of skills; Fluctuation in workload; Subjective physical symptoms; Age 40s Factors associated with lower burnout: Overtime < 5 h; Possess qualifications; Self-esteem; Job control; Responsibility for people Factors with no association: Quantitative workload; Cognitive demands Nurse Manager Burnout Scores (Mean): Emotional Exhaustion: 15.68; Depersonalization: 11.53; Reduced Personal Accomplishment: 20.98 |
| Cha 2020 [42] | Factors associated with lower burnout: Being a manager Nurse Manager Burnout Scores (Mean ± SD): nurse directors: 2.04 ± 0.58; middle managers: 2.93 ± 0.96; first-line managers: 3.07 ± 0.94 |
| Garcia 2021 [43] | Factors associated with higher burnout: Occupational stress Factors associated with lower burnout: Satisfaction with hierarchical relationships; Intrinsic job satisfaction; Being a manager vs. Care nurse Factors with no association: Satisfaction with physical work environment Nurse Manager Burnout Scores (Mean ± SD): Emotional Exhaustion: 2.4 ± 0.7 (Moderate); Depersonalization: 1.6 ± 0.3 (Mild); Disappointment with work: 1.7 ± 0.5 (Moderate) |
| Giannouli 2021 [44] | Factors with no association: Demographic variables: Age, Gender, Yrs. of experience, Education, etc.; Emotions at work; Emotional labor strategies; Emotional regulation style; Physical and psychological interpersonal distance at work; Job satisfaction; Emotional intelligence; State anxiety; Group cohesiveness; Arrogance Nurse Manager Burnout Scores (Mean ± SD): Burnout: 3.24 ± 1.11 |
| Sadati 2021 [45] | Factors associated with higher burnout: Dealing with issues beyond primary duties; Responding to both patients and subordinates; Inadequate organizational response; Multifaceted pressure; Staff shortages |
| Prochnow 2021 [46] | Factors associated with higher burnout: Difficulties in communication and interpersonal relationships; Increased expectations for nurse managers; Managing daily workload; Addressing and improving staff morale; Insufficient flexible work arrangements and lack of remote work opportunities; Addressing daily challenges with limited resources; Lack of administrative support Factors associated with lower burnout: Ensuring work–life balance; Engaging in meaningful work; Providing high-quality care or being part of it |
| Semerci 2021 [47] | Factors associated with lower burnout: Continuing progressive muscle relaxation for ≥2 months; Nurse Manager Burnout Scores (Median, IQR): Before intervention: 18.50, 13.75–26.25; After 1st intervention: 17.00, 12.75–20.00; After 2nd intervention: 14.00, 9.00–19.00 |
| Galura 2022 [48] | Nurse Manager Burnout Scores (Mean ± SD): Exhaustion: 3.88 ± 1.17 (Moderate); Cynicism: 2.68 ± 1.04 (Moderate); Lack of Professional Efficacy: 5.86 ± 0.53 (Severe) |
| Lucas 2022 [49] | Factors associated with lower burnout: Nurse managers vs. Nursing assistants, nursing staff, OR nurses, medical administrators, senior medical administrators, physicians Prevalence of burnout among nurse managers (%): Emotional Exhaustion: 23.0%; Depersonalization: 14.3%; Reduced Personal Accomplishment: 27.0%; Burnout: 45.2%; Severe Burnout: 3.2% |
| Luo 2022 [50] | Factors associated with higher burnout: Nurse directors vs. Middle managers and below Factors associated with lower burnout: Organizational support; High nurse manager leadership; High resilience; Medical/Surgical vs. ICU/Emergency ward staff; Pediatrics vs. ICU/Emergency ward staff; Gynecology, Obstetrics, Psychiatry, OR vs. ICU/Emergency ward staff Nurse Manager Burnout Scores (Mean ± SD): Burnout: 28.8 ± 18.5 Prevalence of burnout among nurse managers (%); Emotional Exhaustion: 39.3% (Moderate–Severe); Depersonalization: 22.5% (Moderate–Severe); Reduced Personal Accomplishment: 40.8% (Moderate–Severe) Other implications: Serial multiple mediation effect: Organizational support → Nurse manager leadership → Resilience → Burn out; Mediation effect: Organizational support → Resilience → Burnout |
| Membrive-Jiménez 2022 [51] | Factors associated with higher burnout: Neuroticism; Depressive symptoms; Anxiety; On-call duties; Conscientiousness * Factors associated with lower burnout; Extraversion *; Conscientiousness *; Agreeableness *; Openness * Factors with no significant association with burnout: Demographic variables: Age, Gender, Marital status, Number of children; Work-related variables: Shift type, Yrs. of experience as a nurse manager, Yrs. of experience as a nurse Prevalence of burnout among nurse managers (%): Emotional Exhaustion: Moderate 30.6% Severe 22.4%; Depersonalization: Moderate 36% Severe 21%; Personal Accomplishment: Moderate 28.2% Severe 14.1%; Burnout: Severe 34.1% |
| Montgomery 2022 [52] | Factors associated with higher burnout: Intention to leave Factors associated with lower burnout: Nurse manager Authority enhancement *; Fair and manageable workload; Constructive relationships between first-line and middle managers; Effective relationships between nurse managers and nursing staff; Adequate budgeted resources; Generative culture *; Culture of meaning *; Better practice environment; Resilience Nurse Manager Burnout Scores (Mean ± SD): Personal Burnout: 54.76 ± 22.48; Work-related Burnout: 52.81 ± 21.49; Client-related Burnout: 38.09 ± 22.66 |
| Pallesen 2022 [53] | Other implications: Mean resilience scores in both the low and high personal burnout groups were at the upper end of the normal range; The high personal burnout group was 6.6 yrs. younger on average than the low personal burnout group; The proportion of participants with formal management education was slightly lower in the high personal burnout group (50.0%) compared to the low personal burnout group (57.1%) Nurse Manager Burnout Scores (Mean ± SD): Personal Burnout: 42.9 ± 18.6; Work-related Burnout: 39.1 ± 19.5; nursing staff-related Burnout: 25.7 ± 18.7 Prevalence of burnout among nurse managers (%): Personal Burnout: 32.3 (Severe); Work-related Burnout: 29.0 (Severe); Client-related Burnout: 6.5 (Severe) |
| Sawyer 2022 [54] | Factors with no significant association with burnout: Educational program fostering joy and satisfaction in work, strengthening managerial roles, and promoting healthy self-care behaviors Nurse Manager Burnout Scores (Median, IQR): Exhaustion: Before intervention: 2.0, 0.8–3.6; After intervention: 1.9, 0.8–3.0; Cynicism Before intervention: 0.8, 0.2–2.4 After intervention: 0.8, 0.2–1.6; Professional Efficacy Before intervention: 5.5, 4.7–5.8 After intervention: 5.5, 5.0–6.0 |
| Sarıbudak 2023 [55] | Factors with no significant association with burnout: Program improving knowledge and coping skills for compassion fatigue Nurse Manager Burnout Scores (Mean ± SD): Pre-intervention: 17.06 ± 5.18 (Mild); Post-intervention: 15.81 ± 5.23 (Mild) |
| Sawyer 2023 [56] | Factors associated with lower burnout: Psychoeducational group program RISE (Effect observed from immediately post-intervention to 1 month) Nurse Manager Burnout Scores (Mean ± SD): Pre-intervention: 23.06 ± 6.45 (Moderate); Post-intervention: 21.47 ± 6.23 (Mild); 1-month follow-up: 20.97 ± 5.02 (Mild); 3-month follow-up: 22.41 ± 7.44 (Mild); 6-month follow-up: 21.97 ± 7.75 (Mild) |
| Alenezi 2024 [57] | Factors associated with higher burnout: Female gender (Associated only with Personal Burnout); Male gender (Associated only with Client-related Burnout) Nurse Manager Burnout Scores (Mean ± SD): Total Personal Burnout: 54.8 ± 15.6, F: 56.2 ± 16.4, M: 49.3 ± 10.0; Total Work-related Burnout: 53.0 ± 14.8, F: 53.6 ± 15.7, M: 50.6 ± 9.8; Total Client-related Burnout: 37.0 ± 19.2, F: 34.8 ± 19.4, M: 45.3 ± 15.7 |
| Bunch 2024 [58] | Factors associated with higher burnout: Weekly work hours at workplace; Weekly work hours at home; Intention to leave for a non-nursing position outside the organization since pandemic onset; Intention to transfer to a non-managerial nursing position within the organization within the next 6–12 months Nurse Manager Burnout Scores (Mean ± SD): Burnout: 29.0 ± 5.3 (Moderate) Factors with no significant association with burnout: Intention to transfer to a non-managerial nursing position within the organization since pandemic onset; Intention to leave for a nursing position outside the organization since pandemic onset; Intention to leave for a non-nursing position outside the organization since pandemic onset; Intention to leave for a nursing position outside the organization within the next 6–12 months; Intention to leave for a non-managerial position outside the organization within the next 6–12 months; Demographic variables: Age, Yrs. of experience as a nurse, Yrs. of experience in current organization, Weekly work hours at workplace, Weekly work hours at home Prevalence of burnout among nurse managers (%): Mild: 9.3; Moderate: 88.9; Severe: 1.9 |
| Melnyk 2024 [59] | Factors associated with higher burnout: Stressful work environment; Staff shortages in the unit Factors associated with lower burnout: Work environment supportive of personal wellness; Perceived ability to practice healthy lifestyle habits daily; Organization supportive of taking leave for medical visits; Perceived importance to the workplace Factors with no significant association with burnout: Supporting nursing staff well-being as a manager Prevalence of burnout among nurse managers (%): Burnout: 54.4 |
| Zhang 2024 [60] | Factors associated with higher burnout: Uncertainty of specific duties and expected roles during patient safety incidents; Unclear communication methods with patients and staff during patient safety incidents *; Significant mental burden despite no direct responsibility for patient safety incidents * |
| Hu 2025 [61] | Factors associated with higher burnout: Perceived stress Factors associated with lower burnout: High job satisfaction; High psychological capital Nurse Manager Burnout Scores (Mean ± SD): Emotional Exhaustion: 15.49 ± 11.24; Depersonalization: 4.12 ± 5.35; Reduced Personal Accomplishment: 37.93 ± 9.55 |
| Sanabria-Delgado 2025 [62] | Factors associated with higher burnout: Fear of the pandemic; Uncertainty due to the pandemic; Pressure to make critical decisions with limited information during the pandemic; Frequent protocol changes during the pandemic; Difficulties in staffing during the pandemic; Shortage of material resources during the pandemic; Managing scarce resources during the pandemic; Balancing empathy for families and patient safety during the pandemic; Being blamed by nurses during the pandemic; Lack of support from colleagues during the pandemic Factors associated with lower burnout: Words of gratitude from colleagues and family Prevalence of burnout among nurse managers (%): Severe Emotional Exhaustion: 25; Severe Depersonalization: 50 Severe Reduced Personal Accomplishment: 25 |
| Urban 2025 [63] | Factors associated with higher burnout: High stress; High life satisfaction Factors associated with lower burnout: High life satisfaction; High self-compassion *; High resilience Nurse Manager Burnout Scores (Mean ± SD): Burnout: 36.35 ± 6.96; Exhaustion: 2.37 ± 0.45; Disengagement: 2.16 ± 0.48 Prevalence of burnout among nurse managers (%): Exhaustion: 59.1; Disengagement: 46.4 |
| JD-R Model Components | Pre-Pandemic | Pandemic-Era |
|---|---|---|
| Job demands | Responsibility and role-related burden as a manager [41,45,46] | Responsibility and pressure associated with the managerial role [51,60,62] |
| Long working hours [41] | Long working hours and on-call duties [51,58] | |
| Resource and staffing management during shortages [45,46] | Resource and staffing management during shortages [59,62] | |
| Continuous changes in protocols [62] | ||
| Difficulty balancing empathy for families with patient safety [62] | ||
| Fear and uncertainty related to the pandemic [62] | ||
| Role uncertainty during critical incidents [60] | ||
| Role ambiguity and additional tasks [41,45] | ||
| Managing and maintaining subordinate morale [46] | ||
| Responding to both patient and staff needs [45] | ||
| Managing daily workload [46] | ||
| Job resources | Organizational support [45,46] | Organizational support and supportive organizational climate [50,52,59] |
| Effective interpersonal relationships and communication [46] | Effective interpersonal relationships and communication [52,62] | |
| Expanded managerial discretion [41] | Expanded managerial discretion [52] | |
| Adequate workload and material resources [52] | ||
| Permeation of a positive organizational culture [52] | ||
| Support from colleagues [62] | ||
| Utilization of professional expertise and skills [41] | ||
| Ensuring work–life balance [40,46] | ||
| Flexible work arrangements [46] | ||
| Intrinsic job satisfaction [43] | ||
| Personal resources | Leadership capacity of nurse managers [40] | Leadership capacity of nurse managers [50] |
| Overall life and job satisfaction [40] | Overall life and job satisfaction [63] | |
| Sense of purpose and contribution as a manager [46] | Meaning derived from the managerial role [59] | |
| Resilience [41] | Resilience [50,51,52,61,63] | |
| Positive personality traits [51] | ||
| Achievable healthy lifestyle habits [59] |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Matsumoto, M.; Hara, Y.; Mayers, T.; Omiya, T. Shifts in Research Focus on Factors Associated with Burnout Among Nurse Managers Before and During the COVID-19 Pandemic: An Integrative Review. Occup. Health 2026, 1, 22. https://doi.org/10.3390/occuphealth1020022
Matsumoto M, Hara Y, Mayers T, Omiya T. Shifts in Research Focus on Factors Associated with Burnout Among Nurse Managers Before and During the COVID-19 Pandemic: An Integrative Review. Occupational Health. 2026; 1(2):22. https://doi.org/10.3390/occuphealth1020022
Chicago/Turabian StyleMatsumoto, Mizuka, Yukari Hara, Thomas Mayers, and Tomoko Omiya. 2026. "Shifts in Research Focus on Factors Associated with Burnout Among Nurse Managers Before and During the COVID-19 Pandemic: An Integrative Review" Occupational Health 1, no. 2: 22. https://doi.org/10.3390/occuphealth1020022
APA StyleMatsumoto, M., Hara, Y., Mayers, T., & Omiya, T. (2026). Shifts in Research Focus on Factors Associated with Burnout Among Nurse Managers Before and During the COVID-19 Pandemic: An Integrative Review. Occupational Health, 1(2), 22. https://doi.org/10.3390/occuphealth1020022