


Abstract
Parkinson’s disease is a progressive neurological disorder typically beginning in middle or late life, with risk increasing with age. Accessing health services for people living with Parkinson’s disease can be challenging and stressful, often resulting in the worsening of current symptoms, the development of new symptoms, including infection, fatigue, and confusion, or medication changes. This can lead to an increased length of stay in hospital and/or readmission, further worsening symptoms. The aim of this scoping review is to explore how quality improvement and healthcare redesign initiatives have contributed to understanding issues around length of stay and readmission to hospital for people living with Parkinson’s disease. The review was guided by Arksey and O’Malley’s framework and reported according to the Preferred Reporting Items for Systematic Reviews and Meta-Analyses Extension for Scoping Reviews Checklist. The Excerpta Medica dataBASE (EMBASE), Medline, and Cumulated Index in Nursing and Allied Health Literature (CINAHL) databases were searched for relevant articles published between 2019 and 2023. The included articles were categorised using thematic analysis. Ten articles were included in this review, resulting in the following three major categories: issues contributing to length of stay and readmission, interventions, and recommendations. Quality improvement and healthcare redesign can improve the length of stay and readmission rates for people living with Parkinson’s disease through robust design, delivery, and evaluation.
1. Introduction
Parkinson’s disease (PD) is a neurological disorder affecting approximately 8.5 million people globally [1] and is characterised by a range of motor and non-motor symptoms. These include tremor, rigidity, postural instability, bradykinesia, autonomic dysfunction, mood disturbances, cognitive impairment, sleep disorders, and pain [2]. These symptoms progress over time, with a recent post-mortem analysis suggesting that people typically live 6.9 years to 14.3 years after a diagnosis [3]. Although the progression of the disease is variable between individuals and highly heterogenic, the resultant increasing disability has been shown to lead to higher hospital admission rates [1,2]. Recent studies have identified four main reasons for hospitalisation among people with PD. These include infections, such as urinary tract infections and pneumonia, worsening motor features contributing to reduced mobility, falls and fractures, delirium, dementia, and associated neuropsychiatric symptoms and autonomic features of PD including gastrointestinal complications, orthostatic hypotension-related syncope, and adverse drug events [2,3,4].
Health services for people living with PD generally involve an integrated care coordination model, due to the complexity of the symptomatology. Integrated care, defined as a care approach designed according to the multidisciplinary needs of the patient, has been shown to improve patient-reported health-related quality of life compared with standard care [5]. Integrated models of care for PD patients typically include healthcare providers working across settings and levels of care. Medical and surgical management and consultations, allied healthcare, and rehabilitation are common for PD patients in both the inpatient and outpatient settings [5]. Integrative models for chronic conditions have been demonstrated to reduce hospital admissions, decrease length of stay, and reduce costs, and are more effective when targeting single conditions and providing care in patients’ homes [6]. Despite this patient-centred multidisciplinary model of care, challenges remain for health services around PD patient admissions and the length of stay in hospital.
Length of stay in hospital is influenced by a range of factors related to PD. Previous studies have reported on complications post-operatively for PD patients including increased costs, mortality, length of stay following total hip arthroplasty [7], increased adverse events such as aspiration pneumonia and urinary tract infection following non-neurologic surgery [8], and the deterioration of respiratory, cardiovascular, and neurologic function due to general anaesthesia [9]. People living with PD who are admitted to hospital with a PD-related cause have been shown to have a significantly longer length of stay than those who do not have a PD-related cause for admission [10,11,12,13]. Gil Prieto (2016) demonstrated that 87% of PD patients had at least one co-morbidity, with the most frequent causes for hospitalisation being respiratory infection, urinary tract infections, cardiovascular disease, and falls and fractures. Hospitalisation rates for PD patients increase with age [13], with emergency PD admissions being the most common cause of hospital admission [12]. Gerlach [14] found that PD patients often left hospital with worse motor function, with medication errors being the most important significantly related risk factors for deterioration, followed by infections during hospitalisation. Therefore, reducing the length of stay of PD patients is one mechanism for the improvement in quality of the overall patient experience and outcomes for people living with PD.
The purpose of this scoping review is to identify whether healthcare redesign and quality improvement projects contribute to improving the PD patient length of stay and (re)admission to hospital. This includes reason(s) for admissions, patient experience in hospital, and quality improvement interventions that have been utilised to reduce length for stay for PD patients. The authors are not aware of any systematic reviews or meta-analyses that focus on redesign work undertaken to improve the management of PD patients in hospital, to date.
2. Materials and Methods
The scoping review was guided by the Arksey and O’Malley [15] six-stage framework, without the optional consultation stage, and was reported using the Preferred Reporting Items for Systematic Reviews and Met-Analyses (PRISMA) framework [16]. We did not register this protocol.
2.1. Stage 1: Identifying the Research Questions
This scoping review assessed the following research questions:
- What issues have been identified that contribute to readmission for PD patients and PD patients having a longer than average length of stay (LOS) compared to the overall hospital average LOS?
- What solutions and interventions have been identified and evaluated to reduce LOS and readmission for PD patients?
2.2. Stage 2: Search Strategy
A search of the literature was conducted in August 2023 using three databases: EMBASE, Medline, and CINHAL. Search terms were informed by previous published literature and categorised into four silos using a Population, Intervention, Context, Outcome (PICO) format [17] (Table 1). The MeSH thesaurus was used for CINAHL and Medline, and the Emtree thesaurus was used for Embase to ensure we captured terms reflecting the aim of our review. The Boolean operator “OR” was used within each silo and “AND” was used to join the silos. Each silo reflects an aspect of the research question. The timeframe for our search was 2019 to 2023, reflecting the period of increasing quality improvement publications in acute health services, relevant to current service delivery.
Table 1.
Search terms according to PICO criteria.
2.3. Stage 3: Screening and Study Selection
After the automatic and manual removal of duplicates (n = 15), titles and abstracts were manually screened by the lead author based on the inclusion and exclusion criteria (Table 2). The full texts of studies that met the inclusion criteria were screened independently by two reviewers and any conflicts were discussed and resolved.
Table 2.
Inclusion and exclusion criteria.
2.4. Stage 4: Data Extraction
The data were extracted according to the project design or process, the aim or problem statement, participant description, setting, and outcomes or goals of each project. Next, information from each report was collected according to the descriptions of the issues their project identified as contributing to LOS and (re)admissions, the solutions or interventions implemented to address the issues, and project evaluation detailing results and benefits. Finally, the steps each project took to adjust their interventions or overcome unexpected barriers to further improve their initial results, and the recommendations outlined for others seeking to perform similar work were listed (Appendix A).
2.5. Stage 5: Data Collation, Summary, and Reporting
The data were analysed and summarised according to themes consistent with the methodology for scoping reviews [18]. The thematic analysis was conducted using a six-step process: familiarisation, coding, generating themes, reviewing themes, defining, and naming themes, and writing up [19].
3. Results
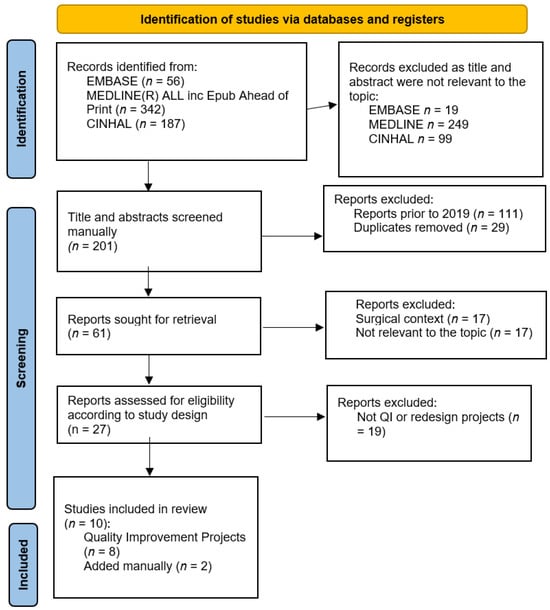
This scoping review yielded eight articles. Two reports known to the author were added manually, one from a non-indexed journal and one from a previous project. A final ten articles were included in the review. This is represented visually in the PRISMA flow chart (Figure 1). A summary of the literature is provided below, and three themes related to the research questions are discussed.
Figure 1.
PRISMA chart.
3.1. Summary of the Literature
Four reports described their work as a redesign or quality improvement project, noting a redesign methodology or framework [20,21,22]. One did not include the framework description [23]. Two reports were retrospective observational evaluations of one of the redesign projects [24,25]. Four reports were retrospective observational studies, audits, or evaluations conducted before and after a described set of interventions [26,27,28,29].
The participants in all reports were people with Parkinson’s disease admitted to acute care hospitals. The identification of participants referred to ICD 10 coding in three cases [20,24,26]; six studies did not provide criteria for the identification of their PD patient cohort [21,22,23,25,29]; three specifically required evidence of PD diagnosis by a specialist [26,27,28]. Three reports described staff as both targets of and participants in the redesign process [21,22,23]. Hospital settings ranged from large tertiary or teaching hospitals [20,22,24,26,28] to smaller regional hospitals without a specialty unit [21,25,27,29]; one report combined resources of a centre of excellence with a regional hospital [23].
All reports aimed to improve services to enhance the patient’s experience. Eight reports listed improved patient journey or experience as a primary goal or outcome, implementing a change in service that involved a new specialist service team or nurse [20,21,22,25,26,28,29]. Seven reports had goals and outcome measures related to medication management, including accurate prescribing, a reduction in medication errors and the avoidance of contraindicated medications [20,21,24,27,29], and the timely administration of medications [21,22,23,29]. Seven reports had goals and outcome measures specific to LOS and (re)admissions [22,24,25,26,27,28,29].
3.2. Theme 1: Issues Contributing to LOS and (Re)Admissions
The severity and complexity of PD symptoms were identified as impacting LOS and (re)admission [24,26,28], particularly with reference to falls and pneumonia [21,23,24,26], poor medication management [20,21,27], and neuropsychiatry and postural hypotension [26]. Due to the complexity of the disease, the reasons for admission varied and often led to admissions across the hospital to various services, contributing to a lack of focused specialised care during admission [20,21,22,24] or gaps in services [28]. A first admission to hospital is an indicator for future admissions [23,26]. Other reasons for admission to hospital included sepsis or other infections, urinary tract infections [24,26], and cardiac, renal, or orthopaedic reasons [24].
3.3. Theme 2: Interventions
Interventions targeted patient identification, specialised care plans or pathways, staff education, and medication management and swallow [20,21,22,23,24,25,26,27,28,29] to reduce length of stay and readmission. The identification of patients within the hospital system used electronic medication record (EMR) systems or electronically generated reports [20,21,29]. These alerts or reports notified specialised care teams or a PD nurse of the arrival of the PD patient to enable timely assessment, the provision of specialised advice, and recommendations for treatment or discharge [20,25,26,28,29]. In one case, the identification of PD patients led to the prospective collection of patient demographic data [26]. Specialised care plans or pathways [20,22] were initiated in an early and timely fashion [25]. These consisted of specialised PD team meetings [24], PD nurse review and interventions [25,29], or posters providing information of key contacts available for medication advice [22].
Multifaceted staff education programmes were implemented across hospitals [24,25]. Education programmes consisted of posters and or stickers [20,21,22,23,30], reminding staff of the time-critical nature of PD medications. These materials complemented regular education sessions focusing on the complex nature of PD symptoms and the medication regimes [20,22,27,29]. In some instances, electronic modules, including videos, were developed to enable the repetitive presentation of material in a time-efficient way [20,22].
Other strategies to improve medication management included timely reviews of medication charts by a pharmacist [20,23,27] or specialist team [26,29]. Medication formularies were reviewed to ensure medications were available, reducing the time until the administration of the first dose of PD medication [20,21,23]. EMR upgrades included prompts and reminders for prescribers and nurses [22,23] or small alarm clocks for nurses to carry to prompt them to administer medication on time [22]. Projects that identified poor patient swallow as a priority developed an algorithm to switch from oral medication if swallow is compromised [21] or implemented an ‘urgent’ pathway for the insertion of nasogastric tubes in radiology for PD patients [22] to minimise disruption to symptom control when swallow was compromised. Reports that followed a robust redesign methodology also included descriptions of gathering a multidisciplinary team of staff to contribute to the redesign process [20,21]. Others emphasised the role of the consumer and the patient’s story to ensure interventions would be effective in addressing patient needs [21,22,28].
Ongoing monitoring of performance indicators was a specific strategy for continued improvement [24]. The evaluation of interventions demonstrated that the identification of patients improved [21,27], medication incidents reduced [21,24,27,29], and pharmacy reviews were conducted in a timely fashion [27]. There were improvements in medication administration workflow [23] and timely administration [21,22,23,24,27,29], with some outcomes including increased self-medication [22,29].
LOS was reported to have reduced by between 8 and 50% [21,24,25,27,28,29] with cost savings of up to AUD 8600 per person per year in Australia [25]. Very little was reported on changes to readmission rates, with one study reporting no change [27]. However, improvements in patient and carer experience [21,22,23,28] and improved staff satisfaction [21,28] were widely reported. Common outcomes included improved service delivery [21,22,28], access to specialised services [26], timely interventions and discharge advice [26], reduced complication rates, and a reduced need to increase care after discharge [27]. Services gained a better understanding of their PD patient cohort [26] and reasons for readmissions [28]. Patients admitted from aged care facilities had longer LOS [26]. Improvements extended beyond the wards, enabling interventions across the hospital [23] and assembling stakeholders with a common goal—to bridge departmental and professional barriers [20,29].
3.4. Theme 3: Recommendations
All studies made recommendations for their service or for others considering similar projects. Recommendations included developing electronic reporting to identify patients and measuring outcomes to allow ongoing data review for enduring benefits [20,21,25,29]. Following up these reports with stakeholders such as hospital executive or nurse managers provides the opportunity to develop further actions to address underperforming measures, non-compliance, and patient and carer complaints [20,21,22,29] until changes become core business [21]. This type of ongoing evaluation process as part of a performance improvement structure or healthcare redesign framework also includes a coordinating committee [20,21], where focus on the consumer’s story and consultation further improves outcomes [22].
Three reports recommend collecting demographic data and occasions of service in a prospective manner/on arrival at the hospital [24,25,27]; one recommends pharmacy or clinic records as a means of doing so [26]. A large cohort is recommended to reach statistical significance, as a larger sample size and longer period of intervention would better indicate resources are well-spent [27,28]. PD is complex, and the impact of orthostatic hypotension, delirium, and dehydration should also be considered [29]. To address this complexity, an ongoing collaborative multidisciplinary team approach to solving problems of patient care that includes occupational therapists and physiotherapists [29], as well as bedside nurses and pharmacy [20,21,22,29]. An on-call service after hours would also be beneficial [29].
Ongoing education [20,22,27] for hospital staff and PD specialists [29] is required to accommodate staff turnover [27]. A formalised clinical guideline or model of care and interventions that are simple and easy to use [21,22,27] means that results are replicable in different settings within the hospital or to other services/hospitals [22,24,25].
Overall, we recommend building on previous redesign work, learning from their lessons and recommendations to avoid reinventing the wheel, so that future redesign projects implement changes to practise that are already known to be effective, cost-efficient, and improve patient outcomes, with the added benefit of further improving on these previous interventions. This means a greater likelihood of effective, sustainable, and meaningful improvements.
3.5. Limitations
The limitations of this scoping review include the small number of published quality improvement and redesign initiative papers that were found. The authors acknowledge that many quality improvement and redesign projects are not published, but still contain valuable, local information pertinent to improving health services for people with Parkinson’s disease. The authors did not quantify variables, such as severity, which contribute to changes in LOS; rather, we broadly scoped the current literature around the outcomes and impact of variables. The dates selected for our search may have further limited the fundings; however, we feel it is important to capture improvement data relevant to current systems and processes within Parkinson’s disease health service delivery. A broader search may yield a higher number of results but may not be relevant to current health services. Further, a quality assessment of the included studies was not performed. This is not a requirement of scoping reviews and may result in some included studies being of poor quality.
4. Conclusions
An increased length of stay is a major contributor to poor experiences and outcomes for patients with Parkinson’s disease (PD). Robust quality improvement and redesign interventions are effective in improving the hospital admission experience of PD patients. However, ongoing review post-implementation is required to sustain improvements in the long term. Improvements to hospital services that address inefficiencies and workflow can reduce LOS and reasons for admissions can be better understood.
Author Contributions
Conceptualization, S.W.; methodology, S.W. and S.J.P.; formal analysis, S.W. and S.J.P.; investigation, S.W. and S.J.P.; data curation, S.W. and S.J.P.; writing—original draft preparation, S.W. and S.J.P.; writing—review and editing, S.W. and S.J.P.; supervision, S.J.P. project administration, S.W. and S.J.P. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Table A1.
Data Extraction Table.
References
- World Health Organisation (WHO). 2019. Available online: https://www.who.int/news-room/fact-sheets/detail/parkinson-disease (accessed on 8 September 2023).
- Sveinbjornsdottir, S. The clinical symptoms of ’Parkinson’s disease. J. Neurochem. 2016, 139, 318–324. [Google Scholar] [CrossRef] [Scilit]
- Macleod, A.D.; Taylor, K.S.; Counsell, C.E. Mortality in Parkinson’s disease: A systematic review and meta-analysis. Mov. Disord. 2014, 29, 1615–1622. [Google Scholar] [CrossRef] [Scilit]
- Kalia, L.V.; Lang, A.E. Parkinson’s disease. Lancet 2015, 386, 896–912. [Google Scholar] [CrossRef] [Scilit]
- Rajan, R.; Brennan, L.; Bloem, B.R.; Dahodwala, N.; Gardner, J.; Goldman, J.G.; Grimes, D.A.; Iansek, R.; Kovács, N.; McGinley, J.; et al. Integrated Care in Parkinson’s Disease: A Systematic Review and Meta-Analysis. Mov. Disord. 2020, 35, 1509–1531. [Google Scholar] [CrossRef] [Scilit]
- Damery, S.; Flanagan, S.; Combes, G. Does integrated care reduce hospital activity for patients with chronic diseases? An umbrella review of systematic reviews. BMJ Open 2016, 21, e011952. [Google Scholar] [CrossRef] [Scilit]
- Kleiner, J.E.; Eltorai, A.E.M.; Rubin, L.E.; Daniels, A.H. Matched cohort analysis of peri-operative outcomes following total knee arthroplasty in patients with and without Parkinson’s disease. Knee 2019, 26, 876–880. [Google Scholar] [CrossRef] [Scilit]
- Huang, Y.F.; Chou, Y.C.; Yeh, C.C.; Hu, C.J.; Cherng, Y.G.; Chen, T.L.; Liao, C.C. Outcomes After Non-neurological Surgery in Patients With Parkinson’s Disease: A Nationwide Matched Cohort Study. Medicine 2016, 95, e3196. [Google Scholar] [CrossRef] [Scilit]
- Nakadate, Y.; Nakashige, D.; Omori, K.; Matsukawa, T. Risk factors for postoperative complications in patients with Parkinson disease: A single center retrospective cohort study. Medicine 2023, 102, e33619. [Google Scholar] [CrossRef] [Scilit]
- Okunoye, O.; Kojima, G.; Marston, L.; Walters, K.; Schrag, A. Factors associated with hospitalisation among people with Parkinson’s disease—A systematic review and meta-analysis. Parkinsonism Relat. Disord. 2020, 71, 66–72. [Google Scholar] [CrossRef] [Scilit]
- Hommel, A.L.A.J.; Krijthe, J.H.; Darweesh, S.; Bloem, B.R. The association of comorbidity with Parkinson’s disease-related hospitalizations. Parkinsonism. Relat. Disord. 2022, 104, 123–128. [Google Scholar] [CrossRef] [Scilit]
- Shaibdat, N.S.; Ahmad, N.; Azmin, S.; Ibrahim, N.M. Causes, factors, and complications associated with hospital admissions among patients with Parkinson’s disease. Front. Neurol. 2023, 14, 1136858. [Google Scholar] [CrossRef] [Scilit]
- Gil-Prieto, R.; Pascual-Garcia, R.; San-Roman-Montero, J.; Martinez-Martin, P.; Castrodeza-Sanz, J.; Gil-de-Miguel, A. Measuring the Burden of Hospitalization in Patients with Parkinson’s Disease in Spain. PLoS ONE 2016, 11, e0151563. [Google Scholar] [CrossRef] [Scilit]
- Gerlach, O.H.; Broen, M.P.; Weber, W.E. Motor outcomes during hospitalization in Parkinson’s disease patients: A prospective study. Parkinsonism. Relat. Disord. 2013, 19, 737–741. [Google Scholar] [CrossRef] [Scilit]
- Arksey, H.; O’Malley, L. Scoping studies: Towards a methodological framework. Int. J. Soc. Res. Methodol. 2005, 8, 19–32. [Google Scholar] [CrossRef] [Scilit]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit]
- Farrugia, P.; Petrisor, B.A.; Farrokhyar, F.; Bhandari, M. Research questions, hypotheses and objectives. Can. J. Surg. 2010, 53, 278. [Google Scholar]
- Booth, A.; Papaioannou, D.; Sutton, A. Systematic Approaches to a Successful Literature Review; Sage Publications: Thousand Oaks, CA, USA, 2012. [Google Scholar]
- Braun, V.; Clarke, V. Using thematic analysis in psychology. Qual. Res. 2008, 3, 77–101. [Google Scholar] [CrossRef] [Scilit]
- Azmi, H.; Cocoziello, L.; Harvey, R.; McGee, M.; Desai, N.; Thomas, J.; Jacob, B.; Rocco, A.; Keating, K.; Thomas, F.P. Development of a Joint Commission Disease-Specific Care Certification Program for Parkinson Disease in an Acute Care Hospital. J. Neurosci. Nurs. 2019, 51, 313–319. [Google Scholar] [CrossRef] [Scilit]
- Carroll, V.; Deutschmann, K.; Andrews, J. Purposeful collaboration: Enriching lives for people with Parkinson’s disease. Australas. J. Neurosci. 2020, 30, 32–43. [Google Scholar] [CrossRef] [Scilit]
- Corrado, J.; Jackson, O.; Baxandall, D.; Robson, J.; Duggan-Carter, P.; Throssell, J.; Westgarth, T.; Chhokar, G.; Alty, J.; Cracknell, A. Get Parkinson’s medications on time: The Leeds QI project. Age Ageing 2020, 49, 865–872. [Google Scholar] [CrossRef] [Scilit]
- Nance, M.A.; Boettcher, L.; Edingerm, G.; Gardner, J.; Kitzmann, R.; Erickson, L.O.; Wichmann, R.; Wielinski, C.L. Quality Improvement in Parkinson’s Disease: A Successful Program to Enhance Timely Administration of Levodopa in the Hospital. J. Parkinsons Dis. 2020, 10, 1551–1559. [Google Scholar] [CrossRef] [Scilit]
- Azmi, H.; Cocoziello, L.; Nyirenda, T.; Douglas, C.; Jacob, B.; Thomas, J.; Cricco, D.; Finnerty, G.; Sommer, K.; Rocco, A.; et al. Adherence to a strict medication protocol can reduce length of stay in hospitalized patients with Parkinson’s Disease. Clin. Park. Relat. Disord. 2020, 3, 100076. [Google Scholar] [CrossRef] [Scilit]
- Bramble, M.; Wong, A.; Carroll, V.; Schwebel, D.; Rossiter, R. Using an economic evaluation approach to support specialist nursing services for people with Parkinson’s in a regional community. J. Adv. Nurs. 2021, 77, 4722–4732. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hobson, P.; Roberts, S.; Davies, G. The introduction of a Parkinson’s disease email alert system to allow for early specialist team review of inpatients. BMC Health Serv. Res. 2019, 19, 271. [Google Scholar] [CrossRef] [Scilit]
- Lance, S.; Travers, J.; Bourke, D. Reducing medication errors for hospital inpatients with Parkinsonism. Intern. Med. J. 2021, 51, 385–389. [Google Scholar] [CrossRef] [Scilit]
- Lovegrove, C.J.; Marsden, J. Service evaluation of an acute Parkinson’s therapy pathway between hospital and home. Int. J. Ther. Rehabil. 2020, 27, 1–6. [Google Scholar] [CrossRef] [Scilit]
- Moore, S.; Jackson, S.; Yousuf, A. Medication management for patients with Parkinson’s: The impact of a nurse specialist and non-medical prescribing in the hospital setting. J. Prescr. Pract. 2022, 4, 200–204. [Google Scholar] [CrossRef] [Scilit]
- Abboud, H.; Genc, G.; Saad, S.; Thompson, N.; Oravivattanakul, S.; Alsallom, F.; Yu, X.X.; Floden, D.; Gostkowski, M.; Ahmed, A.; et al. Factors Associated With Postoperative Confusion and Prolonged Hospital Stay Following Deep Brain Stimulation Surgery for Parkinson Disease. Neurosurgery 2020, 86, 524–529. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).