


Abstract
Background/Objectives: Days Alive and at Home within 30 days (DAH30) is a patient-centred measurement tool designed to assist with the decision-making and management of patients undergoing surgery. Thus, identifying factors associated with better DAH30 scores would support healthcare providers to optimise patient care and outcomes. This systematic review aimed to determine factors associated with DAH30 scores following surgery. Methods: A sensitive electronic search was conducted in MEDLINE, Embase, Scopus, Web of Science and CINAHL databases in September 2022. Eligible studies included patients undergoing surgery and reporting the association of preoperative and/or postoperative factors and DAH30. Risk of bias was assessed using the QUIPs tool. Results: Of the 14 studies identified, the majority (n = 13, 93%) were cohort studies, presenting moderate or high (n = 8, 60%) risk of bias. This review identified a number of factors influencing DAH30 scores in patients undergoing surgery. ASA Physical Status and surgery duration were the most common factors influencing DAH30 scores. Conclusions: Optimising patients’ health prior to surgery and reducing surgical time have the potential to improve patients’ recovery.
1. Introduction
Surgical intervention is often used with caution and as a last-line treatment modality to treat health conditions where other approaches are no longer amenable or will not provide relief or curative outcomes [1,2]. It has been estimated that approximately 312.9 million surgical procedures are performed globally per year [2,3], with low- and middle-income countries requiring an additional 143.0 million surgical procedures to address their current unmet needs [2]. In the Australian context, 2.6 million admissions for surgical procedures were reported in 2017–2018; 2.2 million elective and 0.4 million emergency procedures [4]. Previous investigations identified that an ageing population will also lead to an increase on surgical demand, and emphasise the necessity for strategies to manage an increasing workload [5]. The potential risk of increased postoperative complications with an increased surgical workload can impact hospital costs, with research examining the increased cost per patient from complications [6]. All hospitals in the United States who performed coronary artery bypass, total hip replacement, abdominal aortic aneurysm repair, or colectomy procedures were assessed for surgical quality and associated costs, with the results showing an increase of $2436 to $5353 in episode costs in hospitals with higher complication rates [6]. Considering the number of surgical procedures performed annually, a reduced number of complications can help decrease the economic burden of surgical procedures.
Modulating factors that influence patient safety and improve surgical techniques have been the focus of many recent studies [7]. These include complications, mortality, length of stay, and readmissions. An increase in surgical volume and an increased focus on patient-centred care emphasises the need for a tool to assess patient-centred outcomes. While patient-centred outcomes following surgery have been explored in the literature, especially in quality of life studies [8], there is also a need for further research focusing on the acute outcomes following surgery. The need to reduce cost, reduce harm, and effectively predict patients’ recovery time and outcomes is also important for managing the demand on hospitals [9]. One patient-centred measure which has been used to understand patient outcomes is Days Alive and at Home within 30 days (DAH30).
The DAH30 measure focuses on patients’ postoperative recovery immediately following surgery, by evaluating days at home up to 30 days following surgery [9]. The DAH30 can assess quality of care, in particular surgical care, reflecting personal, social and economic benefit by utilising their postoperative length of stay, hospital readmission rate, discharge location, and mortality within 30 days of surgery, to assess the number of days alive and at home from index surgery (day zero) until 30 days postoperatively. It is a tool which has been used to evaluate the effectiveness of surgical procedures and help surgeons improve services [10]. The potential for a tool that incorporates multiple patient-centred outcomes provides the opportunity for further research, clinical evaluation, and administrative use in the management of patients undergoing surgery [9].
The perspective and needs of patients, surgeons, and the organisation, and how these needs interrelate, requires careful consideration in surgical planning. Patients are often guided by cost, survival rates, recovery, and quality of life postoperatively when deciding on whether to undergo surgery [11]. When participating in the shared decision-making process with the patient to determine the most suitable treatment approach, surgeons need to incorporate the patient perspective in their treatment recommendations. Other considerations for surgeons include the patients’ demographics, diagnosis, type of surgical procedure, and resources required [12]. In addition, hospitals and organisations should have both a cost-effectiveness and patient care focus. A particular demand is to reduce costs by reducing length of stay and complication rates. The DAH30 measure considers these social and economic factors by assessing surgical severity, surgical quality, and patients’ expected recovery. DAH30 can also be calculated and used as a predictor to patient outcomes without additional data collection nor patient burden. In understanding the predictors influencing DAH30 scores and ultimately patients’ recovery, surgeons and patients can be informed of the expected recovery time postoperatively and be better equipped for more effective decision-making. Therefore, the aim of this systematic review was to assess the association between preoperative and postoperative factors on DAH30 scores following surgery.
2. Materials and Methods
This systematic review followed the Preferred Reporting Items for Systematic Reviews and Meta-Analysis (PRISMA) guidelines (Supplementary Material S1) [13]. A protocol was prepared to outline the research question, search strategy, eligibility criteria and analysis, and prospectively registered on PROSPERO (registration number: CRD42022351495). No amendments have been made to the protocol.
2.1. Search Strategy
A sensitive electronic search was conducted in MEDLINE & Embase via Ovid, Scopus, Web of Science and CINAHL in September 2022 (Appendix A). The search strategy was also reviewed by a medical librarian from The University of Sydney to ensure a thorough search of the literature. To gather all available literature, a broad search was performed in the selected databases using keywords and alternatives for “surgery” and “DAH30”. All studies were screened, and clearly irrelevant studies were removed. The remaining studies were imported into COVIDENCE for screening. COVIDENCE is a screening tool designed for systematic reviews, to improve the efficiency of the review process [14]. Two investigators (J.B., T.Y.C.) first assessed the studies for eligibility independently by screening title and abstracts. All studies were then independently assessed for eligibility by reviewing the full text by both investigators. Any disagreements were discussed and resolved with a third investigator (D.S.).
2.2. Eligibility Criteria
Studies were included if they investigated the association of preoperative and/or postoperative factors and DAH30 for patients undergoing a surgical procedure. Both cancer and non–cancer-related surgical procedures were included. No restrictions were placed on publication date, language, and type of study design. No restrictions were placed on the studies’ time frame of follow up; however, they must have assessed DAH30. Reference lists of included articles were also screened for additional relevant articles.
2.3. Risk of Bias (ROB) Assessment
All articles included in the review were assessed for risk of bias using the Quality in Prognosis Studies tool (QUIPs) [15]. The following domains were assessed in each article and rated as “high”, “moderate”, or “low” risk of bias: study participation; study attrition; prognostic factor measurement; outcome measurement; study confounding; statistical analysis; and reporting. Two authors (J.B., T.Y.C.) independently assessed articles for risk of bias. Disagreements were discussed with a third author (D.S.) to obtain a consensus.
2.4. Data Extraction and Synthesis
A standardised piloted data-extraction form was employed to collate study information (including authors, year of publication, study location, and study design), population characteristics, predictors assessed, scoring methods, outcomes, results, and funding. Data extraction and synthesis was performed independently by two review authors (J.B., J.M.). Disagreements were discussed with a third author (S.K.) to obtain a consensus.
The primary intention of this review was to conduct a meta-analysis on the association between preoperative and postoperative factors and DAH30 scores. However, due to the number of studies identified, and heterogeneity on preoperative and postoperative factors, results were presented descriptively.
3. Results
3.1. Study Selection and Characteristics
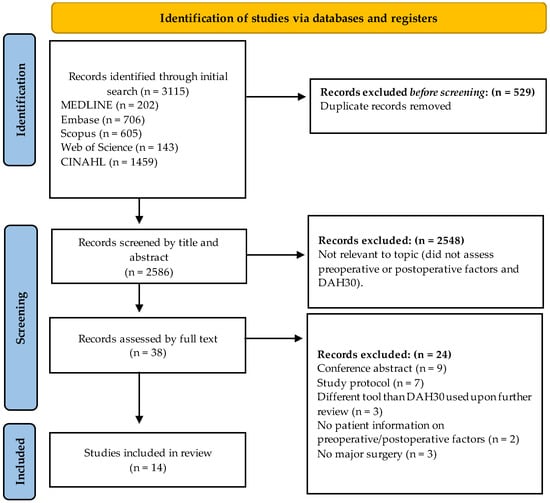
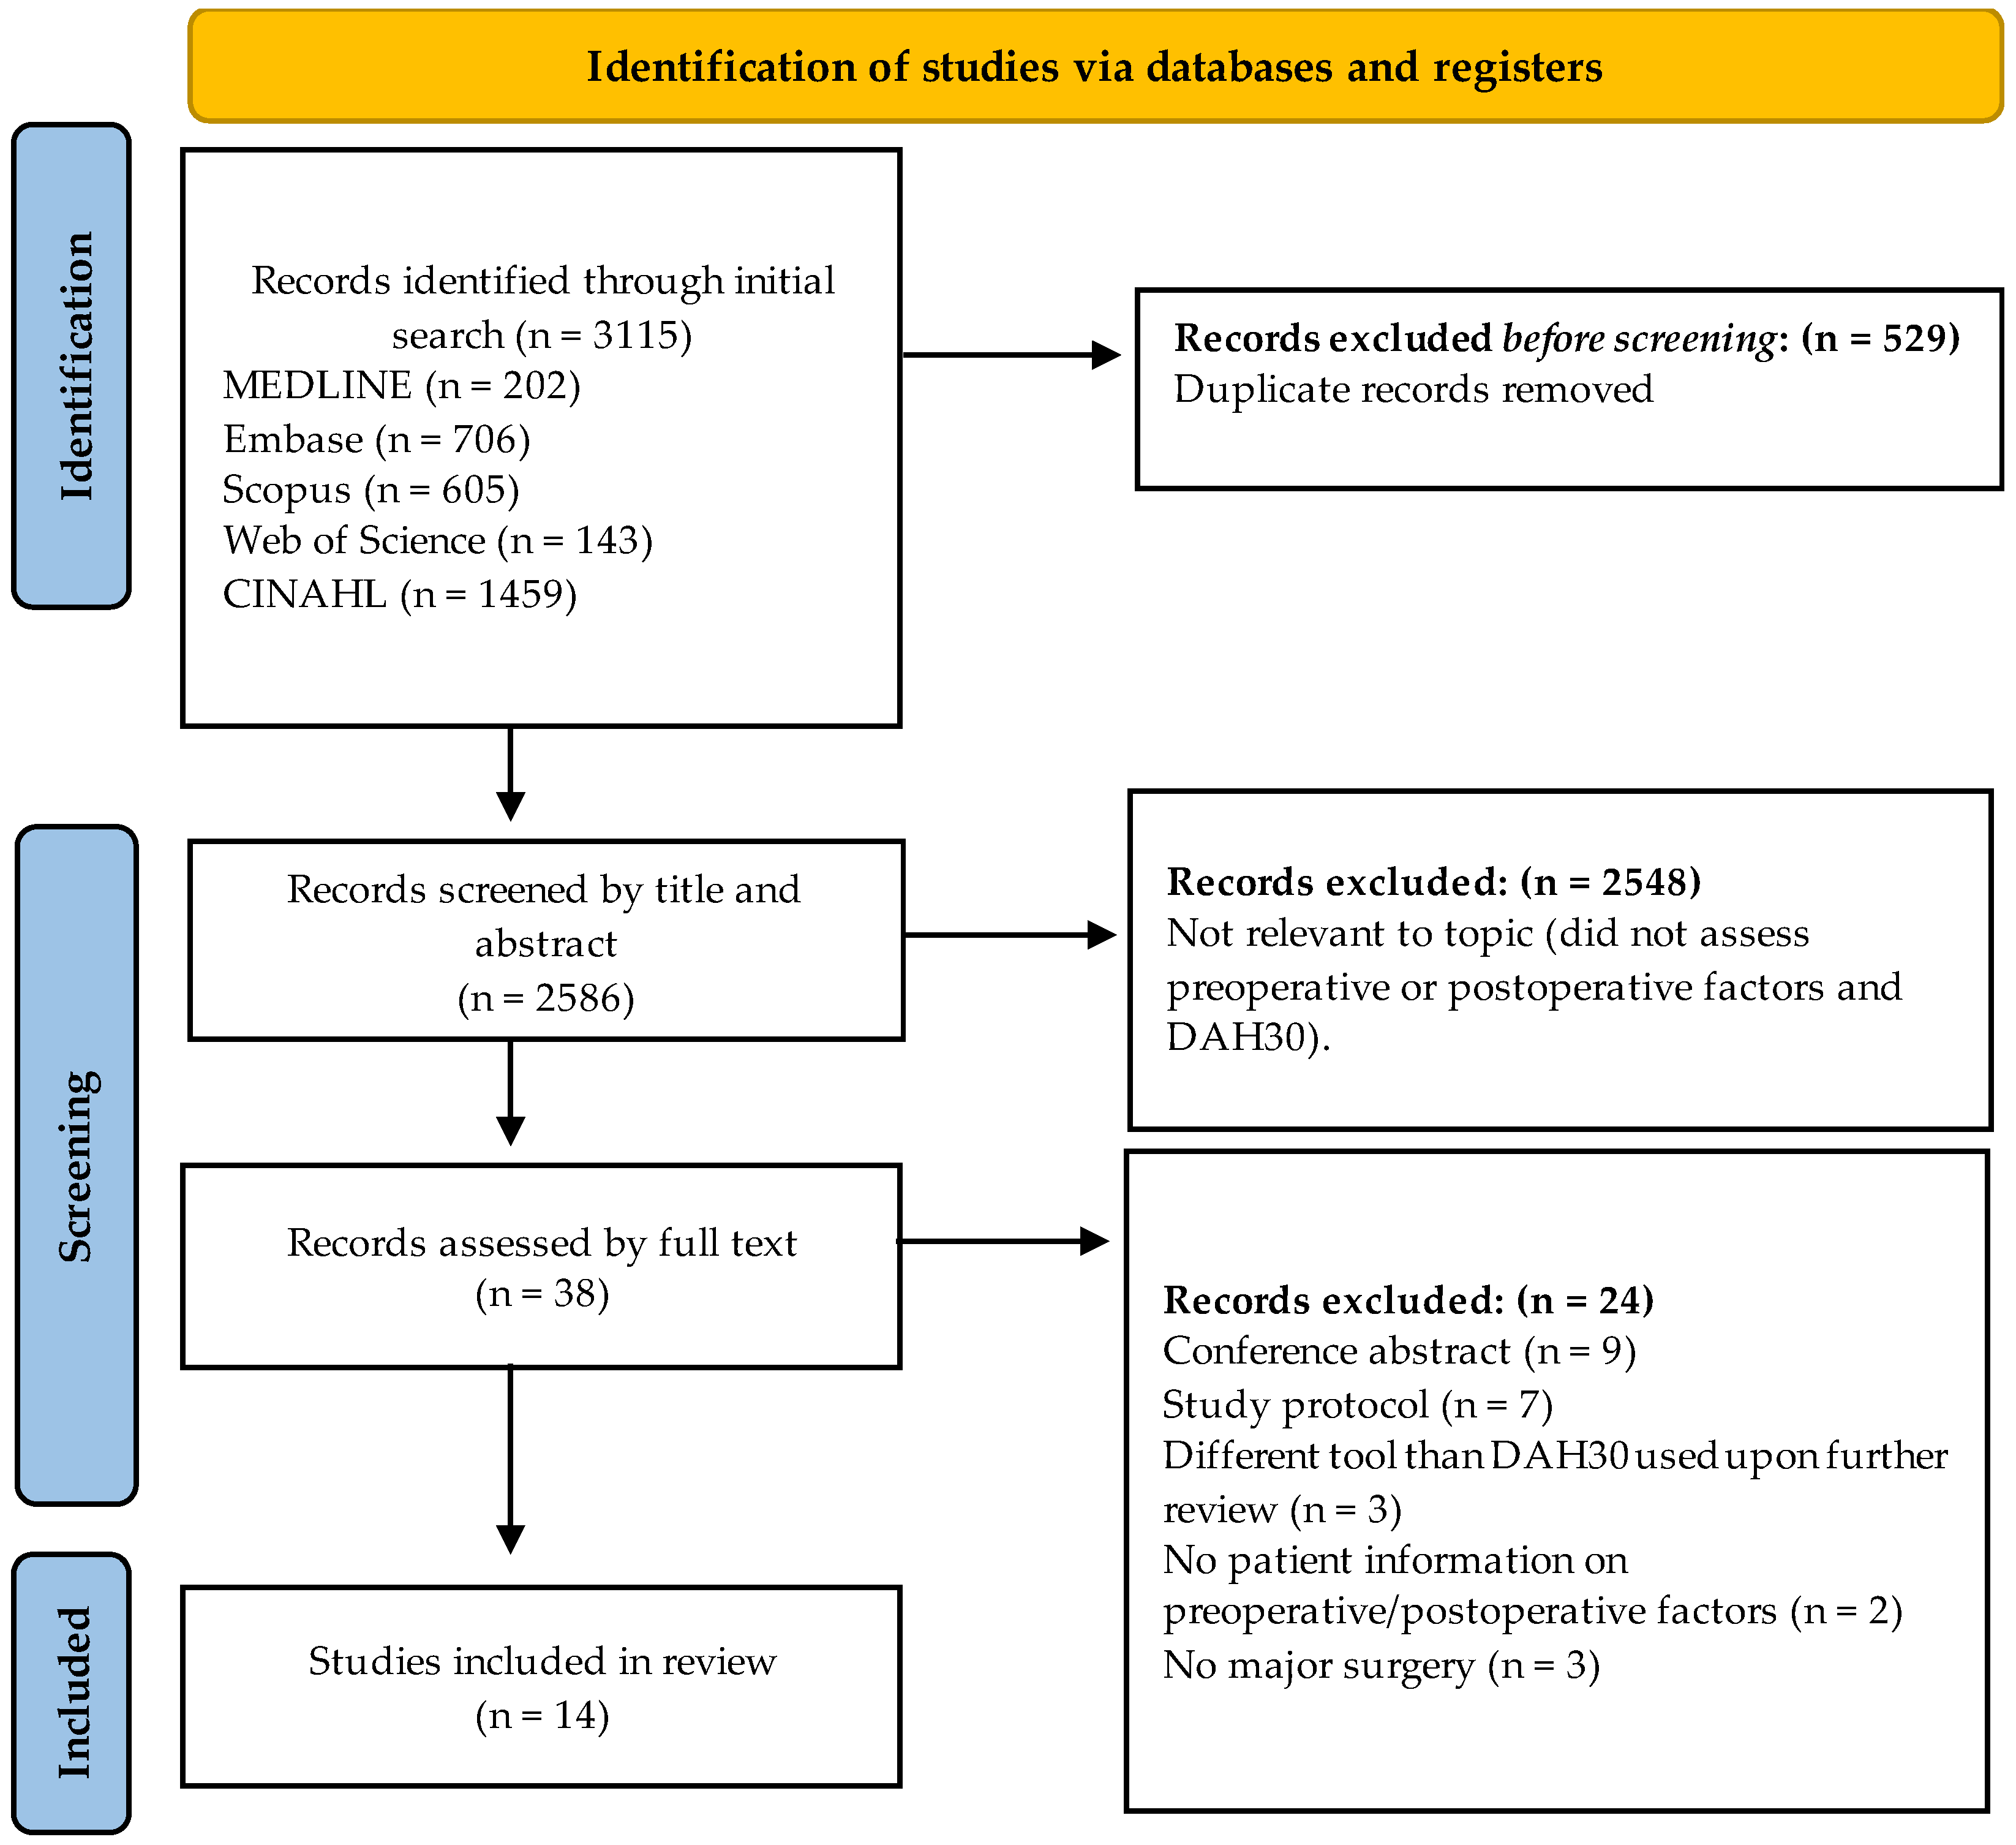
The initial search identified 3115 articles, with 14 studies meeting the eligibility criteria following review (Figure 1).
Figure 1.
PRISMA flow diagram. DAH30 = Days Alive and at Home within 30 days.
Included studies were published between 2017 and 2022, and were predominately cohort studies (n = 13, 93%). A total of 2,262,838 patients were analysed in all studies, with the sample size ranging from 40 to 724,459 [16,17]. The type of surgery assessed varied with 57% (n = 8) of studies including mixed surgeries with varying severity and duration. Reported surgical procedures included total knee and hip arthroplasty (n = two studies, 16,323 patients), hip fracture surgery (n = one study, 1048 patients), cardiac surgery (n = one study, 480 patients), major abdominal surgery (n = one study, 71 patients), colorectal cancer surgery (n = one study, 40 patients) and mixed surgeries (n = nine studies, 2,245,203 patients). A number of articles with large sample sizes were noted as conducted by one collaborative group with a similar patient cohort [17,18,19]. Funding was reported in 12 studies [10,17,18,19,20,21,22,23,24,25,26,27]. The characteristics of the included studies are provided in Table 1.
Table 1.
Characteristics of studies.
Similar methods to calculate DAH30 scores incorporating length of stay, readmission, discharge location, and mortality (where mortality rendered DAH30 to be zero) were used. Myles et al. (2017) was the most commonly cited paper for reference to the DAH30 score calculation (n = 9), which enabled similar scoring methods [24]. Two articles had variations to the way they calculated DAH30, by considering mortality not equal to zero, prolonged admissions, and patients who did not return to their original baseline [21,23]. Jørgensen et al. (2019) recorded the DAH30 score for patients who died as index surgery minus date of death, and adjustments were made for patients admitted for a prolonged period DAH30 scores from the admission date [21]. Miles et al. (2022) accounted for patients who did not return to their original level of care (DAH30 score = zero) [23].
3.2. Risk of Bias
Risk of bias for the included studies was mostly judged as low to moderate (Table 2). There was an equal proportion of included articles that were rated with low (n = 6, 40%) or moderate risk of bias (n = 6, 40%), with a small proportion rated as high risk of bias (n = 2, 20%). Overall, articles performed better in the study attrition and prognostic factor measurement domains; with 93% (n = 13) and 100% (n = 14) of articles being rated as low risk of bias for these domains, respectively. Poorer risk-of-bias results were demonstrated in the outcome measurement and study confounding domains.
Table 2.
Risk of bias assessment.
3.3. Predictors of DAH30
ASA Physical Status and surgery duration were the most reported predictors assessed for DAH30 scores (Table 3). All studies evaluating ASA Physical Status as a predictor found that a higher ASA score was significantly associated with better DAH30 scores [10,20,24,25]. Bell et al. (2019) notably reported statistically significant results (p = 0.0001) of an association between higher ASA Physical Status with higher DAH30 scores [20]. Shorter surgery duration (<60 min) was found to be associated with better DAH30 scores [10,19,20,24,25]. However, lack of consistency was observed across studies with each using different time points to analyse surgical duration due to the variety of surgical procedures. Time point cutoffs included ≥60 min or <60 min [20], intervals from ≥30 min [10], intervals between <2.0 and >4.0 [24], and ≥median DAH30 or <median DAH30 [19]. Elective surgery, intermediate compared to minor surgical severity, and higher surgical volumes were also associated with better DAH30 scores [10,19].
Table 3.
Predictors associated with DAH30.
Patients with a lower Charlson Comorbidity Index [10,20], low-risk patients [21], or younger patients [19,24] were associated with better DAH30 scores. In contrast frailty, postoperative complications, iron deficiency, and iron therapy were associated with worse DAH30 scores. Hospital location (tertiary and central versus district and regional) was also associated with worse DAH30 scores [28].
4. Discussion
To our knowledge, this is the first systematic review investigating the current available literature exploring factors that predict DAH30 scores. This study observed an increase in the use of the DAH30 tool in the literature, with a number of factors significantly associated with DAH30 in patients undergoing surgery.
The impact of predictors for DAH30 scores varied across included studies. For one of the most common predictors, ASA Physical Status, four studies reported it to be positively associated with DAH30 scores [10,20,24,25]. However, two studies (50%) were assessed as high risk of bias [24,25]. This was also found for the predictor surgical time, where five studies reported reduced surgical time being associated with higher DAH30 scores, with only two studies (40%) assessed as low risk of bias [20]. Higher DAH30 scores were also associated with younger age [17], sex [10,20], elective surgery [10], endocrine, breast, eyes, ear nose and throat surgeries [20], and lower Charlson Comorbidity Index at 1- and 5-year follow-up regardless of whether a cancer diagnosis was made [20] in studies with low risk of bias. Conversely, complications, frailty, neighbourhood median household income quintile, and presence of iron or iron therapy were negatively associated with DAH30, with evidence being reported by studies with both low and medium risk of bias. A number of predictors can therefore be used to determine DAH30 scores in patients undergoing surgery to support surgical planning.
Risk-of-bias ratings varied across studies when assessing each predictor, which demonstrates a lack of high-quality research currently available. However, the results of studies were comparable. The DAH30 scores and study results support assumptions and previous research on patients’ postoperative outcomes, though caution should still be applied when relying on the results of studies with medium or high risk of bias. More high-quality and rigorous research is required to confirm and determine the effectiveness of these predictors and their impact on DAH30 scores. The current literature highlights some predictors that are more common in current literature, e.g., ASA Physical Status, surgery duration, and type of surgery, which should be considered when selecting predictors to assess in future research.
Due to the nature of the measurement tool assessed, included studies tended to be retrospective audits of patients who had previously undergone surgical procedures at selected hospitals. In addition, a portion of the included studies were conducted by the same research group from one retrospective cohort of patients, which may explain some similarities in the types of studies, predictors assessed, and analyses conducted [17,18,19]. Some studies also grouped the type of surgery performed into general surgical specialities, which were noted to involve a range of surgical procedures [18,20,24]. It is therefore recommended that high-quality research assessing DAH30 scores in specific surgical procedures and other predictors should be conducted to help guide surgeons and patients when planning and deciding on a treatment approach.
This review was conducted following the PRISMA guidelines. However, it was limited to the quality of the literature currently conducted. It is acknowledged that the novelty of the measurement tool is reflective of the amount and quality of the current literature. Studies tended to have predictive factors on DAH30 scores as secondary outcomes of their research studies, which aligns with the suggestion of further research to better assess the impact of predictors on DAH30 scores. Further research may also help justify and assess the extent of the usefulness of the measurement tool in surgical planning.
5. Conclusions
There is an increasing focus on DAH30 to assist with patient-centred approaches in surgical decision-making. The DAH30 measurement tool can be effective in guiding surgeons and patients when deciding on a surgical procedure as an appropriate treatment option. A variety of predictors were assessed as impacting DAH30 scores, which should be used to predict patients’ recovery and quality of life postoperatively at the surgical-planning stage. Further high-quality research is required to determine the effectiveness of the DAH30 measurement tool and assess the extent of factors which predict DAH30 scores.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/gidisord6040057/s1, Supplementary Material S1: PRISMA Checklist.
Author Contributions
Conceptualisation, J.B. and D.S.; methodology J.B. and D.S.; literature searches and screening, J.B., T.Y.C., and D.S.; formal analysis, J.B., J.M., T.Y.C., S.K. and D.S.; writing—original draft, J.B., J.M., S.K. and D.S.; writing—review and editing, J.B., J.M., S.K., T.Y.C., M.S., C.K., C.S. and D.S.; supervision, S.K., M.S., C.K., C.S. and D.S. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analysed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflict of interests.
Appendix A
| MEDLINE via Ovid | |
| #1 | (Surger* OR operat* OR surgical procedure*).mp |
| #2 | (((DAH30 OR “days at home up to 30 days after surgery” OR days alive and at home OR days at home* OR postoperative 30 days) OR ((postoperative* OR preoperative* OR after surgery* OR after procedure*) adj3 (days alive and at home) OR days at home OR DAH30))).mp |
| #3 | (#1 AND #2) |
| #4 | Limit #3 to humans |
| Embase via Ovid | |
| #1 | (Surger* OR operat* OR surgical procedure).mp |
| #2 | (((DAH30 OR “days at home up to 30 days after surgery” OR days alive and at home OR days at home* OR postoperative 30 days) OR ((postoperative* OR preoperative* OR after surgery* OR after procedure*) adj3 (days alive and at home) OR days at home OR DAH30))).mp |
| #3 | (#1 AND #2) |
| #4 | Limit #3 to humans |
| AMED via Ovid | |
| #1 | (Surger* OR operat* OR surgical procedure).mp |
| #2 | (((DAH30 OR “days at home up to 30 days after surgery” OR days alive and at home OR days at home* OR postoperative 30 days) OR ((postoperative* OR preoperative* OR after surgery* OR after procedure*) adj3 (days alive and at home) OR days at home OR DAH30))).mp |
| #3 | (#1 AND #2) |
| #4 | Limit #3 to humans |
| Scopus | |
| #1 | (Surger* OR operat* OR surgical procedure).mp |
| #2 | (DAH30 OR “days at home up to 30 days after surgery” OR “days alive and at home” OR “days at home” OR “postoperative 30 days”).mp |
| #3 | (#1 AND #2) |
| #4 | Limit #3 to humans |
| Web of Science | |
| #1 | (Surger* OR operat* OR surgical procedure).mp |
| #2 | (((DAH30 OR “days at home up to 30 days after surgery” OR “days alive and at home” OR “days at home*” OR postoperative 30 days) OR ((postoperative* OR preoperative* OR after surgery* OR after procedure*) “NEAR/3” (“days alive and at home” OR “days at home” OR DAH30))).mp |
| #3 | (#1 AND #2) |
| #4 | Limit #3 to humans |
| CINAHL | |
| #1 | (Surger* OR operat* OR surgical procedure).mp |
| #2 | (DAH30 OR “days at home up to 30 days after surgery” OR days alive and at home OR days at home* OR postoperative 30 days).mp |
| #3 | (#1 AND #2) |
| #4 | Limit #3 to humans |
References
- Quene, T.; Bust, L.; Louw, J.; Mwandri, M.; Chu, K.M. Global surgery is an essential component of global health. Surgeon 2022, 20, 9–15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meara, J.G.; Leather, A.J.M.; Hagander, L.; Alkire, B.C.; Alonso, N.; Ameh, E.A.; Bickler, S.W.; Conteh, L.; Dare, A.J.; Davies, J.; et al. Global Surgery 2030: Evidence and solutions for achieving health, welfare, and economic development. Lancet 2015, 386, 569–624. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weiser, T.G.; Haynes, A.B.; Molina, G.; Lipsitz, S.R.; Esquivel, M.M.; Uribe-Leitz, T.; Fu, R.; Azad, T.; Chao, T.E.; Berry, W.R.; et al. Estimate of the global volume of surgery in 2012: An assessment supporting improved health outcomes. Lancet 2015, 385, S11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Australian Institute of Health and Welfare. Hospitals at a Glance 2017–2018. 2019. Available online: https://www.aihw.gov.au/reports/hospitals/hospitals-at-a-glance-2017-18/contents/surgery-in-australia-s-hospitals (accessed on 15 December 2023).
- Etzioni, D.A.; Liu, J.H.; Maggard, M.A.; Ko, C.Y. The aging population and its impact on the surgery workforce. Ann. Surg. 2003, 238, 170–177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Birkmeyer, J.D.; Gust, C.; Dimick, J.B.; Birkmeyer, N.J.O.; Skinner, J.S. Hospital quality and the cost of inpatient surgery in the United States. Ann. Surg. 2012, 255, 1–5. [Google Scholar] [CrossRef] [Scilit]
- Billig, J.I.; Sears, E.D.; Travis, B.N.; Waljee, J.F. Patient-Reported Outcomes: Understanding Surgical Efficacy and Quality from the Patient’s Perspective. Ann. Surg. Oncol. 2020, 27, 56–64. [Google Scholar] [CrossRef] [Scilit]
- Tevis, S.E.; Kennedy, G.D. Postoperative complications and implications on patient-centered outcomes. J. Surg. Res. 2013, 181, 106–113. [Google Scholar] [CrossRef] [Scilit]
- Ferguson, M.; Kusre, S.; Myles, P. Minimal clinically important difference in days at home up to 30 days after surgery. Anaesthesia 2022, 77, 196–200. [Google Scholar] [CrossRef] [Scilit]
- Reilly, J.R.; Myles, P.S.; Wong, D.; Heritier, S.R.; Brown, W.A.; Richards, T.; Bell, M. Hospital costs and factors associated with days alive and at home after surgery (DAH(30)). Med. J. Aust. 2022, 217, 311–317. [Google Scholar] [CrossRef] [Scilit]
- Dellen, M.; Flanagan, M.; Pfafman, R.; Drouin, M.; Pater, J.; Pei, K.Y. Factors Potential Patients Deem Important for Decision-Making in High-Risk Surgical Scenarios. J. Am. Coll. Surg. 2023, 236, 93–98. [Google Scholar] [CrossRef]
- Gunaratnam, C.; Bernstein, M. Factors Affecting Surgical Decision-making-A Qualitative Study. Rambam Maimonides Med. J. 2018, 9, e0003. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moher, D.; Shamseer, L.; Clarke, M.; Ghersi, D.; Liberati, A.; Petticrew, M.; Shekelle, P.; Stewart, L.A. Preferred reporting items for systematic review and meta-analysis protocols (PRISMA-P) 2015 statement. Syst. Rev. 2015, 4, 1. [Google Scholar] [CrossRef] [PubMed]
- COVIDENCE. The World’s #1 Systematic Review Tool. 2024. Available online: https://www.covidence.org/ (accessed on 24 April 2024).
- Hayden, J.A.; van der Windt, D.A.; Cartwright, J.L.; Côté, P.; Bombardier, C. Assessing Bias in Studies of Prognostic Factors. Ann. Intern. Med. 2013, 158, 280–286. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fung, P.L.P.; Lau, V.N.M.; Ng, F.F.; Leung, W.W.; Mak, T.W.C.; Lee, A. Perioperative changes in haemoglobin and ferritin concentrations from preoperative intravenous iron isomaltoside for iron deficiency anaemia in patients with colorectal cancer: A pilot randomised controlled trial. PLoS ONE 2022, 17, e0270640. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jerath, A.; Austin, P.C.; Ko, D.T.; Wijeysundera, H.C.; Fremes, S.; McCormack, D.; Wijeysundera, D.N. Socioeconomic Status and Days Alive and Out of Hospital after Major Elective Noncardiac Surgery: A Population-based Cohort Study. Anesthesiology 2020, 132, 713–722. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jerath, A.; Austin, P.C.; McCormack, D.; Wijeysundera, D.N. Impact of postoperative intensive care unit utilization on postoperative outcomes in adults undergoing major elective noncardiac surgery. J. Clin. Anesth. 2020, 62, 109707. [Google Scholar] [CrossRef] [Scilit]
- Jerath, A.; Austin, P.; Wijeysundera, D.N. Days Alive and Out of Hospital: Validation of a Patient-centered Outcome for Perioperative Medicine. Anesthesiology 2019, 131, 84–93. [Google Scholar] [CrossRef] [Scilit]
- Bell, M.; Eriksson, L.I.; Svensson, T.; Hallqvist, L.; Granath, F.; Reilly, J.; Myles, P.S. Days at Home after Surgery: An Integrated and Efficient Outcome Measure for Clinical Trials and Quality Assurance. EClinicalMedicine 2019, 11, 18–26. [Google Scholar] [CrossRef] [Scilit]
- Jørgensen, C.C.; Petersen, P.B.; Kehlet, H.; Madsen, F.; Hansen, T.B.; Husted, H.; Laursen, M.; Hansen, L.T.; Kjærsgaard-Andersen, P.; Solgaard, S.; et al. Days alive and out of hospital after fast-track total hip and knee arthroplasty: An observational cohort study in 16 137 patients. Br. J. Anaesth. 2019, 123, 671–678. [Google Scholar] [CrossRef] [Scilit]
- McIsaac, D.I.; Fottinger, A.; Sucha, E.; McDonald, B. Association of frailty with days alive at home after cardiac surgery: A population-based cohort study. Br. J. Anaesth. 2021, 126, 1103–1110. [Google Scholar] [CrossRef] [Scilit]
- Miles, L.F.; Soo, V.P.; Braat, S.; Bade-Boon, J.; Heritier, S.; Klein, A.A.; Myles, P.S.; Richards, T.; Symons, J.; Burbury, K.L.; et al. Associations between non-anaemic iron deficiency and outcomes following elective cardiac surgery (IDOCS): A prospective cohort study. The Lancet. Haematology 2022, 9, e514–e522. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Myles, P.S.; Shulman, M.A.; Heritier, S.; Wallace, S.; McIlroy, D.R.; McCluskey, S.; Sillar, I.; Forbes, A. Validation of days at home as an outcome measure after surgery: A prospective cohort study in Australia. BMJ Open 2017, 7, e015828. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schick, V.; Boensch, M.; van Edig, M.; Alfitian, J.; Pola, T.; Ecker, H.; Lindacher, F.; Shah-Hosseini, K.; Wetsch, W.A.; Riedel, B.; et al. Impaired vascular endothelial function as a perioperative risk predictor—A prospective observational trial. BMC Anesthesiol. 2021, 21, 190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shaw, J.F.; Mulpuru, S.; Kendzerska, T.; Moloo, H.; Martel, G.; Eskander, A.; Lalu, M.M.; McIsaac, D.I. Association between frailty and patient outcomes after cancer surgery: A population-based cohort study. Br. J. Anaesth. 2022, 128, 457–464. [Google Scholar] [CrossRef] [Scilit]
- Wu, A.; Fahey, M.T.; Cui, D.; El-Behesy, B.; Story, D.A. An evaluation of the outcome metric ‘days alive and at home’ in older patients after hip fracture surgery. Anaesthesia 2022, 77, 901–909. [Google Scholar] [CrossRef] [Scilit]
- Plenge, U.; Parker, R.; Davids, S.; Davies, G.L.; Fullerton, Z.; Gray, L.; Groenewald, P.; Isaacs, R.; Kauta, N.; Louw, F.M.; et al. Quality of recovery after total hip and knee arthroplasty in South Africa: A national prospective observational cohort study. BMC Musculoskelet. Disord. 2020, 21, 721. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).