


Abstract
Inherited thrombophilias are a group of clinical conditions in which there is a genetic variant defect associated with a predisposition to thrombosis. Genetic testing for inherited thrombophilias has been used in the diagnosis of specific thrombophila at our centre for the last 20 years, this work will summarize our experience.
1. Introduction
Although inherited and acquired thrombophilias are known to increase the risk of thromboembolism, the majority of patients with thromboembolism should not be tested for thrombophilia [1]. The American College of Chest Physicians does not give guidance on thrombophilia testing in its ninth edition of clinical practice guidelines for antithrombotic therapy nor in its 2016 thromboembolism update [2,3], whereas the American Society of Hematology’s 2013 Choosing Wisely campaign recommends not testing for thrombophilia in adults with thromboembolism who have major transient risk factors [4].
Although guidelines advise limiting testing to a narrow range of specific clinical situations and patients, the recommendations are not uniform [5,6].
Factors associated with the presence of an inherited thrombophilia include thromboembolism at a young age, often considered to be less than 40 to 50 years of age; a strong family history of thromboembolism; thromboembolism in conjunction with weak provoking factors at a young age; recurrent thromboembolism events; and thromboembolism in an unusual site such as the central nervous system or splanchnic veins.
In patients with a first or subsequent thromboembolism before age of 50 years and a strong family history of thromboembolism, testing can be considered. The severity of the thromboembolism event can also be a factor in making decisions about testing [1].
The identification of several genetic defects has led to the concept of thrombosis as a multicausal disorder resulting from gene-gene and gene-environment interactions [7].
Genetic testing is available for some inherited thrombophilias and could potencially assist in the diagnosis and/or management of patients with thrombosis. Thrombophilia genetic tests includes: testing for factor V Leiden (FVL), prothrombin gene mutations (PGM), and mutations in the methylenetetrahydrofolate reductase (MTHFR) gene.
The purpose of this study is to outline the practical approach to genetic testing in Centro Hospitalar de São João, through a retrospective analysis conducted in all individuals tested in our centre for thrombophilia during a 20-years period (1998–2017).
2. Materials and Methods
The Molecular Biology Centre in Centro Hospitalar de São João (CHSJ) is responsible for studying human genetics related to thrombosis and haemostasis.
We conducted a retrospective study in all individuals tested in CHSJ for thrombophilia during a 20-years period, between 1998 and 2017.
Individuals with a history of thrombosis and family members of individuals with thrombophilia were studied. Studied individuals belonged both to CHSJ and to other health institutions.
Testing for FVL (G1819A), PGM (G2921A) and MTHFR gene mutation (C677T) were implemented in 1998 and MTHFR gene mutation (A1298C) in 2011 in CHSJ.
Genomic DNA was isolated from peripheral blood samples using the QIAsymphony equipment and QIAsymphony DNA Mini Kit (Qiagen®, Hilden, Germany). To determine the genotypes for the FVL (G1691A) and FII (G20210A), the Factor V Leiden and Factor II (Prothrombin) G20210A kits (Roche Molecular Systems, Mannheim, Germany) were used. The C677T and A1298C mutations of the MTHFR gene were evaluated with an in-house protocol using primers and hybridization probes adapted from Nicolas von Ahsen et al., and the DNA Master Hybridization Probes Kit (Roche Molecular Systems, Mannheim, Germany) on the LightCycler 2.0 equipment (Roche Molecular Systems, Mannheim, Germany).
Data was extracted from hospital databases SISLAB® and Sclinico®. Statistical analyses were performed with RStudio®.
3. Results
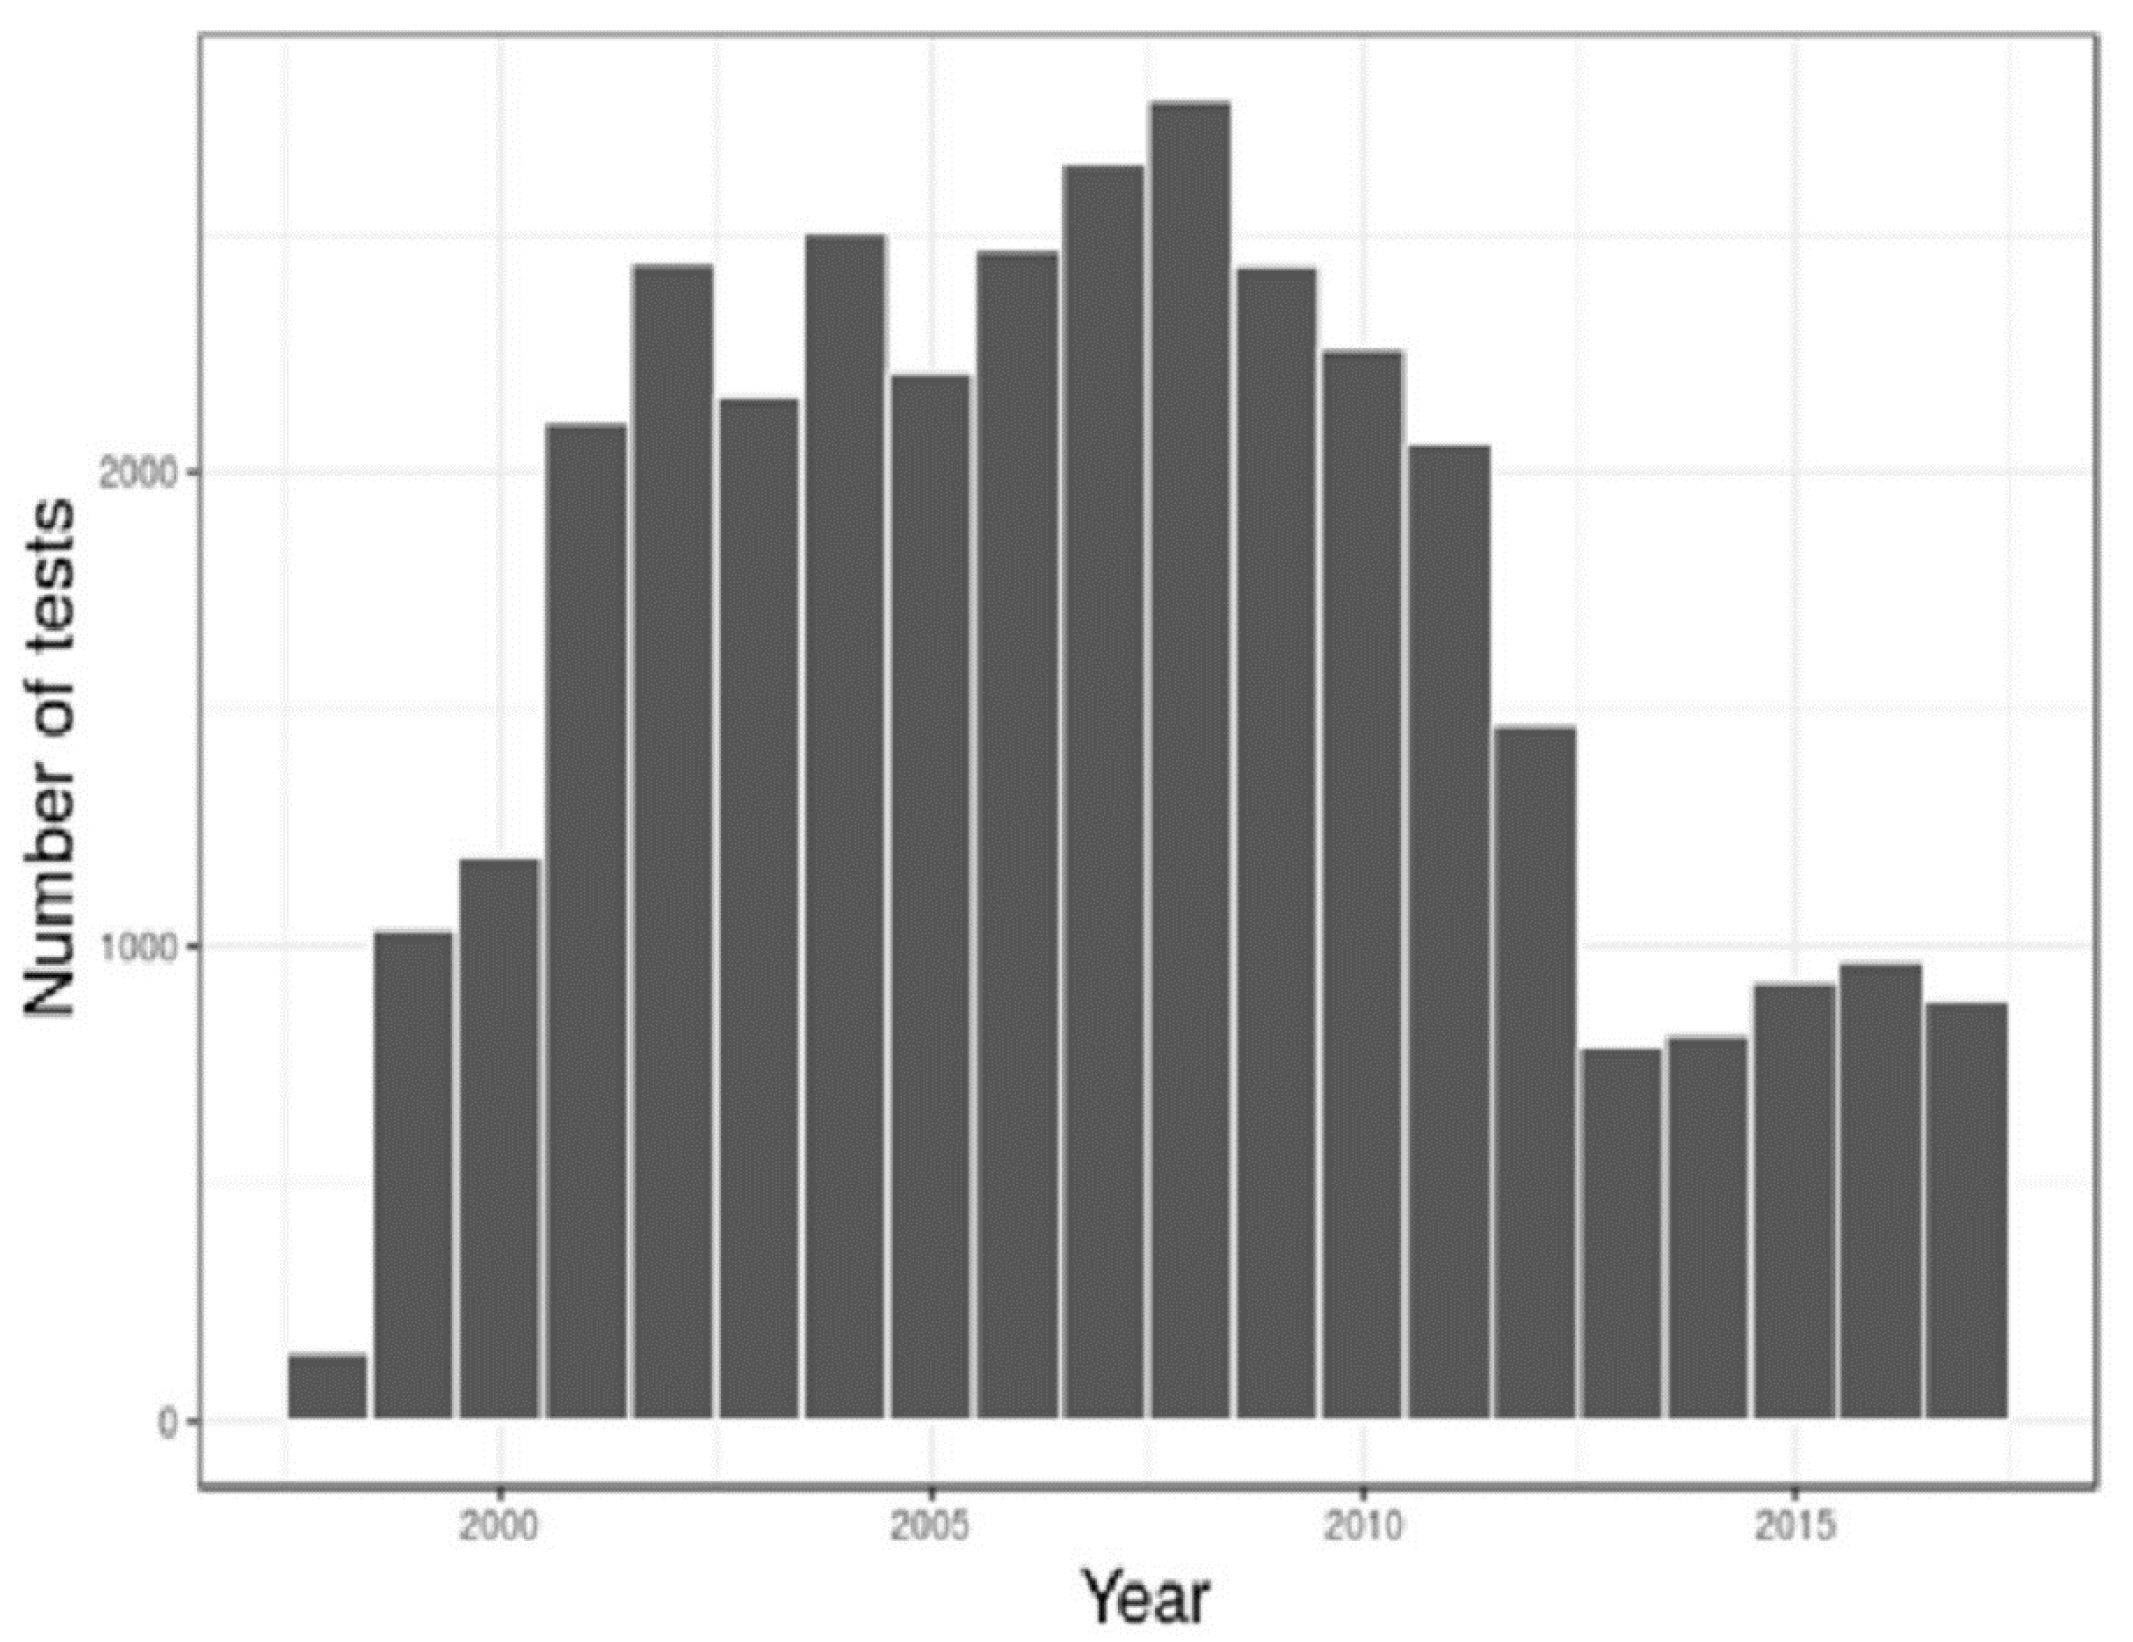
During the study period 34.341 tests were performed and 15.361 individuals underwent workup for genetic testing. Figure 1 shows the genetic tests performed at our centre in the study period.
Figure 1.
Genetic tests performed (1998–2017).
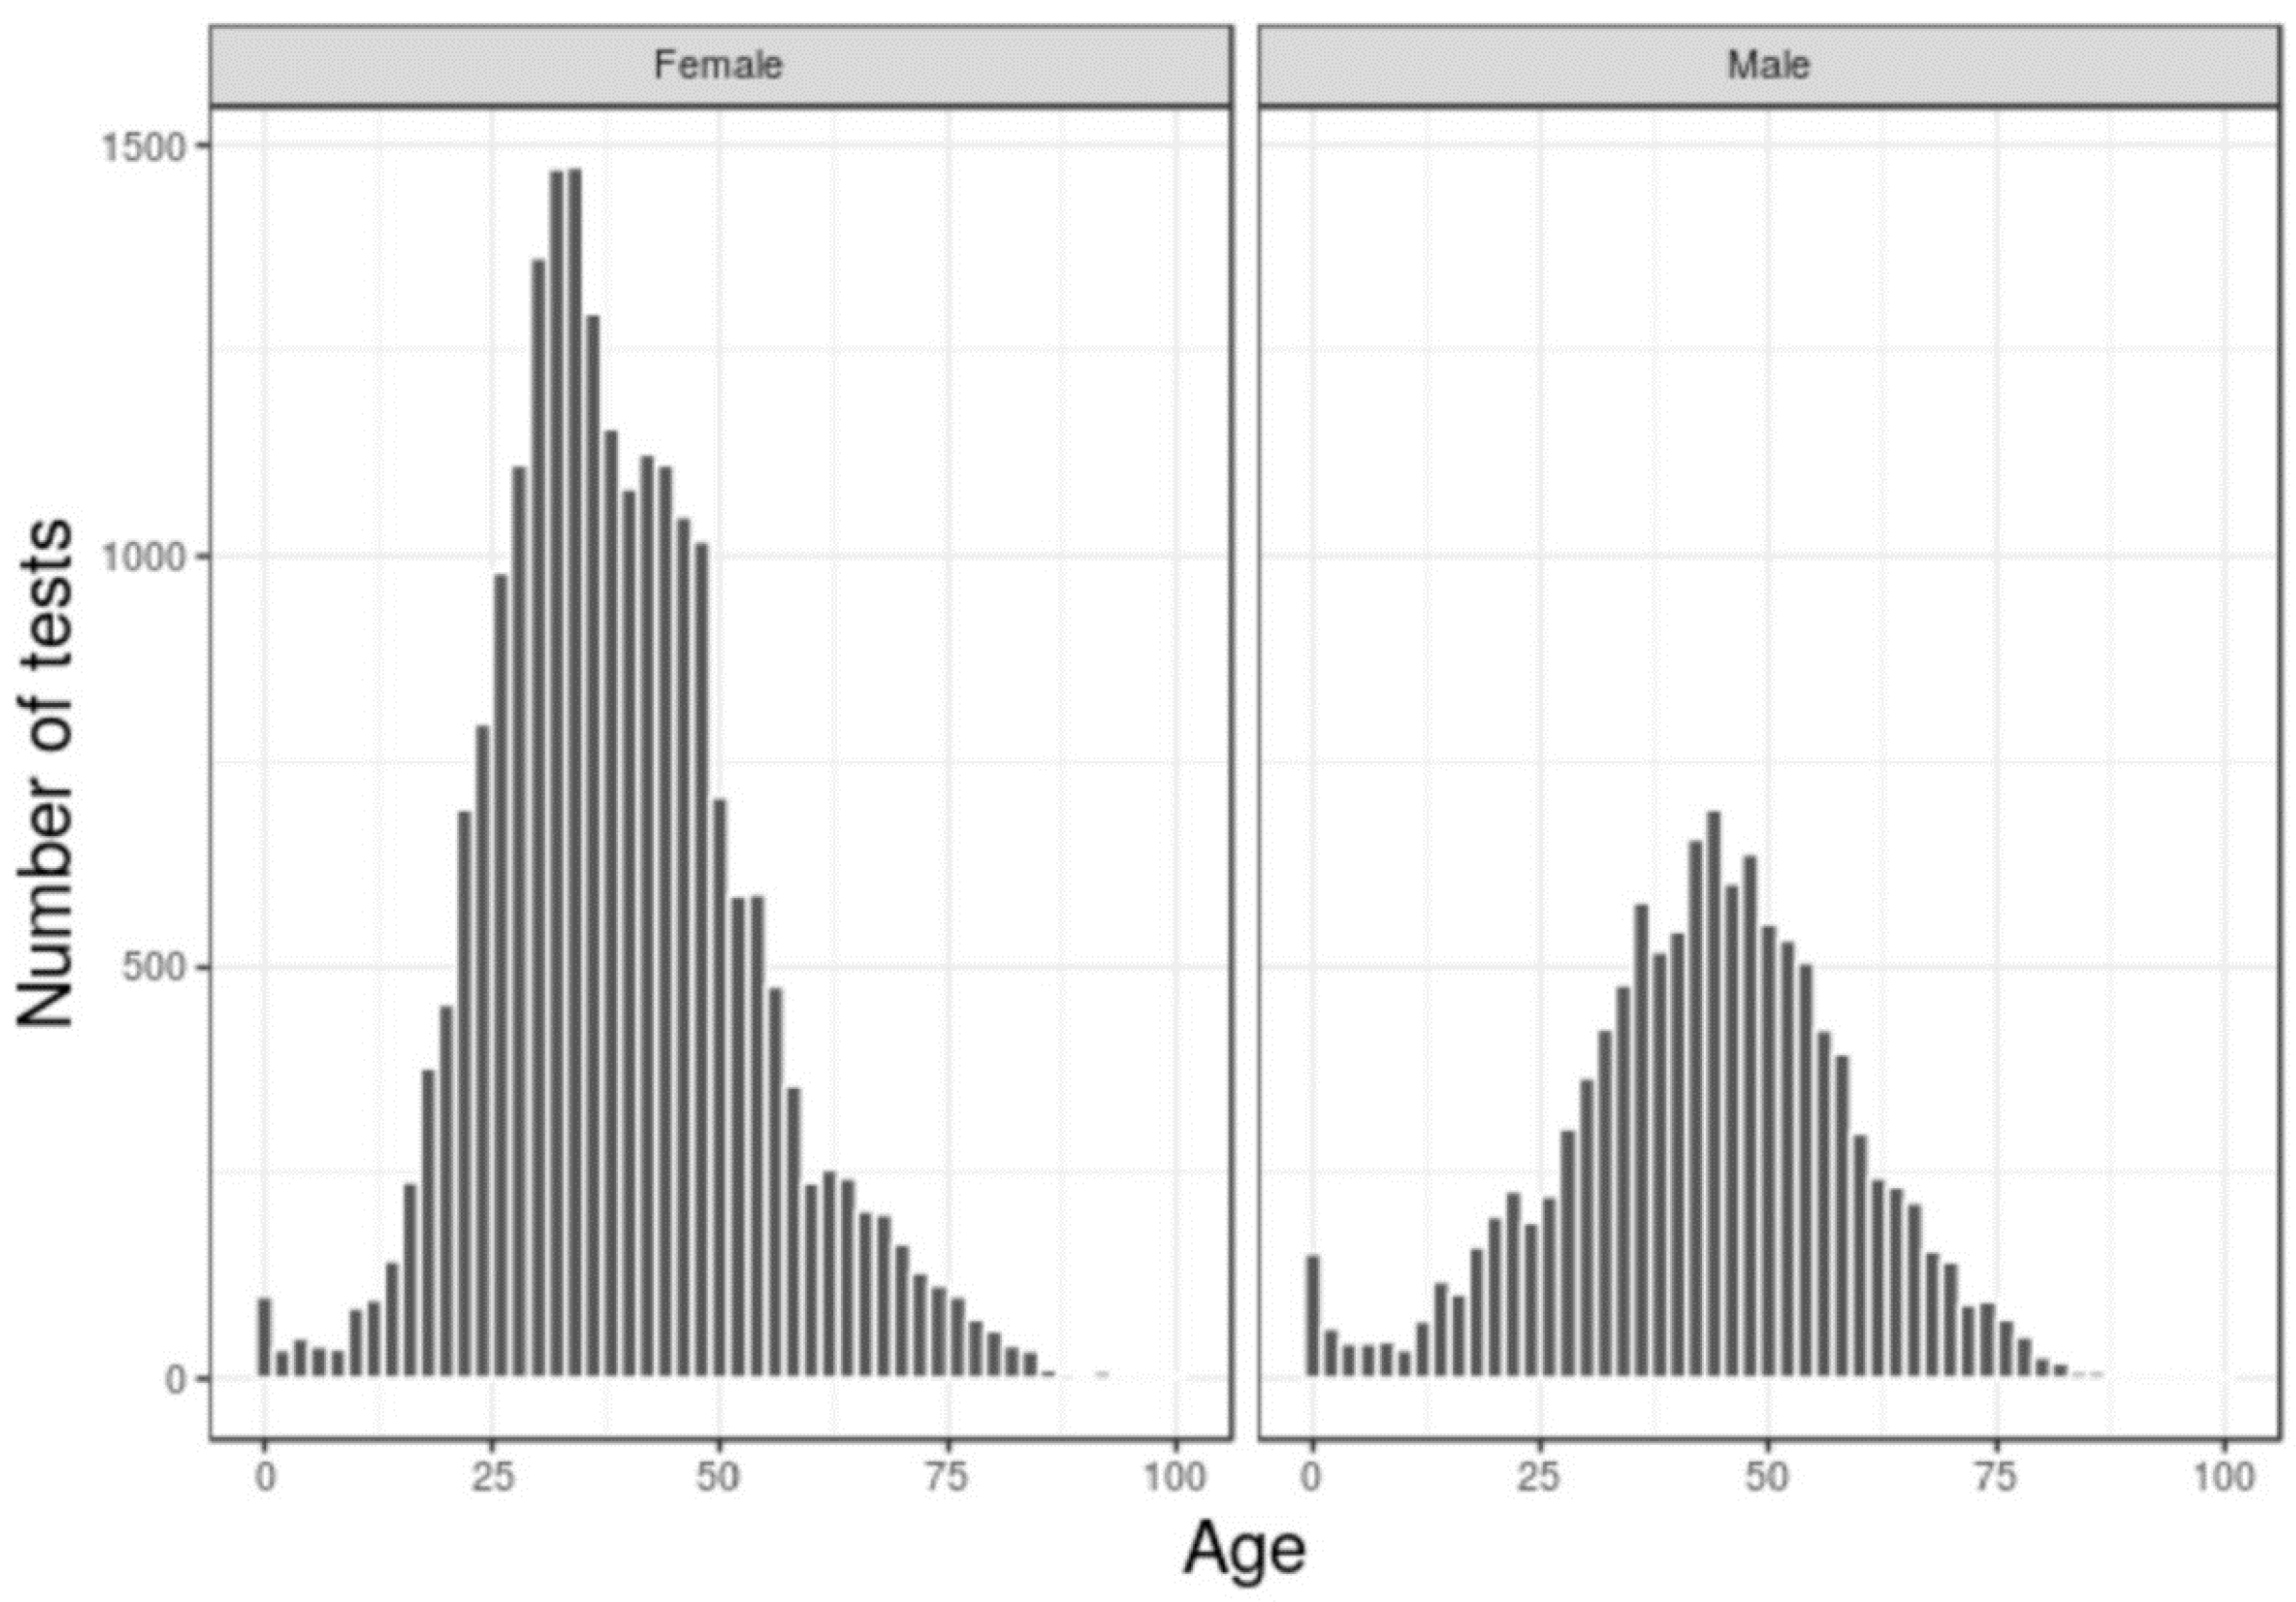
64.7% of the individuals tested were female. The mean age of the individuals was 41.1 years old, 39.7 in females and 43.6 years in males, as shown in Figure 2.
Figure 2.
Genetic tests performed by gender and age (1998–2017).
The mean number of tests performed by patient was 2.2. The overall rate of test positivity was 25.9%. The positivity for both mutations FVL and PGM was 13.2%. A summary of results of the genetic testing is provided in Table 1.
Table 1.
Genetic tests results (1998–2017).
4. Discussion
The positivity for FVL (12.5%) is higher than for PGM (6.1%), as expected, since the FVL is the most common type of inherited thrombophilia.
58.3% of tests for MTHFR gene mutations were positive. This can be explained because MTHFR polymorphisms (C6677T and A1298C) are known to be present in up to 45% of the population and are considered a weak risk factor for thrombosis [1]. CHSJ does not recommend routine testing for MTHFR mutations since 2013.
The genetic testing for thrombophilia has been decreasing in our centre, which was expected since several clinical guidelines do not recommend testing for thrombophilia in adults with thrombosis with major transient risk factors.
Genetic testing for thrombophilia has been available in our centre for the last 20 years and are still being used for the diagnosis and management of individuals with thrombosis and family members of individuals with thrombophilia.
5. Conclusions
This review was useful for evaluating testing practices for individuals with thromboembolism at our centre. Although testing for inherited thrombophilia is controversial, and should not be performed routinely, thrombophilia status is often useful in making decisions about secondary prophylaxis after a first provoked thromboembolism, or about primary prophylaxis in positive family members at time of increased risk.
Departments which perform genetic testing for inherited thrombophilia should select individuals for genetic testing and should help other clinical physicians understanding the utility and limitations of these tests, to provide the best possible care for patients with thromboembolism.
Author Contributions
C.V. and C.K. conceived and designed the experiments and wrote de paper; F.B. and F.V. analyzed the data; F.M. and M.L. conceived and designed the experiments; P.B., G.T., A.A. and M.F. performed the tests.
Acknowledgments
The authors declare no acknowledgments.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Jean Connors, J.C. Thrombophilia Testing and Venous Thrombosis. N. Engl. J. Med. 2017, 377, 1177–1187. [Google Scholar] [CrossRef] [Scilit]
- Kearon, K.C.; Aki, E.A.; Comerota, A.J. Antithrombotic therapy for VTE disease: Antithrombotic therapy and prevention of thrombosis, 9th ed: American College of Chest Physicians evidence-based clinical practice guidelines. Chest 2012, 141, e419S–e494S. [Google Scholar] [CrossRef] [Scilit]
- Kearon, K.C.; Aki, E.A.; Ornelas, J. Antithrombotic therapy for VTE disease: CHEST guideline and expert panel report. Chest 2016, 149, 315–352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hicks, L.K.; Bering, H.; Carson, K.R. The ASH Choosing Wisely campaign: Five hematologic tests and treatments to question. Blood 2013, 122, 3879–3883. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Venous Thromboembolic Diseases: The Management of Venous Thromboembolic Diseases and the Role of Thrombophilia Testing; National Clinical Guideline Centre, Royal College of Physicians: London, UK, 2012.
- Stevens, S.M.; Woller, S.C.; Bauer, K.A. Guidance for the evaluation and treatment of hereditary and acquired thrombophilia. J. Thromb. Thrombolysis 2016, 41, 154–164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mark, S.H. Genetic Testing for Thrombophilia Mutations. Semin. Thromb. Hemost. 2005, 31, 33–38. [Google Scholar]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2018 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).