1. Introduction
Allergic Contact Dermatitis (ACD) is a common inflammatory skin disease, affecting approximately 20% of the general population (overall prevalence 20.1%, 95% CI: 16.8–23.7%) and is a major problem in both clinical and occupational dermatology [
1]. Early and accurate identification of the responsible allergens is crucial for effective disease treatment and relapse prevention. Patch tests are still considered the “gold standard” for ACD diagnosis, with reactions’ evaluation being carried out according to the International Contact Dermatitis Research Group (ICDRG) system, which is based on a four-point visual scale, ranging from negative (−) to strongly positive (+++) reaction [
2].
Although the ICDRG scoring is widely used, it is based solely on the visual assessment of the examiner, which makes it quite subjective. Therefore, some degree of variation in expert judgments is to be expected. Differences have been observed in the way ICDRG criteria are applied [
2], while several reports showed that there is also a significant discrepancy in the interpretation of patch tests, with an error rate of up to 24.6% in final assessments [
3].
This issue becomes even more apparent in borderline cases, such as when it is essential to distinguish between a doubtful (?+) and a weakly positive (+) reaction. In these cases, uncertainty can directly affect the clinical decision. In case of inaccurate assessments the risk for false negatives or false positives increase. For example, false negative assessments could result to probable patient’s continuous exposure to potential allergens, or conversely, in case of false positives unnecessary avoidance instructions could be consulted and unnecessary burden on the patient’s daily life could be caused.
In recent years, there has been increasing interest in how artificial intelligence (AI) can be used for patch testing interpretation. Most studies report on convolutional neural networks (CNNs), which are applied either to clinical images or to processed color maps [
4]. In some cases, data such as hemoglobin and texture maps from the Antera 3D imaging system are used [
5], while other studies manifested good results even with simple clinical photographs [
6]. It also appears that CNNs can contribute to the classification of reactions in patch tests [
7]. However, although these results are encouraging, in most cases it is not easy to understand exactly how these models lead to automated decision-making. This makes their utilization difficult in a daily clinical practice, where concise interpretation of clinical outcomes is of major importance. Furthermore, the connection between imaging data and actual clinical significance is not always straight forward and often needs further confirmation or clarification.
In the present study, we propose a different approach, based not only on the health professional’s evaluation, but also on actual imaging data. More specifically, we utilized structured biomedical engineering features derived from the 3D multispectral imaging system Antera 3D. This system provides quantitative and reliable measurements of various skin properties, such as color (CIELAB) (CIELAB is derived from CIE L*A*B* = “colour space, which expresses color as three numerical values, L* for the lightness and a* and b* for the green–red and blue-yellow color components”), indices related to hemoglobin, surface roughness, but also volume, fluorescence and texture. This information is directly linked to clinically important elements, such as erythema, infiltration and surface morphology, and thus could potentially lead to improved skin reactions’ evaluation.
Thus, our approach included the transformation of imaging data to structured data tables, which could subsequently be used for further analysis, as for example in the present case, machine learning models, or standard statistical analysis. The proposed streamline, is easier to understand, can be consistently reproduced and, most importantly, could potentially be used in clinical practice.
Within this context, our study attempted to address some key questions; first, whether structured biomedical features can be used for a more objective patch-testing reactions classification. Second, we tried to address whether changes observed between 48 and 72 h affect diagnostic accuracy. Third, we investigated whether there is a correlation between specific allergens and the anatomical sites of previously diagnosed dermatitis. Finally, we investigated whether our results could be interpreted in such a way that could have critical meaning for clinical practice.
Overall, the present study aims at investigating if potential quantitative and more “transparent” measurements can function as a reliable, complement to traditional, more subjective diagnostic assessment.
2. Materials and Methods
2.1. Study Design and Data Collection
2.1.1. Study Population
Details of the present study cohort have been previously reported, along with the followed methodology [
5,
8,
9,
10]. In short, the present study was designed as a prospective cohort study, including patients undergoing routine epicutaneous patch testing at the Laboratory of Patch Testing, National Referral Centre of Occupational Dermatoses, “Andreas Syggros” Hospital, National and Kapodistrian University of Athens, Greece.
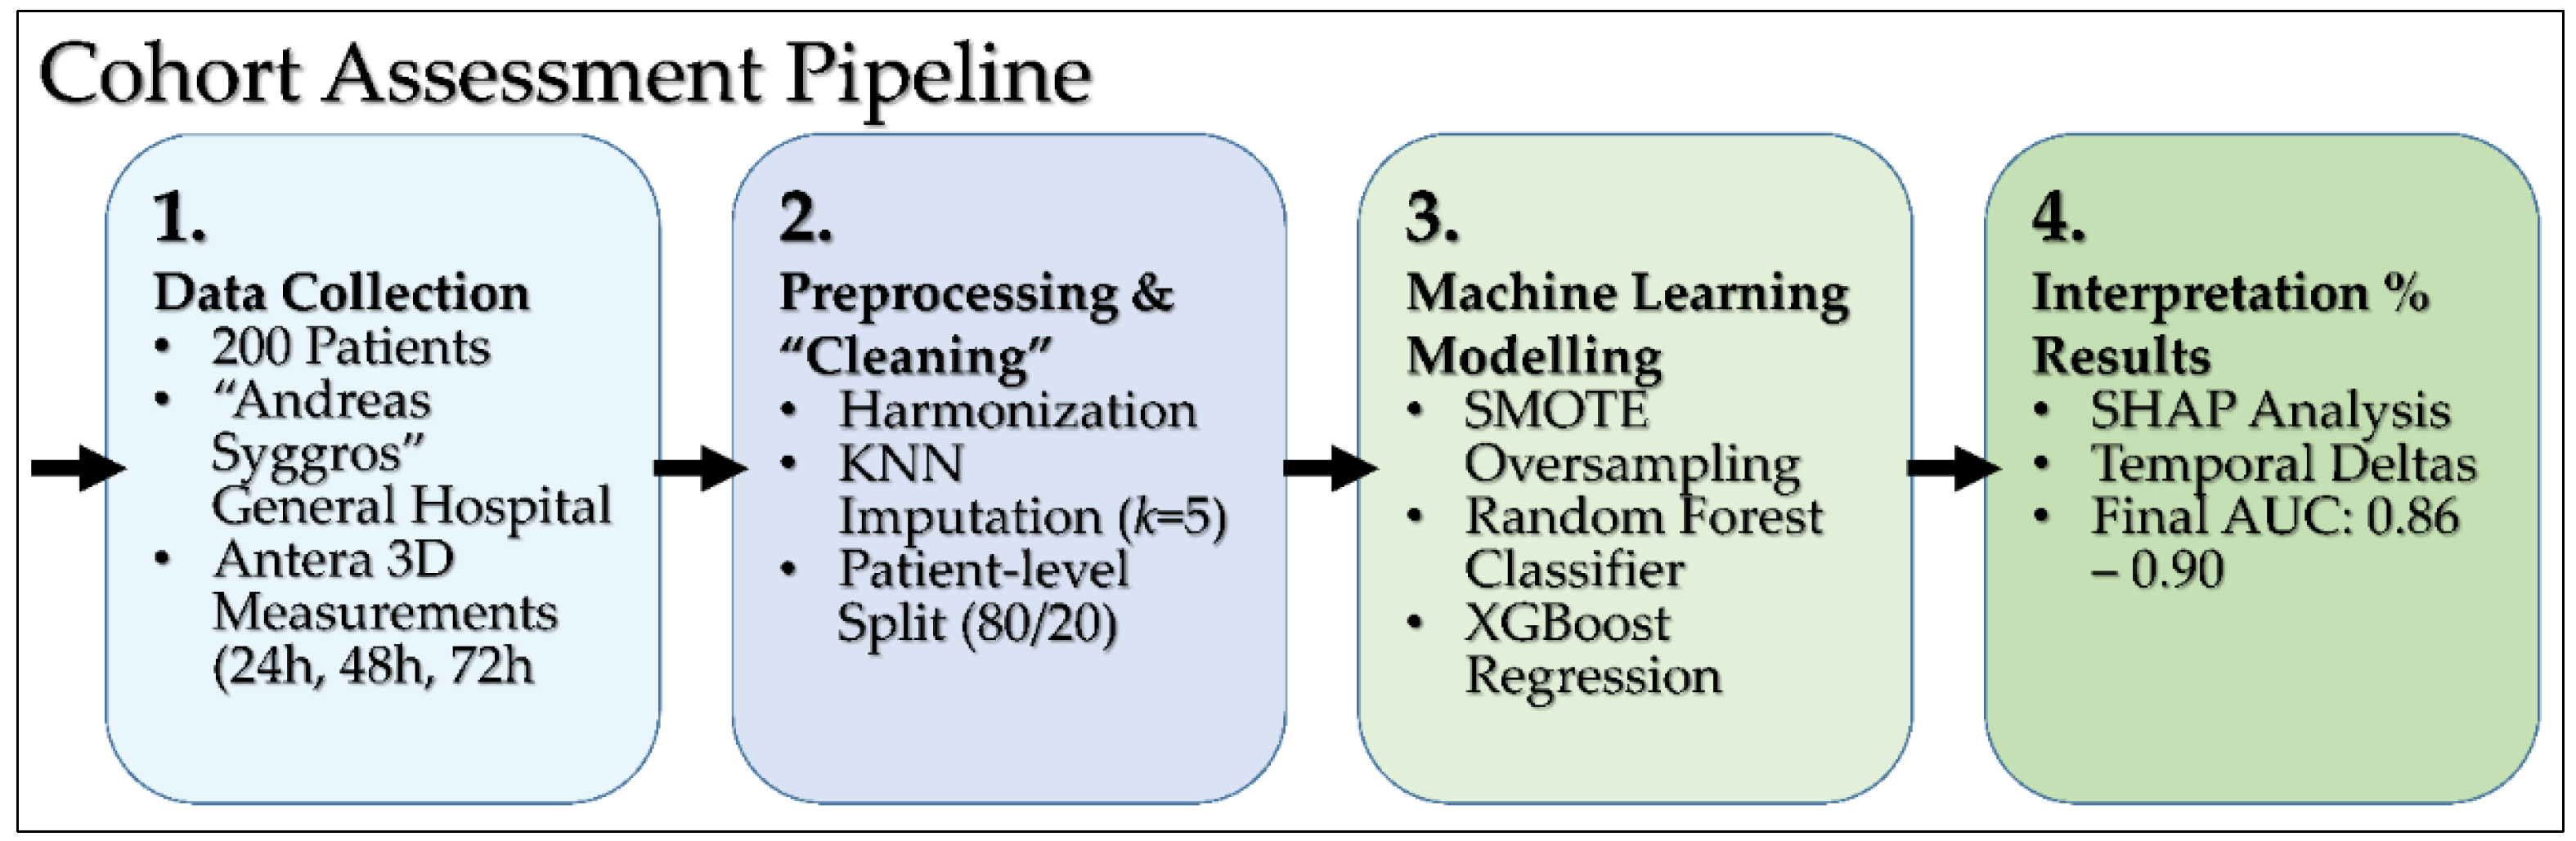
Epicutaneous patch testing constitutes the gold standard diagnostic approach for the identification of causative allergens in allergic contact dermatitis (ACD), enabling controlled allergen exposure and standardized clinical assessment of delayed hypersensitivity reactions. A total of 200 patients with clinical suspicion of ACD were initially enrolled during the study period. Following data quality assessment, 194 patients met the criteria for completeness of the Antera 3D (Miravex Ltd., Dublin, Ireland) measurements and were included in the final machine-learning pipeline, yielding 4477 observations. The remaining six patients were excluded because of incomplete Antera 3D measurements, such as image acquisition failure at critical time points or technical camera-related issues. These exclusions were technical in nature and were not related to patients’ clinical characteristics. Patients were consecutively recruited from those referred during the study period.
2.1.2. Inclusion and Exclusion Criteria
Patients were admitted to the Laboratory of Patch Testing, National Referral Centre of Occupational Dermatoses, and were evaluated for suspected contact dermatitis [
11,
12]. In case of factors that could influence skin reactions interpretation, patients were excluded. In particular, patients were excluded if they were under: systemic immunosuppressive therapy [
13], chronic corticosteroids [
14], or anti-inflammatory therapy [
15]. In addition, subjects with chronic dermatological diseases [
14] and those with recent severe UV exposure [
16] were also excluded. Patients for which data collected with the Antera 3D system were either incomplete or missing were also excluded.
2.1.3. Patch Testing Protocol
The European Baseline Series includes several allergen categories, such as metals, fragrances, preservatives, rubber materials, topical medications, and other ingredients associated with allergic contact dermatitis [
8,
9,
10,
17]. Patch tests were performed with a standardized panel, which includes approximately 30 of the most common allergens, such as metals, preservatives, fragrances, and acrylics. Allergens were applied to the upper back with standard patches and left on for 48 h. Assessments were made at 48 and 72 h after application. Final assessment was performed at 72 h.
2.1.4. ICDRG System
Skin reactions were independently scored by experienced health professionals according to the ICDRG guidelines. Scoring was based on features such as erythema, infiltration, papules and vesicles, on a scale from negative (0) to strongly positive (+++). Although widely used, this method remains somewhat subjective, especially in borderline cases. For the purpose of analysis, results were summarized into two categories: reactions with a score of ≥1 were considered positive, while those with a score of 0 were considered negative.
2.1.5. Antera 3D Imaging and Bioengineering Features
Quantitative assessment of skin reactions was performed using the Antera 3D imaging system (Miravex Ltd., Dublin, Ireland), which allows for the three-dimensional imaging of skin and the measurement of parameters such as hemoglobin and melanin. Parameter sampling was performed with Antera 3D software (Miravex Ltd., Dublin, Ireland, version 1.0). Measurements were performed at three time points (24, 48, and 72 h) to monitor the progression of skin reaction over time. A total of 41 biomedical features were extracted, which were divided into six main categories: color parameters (CIELAB: L*, a*, b*, and ITA), hemoglobin-related indices for assessing erythema, roughness measurements describing skin texture, volumetric features related to papule elevation, fluorescence features, and indices describing skin folds and structural changes (
Table 1). These characteristics are linked to key clinical features, such as the severity of erythema, infiltration and changes in skin appearance. At the same time, demographic and anthropometric patient data, such as age, gender, smoking, allergen, site of occurrence and relevant history, were also collected.
2.1.6. Ethics Statement
The present study was approved by the Institutional Scientific Review Board of the University Hospital “Andreas Syggros”, National and Kapodistrian University of Athens, Medical School (Protocol. Nr. 2851/2018), and the ethical considerations were fully consistent with the Declaration of Helsinki (1975, review 2000). The data were kept anonymously, and there is no way to track back to the patient’s personal data. Prior to inclusion, all participants provided written informed consent.
2.2. Data Preprocessing and Feature Engineering
Clinical, biomedical, photonics and patient data were merged into a single data matrix. Missing values in continuous variables were handled using k-nearest neighbors (KNN) imputation with k = 5 and distance-based weighting. This method preserves relationships between data and avoids errors that can arise from simpler techniques.
Some basic corrections were also made to make the data more consistent. For example, when volumetric measurements were zero, the corresponding height values were also set to zero to be logically consistent. Categorical variables were converted to binary (0, 1) when necessary. In addition, occupational risk was categorized and some clinical variables were adjusted so that they could be used correctly in machine learning models.
2.3. Dataset Structure and Splitting Strategy
The final dataset included 4477 observations from 194 patients, as each patient contributed multiple measurements across different allergens and time points. To avoid information leakage arising from repeated measurements from the same individual, all data partitions were performed at the patient level. The dataset was initially divided into training (80%) and test (20%) sets using grouped splitting, ensuring that all observations from a given patient were assigned exclusively to one of the two sets. This resulted in approximately 3494 observations from 155 patients in the training set and 983 observations from 39 patients in the independent test set. Consequently, model performance was assessed on patients not encountered during model development.
Within the training set, model performance was evaluated using 5-fold cross-validation, again at the patient level. All observations from the same patient were assigned to the same fold, preventing overlap between training and validation subsets. The validation folds were of comparable size, containing 31, 31, 31, 32 and 30 patients, respectively (approximately 700 observations each), which together account for all 155 training patients. The independent test set (39 patients; 983 observations) was held out completely and did not participate in the cross-validation procedure. Cross-validation performance metrics are reported as the mean and standard deviation across the five validation folds.
To further minimise the risk of data leakage, variables directly derived from the outcome labels were excluded before model training. In addition, all preprocessing steps that learned from the data, including KNN imputation, feature scaling where applicable, and SMOTE oversampling, were incorporated within the modelling pipeline and fitted exclusively on the training folds before being applied to the corresponding validation data.
2.4. Synthetic Minority Over-Sampling Technique (SMOTE)-Based Class Imbalance Mitigation
The data was unbalanced, with fewer positive responses than negative ones. To correct this, we used the SMOTE method on the training data, which creates new similar samples for the less frequent category. In the training set, this corresponded to 600 positive (17.2%) and 2894 negative (82.8%) observations before resampling; after SMOTE, the minority class was oversampled to 2894 positive and 2894 negative observations (5788 in total). This procedure was only applied to the training set, in order to leave unaffected the overall evaluation. Where possible, we adjusted the category weights in training.
2.5. Machine Learning Models
All machine-learning analyses were implemented using Python version 3.14.0. Data preprocessing and management were performed using pandas version 3.0.0 and NumPy version 2.4.2. Machine-learning models and evaluation were implemented using scikit-learn version 1.8.0, while SMOTE-based resampling was performed using imbalanced-learn version 0.14.1. The multi-layer perceptron (MLP) was implemented using PyTorch version 2.10.0, gradient boosting was performed using XGBoost version 3.2.0, and model interpretability was conducted using SHAP version 0.50.0.
Random Forest was used as the main model, because it can handle different types of data and capture more complex relationships without “learning by heart”. Other models were also tested for comparison, such as logistic regression and a neural network (Multi-Layer Perceptron (MLP)). At the same time, the intensity of the reaction was examined with XGBoost, in order to obtain a more accurate evaluation of the severity on the ICDRG scale. Especially, the MLP utilization included the following features: Architecture: (a) Three fully connected hidden layers with a pyramidal width of 128, 64, and 32 neurons, (b) Each hidden block consisted of Linear, BatchNorm1d, GELU activation, and Dropout (
p = 0.3), (c) the output is a single linear unit returning a logit, paired with BCEWithLogitsLoss and a pos_weight term to compensate for class imbalance (no terminal sigmoid, for numerical stability) and (d) Input dimensionality is approximately 50 bioengineering features. Training configuration: (a) Optimizer: AdamW (learning rate 1 × 10
−3, weight decay 1 × 10
−4) with ReduceLROnPlateau (factor 0.5, patience 10, min_lr 1 × 10
−6, (b) Batch size 64, maximum 200 epochs, early stopping with patience of 25 epochs on validation loss, and gradient clipping at max_norm = 1.0 and (c) Patient-level GroupShuffleSplit (80/20) for train/test and patient-level GroupKFold (k = 5) for cross-validation, with SMOTE and StandardScaler fitted only on the training fold to prevent leakage. The reported test prediction is the ensemble average across the five fold models (random seed = 42). Design rationale: BatchNorm stabilizes training and reduces sensitivity to learning-rate selection, Dropout 0.3 prevents co-adaptation of neurons on a dataset of moderate size (
n approximately 4500 observations from 194 patients), and GELU was chosen for its smoother gradient behavior than ReLU on small networks [
18]. AdamW was preferred over Adam because of its decoupled weight decay, which is better behaved as an L2 regulariser.
Hyperparameter selection differed according to model complexity. For the KNN baseline, hyperparameters were optimised using GridSearchCV under patient-level GroupKFold cross-validation. In contrast, the Random Forest parameters (n_estimators = 200, max_depth = 10, and class_weight = “balanced”) and the MLP architecture were predefined based on commonly used configurations for tabular medical datasets of comparable size.
2.6. Temporal Feature Engineering
In order to examine how skin reactions evolve over time, features (temporal delta) that record changes between measurements’ intervals were utilized. For each bioengineering feature, the difference between 72 h and 48 h measurements was calculated as:
These characteristics show how quickly and towards which direction inflammation changes. In other words, allergic reactions usually increase over time, while irritant reactions tend to decrease. This way, the model can more easily distinguish between these two cases.
2.7. Model Interpretability
Model interpretation was performed using the SHapley Additive exPlanations (SHAP) method, which detects the contribution of each feature to the predictions. For all tree models, the TreeExplainer algorithm was used, which allows for fast and reliable calculation of these contributions. The analysis was performed on the independent test set, so that the results reflect the behavior of the model on new data and not on the training data. That way, predictions can be interpreted based on clinically important features, enhancing transparency and facilitating their use in practice.
2.8. Statistical Analysis
Model performance for binary classification was mainly evaluated using the Area Under the Curve (AUC) methodology. At the same time, other metrics were calculated, such as sensitivity, specificity, positive and negative predictive value (PPV, NPV), F1-score and confusion matrices, so that the evaluation is closer to clinical practice.
Root Mean Square Error (RMSE) and the coefficient of determination (
R2) were used to estimate the severity. All metrics were calculated with bootstrap (2000 repetitions). To ensure reproducibility, a fixed random value (random_state = 42) was used in the primary analyses, including data partitioning, balancing, and model training. The entire process was performed in a repeatable manner so that the same steps were applied each time (
Figure 1). In addition, a sensitivity analysis using multiple random seeds (42–51) was conducted to assess the stability of the Random Forest model, and the corresponding results are presented in
Supplementary Table S1.
Statistical analyses were performed using SciPy version 1.17.0 and statsmodels version 0.14.6.
4. Discussion
The present study demonstrates that quantitative features derived from the Antera 3D system can be used as inputs for machine-learning models for patch-test assessment. Model performance was satisfactory (AUC = 0.8611) and comparable to previously reported AI-based approaches for patch-test assessment [
5,
6]. Recent AI-based studies have mainly focused on the analysis of patch-test images using deep-learning models [
4,
5,
6]. In the present study, an alternative methodological approach was adopted by using quantitative measurements derived from Antera 3D imaging as model inputs. The methodology combines quantitative skin features with patient-level validation, temporal Δ-features describing the evolution of skin reactions between 48 and 72 h, SHAP-based model interpretation, and robustness analyses for class-imbalance handling. This approach extends previous image-based studies through the integration of quantitative skin measurements, temporal information, and interpretable machine-learning methods, supporting the use of quantitative imaging data in patch-test assessment. At the same time, comparisons with other AI-based studies in dermatology should be interpreted with caution. Most of these studies have focused on image classification tasks using convolutional neural networks and have been developed using different patient populations, outcome definitions, and validation strategies [
6]. In contrast, the present study addressed the evaluation of patch test reactions using quantitative features derived from Antera 3D imaging. Although image-based approaches may identify complex visual patterns, the use of measurable biophysical parameters provides a clearer understanding of how predictions are generated. Therefore, these approaches should be viewed as complementary rather than directly comparable.
A detailed comparison between the present study and recently published AI-based approaches is provided in
Supplementary Table S6. Among the recently published AI studies, Vezakis et al. [
5] were the first to evaluate deep learning using multimodal Antera 3D images, demonstrating that combining complementary imaging modalities and context-retaining preprocessing improved automated patch-test classification. Ravishankar et al. [
19] subsequently demonstrated that a convolutional neural network trained on conventional clinical photographs could accurately discriminate reactive from non-reactive patch-test sites (AUC = 0.940; accuracy = 90.1%). More recently, Kim et al. [
20] reported an accuracy of 98.3% using a YOLOv5x object-detection framework trained on a substantially larger dataset of standardized patch-test photographs. Although these studies differ in network architecture and image acquisition protocols, they share a common image-based deep-learning framework that provides limited insight into the quantitative factors contributing to model predictions.
Unlike these image-based approaches, the present study utilized quantitative bioengineering measurements derived from Antera 3D imaging rather than raw images. This enabled direct modelling of clinically relevant parameters describing erythema, haemoglobin distribution and skin morphology, while also allowing incorporation of temporal changes between the 48-h and 72-h patch-test readings. Furthermore, SHAP analysis identified the quantitative variables contributing most strongly to model predictions, providing a level of interpretability that is not inherently available in conventional convolutional neural network models.
The recent review by Burli et al. [
21] highlighted the diagnostic challenges of patch testing in patients with skin of colour and emphasised the need for more objective assessment methods. Similarly, the systematic review by Al-tharwane and Al Abadie [
22] concluded that although AI-assisted patch testing consistently demonstrates promising diagnostic performance, future research should prioritise external validation, methodological standardisation and explainable AI. The methodology adopted in the present study addresses several of these recommendations by incorporating quantitative imaging biomarkers, patient-level validation, leakage-controlled model development, and explainable machine learning within a clinically interpretable framework.
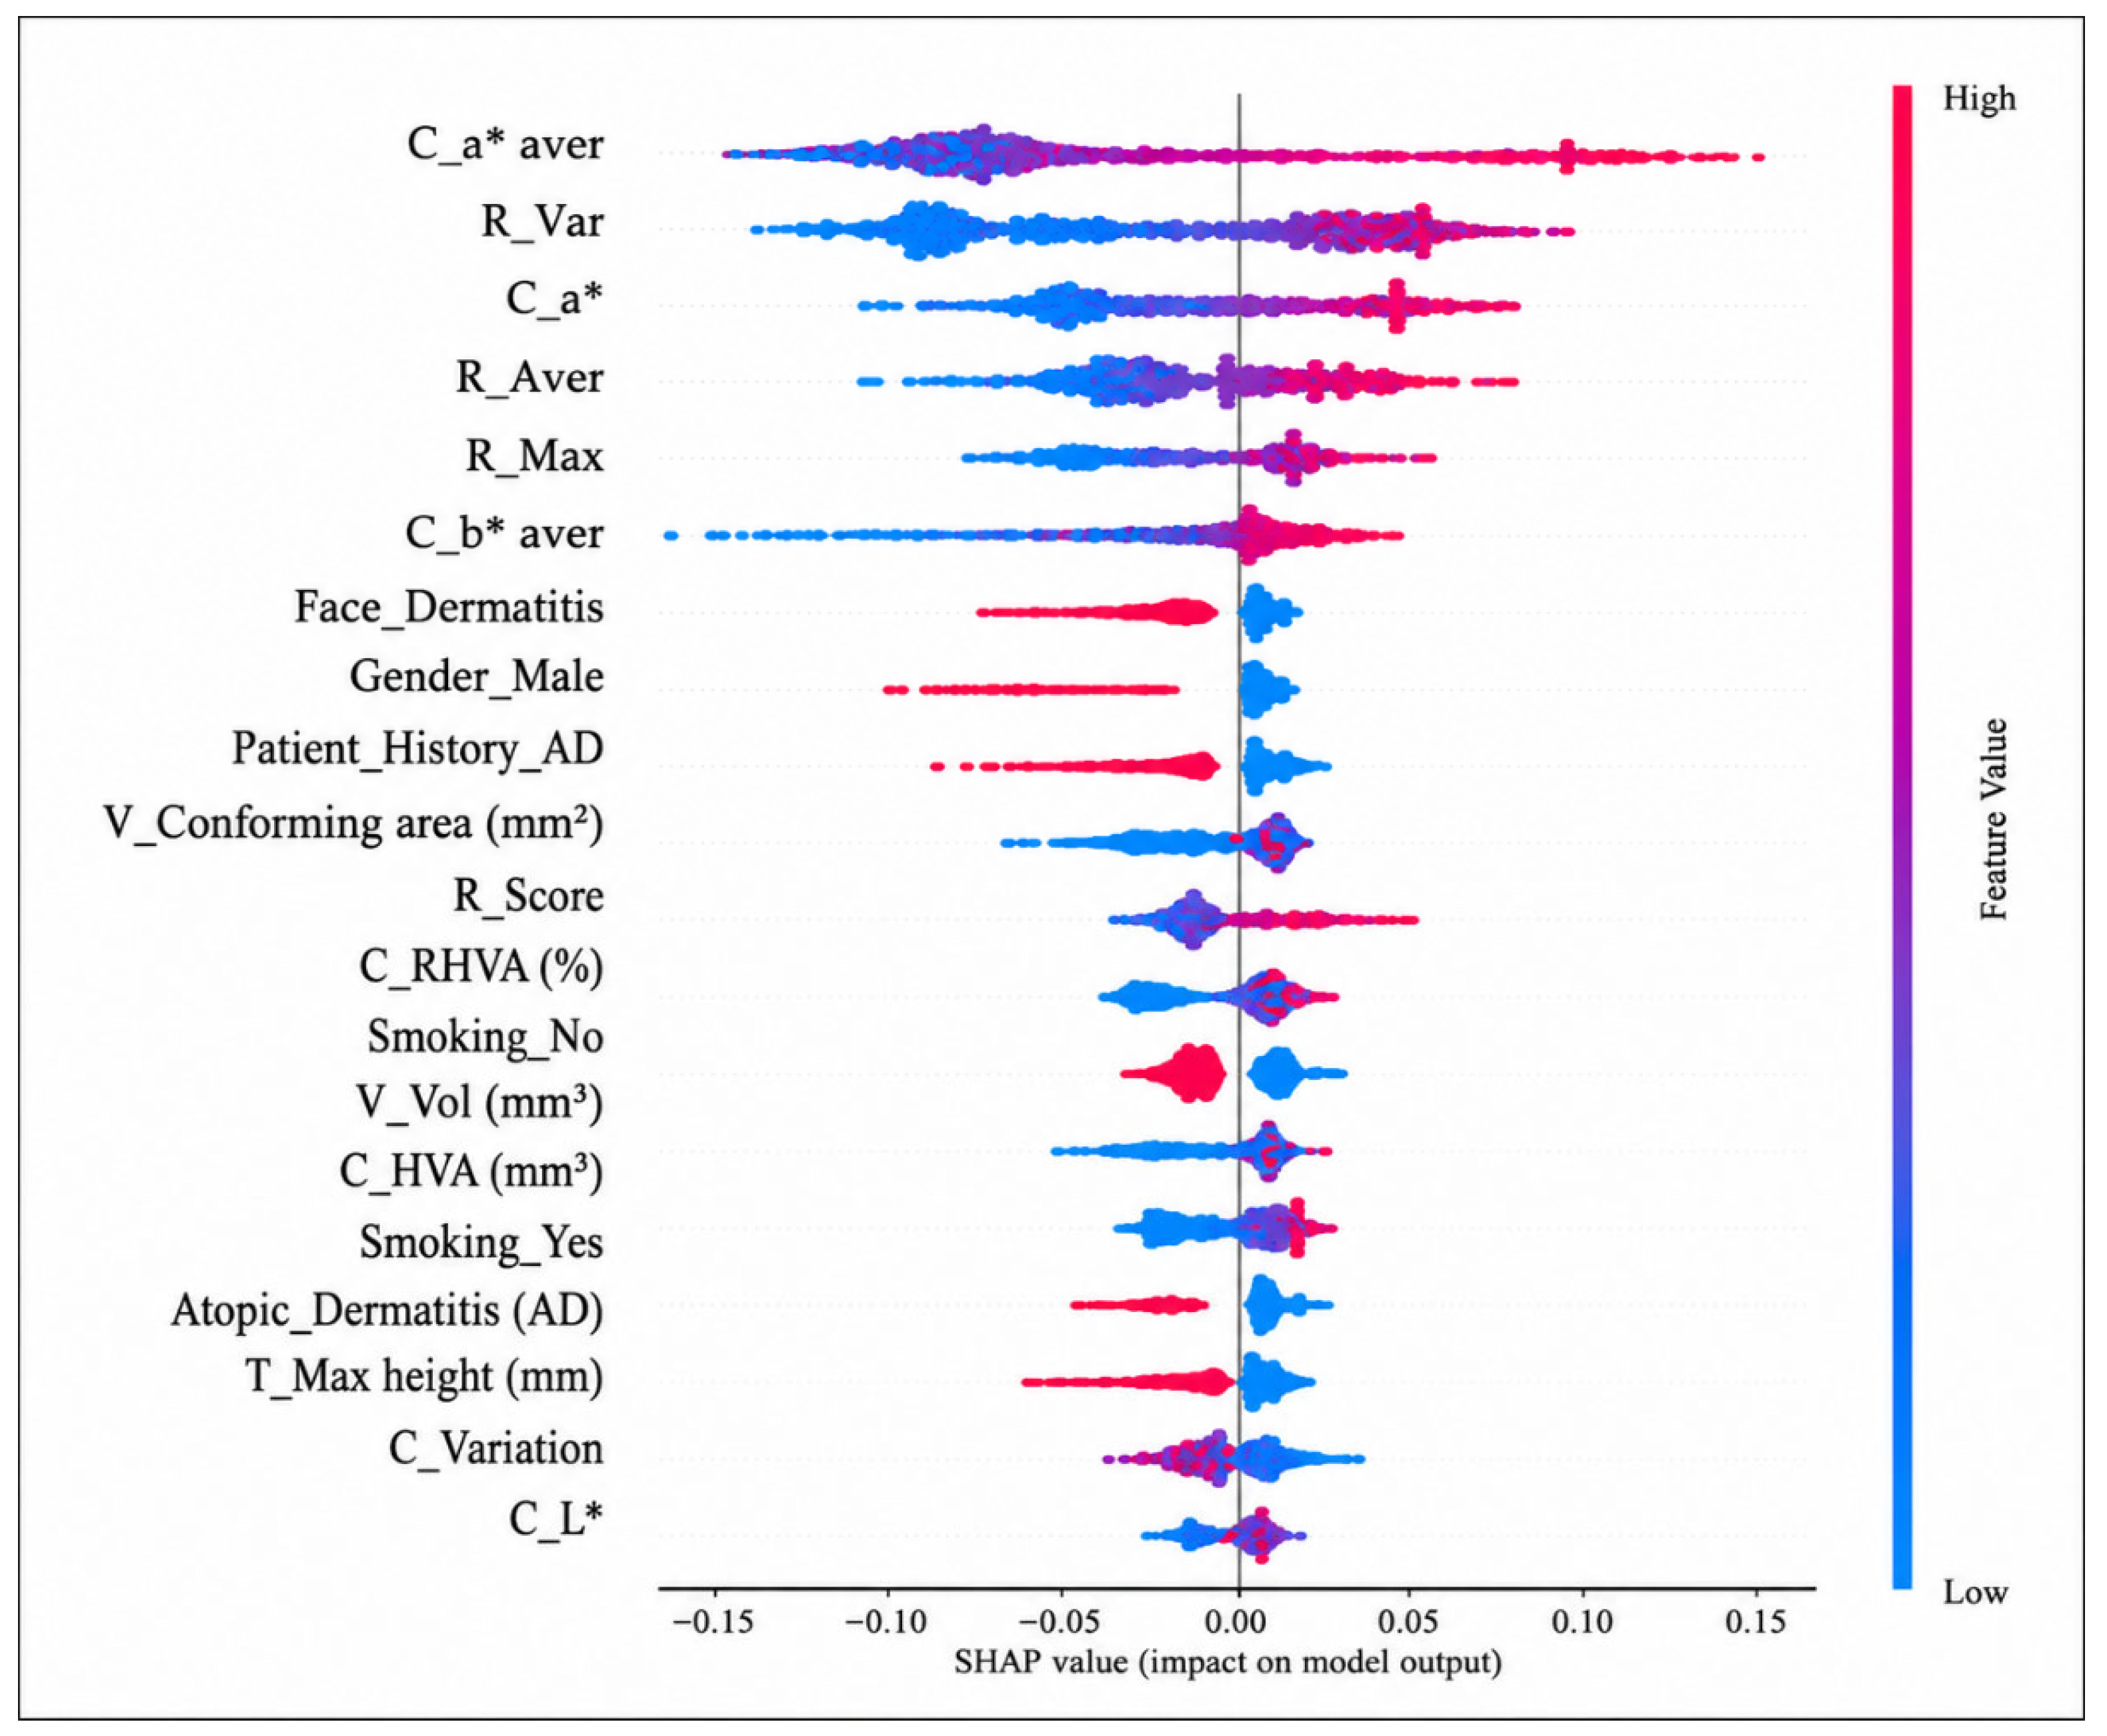
Based on SHAP analysis, the visual features assessed by the clinician are mapped to measurable parameters, such as CIELAB redness indices (C_a aver*, C_a*) and hemoglobin-related parameters (R_Aver, R_Max, R_Var) (
Table 1), which clarifies how the model’s predictions were derived. In particular, in case of a positive result, from the model, it seems to be related to specific changes in the intensity and distribution of erythema. Unlike models based solely on images, which mainly manifest where the model “focuses”, the present approach is more efficient towards a specific diagnostic decision.
One of the key findings of the study is that the progression of reactions over time plays an important role in diagnosis. The model that used changes between the 48 and 72 h intervals (Δ = 72 h − 48 h) performed best (AUC = 0.902), outperforming models based only on measurements from a single time point. This indicates that it is not enough to examine at single temporal measurements, but also it could probably be more effective to examine allergic reactions over time. This finding makes clinically sense: allergic contact dermatitis usually develops gradually, with increasing erythema, edema, and infiltration, while irritant reactions tend to decrease over time. By capturing these changes, the model can better distinguish allergic from non-allergic reactions.
To the best of our knowledge, this is the first study to approach the temporal dynamics of patch tests, which indicates that this information can improve performance as compared to models based on a single time point. However, the temporal difference Δ(72 h − 48 h) should currently be interpreted as a marker of the temporal evolution of the skin response rather than as evidence of an independent construct. Although clinicians performed routine assessments at both 48 and 72 h, the present study was not designed to directly compare temporal delta features with serial clinician evaluations. Therefore, it remains unclear whether these temporal changes provide information beyond that already incorporated into routine clinical assessment or whether they primarily reflect the same temporal patterns recognised by clinicians during evaluation. Future studies directly comparing temporal delta features with serial clinician assessments and biophysical parameters derived from Antera 3D imaging will be necessary to determine their incremental value beyond routine clinical assessment and to clarify their potential role in supporting clinical decision-making.
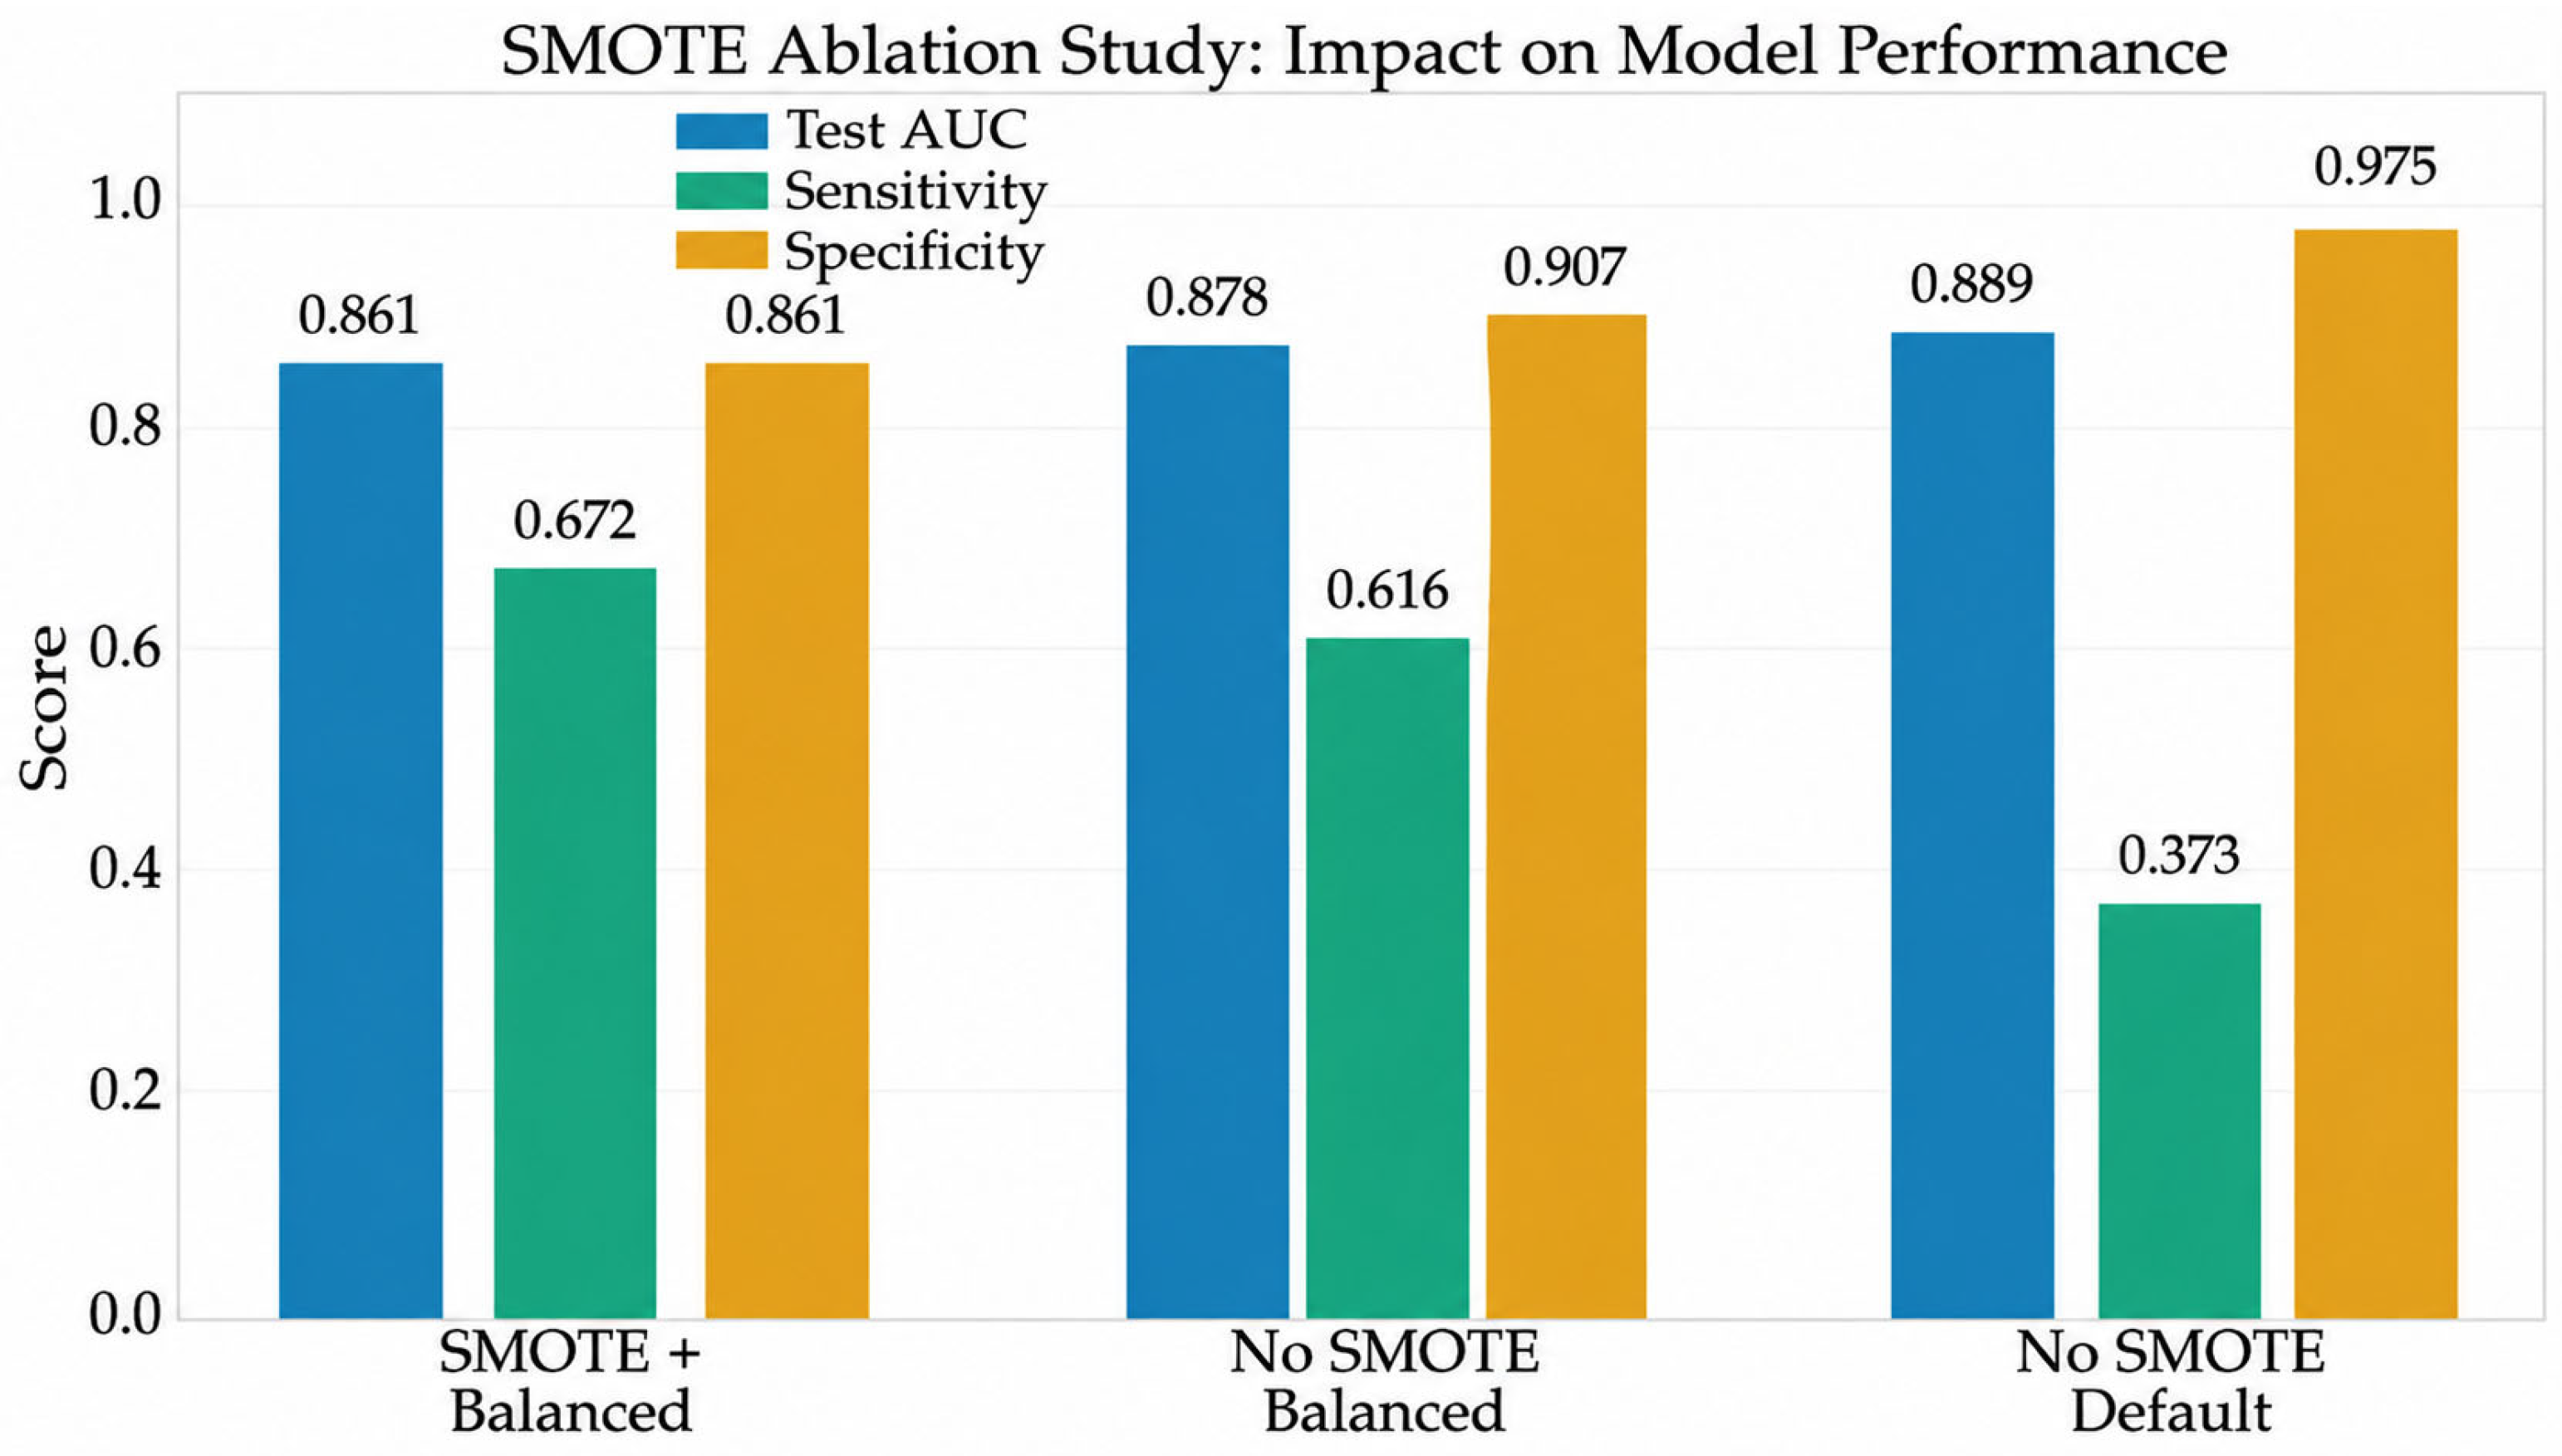
Without any balancing method, the model manifested a higher AUC and specificity, but sensitivity was low (37.3%), which limits its practical utility. By implementing SMOTE and category weighting, sensitivity improved significantly (67.2%), with a relatively small decrease in specificity. This is clinically relevant, because in this case it is more important to identify true allergic reactions than to simply maximize overall accuracy. Although there are reservations about using synthetic oversampling methods, such as SMOTE, in clinical populations [
23,
24], our results show that SMOTE can provide tangible benefits when applied in a well-controlled training setting. The decrease in specificity is expected but may be acceptable in settings where avoiding missed positive cases is considered a priority.
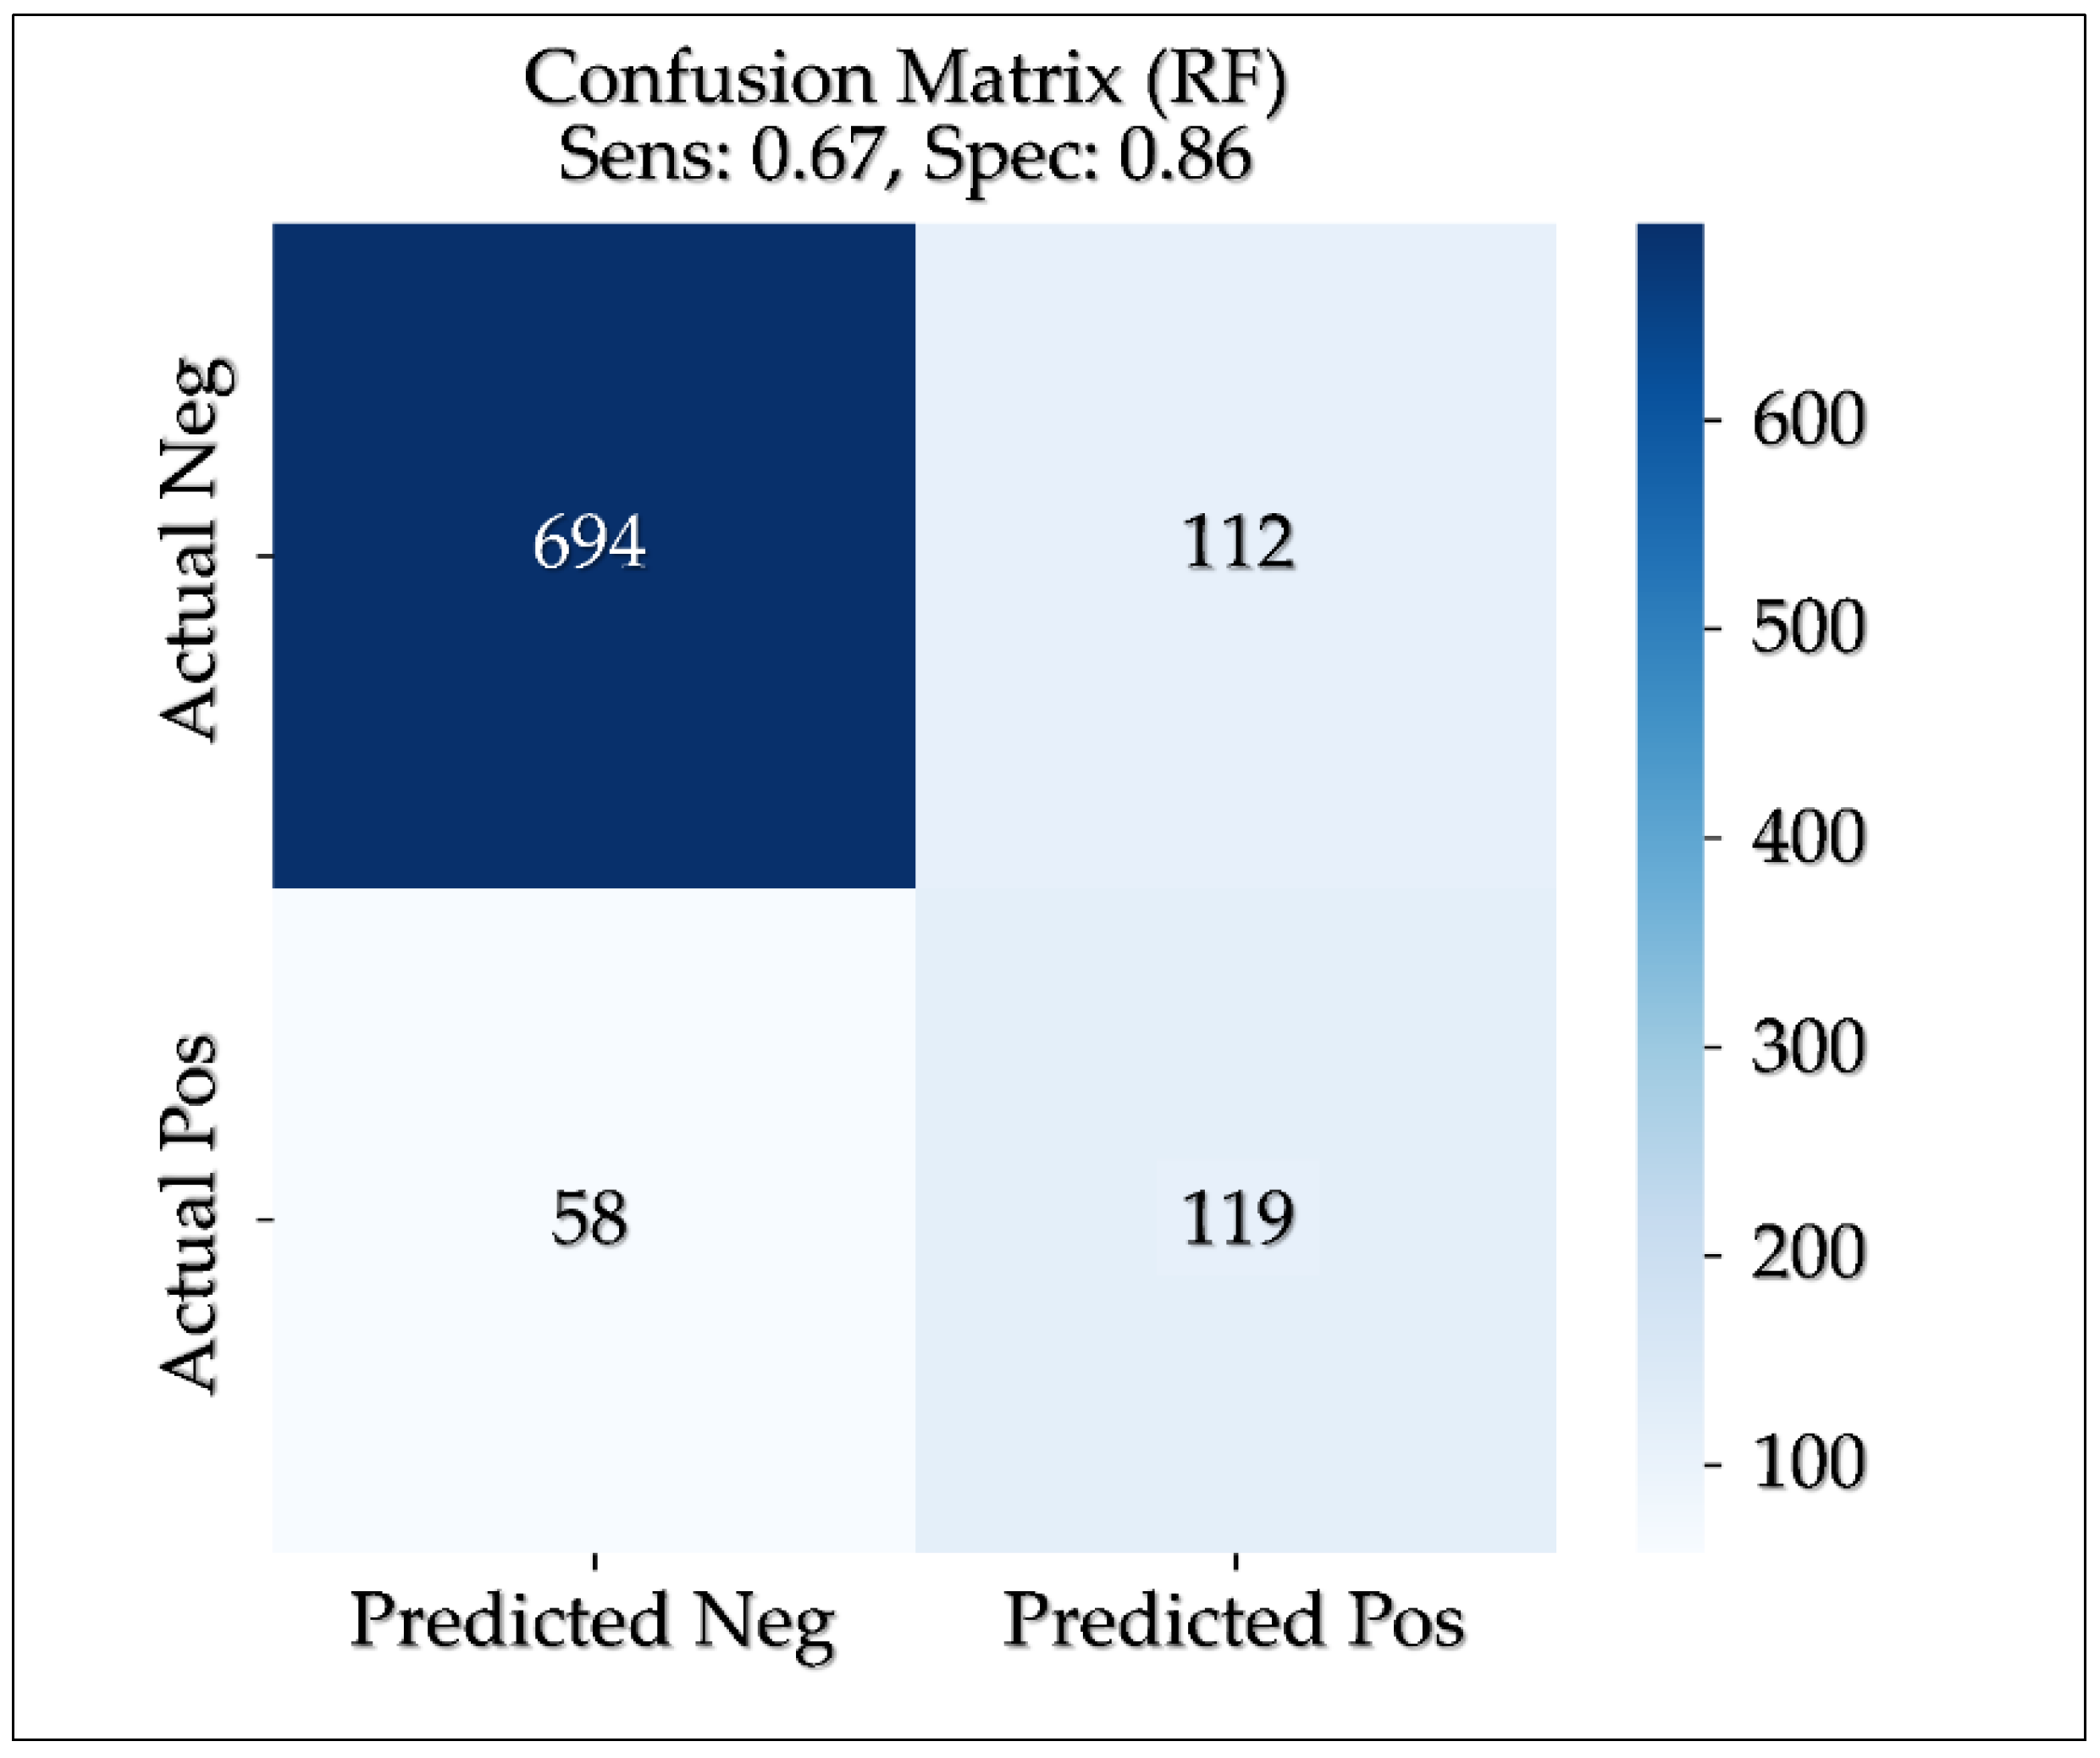
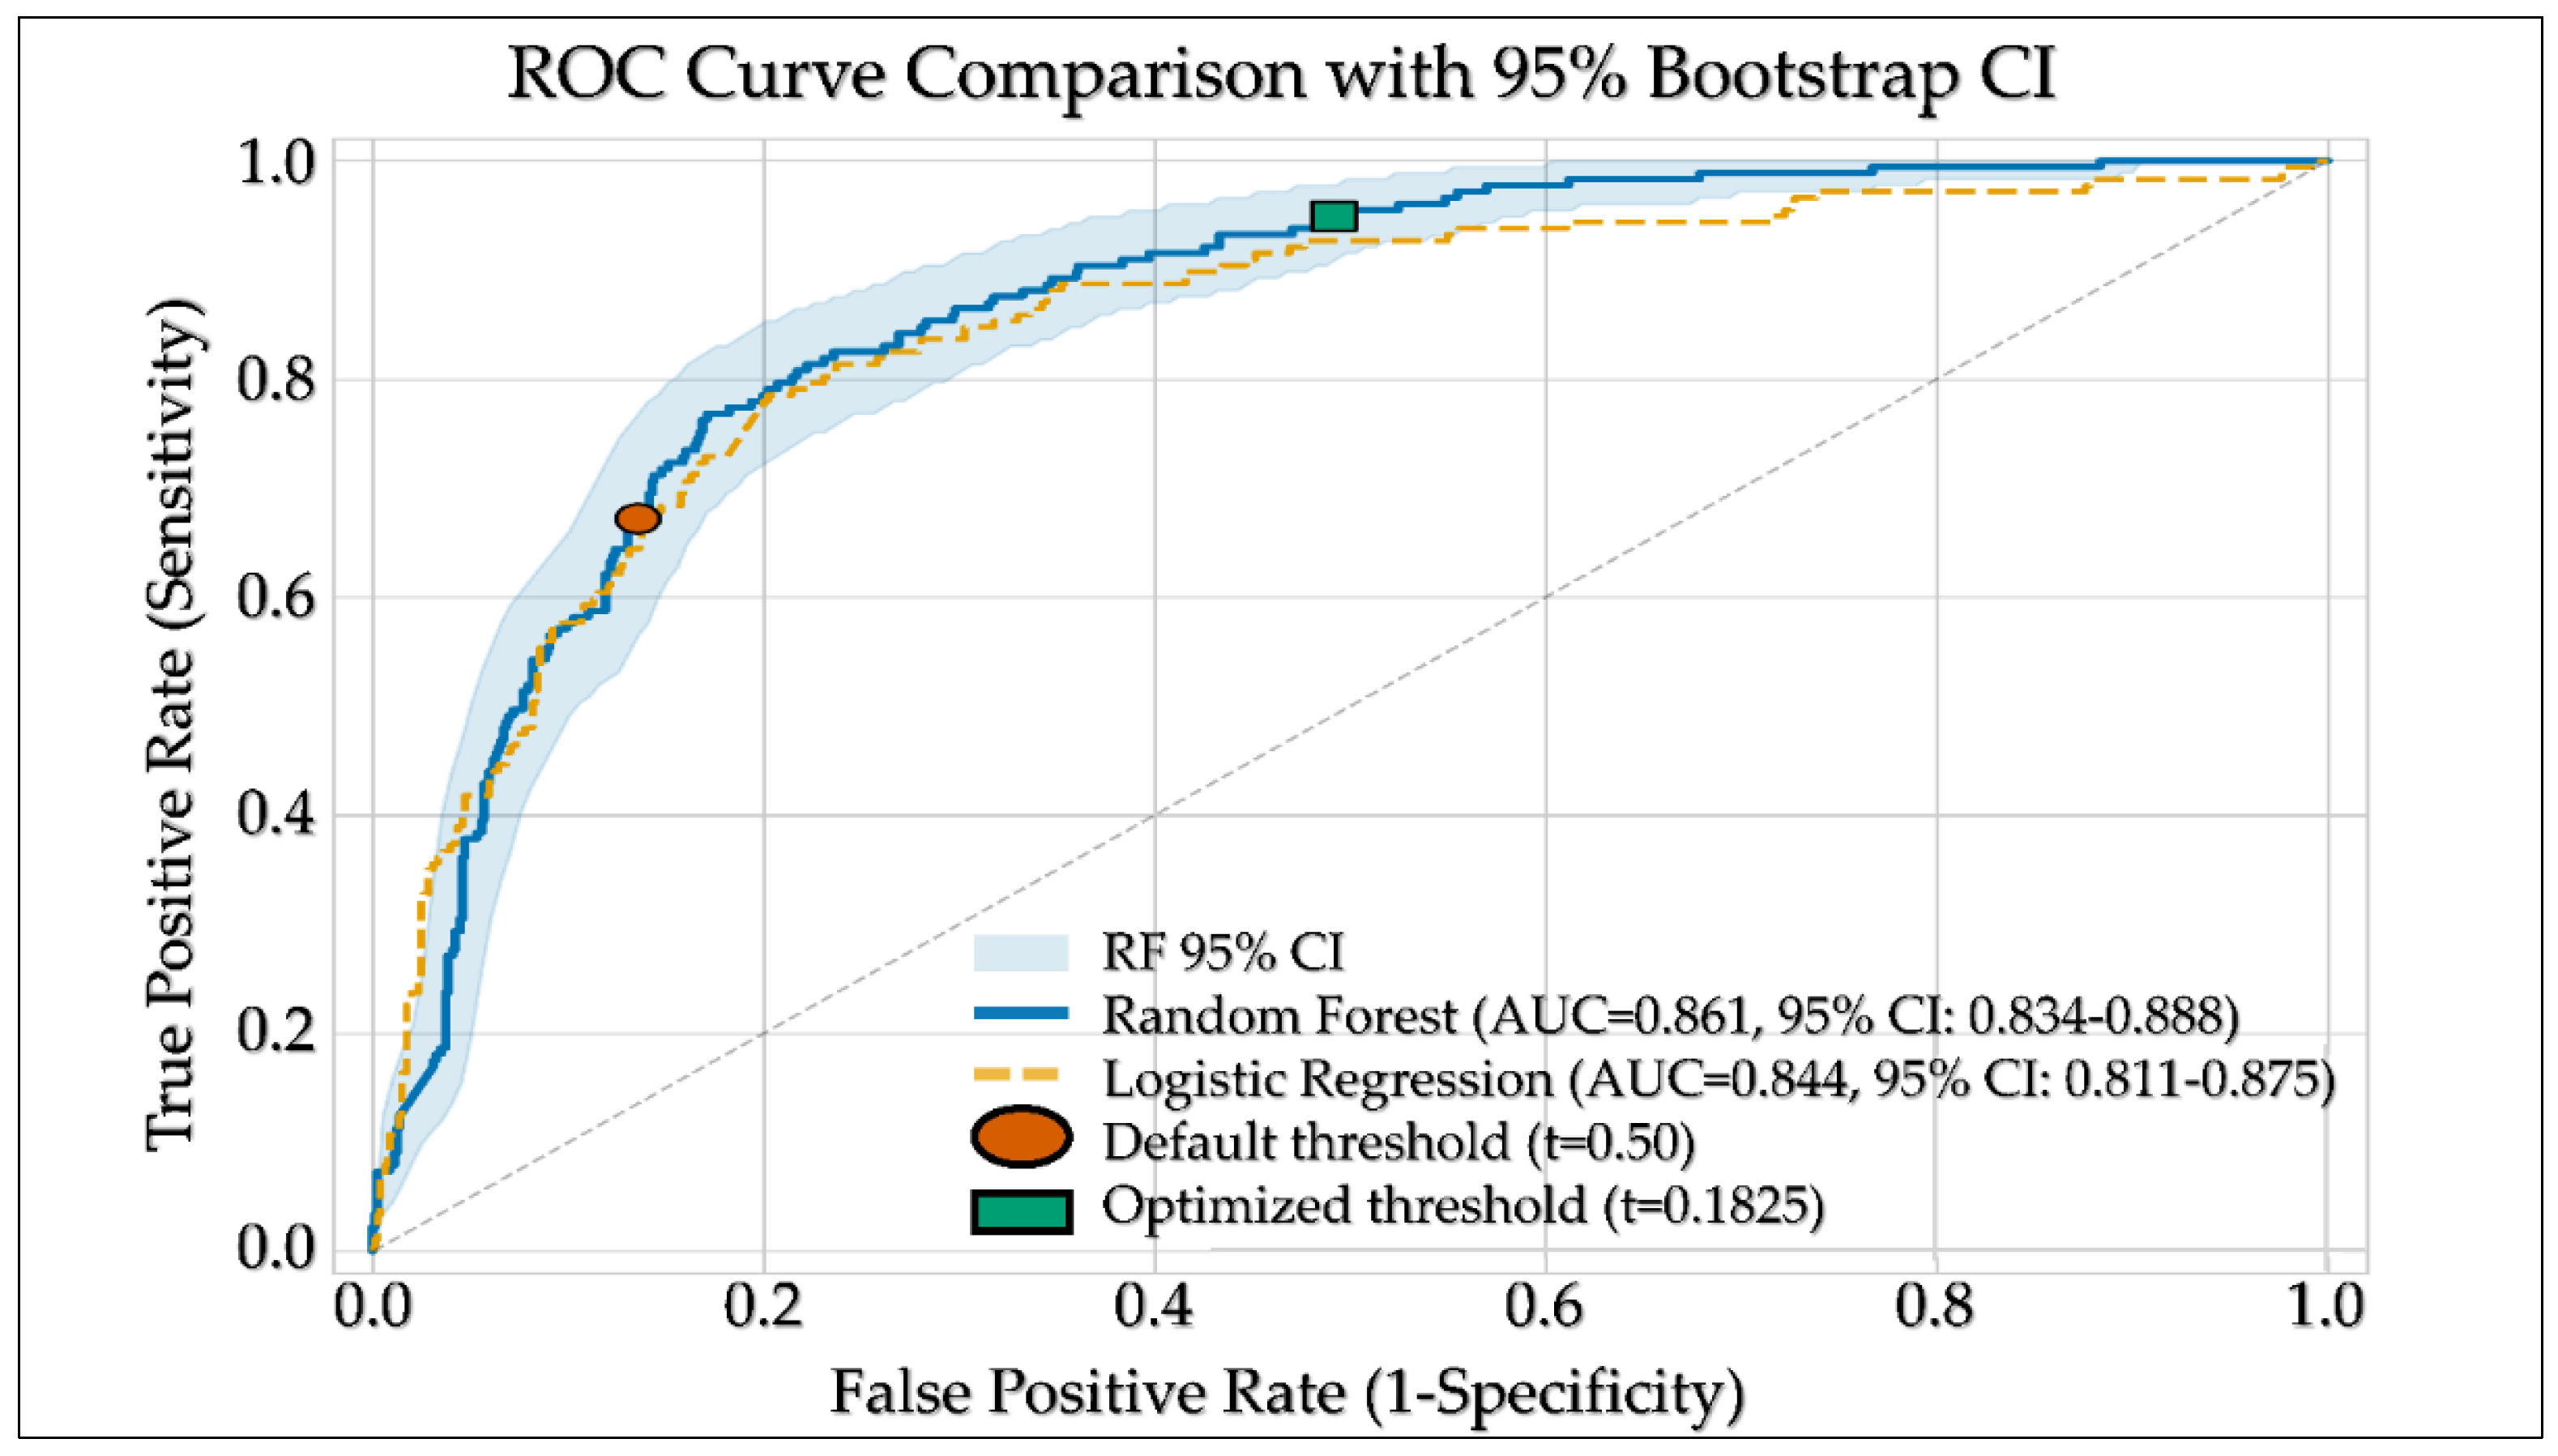
A different classification threshold was also tested, in order to better identify positive cases. With this change, the sensitivity increased to 94.9%, while false negatives were reduced from 58 to 9 in the total number of tests. The specificity was reduced, as expected, but this is acceptable in screening scenarios, where it is more important not to miss positive cases. In any case, the model does not replace the healthcare professional, but it can potentially assist in the assessment, especially for the more borderline cases [
2] giving a more solid basis for the diagnosis.
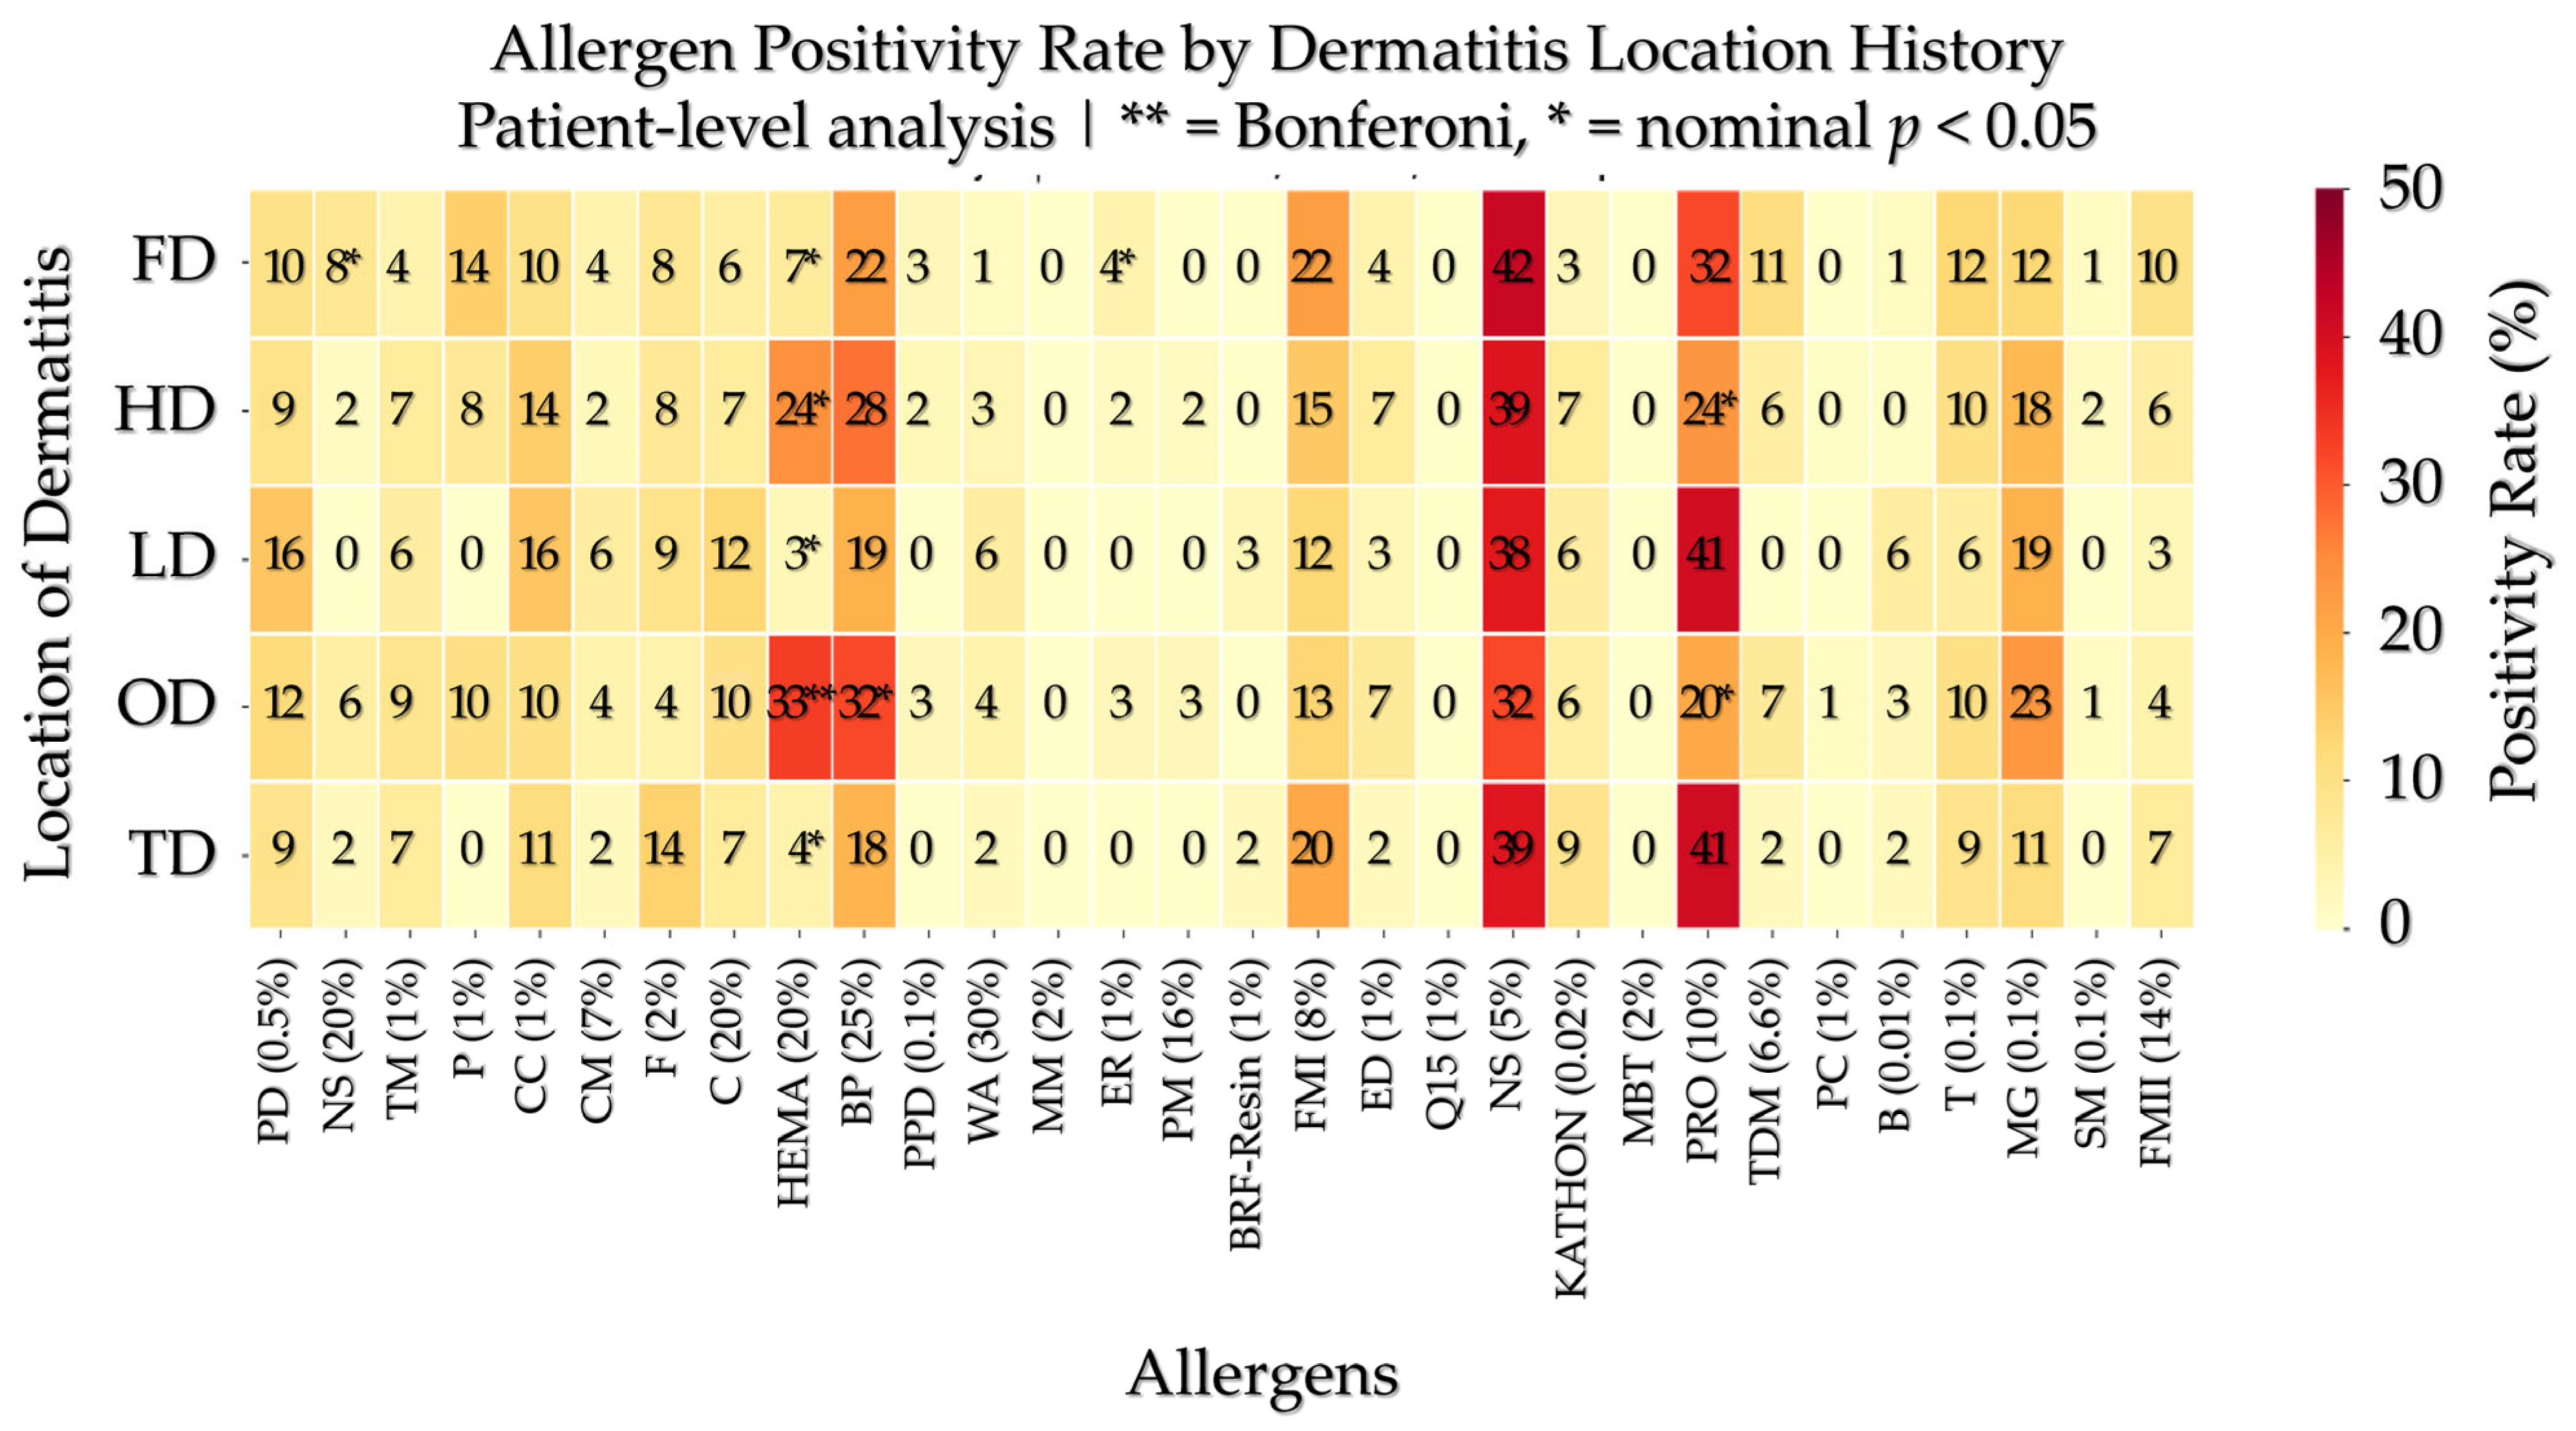
The present study also revealed some clinically useful associations between allergens and localization. The most striking finding was the association of 2-hydroxyethylmethacrylate (HEMA) with occupational dermatitis, which remained statistically significant even after correction for multiple comparisons. This is in line with recent data, as exposure to HEMA has increased, mainly due to its use in nail products and dental materials [
25,
26]. This finding suggests that such approaches can help identify patterns that have practical relevance and may also be useful at the public health level.
At the same time, the value of combining imaging data with machine learning methods to extract useful clinical information is highlighted. In this context, the proposed system can function as a support tool in clinical practice. The data from Antera 3D and the model predictions (AUC = 0.861, 95% CI: 0.830–0.888) can complement the classic ICDRG assessment. By combining measurements, predictions and explanations (as with SHAP), the system can aid in decision-making and reduce cross-examiner differences, especially in more doubtful cases, without replacing the expert’s judgment.
To the best of our knowledge, the present study showed that the use of measurable features combined with interpretable models can help in the evaluation of patch tests. The addition of temporal evolution improved performance, while SHAP analysis provided a better understanding of how predictions are related to clinical features. Overall, the results suggest that a more quantitative approach, which also takes into account time evolution, can be helpful for the specialist, especially in more borderline or doubtful cases.
4.1. Perspectives
The present work does not introduce algorithmic novelty; rather, it contributes a clinically grounded, leakage-controlled measurement-and-modelling framework for objective patch-test quantification, together with the first quantitative evidence that reaction kinetics (Δ = 72 h − 48 h) carry an independent predictive signal beyond single-time-point morphology. Specifically, incorporating Δ-features increased the test AUC from 0.861 (95% CI 0.8301–0.8880) to 0.902, with sensitivity reaching 96.8% and specificity of 50.5% at the operating threshold (
t = 0.22), corresponding to only 3 false negatives among 93 positive samples in the test subset. This represents a clinically meaningful improvement for a screening-oriented task, where missed allergens may have direct consequences for patient management. Furthermore, the proposed framework is, to the best of our knowledge, the first patient-level machine-learning pipeline operating directly on 41 quantitative Antera 3D bioengineering features for ACD patch-test grading, complementing the inherently subjective ICDRG-based assessment—whose inter-observer variability is well documented [
2,
27] with reproducible biophysical measurements. In addition, temporal Δ-features describing changes between the 48- and 72-h readings were introduced to capture reaction kinetics. By quantifying these temporal changes, the proposed model incorporates information beyond single-time-point measurements, contributing to the improved predictive performance observed in this study.
Through this work, we have introduced a leakage-controlled evaluation protocol uncommon in dermatology ML. Parameters such as GroupKFold and GroupShuffleSplit enforce patient-level partitioning, guarded by a programmatic assertion in code (assert overlap = 0, phase2_modeling.py:149); target-revealing columns are removed at the data-preparation stage; and SMOTE is applied strictly inside the sklearn Pipeline so resampling never touches held-out folds.
Finally, we have introduced a three-way ablation of class-imbalance handling paired with Bonferroni and Benjamini–Hochberg correction for the allergen × location multiplicity, and bootstrap 95% confidence intervals (
n = 2000) for AUC, sensitivity, and specificity (
Section 2.8)—rarely reported jointly in the literature. Along with that, SHAP-based clinical interpretability identifying C_a* aver, R_Var, C_a*, R_Aver, and R_Max were identified as dominant predictors, with each linked back to erythema and micro-relief physiology. Thus, the novelty of this study is therefore translational and methodological rather than algorithmic.
4.2. Methodological Considerations
To evaluate the impact of synthetic oversampling on model performance, SMOTE was assessed through a predefined robustness analysis rather than adopted as a default preprocessing strategy. To minimize the risk of optimistic performance estimates commonly associated with synthetic oversampling in medical machine learning [
28], SMOTE was applied exclusively within the training folds by embedding the resampling procedure in an imbalanced-learn pipeline, ensuring that synthetic observations were never introduced into the validation folds or the independent test set. Furthermore, all data partitioning and model evaluation were performed at the patient level using GroupKFold and GroupShuffleSplit (
Section 2.3), ensuring that observations from the same patient were never included in both training and evaluation datasets. Three balancing strategies were evaluated under identical patient-level cross-validation and bootstrap confidence intervals (
n = 2000): (i) SMOTE combined with balanced class weights, (ii) balanced class weights alone, and (iii) no balancing (
Figure 2). Model generalization was subsequently assessed using both five-fold patient-level cross-validation and an independent held-out test set.
The comparison of the three balancing strategies (
Figure 2) demonstrated a clinically relevant trade-off between discrimination and minority-class detection. The no-balancing configuration achieved the highest discrimination (Test AUC = 0.889; CV AUC = 0.880 ± 0.016), but at the expense of markedly reduced sensitivity (37.3%), indicating that nearly two-thirds of true positive patch-test reactions would have been missed. Applying balanced class weights alone improved sensitivity to 61.6% while maintaining good discrimination (Test AUC = 0.878; CV AUC = 0.873 ± 0.017). The combination of SMOTE and balanced class weights further increased sensitivity to 67.2%, with Test AUC = 0.861, specificity = 86.1%, and CV AUC = 0.869 ± 0.017. Although this configuration produced a modest reduction in AUC, it provided the most appropriate balance between sensitivity and specificity for a screening-oriented clinical decision-support tool, where failure to detect a true allergic reaction may result in continued exposure to an unidentified allergen, whereas false-positive results can subsequently be clarified through routine confirmatory clinical assessment.
In addition to sensitivity and specificity, the positive predictive value (precision) of the selected configuration was moderate (0.515 on the independent test set and 0.511 under five-fold cross-validation), indicating that approximately half of the sites flagged as positive corresponded to confirmed reactions. This finding is expected in the present setting for two reasons. First, positive reactions were relatively infrequent (approximately 17% of observations); under such class imbalance, even a well-discriminating model (AUC = 0.861) may achieve only moderate precision because of the well-known base-rate effect, while still maintaining a high specificity (0.861). Second, the operating point was deliberately selected to favor sensitivity, since in a screening context missing a true reaction (false negative) is clinically more consequential than generating a false positive, which can subsequently be resolved through routine confirmatory assessment. Accordingly, the model is intended as a screening aid that complements, rather than replaces, expert ICDRG reading, prioritizing the detection of genuine reactions over maximizing precision. The robustness of the selected approach was further supported by the close agreement between cross-validation performance (AUC = 0.869 ± 0.017) and the independent test-set performance (AUC = 0.861; 95% CI 0.830–0.888, bootstrap n = 2000), suggesting that synthetic oversampling did not result in meaningful overfitting or inflated performance estimates.
Random Forest was selected as the final classifier following an empirical comparison with Logistic Regression and a multilayer perceptron (MLP). These algorithms were chosen to represent three complementary modelling paradigms, namely tree-based ensemble learning, linear classification, and neural-network approaches. Random Forest achieved the best overall balance between discrimination, sensitivity, and specificity (
Table 3). The MLP was included as a benchmark neural-network model to evaluate whether a deep-learning architecture would provide an advantage on this medium-sized tabular dataset; however, its performance was inferior to that of Random Forest (Test AUC: Random Forest = 0.861, Logistic Regression = 0.844, and MLP = 0.836). Accordingly, Random Forest was selected as the final model on the basis of its empirical performance and clinical utility rather than a priori methodological preference. This pattern is consistent with Grinsztajn et al. (2022), who showed that tree-based models outperform deep-learning methods on medium-sized tabular datasets [
29].
Regarding other machine-learning algorithms, the comparison presented in
Table 3 spans three major modelling paradigms. In addition, KNN was evaluated using GridSearchCV, while XGBoost was investigated for the severity regression task.
4.3. Limitations
This study has some limitations that should be considered. First, although the design was prospective and validated at the patient level, the study was conducted at a single center, which may affect the generalizability of the results. Future validation using independent cohorts from other institutions will be important to confirm the robustness and generalisability of the proposed approach. In addition, although predefined eligibility criteria were applied before data analysis, no formal comparison was performed between included and excluded individuals; therefore, some degree of selection bias cannot be entirely excluded. Secondly, although the dataset included 4477 observations, these were derived from 194 patients, which may limit the variety of clinical presentations [
30]. This may also have influenced the allergen–location analyses, where only one association remained significant after correction for multiple testing. It is possible that the limited number of patients reduced the ability to detect additional associations. Therefore, larger studies are needed to further explore potential relationships between allergen sensitisation and anatomical location.
Another limitation is that the model was trained using ICDRG scores, which are inherently subject to some degree of observer variability. The aim of the proposed approach is therefore not to replace expert assessment but to support it in a more standardised manner. As ICDRG assessments performed by experienced dermatologists served as the reference standard, the present study does not allow a direct comparison between model performance and dermatologist performance. Future studies incorporating independent reference standards, such as histopathology or the Repeated Open Application Test (ROAT), as well as blinded assessments by multiple clinicians, may further strengthen label validation and help determine how such tools can complement routine clinical assessment and improve inter-observer consistency. In addition, evaluating model performance independently of the initial labels may help clarify its potential for more objective classification. Finally, our approach was based on the Antera 3D imaging system and it is not yet clear whether the results can be applied to other devices. Although the use of temporal evolution improved performance, the analysis was limited to two patch test reading time points (48 and 72 h) and relied on Δ-feature representations rather than dedicated longitudinal models. Larger cohorts with denser temporal sampling could enable the evaluation of more sophisticated time-series approaches and provide a more complete picture of the evolution of patch test reactions. It also remains uncertain whether the temporal information captured by the Δ-features adds information beyond that already considered by clinicians during routine patch test readings, or simply reflects the same changes in skin responses. Studies combining serial clinical assessments with objective Antera 3D measurements may help address this question.
Finally, SMOTE interpolates within the observed minority distribution and cannot create genuinely novel phenotypes, so external validation on an independent cohort remains necessary.





 ,