


Abstract
(1) Background: The increasing utilization of three-dimensional (3D) photogrammetry has elevated craniofacial analysis to new dimensions. This scoping review seeks to provide a comprehensive overview of the current applications of 3D photogrammetry-supported craniofacial analysis within orthodontic practice, assess its technical superiority, and explore potential areas for enhancement. (2) Methods: A comprehensive search of the literature was carried across three electronic databases (PubMed, Web of Science, Embase). Two independent reviewers screened the articles and extracted data in accordance with the PRISMA-ScR guideline. The primary findings from the included articles were synthesized and analyzed qualitatively. (3) Results: A total of 479 records were obtained initially, with 53 articles ultimately included after removing duplicates and applying eligibility criteria. The application of 3D photogrammetry in craniofacial analysis has become prevalent in orthodontic practice, encompassing normative facial anthropometry, orthodontic problem finding, orthodontic treatment optimization, and treatment outcome evaluation. (4) Conclusion: 3D photogrammetry offers orthodontists a precise and efficient imaging technique for craniofacial analysis.
1. Introduction
Advancements in digital dentistry is irrevocably transforming modern dental practice and establishing itself as the new paradigm in dental healthcare. At the heart of the digital dentistry lies comprehensive digital imaging, which is essential in driving unprecedented precision and workflow optimization. Dental imaging is continuously undergoing transformative evolution, for example, progressing from conventional two-dimensional (2D) imaging to three-dimensional (3D) imaging. Compared with 2D imaging, the dimensional leap of 3D imaging can provide more spatial information and numerical precision in anatomical evaluation [1,2]. Among these advancements, 3D photogrammetry—a technique that reconstructs 3D surface models from overlapping 2D photographs using geometric algorithms—has emerged as a transformative tool. Unlike traditional methods, such as 2D photographs or 3D radiographs, 3D photogrammetry provides a comprehensive and radiation-free approach to capture high-fidelity craniofacial morphology. Its ability to quantify soft-tissue contours with high accuracy enables it to be a critical adjunct to conventional dental practice [3].
Orthodontic treatment aims to achieve dentofacial harmony through moving teeth [4]. Therefore, comprehensive craniofacial analysis, encompassing both hard tissue and soft tissue is essential for a high-quality orthodontic practice. The advent of cone-beam computed tomography (CBCT) has revolutionized hard tissue evaluation in orthodontic practice, improving treatment certainties. For example, observing the spatial relationship between tooth roots and cortical bone to assess the risk of bone dehiscence and fenestration during tooth movement, and evaluating the maturity of the midpalatal suture to provide guidance for skeletal maxillary expansion [5]. Although for soft tissue, the effect of CBCT is not satisfactory as it does not indicate true color and real skin texture [6]. In contrast 3D photogrammetry, which does not cause radiation exposure, is less time consuming, and provides data in three dimensions with color and texture is expected to act as a new robust modality for soft tissue analysis.
With the advent of 3D facial scanning technology, 3D photogrammetry-driven craniofacial analysis is not a novel concept and has been widely applied across many fields, particularly in craniomaxillofacial surgery [7]. However, its utilization in orthodontic practice remains less explored, primarily due to suboptimal imaging accuracy and the operational inefficiencies of the instruments. In recent years, driven by technological advancements, 3D photogrammetry-based craniofacial analysis is becoming more precise and accessible [8,9,10], therefore expanding its clinical applications in orthodontics. For instance, 3D photogrammetry systems have become increasingly accessible due to innovations in consumer-grade cameras [11,12], smartphone-based applications [8], and software [9]. The reduction in hardware costs compared to early commercial systems like 3dMD, enabled chairside imaging without specialized infrastructure, making the technology viable for rural or resource-limited practices. In addition, integration with other advanced technologies, such as artificial intelligence and multimodal imaging data integrations, has further redefined its role in modern orthodontic workflows.
The field of 3D facial photogrammetry has undergone a profound transformation, driven by innovations in camera systems, automated processing algorithms, and sophisticated analytic software. Consequently, there has been a surge in studies exploring its clinical utility in orthodontic diagnosis and treatment planning. However, this accelerated progress has outpaced the available scholarly synthesis. Existing review articles do not focus on the novel applications and technological capabilities specific to craniofacial analysis. It is necessary to map the current landscape, consolidate recent findings, and identify future directions for this dynamic tool. Therefore, this scoping review aims to overview the current applications of 3D photogrammetry-driven craniofacial analysis in orthodontics, discuss its advantages and limitations, and explore potential improvements, thereby giving new insights into future research and clinical applications.
2. Materials and Methods
2.1. Protocol
This scoping review was performed following the Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR) guidelines [13]. This study’s research question was: what are the current applications of 3D photogrammetry-driven craniofacial analysis in Orthodontics? A scoping search of MEDLINE (via PubMed) was first conducted to refine the search strategy. The protocol of this scoping review was registered on Open Science Forum (osf.io/gmc47) (accessed on 22 December 2024).
2.2. Eligibility Criteria
The inclusion criteria were constructed according to the PICOS format: P (Population): Human subjects including patients, healthcare providers, and lay individuals. I (Intervention): 3D photogrammetry-supported craniofacial analysis in clinical orthodontic practice, including combined orthodontic and orthognathic surgery. C (Comparison): Any imaging techniques utilized for craniofacial analysis, manual caliper measurement, or blank control. O (Outcomes): All types of outcomes associated with 3D photogrammetry-assisted craniofacial analysis. S (Study design): Original clinical studies published in English since January 2019, including but not limited to case reports, cross-sectional studies, etc.
Exclusion criteria were as follows: (1) Study not directly related to orthodontics (e.g., sleep apnea, alcohol syndrome, cleft). (2) Non-clinical studies, letters, expert opinions, and review papers. (3) Studies written in a language other than English. (4) Articles without full-text available.
2.3. Information Sources and Search
A formal comprehensive search of the literature was subsequently performed across three electronic databases (MEDLINE/PubMed, Web of Science and Embase) in December 2024. The second round of the search was conducted in June 2025 to collect updated papers. Given the absence of appropriate subject terms, keywords and their synonyms were specifically selected and combined for the literature search (Table S1).
2.4. Study Selection
Reference management and selection were conducted using the EndNote software (EndNote 21, Clarivate Philadelphia, PA, USA). After eliminating duplicate studies, two reviewers (HPK and LJQ) independently screened the titles, abstracts, full texts, and reference list of the included studies. Any disagreement was addressed through discussion or consultation with the third reviewer (SZY) until final consensus was achieved.
2.5. Data Extraction and Synthesis
The data extraction process was conducted by two reviewers (HPK and LJQ) independently. The collected information was organized into tables, including the author names, year of publication, aim of study, study population or sample size, type of 3D scan machine and software employed, and broad-based orthodontic outcome domain.
A comprehensive analysis of the extracted data was performed. The qualitative data synthesis was carried out in a narrative manner, detailing various applications of 3D photogrammetry-supported craniofacial analysis in orthodontics.
3. Results
3.1. Selections and Characteristics of Included Studies
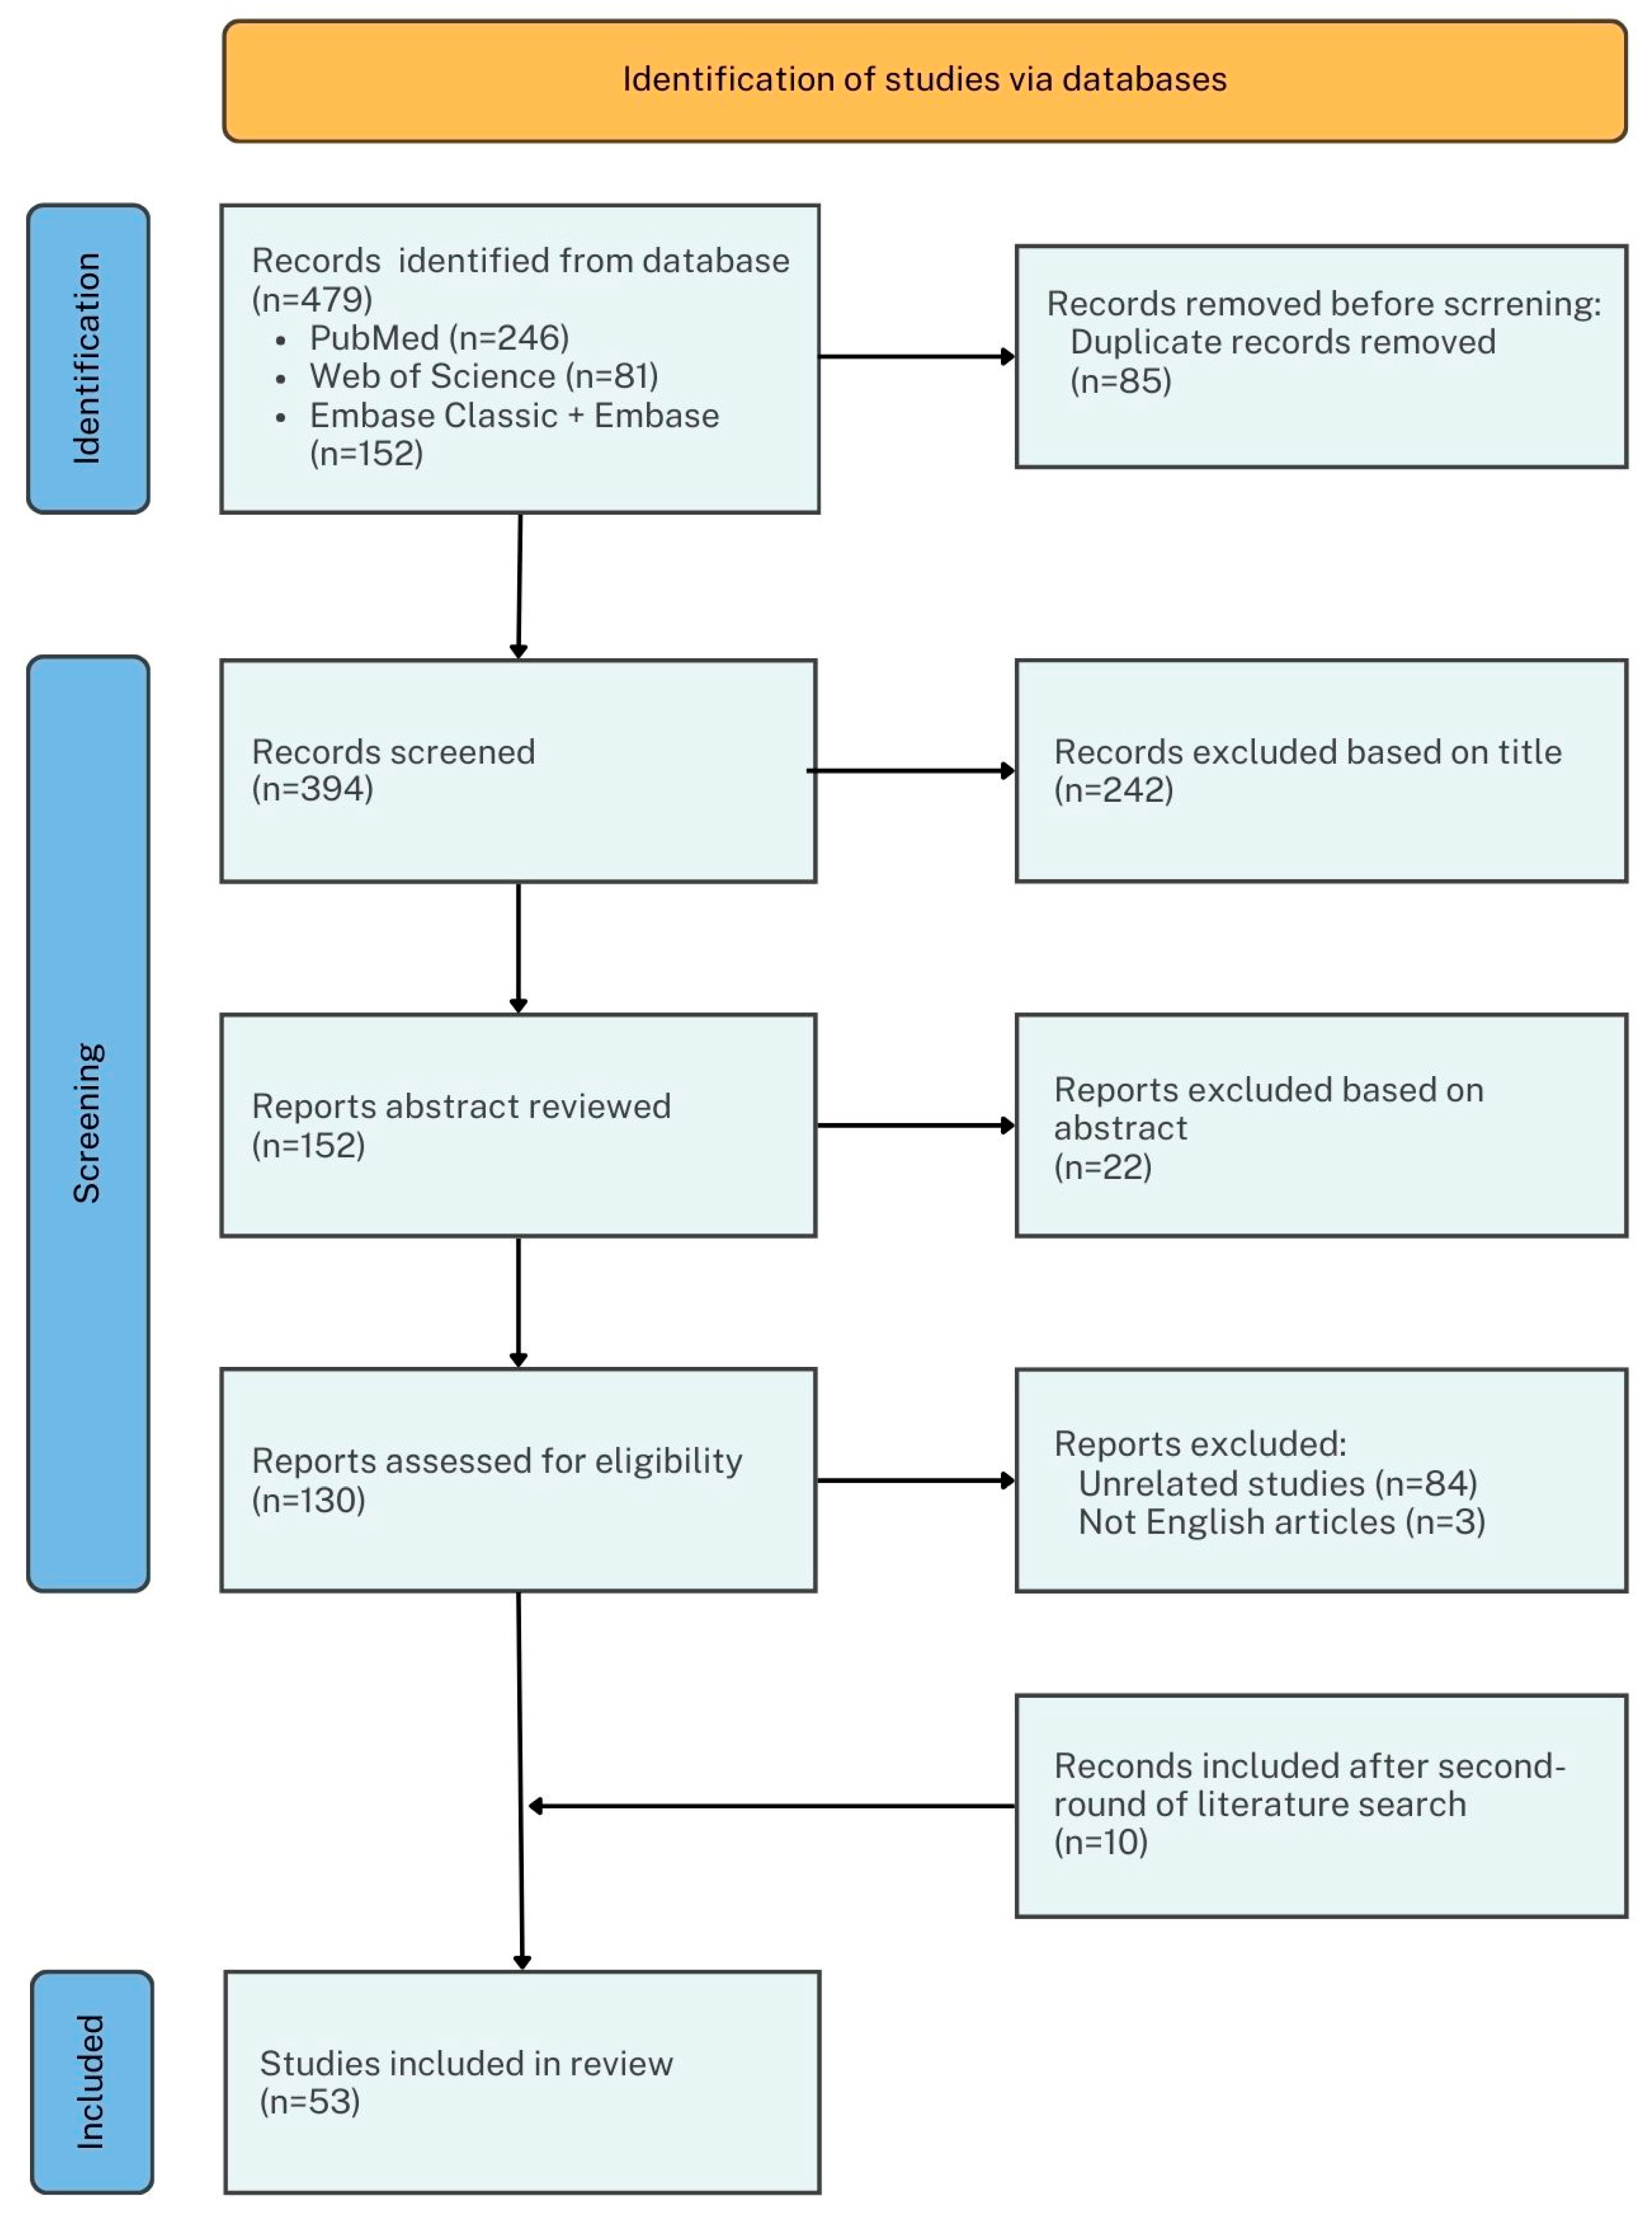
The initial search strategy resulted in 479 records, 85 of which were excluded as duplicates. After removing duplicates, the titles and abstracts of 394 records were screened, leading to the exclusion of 264 records. Of the remaining 130 records undergoing full-text screening, 86 records were excluded for not fulfilling the eligibility criteria. Finally, 43 were selected for the qualitative analysis [14,15,16,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56] (Figure 1). A second round of searching identified 77 additional records. After removing 20 duplicates, the titles and abstracts of 57 records were screened. A total of 42 records were excluded based on title and abstract and 5 were excluded after a full-text screening. A total of 10 were selected for the qualitative analysis at last [57,58,59,60,61,62,63,64,65,66]. (Tables S1 and S2)
Figure 1.
Flow chart of the workflow of identifying eligible studies.
The geographical distribution of the 53 included studies highlights a polycentric yet concentrated field of research. The work is led by a triad of major area contributors: China [21,23,24,26,28,33,36,38,43,47,48,50,57,58], Italy [18,30,37,44,51,55,66] and Taiwan [39,40,52,53,62,63], which together account for over half of all publications. Strong regional activity is also evident in East Asia (South Korea [27,54,56], Japan [20]) and Southern Europe (Greece [45], Spain [19], Türkiye [25,31,32,41,42]), reflecting a broad, global engagement with 3D facial imaging technology. This distribution underscores that the drive for innovation in this domain is not confined to a single region but is a shared priority across international academic and clinical communities, facilitating diverse perspectives and methodologies.
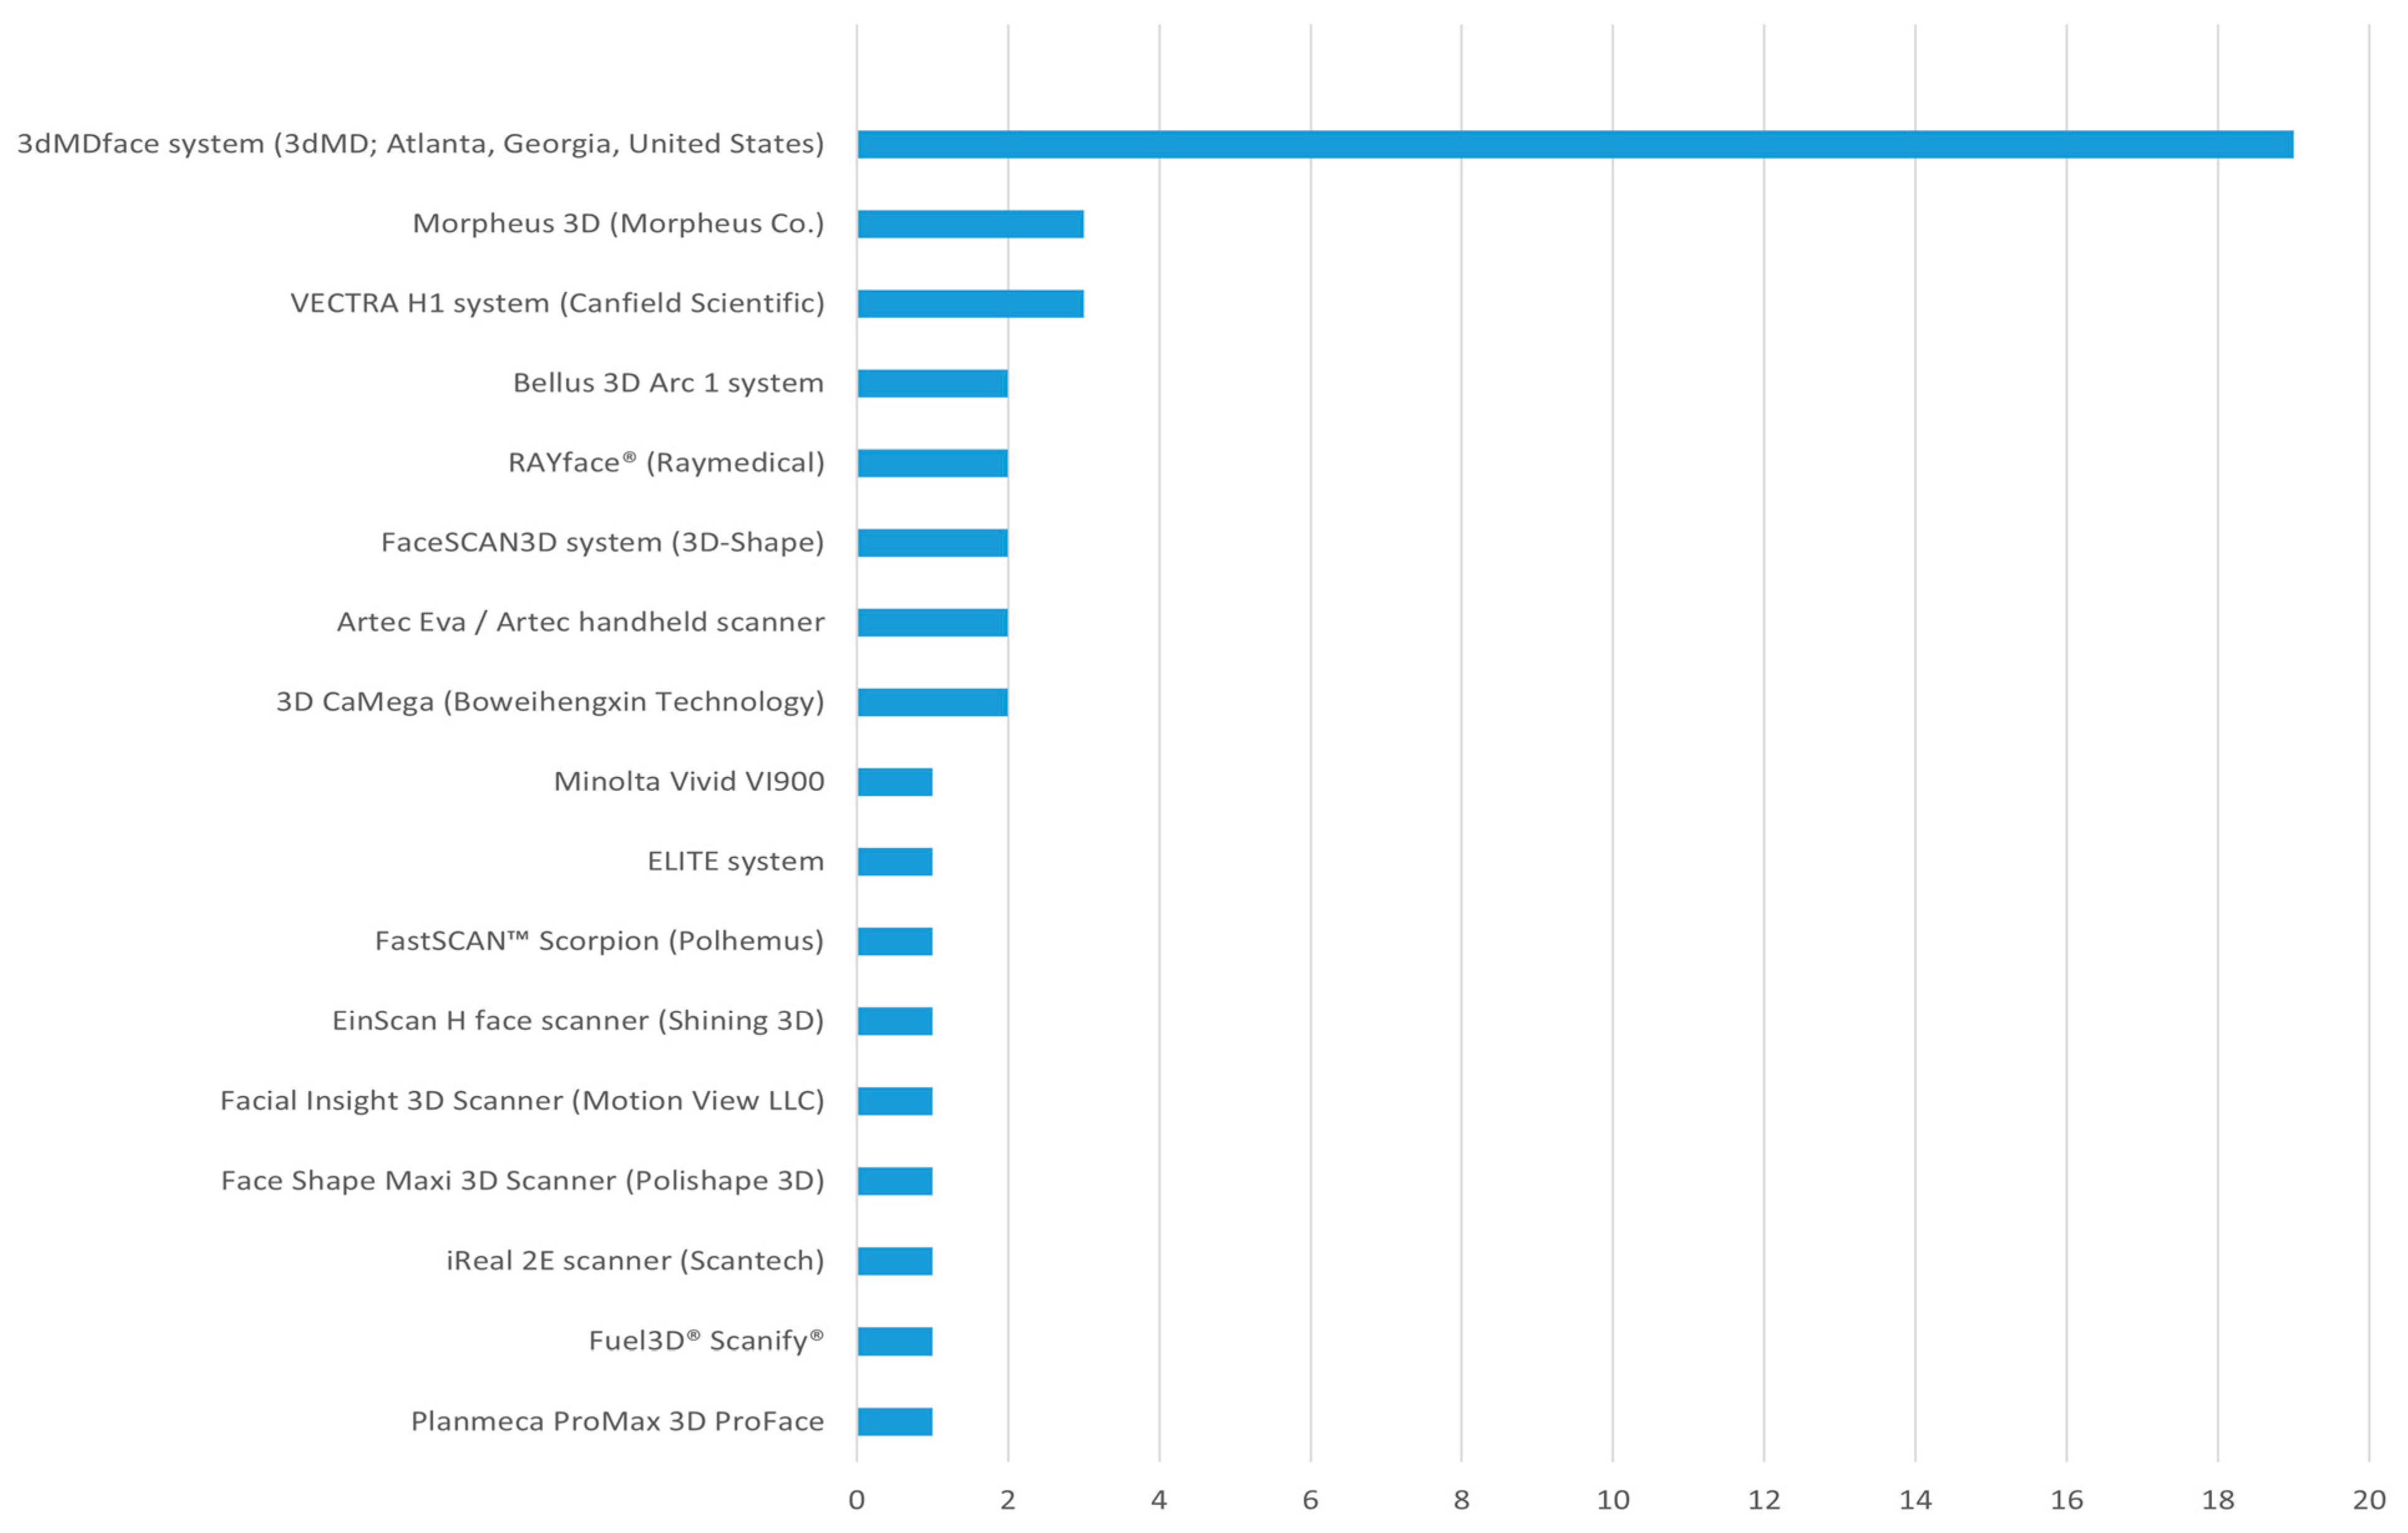
The analysis of the 53 included studies revealed a clear predominance of specific technologies for data acquisition and processing. The 3dMDface system (3dMD LLC) was the overwhelmingly dominant imaging tool, employed in 19 studies (35.8%) [14,15,20,21,22,26,28,29,31,32,35,36,38,39,40,41,42,45,46,52,53,55,59,60,62,63,65] and was used to capture 1652 subjects, solidifying its status as the industry standard for high-resolution 3D facial stereophotogrammetry. Other imaging systems were also utilized, including the VECTRA H1 (Canfield Scientific) [16,17,51], Morpheus 3D [33,54,56], Artec Eva handheld scanner (Artec EvaTM; Artec Group, Luxembourg) [47,49], FaceSCAN3D (3D-Shape) [24,58] and Bellus 3D Arc 1 [23,57] (Figure 2).
Figure 2.
Bar chart of number of studies using different imaging tools.
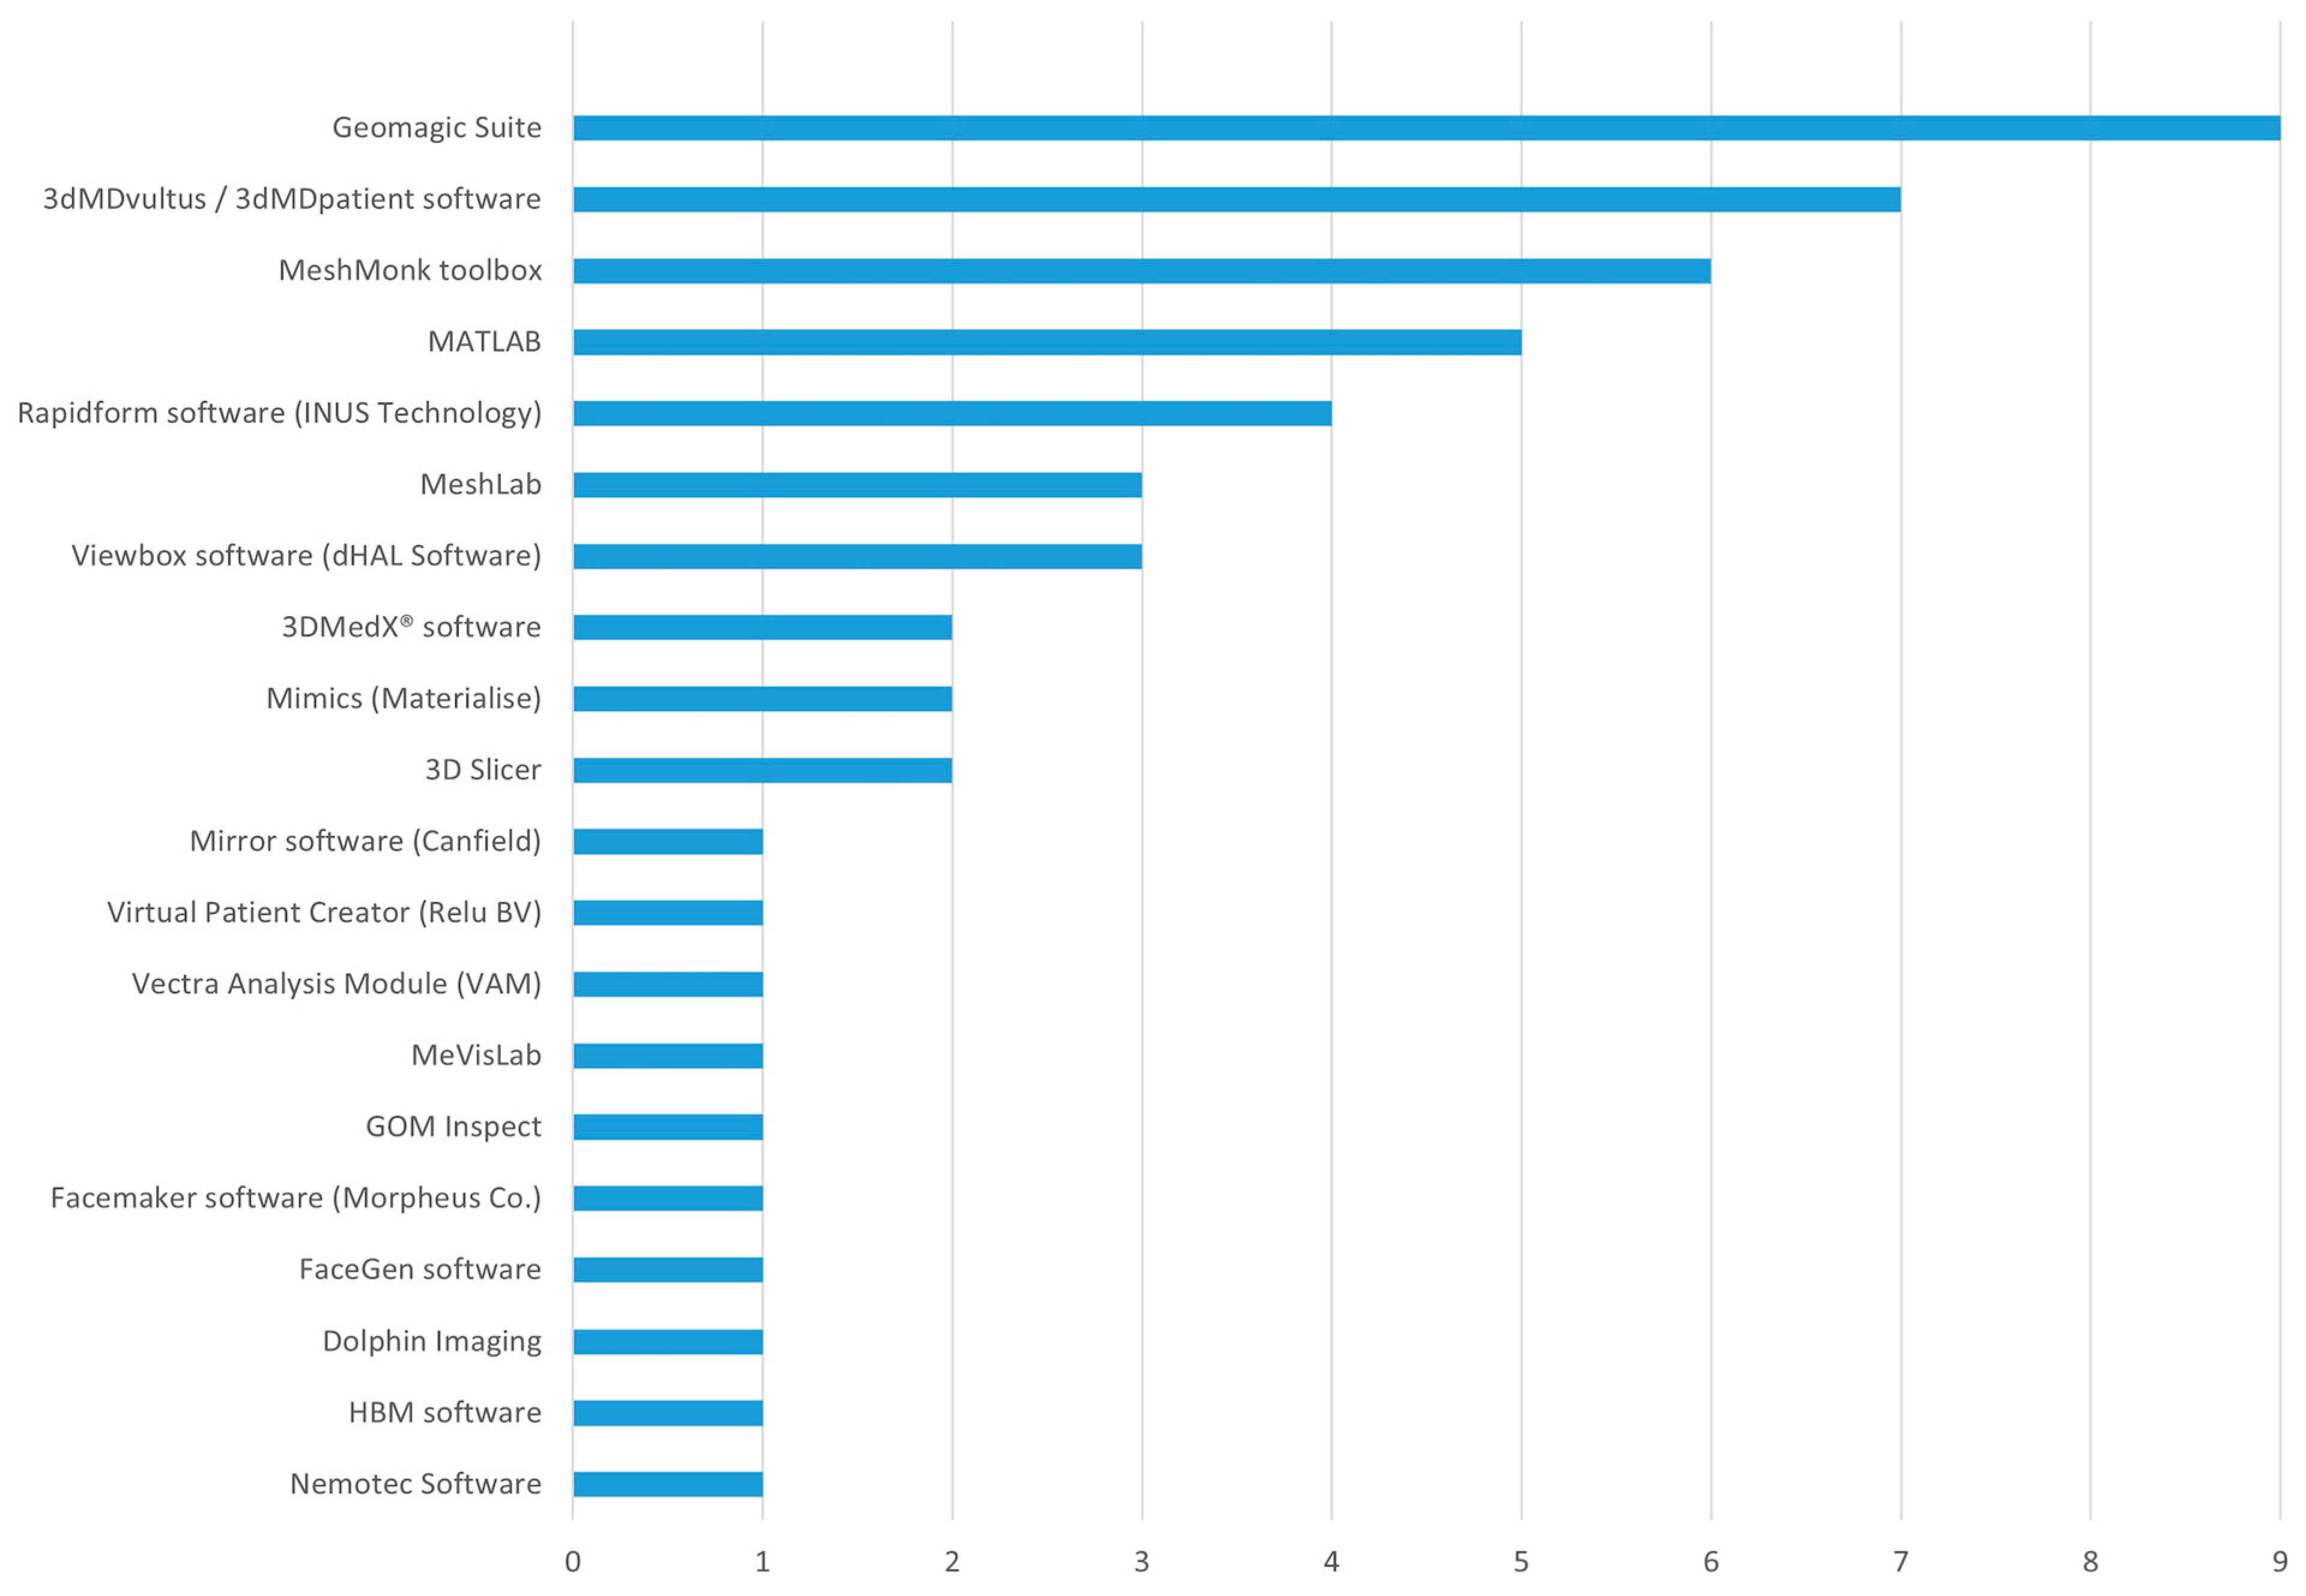
Software usage was more heterogeneous, reflecting a range of analytical approaches. The MeshMonk toolbox, frequently operated within the MATLAB environment, was used to process the largest cohort of subjects (n = 1091) [16,21,33,48,57,58,59,60,62], highlighting its central role in dense surface correspondence and geometric morphometric analysis. The proprietary Geomagic suite (e.g., Studio 2013, Essentials 2, Wrap 2015, Control, Qualify 12, Studio 2015) was the most frequently cited software family, used in nine studies for tasks like surface registration and deviation analysis [24,25,26,28,36,50,57,61,66]. The vendor-specific 3dMDvultus and 3dMDpatient software were also heavily employed for initial data processing and clinical assessment [31,32,41,42,46,55,59,62,63,65]. Other widely used software included Rapidform (INUS Technology) [14,15,43], Viewbox (dHAL Software) [22,29], 3D Slicer [44,64], and 3DMedX® software [52,60]. A variety of specialized software packages were applied for specific tasks, such as Nemotec for anthropometric analysis [19], HBM [20] for constructing normative faces, GOM Inspect for deviation analysis [49]. This landscape demonstrates a methodological ecosystem reliant on a few dominant, high-fidelity imaging systems, paired with a diverse array of software ranging from commercial clinical packages to powerful open-source toolboxes for advanced computational research (Figure 3).
Figure 3.
Bar chart showing number of studies using different softwares.
The 53 eligible publications can be categorized into the following four aspects: normative facial anthropometry [14,15,16,17,18,19,20], orthodontic problem finding [21,22,23,24,25,26,27,28,29,57,58], orthodontic treatment optimization [30,31,32,33,34,35,36,37,38,59,60], and treatment outcome evaluation [27,31,32,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,61,62,63,64,65,66].
3.2. Normative Facial Anthropometry
Eight publications were included regarding the use of 3D photogrammetry in normative anthropometry (Table 1). In these studies, 3D photogrammetry was used to analyze population-[14,15,16,19], age-[17,18] or sex-[19] specific facial features. When analyzing facial morphology, three of the studies generated average faces by aligning the facial scans using commercial softwares. From the generated average face, linear measurements, color histograms, surface areas, and shapes can be measured or calculated for normative facial anthropometry. Three studies identified landmarks manually or automatically by software to calculate a mean value with standard deviation for linear and angular measurements [17,18,19]. All studies calculate quantitative statistics except Tanikawa, C. et al. [20] who proposed the superimposition of average face and individual face scans for diagnostic purpose.
Table 1.
Summary of the findings regarding the use of 3D photogrammetry in normative facial anthropometry.
3.3. Orthodontic Problem Finding
Eleven studies have demonstrated the clinical utility of 3D photogrammetry for identifying various orthodontic problems, either as a standalone technique or in combination with conventional anthropometric methods (Table 2). Half of them focused on evaluating facial asymmetry [21,22,23,24,57,67] employing different approaches such as using spatially dense geometric morphometrics [21], overlapping 3D facial images along the midsagittal plane [22], constructing a 3D facial mask with an average facial model [23], constructing a 3D symmetry reference plane with a mathematical algorithm [24], and constructing a wireframe template with facial landmarks to calculate angle asymmetry [57]. Two studies discussed the analysis of the social smile, focusing on the relationship between smile characteristics and the surrounding hard and soft tissues [25,26]. One study explored the relationship between maxillary central incisors and the forehead [27], when another one evaluated the hard-soft relationship of the lower half of the face [28]. Mao et al. used machine learning to classify sagittal and vertical skeletal discrepancies in 3D facial scans [58]. The one remaining study investigated landmark identification for initial orthodontic diagnosis using a moving 3dMD face camera system, which captured 3D facial scans with recorded motions, enabling the analysis of dynamic facial expressions [29].
Table 2.
Summary of the findings regarding the use of 3D photogrammetry in orthodontic problem finding.
3.4. Orthodontic Treatment Optimization
Ten studies were included regarding treatment optimization (Table 3). Three-dimensional photogrammetry can be used to facilitate the manufacturing of appliances, continuous monitoring of the treatment’s progress or favoring treatment planning and patient communication. One of them focused on the use of 3D facial scanning on the manufacturing of a fully digital protraction facemask [30] and another three were about the continuous monitoring of facial changes during or after orthodontic treatment at fixed intervals [31,32,33]. One of the studies focused on the creation of virtual patients using a facial scan, an intraoral scan with a low-dose computed tomography that is based on artificial intelligence, which was assessed for its realism and usefulness for treatment planning and communication [34]. In addition to virtual patient creation, 3D facial scanning is an effective communication tool for facial aesthetic evaluation. Ponnusamy A et al. demonstrated this by using a generated 3D average face to assess perceptions of attractiveness among both dental professionals and laypersons [35]. Based on the 3D average face, different facial component such as face length, pogonion point, cheek volume or protraction of upper face can be modified to demonstrate the expected treatment outcome for better patient communication or facial aesthetic evaluation [36,37,38,59]. Berends, B. et al. developed a deep learning-based method to predict postoperative facial soft tissue outcomes following orthognathic surgery, which can not only improve treatment outcome, but also enhance communication between patients and orthodontists [60].
Table 3.
Summary of the findings regarding the use of 3D photogrammetry in orthodontic treatment optimization.
3.5. Treatment Outcome Evaluation
3D photogrammetry was commonly used to evaluate soft tissue changes after orthodontic treatments, both objectively and subjectively (Table 4). A total of twenty-seven studies were included regarding post-operative evaluation for orthodontic treatment [27,31,32,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,61,62,63,64,65,66]. Four studies reported subjective evaluation on post-operative facial attractiveness [39,40,62,63]. Other than subjective evaluation, the remaining included studies showed an objective outcome evaluation based on 3D photogrammetry, adopting different methods [27,31,32,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,61,64,65,66]. Twelve of them marked landmarks on the facial scan and directly measured and compared pre-operative and post-operative linear, angular, volumetric or ratio measurements [31,32,41,42,43,44,45,46,47,64,65,66]. Four of them marked specific landmarks and aligned pre- and post-operative face scans using a best-fit approach for 3D space deviation analysis to quantify volumetric changes [48,49,50,66]. Eight of them perform superimposition of two scans with or without a color-coded map for positive or negative change for post-operative evaluation [27,51,52,53,54,55,56,61].
Table 4.
Summary of the findings regarding the use of 3D photogrammetry in post-operative outcome evaluation.
4. Discussion
Three-dimensional photogrammetry has emerged as a transformative technology in orthodontics, enabling precise craniofacial analysis across multiple clinical domains. As indicated by this scoping review summarizing the latest five years of the literature, one of the most common applications of 3D photogrammetry lies in normative facial anthropometry, where the soft tissue measurement is elevated to 3D level, providing a more comprehensive and accurate assessment compared to traditional 2D measurements. It facilitates the creation of population-specific reference datasets for facial soft tissues, allowing clinicians to quantify deviations in symmetry, proportions, and growth patterns with high accuracy and zero radiation exposure [17,18,19]. Similarly, 3D photogrammetry excels in diagnosis by providing detailed 3D quantification of facial morphology (e.g., skeletal discrepancies, lip incompetence, asymmetry) through landmark identification and spatial analysis of scans. Moreover, it is often integrated with CBCT for comprehensive hard/soft tissue evaluation [22,28,67]. Treatment outcome evaluation was another well-validated use case, leveraging superimposition and color-mapped deviation analysis to objectively measure surgical or orthodontic outcomes (e.g., changes in lip volume, mandibular position, or asymmetry). This makes the evaluation of the treatment outcome more intuitive, thereby enhancing the communication between healthcare providers and patients [41,52,54]. Three-dimensional photogrammetry also plays a role in treatment optimization. While studies demonstrate promise in simulating aesthetic outcomes (e.g., virtual modifications of chin asymmetry, lip volume) and integrating scans for digital treatment planning [34,36,37], these applications face limitations in standardization and clinical integration. Overall, 3D photogrammetry significantly enhances the accuracy and efficiency of orthodontic assessment in established domains like anthropometry, diagnosis, and outcome tracking, etc., though its full potential in aesthetic-driven planning and workflow optimization requires further validation and technological refinement.
Benefit from 3D photogrammetry, the creation of a digital “virtual patient” is a transformative concept, moving beyond static records to a dynamic model central to modern care. This model begins with the establishment of normative databases. By aligning numerous scans using software like Rapidform and MeshLab, studies generate population-specific average faces that provide a quantitative baseline for diagnosing asymmetry and ethnic variations [14,15,16,20]. Beyond diagnosis, the virtual patient profoundly enhances treatment communication and aesthetic evaluation. The ability to digitally modify facial components—such as adjusting chin position or cheek volume on a 3D scan—allows patients to visualize potential outcomes, transforming subjective discussions into evidence-based conversations [35,36,38]. The most advanced application involves fully integrated treatment optimization, where facial scans were merged with intraoral and CBCT data to create a comprehensive digital twin. This enables the simulation of hard tissue movements, and their soft tissue impacts before treatment begins, which can be further advanced by deep learning algorithms that can predict postoperative outcomes [34,60].
Complementing 3D photogrammetry’s clinical utility is the pivotal role of specialized software and algorithms. The value of this technology is realized through tools that automate and enhance analysis. Software toolkits like MeshMonk enable automated landmarking and spatially dense geometric morphometrics, facilitating the detection of subtle asymmetries and complex morphological changes over time without manual subjectivity [21,33]. This capability extends to diagnosis, where machine learning models can classify skeletal discrepancies directly from 3D facial scans [58]. Furthermore, bespoke algorithms are being designed for specific orthodontic tasks. These include constructing mathematically derived symmetry reference planes for objective asymmetry assessment and performing best-fit superimposition of sequential scans to generate color-coded deviation maps [24,52,55]. These maps provide an intuitive, quantitative visual assessment of treatment progress, objectively measuring the efficacy of interventions.
Despite its capabilities, there are several limitations and areas for development in 3D photogrammetry that warrant consideration. A primary challenge lies in the lack of standardization and methodological heterogeneity. As evidenced by the wide array of software tools and techniques used across the reviewed studies (e.g., MeshMonk, Geomagic, Rapidform), there is no consensus on a universal protocol for landmark identification, mesh alignment, or asymmetry analysis. This variability may undermine the reproducibility of measurements and complicates the comparison of results across different studies and clinical settings. Reconstruction algorithms should also be improved to further enhance geometric fidelity, especially in capturing complex contours like the alar base or labiomental fold. Similarly, automated landmarking and classification systems for pathologies or facial types need to be trained on larger, more diverse datasets to improve their accuracy and clinical utility. The review also identifies a notable gap in the validation of advanced applications, particularly the “virtual patient” concept and dynamic (4D) capture. While studies like Jindanil et al. [34] demonstrate the technical feasibility of integrating multimodal scans, the clinical accuracy, workflow efficiency, and predictive power of these digital twins for comprehensive treatment simulation remain under-studied. Crucially, the reliability of soft-tissue predictions based on underlying skeletal movements, even with advanced AI as attempted by Berends et al. [60], is not yet fully established and demands extensive longitudinal validation. Similarly, the potential of 4D photogrammetry to assess functional movements is almost entirely unexplored, with only a single study by Coppola et al. [29] focusing on technical accuracy rather than clinical application for mastication or speech analysis.
This scoping review has several inherent methodological limitations that should be considered when interpreting the findings. First, consistent with the objective of mapping the breadth of evidence, we did not perform a formal quality appraisal or risk-of-bias assessment of the included studies. While this review successfully catalogs the diverse applications of 3D photogrammetry, it cannot make definitive conclusions regarding the efficacy, reliability, or accuracy of the reported techniques. The findings represent the scope of research activity rather than a synthesis of validated clinical outcomes. The literature search was conducted in three major databases (PubMed, Web of Science, Embase) to capture the core peer-reviewed literature. It is possible that relevant studies indexed in other databases (e.g., Scopus, Google Scholar) were missed, introducing a potential for selection bias. Finally, the narrative synthesis approach, while appropriate for the research question, precludes statistical pooling of data. Therefore, this review provides a comprehensive overview of the field’s landscape but does not offer depth on specific clinical outcomes, a task that would require a subsequent systematic review with meta-analysis.
5. Conclusions
Three-dimensional photogrammetry represents a paradigm shift in orthodontic practice, safety, and versatility in normative anthropometry, orthodontic diagnosis, simulating and evaluating treatment outcomes. As this technology evolves, its integration into orthodontic workflows helps to advance both functional precision and aesthetic harmony, ensuring treatments align with cultural ideals, and patient expectations. Future research should focus on standardizing landmark protocols, expanding population-specific databases, and integrating artificial intelligence to further automate and refine predictive simulations, solidifying 3D photogrammetry as a cornerstone of modern orthodontics.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/bioengineering12111263/s1, Table S1: Search strategies of each database and number of results for first round search; Table S2: Search strategies of each database and number of results for second round search.
Author Contributions
Conceptualization, P.K.H., J.L. and Z.S.; methodology P.K.H. and J.L.; writing—original draft preparation, P.K.H.; writing—review and editing, P.K.H. and J.L.; supervision, Z.S. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in the study are included in the article, further inquiries can be directed to the corresponding author.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| 2D | Two-dimensional |
| 3D | Three-dimensional |
| CBCT | Cone beam computed tomography |
| PRISMA-ScR | Systematic Reviews and Meta-Analyses extension for Scoping Reviews |
| IT | Imaging tools |
| S | Software |
References
- Gao, P.C.; Zhao, Z.Q.; Chen, Y.L.; Zhao, Y.; Xie, L.Z.; Yan, B.; Wang, L. Accuracy of three-dimensional camera system based on stereophotography on photographic acquisition of deformity facial images. Hua Xi Kou Qiang Yi Xue Za Zhi 2019, 37, 174–179. [Google Scholar]
- Aljawad, H.; Lim, H.J.; Lee, K.C. Anthropometric Comparison of 3-Dimensional Facial Scan Taken with a Low-Cost Facial Scanner with Cone-Beam Computed Tomography Scan. J. Craniofac. Surg. 2023, 34, 1456–1458. [Google Scholar] [CrossRef] [Scilit]
- Gašparović, B.; Morelato, L.; Lenac, K.; Mauša, G.; Zhurov, A.; Katić, V. Comparing Direct Measurements and Three-Dimensional (3D) Scans for Evaluating Facial Soft Tissue. Sensors 2023, 23, 2412. [Google Scholar] [CrossRef] [Scilit]
- Spalj, S.; Slaj, M.; Varga, S.; Strujic, M.; Slaj, M. Perception of orthodontic treatment need in children and adolescents. Eur. J. Orthod. 2010, 32, 387–394. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Angelieri, F.; Cevidanes, L.H.; Franchi, L.; Gonçalves, J.R.; Benavides, E.; McNamara, J.A., Jr. Midpalatal suture maturation: Classification method for individual assessment before rapid maxillary expansion. Am. J. Orthod. Dentofac. Orthop. 2013, 144, 759–769. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kau, C.H.; Richmond, S.; Incrapera, A.; English, J.; Xia, J.J. Three-dimensional surface acquisition systems for the study of facial morphology and their application to maxillofacial surgery. Int. J. Med. Robot. 2007, 3, 97–110. [Google Scholar] [CrossRef] [Scilit]
- Doan, J.; Finlay, N.; Lee, A.; Ethell, T.; Gandedkar, N.; Darendeliler, M.A. The accuracy (trueness and precision) of Bellus3DARC-7 and an in-vivo analysis of intra and inter-examiner reliability of digital and manual anthropometry. Aust. Orthod. J. 2023, 39, 141–157. [Google Scholar] [CrossRef] [Scilit]
- Andrews, J.; Alwafi, A.; Bichu, Y.M.; Pliska, B.T.; Mostafa, N.; Zou, B. Validation of three-dimensional facial imaging captured with smartphone-based photogrammetry application in comparison to stereophotogrammetry system. Heliyon 2023, 9, e15834. [Google Scholar] [CrossRef] [Scilit]
- Barone, S.; Antonelli, A.; Salviati, M.; Greco, V.; Bennardo, F.; Becker, K.; Giudice, A.; Simeone, M. Accuracy Assessment of EM3D App-Based 3D Facial Scanning Compared to Cone Beam Computed Tomography. Dent. J. 2024, 12, 342. [Google Scholar] [CrossRef] [Scilit]
- Pellitteri, F.; Scisciola, F.; Cremonini, F.; Baciliero, M.; Lombardo, L. Accuracy of 3D facial scans: A comparison of three different scanning system in an in vivo study. Prog. Orthod. 2023, 24, 44. [Google Scholar] [CrossRef] [Scilit]
- Mao, B.; Li, J.; Tian, Y.; Zhou, Y. The accuracy of a three-dimensional face model reconstructing method based on conventional clinical two-dimensional photos. BMC Oral. Health 2022, 22, 413. [Google Scholar] [CrossRef] [Scilit]
- Pan, F.; Liu, J.; Cen, Y.; Chen, Y.; Cai, R.; Zhao, Z.; Liao, W.; Wang, J. Accuracy of RGB-D camera-based and stereophotogrammetric facial scanners: A comparative study. J. Dent. 2022, 127, 104302. [Google Scholar] [CrossRef] [Scilit]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit]
- Bhaskar, E.; Kau, C.H. A Comparison of 3D Facial Features in a Population from Zimbabwe and United States. Eur. J. Dent. 2020, 14, 100–106. [Google Scholar] [CrossRef] [Scilit]
- Kau, C.H.; Wang, J.; Davis, M. A Cross-Sectional Study to Understand 3D Facial Differences in a Population of African Americans and Caucasians. Eur. J. Dent. 2019, 13, 485–496. [Google Scholar] [CrossRef] [Scilit]
- Rajbhoj, A.A.; Matthews, H.; Doucet, K.; Claes, P.; Willems, G.; Begnoni, G.; Cadenas de Llano-Pérula, M. Age- and sex-related differences in 3D facial shape and muscle pressure in subjects with normal occlusion. Comput. Biol. Med. 2022, 151, 106325. [Google Scholar] [CrossRef] [Scilit]
- Mengoa, M.G.R.; Garcia, A.; Fioravanti, K.S.; Neppelenbroek, K.H.; Oliveira, T.M.; Sforza, C.; Soares, S. Facial morphology analysis of Caucasian Brazilian adult women using stereophotogrammetry. Braz. Oral. Res. 2024, 38, e105. [Google Scholar] [PubMed]
- Cenzato, N.; Farronato, M.; Tartaglia, F.C.; Giannini, L.; Inchingolo, A.M.; Dipalma, G.; Maspero, C.; Inchingolo, F. Soft Tissue Facial Morphology in Growing Patients with Different Occlusal Classes. J. Pers. Med. 2024, 14, 1042. [Google Scholar] [CrossRef] [Scilit]
- Menéndez López-Mateos, M.L.; Carreño-Carreño, J.; Palma, J.C.; Alarcón, J.A.; Menéndez López-Mateos, C.; Menéndez-Núñez, M. Three-dimensional photographic analysis of the face in European adults from southern Spain with normal occlusion: Reference anthropometric measurements. BMC Oral. Health 2019, 19, 196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tanikawa, C.; Akcam, M.O.; Takada, K. Quantifying faces three-dimensionally in orthodontic practice. J. Craniomaxillofac. Surg. 2019, 47, 867–875. [Google Scholar] [CrossRef] [Scilit]
- Fan, Y.; He, W.; Chen, G.; Song, G.; Matthews, H.; Claes, P.; Jiang, R.; Xu, T. Facial asymmetry assessment in skeletal Class III patients with spatially-dense geometric morphometrics. Eur. J. Orthod. 2022, 44, 155–162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gkantidis, N.; Opacic, J.; Kanavakis, G.; Katsaros, C.; Halazonetis, D. Facial asymmetry and midsagittal plane definition in 3D: A bias-free, automated method. PLoS ONE 2023, 18, e0294528. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lyu, L.; Zhang, M.J.; Wen, A.N.; Wang, S.; Zhao, Y.J.; Yong, W.; Yu, T.T.; Liu, D. 3D facial mask for facial asymmetry diagnosis. Heliyon 2024, 10, e26734. [Google Scholar] [CrossRef] [Scilit]
- Zhu, Y.; Fu, X.; Zhang, L.; Zheng, S.; Wen, A.; Xiao, N.; Wang, Y.; Zhao, Y. A mathematical algorithm of the facial symmetry plane: Application to mandibular deformity 3D facial data. J. Anat. 2022, 240, 556–566. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dindaroğlu, F.; Fırıncıoğulları, E.C.; Duran, G.S. Three-dimensional evaluation of social smile asymmetry in patients with unilateral impacted maxillary canine: A 3D stereophotogrammetry study. Clin. Oral. Investig. 2023, 27, 6915–6924. [Google Scholar] [CrossRef] [Scilit]
- Li, H.; Cao, T.; Zhou, H.; Hou, Y. Lip position analysis of young women with different skeletal patterns during posed smiling using 3-dimensional stereophotogrammetry. Am. J. Orthod. Dentofac. Orthop. 2019, 155, 64–70. [Google Scholar] [CrossRef] [Scilit]
- Cho, S.W.; Byun, S.H.; Yi, S.; Jang, W.S.; Kim, J.C.; Park, I.Y.; Yang, B.E. Sagittal Relationship between the Maxillary Central Incisors and the Forehead in Digital Twins of Korean Adult Females. J. Pers. Med. 2021, 11, 203. [Google Scholar] [CrossRef] [Scilit]
- Wang, T.; Nie, K.; Fan, Y.; Chen, G.; Xu, K.; Han, B.; Pei, Y.; Song, G.; Xu, T. Network analysis of three-dimensional hard-soft tissue relationships in the lower 1/3 of the face: Skeletal Class I-normodivergent malocclusion versus Class II-hyperdivergent malocclusion. BMC Oral. Health 2024, 24, 996. [Google Scholar] [CrossRef] [Scilit]
- Coppola, G.; Hänggi, D.; Cassina, G.; Verna, C.; Gkantidis, N.; Kanavakis, G. Three-dimensional video recordings: Accuracy, reliability, clinical and research guidelines—Reliability assessment of a 4D camera. Orthod. Craniofac. Res. 2024, 27, 803–812. [Google Scholar] [CrossRef] [Scilit]
- Fiorillo, G.; Garrisi, L.; Mandelli, A.; Arnò, F.; Mandelli, G.; Gastaldi, G. Design and manufacturing of a fully digital protraction facemask. AJO-DO Clin. Companion 2024, 4, 165–173. [Google Scholar] [CrossRef] [Scilit]
- Akan, B.; Veli, İ. Evaluation of soft-tissue changes in young adults treated with the Forsus fatigue-resistant device. Am. J. Orthod. Dentofac. Orthop. 2020, 157, 481–489.e482. [Google Scholar] [CrossRef] [Scilit]
- Yüksel Coşkun, E.; Esenlik, E. A Prospective Study Comparing Adolescent and Post-Adolescent Periods Regarding Effects of Activator Appliance in Patients with Class II Mandibular Retrognathia by Using 3dMDface Analysis and Cephalometry. Med. Sci. Monit. 2020, 26, e921401. [Google Scholar] [CrossRef] [Scilit]
- Hou, S.Y.; Zhou, W.; Dai, H.; Wong, H.M.; Wen, Y.F.; Zhou, J. Soft tissue facial changes among adult females during alignment stage of orthodontic treatment: A 3D geometric morphometric study. BMC Oral. Health 2021, 21, 57. [Google Scholar] [CrossRef] [Scilit]
- Jindanil, T.; Burlacu-Vatamanu, O.E.; Meyns, J.; Meewis, J.; Fontenele, R.C.; Perula, M.C.L.; Jacobs, R. Automated orofacial virtual patient creation: A proof of concept. J. Dent. 2024, 150, 105387. [Google Scholar] [CrossRef] [Scilit]
- Ponnusamy, A.; Goonewardene, M.S.; Mian, A.; Eastwood, P.; Rea, A.; Islam, S. Facial soft tissue norms in Caucasians using an innovative three-dimensional approach. Australas. Orthod. J. 2020, 36, 45–54. [Google Scholar] [CrossRef] [Scilit]
- Dong, T.; Ye, N.; Yuan, L.; Wu, S.; Xia, L.; Fang, B. Assessing the Influence of Chin Asymmetry on Perceived Facial Esthetics with 3-Dimensional Images. J. Oral. Maxillofac. Surg. 2020, 78, 1389–1396. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fastuca, R.; Beccarini, T.; Rossi, O.; Zecca, P.A.; Caprioglio, A. Influence of facial components in class III malocclusion esthetic perception of orthodontists, patients, and laypersons. J. Orofac. Orthop. 2022, 83, 48–58. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Feng, J.; Yu, H.; Yin, Y.; Yan, Y.; Wang, Z.; Bai, D.; Han, X. Esthetic evaluation of facial cheek volume: A study using 3D stereophotogrammetry. Angle Orthod. 2019, 89, 129–137. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Denadai, R.; Chou, P.Y.; Su, Y.Y.; Lin, H.H.; Ho, C.T.; Lo, L.J. The Impacts of Orthognathic Surgery on the Facial Appearance and Age Perception of Patients Presenting Skeletal Class III Deformity: An Outcome Study Using the FACE-Q Report and Surgical Professional-Based Panel Assessment. Plast. Reconstr. Surg. 2020, 145, 1035–1046. [Google Scholar] [CrossRef] [Scilit]
- Denadai, R.; Chou, P.Y.; Su, Y.Y.; Lo, C.C.; Lin, H.H.; Ho, C.T.; Lo, L.J. Facial Appearance and Psychosocial Features in Orthognathic Surgery: A FACE-Q- and 3D Facial Image-Based Comparative Study of Patient-, Clinician-, and Lay-Observer-Reported Outcomes. J. Clin. Med. 2019, 8, 909. [Google Scholar] [CrossRef] [Scilit]
- Güler, Ö.; Malkoç, S. Comparison of facial soft tissue changes after treatment with 3 different functional appliances. Am. J. Orthod. Dentofac. Orthop. 2020, 158, 518–526. [Google Scholar] [CrossRef] [Scilit]
- Akan, B.; Gökçe, G.; Şahan, A.O.; Veli, İ. Tooth-borne versus tooth-bone-borne rapid maxillary expanders according to a stereophotogrammetric evaluation of facial soft tissues: A randomized clinical trial. Orthod. Craniofac. Res. 2021, 24, 438–448. [Google Scholar] [CrossRef] [Scilit]
- Liu, Z.Y.; Yu, J.; Dai, F.F.; Jiang, R.P.; Xu, T.M. Three-dimensional changes in lip vermilion morphology of adult female patients after extraction and non-extraction orthodontic treatment. Korean J. Orthod. 2019, 49, 222–234. [Google Scholar] [CrossRef] [Scilit]
- Marino Merlo, M.; Quiroga Souki, B.; Nieri, M.; Bonanno, A.; Giuntini, V.; McNamara, J.A., Jr.; Franchi, L. Comparison of the effects on facial soft tissues produced by rapid and slow maxillary expansion using stereophotogrammetry: A randomized clinical trial. Prog. Orthod. 2024, 25, 1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sitaropoulou, V.; Yilmaz, H.N.; Yilmaz, B.; Kucukkeles, N. Three-dimensional evaluation of treatment results of the Alt-RAMEC and facemask protocol in growing patients. J. Orofac. Orthop. 2020, 81, 407–418. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nike, E.; Radzins, O.; Pirttiniemi, P.; Vuollo, V.; Slaidina, A.; Abeltins, A. Evaluation of facial soft tissue asymmetric changes in Class III patients after orthognathic surgery using three-dimensional stereophotogrammetry. Int. J. Oral. Maxillofac. Surg. 2023, 52, 361–370. [Google Scholar] [CrossRef] [Scilit]
- Shi, Y.; Liu, S.; Shao, X.; Zong, C.; Bai, S.; Yang, Y.; Liu, Y.; Shang, H.; Tian, L. Facial changes in patients with skeletal class III deformity after bimaxillary surgery: An evaluation based on three-dimensional photographs registered with computed tomography. Br. J. Oral. Maxillofac. Surg. 2022, 60, 1404–1410. [Google Scholar] [CrossRef] [Scilit]
- Mao, B.; Tian, Y.; Li, J.; Zhou, Y.; Wang, X. A quantitative analysis of facial changes after orthodontic treatment with vertical control in patients with idiopathic condylar resorption. Orthod. Craniofac. Res. 2023, 26, 402–414. [Google Scholar] [CrossRef] [Scilit]
- Alkhayer, A.; Becsei, R.; Hegedűs, L.; Párkányi, L.; Piffkó, J.; Braunitzer, G.; Segatto, E. Evaluation of the Soft Tissue Changes after Rapid Maxillary Expansion Using a Handheld Three-Dimensional Scanner: A Prospective Study. Int. J. Environ. Res. Public Health 2021, 18, 3379. [Google Scholar] [CrossRef] [Scilit]
- Shen, L.H.; Xie, T.Y.; Jiang, R.P.; Jiang, Y.R.; Chen, G.; Xu, T.M.; Han, B. Measurement of three-dimensional changes in lip vermilion in adult female patients after orthodontic extraction: A retrospective longitudinal study. Head Face Med. 2021, 17, 9. [Google Scholar] [CrossRef] [Scilit]
- Da Pozzo, F.; Gibelli, D.; Beltramini, G.A.; Dolci, C.; Giannì, A.B.; Sforza, C. The Effect of Orthognathic Surgery on Soft-Tissue Facial Asymmetry: A Longitudinal Three-Dimensional Analysis. J. Craniofac. Surg. 2020, 31, 1578–1582. [Google Scholar] [CrossRef] [Scilit]
- Chen, Y.H.; Baan, F.; Bruggink, R.; Ko, E.W.; Bergé, S.; Xi, T. Clockwise versus counterclockwise rotation in bimaxillary surgery: 3D analysis of facial soft tissue outcomes. Oral. Maxillofac. Surg. 2024, 28, 693–703. [Google Scholar] [CrossRef] [Scilit]
- Keardkhong, P.; Chen, Y.F.; Yao, C.F.; Chen, Y.A.; Liao, Y.F.; Chen, Y.R. Comparison of regional soft tissue changes after bimaxillary rotational surgery between class III deformity with overbite and open bite: A 3D imaging analysis. Biomed. J. 2023, 46, 100562. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, K.A.; Chang, Y.J.; Lee, S.H.; An, H.J.; Park, K.H. Three-dimensional soft tissue changes according to skeletal changes after mandibular setback surgery by using cone-beam computed tomography and a structured light scanner. Prog. Orthod. 2019, 20, 25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rongo, R.; Nissen, L.; Leroy, C.; Michelotti, A.; Cattaneo, P.M.; Cornelis, M.A. Three-dimensional soft tissue changes in orthodontic extraction and non-extraction patients: A prospective study. Orthod. Craniofac. Res. 2021, 24 (Suppl. S2), 181–192. [Google Scholar] [CrossRef] [Scilit]
- Choi, T.H.; Kim, S.H.; Yun, P.Y.; Kim, Y.K.; Lee, N.K. Soft Tissue Changes After Clockwise Rotation of Maxillo-Mandibular Complex in Class III Patients: Three-Dimensional Stereophotogrammetric Evaluation. J. Craniofac. Surg. 2021, 32, 612–615. [Google Scholar] [CrossRef] [Scilit]
- Yang, G.; Lyu, L.; Wen, A.; Zhao, Y.; Wang, Y.; Li, J.; Yan, H.; Zhang, M.; Yu, Y.; Yu, T.; et al. Comparison of Mirroring and Overlapping Analysis and Three-Dimensional Soft Tissue Spatial Angle Wireframe Template in Evaluating Facial Asymmetry. Bioengineering 2025, 12, 79. [Google Scholar] [CrossRef] [Scilit]
- Mao, B.; Tian, Y.; Xiao, Y.; Li, J.; Zhou, Y.; Wang, X. Classification of skeletal discrepancies by machine learning based on three-dimensional facial scans. Int. J. Oral. Maxillofac. Surg. 2025, 54, 747–756. [Google Scholar] [CrossRef] [Scilit]
- Nguyen, K.T.; Farella, M.; Bennani, V.; Mei, L. Effect of Biomechanical Properties of Perioral Soft Tissues on Lip Response to Simulated Protraction of Upper Front Teeth. J. Oral. Rehabil. 2025, 52, 632–640. [Google Scholar] [CrossRef] [Scilit]
- Berends, B.; Bielevelt, F.; Baan, F.; Schreurs, R.; Maal, T.; Xi, T.; de Jong, G. Soft-tissue prediction based on 3D photographs for virtual surgery planning of orthognathic surgery. Comput. Biol. Med. 2025, 194, 110529. [Google Scholar] [CrossRef] [Scilit]
- Simões, J.C.M.; Garcia, D.M.; De Mello-Filho, F.V.; De Felício, C.M.; Trawitzki, L.V.V. Masticatory function and three-dimensional facial morphology of soft tissues: One year after orthognathic surgery. Arch. Oral. Biol. 2025, 169, 106103. [Google Scholar] [CrossRef] [Scilit]
- Chiang, W.C.; Chen, H.L.; Lin, H.H. Automated 3D facial smile attractiveness assessment before and after orthognathic surgery using transfer learning: A preliminary study. J. Plast. Reconstr. Aesthet. Surg. 2025, 106, 193–202. [Google Scholar] [CrossRef] [Scilit]
- Hu, J.; Wang, C.; Li, Q. Characteristics of skeletal Class II adolescents with favorable facial attractiveness outcomes based on 3D photos after Twin-block treatment. J. Stomatol. Oral. Maxillofac. Surg. 2025, 126, 102310. [Google Scholar] [CrossRef] [Scilit]
- Molla, N.; Oh, H.; Heo, G.; Catunda, R.; Lagravère, M. Comparison of soft tissue facial changes in patients 7–11 years of age with and without maxillary expansion utilizing CBCTs and 3D facial scans: A preliminary study. Int. Orthod. 2025, 23, 100998. [Google Scholar] [CrossRef] [Scilit]
- Nike, E.; Radzins, O.; Vuollo, V.; Slaidina, A.; Abeltins, A. Changes in Facial Soft Tissue Asymmetry in Class II Patients One Year After Orthognathic Surgery. J. Clin. Med. 2025, 14, 2912. [Google Scholar] [CrossRef] [Scilit]
- Pellitteri, F.; Albertini, P.; Brucculeri, L.; Cremonini, F.; Guiducci, D.; Falconi, V.; Lombardo, L. Soft tissue changes during orthopedic therapy: An in vivo 3-dimensional facial scan study. Am. J. Orthod. Dentofac. Orthop. 2025, 167, 154–165. [Google Scholar] [CrossRef] [Scilit]
- Kwon, S.M.; Hwang, J.J.; Jung, Y.H.; Cho, B.H.; Lee, K.J.; Hwang, C.J.; Choi, S.H. Similarity index for intuitive assessment of three-dimensional facial asymmetry. Sci. Rep. 2019, 9, 10959. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).