


Abstract
Artificial Intelligence (AI) is transforming the healthcare field, offering innovative tools for improving the prediction, detection, and management of diseases. In nephrology, AI holds the potential to improve the diagnosis and treatment of kidney diseases, as well as the optimization of renal replacement therapies. In this review, a comprehensive analysis of recent literature works on artificial intelligence applied to nephrology is presented. Two key research areas structure this review. The first section examines AI models used to support early prediction of acute and chronic kidney disease. The second section explores artificial intelligence applications for hemodialytic therapies in renal insufficiency. Most studies reported high accuracy (e.g., accuracy ≥ 90%) in early prediction of kidney diseases, while fewer addressed therapy optimization and complication prevention, typically reporting moderate-to-high performance (e.g., accuracy ≃ 85%). Filling this gap and developing more accessible AI solutions that address all stages of kidney disease would therefore be crucial to support physicians’ decision-making and improve patient care.
1. Introduction
1.1. Artificial Intelligence
Artificial Intelligence is a discipline that focuses on creating an intelligent system able to perform tasks that require human intelligence, such as reasoning, planning, and natural language understanding, through the use of algorithms and logical models, without needing to learn from data [1].
AI uses a variety of techniques and approaches to achieve these capabilities. Some systems rely on simple rules and logic, while others use more advanced algorithms that allow them to learn and adapt over time. This versatility allows AI to be applied in many different domains and industries, making it a powerful tool for improving productivity and innovation.
There are, in fact, several subcategories of artificial intelligence, each capable of using a different method to achieve intelligent behavior [2], and the main ones are the following.
Machine Learning (ML) focuses specifically on the ability of machines to learn from data and improve their performance over time without being explicitly programmed.
Rules-based Systems use predefined rules to make decisions or solve problems. They operate based on specific logic and are often used in expert systems to mimic human decision-making in specific domains.
Natural Language Processing (NLP) focuses on enabling machines to understand, interpret, and respond to human language. Applications include chatbots, translation services, and voice recognition systems.
Computer Vision allows computers to interpret and understand visual information from the world, such as images and videos. It is used in applications like facial recognition, autonomous vehicles, and medical imaging.
Robotics involves creating intelligent machines that can perform tasks in the physical world. This includes everything from industrial robots to drones and service robots.
Planning and Decision-Making focuses on developing algorithms that help systems make decisions based on available information. This includes optimization problems, game theory, and multi-agent systems.
Expert Systems are computer programs that simulate the judgment and behavior of a human or an organization with expertise in a particular area. They are designed to solve complex problems by reasoning through bodies of knowledge.
Fuzzy Logic Systems allow for degrees of truth unlike traditional binary sets (true/false). This approach is useful in systems that require a more nuanced understanding of data, like control systems in appliances.
1.2. Machine Learning and Deep Learning
The main subcategory of Artificial Intelligence is Machine Learning, which is based on the concept of self-learning.
To implement an ML model successfully, three key components are required: a training dataset, a learning model capable of approximating the behavior of the system to be predicted, and a validation and/or testing dataset.
Specifically, an ML model is a data learning system. To train the model, a dataset containing examples of the problem to be solved must be provided. The model tries to understand the relationships among the data and modifies its parameters so that its predictions align as closely as possible with the training data.
Once trained, the model can be used to make predictions on new data. The effectiveness of a model is evaluated using new validation or test data, which are not used during training. This leads to the creation of very efficient tools capable of making predictions or decisions on new data, often faster and more accurately than traditional models, which often present limitations on particularly complex systems.
Among the most promising models used in ML, deep Artificial Neural Networks (ANNs) have given rise to a further subdiscipline called Deep Learning (DL). An artificial neural network is an adaptive system that learns by using at least two layers of interconnected nodes, which mimic the human neurons. The strength of these interactions is determined by their so-called “weights”. The greater the weight, the more important the contribution of that connection to the output. An important component of the learning process in an artificial neural network is gradient descent. This algorithm optimizes the weights of the connections between nodes during the training process. Essentially, gradient descent seeks to minimize the error between the network’s predictions and the desired outcomes by iteratively updating the weights based on the direction and magnitude of the gradient of the cost function. The cost function quantifies the difference between the predicted outputs of the network and the actual target values, serving as a measure of how well the model is performing. In practice, gradient descent allows the ANN to “learn” from data: starting from randomly initialized weights, the model progressively adapts, improving its performance in recognizing patterns, classifying data, and predicting future events without requiring human intervention [3].
Typical non-strictly deep ANNs are Bayesian Neural Networks (BNNs), machine learning models that, instead of having fixed weights, represent the weights as probabilistic distributions, making it possible to manage and quantify uncertainty in situations where it is an important factor, such as in medicine, robotics, and finance [4]. If ANNs contain at least three layers, they can be classified as “deep”, capable of modeling more complex relationships. In the rest of this paper, we will use the term “Neural Networks” (NNs) to refer to networks belonging to the “deep” field, and the global name of AI to collectively denote artificial intelligence, machine learning, and deep learning, despite the differences between all these approaches.
Since the last century, the use of artificial intelligence techniques has interested many areas, ranging from business to tourism, from telecommunications to health care [5,6,7,8].
Specifically, the use of AI in healthcare dates back to the 1960s, when the growing potential offered by advanced computational techniques made it possible to automate the interpretation of ElectroCardioGrams (ECGs) for the diagnosis of cardiovascular diseases [6]. Despite the initial enthusiasm, the use of artificial intelligence tools in the medical field remained “dormant” until the 1970s, when Gagliardo et al. [7] applied multilinear regression to predict cell-mediated immune reactivity to tumor antigens [8] using a dataset previously analyzed by Heppner et al. [9]. Early expert systems were also developed, including PIP, which modeled disease states in edema patients [10], and MYCIN, designed to suggest antibiotic therapy for bacteremia [8].
All these applications showed the benefit that could be derived from an accurate model that allows for predicting the result even in circumstances in which a particular experiment is not performed, as in the second case, or to stimulate further refinement of the evolving cognitive theory on a given pathology, as in the last two.
It is important to emphasize that, beyond technical performance, the successful integration of AI into clinical workflows requires addressing key issues such as algorithm transparency, data privacy, fairness, and ethical responsibility. These aspects are crucial to ensure patient safety, build clinicians’ trust, comply with regulatory standards, and achieve real clinical impact.
It is encouraging that researchers have devoted increasing attention to these issues in recent years, promoting the growing use of artificial intelligence techniques in the biomedical field to the present day. An example is the increasing use of AI in the study of kidney disease and its application to renal replacement therapies.
1.3. Kidney Diseases and Treatments
Kidney Diseases (KDs) can be divided into two main groups:
- (i).
- Acute Kidney Injury (AKI) refers to a kidney malfunction characterized by rapid deterioration of its functions. Generally, AKI causes renal dysfunction in patients already suffering from other diseases, only for short periods. Despite its reversibility, an incomplete recovery can lead to the terminal stages of the disease and, though not commonly, to death.
- (ii).
- Chronic Kidney Disease (CKD) refers to sustained kidney malfunction related to the presence of structural or functional abnormalities. CKD is stated when a reduction in the so-called “estimated Glomerular Filtration Rate” (eGFR) lasts for three months or more [11]. Chronic kidney disease is very common in patients with diabetes and hypertension and can lead to death. Specifically, eGFR is the best index for kidney function as it measures the kidneys’ ability to filter toxins and waste from the blood. Dialysis treatment or a kidney transplant is required when eGFR is very low. Equation (1) shows the Cockcroft–Gault law for the eGFR calculation [12]:
Chronic kidney disease is one of the leading causes of death in the 21st century, since to date it affects more than 800 million individuals worldwide, with a significant increase in deaths over the past two decades [13]. Despite receiving treatment, CKD patients often experience overlapping episodes of AKI, as this condition is frequently triggered by the use of medication or the presence of previous diseases [14]. Therefore, early detection of chronic kidney disease and its prevention can be crucial to avoid further complications.
There are five levels of CKD, the last of which is called “End-Stage Kidney Disease” (ESKD). The state of progressive loss of kidney function caused by this condition results in the need for renal replacement therapy, such as HemoDialysis (HD) or transplantation, to ensure patients’ survival. Specifically, standard hemodialysis is a process based on the use of a semi-permeable membrane with a hollow fiber configuration. The solute removal through the membrane takes place by means of a diffusive mechanism from the blood to a dilute rinsing solution, called dialysate [15]. The driving force for the separation is the difference in concentration between the two compartments. The fibers are contained within a cylindrical shell housing. It constitutes the core unit of the treatment and contains four ports, two for the dialysate and two for the blood. To improve mass transfer efficiency, the two fluids flow in the module in countercurrent mode. The module, thanks to a potting system, is able to guarantee complete segregation between the two fluids, which is essential to avoid contamination problems. In particular, blood is taken from the patient through a vascular access generally created in the arm, pressurized by a pump, and sent to the module. After the removal of toxins and other waste products, the purified blood returns to the patient through a second vascular access. Figure 1 shows the basic aspects of the hemodialysis process.
Figure 1.
Schematic of the HemoDialysis (HD) circuit.
Variants of hemodialysis treatment are HemoFiltration (HF), HemoDiaFiltration (HDF), and Peritoneal Dialysis (PD).
Hemofiltration is a dialysis technique based on the removal of uremic toxins exclusively by convection. Unlike standard HD, in HF the main driving force is not a concentration gradient but a pressure gradient, which forces the passage of part of the flowing blood (plasmatic components) through the porous membrane and removes plasmatic toxins, entraining and removing also medium and high molecular weight solutes [16]. To maintain a constant blood volume and provide electrolytes, hemofiltration requires the addition of replacement fluids before or after the blood passes through the module. In the former case, it is referred to as pre-dilution replacement, and, in the latter, as post-dilution.
Hemodiafiltration is a renal therapy that combines the characteristics of hemodialysis and hemofiltration. This process combines diffusion and convection, allowing the removal of excess fluids and toxic solutes of low, medium, and high molecular weight, thus best simulating natural renal filtration. This offers some advantages over traditional blood purification techniques, including a more efficient removal of toxins, a better control of water balance, and a greater elimination of certain molecules. This makes hemodiafiltration the most used technique.
Peritoneal dialysis offers the advantage of being feasible for home-based renal treatment. During peritoneal dialysis, a cleansing fluid flows through a tube into the abdomen of the patient [17]. The inner lining of the abdomen, known as the peritoneum, acts as a filter and removes waste metabolites, toxins, etc., from the blood. After a certain period of time, the liquid with accumulated waste flows out of the abdomen and is thrown away. This therapy offers the benefit of being applicable to patients with chronic kidney disease who are not eligible for a kidney transplant or hemodialysis. However, it may not be suitable for patients experiencing abdominal discomfort, drainage problems, or peritoneal membrane complications. Therefore, it is necessary for the patient’s medical team to conduct a comprehensive assessment to determine the most suitable therapeutic approach from the available options. Figure 2 shows schematically the main differences between peritoneal dialysis (Figure 2a) and classic hemodialytic treatment (Figure 2b), while Figure 3 shows a specific focus on the three possible hemodialytic variants.
Figure 2.
Graphic representation of Peritoneal Dialysis (PD) (a) and classic HemoDialysis (HD) (b). In (a), the peritoneum in the patient’s peritoneal cavity is used as the membrane through which excess fluid and solutes are removed from the blood to the dialysate. In (b), the module is used to purify the patient’s blood, drawn via an ArterioVenous Fistula (AVF).
Figure 3.
Scheme of the three hemodialytic variants. Solute clearance can be achieved by diffusion or convection. In HemoDialysis (HD), solutes move down their concentration gradient (Δc) from the blood to the dialysate. In HemoFiltration (HF), a pressure gradient (ΔP) forces solutes and fluids across the filter. In HemoDiaFiltration (HDF), both Δc and ΔP act to remove solutes and fluids across the filter.
1.4. Artificial Intelligence Application on Kidney Diseases and Hemodialysis
Over the years, the use of AI has shown increasing potential in this regard; so much so that its use is now a valuable decision support for experts in many medical fields, including renal care.
AI tools have influenced the field of nephrology since the 1980s, particularly in areas where disease prevention or detection significantly impacts patient survival.
In 1987, Gan et al. [18] described the development of RENPAD, an interactive computer program designed to assist the physician in the preliminary diagnosis of primary renal disease using a rule-based system, OPS5, which allowed for faster diagnostic sessions. It is important to emphasize the relevance of this first example of application of artificial intelligence tools in the renal field, because it later inspired other researchers to invest in this area.
Indeed, in 1992, Agar et al. [19] described in their study a non-invasive computational technique for the assessment and interpretation of clinical and laboratory data in glomerular disease, with the aim of avoiding renal biopsy. While the accuracy was not particularly high, this model can be regarded as one of the first attempts aimed at reducing both the cost and the morbidity associated with investigating glomerular disease in cases where renal biopsy is deemed dangerous or contraindicated.
Then, in 1993, Chang et al. [20] developed a Renal Mass Diagnostic System (RMDS) by using ILIAD, an expert system created for diagnostic consultations. Seventy-two cases of renal mass have been tested on this system, obtaining a diagnostic accuracy of 75%. This system was also able to show the cost of the various possible diagnostic procedures, so that the user could choose the most convenient one to confirm the ILIAD diagnosis. Also in 1993, McMichael et al. [21] realized a very interesting Intelligent Dosing System (IDS), capable of predicting the appropriate doses of the immunosuppressive drug FK506 to be administered to kidney or liver transplant patients. The good performance of the IDS provided a first example of a model capable of minimizing the pharmaceutical dose administered to immunosuppressed patients in order to reduce potential toxicity, costs, and duration of hospitalization.
In 1992, Gray et al. [22] even tried to apply such computerized systems in the context of dialysis. They developed an AI tool capable of alerting doctors and nurses at an early stage to potential abnormal interactions between dialysis patients and prescribed drug therapies. This monitoring system was created with the aim of ensuring that drug therapy was consistent and correct, according to the rules created by healthcare providers, thus avoiding occasional errors in drug therapy.
Another interesting application was developed in 2001 by Akl et al. [23], who implemented a neural network model to study and predict concentrations of urea during a hemodialysis session. After the training, the NN model was able to predict hemodialysis session time needed to reach a target Solute Removal Index (SRI) in patients not previously studied by the NN model with an acceptable prediction error of 10.90%. Also, in 2001, Fernàndez et al. [24] implemented a supervised NN to predict the equilibrated post-dialysis blood Urea (eqU) at 60 min after the end of the hemodialysis session, essential for determining the equilibrated Kt/V (parameter used to evaluate the adequacy of a dialysis treatment), a major determinant of morbidity and mortality in hemodialysis patients. Similarly, in 2003, Ray et al. [25] used Radial Basis Function Neural Network (RBFNN) and Generalised Regression Neural Network (GRNN), functional models even on a small dataset, to predict the Kt/V of a dialysis session and, thus, the rate of urea removal during the treatment. The use of the models described in references [24,25] proved in both cases to be better than traditional methods, demonstrating once again the great potential of artificial intelligence tools in aiding doctors and nurses.
In recent years, applications in the renal field are growing further, especially to prevent or identify the onset of disease, kidney size, complications of previous diseases, or complications from the hemodialysis process. The great interest in this field has led research to increasingly better results, such that in many cases they have supplanted previous ones. For example, in 2015, Hussain et al. [26] proposed a supervised learning approach for kidney volume estimation starting from 3D Computational Tomography (CT) images and using a regression model to simultaneously predict the kidney area per image slice and kidney span per image volume. They validated the model on a dataset of 90 kidney samples, obtaining a volume estimation accuracy higher than other existing methods. In 2018, Norouzi et al. [27] proposed a fuzzy logic-based model for predicting the renal failure timeframe of chronic kidney disease based on real clinical data, analyzing GFR values. Despite numerous uncertainties related to the variability of the disease course, the model was able to accurately predict changes in GFR over long future periods. Recent and noteworthy applications also pertain to hemodialysis. For example, in 2018, Niel et al. [28] used AI to improve the accuracy of dry weight assessment in hemodialysis patients. They showed that an NN prediction outperformed those of experienced nephrologists in most cases, demonstrating that AI is a powerful predictive tool not only for the onset of kidney disease but also for dialysis treatment.
The following figures report the number of publications per year concerning artificial intelligence applications in the renal field in the time intervals between 1979 and 2023 (Figure 4) and, more specifically, 2019–2023 (Figure 5), respectively. The exponential growth of the number of published papers per year highlights the great interest in AI applied to the renal disease and therapy field. Notably, none of the cited publications reported individual-level or anagraphic data, reflecting the authors’ consistent attention to ethical standards aimed at protecting patient privacy. Furthermore, most of the studies included in this paper are based on clinically sourced, validated, and robust datasets, such as “Medical Information Mart for Intensive Care III/IV” (MIMIC-III/IV), and large hospital cohorts, which significantly enhance the reliability and reproducibility of the findings. In cases where smaller datasets were used, their reliability was supported by the reporting of statistical measures such as p-values and confidence intervals, strengthening the robustness of the models’ performance.
Figure 4.
Number of publications per year on Artificial Intelligence (AI) applications related to the topic of kidney disease and relevant therapies in the time interval 1979–2023. The research on the Scopus database used “Artificial Intelligence”, “Kidney Diseases”, and “Hemodialysis” as key search words, limited to English-language publications.
Figure 5.
Number of publications per year on Artificial Intelligence (AI) applications related to the topic of kidney disease and relevant therapies in the time interval 2019–2023. The research on the Scopus database used “Artificial Intelligence”, “Kidney Diseases”, and “Hemodialysis” as key search words, limited to English-language publications.
The breakthrough year seems to be 2022, when the number of published articles increased to 144 (in 2021, it was 78), partly due to the contribution of new transformer variants that have led to superior performance in several applications.
The trend analyzed in the previous histograms confirms the considerable and growing scientific interest in AI themes in this specific field of biomedicine. This vibrant scientific interest justifies the need to review recent literature to capture the current state of the art and identify unresolved aspects that can guide future research endeavors.
The aim of the present review is to analyze the main literature works regarding applications of artificial intelligence in the renal area, considering the most recent time span from 2019 to 2023.
This review is structured in two sections, with a brief concluding discussion on recent developments and emerging trends in artificial intelligence for nephrology, as well as the limitations and challenges of its clinical adoption. The first section offers a concise overview of the primary AI literature models used in the literature and outlines the definition of the associated parameters used for assessing the model’s effectiveness. The second presents the most significant AI literature papers in the renal field, classified as follows:
- AI techniques used as tools for predicting chronic kidney disease in renal-healthy patients or the probability of survival in renal-ill patients, starting from both numeric data and diagnostic images.
- AI techniques used as tools to support traditional methods for the CKD detection in renal-ill patients, considering both numeric data and diagnostic images.
- AI techniques used as tools to improve dialysis treatment or support physicians in managing patients in their care.
- AI techniques used as tools to predict dialysis complications during the treatment or mortality in patients awaiting renal transplantation.
Overall, as will be shown in Section 3, the literature shows a strong focus on the first two categories, with the majority of studies addressing early prediction and diagnosis of kidney diseases. In contrast, research on therapy optimization and complication prevention remains relatively limited, despite its clinical importance, highlighting the need for further studies to develop and validate artificial intelligence tools that can effectively support therapeutic decision-making.
2. Machine Learning: Models’ Classification and Performance Parameters
2.1. Machine Learning and Its Ramifications
In the renal field, various artificial intelligence models are used for prevention, diagnosis, and treatment. Among these, ML encompasses different types of “learning” approaches [29], each defined by the nature of the training data and the problem addressed. These include supervised, unsupervised, semi-supervised, and reinforcement learning. A separate Section 2.2 is dedicated to Deep Learning.
Figure 6 classifies the different types of ML and the relevant models associated with each category.
Figure 6.
Machine Learning (ML) classification in subcategories, along with the relevant models for each of them.
- Supervised Learning uses training data that include the desired outputs. It comprises two main types of models: classification, which assigns inputs to predefined categories, and regression, which predicts continuous numerical values based on input features.
- Unsupervised Learning uses training data that do not include the desired outputs. It embraces clustering (based on grouping similar data points), association models (based on identifying relationships between variables), and dimensionality reduction (based on simplifying datasets by reducing the number of features to reduce the computational load) [30].
- Semi-Supervised Learning uses training data that include a small amount of desired outputs. It includes self-training (based on generating new labeled data using self-generated predictions), low-density separation (used in classification problems where classes are separated by low-density regions), and graph-based algorithms (based on the use of graphical representations to model relationships between data instances) [29].
- Reinforcement Learning trains an agent to make decisions in a complex environment. Input data is not provided; instead, only the output is presented. The algorithm learns how to derive this output through trial and error, relying on past experiences. It includes dynamic programming (based on solving problems by breaking them into sub-problems), Monte Carlo methods (based on estimating solutions via random sampling), and heuristic methods (based on approximating solutions when optimal ones are hard to find).
In turn, deep learning includes supervised, unsupervised, and hybrid NNs, which combine models of the previous two classes. In the following section, the supervised learning models are introduced and briefly presented.
Supervised Learning Models
Most applications of ML models in the renal field involve supervised learning. Figure 7 reports the most commonly used supervised learning [31] models.
Figure 7.
Supervised Learning classification in subcategories along with the relevant models.
Classification models
Naive Bayes (NB) [32] is a simple algorithm based on the assumption of conditional independence between features and on Bayes’ theorem [33]. NB is mainly used for text classification. When applied to data with a normal distribution, it is called “Gaussian”.
Logistic Regression (Log. Reg.) [34] is a linear ML algorithm used for binary classification, predicting the probability that an observation belongs to class 0 or 1. When multiple independent variables influence the outcome, it is called “multivariate logistic regression”.
Logistic Boosting (LogitBoost) [35] improves the performance of weak learning models (often simple decision stumps) by iteratively combining them into a stronger model, reducing classification error.
Linear Discriminant Analysis (LDA) and Quadratic Discriminant Analysis (QDA) [36] are statistical techniques for classification and size reduction, by means of a linear (LDA) or a quadratic (QDA) combination of features separating two or more classes of data, respectively.
Regression models
Linear Regression (LR) [37] is a linear model used to predict a continuous outcome (between 0 and 1). Unlike logistic regression, its output spans a range of real values. When multiple independent variables are involved, it is called “multiple linear regression”.
Non-Linear Regression uses powers of the independent variable to model non-linear relationships with the dependent variable. When multiple independent variables are involved, it is called “multiple non-linear regression”. A common form is the “polynomial regression”, which uses a polynomial function to fit the data of one or more independent variables.
Classification and Regression models
Ridge [34] is a linear model that incorporates a penalty on the sum of the squares of the model coefficients to reduce overfitting by limiting the model complexity.
Least Absolute Shrinkage and Selection Operator (LASSO) incorporates a penalty on the absolute sum of the coefficients.
ElasticNet combines the penalties of Ridge and LASSO, balancing their strengths to improve generalization in models with many correlated predictors.
Support Vector Machine (SVM) model [38] finds an optimal hyperplane to separate classes (classification) or fit a function (regression), minimizing the prediction error and maintaining an optimal margin.
Decision Trees (DTs) [39] structure decisions in a tree format, where nodes represent a decision based on input features. A type of DT is the Classification And Regression Tree (CART), which constructs binary trees where each node always divides into two branches. Another variant of DT is the Conditional Inference Tree (CIT), which uses statistical tests to choose subdivisions, improving interpretability and robustness.
Random Forest (RF) [40] is an ensemble model that combines multiple decision trees using aggregation (bagging). It aggregates results to improve accuracy and reduce overfitting.
Extremely Randomized Trees (Extra Trees) [41] are similar to RF but introduce additional randomness by selecting both the splitting feature and threshold randomly at each node, increasing diversity among trees.
Rotation Forest [42] is another ensemble method that emphasizes the diversity of trees through data rotation, allowing each base classifier to view the data from a different perspective, improving overall accuracy.
k-Nearest Neighbors (kNN) is an algorithm based on the concept of closeness, assuming that similar inputs yield similar outputs. It uses distance metrics such as Euclidean or Manhattan.
Gradient Boosting Machine (GBM) [40] builds decision trees sequentially, with each new tree correcting the errors of the previous one. In this case, GBM is called “Gradient Boosting Decision Tree” (GBDT).
eXtreme Gradient Boosting (XGBoost) [43] extends GBM with additional features such as tree pruning, parallelization, and Ridge and LASSO regularization, improving robustness and overfitting.
Light Gradient Boosting Machine (LGBM) selects in each tree the leaf with the best result, leading only this one to successive divisions. This approach makes LGBM less conservative but more efficient than GBM.
Categorical Boosting (CatBoost) is optimized for categorical data, automatically handling encoding while using oblique trees (non-orthogonal decision boundaries) to separate different data classes. This minimizes overfitting and training time.
Figure 8 shows the different concepts of “tree growth” for the GBM, XGBoost, LGBM, and CatBoost models. The same schematic representation is used for the XGBoost and GBM models, as they are structurally the same and differ only in the calculation mechanisms used.
Figure 8.
Schematic illustrations of eXtreme Gradient Boosting (XGBoost), Light Gradient Boosting Machine (LGBM), and Categorical Boosting (CatBoost) models. XGBoost and GBM build the trees sequentially and maintain constant tree depth between branches. LGBM creates asymmetrical trees, leading only the best leaf to successive divisions. CatBoost is based on oblique trees, where at a given depth, the same division is used in all branches, as indicated by constant division indices.
Adaptive Boosting (AdaBoost) model [40] is similar to the LogitBoost model but provides pure classifications rather than probabilistic estimates for decisions, and is also rarely used as a regressor.
2.2. Deep Learning Models
Deep Learning is a sub-class of Machine Learning. It is based on the use of deep ANNs.
Figure 9 reports the classification of deep learning models [44] into supervised, unsupervised, and hybrid neural networks categories, together with the most employed models for each category.
Figure 9.
Deep Learning (DL) subcategories and the related models.
A separate category is dedicated to Transformer-based models, first introduced in 2017 by Vaswani et al. [45]. These models are characterized by the multi-headed attention mechanism, which allows them to focus on multiple and variable-length parts of the input simultaneously. This property has made transformers the foundation for modern Large Language Models (LLMs) such as “Chat Generative Pre-trained Transformer”, best known as ChatGPT.
Transformer-based models can be divided into four main classes [46].
Encoder-only models are designed mainly for understanding tasks such as text classification, sentiment analysis, and named entity recognition. They take input sequences, encode them into contextual representations, and output embeddings that capture semantic meaning.
Decoder-only models generate text in an autoregressive manner, predicting one token at a time based on the previous context. They are particularly suited for text generation, dialogue systems, and LLM-based applications like ChatGPT.
Encoder-decoder models encode an input sequence into a fixed representation and then decode it into an output sequence. They are widely used for machine translation, text summarization, and question answering, and are also called Sequence-To-Sequence (Seq2Seq) transformers.
Multimodal models are capable of processing and integrating information from multiple modalities, such as text, images, or audio. They are used in applications like text-to-image generation and vision-language alignment.
These subclasses form the backbone of modern AI systems, enabling highly accurate, flexible, and scalable solutions across NLP, vision, and even multimodal reasoning tasks.
2.2.1. Supervised Neural Networks
Supervised NN models include a variety of architectures suited to different data types and tasks.
Convolutional Neural Networks (CNNs) [47] are optimized for gridded data such as images and videos, using convolution layers to detect local patterns (e.g., edges, textures, low-level features). CNNs include the following:
- Alex Networks (AlexNets) were developed by Krizhevsky et al. [48] in 2012. It popularized deep learning in image classification with five convolutional layers.
- Residual Networks (ResNets) use residual blocks to address the gradient degradation, simplifying the back-propagation process during training.
- Inception Networks (InceptionNets), also called GoogLe Networks (GoogLeNets), have multiple convolution modules to capture features at different spatial scales and learn richer representations.
- U-Networks (U-Nets), mainly used for biomedical image segmentation, use a contraction path followed by an expansion path (encoder-decoder), resulting in a typical “U-shape”.
- Dense Networks (DenseNets) connect each convolutional layer to all previous ones within the same dense block, improving learning efficiency.
- Squeeze Networks (SqueezeNets) are similar to AlexNets but smaller in size, used for applications that require low memory usage and high processing speed while maintaining good image classification accuracy.
- Condensed Networks (CondenseNets) reduce parameters and operations through a condensation technique, maintaining high image classification performance with low memory and computational cost.
In Feedforward Neural Networks (FNNs) [49], information moves in only one direction, from input through one or more hidden layers to output. FNNs include:
- Fully Connected Networks, where each neuron in one layer is connected to all neurons in the next layer. A simple form is the MultiLayer Perceptron (MLP), with three layers of nodes: an input layer, one or more hidden layers, and an output layer. MLP is effective for solving general supervised learning tasks.
- Probabilistic Neural Networks (PNNs) provide output probability estimates instead of single predictions. They help to better understand the uncertainty in the data and improve the accuracy of predictions.
Recurrent Neural Networks (RNNs) [50] handle sequential or temporal data. The presence of cyclic connections that can maintain an internal memory allows sequences of data to be processed more efficiently. The “bidirectional” variant improves context understanding by processing both forward and backward sequences. RNNs comprise the following:
- Simple Recurrent Neural Networks (SimpleRNNs) are the simplest form of RNNs, where the output of a hidden layer is fed back as input for the hidden layer itself at each time step.
- Long Short Term Memory (LSTM) networks handle long-term time dependencies, suitable for complex sequences. They can also be used in unsupervised scenarios.
- Gated Recurrent Units (GRUs), similar to LSTM, efficiently address the vanishing gradient problem, consisting of the excessive shrinkage of gradients during back-propagation.
- Simple Recurrent Units (SRUs) are faster and less computationally expensive than GRU, ideal for real-time use. They present an internal state that updates efficiently at each time step, allowing relevant information to be stored over time.
2.2.2. Unsupervised Neural Networks
Unsupervised NNs comprise three different types:
Autoencoders [44] are composed of an encoder—decoder pair that compresses the input into a more compact representation and then reconstructs it. Different autoencoders are the “Variational AutoEncoders” (VAEs), i.e., neural networks designed to generate new data similar to the training set (e.g., images).
Generative Adversarial Networks (GANs) have a generator, which creates realistic data, and a discriminator, which improves its ability to distinguish between real and generated data.
Swarm Intelligence Networks [51] are inspired by the behavior of social organisms interacting in a distributed manner to achieve shared objectives. They emulate the way such organisms coordinate their actions to achieve efficient global outcomes without centralized guidance.
2.2.3. Hybrid Neural Networks
Hybrid Neural Networks combine supervised and unsupervised models to handle complex tasks such as image recognition, pattern analysis, and decision making, where traditional neural networks may be insufficient [52]. Two examples of hybrid NNs are as follows:
CNN-RNN hybrids [53] combine CNNs (excellent for spatial data like images) with RNNs (designed for sequential data like text), making them suitable when spatial patterns over time must be captured (e.g., videos or audio analysis).
GAN-CNN hybrids [54] implement the generator-discriminator structure typical of GANs, where both the generator and discriminator are designed as CNNs. This combination is powerful in image and video generation.
2.3. Machine Learning Models’ Performance Indicators
In order to evaluate the efficacy of a model (especially its ability to generalize and perform well on unseen data), various performance indicators are commonly adopted, depending on the type of problem (e.g., classification, regression).
2.3.1. Classification Performance Indicators
Several metrics are used to evaluate the performance of classification ML models [55]. These metrics are typically based on confusion matrix components. In a classification process, positive (i.e., 1) and negative (i.e., 0) refer to the two possible classes. It follows that, in a classification model, a True Positive (TP) is a value correctly predicted as 1, and a True Negative (TN) is a value correctly predicted as 0. On the other hand, a False Negative (FN) is a value incorrectly predicted as 0, and a False Positive (FP) is a value incorrectly predicted as 1. In binary classification, “positive” often indicates the presence of a condition (e.g., disease) and “negative” its absence. In multi-class classification, the concepts generalize to account for multiple classes, allowing for the assessment of classifier performance across different categories without changing their fundamental definitions. Each metric retains its original meaning but is applied to evaluate each class against all others.
- Accuracy is the percentage of correct predictions over total predictions.
- Specificity is the percentage of negative instances correctly identified.
- Recall (or Sensitivity or True Positive Rate (TPR)) is the percentage of positives correctly identified.
- Precision is the percentage of positive instances correctly identified among all predicted positives.
- Fβ-Score combines precision and recall into a single value weighted by β, thus providing an overall measure of the performance. In Equation (6), for β > 1 the score favors recall, while for β < 1 it gives more weight to precision. The most common is the F1-Score (β = 1), which gives equal weight to precision and recall.
- False Positive Rate (FPR) is the ratio of the number of cases misclassified as positive to the total number of true negatives.
- Area Under the Receiver Operating Characteristic Curve (AUC-ROC) is the area subtended by the TPR vs. FPR curve, as shown in Figure 10a.
- Area Under the Precision-Recall Curve (AUC-PR) is the area subtended by the Precision vs. Recall curve, as shown in Figure 10b.
Figure 10.
Representation of the Area Under the Receiver Operating Characteristic Curve (AUC-ROC) graph (a) and the Area Under the Precision-Recall Curve (AUC-PR) graph (b).
- Average Precision (AP) is the precision averaged across different Recall levels along the Precision-Recall curve.
- The mean Average Precision (mAP) is the average of AP across all classes, used to assess the performance of classification or object detection models.
- The Dice coefficient is used in image analysis; it assesses how closely a segmented region of an image coincides with a reference or truth region.
- Matthews Correlation Coefficient (MCC) measures the correlation between the predictions of a binary classification model and the actual class labels, returning a value from −1 (inverse prediction) to +1 (perfect prediction), with 0 indicating a random prediction.
The mathematical expressions to calculate the classification ML models’ performance indicators are reported in Table 1.
Table 1.
Formulas for the performance parameters of classification Machine Learning (ML) models are defined above.
2.3.2. Regression Performance Indicators
To evaluate the performance of a regression ML model, several standard metrics are commonly used [55]:
- R2 Score measures how well a statistical model predicts an outcome. R2 ranges between 0 and 1: if R2 = 0, the model does not predict the outcome; if R2 = 1, the model perfectly predicts the outcome; if 0 < R2 < 1, the model does not predict the outcome perfectly.
- Mean Squared Error (MSE) calculates the mean square of the differences between predicted and actual values.
- Mean Absolute Error (MAE) averages the absolute differences between predicted and actual values.
- Root Mean Squared Error (RMSE) measures the square root of MSE between predicted values and actual values.
- Concordance index (C-index) measures how well a model predicts the order of events (e.g., survival time of patients). It compares the model predictions with what actually happens. It is the ratio of concordant pairs between real and predicted labels to the total number of comparable pairs.
The mathematical expressions to calculate the ML regression models’ performance indicators are reported in Table 2.
Table 2.
Formulas for the performance parameters of regression Machine Learning (ML) models.
2.4. Comparative Insights: The Main Machine Learning Models Applied to Nephrology
Although a wide range of machine learning models and performance metrics is available, the nephrology literature consistently shows a preference for a limited set of models that are repeatedly applied across different studies. This preference is guided by factors such as the nature and size of available datasets, the need for model interpretability to support clinical decision-making, and the trade-off between predictive performance and implementation feasibility [56,57].
As will be shown in detail in Section 3, supervised learning dominates nephrology applications. Specifically, logistic regression and regularized approaches such as LASSO, Ridge, and ElasticNet are highly used because they provide coefficients that are easy to interpret, perform robustly even with small or moderately imbalanced datasets, and are already familiar to clinicians [57,58]. However, their main limitation is the inability to fully capture complex nonlinear relationships between variables.
Tree-based methods, including decision trees, random forests, and boosting algorithms, such as XGBoost, LightGBM, and CatBoost, are now among the most widely used approaches for structured Electronic Health Record (EHR) and laboratory data. These methods handle missing values efficiently, are accurate and robust to outliers, moderately interpretable, and provide feature importance measures that can highlight the most relevant clinical predictors [56,59], but may overfit if not well-tuned and cross-validated [57].
When larger datasets are available, neural network-based models are increasingly explored. Feedforward artificial neural networks (ANN, MLP) can capture complex non-linear patterns in clinical data and have shown very high accuracy in chronic kidney disease staging and prognosis prediction, although they remain less interpretable and more sensitive to hyperparameter choices than tree-based models [57].
For imaging tasks, deep learning has become the dominant paradigm. CNNs and their derivatives (U-Net, ResNet, DenseNet) automatically extract hierarchical features from biopsy slides, CT scans, and Magnetic Resonance Images (MRIs), achieving excellent segmentation and classification performance. More recently, transformer-based architectures, such as Vision Transformers (ViTs) and multimodal attention-based models, are being explored for Whole-Slide Image (WSI) classification and for integrating imaging with clinical features, obtaining promising results [60]. However, these approaches require large, well-annotated datasets and substantial computational resources, and their “black-box” nature can limit trust among clinicians [56].
To address this limitation, recent years have seen a growing adoption of eXplainable AI (XAI) techniques, such as SHapley Additive exPlanations (SHAP), Local Interpretable Model-agnostic Explanations (LIME), Gradient-weighted Class Activation Mapping (Grad-CAM), and attention-based mechanisms, which aim to make model decisions more transparent and interpretable, and help clinicians understand which features or image regions drive predictions [61,62,63].
Sequential and temporal models, such as SimpleRNN, LSTM networks, and GRU, are particularly valuable for modeling longitudinal data streams, including dialysis session records or Intensive Care Unit (ICU) monitoring data. These models capture time dependencies better than static approaches, but they are computationally demanding, hardly interpretable, and more prone to overfitting if data are scarce [60].
Finally, although they have lower transparency, hybrid models are emerging as promising and accurate strategies for integrating multimodal information (demographic, laboratory, imaging) into a single predictive pipeline and for quantifying predictive uncertainty, which is crucial for clinical decision support [56].
As a summary, Table 3 provides a comparative overview of the model families and parameters presented in Section 2.2 and Section 2.3, most frequently applied in nephrology, summarizing their strengths, limitations, typical applications, and metrics used to evaluate their performance.
Table 3.
Comparative summary of the most frequently used Artificial Intelligence (AI) model families in nephrology.
3. Machine Learning Models Used as Prediction, Detection, and Treatment Support Tools in the Renal Field
Chronic kidney diseases affect about 13.50% of the world’s population [64] at different severity stages, causing millions of victims each year and health care costs of about 140 billion euros just in Europe alone [65]. However, their progression can be slowed, and complications minimized if detected early. Therefore, nephrologists aim to decrease the mortality rate of patients by implementing preventive protocols and closely monitoring their condition.
Acute kidney injuries affect about 15% of all hospitalizations, up to 50% of patients admitted to the ICU [66], and can increase the risk of mortality in patients with end-stage renal disease or chronic kidney disease who require dialysis or kidney replacement.
Therefore, artificial intelligence—and, more specifically, machine learning algorithms—represents an efficient tool to predict early CKD, AKI, and their progression.
Predictions can be based on numerical data or diagnostic images. In the first case, starting from data such as patients’ cardiovascular conditions and glomerular filtration rate measurements, the output typically entails predicting an imminent abnormal condition for the patient, whether it is the onset of a disease or the degeneration of an already compromised state. In the second case, using CTs or MRIs of the kidneys, supervised DL models can be used for pre-classification of kidney allograft biopsies, as models to predict renal survival after transplantation, for scanning all renal biopsies, or for applying certain basic algorithms before examination by the pathologist.
The follow paragraphs focus on the main applications in the field of chronic kidney disease and acute kidney injury as an aid to the individual physician’s prediction of the future renal status of healthy or CKD patients (Section 3.1), the detection of chronic kidney disease in renal-ill patients in support of traditional methods (Section 3.2), the identification of the most suitable treatment options for them (Section 3.3), and the analysis of possible complications related to therapy (Section 3.4). At the end of each section, up to Section 3.4, a summary table will summarize the papers mentioned in that paragraph. Finally, a discussion has been conducted on recent developments in AI (Section 3.5) and on the main limitations and challenges related to the adoption of AI in clinical practice (Section 3.6).
3.1. Machine Learning as a Tool to Predict Kidney Diseases
ML models have been applied to the prediction and classification of hospital data to identify problems such as cases of chronic kidney disease [67,68,69] or, more specifically, kidney cancers [70,71,72,73], also through the use of innovative approaches. High performances were obtained in many of these studies, as shown by an AUC-ROC value of 98.86% using a Deep Neural Network (DNN) [68], F1-Score values greater than 96% using a convolutional neural network [69], or else accuracy values greater than 95% using complex approaches as transfer learning [72] or D-ACO [67]. In detail, D-ACO is a hybrid ML algorithm composed of the Density-based Feature Selection (DFS) algorithm and Ant Colony-based Optimization (ACO), algorithms used especially in the medical field for feature selection and classification, respectively, while transfer learning is a deep learning approach that uses pre-trained models as a starting point for training algorithms with similar and related goals, so as to reduce the time and data needed for training. In this regard, for the implementation of the final model, Nasir et al. [72] used an AlexNet model combined with Stochastic Gradient Descent with Momentum (SGDM), ADAptive Moment estimation (ADAM), and Root Mean Square PROPagation (RMSPROP), which are optimization algorithms able to improve training efficiency by stabilizing convergence and dynamically adjusting learning rates through the strategic use of cost function gradients.
Lower, but still good efficiency parameters were obtained in studies [70,71], such as an accuracy of 83.43% using a MultiModal Deep Learning Model (MMDLM) composed by a ResNet and a fully connected network, an AUC-ROC of 65.10% using a clustering algorithm combined with a LASSO regressor, or a Dice score of 87% using a “V Bottleneck Multi-resolution and Focus-organ Network” (VB-MrFo-Net) demonstrate. Specifically, a VB-MrFo-Net is a model implemented by Chen et al. [71] to segment specific regions of the affected organs thanks to its “bottleneck” function, which reduces data dimensionality while preserving the most important information to optimize the accuracy of the analysis. After the segmentation, the combination of an RF model and an SVM model allowed them to predict the clear-cell Renal-Cell Carcinoma (ccRCC) prognosis and its stage with an AUC-ROC value of 78.20%.
In the context of AI, a trained model can be defined as validated when it is subjected to clinical tests, which, to our knowledge, have not yet been addressed in these studies. This aspect becomes even more important when data from a single database is used for training, as it is potentially responsible for the high-performance efficiencies of the models, as shown in the studies [67,68,69,72]. On the contrary, the presence of data from several hospitals reduced the quality of the models [70,71] in the training phase, but potentially contributed to the implementation of models with a higher capacity for generalization. To prove this, it would be necessary to subject the analyzed studies to clinical trials.
In conclusion of this first block of works, a last interesting study was conducted by Chen et al. [73], who used the so-called “Adaptive Hybridized Deep Convolutional Neural Network” (AHDCNN) on CT images to predict kidney cancer, as shown in Figure 11.
Figure 11.
Example of a Convolutional Neural Network (CNN) as a tool for the prediction of kidney cancer, identifying the interested region through the so-called “automatic segmentation” applied on Computational Tomography (CT) images. Reproduced from Chen et al. [73].
Specifically, AHDCNN is a convolutional neural network with three stages composed of pooling layers and linear convolutions. used in this study to reduce the size of the images and to extract their most important features, respectively. After training, AHDCNN achieved an accuracy of 97.14% in tumor early recognition, thus anticipating the possible achievement of its final stage.
Other authors [74,75,76,77,78,79,80,81,82,83,84,85,86,87] compared several models to identify the best performance in predicting the onset of chronic kidney disease, achieving accuracy [74,77,79,82,84,85] and F1-Score values [75,76,86,87] over 96% using deep neural networks [76,79], or simpler machine learning models [74,77,78,81,84,85,86,87], all of which are shown in Table 4 with the respective authors.
Among these studies, particularly relevant was the research conducted by Islam et al. [75], who implemented a classification and rule generation analysis on a CKD dataset. Their objective was to test different models for the accurate and early identification of chronic kidney disease cases on new data and to derive decision rules illustrating relationships between CKD attributes. For classification, they compared two boosting algorithms, AdaBoost and LogitBoost, while for rule generation, they evaluated two rule induction methods, J48 and Ant-Miner. The dataset consisted of records from 2800 patients, each with 24 attributes. The LogitBoost and Ant-Miner combination achieved the highest performance, with a predictive F1-Score of 99.75%, and identified nine decision-making conditions based on patient attributes as the most relevant for CKD prediction.
With the same aim, Bandera et al. [88] and Pati et al. [89] implemented ML models combined, respectively, with pre- and post-processing algorithms able to further improve the performance of the predictive models, as accuracy and F1-Score values higher than 98.50% demonstrate. Specifically, Bandera et al. [88] used an AdaBoost model in combination with “Decision Making Trial And Evaluation Laboratory” (DEMATEL) neutrosophic, an algorithm capable of selecting the most relevant features, while Pati et al. [89] combined an ANN with Voting and Bagging techniques, ensemble methods of equal (Bagging) or different models (Voting) used to improve the prediction accuracy achieved by the ANN model.
In a similar way, Poonia et al. [80] and Rashid et al. [82] developed a model for the prediction of chronic kidney disease by combining an artificial neural network with Chi-square and Particle Swarm Optimization (PSO), respectively, which are algorithms able to select the most relevant features in the pre-processing stage prior to model application. Accuracy values up to 99.76% were obtained.
Priya et al. [83] also developed a model for predicting and classifying chronic kidney disease, but combining an ANN model with a “Hybrid Gravitational Search Algorithm and Particle Swarm Optimization” (HGSAPSO), an algorithm composed of the Gravitational Search Algorithm (GSA), which was used to explore the solution space to identify optimal solutions for the classifiers’ parameters, and the PSO, which was capable of refining the search for solutions by focusing on the most promising ones. Despite the development of such a model supported by optimization algorithms, this case yielded inferior results compared to what had been seen previously [80,82], with an accuracy of 93%. This is likely due to the lack of a pre-processing algorithm to select the most relevant features prior to model application, a crucial step for an ANN to mitigate the effects of noise, struggling to identify patterns and relationships in the data.
Following this topic, Lakshmanaprabu et al. [90] proposed in 2019 a model able to predict not only the onset of a kidney disease, but also its level of severity using the Internet of Things (IoT), i.e., devices used to collect real-time health data from patients, and cloud systems, used for their storage and processing. Specifically, the implementation of a deep neural network combined with the PSO algorithm, implemented to select the most relevant features on which to apply the model, allowed the researchers to obtain an accuracy value of 99.25%.
Although the results and the ambitious aims, many of the studies described here have some common limitations, which have been partially discussed above, as the presence of data from a single database, which reduces the generalizability of the results, and the absence of clinical studies that can validate the models in real-world settings.
Another critical issue is the poor interpretability of some models, particularly deep learning models [76,79], and the disequilibrium in all datasets used, characterized by more data from CKD patients than from unaffected patients, an aspect that can distort model performance.
In addition, the lack of cross-validation, a key technique for assessing model robustness by splitting the dataset into multiple subsets, prevents reliable performance estimates in some models [76,77,78,79,80,82,83,84,85]. Without this practice, it is more difficult to ensure that the results are representative. Finally, the limited variety of features considered in all these studies may lead to an incomplete understanding of the problem. Addressing these limitations is crucial to improving the reliability and applicability of the analyzed models, which, as shown by the excellent results obtained, possess highly efficient potential.
Despite the presence of some of the limitations already described, the studies conducted by Hamedan et al. [91] and Arulanthu et al. [92] also demonstrated a good validity of the implemented systems and a good predictive ability, with accuracy values of up to 97.75%, using a simple fuzzy system model [91] and a logistic regression model [92], respectively.
Due to the increase in kidney disease cases [13] over the years, the need to develop predictive models for healthy people has become increasingly relevant. Thus, some models were developed capable of identifying in healthy individuals those most prone to the development of CKD [93,94] or AKI [95]. Specifically, a C-index value of 80% was obtained by Bell et al. [95] using a multivariate logistic regression model, while the use of more complex convolutional neural networks allowed Marechal et al. [94] to obtain an AUC-ROC value of 92%. Also innovative was the approach used by Kanda et al. [93], who implemented a Bayesian neural network to assess causal relationships between input and output variables, followed by an SVM to predict chronic kidney disease progression, resulting in predictive errors close to zero.
Furthermore, Bermudez-Lop et al. [96] demonstrated that additional parameters, such as lipoprotein composition and the number of lipid particles in this case, have a greater discrimination capacity with respect to traditional parameters alone. Specifically, in a sample of 209 patients with chronic kidney disease and 186 healthy controls, all non-diabetic, participants’ blood lipids were analyzed with Nuclear Magnetic Resonance (NMR) spectroscopy, an analytical technique used to determine the molecular structure of chemical compounds. The data obtained from these analyses were used in an RF model to assess the ability to distinguish patients with chronic kidney disease from healthy individuals, showing that blood lipid content was a good discriminator for this classification.
In recent years, many researchers have also used ML models to predict CKD or AKI in patients already suffering from other diseases or to study the link between renal diseases and the onset of seemingly unrelated diseases.
For AKIs, some authors developed models to predict acute kidney injury in people who have sustained burns [97], in sepsis survivors [98], or in patients undergoing surgery [99,100,101], with a focus on patients undergoing liver transplantation [102,103,104] or hypotensive patients [105]. Among these studies, an AUC-ROC value of 92% was achieved by Rashidi et al. using a deep neural network [97], followed by lower AUC-ROC values (of up to 86%) obtained with simpler models as random forest [102], eXtreme gradient boosting [98], artificial neural network [104], gradient boosting machine [99,103], and the so-called “Intraoperative and Data Embedded Analytics” (IDEA) [100]. Specifically, IDEA is a simple but innovative model implemented by Adhikari et al. [100] combining random forest with a Generalised Additive Model (GAM), a statistical model capable of modeling linear and non-linear relationships between inputs and outputs. In this study, GAM was used to study the relationships between the pre-operative data of the patients analyzed and the risk of developing acute kidney injury. After that, random forest allowed the pre-operative risk calculated by GAM to be combined with physiological variables collected during the operation, updating the prediction of AKI risk and obtaining an AUC-ROC of 86%.
A strong interest has also been reserved for predicting renal survival after kidney transplantation [106,107] and renal aneurysm repair [108], or the development of fatal pathologies, such as pneumocystis carinii pneumonia [109] and Cardiac Surgery-Associated Acute Kidney Injury (CSA-AKI) [110,111]. Given the complexity of all these diseases, supporting studies have obtained slightly lower but still useful results than those aimed at predicting non-fatal kidney disease, as evidenced by the AUC-ROC value of 83.90% [110] obtained with a RF model or the accuracy of 82.10% [111] and 86% [108] obtained with a XGBoost model called “Detect-A(K)I” by the authors and an ANN model, respectively.
Particularly effective was the use of the joint Bayesian model, a statistical model that allows multiple variables to be analyzed together, using probability theory to update knowledge as new data were collected. Figure 12 presents the typical structure of a joint Bayesian model.
Figure 12.
Schematic representation of a joint Bayesian model, where nodes (classified from “a” to “e”) represent random variables and directed edges represent probabilistic dependencies between variables. A directed edge from a node to another indicates that the second node is conditionally dependent on the first one.
Used to predict renal survival of transplant patients [107], this model, renamed by the authors as “Dynamic Integrative System for Predicting Outcome” (DISPO), provided an AUC-ROC value of 85.70%.
Among the mentioned studies, another relevant approach was that used by Paquette et al. [106], who employed innovative neural networks such as DeepHit and DeepSurv to achieve the same predictive survival goal. Specifically, DeepSurv is a neural network that learns how variables influence the risk of an event, whether in a linear or non-linear manner. In contrast, DeepHit is a more flexible neural network that can analyze the probability of an event occurring at various time points, without adhering to strict rules regarding the data. This network obtained a higher C-index of 66.10%, higher than the 65% obtained by the DeepSurv model.
In regard to acute injuries, the link between COVID-19 and the possible occurrence of acute kidney injury in hospitalized patients has recently attracted the attention of many researchers, including Naser et al. [112] and Lu et al. [113], who addressed the problem using a multivariate logistic regression model and the combination of an LSTM model with an FNN model, respectively. After analyzing data from laboratory tests, medical conditions, and demographic information of several patients, Lu et al. [113] obtained a model that was able to predict the occurrence of acute kidney injury in COVID-19 patients with an AUC-ROC of 96.50%, while Naser et al. [112] obtained an odds ratio between AKI patients died and no-AKI patients equal to 48.6, where odds ratio is a statistical measure used to quantify probabilities of a given event between two groups, especially in epidemiology and medicine. The predictability of acute kidney disease events in the first study and the high odds ratio of the second one proved the expected strong correlation between AKI and COVID-19.
In regard to chronic diseases, predictive models of the kidney function deterioration in sepsis survivors [114] or in patients with Immunoglobulin A Nephropathy (IgAN) [115,116], CKD of unknown etiology (CKDu) [117], hyperkalemia (potassium > 5.5 mmol/L) [118], diabetes [119], or kidney cancer [120] have been implemented. Using simpler ML models as gradient boosting decision tree [114], called “Landmark-Boosting” by the authors and designed specifically to handle time data [119], random forest [115], ANN [116], XGBoost [118], or more complex deep neural networks [117,120], the authors obtained excellent results, such as an AUC-ROC of 95.70% [118], or an accuracy close to 90% [117].
Innovatively, the implementation of the DIstillation with NO labels-Vision Transformer (DINO-ViT) model performed by Wessels et al. [120] enabled them to predict survival in renal cell carcinoma patients. In detail, DINO is a self-supervised, label-free model capable of extracting key features from images of interest, used by the authors prior to applying the transformer. The resulting model provided reliable results, such as a hazard ratio of up to 2.31 for the patients involved, where hazard ratio refers to a measure of the hazard rate (for survival, in this case) of a treatment group compared with a healthy control group. The reliability of the model confirmed the good interpretability of the images produced by the model, which could thus be used as a potential tool to support the disease investigation carried out by medical doctors.
On the contrary, some applications have focused on the prediction of pathologies in patients already suffering from chronic kidney disease, such as hyperkalemia [121] or diabetes [122], since diabetes and CKD together are closely associated with increased mortality risk. Accuracy [122] or AUC-ROC [121] values of up to 89.15% were obtained in these studies.
Other studies proposed artificial intelligence models to monitor eGFR [123] and other factors for predicting future renal deterioration in hospitalized [124,125,126,127] and ICU patients [128,129,130,131,132]. Given the variability of the patients involved, highly variable predictive performances were obtained in the studies cited, such as AUC-ROC values ranging from 73% [124] to 96% [132]. Among the various ML models used, such as random forest [124,132], XGBoost [131], multivariate logistic regression [128], or neural networks [126,127,129,130], particularly innovative approaches were used by Lee et al. [123], Song et al. [125], and Kandasamy et al. [127]. Specifically, the use of the probabilistic Gaussian Mixture Model (GMM) clustering model in combination with a hybrid neural network based on the use of radial functions allowed Kandasamy et al. [127] to analyze in 40,000 ICU patients the progression of their CKD condition. On the other hand, the development of Deep Support-Gradient Boosting Trees (DS-GBT), a hybrid model combining deep learning and decision trees, enabled Song et al. [125] to predict the development of acute kidney injury in hospitalized patients 48 h in advance, achieving an AUC-ROC of 95%. Finally, the implementation of an unsupervised machine learning model based on the “Bag-of-Words” (BoW) model helped Lee et al. [123] to predict the change in renal function after 1 year based on relevant visual features in renal biopsy specimens of CKD patients. In this work, BoW identified and grouped image segments into “visual words” to construct a representative visual vocabulary of kidney biopsies, after the application of a pre-trained neural network able to extract visual features from image segments. The application of a clustering algorithm allowed them to group similar visual segments together to find recurrent patterns. The development of an RF model finally predicted renal function at the time of biopsy and after one year in terms of eGFR, with good AUC-ROC values of 93% and 80%, respectively.
During the same years, some authors have also proposed models able to identify risk factors associated with the rapid decrease in renal function among chronic kidney disease patients [133] considering their CKD severity stage [134,135,136], until end-stage kidney disease condition [137] and mortality [138]. AUC-ROC values equal to [133,134,137], or greater than [135,136] 90% were obtained, and several innovative models were proposed. In this regard, Akter et al. [136] proposed CKD.Net, a model capable of predicting the stages of chronic kidney disease using the combination of a SimpleRNN and an MLP. The implementation of this model allowed the authors to achieve an accuracy of 99.80% in predicting the five chronic kidney disease classes in patients aged from 25 to 90. Bellocchio et al. [137] proposed PROGRES-CKD, a Naive Bayes classifier used on a dataset of adult patients. Using 34 features of 24,535 patients, the model was able to predict the onset of end-stage kidney disease within 6 and 24 months with an AUC-ROC of 91% and 85%, respectively.
Further studies have focused on the problem of kidney stones, a very common renal disease that causes the accumulation of small crystals in the kidney due to an inadequate diet or poor urination.
Using images, it was possible to create models to predict post-operative outcomes after the treatment of large kidney stones through the so-called “PerCutaneous NephroLithotomy” (PCNL) [139] or stones composition with a highly specific, non-invasive approach [140]. For these goals, Black et al. [140] used a ResNet model, while Shabaniyan et al. [139] used an SVM model combined with Sequential Forward Selection (SFS) and Fisher Discriminant Analysis (FDA), algorithms capable of reducing the number of features to be considered and increasing the separability of classes in the classification process, respectively.
In both cases, the predictive capacity of the models proved to be particularly good, obtaining an accuracy value of 94.80% and a recall value of 85%, respectively.
Prediction of possible post-transplant renal rejection through AI analysis of kidney allograft biopsies has also attracted great interest. Histopathological evaluation of transplant biopsies is the most widely used method to diagnose allograft rejection, but it requires expertise and time that can be reduced by using artificial intelligence algorithms, as performed by Kers et al. [141]. They implemented a CNN model to predict possible allograft rejection in test patients, obtaining an AUC-ROC value of 78%, which was sufficient to confirm the discrete generalization ability of the model.
Table 4 reports a list of all quoted literature works, providing key details on adopted models, a brief description of the dataset employed and their origin, the number and type of features used to train the model, the results, in terms of performance parameters, obtained by the best performing model among those tested, and, in the last column, the purpose of the work.
Table 4.
Literature overview on Machine Learning (ML) models developed for kidney disease prediction. Legend: n.a. = not available.
3.2. Machine Learning as a Tool to Detect Kidney Diseases
People with KDs should have regular checks of their kidney function and blood pressure. Urine tests for blood or protein losses, blood tests, or kidney scans are just some of the tests useful for their detection [143]. The identification of kidney diseases at early stages can calm the pathology for further growth and restrain the difficult situations or complications on the patient’s health condition [144].
As in the case of prediction, and also in the detection case, the use of intelligent systems, such as AI tools, can save many lives.
Initial detection and therapy are indeed the best tools for combating chronic kidney disease, and several machine learning models proposed in the literature, such as support vector machine, k-nearest neighbors, decision tree, gradient boosting machine, and random forest, could be an important aid for clinicians’ assessment of the disease.
These tools can act on numerical data or images, for which nephron-pathologists and computer scientists have made considerable progress in developing models able to identify histological structures within WSIs, quantify histological structures, and classify diseases.
In this section, the most recent works dealing with KDs detection with artificial intelligence tools are reviewed.
Interesting applications of smart machine learning models in the renal field concerned the diagnosis of the presence of kidney diseases in pathological patients [145,146,147,148,149,150,151]. Accuracy values up to approximately 100% were obtained and models, such as artificial neural network [148], random forest [145], multilayer perceptron [150], and J48 decision tree [146], that were able to handle unbalanced and missing data better than a classic DT, and a Self-Attention Convolutional Neural Network (SACNN) [151], were implemented. Specifically, “self-attention” is a mechanism that allows the models to assign different importance to each element of an input than to all other elements in the set. Combined with the Season Optimization Algorithm (SOA), which enhances the accuracy and reduces the computation time of AI models, SACNN allowed the authors to achieve the high result mentioned above.
Among the models mentioned, the best result was achieved by Khamparia et al. [147] with the development of an artificial intelligence model capable of identifying healthy and unhealthy patients among 400 individuals. The model applied was a neural network given by the combination of a multilayer autoencoder and the SoftMax probabilistic classifier, used, respectively, for extracting useful features from the dataset and for the final classification, carried out by transforming the raw values into probabilities. The lowest accuracy values were instead obtained by Alsadi et al. [149], who achieved a kidney disease detection accuracy of 78% by analyzing immunobiological materials in kidney biopsies with CNN models. Specifically, they used several versions of pre-trained CNN models on a big dataset of natural images called “ImageNet”, such as ResNet, Inception-v3, Inception-Residual Network version 2 (InceptionResNet-v2), Neural Architecture Search Network (NASNet), and Visual Geometry Group with 16 and 19 convolutional layers (VGG-16/19), and identified the best model. VGG-19 is a model with a simple architecture consisting of many convolutional layers followed by fully connected layers, capable of accurately recognizing specific portions of the images, but taking a lot of time and computing power.
Despite the complexity of this model, its low accuracy could be attributed to the use of Electron Microscopy (EM) images, which, compared to CT or US images, contain intricate ultrastructural details that can closely resemble artifacts or non-pathological structures, potentially confounding the model’s ability to make accurate distinctions.
Beyond these challenges, some authors have implemented models able to detect not only renal diseases, but also the correct intake of potassium, as performed by Granal et al. [152] with the development of a Bayesian-based neural network applied to a dataset of 375 patients with CKD.
As in the predictive case, ML tools have focused on the detection of chronic kidney disease through image analysis or segmentation. Image classifiers or segmentation models were developed by different researchers [153,154,155,156,157,158,159,160], obtaining rapid and precise CKD detection.
The increasingly abundant availability of images prompted the researchers to use CNNs for almost all of these studies, such as ResNets [156,157], or the innovative Single Shot Detector (SSD) Inception-v2, a model implemented by Onthoni et al. [154] to locate and classify multiple objects in an image with a single pass through the network. U-Nets have also been used, either alone [158] or also supported by algorithms as the Extended Maxima Transform (EMT) and Slice Scanning (SSA), able to refine and optimize the detection of kidney boundaries, as in the case of Les et al. [155]. A non-convolutional exception was the hybrid fuzzy-deep neural network implemented by Kumar et al. [160] to recognize kidney disease through image processing. Regardless of the algorithm used, the choice of all these models proved to be optimal, as high values of F1-Score (89.30% [155], 94% [158], 98.70% [159]), accuracy (>90% [153], 92.90% [156], 99.23% [160]), mAP (94% [154]), and AUC-ROC (98% [157]) were obtained.
Other models were implemented to detect specific pathologies, such as Membranous Nephropathy (MN) [161], kidney stones [162,163,164,165,166], kidney cancer [167], or both [168], and Interstitial Fibrosis and Tubular Atrophy (IFTA) [169,170,171].
Computational platforms available online [167], CNNs optimized with artificial data augmentation and dropout [166], an algorithm that “turns off” some neurons to avoid the overfitting during the training phase, and CNN subcategories [171] such as U-Net [170], ResNet [163,168], or their combination [164] were developed to analyze CTs, US images, or WSIs. Specifically, Li et al. [164] identified ResU-Net as the best model following a comparison between specific transformers designed for semantic segmentation of high-resolution images, such as U-NEt TRansformer (UNETR), or multiple convolutional neural networks designed for this task, such as SegNet or DeepLab-v3, identified instead by Ginley et al. [169] as a good segmentation model if combined with a ResNet model, achieving up to 89% accuracy.
On the other hand, Tang et al. [171] used a combination of Mask Region-based Convolutional Neural Network (Mask R-CNN) and Dual-Path Convolutional Neural Network (DPCNN), developed respectively for segmentation of the kidney region under investigation and extraction of features of interest from segmented and resized US images. Figure 13 shows the proposed AI prediction model for IFTA detection.
Figure 13.
Flowchart of Mask Region-based Convolutional Neural Network (Mask R-CNN) and Dual-Path Convolutional Neural Network (DPCNN) proposed for Interstitial Fibrosis and Tubular Atrophy (IFTA) stage by Ginley et al. [169]. The arrow starting from the input image without going through the Mask-CNN indicates that the image can be analyzed directly by the DPCNN. This approach can simplify and speed up the process, but it isolates the kidney with less precision. Reproduced from Tang et al. [171].
Due to its “duality”, the DPCNN was able to identify low-level and high-level features on detailed masks provided by Mask R-CNN, an algorithm able to segment, unlike classical CNNs, at the pixel level. Given its high performance, Mask R-CNN was also used by Yi et al. [170] on images segmented by U-Net to improve the localization and classification of abnormal renal structures.
Studies cited also include GrayNet-SB, a Surface-Based (SB) model implemented by Parakh et al. [162] by pre-training a CNN on the GrayNet online medical database, which performed better than ImageNet-SB, a CNN pre-trained on the ImageNet database, and RandomNet-SB, a CNN trained only on the 535 abdomino-pelvic CT scans selected by the authors.
Innovative models called “StoneNet” and “MN-Net” were proposed by Asif et al. [165] and Hao et al. [161], respectively. Developed for the detection of kidney stones, StoneNet was presented as a novel model based on MobileNet, a CNN architecture designed to be lightweight and suitable for devices with limited computational resources, such as mobile phones. On the other hand, as the name suggests, MN-Net was proposed to detect membranous nephropathy in renal pathological images, a kidney disease that affects the glomeruli. Specifically, Membranous Nephropathy Network (MN-Net) was implemented by combining YOLO-v3, a CNN model useful for detecting glomeruli within the images, and a glomeruli classification network based on Multiple Instance Learning (MIL), a machine learning paradigm applied in contexts where precise data labeling is not available at the individual instance level but only at the group (or bag) level, as in this case.
All these studies demonstrate the great interest in the search for an accurate diagnostic method of kidney diseases, which may lead to a serious deterioration in the renal activity of patients, up to transplantation in the worst cases.
High performances were indeed obtained in many of the models mentioned, such as accuracy values close to or higher than 97% [163,164,165,166], or F1-Score equal to or higher than 95% [161,162,168].
Particular interest has also been directed towards diseases involving glomeruli [172,173] to identify sometimes specific pathologies such as glomerulosclerosis [169,174,175] or glomerular lesions [176,177]. Specifically, glomerulosclerosis is a kidney disease that involves scarring of the glomeruli, the microscopic kidney units responsible for filtering blood to produce urine. In severe cases, this disease may lead to chronic renal failure. Prominent among these models is the U-Net used by Zhang et al. [173] in combination with a convolutional Multiple-Attention Network (MANet). The concept of multiple attention in deep learning refers to a mechanism that allows the model to focus on specific parts of the input during processing. Such a sophisticated approach allowed the authors to achieve 98% accuracy in classifying glomerular pathologies from immunofluorescence images. Another interesting approach was adopted by Lu et al. [174], who implemented Big Transfer-Small (BiT-S) and Big Transfer-Medium (BiT-M) pre-training, respectively, a ResNet model on ImageNet and ImageNet-21k, another large dataset of natural images similar to ImageNet. Specifically, the use of BiT-M proved to be particularly effective in the detection and classification of glomerulosclerosis, achieving an AUC-ROC of 99.40% and demonstrating how transfer learning is highly effective in improving the performance of deep learning models on complex and specific classification tasks, especially when only a limited amount of data is available in the target domain.
Among the cited works, an unpublished model was proposed by Nan et al. [177], i.e., the Uncertainty-Aided Apportionment Network (UAAN) associated with a SegNet model to segment, recognize, and classify glomerular lesions from WSIs. UAAN is a particular classification neural network designed to address problems in which uncertainty in data or predictions can prevent effective prediction of conventional models. This type of network incorporates mechanisms to quantify and utilize uncertainty, thereby improving model decisions and predictions. With the implementation of this model, anticipated by a segmentation optimization algorithm called “Focal Instance Structural Similarity” (FISS), the authors achieved an accuracy of 95.17%, outperforming traditional models such as ResNet, DenseNet, and InceptionNet models, which achieved accuracy values of no more than 86.35%.
Good results were also obtained by other authors, such as an accuracy of 90% reached by Akatsuka et al. [176] using a DenseNet model or an accuracy of 99% obtained by Pesce et al. [175] using a feature-based ANN, a slower but slightly better performing model of Watson Visual Recognition (WVR), which, unlike the former, analyzes and classifies images directly without requiring manual feature extraction. An accuracy of 98.62% was obtained with the WVR model.
Identifying the presence of chronic kidney disease can also be achieved through precise analysis of relevant substances in the renal field. In this regard, some important factors are extracellular calcium and already mentioned potassium ionic concentrations [178], albuminuria levels [179], or urea levels in the saliva sample [180]. Artificial neural networks [178], the combination of deep and not deep algorithms [180], or the use of rule extraction algorithms DT-based as continuous Recursive Rule eXtraction (Re-RX) to make deep models interpretable in presence of continuous variables [179], performed well in terms of accuracy (77.56% [179], 98.04% [180]) or test error (0.01, [178]).
A novel approach using images was finally presented by Sabanayagam et al. [181] and Zhang et al. [182], who developed deep learning algorithms alone [182] or supported by clinical risk factor analysis models [181] to detect chronic kidney disease from retinal fundus photographs, obtaining AUC-ROC values exceeding 81%. Detection of CKD is possible because deteriorating kidney function causes retinal problems such as vascular endothelial dysfunction, chronic inflammation, and thrombosis status, which are easily detected with artificial intelligence tools for image analysis. By developing this type of AI model, the authors in ref. [181,182] have thus contributed to a potential improvement in the complex process of diagnosing kidney disease.
Table 5 reports a list of all quoted literature works, providing key details on adopted models, a brief description of the dataset employed and their origin, the number and type of features used to train the model, the results, in terms of performance parameters, obtained by the best performing model among those tested, and in the last column, the purpose of the work.
Table 5.
Literature overview on Machine Learning (ML) models developed for kidney disease detection.
3.3. Machine Learning as an Assistant Tool for Nephrologists
The number of patients with end-stage kidney disease needing renal replacement therapy is estimated to be between ~4.9 and ~7.1 million [64] globally.
Dialysis is certainly a life-saving therapy for patients with end-stage kidney disease, but there are many problems that can affect them, such as maintaining a stable volume or pressure during dialysis sessions or the onset of dialysis disorders, such as cramps.
New approaches based on artificial intelligence techniques can identify volume-related adverse events, hypotension, or general discomfort during the treatment.
These are just some of the many applications of artificial intelligence as a tool to assist nephrologists in the complex management of hemodialysis therapies.
IntraDialytic Hypotension (IDH) is the main complication of hemodialysis treatment, since it affects more than 10% of patients undergoing treatment [183]. Many authors have addressed this problem using artificial intelligence models, attempting to predict IDH [184,185,186,187] and other minor dialysis discomfort [188,189] at the start of therapy on the basis of clinical and analytical data from patients. These findings collectively highlighted that blood pressure trends, ultrafiltration rate, and patient comorbidities are the strongest predictors of IDH, indicating that future AI-based tools should integrate both static patient characteristics and dynamic intradialytic signals to optimize therapy. Using different approaches, from the simplest machine learning models [185,189] to the most complex neural networks [186,188], part of these studies resulted in accuracy [186,188,189] or AUC-ROC [185] values of over 96%. Particularly interesting is the model bCOWOA-KELM [184], where the “binary COvariance” (bCO) matrix-driven version of the Whale Optimization Algorithm (WOA) was used to select better than other optimization algorithms the most relevant features for the Kernel Extreme Learning Machine (KELM), a type of feedforward neural network with a single hidden layer capable of handling non-linear data. Although it achieved a slightly lower accuracy, equal to 92.41%, this model turns out to be the most structurally complex among those proposed. Relevant is also the “Robust Deep Learning-based Clinical Data Classification” (RDLCDC), developed by Mohammed et al. [186], optimizing a CNN with the Sparrow Search Optimization (SSO), an algorithm able to adjust critical parameters related to the structure of AI models. Given its specific application, the model was more precisely named RDLCDC-IDH, with which the authors obtained an IDH diagnostic accuracy of 97.70%.
The high performance obtained by these models demonstrates their potential to serve as a valuable aid in the management of intradialytic hypotension, provided that future studies focus on improving their generalizability and transparency, thereby facilitating safe and trustworthy clinical deployment.
A second major problem in hemodialysis therapies concerns the atherosclerotic fistula, which is often subject to aneurysms, systoles, or infections due to the continuous stress it undergoes during treatment. Some authors have, therefore, developed models capable of diagnosing such problems by analyzing audio recordings [190,191], patients’ data [192], or images [193,194]. Specifically, using audio recordings, Song et al. [190] developed a ResNet combined with an ANN to non-invasively diagnose stenosis in arteriovenous fistulas, while Ota et al. [191] used a CNN in combination with LSTM and GRU to evaluate and classify arteriovenous bruits. Both achieved good results, more than 90% in F1-Score for the first case, and up to 92% in AUC-ROC value for the second one. The use of clinical and demographic data combined with models such as XGBoost, RF, and multiple regression then allowed Balamuthusamy et al. [192] to predict with an accuracy of 86% the risk of stratification and re-interventions on arteriovenous access, which passed from 1.8 to 1.1 per patient for one year. The problem of arteriovenous aneurysms or other complications, such as nerve injury, hematoma, or emphysema, was, respectively, addressed by Zhang et al. [193] and Hong [194], who used CNNs for their optimal classification and care. These studies demonstrated how early and accurate detection of access dysfunction could allow nephrologists to intervene before thrombosis or infection occurs, potentially extending fistula lifespan and reducing the need for re-interventions, an important component of optimizing long-term dialysis therapy.
To predict these potential complications, many researchers have also developed models capable of well predicting the values of important parameters in therapy, such as Kt/V, heart rate, and blood pressure [195] with ANNs, or classifying the values of serum creatinine [196] with simpler ML models. Specifically, the values of serum creatinine were classified by Brito et al. [196] with an accuracy over 95% on an unusual dataset, i.e., patients undergoing peritoneal dialysis treatment, using kNN-based algorithms as IBk and kStar, or tree-based models as random forest, Reduced Error Pruning Tree (REPTree), and RandomTree. IBk and kStar are algorithms where the distance between values is calculated with the Euclidean distance and the entropy, respectively, while REPTree and RandomTree are single-tree algorithms optimized to improve generalization and reduce overfitting compared with standard decision trees.
Many authors have also developed AI models aimed at studying fluid overload [197] and atherosclerotic plaque formation [198] in hemodialyzed patients or the most significant parameters for screening the patients at high risk [199]. Among them, a particularly interesting study was presented by Tan et al. [197], who obtained comparable results using both YOLACT and Mask R-CNN on Lung UltraSound (LUS) images. Despite the simplicity of YOLACT, a model that detects and segments objects of interest in a single pass for the identification of the fluid overload, the authors achieved the same recall value of 83.30% obtained with the more complex Mask R-CNN model, which works in multiple passes to achieve the same goal. However, regardless of model complexity, both models clearly demonstrate that real-time fluid status assessment could support the implementation of adaptive ultrafiltration profiles, allowing fluid removal to be tailored to each patient’s hemodynamic tolerance and potentially minimizing cardiovascular stress.
Equally innovative, Kanda et al. [199] analyzed hemodialysis patients in Japan by dividing them into clusters using the unsupervised k-means algorithm, where k represents the number of clusters. In their model, each cluster represented a distinct patient group with shared health profiles and potential risk factors, ensuring that patients within a cluster had more homogeneous health profiles. Each cluster was then analyzed with an SVM model for capturing and predicting the unique outcome patterns associated with each cluster’s characteristics more accurately than a single, unified model. The results of the individual SVM models were finally merged to generate an overall risk prediction for the entire patient population, taking advantage of the detailed analysis of each cluster. Figure 14 shows a graphical representation of this innovative ensemble model used by the authors.
Figure 14.
Structure of the ensemble model used to classify dialysis patients according to their risk level. Reproduced from Kanda et al. [199].
Compared to simple machine learning models applied to a single dataset of mixed patients, this approach allowed the authors to obtain better results in classifying patients according to risk, achieving an accuracy of 94.80% and moving dialysis care closer to a precision-medicine paradigm.
Taken together, all the studies presented in this section therefore demonstrate that AI can not only predict adverse events but also serve as a decision-support tool to dynamically adjust treatment parameters, thereby optimizing both safety and efficacy of hemodialysis. Finally, one of the most popular topics in recent years concerns the use of chatbots for nursing [200] or patient care [201]. Specifically, Cheng et al. [201] implemented an AI ChatBot to be tested on patients at the PD center of the National Taiwan University Hospital in Taiwan. Providing valuable advice to dialysis patients at home, this ChatBot was a great success with the 440 participants, who were 90% satisfied at the end of the test. Qarajeh et al. [200] instead compared different ChatBots, such as ChatGPT, Bard AI, and Bing Chat, to classify foods according to their potassium and phosphorus content. Providing an accuracy of around 80%, this study demonstrated how these modern communication tools, if used correctly, can be really helpful to medical staff and patients themselves in the daily management of the disease, improving their quality of life.
Table 6 reports a list of all quoted literature works, providing key details on adopted models, a brief description of the dataset employed and their origin, the number and type of features used to train the model, the results, in terms of performance parameters, obtained by the best performing model among those tested, and in the last column, the purpose of the work.
Table 6.
Literature overview on Machine Learning (ML) models developed as an assistant tool for nephrologists. Legend: n.a. = not available.
3.4. Machine Learning as a Tool to Predict Long-Term Complications in Dialysis Patients
Another use of artificial intelligence algorithms in the dialysis field regards the prediction of the outcome of the therapy, days, months, or years later. Patients may experience many problems after multiple years of therapy, and careful monitoring of their condition can help to improve their quality of life. The onset of diseases such as anemia and sarcopenia, the prolonged hospital stays of dialysis patients, or their low probability of long-term survival are just some of these possible problems [202,203,204]. Specifically, sarcopenia is the progressive and generalized loss of muscle mass and strength, common in patients with chronic diseases. Anemia, on the other hand, is a condition in which the kidneys do not produce enough erythropoietin, the hormone that stimulates the production of red blood cells. Predicting these diseases can be important to avoid further complications in already compromised patients and permit preventive interventions such as nutritional support, exercise programs, and timely initiation of erythropoiesis-stimulating agents, ultimately helping to preserve functional status and improve quality of life. In this regard, there are numerous applications of AI models in the predictive-therapeutic field, which aim to analyze the clinical conditions of patients and anticipate possible future complications, including the most severe outcomes such as hospitalization or mortality.
Mortality in dialysis patients is a complex problem that can be influenced by several factors. Predicting it [205,206,207] or predicting the key factors responsible for it [208] has attracted the interest of several authors, who have studied the problem using different approaches. These studies not only contribute to understanding the problem but also offer potential solutions to improve patients’ quality of life and reduce mortality rates. Specifically, good and comparable AUC-ROC values were obtained, and several machine learning models were tested, such as the RF model [208] or the more sophisticated ANNs and DNNs [206,207]. Among these, the best predictive model was developed by Díez-Sanmartín et al. [205] using an XGBoost classifier optimized by clustering models and the so-called “False Clustering Discovery Reduction” (FCDR) algorithm, which refined the initial clustering models to reduce the total clusters distinguishing groups with statistically significant differences in risk profiles. By identifying high-risk subgroups, this type of modeling could enable clinicians to adjust dialysis prescriptions, manage comorbidities more aggressively, and potentially schedule closer follow-up for patients most likely to experience adverse outcomes. Implementing this model, an AUC-ROC of 99.09% was achieved.
Despite the slightly lower performance, the work of Noh et al. [206] is noteworthy, as they addressed the same task in terms of the C-index, a more reliable parameter for survival models, as it also considers the time variable, which is highly relevant for optimizing long-term treatment strategies. Comparing models as logistic regression, decision tree, random forest, Ridge, and LASSO, they found that the combination of LSTM and autoencoder exhibited the best performance in the 5-year prediction in terms of AUC-ROC, equal to 85.80%, but not in terms of C-index. The highest C-index, equal to 76.90%, was obtained using a Survival Tree, a DT model capable of predicting the time until an event, such as death. Similarly, Siga et al. [207] implemented an optimized Bayesian neural network capable of predicting patients’ conditions 2 years in advance with an AUC-ROC value of 78%, but without providing information on the C-index value. In its model, the optimization was achieved by building the Bayesian network with an algorithm called “Tree Augmented Naive” (TAN), which relaxed the BNN’s condition according to all variables must be conditionally independent given the output. This allowed the final model to capture more complex relationships between variables and improve its performance.
Other authors have developed ML models capable of predicting more specific problems, such as anemia [209], sarcopenia [210], or loss of arteriovenous fistula patency [211], very common in patients undergoing continuous dialysis treatment. All these studies provided good performance, up to an accuracy equal to 87% obtained by Ohara et al. [209] with their innovative model “Artificial Intelligence Supported Anemia Control System” (AISACS), given by the combination of a deep neural network and a recurrent neural network. Notably, comparing five binary machine learning methods and five tree-based models, Liao et al. [210] found that the voting classifier composed of Log. Reg., AdaBoost, and LGBM models guarantees the best performance in predicting sarcopenia at 3 days in men after the last hemodialysis treatment. Figure 15 presents the models selected to implement the voting classifier.
Figure 15.
Representation of the voting classifier used by Liao et al. [210]. It combines the results of Logistic Regression (Log. Reg.), Adaptive Boosting (AdaBoost), and Light Gradient Boosting Machine (LGBM) models to improve the accuracy of the prediction, considering the “vote” cast by each model and the majority of votes obtained. In the figure, “presence of sarcopenia” is the majority output found by the models involved.
Using this approach for predicting sarcopenia in men, the authors obtained an AUC-ROC value of over 85%, but, for women, the best performing model was SVM, with an AUC-ROC of 77.69%. The features associated with sarcopenia in the female population are subtler and less distinct than in men, an aspect that made the SVM model the best among the classifiers tested, given its good ability to handle complex and nuanced relationships in the data [211].
Evaluating model performance using MAE, Garbelli et al. [211] reported promising predictive results with several classification methods. These included the BINary Classifier Model (BINCM), which uses XGBoost to simplify the problem into binary tasks, the Consistent Ordinal Regression Network (CORN), a neural network that works keeping proper class order, and a classical regression model called “REGM” by the authors, which employs XGBoost for analysis of continuous variables to be mapped into classes at the output. The high MAE values, up to 0.27 applying BINCM, demonstrated the potential of these approaches to improve AVF monitoring in clinical practice and how the integration of such models into routine surveillance protocols could allow earlier interventions, preserve vascular access longevity, and reduce costly surgical procedures.
Several authors have also analyzed the occurrence of COVID-19 in dialysis patients or the effects of vaccination cycles. In 2021, Monaghan et al. [212] developed a machine learning model capable of predicting the risk of contracting COVID-19 in HD patients at least 3 days before clinical suspicion of the disease. Using the XGBoost model and analyzing 40,490 patients, the model achieved an AUC-ROC value of 68%, which proved effective given the predictive complexity of the case. For predicting the survival of hemodialysis patients following COVID-19 vaccination, Tang et al. [213] compared several machine learning models, including LGBM, random forest, XGBoost, and CatBoost. They identified the best predictive model in the LGBM model, with an F1-Score of 95% achieved on a cohort of 433 HD patients in Taiwan, highlighting the potential of AI to inform infection control strategies and vaccination policies, which is particularly relevant for the highly vulnerable dialysis population.
Several authors have also developed ML models able to predict the prolonged hospital Length Of Stay (p-LOS) of dialysis patients caused by the onset of complications resulting from home dialysis treatments. As a matter of fact, the hospitalization rate is relatively high in patients undergoing peritoneal dialysis, and the management of those at high risk of p-LOS could improve the management of healthcare resources. In this regard, using simple machine learning models such as the RF model [214] or a stacking model given by the combination of multiple ML models [215], Wu et al. [214] and Kong et al. [215] both achieved AUC-ROC values of approximately 75%.
Altogether, all the studies of this section therefore demonstrate that predictive models can go beyond risk estimation to actively support therapeutic decision-making, allowing nephrologists to tailor interventions, allocate resources more efficiently, and improve long-term survival and quality of life.
Table 7 reports a list of all quoted literature works, providing key details on adopted models, a brief description of the dataset employed and their origin, the number and type of features used to train the model, the results, in terms of performance parameters, obtained by the best performing model among those tested, and in the last column, the purpose of the work.
Table 7.
Literature overview on Machine Learning (ML) models developed as a tool to predict long-term complications in dialysis patients.
3.5. Recent Developments and Emerging Trends in Artificial Intelligence for Nephrology
In recent years, research on artificial intelligence applied to nephrology has undergone a paradigm shift, driven by the rapid adoption of foundation models, large transformer architectures pre-trained on massive datasets, and then adapted to diverse downstream tasks. As introduced in Section 2.2, transformer attention mechanisms enable the transfer of knowledge to text, images, and, more recently, multimodal clinical data, enabling flexible fine-tuning or in-context learning with limited labeled nephrology datasets.
Used in a consistent way, these methods have seen a marked acceleration and have reached their peak impact over the last three years, as shown in Figure 16.
Figure 16.
Number of publications per year on Artificial Intelligence (AI) applications related to the topic kidney disease and relevant therapies in the time interval 2019–2025. The research on the Scopus database used “Artificial Intelligence”, “Kidney Diseases”, and “Hemodialysis” as key search words, limited to English-language publications. Information updated on the 12th September 2025.
Specifically, this acceleration has led to a new generation of artificial intelligence systems capable of integrating heterogeneous sources of information, from laboratory data and imaging to clinical narratives, producing more robust and clinically meaningful predictions. Recent studies have shown that transformer-based models, compared with traditional machine learning models, can improve early identification of kidney disease, prediction of dialysis complications, and automated interpretation of renal pathology slides, while also providing attention maps and feature attribution that enhance interpretability for clinicians [216]. In addition, multimodal approaches combining imaging and clinical variables have demonstrated very high performance in differentiating diabetic nephropathy from non-diabetic renal disease and in improving pathologists’ confidence in membranous nephropathy diagnosis, compared to what has been performed in the past with less advanced models [217,218]. In this regard, recent reviews emphasized that multimodal AI is becoming a key tool to integrate imaging, laboratory data, and electronic health records in a single predictive framework, paving the way for automated, standardized, and explainable nephrology decision support [219]. Similarly, temporal attention architectures applied to hemodialysis time-series data have achieved AUC-ROC values close to 0.95 for intradialytic hypotension prediction, showing that such models can be deployed prospectively and offer real-time alerts [220].
Another emerging trend is the integration of large language models and conversational agents into nephrology practice. Notably, these models are increasingly being used to educate patients, answer common questions, support triage, and provide quick summaries of clinical guidelines for healthcare professionals, making access to information easier and improving patient engagement.
As evidence of this, early pilot studies have shown improvements in patient engagement and adherence to dietary and fluid intake recommendations [221,222], highlighting their potential role in participatory nephrology care. Their ability to perform reasoning, enhanced by the retrieval of clinical knowledge, lays the foundation for a future in which both patients and physicians will benefit from real-time, dialogue-based access to relevant medical information.
Alongside this shift towards transformers and, more specifically, foundation models, recent years have seen continued improvements in the performance of more classical machine learning approaches. Among these, random forest and gradient boosting models have been refined with larger, multicenter datasets, showing improved calibration and discrimination for predicting chronic kidney disease progression and acute kidney injury, in some cases reaching AUC-ROC values close to those of deep learning systems while remaining simpler and more transparent [223,224,225]. In addition, logistic regression-based tools such as the Kidney Failure Risk Equation (KFRE) have been validated in diverse populations, leading to recalibrated thresholds and improved applicability in non-North American cohorts. In regard to medical imaging, U-Net and its recent variants are still the backbone of kidney and tumor segmentation challenges, achieving composite Dice scores above 90% [226,227] and remaining competitive baselines against which transformer-based architectures are now compared. In addition, recent years have seen classical AI approaches applied in new domains of nephrology care, ranging from surrogate models for the prediction of the urea dialyzer clearance (R2 > 0.99) [228], to algorithms that estimate the most appropriate operational dialysis variables for each patient (R2 > 0.65) [229], or anticipate possible dialysis machine failures during sensor calibration tests [230].
Ultimately, these developments demonstrate that the evolution of AI in nephrology is occurring on multiple fronts: while foundation models expand the frontier of multimodal and interactive applications, classical machine learning continues to be optimized and remains highly relevant, especially where model simplicity, interpretability, and ease of clinical implementation are priorities.
3.6. Limitations and Challenges of Artificial Intelligence in Clinical Adoption
Although these studies highlight the remarkable performance of artificial intelligence models applied in nephrology, their results must be interpreted with caution. First, it should be emphasized that, despite some progress described in the previous section, most of the literature is still based on retrospective, single-center cohorts with limited demographic diversity, which makes the reported results highly context-dependent. This is because such datasets may lead to overfitting and generate models that are not transferable to heterogeneous populations or different healthcare infrastructures. Furthermore, frequent imbalances in case-control distributions and the lack of robust cross-validation or prospective testing reduce reliability, meaning that high technical performance does not necessarily translate into clinical benefit.
In addition, many deep learning and transformer-based models achieve outstanding predictive accuracy but remain “black boxes”, offering little transparency into the clinical rationale of their predictions. While methods already mentioned in Section 2.4, such as SHAP, LIME, and Grad-CAM, provide partial insights, their application is inconsistent and often difficult to interpret in real-time clinical settings.
Regulatory approval also remains a moving target, especially for generative models that change dynamically with continuous training, raising challenges for certification, monitoring, and liability. Along with this, such systems also face reproducibility issues and high computational cost, as well as ethical concerns regarding fairness, bias, and patient data privacy, particularly when datasets underrepresent minority or vulnerable populations.
Therefore, to move from proof-of-concept to real-world use, several hurdles need to be overcome, including external validation on large, multicenter datasets to ensure robustness and fairness, and improved interpretability to help clinicians understand the reasoning behind predictions. Regulatory pathways would also have to evolve to clarify approval and post-deployment monitoring, while hospital integration would need to be seamless and interoperable with EHRs and dialysis platforms, without adding burden to physicians. Finally, training programs for clinicians would be essential to foster trust and encourage appropriate adoption.
If these limitations are adequately addressed, AI could profoundly transform nephrology. Specifically, potential benefits include earlier and more accurate risk stratification, proactive detection of chronic kidney disease and acute kidney injury, real-time decision support for dialysis therapy, and optimized allocation of transplant organs. For patients, this could translate into longer survival, improved quality of life, and more equitable access to treatment. Conversely, uncritical adoption of such algorithms may lead to algorithmic bias, misclassification, reduced physician-patient communication, and excessive dependence on systems that lack transparency. It would, therefore, be crucial to adopt a balanced approach, leveraging AI as an augmentative tool rather than a substitute for clinical judgment, ensuring that technological progress does not come at the expense of empathy and human care.
4. Conclusions and Outlooks
This review has reported recent AI developments and advances in kidney disease diagnosis and hemodialysis treatment assistance. The innovations made by AI in this sector are noteworthy. Specifically, this review has focused on artificial intelligence research in the renal field conducted between 2019 and 2023. The papers discussed in the first part of this review have demonstrated how AI-based results support early prediction and determine the level of risk during the diagnosis of acute and chronic kidney disease, with a special focus on patients with previous pathologies, which are responsible for further deterioration of kidney function. The second part of this review has focused more specifically on patients with end-stage renal disease, covering artificial intelligence papers aimed at optimally predicting long-term complications of patients undergoing dialysis treatment and assisting nephrologists’ decision-making in managing therapy.
Most of these papers preferred the use of machine learning algorithms to deep learning models because of their greater simplicity of implementation and their greater interpretability, a key aspect for physicians who wish to understand the reasoning behind the models before adopting them into patient care. At the same time, DL approaches such as convolutional neural networks have shown great potential in medical image analysis, despite their greater complexity. Therefore, an important future challenge will be to balance interpretability and predictive power by making deep learning algorithms more transparent and accessible to healthcare professionals.
In addition, there is a significant disparity in the existing literature between papers dealing with AI techniques applied to prediction and therapy. While the first part of this review has highlighted a large number of studies on the role of AI in early prediction and risk determination during kidney disease diagnosis, the second part, which delves into end-stage renal disease and dialysis-related applications of AI, is relatively underrepresented. This imbalance underscores a crucial gap in current research, as end-stage renal disease patients make up a significant proportion of those in need of advanced medical support. Bridging this gap is essential to ensure that AI innovations comprehensively address the different stages of kidney disease and associated therapeutic challenges.
In conclusion, it is worth noting that true clinical trials, in which artificial intelligence models are directly integrated into real-world medical workflows as practical tools, have yet to be fully implemented. So far, these methods have been tested to prove their effectiveness compared to traditional approaches, but they have never been adopted as part of standard practices in clinical settings.
Contributing factors include clinicians’ skepticism toward automated systems, limited digital infrastructure in some healthcare environments, and the absence of clear regulatory frameworks. Overcoming these barriers will require targeted educational efforts to build trust among physicians, as well as investment in technological resources and institutional support. These measures would strengthen collaboration with healthcare providers and support the clinical validation of the models presented in this paper, which is essential for their integration into routine medical practice.
Author Contributions
Conceptualization, A.N., N.C., J.D.M.G., I.T. and A.C.; methodology, A.N., N.C. and A.C.; software, A.N., J.D.M.G. and I.T.; validation, J.D.M.G., I.T. and A.C.; formal analysis, A.N. and N.C.; investigation, A.N., N.C. and A.C.; resources, A.C.; data curation, A.N., I.T. and J.D.M.G.; writing—original draft preparation, A.N., N.C. and A.C.; writing—review and editing, A.N., N.C., J.D.M.G., I.T. and A.C.; visualization, A.N. and N.C.; supervision, J.D.M.G., I.T. and A.C.; project administration, A.C.; funding acquisition, A.C. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in the study are included in the article, further inquiries can be directed to the corresponding author.
Acknowledgments
The authors acknowledge the financial support of Mozarc Medical® (Mirandola, MO, Italy) and the Piano Nazionale di Ripresa e Resilienza (38-033-20-DOT204NJ79-3458), DM 352 M4C2 I., for funding the PhD scholarship of Alessia Nicosia.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
| ACO | Ant Colony-based Optimization |
| ACR | Albumin-to-Creatinine Ratio |
| AdaBoost | Adaptive Boosting |
| ADAM | ADAptive Moment estimation |
| ADR | ADRamycin |
| AHDCNN | Adaptive Hybridized Deep Convolutional Neural Network |
| AI | Artificial Intelligence |
| AISACS | Artificial Intelligence Supported Anemia Control System |
| AKI | Acute Kidney Injury |
| AlexNet | Alex Network |
| ANN | Artificial Neural Network |
| AP | Average Precision |
| APC | Atherosclerotic Plaque Characteristics |
| AUC-PR | Area Under the Precision-Recall Curve |
| AUC-ROC | Area Under the Receiver Operating Characteristic Curve |
| AUSCAD | AUStralian Chronic Allograft Dysfunction |
| AVF | ArterioVenous Fistula |
| bCO | binary COvariance |
| BDF | Bahrain Defence Force |
| BES | Beijing Eye Study |
| BIDMC | Beth Israel Deaconess Medical Center |
| BINCM | BINary Classifier Model |
| BiT-M | Big Transfer-Medium |
| BiT-S | Big Transfer-Small |
| BNN | Bayesian Neural Network |
| BoW | Bag-of-Words |
| CART | Classification And Regression Tree |
| CatBoost | Categorical Boosting |
| CC-FII | China Consortium of Fundus Image Investigation |
| ccRCC | clear-cell Renal-Cell Carcinoma |
| CCT | Contrast-enhanced Computed Tomography |
| CCTA | Coronary Computed Tomography Angiography |
| ChatGPT | Chat Generative Pre-trained Transformer |
| C-index | Concordance index |
| CIT | Conditional Inference Tree |
| CKD | Chronic Kidney Disease |
| CKDu | Chronic Kidney Disease of unknown etiology |
| CNN | Convolutional Neural Network |
| COCO | Common Objects in COntext |
| Col4a3 KO | Collagen Type IV Alpha 3 Chain Knock-Out |
| CondenseNet | Condensed Network |
| CORN | Consistent Ordinal Regression Network |
| CPTAC | Clinical Proteomic Tumor Analysis Consortium |
| CSA-AKI | Cardiac Surgery-Associated Acute Kidney Injury |
| CT | Computational Tomography |
| DCDLT | Donation after Cardiac Death Liver Transplantation |
| DDLT | Deceased-Donor Liver Transplantation |
| DEMATEL | Decision Making Trial And Evaluation Laboratory |
| DenseNet | Dense Network |
| DETO | Department of Emergency and Organ Transplantations |
| DFS | Density-based Feature Selection |
| DINO-ViT | DIstillation with NO labels-Vision Transformer |
| DISPO | Dynamic Integrative System for Predicting Outcome |
| DL | Deep Learning |
| DNN | Deep Neural Network |
| DPCNN | Dual-Path Convolutional Neural Network |
| DS-GBT | Deep Support-Gradient Boosting Trees |
| DT | Decision Tree |
| ECG | ElectroCardioGram |
| eGFR | estimated Glomerular Filtration Rate |
| EHR | Electronic Health Record |
| eICU | electronic Intensive Care Unit |
| EM | Electron Microscopy |
| EMT | Extended Maxima Transform |
| eqU | equilibrated post-dialysis blood Urea |
| ESKD | End-Stage Kidney Disease |
| EuCliD | European Clinical Database |
| Extra Trees | Extremely Randomized Trees |
| FCDR | False Clustering Discovery Reduction |
| FDA | Fisher Discriminant Analysis |
| FEMH | Far Eastern Memorial Hospital |
| FISS | Focal Instance Structural Similarity |
| FMC | Fresenius Medical Care |
| FN | False Negative |
| FNN | Feedforward Neural Network |
| FP | False Positive |
| FPR | False Positive Rate |
| GAM | Generalised Additive Model |
| GAN | Generative Adversarial Network |
| GBDT | Gradient Boosting Decision Tree |
| GBM | Gradient Boosting Machine |
| GCKD | German Chronic Kidney Disease |
| GGS | Global GlomeruloSclerosis |
| GMM | Gaussian Mixture Model |
| GoCAR | Genomics of Chronic Allograft Rejection |
| Grad-CAM | Gradient-weighted Class Activation Mapping |
| GRNN | Generalised Regression Neural Network |
| GRU | Gated Recurrent Unit |
| GSA | Gravitational Search Algorithm |
| HD | HemoDialysis |
| HDF | HemoDiaFiltration |
| HERON | Healthcare Enterprise Repository for Ontological Narration |
| HF | HemoFiltration |
| HGSAPSO | Hybrid Gravitational Search Algorithm and Particle Swarm Optimization |
| HIS | Hospital Information System |
| HQMS | Hospital Quality Monitoring System |
| ICU | Intensive Care Unit |
| IDEA | Intraoperative and Data Embedded Analytics |
| IDH | IntraDialytic Hypotension |
| IDS | Intelligent Dosing System |
| IFTA | Interstitial Fibrosis and Tubular Atrophy |
| IgAN | Immunoglobulin A Nephropathy |
| InceptionNet | Inception Network |
| InceptionResNet-v2 | Inception-Residual Network version 2 |
| IoT | Internet of Things |
| JSDT | Japanese Society for Dialysis Therapy |
| KD | Kidney Disease |
| KDQOL | Kidney Disease Quality Of Life |
| KELM | Kernel Extreme Learning Machine |
| KFRE | Kidney Failure Risk Equation |
| KH | Kitano Hospital |
| kNN | k-Nearest Neighbors |
| LASSO | Least Absolute Shrinkage and Selection Operator |
| LDA | Linear Discriminant Analysis |
| LGBM | Light Gradient Boosting Machine |
| LIME | Local Interpretable Model-agnostic Explanations |
| LLC | Limited Liability Company |
| LLM | Large Language Model |
| Log. Reg. | Logistic Regression |
| LogitBoost | Logistic Boosting |
| LR | Linear Regression |
| LSTM | Long Short Term Memory |
| LUS | Lung UltraSound |
| MAE | Mean Absolute Error |
| MANet | Multiple-Attention Network |
| mAP | mean Average Precision |
| Mask R-CNN | Mask Region-based Convolutional Neural Network |
| MCC | Matthews Correlation Coefficient |
| MCD | Minimal Change Disease |
| MHD | Maintenance HemoDialysis |
| MIL | Multiple Instance Learning |
| MIMIC-III/IV | Medical Information Mart for Intensive Care III/IV |
| ML | Machine Learning |
| MLP | MultiLayer Perceptron |
| MMDLM | MultiModal Deep Learning Model |
| MN | Membranous Nephropathy |
| MN-Net | Membranous Nephropathy Network |
| MRI | Magnetic Resonance Image |
| MSE | Mean Squared Error |
| NASNet | Neural Architecture Search Network |
| NB | Naive Bayes |
| NCCT | Non-Contrast Computed Tomography |
| NHANES | National Health And Nutrition Examination Survey |
| NHISS | National Health Insurance Sharing Service |
| NHS | National Health Service |
| NIH | National Institutes of Health |
| NLP | Natural Language Processing |
| NMR | Nuclear Magnetic Resonance |
| NN | Neural Network |
| OPTN | Organ Procurement and Transplantation Network |
| PACS | Picture Archiving and Communication System |
| PCNL | PerCutaneous NephroLithotomy |
| p-LOS | prolonged Length Of Stay |
| PNN | Probabilistic Neural Network |
| post-EVAR | post-EndoVascular Aneurysm Repair |
| PSO | Particle Swarm Optimization |
| QDA | Quadratic Discriminant Analysis |
| RBFNN | Radial Basis Function Neural Network |
| RDLCDC | Robust Deep Learning-based Clinical Data Classification |
| REPTree | Reduced Error Pruning Tree |
| Re-RX | Recursive Rule eXtraction |
| ResNet | Residual Network |
| RF | Random Forest |
| RMDS | Renal Mass Diagnostic System |
| RMSE | Root Mean Squared Error |
| RMSPROP | Root Mean Square PROPagation |
| RNN | Recurrent Neural Network |
| RWTH | Rheinisch-Westfälische Technische Hochschule |
| SACNN | Self-Attention Convolutional Neural Network |
| SB | Surface-Based |
| SEED | Singapore Epidemiology of Eye Diseases |
| Seq2Seq | Sequence-To-Sequence |
| SFS | Sequential Forward Selection |
| SGDM | Stochastic Gradient Descent with Momentum |
| SHAP | SHapley Additive exPlanations |
| SimpleRNN | Simple Recurrent Neural Network |
| SOA | Season Optimization Algorithm |
| SP2 | Singapore Prospective Study Program |
| SqueezeNet | Squeeze Network |
| SRI | Solute Removal Index |
| SRTR | Scientific Registry of Transplant Recipients |
| SRU | Simple Recurrent Unit |
| SSA | Slice Scanning Algorithm |
| SSD | Single Shot Detector |
| SSO | Sparrow Search Optimization |
| SVM | Support Vector Machine |
| TAN | Tree Augmented Naive |
| TCGA | The Cancer Genome Atlas |
| TN | True Negative |
| TP | True Positive |
| TPR | True Positive Rate |
| UAAN | Uncertainty-Aided Apportionment Network |
| U-Net | U-Network |
| UNETR | U-NEt TRansformer |
| US | UltraSound |
| UTH | University of Tokyo Hospital |
| VA | Veterans Affairs |
| VAE | Variational AutoEncoder |
| VB-MrFo-Net | V Bottleneck Multi-resolution and Focus-organ Network |
| VGG-16/19 | Visual Geometry Group 16/19 |
| VGH | Veterans General Hospital |
| VIT | Vellore Institute of Technology |
| ViT | Vision Transformer |
| WOA | Whale Optimization Algorithm |
| WSI | Whole-Slide Image |
| WVR | Watson Visual Recognition |
| XAI | eXplainable AI |
| XGBoost | eXtreme Gradient Boosting |
References
- Chen, J.; Remulla, D.; Nguyen, J.H.; Dua, A.; Liu, Y.; Dasgupta, P.; Hung, A.J. Current Status of Artificial Intelligence Applications in Urology and Their Potential to Influence Clinical Practice. BJU Int. 2019, 124, 567–577. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Russell, S.J.; Norvig, P. Artificial Intelligence: A Modern Approach, 4th Global ed.; Prentice Hall series in artificial intelligence; Pearson: Boston, MA, USA, 2022; ISBN 978-1-292-40113-3. [Google Scholar]
- Montesinos López, O.A.; Montesinos López, A.; Crossa, J. (Eds.) Fundamentals of Artificial Neural Networks and Deep Learning. In Multivariate Statistical Machine Learning Methods for Genomic Prediction; Springer International Publishing: Cham, Switzerland, 2022; pp. 379–425. ISBN 978-3-030-89010-0. [Google Scholar]
- Magris, M.; Iosifidis, A. Bayesian Learning for Neural Networks: An Algorithmic Survey. Artif. Intell. Rev. 2023, 56, 11773–11823. [Google Scholar] [CrossRef] [Scilit]
- Mori, F.; Tsuji, H. A System for Decision Support without Explicit Objective Functions. Omega 1983, 11, 567–574. [Google Scholar] [CrossRef] [Scilit]
- Okajima, M.; Stark, L.; Whipple, G.; Yasui, S. Computer Pattern Recognition Techniques: Some Results with Real Electrocardiographic Data. IRE Trans. Bio-Med. Electron. 1963, 10, 106–114. [Google Scholar] [CrossRef]
- Gagliardo, E. An Example of a Test for Adaptive Techniques in a Medical Investigation. Comput. Biol. Med. 1975, 5, 97–104. [Google Scholar] [CrossRef] [Scilit]
- Davis, R.; Buchanan, B.; Shortliffe, E. Production Rules as a Representation for a Knowledge-Based Consultation Program. Artif. Intell. 1977, 8, 15–45. [Google Scholar] [CrossRef] [Scilit]
- Heppner, G.H.; Stolbach, L.; Byrne, M.; Cummings, F.J.; McDonough, E.; Calabresi, P. Cell-Mediated and Serum Blocking Reactivity to Tumor Antigens in Patients with Malignant Melanoma. Int. J. Cancer 1973, 11, 245–260. [Google Scholar] [CrossRef] [Scilit]
- Pauker, S.G.; Gorry, G.A.; Kassirer, J.P.; Schwartz, W.B. Towards the Simulation of Clinical Cognition: Taking a Present Illness by Computer. Am. J. Med. 1976, 60, 981–996. [Google Scholar] [CrossRef] [Scilit]
- Chen, T.K.; Knicely, D.H.; Grams, M.E. Chronic Kidney Disease Diagnosis and Management. JAMA 2019, 322, 1294–1304. [Google Scholar] [CrossRef] [Scilit]
- Ram, E.; Beckerman, P.; Segev, A.; Shlomo, N.; Atlas-Lazar, A.; Sternik, L.; Raanani, E. The Predictive Value of Creatinine Clearance for Mortality in Patients Undergoing Revascularization. J. Cardiothorac. Surg. 2021, 16, 120. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kovesdy, C.P. Epidemiology of Chronic Kidney Disease: An Update 2022. Kidney Int. Suppl. 2022, 12, 7–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, L.; Wei, Q.; Liu, J.; Yi, M.; Liu, Y.; Liu, H.; Sun, L.; Peng, Y.; Liu, F.; Venkatachalam, M.A.; et al. AKI on CKD: Heightened Injury, Suppressed Repair, and the Underlying Mechanisms. Kidney Int. 2017, 92, 1071–1083. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cancilla, N.; Gurreri, L.; Marotta, G.; Ciofalo, M.; Cipollina, A.; Tamburini, A.; Micale, G. Performance Comparison of Alternative Hollow-Fiber Modules for Hemodialysis by Means of a CFD-Based Model. Membranes 2022, 12, 118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ledebo, I. Principles and Practice of Hemofiltration and Hemodiafiltration. Artif. Organs 1998, 22, 20–25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Teitelbaum, I.; Burkart, J. Peritoneal Dialysis. Am. J. Kidney Dis. 2003, 42, 1082–1096. [Google Scholar] [CrossRef] [Scilit]
- Gan, L.; Razdan, R.; Xu, Y.-Q.; Tsai, J.J.-P. RENPAD: An Expert System for Preliminary Diagnosis of Primary Renal Disease. In WESTEX-87; IEEE: New York, NY, USA, 1987; pp. 231–237. [Google Scholar]
- Agar, J.W.M.; Webb, G.I. Application of Machine Learning to a Renal Biopsy Database. Nephrol. Dial. Transplant. 1992, 7, 472–478. [Google Scholar] [CrossRef] [Scilit]
- Chang, P.L.; Li, Y.C.; Wu, C.J.; Huang, M.H. Using ILIAD System Shell to Create an Expert System for Differential Diagnosis of Renal Masses. J. Med. Syst. 1993, 17, 289–297. [Google Scholar] [CrossRef] [Scilit]
- McMichael, J.; Lieberman, R.; Doyle, H.; McCauley, J.; Fung, J.; Starzl, T.E. An Intelligent and Cost-Effective Computer Dosing System for Individualizing FK506 Therapy in Transplantation and Autoimmune Disorders. J. Clin. Pharmacol. 1993, 33, 599–605. [Google Scholar] [CrossRef] [Scilit]
- Hapgood, W. Using Knowledge Base Systems in Healthcare. Healthc. Inform. Bus. Mag. Inf. Commun. Syst. 1991, 8, 37–38, 41. [Google Scholar]
- Akl, A.I.; Sobh, M.A.; Enab, Y.M.; Tattersall, J. Artificial Intelligence: A New Approach for Prescription and Monitoring of Hemodialysis Therapy. Am. J. Kidney Dis. 2001, 38, 1277–1283. [Google Scholar] [CrossRef] [Scilit]
- Fernández, E.A.; Valtuille, R.; Willshaw, P.; Perazzo, C.A. Using Artificial Intelligence to Predict the Equilibrated Postdialysis Blood Urea Concentration. Blood Purif. 2001, 19, 271–285. [Google Scholar] [CrossRef] [Scilit]
- Ray, M.; Qidwai, U. Artificial Intelligence Approach to Determine Minimum Dose of Haemodialysis. Int. Jt. Conf. Neural Netw. 2003, 1, 137–142. [Google Scholar] [CrossRef] [Scilit]
- Hussain, M.A.; Hamarneh, G.; O’Connell, T.W.; Mohammed, M.F.; Abugharbieh, R. Segmentation-Free Estimation of Kidney Volumes in CT with Dual Regression Forests. In Machine Learning in Medical Imaging; Springer: Berlin/Heidelberg, Germany, 2016; pp. 156–163. [Google Scholar] [CrossRef] [Scilit]
- Norouzi, J.; Yadollahpour, A.; Mirbagheri, S.A.; Mazdeh, M.M.; Hosseini, S.A. Predicting Renal Failure Progression in Chronic Kidney Disease Using Integrated Intelligent Fuzzy Expert System. Comput. Math. Methods Med. 2016, 2016, 6080814. [Google Scholar] [CrossRef] [Scilit]
- Niel, O.; Bastard, P.; Boussard, C.; Hogan, J.; Kwon, T.; Deschênes, G. Artificial Intelligence Outperforms Experienced Nephrologists to Assess Dry Weight in Pediatric Patients on Chronic Hemodialysis. Pediatr. Nephrol. 2018, 33, 1799–1803. [Google Scholar] [CrossRef] [Scilit]
- Nassif, A.B.; Shahin, I.; Attili, I.; Azzeh, M.; Shaalan, K. Speech Recognition Using Deep Neural Networks: A Systematic Review. IEEE Access 2019, 7, 19143–19165. [Google Scholar] [CrossRef] [Scilit]
- Taye, M.M. Understanding of Machine Learning with Deep Learning: Architectures, Workflow, Applications and Future Directions. Computers 2023, 12, 91. [Google Scholar] [CrossRef] [Scilit]
- 1. Supervised Learning. Available online: https://scikit-learn.org/stable/supervised_learning.html (accessed on 26 September 2025).
- 1.9. Naive Bayes. Available online: https://scikit-learn.org/stable/modules/naive_bayes.html (accessed on 26 September 2025).
- Berkson, J. Bayes’ Theorem. Ann. Math. Stat. 1930, 1, 42–56. [Google Scholar] [CrossRef] [Scilit]
- 1.1. Linear Models. Available online: https://scikit-learn.org/stable/modules/linear_model.html (accessed on 26 September 2025).
- Friedman, J.; Hastie, T.; Tibshirani, R. Additive Logistic Regression: A Statistical View of Boosting (With Discussion and a Rejoinder by the Authors). Ann. Stat. 2000, 28, 337–407. [Google Scholar] [CrossRef] [Scilit]
- 1.2. Linear and Quadratic Discriminant Analysis. Available online: https://scikit-learn.org/stable/modules/lda_qda.html (accessed on 26 September 2025).
- James, G.; Witten, D.; Hastie, T.; Tibshirani, R.; Taylor, J. Linear Regression. In An Introduction to Statistical Learning: With Applications in Python; James, G., Witten, D., Hastie, T., Tibshirani, R., Taylor, J., Eds.; Springer International Publishing: Cham, Switzerland, 2023; pp. 69–134. ISBN 978-3-031-38747-0. [Google Scholar]
- 1.4. Support Vector Machines. Available online: https://scikit-learn.org/stable/modules/svm.html (accessed on 26 September 2025).
- 1.10. Decision Trees. Available online: https://scikit-learn.org/stable/modules/tree.html (accessed on 26 September 2025).
- 1.11. Ensembles: Gradient Boosting, Random Forests, Bagging, Voting, Stacking. Available online: https://scikit-learn.org/stable/modules/ensemble.html (accessed on 26 September 2025).
- ExtraTreeClassifier. Available online: https://scikit-learn.org/stable/modules/generated/sklearn.tree.ExtraTreeClassifier.html (accessed on 26 September 2025).
- Rodriguez, J.J.; Kuncheva, L.I.; Alonso, C.J. Rotation Forest: A New Classifier Ensemble Method. IEEE Trans. Pattern Anal. Mach. Intell. 2006, 28, 1619–1630. [Google Scholar] [CrossRef] [Scilit]
- Boldini, D.; Grisoni, F.; Kuhn, D.; Friedrich, L.; Sieber, S.A. Practical Guidelines for the Use of Gradient Boosting for Molecular Property Prediction. J. Cheminform. 2023, 15, 73. [Google Scholar] [CrossRef] [Scilit]
- Sarker, I.H. Deep Learning: A Comprehensive Overview on Techniques, Taxonomy, Applications and Research Directions. SN Comput. Sci. 2021, 2, 420. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vaswani, A.; Shazeer, N.; Parmar, N.; Uszkoreit, J.; Jones, L.; Gomez, A.N.; Kaiser, Ł.; Polosukhin, I. Attention Is All You Need. In Advances in Neural Information Processing Systems; Curran Associates, Inc.: Red Hook, NY, USA, 2017; Volume 30. [Google Scholar]
- Lin, T.; Wang, Y.; Liu, X.; Qiu, X. A Survey of Transformers. AI Open 2022, 3, 111–132. [Google Scholar] [CrossRef] [Scilit]
- Elgendy, M. Deep Learning for Vision Systems; Simon and Schuster: New York, NY, USA, 2020; ISBN 978-1-61729-619-2. [Google Scholar]
- Krizhevsky, A.; Sutskever, I.; Hinton, G.E. ImageNet Classification with Deep Convolutional Neural Networks. In Advances in Neural Information Processing Systems; Curran Associates, Inc.: Red Hook, NY, USA, 2012; Volume 25. [Google Scholar]
- Fine, T.L. Feedforward Neural Network Methodology; Springer: New York, NY, USA, 1999; ISBN 978-0-387-98745-3. [Google Scholar] [CrossRef] [Scilit]
- Salem, F.M. Recurrent Neural Networks: From Simple to Gated Architectures; Springer Nature: Berlin/Heidelberg, Germany, 2022; ISBN 978-3-030-89929-5. [Google Scholar] [CrossRef] [Scilit]
- Wang, C.; Zhang, S.; Ma, T.; Xiao, Y.; Chen, M.Z.; Wang, L. Swarm Intelligence: A Survey of Model Classification and Applications. Chin. J. Aeronaut. 2025, 38, 102982. [Google Scholar] [CrossRef] [Scilit]
- Liu, F.; Zheng, H.; Ma, S.; Zhang, W.; Liu, X.; Chua, Y.; Shi, L.; Zhao, R. Advancing Brain-Inspired Computing with Hybrid Neural Networks. Natl. Sci. Rev. 2024, 11, nwae066. [Google Scholar] [CrossRef] [Scilit]
- Ashraf, M.; Abid, F.; Din, I.U.; Rasheed, J.; Yesiltepe, M.; Yeo, S.F.; Ersoy, M.T. A Hybrid CNN and RNN Variant Model for Music Classification. Appl. Sci. 2023, 13, 1476. [Google Scholar] [CrossRef] [Scilit]
- Gurusubramani, S.; Latha, B. Enhancing Cardiac Diagnostics through Semantic-Driven Image Synthesis: A Hybrid GAN Approach. Neural Comput. Appl. 2024, 36, 8181–8197. [Google Scholar] [CrossRef] [Scilit]
- Miller, C.; Portlock, T.; Nyaga, D.M.; O’Sullivan, J.M. A Review of Model Evaluation Metrics for Machine Learning in Genetics and Genomics. Front. Bioinform. 2024, 4, 1457619. [Google Scholar] [CrossRef] [Scilit]
- Singh, P.; Goyal, L.; Mallick, D.C.; Surani, S.R.; Kaushik, N.; Chandramohan, D.; Simhadri, P.K. Artificial Intelligence in Nephrology: Clinical Applications and Challenges. Kidney Med. 2025, 7, 100927. [Google Scholar] [CrossRef] [Scilit]
- Iliyas, I.I.; Boukari, S.; Gital, A.Y. Recent Trends in Prediction of Chronic Kidney Disease Using Different Learning Approaches: A Systematic Literature Review. J. Med. Artif. Intell. 2025, 8, 62. [Google Scholar] [CrossRef] [Scilit]
- Cama-Olivares, A.; Braun, C.; Takeuchi, T.; O’Hagan, E.C.; Kaiser, K.A.; Ghazi, L.; Chen, J.; Forni, L.G.; Kane-Gill, S.L.; Ostermann, M.; et al. Systematic Review and Meta-Analysis of Machine Learning Models for Acute Kidney Injury Risk Classification. J. Am. Soc. Nephrol. 2024, 10-1681. [Google Scholar] [CrossRef] [Scilit]
- Rehman, A.U.; Neyra, J.A.; Chen, J.; Ghazi, L. Machine Learning Models for Acute Kidney Injury Prediction and Management: A Scoping Review of Externally Validated Studies. Crit. Rev. Clin. Lab. Sci. 2025, 62, 454–476. [Google Scholar] [CrossRef] [Scilit]
- Li, C.; Liu, J.; Fu, P.; Zou, J. Artificial Intelligence Models in Diagnosis and Treatment of Kidney Diseases: Current Status and Prospects. Kidney Dis. 2025, 11, 501–517. [Google Scholar] [CrossRef] [Scilit]
- Ghosh, S.K.; Khandoker, A.H. Investigation on Explainable Machine Learning Models to Predict Chronic Kidney Diseases. Sci. Rep. 2024, 14, 3687. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Wang, P.; Zhu, Y.; Zhao, W.; Pan, H.; Wang, D. Interpretable Machine Learning Model for Predicting Acute Kidney Injury in Critically Ill Patients. BMC Med. Inform. Decis. Mak. 2024, 24, 148. [Google Scholar] [CrossRef] [Scilit]
- Gao, Y.; Wang, C.; Dong, W.; Li, B.; Wang, J.; Li, J.; Tian, Y.; Liu, J.; Wang, Y. An Explainable Machine Learning Model to Predict Acute Kidney Injury After Cardiac Surgery: A Retrospective Cohort Study. Clin. Epidemiol. 2023, 15, 1145–1157. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lv, J.-C.; Zhang, L.-X. Prevalence and Disease Burden of Chronic Kidney Disease. Adv. Exp. Med. Biol. 2019, 1165, 3–15. [Google Scholar] [CrossRef] [Scilit]
- Ferro, C.J.; Wanner, C.; Luyckx, V.; Fontana, M.; Gallego, D.; Vanholder, R.; Torra, R.; Ortiz, A. A Call for Urgent Action on Chronic Kidney Disease across Europe. Lancet Reg. Health-Eur. 2025, 54, 101347. [Google Scholar] [CrossRef] [Scilit]
- Kister, T.S.; Remmler, J.; Schmidt, M.; Federbusch, M.; Eckelt, F.; Isermann, B.; Richter, H.; Wehner, M.; Krause, U.; Halbritter, J.; et al. Acute Kidney Injury and Its Progression in Hospitalized Patients—Results from a Retrospective Multicentre Cohort Study with a Digital Decision Support System. PLoS ONE 2021, 16, e0254608. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elhoseny, M.; Shankar, K.; Uthayakumar, J. Intelligent Diagnostic Prediction and Classification System for Chronic Kidney Disease. Sci. Rep. 2019, 9, 9583. [Google Scholar] [CrossRef] [Scilit]
- Arumugham, V.; Sankaralingam, B.P.; Jayachandran, U.M.; Krishna, K.V.S.S.R.; Sundarraj, S.; Mohammed, M. An Explainable Deep Learning Model for Prediction of Early-Stage Chronic Kidney Disease. Comput. Intell. 2023, 39, 1022–1038. [Google Scholar] [CrossRef] [Scilit]
- Pareek, N.K.; Soni, D.; Degadwala, S. Early Stage Chronic Kidney Disease Prediction Using Convolution Neural Network. In Proceedings of the 2023 2nd International Conference on Applied Artificial Intelligence and Computing (ICAAIC), Salem, India, 4–6 May 2023; pp. 16–20. [Google Scholar] [CrossRef] [Scilit]
- Schulz, S.; Woerl, A.-C.; Jungmann, F.; Glasner, C.; Stenzel, P.; Strobl, S.; Fernandez, A.; Wagner, D.-C.; Haferkamp, A.; Mildenberger, P.; et al. Multimodal Deep Learning for Prognosis Prediction in Renal Cancer. Front. Oncol. 2021, 11, 788740. [Google Scholar] [CrossRef] [Scilit]
- Chen, S.; Song, D.; Chen, L.; Guo, T.; Jiang, B.; Liu, A.; Pan, X.; Wang, T.; Tang, H.; Chen, G.; et al. Artificial Intelligence-Based Non-Invasive Tumor Segmentation, Grade Stratification and Prognosis Prediction for Clear-Cell Renal-Cell Carcinoma. Precis. Clin. Med. 2023, 6, pbad019. [Google Scholar] [CrossRef] [Scilit]
- Nasir, M.U.; Zubair, M.; Ghazal, T.M.; Khan, M.F.; Ahmad, M.; Rahman, A.-U.; Hamadi, H.A.; Khan, M.A.; Mansoor, W. Kidney Cancer Prediction Empowered with Blockchain Security Using Transfer Learning. Sensors 2022, 22, 7483. [Google Scholar] [CrossRef] [Scilit]
- Chen, G.; Ding, C.; Li, Y.; Hu, X.; Li, X.; Ren, L.; Ding, X.; Tian, P.; Xue, W. Prediction of Chronic Kidney Disease Using Adaptive Hybridized Deep Convolutional Neural Network on the Internet of Medical Things Platform. IEEE Access 2020, 8, 100497–100508. [Google Scholar] [CrossRef] [Scilit]
- Rabby, A.K.M.S.A.; Mamata, R.; Laboni, M.A.; Ohidujjaman; Abujar, S. Machine Learning Applied to Kidney Disease Prediction: Comparison Study. In Proceedings of the 2019 10th International Conference on Computing, Communication and Networking Technologies (ICCCNT), Kanpur, India, 6–8 July 2019; pp. 1–7. [Google Scholar] [CrossRef] [Scilit]
- Arif-Ul-Islam; Ripon, S.H. Rule Induction and Prediction of Chronic Kidney Disease Using Boosting Classifiers, Ant-Miner and J48 Decision Tree. In Proceedings of the 2019 International Conference on Electrical, Computer and Communication Engineering (ECCE), Cox’s Bazar, Bangladesh, 7–9 February 2019; pp. 1–6. [Google Scholar] [CrossRef] [Scilit]
- Wang, B. Kidney Disease Diagnosis Based on Machine Learning. In Proceedings of the 2020 International Conference on Computing and Data Science (CDS), Stanford, CA, USA, 1–2 August 2020; pp. 307–310. [Google Scholar] [CrossRef] [Scilit]
- Almansour, N.A.; Syed, H.F.; Khayat, N.R.; Altheeb, R.K.; Juri, R.E.; Alhiyafi, J.; Alrashed, S.; Olatunji, S.O. Neural Network and Support Vector Machine for the Prediction of Chronic Kidney Disease: A Comparative Study. Comput. Biol. Med. 2019, 109, 101–111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ogunleye, A.; Wang, Q.-G. XGBoost Model for Chronic Kidney Disease Diagnosis. IEEE/ACM Trans. Comput. Biol. Bioinform. 2020, 17, 2131–2140. [Google Scholar] [CrossRef] [Scilit]
- Akter, S.; Habib, A.; Islam, A.; Hossen, S.; Fahim, W.A.; Sarkar, P.R.; Ahmed, M. Comprehensive Performance Assessment of Deep Learning Models in Early Prediction and Risk Identification of Chronic Kidney Disease. IEEE Access 2021, 9, 165184–165206. [Google Scholar] [CrossRef] [Scilit]
- Poonia, R.C.; Gupta, M.K.; Abunadi, I.; Albraikan, A.A.; Al-Wesabi, F.N.; Hamza, M.A.; B, T. Intelligent Diagnostic Prediction and Classification Models for Detection of Kidney Disease. Healthcare 2022, 10, 371. [Google Scholar] [CrossRef] [Scilit]
- Rajeshwari; Yogish, H.K. Prediction of Chronic Kidney Disease Using Machine Learning Technique. In Proceedings of the 2022 Fourth International Conference on Cognitive Computing and Information Processing (CCIP), Bengaluru, India, 23–24 December 2022; pp. 1–6. [Google Scholar] [CrossRef] [Scilit]
- Rashid, J.; Batool, S.; Kim, J.; Wasif Nisar, M.; Hussain, A.; Juneja, S.; Kushwaha, R. An Augmented Artificial Intelligence Approach for Chronic Diseases Prediction. Front. Public Health 2022, 10, 860396. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Priya, S.; Saranya, N. An Intelligent Approach for Accurate Prediction of Chronic Diseases. CSSE 2023, 46, 2571–2587. [Google Scholar] [CrossRef] [Scilit]
- Moreno-Sánchez, P.A. Data-Driven Early Diagnosis of Chronic Kidney Disease: Development and Evaluation of an Explainable AI Model. IEEE Access 2023, 11, 38359–38369. [Google Scholar] [CrossRef] [Scilit]
- Nunez, I.; Navarro, N.; Saldana Barrios, J. First Experiences in the Process of Developing a Low-Cost Machine Learning Prototype Model Using an Open Access Dataset of Chronic Kidney Diseases—A Case of Study. In Proceedings of the International Conference on Ubiquitous Computing & Ambient Intelligence (UCAmI 2022), Córdoba, Spain, 29 November–2 December 2022; pp. 181–188, ISBN 978-3-031-21332-8. [Google Scholar]
- Revathi, M.; Raghuraman, G.; Visumathi, J. Performance Analysis of Machine Learning Algorithms in the Systematic Prediction of Chronic Kidney Disease on an Imbalanced Dataset. In Inventive Computation and Information Technologies; Smys, S., Kamel, K.A., Palanisamy, R., Eds.; Springer Nature: Singapore, 2023; pp. 149–168. [Google Scholar] [CrossRef] [Scilit]
- Patel, S.; Patel, R.; Ganatra, N.; Khant, S.; Patel, A. An Experimental Study and Performance Analysis of Supervised Machine Learning Algorithms for Prognosis of Chronic Kidney Disease. In Proceedings of the 2022 First International Conference on Electrical, Electronics, Information and Communication Technologies (ICEEICT), Trichy, India, 16–18 February 2022; pp. 1–6. [Google Scholar]
- Bandera, N.H.; Arizaga, J.M.M.; Reyes, E.R. Assessment and Prediction of Chronic Kidney Using an Improved Neutrosophic Artificial Intelligence Model. Int. J. Neutrosophic Sci. 2023, 21, 174–183. [Google Scholar] [CrossRef] [Scilit]
- Pati, A.; Parhi, M.; Pattanayak, B.K. An Ensemble Deep Learning Approach for Chronic Kidney Disease (CKD) Prediction. AIP Conf. Proc. 2023, 2819, 030002. [Google Scholar] [CrossRef] [Scilit]
- Lakshmanaprabu, S.K.; Mohanty, S.N.; Sheeba, R.S.; Krishnamoorthy, S.; Uthayakumar, J.; Shankar, K. Online Clinical Decision Support System Using Optimal Deep Neural Networks. Appl. Soft Comput. 2019, 81, 105487. [Google Scholar] [CrossRef] [Scilit]
- Hamedan, F.; Orooji, A.; Sanadgol, H.; Sheikhtaheri, A. Clinical Decision Support System to Predict Chronic Kidney Disease: A Fuzzy Expert System Approach. Int. J. Med. Inform. 2020, 138, 104134. [Google Scholar] [CrossRef] [Scilit]
- Arulanthu, P.; Perumal, E. An Intelligent IoT with Cloud Centric Medical Decision Support System for Chronic Kidney Disease Prediction. Int. J. Imaging Syst. Technol. 2020, 30, 815–827. [Google Scholar] [CrossRef] [Scilit]
- Kanda, E.; Kanno, Y.; Katsukawa, F. Identifying Progressive CKD from Healthy Population Using Bayesian Network and Artificial Intelligence: A Worksite-Based Cohort Study. Sci. Rep. 2019, 9, 5082. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marechal, E.; Jaugey, A.; Tarris, G.; Paindavoine, M.; Seibel, J.; Martin, L.; Funes de la Vega, M.; Crepin, T.; Ducloux, D.; Zanetta, G.; et al. Automatic Evaluation of Histological Prognostic Factors Using Two Consecutive Convolutional Neural Networks on Kidney Samples. Clin. J. Am. Soc. Nephrol. 2022, 17, 260–270. [Google Scholar] [CrossRef] [Scilit]
- Bell, S.; James, M.T.; Farmer, C.K.T.; Tan, Z.; de Souza, N.; Witham, M.D. Development and External Validation of an Acute Kidney Injury Risk Score for Use in the General Population. Clin. Kidney J. 2020, 13, 402–412. [Google Scholar] [CrossRef] [Scilit]
- Bermudez-Lopez, M.; Forne, C.; Amigo, N.; Bozic, M.; Arroyo, D.; Bretones, T.; Alonso, N.; Cambray, S.; Del Pino, M.D.; Mauricio, D.; et al. An In-Depth Analysis Shows a Hidden Atherogenic Lipoprotein Profile in Non-Diabetic Chronic Kidney Disease Patients. Expert Opin. Ther. Targets 2019, 23, 619–630. [Google Scholar] [CrossRef] [Scilit]
- Rashidi, H.H.; Sen, S.; Palmieri, T.L.; Blackmon, T.; Wajda, J.; Tran, N.K. Early Recognition of Burn- and Trauma-Related Acute Kidney Injury: A Pilot Comparison of Machine Learning Techniques. Sci. Rep. 2020, 10, 205. [Google Scholar] [CrossRef] [Scilit]
- Yue, S.; Li, S.; Huang, X.; Liu, J.; Hou, X.; Zhao, Y.; Niu, D.; Wang, Y.; Tan, W.; Wu, J. Machine Learning for the Prediction of Acute Kidney Injury in Patients with Sepsis. J. Transl. Med. 2022, 20, 215. [Google Scholar] [CrossRef] [Scilit]
- Lei, V.J.; Luong, T.; Shan, E.; Chen, X.; Neuman, M.D.; Eneanya, N.D.; Polsky, D.E.; Volpp, K.G.; Fleisher, L.A.; Holmes, J.H.; et al. Risk Stratification for Postoperative Acute Kidney Injury in Major Noncardiac Surgery Using Preoperative and Intraoperative Data. JAMA Netw. Open 2019, 2, e1916921. [Google Scholar] [CrossRef] [Scilit]
- Adhikari, L.; Ozrazgat-Baslanti, T.; Ruppert, M.; Madushani, R.W.M.A.; Paliwal, S.; Hashemighouchani, H.; Zheng, F.; Tao, M.; Lopes, J.M.; Li, X.; et al. Improved Predictive Models for Acute Kidney Injury with IDEA: Intraoperative Data Embedded Analytics. PLoS ONE 2019, 14, e0214904. [Google Scholar] [CrossRef] [Scilit]
- Schmid, N.; Ghinescu, M.; Schanz, M.; Christ, M.; Schricker, S.; Ketteler, M.; Alscher, M.D.; Franke, U.; Goebel, N. Algorithm-Based Detection of Acute Kidney Injury According to Full KDIGO Criteria Including Urine Output Following Cardiac Surgery: A Descriptive Analysis. BioData Min. 2023, 16, 12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, Z.-L.; Zhou, J.-B.; Liu, Z.-K.; Dong, S.-Y.; Zhang, Y.-T.; Shen, T.; Zheng, S.-S.; Xu, X. Application of Machine Learning Models for Predicting Acute Kidney Injury Following Donation after Cardiac Death Liver Transplantation. Hepatobiliary Pancreat. Dis. Int. 2021, 20, 222–231. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, Y.; Yang, D.; Liu, Z.; Chen, C.; Ge, M.; Li, X.; Luo, T.; Wu, Z.; Shi, C.; Wang, B.; et al. An Explainable Supervised Machine Learning Predictor of Acute Kidney Injury after Adult Deceased Donor Liver Transplantation. J. Transl. Med. 2021, 19, 321. [Google Scholar] [CrossRef] [Scilit]
- Bredt, L.C.; Peres, L.A.B.; Risso, M.; Barros, L.C.d.A.L. Risk Factors and Prediction of Acute Kidney Injury after Liver Transplantation: Logistic Regression and Artificial Neural Network Approaches. World J. Hepatol. 2022, 14, 570–582. [Google Scholar] [CrossRef] [Scilit]
- Mathis, M.R.; Naik, B.I.; Freundlich, R.E.; Shanks, A.M.; Heung, M.; Kim, M.; Burns, M.L.; Colquhoun, D.A.; Rangrass, G.; Janda, A.; et al. Preoperative Risk and the Association between Hypotension and Postoperative Acute Kidney Injury. Anesthesiology 2020, 132, 461–475. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Paquette, F.-X.; Ghassemi, A.; Bukhtiyarova, O.; Cisse, M.; Gagnon, N.; Della Vecchia, A.; Rabearivelo, H.A.; Loudiyi, Y. Machine Learning Support for Decision-Making in Kidney Transplantation: Step-by-Step Development of a Technological Solution. JMIR Med. Inf. 2022, 10, e34554. [Google Scholar] [CrossRef] [Scilit]
- Raynaud, M.; Aubert, O.; Divard, G.; Reese, P.P.; Kamar, N.; Yoo, D.; Chin, C.-S.; Bailly, É.; Buchler, M.; Ladrière, M.; et al. Dynamic Prediction of Renal Survival among Deeply Phenotyped Kidney Transplant Recipients Using Artificial Intelligence: An Observational, International, Multicohort Study. Lancet Digit. Health 2021, 3, e795–e805. [Google Scholar] [CrossRef] [Scilit]
- Kordzadeh, A.; Hanif, M.A.; Ramirez, M.J.; Railton, N.; Prionidis, I.; Browne, T. Prediction, Pattern Recognition and Modelling of Complications Post-Endovascular Infra Renal Aneurysm Repair by Artificial Intelligence. Vascular 2021, 29, 171–182. [Google Scholar] [CrossRef] [Scilit]
- Liu, Y.; Qiu, T.; Hu, H.; Kong, C.; Zhang, Y.; Wang, T.; Zhou, J.; Zou, J. Machine Learning Models for Prediction of Severe Pneumocystis Carinii Pneumonia after Kidney Transplantation: A Single-Center Retrospective Study. Diagnostics 2023, 13, 2735. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tseng, P.-Y.; Chen, Y.-T.; Wang, C.-H.; Chiu, K.-M.; Peng, Y.-S.; Hsu, S.-P.; Chen, K.-L.; Yang, C.-Y.; Lee, O.K.-S. Prediction of the Development of Acute Kidney Injury Following Cardiac Surgery by Machine Learning. Crit. Care 2020, 24, 478. [Google Scholar] [CrossRef] [Scilit]
- Kalisnik, J.M.; Bauer, A.; Vogt, F.A.; Stickl, F.J.; Zibert, J.; Fittkau, M.; Bertsch, T.; Kounev, S.; Fischlein, T. Artificial Intelligence-Based Early Detection of Acute Kidney Injury after Cardiac Surgery. Eur. J. Cardio-Thorac. Surg. 2022, 62, ezac289. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Naser, M.N.; Al-Ghatam, R.; Darwish, A.H.; Alqahtani, M.M.; Alahmadi, H.A.; Mohamed, K.A.; Hasan, N.K.; Perez, N.S. Risk Factors, Predictions, and Progression of Acute Kidney Injury in Hospitalized COVID-19 Patients: An Observational Retrospective Cohort Study. PLoS ONE 2021, 16, e0257253. [Google Scholar] [CrossRef] [Scilit]
- Lu, J.Y.; Zhu, J.; Zhu, J.; Duong, T.Q. Long-Short-Term Memory Machine Learning of Longitudinal Clinical Data Accurately Predicts Acute Kidney Injury Onset in COVID-19: A Two-Center Study. Int. J. Infect. Dis. 2022, 122, 802–810. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, K.-H.; Chu, Y.-C.; Tsai, M.-T.; Tseng, W.-C.; Lin, Y.-P.; Ou, S.-M.; Tarng, D.-C. Artificial Intelligence for Risk Prediction of End-Stage Renal Disease in Sepsis Survivors with Chronic Kidney Disease. Biomedicines 2022, 10, 546. [Google Scholar] [CrossRef] [Scilit]
- Konieczny, A.; Stojanowski, J.; Krajewska, M.; Kusztal, M. Machine Learning in Prediction of IgA Nephropathy Outcome: A Comparative Approach. J. Pers. Med. 2021, 11, 312. [Google Scholar] [CrossRef] [Scilit]
- Schena, F.P.; Anelli, V.W.; Trotta, J.; Di Noia, T.; Manno, C.; Tripepi, G.; D’Arrigo, G.; Chesnaye, N.C.; Russo, M.L.; Stangou, M.; et al. Development and Testing of an Artificial Intelligence Tool for Predicting End-Stage Kidney Disease in Patients with Immunoglobulin A Nephropathy. Kidney Int. 2021, 99, 1179–1188. [Google Scholar] [CrossRef] [Scilit]
- Lokuarachchi, D.N.; Tharindu Manoj, J.V.; Weerasooriya, M.N.H.; Waseem, M.N.M.; Aslam, F.; Kumarasinghe, N.; Kasthurirathne, D. Prediction of CKDu Using KDQOL Score, Ankle Swelling and Risk Factor Analysis Using Neural Networks. In Proceedings of the 2020 2nd International Conference on Advancements in Computing (ICAC), Malabe, Sri Lanka, 10–11 December 2020; pp. 91–96. [Google Scholar]
- Kanda, E.; Okami, S.; Kohsaka, S.; Okada, M.; Ma, X.; Kimura, T.; Shirakawa, K.; Yajima, T. Machine Learning Models Predicting Cardiovascular and Renal Outcomes and Mortality in Patients with Hyperkalemia. Nutrients 2022, 14, 4614. [Google Scholar] [CrossRef] [Scilit]
- Song, X.; Waitman, L.R.; Yu, A.S.L.; Robbins, D.C.; Hu, Y.; Liu, M. Longitudinal Risk Prediction of Chronic Kidney Disease in Diabetic Patients Using a Temporal-Enhanced Gradient Boosting Machine: Retrospective Cohort Study. JMIR Med. Inform. 2020, 8, e15510. [Google Scholar] [CrossRef] [Scilit]
- Wessels, F.; Schmitt, M.; Krieghoff-Henning, E.; Nientiedt, M.; Waldbillig, F.; Neuberger, M.; Kriegmair, M.C.; Kowalewski, K.-F.; Worst, T.S.; Steeg, M.; et al. A Self-Supervised Vision Transformer to Predict Survival from Histopathology in Renal Cell Carcinoma. World J. Urol. 2023, 41, 2233–2241. [Google Scholar] [CrossRef] [Scilit]
- Galloway, C.D.; Valys, A.V.; Shreibati, J.B.; Treiman, D.L.; Petterson, F.L.; Gundotra, V.P.; Albert, D.E.; Attia, Z.I.; Carter, R.E.; Asirvatham, S.J.; et al. Development and Validation of a Deep-Learning Model to Screen for Hyperkalemia From the Electrocardiogram. JAMA Cardiol. 2019, 4, 428–436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, H.; Kong, Y.; Tan, S. Predictive Modeling of Diabetic Kidney Disease Using Random Forest Algorithm along with Features Selection. In Proceedings of the 1st International Symposium on Artificial Intelligence in Medical Sciences, Beijing, China, 11–13 September 2020; Association for Computing Machinery: New York, NY, USA, 2020; pp. 23–27. [Google Scholar] [CrossRef] [Scilit]
- Lee, J.; Warner, E.; Shaikhouni, S.; Bitzer, M.; Kretzler, M.; Gipson, D.; Pennathur, S.; Bellovich, K.; Bhat, Z.; Gadegbeku, C.; et al. Unsupervised Machine Learning for Identifying Important Visual Features through Bag-of-Words Using Histopathology Data from Chronic Kidney Disease. Sci. Rep. 2022, 12, 4832. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Inaguma, D.; Kitagawa, A.; Yanagiya, R.; Koseki, A.; Iwamori, T.; Kudo, M.; Yuzawa, Y. Increasing Tendency of Urine Protein Is a Risk Factor for Rapid EGFR Decline in Patients with CKD: A Machine Learning-Based Prediction Model by Using a Big Database. PLoS ONE 2020, 15, e0239262. [Google Scholar] [CrossRef] [Scilit]
- Song, X.; Yu, A.S.L.; Kellum, J.A.; Waitman, L.R.; Matheny, M.E.; Simpson, S.Q.; Hu, Y.; Liu, M. Cross-Site Transportability of an Explainable Artificial Intelligence Model for Acute Kidney Injury Prediction. Nat. Commun. 2020, 11, 5668. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kuo, C.-C.; Chang, C.-M.; Liu, K.-T.; Lin, W.-K.; Chiang, H.-Y.; Chung, C.-W.; Ho, M.-R.; Sun, P.-R.; Yang, R.-L.; Chen, K.-T. Automation of the Kidney Function Prediction and Classification through Ultrasound-Based Kidney Imaging Using Deep Learning. Npj Digit. Med. 2019, 2, 29. [Google Scholar] [CrossRef] [Scilit]
- Kandasamy, N.; Chaussalet, T.; Basukoski, A. A Conceptual Framework to Predict Disease Progressions in Patients with Chronic Kidney Disease, Using Machine Learning and Process Mining. Stud. Health Technol. Inf. 2023, 305, 190–193. [Google Scholar] [CrossRef] [Scilit]
- Zimmerman, L.P.; Reyfman, P.A.; Smith, A.D.R.; Zeng, Z.; Kho, A.; Sanchez-Pinto, L.N.; Luo, Y. Early Prediction of Acute Kidney Injury Following ICU Admission Using a Multivariate Panel of Physiological Measurements. BMC Med. Inf. Decis. Mak. 2019, 19, 16. [Google Scholar] [CrossRef] [Scilit]
- Alfieri, F.; Ancona, A.; Tripepi, G.; Crosetto, D.; Randazzo, V.; Paviglianiti, A.; Pasero, E.; Vecchi, L.; Cauda, V.; Fagugli, R.M. A Deep-Learning Model to Continuously Predict Severe Acute Kidney Injury Based on Urine Output Changes in Critically Ill Patients. J. Nephrol. 2021, 34, 1875–1886. [Google Scholar] [CrossRef] [Scilit]
- Alfieri, F.; Ancona, A.; Tripepi, G.; Randazzo, V.; Paviglianiti, A.; Pasero, E.; Vecchi, L.; Politi, C.; Cauda, V.; Fagugli, R.M. External Validation of a Deep-Learning Model to Predict Severe Acute Kidney Injury Based on Urine Output Changes in Critically Ill Patients. J. Nephrol. 2022, 35, 2047–2056. [Google Scholar] [CrossRef] [Scilit]
- Hu, C.; Tan, Q.; Zhang, Q.; Li, Y.; Wang, F.; Zou, X.; Peng, Z. Application of Interpretable Machine Learning for Early Prediction of Prognosis in Acute Kidney Injury. Comput. Struct. Biotechnol. J. 2022, 20, 2861–2870. [Google Scholar] [CrossRef] [Scilit]
- Liu, W.T.; Liu, X.Q.; Jiang, T.T.; Wang, M.Y.; Huang, Y.; Huang, Y.L.; Jin, F.Y.; Zhao, Q.; Wu, Q.Y.; Liu, B.C.; et al. Using a Machine Learning Model to Predict the Development of Acute Kidney Injury in Patients with Heart Failure. Front. Cardiovasc. Med. 2022, 9, 911987. [Google Scholar] [CrossRef] [Scilit]
- Tomašev, N.; Glorot, X.; Rae, J.W.; Zielinski, M.; Askham, H.; Saraiva, A.; Mottram, A.; Meyer, C.; Ravuri, S.; Protsyuk, I.; et al. A Clinically Applicable Approach to Continuous Prediction of Future Acute Kidney Injury. Nature 2019, 572, 116–119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xiao, J.; Ding, R.; Xu, X.; Guan, H.; Feng, X.; Sun, T.; Zhu, S.; Ye, Z. Comparison and Development of Machine Learning Tools in the Prediction of Chronic Kidney Disease Progression. J. Transl. Med. 2019, 17, 119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rady, E.-H.A.; Anwar, A.S. Prediction of Kidney Disease Stages Using Data Mining Algorithms. Inform. Med. Unlocked 2019, 15, 100178. [Google Scholar] [CrossRef] [Scilit]
- Akter, S.; Ahmed, M.; Al Imran, A.; Habib, A.; Ul Haque, R.; Rahman, S.; Hasan, R.; Mahjabeen, S. CKD.Net: A Novel Deep Learning Hybrid Model for Effective, Real-Time, Automated Screening Tool towards Prediction of Multi Stages of CKD along with eGFR and Creatinine. Expert Syst. Appl. 2023, 223, 119851. [Google Scholar] [CrossRef] [Scilit]
- Bellocchio, F.; Lonati, C.; Ion Titapiccolo, J.; Nadal, J.; Meiselbach, H.; Schmid, M.; Baerthlein, B.; Tschulena, U.; Schneider, M.; Schultheiss, U.T.; et al. Validation of a Novel Predictive Algorithm for Kidney Failure in Patients Suffering from Chronic Kidney Disease: The Prognostic Reasoning System for Chronic Kidney Disease (PROGRES-CKD). Int. J. Env. Res. Public Health 2021, 18, 12649. [Google Scholar] [CrossRef] [Scilit]
- Tran, N.T.D.; Balezeaux, M.; Granal, M.; Fouque, D.; Ducher, M.; Fauvel, J.-P. Prediction of All-Cause Mortality for Chronic Kidney Disease Patients Using Four Models of Machine Learning. Nephrol. Dial. Transpl. 2023, 38, 1691–1699. [Google Scholar] [CrossRef] [Scilit]
- Shabaniyan, T.; Parsaei, H.; Aminsharifi, A.; Movahedi, M.M.; Jahromi, A.T.; Pouyesh, S.; Parvin, H. An Artificial Intelligence-Based Clinical Decision Support System for Large Kidney Stone Treatment. Australas. Phys. Eng. Sci. Med. 2019, 42, 771–779. [Google Scholar] [CrossRef] [Scilit]
- Black, K.M.; Law, H.; Aldoukhi, A.; Deng, J.; Ghani, K.R. Deep Learning Computer Vision Algorithm for Detecting Kidney Stone Composition. BJU Int. 2020, 125, 920–924. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kers, J.; Bülow, R.D.; Klinkhammer, B.M.; Breimer, G.E.; Fontana, F.; Abiola, A.A.; Hofstraat, R.; Corthals, G.L.; Peters-Sengers, H.; Djudjaj, S.; et al. Deep Learning-Based Classification of Kidney Transplant Pathology: A Retrospective, Multicentre, Proof-of-Concept Study. Lancet Digit. Health 2022, 4, e18–e26. [Google Scholar] [CrossRef] [Scilit]
- Ou, S.-M.; Tsai, M.-T.; Lee, K.-H.; Tseng, W.-C.; Yang, C.-Y.; Chen, T.-H.; Bin, P.-J.; Chen, T.-J.; Lin, Y.-P.; Sheu, W.H.-H.; et al. Prediction of the Risk of Developing End-Stage Renal Diseases in Newly Diagnosed Type 2 Diabetes Mellitus Using Artificial Intelligence Algorithms. BioData Min. 2023, 16, 8. [Google Scholar] [CrossRef] [Scilit]
- Farrell, D.R.; Vassalotti, J.A. Screening, Identifying, and Treating Chronic Kidney Disease: Why, Who, When, How, and What? BMC Nephrol. 2024, 25, 34. [Google Scholar] [CrossRef] [Scilit]
- Kaur, B.; Nikita; Sadawarti, H.; Singla, J. A Comprehensive Review of Medical Expert Systems for Diagnosis of Chronic Kidney Diseases. In Proceedings of the 2019 International Conference on Smart Systems and Inventive Technology (ICSSIT), Tirunelveli, India, 27–29 November 2019; pp. 1008–1013. [Google Scholar] [CrossRef] [Scilit]
- Senan, E.M.; Al-Adhaileh, M.H.; Alsaade, F.W.; Aldhyani, T.H.H.; Alqarni, A.A.; Alsharif, N.; Uddin, M.I.; Alahmadi, A.H.; Jadhav, M.E.; Alzahrani, M.Y. Diagnosis of Chronic Kidney Disease Using Effective Classification Algorithms and Recursive Feature Elimination Techniques. J. Healthc. Eng. 2021, 2021, 1004767. [Google Scholar] [CrossRef] [Scilit]
- Ram, S.; Gupta, S. Building Machine Learning Based Diseases Diagnosis System Considering Various Features of Datasets. In Emerging Trends in Expert Applications and Security; Rathore, V.S., Worring, M., Mishra, D.K., Joshi, A., Maheshwari, S., Eds.; Springer: Singapore, 2019; pp. 147–155. [Google Scholar] [CrossRef] [Scilit]
- Khamparia, A.; Saini, G.; Pandey, B.; Tiwari, S.; Gupta, D.; Khanna, A. KDSAE: Chronic Kidney Disease Classification with Multimedia Data Learning Using Deep Stacked Autoencoder Network. Multimed Tools Appl. 2020, 79, 35425–35440. [Google Scholar] [CrossRef] [Scilit]
- Al-Momani, R.; Al-Mustafa, G.; Zeidan, R.; Alquran, H.; Mustafa, W.A.; Alkhayyat, A. Chronic Kidney Disease Detection Using Machine Learning Technique. In Proceedings of the 2022 5th International Conference on Engineering Technology and Its Applications (IICETA), Al-Najaf, Iraq, 1–25 May 2022; pp. 153–158. [Google Scholar] [CrossRef] [Scilit]
- Alsadi, A.; Majeed, N.; Saeed, D.; Dharmamer, Y.; Singh, M.; Patel, T. A Deep-Learning Approach at Automated Detection of Electron-Dense Immune Deposits in Medical Renal Biopsies. J. Nephropathol. 2020, 11, e17123. [Google Scholar] [CrossRef] [Scilit]
- Vashisth, S.; Dhall, I.; Saraswat, S. Chronic Kidney Disease (CKD) Diagnosis Using Multi-Layer Perceptron Classifier. In Proceedings of the 2020 10th International Conference on Cloud Computing, Data Science & Engineering (Confluence), Noida, India, 29–31 January 2020; pp. 346–350. [Google Scholar] [CrossRef] [Scilit]
- Alikhan, J.S.; Alageswaran, R.; Amali, S.M.J. Self-Attention Convolutional Neural Network Optimized with Season Optimization Algorithm Espoused Chronic Kidney Diseases Diagnosis in Big Data System. Biomed. Signal Process. Control 2023, 85, 105011. [Google Scholar] [CrossRef] [Scilit]
- Granal, M.; Slimani, L.; Florens, N.; Sens, F.; Pelletier, C.; Pszczolinski, R.; Casiez, C.; Kalbacher, E.; Jolivot, A.; Dubourg, L.; et al. Prediction Tool to Estimate Potassium Diet in Chronic Kidney Disease Patients Developed Using a Machine Learning Tool: The UniverSel Study. Nutrients 2022, 14, 2419. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lassau, N.; Estienne, T.; de Vomecourt, P.; Azoulay, M.; Cagnol, J.; Garcia, G.; Majer, M.; Jehanno, E.; Renard-Penna, R.; Balleyguier, C.; et al. Five Simultaneous Artificial Intelligence Data Challenges on Ultrasound, CT, and MRI. Diagn. Interv. Imaging 2019, 100, 199–209. [Google Scholar] [CrossRef] [Scilit]
- Onthoni, D.D.; Sheng, T.-W.; Sahoo, P.K.; Wang, L.-J.; Gupta, P. Deep Learning Assisted Localization of Polycystic Kidney on Contrast-Enhanced CT Images. Diagnostics 2020, 10, 1113. [Google Scholar] [CrossRef] [Scilit]
- Les, T.; Markiewicz, T.; Dziekiewicz, M.; Lorent, M. Kidney Boundary Detection Algorithm Based on Extended Maxima Transformations for Computed Tomography Diagnosis. Appl. Sci. 2020, 10, 7512. [Google Scholar] [CrossRef] [Scilit]
- Tsai, M.-C.; Lu, H.H.-S.; Chang, Y.-C.; Huang, Y.-C.; Fu, L.-S. Automatic Screening of Pediatric Renal Ultrasound Abnormalities: Deep Learning and Transfer Learning Approach. JMIR Med. Inf. 2022, 10, e40878. [Google Scholar] [CrossRef] [Scilit]
- Yamaguchi, R.; Kawazoe, Y.; Shimamoto, K.; Shinohara, E.; Tsukamoto, T.; Shintani-Domoto, Y.; Nagasu, H.; Uozaki, H.; Ushiku, T.; Nangaku, M.; et al. Glomerular Classification Using Convolutional Neural Networks Based on Defined Annotation Criteria and Concordance Evaluation Among Clinicians. Kidney Int. Rep. 2020, 6, 716–726. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jayapandian, C.P.; Chen, Y.; Janowczyk, A.R.; Palmer, M.B.; Cassol, C.A.; Sekulic, M.; Hodgin, J.B.; Zee, J.; Hewitt, S.M.; O’Toole, J.; et al. Development and Evaluation of Deep Learning–Based Segmentation of Histologic Structures in the Kidney Cortex with Multiple Histologic Stains. Kidney Int. 2021, 99, 86–101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Altalbe, A.; Javed, A. Applying Customized Convolutional Neural Network to Kidney Image Volumes for Kidney Disease Detection. CSSE 2023, 47, 2119–2134. [Google Scholar] [CrossRef] [Scilit]
- Kumar, K.; Pradeepa, M.; Mahdal, M.; Verma, S.; RajaRao, M.V.L.N.; Ramesh, J.V.N. A Deep Learning Approach for Kidney Disease Recognition and Prediction through Image Processing. Appl. Sci. 2023, 13, 3621. [Google Scholar] [CrossRef] [Scilit]
- Hao, F.; Li, M.; Liu, X.; Li, X.; Yue, J.; Han, W. Classification of Glomeruli with Membranous Nephropathy on Renal Digital Pathological Images with Deep Learning. In Proceedings of the 2020 Conference on Artificial Intelligence and Healthcare, Taiyuan, China, 23–25 October 2020; Association for Computing Machinery: New York, NY, USA, 2020; pp. 239–243. [Google Scholar] [CrossRef] [Scilit]
- Parakh, A.; Lee, H.; Lee, J.H.; Eisner, B.H.; Sahani, D.V.; Do, S. Urinary Stone Detection on CT Images Using Deep Convolutional Neural Networks: Evaluation of Model Performance and Generalization. Radiol. Artif. Intell. 2019, 1, e180066. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yildirim, K.; Bozdag, P.G.; Talo, M.; Yildirim, O.; Karabatak, M.; Acharya, U.R. Deep Learning Model for Automated Kidney Stone Detection Using Coronal CT Images. Comput. Biol. Med. 2021, 135, 104569. [Google Scholar] [CrossRef] [Scilit]
- Li, D.; Xiao, C.; Liu, Y.; Chen, Z.; Hassan, H.; Su, L.; Liu, J.; Li, H.; Xie, W.; Zhong, W.; et al. Deep Segmentation Networks for Segmenting Kidneys and Detecting Kidney Stones in Unenhanced Abdominal CT Images. Diagnostics 2022, 12, 1788. [Google Scholar] [CrossRef] [Scilit]
- Asif, S.; Zhao, M.; Chen, X.; Zhu, Y. StoneNet: An Efficient Lightweight Model Based on Depthwise Separable Convolutions for Kidney Stone Detection from CT Images. Interdiscip. Sci. Comput. Life Sci. 2023, 15, 633–652. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Subramanian, R.R.; Abilakshmi, A.; Kalyani, T.; Sunayana, P.; Monalisa, G.; Chaithanya, C.V. Design and Evaluation of a Deep Learning Aided Approach for Kidney Stone Detection in CT Scan Images. In Proceedings of the 2023 International Conference on Applied Intelligence and Sustainable Computing (ICAISC), Dharwad, India, 16–17 June 2023; pp. 1–6. [Google Scholar] [CrossRef] [Scilit]
- Gondim, D.D.; Al-Obaidy, K.I.; Idrees, M.T.; Eble, J.N.; Cheng, L. Artificial Intelligence-Based Multi-Class Histopathologic Classification of Kidney Neoplasms. J. Pathol. Inform. 2023, 14, 100299. [Google Scholar] [CrossRef] [Scilit]
- Jhumka, K.; Khan, M.H.-M.; Mungloo-Dilmohamud, Z.; Fedally, S.A. Classification of Kidney Abnormalities Using Deep Learning with Explainable AI. In Proceedings of the 2023 Sixth International Conference of Women in Data Science at Prince Sultan University (WiDS PSU), Riyadh, Saudi Arabia, 14–15 March 2023; pp. 133–137. [Google Scholar] [CrossRef] [Scilit]
- Ginley, B.; Jen, K.-Y.; Han, S.S.; Rodrigues, L.; Jain, S.; Fogo, A.B.; Zuckerman, J.; Walavalkar, V.; Miecznikowski, J.C.; Wen, Y.; et al. Automated Computational Detection of Interstitial Fibrosis, Tubular Atrophy, and Glomerulosclerosis. J. Am. Soc. Nephrol. 2021, 32, 837–850. [Google Scholar] [CrossRef] [Scilit]
- Yi, Z.; Salem, F.; Menon, M.C.; Keung, K.; Xi, C.; Hultin, S.; Haroon Al Rasheed, M.R.; Li, L.; Su, F.; Sun, Z.; et al. Deep Learning Identified Pathological Abnormalities Predictive of Graft Loss in Kidney Transplant Biopsies. Kidney Int. 2022, 101, 288–298. [Google Scholar] [CrossRef] [Scilit]
- Tang, Z.-Y.; Lin, Y.-C.; Shen, C.-C. Dual-Path Convolutional Neural Network for Chronic Kidney Disease Classification in Ultrasound Echography. In Proceedings of the 2022 IEEE International Ultrasonics Symposium (IUS), Venice, Italy, 10–13 October 2022; pp. 1–4. [Google Scholar]
- Weis, C.-A.; Bindzus, J.N.; Voigt, J.; Runz, M.; Hertjens, S.; Gaida, M.M.; Popovic, Z.V.; Porubsky, S. Assessment of Glomerular Morphological Patterns by Deep Learning Algorithms. J. Nephrol. 2022, 35, 417–427. [Google Scholar] [CrossRef] [Scilit]
- Zhang, L.; Li, M.; Wu, Y.; Hao, F.; Wang, C.; Han, W.; Niu, D.; Zheng, W. Classification of Renal Biopsy Direct Immunofluorescence Image Using Multiple Attention Convolutional Neural Network. Comput. Methods Programs Biomed. 2022, 214, 106532. [Google Scholar] [CrossRef] [Scilit]
- Lu, Y.; Yang, H.; Asad, Z.; Zhu, Z.; Yao, T.; Xu, J.; Fogo, A.B.; Huo, Y. Holistic Fine-Grained Global Glomerulosclerosis Characterization: From Detection to Unbalanced Classification. J. Med. Imaging 2022, 9, 014005. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pesce, F.; Albanese, F.; Mallardi, D.; Rossini, M.; Pasculli, G.; Suavo-Bulzis, P.; Granata, A.; Brunetti, A.; Cascarano, G.D.; Bevilacqua, V.; et al. Identification of Glomerulosclerosis Using IBM Watson and Shallow Neural Networks. J. Nephrol. 2022, 35, 1235–1242. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akatsuka, A.; Horai, Y.; Akatsuka, A. Automated Recognition of Glomerular Lesions in the Kidneys of Mice by Using Deep Learning. J. Pathol. Inf. 2022, 13, 100129. [Google Scholar] [CrossRef] [Scilit]
- Nan, Y.; Li, F.; Tang, P.; Zhang, G.; Zeng, C.; Xie, G.; Liu, Z.; Yang, G. Automatic Fine-Grained Glomerular Lesion Recognition in Kidney Pathology. Pattern Recognit. 2022, 127, 108648. [Google Scholar] [CrossRef] [Scilit]
- Pilia, N.; Mesa, M.H.; Dossel, O.; Loewe, A. ECG-Based Estimation of Potassium and Calcium Concentrations: Proof of Concept with Simulated Data. In Proceedings of the 2019 41st Annual International Conference of the IEEE Engineering in Medicine and Biology Society (EMBC), Berlin, Germany, 23–27 July 2019; pp. 2610–2613. [Google Scholar] [CrossRef] [Scilit]
- Hayashi, Y. Detection of Lower Albuminuria Levels and Early Development of Diabetic Kidney Disease Using an Artificial Intelligence-Based Rule Extraction Approach. Diagnostics 2019, 9, 133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhaskar, N.; Manikandan, S. A Deep-Learning-Based System for Automated Sensing of Chronic Kidney Disease. IEEE Sens. Lett. 2019, 3, 7001904. [Google Scholar] [CrossRef] [Scilit]
- Sabanayagam, C.; Xu, D.; Ting, D.S.W.; Nusinovici, S.; Banu, R.; Hamzah, H.; Lim, C.; Tham, Y.-C.; Cheung, C.Y.; Tai, E.S.; et al. A Deep Learning Algorithm to Detect Chronic Kidney Disease from Retinal Photographs in Community-Based Populations. Lancet Digit. Health 2020, 2, e295–e302. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, K.; Liu, X.; Xu, J.; Yuan, J.; Cai, W.; Chen, T.; Wang, K.; Gao, Y.; Nie, S.; Xu, X.; et al. Deep-Learning Models for the Detection and Incidence Prediction of Chronic Kidney Disease and Type 2 Diabetes from Retinal Fundus Images. Nat. Biomed. Eng. 2021, 5, 533–545. [Google Scholar] [CrossRef] [Scilit]
- Davenport, A. Why Is Intradialytic Hypotension the Commonest Complication of Outpatient Dialysis Treatments? Kidney Int. Rep. 2022, 8, 405–418. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Zhao, D.; Liu, G.; Liu, Y.; Bano, Y.; Ibrohimov, A.; Chen, H.; Wu, C.; Chen, X. Intradialytic Hypotension Prediction Using Covariance Matrix-Driven Whale Optimizer with Orthogonal Structure-Assisted Extreme Learning Machine. Front. Neuroinform. 2022, 16, 956423. [Google Scholar] [CrossRef] [Scilit]
- Mendoza-Pitti, L.; Gómez, J.; Vargas-Lombardo, M.; Gomez-Pulido, J.A.; Polo-Luque, M.-L.; Rodriguez-Puyol, D. Machine-Learning Model to Predict the Intradialytic Hypotension Based on Clinical-Analytical Data. IEEE Access 2022, 10, 72065–72079. [Google Scholar] [CrossRef] [Scilit]
- Mohammed, I.H.; Obaid, M.K.; Hadi, M.R.; Alzubaidi, L.H.; Mohammed, A.; Hassan, A.R. Artificial Intelligence Based Robust Clinical Data Classification for Intradialytic Hypotension Diagnosis. In Proceedings of the 2023 6th International Conference on Engineering Technology and its Applications (IICETA), Al-Najaf, Iraq, 15–16 July 2023; pp. 78–84. [Google Scholar] [CrossRef] [Scilit]
- Hong, D.; Chang, H.; He, X.; Zhan, Y.; Tong, R.; Wu, X.; Li, G. Construction of an Early Alert System for Intradialytic Hypotension before Initiating Hemodialysis Based on Machine Learning. Kidney Dis. 2023, 9, 433–442. [Google Scholar] [CrossRef] [Scilit]
- Shih, C.; Lai, Y.; Chen, C.; Chu, W.C.-C. An Early Warning System for Hemodialysis Complications Utilizing Transfer Learning from HD IoT Dataset. In Proceedings of the 2020 IEEE 44th Annual Computers, Software, and Applications Conference (COMPSAC), Madrid, Spain, 13–17 July 2020; pp. 759–767. [Google Scholar]
- Othman, M.; Elbasha, A.M.; Naga, Y.S.; Moussa, N.D. Early Prediction of Hemodialysis Complications Employing Ensemble Techniques. Biomed. Eng. OnLine 2022, 21, 74. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Song, W.T.; Chen, C.C.; Yu, Z.-W.; Huang, H.-C. An Effective AI Model for Automatically Detecting Arteriovenous Fistula Stenosis. Sci. Rep. 2023, 13, 17659. [Google Scholar] [CrossRef] [Scilit]
- Ota, K.; Nishiura, Y.; Ishihara, S.; Adachi, H.; Yamamoto, T.; Hamano, T. Evaluation of Hemodialysis Arteriovenous Bruit by Deep Learning. Sensors 2020, 20, 4852. [Google Scholar] [CrossRef] [Scilit]
- Balamuthusamy, S.; Dhanabalsamy, N.; Thankavel, B.; Bala, M.; Pfaffle, A. Utility of Machine Learning (ML)Analytics on Real Time Risk Stratification and Re-Intervention Risk Prediction on AV Access Outcomes and Cost. J. Vasc. Access 2023, 25, 1224–1228. [Google Scholar] [CrossRef] [Scilit]
- Zhang, H.; Preddie, D.; Krackov, W.; Sor, M.; Waguespack, P.; Kuang, Z.; Ye, X.; Kotanko, P. Deep Learning to Classify Arteriovenous Access Aneurysms in Hemodialysis Patients. Clin. Kidney J. 2021, 15, 829–830. [Google Scholar] [CrossRef] [Scilit]
- Hong, J. Care of Maintenance Hemodialysis Patients through Intelligent Algorithm-Based Low-Dose Digital Subtraction Angiography. Sci. Program. 2021, 2021, 8746962. [Google Scholar] [CrossRef] [Scilit]
- Barbieri, C.; Cattinelli, I.; Neri, L.; Mari, F.; Ramos, R.; Brancaccio, D.; Canaud, B.; Stuard, S. Development of an Artificial Intelligence Model to Guide the Management of Blood Pressure, Fluid Volume, and Dialysis Dose in End-Stage Kidney Disease Patients: Proof of Concept and First Clinical Assessment. Kidney Dis. 2019, 5, 28–33. [Google Scholar] [CrossRef] [Scilit]
- Brito, C.; Esteves, M.; Peixoto, H.; Abelha, A.; Machado, J. A Data Mining Approach to Classify Serum Creatinine Values in Patients Undergoing Continuous Ambulatory Peritoneal Dialysis. Wirel. Netw. 2022, 28, 1269–1277. [Google Scholar] [CrossRef] [Scilit]
- Tan, G.F.L.; Du, T.; Liu, J.S.; Chai, C.C.; Nyein, C.M.; Liu, A.Y.L. Automated Lung Ultrasound Image Assessment Using Artificial Intelligence to Identify Fluid Overload in Dialysis Patients. BMC Nephrol. 2022, 23, 410. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cho, G.W.; Ghanem, A.K.; Quesada, C.G.; Crabtree, T.R.; Jennings, R.S.; Budoff, M.J.; Choi, A.D.; Min, J.K.; Karlsberg, R.P.; Earls, J.P. Quantitative Plaque Analysis with A.I.-Augmented CCTA in End-Stage Renal Disease and Complex CAD. Clin. Imaging 2022, 89, 155–161. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kanda, E.; Epureanu, B.I.; Adachi, T.; Tsuruta, Y.; Kikuchi, K.; Kashihara, N.; Abe, M.; Masakane, I.; Nitta, K. Application of Explainable Ensemble Artificial Intelligence Model to Categorization of Hemodialysis-Patient and Treatment Using Nationwide-Real-World Data in Japan. PLoS ONE 2020, 15, e0233491. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qarajeh, A.; Tangpanithandee, S.; Thongprayoon, C.; Suppadungsuk, S.; Krisanapan, P.; Aiumtrakul, N.; Garcia Valencia, O.A.; Miao, J.; Qureshi, F.; Cheungpasitporn, W. AI-Powered Renal Diet Support: Performance of ChatGPT, Bard AI, and Bing Chat. Clin. Pract. 2023, 13, 1160–1172. [Google Scholar] [CrossRef] [Scilit]
- Cheng, C.-I.; Lin, W.-J.; Liu, H.-T.; Chen, Y.-T.; Chiang, C.-K.; Hung, K.-Y. Implementation of Artificial Intelligence Chatbot in Peritoneal Dialysis Nursing Care: Experience from a Taiwan Medical Center. Nephrology 2023, 28, 655–662. [Google Scholar] [CrossRef] [Scilit]
- Tveit, D.P.; Hshieh, P.; Cruess, D.; Agodoa, L.Y.C.; Welch, P.G.; Abbott, K.C. Risk Factors for Pulmonary Embolism in Chronic Dialysis Patients. J. Nephrol. 2002, 15, 241–247. [Google Scholar]
- Arulkumaran, N.; Navaratnarajah, A.; Pillay, C.; Brown, W.; Duncan, N.; McLean, A.; Taube, D.; Brown, E.A. Causes and Risk Factors for Acute Dialysis Initiation among Patients with End-Stage Kidney Disease—A Large Retrospective Observational Cohort Study. Clin. Kidney J. 2019, 12, 550–558. [Google Scholar] [CrossRef] [Scilit]
- Harmankaya, O.; Akalin, N.; Akay, H.; Okuturlar, Y.; Erturk, K.; Kaptanogullari, H.; Kocoglu, H. Comparison of Risk Factors for Cardiovascular Disease in Hemodialysis and Peritoneal Dialysis Patients. Clinics 2015, 70, 601–605. [Google Scholar] [CrossRef] [Scilit]
- Díez-Sanmartín, C.; Cabezuelo, A.S.; Belmonte, A.A. A New Approach to Predicting Mortality in Dialysis Patients Using Sociodemographic Features Based on Artificial Intelligence. Artif. Intell. Med. 2023, 136, 102478. [Google Scholar] [CrossRef] [Scilit]
- Noh, J.; Yoo, K.D.; Bae, W.; Lee, J.S.; Kim, K.; Cho, J.-H.; Lee, H.; Kim, D.K.; Lim, C.S.; Kang, S.-W.; et al. Prediction of the Mortality Risk in Peritoneal Dialysis Patients Using Machine Learning Models: A Nation-Wide Prospective Cohort in Korea. Sci. Rep. 2020, 10, 7470. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Siga, M.M.; Ducher, M.; Florens, N.; Roth, H.; Mahloul, N.; Fouque, D.; Fauvel, J.-P. Prediction of All-Cause Mortality in Haemodialysis Patients Using a Bayesian Network. Nephrol. Dial. Transplant. 2020, 35, 1420–1425. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gotta, V.; Tancev, G.; Marsenic, O.; Vogt, J.E.; Pfister, M. Identifying Key Predictors of Mortality in Young Patients on Chronic Haemodialysis—A Machine Learning Approach. Nephrol. Dial. Transplant. 2021, 36, 519–528. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ohara, T.; Ikeda, H.; Sugitani, Y.; Suito, H.; Huynh, V.Q.H.; Kinomura, M.; Haraguchi, S.; Sakurama, K. Artificial Intelligence Supported Anemia Control System (AISACS) to Prevent Anemia in Maintenance Hemodialysis Patients. Int. J. Med. Sci. 2021, 18, 1831–1839. [Google Scholar] [CrossRef] [Scilit]
- Liao, H.; Yang, Y.; Zeng, Y.; Qiu, Y.; Chen, Y.; Zhu, L.; Fu, P.; Yan, F.; Chen, Y.; Yuan, H. Use Machine Learning to Help Identify Possible Sarcopenia Cases in Maintenance Hemodialysis Patients. BMC Nephrol. 2023, 24, 34. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garbelli, M.; Neri, L.; Bellocchio, F. Arteriovenous Fistula Flow Level Prediction through Ordinal Classifier Methods. CEUR Workshop 2022, 3307, 12–19. [Google Scholar]
- Monaghan, C.K.; Larkin, J.W.; Chaudhuri, S.; Han, H.; Jiao, Y.; Bermudez, K.M.; Weinhandl, E.D.; Dahne-Steuber, I.A.; Belmonte, K.; Neri, L.; et al. Machine Learning for Prediction of Patients on Hemodialysis with an Undetected SARS-CoV-2 Infection. Kidney360 2021, 2, 456–468. [Google Scholar] [CrossRef] [Scilit]
- Tang, S.-Y.; Chen, T.-H.; Kuo, K.-L.; Huang, J.-N.; Kuo, C.-T.; Chu, Y.-C. Using Artificial Intelligence Algorithms to Predict the Overall Survival of Hemodialysis Patients during the COVID-19 Pandemic: A Prospective Cohort Study. J. Chin. Med. Assoc. 2023, 86, 1020–1027. [Google Scholar] [CrossRef] [Scilit]
- Wu, J.; Kong, G.; Lin, Y.; Chu, H.; Yang, C.; Shi, Y.; Wang, H.; Zhang, L. Development of a Scoring Tool for Predicting Prolonged Length of Hospital Stay in Peritoneal Dialysis Patients through Data Mining. Ann. Transl. Med. 2020, 8, 1437. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kong, G.; Wu, J.; Chu, H.; Yang, C.; Lin, Y.; Lin, K.; Shi, Y.; Wang, H.; Zhang, L. Predicting Prolonged Length of Hospital Stay for Peritoneal Dialysis–Treated Patients Using Stacked Generalization: Model Development and Validation Study. JMIR Med. Inf. 2021, 9, e17886. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shickel, B.; Bihorac, A. The Dawn of Multimodal Artificial Intelligence in Nephrology. Nat. Rev. Nephrol. 2024, 20, 79–80. [Google Scholar] [CrossRef] [Scilit]
- Dong, Z.; Wang, X.; Pan, S.; Weng, T.; Chen, X.; Jiang, S.; Li, Y.; Wang, Z.; Cao, X.; Wang, Q.; et al. A Multimodal Transformer System for Noninvasive Diabetic Nephropathy Diagnosis via Retinal Imaging. Npj Digit. Med. 2025, 8, 50. [Google Scholar] [CrossRef] [Scilit]
- Hu, X.; Yang, J.; Li, Y.; Gong, Y.; Ni, H.; Wei, Q.; Yang, M.; Zhang, Y.; Huang, J.; Ma, C.; et al. Multimodal Deep Learning Improving the Accuracy of Pathological Diagnoses for Membranous Nephropathy. Ren. Fail. 2025, 47, 2528106. [Google Scholar] [CrossRef] [Scilit]
- Saly, D.L.; Allegretti, A.S.; Ufere, N.N.; on behalf of the MGH SILK Collaborative. The SILK Collaborative: A Multidisciplinary Approach to Serious Illness Communication for Patients with Liver Failure and AKI. Kidney360 2024, 5, 456. [Google Scholar] [CrossRef] [Scilit]
- Yun, D.; Yang, H.-L.; Kim, S.G.; Kim, K.; Kim, D.K.; Oh, K.-H.; Joo, K.W.; Kim, Y.S.; Han, S.S. Real-Time Dual Prediction of Intradialytic Hypotension and Hypertension Using an Explainable Deep Learning Model. Sci. Rep. 2023, 13, 18054. [Google Scholar] [CrossRef] [Scilit]
- Koirala, P.; Thongprayoon, C.; Miao, J.; Garcia Valencia, O.A.; Sheikh, M.S.; Suppadungsuk, S.; Mao, M.A.; Pham, J.H.; Craici, I.M.; Cheungpasitporn, W. Evaluating AI Performance in Nephrology Triage and Subspecialty Referrals. Sci. Rep. 2025, 15, 3455. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pham, J.H.; Thongprayoon, C.; Miao, J.; Suppadungsuk, S.; Koirala, P.; Craici, I.M.; Cheungpasitporn, W. Large Language Model Triaging of Simulated Nephrology Patient Inbox Messages. Front. Artif. Intell. 2024, 7, 1452469. [Google Scholar] [CrossRef] [Scilit]
- Khalid, F.; Alsadoun, L.; Khilji, F.; Mushtaq, M.; Eze-odurukwe, A.; Mushtaq, M.M.; Ali, H.; Farman, R.O.; Ali, S.M.; Fatima, R.; et al. Predicting the Progression of Chronic Kidney Disease: A Systematic Review of Artificial Intelligence and Machine Learning Approaches. Cureus 2024, 16, e60145. [Google Scholar] [CrossRef] [Scilit]
- Takkavatakarn, K.; Oh, W.; Cheng, E.; Nadkarni, G.N.; Chan, L. Machine Learning Models to Predict End-Stage Kidney Disease in Chronic Kidney Disease Stage 4. BMC Nephrol. 2023, 24, 376. [Google Scholar] [CrossRef] [Scilit]
- Saito, H.; Yoshimura, H.; Tanaka, K.; Kimura, H.; Watanabe, K.; Tsubokura, M.; Ejiri, H.; Zhao, T.; Ozaki, A.; Kazama, S.; et al. Predicting CKD Progression Using Time-Series Clustering and Light Gradient Boosting Machines. Sci. Rep. 2024, 14, 1723. [Google Scholar] [CrossRef] [Scilit]
- Chen, J.; Fan, H.; Shao, D.; Dai, S. MRFA-Net: Kidney Segmentation Method Based on Multi-Scale Feature Fusion and Residual Full Attention. Appl. Sci. 2024, 14, 2302. [Google Scholar] [CrossRef] [Scilit]
- Hu, W.; Yang, S.; Guo, W.; Xiao, N.; Yang, X.; Ren, X. STC-UNet: Renal Tumor Segmentation Based on Enhanced Feature Extraction at Different Network Levels. BMC Med. Imaging 2024, 24, 179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Giordano, A.; Cancilla, N.; Martín-Guerrero, J.D.; Vives-Gilabert, Y.; Ciofalo, M.; Micale, G.; Tamburini, A. A Machine Learning-Based Surrogate Model of a Hemodialyzer for the Prediction of the Urea Dialyzer Clearance. In Proceedings of the Artificial Intelligence in Healthcare, Cambridge, UK, 8–10 September 2025; Cafolla, D., Rittman, T., Ni, H., Eds.; Springer Nature Switzerland: Cham, Switzerland, 2026; pp. 263–276. [Google Scholar] [CrossRef] [Scilit]
- Nicosia, A.; Cancilla, N.; Di Liberti, E.; Guerrero, J.D.M.; Gilabert, Y.V.; Ferrantelli, A.; Iacono, F.; Brucato, V.M.B.; La Carrubba, V.; Tinnirello, I.; et al. Performance Comparison of Machine Learning Models for the Prediction of Dialysis Treatment Variables. In Proceedings of the Artificial Intelligence in Healthcare, Cambridge, UK, 8–10 September 2025; Cafolla, D., Rittman, T., Ni, H., Eds.; Springer Nature: Cham, Switzerland, 2026; pp. 157–170. [Google Scholar] [CrossRef] [Scilit]
- Nicosia, A.; Cancilla, N.; Passerini, M.; Sau, F.; Tinnirello, I.; Cipollina, A. Performance Comparison of a Neural Network and a Regression Linear Model for Predictive Maintenance in Dialysis Machine Components. Bioengineering 2025, 12, 941. [Google Scholar] [CrossRef] [Scilit]
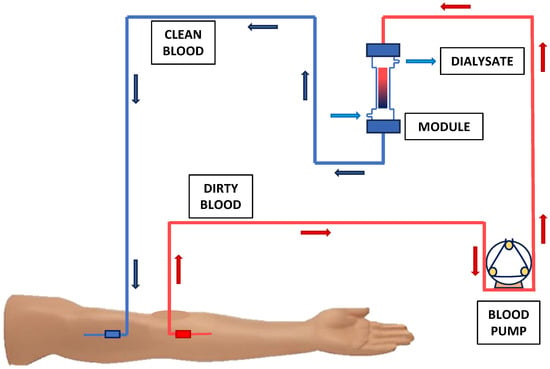
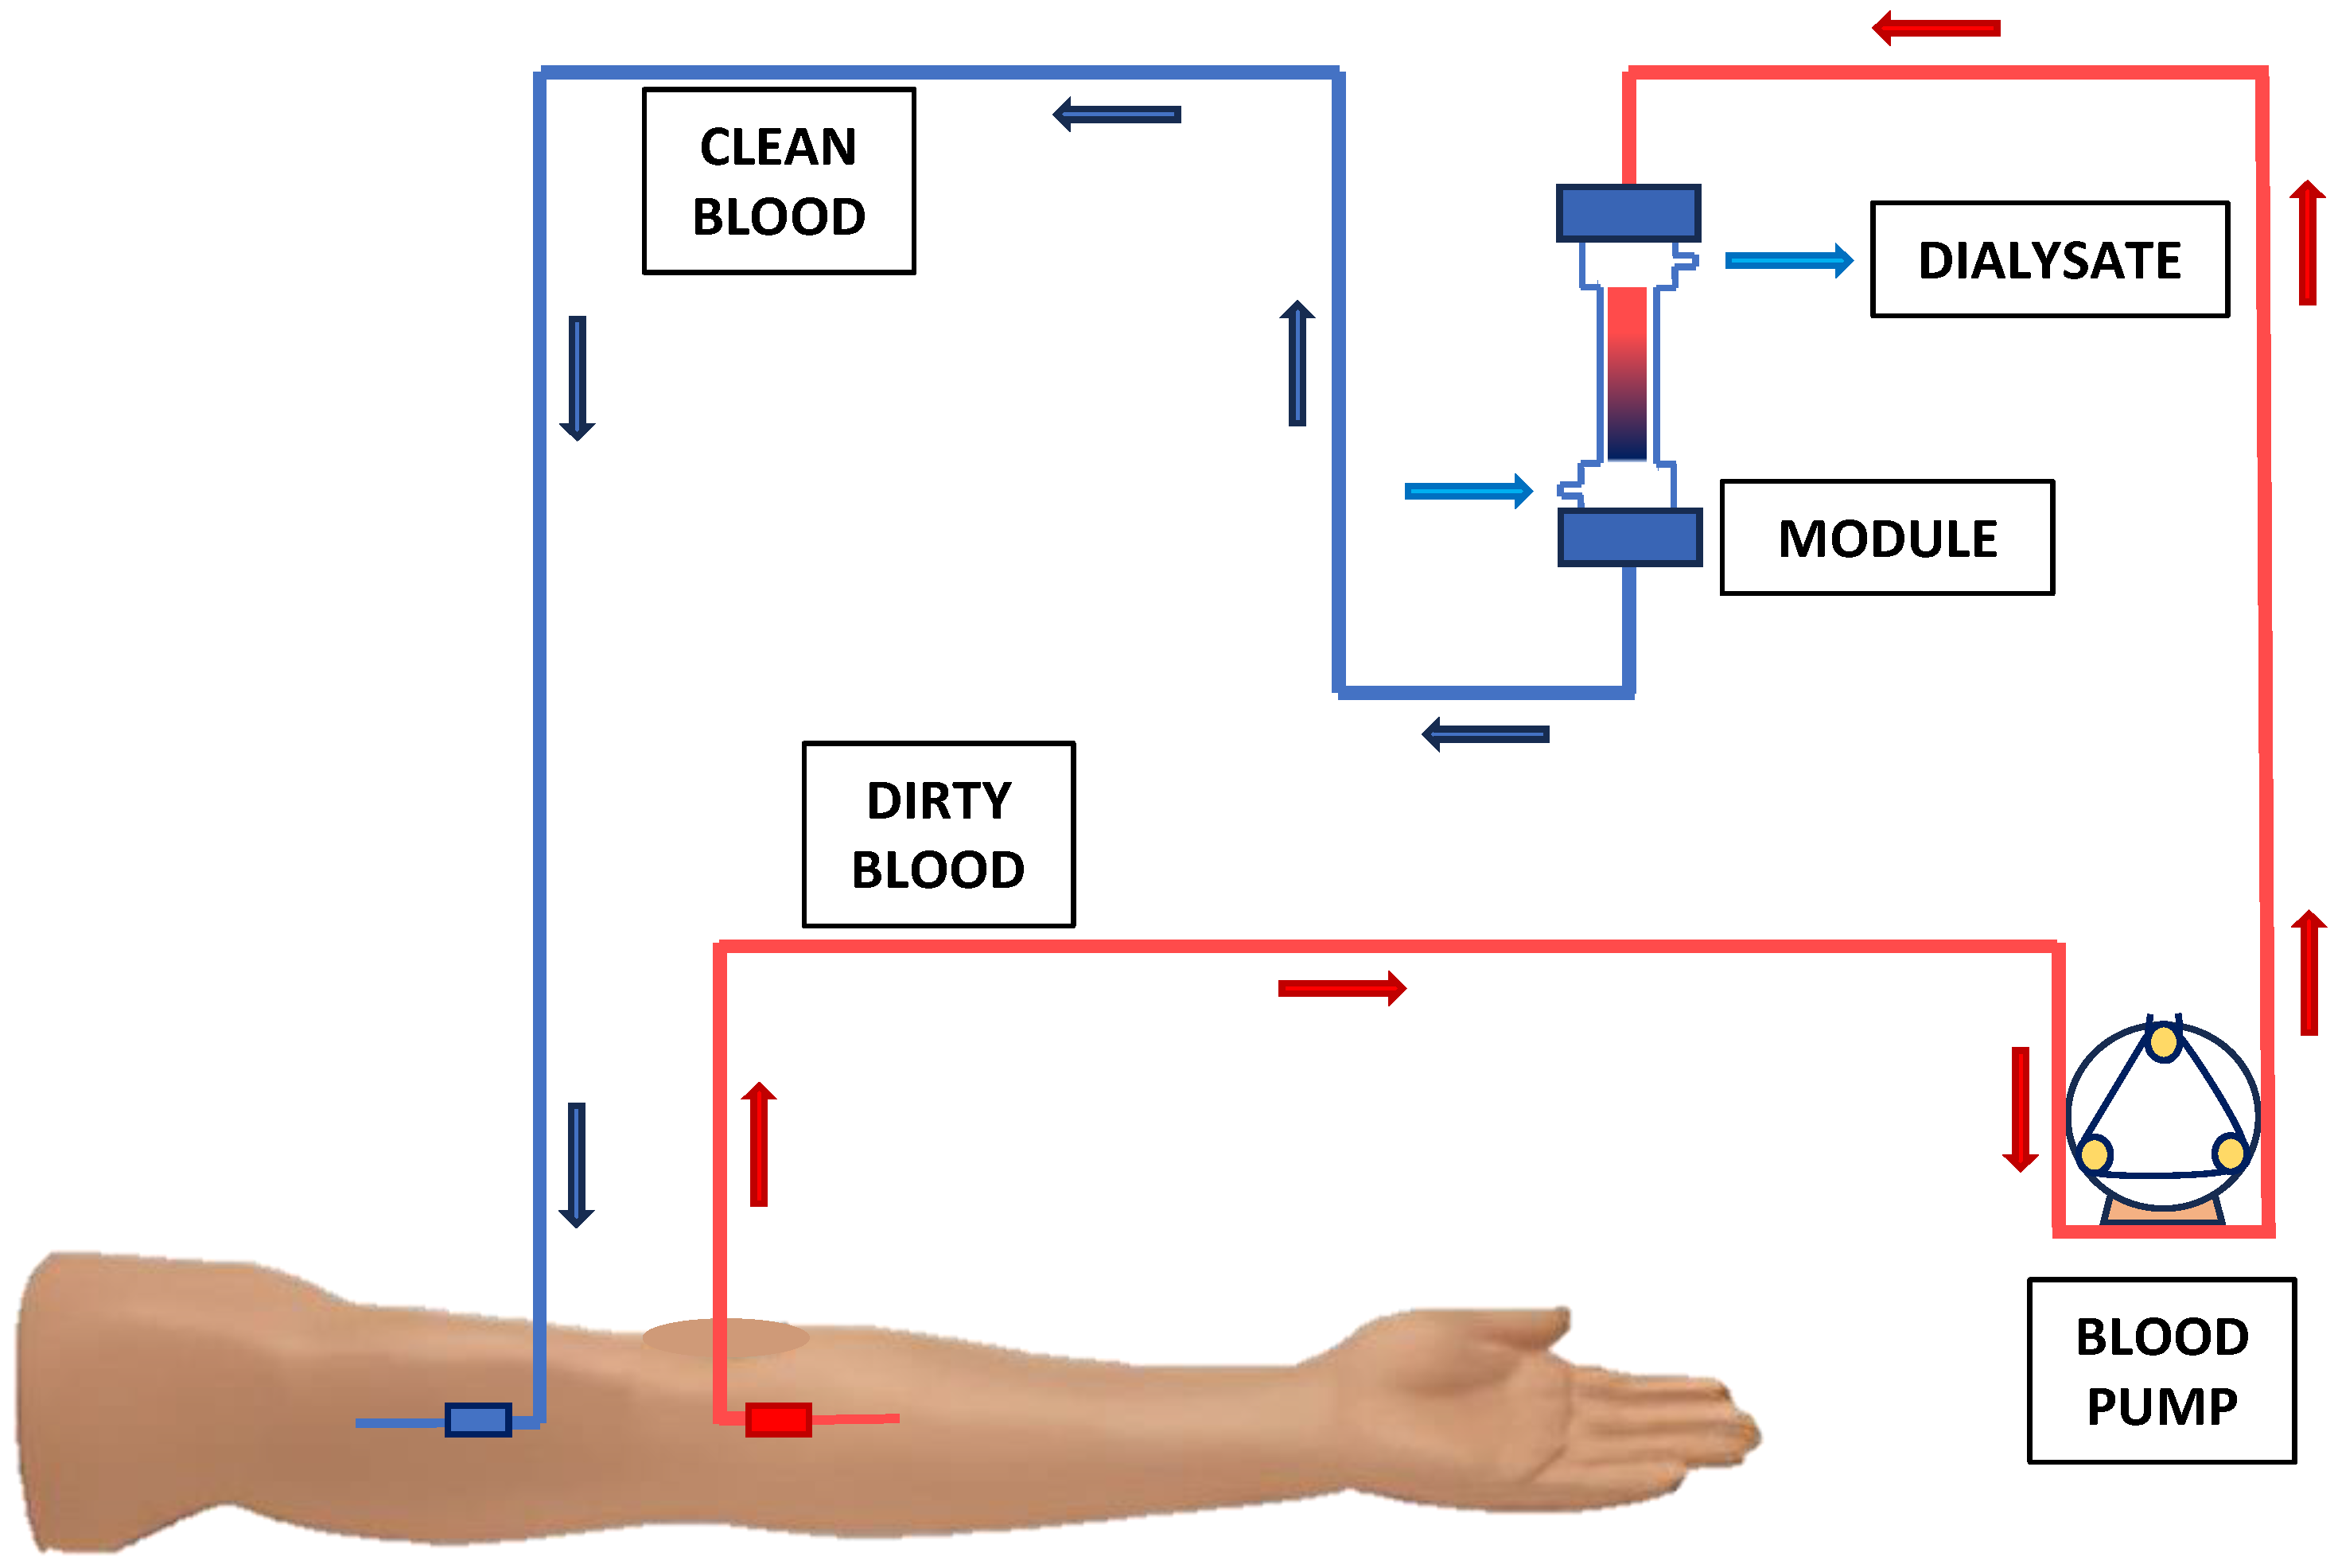
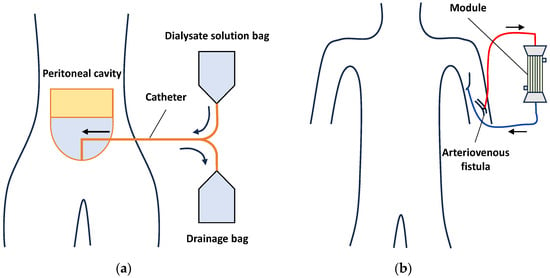
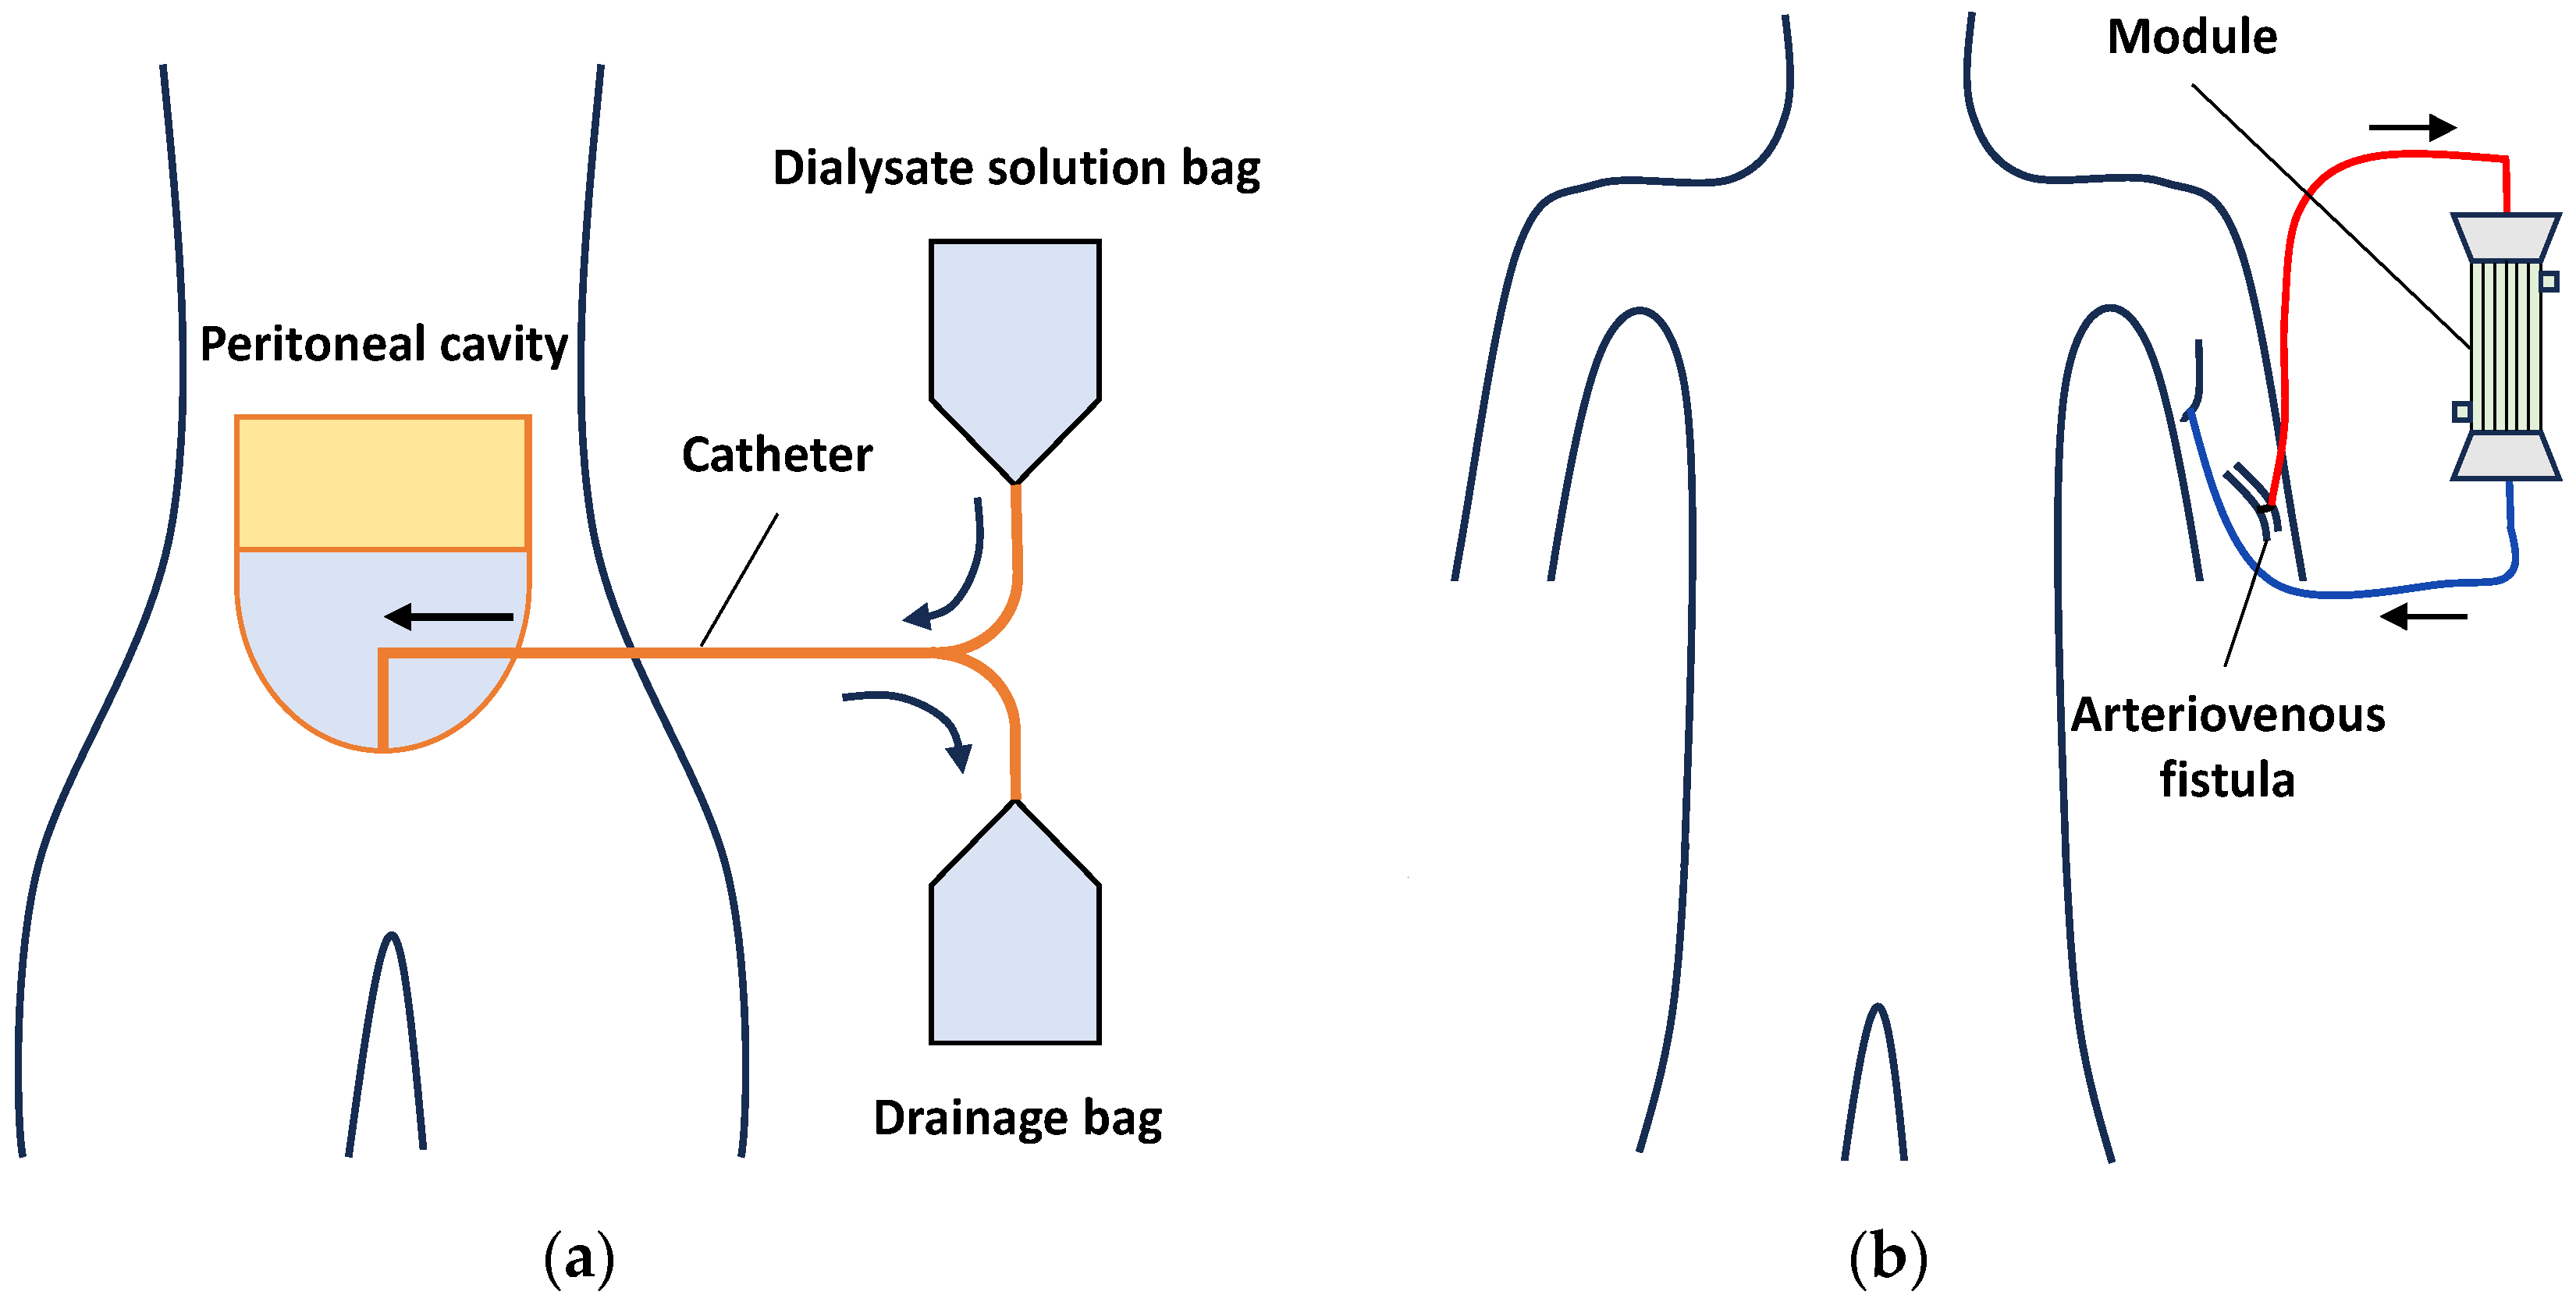
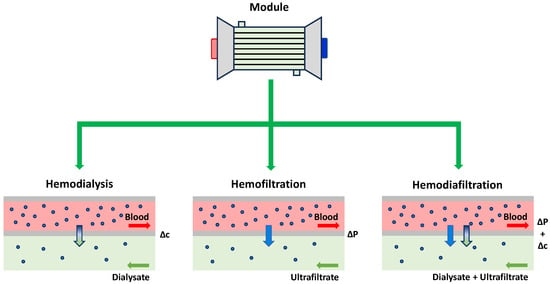
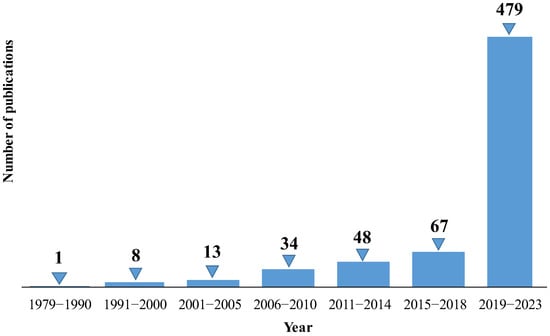
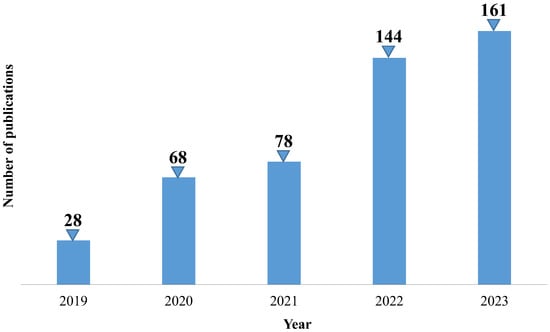
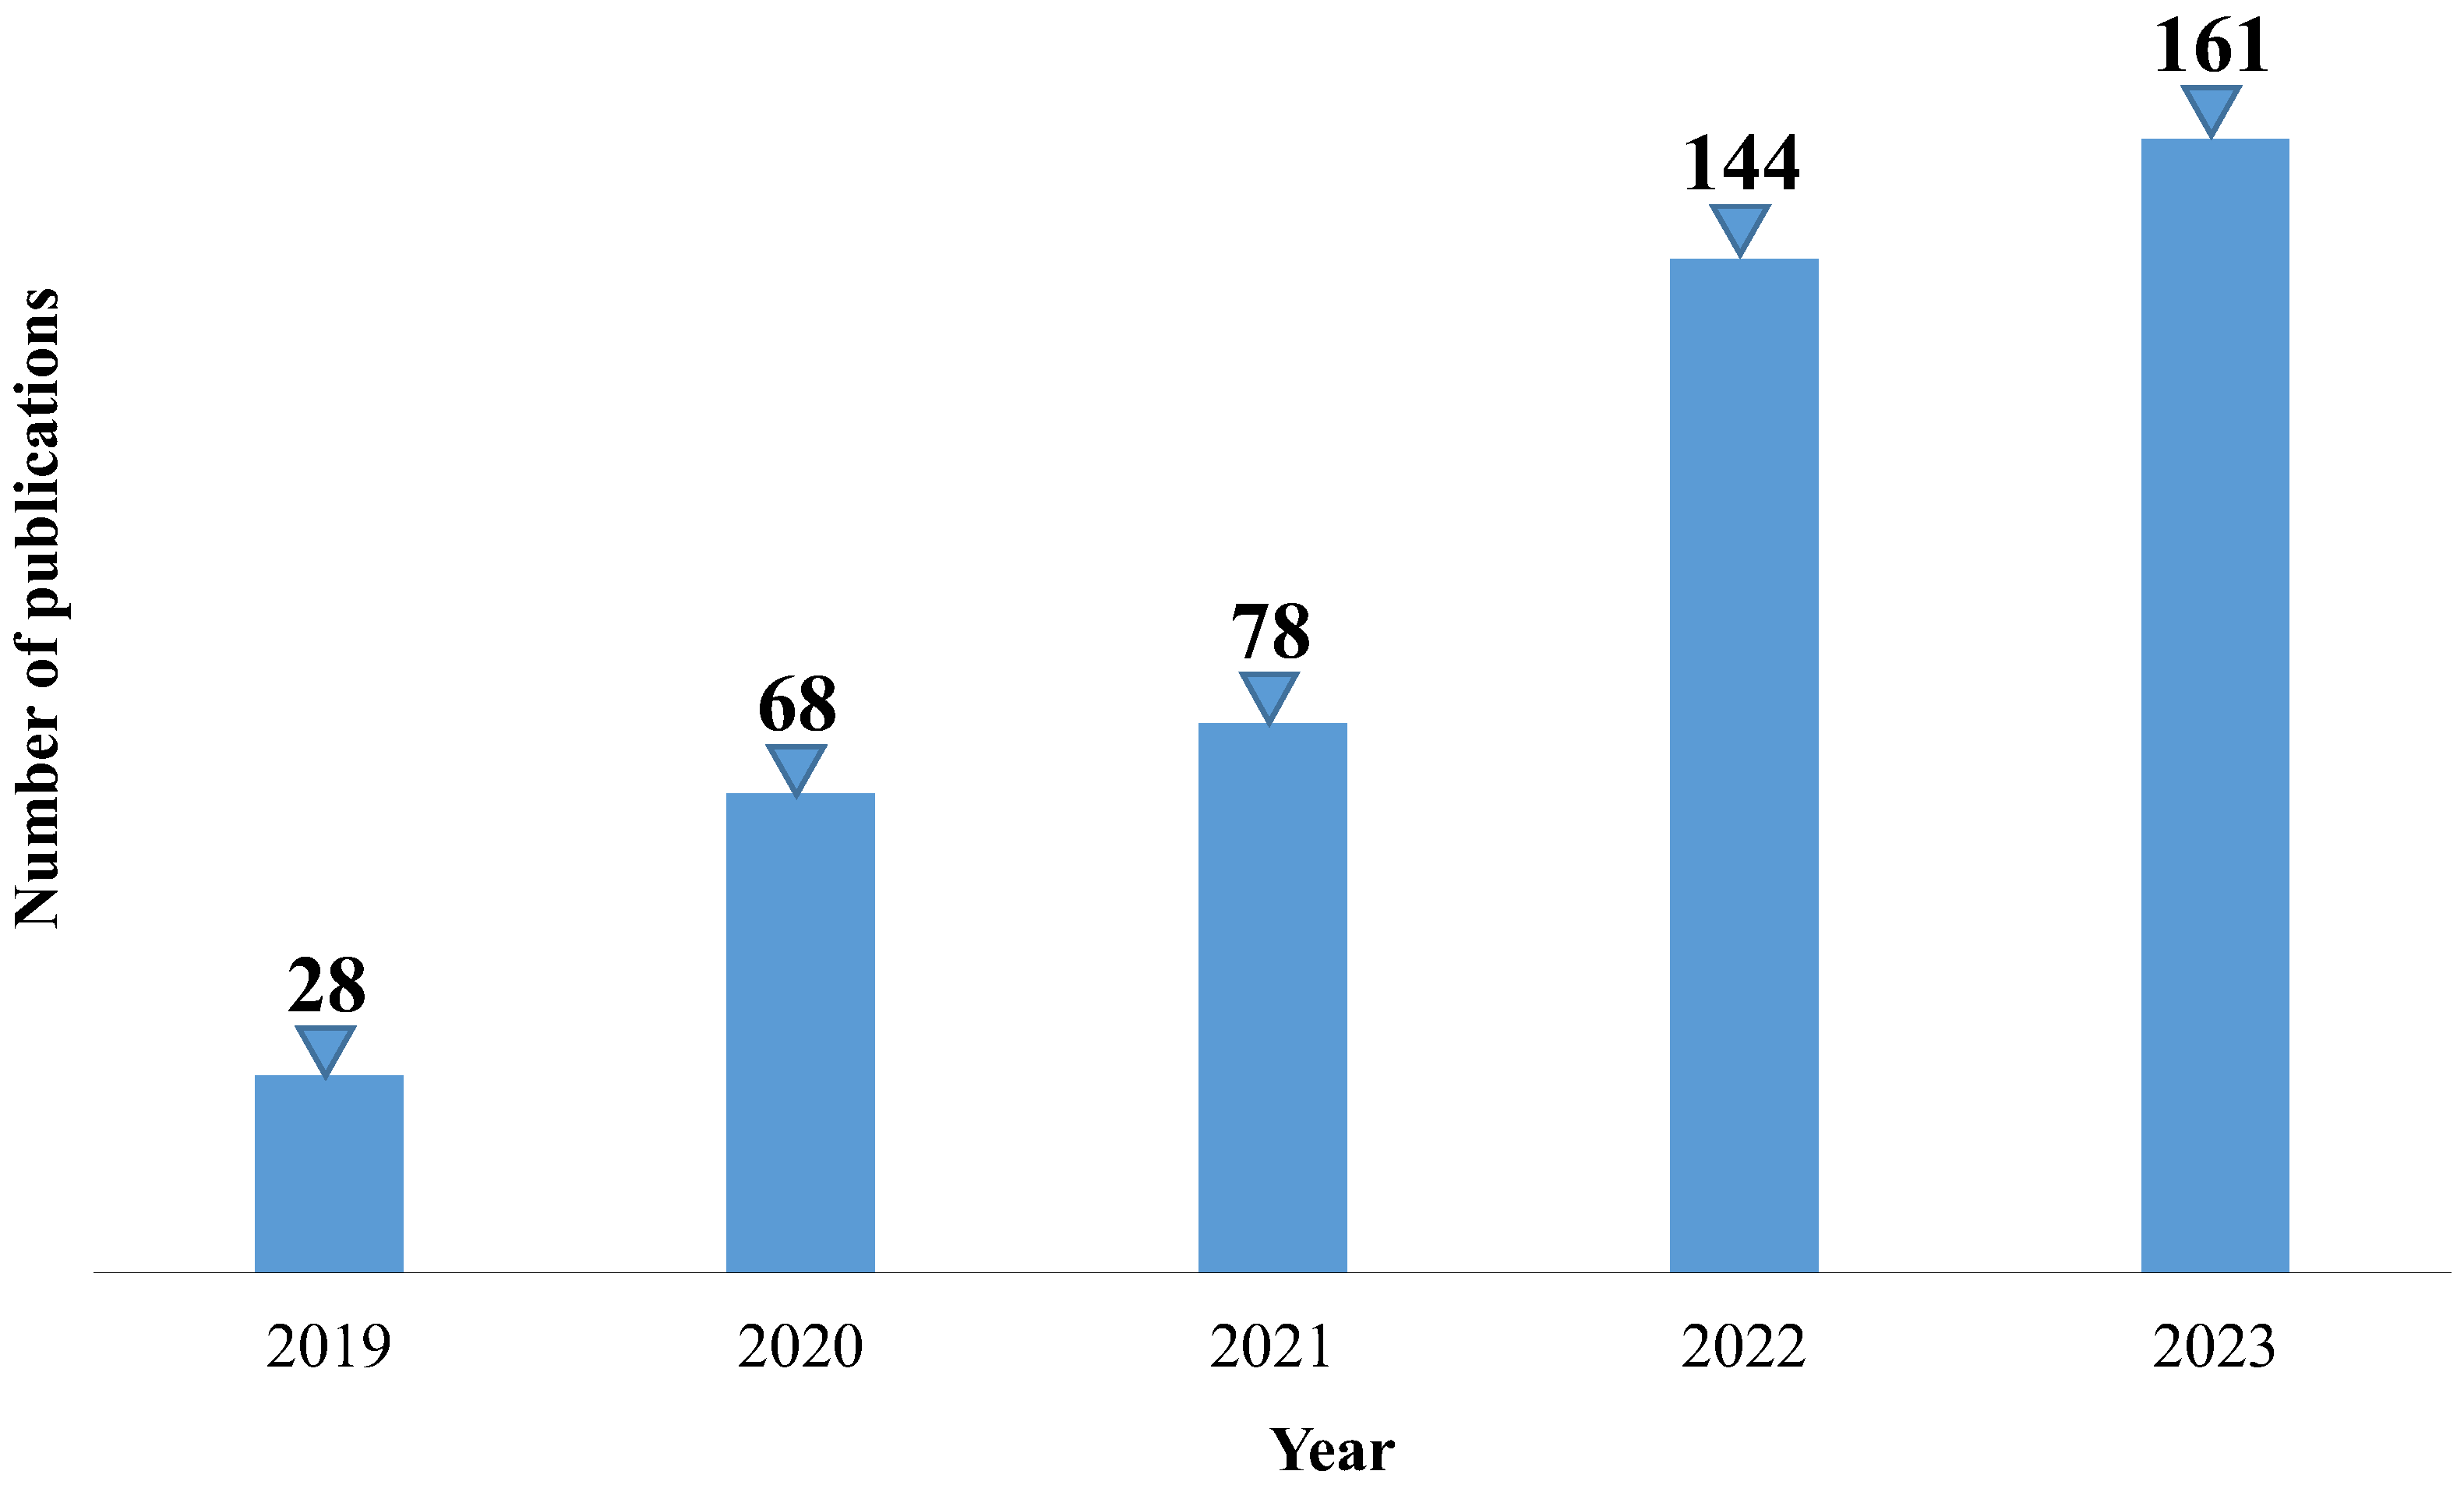
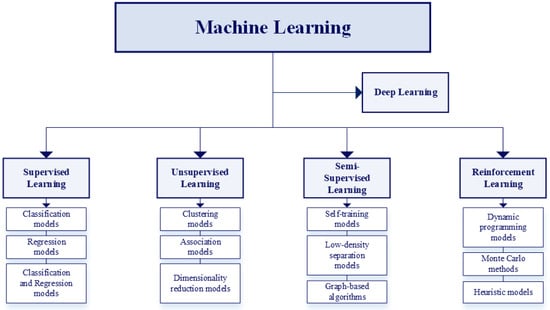
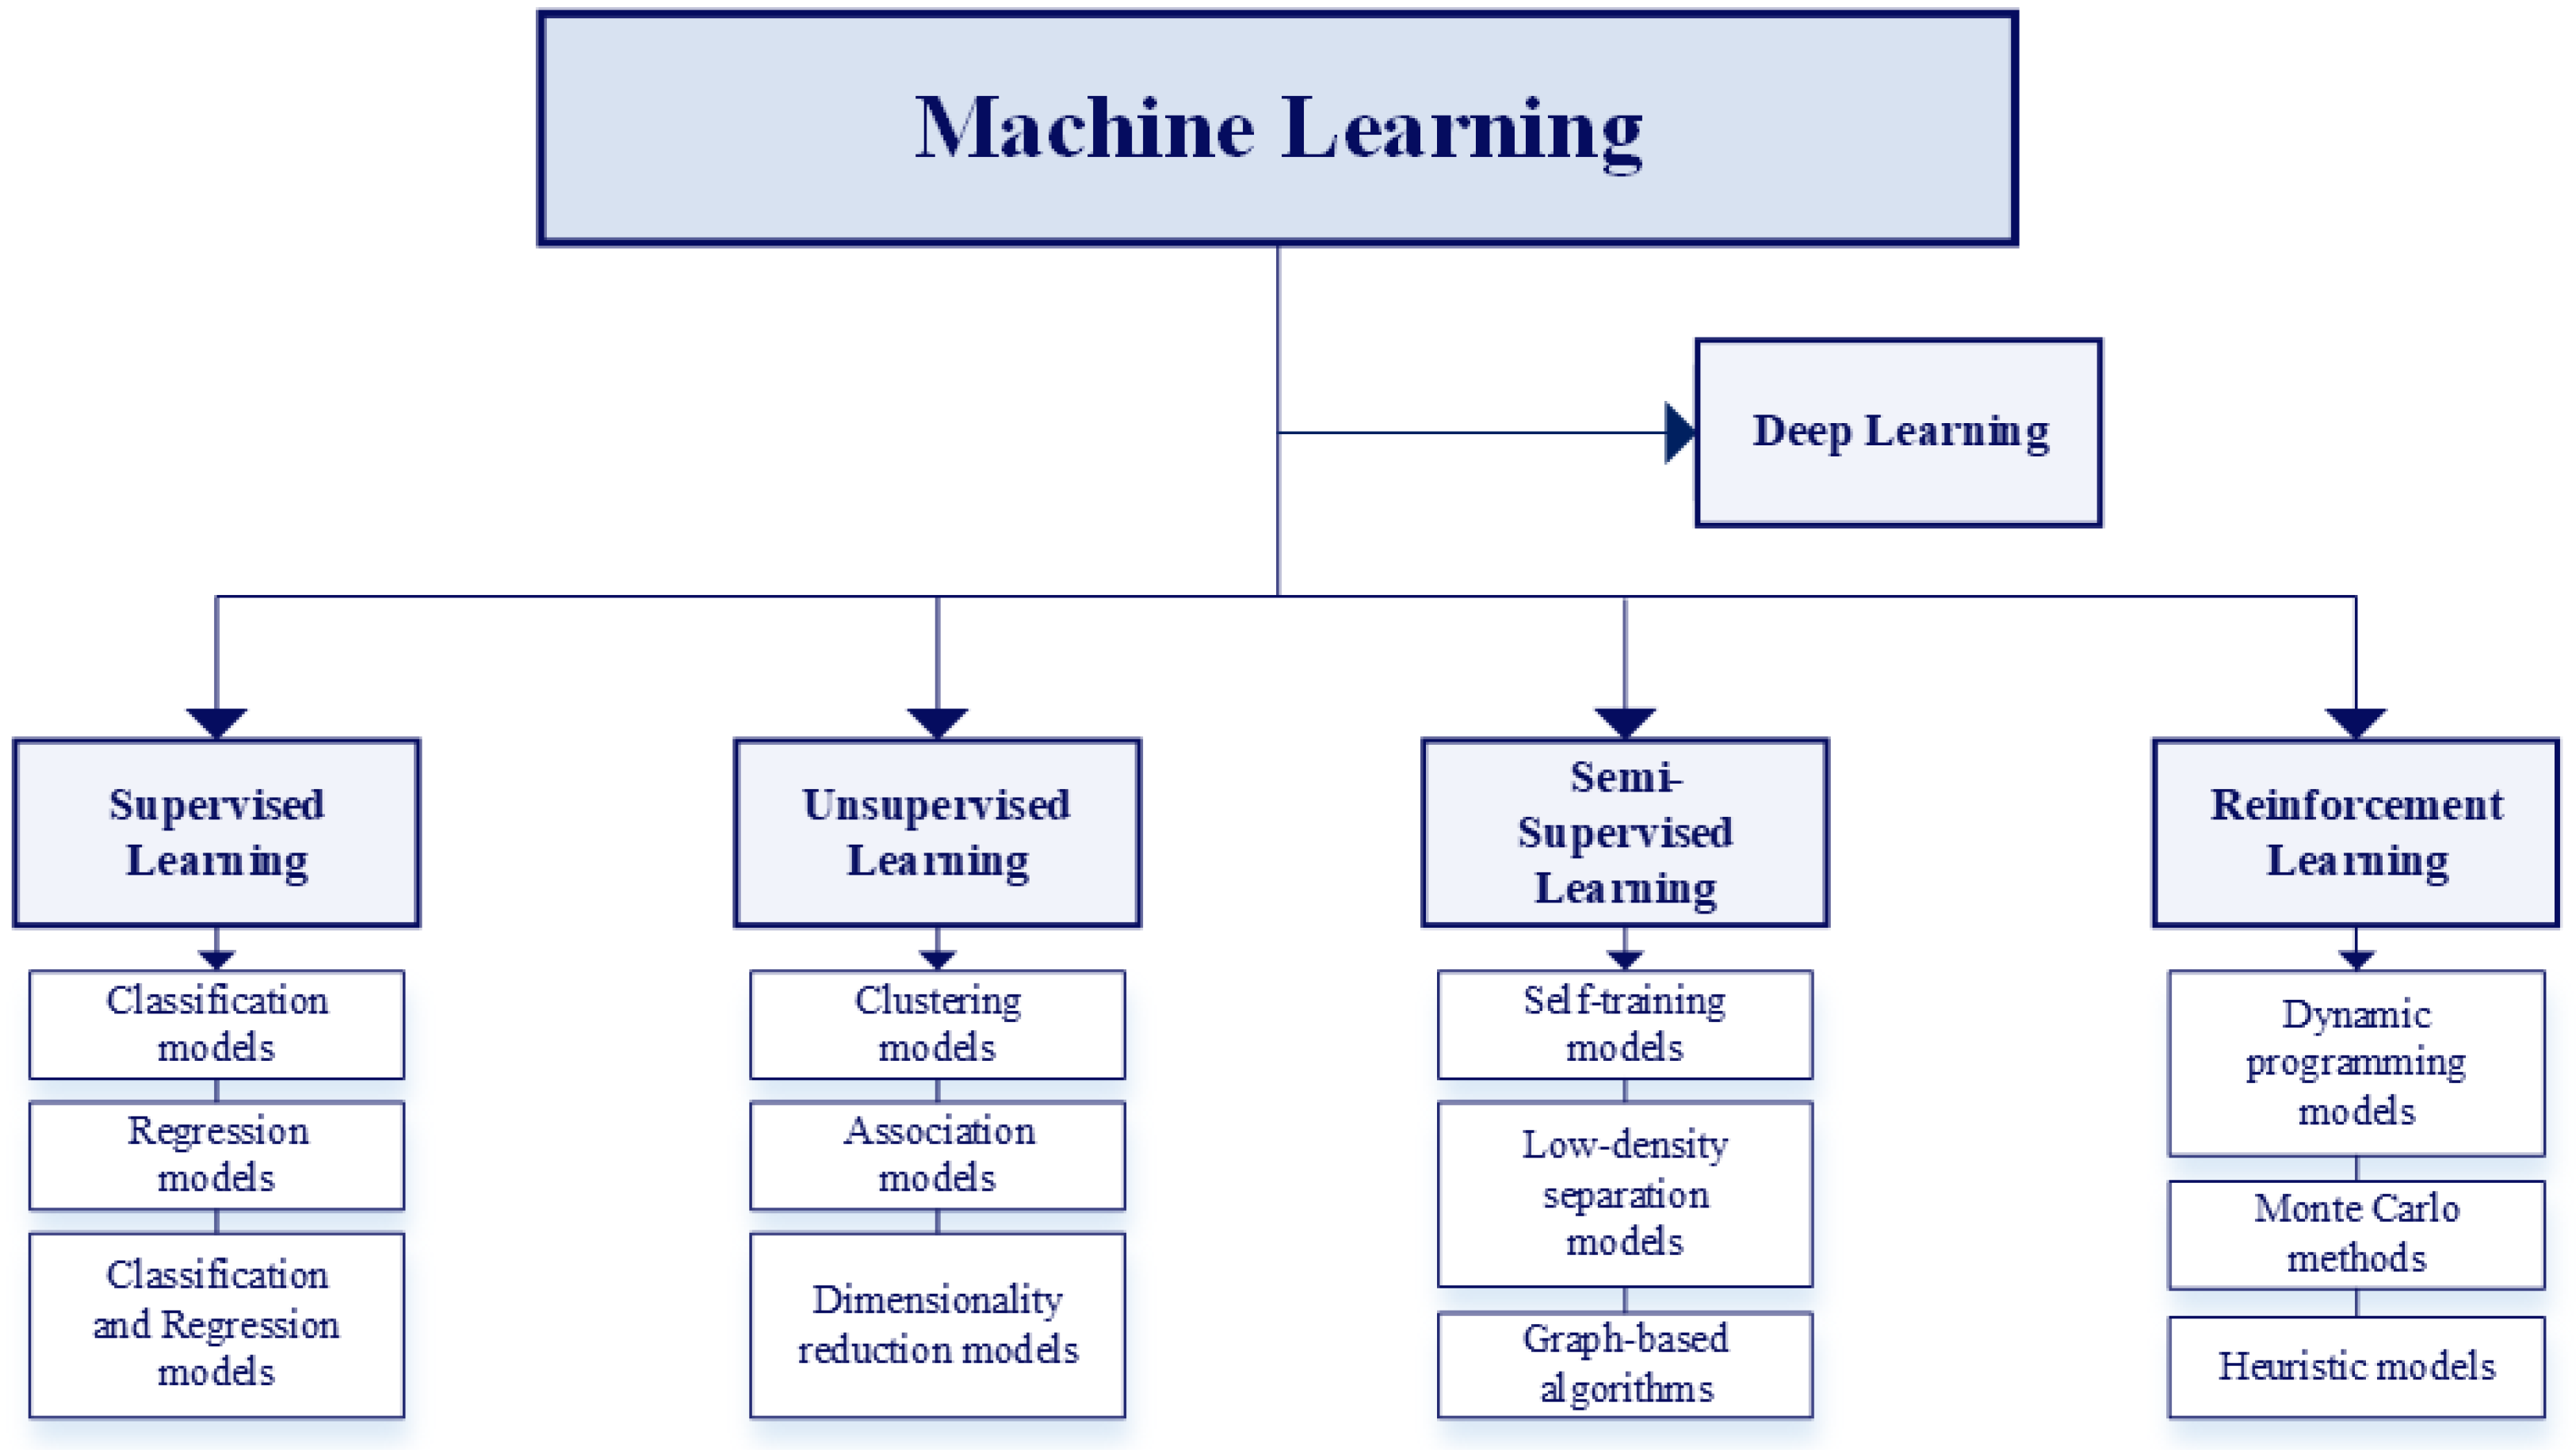
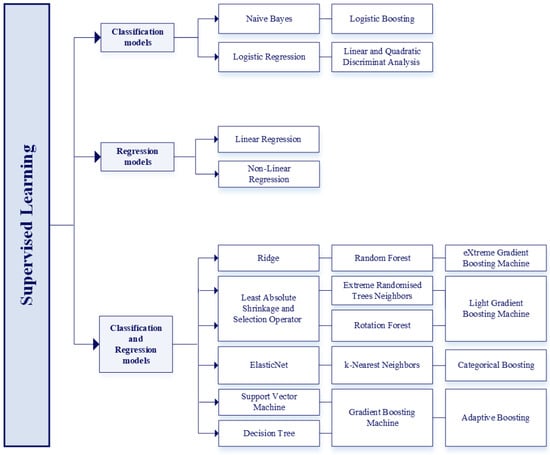
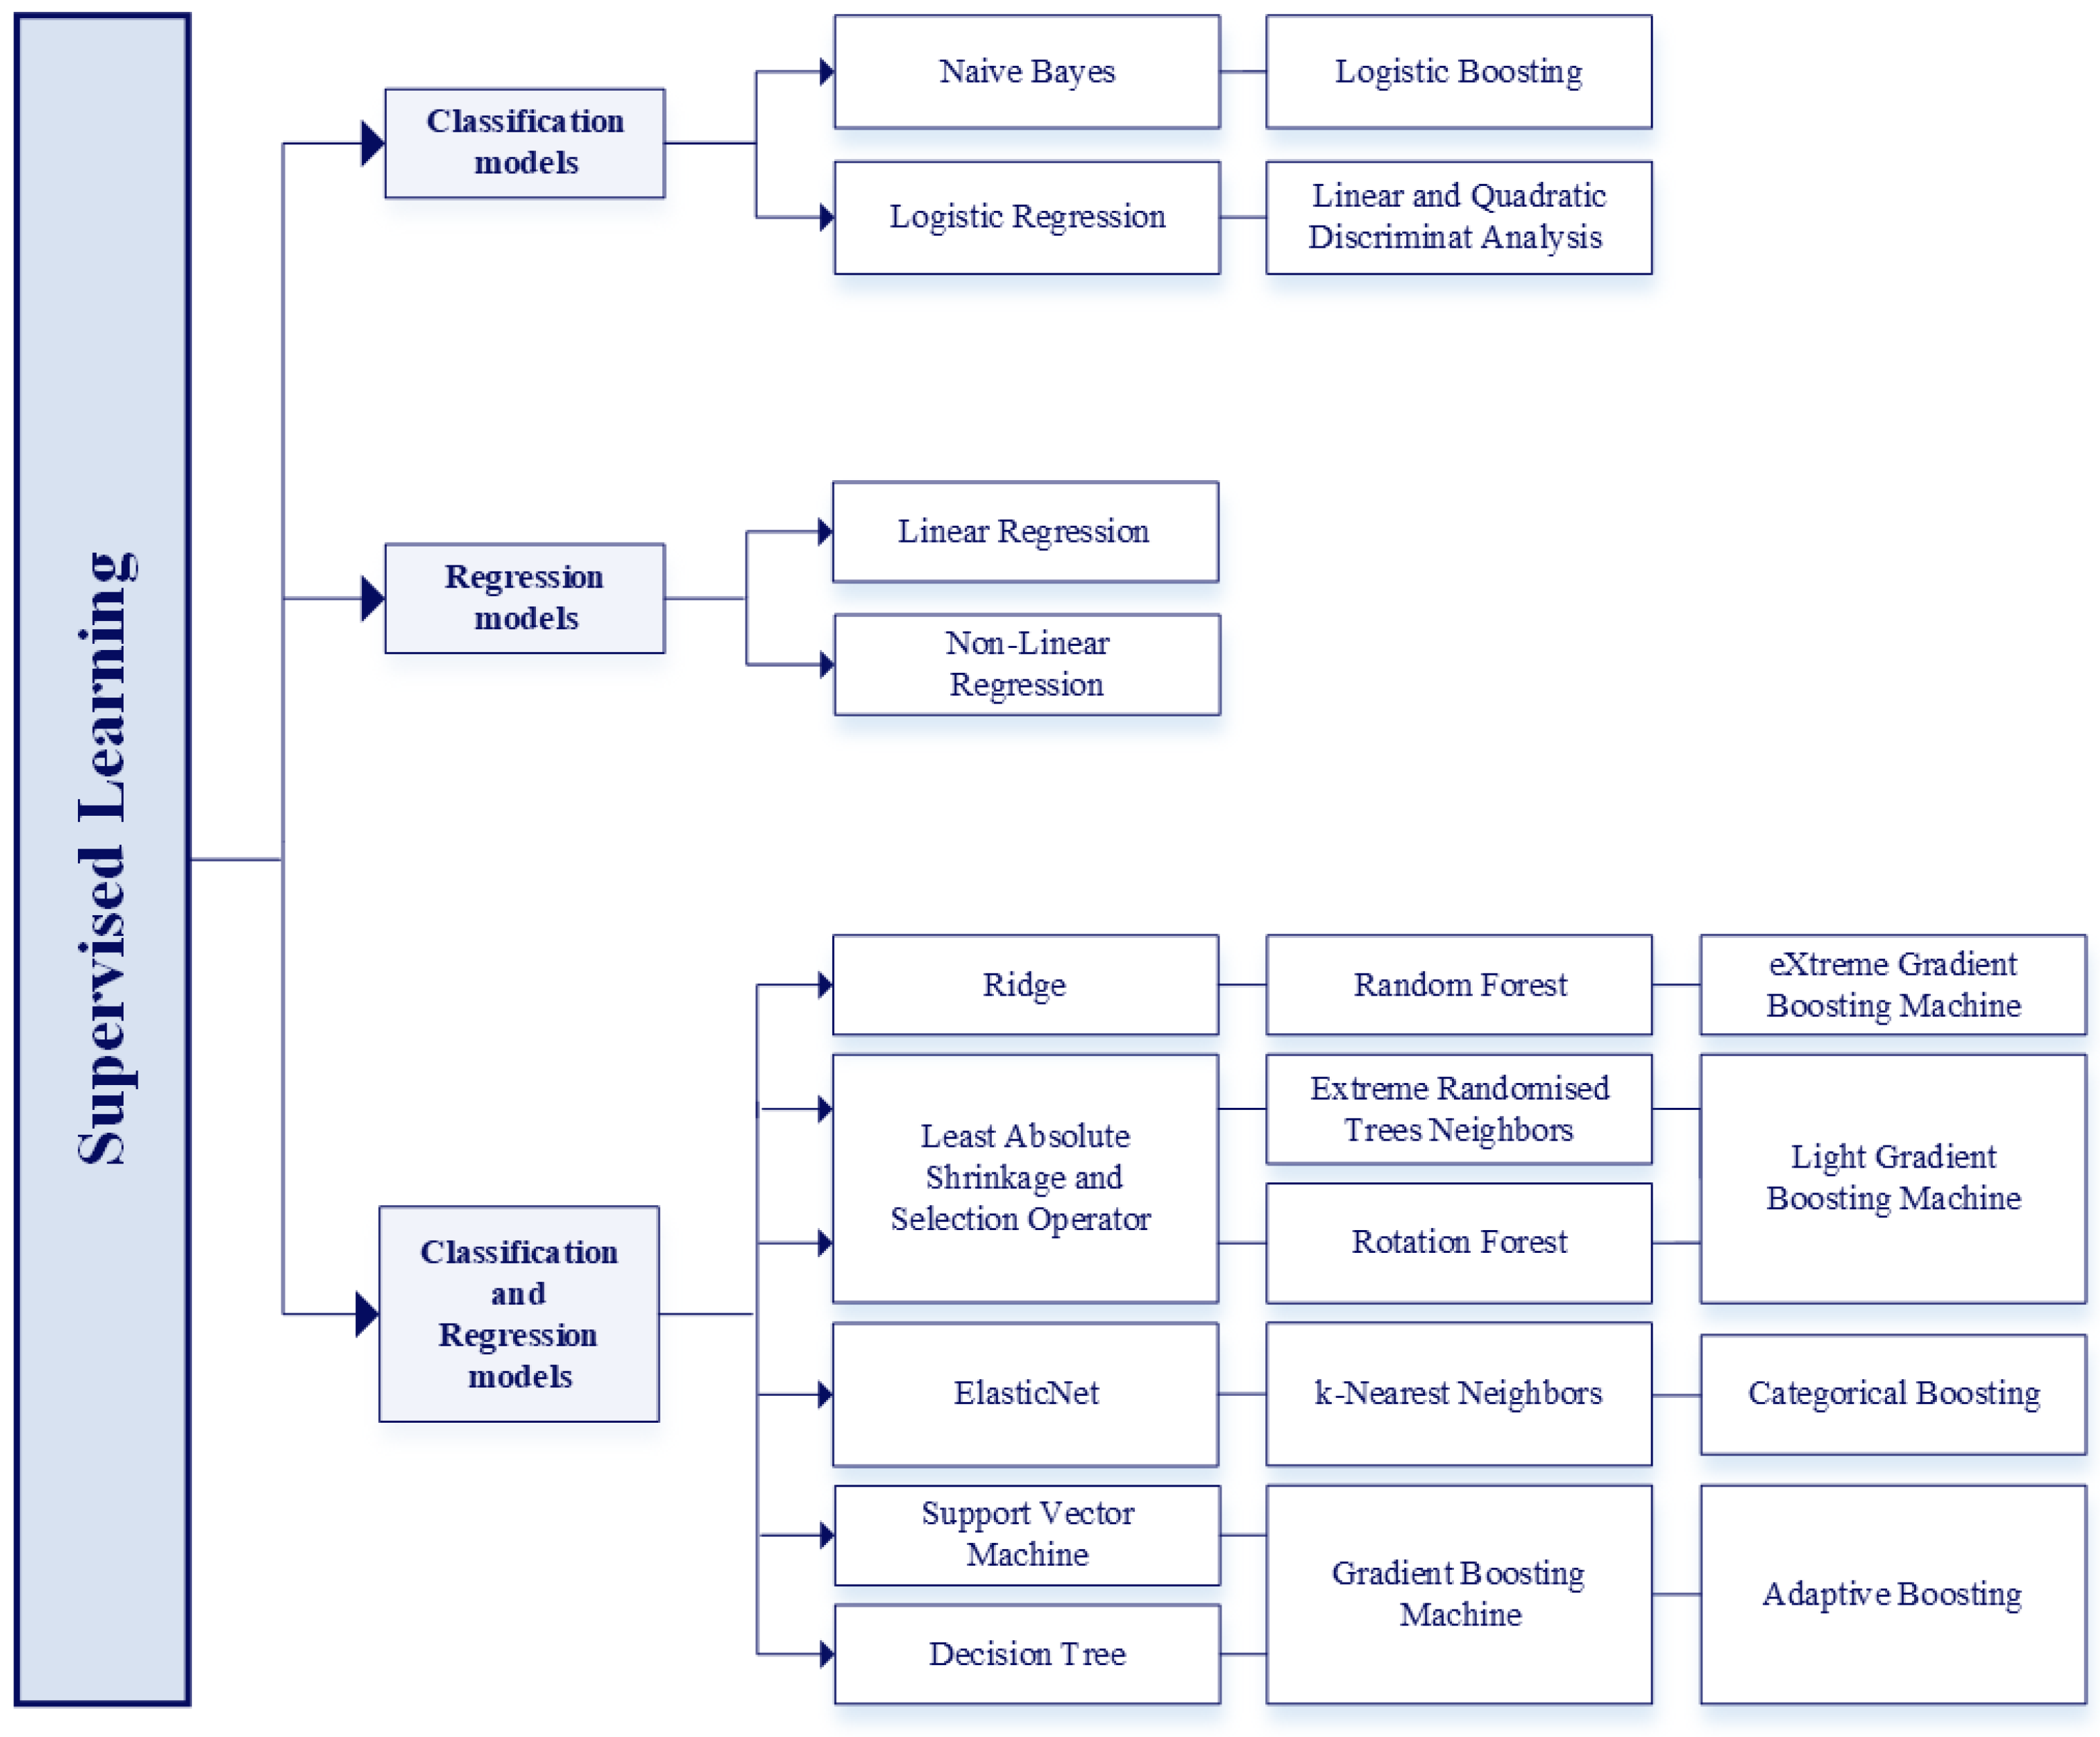
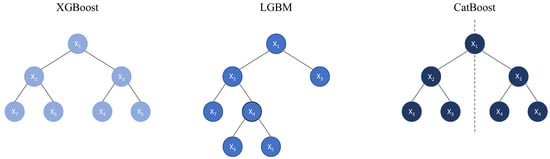
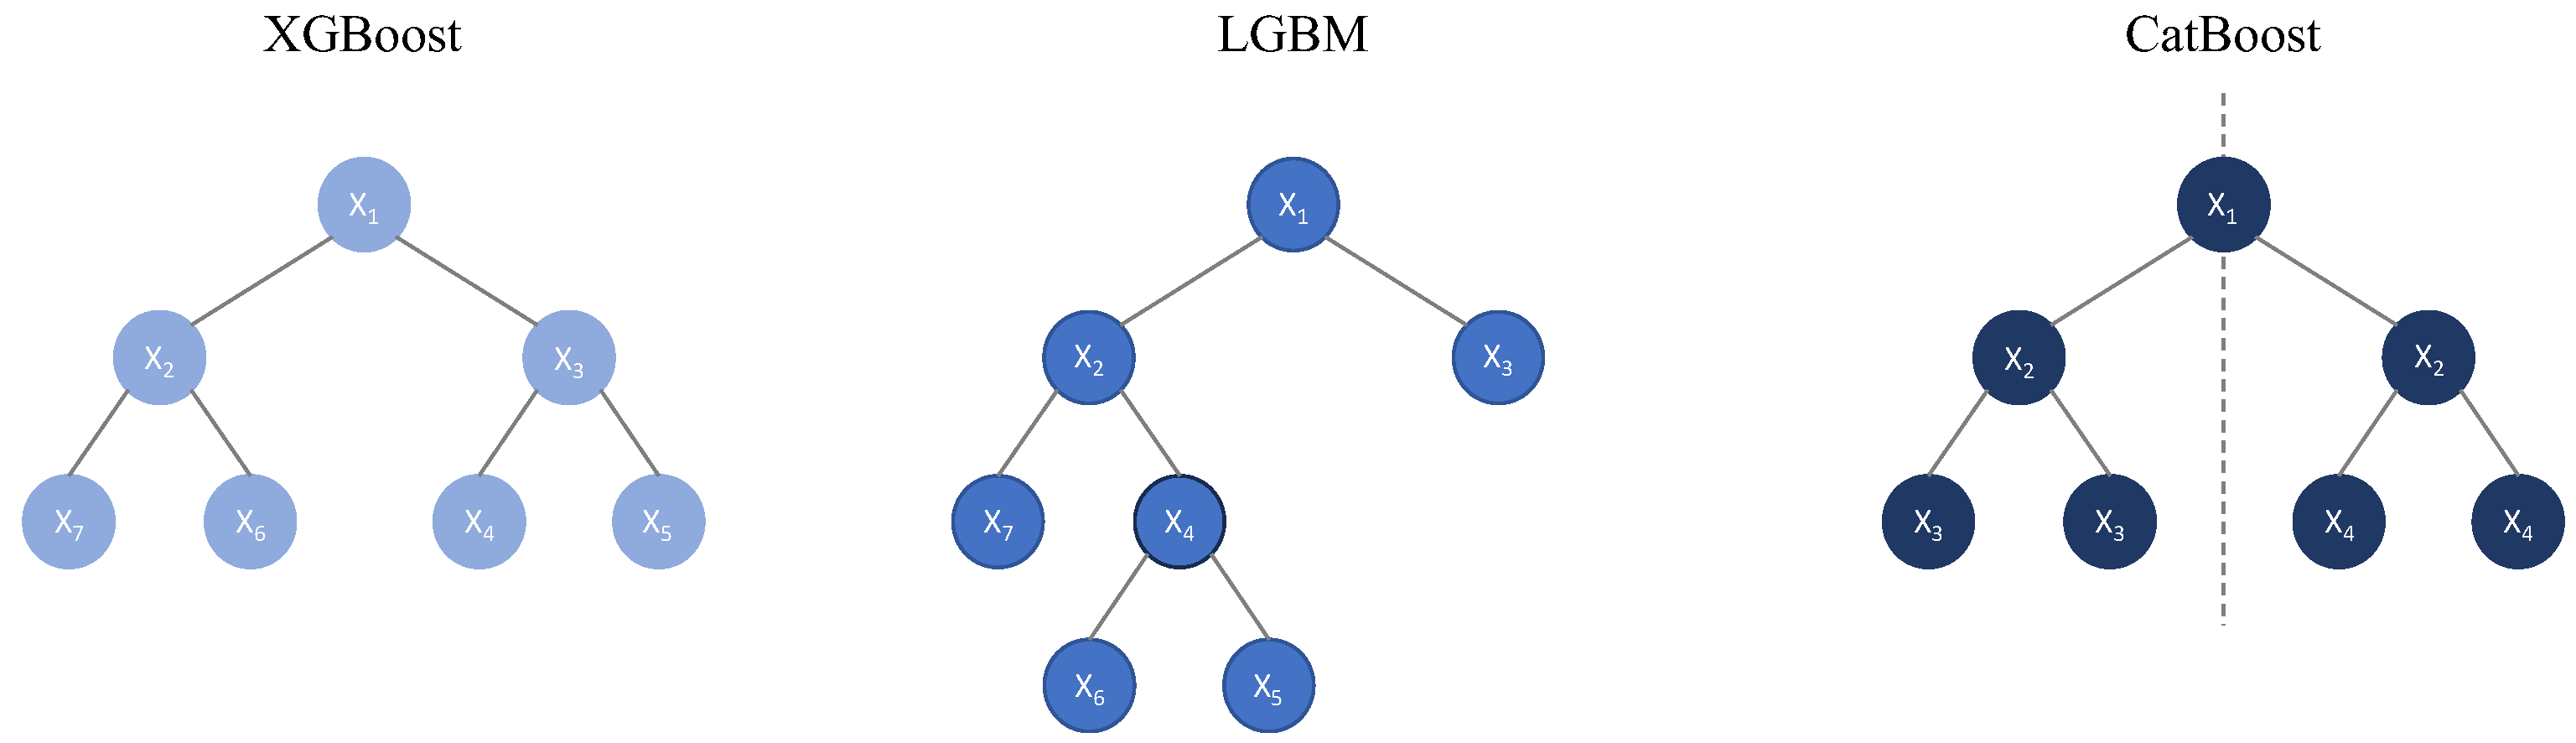
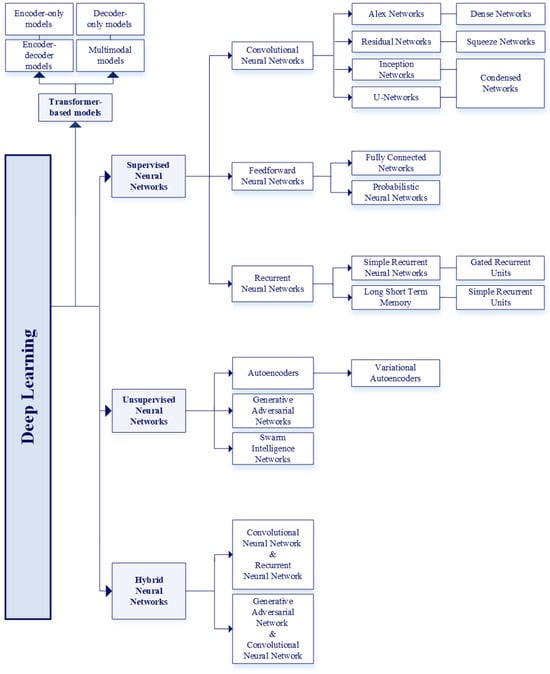
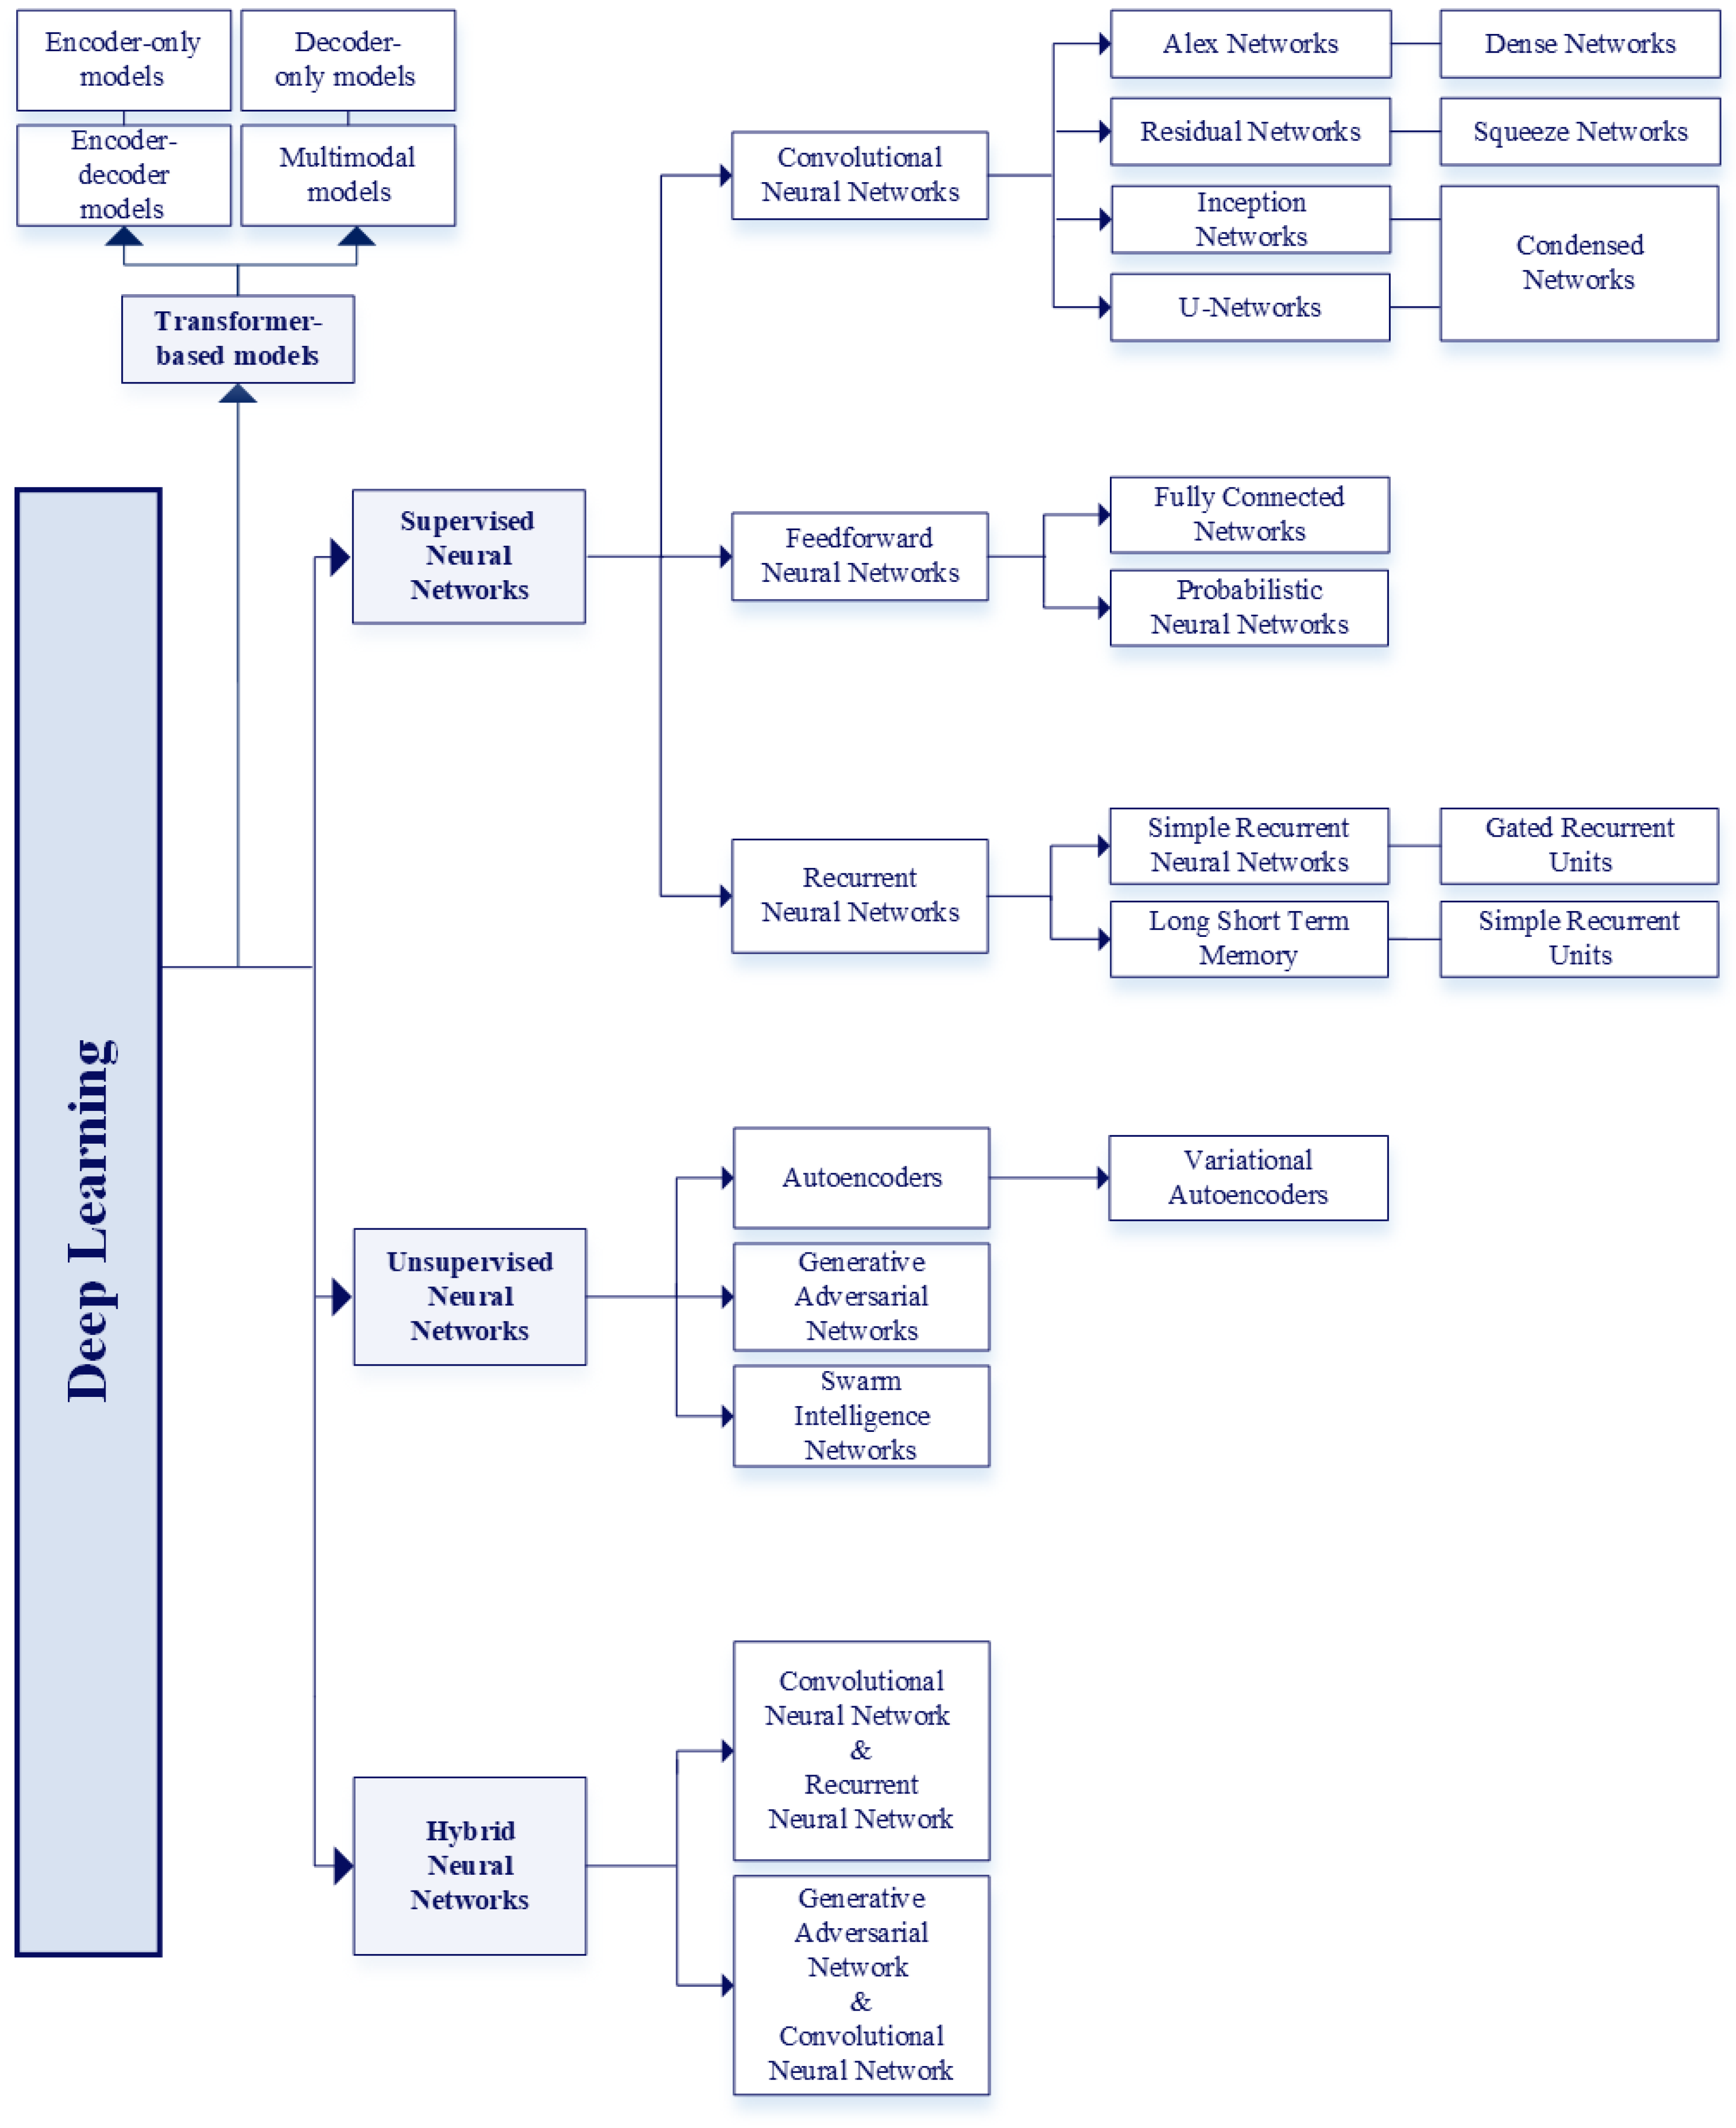
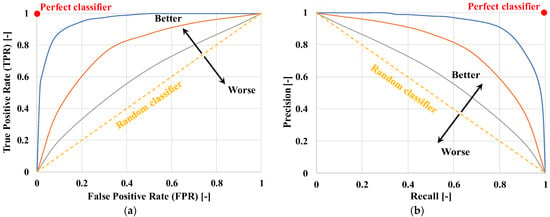
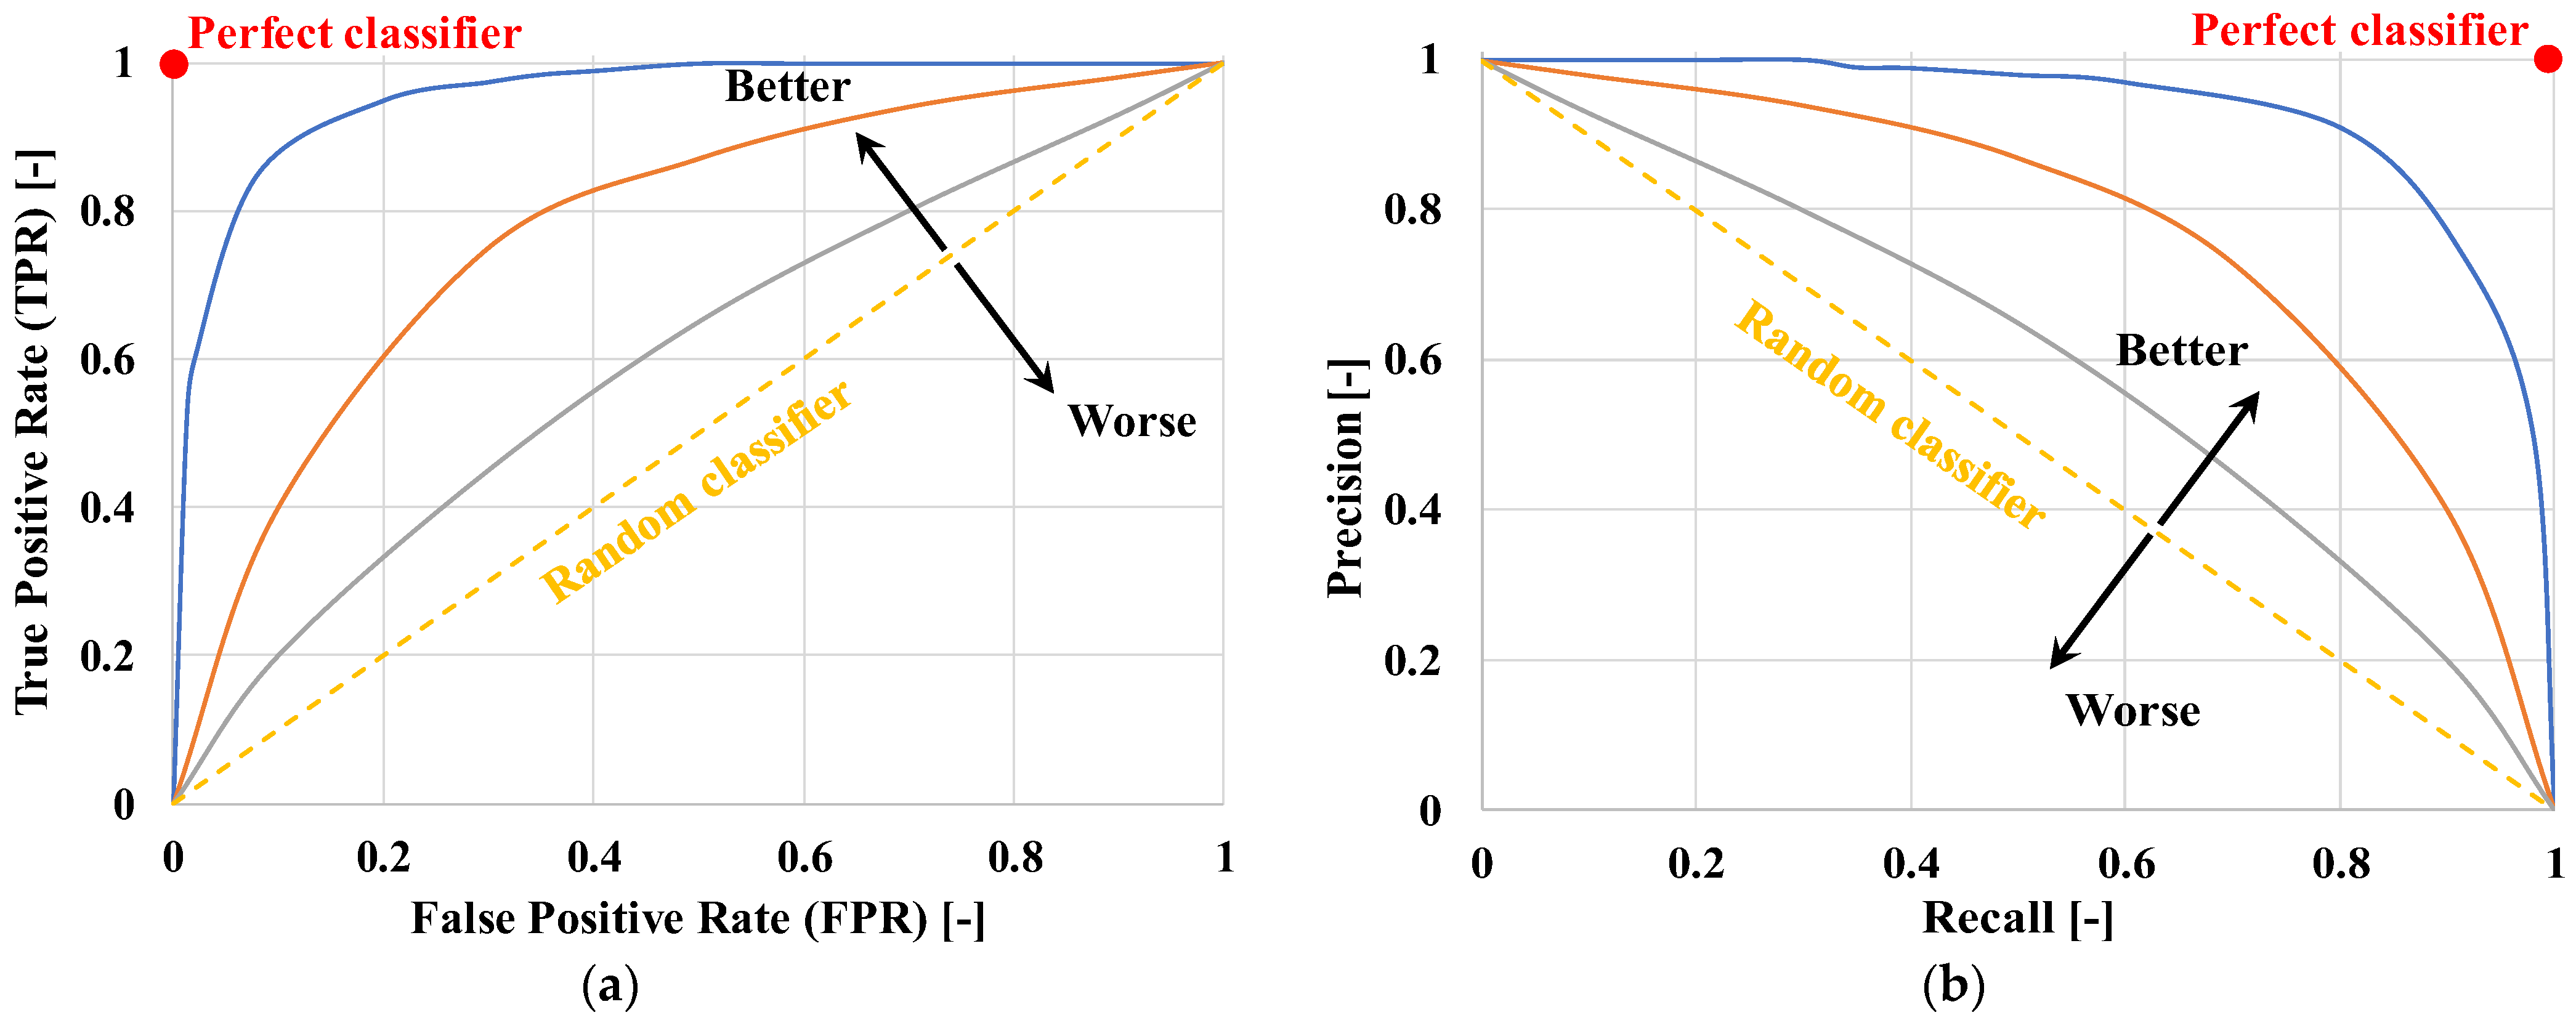
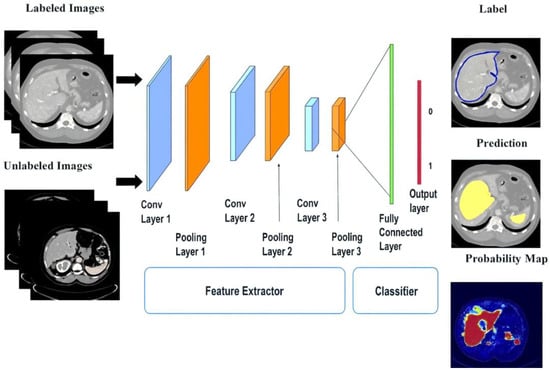
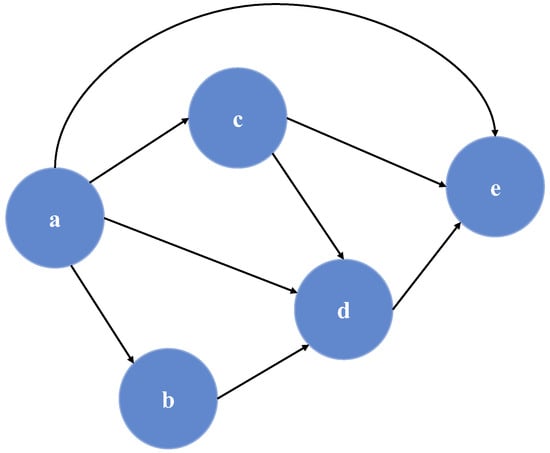
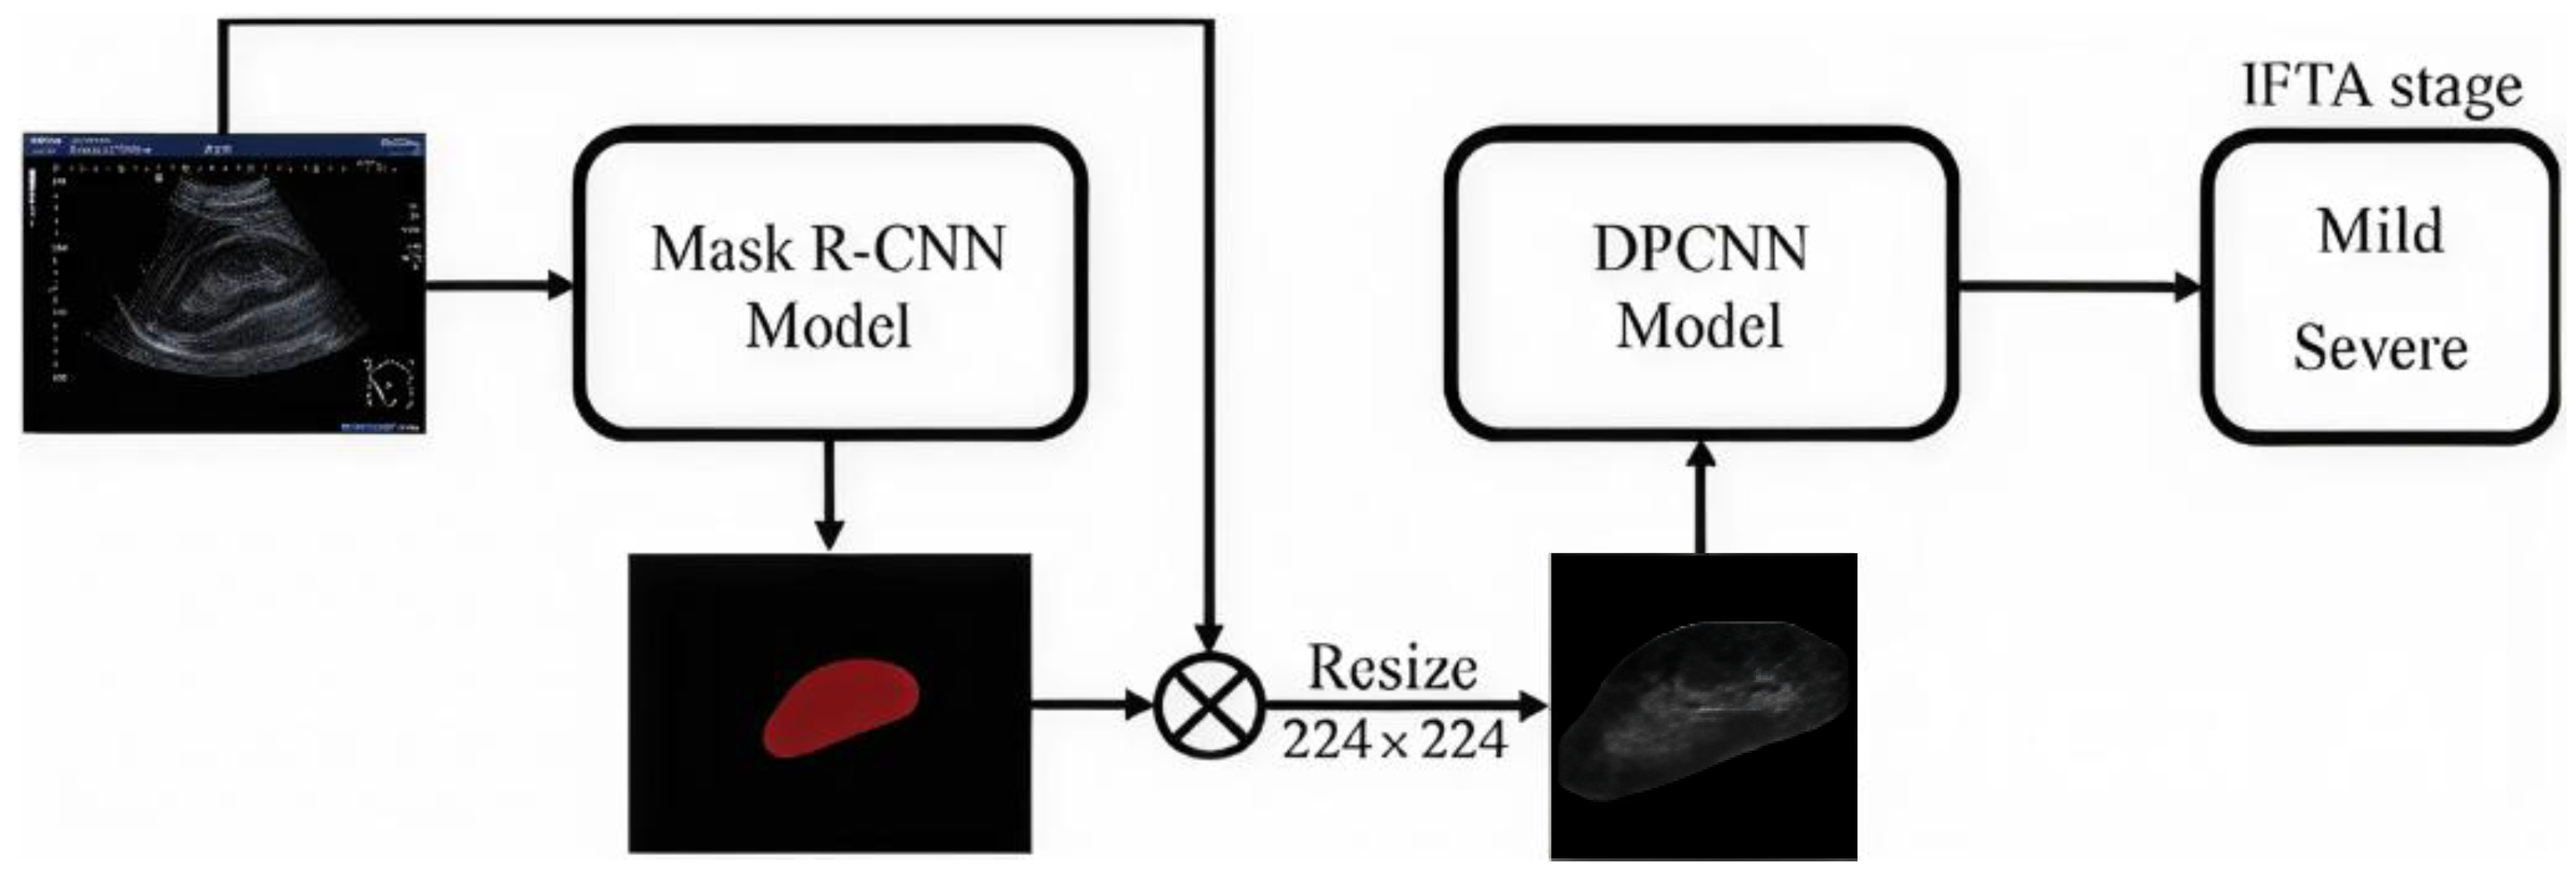
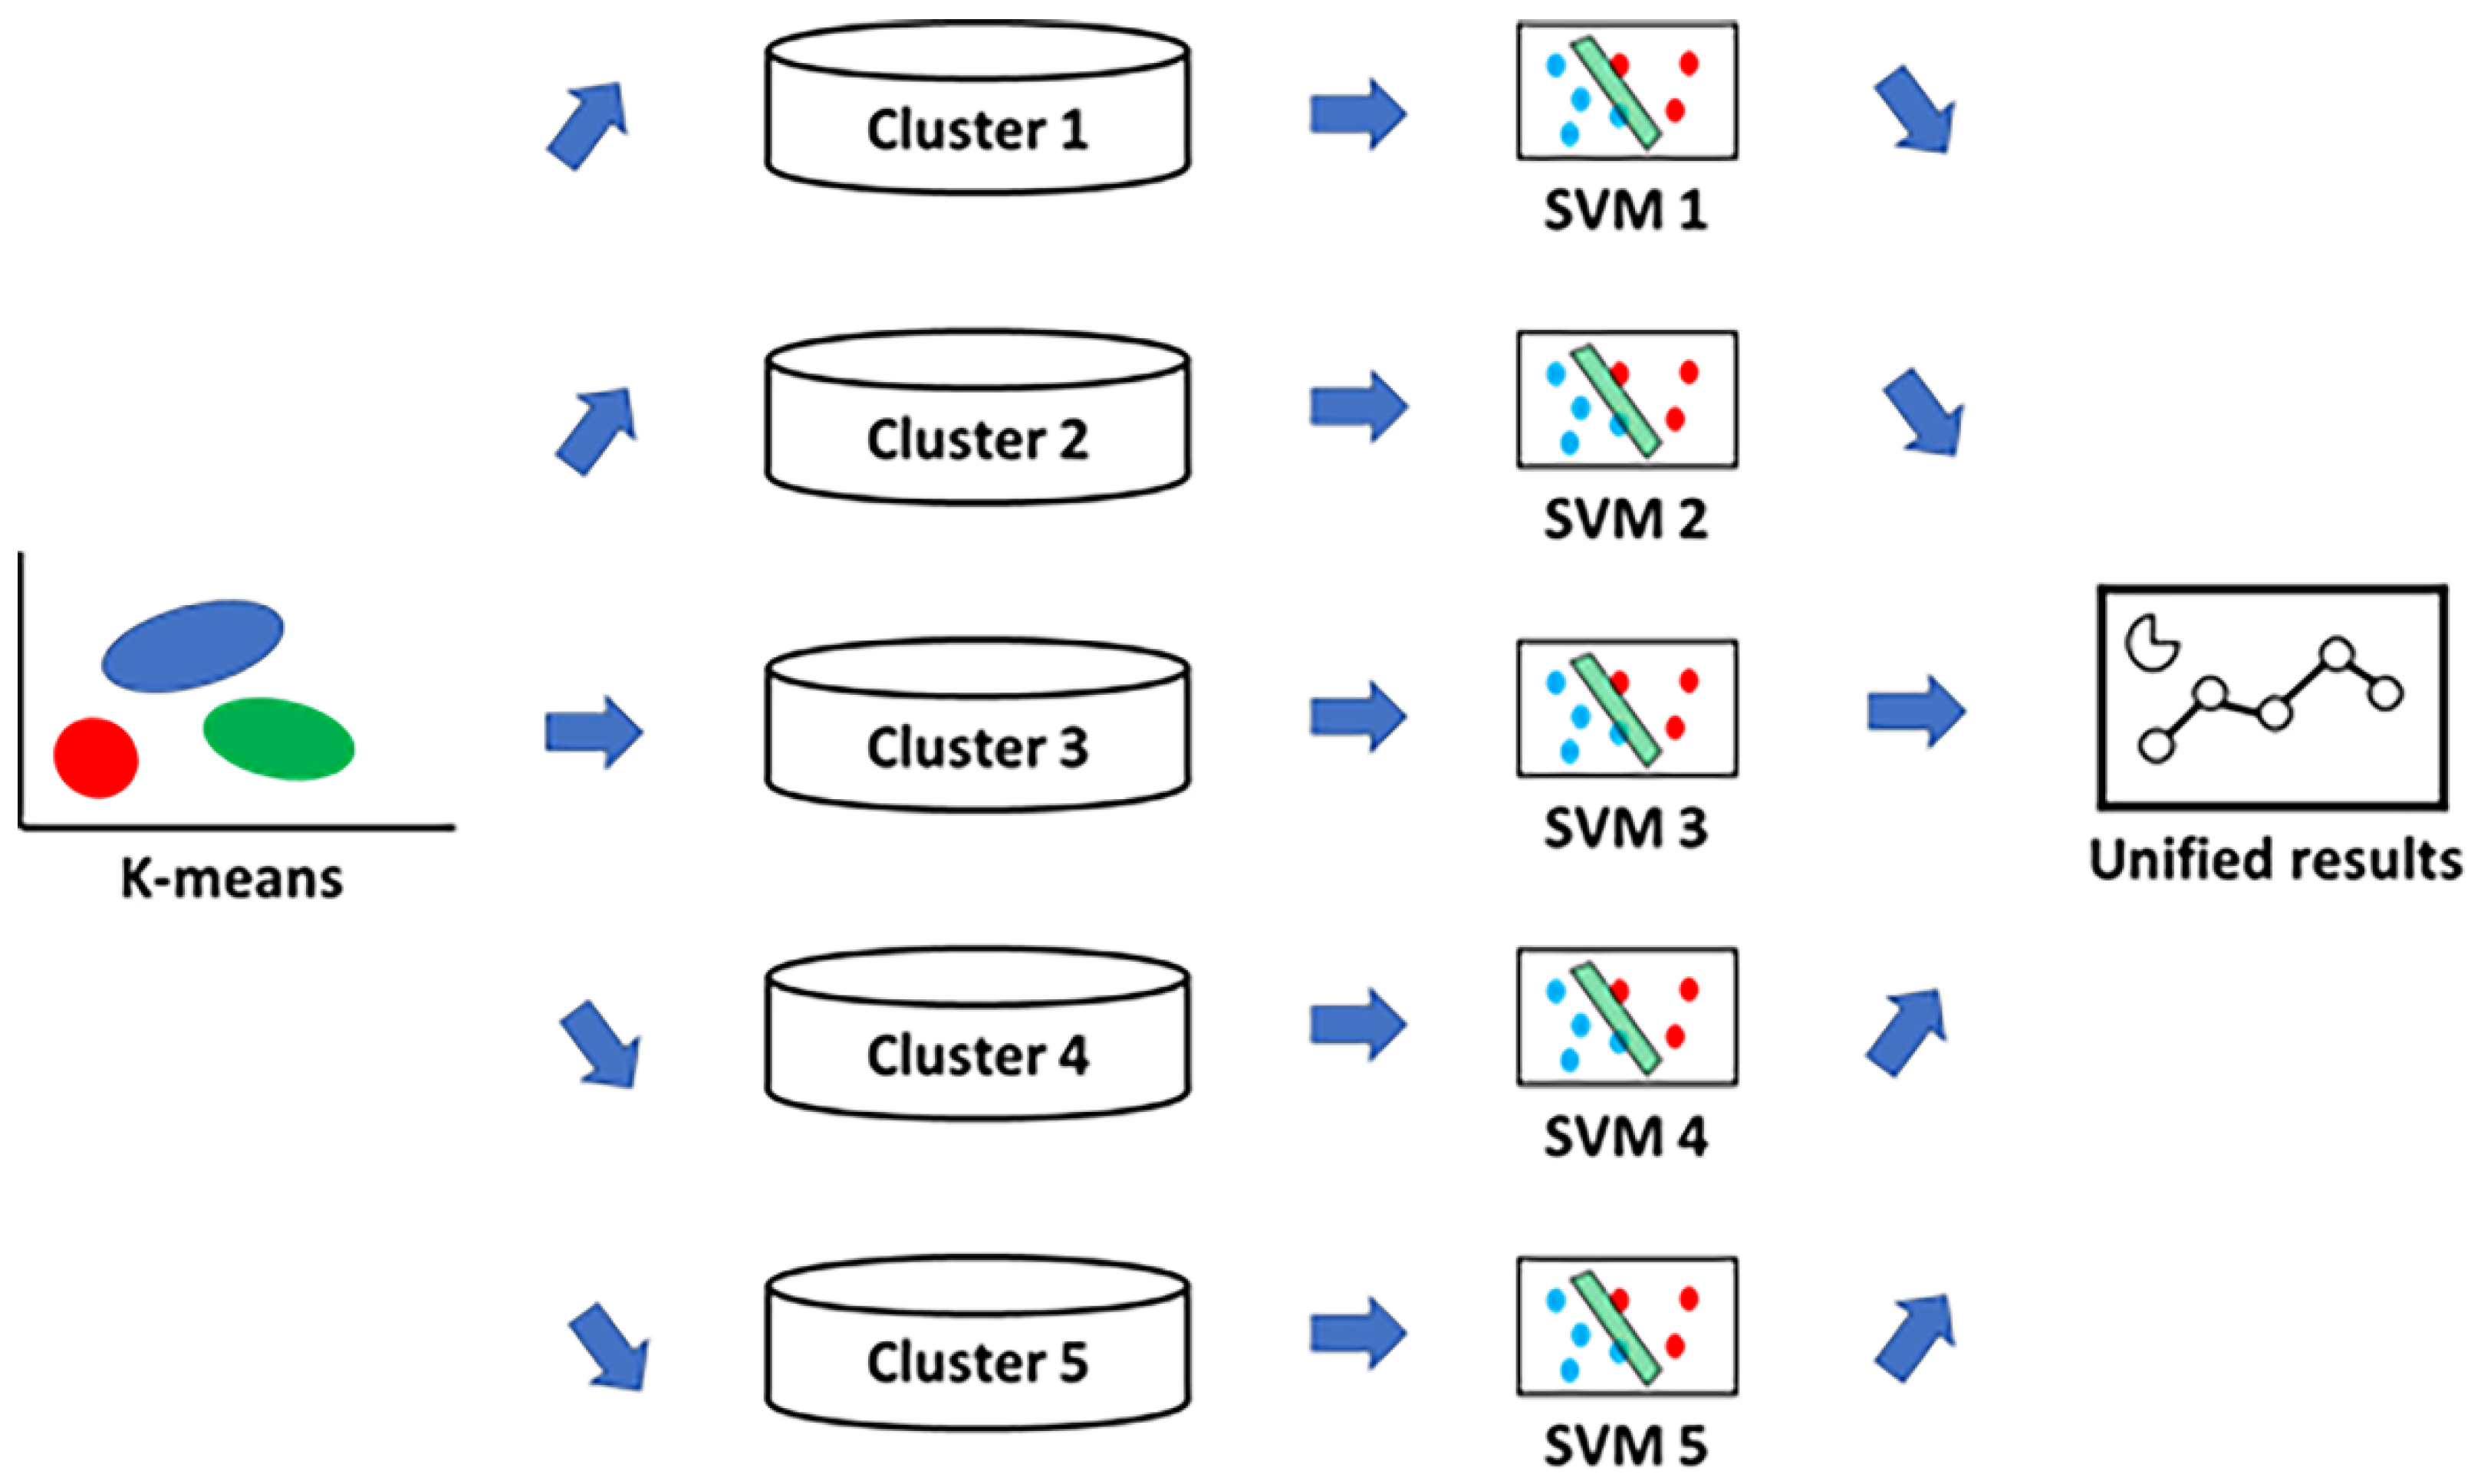
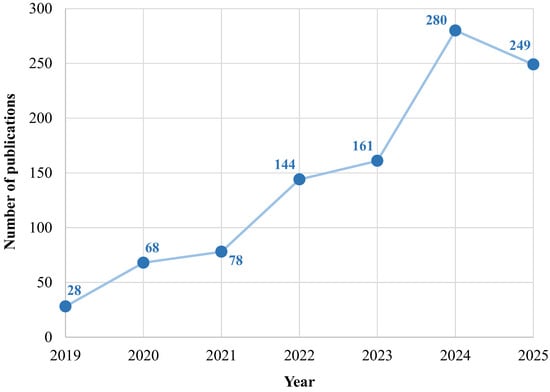

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).