


Abstract
There is limited information regarding caregiver and provider perspectives on uncertainty across the continuum of the neonatal intensive care unit (NICU) experience. Open-ended semi-structured interviews were conducted with providers and English- and Spanish-speaking caregivers of infants with a history of admission to a quaternary safety-net NICU. Major themes were generated using inductive–deductive thematic analysis. Seventy-six individuals participated in the study: 47 caregivers and 29 providers. The median gestational age of the infants was 29 weeks and 85% were classified as having chronic complex disease per the Pediatric Medical Complexity Algorithm. Most providers were neonatologists (37%) and nurses (27%) and more than half had over ten years of experience. A conceptual model of caregiver uncertainty was developed and key domains included drivers of uncertainty and its impact, and factors influencing coping and adaptation. Our analysis found a positive association between caregiver information gathering, clinical continuity, support systems, maternal mental health supports, and witnessing a child’s progress and the development of adjustment to chronic uncertainty. These results suggest key areas for intervention that can promote parental adaptation to the uncertainty inherent in the NICU experience.
1. Introduction
The experience of hospitalization in the neonatal intensive care unit (NICU) is a profoundly transformative and emotionally demanding journey, both for families and healthcare providers. A cross-sectional study highlighted that the NICU environment, with its abundance of monitors, mechanical ventilators, and constant visual and auditory alarms, creates an unfamiliar and challenging context for parents [1]. It poses unique challenges and emotional complexities, requiring families and providers to navigate a complex web of medical interventions, uncertainty, and emotional strain. Mothers of infants in need of specialized care commence their journey of parenthood in the foreign and often overwhelming setting of the NICU, which may result in delayed maternal attachment [2,3]. The delayed maternal attachment experienced by mothers of infants in the NICU can be attributed, in part, to the feeling of uncertainty that often engulfs parents in this challenging environment. NICU parents frequently express additional challenges, including a loss of control, conflicting emotions of hope and hopelessness, and feelings of guilt experienced by mothers who were unable to carry their pregnancy to full term [4].
As parents navigate the intricate and unpredictable journey of their infant’s medical care in NICU, they are frequently confronted with a profound sense of uncertainty. Uncertainty is defined as “the ability to determine the meaning of illness-related events and accurately anticipate or predict health outcomes” [5]. In a prospective study conducted to explore the relationship between feelings of uncertainty among parents of infants requiring NICU care and the increased risk of developing perinatal post-traumatic stress disorder (PPTSD), parents who screened positive for PPTSD 3 months after hospital discharge reported more uncertainty both while in the NICU and 3 months after hospital discharge [6]. In a study conducted to examine the roles of constructive and dysfunctional problem-solving strategies in the relationships between illness uncertainty and adjustment outcomes in caregivers of children newly diagnosed with cancer, greater dysfunctional problems-solving strategies were associated with higher levels of both uncertainty and poorer adjustment outcomes [7]. Provider uncertainty in the NICU is a prevalent aspect of the healthcare environment. Prognostic uncertainty emerged as a key factor associated with moral distress among neonatologists in a prospective qualitative study conducted to study moral distress among neonatologists working in a NICU [8]. By understanding the intricacies of uncertainty, researchers, healthcare providers, and support systems can develop tailored interventions, resources, and strategies to help individuals navigate uncertainty more effectively.
While there has been significant research on the patient and provider experience in the NICU, there are still some gaps in understanding and addressing the specific issue of uncertainty, which is a significant factor influencing their experiences and interactions in that setting. These gaps indicate a need for further research to delve deeper into the complexities of uncertainty in the NICU setting, including its causes, impact, and potential strategies for support and intervention. While studies have focused on uncertainty during the NICU stay, there is a lack of research exploring how uncertainty continues to affect parents and providers during the transition period and beyond. Additionally, the impact of uncertainty on communication and decision-making processes among healthcare providers in the NICU remains an area that requires further investigation [9]. The objectives of this study were to describe the role of uncertainty (1) during the NICU experience and during the transition-to-home period, (2) accessing community-based services, and (3) addressing mental health.
2. Materials and Methods
2.1. Research Team and Reflexivity
The authors that conducted the semi-structured interviews were S.B., M.H., C.M., and S.C. The interviews were supervised by the principal investigator, A.L. (a neonatologist). The research team had experience with qualitative research methods. The participants knew the occupation of the research staff and research objectives. The children’s diagnoses and medical history was known to both the participants and the research team.
2.2. Study Design and Framework
This was a qualitative study that was cross-sectional. We used an inductive–deductive thematic content analysis as our methodological framework to orient our study. We conceived a conceptual model based in Mishel’s Uncertainty in Illness Theory (UIT) [5].
2.3. Participant Selection and Setting
Purposive, typical case sampling was used to recruit caregiver and provider participants at a quaternary urban safety-net children’s hospital between 2019–2021. Caregivers who were >18 years of age or older and English- or Spanish-speaking, whose infants had gestational ages < 37 weeks or required neurodevelopmental intervention were recruited face-to-face or by telephone. To capture a varied range of experiences during transition from NICU to home, caregivers nearing discharge were recruited from the NICU and pediatric wards while caregivers up to 6 months post-NICU discharge were recruited from a high-risk infant clinic. This clinic provided multidisciplinary follow up for infants with gestational age < 32 completed weeks or birth weight < 1500 g or infants at risk for neurologic abnormality. Providers who worked with infants in the NICU, high-risk infant follow-up clinic, or general pediatrics were recruited face-to-face or by email. Study protocol was approved by CHLA Human Subjects Protection Program and all subjects gave informed written consent.
During the COVID-19 pandemic, caregiver recruitment pivoted to the inpatient setting, where caregivers who met inclusion criteria were approached face-to-face by the Principal Investigator (A.L.). In observance of COVID-19 safety measures, caregivers were given information and had the opportunity to ask questions about study participation by telephone and informed written consent was obtained using DocuSign by email and/or text. Provider recruitment experienced no change, but provider informed written consent was also received on DocuSign. We finished recruitment once thematic saturation was reached.
2.4. Development of Interview Guide
The development of the interview guide was informed by previous work [10]. After development of the interview guide, it was pilot tested and refined by key stakeholders (families, providers) prior to administration with study participants. Field notes were collected during all interviews.
2.5. Data Collection
The data collection involved two groups: providers and caregivers. The caregiver interviews were conducted over the telephone approximately three months after enrollment. The telephone call consisted of a 45 min interview. Providers were interviewed during a 15–20 min telephone call. The interviews were audio-recorded using a digital recorder and sent to the third-party service for transcription. The participants received a gift card for their participation in the study.
2.6. Data Analysis
The analysis included descriptive analyses and qualitative analyses. In terms of software, SAS v.9.4 was used for quantitative analyses while Dedoose Version 8.3.35 was used for qualitative analyses. The transcribed audio recordings were uploaded to Dedoose for managing, analyzing, and presenting qualitative and mixed-method research data (2020). Los Angeles, CA, USA: SocioCultural Research Consultants, LLC (www.dedoose.com, accessed on 1 February 2021) [11]. We used an inductive thematic-analysis approach; an iterative process of coding to identify the patterns between concepts. We created codes to help identify recurring themes among the many transcripts. The transcripts were divided between two coders and a third coder double-coded the transcripts to increase validity. We met weekly to discuss progress and adjust the codebook accordingly.
3. Results
3.1. Demographics
Participant characteristics are captured in Table 1 and Table 2. As shown in Table 1, there were a total of 47 caregiver participants. The median (IQR) gestational age was 29 weeks (26, 34). Most infants (85%) were categorized as having complex chronic disease (C-CD) using the Pediatric Medical Complexity Algorithm [12], with nearly half having sensory issues and global developmental delays, and 38% receiving early intervention. Regarding caregiver demographics, 70% of participants were insured by Medicaid/California Children’s Services, the majority categorized English as being their first language (89%), and 15% lived in a service planning area with a 4th-quartile economic hardship index. In terms of providers, most were physicians or nurses (22% attending neonatologists, 14% trainees, and 35% were nurses) and 69% had more than 5 years of work experience.
Table 1.
Infant and parent characteristics (n = 47).
Table 2.
Characteristics of participating providers (n = 29).
3.2. Conceptual Model
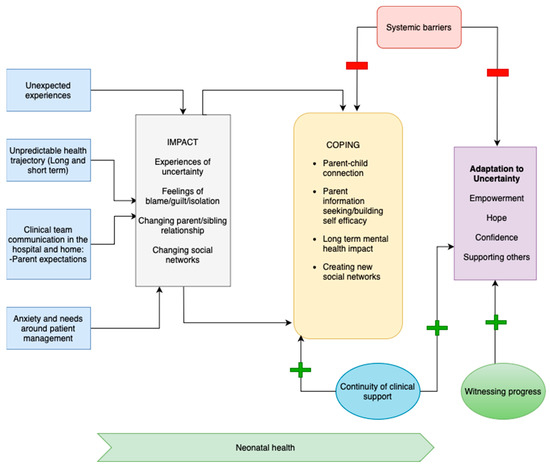
A conceptual model (Figure 1) was constructed to illustrate the process of parental uncertainty in the experience from NICU admission to the follow-up period. This model is based on Mishel’s Uncertainty in Illness Theory (UIT) [5]. In Mishel’s theory, the processing of uncertainty consists of five stages: antecedents to uncertainty, experience of uncertainty, appraisal/impact, coping, and adaptation. The model developed in this analysis adds additional themes of clinical continuity and structural barriers, which were found to impact parental coping and adaptation. The model also seeks to describe the caregiver experience across key timepoints: NICU hospitalization, discharge and transition home, and outpatient follow up. As described in Mishel’s Reconceptualization of the Uncertainty in Illness Theory, chronic uncertainty consists of ongoing processes of appraisal, coping, and adaptation leading to a new equilibrium over time [13]. Thus, this conceptual model should be viewed as an iterative process that builds upon prior parental experiences.
Figure 1.
Conceptual Model.
3.3. Domains/Themes
The following outlines the domains and themes that were captured.
3.4. Antecedents of Uncertainty and Experience of Uncertainty
The themes related to antecedents of uncertainty are captured in Table 3. Parents described experiences of initial disruption followed by feelings of unknown and worry at the time of transition to home. One parent described the feeling that “we were just thrown into these situations…”, emphasizing the unexpected nature of the NICU experience. The feeling of disruption related to the unexpected evolves into an experience of persistent worry in the setting of unknown health trajectories. As described by one caregiver, “It was the thing that scared me most of the time was the fact that we knew there was something with him, but we didn’t know exactly the long term … That was the scary part, like not knowing exactly what we were facing …”. This feeling was echoed by many caregivers, describing fear that their child may, “stop breathing on the way back home” and “always knowing in the back of your head like this could happen. So watching out for signs of that was the scariest part”.
Table 3.
Themes and illustrative quotations, antecedents of uncertainty.
This worry and uncertainty surrounding the transition home was often fueled by feelings of anxiety related to the management of complex medical needs and a sense that “once you get home, you’re by yourself”. Many caregivers described the stress of transitioning from a space of constant support to one where “you’re doing the job of the respiratory therapist, two nurses, the everything. And you have to really know your baby and be able to recognize signs if something’s wrong”.
The unpredictable health trajectory led to a description of persistent uncertainty, often punctuated by disruptive interactions with the health care system. “Sometimes I feel like my world will stop, like when he gets even admitted to [the hospital], from this day, it was like my day, my life is just on hold until he actually gets better within time. Oftentimes I feel like he’s not gonna get better when he gets older because everything that he’s diagnosis is a little more chronic. So I can’t seem to get over that he might be better with the time or he might not”. The initial NICU hospitalization acts as an antecedent for uncertainty, which evolves into a chronic state of unknowing as children continue to grow and their health trajectory evolves.
Provider interviews also emphasized the experience of caregiver uncertainty in the NICU and the need to explicitly address this uncertainty as a means to support caregivers. One provider stated “I think the despair that people can feel about, ‘My baby is really sick. I don’t know what will happen. There’s so much uncertainty’. I think addressing that uncertainty is something that could be done more specifically, to help us take care of the family too”. Another provider echoed this sentiment, describing the importance of the “normalization of the things that parents experience, like the significant rollercoaster and constant uncertainty” as well as having, “something to address that might be helpful as an adjunctive to things like family meetings and social support from the social worker in the unit or something”.
The experience of caregiver uncertainty was impacted by team communication and expectation setting. Caregivers emphasized the importance of honesty in provider communication: “If they didn’t know at the time, they were also honest about that… We rather people tell us they don’t know than for them to tell us something, and then later on not be true…”. One caregiver described coming to a realization of “how much art there is in medicine. I thought it was a lot more science. It was really interesting and eye-opening that we can have dialogue and have discussion about what was going on and what their thought was, and to know that certain things they didn’t know the answer for, it was kind of trial and error”.
Caregiver uncertainty was worsened when the medical team’s communication and expectations eroded parental agency. One caregiver described a feeling that the team saw their baby as “a number” and that this “led to quite a few instances of stress, where they would decide to do something that isn’t something we discussed. …. And then I would show up and they would be like well we want to do this and this. And I’m like no, we’ve already talked about it, I don’t understand why I’m having to like say this again. Those things were very frustrating”. Some caregivers also described limited expectations for parental involvement in cares, stating that “we weren’t allowed to do a whole lot. … When we were finally able to go home, I didn’t know what to do because I was never allowed to do anything”. This also caused distress in transition to a step-down unit prior to discharge home. In a new unit, caregivers were faced with shifting expectations: “we’ve never done this before, so we will need a little instruction now, and figuring out the expectations, in the NICU, where there are things you’re not allowed to do versus upstairs where there are things there that you’re required to do”.
Providers also emphasized the importance of caregivers as decision makers. A provider recognized that “The parents [are] the best historian. They know something that’s changed in their child that isn’t necessarily noted in the doctor’s note. …. The parents have a unique perspective on their child’s well-being that, as medical providers, sometimes we’re just not in tune with”. Providers also described the challenging feeling that can come when the communication regarding an infant’s health trajectory is constantly in flux. The lack of explicitly addressing uncertainty can result in feelings of frustration. “‘Yesterday you said that it was fine. And now today, you’re saying it’s not fine. And that doesn’t make sense’. And parents feel like things are going up and down all the time, it’s like, ‘Well, this can’t be the way that this is supposed to be’”.
3.5. Impact
Caregivers described feelings of guilt, blame, and isolation in response to the uncertainty fostered by the NICU experience, as outlined in Table 4.
Table 4.
Themes and illustrative quotations, impact of uncertainty.
“They used to tell me he was doing good, he was a healthy baby, but I was just blocked in that part… I started blaming myself, probably I put him through this for waiting this long to have a vaginal [delivery]… Then the doctors keep explaining it’s not your fault… So I was just blaming myself for everything that was going on, that I wouldn’t let nobody tell me this is correct, this is the right thing”.
“I just felt very disappointed in myself. I just felt like I couldn’t do anything well, and I couldn’t do anything right, and that I wasn’t the mother who I imagined myself to be, and I just wasn’t the partner, I was failing at everything”.
“I couldn’t concentrate at work, but work was kind of the only thing that I was still able to do okay at, because I didn’t talk about anything there. So nobody even knew what was going on. And not having maternity leave, like I was pregnant, and then I wasn’t, but nobody knew. And it was just very weird, and I just kind of isolated myself”.
The isolation felt by caregivers was reflected in descriptions of altered social networks and a shift stemming from an unexpected and uncertain event. Many described a feeling that people didn’t know how to support them. One parent reflected that, “I think when you lose a child, there is nobody that you can, like, I don’t know. It just was very isolating… And people don’t know how to talk to you and nobody really knows how to support you”. The lack of support from social networks continued into the post-NICU experience, exacerbated by the uncertainty related to the COVID-19 pandemic and a child’s ongoing medical needs.
Provider perspectives on social networks differed slightly from those of caregivers. Multiple providers described the overwhelming number of requests that parents received for updates on the child’s status and suggested tools for addressing this: “So one of the things that I always suggest is to have an outgoing message, basically updating people, giving the information that you are comfortable giving for an update”. Many providers also commented on navigating the impact that the NICU stay might have on older siblings. One provider stated “… quality is more important than quantity. In other words, spending time with each child individually and talking, letting them talk about themselves, not necessarily about the baby, unless they want to talk about. You know but really focused attention, even if it’s for short periods of time it can do wonders”.
3.6. Systemic Barriers
As summarized in Table 5, caregivers raised multiple systemic barriers that impaired their ability to cope and adapt to uncertainty. One described that they “had the biggest issue trying to get her prescriptions because of the insurance”, due to prior authorization needs, and that “it was just a whole complicated mess that upset me ‘cause that was a waste of time, twice”. Others expressed difficulties getting scheduled for follow-up appointments: “Scheduling is the hardest thing, because I know that everything is so backed up all the time. The high-risk infant clinic took us months and months to get in. … And then just the referrals for insurance, it takes a while”. Another reported that, “The most challenging thing was transportation, driving to LA”.
Table 5.
Themes and illustrative quotations, barriers, continuity of care.
3.7. Continuity of Clinical Care
The continuity of clinical care, both inpatient and outpatient, emerged as an important theme impacting parental coping and adaptation, as reviewed in Table 5. Many caregivers emphasized the value of continuity within the inpatient clinical care team, particularly that of primary nursing. They expressed that this provided support, learning opportunities, and a sense of comfort with the NICU process.
“I actually had primary nurses, and I think that that was really helpful because they really got to know [child M.] and I really got to know them. … having that consistency, I think was really beneficial for myself and for the baby. And probably for the staff too, because they felt comfortable and they knew her. If she’s having an off day, or something, because they were able to pick up on those things, it meant that I was going to be able to, too. So, me being consistently with her, I was gonna learn stuff about her and that would help make everything more smooth”.
Parents also voiced frustration with provider turnover, stating that “having a new resident every time was very frustrating, because it was like you don’t know my baby. And if you’re making these decisions, I’d appreciate that we have a conversation about this, so I can catch you up”.
The value of clinical continuity continued into the outpatient space where many children required multiple sub-specialty appointments and connections with developmental services. One parent reflected that, “There’s a lot of appointments and a great team of folks that talk to each other. When I go from one appointment to the other, they already know what one or the other has been talking about, [which] has been very helpful…. It makes me confident [in] the work that they’re doing, and it keeps me at ease knowing that he’s in good hands”.
The transition from the NICU to home stood out as a period in which clinical continuity greatly impacted parental feelings of uncertainty. Many parents felt that having access to a provider for questions would be a helpful resource. One parent stated that it would be helpful to have “a number that you could call somebody 24 h a day. Because like my pediatrician, he’s only available weekdays Monday through Friday” to avoid having to take their child to urgent care and be exposed to sick children. Another reflected on the potential benefit of “having the resource to reach out to nurses or physicians that would get back to you quickly, and for nonurgent things. How do I make sure this dressing is correctly applied? Things like that. Cause if you reach out to your doctor, you know that could take several days for them to get back to you”. Multiple caregivers commented on the value of being connected to developmental services prior to discharge: “I think it’s very important. For the NICU to make that first contact with the regional center for us was really important, cause it’s hard to do that”.
Many providers also commented on the value of care coordination and check-ins to support families in the transition from the NICU to home.
3.8. Coping
Parent empowerment and self-efficacy through active information gathering was a consistent theme that emerged within the domain of coping with uncertainty (Table 6). Within the NICU, parents emphasized the importance of engaging the clinical team (nurses, NPs, and doctors) through question asking: “I asked a lot of questions the whole time that he was in the hospital. Honestly, that’s where I got the bulk of my information”. Parents felt most supported by clinical teams that expressed an openness to providing information: “All of the people that were there were really supportive and very engaged in ensuring our success and providing a lot of support, not just with resources, but also with the openness saying you have any questions, please feel free to ask them. And when we asked, they were answered”. Additionally, parents described the importance of hands-on learning related to infant care (e.g., bathing, feeding) and more complex medical skills (e.g., Gtube management, providing medication) to their management of uncertainty prior to discharge. A parent stated: “Two weeks before I left the hospital they let me do it by myself. They just went and watched me and [brought] me medicine. That was helpful because when I’m [here] at home, nobody else [is] watching me so I got to learn how to do it”. The importance of active engagement in parental learning continues into the outpatient experience. “Even coming home, I still have the support because even when I go to his appointments, I can always ask these questions over and over again, and they’ll always answer these questions for me in a way that I understand and give me all the information I need”.
Table 6.
Themes and illustrative quotations, coping, witnessing progress, and adaptation.
Provider perspectives also emphasized the importance of parent engagement. A nurse reflected on barriers to parental engagement in information gathering: “Being a bedside nurse, I would hear it from the doctor, what they said. And you can see them nodding and nodding. And then, afterwards when they leave, and I’ll say, ‘So did you understand what the doctor said?’ They’re like, ‘I think, but I had a question’. I was like, ‘Oh, my gosh. Why didn’t you say anything’, because they feel they’re just bombarding the doctors, and like their time isn’t worth it”. One provider suggested caregiver access to videos of more complex medical procedures to improve confidence at home.
Parent mental health challenges, specifically those of mothers, emerged as an ongoing process that manifests in response to the emotional impacts of uncertainty. One mother reflected on the ongoing nature of her coping process—“I am a work in progress”. Another emphasized that “It doesn’t just go away. … It’s a much longer trajectory I think you’re dealing with things, and they manifest in different ways”. Mothers also emphasized the importance of recognizing mental health needs and the value of support from the clinical team (social workers, psychologists, nursing, etc.) and family: “I do think that having more specialized care and understanding maternal mental health is something that is just a huge gap, and I think that it’s really important that we do a better job with that. … And I think that we really need to look at it as if it goes untreated, you’re dealing with that forever until it is treated”. Multiple mothers described feeling like their mental health struggle “wasn’t acknowledged and it wasn’t met with any services”. While some mothers felt a “peace of mind” and that they were “in a better place now” after speaking with a mental specialist, others expressed that they, “didn’t feel supported through the follow-up appointments. I didn’t feel supported from the hospital necessarily. …‘cause what I’m dealing with, and still dealing with, is some maternal mental health issues, and PTSD”.
Providers also acknowledged the importance of ongoing maternal mental health supports, emphasizing the value of inpatient screening and connection to services and that they “hope they [the supports] continue that once they leave the hospital. I don’t know how much follow-up [there is] afterwards”. Many providers also brought up the need for parents to engage in self-care. One provider stated “Conveying to parents that you, at some point you need to take care of yourself alone because you should be healthy and maybe you have other kids and just to get through this you need to be healthy and strong. But it’s also important because it does impact the child”. This was occasionally reflected in caregiver perspectives regarding their coping process. One stated, “I had that constant update and reminder all the time from all the nurses, like take some time for yourself. And I appreciated that”.
Caregivers emphasized experiences that enabled them to bond with their infants as key components to help cope with the NICU experience.
“One really helpful component for us was music therapy. We’re both really musical and we couldn’t hold him for the first month and that [14] hard. I think we kind of built that bond through music …We had so many people looking after the medical side of things, but that really helped us build that connection to him when we couldn’t especially when we couldn’t cuddle him… So I think that really helped us like learn how to connect with him”.
Other parents touched on the value of books to read to their infant and ways to promote parent–infant bonding while in the intense medical space of the NICU.
Social support from multiple sources—family, friends, social media, other NICU families, and religion—was an essential factor for caregiver coping. Beneficial support from family and friends often came in the form of practical support such as GoFundMe campaigns, childcare for older siblings, and providing meals. A caregiver expressed gratitude for the financial support organized by a friend through a GoFundMe while their household was limited to one income. “People banded together and helped our family in that way. That really helped us to be able to cover rent”. Many also referenced the support from friends and parents who could care for older children at home and make meals for the family. One parent described how her friend, “just came in and didn’t need anything from us, and made us food, and bought us dinner… She helped streamline things and just made things really easy while we were going to the NICU”. Another commented on the value of support from her mother, commenting, “it’s hard enough with one medically complex kid. Then adding a three year old at the time just made it a little bit more crazy. She decided to stay with us until we got our feet up from under us”.
The support of caregivers with similar experiences provided an important community for the caregivers interviewed. They expressed the value of receiving support from people with similar experiences, a comfort in finding community, and a sense of reassurance regarding their child’s situation. One parent described the difference between support from the clinical team and from other parents: “It’s parents with experience. They’re going through the same thing that happened with you, not a professional who’s only dealt with it by reading… they know what they know, and they’ve put their time into knowing and trying to help others. But I guess it’s different having the knowledge, and having lived experience”.
Providers echoed the importance of connecting caregivers with a community of support from those with current or prior NICU experience. One reflected on how “The NICU’s really overwhelming”, and that often, “most of the parents sometimes feel like they’re very alone in the NICU and they don’t have anybody to talk to, especially if they don’t have support within their family”, and that “if they’re going through something specifically and then you find somebody else that is going through that as well, I feel like you, the parent might potentially feel that they can talk to somebody…so I think [that is] very useful”. Many recommended creating programs and structures that facilitated connections with prior NICU parents, as well as ways to foster community amongst parents within the NICU.
3.9. Adaptation
Despite ongoing challenges, many parents expressed finding a new equilibrium and acceptance of uncertainty in adaptation (Table 6). One parent reported that, “I think my comfort level with caring for him, and seeing his growth, and just his personality come through, like seeing him grow. Besides the oxygen and the G-tube that he’s connected to, and having to go to so many doctor’s appointments, he is a regular baby”. Many other parents echoed these feelings of increased confidence in both their abilities as caregivers but also in their child’s ability to make progress: “I just was feeling very confident that when she came home, that she would thrive, like being home is what she needed to do”. The value of witnessing their child’s progress and the hope and joy that this created emerged as a theme within the domain of adaptation. One parent described the progress their child made with oral feeding: “Now he can eat, and he still doesn’t eat a lot. But the fact that he can eat and not choke is amazing. Just keep loving on that baby, he’ll surprise you”. This experience was echoed by many parents who witnessed progress in their child’s ability to feed and the joy in seeing that progress.
Caregivers reflected on the value of being able to support other parents and finding a sense of empowerment and purpose through this connection. One mother reported that connecting with a support group helped her recognize that, “we’re all kind of dealing with these traumas, and what does that mean, and it gives me something to focus on. I don’t feel hopeless, because I feel like there are things that we can do to change these systems and make sure that this isn’t the way that people are left feeling”.
Providers also commented on the value of witnessing progress. One reflected that, “I think sometimes we focus a lot on all the medical problems that the baby has and kind of lose sight, and I think the providers are guilty of this too, lose sight of the developmental progress that the baby should be making at any given age, and how to support the baby as best we can”.
4. Discussion
This study is among the first to assess the evolution of parental uncertainty from the NICU stay through follow-up care in the outpatient setting. Our analysis aligns with prior work that established parental uncertainty in illness as a key theme throughout the inpatient NICU experience [15,16]. Our study also incorporates provider perspectives on parental experience of uncertainty, which offers additional opportunities to consider how to address the parent experience at a unit and system-wide level. We built upon Mishel’s Reconstitution of Uncertainty in Illness Theory to establish a conceptual model that tracks the initial experience of uncertainty as it evolves through the phases of impact, coping, and adaptation. In her reconstitution of uncertainty in illness, Mishel describes a process by which parents establish a new equilibrium that accepts and adapts to uncertainty [13]. Our data reflect this theory, demonstrating that the cycle from uncertainty to adaptation is iterative as parents face new challenges (e.g., transition to home, new illnesses, etc.) and adapt to a new equilibrium. For many parents, this process resulted in a positive adaptation to chronic uncertainty, in which they described feelings of confidence and hope. However, for others, a lack of positive coping mechanisms led to an ongoing sense of worry and fear that fueled persistent trauma and anxiety. This reflects prior findings by Malin et al., which demonstrated that ongoing negative associations with uncertainty are strongly associated with higher levels of PTSD and anxiety [6]. Given that chronic uncertainty is unavoidable in the setting of complex illness, the data from this study provide insights into ways that the healthcare system can support a positive adaptation and adjustment. Below we map out the findings within the conceptual model over its iterations to identify key areas for intervention.
The nature of uncertainty experienced by families evolved over the course of the NICU hospitalization, the transition to home, and into the outpatient setting. Initial descriptions featured elements of shock and significant prognostic uncertainty. As families transitioned to home, we saw that parents described their experience of uncertainty with words such as “worry”, “alone” and “scary”, reflecting both an ongoing evolution in the child’s health trajectory as well as a significant shift in the amount of immediate support and monitoring available. These feelings sometimes continued in the form of hypervigilance to the infant’s behaviors, while for others there seemed to be an acceptance of uncertainty and focus on the infant’s progress. An analysis of uncertainty during the NICU stay by Krick et al. found that parental uncertainty shifted from feelings of initial shock to what they describe as a “Gray Daze” and finally into “Looking Forward”, a progression which they summarize as a shift in a view of uncertainty as changing, “from something to be feared to something that was accepted and integrated into their view of the future” [15]. We found similar results in our study—demonstrating that the experience of uncertainty can vary across situations and in response to prior experience.
While the experience of uncertainty varies, our analysis makes it clear that uncertainty is unavoidable in the setting of a NICU stay and its sequalae. Providers commented on the importance of openly discussing uncertainty with families and supporting families in the management of ongoing prognostic uncertainty. When providers engaged in open communication regarding clinical uncertainty, families reported a greater acceptance of uncertainty and an ability to move forward. This mirrors the results from an analysis of surrogate decision makers’ preferences in communication regarding a patient’s critical illness, which found a strong preference for an explicit acknowledgement of prognostic uncertainty and that this built trust in the clinical team [17]. Explicit discussions of uncertainty present an opportunity to normalize challenges of the NICU experience and to build connections with caregivers.
The uncertainty that surrounds the NICU experience had a significant impact on parents’ emotional well-being and their relationships with others. Prior research suggests that a major disruption in the parental role and meaning system occurs as a sequalae of the NICU admission [18]. Parents proceed through pregnancy with certain expectations for what parenting will entail, a vision which becomes dramatically disrupted by the NICU experience [18]. This disruption results in feelings of self-blame, guilt, and isolation as parents struggle to comprehend the origins of their current situation. The significant deviation from the expected postnatal experience also impacts the parental social network. Parents described challenges interacting with their prior social networks when the supporting individuals struggled to process the events themselves. Parents also commented on the challenge of caring for and supporting the infant’s older siblings. Many providers noted that siblings may also have feelings of guilt and isolation, and the importance of incorporating them into the NICU experience.
A deviation from the expected parental role continued into the period of transition from the NICU to home. Specifically, the expectation for parental involvement in their child’s care shifted dramatically, from a situation in which the majority of the care and monitoring was performed by clinical providers to the majority being performed by parents. Many caregivers described this transition as scary and emphasized the feeling of being alone. The feeling of worry was exacerbated by a new feeling of ambiguity as to what types of behaviors or changes in their child signified a clinical concern as opposed to an expected change. As suggested by White et al. in their analysis of uncertainty in the transition period, parents would benefit from greater support and explicit planning around uncertainty to minimize the emotional impact from this significant transition [19].
As described in Mishel’s Uncertainty in Illness Theory, impact is followed by a process of appraisal and coping [5]. Parents appraise the uncertainty as a danger or opportunity, and subsequently adopt respective coping mechanisms. Coping ultimately leads to an adaptive or maladaptive state, hinging upon the parental appraisal of uncertainty. As previously discussed, this process often reoccurs over time, as parents constantly reappraise their situation and modify their coping approach. Uncertainty that may have initially been perceived as dangerous can evolve into a scenario of hopefulness and optimism. In our analysis, we saw that coping mechanisms and the factors that influence coping often support this shift. Although uncertainty initially led to feelings of guilt and isolation, over time parental engagement, social support networks, mental health supports, witnessing progress, and clinical continuity promoted feelings of hope, confidence, and self-efficacy among many parents.
In this analysis, we approached parental coping using the social ecological model as a conceptual framework. The social ecological model describes individual behaviors within graduated levels of social and environmental contexts with which the individual interacts. The model has been applied to describe caregiver adaptation to childhood developmental delay and childhood cancer [20]. In this adaptation, we considered five levels: the individual (parent), interpersonal relationships (parent–child, family, etc.), neonatal ICU Community (NICU provider teams and processes), health system (Inpatient and outpatient, insurance, community programs), and public policy.
At the individual level, key coping practices involved information gathering and mental wellbeing. Many parents described an active information-gathering process through asking questions and participating in their child’s care. For many, this approach to knowledge acquisition continued into the outpatient setting as well. Approaching uncertainty through an active engagement in learning fostered confidence despite ongoing complex medical needs at home. Importantly, this learning was supported by the NICU community, which provided parents with opportunities to engage in care and in medical discussions.
The interpersonal level featured key relationships between the parent and child as well as the parent and their social networks. Parents reported witnessing progress in their child as a key factor promoting parental adaptation to child illness. In an analysis of experiences of caregivers of children with Trisomy 21, Truitt et al. found that hope was the most significant factor predicting adaptation with perceived uncertainty as a separate independent predictor [21]. In our study, parental ability to bond with their child and bear witness to positive growth both fostered hope and mediated the impact of perceived uncertainty.
Support from social networks also assisted with adaptation to uncertainty. Financial and practical supports from the parental social network allowed parents to focus their energy on coping as opposed to worry related to financial stressors and childcare. Parents also described important relationships with other NICU families and parents with prior NICU experience. These relationships occurred in person, over social media, and through other connections. For many parents, hearing the experience of others who had been down this path provided reassurance in the face of uncertainty and promoted positive coping behaviors.
The practices and policies at the NICU level impacted parental coping and interacted with all levels of the ecological model. As described above, family-centered communication that empowered families to ask questions and engage with the medical team supported parent confidence and knowledge building. Additionally, primary nursing as a unit policy promoted clinical continuity and decreased parental stress through building trust with clinical providers. Direct and hands-on teaching prior to discharge, as well as establishing connections between parents and outpatient resources (e.g., early intervention and the local school district) enabled parents to feel better prepared for the transition to home. Screening for and addressing mental health needs at the unit level assisted in connecting families with resources, although often failed to meet ongoing needs.
At a greater health systems level, the clinical coordination of care and systemic barriers impacted parental coping and adaptation. Both providers and parents commented on the importance of care coordination within the outpatient setting, both between the subspecialty and primary clinics but also between parents and different providers of medical equipment and other medical needs. Parents expressed appreciation for individuals who helped them navigate the complex landscape of durable medical equipment and insurance. Others reported appreciation for programs such as Early Intervention, which helped them gain tools to support their child’s development. Parents also reported many challenges at the health system level. Some described difficulties obtaining timely appointments and medications, and many expressed a desire for a provider who could assist with medical concerns over the phone. A lack of ongoing mental health support also impacted parents who described difficulties managing their child’s care while also struggling with symptoms of PTSD.
This study is one of the first in the literature to describe uncertainty in the NICU experience across the continuum from admission to the outpatient experience, and is the first to incorporate provider perspectives. The study is also one of the only such papers to focus on a primarily low-income population. Despite these strengths, the study has several limitations. Our study population was recruited from a single center with a focus primarily on those patients receiving Medicaid, potentially limiting the generalizability of our results. Those with private insurance may have differing access to services and reimbursed costs. Recruitment efforts focused on low-income non-Hispanic Black and Hispanic caregivers, which may have resulted in perspectives more specific to the lived experiences of the individuals in these groups. However, given that many prior studies on parental uncertainty have tended to sample White-identifying caregivers, the predominant non-Hispanic Black and Hispanic population adds to the breadth of the current literature. Moreover, the clinical conditions of the infants and the parents perspectives were heterogeneous, which may have impacted the study results although we sought to represent diverse experiences. Lastly, given the retrospective nature of the study, the results are vulnerable to recall bias.
Recommendations for intervention.
Based on the findings described in the previous sections, we make the following recommendations to support parents through the NICU experience.
Individual:
Family-centered communication: encouraging parents to join rounds, providing space for parents to ask questions, explicitly discussing prognostic uncertainty with families;
Provide tangible resources to promote ongoing parental learning: videos of how to manage medical equipment, classes related to infant care and clinical management prior to discharge.
Interpersonal:
Provide parents with tools to track developmental and medical progress;
Create parent support groups and gatherings within the NICU;
Develop a role of Parent Navigator—someone who has prior NICU experience that can meet with parents in the NICU;
Provide parents with connections to larger support groups via social media.
NICU Policies and Processes:
Develop structures that promote primary nursing for long-term admissions;
Ensure mental health screening of all primary caregivers and connect to resources;
Hire adequate mental health support professionals to support parent needs;
Connect families with outpatient developmental programs prior to discharge to limit parental burden;
Ensure that prior authorizations are completed and all equipment is ready at the time of discharge.
Health System:
Establish a Transition-of-Care Navigator who assists parents in obtaining contact information for clinics, assists with coordination of appointments, and performs a check-in call one and two weeks following discharge;
Enable medical record sharing between Electronic Medical Record systems to ensure communication between teams;
Establish mental health support programs for NICU parents in the outpatient setting.
Public Policy:
Ensure funding for outpatient mental health support for NICU parents;
Establish clinical coordinators within Medicaid and CCS to assist with care coordination;
Increase funding for outpatient developmental support programs such as a Regional Center to ensure access;
Reimburse clinicians for telemedicine visits and care coordination work.
5. Conclusions
In this study, we developed a unique conceptual model of parental uncertainty in the NICU experience that draws upon prior theories in the field to illustrate the complex and evolving nature of parental uncertainty in the face of neonatal medical complexity. Through the unique use of parent and provider perspectives, we identified several ideas to support parental coping and adaptation from the individual to policy level. Uncertainty is an unavoidable and ongoing component of the NICU experience; however, improved care coordination, parental empowerment, and increased mental health services may promote positive coping and adaption among parents.
Author Contributions
The following paragraph summarizes the author contributions. Conceptualization, A.L., K.G.G. and M.K.; methodology, A.L., K.G.G., S.B., M.H., C.M., S.C. and M.K.; software, A.L., S.C., S.B., M.H. and C.M.; validation, A.L. and S.C.; formal analysis, A.L., S.C., M.H. and S.B.; investigation, A.L., S.C., S.B., M.H. and C.M.; resources, M.K. and A.L.; data curation, S.C., C.M., M.H. and S.B.; writing—original draft preparation, K.G.G., T.K. and A.L.; writing—review and editing, M.K., S.C., C.M., M.H. and S.B.; visualization, A.L. and T.K.; supervision, A.L.; project administration, S.C.; funding acquisition, M.K. and A.L. All authors have read and agreed to the published version of the manuscript.
Funding
This study was supported by the Zumberge Diversity and Inclusion Award, the Sharon D. Lund Foundation and by grant KL2TR001854 from the National Center for Advancing Translational Science (NCATS) of the U.S. National Institutes of Health. The content is solely the responsibility of the authors and does not necessarily represent the official views of the National Institutes of Health. The funder/sponsor did not participate in the work.
Institutional Review Board Statement
The study was conducted according to the guidelines of the Declaration of Helsinki, and approved by the Institutional Review Board of Children’s Hospital Los Angeles (protocol code CHLA-16-00413, approved 28 September 2016).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The data presented in this study are available on request from the corresponding author.
Acknowledgments
We would like to acknowledge the families and providers who participated in this study.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Bolivar Montes, L.A.; Montalvo Prieto, A. Uncertainty Associated to Parents of Preterm Infants Hospitalized in Neonatal Intensive Care Units. Investig. Educ. Enferm. 2016, 34, 360–367. [Google Scholar] [CrossRef] [Scilit]
- Heermann, J.A.; Wilson, M.E.; Wilhelm, P.A. Mothers in the NICU: Outsider to partner. Pediatr. Nurs. 2005, 31, 176–181, 200. [Google Scholar] [PubMed]
- Shin, H.; White-Traut, R. The conceptual structure of transition to motherhood in the neonatal intensive care unit. J. Adv. Nurs. 2007, 58, 90–98. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bry, A.; Wigert, H. Psychosocial support for parents of extremely preterm infants in neonatal intensive care: A qualitative interview study. BMC Psychol. 2019, 7, 76. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mishel, M.H. Uncertainty in illness. Image J. Nurs. Sch. 1988, 20, 225–232. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malin, K.J.; Johnson, T.S.; Brown, R.L.; Leuthner, J.; Malnory, M.; White-Traut, R.; Rholl, E.; Lagatta, J. Uncertainty and perinatal post-traumatic stress disorder in the neonatal intensive care unit. Res. Nurs. Health 2022, 45, 717–732. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basile, N.L.; Chardon, M.L.; Peugh, J.; Edwards, C.S.; Szulczewski, L.; Morrison, C.F.; Nagarajan, R.; El-Sheikh, A.; Chaney, J.M.; Pai, A.L.H.; et al. Relationship Between Caregiver Uncertainty, Problem-Solving, and Psychological Adjustment in Pediatric Cancer. J. Pediatr. Psychol. 2021, 46, 1258–1266. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Deligianni, M.; Voultsos, P.; Tzitiridou-Chatzopoulou, M.K.; Drosou-Agakidou, V.; Tarlatzis, V. Moral distress among neonatologists working in neonatal intensive care units in Greece: A qualitative study. BMC Pediatr. 2023, 23, 114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Obeidat, H.M.; Bond, E.A.; Callister, L.C. The parental experience of having an infant in the newborn intensive care unit. J. Perinat. Educ. 2009, 18, 23–29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lakshmanan, A.; Sunshine, I.; Escobar, C.M.; Kipke, M.; Vanderbilt, D.; Friedlich, P.S.; Mirzaian, C.B. Connecting to Early Intervention Services After Neonatal Intensive Care Unit Discharge in a Medicaid Sample. Acad. Pediatr. 2021, 22, 253–262. [Google Scholar] [CrossRef] [Scilit]
- Available online: https://www.dedoose.com/userguide/appendix#:~:text=Download-,Citing%20Dedoose,method%20research%20data%20(2018) (accessed on 30 August 2023).
- Simon, T.D.; Haaland, W.; Hawley, K.; Lambka, K.; Mangione-Smith, R. Development and Validation of the Pediatric Medical Complexity Algorithm (PMCA) Version 3.0. Acad. Pediatr. 2018, 18, 577–580. [Google Scholar] [CrossRef] [Scilit]
- Mishel, M.H. Reconceptualization of the uncertainty in illness theory. Image J. Nurs. Sch. 1990, 22, 256–262. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meijssen, D.E.; Wolf, M.J.; Koldewijn, K.; van Wassenaer, A.G.; Kok, J.H.; van Baar, A.L. Parenting stress in mothers after very preterm birth and the effect of the Infant Behavioural Assessment and Intervention Program. Child Care Health Dev. 2011, 37, 195–202. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Krick, J.A.; Weiss, E.M.; Snyder, A.; Haldar, S.; Campelia, G.D.; Opel, D.J. Living with the Unknown: A Qualitative Study of Parental Experience of Prognostic Uncertainty in the Neonatal Intensive Care Unit. Am. J. Perinatol. 2021, 38, 821–827. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malin, K.J.; Johnson, T.S. A Concept Analysis of Parental Uncertainty in Illness of an Infant. MCN Am. J. Matern. Child. Nurs. 2019, 44, 206–211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Evans, L.R.; Boyd, E.A.; Malvar, G.; Apatira, L.; Luce, J.M.; Lo, B.; White, D.B. Surrogate decision-makers’ perspectives on discussing prognosis in the face of uncertainty. Am. J. Respir. Crit. Care Med. 2009, 179, 48–53. [Google Scholar] [CrossRef] [Scilit]
- Lasiuk, G.C.; Comeau, T.; Newburn-Cook, C. Unexpected: An interpretive description of parental traumas′ associated with preterm birth. BMC Pregnancy Childbirth 2013, 13 (Suppl. S1), S13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- White, Z.; Gilstrap, C.; Hull, J. “Me Against the World”: Parental Uncertainty Management at Home Following Neonatal Intensive Care Unit Discharge. J. Fam. Commun. 2017, 17, 105–116. [Google Scholar] [CrossRef] [Scilit]
- Shapiro, J.; Perez, M.; Warden, M.J. The importance of family functioning to caregiver adaptation in mothers of child cancer patients: Testing a social ecological model. J. Pediatr. Oncol. Nurs. 1998, 15, 47–54. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Truitt, M.; Biesecker, B.; Capone, G.; Bailey, T.; Erby, L. The role of hope in adaptation to uncertainty: The experience of caregivers of children with Down syndrome. Patient Educ. Couns. 2012, 87, 233–238. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).