


Abstract
With the aging population, dementia emerges as a public health concern. In 2012, the Health and Retirement Study found that 8.8% of adults over 65 years suffered from dementia. The etiopathogenesis and treatment of dementia are not well understood. Antioxidant properties of Vitamin E and its major elements tocopherols and tocotrienols have been reported to be effective in slowing down the progression of dementia from its initial stage of Mild cognitive impairment (MCI). Therefore, the current review aims to explore the role of vitamin E on MCI. A literature search using the key words “Vitamin E, tocopherols, tocotrienols, and mild cognitive impairment” was conducted in MEDLINE (PubMed), CINAHL, and Google Scholar. The inclusion criteria were: (1) articles published in the past ten years; (2) published in English language; (3) published in peer-reviewed journals; and (4) descriptive and epidemiological or evaluation studies. Articles published prior to 2010, focused on other forms of dementia than MCI, grey literature and non-peer-reviewed articles were excluded. A total of 22 studies were included in the narrative synthesis. The results were equivocal. Eleven studies showed some level of the neuroprotective effect of Vitamin E, tocopherols and tocotrienols on the progression of MCI. The mixed results of this review suggest further exploration of the possible protective effects of Vitamin E on the development of dementia. Future studies can be conducted to decipher antioxidant properties of vitamin E and its association with slowing down the cognitive decline.
1. Introduction
Dementia is a serious public health concern with nearly 50 million people having some form of dementia globally [1]. Reportedly, about 60% of the dementia population live in low and middle-income countries (LMICs) [1]. Estimates suggest that about 10 million people get dementia every year and about 15–20% of elderly population reported having mild cognitive impairment (MCI) as the early stage of dementia [1,2,3]. MCI causes a slight but observable and measurable decline in the memory and thinking skills of an individual. In some individuals, MCI can be reversible (if physiological in origin), however, the likelihood of the reversal to the normal cognitive capability is less for majority of people if it is pathological [2,3]. With due course, MCI advances to the next stage with nearly 65% of people developing more severe forms [2,3].
According to the previous meta-analytical evidence presented by the American Academy of Neurology, the prevalence of MCI was nearly 7% among people with age 60–64 years, which increases with advancing age [3,4]. In the United States (U.S.), the highest prevalence was reported among elderly above 75 years of age [4]. These trends are not only limited to developed countries, low- and middle-income countries indicate similar patterns [5]. However, due to lack of population-based studies, the true estimates are unavailable. According to the previous reports, the prevalence of MCI ranged from 4.5% to 15.4% among South Asian countries [6,7,8,9]. Differences in MCI by demographic characteristics (e.g., gender, race/ethnicity, education) were also noted with women being at greater lifetime risk for dementia compared to their male counterparts [10,11,12]. The occurrence of MCI is found delayed and lenient towards the end of life among whites and highly educated people while the onset of MCI is observed at younger age among blacks and those with lower education attainment [10,11,12]. The lifetime risk of dementia is 21% among men with an associate degree while it is 35% for those who have less than high school education [10,11,12]. White women have a shorter cognitively impaired life compared to black women (6 years vs. 12 to 13 years) [10,11,12]. The burden of dementia further translates into higher cost associated with its management [2]. According to the Alzheimer association, through identification of early stages of Alzheimer disease (AD) i.e., MCI, nearly $7 to $7.9 trillion in health and long-term care can be saved [2].
MCI has severe implications for the patients and their family members and challenges are multifactorial in origin [13]. Often time patients and their family members are unable to identify cognitive decline at earlier stages, particularly in older population groups, in whom cognitive decline is a normal physiological phenomenon. Moreover, cooccurrence of other age-associated diseases are likely to occur in this group with a limited ability to make a differential diagnosis [14,15]. Cognitive insufficiency impacts the quality of life, individual’s functioning, their relationship with the family members, and their self-esteem [14,15]. Caregivers experience high level of caregiving burden for the larger population of MCI [16]. Given the unavailability of medication to treat, prevent, or slow the progression of MCI to dementia, preventive strategies take precedence for at-risk population groups to prevent progressive deficits [17]. Prevention of somatic diseases, promotion of physical and mental exercise, cognitive training, avoidance of toxins, reduction in stress, stopping smoking, and use of dietary compounds such as antioxidants and supplements are some of the suggested to address MCI [17,18]. Among antioxidants, vitamins play a critical role in reducing or delaying to the process of cognitive decline in people with MCI. Among all vitamins, vitamin E was found to be effective in reducing MCI [17,18,19,20,21,22,23]. Vitamin E is a fat-soluble vitamin and found in variety of foods [19]. Its usable form (i.e., alpha tocopherol) is considered a scavenger of free radicals in the body [19], which controls brain prostaglandin synthesis and regulates nucleic acid synthesis. While some studies have documented association of vitamin E intake in slowing down the progression of MCI, collective evidence to investigate its significance is still lacking [17,18,19,20,21,22,23]. Therefore, the purpose of this study was to review existing literature to decipher role of vitamin E in slowing down MCI progression.
2. Methods
2.1. Search Strategy
Bibliographical databases, including Medline (PubMed), CINAHL, and Google Scholar were quickly searched in January/February 2020. Pharmacological synonyms of vitamin E were used as related terms to locate potential evidence to be included in this review. Articles related to cognitive impairment were also sought using the Boolean operator “AND” to narrow down search results to include articles containing the specified terms. A detailed list of key words is shown in Table 1.
Table 1.
List of keywords used for literature search.
2.2. Inclusion Criteria and Data Abstraction
The inclusion criteria of this review were the following; (1) observational, randomized controlled trials, clinical and laboratory studies published over past ten years; (2) studies published in English language; (3) published in peer-reviewed journals; and (4) descriptive and epidemiological or evaluation-based studies. The exploration of preventive relationship of vitamin E with mild cognitive impairment is relatively new. Therefore, we selected to assign a broad range of criteria including human and animals-based studies published in the 10 years of timeframe. Articles published before 2010, focused on other forms of dementia than MCI, grey literature, abstracts—only studies, and non-peer-reviewed articles were excluded. We also conducted a post-hoc search in July 2021 to update our literature matrix used for this review. Details about the search results were saved in the spreadsheet by the lead author. Titles and abstracts were screened for relevancy and eligibility. If found relevant, full-texts were read thoroughly and data were extracted in a standardized data collection form. Variables such as year of publication, study type, outcomes, key findings, neuroprotective role of vitamin E, and conclusions were tabulated in the data collection form.
3. Results
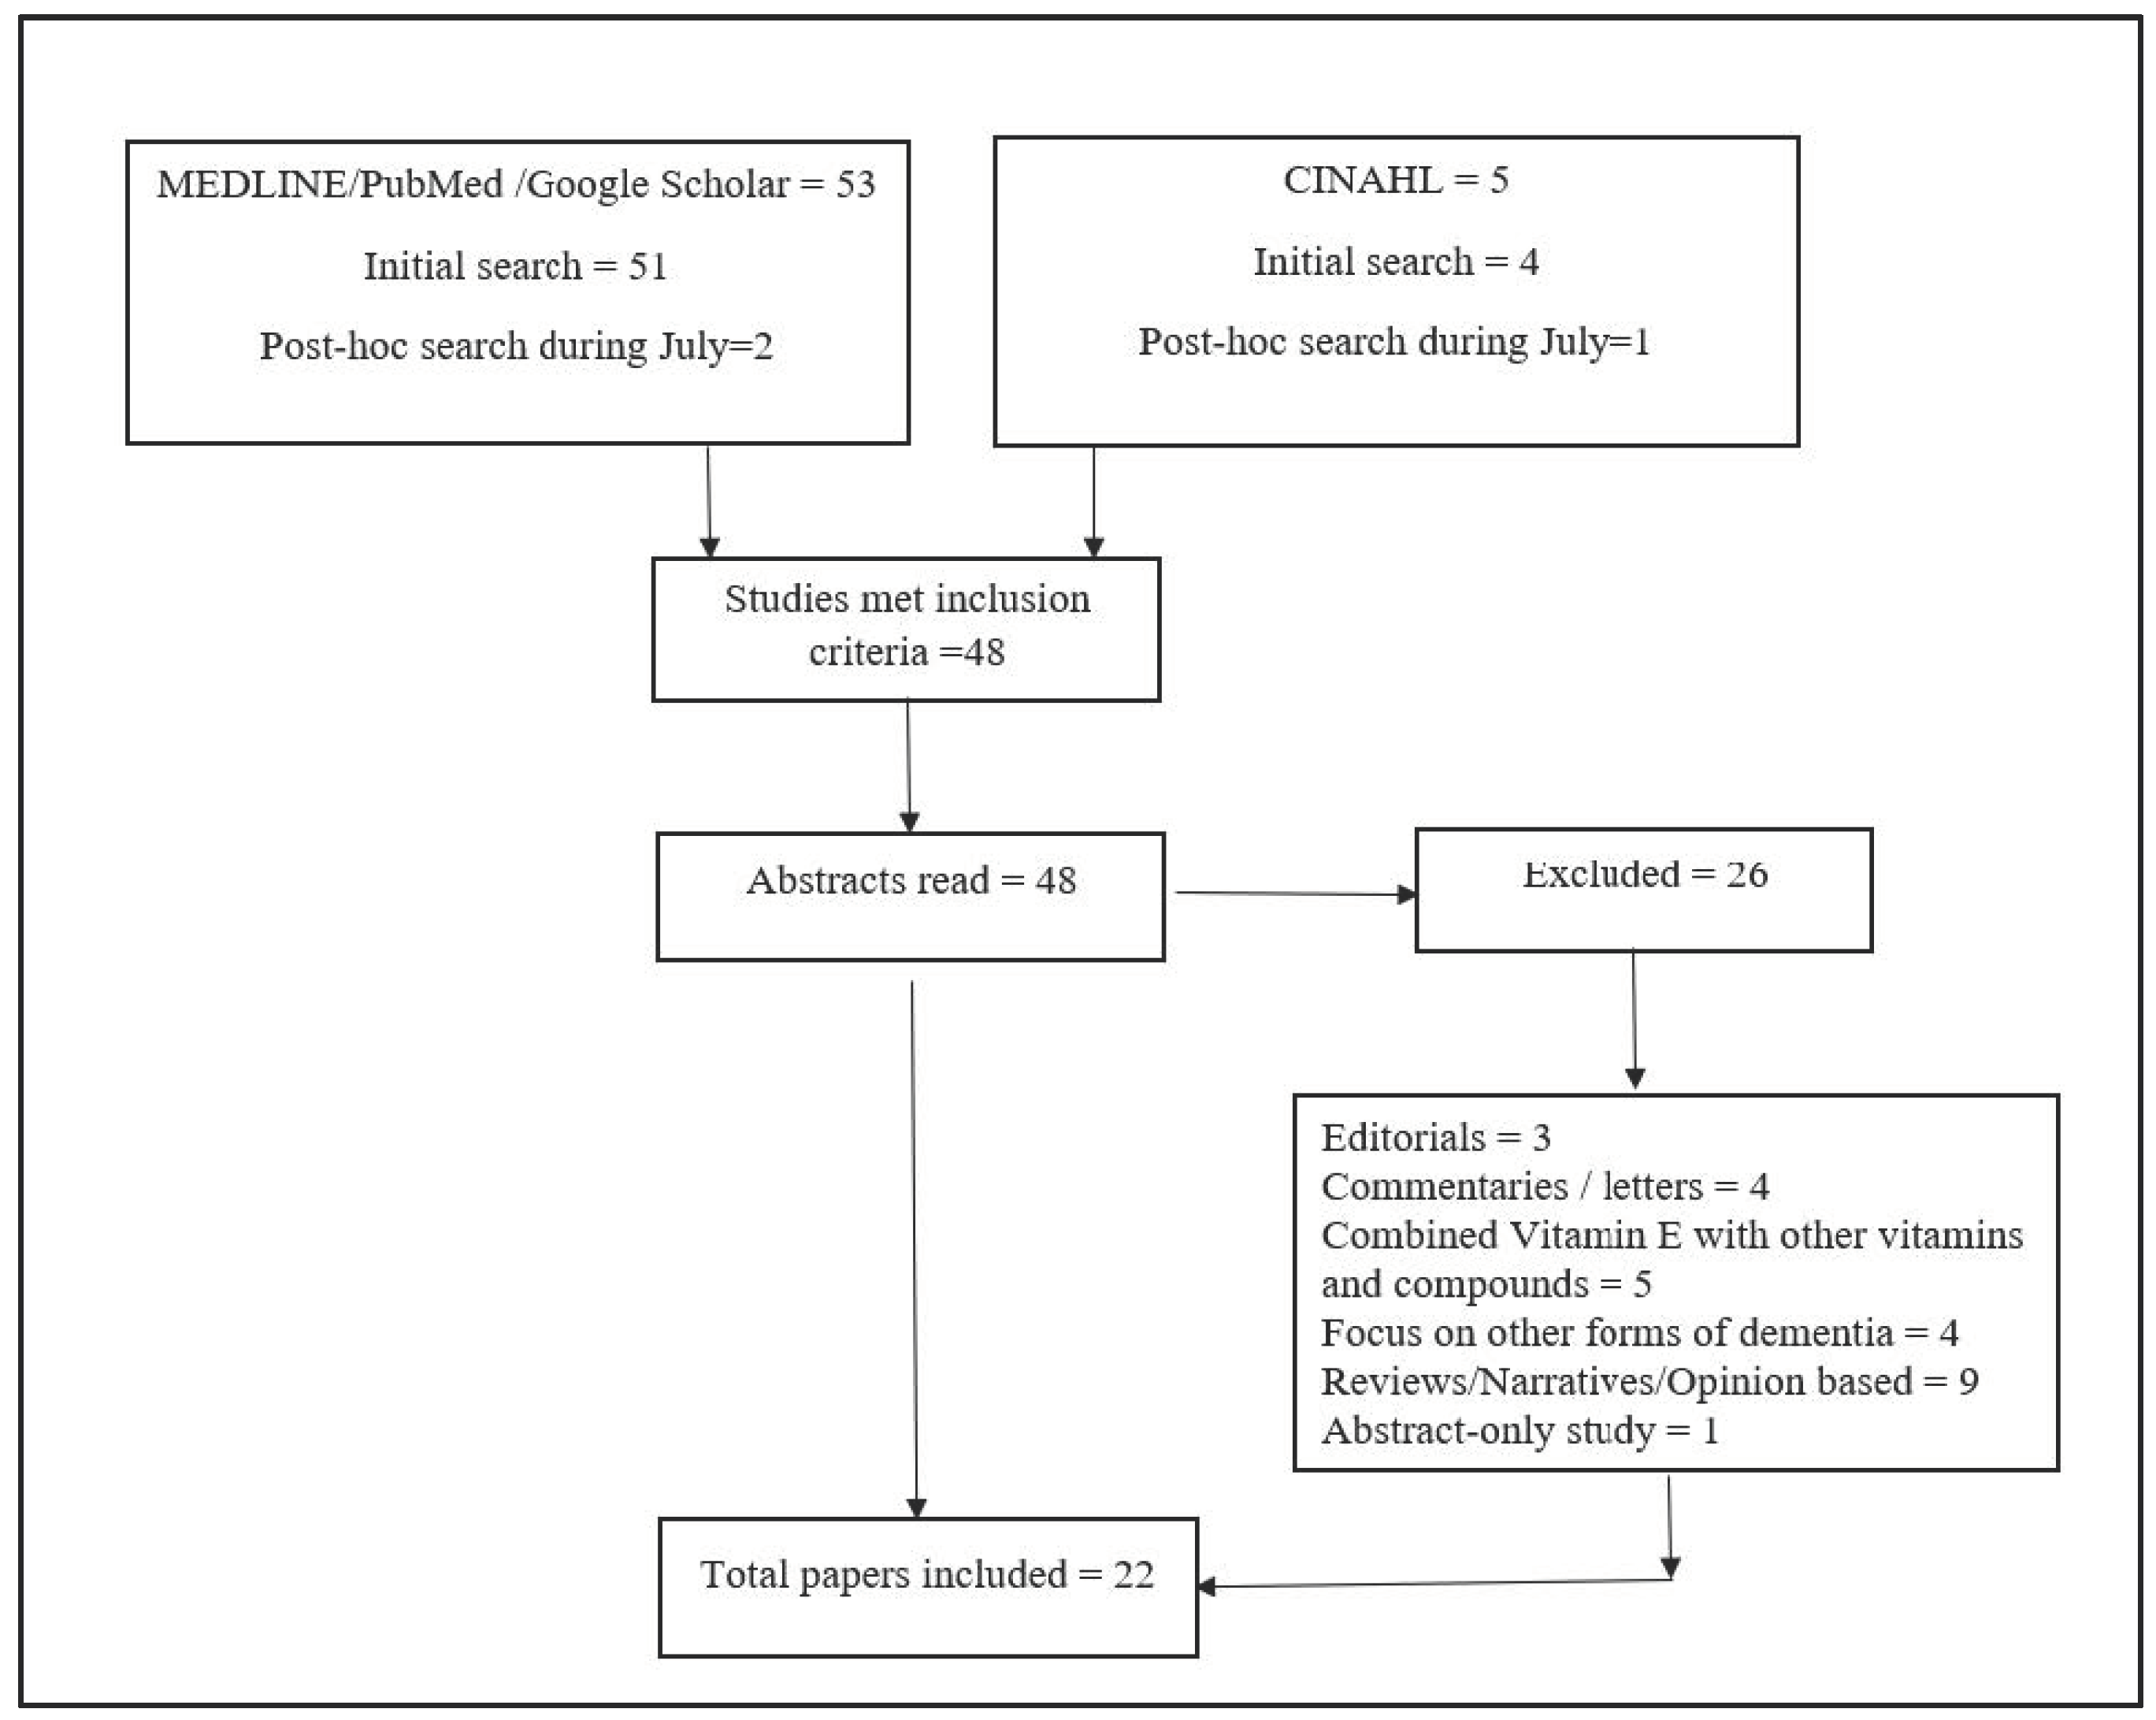
Following keyword search, 53 articles in Medline/PubMed/Google Scholar and 5 in CINAHL database were found. Out of those, 48 studies met the inclusion criteria. Abstracts of all 48 studies were screened. Twenty-six studies were excluded for variety of reasons of being editorials, commentaries/letters, abstract-only study, combined vitamin E with other vitamins, focused on other form of dementia rather than MCI, reviews, narratives and opinion-based papers. Finally, 22 papers [19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41] were included in this review for the data summarization (Figure 1). Characteristics of finally included studies are provided in Table A1 in Appendix A.
Figure 1.
Flow diagram of the literature search and selection process.
Of 22 finally included studies, seven were conducted with animals. Out of seven, six studies conducted on rats, mice, and other animals exhibited some level of the neuroprotective effect of vitamin E by lowering the rate or delaying cognitive impairment progression. Similarly, out of 15 studies conducted on humans, eight studies reported Vitamin E’s role in lowering the risk or delaying cognitive impairment. Two studies, one cohort and a double-blind randomized placebo-controlled study, demonstrated Vitamin E’s effect in improving learning and memory functions. Two studies of each experimental and double-blind randomized placebo-controlled did not find any effect of Vitamin E on cognitive impairment while a clinical study14 suggested a potentially favorable effect (Table 2 and Table A1).
Table 2.
Summary results of all studies in the review (n = 22).
4. Discussion
The purpose of this review was to examine the effect of Vitamin E in slowing down cognitive decline in MCI. Some evidence from our literature synthesis points to the putative role of Vitamin E in slowing down MCI progression to dementia. Overall, the review collectively demonstrated through analysis of various experimental studies in rats, mice, and animals and cross-sectional, case-control, prospective cohort, experimental, clinical, and double-blind randomized in human that Vitamin E has some neuroprotective effect in slowing down progression to dementia. One clinical study carried out to lower the effect of cisplatin chemotherapy neurotoxicity, the supplementation with vitamin E (alpha tocopherol) has shown lower level of neurotoxicity, which indicates that vitamin E plays a neuroprotective role [42] even when the cause of neurotoxicity could be other than mild cognitive impairment. The findings of Gugliandolo et al. (2017) have reported similar physiological responses of Vitamin E on MCI [43,44,45]. Another study by Kaneai et al., indicated that vitamin E offers some neuroprotective benefits by improving neurotransmission [45]. Presently, no medication can treat, prevent, or slow the progression of MCI to dementia. However, it is important to explore the role of vitamins and antioxidants in reducing or delaying to the process of cognitive decline in people with MCI [17]. Studies show that high plasma Vitamin E levels have been associated with better cognitive performance in both ageing populations, dementia, and AD patients [42,43].
Consistent to previous studies it is understood that Vitamin E might have some therapeutic role when it comes to MCI and its progression to dementia. Since several studies in human as well as in rats and mice were MCI associated with lower level of tocopherol. Thus, it may be considered a good practice to maintain Vitamin E level through dietary sources. Vitamin E can also lead to toxicity that can be fatal in some cases which warrants careful monitoring of its levels in the aging population. The guidelines on the safe dose of vitamin E varies from 800–2000 IU/day as reported by previous studies [46,47]. Therefore, these findings should be considered rather carefully to prevent any toxic effects of vitamin E. In the meanwhile, more randomized controlled trials to further elucidate the role of Vitamin E on MCI must be conducted with larger sample sizes. Even though there are mixed results they favor a potential neuroprotective effect of Vitamin E in MCI. It would be recommended for clinical practice that the Vitamin E levels be checked annually in the elderly, and they should be provided Vitamin E supplementation in maintaining its adequate level.
Limitations
This review has certain limitations including that research articles focused on dementia, which have explored relationship of vitamin E on mild cognitive impairment but not necessarily mentioned MCI in the title or abstract, those articles might have left from inclusion. Authors utilized phrase searching, however, due to the lack of truncation rules for some terms of dementia, some articles might have been missed. Therefore, future studies using a systematic literature review with a well-defined and peer-reviewed search strategy can be conducted. Six animal studies are included in this review and comparison were made between findings in human and animals. Comparison of effect of an element between human and animal specially on cognitive function and process is extremely complex. In simpler terms, behavioral studies to investigate cognitive decline among humans offer higher inferential benefits than those being conducted among animals due to differences in their baseline intelligence levels and capabilities. Next, studies included in this review were heterogenous in terms of type of measures used to detect the cognitive decline and these measures had varied threshold criteria. These restricted our ability to generate pooled estimates, which otherwise might have helped us to quantify the association between vitamin E and neuroprotection in the form of appropriate effect sizes (such as odds ratios). In addition, understanding trajectories of change in cognitive function will be difficult with such a heterogeneity. On the other hand, the observation of physiological process relatively easier in animal population compared to human due to ethical consideration. The findings of animal studies showing favorable outcome of vitamin E on cognition process may not be rewarding when compared to human. The database such as LILACS were not explored. Few studies included in this review has a very small sample size or their results were mixed up with some other compound which might have impacted on the conclusion of this review.
Despite the limitations, the study has implications for practice. Vitamin E supplementation should be monitored closely when in combination with Vitamin E nutrients from food sources. Other than alpha tocopherol, no other component of vitamin was found helpful in slowing the process of cognitive decline. It is not known if the other form of vitamin E or its component has negative effect on cognitive process. Therefore, caution needs to be practiced in optimizing level of vitamin E that way the other components of vitamin E do not affect the properties of alpha tocopherol and its impact on MCI. In addition, this review indicates favorable physiological and neurochemical benefits of vitamin E in protecting or delaying cognitive decline process, however, effects may be different among animals and human-beings. These differences may be due to the varied vitamin E requirements and physiological mechanisms among these groups. Therefore, further research to understand associations between vitamin E requirements, consumption, and effects at organismal levels would be critical to unfold interactions of vitamin E with body mechanisms.
5. Conclusions
In conclusion, epidemiological, clinical, nor other studies have provided the conclusive answer to whether or not Vitamin E slows the progression of MCI. Further research with human subjects is needed to understand the safety and efficacy of Vitamin E as a nutritional supplement to promote health ageing. Future research to understand the physiological process of alpha tocopherol on cognitive process in human beings can be conducted.
Author Contributions
Conceptualization, R.L. and M.S.; methodology, R.L., M.S., K.B.; software, R.L., K.B.; validation, K.B., F.B.B., M.S.; data curation, R.L.; writing—original draft preparation, R.L., M.S., K.B., F.B.B.; writing—review and editing, K.B., F.B.B.; visualization, R.L., K.B.; project administration, R.L., M.S. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Table A1.
Reviewed studies and their salient findings (n = 22).
References
- World Health Organization (WHO). WHO Dementia. Available online: https://www.who.int/news-room/fact-sheets/detail/dementia (accessed on 20 November 2020).
- Alzheimer Association. Mild Cognitive Impairment. 2020. Available online: https://www.alz.org/alzheimers-dementia/what-is-dementia/related_conditions/mild-cognitive-impairment (accessed on 21 September 2020).
- Roberts, R.O.; Knopman, D.S.; Mielke, M.M.; Cha, R.H.; Pankratz, V.S.; Christianson, T.J.; Geda, Y.E.; Boeve, B.F.; Ivnik, R.J.; Tangalos, E.G.; et al. Higher risk of progression to dementia in mild cognitive impairment cases who revert to normal. Neurology 2014, 82, 317–325. [Google Scholar] [CrossRef] [Scilit]
- American Academy of Neurology. Update, Mild Cognitive Impairment. Available online: https://www.aan.com/ (accessed on 19 May 2020).
- Sosa, A.L.; Albanese, E.; Stephan, B.; Dewey, M.; Acosta, D.; Ferri, C.; Guerra, M.; Huang, Y.; Jacob, K.S.; Jiménez-Velázquez, I.Z.; et al. Prevalence, distribution, and impact of mild cognitive impairment in Latin America, China, and India: A 10/66 population-based study. PLoS Med. 2012, 9, e1001170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Das, S.K.; Bose, P.; Biswas, A.; Dutt, A.; Banerjee, T.K.; Hazra, A.; Raut, D.K.; Chaudhuri, A.; Roy, T. An epidemiologic study of mild cognitive impairment in Kolkata, India. Neurology 2007, 68, 2019–2026. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, J.; Wang, Y.J.; Zhang, M.; Xu, Z.Q.; Gao, C.Y.; Fang, C.Q.; Yan, J.C.; Zhou, H.D. Vascular risk factors promote conversion from mild cognitive impairment to Alzheimer disease. Neurology 2011, 76, 1485–1491. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, L.K.; Shahar, S.; Chin, A.-V.; Yusoff, N.A.M.; Rajab, N.; Aziz, S.A. Prevalence of gender disparities and predictors affecting the occurrence of mild cognitive impairment (MCI). Arch. Gerontol. Geriatr. 2012, 54, 185–191. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, K.W.; Park, J.H.; Kim, M.-H.; Kim, M.D.; Kim, B.-J.; Kim, S.-K.; Kim, J.L.; Moon, S.W.; Bae, J.N.; Woo, J.I.; et al. A nationwide survey on the prevalence of dementia and mild cognitive impairment in South Korea. J. Alzheimer’s Dis. 2011, 23, 281–291. [Google Scholar] [CrossRef] [Scilit]
- Hale, J.M.; Schneider, D.C.; Mehta, N.K.; Myrskylä, M. Cognitive impairment in the U.S.: Lifetime risk, age at onset, and years impaired. SSM—Popul. Healh 2020, 11, 100577. [Google Scholar] [CrossRef] [Scilit]
- Katz, M.J.; Lipton, R.B.; Hall, C.; Zimmerman, M.E.; Sanders, A.E.; Verghese, J.; Dickson, D.W.; Derby, C.A. Age-specific and sex-specific prevalence and incidence of mild cognitive impairment, dementia, and Alzheimer dementia in blacks and whites: A report from the einstein aging study. Alzheimer Dis. Assoc. Disord. 2012, 26, 335–343. [Google Scholar] [CrossRef] [Scilit]
- McDougall, G.J., Jr.; Vaughan, P.W.; Acee, T.W.; Becker, H. Memory performance and mild cognitive impairment in Black and White community elders. Ethn. Dis. 2007, 17, 381–388. [Google Scholar]
- Langa, K.M.; Levine, D.A. The diagnosis and management of mild cognitive impairment: A clinical review. JAMA 2014, 312, 2551–2561. [Google Scholar] [CrossRef] [Scilit]
- Murman, D.L. The impact of age on cognition. Semin. Hear. 2015, 36, 111–121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Teng, E.; Tassniyom, K.; Lu, P.H. Reduced quality-of-life ratings in mild cognitive impairment: Analyses of subject and informant responses. Am. J. Geriatr. Psychiatry 2012, 20, 1016–1025. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Connors, M.H.; Seeher, K.; Teixeira-Pinto, A.; Woodward, M.; Ames, D.; Brodaty, H. Mild cognitive impairment and caregiver burden: A 3-year-longitudinal study. Am. J. Geriatr. Psychiatry 2019, 27, 1206–1215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eshkoor, S.A.; Mun, C.Y.; Ng, C.K.; Hamid, T.A. Mild cognitive impairment and its management in older people. Clin. Interv. Aging 2015, 10, 687–693. [Google Scholar] [CrossRef] [Scilit]
- Vega, J.; Newhouse, P.A. Mild cognitive impairment: Diagnosis, longitudinal course, and emerging treatments. Curr. Psychiatry Rep. 2014, 16, 490. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Farina, N.; Llewellyn, D.; Isaac, M.G.E.K.N.; Tabet, N. Vitamin E for Alzheimer’s dementia and mild cognitive impairment. Cochrane Database Syst. Rev. 2017, 4, CD002854. [Google Scholar] [CrossRef] [Scilit]
- Wu, A.; Ying, Z.; Gomez-Pinilla, F. Vitamin E protects against oxidative damage and learning disability after mild traumatic brain injury in rats. Neurorehabilit. Neural Repair 2009, 24, 290–298. [Google Scholar] [CrossRef] [Scilit]
- Huang, Q.; Aluise, C.D.; Joshi, G.; Sultana, R.; Clair, D.K.S.; Markesbery, W.R.; Butterfield, D.A. Potential in vivo amelioration by N-acetyl-L-cysteine of oxidative stress in brain in human double mutant APP/PS-1 knock-in mice: Toward therapeutic modulation of mild cognitive impairment. J. Neurosci. Res. 2010, 88, 2618–2629. [Google Scholar] [CrossRef] [Scilit]
- Alzoubi, K.H.; Khabour, O.F.; Salah, H.A.; Hasan, Z. Vitamin E prevents high-fat high-carbohydrates diet-induced memory impairment: The role of oxidative stress. Physiol. Behav. 2013, 119, 72–78. [Google Scholar] [CrossRef] [Scilit]
- Giraldo, E.; Lloret, A.; Fuchsberger, T.; Vina, J. Aβ and tau toxicities in Alzheimer’s are linked via oxidative stress-induced p38 activation: Protective role of vitamin E. Redox Biol. 2014, 2, 873–877. [Google Scholar] [CrossRef] [Scilit]
- Nesari, A.; Mansouri, M.T.; Khodayar, M.J.; Rezaei, M. Preadministration of high-dose alpha-tocopherol improved memory impairment and mitochondrial dysfunction induced by proteasome inhibition in rat hippocampus. Nutr. Neurosci. 2021, 24, 119–129. [Google Scholar] [CrossRef] [Scilit]
- Mehrabadi, S.; Sadr, S.S. Administration of Vitamin D3 and E supplements reduces neuronal loss and oxidative stress in a model of rats with Alzheimer’s disease. Neurol. Res. 2020, 42, 862–868. [Google Scholar] [CrossRef] [Scilit]
- Iuliano, L.; Monticolo, R.; Straface, G.; Spoletini, I.; Gianni, W.; Caltagirone, C.; Bossu, P.; Spalletta, G. Vitamin E and enzymatic/oxidative stress-driven oxysterols in amnestic mild cognitive impairment subtypes and Alzheimer’s disease. J. Alzheimer’s Dis. 2010, 21, 1383–1392. [Google Scholar] [CrossRef] [Scilit]
- Whitehair, D.C.; Sherzai, A.; Emond, J.; Raman, R.; Aisen, P.S.; Petersen, R.C.; Fleisher, A.S. Alzheimer’s disease cooperative study influence of apolipoprotein E ɛ4 on rates of cognitive and functional decline in mild cognitive impairment. Alzheimer’s Dement. 2010, 6, 412–419. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mangialasche, F.; Xu, W.; Kivipelto, M.; Costanzi, E.; Ercolani, S.; Pigliautile, M.; Cecchetti, R.; Baglioni, M.; Simmons, A.; Soininen, H.; et al. Tocopherols and tocotrienols plasma levels are associated with cognitive impairment. Neurobiol. Aging 2012, 33, 2282–2290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mangialasche, F.; Solomon, A.; Kåreholt, I.; Hooshmand, B.; Cecchetti, R.; Fratiglioni, L.; Soininen, H.; Laatikainen, T.; Mecocci, P.; Kivipelto, M. Serum levels of vitamin E forms and risk of cognitive impairment in a Finnish cohort of older adults. Exp. Gerontol. 2013, 48, 1428–1435. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shahar, S.; Lee, L.K.; Rajab, N.; Lim, C.L.; Harun, N.A.; Noh, M.F.N.M.; Mian-Then, S.; Jamal, R. Association between vitamin A, vitamin E and apolipoprotein E status with mild cognitive impairment among elderly people in low-cost residential areas. Nutr. Neurosci. 2013, 16, 6–12. [Google Scholar] [CrossRef] [Scilit]
- Dysken, M.W.; Sano, M.; Asthana, S.; Vertrees, J.E.; Pallaki, M.; Llorente, M.; Love, S.; Schellenberg, G.D.; McCarten, J.R.; Malphurs, J.; et al. Effect of vitamin E and memantine on functional decline in Alzheimer disease: The TEAM-AD VA cooperative randomized trial. JAMA 2014, 311, 33–44. [Google Scholar] [CrossRef] [Scilit]
- Zanotta, D.; Puricelli, S.; Bonoldi, G. Cognitive effects of a dietary supplement made from extract of Bacopa monnieri, astaxanthin, phosphatidylserine, and vitamin E in subjects with mild cognitive impairment: A noncomparative, exploratory clinical study. Neuropsychiatr. Dis. Treat. 2014, 10, 225–230. [Google Scholar] [CrossRef] [Scilit]
- Naeini, A.M.A.; Elmadfa, I.; Djazayery, A.; Barekatain, M.; Ghazvini, M.R.A.; Djalali, M.; Feizi, A. The effect of antioxidant vitamins E and C on cognitive performance of the elderly with mild cognitive impairment in Isfahan, Iran: A double-blind, randomized, placebo-controlled trial. Eur. J. Nutr. 2013, 53, 1255–1262. [Google Scholar] [CrossRef] [Scilit]
- De Beaumont, L.; Pelleieux, S.; Lamarre-Theroux, L.; Dea, D.; Poirier, J. Butyrylcholinesterase K and apolipoprotein E-ɛ4 reduce the age of onset of Alzheimer’s disease, accelerate cognitive decline, and modulate donepezil response in mild cognitively impaired subjects. J. Alzheimer’s Dis. 2016, 54, 913–922. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basambombo, L.L.; Carmichael, P.-H.; Côté, S.; Laurin, D. Use of vitamin E and C supplements for the prevention of cognitive decline. Ann. Pharmacother. 2016, 51, 118–124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, G.; Zhao, Y.; Jin, S.; Hu, Y.; Wang, T.; Tian, R.; Han, Z.; Xu, D.; Jiang, Q. Circulating vitamin E levels and Alzheimer’s disease: A mendelian randomization study. Neurobiol. Aging 2018, 72, 189-e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Y.; Liu, S.; Man, Y.; Li, N.; Zhou, Y.U. Effects of vitamins E and C combined with β-carotene on cognitive function in the elderly. Exp. Ther. Med. 2015, 9, 1489–1493. [Google Scholar] [CrossRef] [Scilit]
- Edmonds, E.C.; Ard, M.C.; Edland, S.D.; Galasko, D.R.; Salmon, D.P.; Bondi, M.W. Unmasking the benefits of donepezil via psychometrically precise identification of mild cognitive impairment: A secondary analysis of the ADCS vitamin E and donepezil in MCI study. Alzheimer’s Dement. 2018, 4, 11–18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Casati, M.; Boccardi, V.; Ferri, E.; Bertagnoli, L.; Bastiani, P.; Ciccone, S.; Mansi, M.; Scamosci, M.; Rossi, P.D.; Mecocci, P.; et al. Vitamin E and Alzheimer’s disease: The mediating role of cellular aging. Aging Clin. Exp. Res. 2019, 32, 459–464. [Google Scholar] [CrossRef] [Scilit]
- Kim, S.H.; Park, Y.M.; Choi, B.Y.; Kim, M.K.; Roh, S.; Kim, K.; Yang, Y.J. Associations of serum levels of vitamins A, C, and E with the risk of cognitive impairment among elderly Koreans. Nutr. Res. Pract. 2018, 12, 160–165. [Google Scholar] [CrossRef] [Scilit]
- McDougall, M.; Choi, J.; Magnusson, K.; Truong, L.; Tanguay, R.; Traber, M.G. Chronic vitamin E deficiency impairs cognitive function in adult zebrafish via dysregulation of brain lipids and energy metabolism. Free Radic. Biol. Med. 2017, 112, 308–317. [Google Scholar] [CrossRef] [Scilit]
- Pace, A.; Savarese, A.; Picardo, M.; Maresca, V.; Pacetti, U.; Del Monte, G.; Biroccio, A.; Leonetti, C.; Jandolo, B.; Cognetti, F.; et al. Neuroprotective effect of vitamin E supplementation in patients teated with cisplatin chemotherapy. J. Clin. Oncol. 2003, 21, 927–931. [Google Scholar] [CrossRef] [Scilit]
- Gugliandolo, A.; Bramanti, P.; Mazzon, E. Role of vitamin E in the treatment of Alzheimer’s disease: Evidence from animal models. Int. J. Mol. Sci. 2017, 18, 2504. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- La Torre, M.E.; Villano, I.; Monda, M.; Messina, A.; Cibelli, G.; Valenzano, A.; Pisanelli, D.; Panaro, M.A.; Tartaglia, N.; Ambrosi, A.; et al. Role of vitamin E and the orexin system in neuroprotection. Brain Sci. 2021, 11, 1098. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaneai, N.; Arai, M.; Takatsu, H.; Fukui, K.; Urano, S. Vitamin E inhibits oxidative stress-induced denaturation of nerve terminal proteins involved in neurotransmission. J. Alzheimer’s Dis. 2012, 28, 183–189. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- La Fata, G.; Weber, P.; Mohajeri, M.H. Effects of vitamin E on cognitive performance during ageing and in Alzheimer’s disease. Nutrients 2014, 6, 5453–5472. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lloret, A.; Badía, M.-C.; Mora, N.J.; Pallardó, F.V.; Alonso, M.-D.; Viña, J. Vitamin E paradox in Alzheimer’s disease: It does not prevent loss of cognition and may even be detrimental. J. Alzheimer’s Dis. 2009, 17, 143–149. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).