


Abstract
Medicines reconciliation is a way to identify and act on discrepancies in patients’ medical histories and it is found to play a key role in patient safety. This review focuses on discrepancies and medical errors that occurred at point of discharge from hospital. Studies were identified through the following electronic databases: PubMed, Sciences Direct, EMBASE, Google Scholar, Cochrane Reviews and CINAHL. Each of the six databases was screened from inception to end of January 2014. To determine eligibility of the studies; the title, abstract and full manuscript were screened to find 15 articles that meet the inclusion criteria. The median number of discrepancies across the articles was found to be 60%. In average patient had between 1.2–5.3 discrepancies when leaving the hospital. More studies also found a relation between the numbers of drugs a patient was on and the number of discrepancies. The variation in the number of discrepancies found in the 15 studies could be due to the fact that some studies excluded patient taking more than 5 drugs at admission. Medication reconciliation would be a way to avoid the high number of discrepancies that was found in this literature review and thereby increase patient safety.
1. Introduction
Ensuring patient safety in the healthcare system is a complex challenge and involves many health care professionals across multiple institutions. One of the most common ways to prevent, manage and cure diseases and illnesses is by the use of medicines. This, however, does not come without its own set of risks. Medication errors (ME) are prevalent and costly; both in terms of patient injury and economics. Over half of these errors occur during transitions of care or at the interface of care [1,2,3,4]. According to Ferner and Aronson (2006), a medication error can be defined as “a failure in the treatment process that leads to, or has the potential to lead to, harm to the patient” [5]. This is in contrast to an adverse drug event (ADE), which is, “an actual unintended medication related event that occurs during treatment of the patient with pharmaceuticals”. The difference therefore lies in the event having taken place (ADE) rather than the error (which may result in an event) being noted (ME). An example of a medication error is when a patient has not been prescribed one of their regular medicines on admission to hospital; this would be an error of omission and an ME. However, if the patient had been prescribed a medicine (even at the correct dose) that resulted in the patient experiencing an unintended side-effect (which could be anything from pruritus to anaphylaxis), this would be classed as an adverse drug event (ADE) [6,7]. It has been documented that there is a positive association between the number of medicines prescribed for a patient and the likelihood of experiencing an ME [8]. A structured handover between carers is one way in which MEs can be reduced [9]. Medication reconciliation has been acknowledged as one of the key elements to improve patient safety by decreasing MEs at discharge and transitions of care [1,10].
Medication reconciliation is defined as the process of “creating the most accurate list possible of all medications a patient is taking—including drug name, dosage, frequency and route—and comparing that list against the physician’s admission, transfer and/or discharge orders, with the goal of providing correct medication to the patient at all transitions points within the hospital” [11]. Medication reconciliation consists of four steps that help to ensure patient safety across the healthcare system: (1) verification: the current medication list is obtained; (2) clarification: the medication and dosages are checked for adequacy; (3) reconciliation: newly-prescribed and previous medications are compared and documented; and (4) transmission: an updated and verified medication list is communicated to the next healthcare provider [11,12].
Two other terms that are commonly used when discussing medication reconciliation are: intentional and unintentional discrepancies. An unintentional discrepancy is one that occurs without the professional involved making a conscious decision to alter therapy. In contrast, those discrepancies that are made due to an underlying co-morbidity or change in drug metabolism (for example, a decline in renal function) are termed intentional. These intentional discrepancies will have been usually documented in a standard manner, in the medical notes, by the physician amending the prescription, as they are consciously making the decision to alter the therapy. Whilst only the unintended discrepancies can be classified as MEs, it is important to note that an intentional discrepancy may still lead to confusion and errors at discharge, if not documented clearly [7].
The aims of this literature review are to compile and analyse journal articles that focus on medication reconciliation at discharge. The objectives are to report the prevalence of ME and the mean number of discrepancies at discharge (expressed as the percentage of patients where available), as well as the most common types of errors and medications (or classes of medications) most frequently implicated.
2. Experimental Section
The following databases were used: PubMed, Sciences Direct, Excerpta Medica dataBASE (EMBASE), Google Scholar, Cochrane and, Cumulative Index to Nursing and Allied Health Literature (CINAHL). To ensure that all relevant articles were found, an advanced search strategy was undertaken. The search strategy is described in Table 1.
Articles had to meet the following inclusion/exclusion criteria.
Inclusion criteria:
- Published in English
- Quantitative studies, i.e., studies that examine the prevalence of ME, or the mean number of discrepancies at discharge (expressed as the percentage of patients where available), or studies that quantify the most common types of errors and medications (or classes of medications) most frequently implicated in these errors.
Exclusion criteria:
- Duplicates
- Articles not published in English
- Review articles, meta-analysis and editorials
- Qualitative studies
The titles and abstracts of the articles found in the searches were screened for relevance before final inclusion.
Table 1.
Results of the search strategy, including: search terms, limits, results, relevant studies and included studies.
Figure 1 shows a flow chart of the selection of relevant articles.
3. Results and Discussion
The key results from each article included in the literature review are summarised in Table 2.
This literature review was conducted to give an overview of the quantitative research on medicine reconciliation at hospital discharge. During the review, 270 articles were screened, after the advanced search strategy was conducted; see Figure 1. This resulted in the inclusion of 15 articles for this review (Table 2). The data from these 15 articles represent international data from over 6000 hospital discharges.
Figure 1.
Flow diagram of studies assessed and included.
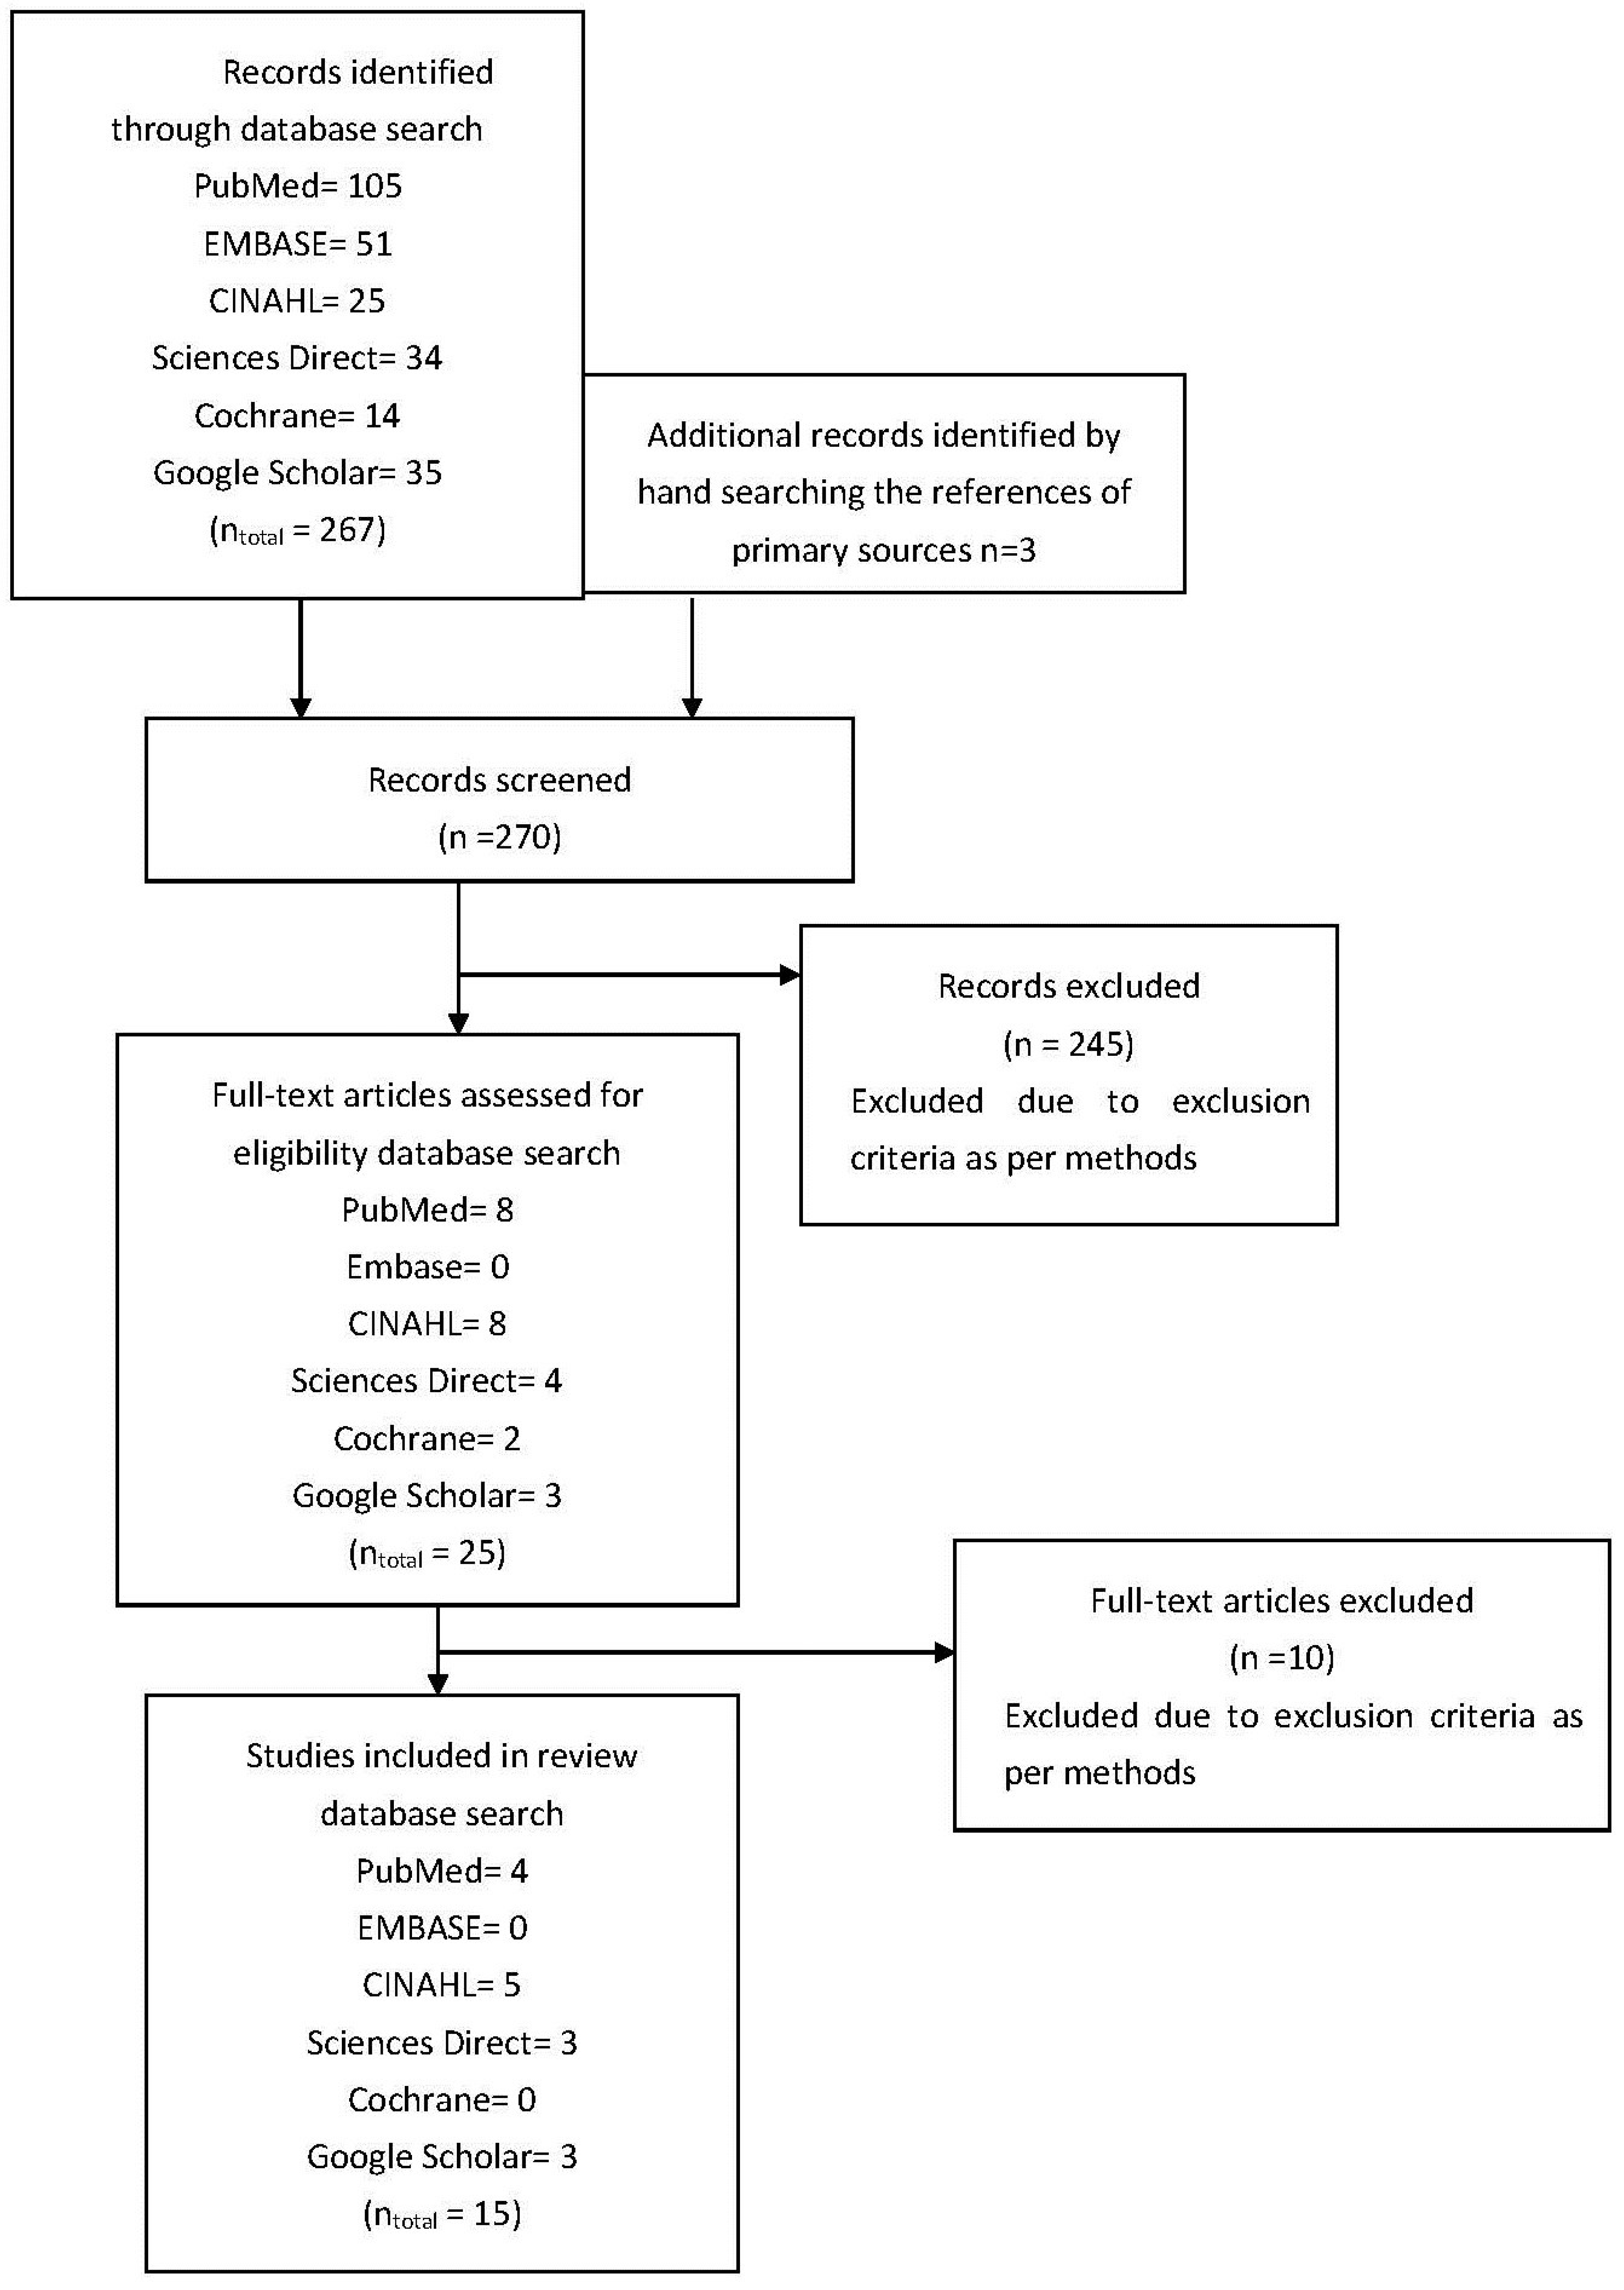
Table 2.
Presentation of results. Key elements for each article are described.
Of the included studies, six were retrospective [1,14,20,21,22,23], and six were prospective studies [7,10,13,15,17,19]. The advantages of these types of studies include the ability to examine multiple outcomes of a single risk factor. The disadvantages of retrospective studies include: (i) if records that were not designed for the study are used, the available data may be of poor quality; (ii) there can be frequently an absence of data on potential confounding factors; and (iii) it may be difficult to identify an appropriate exposed cohort and an appropriate comparison group. Disadvantages of prospective cohort studies include: (i) having to follow large numbers of subjects for a long time; (ii) expensive and time consuming; (iii) not good for rare diseases or diseases with a long latency; and (iv) differential loss to follow up can introduce bias.
Furthermore, one study was a randomised clinical trial (RCT) [16], and two were cross-sectional observational studies [18,24]. An RCT is classified as the gold standard in the clinical setting, as it can greatly reduce the confounding factors by random assignment and, hence, make the study and control groups equivalent at study outset. This (plus any additional blinding) enables a cause and effect relationship to be established. However, the challenge with RCTs in medication reconciliation (MR) studies is that, in effect, you have to conduct MR (or a form thereof) on the controlled group to elicit medication-related problems, and so, most studies are not described as RCTs. Observational studies however reach a conclusion by comparing subjects against a control group, in cases where the researcher has no control over the experiment. One of the primary drivers for undertaking observational research is ethical concerns. One of the main challenges associated with observational studies is that the investigator has no control over the configuration of the control groups and cannot randomise the allocation of subjects. This can lead to bias and may also mask cause and effect relationships or, alternatively, suggest associations where there are none.
The number of included patients/discharges in each article varied from 60–1246. The reason for the big differences in numbers of included subjects can be explained by the fact that some of the studies were conducted at a single site and for a short period of data collection, as evidenced in the work of Vira et al. [15]. In contrast, the work presented by Grimes et al. [24] was conducted at two sites over a 29-month period. Another key difference is that in some articles, they have looked at patients, whereas other articles have looked at discharges during the study period. This means that one patient could appear in the study on more than one occasion. It is well established that increasing the sample size/study population increases the power of the study and the ability to detect with any degree of accuracy the differences between sample cohorts [25]. The mean age of the study populations for the fifteen articles varies from 56 years (standard deviation (SD) 24 years) [15] to 84 years (SD 5.8 years) in the Cornu et al. (2012) [14] study. The mean age in the studies included in this review is 69 (SD 9.1) years, which indicates that overall, the study population would be categorized as elderly. Due to the fact that patients taking five or more drugs are increasingly likely to be found in the older population, it is not surprising that the number of preadmission drugs are high and varies from five [24] to eight drugs per patient [18].
One of the factors identified as having a significant impact on the risk of discrepancies and ME at discharge is the number of drugs a patient is prescribed. For every additional drug, a patient is taking the risk of being exposed to discrepancies, which could lead to increased ME. Cornu et al. has identified this increased risk to be 47% for each additional drug prescribed [14]. Similarly, Stitt et al. refer to a linear relationship between the number of drugs prescribed at discharge and the volume of discrepancies at discharge [20]. A Canadian study has shown an increase in the likelihood of potential drug–drug interactions for patients aged more than 50 years due to the significant increase in the number of medication used per patient [26]. Whilst this finding is not a surprise and follows a simple proportionality association, e.g., the more drugs prescribed, the more drugs errors identified, it is worth noting that this is the case.
Ideally, the same variables would have been collected within each of the 15 studies, and the studies would have been conducted in the same way. This would ensure that a direct comparison would be possible. However, this is not the case, as there are methodological variances between the studies, which, in turn, leads to the variances in the data extracted from the each study. Specifically, the use of non-standard MR processes in Climente-Martí et al. (2010) [13], Cornu et al. (2012) [14], Paiboonvong et al. (2009) [19] and Herrero-Herrero et al. (2010) [21] is a further limitation.
One of the crucial differences between the studies is the way in which discrepancies were designated to be “intentional” or “unintentional”. In most studies, a panel including physicians and pharmacists decided if a discrepancy qualified as intentional or unintentional. This allowed for a range of healthcare professionals to be involved and, hence, is more likely to imitate usual care and take into account the views and knowledge of a range of stakeholders. In Herrero-Herrero et al. [21], the treating physician was solely in charge of performing the medication reconciliation, which could lead to a potential bias in the error-reporting mechanism. These differences in the classification systems and the level of consensus involved in the reporting may account for the variation of the results in between studies. To conduct a research study on medication, reconciliation guidelines regarding inclusion and exclusion of patients have to be structured. Ideally, these criteria are made to ensure that the study population reflects the population that is of interest. In the study conducted by Pippins et al., patients with “short stays” at the ward were not included; the definition of a short stay was not specified in the article, but this could lead to an overestimate of discrepancies, because only those patients who were relatively more complex (and hence, had a longer stay) were included [17]. On the other hand, the exclusion of patients from nursing homes and patients taking more than five drugs could potentially lead to a significantly lower number of both MEs and discrepancies than would otherwise be the case [1,10,27].
For the six prospective studies included in this review, it is important to consider the Hawthorne effect, as suggested by Grimes et al. [24]. This effect can result in modified behaviour of those under observation and, hence, may distort the findings; potentially leading to an underestimate of the errors found.
By comparison of the preadmission medication list against the discharge medication list, discrepancies are identified. After a discrepancy is identified, it might lead to an ME, but this is not always the case. For example, new medications appearing on the discharge list (compared to the admissions list) would be categorised as an intentional discrepancy, but not an ME. Focusing on unintentional discrepancies only, the results of Allende Bandrés et al. [1] (20%) could have been unrealistically low due to the exclusion of patients taking more than five drugs at discharge and the recording of unjustified/undocumented discrepancies only. In the same way, Bjeldbak-Olsen et al. [22] may have overestimated the number of discrepancies by including both intentional and unintentional discrepancies, thereby reporting 86.7% discrepancies at discharge, which is higher than most studies. As the range of discrepancies varies widely and is not uniformly reported, the median value (60%) is possibly the most useful.
The variation in the inclusion and exclusion criteria of the studies examined further contributes to the wide range of reported discrepancies at discharge. If only simple (versus multi-morbid) patients treated with fewer than five medications are included, the number of discrepancies was lower [14]. The average number of discrepancies detected per patient varies from 1.2–5.3, although five of the seven studies that measured average discrepancy per patient found it to be around 2–3. This implies that the majority of patients who leave hospital may have more than one medication discrepancy and, therefore, could be at risk of an ME. This is supported by other studies that state that the likelihood of an ME or potential adverse drug events (PADE) increases for patients with medication discrepancies [17,28]. In addition, the variation in the geographical location of the studies under consideration may also contribute to the differences observed.
The most common discrepancy described in the literature is omission of medication. Omission was found to be the reason for discrepancies in up to 56% of the cases in one study [19]. The other major reasons for discrepancies were inaccuracies related to route/frequency/dose of medicines; one study found that these three factors were the reason for up to 44% of the discrepancies [19]. These findings are supported by other studies, where the main reasons identified for discrepancies in medical history were identified as omitted medication, as well as inconsistencies in route/frequency/dose [29,30].
The therapeutic group most frequently associated with errors regarding medication reconciliation are cardiovascular system (CVS) drugs [1]. The frequency of errors due to CVS drugs was between 20% and 34% [1,13]. The prevalence of cardiovascular diseases (CVD) worldwide is increasing, and some even describe CVD as an epidemic [31]. Many CVD patients are treated with multiple drugs, which increases the risk of ME [32]. Other therapeutic classes involved in errors during medication reconciliation are central nervous system (CNS) drugs (21%) [20] and gastrointestinal (GI) drugs (8%–20%) [10,14]. An Irish study was conducted based on the Health Service Executive (HSE)-Primary care reimbursement services (PCRS) pharmacy database. HSE-PCRS provides free or reduced health services to an estimated 1.2 million people in the Republic of Ireland (accounting for approximately 26% of the total population). This study found that the four most common therapeutic areas that patients were treated for were CVS, CNS, musculoskeletal and GI. Furthermore, this study estimated that three-quarters of the elderly population (defined in this dataset as those aged greater than 70 years) suffer from two or more chronic diseases [33]. The Institute for Safer Medication Practices (ISMP), a non-profit organization in the United States of America working for increased patient safety, has made a list of high-risk drugs according to the Anatomical Therapeutic Chemical Classification system (ATC). When looking at this list, more than 50% of the drugs on the list belong to the groups N (nervous system) and C (cardiovascular system) in the ATC drug classification system. This is due to the greater risk of causing harm if errors are made with this drugs [34]. Not all of the articles have made it clear what types of therapeutics are involved in errors. The types of drug and the frequency of discrepancy most likely change from ward to ward. Studies suggest that specialised wards, e.g., GI versus a general medical ward, tend to be associated with fewer errors, as they usually have a more limited range of illness-specific medicines, and staff at these wards is more experienced in their prescribing [21].
4. Conclusions
In the studies reviewed, between 20% and 87% of patients encounter discrepancies at discharge. This shows that there is a problem and one that the healthcare system needs to address. Unquestionably, the number of discrepancies per patient and the types of drugs will differ not only between hospitals, but also between wards at the hospital. A key finding is that as the number of drugs increases, so too does the risk of discrepancies, putting patients with multi-morbid conditions and receiving more than one drug at greater risk. The reasons for medical discrepancies differ, but the most common was related to omission of medication together with discrepancies in route/frequency/dose.
Author Contributions
Laura J Sahm and Paul McCague developed the initial concept in consultation with Maja Michaelsen and Colin Bradley. Maja H Michaelsen performed the article search, having defined keywords, inclusion and exclusion criteria with Laura J Sahm and Paul McCague. Results were discussed amongst all authors; Maja Michaelsen, Paul McCague, Colin Bradley and Laura J Sahm and consensus was achieved on which key results should be displayed.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Allende Bandres, M.A.; Arenere Mendoza, M.; Gutierrez Nicolas, F.; Calleja Hernandez, M.A.; Ruiz La Iglesia, F. Pharmacist-led medication reconciliation to reduce discrepancies in transitions of care in Spain. Int. J. Clin. Pharm. 2013, 35, 1083–1090. [Google Scholar] [CrossRef] [PubMed]
- Cawthon, C.; Walia, S.; Osborn, C.Y.; Niesner, K.J.; Schnipper, J.L.; Kripalani, S. Improving care transitions: The patient perspective. J. Health Commun. 2012, 17, 312–324. [Google Scholar] [CrossRef] [PubMed]
- Andel, C.; Davidow, S.L.; Hollander, M.; Moreno, D.A. The economics of health care quality and medical errors. J. Health Care Financ. 2012, 39, 39–50. [Google Scholar]
- Mallow, P.J.; Padya, B.; Horblyuk, R.; Kaplan, H.S. Prevalence and cost of hospital medical errors in the general and elderly United States populations. J. Med. Econ. 2013, 16, 1367–1378. [Google Scholar] [CrossRef] [PubMed]
- Ferner, R.E.; Aronson, J.K. Clarification of terminology in medication errors: definitions and classification. Drug Saf. 2006, 29, 1011–1022. [Google Scholar] [CrossRef] [PubMed]
- Bates, D.W.; Boyle, D.L.; Vander Vliet, M.B.; Schneider, J.; Leape, L. Relationship between medication errors and adverse drug events. Gen. Intern. Med. 1995, 10, 199–205. [Google Scholar] [CrossRef]
- Knez, L.; Suskovic, S.; Rezonja, R.; Laaksonen, R.; Mrhar, A. The need for medication reconciliation: A cross-sectional observational study in adult patients. Respir. Med. 2011, 105, S60–S66. [Google Scholar] [CrossRef]
- Frydenberg, K.; Brekke, M. Poor communication on patients’ medication across health care levels leads to potentially harmful medication errors. Scand. J. Primary Health Care 2012, 30, 234–240. [Google Scholar] [CrossRef] [PubMed]
- Ziaeian, B.; Araujo, K.L.; van Ness, P.H.; Horwitz, L.I. Medication reconciliation accuracy and patient understanding of intended medication changes on hospital discharge. J. Gen. Intern. Med. 2012, 27, 1513–1520. [Google Scholar] [CrossRef] [PubMed]
- Karapinar-Carkit, F.; Borgsteede, S.D.; Zoer, J.; Smit, H.J.; Egberts, A.C.; van den Bemt, P.M. Effect of medication reconciliation with and without patient counseling on the number of pharmaceutical interventions among patients discharged from the hospital. Ann. Pharmacother. 2009, 43, 1001–1010. [Google Scholar] [CrossRef] [PubMed]
- Institution for Healthcare Improvment. How-to- Guide: prevent Adverse Drug Events by Implementing Medication Reconciliation. Available online: http://www.texashospitalquality.org/collaboratives/partnership_for_patients/pfp_resources/pfp_2012_conference_documents/adverse_drug_events/4_HowtoGuidePreventADEs.pdf (accessed on 16 June 2015).
- Joint Commission on Accreditation of Healthcare Organizations, USA. Using medication reconciliation to prevent errors. Sentin. Event Alert 2006, 23, 1–4. [Google Scholar]
- Climente-Marti, M.; Garcia-Manon, E.R.; Artero-Mora, A.; Jimenez-Torres, N.V. Potential risk of medication discrepancies and reconciliation errors at admission and discharge from an inpatient medical service. Ann. Pharmacother. 2010, 44, 1747–1754. [Google Scholar] [CrossRef] [PubMed]
- Cornu, P.; Steurbaut, S.; Leysen, T.; de Baere, E.; Ligneel, C.; Mets, T.; Dupont, A.G. Effect of medication reconciliation at hospital admission on medication discrepancies during hospitalization and at discharge for geriatric patients. Ann. Pharmacother. 2012, 46, 484–494. [Google Scholar] [CrossRef] [PubMed]
- Vira, T.; Colquhoun, M.; Etchells, E. Reconcilable differences: correcting medication errors at hospital admission and discharge. Qual. Saf. Health Care 2006, 15, 122–126. [Google Scholar] [CrossRef] [PubMed]
- Kripalani, S.; Roumie, C.L.; Dalal, A.K.; Cawthon, C.; Businger, A.; Eden, S.K.; Shintani, A.; Sponsler, K.C.; Harris, L.J.; Theobald, C.; et al. Effect of a pharmacist intervention on clinically important medication errors after hospital discharge: a randomized trial. Ann. Intern. Med. 2012, 157, 1–10. [Google Scholar] [CrossRef] [PubMed]
- Pippins, J.R.; Gandhi, T.K.; Hamann, C.; Ndumele, C.D.; Labonville, S.A.; Diedrichsen, E.K.; Carty, M.G.; Karson, A.S.; Bhan, I.; Coley, C.M.; et al. Classifying and predicting errors of inpatient medication reconciliation. J. Gen. Intern. Med. 2008, 23, 1414–1422. [Google Scholar] [CrossRef] [PubMed]
- Salanitro, A.H.; Osborn, C.Y.; Schnipper, J.L.; Roumie, C.L.; Labonville, S.; Johnson, D.C.; Neal, E.; Cawthon, C.; Businger, A.; et al. Effect of patient- and medication-related factors on inpatient medication reconciliation errors. J. Gen. Intern. Med. 2012, 27, 924–932. [Google Scholar] [CrossRef] [PubMed]
- Paiboonvong, T.M.; Montakantikul, P.; Chansirkarnjana, S.; Trangulpiankit, P. Incidence of Medication Errors in Medication Reconciliation at General Medical Wards, Ramathibodi Hospital. J. Pharm. Sci. 2009, 36, 44–49. [Google Scholar]
- Stitt, D.M.; Elliott, D.P.; Thompson, S.N. Medication discrepancies identified at time of hospital discharge in a geriatric population. Am. J. Geriatr. Pharmacother. 2011, 9, 234–240. [Google Scholar] [CrossRef] [PubMed]
- Herrero-Herrero, J.I.; Garcia-Aparicio, J. Medication discrepancies at discharge from an internal medicine service. Eur. J. Intern. Med. 2011, 22, 43–48. [Google Scholar] [CrossRef] [PubMed]
- Bjeldbak-Olesen, M.; Danielsen, A.G.; Tomsen, D.V.; Jakobsen, T.J. Medication reconciliation is a prerequisite for obtaining a valid medication review. Dan. Med. J. 2013, 60, A4605. [Google Scholar] [PubMed]
- Geurts, M.M.; van der Flier, M.; de Vries-Bots, A.M.; Brink-van der Wal, T.I.; de Gier, J.J. Medication reconciliation to solve discrepancies in discharge documents after discharge from the hospital. Int. J. Clin. Pharm. 2013, 35, 600–607. [Google Scholar] [CrossRef] [PubMed]
- Grimes, T.C.; Duggan, C.A.; Delaney, T.P.; Graham, I.M.; Conlon, K.C.; Deasy, E.; Jago-Byrne, M.C.; O’Brien, P. Medication details documented on hospital discharge: Cross-sectional observational study of factors associated with medication non-reconciliation. Br. J. Clinical Pharmacol. 2011, 71, 449–457. [Google Scholar] [CrossRef] [PubMed]
- Suresh, K.; Chandrashekara, S. Sample size estimation and power analysis for clinical research studies. J. Hum. Reprod. Sci. 2012, 5, 7–13. [Google Scholar] [CrossRef] [PubMed]
- Tseng, A.; Szadkowski, L.; Walmsley, S.; Salit, I.; Raboud, J. Association of age with polypharmacy and risk of drug interactions with antiretroviral medications in HIV-positive patients. Ann. Pharmacother. 2013, 47, 1429–1439. [Google Scholar] [CrossRef] [PubMed]
- Hovstadius, B.; Hovstadius, K.; Astrand, B.; Petersson, G. Increasing polypharmacy—An individual-based study of the Swedish population 2005–2008. BMC Clin. Pharmacol. 2010, 10, 16. [Google Scholar] [CrossRef] [PubMed]
- Turple, J.; MacKinnon, N.J.; Davis, B. Frequency and type of medication discrepancies in one tertiary care hospital. Healthc. Q. 2006, 9, 119–123. [Google Scholar] [CrossRef] [PubMed]
- Lisby, M.N.; Nielsen, L.P.; Mainz, J. Errors in the medication process: Frequency, type and potential clinical consequences. Int. J. Qual. Health Care 2005, 17, 15–22. [Google Scholar] [CrossRef] [PubMed]
- Nickerson, A.; MacKinnon, N.J.; Roberts, N.; Saulnier, L. Drug-therapy problems, inconsistencies and omissions identified during a medication reconciliation and seamless care service. Healthc. Q. 2005, 8, 65–72. [Google Scholar] [CrossRef] [PubMed]
- Gersh, B.S.; Sliwa, K.; Mayosi, B.M.; Yusuf, S. The epidemic of cardiovascular disease in the developing world: global implications. Eur. Heart J. 2010, 31, 642–648. [Google Scholar] [CrossRef] [PubMed]
- Volpe, M.; Chin, D.; Paneni, F. The challenge of polypharmacy in cardiovascular medicine. Fundam. Clin. Pharmacol. 2010, 24, 9–17. [Google Scholar] [CrossRef] [PubMed]
- Naughton, C.; Bennett, K.; Feely, J. Prevalence of chronic disease in the elderly based on a national pharmacy claims database. Age Ageing 2006, 35, 633–636. [Google Scholar] [CrossRef] [PubMed]
- ISMPs List of High-Alert Medications. Available online: http://www.ismp.org/tools/highalertmedications.pdf (accessed on 3 March 2014).
© 2015 by the authors; licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution license (http://creativecommons.org/licenses/by/4.0/).