


Abstract
Neuropathic pain is a chronic disorder that arises from damaged or malfunctioning nerves. Hypersensitivity to stimuli, also known as hyperalgesia, can cause a person to experience pain from non-painful stimuli, termed allodynia. Cannabis-based medicines (CBMs) may provide new treatment options to manage neuropathic pain. A review of the relevant studies was conducted to evaluate the effectiveness of CBMs in treating neuropathic pain. Scientific literature was systematically searched from January 2003 to December 2024 using the Web of Science Core Collection, PubMed, and MEDLINE. A total of 22 randomized controlled trials (RCTs) were identified that considered the use of 1′,1′-dimethylheptyl-Δ8-tetrahydrocannabinol-11-oic acid (CT-3), Δ9-tetrahydrocannabinol (Δ9-THC), cannabidiol (CBD), combinations of Δ9-THC with CBD, and cannabidivarin for treatment of neuropathic pain. Significant reductions in pain were reported in 15 studies focused on the treatment of multiple sclerosis, spinal cord injuries, diabetic neuropathy, postherpetic neuralgia, HIV-associated sensory neuropathy, peripheral neuropathic pain, complex regional pain syndrome, chronic radicular neuropathic pain, and peripheral neuropathy of the lower extremities. These positive outcomes often adopted personalized and adjusted dosing strategies. By contrast, seven RCTs observed no significant pain relief compared to placebo, although some had minor improvements in secondary outcomes, such as mood and sleep. Collectively, CBM treatments may improve pain scores, but study limitations such as small sample sizes and study durations, high placebo response rates, and trial unblinding because of the psychoactive effects of cannabinoids all hinder data interpretation and the extrapolation to chronic pain conditions. Hence, future RCTs will need to have larger numbers and be more extended studies that explore optimal dosing and delivery methods and identify patient subgroups that are most likely to benefit. While CBMs show potential, their current use balances modest benefits against possible adverse effects and variable outcomes.
1. Introduction
Pain is a condition that includes both sensory and emotional experiences and is commonly a sign of tissue injury, with an intensity and duration that can differ among individuals [1]. Different factors can influence the experience of pain, including its location, intensity, and underlying cause [1]. Activation of nociceptors (from tissue damage) mediated by sensory channels and receptors drives nociceptive pain [2,3]. Tissue injury triggers the release of inflammatory mediators and cytokines, as well as prostanoids and leukotrienes from arachidonic acid that activate or sensitize nociceptor channels, lowering their thresholds and enhancing signaling, resulting in peripheral sensitization [4,5]. Nociceptive pain is primarily treated with non-steroidal anti-inflammatory drugs (NSAIDs) such as aspirin, ibuprofen, and diclofenac, which act by inhibiting the cyclo-oxygenase (COX) enzymes that produce prostaglandins from arachidonic acid [3].
Neuropathic pain is a complicated and long-lasting condition caused by damaged or malfunctioning nerves and affects approximately 7–10% of the population [3,5,6]. Hypersensitivity to pain stimuli (hyperalgesia) can cause a person to experience pain from non-painful stimuli as well (allodynia) [7]. Diseases that can impact the peripheral and central somatosensory neurons can lead to chronic pain [6] and have been the focus of research on how to manage as well as treat it [6,8]. Managing neuropathic disorders can be difficult and, without proper pain control, can harm a patient’s quality of life. Nevertheless, the precise mechanisms underlying neuropathic pain are not completely understood, making it challenging to treat effectively using conventional pain relievers [6,8,9].
Assessing and diagnosing neuropathic pain can also be a difficult and time-consuming process [10]. Peripheral nerve injury can result in persistent and chronic pain, and this condition (maladaptive pain) can be promoted by neuroinflammation, including activation of macrophages and T-lymphocytes, and release of cytokines and chemokines—factors that may normally promote healing and regeneration [9,11]. The nervous system is affected by neuropathic pain injury, with increased excitatory and decreased inhibitory nerve activities [12]. Chronic pain significantly impacts the quality of life, emphasizing the need for personalized medication and treatment approaches [13].
Several different classes of medications are used to treat neuropathic pain. Antidepressants, including tricyclic antidepressants (TCAs), such as amitriptyline, and serotonin-norepinephrine reuptake inhibitors (SNRIs), such as duloxetine, are first-line pharmacotherapies that can influence neurotransmitter levels and result in reduced pain in responsive patients [8,12,13,14,15,16,17]. Other first-line treatments include the use of anticonvulsants such as carbamazepine, pregabalin, and gabapentin (gabapentinoids) that bind to calcium channels and inhibit calcium currents, thereby reducing excitatory transmitter release and spinal sensitization [17,18,19,20]. Gabapentinoids may also elicit secondary effects that limit neuroinflammation to relieve chronic pain [17,18,19,20]. Topical medications such as lidocaine plasters, which locally block sodium channels, and high-dose capsaicin patches, which desensitize nociceptive fibers via Transient Receptor Potential Vanilloid 1 (TRPV1) receptor overstimulation, are considered second-line therapies [6,8,12,17,19,20,21]. Due to risks of tolerance and dependence, opioids are reserved as a third-line option. Opioids primarily act on µ-opioid receptors to modulate pain transmission [16]. NSAIDs are also utilized for the treatment of neuropathic pain, although their efficacy is equivocal [22,23,24].
The management of patients with neuropathic pain can require a non-pharmacological approach used in conjunction with pharmacological therapies [6,8,16]. However, there is a need for guidelines for treatment and a comprehensive algorithm for primary physicians that should consider alternative approaches, such as non-opioid pharmacological management, and interventional therapies such as neurostimulation. Collectively, a treatment pathway that considers optimal drug delivery and non-pharmacological adjuvant therapies such as physiotherapy and cognitive behavioral therapy (CBT) [17,20] will assist with the development of personalized therapy that considers patient responsiveness.
The medical use of cannabis is the subject of an ongoing general and legal debate and controversy. Cannabis-based medicines (CBMs) (cannabinoids) may provide analgesia for managing nociceptive and chronic pain by influencing the activity of endogenous receptors, ion channels, and enzymes [21]. The endocannabinoid system consists of two primary cannabinoid receptors: cannabinoid 1 (CB1) and cannabinoid 2 (CB2) receptors. CB1 receptors are mainly localized to the brain, while CB2 receptors are primarily present in peripheral tissues and immune cells, including brain microglia [25,26]. CB1 activation by cannabinoids can lead to analgesic effects and pain relief [25,26,27], and likewise, activation of CB2 receptors is linked to analgesic effects and pain management [25,26,28]. However, the pharmacological composition of CBMs varies, as do their modes of action. Δ9-Tetrahydrocannabinol (THC) works as a partial agonist at the CB1 and CB2 receptors [29]. The non-psychoactive analog of THC, cannabidiol (CBD), is a CB1 and CB2 receptor antagonist and a negative allosteric modulator of CB1 receptors [29] and has analgesic effects by modulating the activity of non-cannabinoid targets such as TRPV1 ion channels, 5-hydroxytryptamine 1A (5-HT1A receptors), and peroxisome proliferator-activated receptors (PPARs) [21]. Cannabidivarin (CBDV), a homolog of CBD, also has neuromodulatory properties, including potential binding to TRPV family members (which may activate and then desensitize these receptors [30]) and acts as an antagonist of Toll-like receptor 4 (TLR4) to influence neuroinflammation [31].
Currently, there is insufficient data to confirm the use of CBMs as an alternative to opioids for treating chronic pain in patients who depend on opioids for pain management [32]. In addition, CBMs can cause adverse reactions, including psychotropic effects associated with activation of CB1 receptors. Hence, there is a need to consider optimal dosing that is safe and tolerable without the initiation of adverse effects, and this may require titration to determine effective cannabinoid ratios and an appropriate route of administration [33]. Ultimately, there may be potential harm that is greater than the benefit of using a CBM, notably in vulnerable populations such as elderly patients [32,34]. In order to assess the effectiveness of CBMs in treating neuropathic pain and their potential for induction of adverse effects, a systematic review was conducted on studies published in the last 20 years.
2. Materials and Methods
This review was conducted in accordance with the PRISMA guidelines [35]. The search utilized the Web of Science Core Collection, PubMed, and MEDLINE databases. The search period ranged from 1 January 2003, to 30 December 2024 and included search terms related to cannabis, neuropathic pain, interventions, and study types. A full list of the search terms and combinations thereof is included in Table 1. This study considered human clinical trials that used cannabis for treating neuropathic pain and for which the study outcomes were published in English and within the last 20 years. Exclusion criteria included a lack of full-text or evidence-based studies and guidelines that did not address cannabis interventions for neuropathic pain. Studies that were case or clinical case reports, animal (in vivo) and in vitro studies, as well as studies that focused on recreational cannabis use, were excluded. Both the first and last authors independently reviewed all the included papers, considered the data extraction, and discussed all papers that were included in the final review. Due to the qualitative nature and heterogeneity of study outcomes, a meta-analysis was not performed. This review was conceived by the first and last authors and was not registered in a public registry.
Table 1.
The medical databases and search terms used for the systematic review.
3. Results
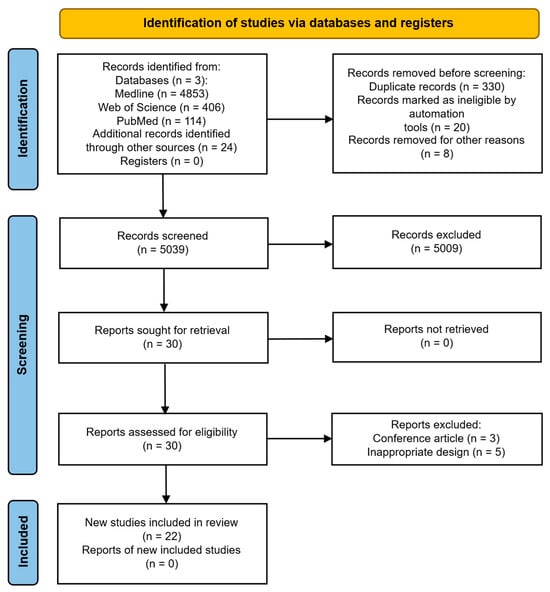
A search of the Web of Science Core Collection, PubMed, and MEDLINE databases, covering the period from 1 January 2003 to 30 December 2024, yielded a total of 5397 papers. After conducting a screening for eligibility and removing duplicates, as well as papers not written in English and irrelevant case reports, 22 studies were deemed to meet the inclusion criteria (Figure 1).
Figure 1.
PRISMA flow chart.
The inclusion criteria for this review were defined according to the PICOS framework [36] and are listed in Table 2. The study considered adult patients of both genders who were suffering from mild to severe neuropathic pain of different etiologies and aimed to assess if a CBM provided pain relief. For each of the studies that met the inclusion criteria, extracted data included the study authors, dates of the research, types of CBMs employed, treatment length, dosages, participation of control groups, and the outcomes of each study, including the key findings and an assessment of medication effectiveness as well as adverse effects. Studies are included in Table 3 and ordered by ascending year of publication.
Table 2.
PICOS (population, intervention, comparison, outcome, setting) criteria for study inclusion [36].
Table 3.
RCTs that investigated the efficacy of CBM as a treatment for neuropathic pain.
The study characteristics of the RCTs, including study size, patient demographics, and analgesic use, are included in Table 4.
Table 4.
Study and participant characteristics for RCTs that investigated the efficacy of CBM as a treatment for neuropathic pain.
All eligible studies were assessed for quality and risk of bias (Supplementary Figure S1) [60]. Nineteen of the RCTs reported adequate methods of random sequence generation, indicating a low risk of selection bias in randomization [37,38,39,40,41,42,43,47,48,49,50,51,52,53,54,55,56,57,59]. Additionally, 20 RCTs described appropriate allocation concealment, reflecting a low risk of selection bias in treatment allocation [37,38,39,40,41,42,43,44,47,48,49,50,51,53,54,55,56,57,58,59].
Fifteen RCTs reported blinding of participants and personnel, indicating a low risk of performance bias. Fourteen of these studies also described blinded outcome assessment, corresponding to a low risk of detection bias. The trials with adequate blinding procedures included [37,39,40,41,43,47,49,51,52,53,54,55,56,57,58,59].
Fourteen RCTs exhibited a low risk of attrition bias, suggesting that incomplete outcome data were adequately addressed [37,38,39,42,44,47,49,50,51,52,53,56,58,59]. Nineteen studies were at low risk of selective reporting bias, implying no evidence of outcomes being omitted or selectively reported [37,38,40,41,42,43,44,46,47,48,49,50,51,52,53,56,57,58,59].
4. Discussion
This review considered 22 RCTs that investigated the benefit of CBMs for the management of neuropathic pain. The CBMs used were 1′,1′-dimethylheptyl-Δ8-tetrahydrocannabinol-11-oic acid (CT-3), Δ9-THC (including dronabinol), CBD, nabiximols (sold under the brand name Sativex®) (a 1:1 Δ9-THC:CBD formulation), and CBDV. Treatment duration varied from acute administration (hours) to several weeks, with the majority of studies using a randomized, double-blinded, placebo-controlled (crossover) design, often referred to as the gold standard for clinical trials [61]. Nevertheless, limitations such as small sample sizes and brief study durations were prevalent. Notwithstanding these constraints, numerous studies reported positive outcomes in pain alleviation, although results were inconsistent and there were frequently observed adverse effects, including dizziness and cognitive impairment. Of the 22 studies examined, 15 reported some favorable outcomes and significant declines in pain for the CBM intervention [37,38,39,40,41,42,43,44,46,47,49,50,51,52,57], whereas seven studies demonstrated no statistically significant benefits for defined markers of pain management across the examined cohort from the CBM intervention [45,48,53,54,55,56,58,59].
4.1. Efficacy of CBMs in Neuropathic Pain Management
The 15 studies that reported reduced pain intensity for patients that experienced a range of central and peripheral neuropathic pain from conditions including spinal cord injuries [37,43,47,50], brachial plexus avulsion (BPA) [38], multiple sclerosis (MS) [39,40,43,46,47], postherpetic neuralgia [41,47], HIV-associated sensory neuropathy [42,44], diabetic neuropathy [43,47,49], postsurgical and post-traumatic neuropathic pain [46], peripheral neuropathy [52], and chronic radicular neuropathic pain [51,57], conditions that can exhibit resistance to conventional analgesics including opioids and anticonvulsants.
1′,1′-Dimethylheptyl-Δ8-tetrahydrocannabinol-11-oic acid (CT-3), a synthetic cannabinoid and analog of THC-11-oic acid, reduced chronic neuropathic pain in patients with hyperalgesia and allodynia [37]. Treatment with Sativex (a Δ9-THC:CBD oromucosal spray) produced significant reductions in pain intensity and improvements in sleep for patients with BPA [38], MS [40], and patients with peripheral neuropathic pain, including those with allodynia [41]. Orally administered dronabinol (Δ9-THC) provided pain relief for patients with MS [39]. Smoked and vaporized cannabis (Δ9-THC) was effective at pain reduction for patients with HIV-associated sensory neuropathy [42,44]; patients with a range of central and peripheral sources [43,47], postsurgical and post-traumatic neuropathic pain [46], diabetic neuropathy [49], and spinal cord injury [50]. Topically applied (transdermal) CBD oil demonstrated significant pain relief for patients with peripheral neuropathy of the lower extremities [52]. Sublingual administration of Δ9-THC was effective at pain reduction for patients with chronic radicular neuropathic pain [51,57]. Accordingly, CBMs may benefit a range of central and peripheral neuropathic pain conditions, but the efficacy could also be influenced by the mechanisms underlying the neuropathic pain, including aberrant signaling in damaged nerves.
Regarding dosage administration, a flexible or titrated approach was employed across several of the studies that recorded improvements in pain for the CBM treatment [38,40,41,44,47,50]. For example, patients utilizing Sativex were permitted to self-titrate their doses up to a maximum of 48 sprays per day (equivalent to 129.6 mg Δ9-THC and 120 mg CBD), although the majority of patients achieved pain relief with fewer sprays (a mean of 9.6 sprays per day) [40]. This individualized dosing strategy can potentially optimize efficacy and balance tolerability, as higher doses often result in increased adverse effects such as dizziness or xerostomia [40,41]. For oral cannabinoid administration, such as dronabinol, doses were typically initiated at low levels (e.g., 2.5 mg/day) and were progressively increased up to 10 mg daily [39]; a gradual dose escalation that facilitated the minimization of adverse effects and can still provide clinically significant reductions in spontaneous pain intensity compared to placebo [39,62].
The route of administration could influence the efficacy of CBMs. CT-3, delivered orally, was efficacious, although patients consumed up to eight capsules per day (two daily doses of 4 × 10 mg capsules) during the treatment phase [37]. Similarly, orally administered dronabinol (Δ9-THC) (doses of up to 10 mg per day) was also efficacious and resulted in a modest yet clinically meaningful reduction in median pain intensity for MS patients [39]. CT-3 (peak plasma concentration within approximately 1–2 h, though occasionally delayed up to 4–5 h) and dronabinol (peak plasma concentration 2 to 4 h) [37,63,64,65] can provide effective pain relief after oral administration, and oral dosing could be optimized to align with these pharmacokinetic profiles to ensure sustained peak plasma concentrations.
Oromucosal administration, as exemplified by Sativex sprays (a Δ9-THC:CBD (1:1) mixture), emerged as a promising method for effective CBM delivery and beneficial analgesia in some studies [38,40,41], although for Berman et al. [38], administration of the CBM did not reach the primary goal of a two-point reduction in pain. Administering drugs through the oromucosal route allows for rapid absorption through the mucous membranes and a quick onset of analgesic effects [38]. This delivery method can reduce gastrointestinal and hepatic first-pass metabolism, leading to increased bioavailability and thereby improving plasma drug concentrations compared to oral administration [65,66,67]. This method also provides flexibility in dose titration, which could potentially contribute to improved patient adherence and overall treatment satisfaction. Inhalation methods (such as vaporization or smoking) also facilitate pain relief [42,43,46,47,49,50], and this can be within minutes due to the expeditious absorption of cannabinoids into the bloodstream [66,68,69] and can therefore be particularly beneficial for acute exacerbations of chronic pain. Nevertheless, while efficacious for symptom management, inhalation methods also elicit concerns regarding potential respiratory adverse effects associated with prolonged usage. However, because vaporization avoids direct combustion [43,47,49,50], it may mitigate some of the long-term respiratory concerns linked to smoking (and its associated xenobiotics) while preserving the rapid absorption of cannabinoids. Similar to the oromucosal route, sublingual administration provides a rapid delivery method of Δ9-THC to the blood via diffusion through tissues under the tongue and can provide effective and relatively rapid pain relief [51,57], as well as bypass hepatic metabolism and improve bioavailability [70].
4.2. Ineffectiveness of CBMs in Neuropathic Pain Management
Seven RCTs that evaluated CBMs for neuropathic pain all failed to demonstrate significant efficacy [45,48,53,54,55,56,58,59], and these were in addition to the study of Berman et al. [38], which reported a significant improvement in pain, but one that did not reach its clinical target. Sativex did not significantly improve primary pain outcomes for diabetic peripheral neuropathy, and there were no notable differences in secondary outcomes that included quality-of-life assessments [45]. Nabiximols were ineffective for chemotherapy-induced neuropathic pain, although a subgroup of five participants (31.5% of the cohort) experienced clinically meaningful pain reduction [48]. CBDV, although well-tolerated, was ineffective at reducing pain in patients suffering from HIV-associated neuropathy [53]. Similarly, neither Δ9-THC, CBD, nor their combination showed significant efficacy in alleviating neuropathic pain or spasticity in patients with MS or SCI or patients suffering from polyneuropathy, postherpetic neuralgia, and nerve damage [54,55,56], and sublingual THC:CBD oil (1:1 ratio) did not produce a clinically meaningful reduction in pain intensity for traumatic brachial plexus injuries, although minor improvements were observed in sleep quality [59]. Topically applied CBD cream was ineffective for pain relief measures in patients with chemotherapy-induced peripheral neuropathy [58].
Hence, these studies indicate that CBMs can have limited and inconsistent effectiveness in managing some neuropathic pain conditions, although this could in part reflect the disease and the mechanism of pain, and that only specific subgroups of patients may benefit from the treatment.
4.3. Limitations of the RCTs
4.3.1. Sample Size and Design
A limitation of the majority of the conducted RCTs is the small sample size (refer to Table 4), which can restrict the detection of effects and limit the ability to generalize the findings to larger cohort sizes. Furthermore, some studies utilized brief treatment durations (refer to Table 3), reducing applicability to long-term (chronic) conditions and the associated safety and efficacy considerations. There were differences between study dosing regimens, with some allowing participants to self-titrate the CBM [38,40,41,44,47,50], which introduces dosing variability and will reduce the standardization of exposure and the potential for comparison between studies. Crossover designs were employed in most of the studies [37,38,39,43,44,46,47,48,49,50,52,53,57,58,59], which, while advantageous for comparing treatments within individuals, are potentially susceptible to carryover effects if washout periods are inadequate or omitted, potentially confounding the results. Furthermore, the lipophilicity of cannabinoids such as THC and CBD can result in distribution to, and potential accumulation within, fatty tissue and an extension of their elimination [63,65]. As a result, some crossover trials for CBMs implemented washout periods of one to approximately three weeks to promote a return to baseline measurements before starting the next treatment [37,39,44,46,51,53,57,59]. Nevertheless, some trials used relatively short or no washout periods (refer to Table 3), which may increase the risk of lingering pharmacodynamic or pharmacokinetic effects from one period carrying over to the next, such that residual plasma concentrations or psychoactive effects could potentially interfere with the outcomes of later treatment phases. This emphasizes the importance of ensuring that the duration of the washout period corresponds appropriately with cannabinoid pharmacokinetics and the specific requirements of the study design. Studies also encountered attrition rates (refer to Table 4), which can diminish study outcomes due to incomplete data sets from all participants.
4.3.2. Dose-Response Relationships
Studies investigating dose-response relationships for CBMs in neuropathic pain management yielded varied results, with higher doses of cannabinoids not always producing a proportionally greater analgesic effect. A comparison of low-dose (3.5% Δ9-THC) and high-dose (7% Δ9-THC) vaporized cannabis cigarettes reported that both doses provided statistically significant pain relief compared to placebo, but without significant differences in analgesia between the treatment groups [43]. A plateau effect was also observed for a comparison between low-dose (1.29% Δ9-THC) and medium-dose (3.53% Δ9-THC) vaporized cannabis, which was also without statistical significance for analgesia between the two study groups [47]; results indicative of a potential ceiling effect in terms of analgesic benefit for this type of CBM when applied to these conditions. For 2.9% and 6.7% Δ9-THC vaporized cannabis, pain relief was dose-dependent, but so was the occurrence of psychoactive side effects in both studies [40,43]. Likewise, while smoked cannabis provided significant pain relief compared to placebo, some participants titrated down from higher Δ9-THC concentrations (8%) to lower doses (2% or 4%) due to adverse effects, suggesting that although higher doses might offer greater analgesia, this needs to be balanced against intolerable adverse effects [44]. Similarly, greater pain relief was observed with higher Δ9-THC concentrations (9.4%) compared to lower concentrations (0% and 2.5%) for treatment of post-traumatic or postsurgical neuropathic pain [46], but intermediate doses (2.5% and 6%) did not provide significantly more relief than placebo, indicating that the dose-response relationship was not evident across all THC concentrations, and the highest Δ9-THC concentrations (9.4%) resulted in the highest number of adverse effects [46]. The administration of vaporized cannabis at low, medium, or high doses (1, 4, or 7% Δ9-THC, respectively) displayed a dose-dependent reduction of pain scores for patients with diabetic peripheral neuropathy, although the pain reductions for the low and medium doses were the same [49].
4.3.3. Study Blinding Challenges
Study blinding is a challenge in clinical trials involving certain CBMs due to the psychotropic effects of Δ9-THC, including euphoria, light-headedness, somnolence, and dizziness [71]. These responses to the CBM may enable participants to discern whether they are receiving the active treatment, potentially introducing bias into study outcomes. Furthermore, despite efforts to match the placebo with the CBM in terms of appearance and taste, side effects were more common with active treatments [37,38,39,40,41,42,44,48,49,50,53,54,55,59], even for agents without psychotropic effects [37]. For a study of dronabinol (Δ9-THC) for MS-associated pain, participants on dronabinol experienced more frequent adverse events, such as dizziness and tiredness, especially during the first week, compared to those on placebo [39], and 67% of the study participants correctly identified having received dronabinol, suggesting potential unblinding [39]. Patients who received a Δ9-THC:CBD oromucosal spray (Sativex for central pain in MS) reported significantly higher adverse effects, such as dizziness, compared to those receiving a placebo [40], and patients who received Sativex for central and peripheral pain conditions experienced more adverse effects in the treatment group [41]. Smoked cannabis was associated with significantly higher side effects, including anxiety, confusion, and sedation [42,44], and 92% of study participants correctly guessed their treatment assignment when they switched to active cannabis, and this likely reflected its psychoactive effects, previous cannabis use, as well as pain relief benefits [44]. The ability to identify the Δ9-THC treatment was influenced by the dose; individuals could not distinguish between a placebo and a low (1.3% Δ9-THC) dose, but at a higher dose (3.5% Δ9-THC), 89% of study participants correctly identified the CBM [47]; results are indicative that the higher Δ9-THC concentrations make it harder to maintain study blinding due to the psychoactive effects. Likewise, adverse effects were more prevalent with high and medium dosing (4 and 7% Δ9-THC, respectively) compared to a placebo [49] and for 6.7% Δ9-THC compared to 2.9% Δ9-THC [50], potentially compromising study blinding. However, adverse effects were similar between the treatment and control (placebo) groups for some studies [51,56].
4.3.4. Pain Measurement Variability
Pain scales are essential tools used in clinical research and practice for evaluating the intensity and impact of pain on patients. However, there were a number of different pain scales utilized in the RCTs, potentially resulting in variability in pain reporting and outcomes (refer to Table 4). The following pain scales were employed: the Visual Analog Scale (VAS) [37,42,43,44,45,47,49,50,51], which comprises a 100 mm horizontal line on which patients indicate their pain level from ‘no pain’ to ‘worst pain ever’; the 11-point ordinal pain severity scale (BS-11) ranging from 0 (‘Best Imaginable’) to 10 (‘Worst Imaginable’) [38]; the Verbal Rating Scale (VRS) in which the VRS utilizes verbal descriptors such as ‘none’, ‘weak’, ‘moderate’, ‘severe’, and ‘excruciating’ to qualitatively assess pain intensity [37]; the 11-point Numerical Rating Scale (NRS-11) [39,40,41,46,48,53,54,55,56], which allows patients to rate their pain from 0 (‘no pain’) to 10 (‘worst possible pain’); the Neuropathic Pain Scale (NPS) [40,42,43,44,45,47,49,50,52], which assesses aspects such as pain intensity, unpleasantness, and specific sensations like burning or tingling; and the Descriptor Differential Scale (DDS) to evaluate pain by rating various descriptors from 0 to 20 points, in which a score of 0 denotes no pain, indicating no intensity or unpleasantness, while a score of 20 represents the most severe pain, reflecting experience of the highest intensity and unpleasantness [44]. In addition to commonly used pain assessment scales, one study utilized methodologies specifically designed to evaluate particular mechanisms, such as the Conditioned Pain Modulation (CPM) paradigm [57]. This approach assesses inhibitory pain pathways by determining the CPM response, calculated as the difference between mean pain intensity ratings of a test stimulus applied alone and ratings recorded when the test stimulus is presented concurrently with a conditioning stimulus. This calculation provides insights into the efficiency of a patient’s pain inhibition mechanisms [57]. A DN4 questionnaire was used to consider the benefit of THC + CBD for traumatic brachial plexus injuries [59]. This DN4 questionnaire categorizes symptoms according to descriptors such as burning, tingling, and electric shock-like sensations, with a score of 4 or higher indicating the presence of neuropathic pain. Lastly, for assessing chemotherapy-induced neuropathy, the EORTC–CIPN20 was used, which evaluates neuropathy symptoms such as pain, tingling, numbness, and functional impairments on a severity scale [58]. Additionally, CIPNAT was employed to assess symptom severity and their impact on daily activities, and the Global Impression of Change scale to capture patient-reported perceptions of improvement, stability, or worsening in neuropathic symptoms following treatment periods [58]. Some of the studies also employed pain measurement scale combinations [37,40,43,44,45,47,50,58], for which a benefit can be the inclusion of quantitative as well as qualitative (descriptive) measures of neuropathic pain.
The variability in pain measurement across clinical trials complicates the direct comparison between results. Moreover, different studies utilized distinct scales and thresholds to evaluate changes in pain intensity and quality. One benchmark used for clinically meaningful pain reduction is a 30% improvement [72], which corresponds to a two-point reduction on the 11-point Pain Intensity-Numerical Rating Scale (PI-NRS) and is considered significant across various chronic pain conditions [72]. However, not all studies considered this threshold when evaluating treatment outcomes. Indeed, significant differences and improvements in pain intensity were observed in Berman et al. [38], but this did not achieve predefined study objectives [38]. Similarly, although improvements in pain levels were recorded for a study of inhaled cannabis, the percentage of patients experiencing at least a 30% reduction in spontaneous pain scores did not differ significantly between the treatment and placebo groups [49]. These discrepancies highlight the need for consistency in applying clinically meaningful thresholds (such as a 30% reduction) to evaluate the effectiveness of pain management interventions and to ensure reliable comparisons between studies.
4.3.5. Neuropathic Pain Diagnosis and Disease Variability
The clinical diagnosis of neuropathic pain exhibits considerable variability across studies due to its diverse etiologies and mechanisms [73]. Neuropathic pain can arise from CNS damage, as observed in MS and SCI, or from peripheral nerve damage, such as in diabetic neuropathy or post-surgical nerve injuries [74,75]. There was some overlap between the study populations (refer to Table 4), although often studies included heterogeneous cohorts with diseases of mixed etiologies.
Research on central neuropathic pain conditions, such as MS and SCI, produced mixed results. In MS, a standardized oromucosal THC:CBD spray (nabiximols) provided significant pain relief [40], and oral Δ9-THC provided modest analgesic benefits, although with variability of response between patients [39]. In trials involving mixed cohorts of patients with neuropathic pain, such as those with MS, SCI, and peripheral neuropathies, smoked or vaporized cannabis resulted in short-term reductions in pain intensity [43,47,50]. However, in contrast, in another study, there were no significant improvements in pain or spasticity when using THC, CBD, or their combination compared to a placebo for patients with MS and SCI [55]. This could reflect patient-specific factors, such as disease progression or concomitant treatments and medications, as these may influence therapeutic outcomes in central neuropathic pain management.
Several studies considered patients with HIV-associated neuropathic pain. Smoked cannabis was effective for pain relief [42,44]; however, the nonpsychoactive cannabinoid, CBDV, was ineffective [53], potentially reflecting a need to engage CB1 receptor activation, which will be minimal when using nonpsychoactive cannabinoids.
For Diabetic Peripheral Neuropathy (DPN), inhaled cannabis (Δ9-THC) for patients with refractory DPN had dose-dependent analgesic effects, although higher doses resulted in increased cognitive impairment and feelings of intoxication [49]. By contrast, an oromucosal THC:CBD spray (Sativex) did not result in a significant difference between the active treatment and placebo [45], although for this study, depression was a confounding factor influencing patient responses, which could obscure analgesic benefits.
Nabiximols (a THC:CBD oromucosal spray) were ineffective for patients with chemotherapy-induced peripheral neuropathy (CIPN) [48]. However, approximately one-third of the participants were identified as “responders”, achieving a clinically meaningful reduction in pain with a decrease of at least 2 points on a 0–10 scale. Certain individuals may therefore benefit from this cannabinoid treatment despite the overall group effect not being significant, although topical CBD was also ineffective for CIPN patients [58].
Several studies examined neuropathic pain conditions that overlap with the aforementioned studies and/or involved mixed patient populations. Brachial plexus injury, a type of peripheral nerve lesion, can lead to central neuropathic pain features, especially in cases of root avulsion. In patients with brachial plexus root avulsion, a THC:CBD oromucosal extract showed improvements in pain and sleep quality but did not meet the predefined threshold for clinical significance [38]. Approximately 80% of patients in that study opted to continue cannabinoid treatment during an open-label extension, suggesting a perceived benefit despite the modest group-level effect [38]. The treatment of patients with traumatic brachial plexus injuries with sublingual Sativex was also ineffective for reducing neuropathic pain but did improve sleep quality [59].
Δ9-THC administration to patients with chronic radicular pain (such as sciatica from nerve root compression) yielded significant analgesia that was accompanied by altered functional connectivity between pain-processing regions of the brain (notably the anterior cingulate and sensorimotor cortices); importantly, individuals with higher baseline connectivity in these networks experienced greater pain relief, suggesting a neurobiological predictor of the cannabinoid response [51].
Noteworthy is that some RCTs included a mixed population of patients with both central and peripheral causes of neuropathic pain [37,41,43] and therefore considered a diverse group of patients with various sources of neuropathic pain within a single trial. This diversity in the study cohorts could lead to variations in study outcomes, as responses to cannabinoid therapy may change based on the underlying cause of pain. Therefore, it is important to recognize the condition-specific evidence from each group while also considering individual patient factors and overlaps among conditions. This highlights the need for a personalized approach when evaluating and applying CBMs for managing neuropathic pain.
4.3.6. Confounding Factors
Multiple confounding variables could potentially influence the outcomes of studies investigating CBMs for neuropathic pain. Depression, a prevalent comorbidity in patients with chronic neuropathic pain, significantly affects both pain perception and response to treatment. Patients with depression can report higher baseline pain scores and exhibit improvement regardless of whether they receive active treatment or a placebo, thereby complicating the interpretation of treatment efficacy in chronic pain trials [45]. Similarly, there was an observed significant placebo effect on mood and daily functioning during cannabis trials for neuropathic pain, although depression was not specifically identified as a confounding variable in this context [44].
Concurrent therapies and medications also represent a pertinent confounding factor in the RCTs. Due to ethical and clinical considerations, study participants were permitted to continue utilizing other analgesics, such as NSAIDs, opioids, anticonvulsants, and antidepressants, during the trials, and these medications could potentially interact with CBMs and either enhance or diminish their efficacy or simply limit the detection of CBM-based effects due to altered pain intensity baselines. Furthermore, some studies allowed concomitant medications but did not provide details of the medications employed [39,45,50,53].
Recent cannabis users (within 30 days prior) were excluded from one CBM trial [58], and prior (or current) cannabis use was identified as an additional factor influencing study outcomes through its impact on tolerance levels or patient expectations [40,47].
The mechanism of action and route of administration of the CBMs may also influence their efficacy. Since nabiximols (Sativex®) is a THC and CBD mixture, it is hypothesized to involve both cannabinoid receptor signaling and non-cannabinoid pathways, such as TRPV1 receptors, which contribute to the modulation of pain perception [34,68,76]. This receptor diversity could explain why some patients respond better to CBD-rich formulations compared to THC-dominant ones [77]. For instance, inhaled cannabis with varying Δ9-THC concentrations provided dose-dependent reductions in spontaneous and evoked pain in patients with diabetic neuropathy [49]. However, evidence remains inconsistent regarding the comparative benefits of THC versus CBD-dominant formulations. A recent study examining oral THC for chronic radicular neuropathic pain demonstrated modulation of pain inhibitory pathways and autonomic regulation, suggesting that patient-specific neurophysiological factors, including autonomic and supraspinal connectivity changes, could influence treatment response [57]. By contrast, topically applied CBD was without an improvement for chemotherapy-induced pain [58], highlighting uncertainties as to whether formulation, dosage, or delivery methods of cannabinoids might influence their therapeutic effectiveness. The mechanism of action of CBDV is not fully understood but is likely to involve binding to TRPV family members [30] and acts as a TLR4 antagonist to influence neuroinflammation [31].
4.3.7. Legislation and Position Statements on the Use of CBMs for Pain Management
Although some of the studies detailed in this review showed promising results for the use of CBMs as an adjunct to current pain medications for the treatment of neuropathic pain, organizations, such as the International Association for the Study of Pain (IASP), do not endorse the general use of cannabinoids for the treatment of pain due to a lack of sufficient high-quality clinical evidence [78]. There is a country-specific regulation regarding the use of CBMs for medical interventions, and regulatory oversight of clinical trials investigating CBMs is notably stringent, often requiring approvals from multiple regulatory bodies before initiation. For example, a German clinical trial that assessed CBDV for neuropathic pain required authorization from state and federal regulatory authorities, including ethics committees and the German Federal Institute for Drugs and Medical Devices [53]. Similarly, a Danish multicenter trial investigating CBMs for neuropathic pain and spasticity was required to obtain clearance from the Danish Medicines Agency, regional ethics committees, and data protection authorities [54]. These complex legal and logistical barriers can impede study feasibility, limit patient recruitment, and contribute to high dropout rates in CBM clinical trials.
In the United States, cannabis research mandates approvals from multiple entities, including the Food and Drug Administration (FDA), the Drug Enforcement Administration (DEA), the National Institute on Drug Abuse (NIDA), state research advisory panels, and institutional review boards. Currently, the FDA maintains a cautious stance regarding the use of cannabinoids, emphasizing the need for an evidence base to validate their safety and efficacy [79]. In the United Kingdom, cannabis-based medicinal products (CBMPs) were rescheduled to Schedule 2 of the Misuse of Drugs Regulations 2001 on 1 November 2018. This change allows for prescription under specific conditions and when made by a specialist medical practitioner [80], but the prescribing of CBMs for chronic pain remains highly restricted (within the National Health Service), such that there is not an offer of nabilone, dronabinol, Δ9-THC, or a combination of CBD with Δ9-THC to manage chronic pain in adults, and likewise, CBD to manage chronic pain in adults unless used as part of a clinical trial [81]. Professional organizations, including the British Pain Society (BPS), emphasize caution, advising that there may be a role for medical cannabis in pain management, but more reliable evidence is needed to support its clinical use [34,82].
5. Conclusions
In conclusion, while CBMs such as Δ9-THC and CBD demonstrate potential in the management of chronic neuropathic pain, the current evidence is constrained by several factors. Clinical trials have yielded mixed results, with some indicating modest improvements in pain relief and quality of life, while others reveal no statistically significant difference compared to placebo. These findings are further complicated by study limitations such as relatively small sample sizes and brief durations, which constrain their capacity to evaluate the long-term efficacy and safety profiles of these interventions. Elevated placebo response rates in certain studies further confound the interpretation of results, while adverse events, particularly those associated with Δ9-THC-containing treatments, including dizziness and cognitive impairments, raise concerns regarding the tolerability of some CBMs. Furthermore, the psychoactive properties of some cannabinoids can potentially compromise the integrity of blinding in trials, introducing bias in the reported outcomes. Studies could also be potentially influenced by variable dosing strategies, carryover effects in crossover designs, and high attrition rates. Additionally, a non-linear dose-response relationship has been observed, with moderate doses often providing optimal benefits, while higher doses may lead to diminishing returns or increased adverse effects such as dizziness and somnolence. Future research should also prioritize identifying specific subgroups of patients who may derive maximal benefit from these therapies while minimizing adverse effects. Addressing factors such as depression, concurrent medications, and consistent outcome measures will be essential for elucidating the therapeutic role of CBMs. Optimal dosing regimens warrant investigation, as numerous studies utilized fixed doses that may not fully reflect the therapeutic potential of cannabinoids. Investigation into alternative delivery methods, such as oral or vaporized formulations, could potentially mitigate adverse effects while maintaining efficacy. Mechanistic studies are essential to elucidate the interactions between cannabinoids and pain pathways, as well as to understand the factors contributing to their inefficacy in certain patients. Collectively, these challenges underscore the necessity for larger, longer-term trials with standardized methodologies to better evaluate the efficacy and safety of CBMs. Furthermore, subsequent trials should incorporate more diverse patient populations and examine various types of neuropathic pain to ascertain the efficacy of cannabinoids across different clinical contexts. Until more robust evidence becomes available, the utilization of CBMs should be approached with caution, balancing their potential benefits against the risks of side effects and inconsistent outcomes.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/biom15060816/s1, Figure S1: Risk of bias assessments of the RCTs.
Author Contributions
Conceptualization: N.A. and W.G.C.; Data curation: N.A. and W.G.C.; Formal analysis: N.A. and W.G.C.; Funding acquisition: N.A.; Investigation: N.A. and W.G.C.; Methodology: N.A.; Project administration: W.G.C.; Resources: W.G.C.; Supervision: W.G.C.; Validation: N.A. and W.G.C.; Visualization: N.A. and W.G.C.; Writing—original draft: N.A.; Writing—review and editing: N.A., B.M.E.S. and W.G.C. All authors have read and agreed to the published version of the manuscript.
Funding
N.A. was supported by a Cultural Bureau and Ministry of Education PhD Scholarship, Kingdom of Saudi Arabia, scholarship number SPR-73707.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in this study are included in the article/Supplementary Materials. Further inquiries can be directed to the first author.
Conflicts of Interest
The authors declare no conflicts of interest. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
References
- Raja, S.N.; Carr, D.B.; Cohen, M.; Finnerup, N.B.; Flor, H.; Gibson, S.; Keefe, F.J.; Mogil, J.S.; Ringkamp, M.; Sluka, K.A.; et al. The revised International Association for the Study of Pain definition of pain: Concepts, challenges, and compromises. Pain 2020, 161, 1976–1982. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Woolf, C.J.; Ma, Q. Nociceptors-Noxious Stimulus Detectors. Neuron 2007, 55, 353–364. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bouhassira, D.; Lantéri-Minet, M.; Attal, N.; Laurent, B.; Touboul, C. Prevalence of chronic pain with neuropathic characteristics in the general population. Pain 2008, 136, 380–387. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kidd, B.L.; Urban, L.A. Mechanisms of inflammatory pain. Br. J. Anaesth. 2001, 87, 3–11. [Google Scholar] [CrossRef] [Scilit]
- Van Hecke, O.; Austin, S.K.; Khan, R.A.; Smith, B.H.; Torrance, N. Neuropathic pain in the general population: A systematic review of epidemiological studies. Pain 2014, 155, 654–662. [Google Scholar] [CrossRef] [Scilit]
- Colloca, L.; Ludman, T.; Bouhassira, D.; Baron, R.; Dickenson, A.H.; Yarnitsky, D.; Freeman, R.; Truini, A.; Attal, N.; Finnerup, N.B.; et al. Neuropathic pain. Nat. Rev. Dis. Primers 2017, 3, 17002. [Google Scholar] [CrossRef] [Scilit]
- Scholz, J.; Finnerup, N.B.; Attal, N.; Aziz, Q.; Baron, R.; Bennett, M.I.; Benoliel, R.; Cohen, M.; Cruccu, G.; Davis, K.D.; et al. The IASP classification of chronic pain for ICD-11, Chronic neuropathic pain. Pain 2019, 160, 53–59. [Google Scholar] [CrossRef] [Scilit]
- Cavalli, E.; Mammana, S.; Nicoletti, F.; Bramanti, P.; Mazzon, E. The neuropathic pain: An overview of the current treatment and future therapeutic approaches. Int. J. Immunopathol. Pharmacol. 2019, 33. [Google Scholar] [CrossRef] [Scilit]
- Kwiatkowski, K.; Mika, J. The importance of chemokines in neuropathic pain development and opioid analgesic potency. Pharmacol. Rep. 2018, 70, 821–830. [Google Scholar] [CrossRef] [Scilit]
- Kritikou, P.; Vadalouca, A.; Rekatsina, M.; Varrassi, G.; Siafaka, I. The Diagnostic Odyssey of Patients with Chronic Neuropathic Pain—Expert Opinion of Greek Pain Specialists. Clin. Pr. 2023, 13, 166–176. [Google Scholar] [CrossRef] [Scilit]
- Sommer, C.; Leinders, M.; Üçeyler, N. Inflammation in the pathophysiology of neuropathic pain. Pain 2018, 159, 595–602. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alles, S.R.A.; Smith, P.A. Etiology and pharmacology of neuropathic pain. Pharmacol. Rev. 2018, 70, 315–347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cohen, S.P.; Vase, L.; Hooten, W.M. Chronic Pain 1 Chronic Pain: An Update on Burden, Best Practices, and New Advances. 2021. Available online: www.thelancet.com (accessed on 14 April 2025).
- Obata, H. Analgesic mechanisms of antidepressants for neuropathic pain. Int. J. Mol. Sci. 2017, 18, 2483. [Google Scholar] [CrossRef] [Scilit]
- Saarto, T.; Wiffen, P.J. Antidepressants for neuropathic pain. Cochrane Database Syst. Rev. 2007, 2007, CD005454. [Google Scholar] [CrossRef] [Scilit]
- Attal, N.; Bouhassira, D. Advances in the treatment of neuropathic pain. Curr. Opin. Neurol. 2021, 34, 631–637. [Google Scholar] [CrossRef] [Scilit]
- Moisset, X.; Bouhassira, D.; Couturier, J.A.; Alchaar, H.; Conradi, S.; Delmotte, M.; Lanteri-Minet, M.; Lefaucheur, J.; Mick, G.; Piano, V.; et al. Pharmacological and non-pharmacological treatments for neuropathic pain: Systematic review and French recommendations. Rev. Neurol. 2020, 176, 325–352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kremer, M.; Salvat, E.; Muller, A.; Yalcin, I.; Barrot, M. Antidepressants and gabapentinoids in neuropathic pain: Mechanistic insights. Neuroscience 2016, 338, 183–206. [Google Scholar] [CrossRef] [Scilit]
- Peppin, J.F.; Pappagallo, M. Capsaicinoids in the treatment of neuropathic pain: A review. Ther. Adv. Neurol. Disord. 2014, 7, 22–32. [Google Scholar] [CrossRef] [Scilit]
- Bates, D.; Schultheis, B.C.; Hanes, M.C.; Jolly, S.M.; Chakravarthy, K.V.; Deer, T.R.; Levy, R.M.; Hunter, C.W. A Comprehensive Algorithm for Management of Neuropathic Pain. Pain Med. 2019, 20, S2-12. [Google Scholar] [CrossRef] [Scilit]
- Finnerup, N.B.; Attal, N.; Haroutounian, S.; McNicol, E.; Baron, R.; Dworkin, R.H.; Gilron, I.; Haanpää, M.; Hansson, P.; Jensen, T.S.; et al. Pharmacotherapy for neuropathic pain in adults: A systematic review and meta-analysis. Lancet Neurol. 2015, 14, 162–173. [Google Scholar] [CrossRef] [Scilit]
- Moore, R.A.; Chi, C.C.; Wiffen, P.J.; Derry, S.; Rice, A.S.C. Oral nonsteroidal anti-inflammatory drugs for neuropathic pain. Cochrane Database Syst. Rev. 2015, 2017, CD010902. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vo, T.; Rice, A.S.C.; Dworkin, R.H. Non-steroidal anti-inflammatory drugs for neuropathic pain: How do we explain continued widespread use? Pain 2009, 143, 169–171. [Google Scholar] [CrossRef] [Scilit]
- Petroianu, G.A.; Aloum, L.; Adem, A. Neuropathic pain: Mechanisms and therapeutic strategies. Front. Cell Dev. Biol. 2023, 11, 1072629. [Google Scholar] [CrossRef] [Scilit]
- Vučkovic, S.; Srebro, D.; Vujovic, K.S.; Vučetic, Č.; Prostran, M. Cannabinoids and pain: New insights from old molecules. Front. Pharmacol. 2018, 9, 1259. [Google Scholar] [CrossRef] [Scilit]
- Wolf, J.; Urits, I.; Orhurhu, V.; Peck, J.; Orhurhu, M.S.; Giacomazzi, S.; Smoots, D.; Piermarini, C.; Manchikanti, L.; Kaye, A.D.; et al. The Role of the Cannabinoid System in Pain Control: Basic and Clinical Implications. Curr. Pain Headache Rep. 2020, 24, 35. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chiou, L.C.; Hu, S.S.J.; Ho, Y.C. Targeting the cannabinoid system for pain relief? Acta Anaesthesiol. Taiwanica 2013, 51, 161–170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, K.; Wu, Y.; Tian, Z.; Xu, Y.; Wu, C.; Wang, Z. Microglial Cannabinoid CB2 Receptors in Pain Modulation. Int. J. Mol. Sci. 2023, 24, 2348. [Google Scholar] [CrossRef] [Scilit]
- Pertwee, R.G. The diverse CB 1 and CB 2 receptor pharmacology of three plant cannabinoids: Δ 9-tetrahydrocannabinol, cannabidiol and Δ 9-tetrahydrocannabivarin. Br. J. Pharmacol. 2008, 153, 199–215. [Google Scholar] [CrossRef] [Scilit]
- Iannotti, F.A.; Hill, C.L.; Leo, A.; Alhusaini, A.; Soubrane, C.; Mazzarella, E.; Russo, E.; Whalley, B.J.; Di Marzo, V.; Stephens, G.J. Nonpsychotropic plant cannabinoids, Cannabidivarin (CBDV) and Cannabidiol (CBD), activate and desensitize Transient Receptor Potential Vanilloid 1 (TRPV1) channels in vitro: Potential for the treatment of neuronal hyperexcitability. ACS Chem. Neurosci. 2014, 5, 1131–1141. [Google Scholar] [CrossRef] [Scilit]
- Wang, X.; Lin, C.; Wu, S.; Zhang, T.; Wang, Y.; Jiang, Y.; Wang, X. Cannabidivarin alleviates neuroinflammation by targeting TLR4 co-receptor MD2 and improves morphine-mediated analgesia. Front. Immunol. 2022, 13, 929222. [Google Scholar] [CrossRef] [Scilit]
- Pantoja-Ruiz, C.; Restrepo-Jimenez, P.; Castañeda-Cardona, C.; Ferreirós, A.; Rosselli, D. Cannabis and pain: A scoping review. Braz. J. Anesthesiol. 2022, 72, 142–151. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, G.; Grovey, B.; Furnish, T.; Wallace, M. Medical Cannabis for Neuropathic Pain. Curr. Pain Headache Rep. 2018, 22, 8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mücke, M.; Phillips, T.; Radbruch, L.; Petzke, F.; Häuser, W. Cannabis-based medicines for chronic neuropathic pain in adults. Cochrane Database Syst. Rev. 2018, 2018, CD012182. [Google Scholar]
- Moher, D.; Liberati, A.; Tetzlaff, J.; Altman, D.G. Preferred reporting items for systematic reviews and meta-analyses: The PRISMA statement. BMJ 2009, 339, 332–336. [Google Scholar] [CrossRef]
- Huang, X.; Lin, J.; Demner-Fushman, D. Evaluation of PICO as a Knowledge Representation for Clinical Questions. 2006. Available online: http://www.fpin.org/ (accessed on 13 March 2025).
- Karst, M.; Salim, K.; Burstein, S.; Conrad, I.; Hoy, L.; Schneider, U. Analgesic Effect of the Synthetic Cannabinoid CT-3 on Chronic Neuropathic Pain A Randomized Controlled Trial [Internet]. 2003. Available online: https://jamanetwork.com/journals/jama/fullarticle/197396 (accessed on 14 April 2025).
- Berman, J.S.; Symonds, C.; Birch, R. Efficacy of two cannabis based medicinal extracts for relief of central neuropathic pain from brachial plexus avulsion: Results of a randomised controlled trial. Pain 2004, 112, 299–306. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Svendsen, K.B.; Jensen, T.S.; Bach, F.W. Does the cannabinoid dronabinol reduce central pain in multiple sclerosis? Randomised double blind placebo controlled crossover trial. BMJ 2004, 329, 253. [Google Scholar] [CrossRef] [Scilit]
- Rog, D.J.; Nurmikko, T.J.; Friede, T.; Young, C.A. Randomized, Controlled Trial of Cannabis-Based Medicine in Central Pain in Multiple Sclerosis. 2005. Available online: www.neurology.org (accessed on 13 March 2025).
- Nurmikko, T.J.; Serpell, M.G.; Hoggart, B.; Toomey, P.J.; Morlion, B.J.; Haines, D. Sativex successfully treats neuropathic pain characterised by allodynia: A randomised, double-blind, placebo-controlled clinical trial. Pain 2007, 133, 210–220. [Google Scholar] [CrossRef] [Scilit]
- Abrams, D.I.; Jay, C.A.; Shade, S.B.; Vizoso, H.; Reda, H.; Press, S.; Kelly, M.E.; Rowbotham, M.C.; Petersen, K.L. Cannabis in painful HIV-associated sensory neuropathy A randomized placebo-controlled trial. Neurology 2007, 68, 515–521. [Google Scholar] [CrossRef] [Scilit]
- Wilsey, B.; Marcotte, T.; Tsodikov, A.; Millman, J.; Bentley, H.; Gouaux, B.; Fishman, S. A Randomized, Placebo-Controlled, Crossover Trial of Cannabis Cigarettes in Neuropathic Pain. J. Pain 2008, 9, 506–521. [Google Scholar] [CrossRef] [Scilit]
- Ellis, R.J.; Toperoff, W.; Vaida, F.; Brande, G.v.D.; Gonzales, J.; Gouaux, B.; Bentley, H.; Atkinson, J.H. Smoked medicinal cannabis for neuropathic pain in HIV: A randomized, crossover clinical trial. Neuropsychopharmacology 2009, 34, 672–680. [Google Scholar] [CrossRef] [Scilit]
- Selvarajah, D.; Gandhi, R.; Emery, C.J.; Tesfaye, S. Randomized placebo-controlled double-blind clinical trial of cannabis-based medicinal product (Sativex) in painful diabetic neuropathy: Depression is a major confounding factor. Diabetes Care 2010, 33, 128–130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ware, M.A.; Wang, T.; Shapiro, S.; Robinson, A.; Ducruet, T.; Huynh, T.; Gamsa, A.; Bennett, G.J.; Collet, J.-P. Smoked cannabis for chronic neuropathic pain: A randomized controlled trial. CMAJ. Can. Med. Assoc. J. 2010, 182, E694–E701. [Google Scholar] [CrossRef] [Scilit]
- Wilsey, B.; Marcotte, T.; Deutsch, R.; Gouaux, B.; Sakai, S.; Donaghe, H. Low-dose vaporized cannabis significantly improves neuropathic pain. J. Pain 2013, 14, 136–148. [Google Scholar] [CrossRef] [Scilit]
- Lynch, M.E.; Cesar-Rittenberg, P.; Hohmann, A.G. A double-blind, placebo-controlled, crossover pilot trial with extension using an oral mucosal cannabinoid extract for treatment of chemotherapy-induced neuropathic pain. J. Pain Symptom Manag. 2014, 47, 166–173. [Google Scholar] [CrossRef] [Scilit]
- Wallace, M.S.; Marcotte, T.D.; Umlauf, A.; Gouaux, B.; Atkinson, J.H. Efficacy of Inhaled Cannabis on Painful Diabetic Neuropathy. J. Pain 2015, 16, 616–627. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilsey, B.L.; Deutsch, R.; Samara, E.; Marcotte, T.D.; Barnes, A.J.; Huestis, M.A.; Le, D. A preliminary evaluation of the relationship of cannabinoid blood concentrations with the analgesic response to vaporized cannabis. J. Pain Res. 2016, 9, 587–598. [Google Scholar] [CrossRef] [Scilit]
- Weizman, L.; Dayan, L.; Brill, S.; Nahman-Averbuch, H.; Hendler, T.; Jacob, G.; Sharon, H. Cannabis analgesia in chronic neuropathic pain is associated with altered brain connectivity. Neurology 2018, 91, E1285-94. [Google Scholar] [CrossRef] [Scilit]
- Xu, D.H.; Cullen, B.D.; Tang, M.; Fang, Y. The Effectiveness of Topical Cannabidiol Oil in Symptomatic Relief of Peripheral Neuropathy of the Lower Extremities. Curr. Pharm. Biotechnol. 2019, 21, 390–402. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eibach, L.; Scheffel, S.; Cardebring, M.; Lettau, M.; Özgür Celik, M.; Morguet, A.; Roehle, R.; Stein, C. Cannabidivarin for HIV-Associated Neuropathic Pain: A Randomized, Blinded, Controlled Clinical Trial. Clin. Pharmacol. Ther. 2021, 109, 1055–1062. [Google Scholar] [CrossRef] [Scilit]
- Hansen, J.S.; Hansen, R.M.; Petersen, T.; Gustavsen, S.; Oturai, A.B.; Sellebjerg, F.; Sædder, E.A.; Kasch, H.; Rasmussen, P.V.; Finnerup, N.B.; et al. The effect of cannabis-based medicine on neuropathic pain and spasticity in patients with multiple sclerosis and spinal cord injury: Study protocol of a national multicenter double-blinded, placebo-controlled trial. Brain Sci. 2021, 11, 1212. [Google Scholar] [CrossRef] [Scilit]
- Hansen, J.S.; Gustavsen, S.; Roshanisefat, H.; Kant, M.; Biering-Sørensen, F.; Andersen, C.; Olsson, A.; Chow, H.H.; Asgari, N.; Hansen, J.R.; et al. Cannabis-Based Medicine for Neuropathic Pain and Spasticity—A Multicenter, Randomized, Double-Blinded, Placebo-Controlled Trial. Pharmaceuticals 2023, 16, 1079. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zubcevic, K.; Petersen, M.; Bach, F.W.; Heinesen, A.; Enggaard, T.P.; Almdal, T.P.; Holbech, J.V.; Vase, L.; Jensen, T.S.; Hansen, C.S.; et al. Oral capsules of tetra-hydro-cannabinol (THC), cannabidiol (CBD) and their combination in peripheral neuropathic pain treatment. Eur. J. Pain 2023, 27, 492–506. [Google Scholar] [CrossRef] [Scilit]
- Weizman, L.; Sharon, H.; Dayan, L.; Espaniol, J.; Brill, S.; Nahman-Averbuch, H.; Hendler, T.; Jacob, G. Oral Delta-9-Tetrahydrocannabinol (THC) Increases Parasympathetic Activity and Supraspinal Conditioned Pain Modulation in Chronic Neuropathic Pain Male Patients: A Crossover, Double-Blind, Placebo-Controlled Trial. CNS Drugs 2024, 38, 375–385. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Andre, S.; Novotny, P.; Walters, C.; Lewis-Peters, S.; Thomé, S.; Toftahagen, C.; Giridhar, K.V.; Loprinzi, C. Topical Cannabidiol for Established Chemotherapy-Induced Neuropathy: A Pilot Randomized Placebo-Controlled Trial. Cannabis Cannabinoid Res. 2024, 9, e1556–e1564. [Google Scholar] [CrossRef] [Scilit]
- Kittithamvongs, P.; Anantasinkul, P.; Siripoonyothai, S.; Anantavorasakul, N.; Malungpaishrope, K.; Uerpairojkit, C.; Leechavengvongs, S. Does Cannabis-based Medicine Improve Pain and Sleep Quality in Patients With Traumatic Brachial Plexus Injuries? A Triple-blind, Crossover, Randomized Controlled Trial. Clin. Orthop. Relat. Res. 2024, 483, 228–234. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Higgins, J.P.T.; Altman, D.G.; Gøtzsche, P.C.; Jüni, P.; Moher, D.; Oxman, A.D.; Savović, J.; Schulz, K.F.; Weeks, L.; Sterne, J.A.C.; et al. The Cochrane Collaboration’s tool for assessing risk of bias in randomised trials. BMJ 2011, 343, d5928. [Google Scholar] [CrossRef] [Scilit]
- Jones, D.S.; Podolsky, S.H. The history and fate of the gold standard. Lancet 2015, 385, 1502–1503. [Google Scholar] [CrossRef] [Scilit]
- Narang, S.; Gibson, D.; Wasan, A.D.; Ross, E.L.; Michna, E.; Nedeljkovic, S.S.; Jamison, R.N. Efficacy of Dronabinol as an Adjuvant Treatment for Chronic Pain Patients on Opioid Therapy. J. Pain 2008, 9, 254–264. [Google Scholar] [CrossRef] [Scilit]
- Grotenhermen, F. Pharmacokinetics and Pharmacodynamics of Cannabinoids. Clin. Pharmacokinet. 2003, 42, 327–360. [Google Scholar] [CrossRef] [Scilit]
- Milman, G.; Bergamaschi, M.M.; Lee, D.; Mendu, D.R.; Barnes, A.J.; Vandrey, R.; Huestis, M.A. Plasma cannabinoid concentrations during dronabinol pharmacotherapy for cannabis dependence. Ther. Drug Monit. 2014, 36, 218–224. [Google Scholar] [CrossRef] [Scilit]
- Huestis, M.A. Human cannabinoid pharmacokinetics. Chem. Biodivers. 2007, 4, 1770–1804. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lucas, C.J.; Galettis, P.; Schneider, J. The pharmacokinetics and the pharmacodynamics of cannabinoids. Br. J. Clin. Pharmacol. 2018, 84, 2477–2482. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karschner, E.L.; Darwin, W.D.; Goodwin, R.S.; Wright, S.; Huestis, M.A. Plasma cannabinoid pharmacokinetics following controlled oral Δ 9-tetrahydrocannabinol and oromucosal cannabis extract administration. Clin. Chem. 2011, 57, 66–75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ashton, C.H. Pharmacology and effects of cannabis: A brief review. Br. J. Psychiatry 2001, 178, 101–106. [Google Scholar] [CrossRef] [Scilit]
- Baglot, S.L.; Hume, C.; Petrie, G.N.; Aukema, R.J.; Lightfoot, S.H.M.; Grace, L.M.; Zhou, R.; Parker, L.; Rho, J.M.; Borgland, S.L.; et al. Pharmacokinetics and central accumulation of delta-9-tetrahydrocannabinol (THC) and its bioactive metabolites are influenced by route of administration and sex in rats. Sci. Rep. 2021, 11, 23990. [Google Scholar] [CrossRef] [Scilit]
- Guy, G.W.; Robson, P.J. A phase I, double blind, three-way crossover study to assess the pharmacokinetic profile of Cannabis Based Medicine Extract (CBME) administered sublingually in variant cannabinoid ratios in normal healthy male volunteers (GWPK0215). J. Cannabis Ther. 2003, 3, 121–152. [Google Scholar] [CrossRef] [Scilit]
- Scheidweiler, K.; Russo, E.B.; Henderson-Redmond, A.; Kessler, C.S.; Müller-Vahl, K.R. Implications for blinding in clinical trials with THC-containing cannabinoids based on the CANNA-TICS trial. Front. Neurosci. 2022, 16, 793703. [Google Scholar]
- Farrar, J.T.; Young, J.P.B.; Lamoreaux, L.; Werth, J.L.; Poole, R.M. Clinical Importance of Changes in Chronic Pain Intensity Measured on an 11-Point Numerical Pain Rating Scale. Available online: https://journals.lww.com/pain/abstract/2001/11000/clinical_importance_of_changes_in_chronic_pain.6.aspx (accessed on 13 March 2025).
- Cruccu, G.; Truini, A. A review of Neuropathic Pain: From Guidelines to Clinical Practice. Pain Ther. 2017, 6, 35–42. [Google Scholar] [CrossRef] [Scilit]
- Watson, J.C.; Sandroni, P. Central Neuropathic Pain Syndromes. Mayo Clin. Proc. 2016, 91, 372–385. [Google Scholar] [CrossRef] [Scilit]
- Doneddu, P.E.; Pensato, U.; Iorfida, A.; Alberti, C.; Nobile-Orazio, E.; Fabbri, A.; Voza, A. Neuropathic Pain in the Emergency Setting: Diagnosis and Management. J. Clin. Med. 2023, 12, 6028. [Google Scholar] [CrossRef] [Scilit]
- Costa, B.; Giagnoni, G.; Franke, C.; Trovato, A.E.; Colleoni, M. Vanilloid TRPV1 receptor mediates the antihyperalgesic effect of the nonpsychoactive cannabinoid, cannabidiol, in a rat model of acute inflammation. Br. J. Pharmacol. 2004, 143, 247–250. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Russo, E.B. Taming THC: Potential cannabis synergy and phytocannabinoid-terpenoid entourage effects. Br. J. Pharmacol. 2011, 163, 1344–1364. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- IASP. International Association for the Study of Pain Presidential Task Force on Cannabis and Cannabinoid Analgesia position statement. Pain 2021, 162, S1–S2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- FDA. FDA and Cannabis: Research and Drug Approval Process. 2023. Available online: https://www.fda.gov/news-events/public-health-focus/fda-and-cannabis-research-and-drug-approval-process (accessed on 13 March 2025).
- Home Office. Rescheduling of Cannabis-Based Products for Medicinal Use in Humans (Accessible Version). 2018. Available online: http://www.legislation.gov.uk/uksi/2018/1055/contents/made (accessed on 13 March 2025).
- NICE; NG144. Cannabis-Based Medicinal Products NICE Guideline. 2019. Available online: www.nice.org.uk/guidance/ng144 (accessed on 13 March 2025).
- British Pain Society. Position Statement on the Medicinal Use of Cannabinoids in Pain Management; John Wiley and Sons Ltd.: Hoboken, NJ, USA, 2025; Available online: https://www.britishpainsociety.org (accessed on 13 March 2025).

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).