


Abstract
Acute pancreatitis (AP) is an acute inflammation of the pancreas caused by the activation of digestive enzymes in the pancreatic tissue. The main causes of AP are cholelithiasis and alcohol abuse; less commonly, it can be caused by drugs, with a prevalence of up to 5%. Causal associations between drugs and pancreatitis are largely based on case reports or case series with limited evidence. We reviewed the available data on drug-induced AP, focusing on antimicrobial drugs and antivirals, and discussed the current evidence in relation to the classification systems available in the literature. We found 51 suspected associations between antimicrobial and antiviral drugs and AP. The drugs with the most evidence of correlation are didanosine, protease inhibitors, and metronidazole. In addition, other drugs have been described in case reports demonstrating positive rechallenge. However, there are major differences between the various classifications available, where the same drug being assigned to different probability classes. It is likely that the presence in multiple case reports of an association between acute pancreatitis and a drug should serve as a basis for conducting prospective randomized controlled trials to improve the quality of the evidence.
1. Introduction
Acute pancreatitis (AP) is an acute inflammation of the pancreas resulting from intrapancreatic activation of digestive enzymes. This condition can lead to pancreatic necrosis, organ failure, and multiple organ dysfunction, with a mortality rate of 1–5% [1,2]. In addition, acute pancreatitis may be associated with significant short- and long-term morbidity, with recurrent symptoms and, in severe cases, exocrine and/or endocrine pancreatic failure [3]. The diagnosis of AP requires the identification of two of the following criteria: (1) abdominal pain suggestive of pancreatitis, (2) serum amylase or lipase levels at least three times the upper normal limit, and (3) imaging findings consistent with pancreatitis on computed tomography (CT) or magnetic resonance imaging (MRI) [1,4,5]. It is clear that the first two criteria alone are sufficient for diagnosis; thus, imaging can be performed later to better identify complications of acute pancreatitis. AP can be classified into mild, moderate, and severe forms according to the Atlanta criteria [1].
Mild acute pancreatitis is not associated with local or systemic complications and often resolves within the first week. Usually, mild AP does not result in organ failure. It is the most common form. Moderate AP is associated with local complications or exacerbation of concomitant diseases; transient organ failure may occur. In contrast, severe acute pancreatitis is defined by persistent organ failure (i.e., organ failure > 48 h). Local complications include pancreatic and peripancreatic necrosis (sterile or infected), peripancreatic fluid collections, pseudocysts, and parietal necrosis (sterile or infected) [1]. The main causes of AP are cholelithiasis and alcohol abuse, which account for more than 80% of cases [6,7]. Less commonly, it can also be caused by medications, with a prevalence ranging from 2 to 5.3% [3,7]. In this narrative review, we focused on the role of pharmacologic agents in causing acute pancreatitis, particularly antimicrobial and antiviral agents, considering the widespread use of these therapies and the absence of specific work on these types of drugs in the literature.
2. Drug-Induced Pancreatitis
According to the Agency for Drugs and Medical Devices Adverse Drug Event Reporting Database, drug-induced acute pancreatitis (DIAP) accounted for 0.17% of all adverse drug reactions (ADRs) [8]. Pharmacologic agents potentially responsible for acute pancreatitis include nearly 200 drugs [8,9]. However, causal relationships are largely based on case reports or case series with limited evidence. Consequently, an important indication of a causal relationship between a drug and AP is the recurrence of AP after reintroduction of the drug after discontinuation and recovery from a previous episode [10]. However, for ethical reasons, drugs in which rechallenge episodes are performed are quite rare. Another key concept in determining the association between a particular drug and an adverse event is latency; latency is the time between the assumption of the drug and the occurrence of AP. Several systematic reviews use latency categories (e.g., <24 h, 1–30 days, >30 days), and if >75% of case reports for a drug fell into the same latency category, this was considered good evidence of an association (adequate latency) [9,11,12]. Currently, only three drugs have been associated with the development of AP in a randomized controlled trial (6-mercaptopurine, azathioprine, and didanosine) [9,11,12,13].
In 2007, based on case reports in the literature, Badalov et al. classified drugs potentially responsible for the development of AP into probability classes based on case reports from the literature (Table 1) [14]. This classification was revised in 2019 by C.R. Simons-Linares et al. The first class includes drugs with a positive rechallenge. This class is further divided into two subclasses, a and b, depending on whether other possible causes were excluded or not. Class II includes drugs for which at least four case reports show similar latency. Class III includes drugs for which there are at least two case reports, but which do not meet the criteria of the above classes. The final class (IV) includes the drugs with the weakest evidence, for which only one case report was published [12]. This classification was updated by Wolfe et al. in 2020 [11].
Table 1.
The classification of drug-induced pancreatitis, according to Badalov, updated by Simons-Linares et al. [13].
However, there are some differences between these two classifications; methodologically, Wolfe et al. developed the rules of their classification a priori, before performing the literature search, whereas the system of C.R. Simons-Linares et al. is based on their review data. In addition, Wolfe et al. applied more stringent criteria in selecting case reports by including only cases of AP diagnosed according to currently accepted diagnostic criteria and excluding cases in which AP was associated with drug combinations (Table 2). In this classification, the classes differ from the previous one; class I was further divided into three subclasses (a, b, c). Class Ic includes drugs for which there is at least one case report with no positive rechallenge, excluding other causes. Drugs for which there are at least two case reports without evidence of rechallenge but with and without exclusion of other causes are classified as class II and class III, respectively. With adequate latency in class II and insufficient latency in class III [11].
Table 2.
The classification of drug-induced pancreatitis, according to Wolfe et al. [11].
More recently, Saini et al. have presented another classification based on an evidence-based approach that includes a comprehensive review of randomized controlled trials (RCTs), cohort studies, pharmacoepidemiologic analyses, and case reports and differs from previous classifications. Table 3 provides an overview of this classification system. They divided drugs considered to trigger AP into four groups according to the quality of the evidence. Thus, class I included RCTs (high evidence), whereas case–control studies and pharmacoepidemiologic studies were classified as class II. Classes III (divided into a, b, and c) and IV included case reports according to quality, presence of rechallenge, adequate latency, and number of reports [9].
Table 3.
The classification of drug-induced pancreatitis, according to Saini et al. [9].
Main Mechanisms of Drug-Induced Pancreatitis
Most of the mechanisms underlying drug-induced pancreatic injury have not been fully elucidated or demonstrated. One of the most common is probably an idiosyncratic delayed immunologic or T-cell-mediated response rather than intrinsic toxicity [13,15]. This has been demonstrated for azathioprine, 6-MP, and sulfasalazine in both in vitro trials and population-based studies [10,16]. Idiosyncratic reactions do not appear to be directly related to dose, and symptoms differ from the pharmacologic effect of the drug. The proposed mechanism for idiosyncratic reactions to drugs is not certain. However, it may be a reactive metabolite of the drug that binds to specific proteins and causes an immune system response (haptenes hypothesis). This response could be triggered by injury or cellular stress (hazard hypothesis) and stimulate the activation of an immune response by the co-stimulation of T lymphocytes [15].
Although the exact mechanism of AP, triggered by thiopurines and antibiotics, remains unknown, there is increasing evidence that certain human leukocyte antigen (HLA) alleles may be predisposed to this type of hypersensitive reaction [17].
Other proposed mechanisms include the hypothesis of a toxic effect on the pancreatic cell membrane (as in the case of valproate) or the formation of edema in the pancreatic ducts, which may occur with angiotensin-converting enzyme inhibitors via the kallikrein/kinin pathway [18]. In addition, some drug therapies have been associated with the occurrence of hypertriglyceridemia pancreatitis [19]. According to some studies, most antiviral protease inhibitors (PI) are associated with a significant increase in plasma triglyceride concentrations; in particular, hypertriglyceridemia is observed more frequently after combination therapy with ritonavir or lopinavir/ritonavir than with other PI -based combinations. As described below, ritonavir and lopinavir/ritonavir-based regimens have been associated with an increased risk of hyperlipidemic pancreatitis [19,20].
Another possible causative mechanism is mitochondrial toxicity [19,21]. This appears to be associated with the use of antiviral drugs such as nuclear reverse transcriptase inhibitors to treat human immunodeficiency virus (HIV) infections [10,22]. This toxicity appears to be due to the inhibition of mitochondrial DNA replication by suppression of the activity of key enzymes involved in mitochondrial DNA replication. Although acute pancreatitis is a well-described complication of HIV infection, an increased incidence of this condition has been reported after the introduction of reverse transcriptase inhibitors in HIV patients [21,23].
Considering antibiotics, it is postulated that tetracyclines may cause DIAP either through a toxin-mediated action of an unknown metabolite or a direct toxic effect on the pancreas due to the supratherapeutic bile concentration of tetracyclines [18]. Pharmacological experiments with tetracyclines have shown that the biliary concentration of minocycline is ten times higher than the serum concentration, and similar results have been observed with tigecycline [24,25].
Another speculative mechanism of metronidazole-induced pancreatitis is the production of redox cycling and hydrogen peroxide, superoxide, and other free radicals under aerobic conditions. These redox-active compounds are toxic to pancreatic β-cells. Oxygen free radicals have been associated with the initiation of pancreatitis [26]. Finally, in the case of opiates, the proposed mechanism is a stimulation of μ-receptors causing hypercontraction of the Oddi sphincter that increases the basal pressure and amplitude of contraction and induces a reflux of pancreatic enzymes into the pancreatic duct [27]. Figure 1 summarizes these mechanisms.
Figure 1.
Main etiopathogenetic mechanisms proposed for DIAP caused by antimicrobials and antivirals.
DIAP: Drug-induced acute pancreatitis
The etiopathogenetic mechanism most involved in the development of DIAP from antimicrobials and antivirals appears to be the delayed idiosyncratic or lymphocyte-T-mediated mechanism. Pancreatic damage caused by the immune system also seems to be associated with certain human leukocyte antigen (HLA) alleles which may be predisposed to this type of hypersensitive reaction. Other pathogenetic mechanisms have been postulated for these drug classes. For example, hypertriglyceridemia induced by protease inhibitor antivirals may increase the risk of developing DIAP. Furthermore, mitochondrial toxicity, oxidative damage, and biliary supersaturation by metabolites or the drug itself have been suggested as additional mechanisms involved in DIAP by reverse transcriptase inhibitors, metronidazole, and tetracyclines, respectively.
3. Antibiotics
In this chapter, we have divided antibiotics according to the most accepted pharmacological classification, as follows: inhibitors of cell wall synthesis, inhibitors of protein synthesis, inhibitors of cell metabolism, inhibitors of nucleic acid synthesis, and antibiotics that alter membrane permeability [28]. Table 4 summarizes the antibiotics associated with acute pancreatitis.
Table 4.
Antibiotics associated with acute pancreatitis.
3.1. Nucleic Acid Synthesis Inhibitors
3.1.1. Metronidazole and 5-Nitroinidazoles
Metronidazole is a bactericidal antibiotic that attacks host microorganisms, causes severe DNA damage, and inhibits the synthesis of nucleic acids. It is the drug of choice for treating infections caused by anaerobic bacteria, Helicobacter pylori, and protozoan infections (e.g., giardiasis).
Metronidazole has been mentioned in several case reports on PA, with three patients having a positive rechallenge and all having a favorable outcome [29]. Based on these data, it is classified as class Ia according to both the classification of Roberto Simons-Linares et al. and the classification of Diana Wolfe et al. We would like to point out that three other cases have been described in the literature that are not included in this narrative review, two of them with a positive rechallenge [11,12,30].
Andrei Barbulescu et al. conducted a large population-based case–control study of 5996 patients with AP in Sweden between January 2006 and December 2008. The odds ratios of metronidazole exposure in individuals with AP were 4 and 11 for single oral exposure and for combined regimens for treatment of H. pylori, respectively [31]. In addition, Nørgaard M. et al. reported an eightfold increased risk of acute pancreatitis in individuals exposed to metronidazole when it was combined with other drugs used to treat H. pylori [32]. As a result of these two case–control studies, metronidazole was placed in class II of the Saini et al. classification [9].
Secnidazole and tinidazole are 5-nitroimidazole derivatives with similar properties to metronidazole, except for a longer-lasting blood concentration, used for hepatic amibiasis, giardiasis, and bacterial vaginosis [33].
Only one case of AP has been described after the use of secnidazole and another case after tinidazole ingestion [34,35]. All other underlying diseases or medications associated with AP were ruled out; however, in both cases, the rechallenge was negative. Therefore, the drugs met the criteria for class IV in the reviewed classification of C. Roberto Simons-Linares et al. At the same time, they belong to class Ic according to the classification system of Diana Wolfe et al. However, of the two drugs described, only secnidazole was included in class IV in the review by Saini et al. [9,11,12].
3.1.2. Fluoroquinolones
Fluoroquinolones are bactericidal antibiotics that inhibit DNA gyrase and topoisomerase IV, which are involved in DNA synthesis. They are broad-spectrum antimicrobial antibiotics with excellent efficacy against several Gram-negative (including Pseudomonas spp.), and some Gram-positive, and also atypical bacteria (e.g., Chlamydia, Legionella, Mycoplasma), and tuberculous and non-tuberculous mycobacteria. Several cases of acute pancreatitis triggered by fluoroquinolones have been described in the literature, but no pathogenetic mechanism has been postulated for this pharmacological class [36,37].
With respect to ciprofloxacin, two cases were described in the literature, with no consistent latency between cases and no rechallenge [36]. For these reasons, it was placed in class III of the classification by Roberto Simons-Linares et al. [12].
However, based on the data reported in the work of Sung HY et al., this drug was classified as class Ib by Wolfe et al. because one case documented a positive rechallenge without exclusion of other causes of AP [37]. However, it was not mentioned in the review by Saini et al. because the case reports cited were probably considered to be of low quality.
Levofloxacin was not included in the classifications of Simons-Linares, Wolfe, and Saini [9,11,12]. However, four cases of AP caused by levofloxacin have been described, including one in which rechallenge positivity was observed without definite exclusion of other causes of AP. However, all cases were characterized by a good outcome [38]. It should be noted that the aforementioned case of rechallenge positivity is marred by a lack of exhaustive details. We can conclude that levofloxacin, regardless of the risk class, should be considered as a drug that, probably, can induce DIAP.
Ofloxacin is not included in Roberto Simons-Linares and Wolfe’s classifications, although a case of DIAP triggered by the drug in question has been reported [39,40]. We can assume that this case was excluded because of the association of this drug with ornidazole. Therefore, it was classified as an orfloxacin–ornidazole association in class IV of the Saini classification because of uncertain rechallenge positivity.
For norfloxacin, only one case without rechallenge was described in the medical literature; therefore, it was placed in class IV by Wolfe et al. [11]. Norfloxacin was not included in the Simons-Linares et al. reviewed classification because the criteria used in the review did not include case reports in languages other than English. Instead, probably for reasons related to the low quality of the case report, it was not included in the classification of Saini et al. [9].
3.1.3. Nitrofurantoin
Nitrofurantoin is an antibacterial drug of the nitrofuran class used mainly against urinary tract infections. It inhibits DNA and RNA functions by a mechanism that has not been fully elucidated, although nitro group bioreduction is thought to be an essential component of the mechanism of action.
The first case of DIAP associated with nitrofurantoin ingestion was described by Neils et al. in 1983 [41]. This case, in which rechallenge positivity was documented without clearly excluding other causes of pancreatitis, allowed to include nitrofurantoin in class Ib according to the classification of Roberto Simons-Linares et al.
Wolfe et al., on the other hand, assigned nitrofurantoin to class Ia because they included two other cases in the review, one of which was rechallenge-positive and other causes of AP were excluded with certainty [42,43]. Saini et al. agreed with the latter classification and therefore assigned it to class IIIb. Finally, all cases described in the literature indicated mild pancreatitis with a good outcome.
3.1.4. Rifampicin
Rifampicin is a bactericidal antibiotic that belongs to class of rifamycins and exerts its mechanism of action by selectively inhibiting bacterial RNA synthesis and blocking transcription. Rifampicin is mainly used for the treatment of nontuberculous mycobacteriosis and tuberculosis and is characterized by a wide spectrum of adverse effects and drug–drug interactions, which, however, are not the subject of this review. In this context, only one case of DIAP caused by rifampicin with a positive rechallenge and uncertain exclusion of other causes of pancreatitis has been described [11].Therefore, it was placed in class Ib of the Wolfe classification and excluded by Simons-Linares et al. and Saini et al. because the reported case was not available in English [11,12].
3.2. Protein Synthesis Inhibitors
3.2.1. Tetracyclines
Tetracyclines are bacteriostatic antibiotics that inhibit protein synthesis by binding to the 30 s subunit of the bacterial ribosome. At least one case of DIAP has been described for drugs in this group (tetracycline, doxycycline, minocycline, tigecycline, and dememocycline [44,45,46].
Tetracycline is not included in the classification of Roberto Simons-Linares et al. because it does not meet the inclusion criteria used, which is probably related to the lack of availability of relevant details in the case.
However, we found three case reports that allowed its classification as class Ia by Wolfe et al. and class IIIb by Saini et al. [9]. Of the reported cases, one is characterized by a positive rechallenge and definitive exclusion of other causes of pancreatitis [24,45,47,48].
Considering Doxycycline, eleven cases of doxycycline-induced acute pancreatitis were reported, four of which were not included in the Roberto Simons-Linares and Wolfe classification. However, because of the different inclusion criteria in the classifications considered, doxycycline was placed in different risk classes. In three of the cases mentioned above, there was no consistent latency between cases and no rechallenge and thus this drug was included in class III in the Simons-Linares classification. In contrast, Wolfe et al. included four different cases from the above-mentioned review, all of which had no positive rechallenge and in which other causes of pancreatitis have been excluded; therefore, the drug was classified as Ic [11,44,46,49,50,51,52,53,54,55].
Saini et al. considered four cases reported in the literature, two of which were not included in the above classifications, all of which had a consistent latency period with no positive rechallenge [56]. The drug was therefore classified as IIIc [9].
Mild to moderate forms of pancreatitis were described in all reported cases, with the exception of a single case of severe pancreatitis.
With respect to tigecycline, ten cases of associated DIAP have been described [25,57,58,59,60,61]. However, because of the variable quality of reported cases, this drug is placed in different, often divergent, classes for the classifications considered. Wolfe et al. and Simons-Linares considered it as a high-risk drug for DIAP, placing it in classes Ia and Ib, respectively. This class difference, consistent with the above criteria, was observed because Wolfe et al. included a clinical case describing rechallenge positivity and exclusion of other pancreatitis etiologies that was not evaluated by Simons-Linares [11,25,62,63,64]. In contrast, Saini et al. included only two cases, none of which had rechallenge positivity and/or consistent latency and thus they were included in class IV [9,65]. Overall, mild to moderate pancreatitis with a good outcome occurred in all reported cases.
Minocycline and demeclocycline were not included in the classification of Saini et al. For minocycline, three case reports were described, and none of these reports described a positive rechallenge [66,67,68]. Due to a disagreement regarding the exclusion of other etiologies of pancreatitis and the concordance of latency among the cases considered, minocycline was included in classes III and Ic of the Simons-Linares et al. and Wolfe classifications, respectively.
In contrast, only one case of associated DIAP is suspected for demeclocycline. A positive rechallenge and complete exclusion of other causes of pancreatitis were not reported and thus it was placed in class IV by Wolfe et al. [11].
3.2.2. Macrolides
Macrolides are bacteriostatic antibiotics that inhibit bacterial protein synthesis by binding to the 50 S ribosomal subunit. The spectrum of activity of this class of drugs includes Gram-positive and Gram-negative cocci and atypical bacteria [69].
Several cases of DIAP have been described for several drugs of this class, such as erythromycin, clarithromycin, and roxithromycin.
Twelve cases of erythromycin-induced AP have been described in the literature, at least one of which had a positive rechallenge [70,71,72,73,74,75,76,77,78,79,80,81]. However, in the classifications considered, there is a wide variability in the inclusion of the different drug classes, due to the poor quality of the details reported in the cases, especially regarding the definitive exclusion of other causes of pancreatitis. All cases reported in the literature were mild forms of pancreatitis with a good outcome.
It was classified as class Ia in the Wolfe et al. classification but it was assigned to class III and IV by Simons-Linares et al. and Sai [9,12].
Six cases of DIAP associated with clarithromycin have been reported in the literature, with no one positive rechallenge [82,82,83,84,85,86] For the same reasons explained earlier for erythromycin, there is considerable discordance in the classification systems used for clarithromycin. While it was classified as class Ic in the Wolfe et al. classification, C. Roberto Simons-Linares placed it in class III, and Siani et al. excluded this drug from their review.
It is worth mentioning two cases of mild pancreatitis induced by roxithromycin, one of which was due to the combination with betamethasone [86]. In both cases, no rechallenge positivity was described, and the drug was included in class IV of all classifications considered in this review [9,11,12].
3.3. Trimethoprim/Sulfamethoxazole—Inhibitors of Cellular Metabolism
Sulfonamides such as sulfamethoxazole and trimethoprim interfere with folic acid biosynthesis by competitive inhibition of dihydropteroate synthetase and dihydrofolate reductase, respectively. These two drugs are often combined and are the treatment of choice for nocardiosis, pneumocystosis, Whipple’s disease, and Stenotrophomonas sp. An association between trimethoprim/sulfamethoxazole and DIAP was established in eight case reports [87]. Two case reports described a positive rechallenge without other possible causes of pancreatitis, and the other two cases resulted in death [88,89,90,91]. One of the case reports described a positive lymphocyte stimulation test with sulfamethoxazole, which may suggest that sulfamethoxazole is the main culprit of the reported DIAP [92,93].
According to the classifications of Wolfe and Simons-Linares et al., trimethoprim/sulfamethoxazole was classified as a high-risk drug in class Ia [12]. According to the criteria used by Saini et al., the drug was classified as class IIIb due to the positive rechallenge in the absence of consistent latency among cases [9].
3.4. Inhibitors of Cell Wall Synthesis
3.4.1. Beta-Lactams
Penicillins belong to the group of beta-lactam antibiotics that bind to bacterial transpeptidases and inhibit the synthesis of peptide crosslinks between peptidoglycan chains. Ampicillin and amoxicillin/clavulanate are the two penicillins most likely to be associated with AP [94].
Hanline MHJ has described a case of AP caused by ampicillin in which rechallenge positivity was observed without completely ruling out other causes of pancreatitis [31]. Therefore, the drug was classified as Ib by Wolfe et al. However, Simons-Linares et al. questioned the positive rechallenge because of insufficient data reported by the authors and reclassified ampicillin as III.
For amoxicillin/clavulanate, only two cases of associated DIAP were reported in the literature [95,96]. In neither case was rechallenge positivity described, and in one of these cases, all other causes of pancreatitis were not excluded. However, because of the different inclusion criteria in the systematic reviews, amoxicillin/clavulanate was classified as class Ic by Wolfe and as class IV by Simons-Linares et al. Finally, no penicillins were included in the review by Saini et al. [9,11,12].
Ceftriaxone is the only cephalosporin for which a possible association with DIAP has been seen; it has excellent activity against most Gram-negative and some Gram-positive bacilli [97].
At least two cases of DIAP caused by ceftriaxone have been described, with no consistent latency between cases and no positive rechallenge [97,98,99,100,101]. Therefore, it was included in classes II and III by Wolfe et al. and Simons-Linares et al., respectively. Saini et al. did not include it in their review [9,11,12].
3.4.2. Isoniazid
Isoniazid is an antitubercular antibiotic that inhibits cell wall synthesis and acts specifically on the synthesis of mycolic acids, which are essential components of the cell wall of the bacterium Mycobacterium tuberculosis [102].
Isoniazid has been associated with pancreatitis in several patients, either during chemoprophylaxis or the treatment of tuberculosis [102,103,104,105,106,107,108,109,110,111,112,113,114]. A positive rechallenge was described in a total of seven patients, with other causes excluded in seven patients. Mild to moderate pancreatitis with a good outcome occurred in all reported cases.
Consistent with the Wolfe and Simons-Linares classifications, isoniazid was considered as a high-risk class Ia drug [11,12]. Similarly, Saini et al. classified it as class IIIb because positive rechallenge was confirmed in the absence of adequate latency among cases.
5. Antifungals and Antiparasitics
5.1. Pentamidine
Pentamidine isethionate is a diamino aromatic compound active against Pneumocystis and several protozoan pathogens, including Leishmanii spp., T. b. gambiense, Trypanosoma, Pneumocistis jirovecii [137].
Since the 1980s, numerous case reports have associated pentamidine in all its forms, intravenous, intramuscular, and aerosol, with the onset of AP, in some cases even with fulminant course [138,139,140,141,142,143,144,145,146,147,148,149,150,151,152,153,154,155,156,157]. Three patients in two case reports had positive rechallenge, although details to exclude other causes are not available.
According to the drug classification system reviewed in 2019 by Simons-Linares et al.’s and also Wolfe’s classification, pentamidine was assigned to class Ib [11,12].
Saini et al. placed pentamidine in class IV, likely due to the different inclusion criteria of the case reports used [9].
5.2. Meglumine Antimoniate
Meglumine antimoniate is a pentavalent antimonials recommended as the first-line agent for the treatment of visceral, mucocutaneous, and cutaneous leishmaniasis [158]. The mechanisms of action and toxicity of pentavalent antimonials, including genotoxic effects, remain unclear, but may involve the inhibition of parasite glycolytic and fatty acid oxidative activity, which promotes oxidative stress-induced DNA damage [158,159].
In 1994, it was reported that a series of 49 patients had leishmaniasis, 48 (98%) of whom had chemical pancreatitis (hyperamylasemia and/or hyperlipasemia), although only half of these patients were symptomatic [160,161,162]. Since the 1990s, five case reports have described the occurrence of AP after the administration of meglumine antimoniate, one involving an infant and one involving a patient with the HIV infection and hepatic dysfunction [161,162,163]. Of the cases described, only one had a positive rechallenge. Therefore, it was assigned to class II in the classification by Simons-Linares et al. Alternatively, Wolfe et al. classified meglumine antimoniate as Ib in 2020 [11,12]. However, it does not fit into the more recent classification of Saini et al. for the same reasons given in the previous chapter for pentamidine.
5.3. Paromomycin
Paromomycin is an antimicrobial agent used to treat various parasitic infections, including amoebiasis, cryptosporidiosis, giardiasis, leishmaniasis, and tapeworm infestation [163]. Its mechanism of action is still unclear.
In 1995, Winston W. Tan et al. reported the case of a 39-year-old man with AIDS, who developed AP after receiving paromomycin for intestinal cryptosporidiosis [164]. A positive rechallenge was described when paromomycin was re-administered. However, because of the concurrent HIV and cryptosporidial infection, prior exposure to didanosine/octreotide/pentamidine, and history of alcoholism, the association was weak [164]. According to the reviewed classification system of Simons-Linares et al., it belonged to class IV, whereas Wolfe et al. classified paromomycin as class Ib due to the presence of a positive rechallenge [11]. In contrast, paromomycin, similarly to pentamidine and meglumine antimonate, does not fit the criteria to be included into the more recent classification by Saini et al. [9].
5.4. Stibogluconate
Sodium stibogluconate is a drug used to treat cutaneous, visceral, and mucosal forms of leishmaniasis [165,166]. Its mechanism of action involves a reduction in ATP and GTP synthesis, which contributes to the decrease in macromolecular synthesis and viability of leishmania.
A total of eighteen case reports describes DIAP in patients receiving sodium stibogluconate for the treatment of leishmaniasis [163,163,167,168,169,170,171,172,173,174,175]. In all reported cases, symptoms occurred within one month of starting treatment. A positive rechallenge was described in seven cases, while in eight cases there was an underlying disease that could be associated with pancreatitis, and in four cases the patients were also receiving other drugs that may be associated with DIAP [175]. Therefore, stibogluconate was classified as class Ib according to the drug classification system for assessing association with DIAP by Simons-Linares et al. and also by Wolfe et al. [11,12]. In contrast, similarly to pentamidine and meglumine antimonate, stibogluconate does not fit into the more recent classification review of Saini et al. [9].
5.5. Triazoles
Triazoles are broad-spectrum antifungal agents that act by inhibiting ergosterol synthesis, the major membrane sterol of fungi. Clinically, they are mainly used to treat all types of invasive fungal infections. At least one case of DIP has been described for some drugs of this group (voriconazole and itraconazole). The specific mechanism of action of triazole-induced pancreatitis is still unclear. It is possible that the difference in distribution in pancreatic tissue explains why voriconazole or itraconazole are more often not tolerated by patients in comparison to fluconazole, which is better tolerated. Therefore, it is conceivable that plasma concentrations of the drug are higher than normal in patients who develop DIAP [175,176]. This could occur as a result of drug–drug interactions, impaired liver function, or polymorphisms of cytochromes such as CYP2C19, CYP2C9, and CYP3A4 that metabolize triazoles [9,176].
5.5.1. Itraconazole
Regarding itraconazole, Passier et al. reported four cases of DIAP that developed after oral intake of itraconazole, two of which probably had a positive rechallenge, although this could not be demonstrated by laboratory or radiological investigations in the first episode. Other underlying diseases associated with AP were probably excluded. However, in 50% of cases, patients were taking other drugs concomitantly, which could not be excluded as a cause of DIAP [177]. Thus, itraconazole met the criteria for drug class Ic in the classification of Diana Wolfe et al. and for class IV in the classification of Siani et al., whereas it was excluded in the previous classification system [9,11].
5.5.2. Voriconazole
Regarding voriconazole, Philip A. reported the case of a 16-year-old girl who developed AP during therapy with voriconazole for the treatment of invasive aspergillosis, with a positive rechallenge and exclusion of other causes of pancreatitis [163,178,179]. Thus, while voriconazole was not classified by Wolfe et al. and Siani et al., it met the criteria for drug class Ib in the classification of Diana Wolfe et al. In 2022, Song Qun Li et al. described a second case of acute DIAP, which occurred after taking voriconazole for more than a month in a 16-year-old girl treated for cryptococcal neoformans meningoencephalitis. All other underlying diseases or medications associated with pancreatitis were excluded and rechallenge was not described [179].
5.6. Artesunate
Artesunate is an artemisinin derivative antimalarial whose intravenous form is preferred to quinine for severe malaria [180]. Artesunate, like any other artemisinin, inhibits the polymerization of heme, generates ROS, destabilizes the parasite membrane, alkylates proteins, and inhibits PfATP6 [181]. Mahdi AS reported the case of a 34-year-old man with severe malaria who developed AP after 8 days of intravenous administration of artesunate [174,175,176,177,178,179,180,181,182,183,184]. Other causes of AP were ruled out; however, no rechallenge was performed. Therefore, the drug met the criteria for class IV in the classification of Simons-Linares et al., whereas it belongs to class Ic according to the classification system of Wolfe et al. It was excluded from the review of Siani et al. [9,12].
Table 6 summarizes the antifungals and antiparasitics associated with acute pancreatitis.
Table 6.
Antifungals and antiparasitics associated with acute pancreatitis.
6. Materials and Methods
In this narrative review, we collected all the original reports that described the new onset of acute pancreatitis after the intake of antibiotics, antivirals, antifungals, and antiparasitics.
A literature search was performed using the following electronic databases: PubMed, Scopus, and Embase databases for English and Spanish literature. The last search was run on 31 August 2023. The terms “drug-induced”, OR “medication-induced”, OR “drug-associated”, OR “medication-associated”, OR “chemically induced”, OR “drug” OR “medications” were matched with the word “pancreatitis”. All the terms were searched both as keywords and Medical Subject Headings (MeSH). We hand-searched the bibliographies of relevant (according to titles and abstracts) articles to provide additional references.
Case reports, case series, case–control studies, randomized trials, pharmacoepidemiologic studies, and systematic reviews were included. We did not use any language restriction in the search filter. Among the different drug categories, only papers involving antibiotics, antifungals, antiparasitics, and antivirals were selected. Results were subsequently divided by pharmacologic class according to mechanism of action, and for each drug for which there was at least one case report, an additional search was performed for the additional available evidence. The association with DIAP was defined for each drug using the classification criteria of the different classifications proposed in the literature. We did not include non-original reports or animal model studies.
Titles and abstracts were independently assessed by three reviewers (A.D.G., C.C., and F.D.V.) to determine the eligibility of the studies. Both investigators checked the fulfillment of inclusion and exclusion criteria; in the case of doubt, the full text of the articles was retrieved and reviewed. A fourth author (E.C.N.) arbitrated in all the cases for a lack of agreement.
Data from eligible studies were independently extracted by three reviewers (A.D.G., C.C., and F.D.V.) and then were cross-checked. Discrepancies were rectified by consensus. If the article grouped patients from a previous study and newly enrolled ones, only the latter were considered. In the case of mixed cohorts, only data regarding patients who respected the eligibility criteria were included in the analysis.
7. Conclusions
There is little evidence for most drugs mentioned in the literature that are identified as triggers of AP. For antimicrobial and antiviral drugs, a total of 51 associations were reported. The drugs with the highest evidence are didanosine, protease inhibitors, and metronidazole. However, we highlight the additional drugs for which there is more evidence of a positive rechallenge in case reports including Isoniazid, tetracyclines, trimethoprim/sulfamethoxazole and erythromycin, lamivudine, pentamidine, stibogluconate, and voriconazole. For the remaining drugs, there is conflicting information because the assignment to a specific probability class in the articles reviewed is left to the judgement of the investigators on the quality of the case reports, and on different inclusion criteria. As a result, there is tremendous variability among current classifications, with the same drug being assigned to significantly different probability classes based on the same reports. Such problems arise with classification models based only on case reports, as in Wolfe et al. and Simons-Linares et al., and as it is well known that these types of papers represent the lowest level of scientific evidence. In addition, the number of DIAP reports for some drugs may also be increasing because of perceptions by the medical community. However, an arbitrary number of case reports is not necessary to increase the strength of evidence for an association and to distinguish it from a causal and nonrandom association. These are the reasons why randomized controlled trials are considered the gold standard. In their classification, Saini et al. created probability classes by considering not only case reports but also cohort studies, pharmacoepidemiologic analyses, and RCTs and thus differed from previous classifications. However, this approach also has its limitations, such as the fact that some studies are not designed to identify AP cases and that investigator reports may be underestimated. In conclusion, we believe that the results of multiple reports of AP cases during therapy should be considered as a basis for conducting prospective randomized controlled trials, improving the quality of evidence. In this way, helpful information can be obtained for the physician to decide whether the drug should be continued or possibly discontinued. In addition, for drugs with better evidence, most mechanisms of harm are still suspected or unknown. Further studies are needed to confirm the suspected etiopathogenetic mechanisms.
Author Contributions
Conceptualization, E.C.N. and T.M.; methodology, E.C.N.; validation, E.C.N. and A.N.; formal analysis, A.N.; investigation, V.S.; resources, A.D.G., C.C. and F.D.V.; data curation, M.C.; writing—original draft preparation, A.D.G., C.C., S.S.D.L. and F.D.V.; writing—review and editing, A.D.G., C.C. and F.D.V.; visualization, M.C.; supervision, A.G.; project administration, E.C.N. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Banks, P.A.; Bollen, T.L.; Dervenis, C.; Gooszen, H.G.; Johnson, C.D.; Sarr, M.G.; Tsiotos, G.G.; Vege, S.S.; Acute Pancreatitis Classification Working Group. Classification of Acute Pancreatitis—2012: Revision of the Atlanta Classification and Definitions by International Consensus. Gut 2013, 62, 102–111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Andersson, B.; Appelgren, B.; Sjödin, V.; Ansari, D.; Nilsson, J.; Persson, U.; Tingstedt, B.; Andersson, R. Acute Pancreatitis—Costs for Healthcare and Loss of Production. Scand. J. Gastroenterol. 2013, 48, 1459–1465. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Szatmary, P.; Grammatikopoulos, T.; Cai, W.; Huang, W.; Mukherjee, R.; Halloran, C.; Beyer, G.; Sutton, R. Acute Pancreatitis: Diagnosis and Treatment. Drugs 2022, 82, 1251–1276. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rompianesi, G.; Hann, A.; Komolafe, O.; Pereira, S.P.; Davidson, B.R.; Gurusamy, K.S. Serum Amylase and Lipase and Urinary Trypsinogen and Amylase for Diagnosis of Acute Pancreatitis. Cochrane Database Syst. Rev. 2017, 4, CD012010. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kiriyama, S.; Gabata, T.; Takada, T.; Hirata, K.; Yoshida, M.; Mayumi, T.; Hirota, M.; Kadoya, M.; Yamanouchi, E.; Hattori, T.; et al. New Diagnostic Criteria of Acute Pancreatitis. J. Hepatobiliary Pancreat. Sci. 2010, 17, 24–36. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iannuzzi, J.P.; King, J.A.; Leong, J.H.; Quan, J.; Windsor, J.W.; Tanyingoh, D.; Coward, S.; Forbes, N.; Heitman, S.J.; Shaheen, A.-A.; et al. Global Incidence of Acute Pancreatitis Is Increasing Over Time: A Systematic Review and Meta-Analysis. Gastroenterology 2022, 162, 122–134. [Google Scholar] [CrossRef] [Scilit]
- Petrov, M.S.; Yadav, D. Global Epidemiology and Holistic Prevention of Pancreatitis. Nat. Rev. Gastroenterol. Hepatol. 2019, 16, 175–184. [Google Scholar] [CrossRef] [Scilit]
- Niinomi, I.; Hosohata, K.; Oyama, S.; Inada, A.; Wakabayashi, T.; Iwanaga, K. Pharmacovigilance Assessment of Drug-Induced Acute Pancreatitis Using a Spontaneous Reporting Database. Int. J. Toxicol. 2019, 38, 487–492. [Google Scholar] [CrossRef] [Scilit]
- Saini, J.; Marino, D.; Badalov, N.; Vugelman, M.; Tenner, S. Drug-Induced Acute Pancreatitis: An Evidence-Based Classification (Revised). Clin. Transl. Gastroenterol. 2023, 14, e00621. [Google Scholar] [CrossRef] [Scilit]
- Sosnowski, K.; Nehring, P.; Przybyłkowski, A. Pancreas and Adverse Drug Reactions: A Literature Review. Drug Saf. 2022, 45, 929–939. [Google Scholar] [CrossRef] [Scilit]
- Wolfe, D.; Kanji, S.; Yazdi, F.; Barbeau, P.; Rice, D.; Beck, A.; Butler, C.; Esmaeilisaraji, L.; Skidmore, B.; Moher, D.; et al. Drug Induced Pancreatitis: A Systematic Review of Case Reports to Determine Potential Drug Associations. PLoS ONE 2020, 15, e0231883. [Google Scholar] [CrossRef] [Scilit]
- Roberto Simons-Linares, C.; Elkhouly, M.A.; Salazar, M.J. Drug-Induced Acute Pancreatitis in Adults: An Update. Pancreas 2019, 48, 1263–1273. [Google Scholar] [CrossRef] [Scilit]
- Trivedi, C.D.; Pitchumoni, C.S. Drug-Induced Pancreatitis. J. Clin. Gastroenterol. 2005, 39, 709–716. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Badalov, N.; Baradarian, R.; Iswara, K.; Li, J.; Steinberg, W.; Tenner, S. Drug-Induced Acute Pancreatitis: An Evidence-Based Review. Clin. Gastroenterol. Hepatol. 2007, 5, 648–661.e3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dhir, R.; Brown, D.K.; Olden, K.W. Drug-Induced Pancreatitis: A Practical Review. Drugs Today 2007, 43, 499. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Teich, N.; Mohl, W.; Bokemeyer, B.; Bündgens, B.; Büning, J.; Miehlke, S.; Hüppe, D.; Maaser, C.; Klugmann, T.; Kruis, W.; et al. Azathioprine-Induced Acute Pancreatitis in Patients with Inflammatory Bowel Diseases—A Prospective Study on Incidence and Severity. J. Crohns Colitis 2016, 10, 61–68. [Google Scholar] [CrossRef] [Scilit]
- Pavlos, R.; Mallal, S.; Phillips, E. HLA and Pharmacogenetics of Drug Hypersensitivity. Pharmacogenomics 2012, 13, 1285–1306. [Google Scholar] [CrossRef] [Scilit]
- Gerstner, T.; Büsing, D.; Bell, N.; Longin, E.; Kasper, J.-M.; Klostermann, W.; Hebing, B.; Hanefeld, F.; Eckel, U.; Hoffmann, R.; et al. Valproic Acid-Induced Pancreatitis: 16 New Cases and a Review of the Literature. J. Gastroenterol. 2007, 42, 39–48. [Google Scholar] [CrossRef] [Scilit]
- Cappell, M.S.; Marks, M. Acute Pancreatitis in HIV-Seropositive Patients: A Case Control Study of 44 Patients. Am. J. Med. 1995, 98, 243–248. [Google Scholar] [CrossRef] [Scilit]
- Qin, W.; Zhao, B.; Shang, Y.; Zhang, L. Clinical Profile of Acute Pancreatitis Following Treatment with Protease Inhibitors: A Real-World Analysis of Post-Marketing Surveillance Data. Expert Opin. Drug Saf. 2021, 20, 1109–1115. [Google Scholar] [CrossRef] [Scilit]
- Li, C.; Jiang, M.; Pan, C.; Li, J.; Xu, L. The Global, Regional, and National Burden of Acute Pancreatitis in 204 Countries and Territories, 1990–2019. BMC Gastroenterol. 2021, 21, 332. [Google Scholar] [CrossRef] [Scilit]
- Foli, A.; Benvenuto, F.; Piccinini, G.; Bareggi, A.; Cossarizza, A.; Lisziewicz, J.; Lori, F. Direct Analysis of Mitochondrial Toxicity of Antiretroviral Drugs. AIDS 2001, 15, 1687–1694. [Google Scholar] [CrossRef] [Scilit]
- Manfredi, R.; Calza, L. HIV Infection and the Pancreas: Risk Factors and Potential Management Guidelines. Int. J. STD AIDS 2008, 19, 99–105. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tariq, S.; Rizvi, S.F.A.; Anwar, U. Tetracycline: Classification, Structure Activity Relationship and Mechanism of Action as a Theranostic Agent for Infectious Lesions—A Mini Review. Biomed. J. Sci. Tech. Res. 2018, 7, 5787–5796. [Google Scholar] [CrossRef] [Scilit]
- Gilson, M.; Moachon, L.; Jeanne, L.; Dumaine, V.; Eyrolle, L.; Morand, P.; Ben M’rad, M.; Salmon, D. Acute Pancreatitis Related to Tigecycline: Case Report and Review of the Literature. Scand. J. Infect. Dis. 2008, 40, 681–683. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sura, M.E.; Heinrich, K.A.; Suseno, M. Metronidazole-Associated Pancreatitis. Ann. Pharmacother. 2000, 34, 1152–1155. [Google Scholar] [CrossRef]
- Wu, S.-D.; Zhang, Z.-H.; Jin, J.-Z.; Kong, J.; Wang, W.; Zhang, Q.; Li, D.-Y.; Wang, M.-F. Effects of Narcotic Analgesic Drugs on Human Oddi’s Sphincter Motility. World J. Gastroenterol. 2004, 10, 2901–2904. [Google Scholar] [CrossRef] [Scilit]
- O’Rourke, A.; Beyhan, S.; Choi, Y.; Morales, P.; Chan, A.P.; Espinoza, J.L.; Dupont, C.L.; Meyer, K.J.; Spoering, A.; Lewis, K.; et al. Mechanism-of-action classification of antibiotics by global transcriptome profiling. Antimicrob. Agents Chemother. 2020, 64, 207–219. [Google Scholar] [CrossRef] [Scilit]
- Sanford, K.A.; Mayle, J.E.; Dean, H.A.; Greenbaum, D.S. Metronidazole-Associated Pancreatitis. Ann. Intern. Med. 1988, 109, 756–757. [Google Scholar] [CrossRef] [Scilit]
- Qian, C.; Abourizk, N.; Rizk, M.-A.; Kim, J.; Smith, D.L.; Westra, K.C.; McLaughlin, J.P. A Rare Case of Metronidazole Induced Recurrent Pancreatitis. Pancreatology 2021, 21, 318–319. [Google Scholar] [CrossRef] [Scilit]
- Barbulescu, A.; Oskarsson, V.; Lindblad, M.; Ljung, R.; Brooke, H.L. Oral Metronidazole Use and Risk of Acute Pancreatitis: A Population-Based Case-Control Study. Clin. Epidemiol. 2018, 10, 1573–1581. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Norgaard, M.; Ratanajamit, C.; Jacobsen, J.; Skriver, M.V.; Pedersen, L.; Sorensen, H.T. Metronidazole and Risk of Acute Pancreatitis: A Population-Based Case-Control Study. Aliment. Pharmacol. Ther. 2005, 21, 415–420. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raether, W.; Hänel, H. Nitroheterocyclic Drugs with Broad Spectrum Activity. Parasitol. Res. 2003, 90, S19–S39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Slim, R.; Salem, C.B.; Zamy, M.; Fathallah, N.; Raynaud, J.-J.; Bouraoui, K.; Biour, M. Secnidazole-Induced Acute Pancreatitis: A New Side-Effect for an Old Drug? JOP 2010, 11, 85–86. [Google Scholar]
- Hegazi, M.O.; Saleh, F.; John, J.E. Is It Tinidazole-Induced Pancreatitis? J. Clin. Pharm. Ther. 2015, 40, 607–608. [Google Scholar] [CrossRef] [Scilit]
- Kefeli, A.; Aktürk, A.; Yeniova, A.Ö.; Basyigit, S. Ciprofloxacin Induced Pancreatitis: Has This Condition Been Overlooked? Acta Gastroenterol. Belg. 2016, 79, 65–66. [Google Scholar]
- Sunga, H.Y.; Kim, J., II; Lee, H.J.; Cho, H.J.; Cheung, D.Y.; Kim, S.S.; Cho, S.H.; Kim, J.K. Acute Pancreatitis Secondary to Ciprofloxacin Therapy in Patients with Infectious Colitis. Gut Liver 2014, 8, 265–270. [Google Scholar] [CrossRef] [Scilit]
- Jiménez Moreno, M.A.; Hontoria Bautista, G.; Pereda García, R. Acute Pancreatitis Associated with Levofloxacin. Rev. Española Enfermedades Dig. 2020, 112, 510. [Google Scholar] [CrossRef] [Scilit]
- Bush, N.; Sharma, V.; Chandrahasan, K.; Patil, A. Ofloxacin-Ornidazole Fixed-Dose Combination Medication-Induced Pancreatitis with Positive Rechallenge. J. Fam. Med. Prim. Care 2020, 9, 3157–3159. [Google Scholar] [CrossRef] [Scilit]
- Drabo, Y.J.; Niakara, A.; Ouedraogo, H. Pancréatite Aiguë Secondaire à Une Prise de Norfloxacine. Ann. Fr. Anesth. Reanim. 2002, 21, 68–69. [Google Scholar] [CrossRef] [Scilit]
- Nelis, G.F. Nitrofurantoin-Induced Pancreatitis: Report of a Case. Gastroenterology 1983, 84, 1032–1034. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Christophe, J.L. Pancreatitis Induced by Nitrofurantoin. Gut 1994, 35, 712–713. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mouallem, M.; Sirotin, T.; Farfel, Z. Nitrofurantoin-Induced Pancreatitis. Isr. Med. Assoc. J. 2003, 5, 754–755. [Google Scholar] [PubMed]
- Rawla, P.; Raj, J.P. Doxycycline-Induced Acute Pancreatitis: A Rare Adverse Event. Gastroenterol. Res. 2017, 10, 244–246. [Google Scholar] [CrossRef] [Scilit]
- Elmore, M.F.; Rogge, J.D. Tetracycline-Induced Pancreatitis. Gastroenterology 1981, 81, 1134–1136. [Google Scholar] [CrossRef] [Scilit]
- Wachira, J.K.; Jensen, C.H.; Rhone, K. Doxycycline-Induced Pancreatitis: A Rare Finding. S D Med. 2013, 66, 227–229. [Google Scholar]
- Torosis, J.; Vender, R. Tetracycline-Induced Pancreatitis. J. Clin. Gastroenterol. 1987, 9, 580–581. [Google Scholar] [CrossRef] [Scilit]
- Nicolau, D.P.; Mengedoht, D.E.; Kline, J.J. Tetracycline-Induced Pancreatitis. Am. J. Gastroenterol. 1991, 86, 1669–1671. [Google Scholar]
- Ocal, S.; Selçuk, H.; Korkmaz, M.; Unal, H.; Yilmaz, U. Acute Pancreatitis Following Doxycycline and Ornidazole Coadministration. JOP 2010, 11, 614–616. [Google Scholar]
- Achecar Justo, L.; Rivero Fernández, M.; Cobo Reinoso, J.; Ruiz Del Árbol Olmos, L. Pancreatitis Aguda Inducida Por Doxiciclina. Med. Clin. 2010, 134, 705–706. [Google Scholar] [CrossRef] [Scilit]
- Inayat, F.; Virk, H.H.; Yoon, D.; Riaz, I. Drug-Induced Pancreatitis: A Rare Manifestation of Doxycycline Administration. N. Am. J. Med. Sci. 2016, 8, 117–120. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moy, B.T.; Kapila, N. Probable Doxycycline-Induced Acute Pancreatitis. Am. J. Health-Syst. Pharm. 2016, 73, 286–291. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shah, N.; Razzano, A.; Grendell, J. Doxycycline Induced Severe Acute Pancreatitis: A Rare Finding To A Common Medication. BMJ Case Rep. 2021, 14, e239640. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reiche, W.; Abodunrin, F.; Destache, C.; Rangray, R.; Velagapudi, M. Doxycycline Induced Pancreatitis: An Uncommon Complication of a Common Drug. Pharmacy 2022, 10, 144. [Google Scholar] [CrossRef] [Scilit]
- Bassi, R.; Prakash, P.; Balakrishnan, E.; Cockey, G. Blame It on the Drug: A Rare Case of Recurrent Doxycycline-Induced Pancreatitis. Cureus 2022, 14, e29171. [Google Scholar] [CrossRef] [Scilit]
- Paulraj, S.; Ashok Kumar, P.; Subedi, D. A Common Medication with an Uncommon Adverse Event: A Case of Doxycycline-Induced Pancreatitis. Cureus 2020, 12, e7496. [Google Scholar] [CrossRef] [Scilit]
- Bernas Albeniz, A.; Aveiga Valencia, D.A.; Etxeberria Zabala, L.; Zaldibar-Gerrikagoitia Bilbao, J.; Aguilera Celorrio, L. Pancreatitis Aguda En La Unidad de Cuidados Intensivos Secundaria a Tratamiento Con Tigeciclina. Rev. Esp. Anestesiol. Reanim. 2017, 64, 46–49. [Google Scholar] [CrossRef] [Scilit]
- Davido, B.; Shourick, J.; Makhloufi, S.; Dinh, A.; Salomon, J. True Incidence of Tigecycline-Induced Pancreatitis: How Many Cases Are We Missing? J. Antimicrob. Chemother. 2016, 71, 2994–2995. [Google Scholar] [CrossRef] [Scilit]
- Hung, W.Y.; Kogelman, L.; Volpe, G.; Iafrati, M.; Davidson, L. Tigecycline-Induced Acute Pancreatitis: Case Report and Literature Review. Int. J. Antimicrob. Agents 2009, 34, 486–489. [Google Scholar] [CrossRef] [Scilit]
- Lipshitz, J.; Kruh, J.; Cheung, P.; Cassagnol, M. Tigecycline-Induced Pancreatitis. J. Clin. Gastroenterol. 2009, 43, 93. [Google Scholar] [CrossRef] [Scilit]
- Marot, J.C.; Jonckheere, S.; Munyentwali, H.; Belkhir, L.; Vandercam, B.; Yombi, J.C. Tigecycline-Induced Acute Pancreatitis: About Two Cases and Review of the Literature. Acta Clin. Belg. 2012, 67, 229–232. [Google Scholar] [PubMed]
- De Mesa, C.; Dajoyag-Mejia, M.A.; Regina, I.; Darouiche, R.O. Tigecycline-Induced Acute Pancreatitis with Rechallenge: A Case Report. J. Pharm. Technol. 2013, 29, 3–8. [Google Scholar] [CrossRef] [Scilit]
- Lin, J.; Wang, R.; Chen, J. Tigecycline-Induced Acute Pancreatitis in a Renal Transplant Patient: A Case Report and Literature Review. BMC Infect. Dis. 2018, 18, 201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hemphill, M.T.; Jones, K.R. Tigecycline-Induced Acute Pancreatitis in a Cystic Fibrosis Patient: A Case Report and Literature Review. J. Cyst. Fibros. 2016, 15, e9–e11. [Google Scholar] [CrossRef] [Scilit]
- Prot-Labarthe, S.; Youdaren, R.; Benkerrou, M.; Basmaci, R.; Lorrot, M. Pediatric Acute Pancreatitis Related to Tigecycline. Pediatr. Infect. Dis. J. 2010, 29, 890–891. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boyle, M.P. Minocycline-Induced Pancreatitis in Cystic Fibrosis. Chest. 2001, 119, 1283–1285. [Google Scholar] [CrossRef] [Scilit]
- Chetaille, E.; Delcenserie, R.; Yzet, T.; Decocq, G.; Biour, M.; Andrejak, M. Minocycline Involvement in Two Cases of Acute Pancreatitis. Gastroenterol. Clin. Biol. 1998, 22, 555–556. [Google Scholar]
- Gabriel, J.G.; Bhogal, S.; Kapila, A. Minocycline-Associated Pancreatitis. Am. J. Ther. 2018, 25, e556–e557. [Google Scholar] [CrossRef] [Scilit]
- Anton Aranda, E.; Altuna Basurto, E. Acute Pancreatitis and Erythromycin. Med. Clin. 1991, 96, 638. [Google Scholar]
- Berger, T.M.; Cook, W.J.; O’Marcaigh, A.S.; Zimmerman, D. Acute Pancreatitis in a 12-Year-Old Girl after an Erythromycin Overdose. Pediatrics 1992, 90, 624–626. [Google Scholar] [CrossRef] [Scilit]
- Gonzalez Carro, P.; Ribes, F.; Garcia, M.J. Acute Pancreatitis Associated with Erythromycin [2]. Rev. Esp. Enfermedades Dig. 1995, 87, 757–758. [Google Scholar]
- Fang, C.-C.; Wang, H.-P.; Lin, J.-T. Erythromycin-Induced Acute Pancreatitis. J. Toxicol. Clin. Toxicol. 1996, 34, 93–95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guerrero Igea, F.J.; Lepe Jiménez, J.A.; Garrido Serrano, A.; Palomo Gil, S. Acute Pancreatitis Caused by Erythromycin. An. Med. Interna 2001, 18, 400. [Google Scholar] [PubMed]
- Gumaste, V.V. Erythromycin-Induced Pancreatitis. Am. J. Med. 1989, 86, 725. [Google Scholar] [CrossRef] [Scilit]
- Hawksworth, C.R. Acute Pancreatitis Associated with Infusion of Erythromycin Lactobionate. BMJ 1989, 298, 190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pascual Velasco, F.; Goicoechea Ibarra, L.; Bichara Antanios, G. Acute Pancreatitis Induced by Erythromycin: A New Case. Med. Clin. 1991, 97, 473–474. [Google Scholar]
- Surinach, J.M.; Alegre, J.; Fernandez de Sevilla, T.; Queralt, M. Acute Pancreatitis from Erythromycin. Rev. Clin. Esp. 1993, 192, 458. [Google Scholar]
- Teillet, L.; Chaussade, S.; Mory, B.; Roche, H.; Couturier, D.; Guerre, J. Drug-Induced Acute Pancreatitis following Intravenous Erythomycin Antibiotherapy. Gastroenterol. Clin. Biol. 1991, 15, 265–266. [Google Scholar]
- Tenenbein, M.S.; Tenenbein, M. Acute Pancreatitis Due to Erythromycin Overdose. Pediatr. Emerg. Care 2005, 21, 675–676. [Google Scholar] [CrossRef] [Scilit]
- Acharya, G.K.; Hita, A.G.; Yeung, S.-C.J. Diabetic Ketoacidosis and Acute Pancreatitis: Serious Adverse Effects of Everolimus. Ann. Emerg. Med. 2017, 69, 666–667. [Google Scholar] [CrossRef] [Scilit]
- Wong, P.W.K.; Dillard, T.A.; Kroenke, K. Multiple Organ Toxicity From Addition of Erythromycin to Long-Term Lovastatin Therapy. South. Med. J. 1998, 91, 202–205. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Avraam, C.; Siomos, K.; Armenaka, M.; Sion, M.L. Clarithromycin associated acute pancreatitis. Ann. Gastroenterol. 2007, 20, 35–37. [Google Scholar]
- Schouwenberg, B.J.J.W.; Deinum, J. Acute Pancreatitis after a Course of Clarithromycin. Neth. J. Med. 2003, 61, 266–267. [Google Scholar]
- Carro, P.G.; Roldán, F.P.; Huidobro, M.L.L.; de Acufia, M.M.; García, J.C.N. Acute Pancreatitis and Modified-Release Clarithromycin. Ann. Pharmacother. 2004, 38, 508–509. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pomero, F.; Fenoglio, L.; Melchio, R.; Serraino, C.; Ageno, W.; Dentali, F. Incidence and Diagnosis of Pulmonary Embolism in Northern Italy: A Population-Based Study. Eur. J. Intern. Med. 2013, 24, e77–e78. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Renkes, P.; Petitpain, N.; Cosserat, F.; Bangratz, S.; Trechot, P. Can Roxithromycin and Betamethasone Induce Acute Pancreatitis? A Case Report. JOP 2003, 4, 184–186. [Google Scholar] [PubMed]
- Park, T.Y.; Oh, H.-C.; Do, J.H. A Case of Recurrent Pancreatitis Induced by Trimethoprim-Sulfamethoxazole Re-Exposure. Gut Liver 2010, 4, 250–252. [Google Scholar] [CrossRef] [Scilit]
- Versleijen, M.W.; Naber, A.H.; Riksen, N.P.; Wanten, G.J.; Debruyne, F.M.J. Recurrent Pancreatitis after Trimethoprim-Sulfamethoxazole Rechallenge. Neth. J. Med. 2005, 63, 275–277. [Google Scholar]
- Brett, A.S.; Shaw, S.V. Simultaneous pancreatitis and hepatitis associated with trimethoprim-sulfamethoxazole. Am. J. Gastroenterol. 1999, 94, 267–268. [Google Scholar] [CrossRef]
- Bartels, R.H.M.A.; van der Spek, J.A.N.; Oosten, H.R. Acute Pancreatitis Due to Sulfamethoxazole-Trimethoprim. South. Med. J. 1992, 85, 1006–1007. [Google Scholar] [CrossRef] [Scilit]
- Alberti-Flor, J.J.; Hernandez, M.E.; Ferrer, J.P.; Howell, S.; Jeffers, L. Fulminant Liver Failure and Pancreatitis Associated with the Use of Sulfamethoxazole-Trimethoprim. Am. J. Gastroenterol. 1989, 84, 1577–1579. [Google Scholar] [PubMed]
- Brazer, S.R.; Medoff, J.R. Sulfonamide-Induced Pancreatitis. Pancreas 1988, 3, 583–586. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Antonow, D.R. Acute Pancreatitis Associated with Trimethoprim-Sulfamethoxazole. Ann. Intern. Med. 1986, 104, 363–365. [Google Scholar]
- Hanline, M.H. Acute Pancreatitis Caused By Ampicillin. South. Med. J. 1987, 80, 1069. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chams, S.; El Sayegh, S.; Hamdon, M.; Kumar, S.; Tegeltija, V. Amoxicillin/Clavulanic Acid-Induced Pancreatitis: Case Report. BMC Gastroenterol. 2018, 18, 122. [Google Scholar] [CrossRef] [Scilit]
- Galindo, C.; Buenestado, J.; Rene Espinet, J.M.; Pinol, M.C. Acute Pancreatitis and Liver Injury Associated with Amoxicillin-Clavulanic Therapy. Rev. Esp. Enfermedades Dig. 1995, 87, 597–600. [Google Scholar]
- Famularo, G.; Polchi, S.; De Simone, C. Acute Cholecystitis and Pancreatitis in a Patient with Biliary Sludge Associated with the Use of Ceftriaxone: A Rare but Potentially Severe Complication. Ann. Ital. Med. Int. 1999, 14, 202–204. [Google Scholar]
- Maranan, M.C.; Gerber, S.I.; Miller, G.G. Gallstone pancreatitis caused by ceftriaxone. Pediatr. Infect. Dis. J. 1998, 17, 662–663. [Google Scholar] [CrossRef] [Scilit]
- Zimmermann, A.E.; Katona, B.G.; Jodhka, J.S.; Williams, R.B. Ceftriaxone-Induced Acute Pancreatitis. Ann. Pharmacother. 1993, 27, 36–37. [Google Scholar] [CrossRef] [Scilit]
- Zinberg, J.; Chernaik, R.; Coman, E.; Rosenblatt, R.; Brandt, L.J. Reversible Symptomatic Biliary Obstruction Associated with Ceftriaxone Pseudolithiasis. Am. J. Gastroenterol. 1991, 86, 1251–1254. [Google Scholar]
- Nakagawa, N.; Ochi, N.; Yamane, H.; Honda, Y.; Nagasaki, Y.; Urata, N.; Nakanishi, H.; Kawamoto, H.; Takigawa, N. Ceftriaxone-Associated Pancreatitis Captured on Serial Computed Tomography Scans. Radiol. Case Rep. 2018, 13, 43–46. [Google Scholar] [CrossRef] [Scilit]
- Pandey, A.S.; Surana, A. Isoniazid-Induced Recurrent Acute Pancreatitis. Trop. Doct 2011, 41, 249–250. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mattioni, S.; Zamy, M.; Mechai, F.; Raynaud, J.-J.; Chabrol, A.; Aflalo, V.; Biour, M.; Bouchaud, O. Isoniazid-Induced Recurrent Pancreatitis. JOP 2012, 13, 314–316. [Google Scholar] [PubMed]
- Kharibam, P.; Jithesh, G.; Ronanki, K.; Pathania, M. A Rare Case of Isoniazid Induced Recurrent Acute Pancreatitis. J. Cardiovasc. Dis. Res. 2021, 12, 1121–1124. [Google Scholar]
- Briongos-Figuero, L.S.; Bachiller-Luque, P.; Pons-Renedo, F.; Eiros-Bouza, J.M. Pancreatitis Aguda Inducida Por Isoniazida. Enfermedades Infecc. Microbiol. Clin. 2007, 25, 217–218. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chan, K.L.; Chan, H.S.; Lui, S.F.; Lai, K.N. Recurrent Acute Pancreatitis Induced by Isoniazid. Tuber. Lung Dis. 1994, 75, 383–385. [Google Scholar] [CrossRef] [Scilit]
- Chow, K.M.; Szeto, C.C.; Leung, C.B.; Li, P.K.T. Recurrent Acute Pancreatitis after Isoniazid. Neth. J. Med. 2004, 62, 172–174. [Google Scholar]
- Izzedine, H.; Launay-Vacher, V.; Storme, T.; Deray, G. Acute Pancreatitis Induced by Isoniazid. Am. J. Gas Troenterol. 2001, 96, 3208–3209. [Google Scholar] [CrossRef]
- Mendoza, J.L.; Larrubia, J.R.; Lana, R.; Espinos, D.; Diaz-Rubio, M. Acute Pancreatitis Induced by Isoniazid, a Casual Association. An. Med. Interna 1998, 15, 588–590. [Google Scholar]
- Rabassa, A.A. Isoniazid-Induced Acute Pancreatitis. Ann. Intern. Med. 1994, 121, 433. [Google Scholar] [CrossRef] [Scilit]
- Saleem, A.F.; Arbab, S.; Naz, F.Q. Isoniazid Induced Acute Pancreatitis in a Young Girl. J. Coll. Physicians Surg. Pak. 2015, 25, 299–300. [Google Scholar]
- Sanchez, A.J.; Boken, D.J. Isoniazid-Associated Pancreatitis. Infect. Med. 2004, 21, 622–623. [Google Scholar]
- Stephenson, I.; Wiselka, M.J.; Qualie, M.J. Acute Pancreatitis Induced by Isoniazid in the Treatment of Tuberculosis. Am. J. Gastroenterol. 2001, 96, 2271–2272. [Google Scholar] [CrossRef]
- Yi, P.H.; Veltre, D.R.; Kuttab, J.S.; Rangan, V.; Norton, L. Acute Groove Pancreatitis Due to Isoniazid. Neth. J. Med. 2013, 71, 104. [Google Scholar]
- Ghosh, A.K.; Osswald, H.L.; Prato, G. Recent Progress in the Development of HIV-1 Protease Inhibitors for the Treatment of HIV/AIDS. J. Med. Chem. 2016, 59, 5172–5208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hughes, P.J.; Cretton-Scott, E.; Teague, A.; Wensel, T.M. Protease Inhibitors for Patients with HIV-1 Infection: A Comparative Overview. Phys. Ther. Rehabil. J. 2011, 36, 332–345. [Google Scholar]
- Lin, C.; Verma, V.; Lazenby, A.; Ly, Q.P.; Berim, L.D.; Schwarz, J.K.; Madiyalakan, M.; Nicodemus, C.F.; Hollingsworth, M.A.; Meza, J.L.; et al. Phase I/II Trial of Neoadjuvant Oregovomab-Based Chemoimmunotherapy Followed by Stereotactic Body Radiotherapy and Nelfinavir For Locally Advanced Pancreatic Adenocarcinoma. Am. J. Clin. Oncol. 2019, 42, 755–760. [Google Scholar] [CrossRef] [Scilit]
- Di Martino, V.; Ezenfis, J.; Benhamou, Y.; Bernard, B.; Opolon, P.; Bricaire, F.; Poynard, T. Severe Acute Pancreatitis Related to the Use of Nelfinavir in HIV Infection: Report of a Case with Positive Rechallenge. AIDS 1999, 13, 1421–1423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ventura, C.; Urich, R.; Skinner, S.; Bina, R.; Chuang, K.-Y.; Van Thiel, D.H.; Nadir, A. First Report of Telaprevir-Induced Pancreatitis. Dig. Dis. Sci. 2013, 58, 887–888. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bilar, J.M.; Mota, C.F.M.G.P.; Carvalho-Filho, R.J.; da Silva Fucuta, P.; Ferraz, M.L.C.G. Acute Pancreatitis Associated with Boceprevir: A Case Report. Braz. J. Infect. Dis. 2014, 18, 454–456. [Google Scholar] [CrossRef] [Scilit]
- Da Silva, J.; Giroldi, S.B.; Basso, F.d.O.; Antunes, G.N.; Borba, L.A.; de Lima, C.R.M. Acute Pancreatitis during Interferon-Alpha and Ribavirin Treatment for Hepatitis C. BMJ Case Rep. 2009, 2009, 1000–1006. [Google Scholar] [CrossRef] [Scilit]
- Rocca, E. Remdesivir and Pancreatic Toxicity. WHO Pharm. Newsl. 2021, 3, 16–21. Available online: https://www.who.int/publications/i/item/who-pharmaceuticals-newsletter---n-3-2021 (accessed on 1 August 2023).
- Miyazaki, K.; Yoshimura, Y.; Miyata, N.; Sasaki, H.; Shiba, A.; Aga, M.; Hamakawa, Y.; Taniguchi, Y.; Misumi, Y.; Agemi, Y.; et al. Acute Pancreatitis or Severe Increase in Pancreatic Enzyme Levels Following Remdesivir Administration in COVID-19 Patients: An Observational Study. Sci. Rep. 2022, 12, 5323. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Papa, A.; Covino, M.; De Lucia, S.S.; Del Gaudio, A.; Fiorani, M.; Polito, G.; Settanni, C.R.; Piccioni, A.; Franceschi, F.; Gasbarrini, A. Impact of COVID-19 in Individuals with and without Pre-Existent Digestive Disorders with a Particular Focus on Elderly Patients. World J. Gastroenterol. 2023, 29, 4099–4119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Inamdar, S.; Benias, P.C.; Liu, Y.; Sejpal, D.V.; Satapathy, S.K.; Trindade, A.J. Northwell COVID-19 Research Consortium. Prevalence, Risk Factors, and Outcomes of Hospitalized Patients with Coronavirus Disease 2019 Presenting as Acute Pancreatitis. Gastroenterology 2020, 159, 2226–2228.e2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grosser, M.R.; Hale, R.E. Analysis of a COVID-19 Clinical Trial to Emphasize Experimental Design and Quantitative Reasoning in an Introductory Biology Course. J. Microbiol. Biol. Educ. 2021, 22, 10-1128. [Google Scholar] [CrossRef] [Scilit]
- Maxson, C.J.; Greenfield, S.M.; Turner, J.L. Acute Pancreatitis Is a Common Complication of 2′,3′-Dideoxyinosine Therapy in the Acquired Immunodeficiency Syndrome. Am. J. Gas-Troenterol. 1992, 87, 708–713. [Google Scholar]
- Shelton, M.J.; O’Donnell, A.M.; Morse, G.D. Didanosine. Ann. Pharmacother. 1992, 26, 660–670. [Google Scholar] [CrossRef] [Scilit]
- Seidlin, M.; Lambert, J.S.; Dolin, R.; Valentine, F.T. Pancreatitis and Pancreatic Dysfunction in Patients Taking Dideoxyinosine. AIDS 1992, 6, 831–836. [Google Scholar] [CrossRef] [Scilit]
- Grasela, T.H.; Walawander, C.A.; Beltangady, M.; Knupp, C.A.; Martin, R.R.; Dunkle, L.M.; Barbhaiya, R.H.; Pittman, K.A.; Dolin, R.; Valentine, F.T.; et al. Analysis of Potential Risk Factors Associated with the Development of Pancreatitis in Phase I Patients with AIDS or AIDS-Related Complex Receiving Didanosine. J. Infect. Dis. 1994, 169, 1250–1255. [Google Scholar] [CrossRef] [Scilit]
- Oliveira, N.M.; Ferreira, F.A.Y.; Yonamine, R.Y.; Chehter, E.Z. Antiretroviral Drugs and Acute Pancreatitis in HIV/AIDS Patients: Is There Any Association? A Literature Review. Einstein 2014, 12, 112–119. [Google Scholar] [CrossRef] [Scilit]
- Sarner, L.; Fakoya, A. Acute Onset Lactic Acidosis and Pancreatitis in the Third Trimester of Pregnancy in HIV-1 Positive Women Taking Antiretroviral Medication. Sex. Transm. Infect. 2002, 78, 58–59. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reisler, R.B.; Murphy, R.L.; Redfield, R.R.; Parker, R.A. Incidence of Pancreatitis in HIV-1-Infected Individuals Enrolled in 20 Adult AIDS Clinical Trials Group Studies: Lessons Learned. J. Acquir. Immune Defic. Syndr. 2005, 39, 159–166. [Google Scholar] [PubMed]
- Umar, J.; Zayac, A.; Masood, U.; Rawlins, S. Lamivudine-Associated Pancreatitis: Strongest Evidence to Date. Am. J. Ther. 2017, 24, e636–e637. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goffin, E.; Horsmans, Y.; Pirson, Y.; Cornu, C.; Geubel, A.; van Ypersele De Strihou, C. Acute Necrotico-Hemorrhagic Pancreatitis after Famciclovir Prescription. Transplantation 1995, 59, 1218–1219. [Google Scholar]
- Weber, A.; Carbonnel, F.; Simon, N.; Kantelip, B.; Coaquette, A.; Mantion, G.; Miguet, J.-P.; Di Martino, V. Severe Acute Pancreatitis Related to the Use of Adefovir in a Liver Transplant Recipient. Gastroenterol. Clin. Biol. 2008, 32, 247–249. [Google Scholar] [CrossRef] [Scilit]
- Sands, M.; Kron, M.A.; Brown, R.B. Pentamidine: A Review. Rev. Infect. Dis. 1985, 7, 625–634. [Google Scholar] [CrossRef] [Scilit]
- Zhou, Y.; Huang, W.; Lei, E.; Yang, A.; Li, Y.; Wen, K.; Wang, M.; Li, L.; Chen, Z.; Zhou, C.; et al. Cooperative Membrane Damage as a Mechanism for Pentamidine–Antibiotic Mutual Sensitization. ACS Chem. Biol. 2022, 17, 3178–3190. [Google Scholar] [CrossRef] [Scilit]
- Echinard, E.; Dupon, M.; Malou, M.; Ragnaud, J.M.; Lacut, J.Y.; Albin, H. Acute Fatal Pancreatitis Following Treatment with Pentamidine. Therapie 1986, 41, 520. [Google Scholar]
- Foisy, M.M.; Slayter, K.L.; Hewitt, R.G.; Morse, G.D. Pancreatitis during Intravenous Pentamidine Therapy in an AIDS Patient with Prior Exposure to Didanosine. Ann. Pharmacother. 1994, 28, 1025–1028. [Google Scholar] [CrossRef] [Scilit]
- Hart, C.C. Aerosolized Pentamidine and Pancreatitis. Ann. Intern. Med. 1989, 111, 691. [Google Scholar] [CrossRef] [Scilit]
- Herer, B.; Chinet, T.; Labrune, S.; Collignon, M.A.; Chretien, J.; Huchon, G. Pancreatitis Associated with Pentamidine by Aerosol. BMJ 1989, 298, 605. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, S.; Schnadig, V.J.; MacGregor, M.G. Fatal Acute Pancreatitis Associated with Pentamidine Therapy. Am. J. Gastroenterol. 1989, 84, 451–453. [Google Scholar]
- Salah, A.; Lortholary, O.; Lhote, F.; Cohen, P.; Guillevin, L. Acute Pancreatitis Induced by Pentamidine Isethionate in Aerosols. Presse Med. 1994, 23, 49. [Google Scholar]
- Harris, A.G.; Caroli-Bosc, F.X.; Demarquay, J.F.; Hastier, P.; Delmont, J. Acute Pancreatitis in an Octreotide-Treated AIDS Patient—Suggested Alternative Mechanisms. Pancreas 1995, 11, 318–319. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Neil, M.G.; Selub, S.E.; Hak, L.J. Pancreatitis during Pentamidine Therapy in Patients with AIDS. Clin. Pharm. 1991, 10, 56–59. [Google Scholar] [PubMed]
- Murphey, S.A.; Josephs, A.S. Acute Pancreatitis Associated With Pentamidine Therapy. Arch. Intern. Med. 1981, 141, 56–58. [Google Scholar] [CrossRef]
- Pais, J.R.; Cazorla, C.; Novo, E.; Viana, A. Massive Haemorrhage from Rupture of a Pancreatic Pseudocyst after Pentamidine-Associated Pancreatitis. Eur. J. Med. 1992, 1, 251–253. [Google Scholar]
- Pauwels, A.; Eliaszewicz, M.; Larrey, D.; Lacassin, F.; Poirier, J.M.; Meyohas, M.C.; Frottier, J. Pentamidine-Induced Acute Pancreatitis in a Patient with AIDS. J. Clin. Gastroenterol. 1990, 12, 457–459. [Google Scholar] [CrossRef] [Scilit]
- Salmeron, S.; Petitpretz, P.; Katlama, C.; Herve, P.; Brivet, F.; Simonneau, G.; Duroux, P.; Régnier, B. Pentamidine and Pancreatitis. Ann. Intern. Med. 1986, 105, 140. [Google Scholar] [CrossRef] [Scilit]
- Sauleda, J.; Gea, J.G.; Aguar, M.C.; Aran, X.; Pastó, M.; Broquetas, J.M. Probable Pentamidine-Induced Acute Pancreatitis. Ann. Pharmacother. 1994, 28, 52–53. [Google Scholar] [CrossRef] [Scilit]
- Singh, G.; el-Gadi, S.M.; Sparks, R.A. Pancreatitis Associated with Aerosolised Pentamidine. Sex. Transm. Infect. 1995, 71, 130–131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wood, G.; Wetzig, N.; Hogan, P.; Whitby, M. Survival from Pentamidine Induced Pancreatitis and Diabetes Mellitus. Aust. N. Z. J. Med. 1991, 21, 341–342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Villamil, A.; Hammer, R.A.; Rodriguez, F.H. Edematous Pancreatitis Associated with Intravenous Pentamidine. South. Med. J. 1991, 84, 796–798. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zuger, A.; Wolf, B.Z.; El-Sadr, W.; Simberkoff, M.S.; Rahal, J.J. Pentamidine-Associated Fatal Acute Pancreatitis. JAMA 1986, 256, 2383–2385. [Google Scholar] [CrossRef]
- Murphy, R.L.; Noskin, G.A.; Ehrenpreis, E.D. Acute Pancreatitis Associated with Aerosolized Pentamidine. Am. J. Med. 1990, 88, 53N–56N. [Google Scholar]
- World Health Organization. WHO Model Formulary 2008; Stuart, M.C., Kouimtzi, M., Hill, S.R., Eds.; World Health Organization: Geneva, Switzerland, 2009; p. 183. ISBN 9789241547659. [Google Scholar]
- Moreira, V.R.; de Jesus, L.C.L.; Soares, R.-E.P.; Silva, L.D.M.; Pinto, B.A.S.; Melo, M.N.; de Andrade Paes, A.M.; Pereira, S.R.F. Meglumine Antimoniate (Glucantime) Causes Oxidative Stress-Derived DNA Damage in BALB/c Mice Infected by Leishmania (Leishmania) Infantum. Antimicrob. Agents Chemother. 2017, 61, e02360. [Google Scholar] [CrossRef] [Scilit]
- Barthet, M.; Brunet, P.; Bernard, J.C.; Dussol, B.; Rodor, F.; Jouglard, J.; Berland, Y.; Sahel, J. Acute Pancreatitis during Treatment with Meglumine Antimoniate (Glucantime). Gastroenterol. Clin. Biol. 1994, 18, 90–92. [Google Scholar]
- de Lalla, F.; Pellizzer, G.; Gradoni, L.; Vespignani, M.; Franzetti, M.; Stecca, C. Acute Pancreatitis Associated with the Administration of Meglumine Antimonate for the Treatment of Visceral Leishmaniasis. Clin. Infect. Dis. 1993, 16, 730–731. [Google Scholar] [CrossRef] [Scilit]
- Kuyucu, N.; Kara, C.; Bakirtaç, A.; Teziç, T. Successful treatment of visceral leishmaniasis with allopurinol plus ketoconazole in an infant who developed pancreatitis caused by meglumine antimoniate. Pediatr. Infect. Dis. J. 2001, 20, 455–457. [Google Scholar] [CrossRef] [Scilit]
- Torrús, D.; Massa, B.; Boix, V.; Portilla, J.; Pérez-Mateo, M. Meglumine Antimoniate-Induced Pancreatitis. Am. J. Gastroenterol. 1996, 91, 820–821. [Google Scholar]
- Santos, J.; Rivero, A.; Márquez, M. Acute pancreatitis with a fatal evolution due to antimonials in patients with visceral leishmaniasis and HIV infection. An. Med. Interna 2000, 17, 562–563. [Google Scholar] [PubMed]
- Tan, W.W.; Chapnick, E.K.; Abter, E.I.M.; Haddad, S.; Zimbalist, E.H.; Lutwick, L.I. Paromomycin-Associated Pancreatitis in Hiv-Related Cryptosporidiosis. Ann. Pharmacother. 1995, 29, 22–24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Berman, J.D.; Herwaldt, B.L. Recommendations for Treating Leishmaniasis with Sodium Stibogluconate (Pentostam) and Review of Pertinent Clinical Studies. Am. J. Trop. Med. Hyg. 1992, 46, 296–306. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. Control of the Leishmaniasis: Report of a Meeting of the WHO Expert Committee on the Control of Leishmaniases (PDF); World Health Organization: Geneva, Switzerland, 2010; pp. 55, 186. ISBN 9789241209496. [Google Scholar]
- Berman, J.D.; Waddell, D.; Hanson, B.D. Biochemical Mechanisms of the Antileishmanial Activity of Sodium Stibogluconate. Antimicrob. Agents Chemother. 1985, 27, 916–920. [Google Scholar] [CrossRef] [Scilit]
- Cortes, E.; Ribera, E.; Cucurull, E.; de Otero, J.; Ocana, I.; Pahissa, A. Acute Pancreatitis Due to Antimonials in Patients with Visceral Leishmaniasis and HIV Infection. Med. Clin. 1995, 104, 578–580. [Google Scholar]
- Domingo, P. Acute Pancreatitis Associated with Sodium Stibogluconate Treatment in a Patient with Human Immunodeficiency Virus. Arch. Intern. Med. 1996, 156, 1029. [Google Scholar] [CrossRef] [Scilit]
- Donovan, K.L.; White, A.D.; Cooke, D.A.; Fisher, D.J. Pancreatitis and Palindromic Arthropathy with Effusions Associated with Sodium Stibogluconate Treatment in a Renal Transplant Recipient. J. Infect. 1990, 21, 107–110. [Google Scholar] [CrossRef] [Scilit]
- Gasser, R.A.; Magill, A.J.; Oster, C.N.; Franke, E.D.; Grogl, M.; Berman, J.D. Pancreatitis Induced by Pentavalent Antimonial Agents During Treatment of Leishmaniasis. Clin. Infect. Dis. 1994, 18, 83–90. [Google Scholar] [CrossRef] [Scilit]
- McCarthy, A.E.; Keystone, J.S.; Kain, K.C. Pancreatitis Occurring During Therapy with Stibogluconate: Two Case Reports. Clin. Infect. Dis. 1993, 17, 952–953. [Google Scholar] [CrossRef] [Scilit]
- Halim, M.A.; Alfurayh, O.; Kalin, M.E.; Dammas, S.; Al-Eisa, A.; Damanhouri, G. Successful Treatment of Visceral Leishmaniasis with Allopurinol plus Ketoconazole in a Renal Transplant Recipient after the Occurrence of Pancreatitis Due to Stibogluconate. Clin. Infect. Dis. 1993, 16, 397–399. [Google Scholar] [CrossRef] [Scilit]
- Valencia, M.E.; Laguna, F.; Gonzalez Lahoz, J. Nephrotic Syndrome and Acute Pancreatitis Related to Glucantime Administration. An. Med. Interna 2000, 17, 54. [Google Scholar] [PubMed]
- Meczker, Á.; Hanák, L.; Párniczky, A.; Szentesi, A.; Erőss, B.; Hegyi, P.; Hungarian Pancreatic Study Group. Analysis of 1060 Cases of Drug-Induced Acute Pancreatitis. Gastroenterology 2020, 159, 1958–1961.e8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Felton, T.W.; Hope, W.W.; Roberts, J.A. How Severe Is Antibiotic Pharmacokinetic Variability in Critically Ill Patients and What Can Be Done about It? Diagn. Microbiol. Infect. Dis. 2014, 79, 441–447. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Passier, J.L.M.; van Puijenbroek, E.P.; Jonkers, G.J.P.M.; van Grootheest, A.C. Pancreatitis Associated with the Use of Itraconazole. Neth. J. Med. 2010, 68, 285–289. [Google Scholar]
- Philip, A.; Sivaprakasam, P.; Sagar, T.G.; Ganesan, P. Voriconazole-Induced Pancreatitis in a Patient of Acute Myeloid Leukemia and Invasive Aspergillosis. J. Pediatr. Hematol. Oncol. 2012, 34, 406. [Google Scholar] [CrossRef] [Scilit]
- Song, Q.L.; Guan, Y. A Case of Acute Pancreatitis Induced by Voriconazole during Treatment of Cryptococcal Meningitis. Br. J. Clin. Pharmacol. 2022, 88, 1925–1929. [Google Scholar] [CrossRef] [Scilit]
- Ruwizhi, N.; Maseko, R.B.; Aderibigbe, B.A. Recent Advances in the Therapeutic Efficacy of Artesunate. Pharmaceutics 2022, 14, 504. [Google Scholar] [CrossRef] [Scilit]
- Adebayo, J.O.; Tijjani, H.; Adegunloye, A.P.; Ishola, A.A.; Balogun, E.A.; Malomo, S.O. Enhancing the Antimalarial Activity of Artesunate. Parasitol. Res. 2020, 119, 2749–2764. [Google Scholar] [CrossRef] [Scilit]
- Abanyie, F.; Acharya, S.D.; Leavy, I.; Bowe, M.; Tan, K.R. Safety and Effectiveness of Intravenous Artesunate for Treatment of Severe Malaria in the United States—April 2019 Through December 2020. Clin. Infect. Dis. 2021, 73, 1965–1972. [Google Scholar] [CrossRef] [Scilit]
- Mahdi, A.S.; Molai, M.; Chandwani, J.; Al Khalili, H.; Ibrahim, H.; Pandak, N.; Khamis, F.; Petersen, E. Late Onset Acute Pancreatitis in P. Falciparum Malar—An An adverse reaction to intravenous artesunate? IDCases 2018, 12, 124–126. [Google Scholar] [CrossRef] [Scilit]
- Kurth, F.; Lingscheid, T.; Steiner, F.; Stegemann, M.S.; Bélard, S.; Menner, N.; Pongratz, P.; Kim, J.; von Bernuth, H.; Mayer, B.; et al. Hemolysis after Oral Artemisinin Combination Therapy for Uncomplicated Plasmodium falciparum Malaria. Emerg. Infect. Dis. 2016, 22, 1381–1386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
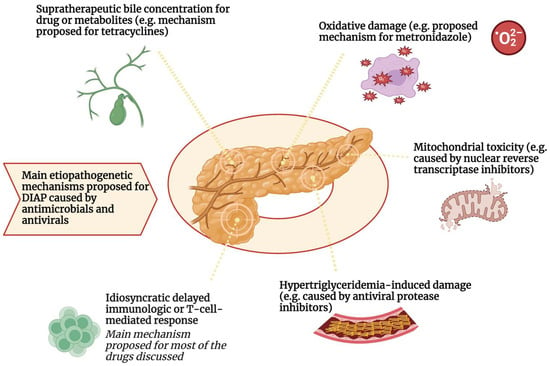
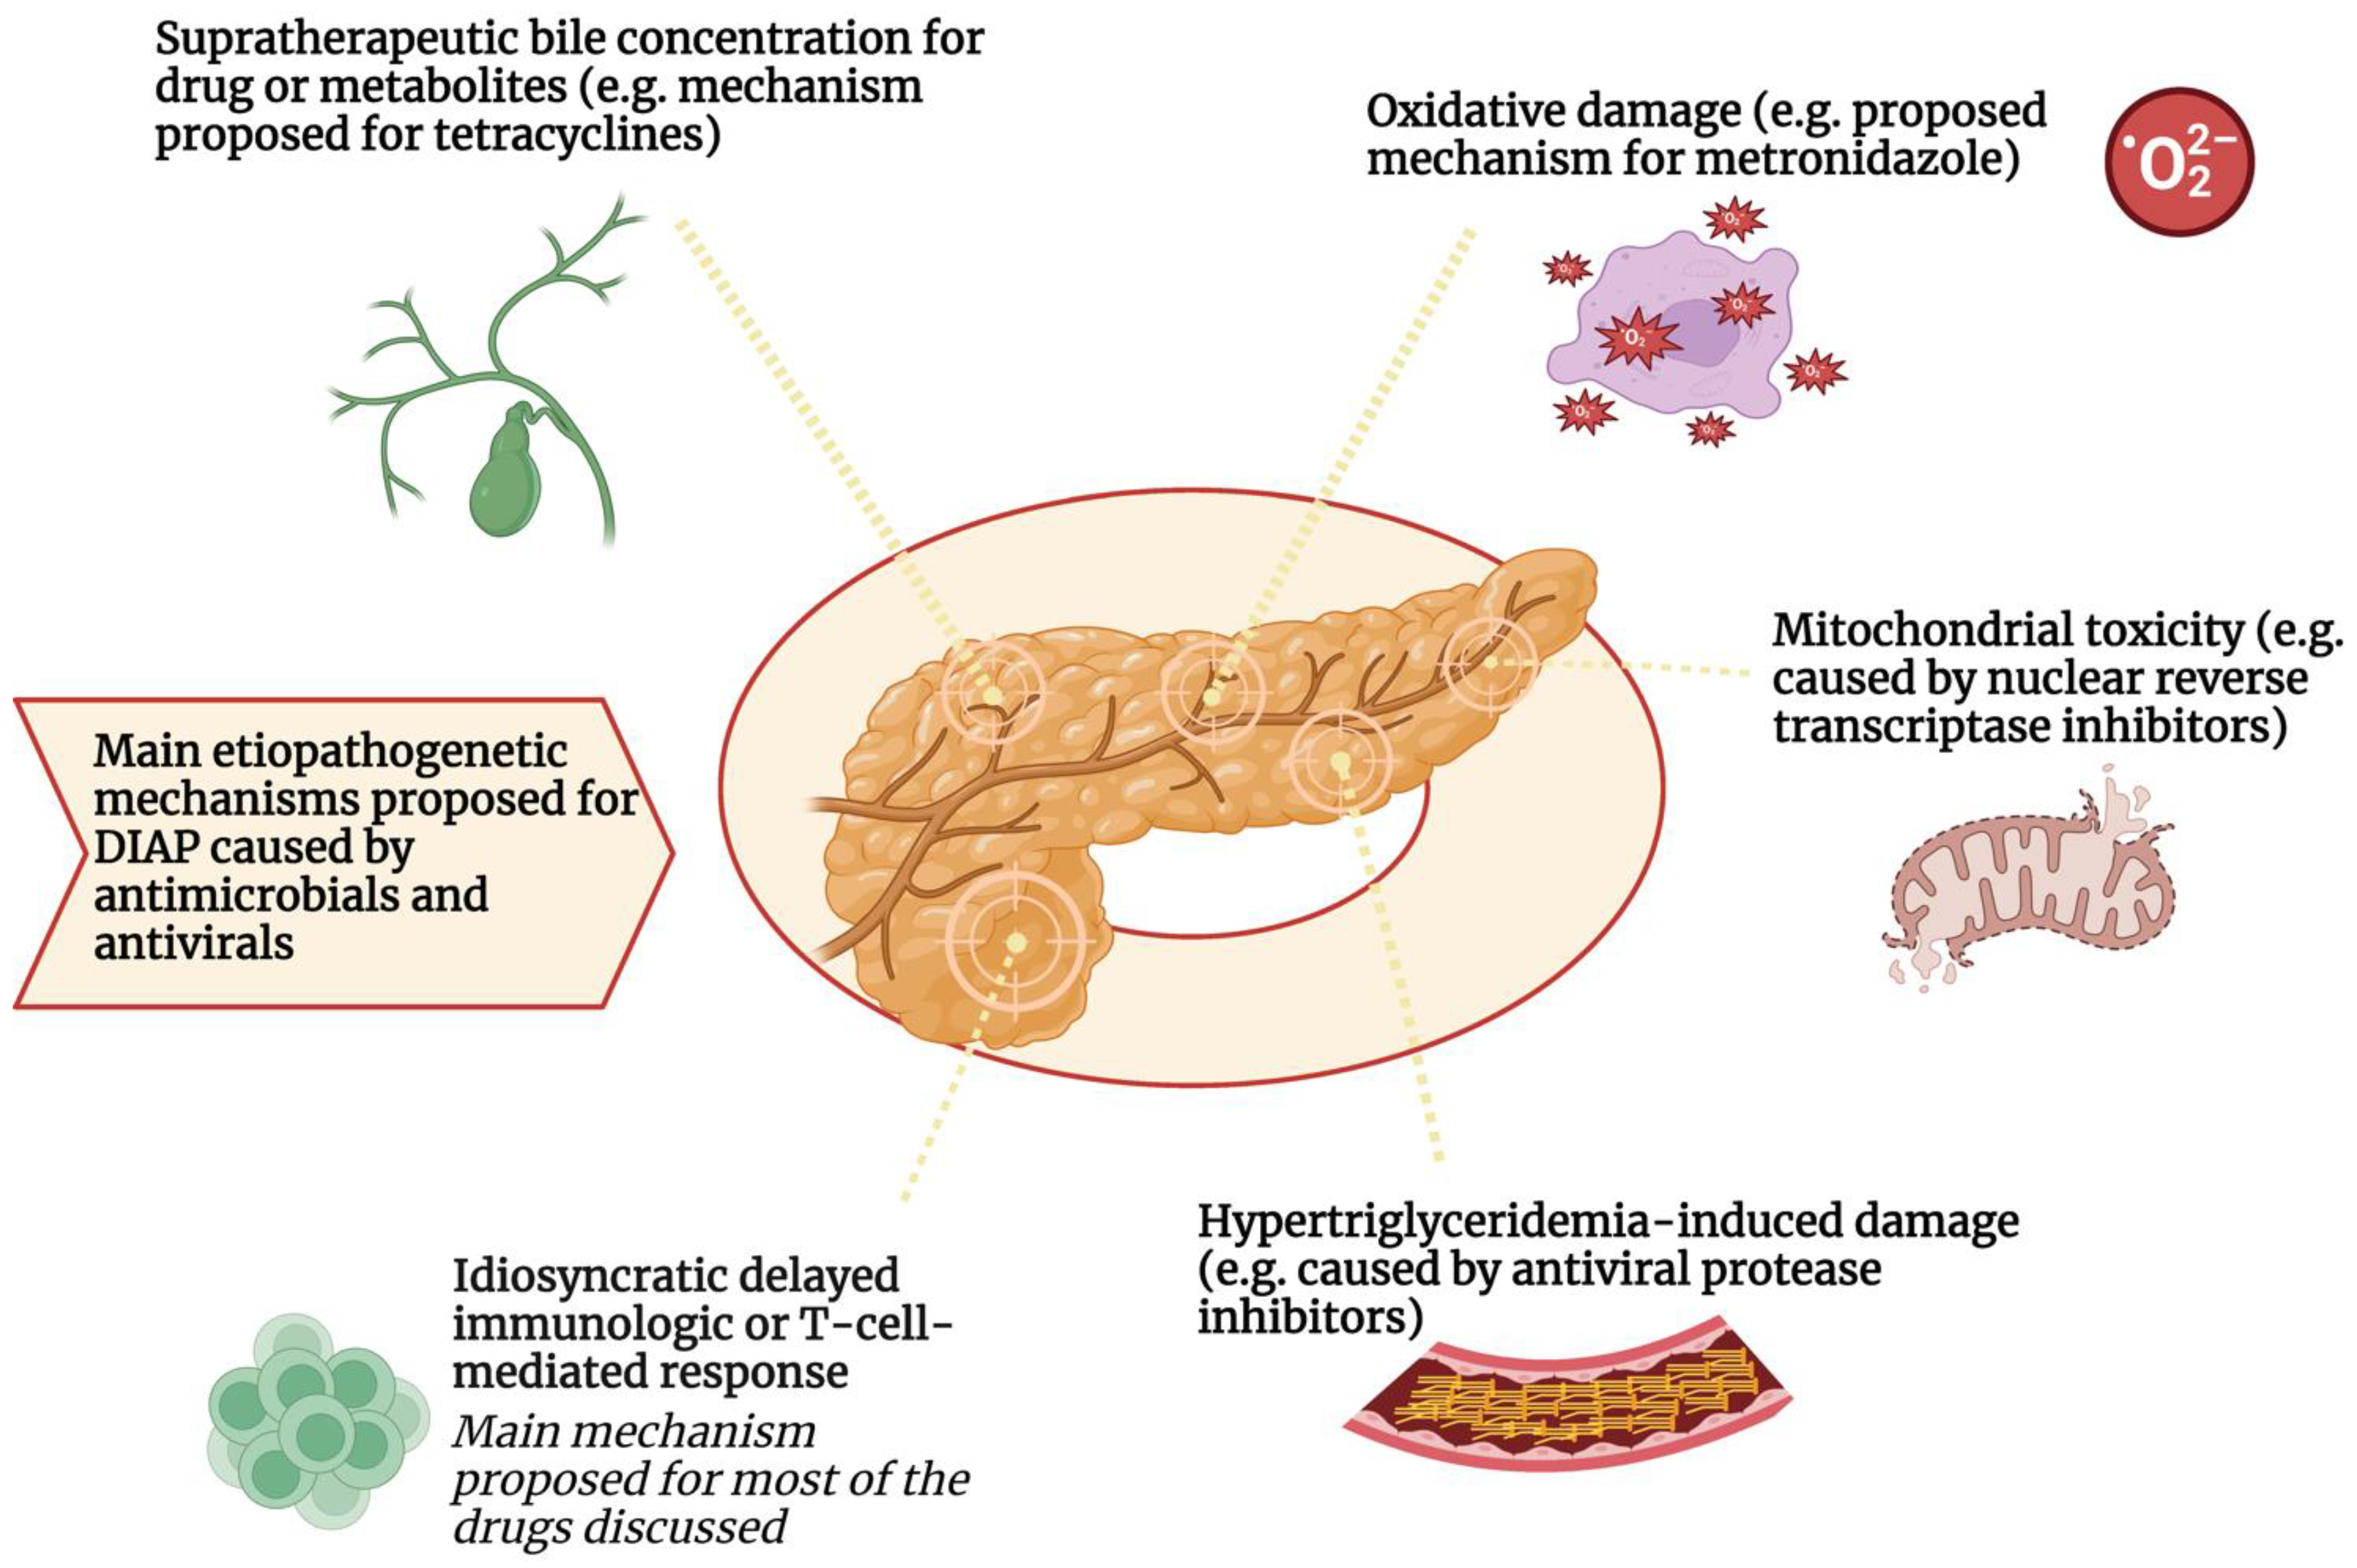

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).