


Abstract
Background: Chronic disease self-management (CDSM) interventions have shown promise in improving patient outcomes in heart failure (HF), particularly for those with reduced ejection fraction (HFrEF). Patient-centric self-management programs often incorporate key components such as education, self-monitoring, and goal setting. However, the extent to which these components are consistently reported and integrated into studies remains unclear. This umbrella narrative review aims to analyze systematic reviews to assess the consistency of reporting on patient-centric self-management components implemented in trials and studies. Methods: This umbrella narrative review synthesized findings from systematic reviews and meta-analyses published between 2000 and 2023 for CDSM tools in HF. Eligible studies were assessed for the presence and consistency of reporting on education, self-monitoring, and goal setting in self-management interventions for HFrEF. Data extraction focused on the frequency of reporting these components and the gaps in reporting long-term patient outcomes. Results: Among the included systematic reviews, education was the most consistently reported component (100%), while self-monitoring and goal setting were each reported in around 50% of studies. Reporting of long-term outcomes, such as mortality and quality of life, was highly variable and often absent. These inconsistencies highlight significant gaps in the evidence base for CDSM interventions. Conclusions: This review identifies gaps in the consistent reporting of key CDSM components in systematic reviews of HFrEF interventions. The inconsistent inclusion of all three components together and limited reporting of long-term outcomes may hinder the development of a robust evidence base for the adoption of these tools in HF guidelines. Future studies should prioritize comprehensive reporting to strengthen the foundation for patient-centric self-management strategies in HF care. PROSPERO registration number CRD42023431539.
1. Introduction
Heart failure with reduced ejection fraction (HFrEF) is a chronic, progressive condition that requires effective long-term management to improve patient outcomes and reduce hospitalizations. Comprehensive care for HFrEF involves both pharmacological treatments and patient-centered self-management strategies. These strategies aim to empower patients, encouraging active participation in their own care through patient education, self-monitoring, and goal setting. Such interventions are thought to improve self-management behaviors and help patients better manage symptoms, medications, and lifestyle changes [1].
While evidence supports the potential of self-management interventions for heart failure (HF) management, there is significant heterogeneity in the way these interventions are designed and implemented. Multicomponent interventions, which combine education, self-monitoring, and goal setting, are considered optimal for managing chronic diseases, as they address various aspects of self-management, improve patient engagement, and lead to better outcomes, including adherence, self-management behaviors, and quality of life [2,3,4,5,6]. However, despite the growing recognition of their importance, the extent to which all relevant components are integrated into self-management interventions for HFrEF remains unclear in the existing literature. Furthermore, psychosocial support and personalized care, both of which have been shown to be important for enhancing patient engagement and adherence, are often not included, or inadequately integrated into HF self-management interventions.
This umbrella narrative review aims to identify and reflect on the combinations of components of patient-centric self-management interventions that have previously been implemented for HFrEF. We focus on their inclusion in combination with stated outcome measures. Specifically, the absence or incomplete inclusion of critical components such as patient education, self-monitoring, goal setting, and psychosocial patient and carer support may have contributed to the historical lack of comprehensive evidence for the adoption of chronic disease self-management tools in clinical guidelines. Our goal is to identify these gaps in the existing literature, where interventions may have fallen short, and to explain how addressing these gaps could enhance the future development of clinical guidelines for managing HFrEF.
2. Methods
2.1. Study Design
This paper is designed with an umbrella narrative format and synthesizes findings from systematic reviews and meta-analyses to explore the inclusion of key components in patient-centric self-management interventions for patients with HFrEF. The methodology and systematic review on efficacy have previously been published [7,8]. The current review does not aim to assess the effectiveness of interventions, but rather, it advances the topic in a narrative fashion and aims to expose gaps in the integration of essential components such as patient education, self-monitoring, goal setting, and psychosocial support, which are critical to comprehensive chronic disease management. By analyzing the components included in these interventions, we seek to understand how the absence or incomplete inclusion of these elements may have impacted the current evidence base and the historical adoption of self-management tools in clinical guidelines and generate hypotheses [9,10,11,12,13,14,15,16].
2.2. Eligibility Criteria
We included systematic reviews and meta-analyses published between 2000 and 2023 that assessed the effects of self-management interventions for HFrEF patients. The interventions must have included at least two of the following components: patient education, self-monitoring, goal setting, and psychosocial support. Studies that focused on interventions without these core elements, or those not specifically targeting HFrEF, were excluded. Reviews that did not provide sufficient details on the components of the interventions or the reporting of outcomes were also excluded [7].
2.3. Data Sources and Search Strategy
We conducted a comprehensive search across multiple databases, including PubMed, Cochrane Database of Systematic Reviews, Web of Science, Embase, and CINAHL, using the following keywords: “heart failure with reduced ejection fraction”, “self-management interventions”, “patient education”, “self-monitoring”, “goal setting”, and “psychosocial support”. The search was limited to English-language articles published from 2000 to 2023 [7].
2.4. Data Extraction
Two independent reviewers screened the systematic reviews and meta-analyses for eligibility (TP and PI) based on predefined inclusion and exclusion criteria. Relevant data were extracted, including (i) study characteristics: author, year of publication, sample size, study design, and participant demographics; (ii) intervention components: details of the self-management interventions included in the studies, focusing on whether patient education, self-monitoring, goal setting, and psychosocial support were part of the intervention; (iii) outcome measures: the outcomes measured in each study, particularly focusing on self-management behaviors, hospital readmissions, quality of life, and psychosocial outcomes; (iv) study quality: the quality of the systematic reviews and meta-analyses was assessed using the AMSTAR-2 tool [7,17], which evaluates methodological rigor in systematic reviews.
2.5. Synthesis of Results
Data were synthesized qualitatively to assess the presence or absence of the key components in the included self-management interventions. We focused on identifying the most commonly included components and exploring how their absence or incomplete inclusion might have influenced the reported outcomes. Given the heterogeneity in study designs and outcomes, a narrative synthesis was performed rather than a statistical meta-analysis. Studies were divided into pre 2014 (Historical gaps) and post 2014 (Umbrella Narrative review “UmbNR”) based on a decade of new articles, the demotion of CDSM grading as an HF performance measure [4], and the subsequent shaping of the 2022 HF guidelines [1].
2.6. Definitions of Key Terms
To ensure clarity, the following key terms related to patient-centric self-management interventions are defined in Table 1 (Appendix A, Table A1 glossary).
Table 1.
Definition of key terms.
3. Results
3.1. Study Characteristics
A total of 60 systematic reviews and meta-analyses were included, covering a total of 276,381 participants. Interventions ranged from single component to multicomponent self-management strategies. The studies assessed a range of self-management interventions focused on patient education, self-monitoring, and goal setting, with varying intervention formats, including telehealth, patient education programs, self-monitoring tools, and carer education and support. The included systematic reviews and meta-analyses were diverse in their design, populations, and intervention types. Appendix A, Table A1 provides an overview of the key characteristics (from Historical Gaps and UmrNR) of these studies, including sample sizes, study durations, and reported outcomes. The predominant management difference in historical gap and UmbNR studies involved the use of newly approved therapeutics and novel technologies. The main study related aims for the UmbNR are highlighted below.
3.2. Umbrella Narrative Review
- i.
- Intervention Components
The most used intervention component was patient education, which appeared in 100% of the included reviews. Self-monitoring and goal setting were also frequently used, appearing in 50% of the studies. Interventions describing education, support, and the patients’ carers were around 15% (Table 2).
Table 2.
Reported outcomes and frequency of the core components of self-management interventions from UmbNR compared to historical gaps.
- ii.
- Outcome Measures
The studies assessed a variety of outcomes, with the most measured outcomes being quality of life and self-management behaviors, followed by readmissions, hospitalizations, and finally, in only 47.5%, mortality. The frequency of these outcomes is described in Table 2 and Table 3.
Table 3.
Frequency of core components in chronic disease self-management models as reported from UmbNR and historical gaps studies.
- iii.
- Frequency of Intervention Components
An assessment of intervention components revealed variability in the inclusion of critical self-management elements. As shown in Table 2 and Table 3, patient education was the most frequently included component (100%), while self-management, including components of self-monitoring, goal setting, psychosocial support, and carer involvement were included in only 50% and 15% of studies, respectively. This variability highlights gaps in the integration of essential patient-centric elements. To provide additional context Table 3 and Table A1 (from Historical Gaps) expands on the intervention types, categorizing them into single- and multicomponent approaches. It shows that multicomponent interventions, while more comprehensive, were inconsistently implemented across UmbNR studies.
- iv.
- Outcome Reporting
The outcome measures reported across the studies varied significantly. Table 2 presents a breakdown of the outcomes, such as self-management behaviors, hospital readmissions, and quality of life. However, long-term outcomes such as mortality were reported in less than 47% of studies, as noted in Table 1 (from Historical Gaps), which provides additional insights into the endpoints and their frequency of reporting, where mortality was reported at 65%.
3.3. Study Quality and Gaps
Study quality, evaluated using the AMSTAR-2 tool, is summarized in Table 4. Approximately 66% of studies were rated as moderate-to-high quality. However, gaps in reporting intervention components, especially psychosocial and carer support, and the lack of standardized outcome measures were common across studies. These gaps may partially explain the historical challenges in integrating CDSM tools into clinical guidelines.
Table 4.
AMSTAR grading of articles and certainty of evidence (study quality and identified gaps).
4. Discussion
This umbrella narrative review consolidates findings from several systematic reviews and meta-analyses examining the effectiveness of patient-centric self-management interventions for patients with HFrEF [8]. The findings underscore the missed approaches to multicomponent interventions that incorporate patient education, self-monitoring, and goal setting in improving self-management behaviors and reducing hospital readmissions. These interventions, if paired with optimized measures, telehealth and psychosocial support, may enhance patient engagement and support sustainable self-management [1,3,4,6,78,79,80,81,82].
If the inclusion of these essential components is critical for HF outcomes, then our analysis reveals substantial gaps in the existing evidence base [3,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,57,58,59,60,61,62,63,64,65,66,67,68,69,70,71,72,73,74,75,76,77,80,83]. A key gap is the incomplete integration of all relevant patient-centric components. Despite the prevalence of patient education in the included studies, psychosocial support, a crucial factor in fostering patient adherence and engagement, was notably absent in many interventions. The heterogeneity of the included studies, with varying intervention designs and outcome measures, further suggests that it may be incorrect that chronic disease management tools have limited capacity if all their subcomponents are not adhered to; hence well designed trials are needed to evaluate the totality of their effectiveness.
The multicomponent interventions that we think would be most effective, including education, self-monitoring, and goal setting, have been shown historically to be most frequently associated with improvements in self-care behaviors, such as medication adherence and symptom monitoring. Indeed, previous studies suggest that interventions targeting multiple aspects of self-management tend to be more effective than single-component programs [5,7]. However, the absence of consistent reporting on long-term outcomes, such as mortality and sustained improvements in quality of life, hinders the ability to assess evidence for clinical uptake into practice.
4.1. Psychosocial Factors and Patient-Centered Care
One of the critical gaps identified in this review is the lack of integration of psychosocial factors in the intervention design. As noted by Lee and Villero (Table 3), mental health issues, including anxiety and depression, significantly influence a patient’s ability to engage in self-management behaviors. Addressing these factors through psychosocial support could improve patient adherence and quality of life, especially in populations at higher risk of poor health outcomes. Incorporating personalized care tailored to the psychosocial and emotional needs of patients with chronic diseases, including HF, is essential for optimizing self-management strategies. There remains an underappreciation for the burden of HF and chronic diseases on psychological health. The INTERHEART study across 52 countries and in excess of 27,000 participants attribute risk of at least 25% of mental health in preventing primary myocardial infarction in older and even higher (>43%) in younger patients [84]. The impact of chronic diseases on mental health is underappreciated. For instance, the INTERHEART study (a study of risk factors for first myocardial infarction in 52 countries and over 27,000 subjects) reported an attributable risk of psychosocial risk factors in the primary prevention of myocardial infarction of 25.2% in older patients (men > 55 years of age, women >65 years of age) and of 43.5% in younger patients. When established intervention can influence this outcome, it is no surprise some advocate for paradigm changes in our approach [85]. Finally, the influences and determinants of psychosocial health are broadly focusing on the self-management capabilities generically will cover this need. Adding the concept of dyads broadens the patients who can receive this type of care and negates the influence of some modifiable determinants [86,87].
4.2. Quality and Discernible Evidence
The study further shows that consensus is difficult as the large body of published evidence has tremendous heterogeneity. The authors identify four areas of relevance to shape future models. Firstly, chronic disease strategies have sentinel links to Wagner’s models [1,2]. The study noted that historical high-quality trials [31,32,33,79,80,81,82,83,84] have well described DMPs, e.g., multidisciplinary, case management, or clinical models (Table 4). Program leads were most often nurses, doctors, and various allied health personnel, looking after inpatients, transitioned patients, or predominately ambulatory outpatients. The evidence of improvements is a mixture of qualitative and quantitative. Secondly, there is difficulty in sieving through evidence and weighing contributions of new technologies or models from newer studies. The high cost of new treatments entails a weighting must be used to judge value. Thirdly, newer studies appear to explore more sophisticated delivery methods and technologies. The studies were complex in their mechanisms and tended to receive low grades. Finally, we raise the point of the value of cost-effectiveness in health services research.
5. Limitations
A limitation of this umbrella narrative review is the reliance on published systematic reviews and meta-analyses, which may introduce publication bias. This design excludes unpublished studies or data, potentially overlooking relevant findings that could affect the overall synthesis of evidence. Despite these limitations, the review’s aim was to identify patterns in the existing evidence and highlight areas where future research could address these gaps. Technological advances in health applications, e.g., mobile or AI-based tools, can contribute to self-management improvements. These factors are difficult to quantify and factor in when comparing the historical and current studies. In addition, there are pleiotropic effects of HF drug therapies which can also influence this comparison, and could be factored [88].
6. Conclusions
This umbrella narrative review underscores the importance of patient-centric self-management interventions for improving outcomes in HFrEF patients, but it also highlights significant gaps that limit the applicability and endorsement of these interventions in clinical guidelines. Key gaps include inconsistent adding of inclusive self-monitoring and goal setting as well as inconsistent endpoint reporting and the absence of long-term data on outcomes like mortality and health-related quality of life. This variability likely influences inconsistent outcome measures across studies. Our review emphasizes that individual multicomponent patient education, self-monitoring, goal setting, and psychosocial support are the most effective approach for improving self-care behaviors when all are included. However, without all individual multicomponents, further research that accounts for semi-component interventions will remain limited in their ability to deliver consistent and meaningful improvements in HFrEF management. To bridge these gaps, future research must prioritize standardized patient centric self-care methodological approaches and practices that match consistent outcome measures, with long-term follow-up. This would help ensure that the benefits of self-management interventions can be more effectively realized, tailored to the diverse needs of patients, and ultimately endorsed by clinical guidelines (Figure 1).
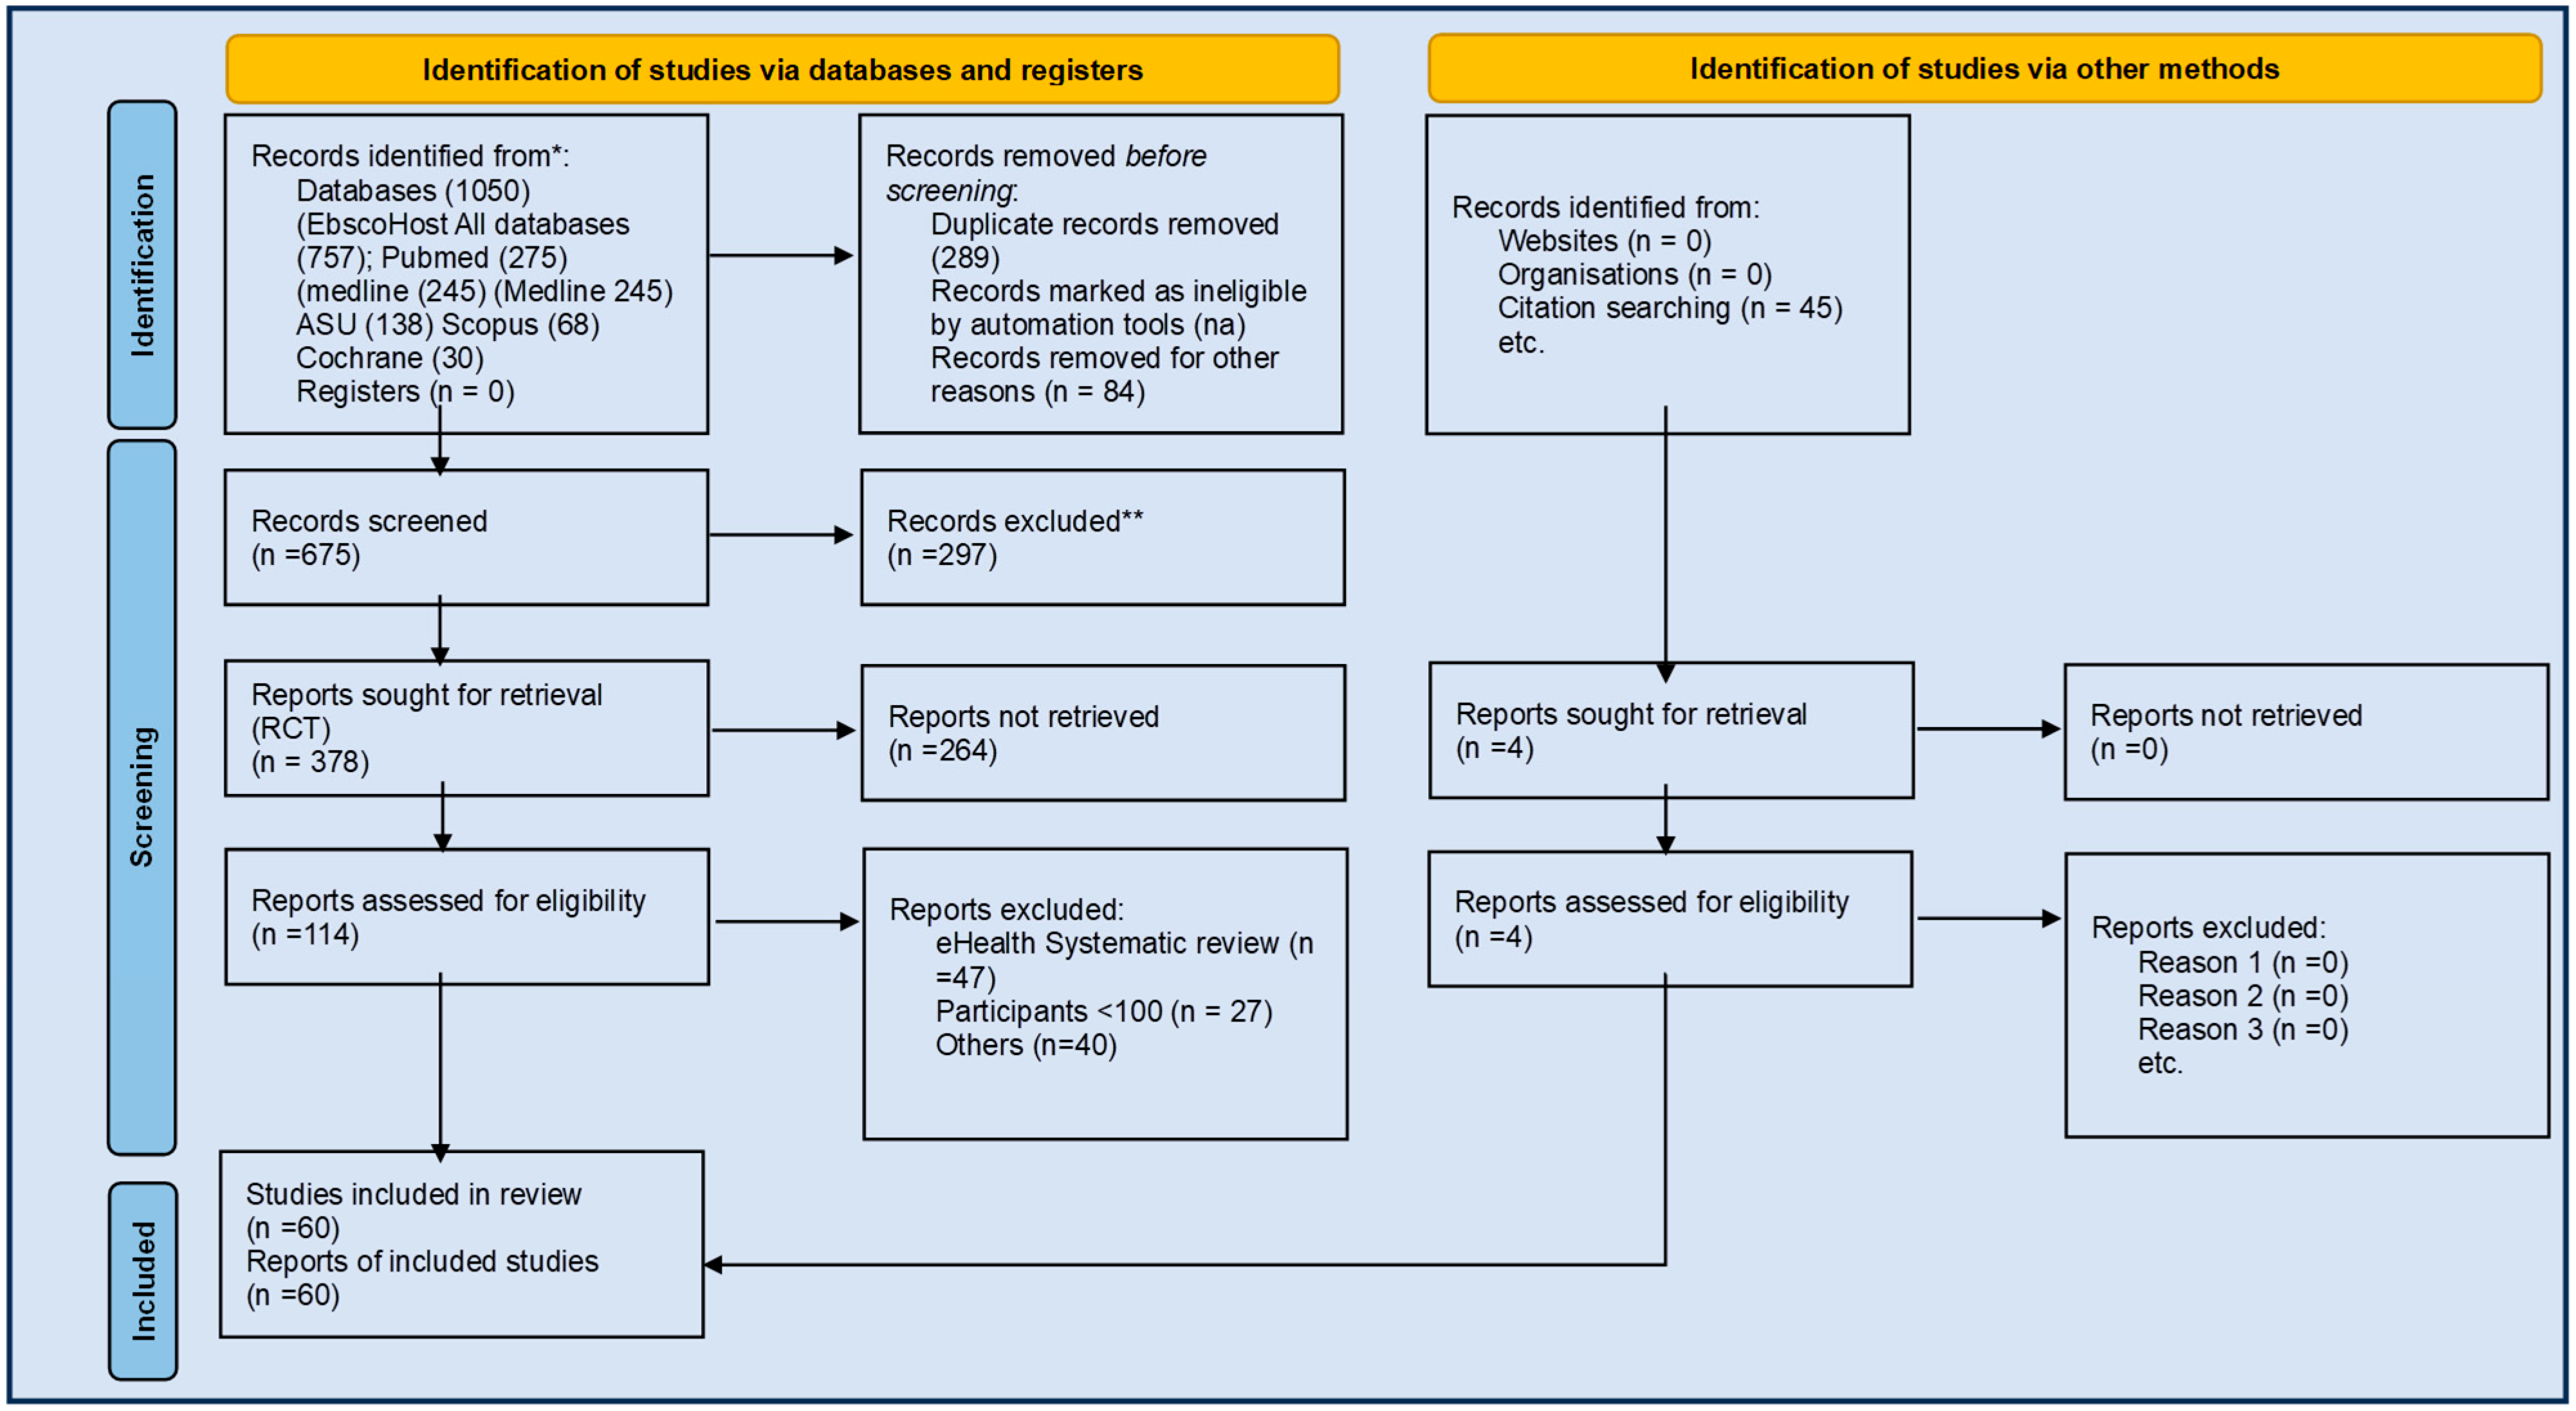
Figure 1.
PRISMA 2020 flow diagram for new systematic reviews, which included searches of databases, registers, and other sources. Modified from: Page, M.J., et al., 2021 [9]. For more information, visit: http://www.prisma-statement.org/ (accessed on 1 June 2024).
Author Contributions
P.I. and F.H. participated in research design, data analysis, and writing of the paper. P.I., F.H., T.P., H.N. and F.F. participated in the performance of the research and data collection. P.I. and F.H. provided advice and support. P.I. assisted. F.H. in statistical analysis. All authors have read and agreed to the published version of the manuscript.
Funding
P.I. was the recipient of 2023 RACP Fellows Research Entry Scholarship (2023RES00137).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
We abide by the data sharing policy.
Acknowledgments
We acknowledge support from Craig McLachlan, and Torrens University Australia library staff.
Conflicts of Interest
Professor Malcolm Battersby is the co-inventor of the “Flinders Model of Chronic Condition Self-Management” and has received competitive and Federal Government funding for research in chronic condition self-management. All other authors have received governmental and non-governmental funding. None pose a conflict of interest for this publication.
Appendix A
Table A1.
Summary (characteristics) of intervention types and component integration of studies included in the umbrella narrative review and from historical gap studies.
Table Glossary and Abbreviation:
Databases Abbreviations: Am = AMED; BNI = British Nursing Index; CE = (CENTRAL) Cochrane Central Register of Controlled Trials; CI = (CINAHL) Cumulative Index to Nursing and Allied Health Literature; CK = CNKI; CL = Cochrane Library; CP = Chinese Electronic Periodical Services; D = DARE; DMP = disease management programs; Dy = DynaMed; Eb = EBSCO; Em = (Embase) Excerpta Medica Database; ERIC = Education Resources Information Center; GS—Google Scholar; HF—heart failure; HS—Health Source/Nursing/Academic Edition; ICTRP—Registry of International Clinical Trials; IPA—International Pharmaceutical Abstracts; LI—LILACS; Ma—Magiran; Med = Medline; National Research Register (July 2003); NAHL—Nursing and allied Health Literature; NHS Economic Evaluations Database; OP—hospital outpatients; Ov = Ovid; Pb = PubMed; pEM—printed educational material; PQ—ProQuest; PsI = PsycInfo; S = Science Direct; SC = Scopus; SCI = Science Citation Index; Si = SIGLE; SID = Scientific Information Database; Up-To-Date; WHO—World Health Organization; VIP = Wan Fang, Wei Pu; WoS = Web of Science.
Table abbreviations: EF—ejection fraction; Exp Gp—experimental group (IR—intervention received; IC—intervention content); MACE—major adverse cardiovascular events; MDT—multidisciplinary team; n—number of studies; QOL—quality of life; RCT—randomized controlled trial; SM—self-management.
Health resourcing Abbreviations: Health services (QALY), cost, effectiveness, utilization of individual health journey domains; health economics; DMP: counselling, and monitoring to enhance self-control mechanisms, timely medical visits, diet, and drug therapy compliance. Early discharge planning and coordination of care, individualized and comprehensive patient and family HF education, telephone follow-up and surveillance, promotion of optimal HF medications and medication doses based on consensus guidelines; SM:—self-care components, education, skills knowledge, behaviors, monitoring, theories; SCHFI on Goal setting and motivational interviewing, educational and self-care needs, barriers and facilitators; MACE—one component of readmission, mortality, either general or heart failure related; Physical function—6 MWT; Intervention: Facilitated, Education, Self-management, Weight-monitoring, Sodium diet advice/restriction, Exercise recommendation, Medication review, Social and psychological support education, discharge plan, counselling.
Intervention Category Description:
- Case Management—Based on implementation of a collaborative process between one or more care coordinators or case managers and the patient, to assess, plan, and facilitate service delivery for patients with chronic diseases, particularly when transitions across healthcare settings are required.
- ○
- The Collaborative Health Management—is a model that builds on teamwork between the nurse practitioners and physicians, as an egalitarian partnership. Its long-term purpose is to operationalize Advanced Practice Registered Nurses to deliver high-quality chronic disease management.
- ○
- Transitional Care—The support provided to patients as they from one phase of disease or its management, such as from hospital-based care to home based care. This can involve both patients and families and with a range of medical emotional and other needs as they adjust and attain their care goals.
- ○
- Multicomponent Integrated Care—Coordination between different healthcare providers, providing patient education and self-management support, and facilitating smooth transitions between hospital and home care settings.
- ○
- Care Pathways—e.g., Telemonitoring, Structured telephone support, MDT clinic, cardiac care clinics (center based: individual or disease management programs; rehabilitation; community-based follow-up).
- Chronic Care Model—Model that identifies six modifiable elements of healthcare systems: (1) organizational support, addressing organizational culture and leadership, (2) clinical information systems to organize patient, population and provider data, (3) delivery system design to address composition and function of the care team and follow-up management, (4) decision support to increase provider access to evidence-based guidelines and specialists for collaboration, (5) self-management support to provide tailored education, skills training, psychosocial support and goal-setting, and (6) community resources to provide peer support, care coordination, and community-based interventions.
- Discharge Management—Interventions designed to facilitate effective transitions from hospital care to other settings. Typically includes a predischarge phase of support, transitional care for the move between the hospital and community/home setting, and post discharge follow-up and monitoring, often incorporating rehabilitation or reablement support.
- Complex Interventions—Two reviews assessed a range of interventions rather than focusing on a single intervention or service model.
- Multidisciplinary Team—Interventions comprising teams composed of multiple health and/or social care professionals working together to provide care for people with complex needs. Teams typically included condition-specific expertise, nurses, occupational therapists, physiotherapists, social workers, GPs, and occasionally pharmacists or case managers.
- Disease Management—Six components: 1. Population identification process, 2. Evidence-based practice guideline, 3. Collaborative practice models, 4. Patient self-management education, 5. Process and outcome management, 6. Reporting and feedback loop.
References
- Heidenreich, P.A.; Bozkurt, B.; Aguilar, D.; Allen, L.A.; Byun, J.J.; Colvin, M.M.; Deswal, A.; Drazner, M.H.; Dunlay, S.M.; Evers, L.R.; et al. 2022 AHA/ACC/HFSA Guideline for the Management of Heart Failure: Executive Summary. J. Am. Coll. Cardiol. 2022, 79, 1757–1780. [Google Scholar] [CrossRef] [PubMed]
- Allegrante, J.P.; Wells, M.T.; Peterson, J.C. Interventions to Support Behavioral Self-Management of Chronic Diseases. Annu. Rev. Public Health 2019, 40, 127–146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Clark, A.M.; Savard, L.A.; Thompson, D.R. What Is the Strength of Evidence for Heart Failure Disease-Management Programs? J. Am. Coll. Cardiol. 2009, 54, 397–401. [Google Scholar] [CrossRef] [Scilit]
- Heidenreich, P.A.; Fonarow, G.C.; Breathett, K.; Jurgens, C.Y.; Pisani, B.A.; Pozehl, B.J.; Spertus, J.A.; Taylor, K.G.; Thibodeau, J.T.; Yancy, C.W.; et al. 2020 ACC/AHA Clinical Performance and Quality Measures for Adults with Heart Failure. J. Am. Coll. Cardiol. 2020, 76, 2527–2564. [Google Scholar] [CrossRef]
- Jaarsma, T.; Hill, L.; Bayes-Genis, A.; La Rocca, H.P.; Castiello, T.; Čelutkienė, J.; Marques-Sule, E.; Plymen, C.M.; Piper, S.E.; Riegel, B.; et al. Self-care of heart failure patients: Practical management recommendations from the Heart Failure Association of the European Society of Cardiology. Eur. J. Heart Fail. 2021, 23, 157–174. [Google Scholar] [CrossRef] [Scilit]
- Toukhsati, S.R.; Jaarsma, T.; Babu, A.S.; Driscoll, A.; Hare, D.L. Self-Care Interventions That Reduce Hospital Readmissions in Patients with Heart Failure; Towards the Identification of Change Agents. Clin. Med. Insights Cardiol. 2019, 13, 1179546819856855. [Google Scholar] [CrossRef] [Scilit]
- Iyngkaran, P.; Buhler, M.; de Courten, M.; Hanna, F. Effectiveness of self-management programmes for heart failure with reduced ejection fraction: A systematic review protocol. BMJ Open 2024, 14, e079830. [Google Scholar] [CrossRef] [Scilit]
- Iyngkaran, P.; Buhler, M.; McLachlan, C.; Gupta, B.; de Courten, M.; Hanna, F. Effectiveness of self-management programmes for heart failure with reduced ejection fraction. ESC-HF, in process.
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Hartling, L.; Ospina, M.; Liang, Y.; Dryden, D.M.; Hooton, N.; Krebs Seida, J.; Klassen, T.P. Risk of bias versus quality assessment of randomised controlled trials: Cross sectional study. BMJ 2009, 339, b4012. [Google Scholar] [CrossRef] [Scilit]
- Higgins, J.P.T.; Thomas, J.; Chandler, J.; Cumpston, M.; Li, T.; Page, M.J.; Welch, V.A. Cochrane Handbook for Systematic Reviews of Interventions Version 6.2 (Updated February 2021). Available online: http://www.training.cochrane.org/handbook (accessed on 1 June 2024).
- Cochrane Effective Practice and Organisation of Care Group. Available online: https://epoc.cochrane.org/ (accessed on 1 June 2024).
- Iyngkaran, P.; Smith, D.; McLachlan, C.; Battersby, M.; De Courten, M.; Hanna, F. Validation of Psychometric Properties of Partners in Health Scale for Heart Failure. J. Clin. Med. 2024, 13, 7374. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Freund, T.; Kayling, F.; Miksch, A.; Szecsenyi, J.; Wensing, M. Effectiveness and efficiency of primary care based case management for chronic diseases: Rationale and design of a systematic review and meta-analysis of randomized and non-randomized trials [CRD32009100316]. BMC Health Serv. Res. 2010, 10, 112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shepperd, S.; Lewin, S.; Straus, S.; Clarke, M.; Eccles, M.P.; Fitzpatrick, R.; Wong, G.; Sheikh, A. Can we systematically review studies that evaluate complex interventions? PLoS Med. 2009, 6, e1000086. [Google Scholar] [CrossRef] [Scilit]
- Belbasis, L.; Bellou, V.; Ioannidis, J.P.A. Conducting umbrella reviews. BMJ Med. 2022, 1, e000071. [Google Scholar] [CrossRef] [Scilit]
- Shea, B.J.; Reeves, B.C.; Wells, G.; Thuku, M.; Hamel, C.; Moran, J.; Moher, D.; Tugwell, P.; Welch, V.; Kristjansson, E.; et al. AMSTAR 2: A critical appraisal tool for systematic reviews that include randomised or non-randomised studies of healthcare interventions, or both. BMJ 2017, 358, j4008. [Google Scholar] [CrossRef] [Scilit]
- Zhao, X.; Wu, S.; Luo, N.; Lin, Q.; Zhao, X.; Li, K. Care models for patients with heart failure at home: A systematic review. J. Clin. Nurs. 2024, 33, 1295–1305. [Google Scholar] [CrossRef] [Scilit]
- Chen, C.W.; Lee, M.-C.; Wu, S.-F.V. Effects of a collaborative health management model on people with congestive heart failure: A systematic review and meta-analysis. J. Adv. Nurs. 2023, 80, 2290–2307. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Liu, Y. Effect of Transitional Care Strategies on Health-Related Quality of Life (HRQoL) in Heart Failure with Reduced Ejection Fraction (HFrEF): A Systematic Review and Meta-analysis of Randomized Controlled Trails. Altern. Ther. Health Med. 2023, 30, 148–153. [Google Scholar]
- Yang, Y.-F.; Hoo, J.-X.; Tan, J.-Y.; Lim, L.-L. Multicomponent integrated care for patients with chronic heart failure: Systematic review and meta-analysis. ESC Heart Fail. 2023, 10, 791–807. [Google Scholar] [CrossRef] [Scilit]
- Hafkamp, F.J.; Tio, R.A.; Otterspoor, L.C.; de Greef, T.; van Steenbergen, G.J.; van de Ven, A.R.; Smits, G.; Post, H.; van Veghel, D. Optimal effectiveness of heart failure management—An umbrella review of meta-analyses examining the effectiveness of interventions to reduce (re)hospitalizations in heart failure. Heart Fail. Rev. 2022, 27, 1683–1748. [Google Scholar] [CrossRef] [Scilit]
- Hsu, S.-F.; Lee, S.-Y.; Hsu, T.-F.; Li, J.-Y.; Tung, H.-H. Patient Navigators for Transition Care of Heart Failure: A Systematic Review and Meta-Analysis. Int. J. Gerontol. 2022, 16, 76–82. [Google Scholar]
- Toback, M.; Clark, N. Strategies to improve self-management in heart failure patients. Contemp. Nurse 2017, 53, 105–120. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taylor, S.; Bestall, J.; Cotter, S.; Falshaw, M.; Hood, S.G.; Parsons, S.; Wood, L.; Underwood, M. Clinical service organization for heart failure. Cochrane Database Syst. Rev. 2005, 2, CD002752. [Google Scholar]
- Roccaforte, R.; Demers, C.; Baldassarre, F.; Teo, K.K.; Yusuf, S. Effectiveness of comprehensive disease management programmes in improving clinical outcomes in heart failure patients. A meta-analysis. Eur. J. Heart Fail. 2005, 7, 1133–1144. [Google Scholar] [CrossRef] [Scilit]
- Gonseth, J.; Guallar-Castillón, P.; Banegas, J.R.; Rodríguez-Artalejo, F. The effectiveness of disease management programmes in reducing hospital re-admission in older patients with heart failure: A systematic review and meta-analysis of published reports. Eur. Heart J. 2004, 25, 1570–1595. [Google Scholar] [CrossRef] [Scilit]
- Huang, Z.; Liu, T.; Gao, R.; Chair, S.Y. Effects of nurse-led self-care interventions on health outcomes among people with heart failure: A systematic review and meta-analysis. J. Clin. Nurs. 2023, 33, 1282–1294. [Google Scholar] [CrossRef] [Scilit]
- Nwosu, W.O.; Rajani, R.; McDonaugh, T.; Goulder, A.; Smith, D.; Hughes, L. The impact of nurse-led patient education on quality of life in patients with heart failure. Br. J. Card. Nurs. 2023, 18, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Checa, C.; Canelo-Aybar, C.; Suclupe, S.; Ginesta-López, D.; Berenguera, A.; Castells, X.; Brotons, C.; Posso, M. Effectiveness and Cost-Effectiveness of Case Management in Advanced Heart Failure Patients Attended in Primary Care: A Systematic Review and Meta-Analysis. Int. J. Environ. Res. Public Health 2022, 19, 13823. [Google Scholar] [CrossRef] [Scilit]
- Huang, Z.; Liu, T.; Chair, S.Y. Effectiveness of nurse-led self-care interventions on self-care behaviors, self-efficacy, depression and illness perceptions in people with heart failure: A systematic review and meta-analysis. Int. J. Nurs. Stud. 2022, 132, 104255. [Google Scholar] [CrossRef] [Scilit]
- do Céu Sá, M.; Nabais, A. How to care for patients with heart failure—A systematic review of nursing interventions. New Trends Qual. Res. 2022, 11, e557. [Google Scholar]
- Imanuel Tonapa, S.; Inayati, A.; Sithichoksakulchai, S.; Daryanti Saragih, I.; Efendi, F.; Chou, F.H. Outcomes of nurse-led telecoaching intervention for patients with heart failure: A systematic review and meta-analysis of randomised controlled trials. J. Clin. Nurs. 2022, 31, 1125–1135. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Son, Y.J.; Choi, J.; Lee, H.J. Effectiveness of Nurse-Led Heart Failure Self-Care Education on Health Outcomes of Heart Failure Patients: A Systematic Review and Meta-Analysis. Int. J. Environ. Res. Public Health 2020, 17, 6559. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Walsh, J.C. A Nurse Led Clinic’s contribution to Patient Education and Promoting Self-care in Heart Failure Patients: A Systematic Review. Int. J. Integr. Care 2017, 17, 1–2. [Google Scholar] [CrossRef] [Scilit]
- Alnomasy, N.; Still, C.H. Nonpharmacological Interventions for Preventing Rehospitalization Among Patients with Heart Failure: A Systematic Review and Meta-Analysis. SAGE Open Nurs. 2023, 9, 23779608231209220. [Google Scholar] [CrossRef] [Scilit]
- Mhanna, M.; Sauer, M.C.; Al-Abdouh, A.; Jabri, A.; Abusnina, W.; Safi, M.; Beran, A.; Mansour, S. Cognitive behavioral therapy for depression in patients with heart failure: A systematic review and metanalysis of randomized control trials. Heart Fail. Rev. 2023, 28, 1091–1100. [Google Scholar] [CrossRef] [Scilit]
- Olano-Lizarraga, M.; Wallström, S.; Martín-Martín, J.; Wolf, A. Interventions on the social dimension of people with chronic heart failure: A systematic review of randomized controlled trials. Eur. J. Cardiovasc. Nurs. 2023, 22, 113–125. [Google Scholar] [CrossRef] [Scilit]
- Nso, N.; Emmanuel, K.; Nassar, M.; Kaveh, R.B.; Daniel, A.-A.; Mohsen, A.; Ravali, K.; Ritika, K.; Sofia, L.; Vincent, R.; et al. Efficacy of Cognitive Behavioral Therapy in Heart Failure Patients: A Systematic Review and Meta-Analysis. Cardiol. Rev. 2023, 31, 139–148. [Google Scholar] [CrossRef] [Scilit]
- Balata, M.; Gbreel, M.I.; Elrashedy, A.A.; Westenfeld, R.; Pfister, R.; Zimmer, S.; Nickenig, G.; Becher, M.U.; Sugiura, A. Clinical effects of cognitive behavioral therapy in heart failure patients: A meta-analysis of randomized controlled trials. BMC Complement Med. Ther. 2023, 23, 280. [Google Scholar] [CrossRef] [Scilit]
- Koikai, J.; Khan, Z. The Effectiveness of Self-Management Strategies in Patients with Heart Failure: A Narrative Review. Cureus 2023, 15, e41863. [Google Scholar] [CrossRef] [Scilit]
- Feng, C.; Wang, Y.; Li, S.; Qu, Z.; Zheng, S. Effect of self-management intervention on prognosis of patients with chronic heart failure: A meta-analysis. Nurs. Open 2023, 10, 2015–2029. [Google Scholar] [CrossRef] [Scilit]
- Nahlén Bose, C. A meta-review of systematic reviews and meta-analyses on outcomes of psychosocial interventions in heart failure. Front. Psychiatry 2023, 14, 1095665. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, C.S.; Westland, H.; Faulkner, K.M.; Iovino, P.; Thompson, J.H.; Sexton, J.; Farry, E.; Jaarsma, T.; Riegel, B. The effectiveness of self-care interventions in chronic illness: A meta-analysis of randomized controlled trials. Int. J. Nurs. Stud. 2022, 134, 104322. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Villero-Jiménez, A.I.; Martínez-Torregrosa, N.; Olano Lizarraga, M.; Garai-López, J.; Vázquez-Calatayud, M. Dyadic self-care interventions in chronic heart failure in hospital settings: A systematic review. An. Sist. Sanit. Navarra 2022, 45, e1001. [Google Scholar] [CrossRef] [Scilit]
- Ghizzardi, G.; Arrigoni, C.; Dellafiore, F.; Vellone, E.; Caruso, R. Efficacy of motivational interviewing on enhancing self-care behaviors among patients with chronic heart failure: A systematic review and meta-analysis of randomized controlled trials. Heart Fail. Rev. 2022, 27, 1029–1041. [Google Scholar] [CrossRef] [Scilit]
- Suksatan, W.; Tankumpuan, T. The Effectiveness of Transition Care Interventions from Hospital to Home on Rehospitalization in Older Patients with Heart Failure: An Integrative Review. Home Health Care Manag. Pract. 2022, 34, 63–71. [Google Scholar] [CrossRef] [Scilit]
- Meng, X.; Wang, Y.; Tang, X.; Gu, J.; Fu, Y. Self-management on heart failure: A meta-analysis. Diabetes Metab. Syndr. 2021, 15, 102176. [Google Scholar] [CrossRef] [Scilit]
- Tinoco, J.D.M.V.P.; Figueiredo, L.D.S.; Flores, P.V.P.; Padua, B.L.R.D.; Mesquita, E.T.; Cavalcanti, A.C.D. Effectiveness of health education in the self-care and adherence of patients with heart failure: A meta-analysis. Rev. Lat.-Am. Enferm. 2021, 29, e3389. [Google Scholar] [CrossRef] [Scilit]
- Aghajanloo, A.; Negarandeh, R.; Janani, L.; Tanha, K.; Hoseini-Esfidarjani, S.S. Self-care status in patients with heart failure: Systematic review and meta-analysis. Nurs. Open 2021, 8, 2235–2248. [Google Scholar] [CrossRef] [Scilit]
- Cañon-Montañez, W.; Duque-Cartagena, T.; Rodríguez-Acelas, A.L. Effect of Educational Interventions to Reduce Readmissions due to Heart Failure Decompensation in Adults: A Systematic Review and Meta-analysis. Investig. Educ. Enferm. 2021, 39, e05. [Google Scholar] [CrossRef] [Scilit]
- Anderson, D.A.; Clemett, V. What impact do specialist and advanced-level nurses have on people living with heart failure compared to physician-led care? A literature review. J. Res. Nurs. 2021, 26, 229–249. [Google Scholar] [CrossRef] [Scilit]
- Zhao, Q.; Chen, C.; Zhang, J.; Ye, Y.; Fan, X. Effects of self-management interventions on heart failure: Systematic review and meta-analysis of randomized controlled trials. Int. J. Nurs. Stud. 2021, 116, 103909. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Poudel, N.; Kavookjian, J.; Scalese, M.J. Motivational Interviewing as a Strategy to Impact Outcomes in Heart Failure Patients: A Systematic Review. Patient 2020, 13, 43–55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Świątoniowska-Lonc, N.A.; Sławuta, A.; Dudek, K.; Jankowska, K.; Jankowska-Polańska, B.K. The impact of health education on treatment outcomes in heart failure patients. Adv. Clin. Exp. Med. 2020, 29, 481–492. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peng, Y.; Fang, J.; Huang, W.; Qin, S. Efficacy of Cognitive Behavioral Therapy for Heart Failure. Int. Heart J. 2019, 60, 665–670. [Google Scholar] [CrossRef] [Scilit]
- Parajuli, D.R.; Kourbelis, C.; Franzon, J.; Newman, P.; Mckinnon, R.A.; Shakib, S.; Whitehead, D.; Clark, R.A. Effectiveness of the Pharmacist-Involved Multidisciplinary Management of Heart Failure to Improve Hospitalizations and Mortality Rates in 4630 Patients: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. J. Card. Fail. 2019, 25, 744–756. [Google Scholar] [CrossRef] [Scilit]
- Shanbhag, D.; Graham, I.D.; Harlos, K.; Haynes, R.B.; Gabizon, I.; Connolly, S.J.; Van Spall, H.G.C. Effectiveness of implementation interventions in improving physician adherence to guideline recommendations in heart failure: A systematic review. BMJ Open 2018, 8, e017765. [Google Scholar] [CrossRef] [Scilit]
- Sterling, M.R.; Shaw, A.L.; Leung, P.B.; Safford, M.M.; Jones, C.D.; Tsui, E.K.; Delgado, D. Home care workers in heart failure: A systematic review. J. Multidiscip. Healthc. 2018, 11, 481–492. [Google Scholar] [CrossRef] [Scilit]
- Jiang, Y.; Shorey, S.; Seah, B.; Chan, W.X.; Tam, W.W.S.; Wang, W. The effectiveness of psychological interventions on self-care, psychological and health outcomes in patients with chronic heart failure-A systematic review and meta-analysis. Int. J. Nurs. Stud. 2018, 78, 16–25. [Google Scholar] [CrossRef] [Scilit]
- Jonkman, N.H.; Westland, H.; Groenwold, R.H.; Ågren, S.; Anguita, M.; Blue, L.; de la Porte, P.W.F.B.-A.; DeWalt, D.A.; Hebert, P.L.; Heisler, M.; et al. What Are Effective Program Characteristics of Self-Management Interventions in Patients with Heart Failure? An Individual Patient Data Meta-analysis. J. Card. Fail. 2016, 22, 861–871. [Google Scholar] [CrossRef] [Scilit]
- Ruppar, T.M.; Cooper, P.S.; Mehr, D.R.; Delgado, J.M.; Dunbar-Jacob, J.M. Medication Adherence Interventions Improve Heart Failure Mortality and Readmission Rates: Systematic Review and Meta-Analysis of Controlled Trials. J. Am. Heart Assoc. 2016, 5, e002606. [Google Scholar] [CrossRef] [Scilit]
- Jonkman, N.H.; Westland, H.; Groenwold, R.H.; Ågren, S.; Atienza, F.; Blue, L.; de la Porte, P.W.B.-A.; DeWalt, D.A.; Hebert, P.L.; Heisler, M.; et al. Do Self-Management Interventions Work in Patients with Heart Failure? An Individual Patient Data Meta-Analysis. Circulation 2016, 133, 1189–1198. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Srisuk, N.; Cameron, J.; Ski, C.F.; Thompson, D.R. Heart failure family-based education: A systematic review. Patient Educ. Couns. 2016, 99, 326–338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ha Dinh, T.T.; Bonner, A.; Clark, R.; Ramsbotham, J.; Hines, S. The effectiveness of the teach-back method on adherence and self-management in health education for people with chronic disease: A systematic review. JBI Database Syst. Rev. Implement. Rep. 2016, 14, 210–247. [Google Scholar] [CrossRef] [Scilit]
- Inglis, S.C.; Clark, R.A.; Dierckx, R.; Prieto-Merino, D.; Cleland, J.G.F. Structured telephone support or non-invasive telemonitoring for patients with heart failure. Cochrane Database Syst. Rev. 2015, 2015, CD007228. [Google Scholar] [CrossRef] [Scilit]
- Ruppar, T.M.; Delgado, J.M.; Temple, J. Medication adherence interventions for heart failure patients: A meta-analysis. Eur. J. Cardiovasc. Nurs. 2015, 14, 395–404. [Google Scholar] [CrossRef] [Scilit]
- Casimir, Y.E.; Williams, M.M.; Liang, M.Y.; Pitakmongkolkul, S.; Slyer, J.T. The effectiveness of patient-centered self-care education for adults with heart failure on knowledge, self-care behaviors, quality of life, and readmissions: A systematic review. JBI Database Syst. Rev. Implement. Rep. 2014, 12, 188–262. [Google Scholar] [CrossRef] [Scilit]
- Wakefield, B.J.; Boren, S.A.; Groves, P.S.; Conn, V.S. Heart failure care management programs: A review of study interventions and meta-analysis of outcomes. J. Cardiovasc. Nurs. 2013, 28, 8–19. [Google Scholar] [CrossRef] [Scilit]
- Barnason, S.; Zimmerman, L.; Young, L. An integrative review of interventions promoting self-care of patients with heart failure. J. Clin. Nurs. 2012, 21, 448–475. [Google Scholar] [CrossRef] [Scilit]
- Boyde, M.; Turner, C.; Thompson, D.R.; Stewart, S. Educational interventions for patients with heart failure: A systematic review of randomized controlled trials. J. Cardiovasc. Nurs. 2011, 26, E27–E35. [Google Scholar] [CrossRef] [Scilit]
- Dickson, V.V.; Buck, H.; Riegel, B. A qualitative meta-analysis of heart failure self-care practices among individuals with multiple comorbid conditions. J. Card. Fail. 2011, 17, 413–419. [Google Scholar] [CrossRef] [Scilit]
- Yehle, K.S.; Plake, K.S. Self-efficacy and educational interventions in heart failure: A review of the literature. J. Cardiovasc. Nurs. 2010, 25, 175–188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ditewig, J.B.; Blok, H.; Havers, J.; van Veenendaal, H. Effectiveness of self-management interventions on mortality, hospital readmissions, chronic heart failure hospitalization rate and quality of life in patients with chronic heart failure: A systematic review. Patient Educ. Couns. 2010, 78, 297–315. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boren, S.A.; Wakefield, B.J.; Gunlock, T.L.; Wakefield, D.S. Heart failure self-management education: A systematic review of the evidence. Int. J. Evid.-Based Healthc. 2009, 7, 159–168. [Google Scholar] [CrossRef] [Scilit]
- Jovicic, A.; Holroyd-Leduc, J.M.; Straus, S.E. Effects of self-management intervention on health outcomes of patients with heart failure: A systematic review of randomized controlled trials. BMC Cardiovasc. Disord. 2006, 6, 43. [Google Scholar] [CrossRef] [Scilit]
- McAlister, F.A.; Stewart, S.; Ferrua, S.; McMurray, J.J. Multidisciplinary strategies for the management of heart failure patients at high risk for admission: A systematic review of randomized trials. J. Am. Coll. Cardiol. 2004, 44, 810–819. [Google Scholar]
- Fonarow, G.C.; Abraham, W.T.; Albert, N.M.; Stough, W.G.; Gheorghiade, M.; Greenberg, B.H.; O’Connor, C.M.; Pieper, K.; Sun, J.L.; Yancy, C.; et al. Association between performance measures and clinical outcomes for patients hospitalized with heart failure. JAMA 2007, 297, 61–70. [Google Scholar] [CrossRef] [Scilit]
- Toukhsati, S.R.; Driscoll, A.; Hare, D.L. Patient Self-management in Chronic Heart Failure—Establishing Concordance Between Guidelines and Practice. Card. Fail. Rev. 2015, 1, 128–131. [Google Scholar] [CrossRef] [Scilit]
- McGreal, M.H.; Hogan, M.J.; Walsh-Irwin, C.; Maggio, N.J.; Jurgens, C.Y. Heart failure self-care interventions to reduce clinical events and symptom burden. Res. Rep. Clin. Cardiol. 2014, 5, 243–257. [Google Scholar]
- Iyngkaran, P.; Smith, D.; McLachlan, C.; Battersby, M.; de Courten, M.; Hanna, F. Evaluating a New Short Self-Management Tool in Heart Failure Against the Traditional Flinders Program. J. Clin. Med. 2024, 13, 6994. [Google Scholar] [CrossRef] [Scilit]
- Barr, V.; Robinson, S.; Marin-Link, B.; Underhill, L.; Dotts, A.; Ravensdale, D.R.; Salivaras, S. The expanded Chronic Care Model: An integration of concepts and strategies from population health promotion and the Chronic Care Model. Hosp. Q. 2003, 7, 73–82. [Google Scholar] [CrossRef] [Scilit]
- McBain, H.; Shipley, M.; Newman, S. The impact of self-monitoring in chronic illness on healthcare utilisation: A systematic review of reviews. BMC Health Serv. Res. 2015, 15, 565. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goldfarb, M.; De Hert, M.; Detraux, J.; Di Palo, K.; Munir, H.; Music, S.; Piña, I.; Ringen, P.A. Severe Mental Illness and Cardiovascular Disease: JACC State-of-the-Art Review. J. Am. Coll. Cardiol. 2022, 80, 918–933. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chernoff, R.A.; Messineo, G.; Kim, S.; Pizano, D.; Korouri, S.; Danovitch, I.; IsHak, W.W. Psychosocial Interventions for Patients with Heart Failure and Their Impact on Depression, Anxiety, Quality of Life, Morbidity, and Mortality: A Systematic Review and Meta-Analysis. Psychosom Med. 2022, 84, 560–580. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- White-Williams, C.; Rossi, L.P.; Bittner, V.A.; Driscoll, A.; Durant, R.W.; Granger, B.B.; Graven, L.J.; Kitko, L.; Newlin, K.; Shirey, M.; et al. Addressing Social Determinants of Health in the Care of Patients with Heart Failure: A Scientific Statement from the American Heart Association. Circulation 2020, 141, e841–e863. [Google Scholar] [CrossRef] [Scilit]
- Bidwell, J.T.; Conway, C.; Babicheva, V.; Lee, C.S. Person with Heart Failure and Care Partner Dyads: Current Knowledge, Challenges, and Future Directions: State-of-the-Art Review. J. Card. Fail. 2023, 29, 1187–1206. [Google Scholar] [CrossRef] [Scilit]
- Mariani, M.V.; Lavalle, C.; Palombi, M.; Pierucci, N.; Trivigno, S.; D’Amato, A.; Filomena, D.; Cipollone, P.; Laviola, D.; Piro, A.; et al. SGLT2i reduce arrhythmic events in heart failure patients with cardiac implantable electronic devices. ESC Heart Fail. 2025; Early View. [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).