


Abstract
This systematic review aims to identify what rehabilitation care networks, within primary care or between primary and other health care settings, have been described for patients with chronic musculoskeletal pain, and what their impact is on the Quadruple Aim outcomes (health; health care costs; quality of care experienced by patients; work satisfaction for health care professionals). Studies published between 1 January 1994 and 11 April 2019 were identified in PubMed, CINAHL, Web of Science, and PsycInfo. Forty-nine articles represented 34 interventions: 21 within primary care; 6 between primary and secondary/tertiary care; 1 in primary care and between primary and secondary/tertiary care; 2 between primary and social care; 2 between primary, secondary/tertiary, and social care; and 2 between primary and community care. Results on impact were presented in 19 randomized trials, 12 non-randomized studies, and seven qualitative studies. In conclusion, there is a wide variety of content, collaboration, and evaluation methods of interventions. It seems that patient-centered interdisciplinary interventions are more effective than usual care. Further initiatives should be performed for interdisciplinary interventions within and across health care settings and evaluated with mixed methods on all Quadruple Aim outcomes.
1. Introduction
Chronic musculoskeletal pain (CMP) is a leading cause of disability occurring in 19–28% of the European population [1,2]. As many as one-third of primary care consultations concern CMP complaints such as back or knee pain [3]. Complaints often persist for more than five years and have significant impacts on patients’ daily life, leading to high societal and health care costs [4,5,6].
Research indicates that pain needs an integrated biopsychosocial approach to decrease its impact on health. Nevertheless, this impact is expected to increase as people live longer [7,8]. Current care is organized in “silos” with a focus on only one aspect of pain (biomedical, psychological, or societal), instead of an integrated approach. There is little coordination and communication among health care professionals (HCPs), leading to fragmented care [9,10,11]. This results in many monodisciplinary treatments, with a wide variety of treatment approaches, restricted in available time and resources. Thus, there is a call for a different organization of care for patients with CMP [12]. As a possible solution for this fragmented care, the general practitioner (GP) should have a more prominent role in managing patients with chronic and complex diseases such as CMP [13], as there is a need for continuity, comprehensiveness, and coordination in CMP care [14]. Primary care should play a central role in effectively managing and integrating care with mono- and multidisciplinary treatments, with the GP as the case-manager for chronic and complex diseases [15].
Accordingly, the World Health Organization (WHO) developed a guideline for redesigning rehabilitation in health systems [16]. It indicates that rehabilitation services should be integrated within primary care, as well as between primary, secondary, and tertiary levels of health systems, with a case-management role for primary care. This is in line with Coleman et al., who state that disease management interventions that target only patients may be less effective than those that also focus on organization of care and redesign of care delivery [9]. Cieza et al. advise scaling up rehabilitation services in primary care worldwide to ensure that a life-course and integrated perspective on care is achieved [2]. CMP must be approached within a biopsychosocial framework in order to deliver the most effective treatment. Depending on the complexity of the pain problem, it must be provided by different health care disciplines in collaborative teams, either in primary care alone or combined with secondary and tertiary care [17,18].
Collaborative teams of HCPs for pain management in primary care could range in scope from less extensive combinations of GPs and HCPs, focusing on physical and psychological aspects of pain, to broad teams including rehabilitation, psychology, nursing, and case management [19,20]. If these treatments are multimodal, meaning one therapeutic aim per discipline, and involve HCPs from different disciplines, they are termed “multidisciplinary” [21]. For patients with more complex complaints, an interdisciplinary treatment is needed, where all HCPs involved have a common therapeutic aim and a shared biopsychosocial focus. These interdisciplinary care networks can improve clinical care and service delivery, as suggested by Coleman et al. [9].
In order to optimize health system performance, including interdisciplinary care networks, an approach known as the Quadruple Aim is recommended. This comprises four dimensions: health, quality of care experienced by patients, healthcare costs, and HCP work satisfaction [22,23]. There is some evidence that interdisciplinary care networks designed for various diseases can improve these four Quadruple Aim pillars [24,25,26]. Moreover, interdisciplinary care networks for CMP, incorporating a biopsychosocial model in assessing and treating pain, can result in pain reduction, improved quality of life, and improved social functioning [20]. In some cases, return-to-work and vocational outcomes may be seen.
However, it is not known which biopsychosocial interdisciplinary care networks exist within primary care, or between primary care and other health care settings, for the rehabilitation of patients with CMP. Furthermore, the impact of such networks on the Quadruple Aim outcomes of health, health care costs, quality of care experienced by patients, and work satisfaction of HCPs, is unknown. Therefore, this study aims to address these uncertainties. The first research question is: Which interdisciplinary care networks within primary care and between primary care and other health care settings have been implemented in rehabilitation care for patients ≥18 years with CMP over the last 25 years? The second question is: What is the impact of these interdisciplinary care networks on rehabilitation care for patients with CMP, in terms of the Quadruple Aim outcomes: health, health care costs, quality of care experienced by patients, and HCP work satisfaction?
2. Materials and Methods
We conducted a systematic literature review to synthesize studies with interdisciplinary care networks in care for patients with CMP. These interdisciplinary care networks must be implemented within primary care or between primary care and other healthcare settings (secondary or tertiary care, social care, or community-based care) (see Figure 1). As this research did not involve human subjects, we did not seek ethics clearance for the project. The protocol was registered in the international prospective register of systematic reviews (PROSPERO; http://www.crd.york.ac.uk/PROSPERO/ (accessed date: 6 May 2021)) on 28 August 2020 (registration number CRD42020158057). The review was conducted following PRISMA guidelines [27,28].
Figure 1.
Overview of interdisciplinary care networks. GPs = general practitioners; THs = therapists; NRSs = nurses; HCPs = health care professionals.
2.1. Databases Searched and Inclusion and Exclusion Criteria
Studies published between the 1 January 1994 and the 14 November 2019 were identified by searching the databases PubMed, CINAHL, Web of Science, and PsycInfo, and tracing publications from the reference sections of included papers and relevant reviews. Studies were included if the main population comprised patients with CMP, the intervention was implemented in primary care, or a combination of primary care and other health care settings, with a rehabilitation aim and an interdisciplinary care network. Only original descriptions of interventions in Dutch, English, or German were included. Detailed definitions of the in- and exclusion criteria can be found in Table 1. In addition to these criteria, studies with populations comprising a mix of patients with subacute and chronic complaints or with a non-disease-specific intervention were included. From these studies, only the results for patients with CMP were taken into account. Studies investigating group interventions delivered at the same time by HCPs of different disciplines were also included in this review as it was assumed that they would have discussed treatment approaches. In all interventions, the collaboration between HCPs had to be bidirectional to be included. When other articles described the same intervention, these were also included in our review.
Table 1.
Inclusion and exclusion criteria.
2.2. Search Strategy
Terms used were defined by scoping searches and team discussions. An information specialist finalized the search strategy and adapted keywords according to the configuration of each database. Our search strategy has been published online in detail (Appendix A). Briefly, it included variations on the following terms: ‘chronic musculoskeletal pain, fibromyalgia, regional pain, arthritis, interdisciplinary, integrated, multidisciplinary, service, system, delivery, network, physical and rehabilitation medicine, Quadruple Aim, health outcome, quality of care, healthcare costs and satisfaction with work’. Three reviewers (CL (100%), WM (75%), and LB (25%)) independently screened title and abstract, and two reviewers (CL (100%) and LB (100%)) screened all full texts. Disagreements were solved by an arbitrator (IH). Identified references were downloaded and collected using EndNote bibliographic software (Clarivate Analytics, Philadelphia, PA, USA), and the article selection was performed in the review processing software, Rayyan [29].
2.3. Data Extraction and Analysis
CL extracted data on the interdisciplinary care networks, study aims, and outcomes of the included articles. LB reviewed 25% of the data extraction. First, descriptions of the included interventions were compiled. These included: country; name of intervention; target population; health care setting; and description of the collaboration and intervention. If multiple articles were published for one intervention, these were merged to give a complete overview. As shown in Figure 1, health care settings were classified based on the type of intervention: within primary care or between primary care and secondary or tertiary care, community-based care, and/or social care. Interventions in secondary or tertiary care were combined as one category because the distinction between secondary or tertiary care was not always clear from the descriptions given. Descriptions of interventions were extracted from the studies and classified into these categories:
- Assessment (a systematic approach to ensuring that the health service uses its resources to improve the health of the population most efficiently) [31];
- Education—basic knowledge (anatomy, biomechanics, the function of the body, and pathophysiology) [32];
- Education—knowledge of disease prevention and ergonomics (information on prevention, cause of pain, ergonomics, information on posture, information on activity, exercise) [32];
- Education—knowledge of treatment (self-management, lifestyle modification, information on coping with the problems) [32];
- Manual Therapy (passive joint mobilization and massage therapy) [33];
- Specific Exercise Therapy (active and/or active-assisted strengthening, mobilizing, and stretching exercises to restore the function of the affected region) [34];
- General Exercise Therapy (aerobic and resistance training, causing an increase in energy expenditure, to maintain health-related outcomes) [35];
- Mind-Body Exercise Therapy (to enhance the mind’s capacity to positively affect bodily functions and symptoms, including pain, by combining exercises with mental focus) [36];
- Cognitive behavioral therapy (CBT) (integration of exercise therapy with daily performed activities based on cognitive-behavioral principles, time-contingent) [37,38,39,40,41];
- Workplace intervention (a set of comprehensive health promotion and occupational health strategies implemented in the workplace to improve work-related outcomes) [42];
- Anesthetics (local anesthetics for diagnosis and therapy, indications include functional disorders, inflammatory diseases, and acute and chronic pain) [43];
- Medication management (a systematic process of ensuring that the patient’s medication regimen is optimally appropriate, effective, and safe, and that the patient is adhering to this regimen to promote health and reduce the need for health care use) [44].
Second, outcomes relevant to the Quadruple Aim were extracted for each intervention. For these, study dates, study designs, outcome measures with measurement instruments for relevant primary outcomes, and results were recorded. The results of randomized trial designs were presented in two categories: either (1) positive and significant (+) (p < 0.05) compared to the comparator intervention for randomized controlled trial (RCT) designs; or (2) positive and non-significant (p > 0.05), no difference between the intervention and comparator intervention, or alternatively negative and significant for the intervention compared to the comparator intervention (-) (p < 0.05). For non-randomized trial designs, results were classed as significant (+) (p < 0.05) or non-significant (-) (p > 0.05), compared to baseline. Mixed positive and negative results for subdomains are indicated by +/-. For the qualitative studies, opinions are summarized as all positive (+), negative (-), neutral (=), or mixed (+/-). All outcomes from the studies relevant to the Quadruple Aim are presented. Primary outcomes of the studies were identified using the following procedure. First, the primary outcome, as described by the authors, was chosen. If this was not described, the outcome measure used in the sample size calculation was chosen. If this was also not described in the article, the outcome measure best fitting the aim of the intervention was chosen (e.g., aim: improving functioning, outcome measure: health-related quality of life or functioning; aim: return to work, outcome measure: return to work or sick leave; etc.). In the case where this was also unclear from the article, the first choice was the outcome measure for quality of life (often measured in this type of study, making it comparable). Then, costs such as sick leave or return to work were the second choice. After that, quality of care experienced by patients or HCP work satisfaction were the third choice. Based on the homogeneity and the chosen outcome measures, a meta-analysis was considered.
2.4. Risk of Bias in Individual Studies
Quality assessment tools specific to the method(s) employed were used. These tools were used to assess and compare the quality of RCT designs, non-randomized study designs and qualitative designs. For RCT designs, the risk of bias was assessed using Version 2 of the Cochrane risk-of-bias tool for randomized trials (RoB2 tool) [45]. The Risk of Bias in Non-randomized Studies-of Interventions (ROBINS-I) tool was used for assessing non-randomized study designs [46]. Domains not relevant for studies without a control group are marked (-) or (NA). For qualitative designs, the Joanna Briggs Institute Critical Appraisal Tools, Checklist for Qualitative Research, was used for a critical appraisal [47]. This critical appraisal tools assist in assessing the trustworthiness, relevance and results of published papers. At least seven questions (out of 10) had to be answered “yes” to receive a positive overall appraisal. Articles describing study protocols were not assessed for risk of bias. One researcher (CL) assessed the risk of bias and performed the critical appraisal for each study. One researcher (LB) randomly cross-checked 25% of the included studies. Disagreements were resolved by an arbitrator (IH). Review authors were not blinded for author names, institutions, or journals. If additional information was needed, corresponding authors would have been contacted. Results are reported through graphical representation of bias judgements grouped by design of study.
3. Results
The process of the literature review is shown in Figure 2. The combination of keywords yielded 15,428 potentially relevant articles in the databases on 14 November 2019. Overall, 2926 articles were excluded by deduplication, and 11 studies were added with the snowball method, resulting in 12,513 articles. After reviewing the titles and abstracts of the articles, 12,152 of these were excluded. In total, 361 full-text articles were assessed for eligibility, and 320 were excluded for not meeting one or more of the criteria. The most common reasons for exclusion were interventions without an interdisciplinary care component or interdisciplinary interventions without a role for primary care. If interventions were described in other articles as protocols or allied studies, these were also included, leading to 49 included articles describing 34 interventions.
Figure 2.
Process of literature selection.
3.1. Overview of Included Studies
An overview of the included interventions is presented in Table 2. Of the 34 included, 21 consisted of a collaboration of HCPs within primary care [25,48,49,50,51,52,53,54,55,56,57,58,59,60,61,62,63,64,65,66,67,68,69,70,71,72,73,74,75,76]. Examples of these were collaborations between therapists (TH) and nurse practitioners (NP) or more extensive collaborations between physicians/physiatrists (PH), psychologists (PSY), and various THs. These collaborations ranged from merely performing an assessment to giving a complete interdisciplinary treatment in primary care. Nearly all interventions included at least one education module. Only three had a medication management module. Moreover, most studies with collaborating THs had general or specific exercise therapy modules in the intervention. If the interventions had a PSY or Psychosocial counsellor (PSY-C) in the team, these interventions were often focused on Mind-Body Exercise Therapy or CBT.
Table 2.
Overview of included studies.
Furthermore, six interventions existed of a collaboration between primary care and secondary or tertiary care [48,49,50,51,52,53]. Two of these interventions were between a rehabilitation department and primary care [48,51]. Examples of these collaborations were a GP in primary care with a TH, orthopedic surgeon/specialist (OS), or NP in secondary or tertiary care. Collaborations between GPs and extensive rehabilitation teams, consisting of a nurse (NRS), PSY, TH, or PSY-C, and OS. Four interventions existed of an interdisciplinary assessment. In one study, assessment and follow-up were performed by an HCP in secondary care, a TH and a patient via video-conferencing (due to long-distance) [53]. Rothman et al. evaluated a collaboration in assessment and giving advice between a GP and at least three HCPs in secondary or tertiary care [52]. Two of these interventions consisted of an interdisciplinary assessment followed by treatment [48,51]. The other two interventions consisted of an interdisciplinary treatment without an interdisciplinary assessment [49,50].
Additionally, one intervention was applied in an interdisciplinary pain clinic in primary care with collaboration in primary care, as well as between primary care and secondary and tertiary care [54]. THs who usually work in both primary care and secondary/tertiary care settings delivered the treatment in this interdisciplinary pain clinic in primary care, consisting of specific exercise therapy, medication management, and education.
Two interventions were a collaboration between primary care and social care [55,56]. Here, the teams consisted of several THs, a PH, and a case manager. Together, they performed a team assessment and, during the treatment and follow-up meetings, combinations of the HCPs involved delivered the treatment. In both treatments, workplace interventions were included, aimed at a return to work.
In addition, two interventions consisted of a collaboration between primary care, secondary/tertiary care, and social care [57,61]. These extensive interventions also involved the patients’ medical specialists during workplace interventions, in addition to THs, GPs, and occupational physicians (OPs). While both interventions had many similarities, the recruitment of the study populations differed. In the studies of Steenstra et al. and Anema et al., the participants were recruited by the OP, while in the studies of Lambeek et al., the recruitment was by the PHs of the outpatient clinics of participating hospitals [57,59,60,61].
Finally, two interventions existed of a collaboration between primary care and community-based initiatives [62,66]. In the intervention of McBeth et al., & Bee et al., the TH delivered the CBT, and the fitness instructor (FI) from a community-based initiative gave the general exercise therapy [62,66]. The intervention of Bennell et al., and Hinman et al. comprised a physical therapy program delivered by the TH in primary care, CBT by the telephone coach (TC), and an information booklet for education about the disease [64,65].
3.2. Quadruple Aim Outcomes
An overview of the Quadruple Aim outcomes for each intervention is presented in Table 3. After data extraction from the included studies, it became evident that the interventions, outcome measures, and study designs were too heterogeneous to justify meta-analysis in the included studies. Therefore, narrative analyses were conducted.
Table 3.
Overview of study designs, study outcomes, and results based on the Quadruple Aim.
Among the 49 articles, 19 randomized trials, 12 non-randomized studies, 7 qualitative studies, 7 study protocols, 1 description of an intervention, 2 studies with a population with mixed diagnoses, and 1 study regarding barriers and facilitators, were found. Thirty-nine articles had at least one of the Quadruple Aim outcomes as the primary outcome: 18 articles described health outcome measures, 12 described cost outcome measures, 4 described quality of care experienced by patients, and 5 articles describe work satisfaction for HCPs. Hinman et al. described quality of care experienced by patients and HCP work satisfaction as the combined primary outcome [65]. Most studies measured more than one Quadruple Aim outcome, but only two interventions intended to assess all Quadruple Aim outcomes. Dobscha et al. measured all Quadruple Aim outcomes but presented only the baseline results [67]. Bath et al. described all Quadruple Aim outcomes in the protocol article, but not all results are published yet [68].
The outcomes of Dobscha et al., and Gustavsson et al., were only described as baseline measurements for an RCT [67,69]. From the remaining articles, comprising study protocols, description of the intervention, studies with mixed diagnoses, and the study regarding barriers and facilitators, no outcomes could be extracted [25,48,51,52,53,54,58,60,71,72,83,84,85,96]. These studies were used for descriptions of interventions in Table 2.
3.2.1. Within Primary Care—Randomized Trial Designs
The most frequently presented outcome measure among randomized trial designs was pain intensity (five studies [70,71,72,73,74]). For Helminen et al., the maximum follow-up time was three months, resulting in a non-significant difference between intervention and control groups [73]. Four studies reported outcomes at one-year follow-up: two reported a significant improvement (50%) [71,72], while two reported no significant improvement (50%) [70,74]. Pain intensity scores were measured with the 100-mm Visual Analogue Scale (VAS), the Chronic Pain Grade Severity subscale, or the 0–10 numerical pain rating scale (NPRS). Health-related quality of life (HRQoL) was measured in five studies. The improvement on the VAS score at six months of Hansson et al. (2010) was significantly different between intervention and control groups (20%) [75]. In the other four studies (80%), HRQoL was not different between the groups at three, four, or twelve months, as measured with the RAND-36, Short Form-36, and EQ-5D questionnaires [70,72,73,76].
Outcomes regarding sick leave/working days or medication prescription and use were most often measured for the Quadruple Aim of health care costs (five studies). At four-month follow-up, Calner et al. found positive and negative changes at the different levels of working percentages for the number of working participants in the intervention group compared to the control group [70]. Regarding sickness absence, Gustavsson et al. found no significant change in absence at one-year follow-up [69]. Additionally, Helminen et al. found no significant difference in the number of sick-leave days at three-month follow-up between the intervention and control groups [73,76]. They also found no difference in medication use at three-month follow-up between the control and intervention group, just like Sundberg et al. at four-month follow-up [73,76]. Dobscha et al. found a significant difference in opioid prescriptions at one-year follow-up but non-significant differences in the use of adjuvant pain medications between intervention and control groups [72].
Quality of care experienced by patients was measured in two studies. On a self-assessment questionnaire measuring the quality of care completed by patients, Chelimsky et al. found a significant result at one year for the facilitation of patient involvement in care, though no differences at nine weeks and one year were seen by Gustavsson et al. [69,71].
Both of these studies also examined HCP satisfaction with the care they delivered. At one-year follow-up, HCPs providing the interventions rated their work (significantly) more positively than did HCPs in the control conditions.
3.2.2. Within Primary Care—Non-Randomized Study Designs
All included studies had a longitudinal design (follow-up after intervention), but only two studies included a control condition. All seven interventions evaluated health outcomes. Pain intensity was only reported in two studies, with mixed results at one year and significant pain decreases at five years in both studies [87,89]. In four studies, including one protocol, HRQoL was the primary outcome, and in one study, it was the secondary outcome. At three months, six months, one year, and five years, significant changes were found. HRQoL was measured with the Short Form-36 or a self-constructed questionnaire [86,87,90]. Three studies reported no change in quality of life at one- and three-year follow-ups, as measured with the Short Form-36, EQ-5D, or self-constructed questionnaire [87,89,90].
Costs were evaluated in six interventions, with sick leave or paid work participation as the most frequently reported measurement. In Dunstan et al. and Westman et al., the changes in paid work participation and sick leave were non-significant (40% of the studies) at six-months and three-year follow-up, respectively [80,90]. Stein et al. and Mårtensson et al. found at one- and two-year follow-ups significant changes, compared with baseline assessment (40% of the studies) [84,87]. Westman et al. reported mixed results (20% of the studies) for both sick leave and return to work [89]. Stein et al. and Westman et al. found no significant changes at one- and three-year follow-ups for opioids and drug consumption [87,90]. On the other hand, Gurden et al. found a significant decrease in medication usage after discharge [82].
Three studies found significant positive (100%) results for quality of care experienced by patients [82,86,89].
None of these interventions evaluated HCPs’ satisfaction with the care they delivered.
3.2.3. Within Primary Care—Qualitative Designs
None of the six qualitative designs within the primary care interventions evaluated changes in health or costs.
Quality of care experienced by patients was assessed on different items by three studies, with mixed results [79,81,93]. For example, Dunstan et al. found that patients made both positive and negative points about the usefulness of the program for managing their pain, helping them to become more active and to get back to work, but expressed only positive views about the quality of treatment by HCPs. [81]. Additionally, one study found clear positive results (atmosphere, environment, value of one’s contribution) and negative results (expectations of a sick person, reacting but not acting, awareness and integration) on various items [85]. Lovo et al. reported positive results for the quality of care, measured with both qualitative questionnaires and interviews [92].
Lovo et al. evaluated HCP work satisfaction, reporting overall positive results regarding access to care, effective inter-professional practice, and enhanced clinical care [92]. Only technology (telehealth) was scored less positively.
3.2.4. Between Primary Care and Secondary or Tertiary Care—Randomized Trial Designs
All three randomized trial designs of the interventions combining primary care and secondary or tertiary care measured health outcomes [50,52,53]. Rothman et al. reported a non-significant difference between the intervention and control groups at 15-month follow-up for the primary outcome of pain intensity [52]. In the study of Taylor-Gjevre et al., the difference between intervention and control groups in disease activity at a nine-month follow-up was also non-significant [53]. All three studies measured HRQoL but different measurement instruments were used (EQ-5D, Short Form-36, and a self-constructed questionnaire). In two studies, significant results were found on some questionnaires’ subscales, with non-significant results on other subscales, at one-year and 15-month follow-ups, while one study found non-significant results at a nine-month follow-up.
Cost outcomes were measured by Haldersen et al., and Rothman et al. [50,52]. Changes in return to work after 12 months did not differ between groups, while changes in ability to work did at a 15-month follow-up.
Rothman et al., and Taylor-Gjevre et al. measured experienced quality of care by patients with questionnaires [52,53]. Although no differences were found at nine months, at the 15-month follow-up, the intervention group rated quality of care experienced higher than did the control group. HCP work satisfaction was not measured in any of these three studies.
3.2.5. Between Primary Care and Secondary or Tertiary Care—Non-Randomized Trial Designs
Health outcomes were assessed with less widely used outcome measures by all three non-randomized trial designs [48,49,51]. Burnham et al. had pain interference as the primary outcome, which was significant after treatment discharge in the cohort study [48]. Plagge et al. found significant changes in all domains of HRQoL post-intervention [51]. Claassen et al. found significant improvement only in illness perceptions after three months, whereas non-significant differences were found for BMI, pain, and limitations in functional activities, and physical activity after three months [49].
The study of Claassen et al. was the only one measuring the health care costs and quality of care experienced by patients, goals of the Quadruple Aim; both had significant results at the three-month follow-up [49].
None of the three included studies measured HCP work satisfaction.
3.2.6. In Primary Care and between Primary Care and Secondary or Tertiary Care—Randomized Trial Design
Only one study was included which described a collaboration within primary care as well as between primary care and secondary or tertiary care [54]. The study had grip strength as the primary outcome, which was significantly different in the intervention group at the two-month follow-up. The other health outcomes, pain and health status, showed non-significant differences at that time point.
This study also found significant results regarding quality of care experienced by patients at the two-month follow-up.
Costs and HCP work satisfaction were not measured.
3.2.7. Between Primary Care and Social Care—Randomized Trial Design
Bültmann et al. was the only included study evaluating collaboration between primary and social care [55]. For health outcomes, no significant changes in pain intensity and functional disability between intervention and control groups were reported at any time point.
Cumulative sickness absence hours was the primary outcome of this study. Results showed a significant decrease in sick leave at six and 12 months, compared to the control group.
Bültmann et al. did not measure outcomes on quality of care experienced by patients or HCP work satisfaction [55].
3.2.8. Between Primary Care and Social Care—Non-Randomized Study Design
Heijbel et al. evaluated the collaboration between primary and social care, but, in this study, health outcomes and quality of care experienced by patients were not measured [56].
For return to work, the primary outcome of this study, a significant improvement was found after two years.
Mixed results were reported regarding HCP work satisfaction, measuring the experiences of executing and implementing a workplace-based rehabilitation intervention.
3.2.9. Between Primary Care and Secondary or Tertiary Care and Social Care—Randomized Trial Designs
Two interventions in this group were evaluated, one intervention by two studies and the other by one [57,59,60]. Two studies measured health outcomes: pain intensity with the VAS and functional status with the Roland-Morris Disability Questionnaire [57,60]. Only functional status was positively changed at 12 months, whereas the other associations at 3, 6, and 12 months were all non-significant between the groups.
In all three studies, the primary outcome was the duration of sick leave to a full return to work. In both studies of Lambeek, significant differences were found at the 12-month follow-up, favoring the intervention over the control group [59,60]. However, in the study of Anema et al., non-significant differences between interventions were found within the same timeframe [57].
No measurements were performed for the quality of care experienced by patients or HCP work satisfaction.
3.2.10. Between Primary Care and Community-Based Care—Randomized Trial Designs
Two interventions, with three randomized trial designs, of which one was a protocol, were found reporting such collaboration between primary care and community-based care. Two studies measured health outcomes [63,66]. McBeth et al. had change in health as the primary outcome, which was significantly more improved at six and nine months than in the control group [66]. Significant differences in changes were also found between both conditions for kinesiophobia at nine months and for the physical component of HRQoL at both time points, measured with the Short Form-36. For the mental component score, general health and chronic pain grade, no significant results were found. Bennell et al. found non-significant differences in measured health outcomes, of which knee pain intensity and physical functioning in the previous 48 h were the primary outcomes [63].
Costs were assessed in the study of McBeth et al. with a cost-effectiveness analysis [66]. Non-significant differences between intervention and control group at the six- and nine-month follow-ups were found.
No measurements were performed for the quality of care experienced by patients or for HCP work satisfaction.
3.2.11. Between Primary Care and Community-Based Care—Qualitative Designs
Bee et al., and Hinman et al. performed qualitative evaluations for Quadruple Aim goals [62,65]. Mixed results were found regarding participants’ illness experiences, which was a health outcome [62]. No cost outcomes were assessed qualitatively.
Quality of care experienced by patients had mixed results in the study of Bee et al. [62]. Positive as well as negative results were found regarding treatment preferences and the perceived fit with the interventions and their patients’ needs. Hinman et al. measured the satisfaction of HCPs in combination with experiences of patients [65]: their only positive results regarded HCPs’ interest in patients during the treatment and in collaboration. Mixed results were found regarding information and accountability, program structure, and roles and communication in teamwork.
3.3. Risk of Bias
The results of the risk of bias (RoB) per domain for the randomized trial designs (n = 19) are presented in Figure 3 and for the non-randomized study designs (n = 12) in Figure 4. The results of the critical appraisal of the qualitative designs (n = 7) can be found in Figure 5.
Figure 3.
Risk of bias of randomized trial designs.
Figure 4.
Risk of bias of non-randomized study designs.
Figure 5.
Critical appraisal qualitative designs.
3.4. Randomized Trial Designs
Overall, the studies of Dobscha et al., and Lambeek et al., were found to have a low RoB [60,72]. Ten studies raised some concerns in the RoB, and seven studies had a high RoB. The randomization process had a low RoB for 15 studies, while four studies had some concerns [53,57,69,71]. Deviations from the intended interventions most often led to there being some concerns for RoB, in most cases because participants, patients and HCPs, were unblinded. Chemelinsky et al. and Halderson et al. were judged to have some concerns for this RoB domain [50,71]. Completeness of outcome data and measurements of outcomes most often had a low RoB, though there some concerns for three studies [54,73,95]. Six studies had a high RoB on these domains [55,60,66,69,70,71]. There were some concerns about possible selection of reported results with fourteen studies because most study protocols were not published, so planned outcomes could not be matched with published outcomes [49,50,52,53,54,55,66,67,69,70,71,74,75,76].
3.5. Non-Randomized Study Designs
The studies of Dunstan et al., and Heijbel et al. did not report enough information to assess the RoB [56,80]. All other studies were assessed as at high RoB [48,49,50,51,56,80,82,83,84,86,90]. The main reason was the lack of a control group in these studies, which indicated a serious RoB in the domain of confounding. The domain classification of the interventions was not applicable for studies without a control group. Moreover, this domain was found to have a serious RoB because outcome measures could be influenced by the outcome assessors and/or unblinded patients in most studies. The lack of publication of a protocol in any of these studies led to an absence of information about any bias in the selection of the reported results.
3.6. Qualitative Designs
Six studies scored positively in the critical appraisal of study methods [62,65,79,85,92,93]. The study of Dunstan et al. was described only briefly, hindering assessment, and so this study scored negatively [81]. In most studies, the philosophical perspective was not described and a statement locating the researcher culturally or theoretically was not made.
4. Discussion
As far as we know, this systematic review is the first to identify which interdisciplinary rehabilitation interventions have been described within primary care, and between primary care and other health care settings, delivering rehabilitation care to patients with CMP. In addition, we describe the impact of these interdisciplinary interventions in rehabilitation care for patients with CMP, in terms of the Quadruple Aim goals: health, quality of care experienced by patients, health care costs, and HCP work satisfaction. The review was based on 49 articles (34 separate interventions), including 19 randomized trials, 12 non-randomized studies, 7 qualitative studies, and 11 articles with a description of the intervention but without a description of relevant outcomes and/or results.
In summary, of the studies that examined interventions situated in primary care (n = 19), most did not find significantly improved health outcomes compared to care as usual. In the non-randomized designs, in general, health outcomes seemed to improve over time. However, cost outcomes and quality of care experienced by patients in intervention groups showed a mixture of significant improvements and non-improvements in both randomized and non-randomized trial designs. The differences in satisfaction levels may relate to the fact that new interventions can change the usual care pathways, which could be challenging for the patient to follow and thus lead to lower satisfaction. Alternatively, patients who were already very satisfied with the current regular health care received might experience little or even no improvements in satisfaction level after receiving the new intervention (which has also been seen in other studies on substitution of care [96,97,98]). However, it may be concluded that an intervention provides added value even if not all Quadruple Aim goals have shown improvement. For example, if costs decrease, patients’ health and HCP work satisfaction increase, but the quality of care experienced by patients remains unchanged, the intervention is of added value. It is essential that all Quadruple Aim goals be assessed and that a balanced conclusion for follow-up be drawn based on these outcomes [99,100]. For included interventions, HCP work satisfaction was found to be improved in the intervention groups, compared with care as usual and with baseline.
For interventions between primary care and secondary or tertiary care (n = 6), in the randomized trial designs, no significant differences between intervention and care-as-usual groups were found for most health outcomes. Over time, no improvements were seen in a restricted program containing a three-hour educational intervention [49], whereas improvements were seen in two, more extensive, interventions. These latter comprised more treatment hours, involved more health care disciplines, and consisted of an assessment and, depending on patients’ needs, psychological and exercise treatments. Both of the interventions showing improvement included collaboration with a rehabilitation setting [48,51]. Unfortunately, both also displayed a serious risk of bias and, therefore, more research is warranted before drawing definite conclusions. Regarding cost outcomes, ability to work significantly improved while the return to work after 12 months did not improve in these groups [49,50,52]. Grant et al. found that facilitators such as managing pain, managing work, and making workplace adjustments appear to be key factors for successful return to work [101]. It could be that patients perceived their ability to work sufficiently improved for return to work, but that, for example, workplace adjustments were not yet adequate to allow this. Mixed results were reported regarding quality of care experienced by patients in two different interventions containing an interdisciplinary assessment [52,53], while this was perceived positively in a three-hour educational intervention [49].
The combined intervention in primary care and between primary care and secondary or tertiary care (n = 1), described by Stoffer-Marx et al., had some concerns in the risk of bias [54]. The study only showed improvements on the primary health outcome of grip strength, while no difference between groups was seen for pain and health status after two months. Patients receiving the intervention perceived the quality of care as improved after a two-month follow-up, compared to patients receiving care as usual. As this was the only intervention with an extensive interdisciplinary collaboration, no comparisons could be made. However, as future care aims to shift to clinical networks based on collaborations [30], it is important to further explore implementation in clinical practice and research with such collaborations.
An assessment and workplace intervention between primary care and social care (n = 2) did not show a significantly greater improvement in health outcomes for the intervention compared with care as usual [55]. Cost outcomes showed a mixture of improved and unchanged results between the intervention and care as usual at different measurement points in a randomized trial design [55], while return to work improved over time after two years in a longitudinal study [56].
In interventions between primary care and secondary or tertiary care and social care (n = 2), most health outcomes did not differ between patients who received a workplace intervention combined with graded activity and those who received usual care. For cost outcomes, the duration of sick leave differed between groups in two studies [59,60], but not in another [57]. This could probably be explained by the fact that, in addition to the study of Anema et al. [57], in the studies of Lambeek et al. [59,60], the intervention was extended, involving HCPs of different disciplines (such as a case manager and the patients’ pre-existing specialists), potentially leading to a better effect on duration of sick leave. Due to this interdisciplinary collaboration, such interventions may have a more patient-centered focus and biopsychosocial approach, which could explain the reported results. Currently developed eHealth technologies could make it easier to work interdisciplinarily [102]. However, little research has been performed for both types of workplace interventions. This was also found in the systematic review of Skamagki et al. [103]. In contradiction to our review, they found some consistency in health outcomes for (integrated) workplace interventions. In contrast with our included studies, in the review of Skamagki et al., not all included studies comprised integrated, interdisciplinary interventions [103].
For interventions between primary care and community-based care (n = 2), most health outcomes did not differ more in the integrated care condition than with usual care [62,64,66]. No differences in cost outcomes were found between the groups of an intervention existing of combined cognitive behavioral therapy and prescribed exercise compared to treatment as usual (high risk of bias). Quality of care experienced by patients and HCP work satisfaction were found to have both positive and negative results in the interventions. In contrast to our results, other studies found community-based interventions to lower health care costs and improve health outcomes [80,104]. They found that patients often visit HCPs for other complaints than their actual pain or during periods of stress. Easily accessible community-based interventions could take over these kinds of health care visits to both lower costs and increase health.
4.1. Strengths and Limitations
This review is the first with an overview of interdisciplinary rehabilitation interventions within primary care and between primary care and other healthcare settings for patients with CMP. The interventions identified cover a broad spectrum of interdisciplinary care interventions with a wide variety of content, duration, and HCP disciplines involved. Moreover, this review is the first focusing on all Quadruple Aim outcomes for integrated interdisciplinary care interventions. Such an overview is valuable given the recommendation of the WHO that rehabilitation services should be integrated within primary care, as well as between primary, secondary, and tertiary levels of health systems, with a case-management role for primary care [16,105]. Another strength of our study is the classification of interventions into subgroups, facilitating comparisons of studies. This classification is based on classifications used earlier and on definitions of intervention types. Moreover, a strength of our study process was the involvement of an information specialist to ensure the quality of the search strategy. Additionally, the PRISMA guidelines for reporting reviews were used. However, a meta-analysis could not be performed as the intervention types and outcome measures were too heterogeneous.
That the selection of articles was limited to those in English, Dutch, or German may have resulted in the exclusion of valid interventions reported in other languages. Unfortunately, interventions were often not described in full detail and/or the health care settings left unclear, potentially resulting in erroneous exclusions of studies. In some studies, it was not clear in which health care setting an HCP, for example, a physician, worked. Furthermore, it was also not always clear how a health care setting should be classified, due to differences between countries and/or the lack of appropriate descriptions. Due to time constraints, it was not possible to contact the authors for additional information. Therefore, potentially relevant interventions (reported with incomplete descriptions of content) may have been excluded in error. In this review, an interdisciplinary care network is defined based on the IASP definition [21]. Thus, all studies with a multimodal treatment provided by a multidisciplinary team (with at least one participating primary care HCP collaborating in assessment and/or treatment using a shared biopsychosocial model and goals) were taken into account. An alternative definition of interdisciplinary care might have led to a different selection of articles. For the randomized trial designs, positive but non-significant results (compared to the control intervention), results with no difference, and results in favor of the control intervention, were all grouped into one category (non-significant (-)). We chose this grouping because not all articles described the results in much detail. A more precise categorization of significant or non-significant results would have given a broader overview.
4.2. Implications for Future Innovations and Studies
As future health care shifts to the implementation of clinical networks, more interdisciplinary collaborations will have to be developed and evaluated in the field of rehabilitation for patients with CMP. As it is important that these interventions have a good fit with, and are implemented in, daily health care, we recommend applying co-creation research together with the HCP disciplines involved, patients with CMP, and other stakeholders. In the ideal situation, an evaluation of all Quadruple Aim outcomes needs to be performed with mixed methods to give a full overview of a new interdisciplinary care intervention’s impact.
In order to develop, implement, and evaluate interdisciplinary care interventions across different health care settings, it is recommended that an adjusted version of the IASP definition of interdisciplinary care be used, the current one having been developed for treatments in secondary or tertiary care settings. Moreover, the Quadruple Aim was used to classify the various outcomes in four outcome domains to identify the effect of interventions in these domains. However, in our review, it was difficult to compare the effect of the various interventions on these outcomes, as a wide range of outcome measures and assessment methods were used. Due to the large variation found, a meta-analysis could not be executed. Therefore, to improve uniformity, we propose to develop a core outcome set with measurement instruments and assessment methods with standardized measurement moments for each Quadruple Aim goal (health, quality of care experienced by patients, health care costs, and HCP work satisfaction). This will facilitate future research comparing the effect of interventions. Moreover, not all study designs (e.g., mixed methods or qualitative methods) incorporated Quadruple Aim outcomes so our overview could not be complete. Therefore, it is recommended that interventions developed in the future be evaluated with mixed methods study designs. In this review, a large number of full papers had to be screened before making a decision because most abstracts, and some full papers, did not clearly describe the content of their intervention and the degree of collaboration between HCPs. We recommend that articles use reporting guidelines for abstracts and intervention details, such as the Template for Intervention Description and Replication (TIDieR) checklist [106].
5. Conclusions
There is a wide variety in content, collaboration, and evaluation methods of interdisciplinary rehabilitation interventions within primary care, and between primary care and other health care settings, delivering rehabilitation care for patients with CMP. Most interdisciplinary interventions are evaluated in primary care, while fewer interventions are implemented between primary care and other health care settings. It seems that interventions with the involvement of different HCP disciplines, and more patient-centered interventions, with a broader content and duration of treatment, are more effective than care as usual. Therefore, further initiatives and research have to be performed for interdisciplinary care interventions within and across health care settings for patients with CMP. These interventions have to be evaluated with mixed methods on all Quadruple Aim outcomes.
Author Contributions
C.L. was involved in data curation, formal analysis, investigation, methodology, project administration, supervision, validation, visualization, and writing—original draft. L.B. was involved in formal analysis, investigation, methodology, supervision, validation, and writing—review and editing. I.H. was involved in supervision, validation, and writing—review and editing. M.K. and J.V. were involved in supervision and writing—review and editing. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Acknowledgments
We would like to thank Wieneke Meijer (W.M.), for her contribution to the development of the search strategy and her contribution to article selection. Furthermore, we would like to thank Gregor Franssen for his role as information specialist in this review. Scientific proofreading and English editing was done by Les Hearn (les_hearn@yahoo.co.uk).
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A. Literature Searches
Search Pubmed:
| Patient | (((Pain[MeSH:NoExp] OR Pain*[tiab] OR Ache*[tiab]) AND (chronic*[tiab] OR back[tiab] OR musculoskeletal*[tiab] OR Neck[tiab] OR cervical*[tiab] OR lumb*[tiab] OR ankle*[tiab] OR knee*[tiab] OR wrist*[tiab] OR elbow*[tiab] OR shoulder*[tiab] OR hip[tiab] OR pelvic girdle[tiab] OR Physical Suffering*[tiab])) OR Arthralgia[MESH] OR arthralgia*[tiab] OR polyarthralgia*[tiab] OR Muscular Rheumatism[tiab] OR Lumbago[tiab] OR Fibromyalgi*[tiab] OR Neckache*[tiab] OR complex regional pain syndrome[tiab] OR regional pain[tiab] OR Arthritis[MeSH] OR Arthriti*[tiab] OR osteoarthr*[tiab]) |
| AND | |
| Intervention | (((interdisciplin*[tiab] OR integrat*[tiab] OR intersect*[tiab] OR transmural[tiab] OR multidisciplinar*[tiab] OR chain*[tiab] OR Comprehensive[tiab] OR deliver*[tiab] OR network*[tiab] OR coordinat*[tiab] OR collaboration*[tiab] OR level*[tiab] OR appropriate[tiab] OR outpatient[tiab] OR ambulatory[tiab] OR Patient focused[tiab] OR transition*[tiab]) AND (healthcare[tiab] OR care[tiab] OR health care[tiab] OR service*[tiab] OR system*[tiab])) OR Patient Care Management [MeSH:NoExp] OR patient care management [tiab] OR comprehensive health care[MeSH] OR Delivery of Health Care[MeSH] OR pain management[MeSH] OR Pain Management*[tiab] OR integrated delivery system*[tiab] OR managed clinical network*[tiab] OR Intersectoral Collaboration*[tiab] OR managed care[tiab] OR shared care[tiab]) |
| AND | |
| Comparison | ((Physical and Rehabilitation Medicine[MESH] OR physical and rehabilitation medicine[tiab] OR rehabilitation [MESH] OR rehabilitation[tiab] OR Physical Therapy Specialty[MeSH] OR physical therap*[tiab] OR Physical Therapy Modalities[MeSH] OR Physical Therapy Modalit*[tiab] OR occupational therapy[MeSH] OR Occupational Therap*[tiab] OR Physiatry[tiab] OR Habilitation[tiab] OR physiotherap*[tiab] OR biopsychosocial[tiab] OR exercise therapy[tiab])) |
| AND | |
| Outcome | (Quadruple Aim[tiab] OR Triple Aim[tiab] OR health outcome*[tiab] OR quality of health care[MeSH] OR quality of healthcare[tiab] OR Population health[MeSH] OR population health[tiab] OR Quality of Life[MeSH] OR quality of life[tiab] OR treatment Outcome[MeSH] OR treatment outcome*[tiab] OR Clinical Effect*[tiab] OR Rehabilitation Outcome*[tiab] OR Treatment Efficacy[tiab] OR Experienced health[tiab] OR HRQOL[tiab] OR health related quality of life[tiab] OR life quality[tiab] OR patient satisfaction[MeSH] OR patient satisfaction*[tiab] OR Consumer Satisfaction[tiab] OR patient experience*[tiab] OR meaning in work[tiab] OR meaningful work[tiab] OR workforce engagement[tiab] OR work pressure[tiab] OR job satisfaction[MeSH] OR job satisfaction*[tiab] OR work satisfaction[MeSH] OR work satisfaction*[tiab] OR workforce satisfaction[tiab] OR Health care costs[MeSH] OR Health Care Cost*[tiab] OR Health Expenditures[MeSH] OR Health Expenditure*[tiab] OR Cost-Benefit Analysis[MeSH] OR Cost-Benefit Analys*[tiab] OR Costs and Cost Analysis[MeSH] OR Costs and cost analys*[tiab] OR cost effect*[tiab] OR Costs[tiab]) |
| AND | |
| Time | (“1994/11/1”[Date-Publication]: “3000”[Date-Publication]) |
| Final | #6,”Search (((((((((Pain[MeSH:NoExp] OR Pain*[tiab] OR Ache*[tiab]) AND (chronic*[tiab] OR back[tiab] OR musculoskeletal*[tiab] OR Neck[tiab] OR cervical*[tiab] OR lumb*[tiab] OR ankle*[tiab] OR knee*[tiab] OR wrist*[tiab] OR elbow*[tiab] OR shoulder*[tiab] OR hip[tiab] OR pelvic girdle[tiab] OR Physical Suffering*[tiab])) OR Arthralgia[MESH] OR arthralgia*[tiab] OR polyarthralgia*[tiab] OR Muscular Rheumatism[tiab] OR Lumbago[tiab] OR Fibromyalgi*[tiab] OR Neckache*[tiab] OR complex regional pain syndrome[tiab] OR regional pain[tiab] OR Arthritis[MeSH] OR Arthriti*[tiab] OR osteoarthr*[tiab])))) AND (((((interdisciplin*[tiab] OR integrat*[tiab] OR intersect*[tiab] OR transmural[tiab] OR multidisciplinar*[tiab] OR chain*[tiab] OR Comprehensive[tiab] OR deliver*[tiab] OR network*[tiab] OR coordinat*[tiab] OR collaboration*[tiab] OR level*[tiab] OR appropriate[tiab] OR outpatient[tiab] OR ambulatory[tiab] OR Patient focused[tiab] OR transition*[tiab]) AND (healthcare[tiab] OR care[tiab] OR health care[tiab] OR service*[tiab] OR system*[tiab])) OR Patient Care Management [MeSH:NoExp] OR patient care management [tiab] OR comprehensive health care[MeSH] OR Delivery of Health Care[MeSH] OR pain management[MeSH] OR Pain Management*[tiab] OR integrated delivery system*[tiab] OR managed clinical network*[tiab] OR Intersectoral Collaboration*[tiab] OR managed care[tiab] OR shared care[tiab])))) AND ((((Physical and Rehabilitation Medicine[MESH] OR physical and rehabilitation medicine[tiab] OR rehabilitation [MESH] OR rehabilitation[tiab] OR Physical Therapy Specialty[MeSH] OR physical therap*[tiab] OR Physical Therapy Modalities[MeSH] OR Physical Therapy Modalit*[tiab] OR occupational therapy[MeSH] OR Occupational Therap*[tiab] OR Physiatry[tiab] OR Habilitation[tiab] OR physiotherap*[tiab] OR biopsychosocial[tiab] OR exercise therapy[tiab]))))) AND (((Quadruple Aim[tiab] OR Triple Aim[tiab] OR health outcome*[tiab] OR quality of health care[MeSH] OR quality of healthcare[tiab] OR Population health[MeSH] OR population health[tiab] OR Quality of Life[MeSH] OR quality of life[tiab] OR treatment Outcome[MeSH] OR treatment outcome*[tiab] OR Clinical Effect*[tiab] OR Rehabilitation Outcome*[tiab] OR Treatment Efficacy[tiab] OR Experienced health[tiab] OR HRQOL[tiab] OR health related quality of life[tiab] OR life quality[tiab] OR patient satisfaction[MeSH] OR patient satisfaction*[tiab] OR Consumer Satisfaction[tiab] OR patient experience*[tiab] OR meaning in work[tiab] OR meaningful work[tiab] OR workforce engagement[tiab] OR work pressure[tiab] OR job satisfaction[MeSH] OR job satisfaction*[tiab] OR work satisfaction[MeSH] OR work satisfaction*[tiab] OR workforce satisfaction[tiab] OR Health care costs[MeSH] OR Health Care Cost*[tiab] OR Health Expenditures[MeSH] OR Health Expenditure*[tiab] OR Cost-Benefit Analysis[MeSH] OR Cost-Benefit Analys*[tiab] OR Costs and Cost Analysis[MeSH] OR Costs and cost analys*[tiab] OR cost effect*[tiab] OR Costs[tiab])))) AND (““1994/11/1”“[Date-Publication]: ““3000”“[Date-Publication])”,9968,07:24:25 |
Search CINAHL:
| Patient | (((TI Pain OR AB Pain) OR (TI Ache OR AB ache)) AND ((TI chronic OR AB chronic) OR (TI back OR AB back) OR (TI musculoskeletal OR AB musculoskeletal) OR (TI Neck OR AB neck) OR (TI cervical OR AB cervical) OR (TI lumb OR AB lumb) OR (TI ankle OR AB ankle) OR (TI knee OR AB knee) OR (TI wrist OR AB wrist) OR (AB elbow OR TI elbow) OR (TI shoulder OR AB shoulder) OR (TI hip OR AB hip) OR (TI pelvic girdle OR AB pelvic girdle) OR (TI Physical Suffering OR AB physical suffering))) OR TI Arthralgia OR AB arthralgia OR TI polyarthralgia OR AB polyarthralgia OR TI Muscular Rheumatism OR AB muscular rheumatism OR TI Lumbago OR AB lumbago OR TI Fibromyalgia OR AB fibromyalgia OR TI Neckache OR AB neckache OR TI complex regional pain syndrome OR AB complex regional pain syndrome OR TI regional pain OR AB regional pain OR TI Arthritis OR AB arthritis OR TI osteoarthritis OR AB osteoarthritis |
| AND | |
| Intervention | ((TI interdisciplinary OR AB interdisciplinary OR TI integrated OR AB integrated OR TI intersection OR AB intersection OR TI transmural OR AB transmural OR TI multidisciplinary OR AB multidisciplinary OR TI chain OR AB chain OR TI Comprehensive OR AB Comprehensive OR TI delivery OR AB delivery OR TI network OR AB network OR TI coordination OR AB coordination OR TI collaboration OR AB collaboration OR TI level OR AB level OR TI levels OR AB levels OR TI appropriate OR AB appropriate OR TI outpatient OR AB outpatient OR TI ambulatory OR AB ambulatory OR TI Patient focused OR AB patient focused OR TI transition OR AB transition) AND (TI healthcare OR AB healthcare OR TI care OR AB care OR TI health care OR AB health care OR TI service OR AB service OR TI system OR AB system)) OR TI Patient Care Management OR AB patient care management OR TI patient care management OR AB patient care management OR TI comprehensive health care OR AB comprehensive health care OR TI Delivery of Health Care OR AB delivery of health care OR TI pain management OR AB pain management OR TI integrated delivery system OR AB integrated delivery system OR TI managed clinical network OR AB managed clinical network OR TI Intersectoral Collaboration OR AB intersectoral collaboration OR TI managed care OR AB managed care OR TI shared care OR AB shared care |
| AND | |
| Comparison | (TI Physical and Rehabilitation Medicine AB physical and rehabilitation medicine OR TI rehabilitation OR AB rehabilitation OR TI Physical Therapy Specialty OR AB physical therapy specialty OR TI Physical Therapy Modalities OR AB Physical Therapy Modalities OR TI occupational therapy OR AB occupational therapy OR TI Physiatry OR AB physiatry OR TI Habilitation OR AB habilitation OR TI physiotherapy OR AB physiotherapy OR TI biopsychosocial OR AB biopsychosocial OR TI exercise therapy OR AB exercise therapy) |
| AND | |
| Outcome | TI Quadruple Aim OR AB quadruple aim OR TI Triple Aim OR AB triple aim OR TI health outcome OR AB health outcome OR TI quality of health care OR AB quality of healthcare OR TI Population health OR AB population health OR TI Quality of Life OR AB quality of life OR TI treatment Outcome OR AB treatment outcome OR TI Clinical Effect OR AB clinical effect OR TI Rehabilitation Outcome OR AB rehabilitation outcome OR TI Treatment Efficacy OR AB treatment efficacy OR TI Experienced health OR AB experienced health OR TI HRQOL OR AB HRQOL OR TI health related quality of life OR AB health related quality of life OR TI life quality OR AB life quality OR TI patient satisfaction OR AB patient satisfaction OR TI Consumer Satisfaction OR AB consumer satisfaction OR TI patient experience OR AB patient experience OR AB meaning in work OR TI meaning in work OR TI meaningful work OR AB meaningful work OR TI workforce engagement OR AB workforce engagement OR TI work pressure OR AB work pressure OR TI job satisfaction OR AB job satisfaction OR TI work satisfaction OR AB work satisfaction OR TI workforce satisfaction OR AB workforce satisfaction OR TI Health care costs OR AB Health Care Costs OR TI Health Expenditures OR AB Health Expenditures OR TI Cost-Benefit Analysis OR AB Cost-Benefit Analysis OR TI Costs and Cost Analysis OR AB Costs and cost analysis OR TI cost effectivity OR AB cost effectivity OR TI Costs OR AB costs |
| AND | |
| Time | DT 1994–2019 |
| (((TI Pain OR AB Pain) OR (TI Ache OR AB ache)) AND ((TI chronic OR AB chronic) OR (TI back OR AB back) OR (TI musculoskeletal OR AB musculoskeletal) OR (TI Neck OR AB neck) OR (TI cervical OR AB cervical) OR (TI lumb OR AB lumb) OR (TI ankle OR AB ankle) OR (TI knee OR AB knee) OR (TI wrist OR AB wrist) OR (AB elbow OR TI elbow) OR (TI shoulder OR AB shoulder) OR (TI hip OR AB hip) OR (TI pelvic girdle OR AB pelvic girdle) OR (TI Physical Suffering OR AB physical suffering))) OR TI Arthralgia OR AB arthralgia OR TI polyarthralgia OR AB polyarthralgia OR TI Muscular Rheumatism OR AB muscular rheumatism OR TI Lumbago OR AB lumbago OR TI Fibromyalgia OR AB fibromyalgia OR TI Neckache OR AB neckache OR TI complex regional pain syndrome OR AB complex regional pain syndrome OR TI regional pain OR AB regional pain OR TI Arthritis OR AB arthritis OR TI osteoarthritis OR AB osteoarthritis) AND (((TI interdisciplinary OR AB interdisciplinary OR TI integrated OR AB integrated OR TI intersection OR AB intersection OR TI transmural OR AB transmural OR TI multidisciplinary OR AB multidisciplinary OR TI chain OR AB chain OR TI Comprehensive OR AB Comprehensive OR TI delivery OR AB delivery OR TI network OR AB network OR TI coordination OR AB coordination OR TI collaboration OR AB collaboration OR TI level OR AB level OR TI levels OR AB levels OR TI appropriate OR AB appropriate OR TI outpatient OR AB outpatient OR TI ambulatory OR AB ambulatory OR TI Patient focused OR AB patient focused OR TI transition OR AB transition) AND (TI healthcare OR AB healthcare OR TI care OR AB care OR TI health care OR AB health care OR TI service OR AB service OR TI system OR AB system)) OR TI Patient Care Management OR AB patient care management OR TI patient care management OR AB patient care management OR TI comprehensive health care OR AB comprehensive health care OR TI Delivery of Health Care OR AB delivery of health care OR TI pain management OR AB pain management OR TI integrated delivery system OR AB integrated delivery system OR TI managed clinical network OR AB managed clinical network OR TI Intersectoral Collaboration OR AB intersectoral collaboration OR TI managed care OR AB managed care OR TI shared care OR AB shared care) AND ((TI Physical and Rehabilitation Medicine AB physical and rehabilitation medicine OR TI rehabilitation OR AB rehabilitation OR TI Physical Therapy Specialty OR AB physical therapy specialty OR TI Physical Therapy Modalities OR AB Physical Therapy Modalities OR TI occupational therapy OR AB occupational therapy OR TI Physiatry OR AB physiatry OR TI Habilitation OR AB habilitation OR TI physiotherapy OR AB physiotherapy OR TI biopsychosocial OR AB biopsychosocial OR TI exercise therapy OR AB exercise therapy)) AND (TI Quadruple Aim OR AB quadruple aim OR TI Triple Aim OR AB triple aim OR TI health outcome OR AB health outcome OR TI quality of health care OR AB quality of healthcare OR TI Population health OR AB population health OR TI Quality of Life OR AB quality of life OR TI treatment Outcome OR AB treatment outcome OR TI Clinical Effect OR AB clinical effect OR TI Rehabilitation Outcome OR AB rehabilitation outcome OR TI Treatment Efficacy OR AB treatment efficacy OR TI Experienced health OR AB experienced health OR TI HRQOL OR AB HRQOL OR TI health related quality of life OR AB health related quality of life OR TI life quality OR AB life quality OR TI patient satisfaction OR AB patient satisfaction OR TI Consumer Satisfaction OR AB consumer satisfaction OR TI patient experience OR AB patient experience OR AB meaning in work OR TI meaning in work OR TI meaningful work OR AB meaningful work OR TI workforce engagement OR AB workforce engagement OR TI work pressure OR AB work pressure OR TI job satisfaction OR AB job satisfaction OR TI work satisfaction OR AB work satisfaction OR TI workforce satisfaction OR AB workforce satisfaction OR TI Health care costs OR AB Health Care Costs OR TI Health Expenditures OR AB Health Expenditures OR TI Cost-Benefit Analysis OR AB Cost-Benefit Analysis OR TI Costs and Cost Analysis OR AB Costs and cost analysis OR TI cost effectivity OR AB cost effectivity OR TI Costs OR AB costs) Limiters-Published Date: 19941101–20191131 Expanders-Apply related words; Apply equivalent subjects Search modes-Boolean/Phrase |
Search web of science:
| Patient | (((Pain* OR Ache*) AND (chronic* OR musculoskeletal* OR Neck OR cervical* OR lumb* OR ankle* OR knee* OR wrist* OR elbow* OR shoulder* OR hip* OR pelvic girdle OR Physical Suffering*)) OR arthralgia* OR polyarthralgia* OR “Muscular Rheumatism*” OR Lumbago OR Fibromyalgi* OR Neckache* OR “complex regional pain syndrome” OR “regional pain” OR Arthriti* OR osteoarthritis) |
| AND | |
| Intervention | (((interdisciplinary OR integrated OR intersectoral OR transmural OR multidisciplinary OR chain* OR Comprehensive OR deliver* OR network* OR coordination OR collaboration* OR level* OR appropriate OR outpatient OR ambulatory OR Patient focused OR transitional) AND (healthcare OR care OR health care OR service* OR system*)) OR “Patient Care Management” OR “comprehensive health care” OR “Delivery of Health Care” OR “pain management” OR “integrated delivery system*” OR “managed clinical network*” OR “Intersectoral Collaboration*” OR “managed care” OR “shared care”) |
| AND | |
| Comparison | (“Physical and Rehabilitation Medicine” OR rehabilitation OR “Physical Therapy Specialty” OR “physical therap*” OR “Physical Therapy Modalit*” OR “occupational therap*” OR Physiatr* OR Habilitation OR physiotherap* OR biopsychosocial treatment OR “exercise therapy”) |
| AND | |
| Outcome | (“Quadruple Aim” OR “Triple Aim” OR health outcome* OR “quality of health care” OR “quality of healthcare” OR “Population health” OR “Quality of Life” OR “treatment Outcome” OR “Clinical Effect*” OR “Rehabilitation Outcome*” OR “Treatment Efficacy” OR “Experienced health” OR HRQOL OR “health related quality of life” OR “life quality” OR “patient satisfaction” OR “Consumer Satisfaction” OR “patient experience*” OR “meaning in work” OR “meaningful work” OR “workforce engagement” OR “work pressure” OR “job satisfaction” OR “work satisfaction” OR “workforce satisfaction” OR “Health care cost*” OR “Health Expenditure*” OR “Cost-Benefit Analys*” OR “Costs and Cost Analys*” OR “cost effect*” OR Costs) |
| AND | |
| Time | 1994–2019 |
| TOPIC: ((((Pain* OR Ache*) AND (chronic* OR musculoskeletal* OR Neck OR cervical* OR lumb* OR ankle* OR knee* OR wrist* OR elbow* OR shoulder* OR hip* OR pelvic girdle OR Physical Suffering*)) OR arthralgia* OR polyarthralgia* OR “Muscular Rheumatism*” OR Lumbago OR Fibromyalgi* OR Neckache* OR “complex regional pain syndrome” OR “regional pain” OR Arthriti* OR osteoarthritis)) AND TOPIC: ((((interdisciplinary OR integrated OR intersectoral OR transmural OR multidisciplinary OR chain* OR Comprehensive OR deliver* OR network* OR coordination OR collaboration* OR level* OR appropriate OR outpatient OR ambulatory OR Patient focused OR transitional) AND (healthcare OR care OR health care OR service* OR system*)) OR “Patient Care Management” OR “comprehensive health care” OR “Delivery of Health Care” OR “pain management” OR “integrated delivery system*” OR “managed clinical network*” OR “Intersectoral Collaboration*” OR “managed care” OR “shared care”)) AND TOPIC: ((“Physical and Rehabilitation Medicine” OR rehabilitation OR “Physical Therapy Specialty” OR “physical therap*” OR “Physical Therapy Modalit*” OR “occupational therap*” OR Physiatr* OR Habilitation OR physiotherap* OR biopsychosocial treatment OR “exercise therapy”)) AND TOPIC: ((“Quadruple Aim” OR “Triple Aim” OR health outcome* OR “quality of health care” OR “quality of healthcare” OR “Population health” OR “Quality of Life” OR “treatment Outcome” OR “Clinical Effect*” OR “Rehabilitation Outcome*” OR “Treatment Efficacy” OR “Experienced health” OR HRQOL OR “health related quality of life” OR “life quality” OR “patient satisfaction” OR “Consumer Satisfaction” OR “patient experience*” OR “meaning in work” OR “meaningful work” OR “workforce engagement” OR “work pressure” OR “job satisfaction” OR “work satisfaction” OR “workforce satisfaction” OR “Health care cost*” OR “Health Expenditure*” OR “Cost-Benefit Analys*” OR “Costs and Cost Analys*” OR “cost effect*” OR Costs)) Timespan: 1994–2019. Indexes: SCI-EXPANDED, SSCI, A&HCI, CPCI-S, CPCI-SSH, ESCI. |
Search in psycinfo:
| Patient | (((Pain* OR Ache*) AND (chronic* OR musculoskeletal* OR Neck OR cervical* OR lumb* OR ankle* OR knee* OR wrist* OR elbow* OR shoulder* OR hip* OR pelvic girdle OR Physical Suffering*)) OR arthralgia* OR polyarthralgia* OR “Muscular Rheumatism*” OR Lumbago OR Fibromyalgi* OR Neckache* OR “complex regional pain syndrome” OR “regional pain” OR Arthriti* OR osteoarthritis) |
| AND | |
| Intervention | (((interdisciplinary OR integrated OR intersectoral OR transmural OR multidisciplinary OR chain* OR Comprehensive OR deliver* OR network* OR coordination OR collaboration* OR level* OR appropriate OR outpatient OR ambulatory OR Patient focused OR transitional) AND (healthcare OR care OR health care OR service* OR system*)) OR “Patient Care Management” OR “comprehensive health care” OR “Delivery of Health Care” OR “pain management” OR “integrated delivery system*” OR “managed clinical network*” OR “Intersectoral Collaboration*” OR “managed care” OR “shared care”) |
| AND | |
| Comparison | (“Physical and Rehabilitation Medicine” OR rehabilitation OR “Physical Therapy Specialty” OR “physical therap*” OR “Physical Therapy Modalit*” OR “occupational therap*” OR Physiatr* OR Habilitation OR physiotherap* OR biopsychosocial OR “exercise therapy”) |
| AND | |
| Outcome | (“Quadruple Aim” OR “Triple Aim” OR health outcome* OR “quality of health care” OR “quality of healthcare” OR “Population health” OR “Quality of Life” OR “treatment Outcome” OR “Clinical Effect*” OR “Rehabilitation Outcome*” OR “Treatment Efficacy” OR “Experienced health” OR HRQOL OR “health related quality of life” OR “life quality” OR “patient satisfaction” OR “Consumer Satisfaction” OR “patient experience*” OR “meaning in work” OR “meaningful work” OR “workforce engagement” OR “work pressure” OR “job satisfaction” OR “work satisfaction” OR “workforce satisfaction” OR “Health care cost*” OR “Health Expenditure*” OR “Cost-Benefit Analys*” OR “Costs and Cost Analys*” OR “cost effect*” OR Costs) |
| AND | |
| Time | 1994–2019 |
| ((Pain* OR Ache*) AND (chronic* OR musculoskeletal* OR Neck OR cervical* OR lumb* OR ankle* OR knee* OR wrist* OR elbow* OR shoulder* OR hip* OR pelvic girdle OR Physical Suffering*)) OR arthralgia* OR polyarthralgia* OR “Muscular Rheumatism*” OR Lumbago OR Fibromyalgi* OR Neckache* OR “complex regional pain syndrome” OR “regional pain” OR Arthriti* OR osteoarthritis)) AND ((((interdisciplinary OR integrated OR intersectoral OR transmural OR multidisciplinary OR chain* OR Comprehensive OR deliver* OR network* OR coordination OR collaboration* OR level* OR appropriate OR outpatient OR ambulatory OR Patient focused OR transitional) AND (healthcare OR care OR health care OR service* OR system*)) OR “Patient Care Management” OR “comprehensive health care” OR “Delivery of Health Care” OR “pain management” OR “integrated delivery system*” OR “managed clinical network*” OR “Intersectoral Collaboration*” OR “managed care” OR “shared care”)) AND ((“Physical and Rehabilitation Medicine” OR rehabilitation OR “Physical Therapy Specialty” OR “physical therap*” OR “Physical Therapy Modalit*” OR “occupational therap*” OR Physiatr* OR Habilitation OR physiotherap* OR biopsychosocial OR “exercise therapy”)) AND ((“Quadruple Aim” OR “Triple Aim” OR health outcome* OR “quality of health care” OR “quality of healthcare” OR “Population health” OR “Quality of Life” OR “treatment Outcome” OR “Clinical Effect*” OR “Rehabilitation Outcome*” OR “Treatment Efficacy” OR “Experienced health” OR HRQOL OR “health related quality of life” OR “life quality” OR “patient satisfaction” OR “Consumer Satisfaction” OR “patient experience*” OR “meaning in work” OR “meaningful work” OR “workforce engagement” OR “work pressure” OR “job satisfaction” OR “work satisfaction” OR “workforce satisfaction” OR “Health care cost*” OR “Health Expenditure*” OR “Cost-Benefit Analys*” OR “Costs and Cost Analys*” OR “cost effect*” OR Costs)) Limiters-Published Date: 19941101–20191131 Expanders-Apply related words; Apply equivalent subjects Search modes-Boolean/Phrase |
References
- Breivik, H.; Collett, B.; Ventafridda, V.; Cohen, R.; Gallacher, D. Survey of chronic pain in Europe: Prevalence, impact on daily life, and treatment. Eur. J. Pain 2006, 10, 287. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cieza, A.; Causey, K.; Kamenov, K.; Hanson, S.W.; Chatterji, S.; Vos, T. Global estimates of the need for rehabilitation based on the Global Burden of Disease study 2019: A systematic analysis for the Global Burden of Disease Study. Lancet 2020, 396, 2006–2017. [Google Scholar] [CrossRef] [Scilit]
- Jordan, K.P.; Jöud, A.; Bergknut, C.; Croft, P.; Edwards, J.J.; Peat, G.; Petersson, I.F.; Turkiewicz, A.; Wilkie, R.; Englund, M. International comparisons of the consultation prevalence of musculoskeletal conditions using population-based healthcare data from England and Sweden. Ann. Rheum. Dis. 2013, 73, 212–218. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gaskin, D.J.; Richard, P. The economic costs of pain in the United States. J. Pain 2012, 13, 715–724. [Google Scholar] [CrossRef] [Scilit]
- Breivik, H.; Eisenberg, E.; O’Brien, T. The individual and societal burden of chronic pain in Europe: The case for strategic prioritisation and action to improve knowledge and availability of appropriate care. BMC Public Health 2013, 13, 1229. [Google Scholar] [CrossRef] [Scilit]
- Bekkering, G.E.; Bala, M.M.; Reid, K.; Kellen, E.; Harker, J.; Riemsma, R.; Huygen, F.J.P.M.; Kleijnen, J. Epidemiology of chronic pain and its treatment in The Netherlands. Neth. J. Med. 2011, 69, 141–153. [Google Scholar]
- Hoy, D.G.; Smith, E.; Cross, M.; Sanchez-Riera, L.; Buchbinder, R.; Blyth, F.M.; Brooks, P.; Woolf, A.D.; Osborne, R.H.; Fransen, M.; et al. The global burden of musculoskeletal conditions for 2010: An overview of methods. Ann. Rheum. Dis. 2014, 73, 982–989. [Google Scholar] [CrossRef] [Scilit]
- Brooks, P.M. The burden of musculoskeletal disease—A global perspective. Clin. Rheumatol. 2006, 25, 778–781. [Google Scholar] [CrossRef] [Scilit]
- Coleman, K.; Mattke, S.; Perrault, P.J.; Wagner, E.H. Untangling practice redesign from disease management: How do we best care for the chronically ill? Annu. Rev. Public Health 2009, 30, 385–408. [Google Scholar] [CrossRef] [Scilit]
- Anderson, G.; Knickman, J.R. Changing the chronic care system to meet people’s needs. Health Aff. 2001, 20, 146–160. [Google Scholar] [CrossRef] [Scilit]
- Wagner, E.H.; Austin, B.T.; Davis, C.; Hindmarsh, M.; Schaefer, J.; Bonomi, A. Improving chronic illness care: Translating evidence into action. Health Aff. 2001, 20, 64–78. [Google Scholar] [CrossRef] [Scilit]
- Smith, B.H.; Torrance, N. Management of chronic pain in primary care. Curr. Opin. Support. Palliat. Care 2011, 5, 137–142. [Google Scholar] [CrossRef] [Scilit]
- Starfield, B.; Shi, L.; Macinko, J. Contribution of primary care to health systems and health. Milbank Q. 2005, 83, 457–502. [Google Scholar] [CrossRef] [Scilit]
- Rothman, A.A.; Wagner, E.H. Chronic illness management: What is the role of primary care? Ann. Intern. Med. 2003, 138, 256–261. [Google Scholar] [CrossRef] [Scilit]
- Boeckxstaens, P.; Maeseneer, J.; Sutter, A. The role of general practitioners and family physicians in the management of multimorbidity. In Comorbidity of Mental and Physical Disorders; Karger Publishers: Basel, Switzerland, 2015; pp. 129–147. [Google Scholar]
- World Health Organization. Rehabilitation in Health Systems; WHO: Geneva, Switzerland, 2017. [Google Scholar]
- Gatchel, R.J.; Peng, Y.B.; Peters, M.L.; Fuchs, P.N.; Turk, D.C. The biopsychosocial approach to chronic pain: Scientific advances and future directions. Psychol. Bull. 2007, 133, 581–624. [Google Scholar] [CrossRef] [Scilit]
- Kamper, S.J.; Apeldoorn, A.T.; Chiarotto, A.; Smeets, R.J.; Ostelo, R.W.J.G.; Guzman, J.; Van Tulder, M.W. Multidisciplinary biopsychosocial rehabilitation for chronic low back pain. Cochrane Database Syst. Rev. 2014, 2014, CD000963. [Google Scholar] [CrossRef] [Scilit]
- Gatchel, R.J.; McGeary, D.D.; Peterson, A.; Moore, M.; LeRoy, K.; Isler, W.C.; Hryshko-Mullen, A.S.; Edell, T. Preliminary findings of a randomized controlled trial of an interdisciplinary military pain program. Mil. Med. 2009, 174, 270–277. [Google Scholar] [CrossRef] [Scilit]
- Stanos, S.; Houle, T.T. Multidisciplinary and interdisciplinary management of chronic pain. Phys. Med. Rehabil. Clin. N. Am. 2006, 17, 435–450. [Google Scholar] [CrossRef] [Scilit]
- International Association for the Study of Pain Terminology Working Group. Classification of Chronic Pain, 2nd ed.; IASP: Washington, DC, USA, 2011; Available online: https://www.iasp-pain.org/PublicationsNews/Content.aspx?ItemNumber=1673&.navItemNumber=677 (accessed on 6 May 2021).
- Berwick, D.M.; Nolan, T.W.; Whittington, J. The triple aim: Care, health, and cost. Health Aff. 2008, 27, 759–769. [Google Scholar] [CrossRef] [Scilit]
- Bodenheimer, T.; Sinsky, C. From triple to quadruple aim: Care of the patient requires care of the provider. Ann. Fam. Med. 2014, 12, 573–576. [Google Scholar] [CrossRef] [Scilit]
- D’Alleva, A.; Leigheb, F.; Rinaldi, C.; Di Stanislao, F.; Vanhaecht, K.; De Ridder, D.; Bruyneel, L.; Cangelosi, G.; Panella, M. Achieving quadruple aim goals through clinical networks: A systematic review. J. Health Qual. Res. 2019, 34, 29–39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Purcell, N.; Zamora, K.; Tighe, J.; Li, Y.; Douraghi, M.; Seal, K. The integrated pain team: A mixed-methods evaluation of the impact of an embedded interdisciplinary pain care intervention on primary care team satisfaction, confidence, and perceptions of care effectiveness. Pain Med. 2017, 19, 1748–1763. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Metzelthin, S.F.; Daniëls, R.; Van Rossum, E.; Cox, K.; Habets, H.; De Witte, L.P.; Kempen, G.I. A nurse-led interdisciplinary primary care approach to prevent disability among community-dwelling frail older people: A large-scale process evaluation. Int. J. Nurs. Stud. 2013, 50, 1184–1196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moher, D.; Liberati, A.; Tetzlaff, J.; Altman, D.G.; The PRISMA Group. Preferred reporting items for systematic reviews and meta-analyses: The PRISMA statement. PLoS Med. 2009, 6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liberati, A.; Altman, D.G.; Tetzlaff, J.; Mulrow, C.D.; Gøtzsche, P.C.; Ioannidis, J.P.; Clarke, M.F.; Devereaux, P.J.; Kleijnen, J.; Moher, D. The PRISMA statement for reporting systematic reviews and meta-analyses of studies that evaluate health care interventions: Explanation and elaboration. Ann. Intern. Med. 2009, 151. [Google Scholar] [CrossRef] [PubMed]
- Ouzzani, M.; Hammady, H.; Fedorowicz, Z.; Elmagarmid, A. Rayyan—A web and mobile app for systematic reviews. Syst. Rev. 2016, 5, 1–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization. Rehabilitation. 2020. Available online: https://www.who.int/news-room/fact-sheets/detail/rehabilitation (accessed on 23 December 2020).
- Wright, J.; Williams, R.; Wilkinson, J.R. Health needs assessment: Development and importance of health needs assessment. Br. Med. J. 1998, 316, 1310–1313. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ainpradub, K.; Sitthipornvorakul, E.; Janwantanakul, P.; van der Beek, A.J. Effect of education on non-specific neck and low back pain: A meta-analysis of randomized controlled trials. Man. Ther. 2016, 22, 31–41. [Google Scholar] [CrossRef] [Scilit]
- Egmond, D.L.; Schuitemaker, R.; Mink, A.J.F. Extremiteiten: Manuele Therapie in Enge en Ruime Zin; Bohn Stafleu van Loghum: Houten, The Netherlands, 2014. [Google Scholar]
- McNeely, M.L.; Campbell, K.; Ospina, M.; Rowe, B.H.; Dabbs, K.; Klassen, T.P.; Mackey, J.; Courneya, K. Exercise interventions for upper-limb dysfunction due to breast cancer treatment. Cochrane Database Syst. Rev. 2010, 2010, CD005211. [Google Scholar] [CrossRef] [Scilit]
- Mishra, S.I.; Scherer, R.W.; Geigle, P.M.; Berlanstein, D.R.; Topaloglu, O.; Gotay, C.C.; Snyder, C. Exercise interventions on health-related quality of life for cancer survivors. Cochrane Database Syst. Rev. 2012, 2012, CD007566. [Google Scholar] [CrossRef] [Scilit]
- Husebø, A.M.L.; Husebø, T.L. Quality of life and breast cancer: How can mind-body exercise therapies help? An overview study. Sports 2017, 5, 79. [Google Scholar] [CrossRef] [Scilit]
- Lindström, I.; Öhlund, C.; Eek, C.; Wallin, L.; Peterson, L.-E.; Fordyce, W.E.; Nachemson, A.L. The effect of graded activity on patients with subacute low back pain: A randomized prospective clinical study with an operant-conditioning behavioral approach. Phys. Ther. 1992, 72, 279–290. [Google Scholar] [CrossRef] [Scilit]
- Linton, S.J.; Hellsing, A.-L.; Andersson, D. A controlled study of the effects of an early intervention on acute musculoskeletal pain problems. Pain 1993, 54, 353–359. [Google Scholar] [CrossRef] [Scilit]
- Ostelo, R.W.J.G.; De Vet, H.C.W.; Berfelo, M.W.; Kerckhoffs, M.R.; Vlaeyen, J.W.S.; Wolters, P.M.J.C.; Brandt, P.A.V.D. Effectiveness of behavioral graded activity after first-time lumbar disc surgery: Short term results of a randomized controlled trial. Eur. Spine J. 2003, 12, 637–644. [Google Scholar] [CrossRef] [Scilit]
- Fordyce, W.E.; Fowler, R.S.; Lehmann, J.F.; DeLateur, B.J.; Sand, P.L.; Trieschmann, R.B. Operant conditioning in the treatment of chronic pain. Arch. Phys. Med. Rehabil. 1973, 54, 399–408. [Google Scholar]
- Vlaeyen, J.W.S.; Haazen, I.W.C.J.; Schuerman, J.A.; Kole-Snijders, A.M.J.; Eek, H. Behavioural rehabilitation of chronic low back pain: Comparison of an operant treatment, an operant-cognitive treatment and an operant-respondent treatment. Br. J. Clin. Psychol. 1995, 34, 95–118. [Google Scholar] [CrossRef] [Scilit]
- Centers for Disease Control and Prevention Division of Population Health National Center for Chronic Disease Prevention and Health Promotion. Workplace Health Model. 2016. Available online: https://www.cdc.gov/workplacehealthpromotion/model/index.html (accessed on 6 May 2021).
- Egli, S.; Pfister, M.; Ludin, S.M.; De La Vega, K.P.; Busato, A.; Fischer, L. Long-term results of therapeutic local anesthesia (neural therapy) in 280 referred refractory chronic pain patients. BMC Complement. Altern. Med. 2015, 15, 200. [Google Scholar] [CrossRef] [Scilit]
- Pellegrin, K.; Chan, F.; Pagoria, N.; Jolson-Oakes, S.; Uyeno, R.; Levin, A. A statewide medication management system: Health information exchange to support drug therapy optimization by pharmacists across the continuum of care. Appl. Clin. Inform. 2018, 9, 1–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Higgins, J.P.T.; Altman, D.G.; Gøtzsche, P.C.; Jüni, P.; Moher, D.; Oxman, A.D.; Savović, J.; Schulz, K.F.; Weeks, L.; Sterne, J.A.C.; et al. The Cochrane Collaboration’s tool for assessing risk of bias in randomised trials. Br. Med. J. 2011, 343, d5928. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sterne, J.A.; Hernán, M.A.; Reeves, B.C.; Savović, J.; Berkman, N.D.; Viswanathan, M.; Henry, D.; Altman, D.G.; Ansari, M.T.; Boutron, I.; et al. ROBINS-I: A tool for assessing risk of bias in non-randomised studies of interventions. Br. Med. J. 2016, 355, i4919. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- The Joanna Briggs Institute. Critical Appraisal Tools, Checklist for Qualitative Research; JBI: Adelaide, Australia, 2020. [Google Scholar]
- Burnham, R.; Day, J.; Dudley, W. Multidisciplinary chronic pain management in a rural Canadian setting. Can. J. Rural Med. 2010, 15, 7–13. [Google Scholar]
- Claassen, A.A.O.M.; Schers, H.J.; Koëter, S.; Van Der Laan, W.H.; Kremers-van de Hei, K.C.A.L.C.; Botman, J.; Busch, V.J.J.F.; Rijnen, W.H.C.; van den Ende, C.H.M. Preliminary effects of a regional approached multidisciplinary educational program on healthcare utilization in patients with hip or knee osteoarthritis: An observational study. BMC Fam. Pract. 2018, 19, 82. [Google Scholar] [CrossRef] [Scilit]
- Haldorsen, E.M.; Kronholm, K.; Skouen, J.S.; Ursin, H. Multimodal cognitive behavioral treatment of patients sicklisted for musculoskeletal pain: A randomized controlled study. Scand. J. Rheumatol. 1998, 27, 16–25. [Google Scholar]
- Plagge, J.M.; Lu, M.W.; Lovejoy, T.I.; Karl, A.I.; Dobscha, S.K. Treatment of comorbid pain and PTSD in returning veterans: A collaborative approach utilizing behavioral activation. Pain Med. 2013, 14, 1164–1172. [Google Scholar] [CrossRef] [Scilit]
- Rothman, M.G.; Ortendahl, M.; Rosenblad, A.; Johansson, A.C. Improved quality of life, working ability, and patient satisfaction after a pretreatment multimodal assessment method in patients with mixed chronic muscular pain: A randomized-controlled study. Clin. J. Pain 2013, 29, 195–204. [Google Scholar] [CrossRef] [Scilit]
- Taylor-Gjevre, R.; Nair, B.; Bath, B.; Okpalauwaekwe, U.; Sharma, M.; Penz, E.; Trask, C.; Stewart, S.A. Addressing rural and remote access disparities for patients with inflammatory arthritis through video-conferencing and innovative inter-professional care models. Musculoskelet. Care 2018, 16, 90–95. [Google Scholar] [CrossRef] [Scilit]
- Stoffer-Marx, M.A.; Klinger, M.; Luschin, S.; Meriaux-Kratochvila, S.; Zettel-Tomenendal, M.; Nell-Duxneuner, V.; Zwerina, J.; Kjeken, I.; Hackl, M.; Öhlinger, S.; et al. Functional consultation and exercises improve grip strength in osteoarthritis of the hand—A randomised controlled trial. Arthritis Res. 2018, 20, 253. [Google Scholar] [CrossRef] [Scilit]
- Bültmann, U.; Sherson, D.; Olsen, J.; Hansen, C.L.; Lund, T.; Kilsgaard, J. Coordinated and tailored work rehabilitation: A randomized controlled trial with economic evaluation undertaken with workers on sick leave due to musculoskeletal disorders. J. Occup. Rehabil. 2009, 19, 81–93. [Google Scholar] [CrossRef] [Scilit]
- Heijbel, B.; Josephson, M.; Vingård, E. Implementation of a rehabilitation model for employees on long-term sick leave in the public sector: Difficulties, counter-measures, and outcomes. Work 2013, 45, 323–333. [Google Scholar] [CrossRef] [Scilit]
- Anema, J.R.; Steenstra, I.A.; Bongers, P.M.; de Vet, H.C.; Knol, D.L.; Loisel, P.; van Mechelen, W. Multidisciplinary rehabilitation for subacute low back pain: Graded activity or workplace intervention or both? A randomized controlled trial. Spine 2007, 32, 291–298. [Google Scholar] [CrossRef] [Scilit]
- Lambeek, L.C.; Anema, J.R.; Van Royen, B.J.; Buijs, P.C.; Wuisman, P.I.; Van Tulder, M.W.; Van Mechelen, W. Multidisciplinary outpatient care program for patients with chronic low back pain: Design of a randomized controlled trial and cost-effectiveness study [ISRCTN28478651]. BMC Public Health 2007, 7, 254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lambeek, L.C.; Bosmans, J.E.; Van Royen, B.J.; Van Tulder, M.W.; Van Mechelen, W.; Anema, J.R. Effect of integrated care for sick listed patients with chronic low back pain: Economic evaluation alongside a randomised controlled trial. Br. Med. J. 2010, 341, c6414. [Google Scholar] [CrossRef] [Scilit]
- Lambeek, L.C.; Van Mechelen, W.; Knol, D.L.; Loisel, P.; Anema, J.R. Randomised controlled trial of integrated care to reduce disability from chronic low back pain in working and private life. Br. Med. J. 2010, 340, c1035. [Google Scholar] [CrossRef] [Scilit]
- Steenstra, I.A.; Anema, J.R.; Bongers, P.M.; De Vet, H.C.W.; Van Mechelen, W. Cost effectiveness of a multi-stage return to work program for workers on sick leave due to low back pain, design of a population based controlled trial [ISRCTN60233560]. BMC Musculoskelet. Disord. 2003, 4, 26. [Google Scholar] [CrossRef] [Scilit]
- Bee, P.; McBeth, J.; Macfarlane, G.J.; Lovell, K. Managing chronic widespread pain in primary care: A qualitative study of patient perspectives and implications for treatment delivery. BMC Musculoskelet. Disord. 2016, 17, 354. [Google Scholar] [CrossRef] [Scilit]
- Bennell, K.L.; Campbell, P.K.; Egerton, T.; Metcalf, B.; Kasza, J.; Forbes, A.; Bills, C.; Gale, J.; Harris, A.; Kolt, G.S.; et al. Telephone coaching to enhance a home-based physical activity program for knee osteoarthritis: A randomized clinical trial. Arthritis Care Res. 2017, 69, 84–94. [Google Scholar] [CrossRef] [Scilit]
- Bennell, K.L.; Egerton, T.; Bills, C.; Gale, J.; Kolt, G.S.; Bunker, S.J.; Hunter, D.J.; Brand, C.A.; Forbes, A.; Harris, A.; et al. Addition of telephone coaching to a physiotherapist-delivered physical activity program in people with knee osteoarthritis: A randomised controlled trial protocol. BMC Musculoskelet. Disord. 2012, 13, 246. [Google Scholar] [CrossRef] [Scilit]
- Hinman, R.S.; Delany, C.M.; Campbell, P.K.; Gale, J.; Bennell, K.L. Physical therapists, telephone coaches, and patients with knee osteoarthritis: Qualitative study about working together to promote exercise adherence. Phys. Ther. 2016, 96, 479–493. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McBeth, J.; Prescott, G.; Scotland, G.; Lovell, K.; Keeley, P.; Hannaford, P.; McNamee, P.; Symmons, D.P.M.; Woby, S.; Gkazinou, C.; et al. Cognitive behavior therapy, exercise, or both for treating chronic widespread pain. Arch. Intern. Med. 2012, 172, 48–57. [Google Scholar] [CrossRef] [Scilit]
- Dobscha, S.K.; Corson, K.; Leibowitz, R.Q.; Sullivan, M.D.; Gerrity, M.S. Rationale, design, and baseline findings from a randomized trial of collaborative care for chronic musculoskeletal pain in primary care. Pain Med. 2008, 9, 1050–1064. [Google Scholar] [CrossRef] [Scilit]
- Bath, B.; Grona, S.L.; Milosavljevic, S.; Sari, N.; Imeah, B.; O’Connell, M.E. Advancing interprofessional primary health care services in rural settings for people with chronic low back disorders: Protocol of a community-based randomized controlled trial. JMIR Res. Protoc. 2016, 5, e212. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gustavsson, C.; Nordlander, J.; Söderlund, A. Activity and life-role targeting rehabilitation for persistent pain: Feasibility of an intervention in primary healthcare. Eur. J. Physiother. 2018, 20, 141–151. [Google Scholar] [CrossRef] [Scilit]
- Calner, T.; Nordin, C.; Eriksson, M.; Nyberg, L.; Gard, G.; Michaelson, P. Effects of a self-guided, web-based activity programme for patients with persistent musculoskeletal pain in primary healthcare: A randomized controlled trial. Eur. J. Pain 2017, 21, 1110–1120. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chelimsky, T.C.; Fischer, R.L.; Levin, J.B.; Cheren, M.I.; Marsh, S.K.; Janata, J.W. The primary practice physician Program for Chronic Pain (© 4PCP): Outcomes of a primary physician-pain specialist collaboration for community-based training and support. Clin. J. Pain 2013, 29, 1036–1043. [Google Scholar] [CrossRef] [Scilit]
- Dobscha, S.K.; Corson, K.; Perrin, N.A.; Hanson, G.C.; Leibowitz, R.Q.; Doak, M.N.; Dickinson, K.C.; Sullivan, M.D.; Gerrity, M.S. Collaborative care for chronic pain in primary care: A cluster randomized trial. J. Am. Med. Assoc. 2009, 301, 1242–1252. [Google Scholar] [CrossRef] [Scilit]
- Helminen, E.-E.; Sinikallio, S.H.; Valjakka, A.L.; Väisänen-Rouvali, R.H.; Arokoski, J.P.A. Effectiveness of a cognitive–behavioural group intervention for knee osteoarthritis pain: A randomized controlled trial. Clin. Rehabil. 2015, 29, 868–881. [Google Scholar] [CrossRef] [Scilit]
- Nordin, C.A.; Michaelson, P.; Gard, G.; Eriksson, M.K.; Gustavsson, C.; Buhrman, M. Effects of the web behavior change program for activity and multimodal pain rehabilitation: Randomized controlled trial. J. Med. Internet Res. 2016, 18, e265. [Google Scholar] [CrossRef] [Scilit]
- Hansson, E.E.; Sörensson, E.; Ronnheden, A.-M.; Lundgren, M.; Bjärnung, A.; Dahlberg, L.E. Arthritis school in primary health care. A pilot study of 14 years of experiences from Malmo. Lakartidningen 2008, 105, 2175–2177. [Google Scholar]
- Sundberg, T.; Halpin, J.; Warenmark, A.; Falkenberg, T. Towards a model for integrative medicine in Swedish primary care. BMC Health Serv. Res. 2007, 7, 107. [Google Scholar] [CrossRef] [Scilit]
- DeBar, L.; Benes, L.; Bonifay, A.; Deyo, R.A.; Elder, C.R.; Keefe, F.J.; Leo, M.C.; McMullen, C.; Mayhew, M.; Owen-Smith, A.; et al. Interdisciplinary team-based care for patients with chronic pain on long-term opioid treatment in primary care (PPACT)—Protocol for a pragmatic cluster randomized trial. Contemp. Clin. Trials 2018, 67, 91–99. [Google Scholar] [CrossRef] [Scilit]
- Helminen, E.-E.; Sinikallio, S.H.; Valjakka, A.L.; Väisänen-Rouvali, R.H.; Arokoski, J.P. Effectiveness of a cognitive-behavioral group intervention for knee osteoarthritis pain: Protocol of a randomized controlled trial. BMC Musculoskelet. Disord. 2013, 14, 46. [Google Scholar] [CrossRef] [Scilit]
- Nordin, C.; Michaelson, P.; Eriksson, M.K.; Gard, G. It’s about me: Patients’ experiences of patient participation in the web behavior change program for activity in combination with multimodal pain rehabilitation. J. Med. Internet Res. 2017, 19, e22. [Google Scholar] [CrossRef] [Scilit]
- Dunstan, D.A.; Covic, T. Can a rural community-based work-related activity program make a difference for chronic pain-disabled injured workers? Aust. J. Rural Health 2007, 15, 166–171. [Google Scholar] [CrossRef] [Scilit]
- Dunstan, D.A. Participants’ evaluation of a brief intervention for pain-related work disability. Int. J. Rehabil. Res. 2014, 37, 368–370. [Google Scholar] [CrossRef] [Scilit]
- Gurden, M.; Morelli, M.; Sharp, G.; Baker, K.; Betts, N.; Bolton, J. Evaluation of a general practitioner referral service for manual treatment of back and neck pain. Prim. Health Care Res. Dev. 2012, 13, 204–210. [Google Scholar] [CrossRef] [Scilit]
- Mårtensson, L.; Marklund, B.; Fridlund, B. Evaluation of a biopsychosocial rehabilitation programme in primary healthcare for chronic pain patients. Scand. J. Occup. Ther. 1999, 6, 157–165. [Google Scholar]
- Mårtensson, L.; Marklund, B.; Baigi, A.; Gunnarsson, M.; Fridlund, B. Long-term influences of a biopsychosocial rehabilitation programme for chronic pain patients. Musculoskelet. Care 2004, 2, 152–164. [Google Scholar] [CrossRef] [Scilit]
- Mårtensson, L.; Dahlin-Ivanoff, S. Experiences of a primary health care rehabilitation programme. A focus group study of persons with chronic pain. Disabil. Rehabil. 2006, 28, 985–995. [Google Scholar] [CrossRef] [Scilit]
- Schütze, R.; Slater, H.; O’Sullivan, P.; Thornton, J.; Finlay-Jones, A.; Rees, C.S. Mindfulness-based functional therapy: A preliminary open trial of an integrated model of care for people with persistent low back pain. Front. Psychol. 2014, 5, 839. [Google Scholar]
- Stein, K.F.; Miclescu, A. Effectiveness of multidisciplinary rehabilitation treatment for patients with chronic pain in a primary health care unit. Scand. J. Pain 2013, 4, 190–197. [Google Scholar] [CrossRef] [Scilit]
- Tyack, Z.; Frakes, K.-A.; Cornwell, P.; Kuys, S.S.; Barnett, A.G.; McPhail, S.M. The health outcomes and costs of people attending an interdisciplinary chronic disease service in regional Australia: Protocol for a longitudinal cohort investigation. BMC Health Serv. Res. 2013, 13, 410. [Google Scholar] [CrossRef] [Scilit]
- Westman, A.; Linton, S.J.; Theorell, T.; Öhrvik, J.; Wåhlén, P.; Leppert, J. Quality of life and maintenance of improvements after early multimodal rehabilitation: A 5-year follow-up. Disabil. Rehabil. 2006, 28, 437–446. [Google Scholar] [CrossRef] [Scilit]
- Westman, A.; Linton, S.J.; Öhrvik, J.; Wahlén, P.; Theorell, T.; Leppert, J. Controlled 3-year follow-up of a multidisciplinary pain rehabilitation program in primary health care. Disabil. Rehabil. 2009, 32, 307–316. [Google Scholar] [CrossRef] [Scilit]
- Dorflinger, L.M.; Ruser, C.; Sellinger, J.; Edens, E.L.; Kerns, R.D.; Becker, W.C. integrating interdisciplinary pain management into primary care: Development and implementation of a novel clinical program. Pain Med. 2014, 15, 2046–2054. [Google Scholar] [CrossRef] [Scilit]
- Lovo, S.; Harrison, L.; O’Connell, M.E.; Trask, C.; Bath, B. Experience of patients and practitioners with a team and technology approach to chronic back disorder management. J. Multidiscip. Health 2019, 12, 855–869. [Google Scholar] [CrossRef] [Scilit]
- Holmner, E.P.; Stålnacke, B.-M.; Enthoven, P.; Stenberg, G. “The acceptance” of living with chronic pain—An ongoing process: A qualitative study of patient experiences of multimodal rehabilitation in primary care. J. Rehabil. Med. 2018, 50, 73–79. [Google Scholar] [CrossRef] [Scilit]
- Stenberg, G.; Holmner, E.P.; Stålnacke, B.-M.; Enthoven, P. Healthcare professional experiences with patients who participate in multimodal pain rehabilitation in primary care—A qualitative study. Disabil. Rehabil. 2016, 38, 2085–2094. [Google Scholar] [CrossRef] [Scilit]
- Sundberg, T.; Petzold, M.; Wändell, P.; Ryden, A.; Falkenberg, T. Exploring integrative medicine for back and neck pain—A pragmatic randomised clinical pilot trial. BMC Complement. Altern. Med. 2009, 9, 33. [Google Scholar] [CrossRef] [Scilit]
- Quanjel, T.C.C.; Spreeuwenberg, M.D.; Struijs, J.N.; Baan, C.A.; Ruwaard, D. Substituting hospital-based outpatient cardiology care: The impact on quality, health and costs. PLoS ONE 2019, 14, e0217923. [Google Scholar] [CrossRef] [Scilit]
- Sibbald, B.; Pickard, S.; McLeod, H.; Reeves, D.; Mead, N.; Gemmell, I.; Coast, J.; Roland, M.; Leese, B. Moving specialist care into the community: An initial evaluation. J. Health Serv. Res. Policy 2008, 13, 233–239. [Google Scholar] [CrossRef] [Scilit]
- Nocon, A.; Rhodes, P.J.; Wright, J.P.; Eastham, J.; Williams, D.R.R.; Harrison, S.R.; Young, R.J. Specialist general practitioners and diabetes clinics in primary care: A qualitative and descriptive evaluation. Diabet. Med. 2004, 21, 32–38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Obucina, M.; Harris, N.; Fitzgerald, J.; Chai, A.; Radford, K.; Ross, A.; Carr, L.; Vecchio, N. The application of triple aim framework in the context of primary healthcare: A systematic literature review. Health Policy 2018, 122, 900–907. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kerman, N.; Kidd, S.A. The healthcare triple aim in the recovery era. Adm. Policy Ment. Health Ment. Health Serv. Res. 2020, 47, 492–496. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grant, M.; Joanne, O.; Froud, R.; Underwood, M.; Seers, K. The work of return to work. Challenges of returning to work when you have chronic pain: A meta-ethnography. Br. Med. J. Open 2019, 9, e025743. [Google Scholar] [CrossRef] [Scilit]
- Furlan, A.D.; Zhao, J.; Voth, J.; Hassan, S.; Dubin, R.; Stinson, J.N.; Jaglal, S.; Fabico, R.; Smith, A.J.; Taenzer, P.; et al. Evaluation of an innovative tele-education intervention in chronic pain management for primary care clinicians practicing in underserved areas. J. Telemed. Telecare 2019, 25, 484–492. [Google Scholar] [CrossRef] [Scilit]
- Skamagki, G.; King, A.; Duncan, M.; Wåhlin, C. A systematic review on workplace interventions to manage chronic musculoskeletal conditions. Physiother. Res. Int. 2018, 23, e1738. [Google Scholar] [CrossRef] [Scilit]
- Dubin, R.; King-VanVlack, C. The trajectory of chronic pain: Can a community-based exercise/education program soften the ride? Pain Res. Manag. 2010, 15, 361–368. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization. Integreated health services—What and why? In Technical Brief; WHO: Geneva, Switzerland, 2008. [Google Scholar]
- Hoffmann, T.C.; Glasziou, P.P.; Boutron, I.; Milne, R.; Perera, R.; Moher, D.; Altman, D.G.; Barbour, V.; Macdonald, H.; Johnston, M.; et al. Better reporting of interventions: Template for intervention description and replication (TIDieR) checklist and guide. Br. Med. J. 2014, 348, 1687. [Google Scholar] [CrossRef] [Scilit]
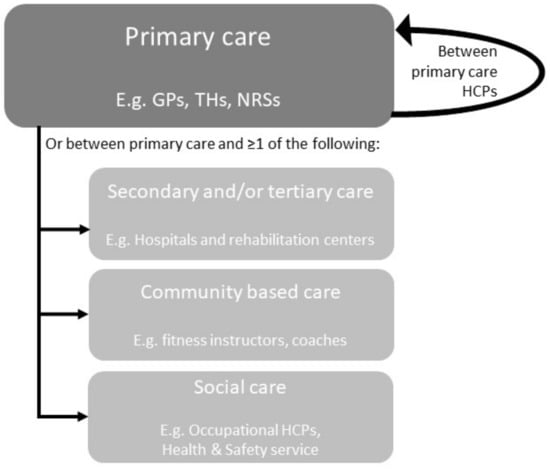
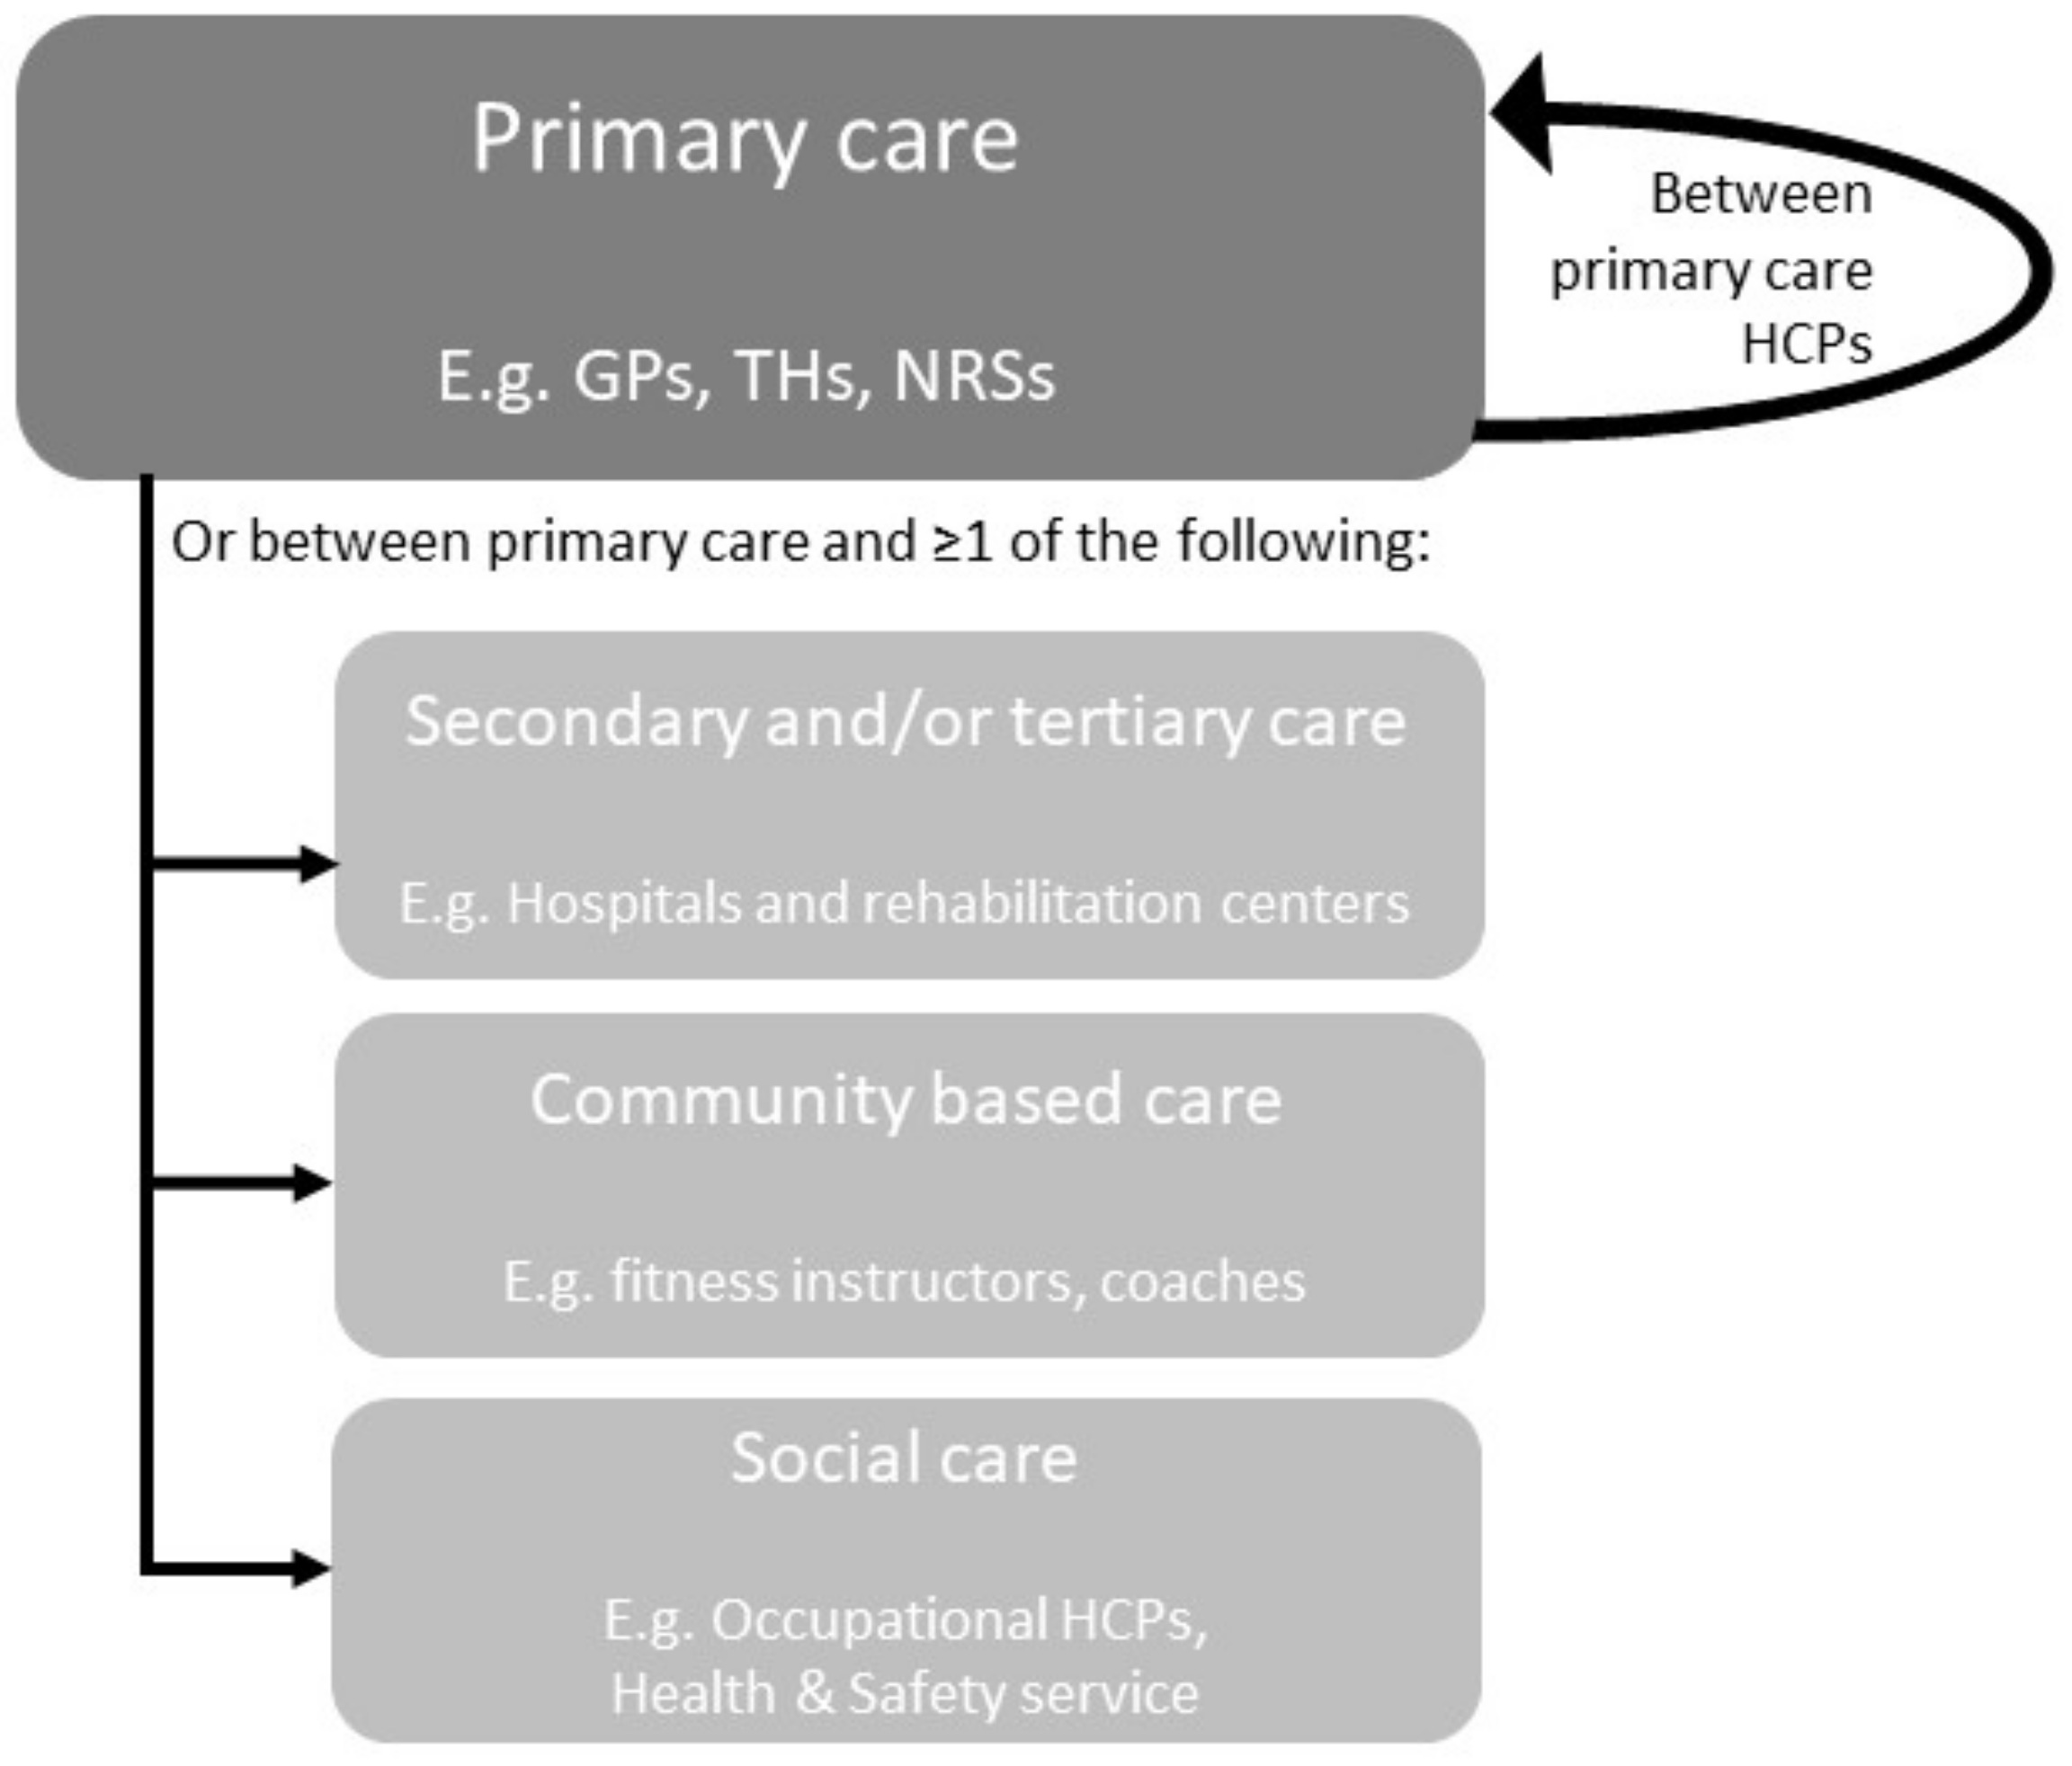
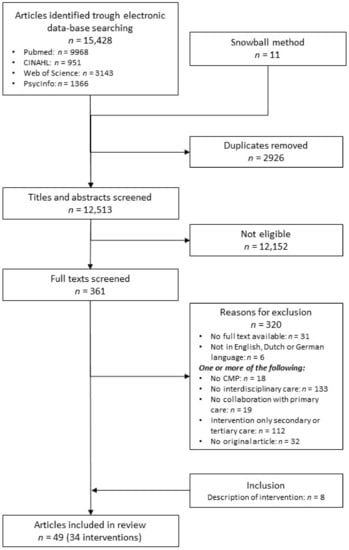
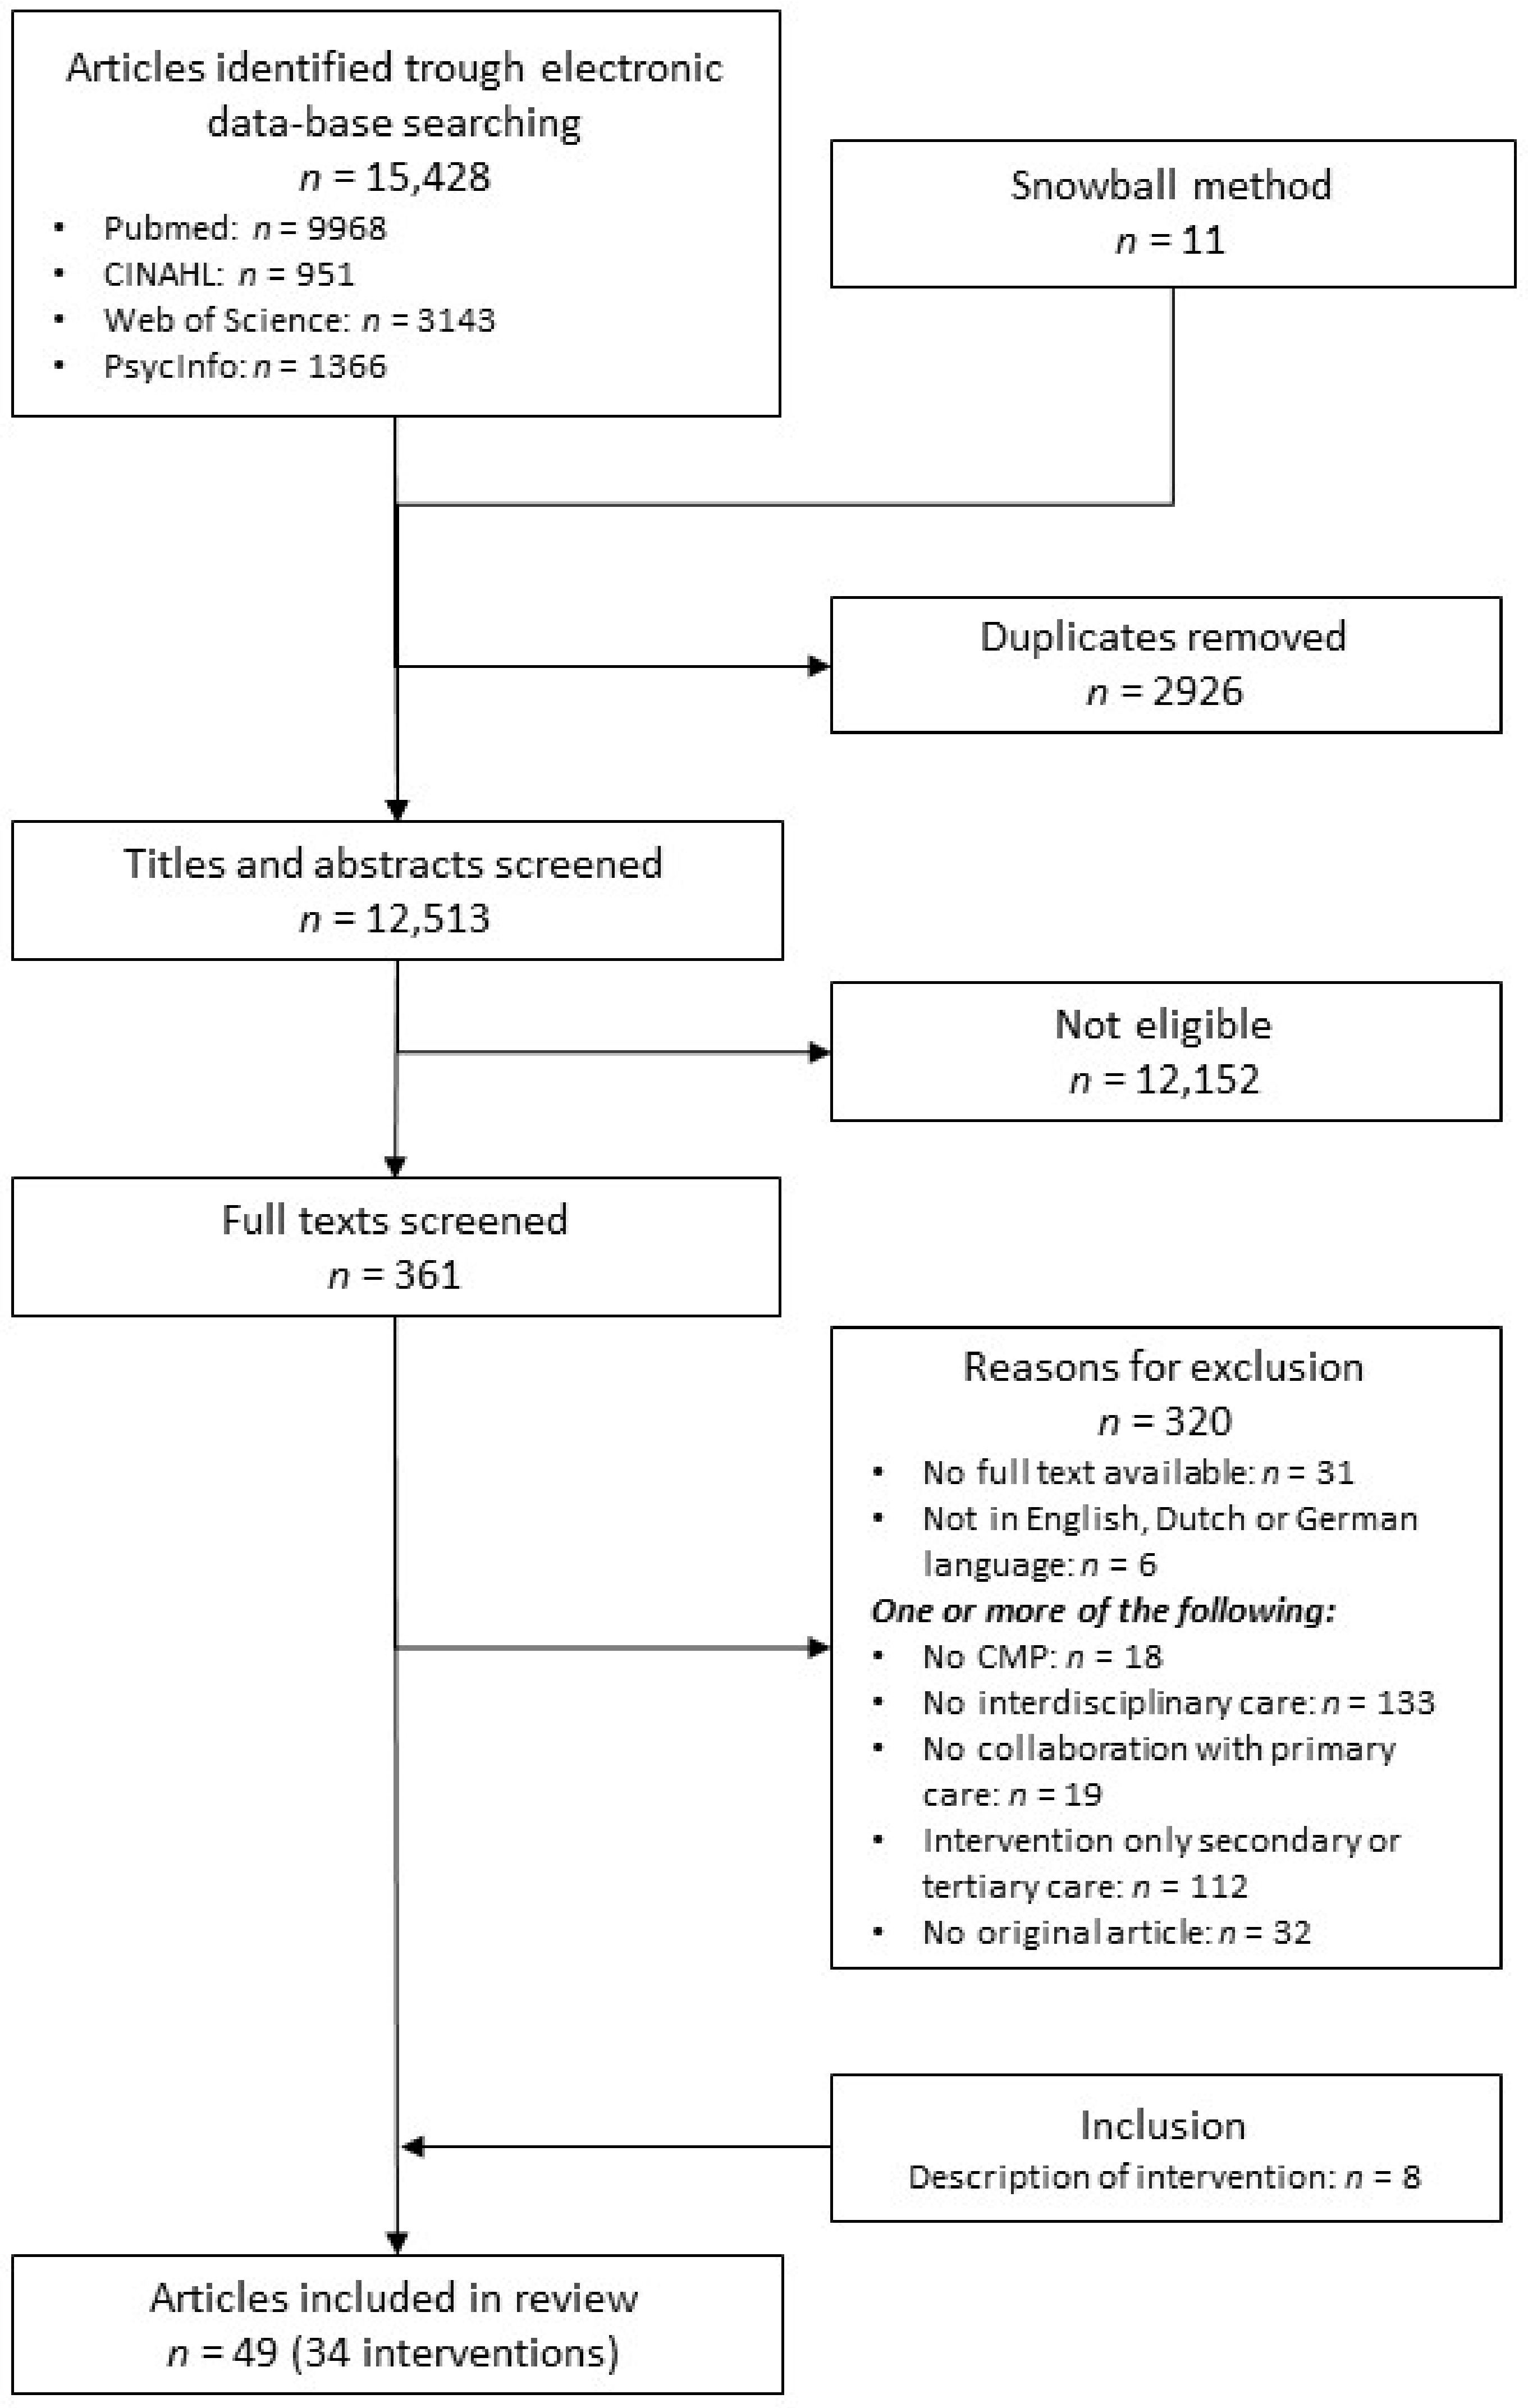
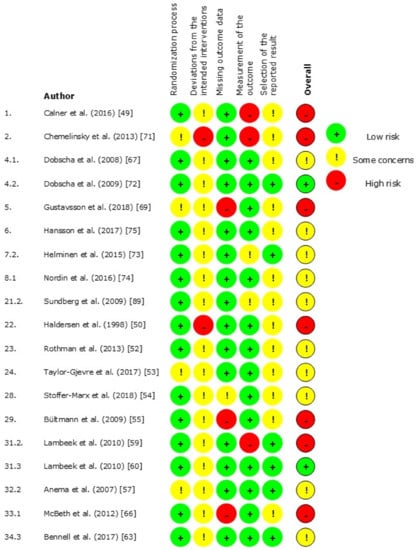
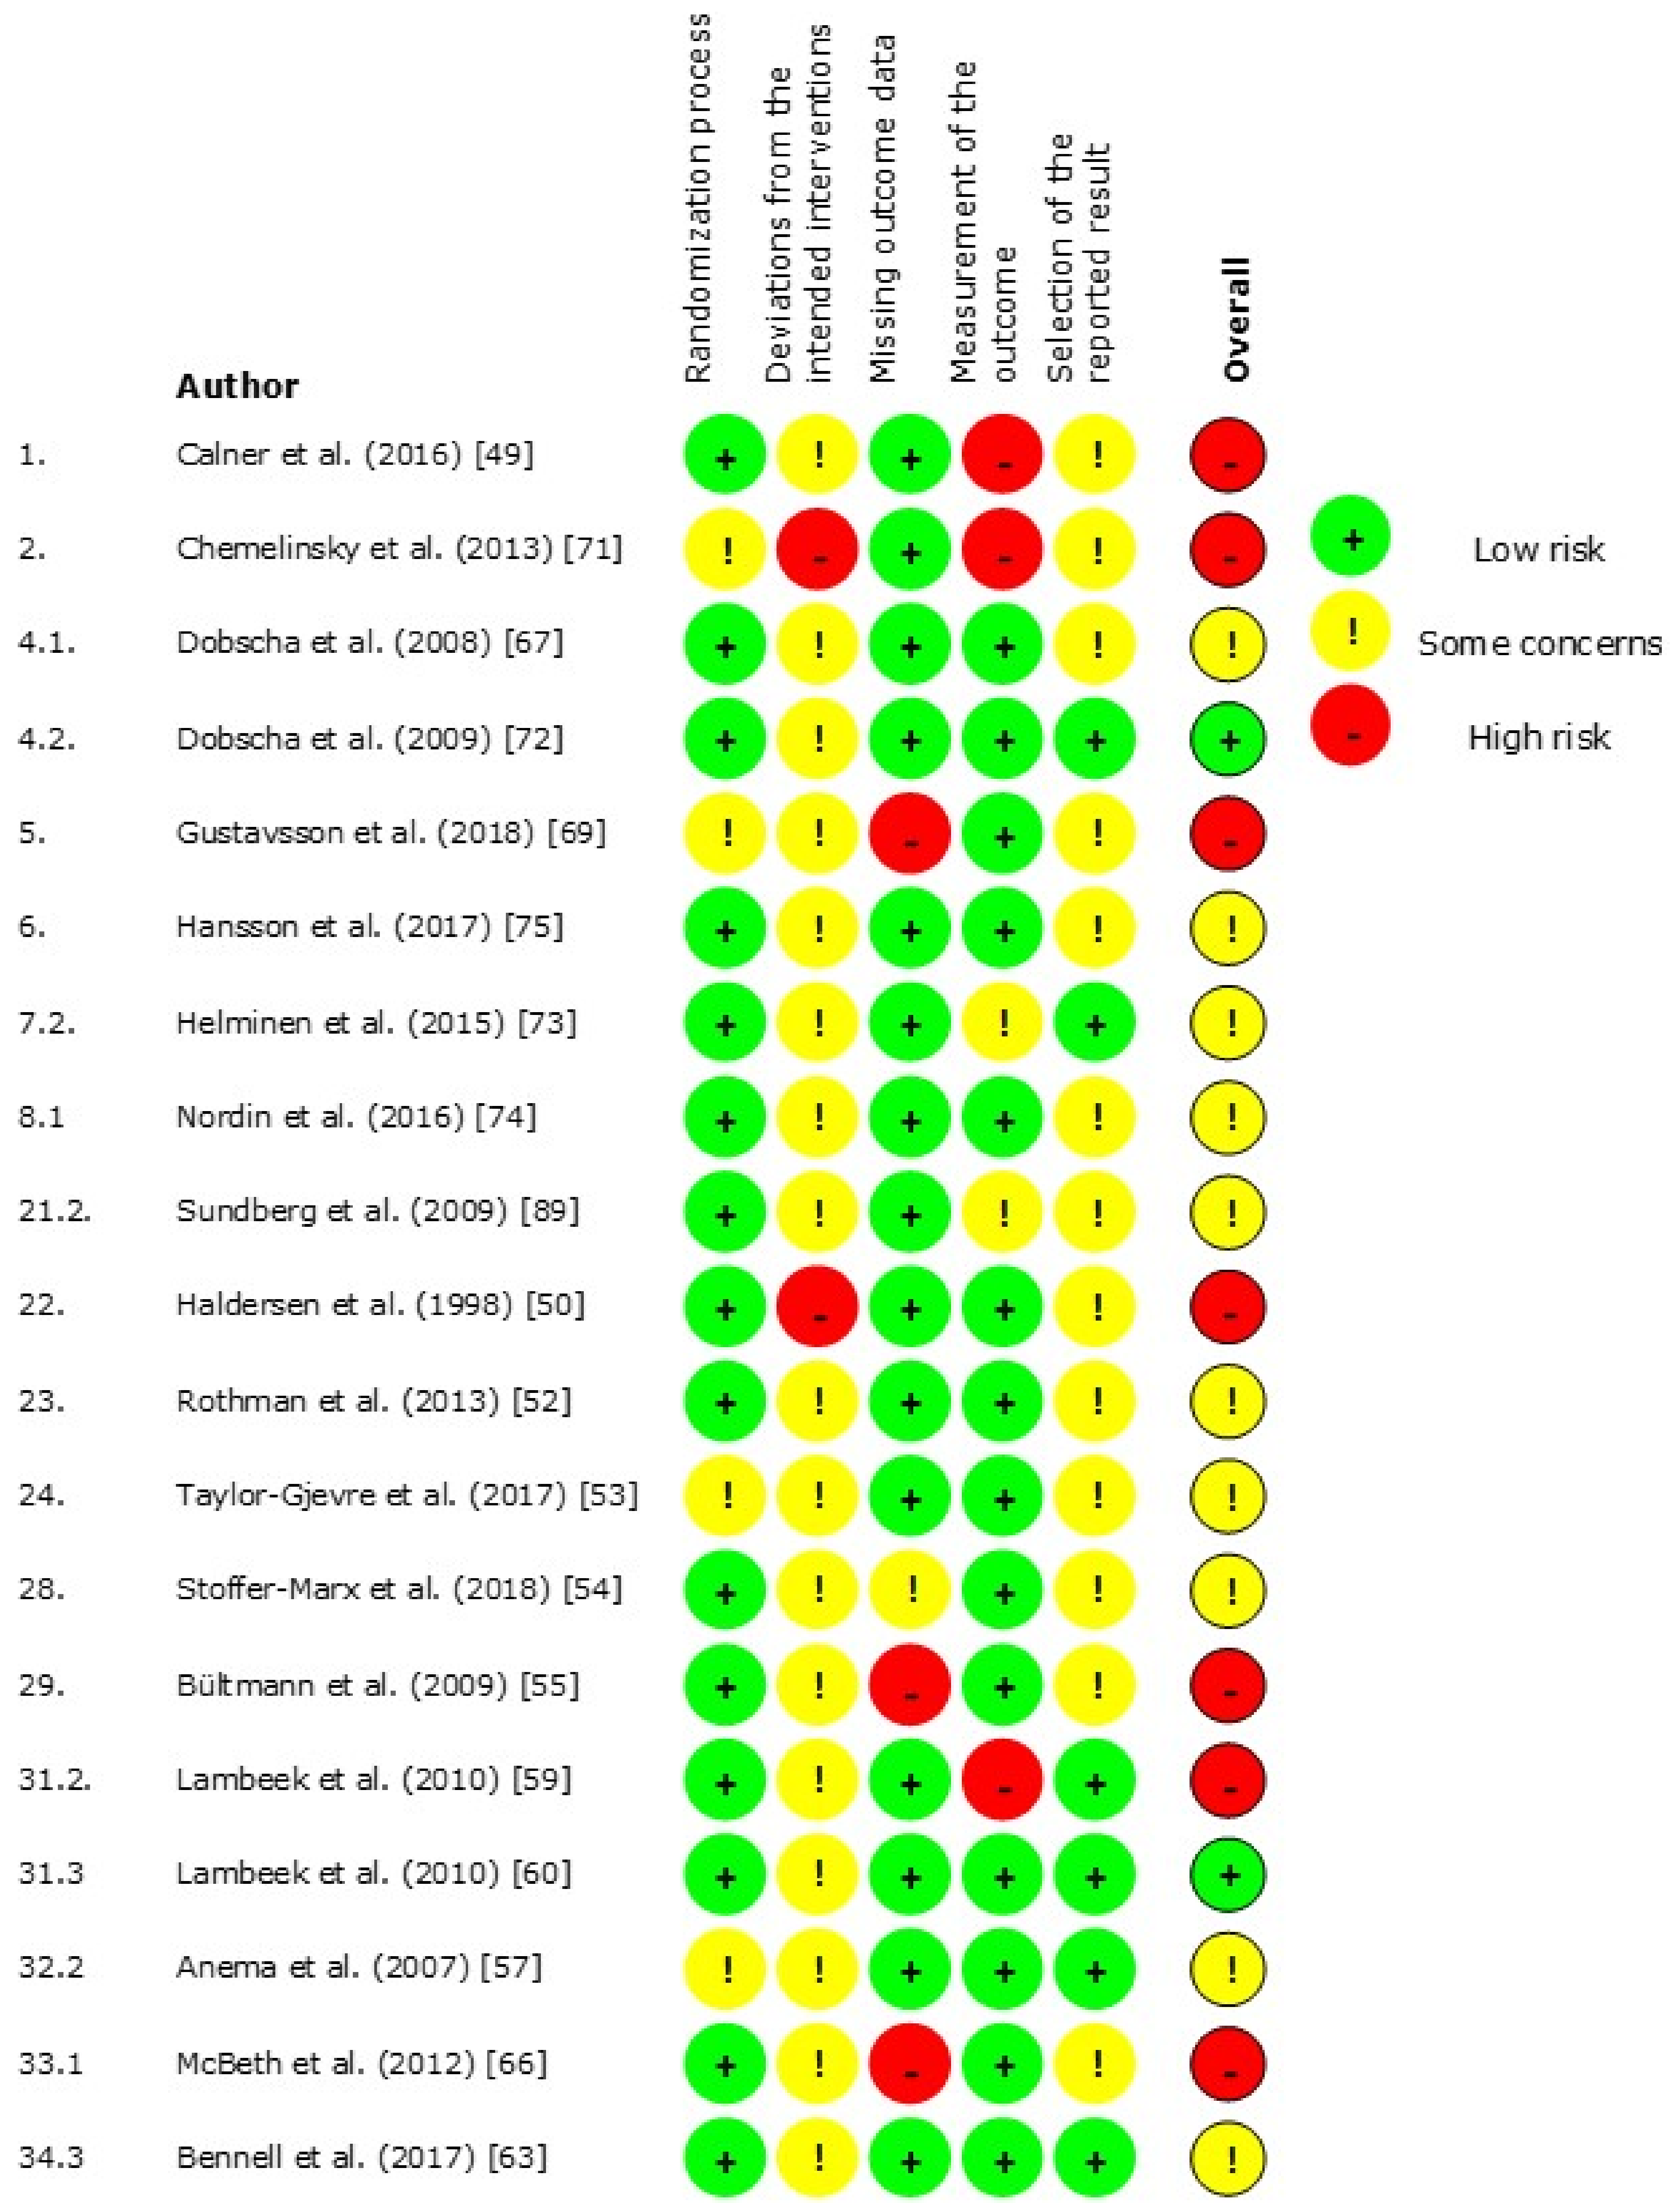
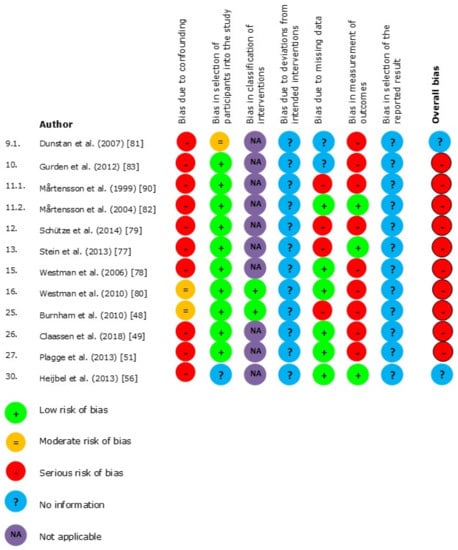
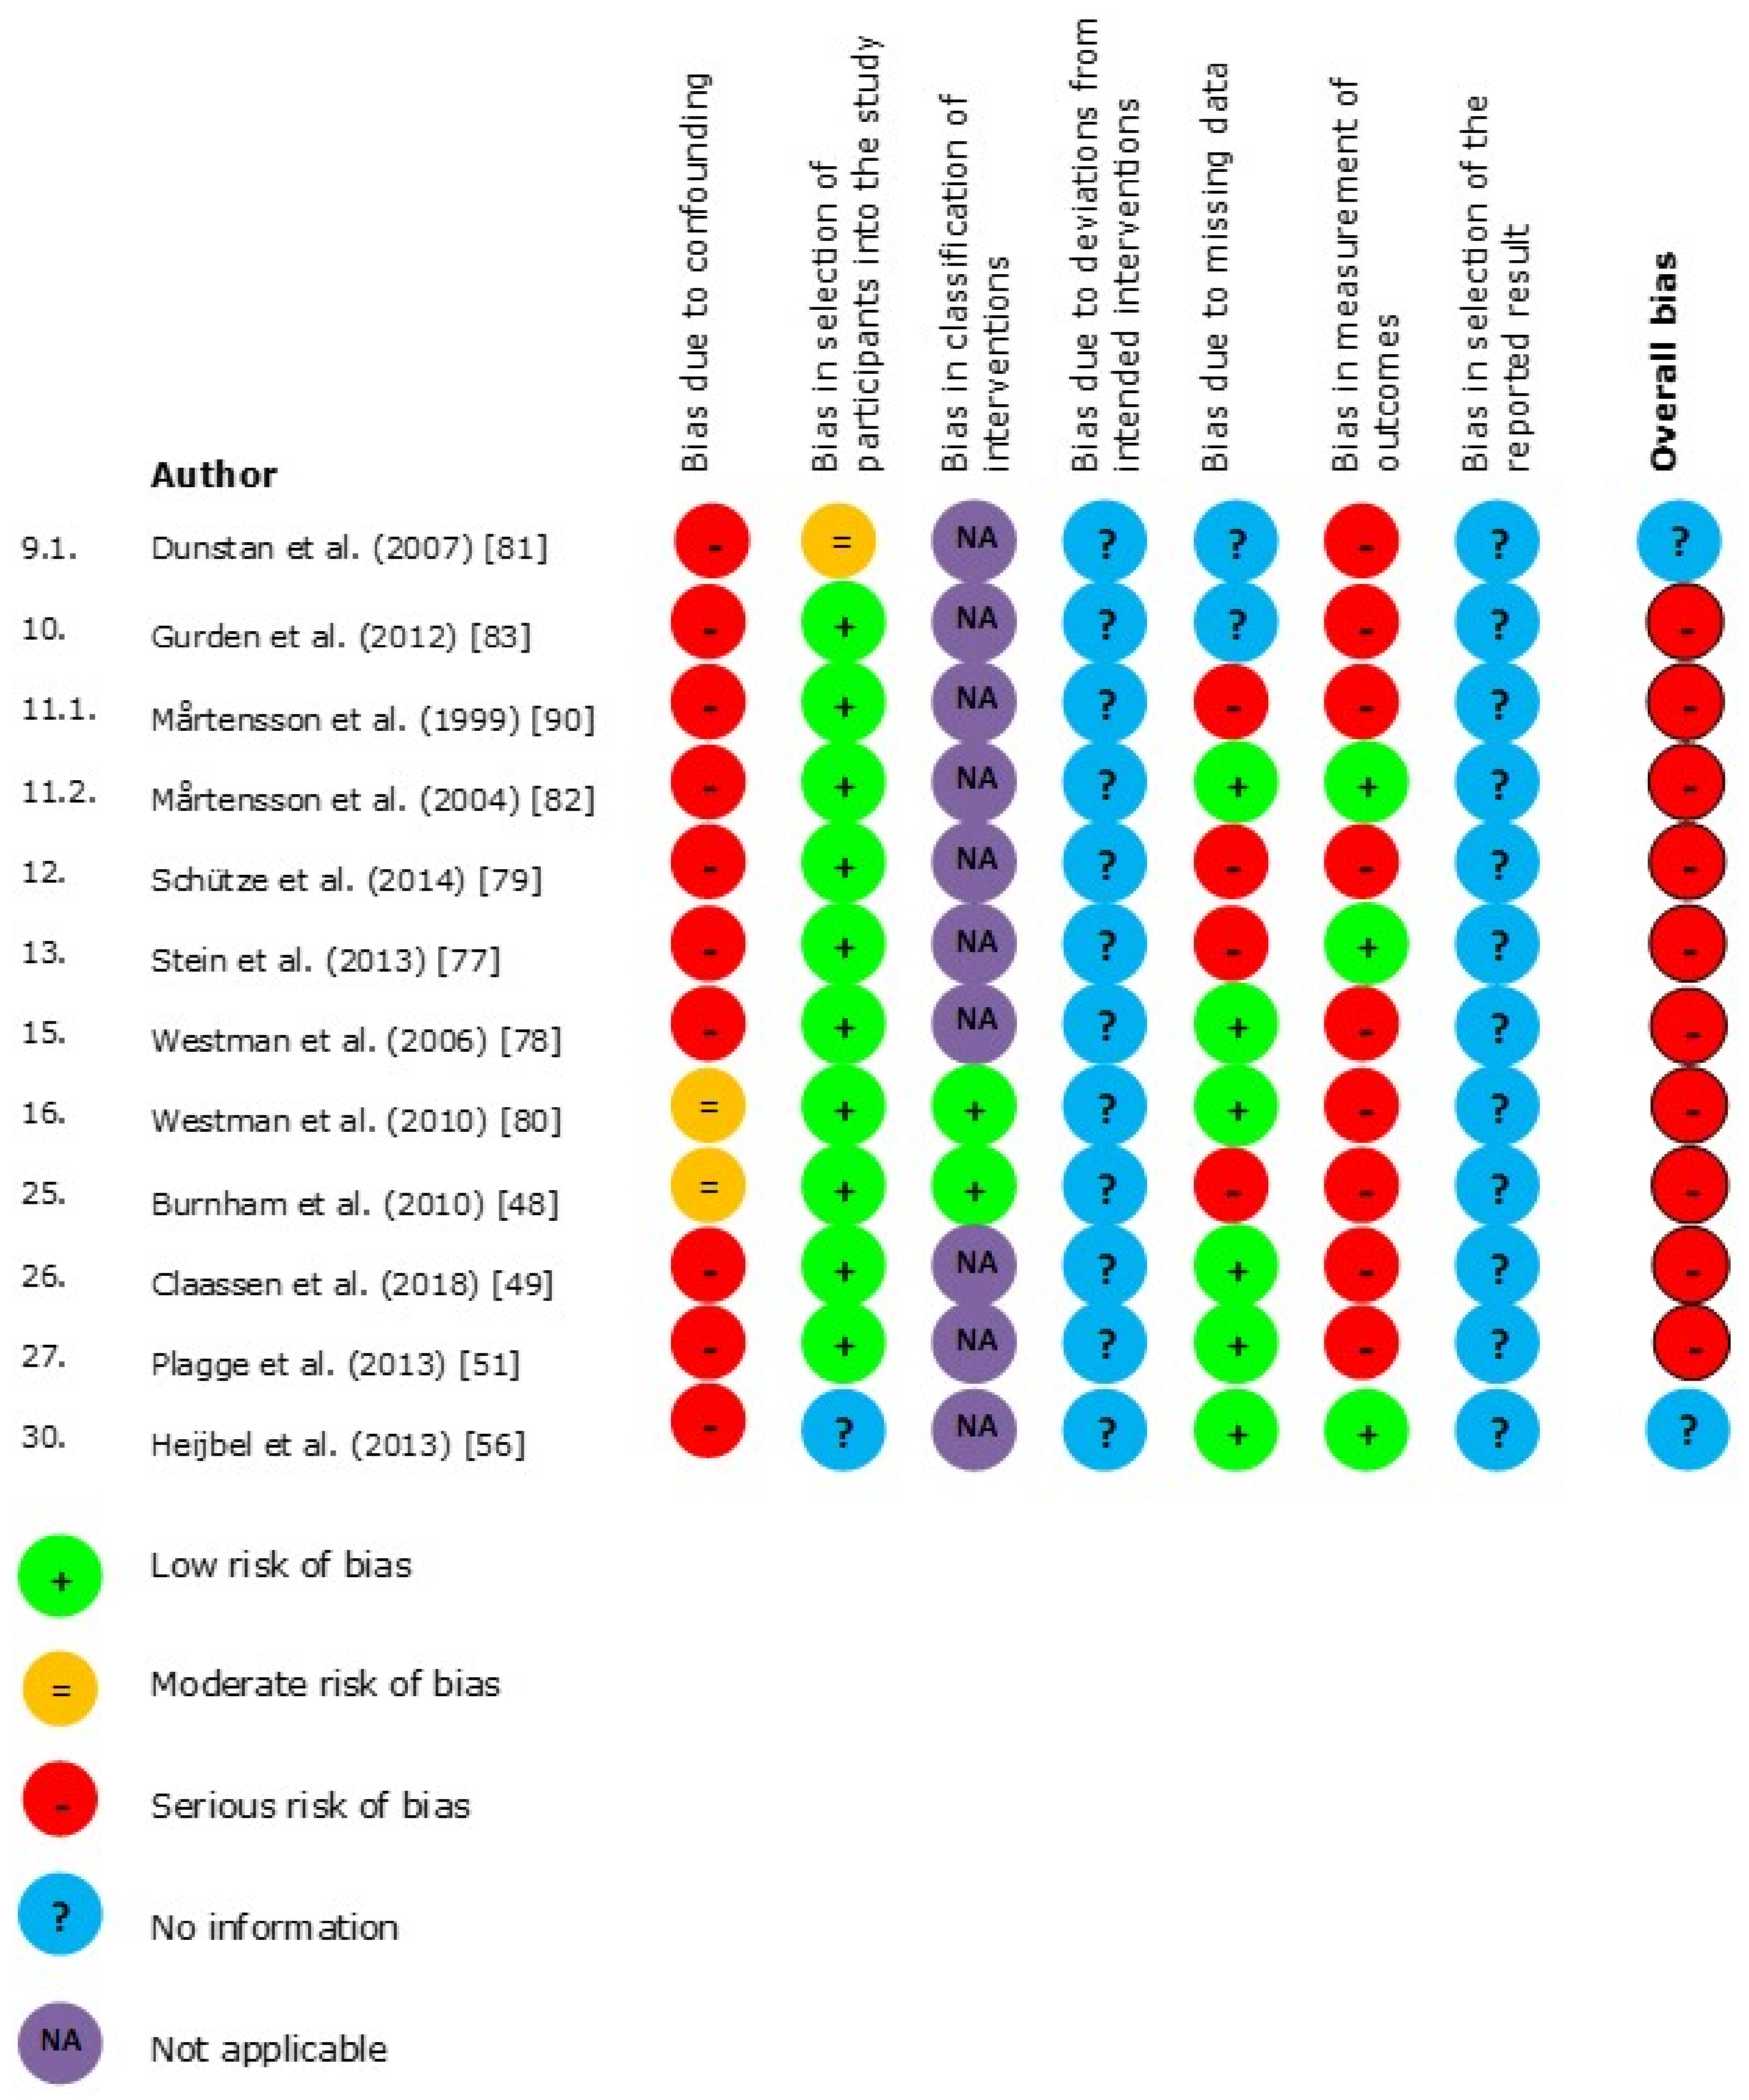
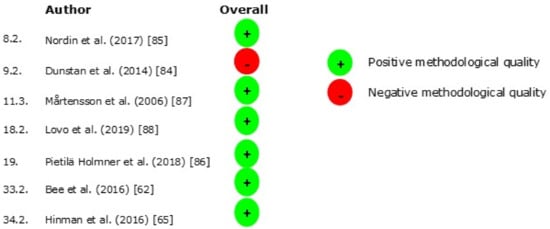
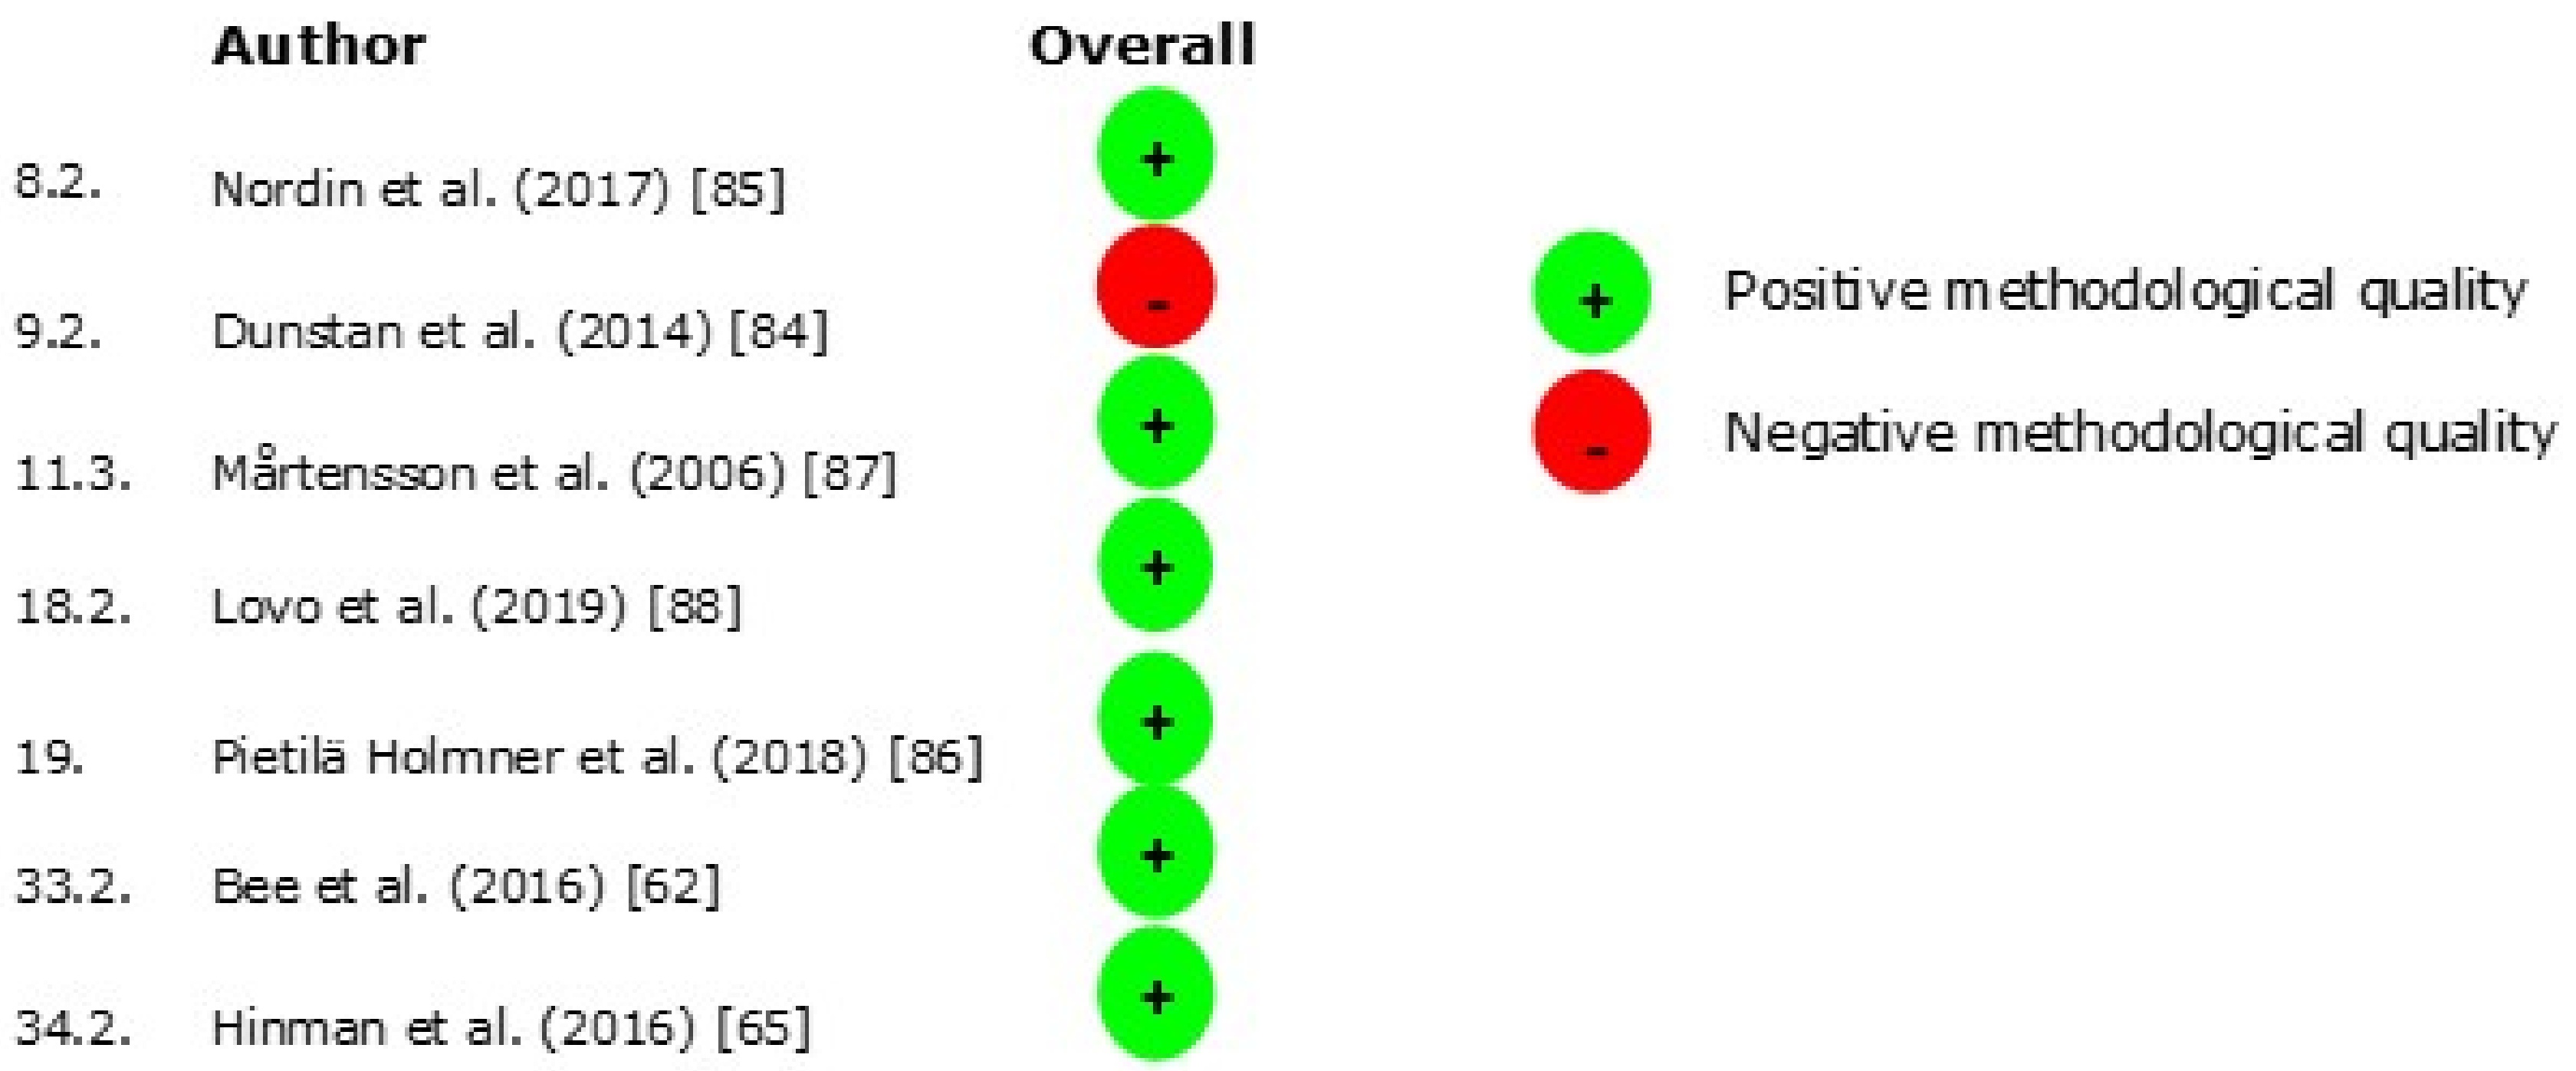

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).