


Abstract
Background: The existing recommendations for after open liver surgery, published in 2019, contains limited evidence on the use of regional analgesia techniques. The aim of this systematic review is to summarize available clinical evidence, published after September 2013, on systemic or blended postoperative analgesia for the prevention or treatment of postoperative pain after open liver surgery. Methods: The PUBMED and EMBASE registries were used for the literature search to identify suitable studies. Keywords for the literature search were selected, with the authors’ agreement, using the PICOS approach: participants, interventions, comparisons, outcomes, and study design. Results: The literature search led to the retrieval of a total of 800 studies. A total of 36 studies including 25 RCTs, 5 prospective observational, and 7 retrospective observational studies were selected as suitable for this systematic review. Conclusions: The current evidence suggests that, in these patients, optimal postoperative pain management should rely on using a “blended approach” which includes the use of systemic opioids and the infusion of NSAIDs along with regional techniques. This approach warrants the highest efficacy in terms of pain prevention, including the lower incretion of postoperative “stress hormones”, and fewer side effects. Furthermore, concerns about the potential for the increased risk of wound infection related to the use of regional techniques have been ruled out.
1. Introduction
Pain after open liver surgery can be attributed to two major mechanisms: peripheral nociceptors stimulation (induced by subcostal incision, rib retraction, diaphragmatic irritation, etc.) and visceral origin transmitted by sympathetic nerves [1,2,3]. Due to its multifactorial origin, it remains a major clinical challenge and current evidence suggests that adequate postoperative pain relief is accomplished in only 20–45% of patients undergoing major abdominal surgery [4,5,6,7,8]. Many perioperative strategies have been evaluated in this group of patients but there is still no consensus on the best practice [9,10]. Commonly used modalities for postoperative pain control are systemic intravenous analgesics, epidural analgesia, and peripheral nerve blocks [11,12]. Systemic intravenous administration of analgesics (as opioids and non-steroidal anti-inflammatory drugs) is effective but associated with potentially harmful side effects, such as respiratory depression, nausea and vomiting, pruritus, gastrointestinal bleeding, and renal failure [13,14]. Epidural analgesia might provide improved pain control, but in the specific setting of open liver surgery, may potentially challenge and have harmful drawbacks as a sympathetic blockade (with hypotension, bradycardia) and intraoperative fluid overload arises and its use might be limited because of the possible perioperative coagulopathy [13,15,16,17,18]. A peripheral nerve block, such as the paravertebral nerve block (PVB), transversus abdominis plane block (TAP), or quadratus lumborum block (QLB), performed under ultrasound guidance is an emerging alternative that could provide effective analgesia with a potentially low-risk profile after open liver surgery.
In 2015, a comprehensive review, that included fourteen studies published between November 1966 and September 2013, reported the superiority of epidural analgesia in pain relief over alternatives, but without translating into a reduction in length of hospital stay (LOS) and postoperative complication rates [19]. The existing recommendation from ESRA for Procedure-Specific Postoperative Pain Management (PROSPECT) after open liver surgery published in 2020 contains limited evidence on the use of regional analgesia techniques in this setting [20]. Since then, new relevant clinical evidence has emerged, and clinical practice is evolving accordingly.
The aim of this systematic review (SR) is to summarize the available clinical evidence, published after September 2013, on systemic or blended postoperative analgesia for the prevention or treatment of postoperative pain after open liver surgery.
2. Materials and Methods
2.1. Search Strategy
This SR was performed in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) statement recommendations, and the study was registered in the International Prospective Register Of Systematic Review (PROSPERO registration number CRD42020152836) [21,22]. Systematic research using PUBMED and EMBASE was performed to identify trials suitable for inclusion in this SR. Keywords for the literature search were selected, with the authors’ agreement, using the PICOS approach: participants, interventions, comparisons, outcomes, and study design [23]. The terms used as key words are listed in Appendix A.
2.2. Study Selection and Inclusion Criteria
The inclusion criteria were randomized controlled trials (RCTs) and prospective (POS) and retrospective (RO) studies published between October 2013 and December 2020 in the adult population (older than 18 years) on analgesia in patients who had undergone open liver surgery. Papers examining analgesia in other hepatic procedures were excluded (laparoscopic resections, liver transplant recipients, hepatic ablations, liver biopsy). Only full-text papers in the English language were considered for eligibility. Studies reporting evidence on pharmacological therapies (systemic and blended analgesia) in patients who had undergone open liver surgery that included qualitative or semiquantitative pain assessment were considered suitable for this SR.
2.3. Outcomes
The primary outcome measure of this SR is to report evidence in terms of the reduction in pain measured with patient-derived qualitative or semiquantitative scales referable to tested analgesic therapy. The secondary outcome measures are related to safety and clinical complication as recorded in selected studies: safety (the incidences of side effects of the tested analgesic modality), need of rescue analgesia, the total amount of opioid consumption, anesthesia recovery time, hemodynamic stability, vasopressor and fluid requirement, need for blood transfusion, postoperative complication rates, inflammatory and immune response, indicators of patients’ recovery, patient satisfaction, and LOS.
2.4. Data Extraction and Data Analysis
Two authors (PD, MZ) independently screened and assessed titles, abstracts, and full-text papers to identify eligible articles, with FB and PA acting as arbiters. Details of the study population, type of interventions, outcomes, and other information were extracted using a standardized data extraction form that included: study design, eligibility and exclusion criteria, duration of follow-up, randomization, blinding, number and characteristics of patients, type of surgery, and drug dose and method of administration. We reported as significant efficacy those treatments that are related to p < 0.05.
2.5. Risk of Bias
The risk of bias for all included trials was assessed according to the Cochrane Collaboration’s criteria for RCTs and non-randomized controlled trials (non-RCTs) (http://handbook.cochrane.org, accessed on 1 September 2020).
3. Results
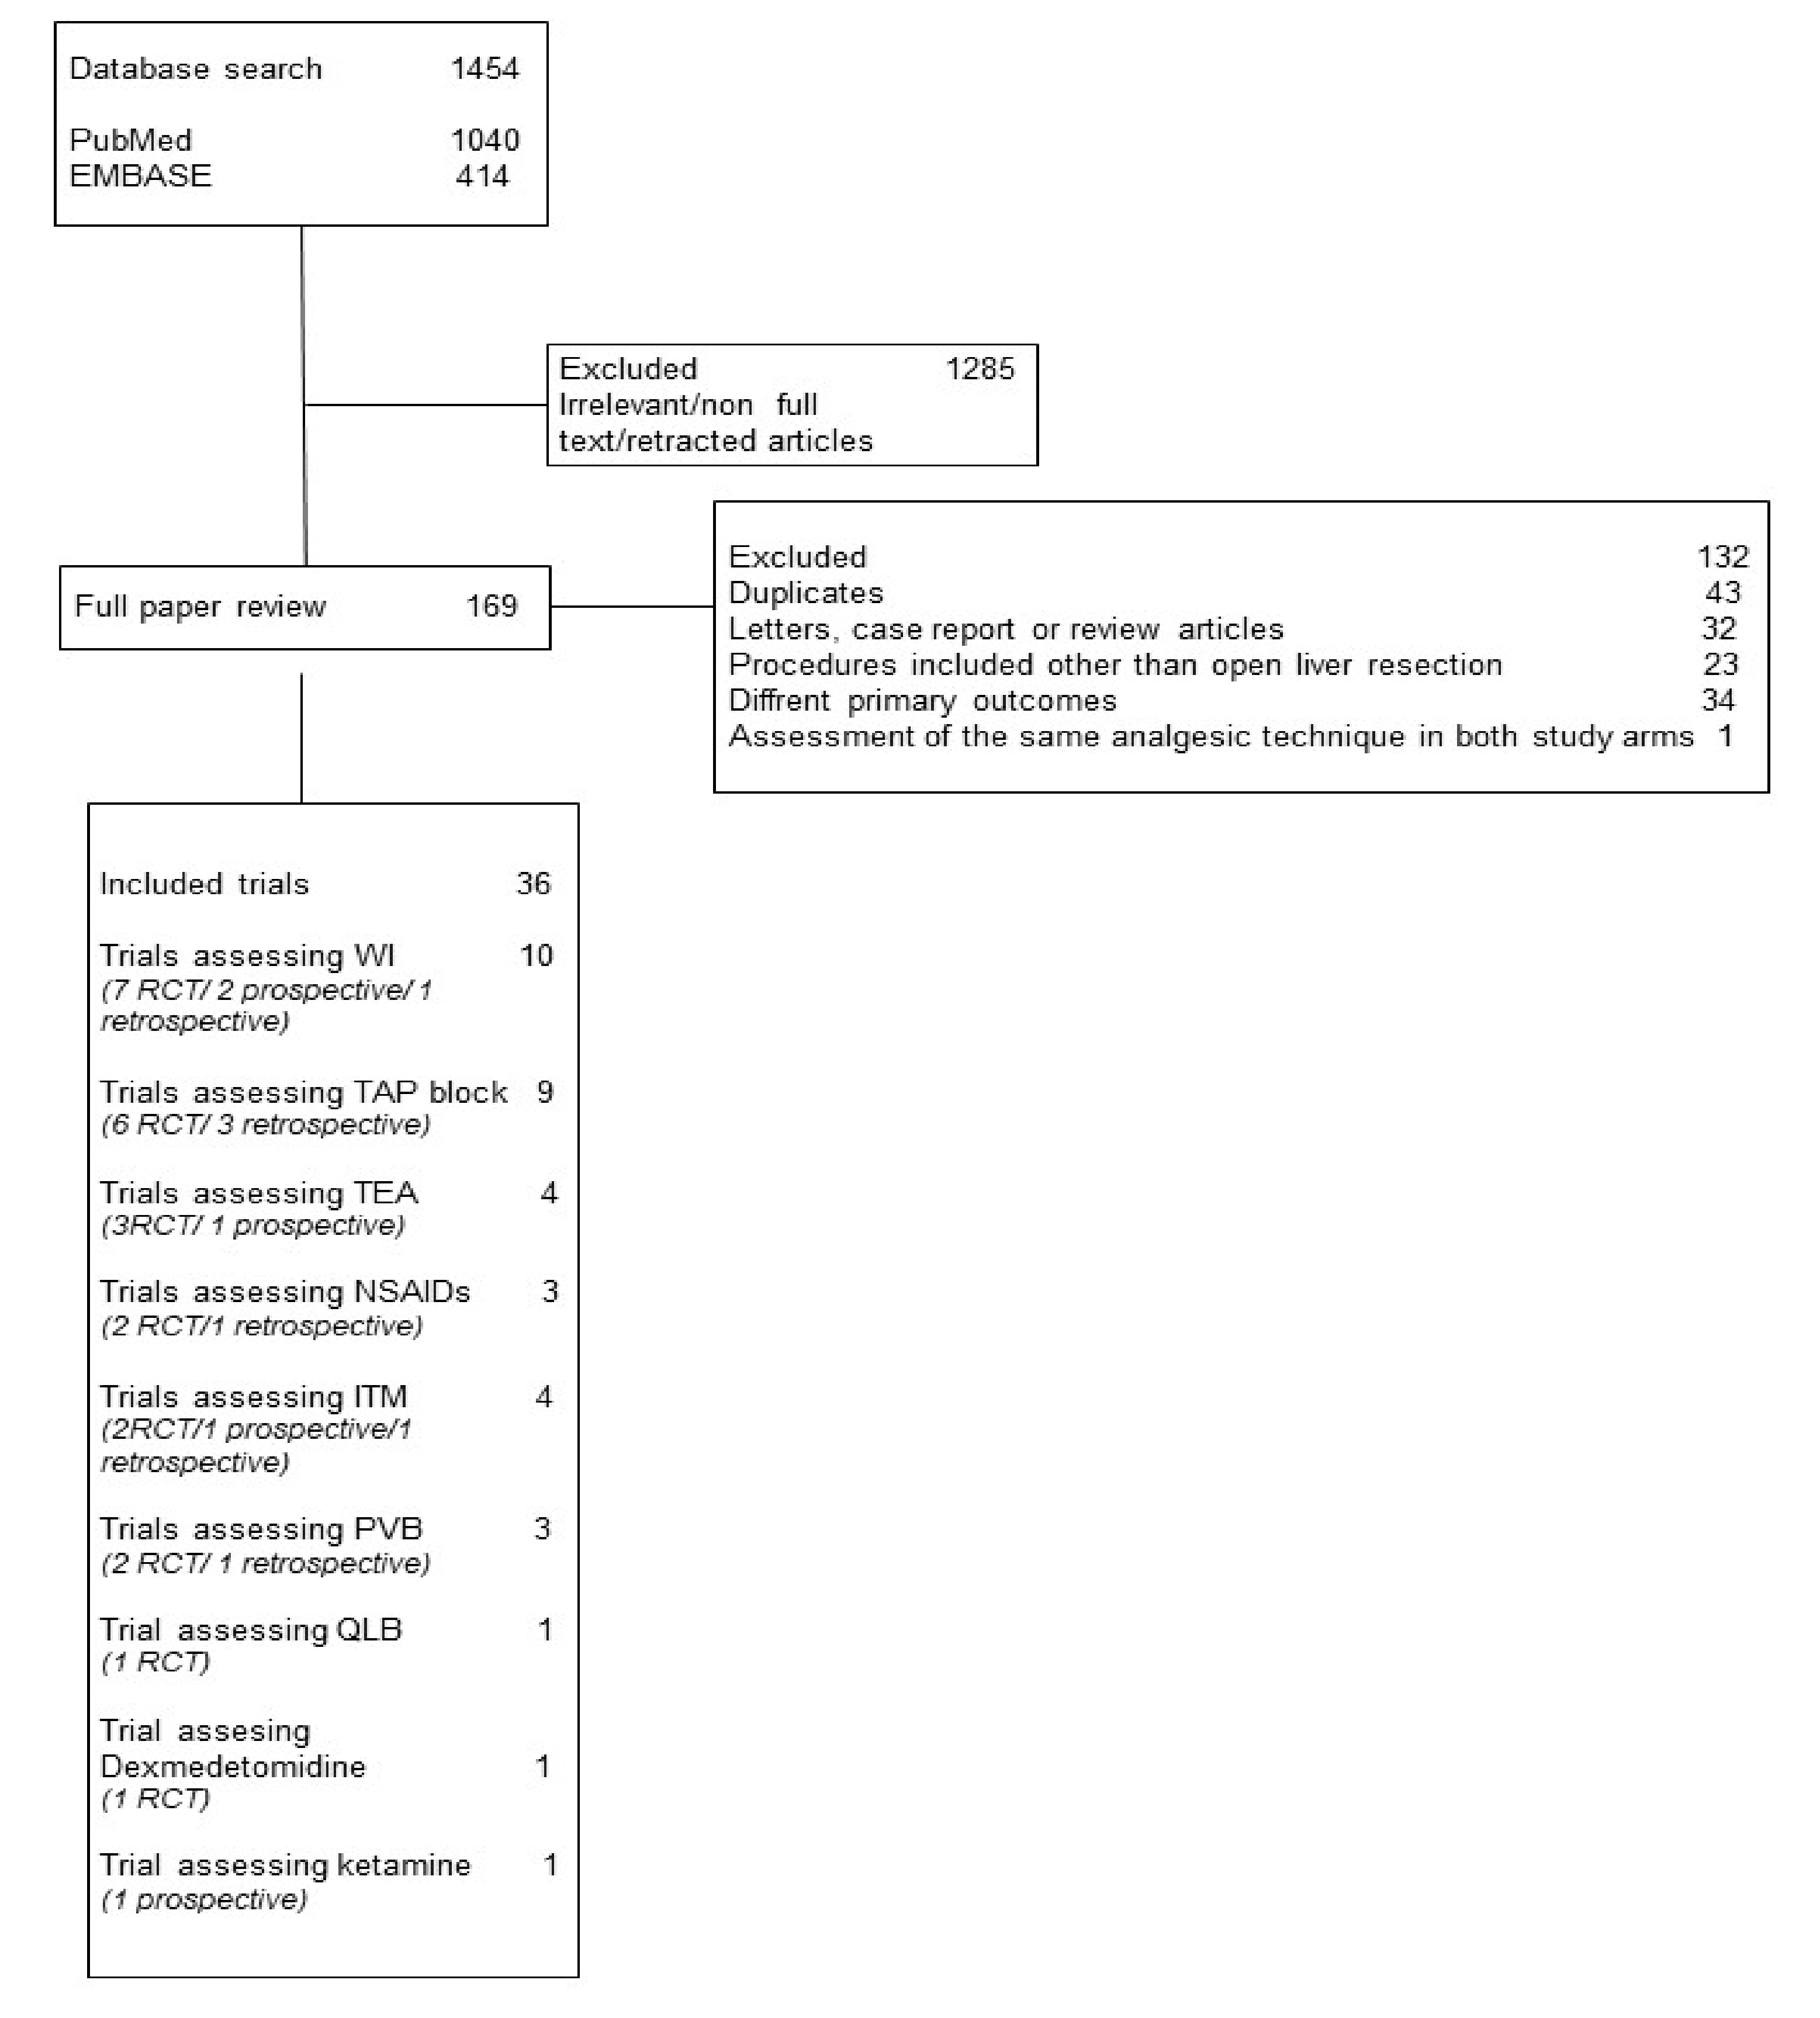
The literature search led to the retrieval of a total of 1454 studies; after the initial screening for eligibility, 1285 studies were excluded as they did not match the inclusion criteria. A total of 36 studies (involving 3560 patients, with an age range between 18 and 86) including 24 RCTs, 5 prospective observational (POS), and 7 retrospective observational (RO) studies were selected as suitable for this SR, and risk of bias was evaluated (Figure 1, Table 1 and Table 2). In 35 of the 37 studies, patients who underwent elective open liver surgery were selectively recruited, while 2 also included patients who underwent hepato-pancreato-biliary surgery; 28 studies included patients scheduled for tumor resection, and 9 studies included living donors. In the selected trials, 9 different analgesic modalities and their combinations were assessed: wound infiltration (WI), transversus abdominal plane (TAP) block, thoracic epidural analgesia (TEA), non-steroidal anti-inflammatory drugs (NSAIDs), intrathecal morphine (ITM), paravertebral block (PVB), quadratus lumborum block (QLB), dexmedetomidine, and ketamine. The evaluation of postoperative pain was assessed using various quantitative and semi-quantitative pain-rating scales and the consumption of opioid/non-opioid analgesics (Table 3). The duration of follow-up ranged from the immediate postoperative period up to 6 months after surgery. The evidence supported by the larger number of recruited patients will be displayed first.
Figure 1.
WI, wound infiltration; TAP, transversus abdominis plane; TEA, thoracic epidural analgesia; NSAIDs, nonsteroidal anti-inflammatory drugs ITM, intrathecal morphine; PVB, paravertebral block; QLB, quadratus lumborum block.
Table 1.
Risk of bias for the randomized controlled trials included.
Table 2.
Risk of bias for the non-randomized controlled trials included.
Table 3.
Summary of the studies included in this systematic review.
3.1. Trials Assessing WI
The role of WI with local anesthetics to prevent postoperative pain after open liver surgery was evaluated in ten studies, which included a total of 1412 patients: five compared to TEA (2 RCTs, 2 POS, and 1 RO), four to placebo (RCTs), and one to systemic opioids (RCT) [24,25,26,27,28,29,30,48,49,50]. When compared to TEA, the use of WI produced conflicting evidence: two studies proved WI less effective in pain control than TEA while three studies proved no difference; of the three studies that reported data on LOS, one proved WI was associate with shorter LOS compared to TEA and two recorded no differences; no differences in surgical complication after WI or TEA were reported (Table 3) [24,25,48,49,50]. When compared to the placebo, results showed WI as being more effective in preventing pain and it reduced opioid consumption, but no differences in patient satisfaction were proven; the use of WI was associated with a less systemic release of “stress hormones” (plasma concentration of epinephrine, norepinephrine, and cortisol) than the placebo; there were no differences in the side effects rates between the two treatments (Table 3) [26,27,28,29]. In a 3-arms RCT, treatment with WI resulted in better pain control and a lower side effects or serious complications rate than assignment to systemic PCA fentanyl or tramadol. Of note, patients assigned to receive tramadol had a higher mortality rate at the 25 months follow-up than those in the two other study groups (Table 3) [30].
3.2. Trials Assessing TAP Block
The efficacy of a TAP block in preventing postoperative pain after open liver surgery was tested in nine studies, which included a total of 816 patients: two compared to neuraxial analgesia (2 RO), two to placebo (2 RCTs), three to systemic opioids (2 RCTs and 1 RO), one assessed the combination with NSAID-parecoxib-(RCT) and one to WI (RCT) [31,32,33,34,35,36,51,52,53]. According to results reported in an RO that included four study groups (combination of TAP block plus neuraxial analgesia; TAP block alone; neuraxial analgesia alone; or systemic opioids), patients that received a TAP block in combination with TEA showed the lowest pain scores and required less opioid consumption; those treated with the remaining approaches resulted in progressively lower efficacy (Table 3). Of note, the use of a TAP block is associated with the shortest LOS compared to the other treatments (Table 3) [51]. Data on better pain control with a TAP block vs. intrathecal morphine is also confirmed by an RO that proved lower pain scores on day 1, but no difference on the subsequent days (Table 3) [52]. When compared to the placebo, to the use of systemic opioids or parecoxib, the use of a TAP block proved to be consistently more effective in preventing pain and reducing opioid consumption (Table 3) [31,32,33,34,35,53]. Compared to WI, the TAP block was equally effective in pain control and led to lower opioid consumption (Table 3) [36].
3.3. Trials Assessing TEA
The effectiveness of TEA in pain management after open liver surgery was evaluated in four studies, which included a total of 393 patients: three compared to systemic opioids (2 RCTs and 1 POS) and one compared to a combination of systemic opioids and WI (RCT) [37,38,39,54]. When compared to systemic opioids, the use of TEA resulted in more effective pain control and in being associated with less opioid consumption and greater patient satisfaction with pain control (Table 3) [38,39,54]. Furthermore, the association of systemic opioids with WI provided greater pain control than TEA.
3.4. Trials Assessing NSAIDs
The role of NSAIDs in preventing postoperative pain after open liver surgery was evaluated in three studies, which included a total of 186 patients: two compared to placebo (RCTs) and one compared parecoxib to ketorolac (RO) [40,45,55]. When compared to the placebo, the use of NSAIDs proved to be more effective in pain control and associated with a higher opioid-sparing effect. These studies also suggest that NSAID use is possibly associated with a more preserved immune function (by increasing CD3+ and NK cell levels), reduced systemic inflammatory response (decreased levels of IL-4 and increased TGF-β), associated with a longer tumor-free interval and disease-free survival time (Table 3) [40,45]. The use of parecoxib or ketorolac leads to similar results in terms of postoperative pain control (Table 3) [55].
3.5. Trial Assessing ITM
The efficacy of ITM in preventing postoperative pain after open liver surgery was evaluated in four studies, which included a total of 374 patients: three compared to systemic opioids (RO and 2 RCTs) and one to TEA (PO) [42,43,56,57]. When compared to systemic opioids, the use of ITM proved to be associated with lower pain, but not the reduction in complications or the side effects of analgesia rates; no differences in functional recovery time were proven (Table 3) [42,43,56]. When compared to TEA, ITM was less effective in controlling pain during the first 12 postoperative hours, but there were no observed differences afterward, and patients receiving ITM had larger intraoperative blood loss (Table 3) [57].
3.6. Trials Assessing PVB
The role of PVB in preventing postoperative pain after open liver surgery was tested in three studies, which included a total of 150 patients: one compared to TEA (RCT), one to placebo (RCT), and one to systemic opioids (RO) [41,44,58]. When compared to TEA, bilateral PVB was less effective in preventing pain; the two groups had a similar rate of side effects, associated complications, rate of ICU admission, and LOS (Table 3) [44]. When compared to the placebo, the use of the right PVB was superior for pain control and was also associated with greater patient satisfaction; there were no differences reported in side effects, associated complications, and LOS between the study groups (Table 3) [41]. When compared to systemic opioids, the use of the right PVB was associated with lower opioid consumption, but there were no differences in pain scores and there were similar rates of side effects between the two study groups (Table 3) [58].
3.7. Trial Assessing QLB
The effects of continuous QLB in preventing postoperative pain after open liver surgery was evaluated and compared to systemic opioids in 1 RCT that enrolled a total of 63 patients [46]. When compared to systemic opioids, the use of QLB resulted in more effective pain control, shorter recovery time from anesthesia, and earlier independent mobilization after surgery; no differences in the rate of side effects were recorded between the two treatment groups (Table 3).
3.8. Trial Assessing Dexmedetomidine
Adding dexmedetomidine to pain management after open liver surgery was tested in one study (RCT) and compared to a placebo in a total of 52 patients [47]. Dexmedetomidine infusion, started at anesthesia induction and continued for 48 postoperative hours, was associated with better pain control than the placebo (Table 3) [47].
3.9. Trial Assessing Ketamine
Differences in ketamine administration routes, intravenous vs. epidural, were tested to prevent pain after open liver surgery in one study (POS) which included a total of 44 patients [59]. The two tested approaches resulted in similar efficacy in controlling postoperative pain. Of note, in patients that received intravenous ketamine, there was a higher rate of cognitive side effects: hallucinations, acute confusional syndrome, and nightmares (Table 3) [59].
4. Discussion
This SR is intended to update a previous review and PROSPECT guidelines on postoperative analgesia in open liver surgery and includes studies published between September 2013 and December 2020. Current evidence suggests that, in these patients, optimal postoperative pain management should rely on using a “blended approach” that includes the use of systemic opioids and NSAID infusion along with regional techniques (WI, TAP blocks, TEA, ITM, PVB, QLB). This approach warrants the highest efficacy in terms of pain prevention, including lower incretion of postoperative “stress hormones”, and fewer side effects. Furthermore, concerns on the potential for the increased risk of wound infection related to the use of regional techniques have been ruled out.
Compared to the evidence reported in the review published by Hughes and Coll [19], there are several notable differences: it is now clear that the systemic infusion of analgesics (opioids and NSAIDs) is an essential component of postoperative analgesia and there are specific indications for the most appropriate prescription considering that opioids should be better used as PCA and NSAIDs according to a pre-scheduled, TEA and other regional approaches, WI and TAP blocks, associate with similar effectiveness. Furthermore, when compared to the PROSPECT recommendation of ESRA for pain management after open liver resection, new evidence has emerged about the efficacy of QLB, dexmedetomidine infusion, and few benefits in ITM utilization in these settings [20]. As with other subspecialty procedures, postoperative pain management should be addressed considering the specific evidence-based principles [60,61,62]. This SR now provides a detailed and comprehensive summary of specific clinical evidence targeted to postoperative analgesia in open liver surgery. Of note, it is important to consider that implementing TEA into routine clinical management is affected by the so-called “team approach” [63]. It means that when an experienced team (surgeon, anesthesiologist, perioperative nurses, pharmacists, physical and respiratory therapist) takes care of patients it improves the functional outcome.
The present SR is intended to update a previous review article and has unique methodological features. First, the current SR presented was conducted in accordance with the PRISMA guidelines as with the previous one but was also approved and recorded by the PRISMA board. Data extraction was accomplished, with a dedicated data extraction form, using a PICOS approach intended to identify specific primary and secondary end points that namely included the efficacy and safety of the tested approaches. The current primary end point was selected to report on the efficacy of the tested therapies, thus, introducing a distinct perspective when compared to the previous review that primarily reported an “overall systemic complication rate”. The previous approach led the authors to find no differences among the reported approaches, while in the present SR the benefits of a blended approach are shown, as is the superiority of the pre-scheduled administration of NSAIDs, while opioids should be better prescribed as PCA. As secondary end points, the previous review reported LOS and pain scores at 24 postoperative hours both at rest and when moving proved unbeneficial. In the present SR, safety was the main focus of the selected secondary end points, and collected evidence excluded the potential for additional risk associated with regional analgesic strategies. Studies that included patients who underwent liver transplants have been excluded from the present SR because it was selectively intended to present the clinical management of patients undergoing an elective surgical procedure.
This SR has several limitations including the methodological approach that relied on the literature search being limited to two databases (PubMed and EMBASE). Despite the potential for having missed other published studies, it is appropriate to underline that the most prestigious journals are referred to in these databases and therefore the risk of omitting major information was limited. Another possible limitation refers to the exclusion of studies that presented mixed cases of open, laparoscopic, and percutaneous procedures. This might have prevented adding details collected in some studies however enabled the selection of evidence from patients with a more homogeneous clinical background. Of note, most of the studies in each treatment section have widely different design and clinical relevance. As a result of this and other shortcomings, there are often contradicting results. We acknowledge that utilizing the GRADE approach to evaluation might have added strength to data extraction. Nevertheless, as mentioned among the study’s limitations, the limited number and heterogeneity of retrieved studies prevent reaching ultimate conclusions and the present systematic review should be considered as an updated summary of available evidence and the proposal for future studies.
In conclusion, the latest evidence on postoperative analgesia in open liver surgery provides new relevant information on the effectiveness and safety of various tested approaches and supports “blended” approaches with systemic analgesic infusion (opioids and NSAIDs) along with regional techniques. Patients undergoing open liver surgery have unique clinical problems and requirements that include: the risk for hemodynamic instability due to intraoperative vascular clamping and fluid shift, potential postoperative pulmonary complications, coagulation disturbances, and metabolic abnormalities after excessive parenchymal resection, altered drugs metabolism, etc. Blended multimodal approaches were associated with the highest effectiveness and the least side effects. The NSAIDs should be better administered on a pre-scheduled structured prescription and opioids have the highest efficacy/safety profile when administered as PCA. Continuous opioid infusion, along with scheduled NSAID administration, emerged as a possible treatment after the careful analysis of available clinical evidence in this setting. None of the referenced studies specifically tested this approach that is a part of the new information presented in this systematic review as possible future research proposals. Future studies should also be addressed to identify how postoperative analgesia can effectively contribute to shortening LOS and improving functional recovery of physical and cognitive abilities.
Author Contributions
Conceptualization, P.D. and F.B.; methodology, P.D. and M.Z.; software, M.Z.; validation, F.B., P.A. and F.P.; formal analysis, R.G.; investigation, P.D. and F.B.; resources, M.Z.; data curation, P.D.; writing—original draft preparation, P.D. and F.B.; writing—review and editing, P.D. and F.B.; visualization, M.Z.; supervision, F.B. and P.A.; project administration, F.B. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
resection* OR excision* OR surgery* OR surgery[Mesh]
AND
liver* OR liver[Mesh] OR hepatic*OR hepatectomy*
AND
epidural OR spinal OR intrathecal OR paravertebral OR erector spinae plane OR ESP OR transversus abdominis plane block OR TAP OR regional OR local OR nerve block OR wound infiltration OR wound catheter OR local infiltration OR opiate OR opioid OR systemic OR patient controlled analgesia OR PCA OR ropivacaine OR bupivacaine OR levobupivacaine OR mepivacaine OR lidocaine OR lignocaine OR xylocaine OR tetracaine OR fentanyl OR sufentanil OR remifentanil OR alfentanil
AND
pain OR analgesia OR VAS OR visual analogue scale OR postoperative pain OR pain management
References
- Carr, D.B.; Goudas, L.C. Acute pain. Lancet 1999, 353, 2051–2058. [Google Scholar] [CrossRef] [Scilit]
- Kelly, D.J.; Ahmad, M.; Brull, S.J. Preemptive analgesia I: Physiological pathways and pharmacological modalities. Can. J. Anesth. Can. d’anesthésie 2001, 48, 1000–1010. [Google Scholar] [CrossRef] [Scilit]
- Soliz, J.M.; Gebhardt, R.; Feng, L.; Dong, W.; Reich, M.; Curley, S. Comparing epidural analgesia and ON-Q infiltrating catheters for pain management after hepatic resection. Open J Anesth. 2013, 3, 3–7. [Google Scholar] [CrossRef]
- Lentschener, C.; Ozier, Y. Anaesthesia for elective liver resection: Some points should be revisited. Eur. J. Anaesthesiol. 2002, 19, 780. [Google Scholar] [CrossRef] [Scilit]
- Milan, Z.B.; Kalami, T.; Harbis, A.; Hooper, J.; Westwood, P.; Milic, N.; Bellamy, M. An audit on postoperative pain in liver resection surgery following epidural catheter removal. J. Pain Manag. 2011, 4, 381–386. [Google Scholar]
- Chou, R.; Gordon, D.B.; de Leon-Casasola, O.A.; Rosenberg, J.M.; Bickler, S.; Brennan, T.; Carter, T.; Cassidy, C.L.; Chittenden, H.; Degenhardt, E.; et al. Guidelines on the management of postoperative pain. J. Pain 2016, 17, 131–157. [Google Scholar] [CrossRef] [Scilit]
- Apfelbaum, J.L.; Chen, C.; Mehta, S.S.; Gan, T.J. Postoperative pain experience: Results from a national survey suggest postoperative pain continues to be undermanaged. Anesth. Analg. 2003, 97, 534–540. [Google Scholar] [CrossRef] [Scilit]
- Sommer, M.; De Rijke, J.M.; Van Kleef, M.; Kessels, A.G.H.; Peters, M.L.; Geurts, J.W.J.M.; Gramke, H.F.; Marcus, M.A.E. The prevalence of postoperative pain in a sample of 1490 surgical inpatients. Eur. J. Anaesthesiol. 2008, 25, 267–274. [Google Scholar] [CrossRef] [Scilit]
- Kim, B.J.; Soliz, J.M.; Aloia, T.A.; Vauthey, J.N. What is the best pain control after major hepatopancreatobiliary surgery? Adv. Surg. 2018, 52, 235–246. [Google Scholar] [CrossRef] [Scilit]
- Wrighton, L.J.; O’Bosky, K.R.; Namm, J.P.; Senthil, M. Postoperative management after hepatic resection. J. Gastrointest. Oncol. 2012, 3, 41–47. [Google Scholar] [CrossRef] [Scilit]
- Redai, I.; Emond, J.; Brentjens, T. Anesthetic considerations during liver surgery. Surg. Clin. North Am. 2004, 84, 401–411. [Google Scholar] [CrossRef] [Scilit]
- Zhou, L.; Huang, J.; Chen, C. Most effective pain-control procedure for open liver surgery: A network meta-analysis. ANZ J. Surg. 2018, 88, 1236–1242. [Google Scholar] [CrossRef] [Scilit]
- Salicath, J.H.; Yeoh, E.C.Y.; Bennett, M.H. Epidural analgesia versus patient-controlled intravenous analgesia for pain following intra-abdominal surgery in adults. Cochrane Database Syst. Rev. 2018, CD010434. [Google Scholar] [CrossRef] [Scilit]
- Sheth, K.R.; Bernthal, N.M.; Ho, H.S.; Bergese, S.D.; Apfel, C.C.; Stoicea, N.; Jahr, J.S. Perioperative bleeding and non-steroidal anti-inflammatory drugs (NSAIDs): An evidence-based literature review, and current clinical appraisal. Medicine 2020, 99, e20042. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, J.; Pourrahmat, M.M.; Vasilyeva, E.; Kim, P.T.W.; Osborn, J.; Wiseman, S.M. Efficacy and safety of patient-controlled analgesia compared with epidural analgesia after open hepatic resection: A systematic review and meta-analysis. Ann. Surg. 2019, 270, 200–208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weinberg, L.; Scurrah, N.; Gunning, K.; McNicol, L. Postoperative changes in prothrombin time following hepatic resection: Implications for perioperative analgesia. Anaesth. Intensive Care 2006, 34, 438–443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jacquenod, P.; Wallon, G.; Gazon, M.; Darnis, B.; Pradat, P.; Virlogeux, V.; Farges, O.; Aubrun, F. Incidence and risk factors of coagulation profile derangement after liver surgery: Implications for the use of epidural analgesia—A retrospective cohort study. Anesth. Analg. 2018, 126, 1142–1147. [Google Scholar] [CrossRef] [Scilit]
- Shontz, R.; Karuparthy, V.; Temple, R.; Brennan, T.J. Prevalence and risk factors predisposing to coagulopathy in patients receiving epidural analgesia for hepatic surgery. Reg. Anesth. Pain Med. 2009, 34, 308–311. [Google Scholar] [CrossRef] [Scilit]
- Hughes, M.; McNally, S.; McKeown, D.W.; Wigmore, S. Effect of analgesic modality on outcome following open liver surgery: A systematic review of postoperative analgesia. Minerva Anestesiol. 2015, 81, 541–556. [Google Scholar]
- Dieu, A.; Huynen, P.; Lavand’homme, P.; Beloeil, H.; Freys, S.M.; Pogatzki-Zahn, E.M.; Joshi, G.P.; Van de Velde, M. Pain management after open liver resection: Procedure-specific postoperative pain management (PROSPECT) recommendations. Reg. Anesth. Pain Med. 2021, 46, 433–445. [Google Scholar] [CrossRef] [Scilit]
- Moher, D.; Liberati, A.; Tetzlaff, J.; Altman, D.G.; Altman, D.; Antes, G.; Atkins, D.; Barbour, V.; Barrowman, N.; Berlin, J.A.; et al. Preferred reporting items for systematic reviews and meta-analyses: The PRISMA statement. PLoS Med. 2009, 6, e1000097. [Google Scholar] [CrossRef] [Scilit]
- Liberati, A.; Altman, D.G.; Tetzlaff, J.; Mulrow, C.; Gøtzsche, P.C.; Ioannidis, J.P.A.; Clarke, M.; Devereaux, P.J.; Kleijnen, J.; Moher, D. The PRISMA statement for reporting systematic reviews and meta-analyses of studies that evaluate healthcare interventions: Explanation and elaboration. BMJ 2009, 339, b2700. [Google Scholar] [CrossRef] [Scilit]
- Schardt, C.; Adams, M.B.; Owens, T.; Keitz, S.; Fontelo, P. Utilization of the PICO framework to improve searching PubMed for clinical questions. BMC Med. Inform. Decis. Mak. 2007, 7, 1–6. [Google Scholar] [CrossRef] [Scilit]
- Hughes, M.J.; Harrison, E.M.; Peel, N.J.; Stutchfield, B.; McNally, S.; Beattie, C.; Wigmore, S.J. Randomized clinical trial of perioperative nerve block and continuous local anaesthetic infiltration via wound catheter versus epidural analgesia in open liver resection (LIVER 2 trial). Br. J. Surg. 2015, 102, 1619–1628. [Google Scholar] [CrossRef] [Scilit]
- Bell, R.; Ward, D.; Jeffery, J.; Toogood, G.J.; Lodge, J.A.; Rao, K.; Lotia, S.; Hidalgo, E. A randomized controlled trial comparing epidural analgesia versus continuous local anesthetic infiltration via abdominal wound catheter in open liver resection. Ann. Surg. 2019, 269, 413–419. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dalmau, A.; Fustran, N.; Camprubi, I.; Sanzol, R.; Redondo, S.; Ramos, E.; Torras, J.; Sabaté, A. Analgesia with continuous wound infusion of local anesthetic versus saline: Double-blind randomized, controlled trial in hepatectomy. Am. J. Surg. 2018, 215, 138–143. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peres-Bachelot, V.; Blanc, E.; Oussaid, N.; Pérol, D.; Daunizeau-Walker, A.L.; Pouderoux, S.; Peyrat, P.; Rivoire, M.; Dupré, A. A 96-hour continuous wound infiltration with ropivacaine reduces analgesic consumption after liver resection: A randomized, double-blind, controlled trial. J. Surg. Oncol. 2019, 119, 47–55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, J.-X.; Bai, K.-Y.; Liu, Y.-F.; Du, G.; Fu, Z.-H.; Zhang, H.; Yang, J.-H.; Wang, B.; Wang, X.-Y.; Jin, B. Effect of local wound infiltration with ropivacaine on postoperative pain relief and stress response reduction after open hepatectomy. World J. Gastroenterol. 2017, 23, 6733–6740. [Google Scholar] [CrossRef] [Scilit]
- Xin, Y.; Hong, Y.; Yong, L.Z. Efficacy of postoperative continuous wound infiltration with local anesthesia after open hepatectomy. Clin. J. Pain 2014, 30, 571–576. [Google Scholar] [CrossRef] [Scilit]
- Wu, Y.F.; Li, X.P.; Yu, Y.B.; Chen, L.; Jiang, C.B.; Li, D.Y.; Chen, M.L. Postoperative local incision analgesia for acute pain treatment in patients with hepatocellular carcinoma. Rev. Assoc. Med. Bras. 2018, 64, 175–180. [Google Scholar] [CrossRef] [Scilit]
- Karanicolas, P.J.; Cleary, S.; McHardy, P.; Kiss, A.; Sawyer, J.; Behman, R.; Ladak, S.; McCluskey, S.A.; Srinivas, C.; Katz, J.; et al. Medial open transversus abdominis plane (MOTAP) catheters reduce opioid requirements and improve pain control following open liver resection: A multicenter, blinded, randomized controlled trial. Ann. Surg. 2018, 268, 233–240. [Google Scholar] [CrossRef] [Scilit]
- Guo, J.-G.; Li, H.-L.; Pei, Q.-Q.; Feng, Z.-Y. The analgesic efficacy of subcostal transversus abdominis plane block with Mercedes incision. BMC Anesthesiol. 2018, 18, 36. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kıtlık, A.; Erdogan, M.A.; Ozgul, U.; Aydogan, M.S.; Ucar, M.; Toprak, H.I.; Colak, C.; Durmus, M. Ultrasound-guided transversus abdominis plane block for postoperative analgesia in living liver donors: A prospective, randomized, double-blinded clinical trial. J. Clin. Anesth. 2017, 37, 103–107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Erdogan, C.; Uzgul, U.; Uçar, M.; Yalin, R.; Colak, Y.Z.; Çolak, C.; Toprak, H.I. Effect of transversus abdominis plane block in combination with general anesthesia on perioperative opioid consumption, hemodynamics, and recovery in living liver donors: The prospective, double-blinded, randomized study. Clin. Transplant. 2017, 31, e12931. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qiao, X.-F.F.; Jia, W.-D.D.; Li, Y.-Q.Q.; Lv, J.-G.G.; Zhou, H. Effectiveness of Parecoxib Sodium Combined with Transversus Abdominis Plane Block for Pain Management After Hepatectomy for Hepatocellular Carcinoma: A Prospective Controlled Study. Med. Sci. Monit. 2019, 25, 1053–1060. [Google Scholar] [CrossRef] [Scilit]
- Su, W.; Deng, X.; Li, X.; Deng, J.; Li, P.; Yang, M. Effect of the transversus abdominis plane block on postoperative pain and recovery in patients with hepatic echinococcosis. J. Int. Med. Res. 2018, 46, 3563–3569. [Google Scholar] [CrossRef] [Scilit]
- Hausken, J.; Fretland, Å.A.; Edwin, B.; Andersen, M.H.; Dagenborg, V.J.; Bjørnelv, G.M.W.; Kristiansen, R.; Røysland, K.; Kvarstein, G.; Tønnessen, T.I. Intravenous patient-controlled analgesia versus thoracic epidural analgesia after open liver surgery: A prospective, randomized, controlled, noninferiority trial. Ann. Surg. 2019, 270, 193–199. [Google Scholar] [CrossRef] [Scilit]
- Aloia, T.A.; Kim, B.J.; Segraves-Chun, Y.S.; Cata, J.P.; Truty, M.J.; Shi, Q.; Holmes, A.; Soliz, J.M.; Popat, K.U.; Rahlfs, T.F.; et al. A Randomized Controlled Trial of Postoperative Thoracic Epidural Analgesia Versus Intravenous Patient-controlled Analgesia after Major Hepatopancreatobiliary Surgery. Ann. Surg. 2017, 266, 545–554. [Google Scholar] [CrossRef] [Scilit]
- Aydogan, M.S.; Biçakcioʇlu, M.; Sayan, H.; Durmus, M.; Yilmaz, S.; Bıçakcıoglu, M.; Sayan, H.; Durmus, M. Effects of two different techniques of postoperative analgesia management in liver transplant donors: A prospective, randomized, double-blind study. Transplant. Proc. 2015, 47, 1204–1206. [Google Scholar] [CrossRef] [Scilit]
- Wang, R.D.; Zhu, J.-Y.; Zhu, Y.; Ge, Y.-S.; Xu, G.-L.; Jia, W.-D. Perioperative analgesia with parecoxib sodium improves postoperative pain and immune function in patients undergoing hepatectomy for hepatocellular carcinoma. J. Eval. Clin. Pract. 2020, 26, 992–1000. [Google Scholar] [CrossRef] [Scilit]
- Chen, H.; Liao, Z.; Fang, Y.; Niu, B.; Chen, A.; Cao, F.; Mei, W.; Tian, Y. Continuous right thoracic paravertebral block following bolus initiation reduced postoperative pain after right-lobe hepatectomy: A randomized, double-blind, placebo-controlled trial. Reg. Anesth. Pain Med. 2014, 39, 506–512. [Google Scholar] [CrossRef] [Scilit]
- Dichtwald, S.; Ben-Haim, M.; Papismedov, L.; Hazan, S.; Cattan, A.; Matot, I. Intrathecal morphine versus intravenous opioid administration to impact postoperative analgesia in hepato-pancreatic surgery: A randomized controlled trial. J. Anesth. 2017, 31, 237–245. [Google Scholar] [CrossRef] [Scilit]
- Niewiński, G.; Figiel, W.; Grąt, M.; Dec, M.; Morawski, M.; Patkowski, W.; Zieniewicz, K. A comparison of intrathecal and intravenous morphine for analgesia after hepatectomy: A randomized controlled trial. World J. Surg. 2020, 44, 2340–2349. [Google Scholar] [CrossRef] [Scilit]
- Schreiber, K.L.; Chelly, J.E.; Scott Lang, R.; Abuelkasem, E.; Geller, D.A.; Wallis Marsh, J.; Tsung, A.; Sakai, T. Epidural versus paravertebral nerve block for postoperative analgesia in patients undergoing open liver resection a randomized clinical trial. Reg. Anesth. Pain Med. 2016, 41, 460–468. [Google Scholar] [CrossRef] [Scilit]
- Chen, M.-T.T.; Jin, B.; Da Du, S.-D.; Pei, L.-J.J.; Zhu, B.; Yan, L.; Chi, T.-Y.Y.; Xu, H.-F.F.; Zheng, Y.-C.C.; Xu, Y.-Y.Y.; et al. Role of a selective cyclooxygenase-2 inhibitor on pain and enhanced recovery after open hepatectomy: A randomized controlled trial. Transl. Cancer Res. 2017, 6, 806–814. [Google Scholar] [CrossRef] [Scilit]
- Zhu, Q.; Li, L.; Yang, Z.; Shen, J.; Zhu, R.; Wen, Y.; Cai, W.; Liu, L. Ultrasound guided continuous quadratus lumborum block hastened recovery in patients undergoing open liver resection: A randomized controlled, open-label trial. BMC Anesthesiol. 2019, 19, 1–9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, B.; Wang, G.; Liu, X.; Wang, T.L.; Chi, P. The opioid-sparing effect of perioperative dexmedetomidine combined with oxycodone infusion during open hepatectomy: A randomized controlled trial. Front. Pharmacol. 2018, 8, 1–9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wong-Lun-Hing, E.M.; van Dam, R.M.; Welsh, F.K.S.; Wells, J.K.G.; John, T.G.; Cresswell, A.B.; Dejong, C.H.C.; Rees, M. Postoperative pain control using continuous i.m. bupivacaine infusion plus patient-controlled analgesia compared with epidural analgesia after major hepatectomy. HPB 2014, 16, 601–609. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khan, J.; Katz, J.; Montbriand, J.; Ladak, S.; McCluskey, S.; Srinivas, C.; Ko, R.; Grant, D.; Bradbury, A.; LeManach, Y.; et al. Surgically placed abdominal wall catheters on postoperative analgesia and outcomes after living liver donation. Liver Transplant. Off. Publ. Am. Assoc. Study Liver Dis. Int. Liver Transplant. Soc. 2015, 21, 478–486. [Google Scholar] [CrossRef] [Scilit]
- Che, L.; Lu, X.; Pei, L. Efficacy and safety of a continuous wound catheter in open abdominal partial hepatectomy. Chin. Med. Sci. J. 2017, 32, 171–176. [Google Scholar] [CrossRef] [Scilit]
- Hernandez, M.C.; Panchamia, J.; Finnesgard, E.J.; Leiting, J.L.; Franssen, B.; Saleem, H.; Kendrick, M.L.; Nagorney, D.M.; Truty, M.J.; Smoot, R.L. Transversus abdominis plane blocks with liposomal bupivacaine after open major hepatectomy is associated with reduced early patient-reported pain scores and opioid administration. Surgery 2018, 164, 1251–1258. [Google Scholar] [CrossRef] [Scilit]
- Amundson, A.W.; Olsen, D.A.; Smith, H.M.; Torsher, L.C.; Martin, D.P.; Heimbach, J.K.; Findlay, J.Y. Acute benefits after liposomal bupivacaine abdominal wall blockade for living liver donation: A retrospective review. Mayo Clin. Proc. Innov. Qual. Outcomes 2018, 2, 186–193. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maeda, A.; Shibata, S.C.; Wada, H.; Marubashi, S.; Kamibayashi, T.; Eguchi, H.; Fujino, Y. The efficacy of continuous subcostal transversus abdominis plane block for analgesia after living liver donation: A retrospective study. J. Anesth. 2016, 30, 39–46. [Google Scholar] [CrossRef] [Scilit]
- Ganapathi, S.; Roberts, G.; Mogford, S.; Bahlmann, B.; Ateleanu, B.; Kumar, N. Epidural analgesia provides effective pain relief in patients undergoing open liver surgery. Br. J. Pain 2015, 9, 78–85. [Google Scholar] [CrossRef] [Scilit]
- Lim, K.I.; Liu, C.K.; Chen, C.L.; Wang, C.H.; Huang, C.J.; Cheng, K.W.; Wu, S.C.; Shih, T.H.; Yang, S.C.; Lee, Y.E.; et al. Transitional study of patient-controlled analgesia morphine with ketorolac to patient-controlled analgesia morphine with parecoxib among donors in adult living donor liver transplantation: A single-center experience. Transplant. Proc. 2016, 48, 1074–1076. [Google Scholar] [CrossRef] [Scilit]
- Tang, J.; Churilov, L.; Tan, C.O.; Hu, R.; Pearce, B.; Cosic, L.; Christophi, C.; Weinberg, L. Intrathecal morphine is associated with reduction in postoperative opioid requirements and improvement in postoperative analgesia in patients undergoing open liver resection. BMC Anesthesiol. 2020, 20, 1–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kasivisvanathan, R.; Abbassi-Ghadi, N.; Prout, J.; Clevenger, B.; Fusai, G.K.; Mallett, S. V A prospective cohort study of intrathecal versus epidural analgesia for patients undergoing hepatic resection. HPB 2014, 16, 768–775. [Google Scholar] [CrossRef] [Scilit]
- Mistry, K.; Hutchins, J.; Leiting, J.; Mangalick, K.; Pruett, T.; Chinnakotla, S. Continuous paravertebral infusions as an effective adjunct for postoperative pain management in living liver donors: A retrospective observational study. Transplant. Proc. 2017, 49, 309–315. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Masgoret, P.; Gomar, C.; Tena, B.; Taurá, P.; Ríos, J.; Coca, M.; Taura, P.; Rios, J.; Coca, M. Incidence of persistent postoperative pain after hepatectomies with 2 regimes of perioperative analgesia containing ketamine. Medicine 2017, 96, e6624. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Terrazina, S.; Robba, C.; Prette, A.; Sergi, P.; Bilotta, F. Prevention and treatment of postoperative pain after lumbar spine procedures: A systematic review. Pain Pract. 2018, 18, 925–945. [Google Scholar] [CrossRef] [Scilit]
- Tsaousi, G.; Logan, S.; Bilotta, F. Postoperative pain control following craniotomy: A systematic review of recent clinical literature. Pain Pract. 2017, 17, 968–981. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gottschalk, A.; Cohen, S.; Yang, S.; Ochroch, E.A. Preventing and treating pain after thoracic surgery. Anesthesiology 2006, 104, 594–600. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ramsay, M.A. Postoperative Pain Management: Is the Surgical Team Approach Finally Getting It Right? Ann. Surg. 2019, 270, 209–210. [Google Scholar] [CrossRef] [Scilit] [PubMed]


Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).