


Abstract
Background/Objectives: Progressive supranuclear palsy (PSP) is an atypical Parkinsonian disorder characterized by Parkinsonism with gait imbalance, vertical gaze palsy, and frontal cognitive dysfunction. Though digital health technologies (DHTs) are widely used both clinically and in research as outcome measures, there is a lack of consistency applied to these devices and their resulting metrics. This scoping review aims to identify efforts taken to validate wearable DHTs for use in PSP, identify gaps in research, and discuss the steps needed to expand their use and acceptance as primary trial endpoints. Methods: In this scoping review, we conducted a search of the MEDLINE database to examine the use of DHTs as outcome measures in Progressive Supranuclear Palsy. Results: A total of 17 publications were identified and reviewed. Included articles evaluated the use of DHT to measure lower extremity function/gait, balance, upper extremity function, and speech. Conclusions: Our scoping review highlights the importance of standardization of DHT metrics by thorough assessment of their content validity, reliability, construct validity, responsiveness, and discriminant validity. Efforts must be taken to ensure DHTs capture clinically relevant, patient-centered outcome measures that are comparable to conventional rating scales, that consistently discriminate disease progression. Incorporation of DHTs as clinical trial endpoints has the potential to encourage clinical research and to advance patient care.
1. Introduction
Progressive supranuclear palsy (PSP) is an atypical Parkinsonian disorder (APD) clinically characterized by Parkinsonism, specifically akinesia, with early and severe gait imbalance, vertical gaze palsy and frontal cognitive dysfunction [1]. Pathologically, PSP is a 4R-tauopathy characterized by hyperphosphorylated tau proteins that deposit in neurons and glial cells leading to neuronal degeneration [2,3]. In PSP, neurofibrillary tangle deposition in neurons is often observed in the globus pallidus, subthalamic nucleus and substantia nigra, while tufted astrocyte accumulation in glial cells is predominantly detected in peri-Rolandic cortices and the putamen [3].
PSP is a progressive and, ultimately, fatal disorder with no effective treatment [1]. The current gold-standard for measuring PSP progression is the Progressive Supranuclear Palsy Rating Scale (PSPRS) [4]. Most clinical trials for PSP currently require in-person assessments with a rater trained in the administration of the PSPRS to quantify outcome measures [5,6].
The U.S. Food and Drug Administration (FDA) defines digital health technology (DHT) as “a system that uses computing platforms, connectivity, software, and/or sensors, for health care and related uses” [7]. There are a wide variety of wearable DHTs available in today’s global market for both clinical and research use [8]. DHTs are often used only as secondary or exploratory endpoints in clinical trials. Though DHTs currently have some limitations, they offer several unique opportunities relative to conventional rating scales (Table 1).
Table 1.
Current limitations and opportunities of digital health technologies.
1.1. Assessing Validity of Digital Health Technologies
To achieve adoption as a clinical trial endpoint and to meet regulatory requirements, there are several metrics that a DHT must meet, including content validity, reliability, construct validity, responsiveness, and discriminant validity. Content validity, also called technical validity, compares a measurement derived from a DHT with a measurement obtained via conventional methods [13]. Reliability of the sensor implies minimal variance when the same device is used repeatedly to measure a single patient outcome; however, it should also denote minimal inter-device variance [9,13]. Construct validity, also known as clinical validity, suggests that outcome measures have shown comparable results when evaluated against a defined clinical scale [9,13,14]. Responsiveness suggests the endpoint can identify longitudinal changes within a group [13]. In their review of wearable devices for Parkinson’s disease (PD), Del Din et al. also emphasize that a DHT should demonstrate discriminant validity: the ability to differentiate between groups (such as between healthy and control populations) [14].
Finally, the digital biomarker must reflect patient-centered, clinically relevant outcome measures [15]. Mitsi et al. postulate that this question of participant engagement and, ultimately, adherence is the last and possibly most essential form of validation [16].
1.2. Process to Obtain Regulatory Approval for DHTs in Other Neurologic Diseases
We examined the regulatory pathway for DHTs in other neurological diseases in order to contextualize this review. The first DHT to obtain EMA regulatory approval for use as a secondary clinical trial endpoint is called ActiMyo®, a two-strap-based wearable sensor [17,18]. ActiMyo® was approved for use in Duchenne muscular dystrophy (DMD). To obtain regulatory approval, several steps were taken to validate the technology. Technical validity, also called content validity, was established by comparing DHT and clinical measures of the 6 min walk test, showing only a 5% difference between the two outcomes [17]. Reliability was shown by measuring variance in stride length and velocity demonstrating only 2.2–4.4% variability [17]. Clinical validity, also called construct validity, was also shown through comparison to the North Star Ambulatory Assessment, and the 4-stair climbing test, demonstrating high correlation (0.78 and 0.64, respectively) [17]. In addition, ActiMyo sensors demonstrated responsiveness by tracking individuals’ clinical decline with longitudinal data collection over a 6-month period [17]. This success can inform efforts to streamline regulatory approval of DHTs as clinical trial endpoints in other diseases.
Wearable DHTs have been extensively tested in individuals with PD. The devices currently on the market for use in PD have been ‘FDA-cleared’, which indicates that they demonstrated ‘substantial equivalence’ to another device already on the market. Wearable DHTs are typically categorized by the FDA as class II, or moderate risk devices. As such, the FDA clearance process requires submission of a Premarket Notification via the 510(k) clearance process [19]. In 2021, Del Din et al. summarized DHT motor-specific outcomes for individuals with PD with a goal to establish technical and clinical validation (in this case designated as ‘criterion validity’ and ‘construct validity’) for these devices [14]. By their analysis, several DHTs achieved these validation metrics for use in PD to measure motor symptoms, including tremor and bradykinesia, postural instability and gait disturbance [14]. Despite this, regulatory bodies have approved very few DHTs for use in PD and no DHT has been approved as a clinical trial endpoint in PD.
1.3. Objective of This Scoping Review
Based on the gathered information, we decided to conduct further research to analyze the use of DHTs in PSP. The aim of this scoping review is to outline efforts taken to validate wearable DHTs for use in PSP, identify gaps in research, and to discuss the steps needed to expand their use and acceptance as primary trial endpoints by United States and European regulatory agencies.
2. Materials and Methods
This review follows the guidelines outlined in the Preferred Reporting Items for Systematic Review and Meta-Analysis (PRISMA) Extension for Scoping Reviews [20].
The review was conducted using the MEDLINE database. The review began in February of 2025 and was completed in March of 2025 with most recent search performed on 23 March 2025. The search was conducted using the keywords outlined in Table 2. An additional search filter for a 15-year date restriction was applied for inclusion in the study. All searches were performed in English.
Table 2.
MEDLINE search terms.
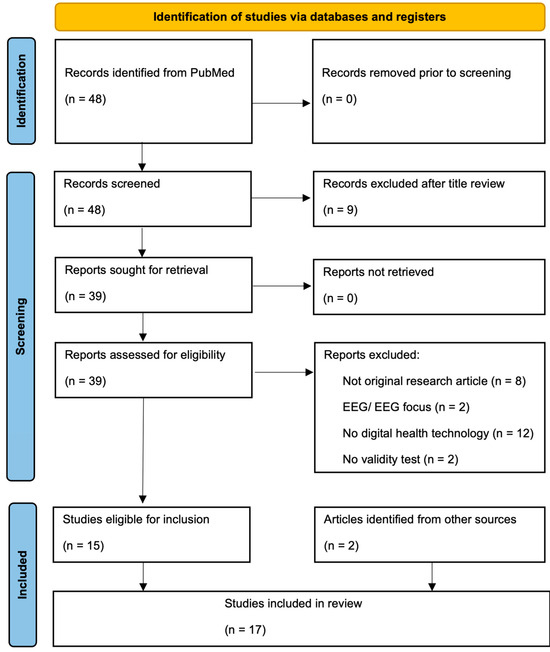
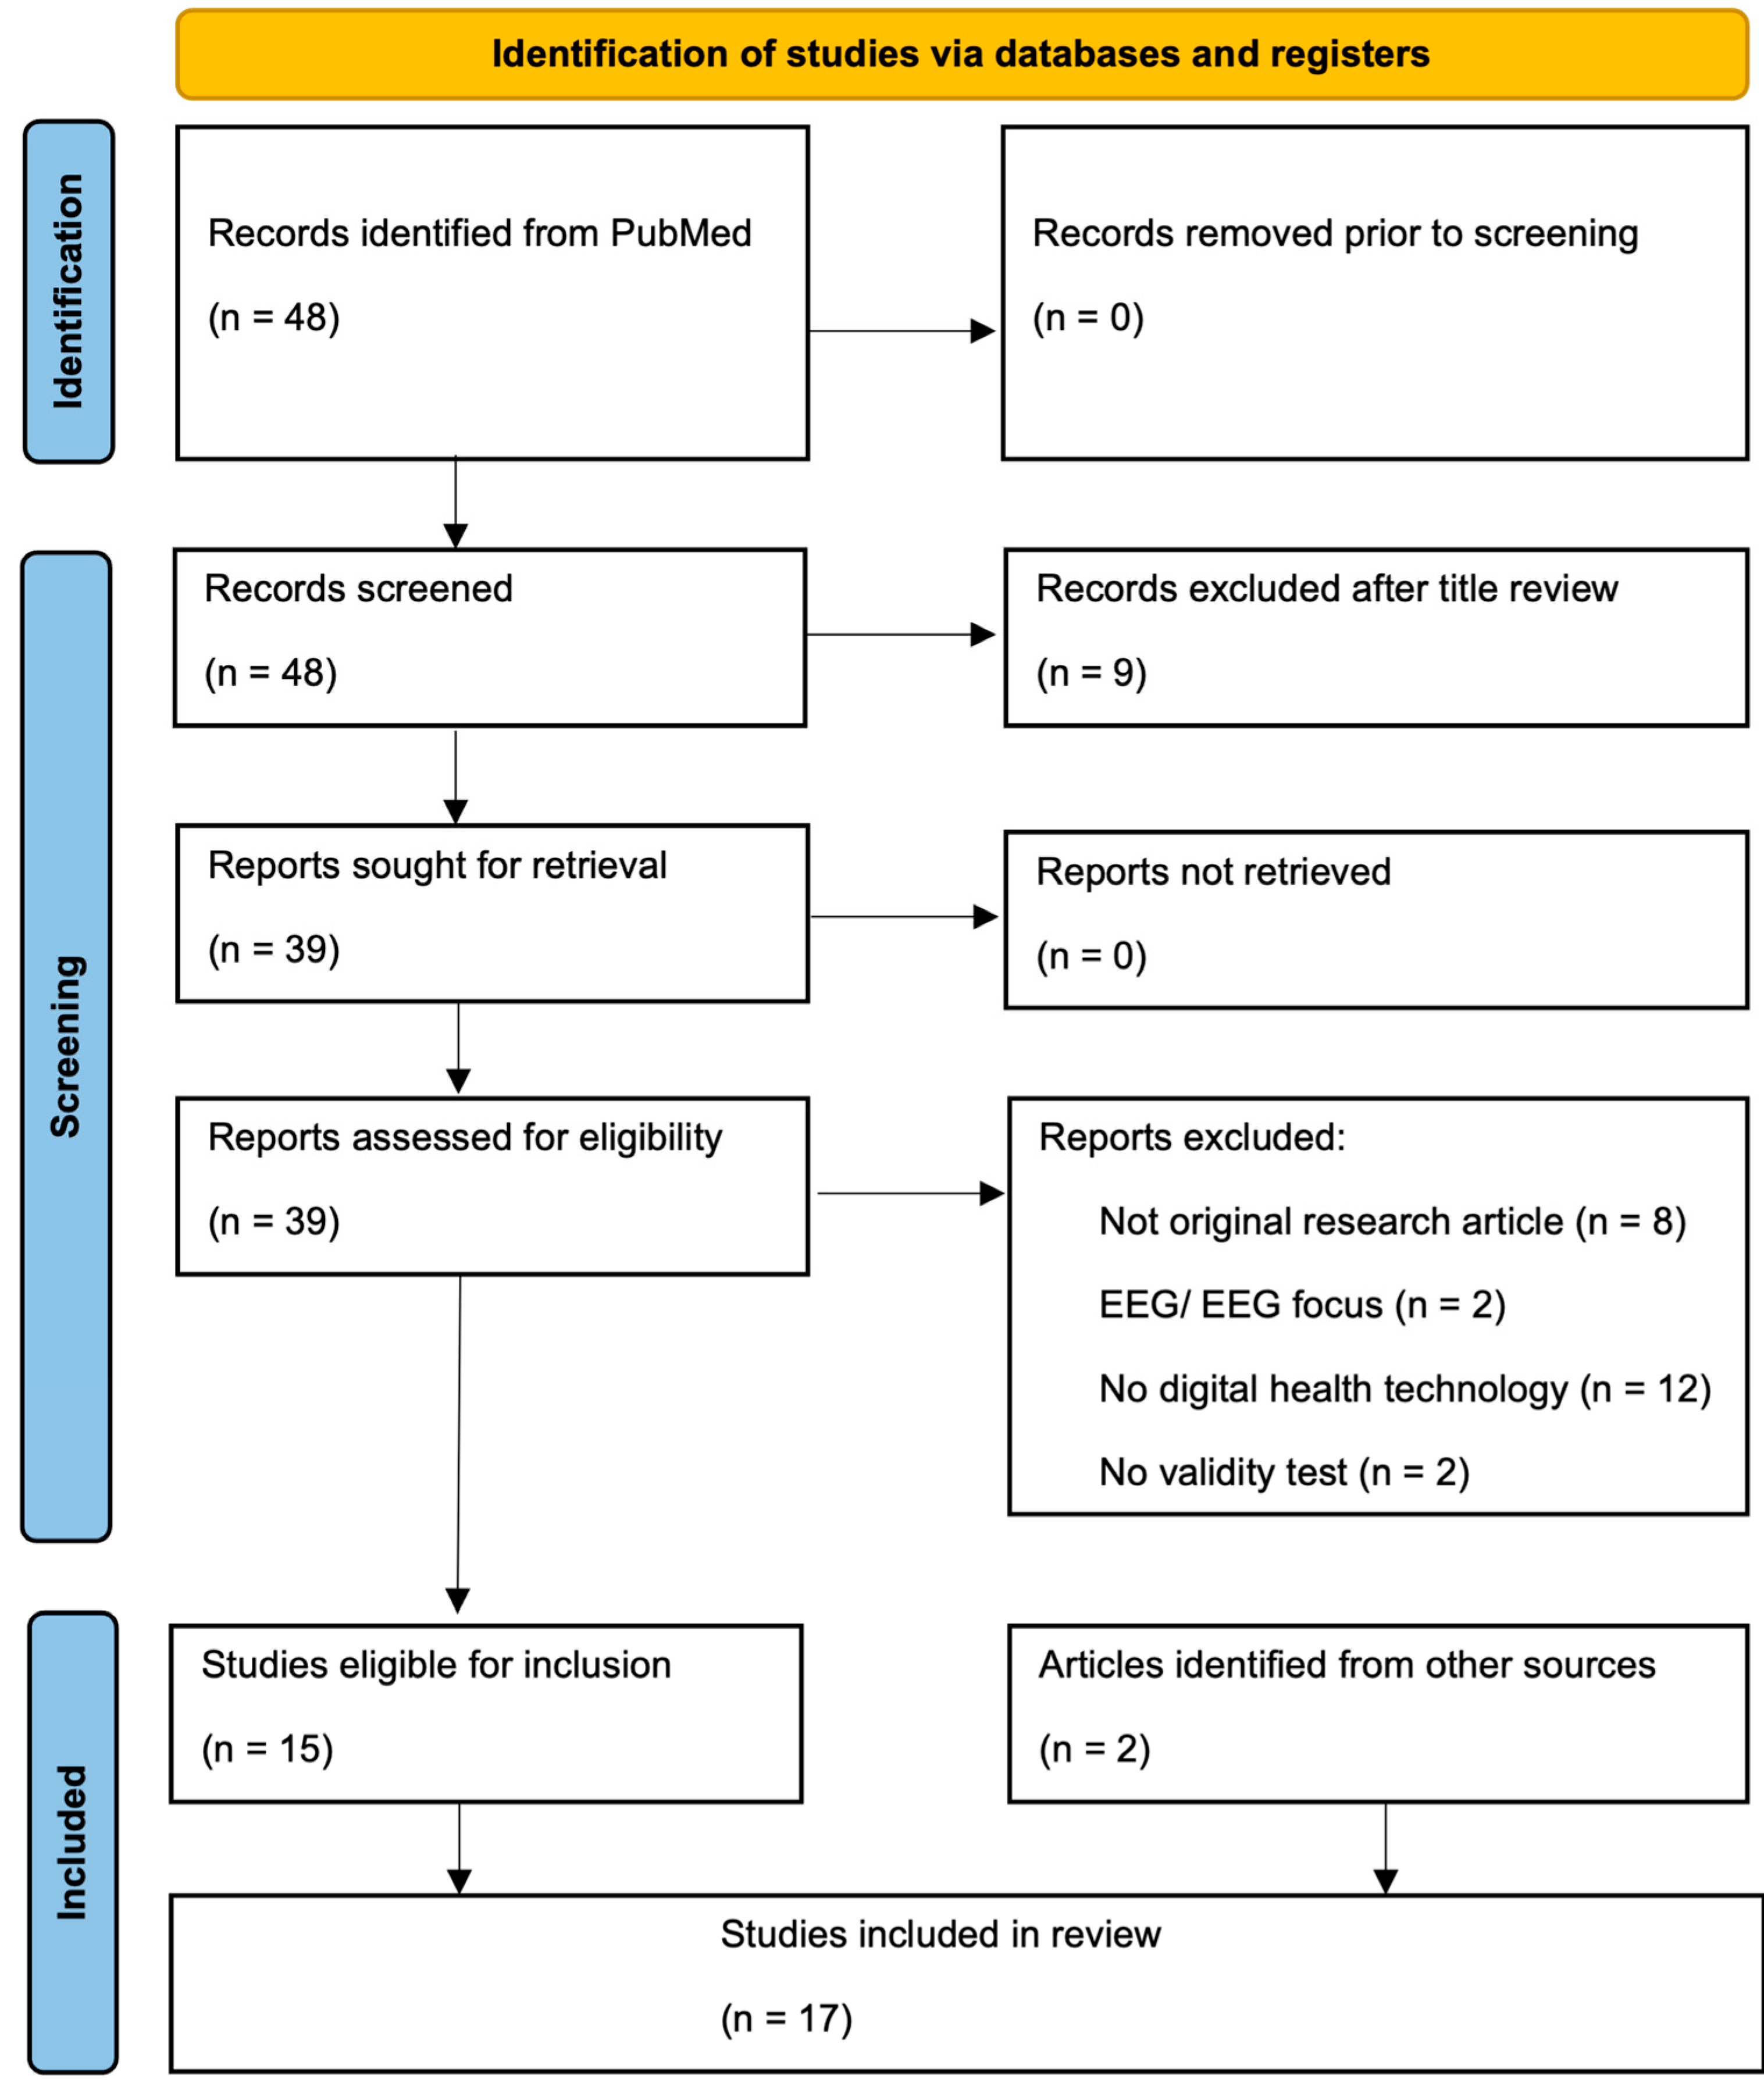
This review was conducted by first assessing the titles of the papers, followed by the abstracts, and finally the full papers. Only English-language articles were included. The review included studies with participants from all age groups within the PSP population. Only original research articles, including peer-reviewed journal articles and conference papers, were included in the review. Articles on digital health technology as an outcome measure in individuals with PSP were included. Studies that focused solely on electroencephalogram or electrocardiogram data were also excluded. Studies with and without comparison groups (e.g., healthy controls, other movement disorders) were included in this review. Studies utilizing DHT-derived endpoints as outcome measures were included in the review. Studies that did not address validity, reliability, or responsiveness were excluded. Finally, an additional step to evaluate the reference list of included articles was performed to locate other articles that were not included in the database search but could potentially be eligible for inclusion in the review. The selection process is displayed in a PRISMA flowchart (see Figure 1). Data charting was performed independently by C.I.
Figure 1.
PRISMA flow diagram.
A complete synthesis of the results is conducted in tabular and descriptive form in the Results section.
3. Results
The entire article selection process can be reviewed in the PRISMA flowchart (Figure 1). The search criteria initially identified 48 articles. A total of 9 articles were excluded after reviewing the titles for eligibility, resulting in 39 articles. All reports were retrieved. A total of 15 articles were eligible for inclusion after full-text assessment. Two additional eligible articles were identified from other resources including assessment of included reference lists and dedicated search for articles evaluating the previously described sensors. In summary, a total of 17 articles were included in this scoping review.
The included studies were published between 2014 and 2024 with 12 of the 17 studies published since 2019, underlining growing interest in this area. All studies were published in peer-reviewed journals. Three of the articles included more than one validation technique [21,22,23]. The sensors evaluated include the Opal IMU Sensor (APDM, Portland, OR, USA), SHIMMER 2 Sensor (Shimmer, Dublin, Ireland), LEGSys+ Sensors (BioSensics LLC, Newton, MA, USA), Balance Master Clinical Research System (NeuroCom International, Clarckamas, OR, USA), activPAL accelerometer (PAL Technologies Ltd., Glasgow, UK), IMSUs from the University of Belgrade, Serbia (STMicroelectronics, Geneva, Switzerland), BioDigit Speech Sensor (BioSensics LLC, Newton, MA, USA), ki: SB-M intelligibility score (ki:elements, Saarbrücken, Germany), and the Speech Activity Detector (University of Pennsylvania Linguistic Data Consortium, Philadelphia, PA, USA). Details and outcomes from the qualified scientific papers can be found in Table 3.
Nine of the seventeen studies [21,22,23,24,25,26,27,28,29] in this review utilized the 2017 MDS diagnostic criteria [30] for inclusion of PSP participants (either probable or possible PSP), while six [31,32,33,34,35,36] used the older 1996 NINDS-SPSP criteria [37] for inclusion in the studies. Two of the included studies did not specify the PSP diagnostic criteria used [38,39]. Most studies did not specify PSP predominance type, but three studies reported inclusion of only PSP-Richardson’s syndrome or PSP-Parkinsonism predominant variants [24,25,28].
This review determined that there are a few notable gaps in the assessment of the use of wearable DHTs in progressive supranuclear palsy. Some sensors have demonstrated content validity in PSP; however, others have only been technically assessed in healthy control populations or in Parkinson’s disease [40,41]. Currently the FDA recommends that the DHT be assessed in the proposed participant population [7]. Additionally, the review highlights the paucity of non-motor DHT-derived outcomes with only three studies highlighting speech assessment through the use of DHT [22,23,29]. The search revealed no articles assessing oculography even though ocular motor dysfunction is a core clinical feature of PSP as defined by the Movement Disorder Society 2017 Criteria [30].
While excluded from this review due to lack of validity testing, a paper by Ohara et al. is novel as it utilizes DHT data as the primary outcome measure [42]. The study assessed response to spinal tap vs. sham spinal tap procedures in PSP, normal pressure hydrocephalus (NPH), and healthy controls [42]. DHT was used in assessment of timed up-and-go test and showed that the ratio of tap responders and sham tap responders in PSP was not statistically different from those with NPH but was different from the response seen in HC [42].
Many of the included studies assess the construct validity and responsiveness of the sensors relative to the PSPRS to demonstrate the non-inferiority of the DHT-derived data. Importantly, Sotirakis et al. report that their linear regression model, which incorporates three sensor-measured gait parameters, detected a quantifiable change from baseline three months earlier than the PSPRS [25]. This suggests the potential for DHTs to yield outcome measures that are more discriminant than conventional rating scales.
Table 3.
Measurement properties and study outcomes of several DHTs in PSP.
4. Discussion
This paper maps the efforts to substantiate various DHTs for use in PSP through a scoping review of 17 studies. As shown above, several DHTs have demonstrated content validity, reliability, construct validity, responsiveness, and discriminant validity in PSP to capture gait, balance, upper extremity function, and speech data. These outcome measures can be used alone or in combination to generate insight into PSP disease severity.
There are several limitations to our review. First, PSP is a heterogeneous disease [43]. Only two major subtypes—PSP-Richardson’s syndrome and PSP-Parkinsonism predominant—were included in most of these studies. Additionally, the sample size of all included DHT studies was low, raising concerns for generalizability of the data.
In addition, our search criteria did not capture studies focused on oculography. As ocular motor dysfunction is a core feature of PSP, oculography could lend additional insight into disease severity and further validate DHT data for use in clinical trials.
Currently, DHTs attempt to replicate measures derived via conventional methods. As the technology continues to advance, regulators will need to decide (1) whether this comparison remains valid and (2) how to treat digital biomarkers with no conventional comparator.
In order for DHTs to be accepted as clinical trial endpoints in PSP, they must first demonstrate responsiveness and the ability to capture disease progression and longitudinal change. Abate et al. demonstrated a significant longitudinal change in DHT outcome measures of gait at 3 months, suggesting that these wearable sensors can quantify progression of gait changes in PSP [21]. The use of DHTs as a primary outcome measure in the study by Ohara et al. suggests the feasibility of including DHT-derived data as a primary endpoint [42]. However, more studies are needed to corroborate DHT’s sensitivity to progressive change at additional timepoints.
Interestingly, Sotirakis et al. demonstrate that the longitudinal difference in gait captured by DHT is detectable up to three months earlier than by the PSPRS alone [25]. Earlier detection of clinical differences in clinical trials could lead to a positive trial outcome in a disease that otherwise has limited treatments. However, studies have not yet shown that these early changes identified by DHT are clinically meaningful to patients, caregivers and clinicians [7]. Demonstrating clinical meaningfulness is a critical step, not only to obtain regulatory approval of these devices, but also to ensure patient adoption of the studied intervention.
Despite these caveats, there are many potential advantages to adopting DHT’s as clinical outcome measures. DHTs have the potential to provide more frequent, standardized, and quantitative assessments. Ultimately, this precision implies smaller, more efficient, and cost-effective clinical trials in the future. DHTs also offer the ability to assess participants in a remote, home-based, real-world setting [9,44]. The remote nature of DHT assessments also offer wider inclusivity for patients who are geographically or financially limited. For these reasons, it is of the utmost importance that regulatory bodies continue to assess the use of these technologies as clinical trial endpoints in PSP. Assessment of content validity, reliability, construct validity, responsiveness, and discriminant validity for these DHTs in PSP should provide additional evidence to the regulatory agencies towards acceptance as clinical trials endpoints.
Author Contributions
Conceptualization, C.I., M.L.D., A.P., A.-M.W. and C.A.A.; writing—original draft preparation, C.I.; writing—review and editing, C.I., K.K., A.J.E., M.L.D., A.P., A.-M.W. and C.A.A. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
C.I., A.-M.W. and A.P. have received funding from the NHA/NIA SBIR R44AG080861 in collaboration with BioSensics. A.P. has consulted for Ono Pharma, Ferrer International and MedRhythms, Inc. M.L.D. has received funding from NIH/NINDS K23NS121402 and has consulted for Cognito Therapeutics.
Abbreviations
The following abbreviations are used in this manuscript:
| DHT | Digital health technologies |
| PSP | Progressive Supranuclear Palsy |
| PSPRS | Progressive Supranuclear Palsy Rating Scale |
| PD | Parkinson’s disease |
| DA | Degenerative ataxia |
| ALS | Amyotrophic Lateral Sclerosis |
| HD | Huntington’s disease |
| MSA | Multiple system atrophy |
| naPPA | Non-fluent/agrammatic primary progressive aphasia |
| CBS | Corticobasal syndrome |
| HC | Healthy controls |
| DMD | Duchenne muscular dystrophy |
| EMA | European Medicines Agency |
| FDA | Food and Drug Administration |
| FAB | Frontal Assessment Battery (FAB) |
| IMU | Inertial Measurement Unit |
| IMSUs | Inertial Measurement Sensor Units |
| LCC | Lin’s concordance correlation coefficient |
| PCC | Pearson correlation coefficient |
| SCC | Spearman’s correlation coefficient |
| ICC | Intraclass correlation coefficient |
| SB-M | Speech biomarker score for motor speech disorders (SB-M) |
| NNIPPS | Natural History and Neuroprotection in Parkinson Plus Syndromes—Parkinson Plus Scale |
References
- Boxer, A.L.; Yu, J.-T.; Golbe, L.I.; Litvan, I.; Lang, A.E.; Höglinger, G.U. New Diagnostics and Therapeutics for Progressive Supranuclear Palsy. Lancet Neurol. 2017, 16, 552–563. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Giagkou, N.; Höglinger, G.U.; Stamelou, M. Chapter Three—Progressive Supranuclear Palsy. In International Review of Neurobiology; Stamelou, M., Höglinger, G.U., Eds.; Parkinsonism Beyond Parkinson’s Disease; Academic Press: Cambridge, MA, USA, 2019; Volume 149, pp. 49–86. [Google Scholar]
- Roemer, S.F.; Grinberg, L.T.; Crary, J.F.; Seeley, W.W.; McKee, A.C.; Kovacs, G.G.; Beach, T.G.; Duyckaerts, C.; Ferrer, I.A.; Gelpi, E.; et al. Rainwater Charitable Foundation Criteria for the Neuropathologic Diagnosis of Progressive Supranuclear Palsy. Acta Neuropathol. 2022, 144, 603. [Google Scholar] [CrossRef] [Scilit]
- Golbe, L.I.; Ohman-Strickland, P.A. A Clinical Rating Scale for Progressive Supranuclear Palsy. Brain 2007, 130, 1552–1565. [Google Scholar] [CrossRef] [Scilit]
- Wills, A.-M.; Pantelyat, A.; Espay, A.; Chan, J.; Litvan, I.; Xie, T.; Dale, M.L.; Gunzler, S.A.; Tartaglia, M.C.; Fox, S.H.; et al. A Modified Progressive Supranuclear Palsy Rating Scale for Virtual Assessments. Mov. Disord. 2022, 37, 1265–1271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wills, A.; Golbe, L.I.; Lang, A.E.; Xie, T.; Dale, M.L.; Espay, A.; Tartaglia, M.C.; Fox, S.H.; Parashos, S.A.; McFarland, N.R.; et al. Recommendations for Virtual Administration of the PSP Rating Scale. Mov. Disord. 2022, 37, 1960–1961. [Google Scholar] [CrossRef] [Scilit]
- U.S. Department of Health and Human Services: Food and Drug Administration. Digital Health Technologies for Remote Data Acquisition in Clinical Investigations: Guidance for Industry, Investigators, and Other Stakeholders. 2023. Available online: https://www.fda.gov/media/155022/download (accessed on 17 February 2025).
- Marra, C.; Chen, J.L.; Coravos, A.; Stern, A.D. Quantifying the Use of Connected Digital Products in Clinical Research. NPJ Digit. Med. 2020, 3, 50. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Espay, A.J.; Hausdorff, J.M.; Sánchez-Ferro, Á.; Klucken, J.; Merola, A.; Bonato, P.; Paul, S.S.; Horak, F.B.; Vizcarra, J.A.; Mestre, T.A.; et al. A Roadmap for Implementation of Patient-Centered Digital Outcome Measures in Parkinson’s Disease Obtained Using Mobile Health Technologies. Mov. Disord. 2019, 34, 657–663. [Google Scholar] [CrossRef] [Scilit]
- Toosizadeh, N.; Mohler, J.; Lei, H.; Parvaneh, S.; Sherman, S.; Najafi, B. Motor Performance Assessment in Parkinson’s Disease: Association between Objective In-Clinic, Objective In-Home, and Subjective/Semi-Objective Measures. PLoS ONE 2015, 10, e0124763. [Google Scholar] [CrossRef] [Scilit]
- Espay, A.J.; Bonato, P.; Nahab, F.B.; Maetzler, W.; Dean, J.M.; Klucken, J.; Eskofier, B.M.; Merola, A.; Horak, F.; Lang, A.E.; et al. Technology in Parkinson’s Disease: Challenges and Opportunities. Mov. Disord. 2016, 31, 1272–1282. [Google Scholar] [CrossRef] [Scilit]
- Awad, A.; Trenfield, S.J.; Pollard, T.D.; Ong, J.J.; Elbadawi, M.; McCoubrey, L.E.; Goyanes, A.; Gaisford, S.; Basit, A.W. Connected Healthcare: Improving Patient Care Using Digital Health Technologies. Adv. Drug Deliv. Rev. 2021, 178, 113958. [Google Scholar] [CrossRef] [Scilit]
- COSMIN Taxonomy of Measurement Properties. Available online: https://www.cosmin.nl/tools/cosmin-taxonomy-measurement-properties/ (accessed on 1 March 2025).
- Del Din, S.; Kirk, C.; Yarnall, A.J.; Rochester, L.; Hausdorff, J.M. Body-Worn Sensors for Remote Monitoring of Parkinson’s Disease Motor Symptoms: Vision, State of the Art, and Challenges Ahead. J. Park. Dis. 2021, 11, S35–S47. [Google Scholar] [CrossRef] [Scilit]
- Ilg, W.; Milne, S.; Schmitz-Hübsch, T.; Alcock, L.; Beichert, L.; Bertini, E.; Mohamed Ibrahim, N.; Dawes, H.; Gomez, C.M.; Hanagasi, H.; et al. Quantitative Gait and Balance Outcomes for Ataxia Trials: Consensus Recommendations by the Ataxia Global Initiative Working Group on Digital-Motor Biomarkers. Cerebellum 2023, 23, 1566–1592. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mitsi, G.; Mendoza, E.U.; Wissel, B.D.; Barbopoulou, E.; Dwivedi, A.K.; Tsoulos, I.; Stavrakoudis, A.; Espay, A.J.; Papapetropoulos, S. Biometric Digital Health Technology for Measuring Motor Function in Parkinson’s Disease: Results from a Feasibility and Patient Satisfaction Study. Front. Neurol. 2017, 8, 273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Servais, L.; Camino, E.; Clement, A.; McDonald, C.M.; Lukawy, J.; Lowes, L.P.; Eggenspieler, D.; Cerreta, F.; Strijbos, P. First Regulatory Qualification of a Novel Digital Endpoint in Duchenne Muscular Dystrophy: A Multi-Stakeholder Perspective on the Impact for Patients and for Drug Development in Neuromuscular Diseases. Digit. Biomark. 2021, 5, 183–190. [Google Scholar] [CrossRef] [Scilit]
- European Medicines Agency Committee for Medicinal Products for Human Use. Qualification Opinion for Stride Velocity 95th Centile as Primary Endpoint in Studies in Ambulatory Duchenne Muscular Dystrophy Studies. 2023. Available online: https://www.ema.europa.eu/en/documents/scientific-guideline/qualification-opinion-stride-velocity-95th-centile-primary-endpoint-studies-ambulatory-duchenne-muscular-dystrophy-studies_en.pdf (accessed on 2 February 2025).
- FDA Center for Devices and Radiological Health (CDRH). Medical Device Safety and the 510(k) Clearance Process. 2024. Available online: https://www.fda.gov/medical-devices/510k-clearances/medical-device-safety-and-510k-clearance-process (accessed on 2 February 2025).
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit]
- Abate, F.; Russo, M.; Ricciardi, C.; Tepedino, M.F.; Romano, M.; Erro, R.; Pellecchia, M.T.; Amboni, M.; Barone, P.; Picillo, M. Wearable Sensors for Assessing Disease Severity and Progression in Progressive Supranuclear Palsy. Park. Relat. Disord. 2023, 109, 105345. [Google Scholar] [CrossRef] [Scilit]
- Tröger, J.; Dörr, F.; Schwed, L.; Linz, N.; König, A.; Thies, T.; Barbe, M.T.; Orozco-Arroyave, J.R.; Rusz, J. An Automatic Measure for Speech Intelligibility in Dysarthrias—Validation across Multiple Languages and Neurological Disorders. Front. Digit. Health 2024, 6, 1440986. [Google Scholar] [CrossRef] [Scilit]
- Parjane, N.; Cho, S.; Ash, S.; Cousins, K.A.Q.; Shellikeri, S.; Liberman, M.; Shaw, L.M.; Irwin, D.J.; Grossman, M.; Nevler, N. Digital Speech Analysis in Progressive Supranuclear Palsy and Corticobasal Syndromes. J. Alzheimers Dis. 2021, 82, 33–45. [Google Scholar] [CrossRef] [Scilit]
- De Vos, M.; Prince, J.; Buchanan, T.; FitzGerald, J.J.; Antoniades, C.A. Discriminating Progressive Supranuclear Palsy from Parkinson’s Disease Using Wearable Technology and Machine Learning. Gait Posture 2020, 77, 257–263. [Google Scholar] [CrossRef] [Scilit]
- Sotirakis, C.; Conway, N.; Su, Z.; Villarroel, M.; Tarassenko, L.; FitzGerald, J.J.; Antoniades, C.A. Longitudinal Monitoring of Progressive Supranuclear Palsy Using Body-Worn Movement Sensors. Mov. Disord. 2022, 37, 2263–2271. [Google Scholar] [CrossRef] [Scilit]
- Ricciardi, C.; Pisani, N.; Donisi, L.; Abate, F.; Amboni, M.; Barone, P.; Picillo, M.; Cesarelli, M.; Amato, F. Agreement between Optoelectronic System and Wearable Sensors for the Evaluation of Gait Spatiotemporal Parameters in Progressive Supranuclear Palsy. Sensors 2023, 23, 9859. [Google Scholar] [CrossRef] [Scilit]
- Sharma, M.; Mishra, R.K.; Hall, A.J.; Casado, J.; Cole, R.; Nunes, A.S.; Barchard, G.; Vaziri, A.; Pantelyat, A.; Wills, A.-M. Remote At-Home Wearable-Based Gait Assessments in Progressive Supranuclear Palsy Compared to Parkinson’s Disease. BMC Neurol. 2023, 23, 434. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Belić, M.; Radivojević, Z.; Bobić, V.; Kostić, V.; Đurić-Jovičić, M. Quick Computer Aided Differential Diagnostics Based on Repetitive Finger Tapping in Parkinson’s Disease and Atypical Parkinsonisms. Heliyon 2023, 9, e14824. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kang, K.; Nunes, A.S.; Sharma, M.; Hall, A.J.; Mishra, R.K.; Casado, J.; Cole, R.; Derhammer, M.; Barchard, G.; Najafi, B.; et al. Utilizing Speech Analysis to Differentiate Progressive Supranuclear Palsy from Parkinson’s Disease. Park. Relat. Disord. 2023, 115, 105835. [Google Scholar] [CrossRef] [Scilit]
- Hoglinger, G.U.; Respondek, G.; Stamelou, M.; Kurz, C.; Josephs, K.A.; Lang, A.E.; Mollenhauer, B.; Muller, U.; Nilsson, C.; Whitwell, J.L.; et al. Clinical Diagnosis of Progressive Supranuclear Palsy: The Movement Disorder Society Criteria. Mov. Disord. 2017, 32, 853–864. [Google Scholar] [CrossRef] [Scilit]
- Klenk, J.; Srulijes, K.; Schatton, C.; Schwickert, L.; Maetzler, W.; Becker, C.; Synofzik, M. Ambulatory Activity Components Deteriorate Differently across Neurodegenerative Diseases: A Cross-Sectional Sensor-Based Study. Neurodegener. Dis. 2016, 16, 317–323. [Google Scholar] [CrossRef] [Scilit]
- Gassner, H.; Raccagni, C.; Eskofier, B.M.; Klucken, J.; Wenning, G.K. The Diagnostic Scope of Sensor-Based Gait Analysis in Atypical Parkinsonism: Further Observations. Front. Neurol. 2019, 10, 5. [Google Scholar] [CrossRef] [Scilit]
- Raccagni, C.; Gaßner, H.; Eschlboeck, S.; Boesch, S.; Krismer, F.; Seppi, K.; Poewe, W.; Eskofier, B.M.; Winkler, J.; Wenning, G.; et al. Sensor-Based Gait Analysis in Atypical Parkinsonian Disorders. Brain Behav. 2018, 8, e00977. [Google Scholar] [CrossRef] [Scilit]
- Dale, M.L.; Horak, F.B.; Wright, W.G.; Schoneburg, B.M.; Nutt, J.G.; Mancini, M. Impaired Perception of Surface Tilt in Progressive Supranuclear Palsy. PLoS ONE 2017, 12, e0173351. [Google Scholar] [CrossRef] [Scilit]
- Srulijes, K.; Klenk, J.; Schwenk, M.; Schatton, C.; Schwickert, L.; Teubner-Liepert, K.; Meyer, M.; Srijana, K.C.; Maetzler, W.; Becker, C.; et al. Fall Risk in Relation to Individual Physical Activity Exposure in Patients with Different Neurodegenerative Diseases: A Pilot Study. Cerebellum 2019, 18, 340–348. [Google Scholar] [CrossRef] [Scilit]
- Djurić-Jovičić, M.; Petrović, I.; Ječmenica-Lukić, M.; Radovanović, S.; Dragašević-Mišković, N.; Belić, M.; Miler-Jerković, V.; Popović, M.B.; Kostić, V.S. Finger Tapping Analysis in Patients with Parkinson’s Disease and Atypical Parkinsonism. J. Clin. Neurosci. 2016, 30, 49–55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Litvan, I.; Agid, Y.; Calne, D.; Campbell, G.; Dubois, B.; Duvoisin, R.C.; Goetz, C.; Golbe, L.I.; Grafman, J.; Growdon, J.H.; et al. Clinical Research Criteria for the Diagnosis of Progressive Supranuclear Palsy (Steele-Richardson-Olszewski Syndrome): Report of the NINDS-SPSP International Workshop. Neurology 1996, 47, 1–9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baston, C.; Mancini, M.; Schoneburg, B.; Horak, F.; Rocchi, L. Postural Strategies Assessed with Inertial Sensors in Healthy and Parkinsonian Subjects. Gait Posture 2014, 40, 70–75. [Google Scholar] [CrossRef] [Scilit]
- Bobić, V.; Djurić-Jovičić, M.; Dragašević, N.; Popović, M.B.; Kostić, V.S.; Kvaščev, G. An Expert System for Quantification of Bradykinesia Based on Wearable Inertial Sensors. Sensors 2019, 19, 2644. [Google Scholar] [CrossRef] [Scilit]
- Kluge, F.; Gaßner, H.; Hannink, J.; Pasluosta, C.; Klucken, J.; Eskofier, B.M. Towards Mobile Gait Analysis: Concurrent Validity and Test-Retest Reliability of an Inertial Measurement System for the Assessment of Spatio-Temporal Gait Parameters. Sensors 2017, 17, 1522. [Google Scholar] [CrossRef] [Scilit]
- Homes, R.; Clark, D.; Moridzadeh, S.; Tosovic, D.; Van den Hoorn, W.; Tucker, K.; Midwinter, M. Comparison of a Wearable Accelerometer/Gyroscopic, Portable Gait Analysis System (LEGSYS+TM) to the Laboratory Standard of Static Motion Capture Camera Analysis. Sensors 2023, 23, 537. [Google Scholar] [CrossRef] [Scilit]
- Ohara, M.; Hattori, T.; Chen, Q.; Shimano, K.; Hirata, K.; Matsui, M.; Yokota, T. Is There a Spinal Tap Responder in Progressive Supranuclear Palsy? The First Prospective Study. J. Neurol. 2024, 271, 4473–4484. [Google Scholar] [CrossRef] [Scilit]
- Krzosek, P.; Madetko, N.; Migda, A.; Migda, B.; Jaguś, D.; Alster, P. Differential Diagnosis of Rare Subtypes of Progressive Supranuclear Palsy and PSP-Like Syndromes—Infrequent Manifestations of the Most Common Form of Atypical Parkinsonism. Front. Aging Neurosci. 2022, 14, 804385. [Google Scholar] [CrossRef] [Scilit]
- Inan, O.T.; Tenaerts, P.; Prindiville, S.A.; Reynolds, H.R.; Dizon, D.S.; Cooper-Arnold, K.; Turakhia, M.; Pletcher, M.J.; Preston, K.L.; Krumholz, H.M.; et al. Digitizing Clinical Trials. NPJ Digit. Med. 2020, 3, 101. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).