Global, Regional, and Country Incidence of Peritoneal Dialysis-Associated Peritonitis in the Contemporary Peritoneal Dialysis Practice: A Systematic Review and Meta-Analysis
 , , , , , ,

Abstract
1. Introduction
2. Materials and Methods
2.1. Data Source and Search Strategy
2.2. Study Selection Criteria and Outcome of Interest
2.3. Data Extraction and Study Quality Assessment
- (i)
- Patient and PD treatment characteristics: mean age of the study population, study population (i.e., adult [elderly and non-elderly], pediatric, mixed, or not specified), sex (proportion of males), comorbid conditions (e.g., diabetes), level of education, PD modality (i.e., continuous ambulatory PD [CAPD], automated PD [APD], mixed, or not specified), and number of PD centers included in the study.
- (ii)
- Study characteristics: first author’s name, sample size, study setting and country, year of publication, period of data collection, and data collection approach (i.e., retrospective, prospective, ambispective, or registry data).
- (iii)
- Predefined outcomes: the overall rate of PD-associated peritonitis (i.e., total episodes of peritonitis, total patient-years at risk, overall episodes per patient-year, or patient-months per episode). If available, we also extracted relevant information by causative microorganism (i.e., Gram-positive bacteria, Gram-negative bacteria, fungi, Mycobacterium, polymicrobial, and culture-negative).
2.4. Statistical Analyses
3. Results
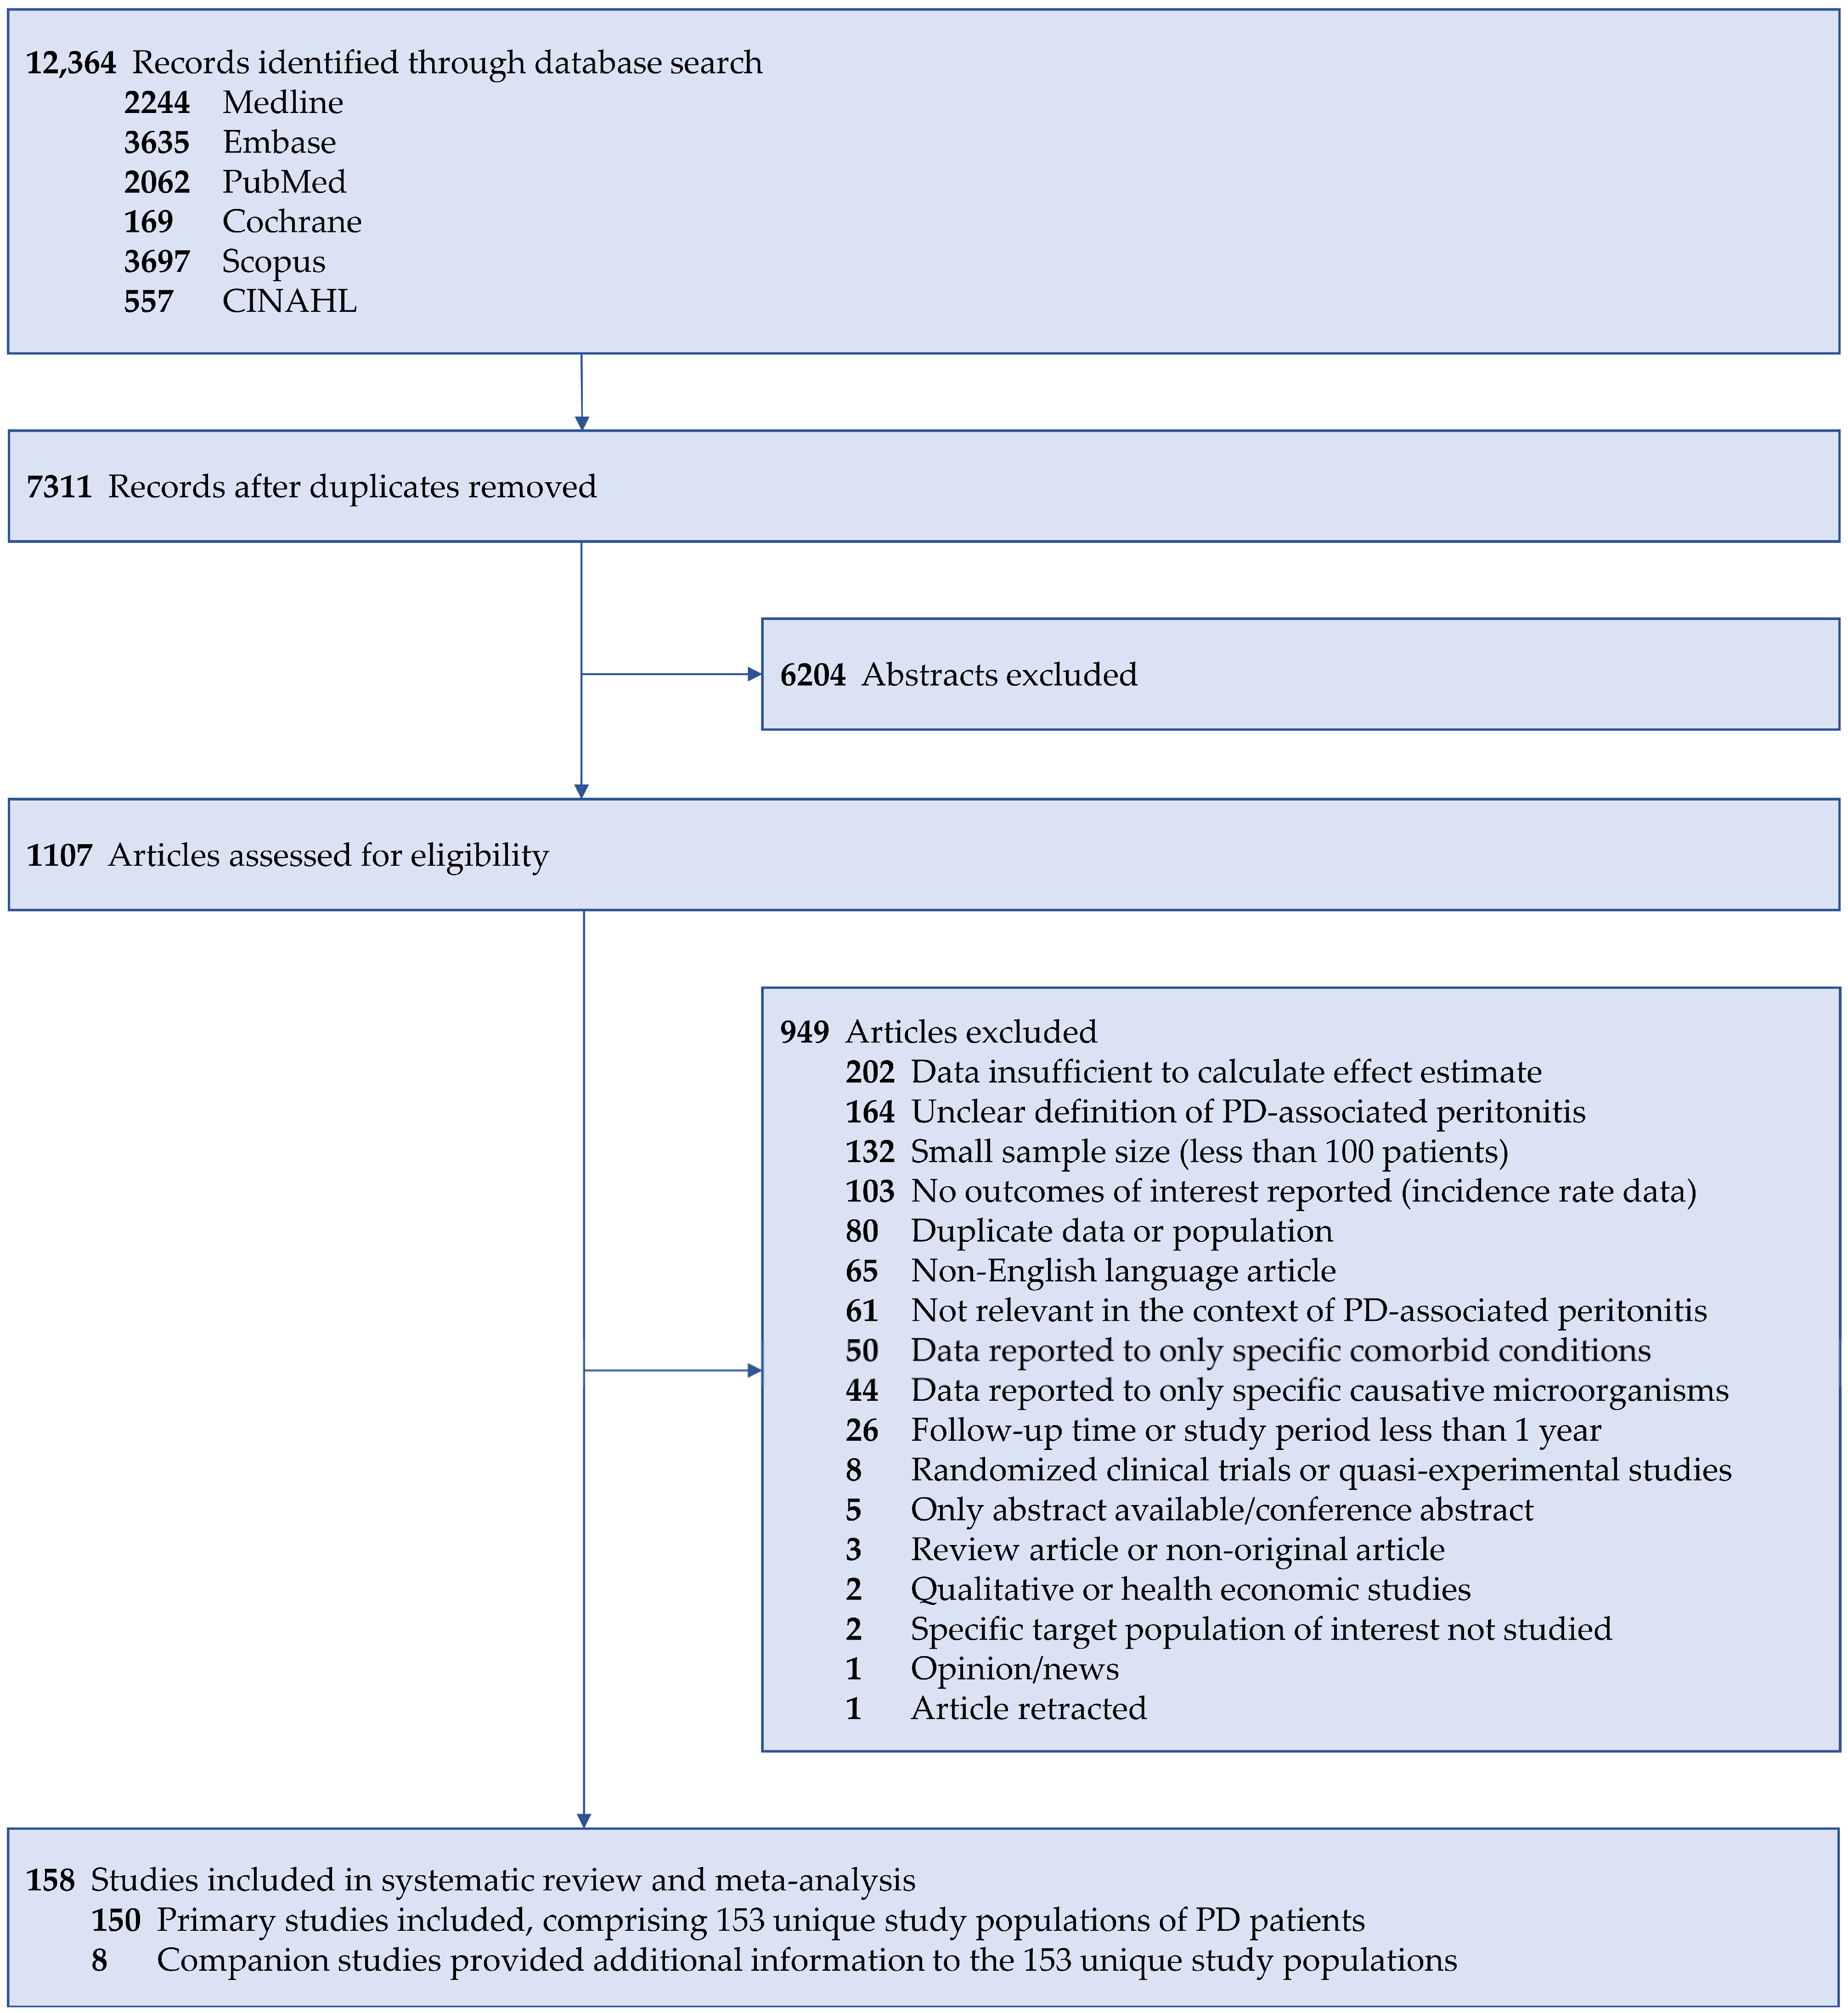
3.1. Search Findings and Study Selection
3.2. Key Features of the Included Study Populations
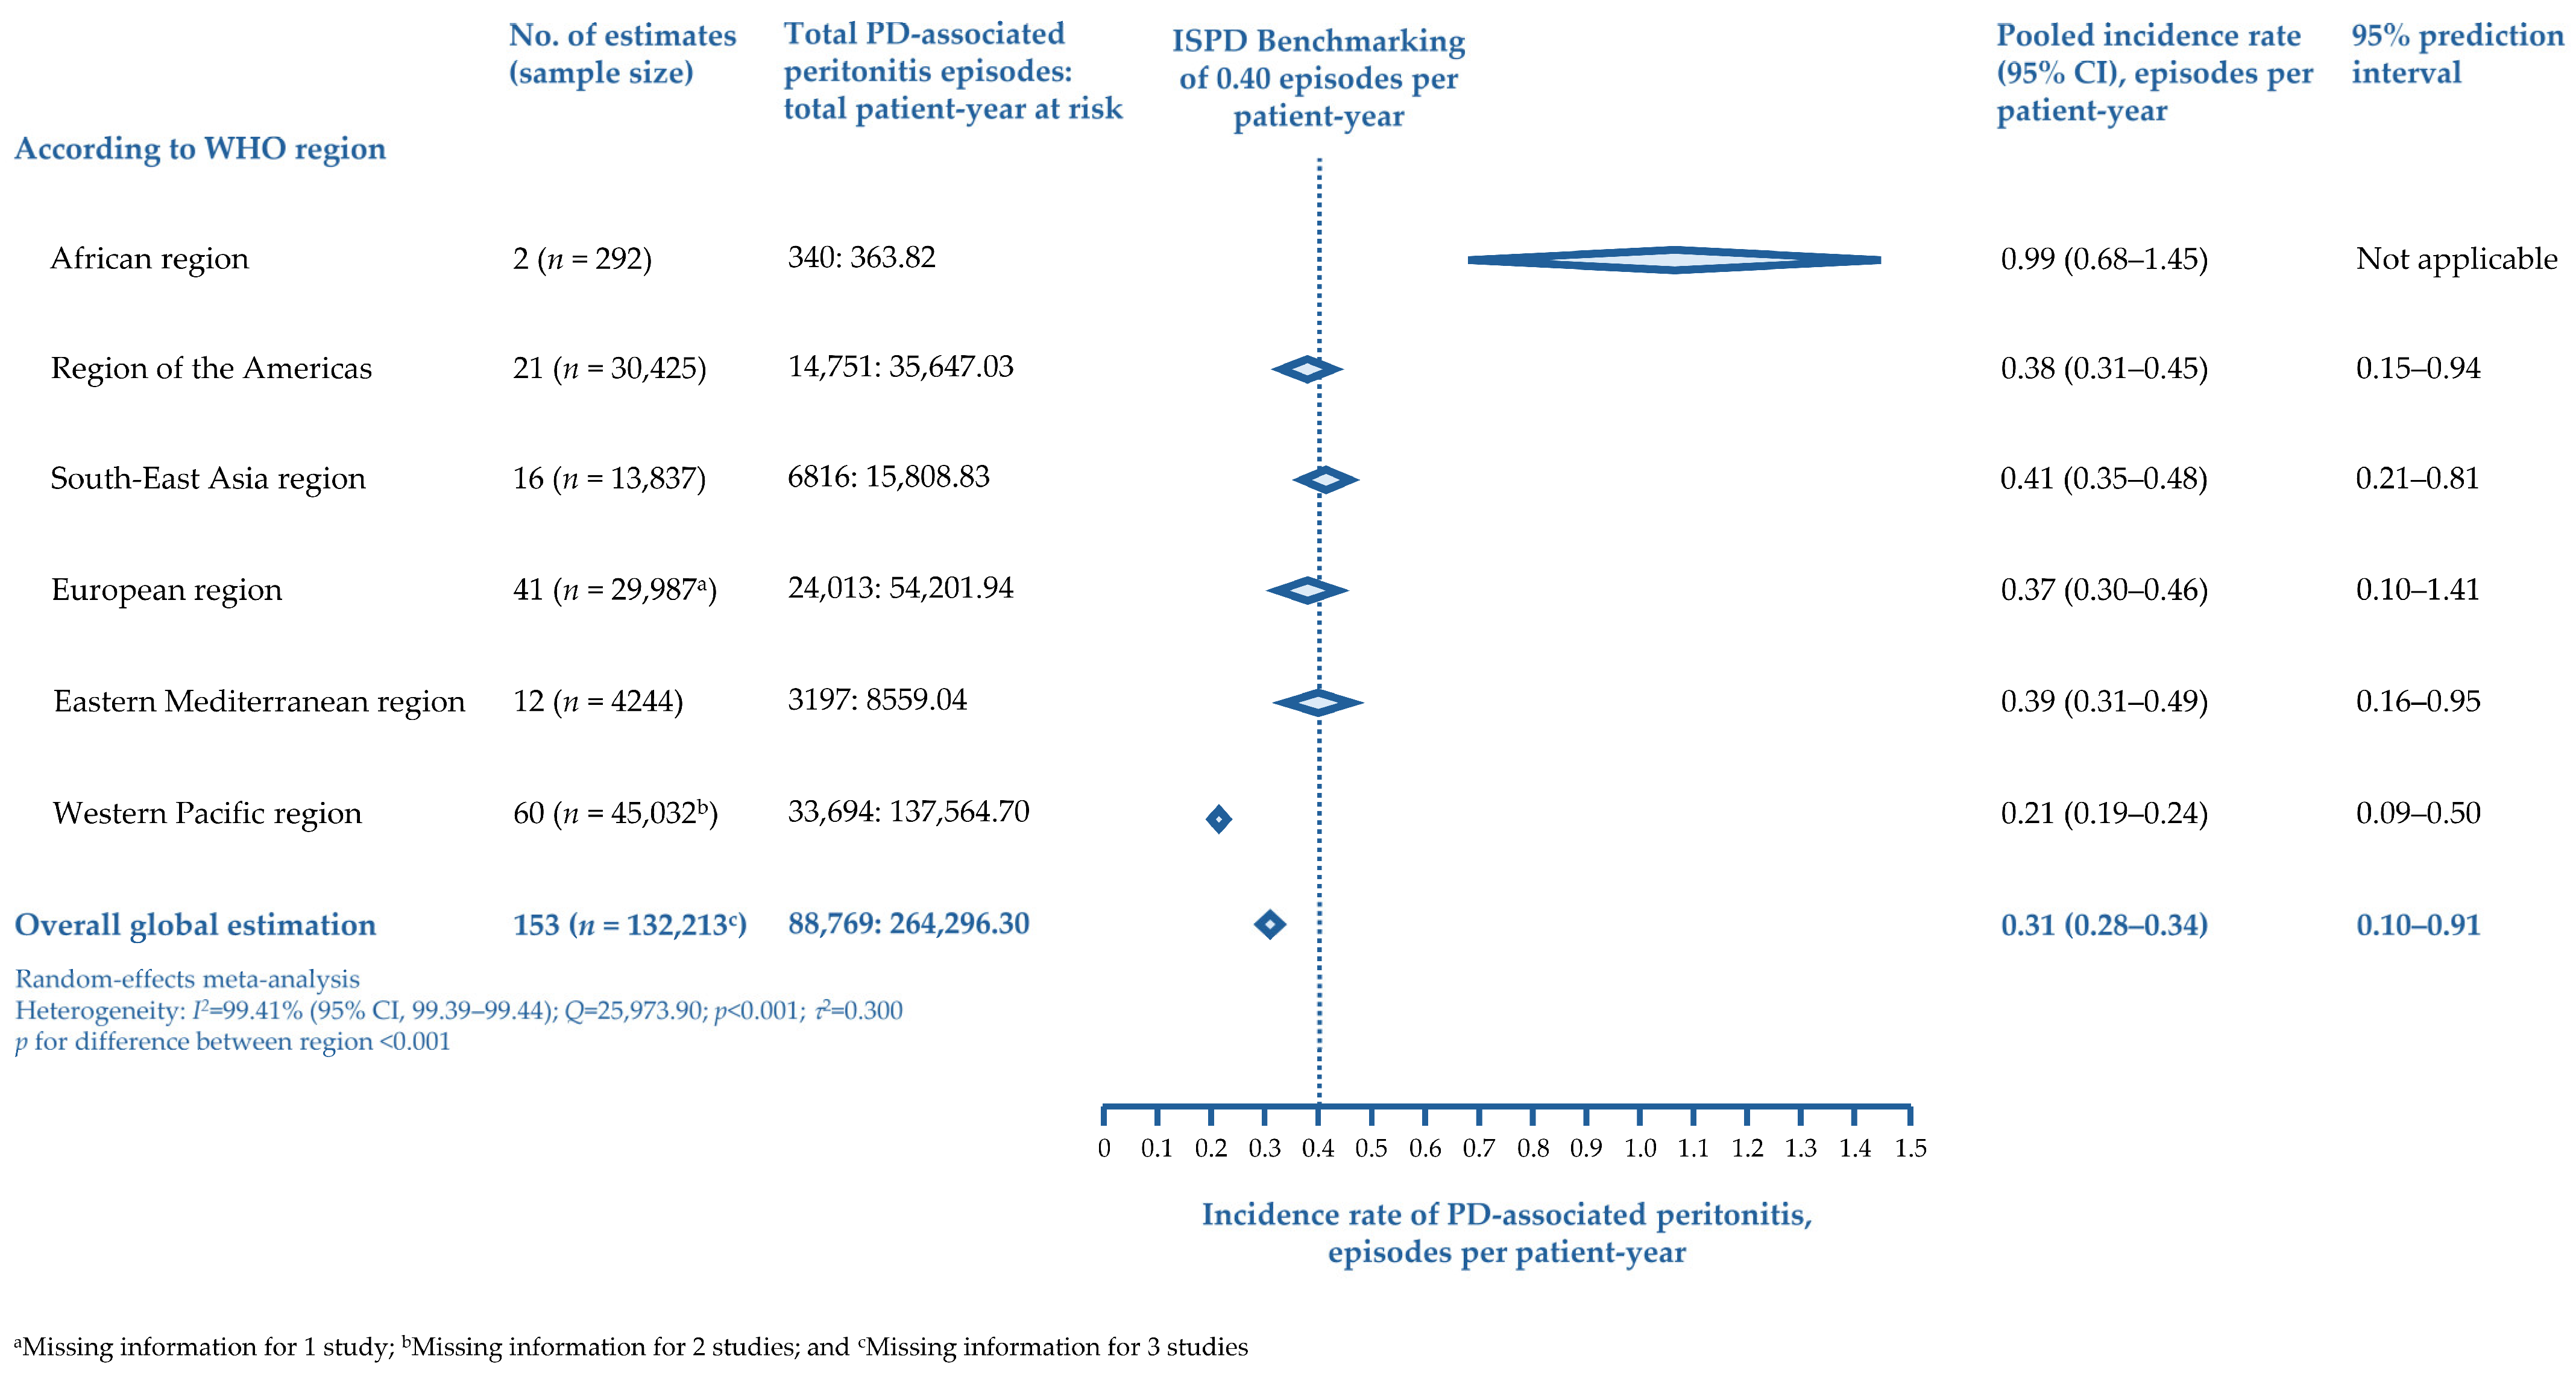
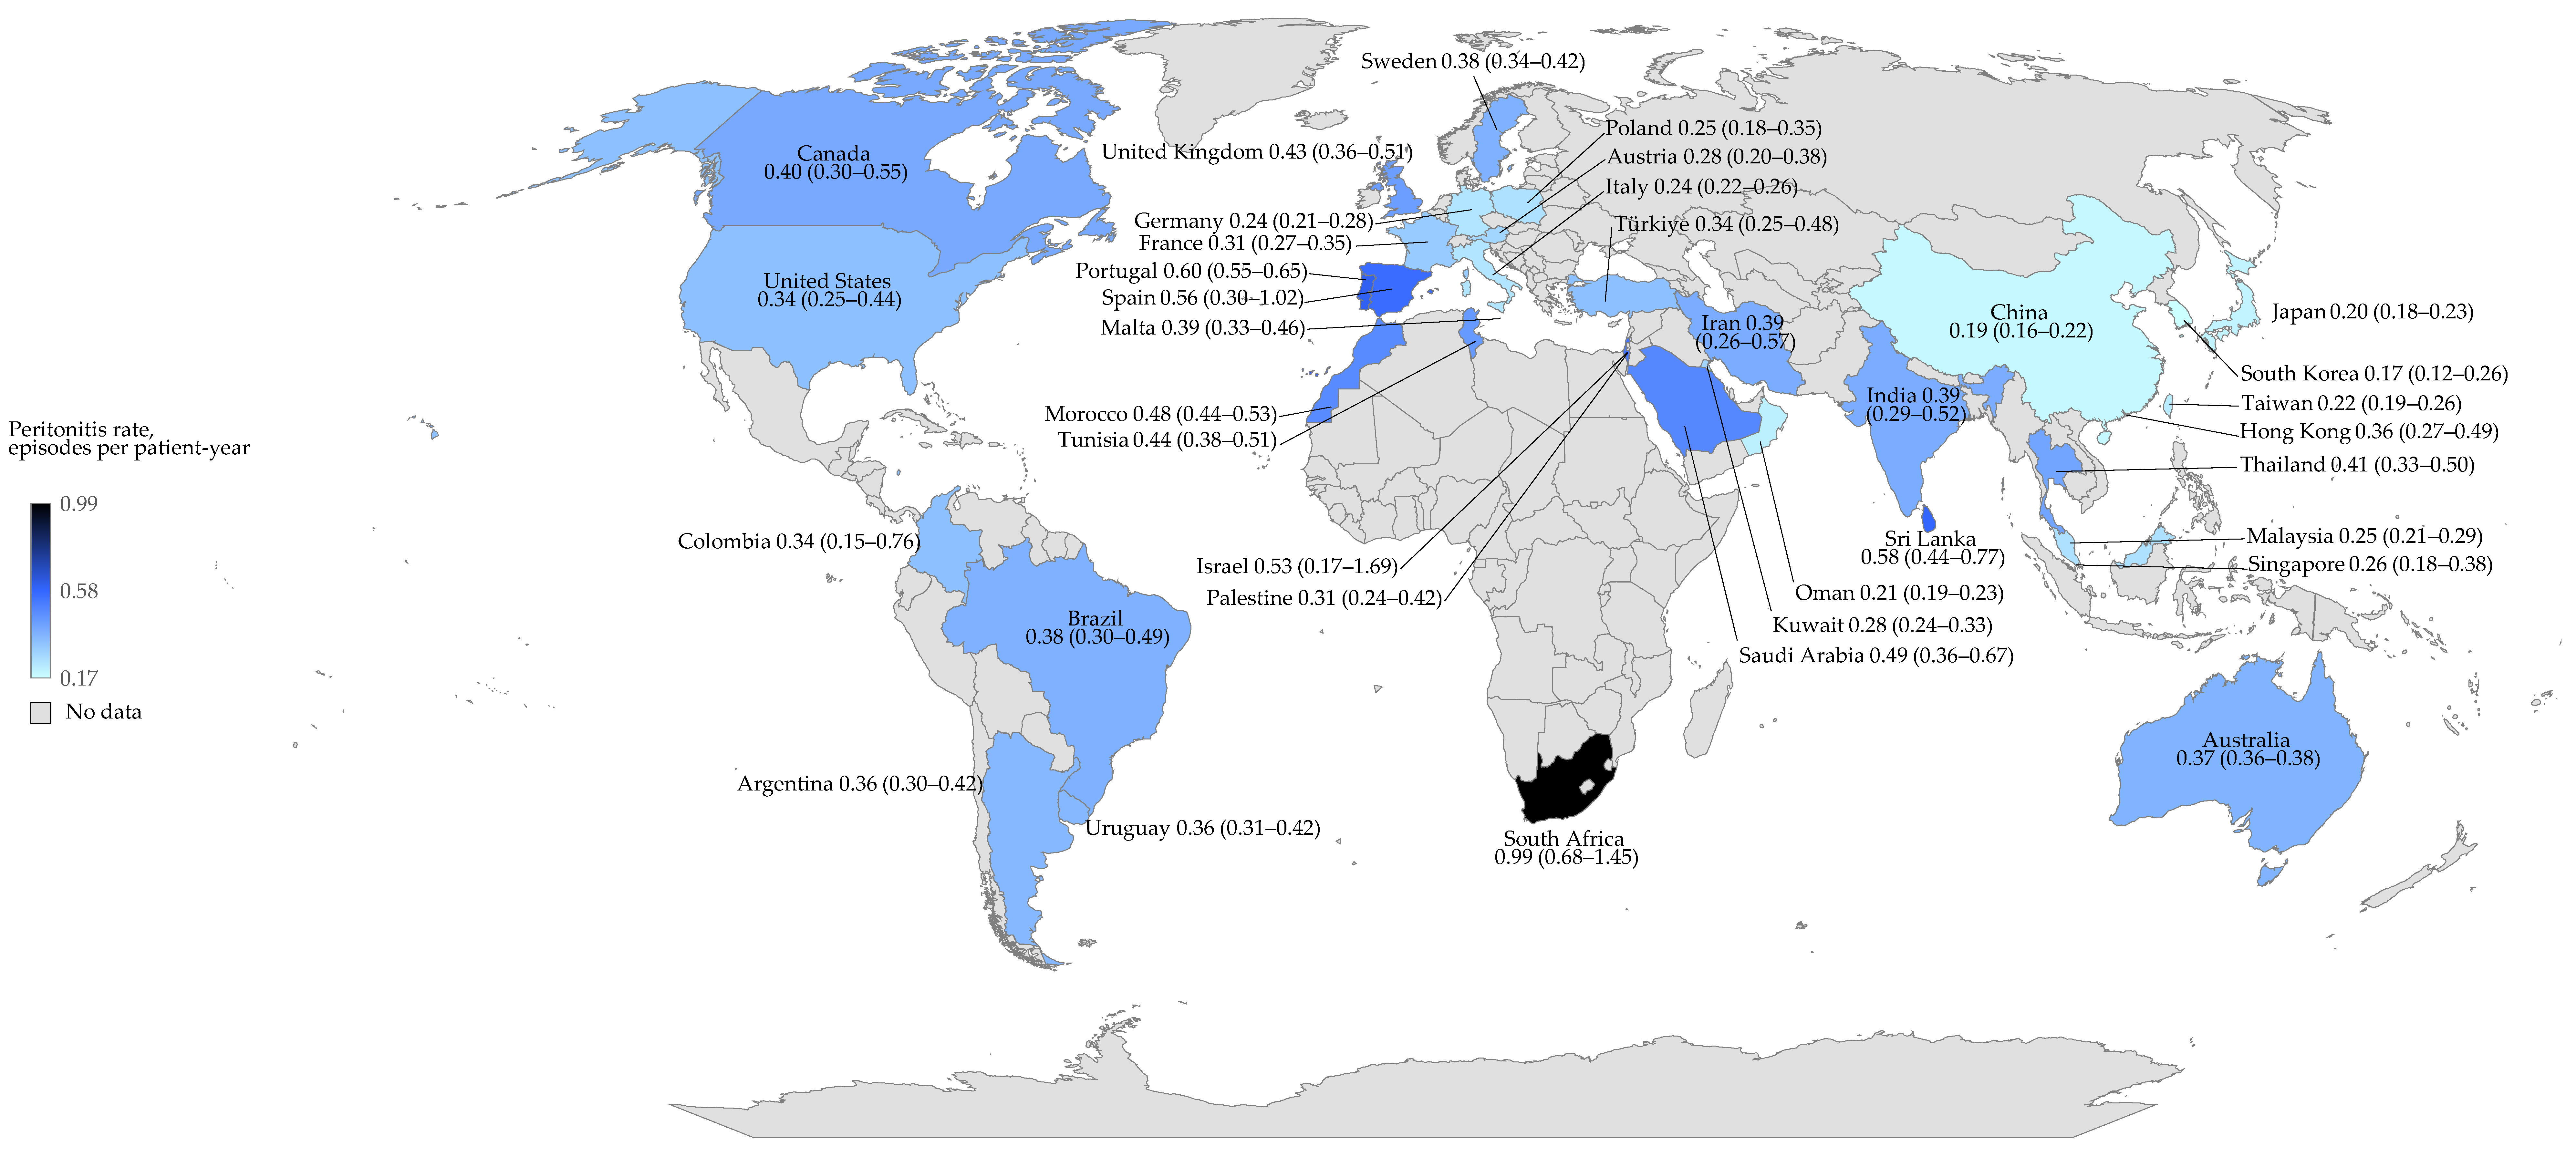
3.3. Global, Regional, and Country Incidence Rate Estimates of PD-Associated Peritonitis
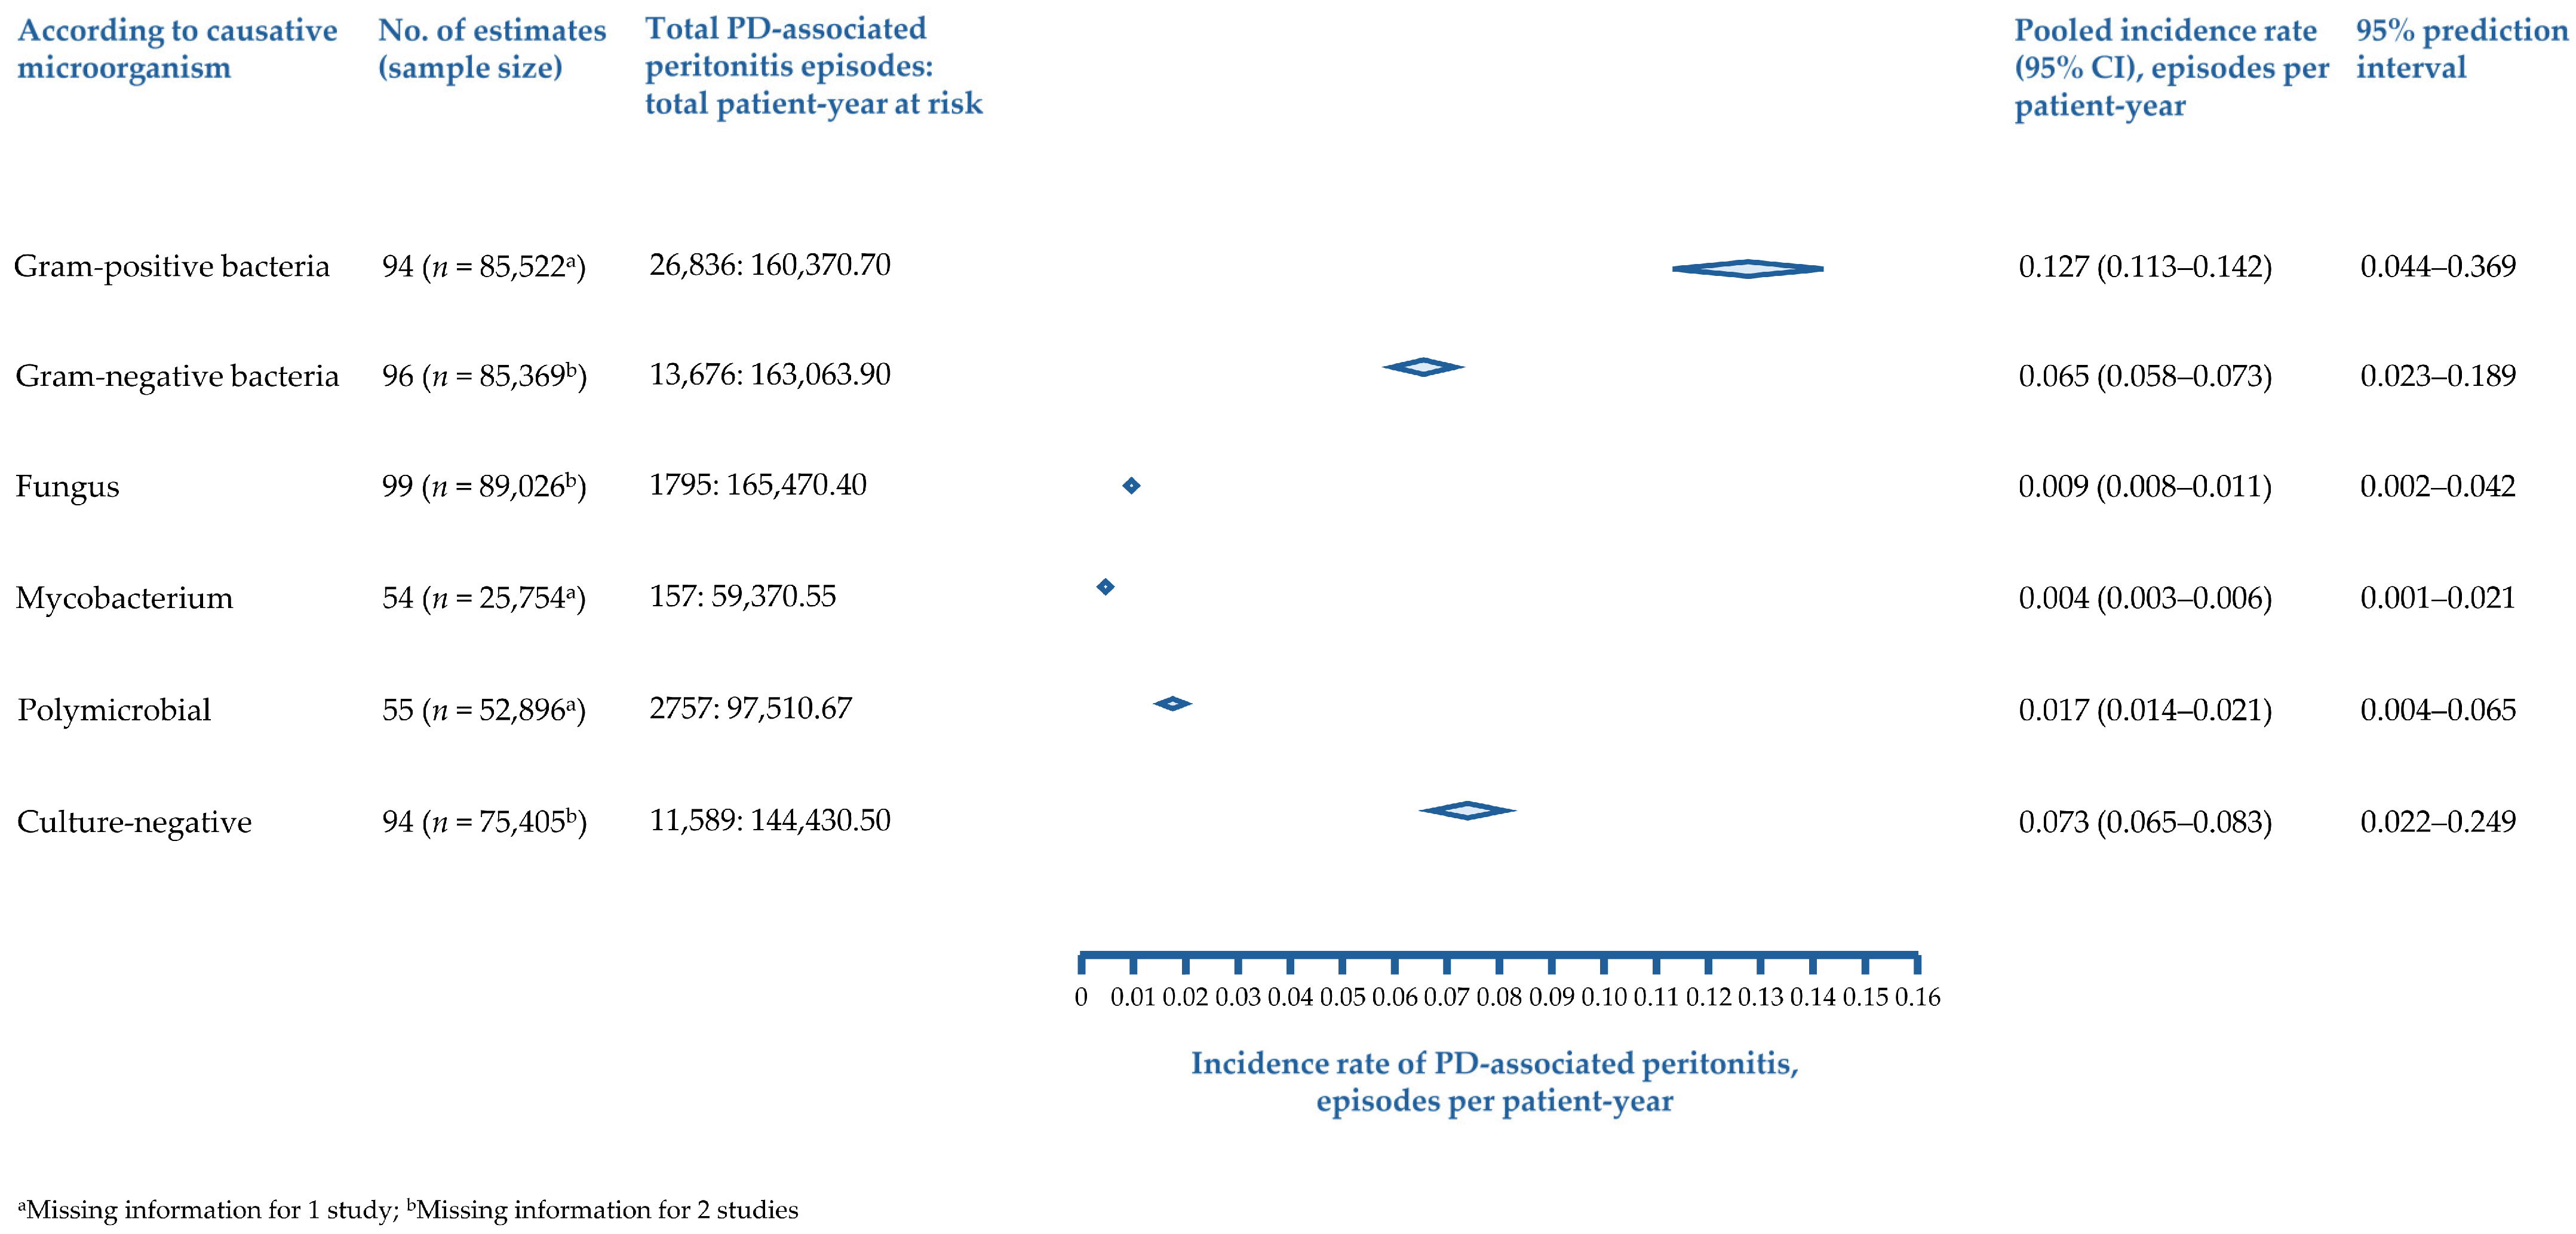
3.4. Causative Microorganism of PD-Associated Peritonitis
3.5. Subgroup Analysis, Sensitivity Analysis, and Assessment of Potential Small-Study Effects
4. Discussion
4.1. Overview of the Findings
4.2. Contextualizing Findings with Relevant Evidence
4.3. Strengths and Limitations
4.4. PD Practice Considerations, Implications for Public Health, and Future Perspectives
5. Conclusions
Supplementary Materials
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
References
- Flythe, J.E.; Watnick, S. Dialysis for Chronic Kidney Failure: A Review. JAMA 2024, 332, 1559–1573. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cho, Y.; Cullis, B.; Ethier, I.; Htay, H.; Jha, V.; Arruebo, S.; Caskey, F.J.; Damster, S.; Donner, J.A.; Levin, A.; et al. Global structures, practices, and tools for provision of chronic peritoneal dialysis. Nephrol. Dial. Transpl. 2024, 39, ii18–ii25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bello, A.K.; Okpechi, I.G.; Osman, M.A.; Cho, Y.; Cullis, B.; Htay, H.; Jha, V.; Makusidi, M.A.; McCulloch, M.; Shah, N.; et al. Epidemiology of peritoneal dialysis outcomes. Nat. Rev. Nephrol. 2022, 18, 779–793. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ngamvichchukorn, T.; Ruengorn, C.; Noppakun, K.; Thavorn, K.; Hutton, B.; Sood, M.M.; Knoll, G.A.; Nochaiwong, S. Association Between Pretransplant Dialysis Modality and Kidney Transplant Outcomes: A Systematic Review and Meta-analysis. JAMA Netw. Open 2022, 5, e2237580. [Google Scholar] [PubMed]
- Yang, F.; Liao, M.; Wang, P.; Yang, Z.; Liu, Y. The Cost-Effectiveness of Kidney Replacement Therapy Modalities: A Systematic Review of Full Economic Evaluations. Appl. Health Econ. Health Policy 2021, 19, 163–180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wulandari, W.; Alfaqeeh, M.; Zakiyah, N.; Shafie, A.A.; Suwantika, A.A. Cost-Utility Analyses of Hemodialysis, Peritoneal Dialysis, and Kidney Transplantation in Patients with End-Stage Kidney Disease: A Systematic Review. Clin. Outcomes Res. 2025, 17, 883–895. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, P.K.; Chow, K.M.; Cho, Y.; Fan, S.; Figueiredo, A.E.; Harris, T.; Kanjanabuch, T.; Kim, Y.L.; Madero, M.; Malyszko, J.; et al. ISPD peritonitis guideline recommendations: 2022 update on prevention and treatment. Perit. Dial. Int. 2022, 42, 110–153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manera, K.E.; Johnson, D.W.; Craig, J.C.; Shen, J.I.; Gutman, T.; Cho, Y.; Wang, A.Y.; Brown, E.A.; Brunier, G.; Dong, J.; et al. Establishing a Core Outcome Set for Peritoneal Dialysis: Report of the SONG-PD (Standardized Outcomes in Nephrology-Peritoneal Dialysis) Consensus Workshop. Am. J. Kidney Dis. 2020, 75, 404–412. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nochaiwong, S.; Ruengorn, C.; Koyratkoson, K.; Thavorn, K.; Awiphan, R.; Chaisai, C.; Phatthanasobhon, S.; Noppakun, K.; Suteeka, Y.; Panyathong, S.; et al. A Clinical Risk Prediction Tool for Peritonitis-Associated Treatment Failure in Peritoneal Dialysis Patients. Sci. Rep. 2018, 8, 14797. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nochaiwong, S.; Noppakun, K.; Sood, M.M.; Thavorn, K.; Knoll, G.A.; Ruengorn, C.; Tantraworasin, A. Association Between Peritoneal Dialysis-Associated Peritonitis and the Risk of All-Cause Mortality and Cardiovascular Death: A Time-Matched Retrospective Cohort Study. Med. Sci. 2025, 13, 249. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cho, Y.; Chow, K.M.; Kam-Tao Li, P.; Runnegar, N.; Johnson, D.W. Peritoneal Dialysis-Related Infections. Clin. J. Am. Soc. Nephrol. 2024, 19, 641–649. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Song, Y.; Wu, J.; Yan, H.; Chen, J. Peritoneal dialysis-associated nontuberculous mycobacterium peritonitis: A systematic review of reported cases. Nephrol. Dial. Transpl. 2012, 27, 1639–1644. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Okpechi, I.G.; Ekrikpo, U.; Moloi, M.W.; Noubiap, J.J.; Okpechi-Samuel, U.S.; Bello, A.K. Prevalence of peritonitis and mortality in patients with ESKD treated with chronic peritoneal dialysis in Africa: A systematic review. BMJ Open 2020, 10, e039970. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marshall, M.R. A systematic review of peritoneal dialysis-related peritonitis rates over time from national or regional population-based registries and databases. Perit. Dial. Int. 2022, 42, 39–47. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Phatthanasobhon, S.; Nochaiwong, S.; Thavorn, K.; Noppakun, K.; Panyathong, S.; Suteeka, Y.; Hutton, B.; Sood, M.M.; Knoll, G.A.; Ruengorn, C. Effectiveness of Renin-Angiotensin-Aldosterone System Blockade on Residual Kidney Function and Peritoneal Membrane Function in Peritoneal Dialysis Patients: A Network Meta-Analysis. Sci. Rep. 2019, 9, 19582. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nochaiwong, S.; Ruengorn, C.; Mongkhon, P.; Thavorn, K.; Awiphan, R.; Noppakun, K.; Vongsanim, S.; Chongruksut, W.; Hutton, B.; Sood, M.M.; et al. Effects of angiotensin-converting enzyme inhibitors or angiotensin receptor blockers on all-cause mortality, cardiovascular death, and cardiovascular events among peritoneal dialysis patients: A protocol for systematic review. Medicine 2020, 99, e19767. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nochaiwong, S.; Ruengorn, C.; Noppakun, K.; Wachiraphansakul, N.; Vongchaiudomchoke, T.; Ngamvichchukorn, T.; Thavorn, K.; Sood, M.M.; Knoll, G.A.; Tantraworasin, A. Exit-site infection and subsequent incident risk of peritoneal dialysis-associated peritonitis: A retrospective cohort study with meta-analysis. Front. Public Health 2026, 14, 1893696. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hoy, D.; Brooks, P.; Woolf, A.; Blyth, F.; March, L.; Bain, C.; Baker, P.; Smith, E.; Buchbinder, R. Assessing risk of bias in prevalence studies: Modification of an existing tool and evidence of interrater agreement. J. Clin. Epidemiol. 2012, 65, 934–939. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DerSimonian, R.; Laird, N. Meta-analysis in clinical trials. Control Clin. Trials 1986, 7, 177–188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Riley, R.D.; Higgins, J.P.; Deeks, J.J. Interpretation of random effects meta-analyses. BMJ 2011, 342, d549. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Higgins, J.P.; Thompson, S.G.; Deeks, J.J.; Altman, D.G. Measuring inconsistency in meta-analyses. BMJ 2003, 327, 557–560. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Borenstein, M.; Higgins, J.P.; Hedges, L.V.; Rothstein, H.R. Basics of meta-analysis: I2 is not an absolute measure of heterogeneity. Res. Synth. Methods 2017, 8, 5–18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Begg, C.B.; Mazumdar, M. Operating characteristics of a rank correlation test for publication bias. Biometrics 1994, 50, 1088–1101. [Google Scholar] [CrossRef] [Scilit]
- Egger, M.; Davey Smith, G.; Schneider, M.; Minder, C. Bias in meta-analysis detected by a simple, graphical test. BMJ 1997, 315, 629–634. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Furuya-Kanamori, L.; Barendregt, J.J.; Doi, S.A.R. A new improved graphical and quantitative method for detecting bias in meta-analysis. Int. J. Evid. Based Healthc. 2018, 16, 195–203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Duval, S.; Tweedie, R. Trim and fill: A simple funnel-plot-based method of testing and adjusting for publication bias in meta-analysis. Biometrics 2000, 56, 455–463. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Balasubramanian, G.; McKitty, K.; Fan, S.L. Comparing automated peritoneal dialysis with continuous ambulatory peritoneal dialysis: Survival and quality of life differences? Nephrol. Dial. Transpl. 2011, 26, 1702–1708. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brown, M.C.; Simpson, K.; Kerssens, J.J.; Mactier, R.A. Peritoneal dialysis-associated peritonitis rates and outcomes in a national cohort are not improving in the post-millennium (2000-2007). Perit. Dial. Int. 2011, 31, 639–650. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davenport, A.; Wellsted, D.; on behalf of the Pan Thames Renal Audit Peritoneal Dialysis Group. Does antifungal prophylaxis with daily oral fluconazole reduce the risk of fungal peritonitis in peritoneal dialysis patients? Pan Thames Ren. Audit. Blood Purif. 2011, 32, 181–185. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, S.T.; Chuang, Y.W.; Cheng, C.H.; Wu, M.J.; Chen, C.H.; Yu, T.M.; Shu, K.H. Evolution of microbiological trends and treatment outcomes in peritoneal dialysis-related peritonitis. Clin. Nephrol. 2011, 75, 416–425. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kanjanabuch, T.; Chancharoenthana, W.; Katavetin, P.; Sritippayawan, S.; Praditpornsilpa, K.; Ariyapitipan, S.; Eiam-Ong, S.; Dhanakijcharoen, P.; Lumlertgul, D. The incidence of peritoneal dialysis-related infection in Thailand: A nationwide survey. J. Med. Assoc. Thail. 2011, 94, S7–S12. [Google Scholar]
- Liawnoraset, W. Prevalence and factors affecting peritonitis in CAPD patients in Maharat Nakhon Ratchasima Hospital under universal coverage scheme during 2008-2010: A three-year experience. J. Med. Assoc. Thail. 2011, 94, S19–S24. [Google Scholar]
- Luvira, V.; Satirapoj, B.; Supasyndh, O.; Chaiprasert, A.; Ruangkanchanasetr, P.; Nata, N.; Kanjanakul, I.; Supaporn, T.; Choovichian, P.; Bijaphala, S.; et al. A single-centre experience: Peritoneal dialysis-related infections in patients on long-term dialysis. J. Med. Assoc. Thail. 2011, 94, S30–S36. [Google Scholar]
- Martin, L.C.; Caramori, J.C.; Fernandes, N.; Divino-Filho, J.C.; Pecoits-Filho, R.; Barretti, P. Geographic and educational factors and risk of the first peritonitis episode in Brazilian Peritoneal Dialysis study (BRAZPD) patients. Clin. J. Am. Soc. Nephrol. 2011, 6, 1944–1951. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muñoz de Bustillo, E.; Borrás, F.; Gómez-Roldán, C.; Pérez-Contreras, F.J.; Olivares, J.; García, R.; Miguel, A. Impact of peritonitis on long-term survival of peritoneal dialysis patients. Nefrologia 2011, 31, 723–732. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oygar, D.D.; Yalin, A.S.; Altiparmak, M.R.; Ataman, R.; Serdengecti, K. Obligatory referral among other factors associated with peritonitis in peritoneal dialysis patients. Nefrologia 2011, 31, 435–440. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Quintanar Lartundo, J.A.; Palomar, R.; Dominguez-Diez, A.; Salas, C.; Ruiz-Criado, J.; Rodrigo, E.; Martinez De Francisco, A.L.; Arias, M. Microbiological profile of peritoneal dialysis peritonitis and predictors of hospitalization. Adv. Perit. Dial. 2011, 27, 38–42. [Google Scholar] [PubMed]
- Topanthanont, S.; Sakulsaengprapha, A. Peritonitis in peritoneal dialysis patients: Ramathibodi Hospital experience. J. Med. Assoc. Thail. 2011, 94, S25–S29. [Google Scholar]
- Aksu, N.; Yavascan, O.; Anil, M.; Kara, O.D.; Bal, A.; Anil, A.B. Chronic peritoneal dialysis in children with special needs or social disadvantage or both: Contraindications are not always contraindications. Perit. Dial. Int. 2012, 32, 424–430. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barone, R.J.; Cámpora, M.I.; Gimenez, N.S.; Ramirez, L.; Panese, S.A.; Santopietro, M. Continuous ambulatory peritoneal dialysis versus automated peritoneal dialysis and peritonitis in the short and very long term at risk. Adv. Perit. Dial. 2012, 28, 44–49. [Google Scholar] [PubMed]
- Basturk, T.; Koc, Y.; Unsal, A.; Ahbap, E.; Sakaci, T.; Yildiz, I.; Kayabasi, H.; Sevinc, M.; Kose, S.; Arar, A. Fungal peritonitis in peritoneal dialysis: A 10 year retrospective analysis in a single center. Eur. Rev. Med. Pharmacol. Sci. 2012, 16, 1696–1700. [Google Scholar] [PubMed]
- Chen, A.; Martz, K.; Rao, P.S. Does allograft failure impact infection risk on peritoneal dialysis: A North American Pediatric Renal Trials and Collaborative Studies Study. Clin. J. Am. Soc. Nephrol. 2012, 7, 153–157. [Google Scholar] [PubMed]
- Levallois, J.; Nadeau-Fredette, A.C.; Labbé, A.C.; Laverdière, M.; Ouimet, D.; Vallée, M. Ten-year experience with fungal peritonitis in peritoneal dialysis patients: Antifungal susceptibility patterns in a North-American center. Int. J. Infect. Dis. 2012, 16, e41–e43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nayak, A.; Karopadi, A.; Antony, S.; Sreepada, S.; Nayak, K.S. Use of a peritoneal dialysis remote monitoring system in India. Perit. Dial. Int. 2012, 32, 200–204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oliveira, L.G.; Luengo, J.; Caramori, J.C.; Montelli, A.C.; de Cunha, M.L.; Barretti, P. Peritonitis in recent years: Clinical findings and predictors of treatment response of 170 episodes at a single Brazilian center. Int. Urol. Nephrol. 2012, 44, 1529–1537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pierce, D.A.; Williamson, J.C.; Mauck, V.S.; Russell, G.B.; Palavecino, E.; Burkart, J.M. The effect on peritoneal dialysis pathogens of changing topical antibiotic prophylaxis. Perit. Dial. Int. 2012, 32, 525–530. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rocha, A.; Rodrigues, A.; Teixeira, L.; Carvalho, M.J.; Mendonça, D.; Cabrita, A. Temporal trends in peritonitis rates, microbiology and outcomes: The major clinical complication of peritoneal dialysis. Blood Purif. 2012, 33, 284–291. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Su, C.Y.; Pei, J.; Lu, X.H.; Tang, W.; Wang, T. Gastrointestinal symptoms predict peritonitis rates in CAPD patients. Clin. Nephrol. 2012, 77, 267–274. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, R.; Chen, Y.; Luo, S.; Li, Y.; Dong, J. The influence of duration of peritoneal dialysis therapy on the outcomes of initial and subsequent peritonitis is different. Perit. Dial. Int. 2012, 32, 473–476. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, R.; Zhuo, M.; Yang, Z.; Dong, J. Experiences with assisted peritoneal dialysis in China. Perit. Dial. Int. 2012, 32, 94–101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yap, D.Y.; Chu, W.L.; Ng, F.; Yip, T.P.; Lui, S.L.; Lo, W.K. Risk factors and outcome of contamination in patients on peritoneal dialysis—A single-center experience of 15 years. Perit. Dial. Int. 2012, 32, 612–616. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yap, D.Y.; To, K.K.; Yip, T.P.; Lui, S.L.; Chan, T.M.; Lai, K.N.; Lo, W.K. Streptococcus bovis peritonitis complicating peritoneal dialysis—A review of 10 years’ experience. Perit. Dial. Int. 2012, 32, 55–59. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chern, Y.B.; Ho, P.S.; Kuo, L.C.; Chen, J.B. Lower education level is a major risk factor for peritonitis incidence in chronic peritoneal dialysis patients: A retrospective cohort study with 12-year follow-up. Perit. Dial. Int. 2013, 33, 552–558. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, J.W.; Lien, Y.C.; Yang, C.Y.; Liu, K.L.; Fang, C.C.; Wu, C.K.; Lee, J.K.; Wu, H.Y.; Chiang, C.K.; Cheng, H.T.; et al. High peritoneal KT/V and peritonitis rates are associated with peritoneal calcification. PLoS ONE 2013, 8, e71636. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kerschbaum, J.; Vychytil, A.; Lhotta, K.; Prischl, F.C.; Wiesholzer, M.; Machhold-Fabrizii, V.; Kopriva-Altfahrt, G.; Schwarz, C.; Balcke, P.; Oberbauer, R.; et al. Treatment with oral active vitamin D is associated with decreased risk of peritonitis and improved survival in patients on peritoneal dialysis. PLoS ONE 2013, 8, e67836. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nessim, S.J.; Komenda, P.; Rigatto, C.; Verrelli, M.; Sood, M.M. Frequency and microbiology of peritonitis and exit-site infection among obese peritoneal dialysis patients. Perit. Dial. Int. 2013, 33, 167–174. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Özbalci, N.; Sezer, M.T.; Koyuncuoǧlu, J.; Ergonul, E.; Yayli, G. Evaluation of peritonitis incidence, etiology, associated factors and prognosis of continuous ambulatory peritoneal dialysis patients. Turk. Nephrol. Dial. Transplant. J. 2013, 22, 158–162. [Google Scholar] [CrossRef] [Scilit]
- Portolés, J.; Janeiro, D.; Lou-Arnal, L.M.; López-Sánchez, P.; Ortega, M.; del Peso, G.; Felipe, C.; Tato, A.M.; Velo, M.; Castellano, I.; et al. First episodes of peritoneal infection: Description and prognostic factors. Nefrologia 2013, 33, 316–324. [Google Scholar] [PubMed]
- Tsai, C.C.; Lee, J.J.; Liu, T.P.; Ko, W.C.; Wu, C.J.; Pan, C.F.; Cheng, S.P. Effects of age and diabetes mellitus on clinical outcomes in patients with peritoneal dialysis-related peritonitis. Surg. Infect. 2013, 14, 540–546. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsieh, Y.P.; Wang, S.C.; Chang, C.C.; Wen, Y.K.; Chiu, P.F.; Yang, Y. The negative impact of early peritonitis on continuous ambulatory peritoneal dialysis patients. Perit. Dial. Int. 2014, 34, 627–635. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Isla, R.A.; Mapiye, D.; Swanepoel, C.R.; Rozumyk, N.; Hubahib, J.E.; Okpechi, I.G. Continuous ambulatory peritoneal dialysis in Limpopo province, South Africa: Predictors of patient and technique survival. Perit. Dial. Int. 2014, 34, 518–525. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, K.V.; Mallikarjuna, H.M.; Gokulnath; Jayanthi, S. Fungal peritonitis in continuous ambulatory peritoneal dialysis: The impact of antifungal prophylaxis on patient and technique outcomes. Indian J. Nephrol. 2014, 24, 297–301. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Najafi, I.; Alatab, S.; Atabak, S.; Majelan, N.N.; Sanadgol, H.; Makhdoomi, K.; Ardalan, M.R.; Azmandian, J.; Shojaee, A.; Keshvari, A.; et al. Seventeen years’ experience of peritoneal dialysis in Iran: First official report of the Iranian peritoneal dialysis registry. Perit. Dial. Int. 2014, 34, 636–642. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nieto-Ríos, J.F.; Díaz-Betancur, J.S.; Arbeláez-Gómez, M.; García-García, Á.; Rodelo-Ceballos, J.; Reino-Buelvas, A.; Serna-Higuita, L.M.; Henao-Sierra, J.E. Peritoneal dialysis-related peritonitis: Twenty-seven years of experience in a Colombian medical center. Nefrologia 2014, 34, 88–95. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nishina, M.; Yanagi, H.; Kakuta, T.; Endoh, M.; Fukagawa, M.; Takagi, A. A 10-year retrospective cohort study on the risk factors for peritoneal dialysis-related peritonitis: A single-center study at Tokai University Hospital. Clin. Exp. Nephrol. 2014, 18, 649–654. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Núñez-Moral, M.; Sánchez-Álvarez, J.E.; González-Díaz, I.; Peláez-Requejo, B.; Quintana-Fernández, A.; Rodríguez-Suárez, C. Seasonal variations and influence of the weather on the appearance of peritoneal infection. Nefrologia 2014, 34, 743–748. [Google Scholar] [PubMed]
- Prasad, K.N.; Singh, K.; Rizwan, A.; Mishra, P.; Tiwari, D.; Prasad, N.; Gupta, A. Microbiology and outcomes of peritonitis in northern India. Perit. Dial. Int. 2014, 34, 188–194. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chang, T.I.; Kang, E.W.; Kim, H.W.; Ryu, G.W.; Park, C.H.; Park, J.T.; Yoo, T.H.; Shin, S.K.; Kang, S.W.; Choi, K.H.; et al. Low Serum Bicarbonate Predicts Residual Renal Function Loss in Peritoneal Dialysis Patients. Medicine 2015, 94, e1276. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Courivaud, C.; Bardonnet, K.; Crepin, T.; Bresson-Vautrin, C.; Rebibou, J.M.; Ducloux, D. Serum immunoglobulin G levels and peritonitis in peritoneal dialysis patients. J. Nephrol. 2015, 28, 511–515. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Figueiredo, A.E.; Moraes, T.P.; Bernardini, J.; Poli-de-Figueiredo, C.E.; Barretti, P.; Olandoski, M.; Pecoits-Filho, R. Impact of patient training patterns on peritonitis rates in a large national cohort study. Nephrol. Dial. Transpl. 2015, 30, 137–142. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lei, Y.; Xiong, Y.; Zhang, L.; Yan, H.; Li, Z.; Cao, L.; Huang, J.; Gu, A.; Ni, Z.; Qian, J.; et al. Comparison of Long-Term Outcomes between Peritoneal Dialysis Patients with Diabetes as a Primary Renal Disease or as a Comorbid Condition. PLoS ONE 2015, 10, e0126549. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ozisik, L.; Ozdemir, F.N.; Tanriover, M.D. The changing trends of peritoneal dialysis related peritonitis and novel risk factors. Ren. Fail. 2015, 37, 1027–1032. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pi, H.C.; Ren, Y.P.; Wang, Q.; Xu, R.; Dong, J. Serum 25-Hydroxyvitamin D Level Could Predict the Risk for Peritoneal Dialysis-Associated Peritonitis. Perit. Dial. Int. 2015, 35, 729–735. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sanabria, M.; Devia, M.; Hernández, G.; Astudillo, K.; Trillos, C.; Uribe, M.; Latorre, C.; Bernal, A.; Rivera, A. Outcomes of a peritoneal dialysis program in remote communities within Colombia. Perit. Dial. Int. 2015, 35, 52–61. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Buttigieg, J.; Borg Cauchi, A.; Rogers, M.; Farrugia, E.; Fava, S. Seasonal Variation in the Peritoneal Dialysis-Related Infections: A Single Center Experience in the Mediterranean. Ther. Apher. Dial. 2016, 20, 501–506. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Duquennoy, S.; Béchade, C.; Verger, C.; Ficheux, M.; Ryckelynck, J.P.; Lobbedez, T. Is Peritonitis Risk Increased in Elderly Patients on Peritoneal Dialysis? Report from the French Language Peritoneal Dialysis Registry (RDPLF). Perit. Dial. Int. 2016, 36, 291–296. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- El-Reshaid, W.; Al-Disawy, H.; Nassef, H.; Alhelaly, U. Comparison of peritonitis rates and patient survival in automated and continuous ambulatory peritoneal dialysis: A 10-year single center experience. Ren. Fail. 2016, 38, 1187–1192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Higuchi, C.; Ito, M.; Masakane, I.; Sakura, H. Peritonitis in peritoneal dialysis patients in Japan: A 2013 retrospective questionnaire survey of Japanese Society for Peritoneal Dialysis member institutions. Ren. Replace. Ther. 2016, 2, 2. [Google Scholar] [CrossRef] [Scilit]
- Kotera, N.; Tanaka, M.; Aoe, M.; Chikamori, M.; Honda, T.; Ikenouchi, A.; Miura, R.; Sugahara, M.; Furuse, S.; Saito, K.; et al. Age-Related Differences of Organism-Specific Peritonitis Rates: A Single-Center Experience. Ther. Apher. Dial. 2016, 20, 655–660. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mizuno, M.; Ito, Y.; Suzuki, Y.; Sakata, F.; Saka, Y.; Hiramatsu, T.; Tamai, H.; Mizutani, M.; Naruse, T.; Ohashi, N.; et al. Recent analysis of status and outcomes of peritoneal dialysis in the Tokai area of Japan: The second report of the Tokai peritoneal dialysis registry. Clin. Exp. Nephrol. 2016, 20, 960–971. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakao, M.; Yamamoto, I.; Maruyama, Y.; Nakashima, A.; Matsuo, N.; Tanno, Y.; Ohkido, I.; Ikeda, M.; Yamamoto, H.; Yokoyama, K.; et al. 33 Years of Peritoneal Dialysis-Associated Peritonitis: A Single-Center Study in Japan. Ther. Apher. Dial. 2016, 20, 60–65. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pai, M.F.; Yang, J.Y.; Chen, H.Y.; Hsu, S.P.; Chiu, Y.L.; Wu, H.Y.; Tsai, W.C.; Peng, Y.S. Comparing long-term outcomes between early and delayed initiation of peritoneal dialysis following catheter implantation. Ren. Fail. 2016, 38, 875–881. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pérez-Fontan, M.; Machado Lopes, D.; García Enríquez, A.; López-Calviño, B.; López-Muñiz, A.; García Falcón, T.; Rodríguez-Carmona, A. Inhibition of Gastric Acid Secretion by H2 Receptor Antagonists Associates a Definite Risk of Enteric Peritonitis and Infectious Mortality in Patients Treated with Peritoneal Dialysis. PLoS ONE 2016, 11, e0148806. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Perl, J.; Parpia, S.; Nessim, S.J. Does the risk of peritoneal dialysis-associated peritonitis vary by time on treatment? Clin. Nephrol. 2016, 85, 209–214. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sandrini, M.; Vizzardi, V.; Valerio, F.; Ravera, S.; Manili, L.; Zubani, R.; Lucca, B.J.; Cancarini, G. Incremental peritoneal dialysis: A 10 year single-centre experience. J. Nephrol. 2016, 29, 871–879. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Santhakumaran, T.; Samad, N.; Fan, S.L. Hydration status measured by BCM: A potential modifiable risk factor for peritonitis in patients on peritoneal dialysis. Nephrology 2016, 21, 404–409. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shea, Y.F.; Lam, M.F.; Lee, M.S.; Mok, M.Y.; Lui, S.L.; Yip, T.P.; Lo, W.K.; Chu, L.W.; Chan, T.M. Prevalence of Cognitive Impairment Among Peritoneal Dialysis Patients, Impact on Peritonitis and Role of Assisted Dialysis. Perit. Dial. Int. 2016, 36, 284–290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tian, Y.; Xie, X.; Xiang, S.; Yang, X.; Zhang, X.; Shou, Z.; Chen, J. Risk factors and outcomes of high peritonitis rate in continuous ambulatory peritoneal dialysis patients: A retrospective study. Medicine 2016, 95, e5569. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alatab, S.; Najafi, I.; Pourmand, G.; Hosseini, M.; Shekarchian, S. Risk factors of severe peritoneal sclerosis in chronic peritoneal dialysis patients. Ren. Fail. 2017, 39, 32–39. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Htay, H.; Johnson, D.W.; Wu, S.Y.; Oei, E.L.; Foo, M.W.Y.; Choo, J.C.J. Comparison of Topical Chlorhexidine and Mupirocin for the Prevention of Exit-Site Infection in Incident Peritoneal Dialysis Patients. Perit. Dial. Int. 2017, 37, 266–272. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, S.M.; Son, Y.K.; Kim, S.E.; An, W.S. Clinical Outcomes of Peritoneal Dialysis in End-Stage Renal Disease Patients with Liver Cirrhosis: A Propensity Score Matching Study. Perit. Dial. Int. 2017, 37, 314–320. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ndlovu, K.C.; Sibanda, W.; Assounga, A. Peritonitis outcomes in patients with HIV and end-stage renal failure on peritoneal dialysis: A prospective cohort study. BMC Nephrol. 2017, 18, 48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ong, L.M.; Ch’ng, C.C.; Wee, H.C.; Supramaniam, P.; Zainal, H.; Goh, B.L.; Bavanandan, S.; Mushahar, L.; Hooi, L.S.; Ahmad, G. Risk of Peritoneal Dialysis-Related Peritonitis in a Multi-Racial Asian Population. Perit. Dial. Int. 2017, 37, 35–43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vargas, E.; Blake, P.G.; Sanabria, M.; Bunch, A.; López, P.; Vesga, J.; Buitrago, A.; Astudillo, K.; Devia, M.; Sánchez, R. Early Peritonitis in a Large Peritoneal Dialysis Provider System in Colombia. Perit. Dial. Int. 2017, 37, 30–34. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al Wakeel, J.S.; Al Ghonaim, M.A.; Aldohayan, A.; Usama, S.; Al Obaili, S.; Tarakji, A.R.; Alkhowaiter, M. Appraising the outcome and complications of peritoneal dialysis patients in self-care peritoneal dialysis and assisted peritoneal dialysis: A 5-year review of a single Saudi center. Saudi J. Kidney Dis. Transpl. 2018, 29, 71–80. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fang, P.; Lu, J.; Liu, Y.H.; Deng, H.M.; Zhang, L.; Zhang, H.Q. Benefit of an operating vehicle preventing peritonitis in peritoneal dialysis patients: A retrospective, case-controlled study. Int. Urol. Nephrol. 2018, 50, 1163–1170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsu, C.K.; Lee, C.C.; Chen, Y.T.; Ting, M.K.; Sun, C.Y.; Chen, C.Y.; Hsu, H.J.; Chen, Y.C.; Wu, I.W. Multidisciplinary predialysis education reduces incidence of peritonitis and subsequent death in peritoneal dialysis patients: 5-year cohort study. PLoS ONE 2018, 13, e0202781. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ponce, D.; de Moraes, T.P.; Pecoits-Filho, R.; Figueiredo, A.E.; Barretti, P. Peritonitis in Children on Chronic Peritoneal Dialysis: The Experience of a Large National Pediatric Cohort. Blood Purif. 2018, 45, 118–125. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rope, R.; Nanayakkara, N.; Wazil, A.; Dickowita, S.; Abeyeskera, R.; Gunerathne, L.; Adoosoriya, D.; Karunasena, N.; Rathnayake, C.; Anand, S.; et al. Expanding CAPD in Low-Resource Settings: A Distance Learning Approach. Perit. Dial. Int. 2018, 38, 343–348. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wojtaszek, E.; Grzejszczak, A.; Grygiel, K.; Małyszko, J.; Matuszkiewicz-Rowińska, J. Urgent-Start Peritoneal Dialysis as a Bridge to Definitive Chronic Renal Replacement Therapy: Short- and Long-Term Outcomes. Front. Physiol. 2018, 9, 1830. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alfayez, S.M.; Alsaqoub, S.M.; Qattan, A.Y.; Alghamdi, M.A.; Elfeky, D.S.; Alrowaie, F.A.; Aljasser, D.S.; Syed, S.B. Peritoneal dialysis related infections in a tertiary care hospital in Riyadh, Saudi Arabia. Saudi Med. J. 2019, 40, 147–151. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Balzer, M.S.; Claus, R.; Haller, H.; Hiss, M. Are ISPD Guidelines on Peritonitis Diagnosis Too Narrow? A 15-Year Retrospective Single-Center Cohort Study on PD-Associated Peritonitis Accounting for Untrained Patients. Perit. Dial. Int. 2019, 39, 220–228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Einbinder, Y.; Cohen-Hagai, K.; Shitrit, P.; Zitman-Gal, T.; Erez, D.; Benchetrit, S.; Korzets, Z.; Kotliroff, A. ISPD guideline-driven retraining, exit site care and decreased peritonitis: A single-center experience in Israel. Int. Urol. Nephrol. 2019, 51, 723–727. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gadola, L.; Poggi, C.; Dominguez, P.; Poggio, M.V.; Lungo, E.; Cardozo, C. Risk Factors and Prevention of Peritoneal Dialysis-Related Peritonitis. Perit. Dial. Int. 2019, 39, 119–125. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hu, S.; Tong, R.; Bo, Y.; Ming, P.; Yang, H. Fungal peritonitis in peritoneal dialysis: 5-year review from a North China center. Infection 2019, 47, 35–43. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jahromi, S.E.; Ahmed, F.; Pourahmad, S.; Roozbeh, J.; Najafi, I.; Ebrahimi, V. Predictors of peritoneal dialysis associated peritonitis; application of the zero-inflated negative binomial model. J. Nephropathol. 2019, 8, e36. [Google Scholar] [CrossRef] [Scilit]
- Karthikeyan, B.; Sharma, R.K.; Kaul, A.; Gupta, A.; Prasad, N.; Bhadauria, D.S. Clinical Characteristics, Patient and Technique Survival in Elderly Patients on Peritoneal Dialysis. Indian J. Nephrol. 2019, 29, 334–339. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lasfar, L.B.; Guedri, Y.; Zellama, D.; El Meknassi, I.; Azzebi, A.; Mrabet, S.; Fradi, A.; Toumi, S.; Sabri, F.; Amor, S.B.; et al. Long-term clinical outcomes of peritoneal dialysis patients: 10-year experience of a single unit from Tunisia. Saudi J. Kidney Dis. Transpl. 2019, 30, 451–461. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liao, J.L.; Zhang, Y.H.; Xiong, Z.B.; Hao, L.; Liu, G.L.; Ren, Y.P.; Wang, Q.; Duan, L.P.; Zheng, Z.X.; Xiong, Z.Y.; et al. The Association of Cognitive Impairment with Peritoneal Dialysis-Related Peritonitis. Perit. Dial. Int. 2019, 39, 229–235. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lichodziejewska-Niemierko, M.; Chmielewski, M.; Wojtaszek, E.; Suchowierska, E.; Gołembiewska, E.; Grajewska, M.; Matuszkiewicz-Rowińska, J.; Naumnik, B.; Sulikowska, B.; Niemczyk, S.; et al. Current epidemiology and practice patterns in prevention and treatment of PD-related infections in Poland. Int. Urol. Nephrol. 2019, 51, 335–341. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, H.H.; Huang, C.H.; Kuo, M.C.; Lin, S.Y.; Hsu, C.H.; Lee, C.Y.; Chiu, Y.W.; Chen, Y.H.; Lu, P.L. Microbiology of peritoneal dialysis-related infection and factors of refractory peritoneal dialysis related peritonitis: A ten-year single-center study in Taiwan. J. Microbiol. Immunol. Infect. 2019, 52, 752–759. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bonnal, H.; Bechade, C.; Boyer, A.; Lobbedez, T.; Guillouët, S.; Verger, C.; Ficheux, M.; Lanot, A. Effects of educational practices on the peritonitis risk in peritoneal dialysis: A retrospective cohort study with data from the French peritoneal Dialysis registry (RDPLF). BMC Nephrol. 2020, 21, 205. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hwang, T.Y.; Kim, M.G.; Oh, S.W.; Jo, S.K.; Cho, W.Y.; Yang, J. Pathogens of peritoneal dialysis peritonitis: Trends from a single-center experience over 15 years. Kidney Res. Clin. Pract. 2020, 39, 221–227. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ma, X.; Shi, Y.; Tao, M.; Jiang, X.; Wang, Y.; Zang, X.; Fang, L.; Jiang, W.; Du, L.; Jin, D.; et al. Analysis of risk factors and outcome in peritoneal dialysis patients with early-onset peritonitis: A multicentre, retrospective cohort study. BMJ Open 2020, 10, e029949. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Noppakun, K.; Kasemset, T.; Wongsawad, U.; Ruengorn, C.; Thavorn, K.; Sood, M.M.; Nochaiwong, S. Changes in serum albumin concentrations during transition to dialysis and subsequent risk of peritonitis after peritoneal dialysis initiation: A retrospective cohort study. J. Nephrol. 2020, 33, 1275–1287. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Perl, J.; Fuller, D.S.; Bieber, B.A.; Boudville, N.; Kanjanabuch, T.; Ito, Y.; Nessim, S.J.; Piraino, B.M.; Pisoni, R.L.; Robinson, B.M.; et al. Peritoneal Dialysis-Related Infection Rates and Outcomes: Results from the Peritoneal Dialysis Outcomes and Practice Patterns Study (PDOPPS). Am. J. Kidney Dis. 2020, 76, 42–53. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Santos, J.E.; Rodríguez Magariños, C.; García Gago, L.; Astudillo Jarrín, D.; Pértega, S.; Rodríguez-Carmona, A.; García Falcón, T.; Pérez Fontán, M. Long-term trends in the incidence of peritoneal dialysis-related peritonitis disclose an increasing relevance of streptococcal infections: A longitudinal study. PLoS ONE 2020, 15, e0244283. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tekkarişmaz, N.; Torun, D. Long-term clinical outcomes of peritoneal dialysis patients: 9-year experience of a single centre in Turkey. Turk. J. Med. Sci. 2020, 50, 386–397. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Viglino, G.; Neri, L.; Barbieri, S.; Tortone, C. Videodialysis: A pilot experience of telecare for assisted peritoneal dialysis. J. Nephrol. 2020, 33, 177–182. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zeng, Y.; Jiang, X.; Feng, S.; Jiang, L.; Wang, Z.; Shen, H.; Jiang, S. The influence of seasonal factors on the incidence of peritoneal dialysis-associated peritonitis. Ren. Fail. 2020, 42, 807–817. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- AlZabli, S.M.; Alsuhaibani, M.A.; BinThunian, M.A.; Alshahrani, D.A.; Al Anazi, A.; Varghese, S.; Rose, V.; Rahim, K.A. Peritonitis in children on peritoneal dialysis: 12 years of tertiary center experience. Int. J. Pediatr. Adolesc. Med. 2021, 8, 229–235. [Google Scholar] [PubMed]
- de la Espada Piña, V.; Ganga, P.L.Q.; Junquero, J.M.G.; Fosalba, N.A.; Girón, F.F.; Huete, M.J.E.; Ortega, M.P.; Barrero, G.V.; Salazar, A.M.; Martínez, F.M.; et al. Two decades of analysis of peritonitis in peritoneal dialysis in Andalusia: Epidemiological, clinical, microbiological and progression aspects. Nefrologia 2021, 41, 417–425. [Google Scholar] [PubMed]
- Htay, H.; Choo, J.C.J.; Johnson, D.W.; Pascoe, E.M.; Jayaballa, M.; Oei, E.L.; Ng, L.C.; Wu, S.Y.; Foo, M.W.Y. Chlorhexidine-impregnated sponge dressing for prevention of catheter exit-site infection in peritoneal dialysis patients: A pilot study. Int. Urol. Nephrol. 2021, 53, 803–812. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hu, J.; Zhang, H.; Yi, B. Peritoneal transport status and first episode of peritonitis: A large cohort study. Ren. Fail. 2021, 43, 1094–1103. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kang, M.; Kim, Y.L.; Kang, E.; Ryu, H.; Kim, Y.C.; Kim, D.K.; Lee, H.; Han, S.S.; Joo, K.W.; Kim, Y.S.; et al. Evolving outcomes of peritoneal dialysis: Secular trends at a single large center over three decades. Kidney Res. Clin. Pract. 2021, 40, 472–483. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, R.; Zhang, D.; He, J.; Ou, J.; Zhang, L.; Hu, X.; Wu, J.; Liu, H.; Peng, Y.; Xu, Y.; et al. Characteristics Analysis, Clinical Outcome and Risk Factors for Fungal Peritonitis in Peritoneal Dialysis Patients: A 10-Year Case-Control Study. Front. Med. 2021, 8, 774946. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, D.; Lin, Y.; Gong, N.; Xiao, Z.; Zhang, F.; Zhong, X.; Yi, Z.; Yang, C.; Zhang, G.; Ai, J. Degree and duration of hypokalemia associated with peritonitis in patients undergoing peritoneal dialysis. Int. J. Clin. Pract. 2021, 75, e14188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neu, A.M.; Richardson, T.; De Souza, H.G.; Mahon, A.R.; Keswani, M.; Zaritsky, J.; Munshi, R.; Swartz, S.; Sethna, C.B.; Somers, M.J.G.; et al. Continued reduction in peritonitis rates in pediatric dialysis centers: Results of the Standardizing Care to Improve Outcomes in Pediatric End Stage Renal Disease (SCOPE) Collaborative. Pediatr. Nephrol. 2021, 36, 2383–2391. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oki, R.; Tsuji, S.; Hamasaki, Y.; Komaru, Y.; Miyamoto, Y.; Matsuura, R.; Yamada, D.; Doi, K.; Kume, H.; Nangaku, M. Time until treatment initiation is associated with catheter survival in peritoneal dialysis-related peritonitis. Sci. Rep. 2021, 11, 6547. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sakurada, T.; Fujishima, R.; Yamada, S.; Kohatsu, K.; Kojima, S.; Koitabashi, K.; Shibagaki, Y. Seasonality of peritoneal dialysis-related peritonitis in Japan: A single-center, 10-year study. Clin. Exp. Nephrol. 2021, 25, 52–57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Song, Q.; Yan, H.; Yu, Z.; Li, Z.; Yuan, J.; Ni, Z.; Fang, W. Assisted peritoneal dialysis: A feasible KRT modality for frail older patients with end-stage kidney disease (ESKD). Sci. Rep. 2021, 11, 14928. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tangjittrong, K. Risk Factors for The First Episode of Peritonitis in Continuous Ambulatory Peritoneal Dialysis Patients in Pranangklao Hospital. J. Med. Assoc. Thail. 2021, 104, 1966–1970. [Google Scholar] [CrossRef] [Scilit]
- Witoon, R.; Yongsiri, S.; Wanitchanont, A.; Chaivanit, P. Effect of glomerular filtration rate at peritoneal dialysis initiation on clinical outcomes: A retrospective cohort study. J. Med. Assoc. Thail. 2021, 104, 10–17. [Google Scholar] [CrossRef] [Scilit]
- Cheikh Hassan, H.I.; Murali, K.; Lonergan, M.; Boudville, N.; Johnson, D.; Borlace, M.; Chen, J.H.C. Association of Peritonitis with Cardiovascular Mortality over Time in the Peritoneal Dialysis Population: An Australia and New Zealand Dialysis and Transplant Registry Study. Kidney Int. Rep. 2022, 7, 2388–2396. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kanjanabuch, T.; Puapatanakul, P.; Halue, G.; Lorvinitnun, P.; Tangjittrong, K.; Pongpirul, K.; Narenpitak, S.; Boonyakrai, C.; Tatiyanupanwong, S.; Chieochanthanakij, R.; et al. Implementation of PDOPPS in a middle-income country: Early lessons from Thailand. Perit. Dial. Int. 2022, 42, 83–91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kolland, M.; Ribitsch, W.; Prenner, A.; Buchgraber, J.; Odler, B.; Krause, R.; Rosenkranz, A.R. Effluent microscopy is a useful adjuvant diagnostic tool in peritoneal dialysis-associated peritonitis. Clin. Nephrol. 2022, 98, 33–41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lau, S.Y.; Bee, B.C.; Wong, H.S.; Omar, M.S.; Bahari, N. Predictive Factors, Treatment, and Outcomes of Coagulase-Negative Staphylococcal Peritonitis in Malaysian Peritoneal Dialysis Patients: A Single-Center Study. Int. J. Nephrol. 2022, 2022, 8985178. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Melanson, J.; Kachmar, J.; Laurin, L.P.; Elftouh, N.; Nadeau-Fredette, A.C. Assisted Peritoneal Dialysis Implementation: A Pilot Program from a Large Dialysis Unit in Quebec. Can. J. Kidney Health Dis. 2022, 9, 20543581221113387. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Özbek, Ö.; Akdam, H.; Öncü, S.; Yeniçerioğlu, Y.; Öncü, S. Peritoneal dialysis related peritonitis; a single center results. Rev. De Nefrol. Dial. Y Traspl. 2022, 42, 206–214. [Google Scholar]
- Szeto, C.C.; Ng, J.K.; Fung, W.W.; Chan, G.C.; Cheng, P.M.; Law, M.C.; Pang, W.F.; Li, P.K.; Leung, C.B.; Chow, K.M. Excessive risk and poor outcome of hospital-acquired peritoneal dialysis-related peritonitis. Clin. Kidney J. 2022, 15, 2107–2115. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, H.; Yi, C.; Zhang, D.; Guo, Q.; Lin, J.; Mao, H.; Huang, F.; Yu, X.; Yang, X. Changes of antibiotic resistance over time among Escherichia coli peritonitis in Southern China. Perit. Dial. Int. 2022, 42, 218–222. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhai, Y.; Zhou, Q.; Fang, X.; Shen, X.; Chen, J.; Zhang, J.; Miao, Q.; Guo, W.; Cao, Q.; Rao, J.; et al. Reduction in peritonitis rates: 18-year results from the most active pediatric peritoneal dialysis center in China. Pediatr. Nephrol. 2022, 37, 2437–2448. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alves, C.A.; Cálice-Silva, V.; Rufino, E.M.; Garms, D.; Ferreira, H.C.; Baptistella, M.; Dias, D.B.; Mendes, M.L.; Banin, V.B.; Ponce, D. Urgent-Start Peritoneal Dialysis: Brazilian Experience. Blood Purif. 2023, 52, 556–563. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Çankaya, E.; Altunok, M.; Yağanoğlu, A.M. The effect of rural and urban life on peritonitis rates in chronic peritoneal patients. Ren. Fail. 2023, 45, 2163504. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chienwichai, K.; Sangaew, S.; Chuachanpipat, L.; Chang, A. Comparison of clinical outcomes between culture-negative and positive peritonitis in patients undergoing maintenance peritoneal dialysis: A prospective cohort study. BMC Nephrol. 2023, 24, 340. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Forté, V.; Novelli, S.; Zaidan, M.; Snanoudj, R.; Verger, C.; Beaudreuil, S. Microbiology and outcomes of polymicrobial peritonitis associated with peritoneal dialysis: A register-based cohort study from the French Language Peritoneal Dialysis Registry. Nephrol. Dial. Transpl. 2023, 38, 1271–1281. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guo, S.; Wu, H.; Ji, J.; Sun, Z.; Xiang, B.; Wu, W.; Ji, J.; Teng, J.; Ding, X.; Yu, X. Association between gut microbial diversity and technique failure in peritoneal dialysis patients. Ren. Fail. 2023, 45, 2195014. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pak, W.L.W.; Chan, K.L.; Chan, Z.; Wong, Y.H.; Law, W.P.; Lam, C.K.; Sunny Wong, S.H. Device-assisted continuous ambulatory peritoneal dialysis: A single-centre experience. Perit. Dial. Int. 2023, 43, 92–99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rivera, A.S.; Vesga, J.I.; Páez, S.; Astudillo, K.; Aldana, A.; Alba, Y.; Niño, L.E.; Castillo, J.C.; Sanabria, M.; Lindholm, B.; et al. Early outcomes of peritoneal dialysis in a middle-income country: A retrospective cohort study of a large dialysis network in Colombia. Perit. Dial. Int. 2023, 43, 467–474. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Srivastava, A.K.; Ghosh, I.; Sonawane, S. Clinical profile and microbiological spectrum of patients with continuous ambulatory peritoneal dialysis-associated peritonitis at a tertiary care center. Med. J. Armed Forces India 2023, 79, S175–S180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taher, A.; Enaya, A.; Sarsour, A.; Bahar, S.; Hamayel, D.; Safarini, O.; Hamdan, Z.; Nazzal, Z. Growing a peritoneal dialysis program in Palestine from zero to 178 patients in 5 years: A single-center experience. BMC Nephrol. 2023, 24, 21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, T.Y.; Tian, Y.C.; Yen, T.H.; Chang, M.Y.; Lin, C.Y.; Liu, S.H. Tuberculous peritonitis in patients on peritoneal dialysis: A 35-year experience from a large medical center in Northern Taiwan. Ren. Fail. 2023, 45, 2153064. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ye, Y.J.; Lou, J.J.; Zhang, Y.N.; Lou, X.Y.; Chen, Q. Is simply washing hands before dialysis procedures sufficient for reducing peritoneal dialysis peritonitis?—A single center study from 2015 to 2020 in Yiwu, China. Ther. Apher. Dial. 2023, 27, 335–342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aldriwesh, M.G.; Alaqeel, R.A.; Alangari, R.O.; Alzaben, S.A.; Albass, H.S.; Alajroush, L.N.; Hakami, A.R. Microbiology and Antimicrobial Resistance Profile of Infectious Peritonitis: A Cohort Study with 10-year Follow-up. J. Nat. Sci. Med. 2024, 7, 35–41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Centellas-Pérez, F.J.; Ortega-Cerrato, A.; Vera, M.; Devesa-Buch, R.J.; Muñoz-de-Bustillo, E.; Prats, M.; Alonso-Valente, R.; Morais, J.P.; Cara-Espada, P.J.; Yuste-Lozano, C.; et al. Impact of Remote Monitoring on Standardized Outcomes in Nephrology-Peritoneal Dialysis. Kidney Int. Rep. 2024, 9, 266–276. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dandecha, P.; Phongphithakchai, A. Effect of Exchange Systems and Procedure on Long Term Peritonitis in ESKD Patients Undergoing CAPD:A Retrospective Comparative Cohort Study. Iran. J. Kidney Dis. 2024, 18, 212–220. [Google Scholar] [PubMed]
- Dogan, I.; Ucar, E.; Odabas, M.; Kaya, N.U.; Sadioglu, R.E.; Celik, G.; Acikgoz, E.; Sayarlioglu, H.; Turkmen, E.; Delibalta, B.; et al. The effect of hand fine motor skills on peritoneal dialysis-related peritonitis. Ther. Apher. Dial. 2024, 28, 284–296. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dong, X.; Xie, C.; Yi, C.; Ye, P.; Ye, H.; Guo, Q.; Huang, F.; Kong, Y.Z.; Yang, X. Clinical characteristics and antibiotic treatment of peritoneal dialysis-associated peritonitis caused by Pseudomonas species: A review of 15 years’ experience from southern China. Microbiol. Spectr. 2024, 12, e0009624. [Google Scholar] [PubMed]
- Gül, C.B. Peritonitis in patients on peritoneal dialysis: A 12-year experience from a large medical center in Bursa. Eur. Res. J. 2024, 10, 92–96. [Google Scholar] [CrossRef] [Scilit]
- Ito, Y.; Tu, C.; Yamaguchi, M.; Koide, S.; Ryuzaki, M.; Bieber, B.; Pisoni, R.L.; Perl, J.; Minakuchi, J.; Kawanishi, H.; et al. Risk factors of peritoneal dialysis-related peritonitis in the Japan Peritoneal Dialysis Outcomes and Practice Patterns Study (PDOPPS). Clin. Kidney J. 2024, 17, sfae202. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liang, Q.; Zhao, H.; Wu, B.; Niu, Q.; Lu, L.; Qiao, J.; Men, C.; He, Y.; Chu, X.; Zuo, L.; et al. Risk Factors of the Occurrence and Treatment Failure of Refractory Peritoneal Dialysis-Associated Peritonitis: A Single-Center Retrospective Study from China. Semin. Dial. 2024, 37, 386–392. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mehrotra, R.; Williamson, D.E.; Betts, C.R.; Greco, B.A.; Yu, E.; El-Badry, A.; Fisher, B.; Mehoudar, P.D.; Briggs, B.; Chertow, G.M. A Prospective Clinical Study to EvaluAte the AbiliTy of the CloudCath System to Detect Peritonitis During In-Home Peritoneal Dialysis (CATCH). Kidney Int. Rep. 2024, 9, 929–940. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nabil, H.; Sara, E.M.; Hajar, F.; Naima, O.; Loubna, B. Repeat peritonitis in peritoneal dialysis: A cohort study. Bull. Dial. Domic. 2024, 7, 1–9. [Google Scholar] [CrossRef] [Scilit]
- Nardelli, L.; Scalamogna, A.; Ponzano, F.; Sikharulidze, A.; Tripodi, F.; Vettoretti, S.; Alfieri, C.; Castellano, G. Peritoneal dialysis related peritonitis: Insights from a long-term analysis of an Italian center. BMC Nephrol. 2024, 25, 163. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, P.G.; Ahn, Y.H.; Kang, H.G.; Ha, I.S. Decreased incidence of peritoneal dialysis-associated peritonitis in young children. J. Paediatr. Child Health 2024, 60, 531–537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tobijaszewska, M.; Martus, G.; Sunnerhagen, T.; Segelmark, M.; Ljungquist, O. A population-based study on the incidence and aetiology of infectious complications in peritoneal dialysis in South Sweden. Infect. Dis. 2024, 56, 230–243. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alfano, G.; Pittiglio, M.; Ferri, C.; Romaniello, R.; Oliviero, G.; Cancelli, Y.; Melara, L.; Tonelli, L.; Montani, M.; Raimondo, D.; et al. Screening for nasal carriage of Staphylococcus (S.) aureus reduces the risk of S. aureus peritonitis in patients on peritoneal dialysis (PD). Int. Urol. Nephrol. 2025, 57, 1639–1648. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Andrew, W.; Michael, C.; Daniel, C.; James, M.; Damian, M.; Damian, F.; Stephen, O. Peritoneal dialysis catheter insertion in patients with obesity: A cohort study and single centre approach to increasing uptake. BMC Nephrol. 2025, 26, 293. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guo, L.; Karim, S.A.; Qian, H.; Shen, Y.; Qian, W.; Liu, Y.; Xu, M.; Li, N. Retrospective Analysis of Multi-Center Peritoneal Dialysis-Associated Peritonitis in Jiangsu Province: A Retrospective Analysis from 2016 to 2024. J. Nat. Sci. Biol. Med. 2025, 16, 201–210. [Google Scholar]
- Kim, J.H.; Kim, S.M.; Kang, M.; Kang, E.; Park, S.H.; Kim, Y.L.; Pecoits-Filho, R.; Bieber, B.; Pisoni, R.L.; Oh, K.H.; et al. Characteristics of patients and facility of peritoneal dialysis in Korea: Results from the Peritoneal Dialysis Outcomes and Practice Patterns Study (PDOPPS) Korea. Perit. Dial. Int. 2025, 45, 281–290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Soetendorp, H.; Grupper, A.; Hazan, E.; Wasserman, A.; Schwartz, D.; Kliuk-Ben Bassat, O. Reduction of peritoneal dialysis associated infections using a novel exit-site care practice. Perit. Dial. Int. 2025, 45, 113–120. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsuchiya, Y.; Matsuo, N.; Masuda, N.; Maruyama, Y.; Tanno, Y.; Yokoo, T. Clinical impact of device connections on PD-related peritonitis. Clin. Exp. Nephrol. 2025, 29, 1279–1285. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yu, X.; Wang, J.; Liang, C.; Li, Z.; Lu, W.; Lv, J.; Ma, Y. Elevated effluent lactate independently predicts the adverse outcomes of peritoneal dialysis associated peritonitis. Sci. Rep. 2025, 15, 24009. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al Laham, J.; Alshaaili, K.; Elsayed, H.M.E.; Al-Kharusi, A.W.; Al Kharusi, K.; Al Aamri, K. Fungal Peritonitis in Peritoneal Dialysis: An 18-year Experience from Nizwa Hospital, Sultanate of Oman. Saudi J. Med. Med. Sci. 2026, 14, 75–79. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cho, H.G.; Lee, J.G.; Park, J.W.; Lim, J.; Heo, N.H.; Cho, N.J.; Park, S.; Gil, H.W.; Lee, E.Y. Characteristics of peritoneal dialysis-related infection according to pet ownership: An 8-year single-center experience. PLoS ONE 2026, 21, e0348012. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Okamoto, K.; Matsui, M.; Eriguchi, M.; Samejima, K.I.; Tsuruya, K. Association of nephrology referral timing with long-term survival and peritoneal dialysis-associated peritonitis in patients initiating peritoneal dialysis: A single-center retrospective study. BMC Nephrol. 2026, 27, 314. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cho, Y.; Badve, S.V.; Hawley, C.M.; McDonald, S.P.; Brown, F.G.; Boudville, N.; Wiggins, K.J.; Bannister, K.M.; Clayton, P.A.; Johnson, D.W. Seasonal variation in peritoneal dialysis-associated peritonitis: A multi-centre registry study. Nephrol. Dial. Transpl. 2012, 27, 2028–2036. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, J.; Zhang, H.; Liu, J.; Zhang, K.; Yi, B.; Liu, Y.; Liu, J.; Zhang, X.; Ji, Y. Implementation of a continuous quality improvement program reduces the occurrence of peritonitis in PD. Ren. Fail. 2014, 36, 1029–1032. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hu, S.; Ming, P.; Qureshi, A.R.; Lindholm, B.; Bo, Y.; Yang, H. Peritonitis: Episode Sequence, Microbiological Variation, Risk Factors and Clinical Outcomes in a North China Peritoneal Dialysis Center. Kidney Blood Press. Res. 2018, 43, 1573–1584. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jegatheesan, D.; Johnson, D.W.; Cho, Y.; Pascoe, E.M.; Darssan, D.; Htay, H.; Hawley, C.; Clayton, P.A.; Borlace, M.; Badve, S.V.; et al. The Relationship Between Body Mass Index and Organism-Specific Peritonitis. Perit. Dial. Int. 2018, 38, 206–214. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Benbella, M.; Guennoun, A.; Belrhiti, M.; Bouattar, T.; Bayahia, R.; Ouzeddoun, N.; Benamar, L. Peritoneal Dialysis at Ibn Sina Hospital in Rabat: 10 years’ experience. Bull. Dial. Domic. 2020, 3, 27–35. [Google Scholar] [CrossRef] [Scilit]
- Nardelli, L.; Scalamogna, A.; Messa, P. The impact of the superficial cuff position on the exit site and tunnel infections in CAPD patients. J. Nephrol. 2021, 34, 493–501. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, D.; Yang, Y.; Li, R.; Li, Z.; Wu, J.; Liu, H.; Xu, Y.; Hou, H.; Peng, Y.; Liu, X.; et al. Comparison of long-term outcomes between Chinese peritoneal dialysis patients with and without diabetes: A 10-year cohort study. J. Diabetes Complicat. 2021, 35, 107888. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hayat, A.; Cho, Y.; Pascoe, E.M.; Krishnasamy, R.; Borlace, M.; Chen, J.; Boudville, N.; Sud, K.; Varnfield, M.; Francis, R.; et al. Uptake and Outcomes of Peritoneal Dialysis among Aboriginal and Torres Strait Islander People: Analysis of Registry Data. Kidney Int. Rep. 2024, 9, 1484–1495. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sahlawi, M.A.; Wilson, G.; Stallard, B.; Manera, K.E.; Tong, A.; Pisoni, R.L.; Fuller, D.S.; Cho, Y.; Johnson, D.W.; Piraino, B.; et al. Peritoneal dialysis-associated peritonitis outcomes reported in trials and observational studies: A systematic review. Perit. Dial. Int. 2020, 40, 132–140. [Google Scholar] [CrossRef] [Scilit] [PubMed]




| Characteristics of Included Studies | Number of Studies (%) |
|---|---|
| Mean age in year, grand mean (SD); median (min–max); missing information for 15 studies (9.8%) | 54.5 (11.1); 56.1 (7.7–78.6) |
| Study population | |
| Adult | 86 (56.2) |
| Pediatric | 7 (4.6) |
| Mixed | 16 (10.5) |
| Not specified | 44 (28.7) |
| % Male, mean (SD); median (min–max); missing information for 12 studies (7.8%) | 55.9 (8.4); 55.8 (37.3–80.0) |
| PD modality | |
| CAPD | 35 (22.9) |
| APD | 2 (1.3) |
| Mixed | 82 (53.6) |
| Not specified | 34 (22.2) |
| PD center, median (min–max) | 1 (1–158) |
| Single center | 100 (65.4) |
| Multicenter: 2–25 | 38 (24.8) |
| Multicenter: >25 | 15 (9.8) |
| Sample size, median (min–max); missing information for 3 studies (2.0%) | 336.5 (100–9699) |
| 100–500 | 98 (65.3) |
| 501–1000 | 22 (14.7) |
| >1000 | 30 (20.0) |
| Year of publication | |
| 2011–2015 | 48 (31.4) |
| 2016–2020 | 48 (31.4) |
| 2021–2026 | 57 (37.2) |
| Period of data collection | |
| Before 2020 (before COVID-19 pandemic) | 122 (79.7) |
| 2020 onward (peri/during COVID-19 pandemic and post-emergency/post-COVID-19 pandemic) | 5 (3.3) |
| Comprised both before and after 2020 | 26 (17.0) |
| Data collection approach | |
| Retrospective | 103 (67.3) |
| Prospective | 27 (17.6) |
| Ambispective | 3 (2.0) |
| Registry data | 20 (13.1) |
| Study quality, mean (SD); median (min–max) b | 9.2 (0.5); 9 (8–10) |
| 8 points | 3 (2.0) |
| 9 points | 112 (73.2) |
| 10 points | 38 (24.8) |
| WHO region: country (no. of studies) c | |
| African Region: South Africa (2) | 2 (1.3) |
| Region of the Americas: Argentina (1), Brazil (5), Canada (5), Colombia (4), United States (4), Uruguay (1), and mixed Canada and United States (1) | 21 (13.8) |
| South-East Asia Region: India (5), Sri Lanka (1), and Thailand (10) | 16 (10.5) |
| European Region: Austria (2), France (3), Germany (1), Israel (2), Italy (4), Malta (1), Poland (2), Portugal (1), Spain (8), Sweden (1), Türkiye (10), and United Kingdom (6) | 41 (27.0) |
| Eastern Mediterranean Region: Iran (3), Kuwait (1), Morocco (1), Oman (1), Palestine (1), Saudi Arabia (4), and Tunisia (1) | 12 (7.9) |
| Western Pacific Region: Australia (2), China (23), Hong Kong (5), Japan (10), Malaysia (2), Singapore (2), South Korea (7), Taiwan (9), and mixed Australia/New Zealand (1) | 60 (39.5) |
| Meta-Analysis of Evidence | No. of Estimates (Total Sample Size) | Total PD-Associated Peritonitis Episodes: Total Patient-Year at Risk | Incidence Rate Estimation (95% CI), Episodes per Patient-Year | 95% Prediction Interval | Heterogeneity | p for Difference Between Subgroup | |||
|---|---|---|---|---|---|---|---|---|---|
| Q Statistic | p-Value | I2 (95% CI), % | τ2 | ||||||
| Main analysis | |||||||||
| Overall global estimation | 153 (n = 132,213 a) | 88,769:264,296.30 | 0.31 (0.28–0.34) | 0.10–0.91 | 25,973.90 | <0.001 | 99.41 (99.39–99.44) | 0.300 | NA |
| According to WHO region | |||||||||
| 2 (n = 292) | 340:363.82 | 0.99 (0.68–1.45) | NA | 11.99 | 0.001 | 91.70 (NA) | 0.068 | <0.001 |
| 21 (n = 30,425) | 14,751:35,647.03 | 0.38 (0.31–0.45) | 0.15–0.94 | 2416.01 | <0.001 | 99.17 (99.04–99.29) | 0.182 | |
| 16 (n = 13,837) | 6816:15,808.83 | 0.41 (0.35–0.48) | 0.21–0.81 | 539.18 | <0.001 | 97.22 (96.41–97.84) | 0.095 | |
| 41 (n = 29,987 b) | 24,013:54,201.94 | 0.37 (0.30–0.46) | 0.10–1.41 | 9414.25 | <0.001 | 99.58 (99.54–99.61 | 0.425 | |
| 12 (n = 4244) | 3197:8559.04 | 0.39 (0.31–0.49) | 0.16–0.95 | 394.06 | <0.001 | 97.21 (96.24–97.93) | 0.146 | |
| 60 (n = 45,032 c) | 33,694:137,564.70 | 0.21 (0.19–0.24) | 0.09–0.50 | 5443.41 | <0.001 | 98.92 (98.81–99.01) | 0.177 | |
| Additional analysis | |||||||||
| According to causative microorganism | |||||||||
| 94 (n = 85,522 c) | 26,836:160,370.70 | 0.127 (0.113–0.142) | 0.044–0.369 | 7293.71 | <0.001 | 98.72 (98.62–98.82) | 0.286 | <0.001 |
| 96 (n = 85,369 b) | 13,676:163,063.90 | 0.065 (0.058–0.073) | 0.023–0.189 | 3731.79 | <0.001 | 97.45 (97.19–97.69) | 0.284 | |
| 99 (n = 89,026 b) | 1795:165,470.40 | 0.009 (0.008–0.011) | 0.002–0.042 | 1025.79 | <0.001 | 91.23 (89.81–92.44) | 0.555 | |
| 29 (n = 16,684 c) | 157:42,603.07 | 0.004 (0.003–0.006) | 0.001–0.021 | 109.23 | <0.001 | 74.37 (63.17–82.16) | 0.631 | |
| 55 (n = 52,896 c) | 2757:97,510.67 | 0.017 (0.014–0.021) | 0.004–0.065 | 1094.48 | <0.001 | 95.34 (94.51–96.04) | 0.436 | |
| 94 (n = 75,405 b) | 11,589:144,430.50 | 0.073 (0.065–0.083) | 0.022–0.249 | 4236.81 | <0.001 | 97.80 (97.58–98.00) | 0.373 | |
| Subgroup analysis | |||||||||
| Study population | |||||||||
| 86 (n = 79,932 a) | 50,783:166,327.10 | 0.29 (0.26–0.32) | 0.12–0.69 | 9306.77 | <0.001 | 99.09 (99.02–99.15) | 0.194 | 0.017 |
| 7 (n = 5083) | 4036:7919.74 | 0.46 (0.36–0.58) | 0.19–1.12 | 264.05 | <0.001 | 97.73 (96.69–98.44) | 0.105 | |
| 16 (n = 9471 a) | 6892:17,278.32 | 0.37 (0.28–0.48) | 0.11–1.24 | 1732.89 | <0.001 | 99.13 (98.97–99.27) | 0.299 | |
| 44 (n = 37,727) | 27,058:72,771.20 | 0.31 (0.25–0.38) | 0.07–1.30 | 12,464.43 | <0.001 | 99.66 (99.63–99.68) | 0.494 | |
| PD modality | |||||||||
| 35 (n = 17,448) | 13,648:46,261.24 | 0.31 (0.25–0.38) | 0.08–1.21 | 5568.33 | <0.001 | 99.39 (99.32–99.45) | 0.437 | 0.097 |
| 2 (n = 363) | 248:465.00 | 0.42 (0.16–1.12) | NA | 33.79 | <0.001 | 97.00 (NA) | 0.489 | |
| 82 (n = 90,369 a) | 56,583:150,187.50 | 0.33 (0.29–0.37) | 0.12–0.92 | 13,667.12 | <0.001 | 99.41 (99.37–99.44) | 0.255 | |
| 34 (n = 24,033) | 18,290:67,382.61 | 0.25 (0.20–0.30) | 0.07–0.82 | 5627.30 | <0.001 | 99.41 (99.35–99.47) | 0.338 | |
| PD center | |||||||||
| 100 (n = 36,040 b) | 32,307:117,513.30 | 0.28 (0.25–0.32) | 0.09–0.86 | 9772.45 | <0.001 | 98.99 (98.91–99.06) | 0.309 | 0.054 |
| 38 (n = 33,990 c) | 26,246:66,637.89 | 0.36 (0.29–0.46) | 0.09–1.52 | 11,873.84 | <0.001 | 99.69 (99.66–99.71) | 0.483 | |
| 15 (n = 62,183) | 30,216:80,145.10 | 0.34 (0.30–0.39) | 0.18–0.63 | 1907.24 | <0.001 | 99.26 (99.13–99.38) | 0.075 | |
| Sample size | |||||||||
| 98 (n = 23,171) | 17,610:60,966.28 | 0.30 (0.27–0.34) | 0.10–0.88 | 5040.02 | <0.001 | 98.08 (97.90–98.24) | 0.285 | 0.125 |
| 22 (n = 15,057) | 9809:35,268.23 | 0.26 (0.21–0.33) | 0.09–0.81 | 2555.32 | <0.001 | 99.18 (99.05–99.29) | 0.276 | |
| 30 (n = 93,985) | 58,181:159,458.30 | 0.36 (0.29–0.44) | 0.11–1.14 | 16,683.15 | <0.001 | 99.83 (99.81–99.84) | 0.305 | |
| Year of publication | |||||||||
| 48 (n = 38,813 c) | 30,151:66,547.53 | 0.37 (0.34–0.42) | 0.18–0.80 | 3993.53 | <0.001 | 98.82 (98.69–98.94) | 0.138 | 0.001 |
| 48 (n = 41,041) | 21,123:70,156.58 | 0.28 (0.25–0.32) | 0.11–0.72 | 4002.27 | <0.001 | 98.82 (98.69–98.95) | 0.210 | |
| 57 (n = 52359 b) | 37,495:127,592.20 | 0.28 (0.24–0.33) | 0.07–1.09 | 15,355.66 | <0.001 | 99.64 (99.61–99.66) | 0.450 | |
| Period of data collection | |||||||||
| 125 d (n = 107,222) | 76,615:213,322.00 | 0.32 (0.29–0.35) | 0.11–0.95 | 22,129.83 | <0.001 | 99.44 (99.41–99.47) | 0.298 | 0.473 |
| 5 (n = 1474) | 366: 1416.30 | 0.28 (0.19–0.40) | 0.07–1.15 | 48.23 | <0.001 | 91.71 (83.63–95.80) | 0.162 | |
| Data collection approach | |||||||||
| 103 (n = 60,679 b) | 44,200:155,479.60 | 0.29 (0.26–0.32) | 0.10–0.84 | 12,035.28 | <0.001 | 99.15 (99.09–99.21) | 0.277 | 0.164 |
| 27 (n = 12,573) | 4803:15,598.74 | 0.30 (0.25–0.37) | 0.10–0.90 | 1225.56 | <0.001 | 97.88 (97.46–98.22) | 0.268 | |
| 3 (n = 4648) | 2649:7418.08 | 0.29 (0.20–0.41) | 0.00–21.02 | 17.04 | <0.001 | 88.26 (67.36–95.78) | 0.082 | |
| 20 (n = 54,313 c) | 37,117:85,799.90 | 0.41 (0.32–0.52) | 0.13–1.32 | 9690.84 | <0.001 | 99.80 (99.79–99.82) | 0.296 | |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Nochaiwong, S.; Ruengorn, C.; Noppakun, K.; Koyratkoson, K.; Chuamanochan, M.; Chieosilapatham, P.; Mongkhon, P.; Wachiraphansakul, N.; Vongchaiudomchoke, T.; Ngamvichchukorn, T.; et al. Global, Regional, and Country Incidence of Peritoneal Dialysis-Associated Peritonitis in the Contemporary Peritoneal Dialysis Practice: A Systematic Review and Meta-Analysis. Med. Sci. 2026, 14, 592. https://doi.org/10.3390/medsci14050592
Nochaiwong S, Ruengorn C, Noppakun K, Koyratkoson K, Chuamanochan M, Chieosilapatham P, Mongkhon P, Wachiraphansakul N, Vongchaiudomchoke T, Ngamvichchukorn T, et al. Global, Regional, and Country Incidence of Peritoneal Dialysis-Associated Peritonitis in the Contemporary Peritoneal Dialysis Practice: A Systematic Review and Meta-Analysis. Medical Sciences. 2026; 14(5):592. https://doi.org/10.3390/medsci14050592
Chicago/Turabian StyleNochaiwong, Surapon, Chidchanok Ruengorn, Kajohnsak Noppakun, Kiatkriangkrai Koyratkoson, Mati Chuamanochan, Panjit Chieosilapatham, Pajaree Mongkhon, Nuttaya Wachiraphansakul, Thanawat Vongchaiudomchoke, Tanun Ngamvichchukorn, and et al. 2026. "Global, Regional, and Country Incidence of Peritoneal Dialysis-Associated Peritonitis in the Contemporary Peritoneal Dialysis Practice: A Systematic Review and Meta-Analysis" Medical Sciences 14, no. 5: 592. https://doi.org/10.3390/medsci14050592
APA StyleNochaiwong, S., Ruengorn, C., Noppakun, K., Koyratkoson, K., Chuamanochan, M., Chieosilapatham, P., Mongkhon, P., Wachiraphansakul, N., Vongchaiudomchoke, T., Ngamvichchukorn, T., Thavorn, K., Sood, M. M., Knoll, G. A., & Tantraworasin, A. (2026). Global, Regional, and Country Incidence of Peritoneal Dialysis-Associated Peritonitis in the Contemporary Peritoneal Dialysis Practice: A Systematic Review and Meta-Analysis. Medical Sciences, 14(5), 592. https://doi.org/10.3390/medsci14050592