


Abstract
Introduction: Antipsychotic (AP) medications are widely prescribed beyond psychotic disorders, yet their long-term safety profile regarding breast cancer (BC) risk remains uncertain. Methods: We conducted a systematic review and meta-analysis of observational studies evaluating the association between AP exposure and incident BC. Eligible studies reported adjusted odds ratios (ORs) with 95% confidence intervals for any AP, prolactin-increasing antipsychotics (PIAPs), or prolactin-sparing antipsychotics (PSAPs). Study quality was assessed using the modified Newcastle-Ottawa Scale (mNOS), and certainty of evidence was graded with the GRADE framework. Random-effect models were used to pool effect estimates by exposure category, duration, and cumulative Defined Daily Dose (DDD). Results: Nine high-quality observational studies encompassing 108 effect estimates were included. Most studies achieved mNOS scores of 9, yet GRADE certainty ranged from very low to moderate, with the overall body of evidence graded as low certainty due primarily to residual confounding. Any AP exposure was associated with a modestly increased BC risk, particularly with long-term use: use for >5 years yielded pooled ORs around 1.5–1.6, while short-to-medium duration (1–5 years) showed smaller increases (pooled ORs in the range 1.2–1.3). For PIAPs, both longer duration (>5 years) and higher cumulative exposure (>1000–2000 DDDs) were consistently associated with ORs/HRs in the 1.3–1.6 range, suggesting a possible dose–response pattern. Histological analyses indicated stronger associations for ductal than lobular BC, and elevated risks were observed across age strata, including women aged <55 and ≥70 years. Discussion: This meta-analysis suggests that chronic exposure to prolactin-increasing antipsychotics is associated with a potentially clinically relevant increase in BC risk, whereas prolactin-sparing agents do not show a clear signal of harm. However, the certainty of this association is limited by inconsistently measured confounders and by the observational nature of the data. These findings support a cautious, individualized approach in which clinicians preferentially consider PSAPs when appropriate, discuss BC risk as part of shared decision-making, and integrate tailored screening strategies for women requiring long-term PIAP therapy. Further high-quality pharmacoepidemiologic studies with better confounder control and mechanistic integration are needed to refine risk estimates and inform preventive neuropsychopharmacology.
1. Introduction
The clinical application of antipsychotic (AP) medications has expanded considerably in recent years. Beyond their established roles in treating schizophrenia and bipolar disorders, these agents are now frequently prescribed off-label for mood stabilization, refractory anxiety, and sleep disturbances [1,2]. While their psychiatric efficacy is well-documented, the long-term effects of APs on female oncological health, particularly regarding breast cancer (BC) risk, remain under active scientific investigation.
This concern arises from the dopaminergic mechanism of action of most APs, which function as D2 receptor antagonists and frequently induce significant hyperprolactinemia. Since prolactin serves as a potent mitogen for mammary epithelial cells [3], the hypothesis that chronic hormonal stimulation may promote tumorigenesis is gaining traction. Nevertheless, the literature remains inconclusive; some observational studies report a clear correlation, whereas others do not demonstrate statistically significant associations. This inconsistency has led to the absence of unified guidelines for risk management.
This meta-analysis was designed to systematically evaluate the existing evidence by analyzing a cohort of over 1.3 million participants. The analysis specifically examines the impact of treatment duration, cumulative dosage (defined daily doses, DDDs), and pharmacological class, with a distinction between prolactin-increasing (PIAPs) and prolactin-sparing (PSAPs) agents. Assessing the interaction between pharmacological variables and histological subtypes is critical for optimizing patient care. The findings seek to bridge the gap between psychiatric efficacy and oncological safety, supporting the development of preventive neuropsychopharmacology models in which screening protocols are tailored to individual medication histories.
2. Materials and Methods
We followed a standardized procedure and reported the results in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines [4,5] and Meta-analyses of Observational Studies in Epidemiology (MOOSE) guidelines [6,7]. The meta-analysis is recorded in PROSPERO n. CRD420251169808.
2.1. Search Strategy
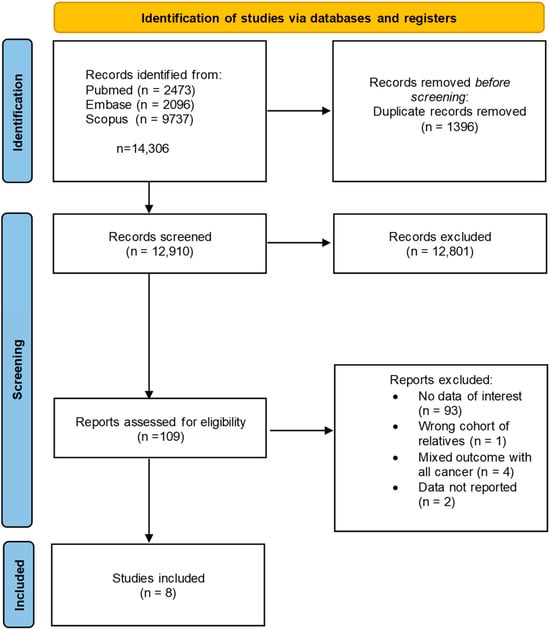
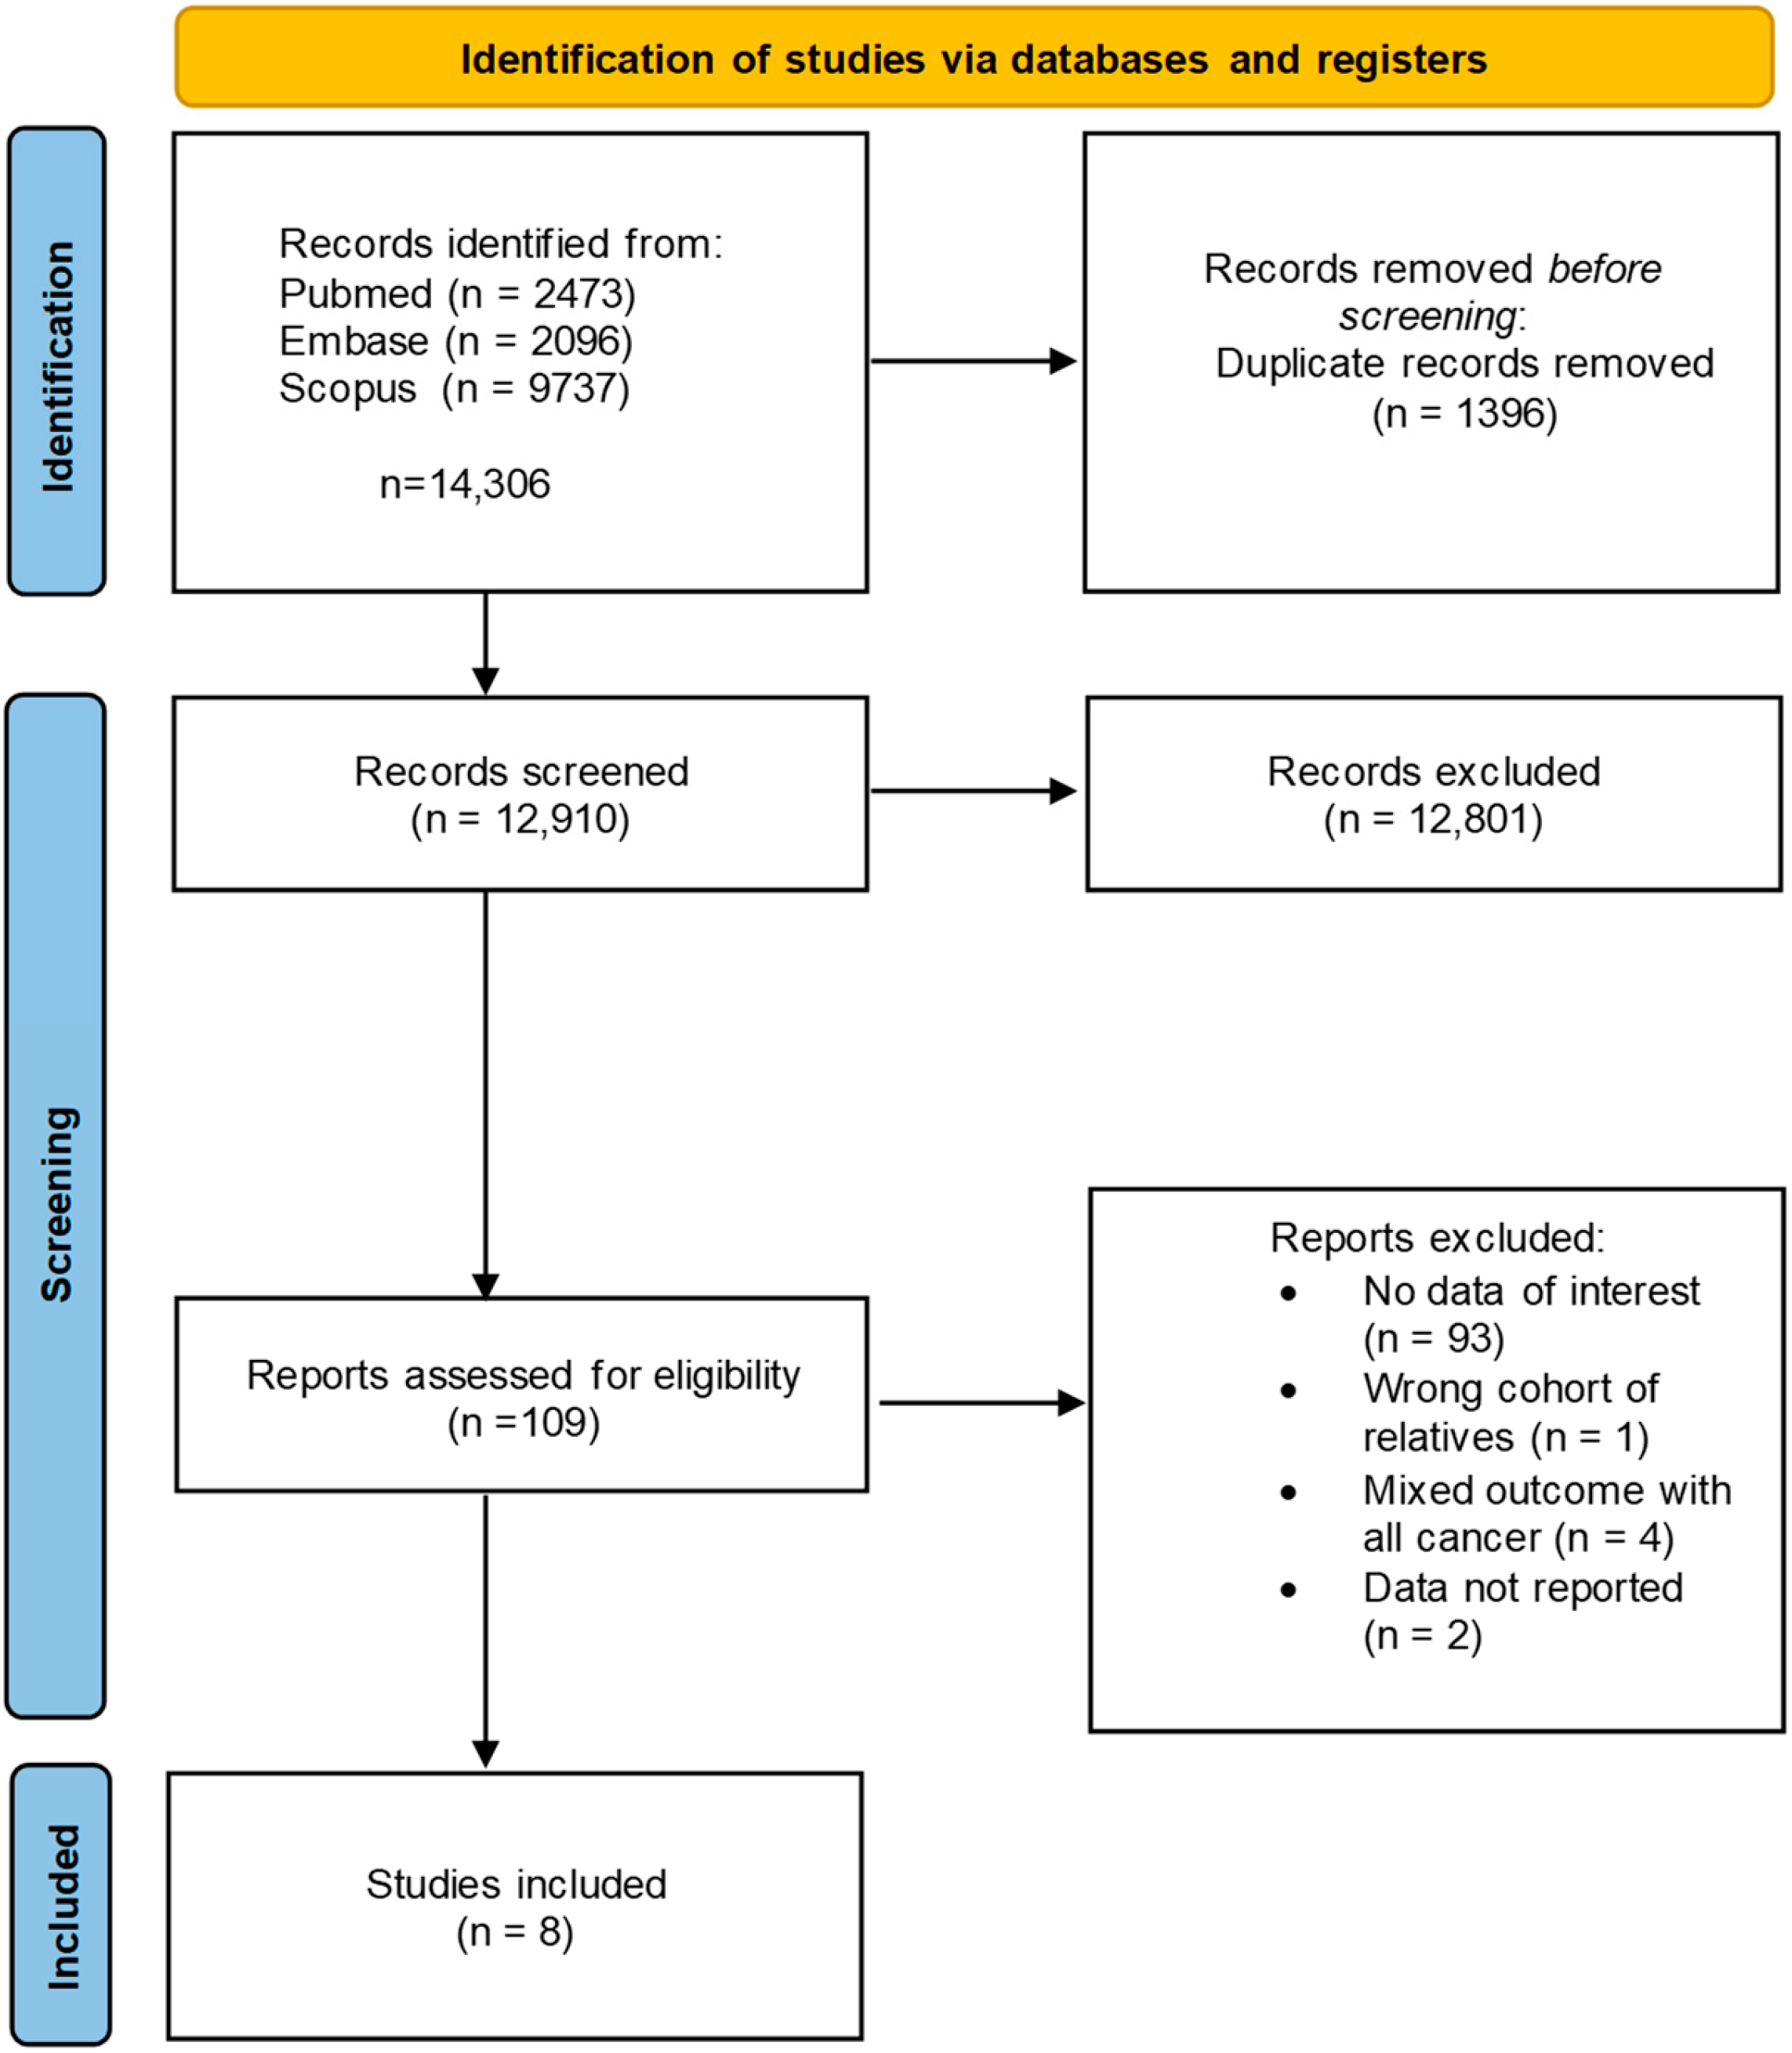
Eligible studies were identified through systematic screening of PubMed, Embase, and Scopus from database inception to 13 June 2025. The search strategy incorporated MeSH descriptors for neuroleptics and breast neoplasms, restricting results to human studies. To maintain currency, an updated search was performed on 16 March 2026, using the original search strings. Electronic retrieval was complemented by manual review of reference lists from all included articles and relevant systematic reviews (see Figure 1). This snowballing approach enabled the identification of citations potentially missed by database indexing. Detailed search protocols are available in the Supplementary Materials.
Figure 1.
PRISMA flowchart selection progress.
2.2. Eligibility Criteria and Study Selection
Eligibility screening was independently conducted by two investigators (E.A.G. and P.P.) in a blinded manner. Discrepancies were resolved by consensus or, if necessary, by a third senior reviewer (F.F.). Selection criteria were not restricted by geography, sex, or ethnicity. Studies were included if they met the following parameters:
- Design: Randomized controlled trials (RCTs), population-based case–control, nested case–control, or prospective/retrospective cohort studies.
- Outcome: The primary endpoint was the incidence of breast cancer.
- Statistical Reporting: Availability of Odds Ratios (ORs), Relative Risks (RRs), or Hazard Ratios (HRs) with corresponding 95% Confidence Intervals (CIs), or sufficient raw data for their derivation.
- Exposure Definition: AP exposure was characterized by at least one documented prescription or dispense recorded in validated national pharmacy databases or confirmed via healthcare professional interviews within a 14-day window.
Studies focused solely on mortality or review-only manuscripts were excluded. To prevent data inflation, duplicate cohorts were identified, and only the most comprehensive publication, defined as the one with the longest follow-up, was retained for analysis.
2.3. Data Extraction and Quality Assessment
A standardized data extraction protocol was implemented independently by two authors (E.A.G. and C.G.), with F.F. serving as an arbitrator. Extracted data included cohort size, publication year, follow-up duration, exposure confirmation methodology, pharmacological class, and geographical location. Effect estimates (ORs, RRs, or HRs) adjusted for the most comprehensive set of confounding variables in the primary studies were prioritized to maximize precision.
Methodological quality was rigorously assessed using the 9-star modified Newcastle-Ottawa Scale [8,9] (mNOS), covering three key domains: cohort selection, group comparability, and outcome/exposure verification. Studies attaining a full 9-star score were classified as high-quality. The certainty of evidence was further evaluated using the GRADE [10] framework.
2.4. Anatomical Therapeutic Chemical Classification
Antipsychotic exposure in this study was operationalised at three hierarchical levels: any antipsychotic, prolactin-increasing antipsychotics (PIAPs), and prolactin-sparing antipsychotics (PSAPs), all classified within the N05A group of the WHO Anatomical Therapeutic Chemical (ATC) system. Any antipsychotic corresponds to the entire N05A category, which includes both typical (first-generation) and atypical (second-generation) neuroleptics used for schizophrenia, bipolar disorder, and related indications. Within this overarching class, PIAPs were defined as antipsychotic agents within N05A that are known to induce sustained hyperprolactinemia through strong D2 receptor blockade in the tuberoinfundibular pathway (predominantly high-potency typicals and some atypicals), whereas PSAPs were defined as N05A agents with a prolactin-sparing profile, characterized by minimal, transient, or clinically negligible prolactin elevation, such as several second-generation antipsychotics with lower D2 occupancy or more rapid dissociation kinetics. For meta-analytic purposes, individual N05A substances from these subclasses were aggregated into three pharmacological exposure groups, any antipsychotic (N05A overall), PIAPs (N05A with a prolactin-increasing profile), and PSAPs (N05A with a prolactin-sparing profile), to align ATC classification with the mechanistic hypothesis of prolactin-mediated breast carcinogenesis.
Specifically:
- All antipsychotics are coded within N05A and its subclasses (e.g., N05AA phenothiazines, N05AD butyrophenones, N05AH diazepines/oxazepines/thiazepines, N05AL benzamides, N05AX other antipsychotics).
- Drugs typically considered prolactin-increasing (PIAPs), such as many first-generation antipsychotics and agents like risperidone or amisulpride, have their own N05A-subgroup codes (e.g., haloperidol N05AD01, risperidone N05AX08, amisulpride N05AL05).
- Drugs commonly regarded as prolactin-sparing (PSAPs), for example aripiprazole (N05AX12), quetiapine (N05AH04), ziprasidone (N05AE04), clozapine (N05AH02).
2.5. Statistical Analysis
Random-effect models were utilized to synthesize pooled estimates, accounting for anticipated inter-study heterogeneity [11]. When 95% confidence intervals (CIs) were unavailable, they were derived under the assumption of a Gaussian distribution. Primary estimates underwent log-transformation to ensure symmetry before back-transformation for reporting. Between-study variance was estimated using the restricted maximum likelihood (REML) method [12,13,14].
Statistical analyses were conducted using R (v2024; R Foundation for Statistical Computing). Heterogeneity, precision, and publication bias were evaluated using Galbraith and Funnel plots [15]. The robustness of the estimates was confirmed at the 0.05 alpha level. Each comprehensive forest plot represents an independent meta-analytic synthesis.
2.6. Ethics Statement
This comprehensive meta-analysis was managed by analyzing data from published manuscripts. The eligible studies had obtained the ethical agreement from their corresponding Institutional Review Boards, as recognized in the original papers.
3. Results
3.1. Literature Search
The literature search generated 108 different effect estimates in 8 observational studies comprising 1,371,985 participants. The publication dates ranged from 1978 to 2022.
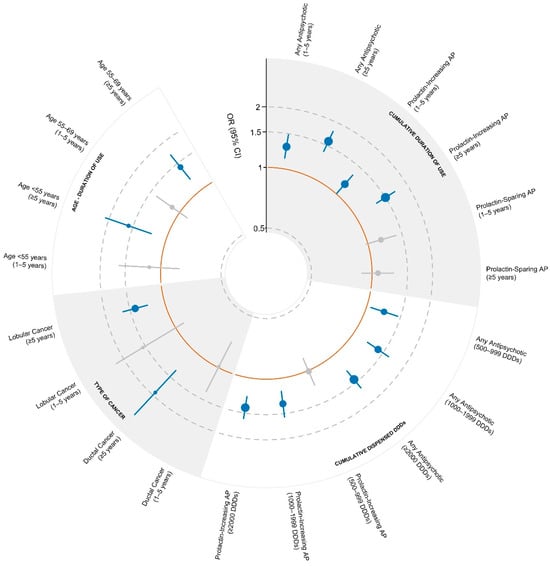
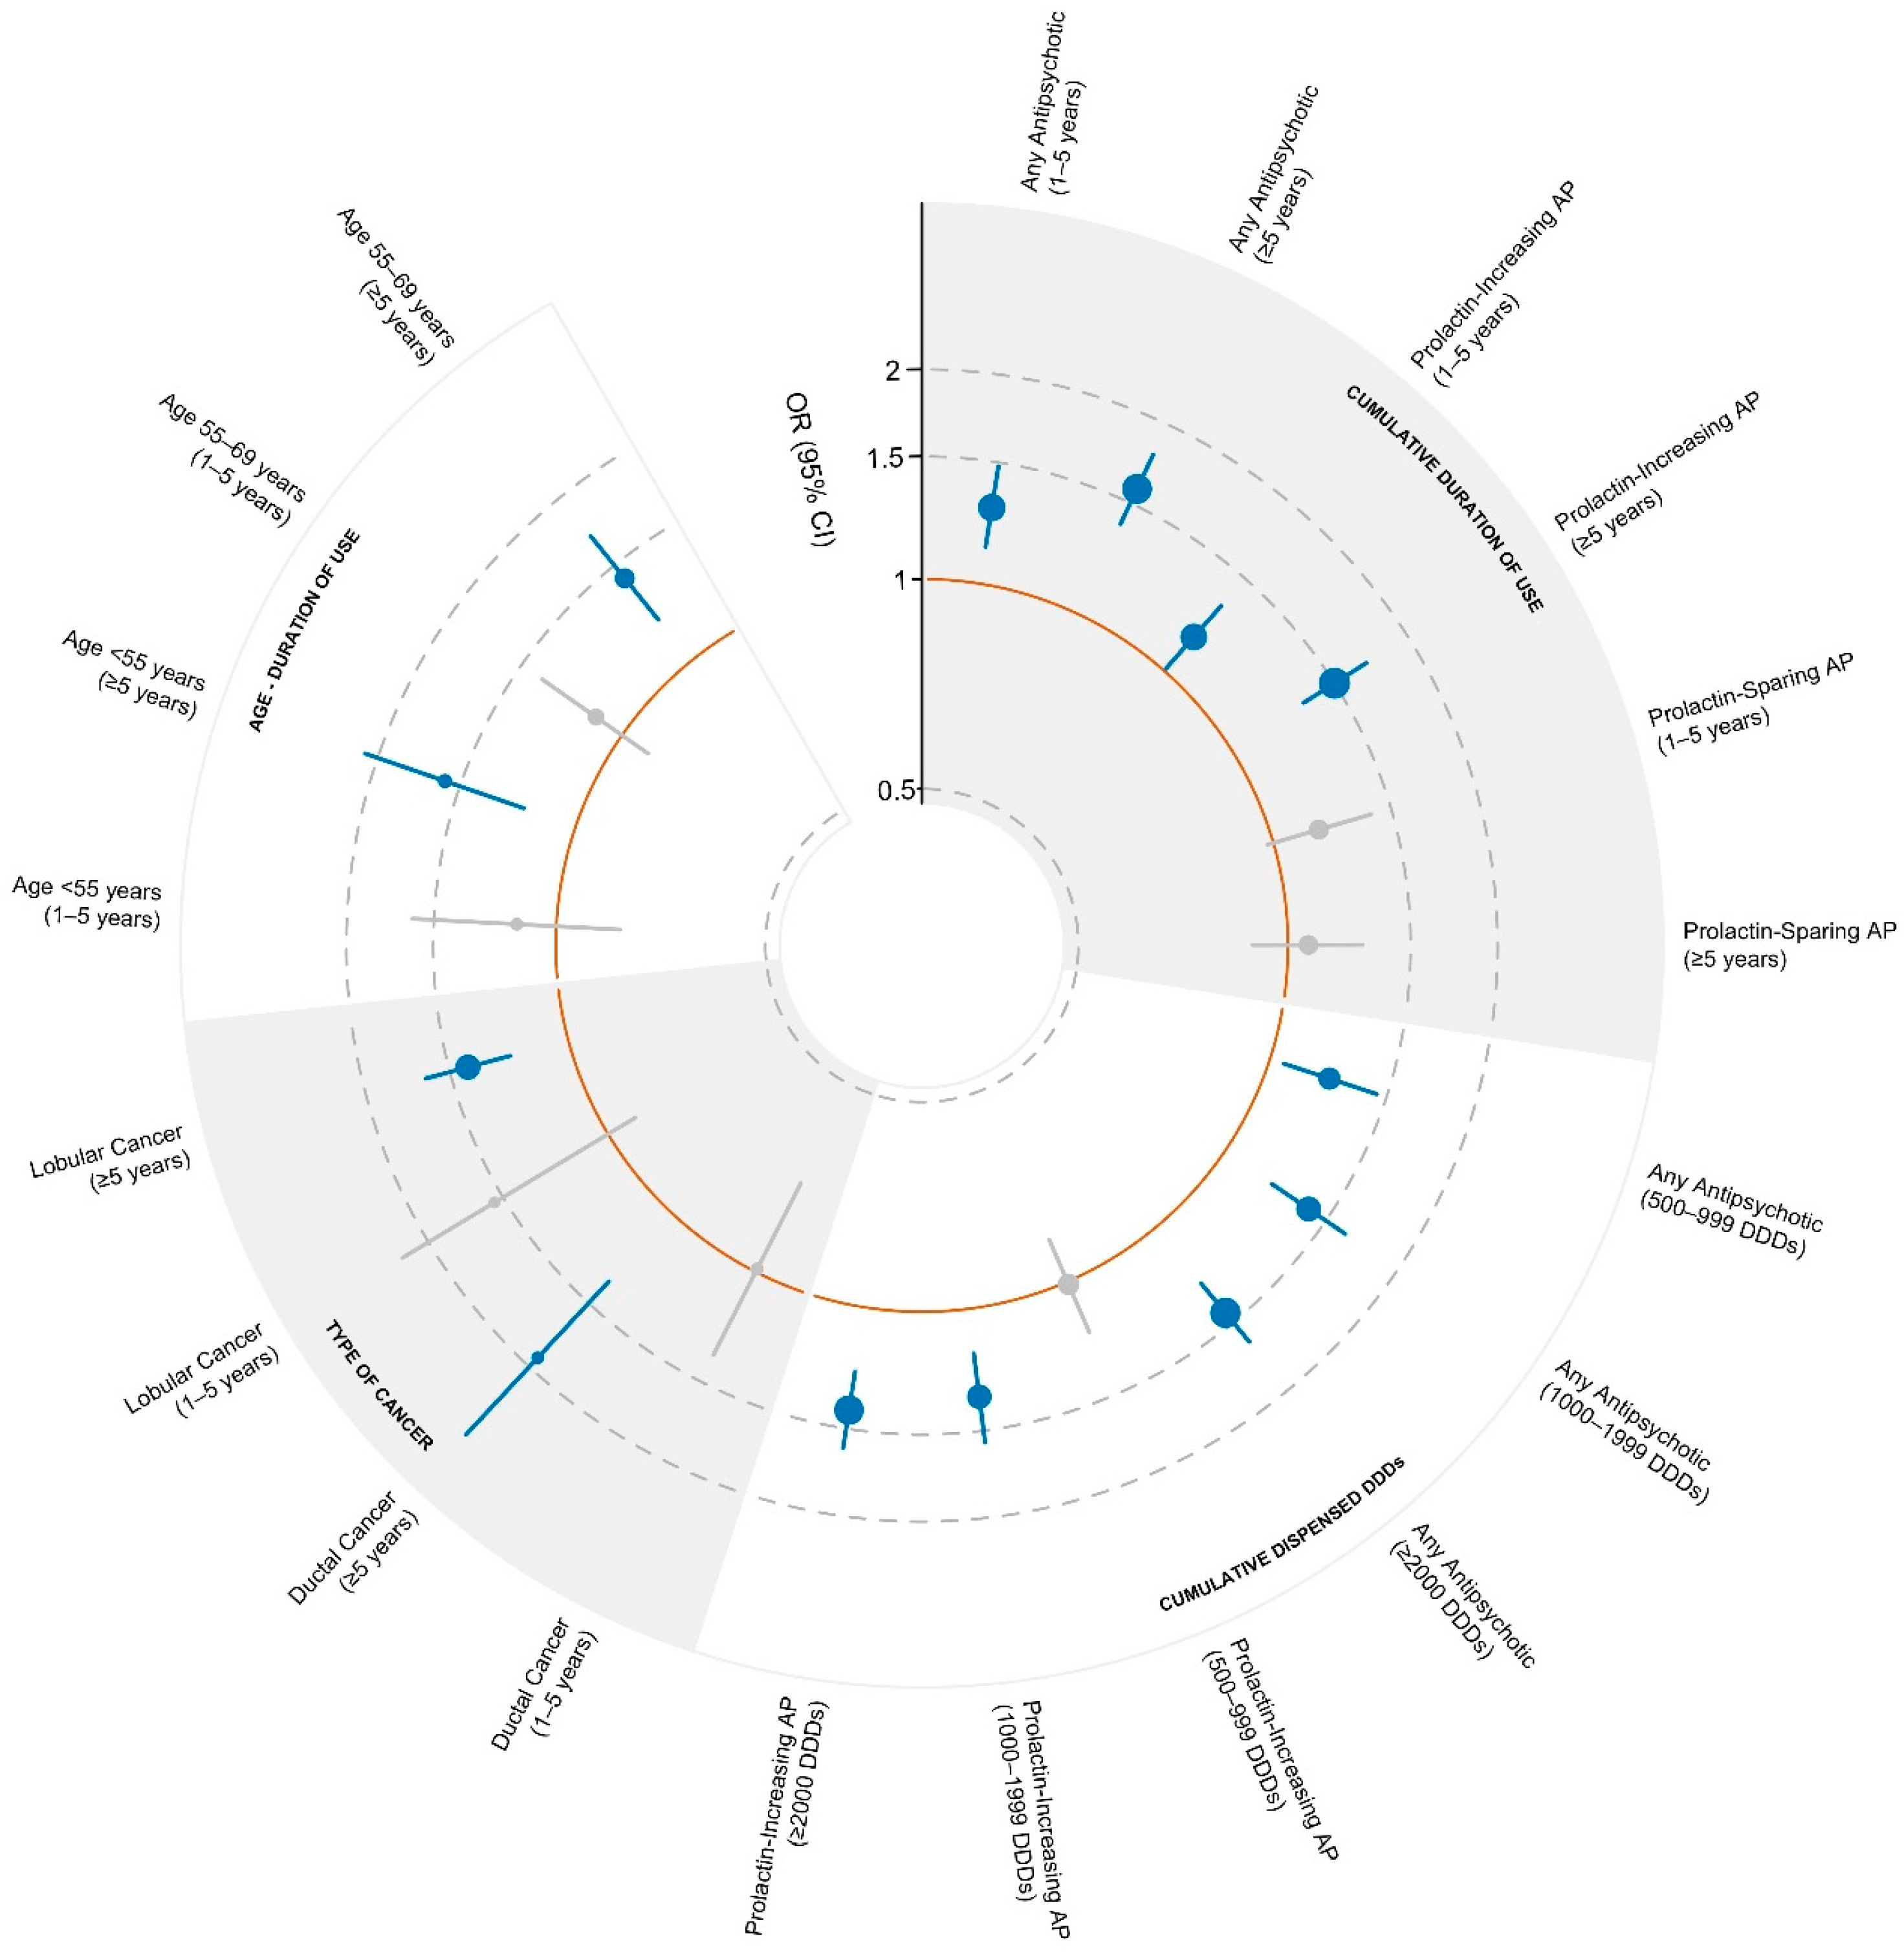
A total of 25 meta-analytic pooled estimates were appraised for the main analysis: 12 (48%) reported effects that were significant at p < 0.001, two (8%) at p = 0.01 and one (4%) at p = 0.03 (See Table 1 and Figure 2).
Table 1.
Characteristics of included studies and availability of data on patients with BC receiving Aps *.
Figure 2.
Summary of evidence. The pooled OR associated with breast cancer for each patient condition, duration, histotypes and demographic characteristic. The horizontal lines through the circles represent the 95% confidence interval (C.I.) for each study statistically significant result are coloured in blue, while not significant are coloured grey; each different variable corresponds to one meta-analysis. Results are reported in logarithmic scale for symmetry.
3.2. Quality Assessment of the Studies
The Modified Newcastle-Ottawa Scale rating for all studies was high: five studies received 9 stars (67%), two studies received 8 stars (25%), and one study received 7 stars (8%) (see Supplementary Materials Table S3). Despite the high NOS scores, the GRADE assessment highlighted a more nuanced landscape, with the certainty of evidence ranging from very low to moderate. Across the included large observational studies, the GRADE assessment indicates low overall certainty that long-term or prolactin-elevating antipsychotic use modestly increases breast cancer risk. The main limitation is residual confounding, because even the registry cohorts cannot fully adjust for key reproductive and lifestyle factors such as parity, age at first birth, family history, alcohol, smoking, and obesity in a consistent way; this leads to a downgrade for risk of bias. Nevertheless, effect estimates are reasonably precise and broadly consistent: most high-quality studies report adjusted relative risks or odds ratios in the 1.2–1.6 range for high cumulative or long-duration exposure to prolactin-increasing agents while low or short-term exposure is often compatible with no important increase. Translating this into absolute terms, for a typical baseline postmenopausal breast cancer risk of about 3–4% over 10–15 years [24], a 30–50% relative increase would correspond to an absolute excess of roughly 1–2 additional cases per 100 women with long-term prolactin-elevating antipsychotic exposure, but because of the low GRADE certainty, this estimate should be interpreted cautiously and framed as an approximate range rather than a precise risk.
3.3. Pharmacological Exposure and BC Risk
3.3.1. Any Antipsychotic
Exposure to any AP was positively correlated with BC incidence. Short-to-medium term use (1–5 years) yielded an OR of 1.29 (95% CI: 1.13–1.48). Notably, long-term exposure (>5 years) significantly escalated the risk to an OR of 1.58 (95% CI: 1.39–1.79), invasive BC is reported with an HR 1.13, CI 95% 0.6–2.11; a clear dose–response relationship was observed: 500–999 Defined Daily Doses (DDDs, a standard measure of drug consumption), OR 1.23; 1000–1999 DDDs, OR 1.40; and ≥2000 DDDs, OR 1.44 (95% CI: 1.27–1.63).
3.3.2. Prolactin-Increasing Antipsychotic
The risk associated with PIAPs is also associated with a higher risk of BC.
Patients who used PIAP between 1 and 5 years present an OR of 1.16, CI 95% 1.01–1.33 while those who used PIAP for a period longer than 5 years have an OR of 1.5, CI 95% 1.33–1.7. Having between 500 and 999 DDDs presents a risk of 1.01, CI 95% 0.86–1.2, between 1000 and 1999 DDDs 1.34, CI 95% 1.16–1.56 and people who have more than 2000 DDDs had a risk of 1.14, 1.24–1.6.
3.3.3. Prolactin-Sparing Antipsychotic
PSAPs are unclearly associated with BC. Having used PSAPs between 1 and 5 years reports a risk associated OR as 1.17, CI 95% 0.98–1.4 while using them for more than 5 years report a risk of 1.07, CI 95% 0.89–1.28. Possessing between 500 and 999 DDDs is associated with an OR 1.00, CI 95% 0.34–1.74, between 1000 and 1999 the OR is 1.12, 0.87–1.44 and more than 2000 DDDs 1.03–0.86–1.25.
3.3.4. Histological Subtypes and Demographic Factors
Analysis of histological subtypes revealed a significant divergence in vulnerability to long-term antipsychotic exposure. Ductal breast cancer demonstrated the strongest association with prolonged AP use (exceeding 5 years), with an OR of 1.92 (95% CI: 1.36–2.72). Although the association for lobular breast cancer remained statistically significant after five years, the effect size was notably lower (OR 1.41, 95% CI: 1.22–1.63). In both histotypes, shorter exposure durations (1–5 years) did not reach statistical significance, indicating that the oncogenic stimulus, likely mediated by sustained hyperprolactinemia, requires a prolonged latency period to result in clinically detectable invasive disease.
When stratified by demographic factors, the risk profile demonstrated a remarkable consistency across the age spectrum, contradicting the hypothesis that age-related hormonal shifts might mitigate the impact of APs. For patients treated for more than 5 years, the risk remained significantly elevated across all cohorts: those aged < 55 years had an OR of 1.58, those aged 55–69 an OR of 1.42, and those aged > 70 an OR of 1.55.
This trans-generational risk suggests that mammary tissue sensitivity to drug-induced endocrine disruption persists into older age. While younger patients may be more susceptible to prolactin’s mitogenic effects due to higher baseline glandular activity, the continued risk in elderly populations highlights the need for vigilant oncological surveillance regardless of menopausal status or chronological age.
4. Heterogeneity and Publication Bias
To evaluate the statistical consistency of our findings, we utilized Galbraith plots to visually inspect inter-study heterogeneity and identify potential outliers that might disproportionately influence the pooled estimates. This approach allowed for a systematic exploration of variance sources beyond what is captured by standard I2 statistics.
Additionally, the potential for publication bias was rigorously assessed using Funnel plots, which illustrate the relationship between effect sizes and their standard errors. Funnel asymmetry was evaluated as an indicator of missing small-study effects or reporting biases. By combining graphical assessments with study-quality audits, this dual-layered approach ensures that the meta-analytic conclusions are based on a precise and transparent evaluation of the available observational evidence, adhering to the highest standards of evidence-based synthesis. Plots are not showed due to high similarity.
5. Discussion
The management of psychiatric disorders has become a complex clinical challenge [25,26]. The focus has shifted from solely addressing acute symptomatology to balancing psychotropic efficacy with long-term metabolic and oncological safety. In this context, clinicians often operate within a “grey zone,” where evidence-based decisions must be weighed against the emerging risks of chronic pharmacological exposure. This meta-analysis addresses a critical knowledge gap at the intersection of clinical psychiatry and preventive oncology. The investigation of the association between antipsychotics (APs) and breast cancer (BC) extends beyond statistical correlation and challenges current standards of care regarding the long-term safety profiles of treatments administered to millions of women worldwide.
The non-linear escalation of risk observed after the five-year mark strongly supports the “promotion” hypothesis in mammary carcinogenesis. Unlike direct mutagens, which initiate DNA damage rapidly, hormonal promoters such as prolactin (PRL) act by accelerating the proliferation of preneoplastic clones [27,28]. The prolonged D2 receptor antagonism inherent in chronic AP therapy leads to sustained disinhibition of lactotroph cells in the anterior pituitary [29]. This chronic hyperprolactinemia does not merely alter the systemic hormonal milieu; it fundamentally rewires the local microenvironment of the breast tissue.
Our finding of a nearly doubled risk for ductal carcinoma (OR 1.92) compared to the more modest elevation in lobular carcinoma (OR 1.41) is particularly salient, given that ductal lesions represent the vast majority of invasive breast cancers diagnosed clinically.
From a biological standpoint, this suggests a differential sensitivity of ductal epithelial cells to PRL-mediated signalling. Prolactin receptors are known to activate the JAK2/STAT5 and MAPK/ERK pathways, which collectively drive cell cycle progression and inhibit pro-apoptotic signals [30,31,32].
It is plausible that ductal cells, which are the primary site for the majority of breast malignancies, possess a lower threshold for hormonal saturation, beyond which homeostatic repair mechanisms are overwhelmed as a “biological fatigue.”
Furthermore, the robust dose–response relationship identified in our cohort, climbing from an OR of 1.23 for lower dosages to an OR of 1.44 for heavy exposure (>2000 DDDs), fulfils the essential “Hill’s Criteria” for biological causality [33]. This direct correlation between cumulative pharmacological load and disease probability suggests that the stimulus’s intensity is as critical as its duration. The convergence of time-dependent risk and dose-dependent escalation supports the hypothesis that iatrogenic hyperprolactinemia acts as a relentless promoter of mammary carcinogenesis, particularly when cumulative exposure exceeds the physiological resilience of the ductal epithelium.
The sharp divergence between prolactin-increasing and prolactin-sparing agents represents the interpretative cornerstone of this study. Our results demonstrate that BC risk is not a class-wide property of antipsychotics but is specifically tethered to the drug’s affinity for D2 receptors in the tuberoinfundibular pathway [21].
PIAPs induce a sustained disruption of the endocrine axis, converting what is often dismissed as a transient side effect into a chronic, systemic biochemical signal.
At the molecular level, prolactin functions as a potent mitogen and survival factor for mammary epithelial cells. Upon binding to its receptor, it triggers the JAK2/STAT5 and MAPK/ERK cascades, downstream signalling pathways that are well-documented drivers of cell cycle progression and potent inhibitors of programmed cell death [19,20,22,23] (apoptosis). The data illustrate a clear biological divide: while PIAPs demonstrated a dose-dependent escalation in risk, PSAPs maintained a neutral safety profile even in long-term cohorts (>5 years). This neutrality is a critical finding, as it addresses the issue of confounding by indication. The absence of increased risk in the PSAP group suggests that psychiatric illness itself, or shared lifestyle factors such as obesity and sedentary behaviour, are not the primary drivers of the observed oncological risk. Instead, the evidence implicates the iatrogenic hormonal environment created by specific dopaminergic blockade. This distinction shifts the clinical choice of antipsychotics from a purely symptomatic decision to a pivotal act of preventive neuropsychopharmacology.
This meta-analysis has few limitations: the evidence base is almost entirely observational, residual confounding for key breast cancer risk factors remains substantial, and exposure, outcome, and latency definitions are heterogeneous across studies, limiting causal inference. In addition, the PIAP/PSAP dichotomy, although ATC-based and biologically motivated, simplifies intra-class variability and does not allow precise drug-specific estimates. Strengths include the very large sample size, the explicit integration of duration and cumulative DDDs, the mechanistically informed separation of prolactin-increasing versus prolactin-sparing agents, and the use of PRISMA, MOOSE, mNOS and GRADE frameworks, which together provide a transparent and clinically oriented synthesis of the current observational evidence.
6. Conclusions and Clinical Recommendations
This meta-analysis suggests that prolonged antipsychotic use, particularly beyond five years, may be associated with a modest but potentially clinically relevant increase in breast cancer risk, especially for prolactin-increasing agents. Given the predominantly observational nature of the available studies and the low overall certainty of evidence, these findings should be interpreted with caution and viewed as hypothesis-generating rather than definitive. Nevertheless, the consistent signal for higher risk at longer durations and higher cumulative doses together with the stronger association observed for ductal carcinoma, supports a prudent, individualized approach in psychiatric practice, in which the potential oncological implications of long-term prolactin-elevating therapy are discussed and weighed against therapeutic benefits.
Supplementary Materials
The following supporting information can be downloaded at https://www.mdpi.com/article/10.3390/medsci14020205/s1.
Author Contributions
E.A.G. (Conceptualization: Lead; Data curation: Lead; Formal analysis: Lead; Investigation: Lead; Methodology: Lead; Software: Equal; Validation: Equal; Visualization: Equal; Writing—original draft: Lead; Writing—review and editing: Equal). V.O. (Methodology: Equal; Formal analysis: Equal; Validation: Equal; Investigation: Equal; Writing—original draft: Equal). G.G. (Methodology: Equal; Formal analysis: Equal; Investigation: Equal; Validation: Equal; Writing—original draft: Equal). D.A.B. (Methodology: Equal; Validation: Equal; Writing—review and editing: Supporting). J.G. (Methodology: Equal; Formal analysis: Equal; Investigation: Equal; Validation: Equal; Writing—original draft: Equal). P.P. (Conceptualization: Equal; Investigation: Supporting; Methodology: Equal; Validation: Equal; Writing—review and editing: Equal). C.G. (Conceptualization: Equal; Investigation: Supporting; Methodology: Equal; Validation: Equal; Writing—review and editing: Equal). F.F. (Conceptualization: Equal; Investigation: Supporting; Data curation: Equal; Formal analysis: Equal; Methodology: Equal; Software: Equal; Validation: Equal; Visualization: Equal; Writing—original draft: equal; Writing—review and editing: Equal). All authors have read and agreed to the published version of the manuscript.
Funding
This original research is funded by Dipartimento di Eccellenza 2023–2027—Scienze Mediche—ADAQ RICERCA—CUP F77G22000340001 (2023_DDE_SCM_ADAQ_RICERCA), University of Ferrara.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in this study are included in the article/Supplementary Materials. Further inquiries can be directed to the corresponding authors.
Acknowledgments
C.G. is supported by the European Research Council (853057-InflaPML); FARE 2020 (INFLA-THROMB); the Italian Association for Cancer Research (IG-32575); the Association A-ROSE ODV; the Italian Ministry of Health (PNRR-MCNT1-2023-12378355) and local funds from the University of Ferrara. P.P. is supported by the Unione Europea–NextGenerationEU, Mission 4 componente 1-Italian Ministry of Education, University, and Research, PRIN2017E5L5P3 and PRIN2020RRJP5L003, Piano Nazionale di Ripresa e Resilienza, Missione 4 Componente 2-Investimento 1.3-NextGenerationEU-PE 00000019-CUP E83C22004670001, Investimento 1.4-NextGenerationEU-CN 00000041-CUP C93C22002780006, Italian Association for Cancer Research (AIRC, IG-23670) and by the Association A-ROSE ODV. ChatGPT 5.4 was used to improve the readability and linguistic clarity of the manuscript. The authors reviewed and approved all suggested modifications and are fully responsible for the content of this manuscript.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
AP (antipsychotic), BC (breast cancer), CI (confidence interval), HR (hazard ratio), ICD (International Classification of Diseases), mNOS (modified Newcastle-Ottawa Scale), and OR (odds ratio). Additional methodological and pharmacological abbreviations include DDD (Defined Daily Dose), PIAPs (prolactin-increasing antipsychotics), PSAPs (prolactin-sparing antipsychotics), and ATC (Anatomical Therapeutic Chemical classification system). The reporting and evidence-grading framework introduces PRISMA (Preferred Reporting Items for Systematic Reviews and Meta-Analyses), MOOSE (Meta-analyses of Observational Studies in Epidemiology), RCT(s) (randomized controlled trial(s)), RR(s) (relative risk(s)), PROSPERO (International Prospective Register of Systematic Reviews), and REML (restricted maximum likelihood).
References
- Haddad, N.; Farhat, N.; Go, J.; Chen, Y.; Gravel, C.A.; Momoli, F.; Mattison, D.R.; McNair, D.; Alami, A.; Krewski, D. Trends in antipsychotic drug use in the United States, 2000–2016. Pharmacy 2026, 14, 14. [Google Scholar] [CrossRef] [Scilit]
- Hálfdánarson, Ó.; Zoëga, H.; Aagaard, L.; Bernardo, M.; Brandt, L.; Fusté, A.C.; Furu, K.; Garuoliené, K.; Hoffmann, F.; Huybrechts, K.F.; et al. International trends in antipsychotic use: A study in 16 countries, 2005–2014. Eur. Neuropsychopharmacol. 2017, 27, 1064–1076. [Google Scholar] [CrossRef] [Scilit]
- Schuler, L.A.; O’Leary, K.A. Prolactin: The third hormone in breast cancer. Front. Endocrinol. 2022, 13, 910978. [Google Scholar] [CrossRef] [Scilit]
- Moher, D.; Liberati, A.; Tetzlaff, J.; Altman, D.G. Preferred reporting items for systematic reviews and meta-analyses: The PRISMA statement. PLoS Med. 2009, 6, e1000097. [Google Scholar] [CrossRef] [Scilit]
- Higgins, J.P.T.; Green, S. Cochrane Handbook for Systematic Reviews of Interventions; Version 5.1.0; John Wiley & Sons Ltd.: London, UK, 2011. [Google Scholar]
- Brooke, B.S.; Schwartz, T.A.; Pawlik, T.M. MOOSE reporting guidelines for meta-analyses of observational studies. JAMA Surg. 2021, 156, 787–788. [Google Scholar] [CrossRef] [Scilit]
- Stroup, D.F.; Berlin, J.A.; Morton, S.C.; Olkin, I.; Williamson, G.D.; Rennie, D.; Moher, D.; Becker, B.J.; Sipe, T.A.; Thacke, S.B. Meta-analysis of observational studies in epidemiology: A proposal for reporting. JAMA 2000, 283, 2008–2012. [Google Scholar] [CrossRef] [Scilit]
- Wells, G.A.; Shea, B.; O’Connell, D.; Peterson, J.; Welch, V.; Losos, M.; Tugwell, P. The Newcastle-Ottawa Scale (NOS) for Assessing the Quality of Nonrandomized Studies in Meta-Analysis; The Ottawa Hospital Research Institute: Ottawa, ON, Canada, 2000. [Google Scholar]
- Stang, A. Critical evaluation of the Newcastle-Ottawa scale for the assessment of the quality of nonrandomized studies in meta-analyses. Eur. J. Epidemiol. 2010, 25, 603–605. [Google Scholar] [CrossRef] [Scilit]
- Brozek, J.L.; Canelo-Aybar, C.; Akl, E.A.; Bowen, J.M.; Bucher, J.; Chiu, W.A.; Cronin, M.; Djulbegovic, B.; Falavigna, M.; Guyatt, G.H.; et al. GRADE Guidelines 30: The GRADE approach to assessing the certainty of modeled evidence—An overview in the context of health decision-making. J. Clin. Epidemiol. 2021, 129, 138–150. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Higgins, J.P.T.; Thompson, S.G. Quantifying heterogeneity in a meta-analysis. Stat. Med. 2002, 21, 1539–1558. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Corbeil, R.R.; Searle, S.R. Restricted maximum likelihood (REML) estimation of variance components in the mixed model. Technometrics 1976, 18, 31–38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smith, S.P.; Graser, H.-U. Estimating variance components in a class of mixed models by restricted maximum likelihood. J. Dairy Sci. 1986, 69, 1156–1165. [Google Scholar] [CrossRef] [Scilit]
- Van Arendonk, J.A.; Tier, B.; Bink, M.C.A.M.; Bovenhuis, H. Restricted maximum likelihood analysis of linkage between genetic markers and quantitative trait loci for a granddaughter design. J. Dairy Sci. 1998, 81, 76–84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Verburg, I.W.M.; Holman, R.; Peek, N.; Abu-Hanna, A.; de Keizer, N.F. Guidelines on constructing funnel plots for quality indicators: A case study on mortality in intensive care unit patients. Stat. Methods Med. Res. 2018, 27, 3350–3366. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chou, A.I.W.; Wang, Y.C.; Lin, C.L.; Kao, C.H. Female schizophrenia patients and risk of breast cancer: A population-based cohort study. Schizophr. Res. 2017, 188, 165–171. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- George, A.; Sturgeon, S.R.; Hankinson, S.E.; Shadyab, A.H.; Wallace, R.B.; Reeves, K.W. Psychotropic medication use and postmenopausal breast cancer risk. Cancer Epidemiol. Biomarkers Prev. 2020, 29, 254–256. [Google Scholar] [CrossRef] [Scilit]
- Hippisley-Cox, J.; Vinogradova, Y.; Coupland, C.; Parker, C. Risk of malignancy in patients with schizophrenia or bipolar disorder: Nested case-control study. Arch. Gen. Psychiatry 2007, 64, 1368–1376. [Google Scholar] [CrossRef] [Scilit]
- Pottegård, A.; Lash, T.L.; Cronin-Fenton, D.; Ahern, T.P.; Damkier, P. Use of antipsychotics and risk of breast cancer: A Danish nationwide case–control study. Br. J. Clin. Pharmacol. 2018, 84, 2152–2161. [Google Scholar] [CrossRef] [Scilit]
- Rahman, T.; Sahrmann, J.M.; Olsen, M.A.; Nickel, K.B.; Miller, J.P.; Ma, C.; Grucza, R.A. Risk of breast cancer with prolactin elevating antipsychotic drugs: An observational study of US women (ages 18–64 years). J. Clin. Psychopharmacol. 2022, 42, 7–16. [Google Scholar] [CrossRef] [Scilit]
- Solmi, M.; Lähteenvuo, M.; Tanskanen, A.; Corbeil, O.; Mittendorfer-Rutz, E.; Correll, C.U.; Tiihonen, J.; Taipale, H. Antipsychotic use and risk of breast cancer in women with severe mental illness: Replication of a nationwide nested case-control database study. Schizophr. Bull. 2024, 50, 1471–1481. [Google Scholar] [CrossRef] [Scilit]
- Taipale, H.; Solmi, M.; Lähteenvuo, M.; Tanskanen, A.; Correll, C.U.; Tiihonen, J. Antipsychotic use and risk of breast cancer in women with schizophrenia: A nationwide nested case-control study in Finland. Lancet Psychiatry 2021, 8, 883–891. [Google Scholar] [CrossRef] [Scilit]
- Chu, R.Y.K.; Wei, Y.; Osborn, D.P.; Ng, V.W.S.; Cheng, F.W.T.; Chan, S.K.W.; Chan, S.S.M.; Wong, I.C.K.; Chan, E.W.Y.; Lai, F.T.T. Breast cancer risks following antipsychotic use in women with bipolar disorder versus schizophrenia: A territory-wide nested case-control study spanning two decades. Psychiatry Res. 2023, 326, 115287. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schonberg, M.A.; Li, V.W.; Eliassen, A.H.; Davis, R.B.; LaCroix, A.Z.; McCarthy, E.P.; Rosner, B.A.; Chlebowski, R.T.; Hankinson, S.E.; Marcantonio, E.R.; et al. Accounting for individualized competing mortality risks in estimating postmenopausal breast cancer risk. Breast Cancer Res. Treat. 2016, 160, 547–562. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Firth, J.; Siddiqi, N.; Koyanagi, A.; Siskind, D.; Rosenbaum, S.; Galletly, C.; Allan, S.; Caneo, C.; Carney, R.; Carvalho, A.F.; et al. The Lancet Psychiatry Commission: A blueprint for protecting physical health in people with mental illness. Lancet Psychiatry 2019, 6, 675–712. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tiihonen, J.; Mittendorfer-Rutz, E.; Majak, M.; Mehtälä, J.; Hoti, F.; Jedenius, E.; Enkusson, D.; Leval, A.; Sermon, J.; Tanskanen, A.; et al. Real-world effectiveness of antipsychotic treatments in a nationwide cohort of 29,823 patients with schizophrenia. JAMA Psychiatry 2017, 74, 686–693. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Clevenger, C.V.; Rui, H. Breast cancer and prolactin—New mechanisms and models. Endocrinology 2022, 163, bqac122. [Google Scholar] [CrossRef] [Scilit]
- Clevenger, C.V.; Furth, P.A.; Hankinson, S.E.; Schuler, L.A. The role of prolactin in mammary carcinoma. Endocr. Rev. 2003, 24, 1–27. [Google Scholar] [CrossRef] [Scilit]
- Peuskens, J.; Pani, L.; Detraux, J.; De Hert, M. The effects of novel and newly approved antipsychotics on serum prolactin levels: A comprehensive review. CNS Drugs 2014, 28, 421–453. [Google Scholar] [CrossRef] [Scilit]
- Tworoger, S.S.; Hankinson, S.E. Prolactin and breast cancer risk. Cancer Lett. 2006, 243, 160–169. [Google Scholar] [CrossRef] [Scilit]
- Tworoger, S.S.; Eliassen, A.H.; Rosner, B.; Sluss, P.; Hankinson, S.E. Plasma prolactin concentrations and risk of postmenopausal breast cancer. Cancer Res. 2004, 64, 6814–6819. [Google Scholar] [CrossRef] [Scilit]
- Tworoger, S.S.; Eliassen, A.H.; Zhang, X.; Qian, J.; Sluss, P.M.; Rosner, B.A.; Hankinson, S.E. A 20-year prospective study of plasma prolactin as a risk marker of breast cancer development. Cancer Res. 2013, 73, 4810–4819. [Google Scholar] [CrossRef] [Scilit]
- Hill, A.B. The environment and disease: Association or causation? J. R. Soc. Med. 2015, 108, 32–37. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.