


Abstract
Metformin (MET) and atorvastatin (ATO) are promising treatments for COVID-19. This review explores the potential of MET and ATO, commonly prescribed for diabetes and dyslipidemia, respectively, as versatile medicines against SARS-CoV-2. Due to their immunomodulatory and antiviral capabilities, as well as their cost-effectiveness and ubiquitous availability, they are highly suitable options for treating the virus. MET’s effect extends beyond managing blood sugar, impacting pathways that can potentially decrease the severity and fatality rates linked with COVID-19. It can partially block mitochondrial complex I and stimulate AMPK, which indicates that it can be used more widely in managing viral infections. ATO, however, impacts cholesterol metabolism, a crucial element of the viral replicative cycle, and demonstrates anti-inflammatory characteristics that could modulate intense immune reactions in individuals with COVID-19. Retrospective investigations and clinical trials show decreased hospitalizations, severity, and mortality rates in patients receiving these medications. Nevertheless, the journey from observing something to applying it in a therapeutic setting is intricate, and the inherent diversity of the data necessitates carefully executed, forward-looking clinical trials. This review highlights the requirement for efficacious, easily obtainable, and secure COVID-19 therapeutics and identifies MET and ATO as promising treatments in this worldwide health emergency.
1. Introduction
SARS-CoV-2, the etiological agent of COVID-19 disease, has generated an unprecedented epidemic, putting enormous strain on healthcare systems around the world. Despite the widespread use of multiple vaccines, the recurrence of symptomatic cases underscores the necessity of practical treatment approaches against this virus [1,2]. Although vaccines are the primary prevention method, the appearance of viral variants and the risk of inadequate immune responses in some people underline the need for effective therapy [3]. The Food and Drug Administration (FDA) of the United States has approved and permitted the emergency use of medications to treat COVID-19. These cover many therapeutic techniques, from direct antiviral medicines to immunomodulatory [1,4].
On the other hand, the genetic diversity of SARS-CoV-2 is a decisive factor in its infective capacity and transmission dynamics in the human population. Because its RNA polymerase lacks proofreading mechanisms during replication, it has an inherent propensity to accumulate mutations as a single-stranded RNA virus. When these mutations occur in essential areas, such as the S protein, they are critical because they play a role in the virion entry into host cells, affecting the primary target of immune responses and antiviral medicines [5].
Reevaluating current medications for new therapeutic applications has emerged as a critical tactic in this setting. This review focuses on repositioning metformin (MET) and atorvastatin (ATO) as prospective COVID-19 therapy candidates. Traditionally used to treat diabetes [6,7] and dyslipidemia [8,9], these medicines have been demonstrated to have immunomodulatory and antiviral effects that may be useful in treating SARS-CoV-2 infection [10,11,12,13,14,15,16].
It is necessary to find treatments that are safe, effective, and easy to obtain. With their well-known security features and wide availability, MET and ATO offer a unique chance. This review carefully examines the pharmacological basis of both drugs and the latest information on COVID-19 and its antiviral properties.
2. Fundamentals and Mechanisms: An In-Depth Analysis of the Pharmacology of Metformin and Atorvastatin
MET (N, N-dimethylbiguanide) is one of the most prescribed drugs worldwide. It is used for treating diabetes, prediabetes, gestational diabetes, polycystic ovarian syndrome, cancer, HIV-associated diabetes, and cardiac ischemia [17]. During the 1920s, guanidine, the active component of Galega officinalis, was used to synthesize multiple antidiabetic compounds, including the main biguanides, MET, and phenformin [18]. Still, MET distinguishes itself due to its favorable profile in treating type 2 diabetes. The structure of biguanides consists of two guanidine groups linked by a methylene bridge (-CH2-). MET has demonstrated a higher safety margin concerning severe complications such as lactic acidosis. Its therapeutic range in hepatic concentrations varies between 10 and 40 µM in type 2 diabetic patients [19]. MET lowers the basal and postprandial plasma glucose (PPG) as a biguanide agent [20]. MET actions ameliorate insulin resistance by inhibiting principally hepatic gluconeogenesis, reducing intestinal glucose adsorption, and improving glucose uptake and utilization. Within the liver, the principal effect of MET is a reduction in the hepatic glucose output. Besides lowering blood glucose levels, MET has additional health benefits, including weight reduction, reducing plasma lipid levels, and preventing some microvascular complications [21]. The drug is not metabolized and is widely distributed into the body tissues, including the intestine, liver, and kidney, by organic cation transporters [22].
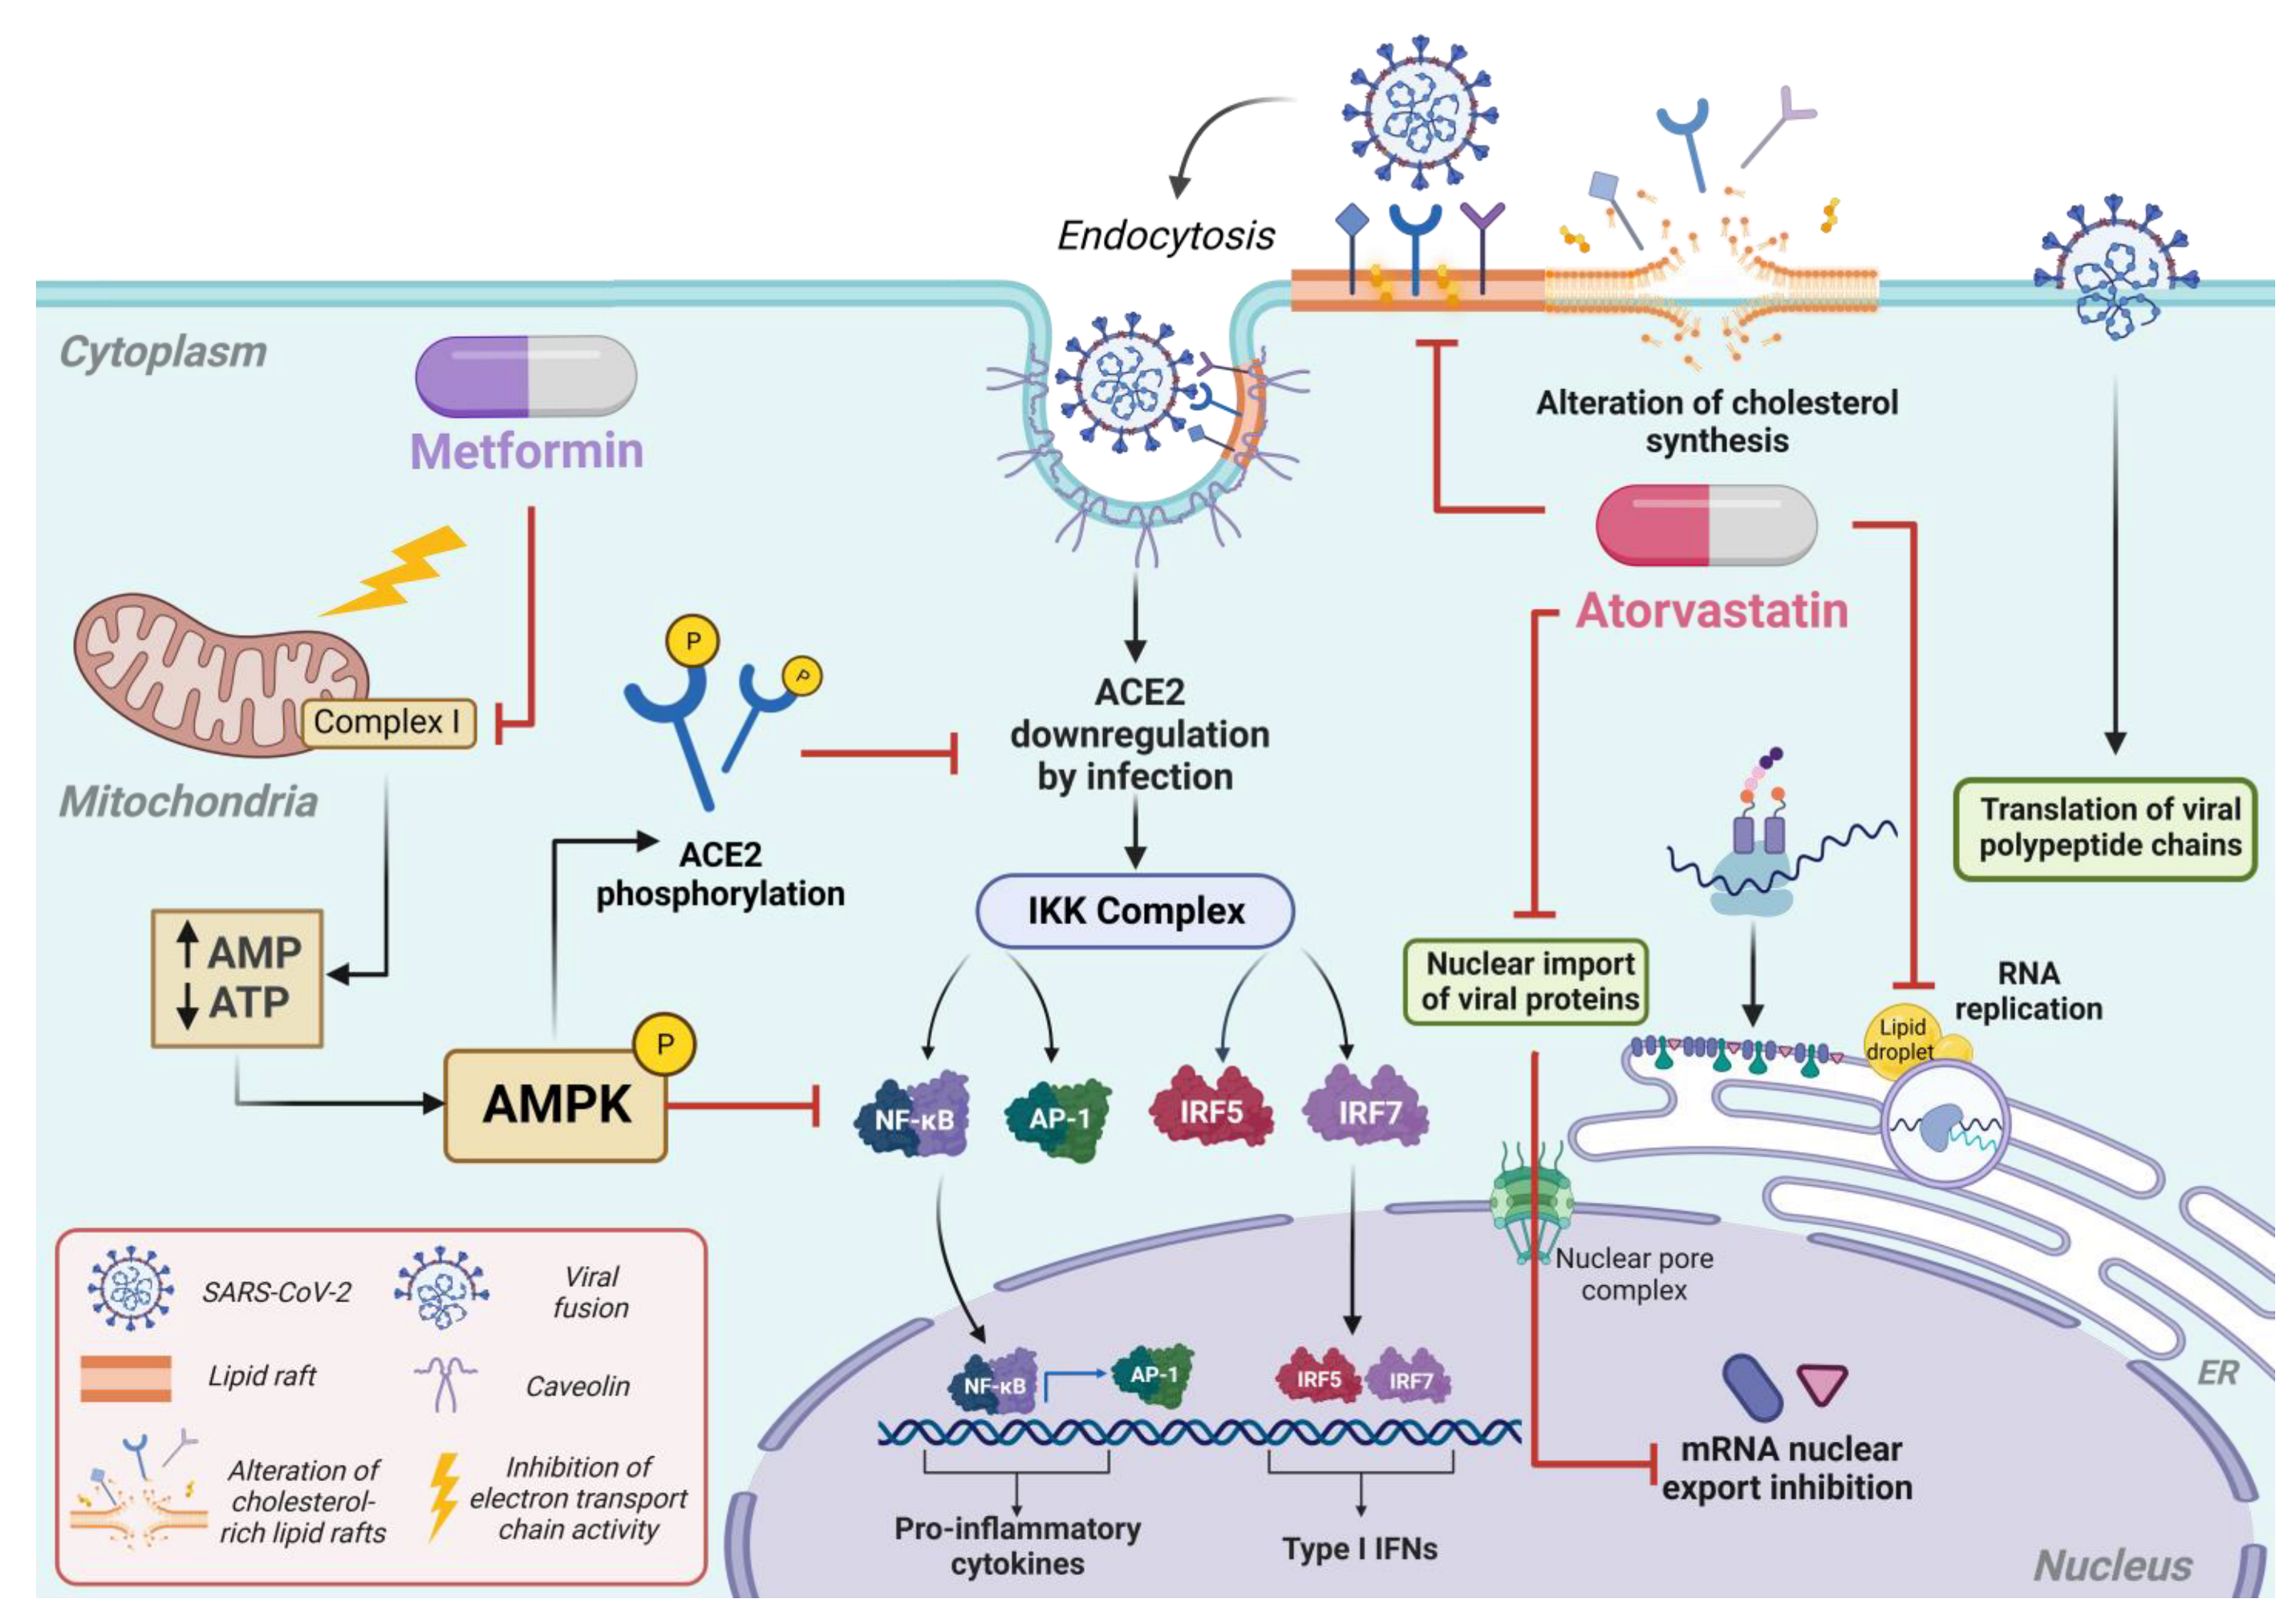
MET’s antidiabetic effect is due to the partial reduction of the activity of the respiratory chain on mitochondrial complex I through interfering with electron transfer and ATP production [6,7]. Interestingly, MET inhibits the mitochondrial glycerophosphate (mGPD) activity and mitochondrial respiration from glycerol-3-phosphate at lower concentrations than those affecting complex I [23]. This mechanism leads to other downstream events, including the activation of adenosine monophosphate kinase (AMPK), inhibition of 1,6-bisphosphatase, and glucagon signaling [24].
The defined mechanism of MET action is AMPK activation, inhibiting the liver’s critical enzymes involved in gluconeogenesis and glycogen synthesis while stimulating insulin signaling and glucose transport in muscles [24]. AMPK regulates the cellular and organ metabolism, where any decrease in hepatic energy leads to the activation of AMPK by increasing the adenosine monophosphate (AMP) to adenosine triphosphate (ATP) AMP:ATP and adenine diphosphate (ADP) ADP:ATP ratios, as regulated by adenylate cyclase. AMP binds to the sensing domain, where it allosterically activates AMPK. Also, AMP causes the inhibition of the dephosphorylation of Thr172 on the γ subunits [25].
AMPK activation requires the phosphorylation of Thr172 of the catalytic α-subunit, which is regulated upstream by the tumor suppressor serine/threonine kinase 11 (STK11/LKB1) [26] and by the Ca2+ calmodulin-dependent kinase kinases CaMKK-α and -β [27]. The LKB1 pathway regulates downstream the phosphorylation of the transducer of regulated CREB activity 2 (TORC2) [28]. The activated AMPK cascade is a metabolic switch sensor in cells that switches from an anabolic to a catabolic state, switching off the ATP-consuming synthetic pathways and restoring the energy balance by switching on the uptake of glucose and fatty acids [29].
Similar to all medicines, MET can cause side effects, including nausea, vomiting, diarrhea, indigestion, heartburn, flatulence, weakness, myalgia, chest discomfort, palpitations, flushing, headache, lightheadedness, dyspnea, a flu-like condition, reduced vitamin B12 levels, increased diaphoresis and cutaneous side effects [30]. MET is contraindicated in patients with severe renal failure as there is an increased risk of lactic acidosis [31].
On the other hand, ATO is a statin that inhibits 3-hydroxy-3-methyl-glutaryl-CoA (HMG-CoA) reductase (HMGCR). In 1980, it was shown that mevastatin, formerly called ML-236B or compactin, markedly lowers the levels of low-density lipoprotein (LDL) cholesterol [32] and apolipoprotein B (apo-B). ATO is a synthetic variant of this statin, approved in 1996 [8].
ATO exhibits a potent competitive inhibitory effect on the activity of the enzyme HMGCR, which plays a pivotal role in the biosynthesis of cholesterol in the liver. By inhibiting this enzyme, ATO decreases the production of cholesterol. HMGCR inhibition has a rate-limiting effect in the cholesterol synthesis pathway through converting 3-hydroxy-3-methyl glutaryl-CoA (HMG-CoA) into mevalonate, the precursor of cholesterol and other sterols [33]. Consequently, hepatocytes lead to increased production (upregulation) of LDL receptors on their surface, enhancing the uptake and clearance of LDL cholesterol from the bloodstream [8,9].
This reduction in the LDL cholesterol levels helps mitigate the risk of cardiovascular diseases associated with high cholesterol. ATV can also raise the HDL cholesterol levels and decrease triglycerides [18]. The common side effects of ATV happen in more than 1 in 100 people, including gastrointestinal, nausea, bloating, diarrhea or constipation, hepatitis, myalgia, and myopathy [19].
This reduction in the LDL cholesterol levels helps mitigate the risk of cardiovascular diseases associated with high cholesterol. ATO can also raise the HDL cholesterol levels and decrease triglycerides [34]. The common side effects of ATO happen in more than 1 in 100 people, including gastrointestinal, nausea, bloating, diarrhea or constipation, hepatitis, myalgia, and myopathy [35].
4. The Impact of Metformin and Atorvastatin on the Immune Response
The term “Immunomodulators” pertains to drugs that modify the immune system’s response. These essential medications combat various conditions, such as infectious diseases, tumors, and primary or secondary immunodeficiency. However, these molecules may have differential impacts involved in the given pathology. Some reports have shown that immune modulators can decrease the morbidity and mortality in severely affected patients during viral infections [91]. The antiviral activity of MET is due, in part, to its immunostimulatory effects [92]. These effects mainly depend on AMP-activated protein kinase (AMPK) activation, as described above. Briefly, the activation of MAPK increases mTOR signaling by phosphorylating TSC2 and RAPTOR, a crucial connection between immune function and metabolism [93].
Additionally, this response can inhibit the NF-κB pathway, a master regulator of the inflammatory response [94]. For instance, several studies have demonstrated in animal models that MET decreases inflammatory cytokines, such as IL-1β, IL-6, and TNFα, and increases anti-inflammatory via IL-10 expression [92,93,95]. Thus, it protects against acute lung injuries or can suppress the cytokine storm produced by severe COVID-19 [96].
On the other hand, MET modulates the differentiation and activation effects of various immune cells. Macrophages exhibit two primary phenotypes: pro-inflammatory (M1) and “alternatively” activated (M2) macrophages. These distinct macrophage phenotypes are primarily pro-inflammatory responses or the resolution of inflammation [97]. In vitro, MET can have anti-inflammatory preferences. Thus, the response in macrophages stimulated with LPS decreases the TNF-α, IL-6, MCP-1, ROS, and pro-IL-1β while boosting IL-10 expression [98]. However, MET in a cancer environment induces a shift from M2 to M1 polarization of macrophages [99]. This provides evidence of MET’s ability to enhance the balance between M1 and M2 macrophages. In addition, MET has demonstrated a reduction in the neutrophil count in patients with diabetes and polycystic ovarian disease. Furthermore, MET modulates the function of neutrophils by decreasing the formation of neutrophil extracellular traps (NETs) [100]. This effect is particularly relevant considering the involvement of neutrophils in various complications of SARS-CoV-2 infection [101].
The adaptive immune response begins with the recognition of specific antigens, marking the commencement of a cascade that transforms naive T cells into effector T cells. These effector cells can differentiate into T-helper cells (CD4) or cytotoxic T cells (CD8). In the MET-treated mouse model, the T-helper response showed a decrease in the levels of Th1 and Th17 cytokines profile through the downregulation of T-box and RORγt transcription factors [102]. Also, upregulation of the anti-inflammatory or immunosuppressive response has been reported, characterized by increased Th2 and T-regulatory cell subpopulations, respectively. Moreover, some reports have demonstrated that MET reduced the levels of autoantibodies in relevant autoimmune disease models. Similarly, MET has shown favorable outcomes in the context of cancer, such as reduced tumor progression and, in some cases, complete tumor eradication. This beneficial effect is attributed to enhancing the downregulation of the immunosuppressive T-regulatory cells and the upregulation of T memory cells [103,104].
Although the immunomodulatory effect of ATO has been less studied than that of MET, statins appear to play a crucial role in modulating the immune response at various levels. The growing body of evidence has identified statins as potential anti-inflammatory agents. As described above, several cholesterol metabolites and their associated nuclear receptors can regulate the immune system.
The in vitro studies investigating the impact of ATO on inflammatory cytokines, such as IL-6 and IL-1β, suggest a potential role in reducing their concentrations [105]. If applicable in vivo, this could imply that statins, like ATO, may possess the ability to mitigate the pro-inflammatory effects of these cytokines within tissues. For instance, the use of ATO in Multiple Sclerosis increased the levels of IL-4, IL-10, and TGF-β, while IL-17 and TNF-α decreased compared to the control group [106]. Similarly, in Kawasaki disease, ATO exhibited inhibitory effects in producing soluble mediators of inflammation, including IL-2 and TNF-α, impacting T cell proliferation [107].
Additional studies have highlighted the substantial immune-suppressive effects of statins on adaptive immune cells, leading to a decrease in the T cell quantity, impairment of antigen-presenting cell activation of T cells, and a shift toward Th2 cytokines, potentially resolving autoimmunity. Moreover, some reports have demonstrated an influence on humoral immunity in healthy individuals through the short-term statin administration, potentially leading to improved vaccine efficacy and immunomodulatory actions. This warrants further investigation to fully understand their implications in various health conditions [108,109,110].
5. Retrospective Studies and Clinical Trials That Have Evaluated the Potential for Use of Metformin and Atorvastatin during COVID-19
Several retrospective studies have examined the efficacy of specific drugs, such as MET and ATO, in combating COVID-19. These findings indicate that MET, a medication routinely recommended for diabetes, may have additional beneficial effects outside its typical application. Notably, diabetic individuals who were already undergoing MET therapy when diagnosed with COVID-19 showed a propensity for improved clinical results. Based on these investigations, it was found that these people had a diminished likelihood of developing severe manifestations of COVID-19. Additionally, they saw a decrease in the necessity for admission to intensive care units due to progression and severity and a lower mortality rate in comparison to individuals who were not using the medication. These findings are noteworthy as they indicate that MET can be used not only as a treatment for diabetes but also as a potential aid in mitigating the severity of COVID-19 [12,111,112,113].
On the other hand, dysbiosis in the intestinal microbiota has been described as contributing to the appearance and progression of many viral diseases, including COVID-19 and its subsequent manifestations (long COVID) [114]. MET has been shown to modulate the intestinal microbiota in patients with COVID-19, increasing the alpha diversity of bacteria, which contributes to the modulation of the immune response and reduces the appearance of long COVID cases [14,115,116].
However, research has also been conducted on ATO, a statin recognized for its role in cholesterol regulation, concerning COVID-19. Several retrospective cohort studies have indicated that this medication may be linked to a reduction in both COVID-19 mortality and progression. Despite the encouraging nature of these findings, they must be interpreted critically on account of the inherent limitations of these research studies [117,118,119]. In addition, it has been described that it can modulate the immune response of patients with COVID-19, preventing the appearance of long COVID, and as a treatment for this [120,121].
However, it is essential to consider these findings within the context of the methodological limitations of the studies and the need for further research, preferably through prospective clinical trials, to confirm these effects and better understand how these drugs can be used effectively against COVID-19.
5.1. Clinical Trials with Metformin
Several clinical trials have been conducted to investigate MET usage during COVID-19. A summary of them and their main findings are presented in Table 3.
Table 3.
Clinical trials with MET.
Evidence suggests that MET may be clinically beneficial for patients with COVID-19. For instance, Reis et al., 2022 conducted a randomized, placebo-controlled clinical trial in Brazil to determine the possible use of MET during COVID-19. The researchers enrolled 421 adults during different waves of SARS-CoV-2 variants to evaluate whether extended-release MET at a dose of 750 mg twice daily would provide benefits over placebo, even in patients already taking 1000 mg of immediate-release MET for conditions such as diabetes, prediabetes, weight loss, polycystic ovary syndrome, or nonalcoholic fatty liver disease. The relative risk of hospitalization or prolonged emergency service visit with MET was 1.03 (95% Bayesian credible interval, 0.64 to 1.66). In this trial, patients were started on MET at 1500 mg daily without dose adjustment, which may have caused side effects and discontinuations. However, hospitalization occurred in 8 of 168 patients (4.8%) in the MET group and 14 of 179 patients (7.8%) in the control group [10]. The authors suggest that MET was crucial in early treatment during the health crisis caused by COVID-19.
Another study was carried out by Ventura-López et al., 2022. The authors claim that MET is a therapeutic option for COVID-19 patients. They first evaluated the impact of MET in an in vitro model using lung cells infected with SARS-CoV-2 clinically isolated (alpha, delta, and epsilon variants of SARS-CoV-2). In the in vitro aspect, MET effectively inhibited viral replication after 48 h of exposure (IC50 189.8 µM) without showing toxicity up to doses of 100 µM and was effective against the variants studied [11].
The clinical trial in patients with SARS-CoV-2 infection and diagnosis of type 2 diabetes mellitus, performed as an adaptive, randomized, prospective, longitudinal, double-blind, multicenter, phase IIb study, compared MET administered at 620 mg twice daily for 14 days vs. placebo. In patients treated with MET, changes were observed in the levels of AST (33.8 to 31.5 U/L), lymphocytes (8.1 to 17%), neutrophils (85.2 to 76.2%), D-dimer (480 to 634 ng/mL), CPR (4.16 to 0.10 mg/L), DHL (257.5 to 256.5 µL/L) and IgG (969 to 781 mg/dL) from the beginning to the end of the study. Additionally, the MET group showed a notable reduction in the viral load, decreasing by 93.2% in just 3.3 days, compared to a 78.3% reduction in 5.6 days in the placebo group. The average hospitalization time was shorter in the MET group (8.8 days) compared to the placebo group (9.8 days), and the patients treated with MET required less supplemental oxygen (5.9 vs. 10.6 points) [11]. The average hospitalization time was shorter in the MET group (8.8 days) compared to the placebo group (9.8 days), and the patients treated with MET required less supplemental oxygen (5.9 vs. 10.6 points) [11]. Regarding safety, mild adverse events were recorded in both groups, with no incidences of hypoglycemia. This study highlights the potential efficacy of MET in decreasing the SARS-CoV-2 viral load and improving the clinical outcomes in patients with COVID-19 and type 2 diabetes mellitus [11].
Clinical studies were conducted by Bramante et al. in 2022, with a phase 3, double-blind, randomized, and placebo-controlled design. They tested the effectiveness of three repurposed drugs (MET, ivermectin, and fluvoxamine) in 1431 US patients with COVID-19 to prevent severe disease cases in non-hospitalized adults. The patients were between 30 and 85 years old, and all were overweight or obese. The outcome variables evaluated were hypoxia (≤93% oxygen saturation on home oximetry), emergency department visits, hospitalization, or death. The groups received the trial drugs according to the following doses: immediate-release MET administered with a dose escalation over six days to 1500 mg per day for 14 days, ivermectin at an amount of 390 to 470 μg per kilogram per day for three days, and fluvoxamine at a dose of 50 mg twice a day for 14 days [13].
Additionally, patients were asked to record the severity of their daily symptoms in paper diaries over 14 days. Neither overall signs nor specific symptoms of COVID-19 were reduced more rapidly with placebo than with any of the trial drugs. This study highlights no serious adverse events related to the medication [13].
Ultimately, the clinical trial concluded that none of the medications were effective in preventing hypoxia, ICU visits, hospitalization, or death. However, the authors mention that in the case of MET, there was a trend of benefit for the prevention of the severe form, according to their criteria (visit to the emergency department, hospitalization, or death), so they argue that more studies are needed with different doses or other populations to determine if any of the antiviral mechanisms (reduction of hepatitis C viral load [123]) or anti-inflammatory have clinical activity in the treatment of COVID-19 [13].
Derived from the previous study, two more studies were generated. In one of them, the authors followed up for up to 300 days with 1126 participants from the original study, who received MET plus ivermectin (group 1), MET plus fluvoxamine (group 2), MET plus placebo (group 3), ivermectin plus placebo (group 4), fluvoxamine plus placebo (group 5) or placebo plus placebo (group 6)), and they found that MET reduced the incidence of post-COVID-19 (4.1% absolute reduction) compared to the placebo. The main post-COVID-19 symptoms were fatigue, difficulty focusing, difficulty sleeping, difficulty breathing, headache, loss of taste, and depression [14].
The latest work was presented during a conference on retroviruses and opportunistic diseases in the USA by Boulware et al., 2023. In this work, they mention that MET has in vitro activity against SARS-CoV-2. Furthermore, they mention that in a randomized phase 3, quadruple-blind, placebo-controlled trial in 1323 participants, MET (1000 mg/day on days 2 to 5; 1500 mg/day on days 6 to 14) resulted in a 42% reduction in ER visits, hospitalizations, and deaths on day 14, a 58% reduction in hospitalizations and deaths on day 28, and a 42% reduction in long COVID in 10 months [122].
Additionally, they mention that MET reduced the viral load by 4.4 times compared to the placebo from baseline to follow-up (5, 10, and 14 days). The antiviral effect increased with an increasing MET dose on days 6 to 14. Conversely, they mention that the antiviral effect was more significant in the unvaccinated group (mean −0.95 log copies/mL) than in the vaccinated group (mean −0.39 log copies/mL). There were no changes in the viral load versus the placebo for ivermectin or fluvoxamine [122].
Finally, the authors conclude that MET reduced the viral load of SARS-CoV-2 in this clinical trial. The temporal relationship with dose titration suggests a dose-dependent effect. The magnitude of the antiviral effect was similar to that of nirmatrelvir on day five and more significant than that of nirmatrelvir on day ten. And they emphasize that MET is safe, widely available, and has few contraindications [122].
5.2. Clinical Trials with Atorvastatin
Several clinical trials investigated ATO usage during COVID-19. The following is a summary of them and their principal findings (Table 4).
Table 4.
Clinical trials with ATO.
On the other hand, ATO, a statin used to reduce cholesterol levels, has been researched due to its anti-inflammatory and anticoagulant properties. Davoodi et al., 2021 conducted a randomized controlled clinical trial on 40 Iranian adults hospitalized with COVID-19. Patients were randomly assigned (1:1) to a treatment group receiving ATO 40 mg + lopinavir/ritonavir 400/100 mg or a control group receiving lopinavir/ritonavir alone. ATO was administered as one tablet daily. In the case of lopinavir/ritonavir, it was administered twice daily. Both treatments were administered for five days [15].
The primary outcome of the trial was the length of hospitalization; the secondary outcomes were the need for interferon or immunoglobulin, receipt of invasive mechanical ventilation, O2 saturation (O2 sat), and C-reactive protein (CRP) level, assessed at baseline and on the sixth day of treatment [15].
The CRP level decreased significantly in the lopinavir/ritonavir + ATO group (p < 0.0001, Cohen’s d = 0.865) so that there was a significant difference in the CRP level on the sixth day between the two groups (p = 0.01). However, there was no significant difference in O2 sat on day 6. Although the duration of hospitalization in the lopinavir/ritonavir + ATO group was significantly reduced compared with the control group (p = 0.012), there was no significant difference in the invasive mechanical ventilation, receipt, and need for interferon and immunoglobulin. The authors conclude that combining ATO + lopinavir/ritonavir may be more effective than lopinavir/ritonavir in treating adult patients hospitalized with COVID-19 [15].
In another randomized controlled trial published in The BMJ, in 11 hospitals in Iran, 605 patients >18 years of age with COVID-19 admitted to the ICU participated. ATO 20 mg was administered orally once daily versus placebo; follow-up was performed for 30 days from randomization, regardless of the hospital discharge status [16].
Death occurred in 90 (31%) patients in the ATO group and 103 (35%) in the placebo group (odds ratio 0.84, 95% confidence interval 0.58 to 1.22). The venous thromboembolism rates were 2% (n = 6) in the ATO group and 3% (n = 9) in the placebo group (odds ratio 0.71, 95% confidence interval: 0.24 to 2.06). Myopathy was not diagnosed clinically in either group. The liver enzyme levels increased (2%) in five patients assigned to ATO and six assigned to placebo (odds ratio 0.85, 95% confidence interval 0.25 to 2.81). The main drugs in the co-treatment were aspirin and antivirals such as remdesivir and favipiravir [16].
The authors conclude that ATO was not associated with a significant reduction in composite venous or arterial thrombosis, extracorporeal membrane oxygenation treatment, or all-cause mortality compared with placebo. However, the treatment was found to be safe. The overall event rates were lower than expected, so a clinically significant treatment effect cannot be excluded. Furthermore, they found a slight reduction in white blood cells, platelets, and D-dimer levels in the patients treated with ATO [16].
Visos-Varela et al., 2023 analyzed the chronic use of statins (simvastatin, lovastatin, pravastatin, fluvastatin, ATO, rosuvastatin, and pitavastatin) and severe outcomes of COVID-19 (risk of hospitalization and mortality), progression to severe consequences and susceptibility to the virus. The study evaluated the risk of hospitalization, mortality, progression, and susceptibility to COVID-19. They collected data on 2821 hospitalized cases, 26,996 non-hospitalized cases, and 52,318 controls [121].
Chronic use of ATO was associated with a decreased risk of hospitalization (adjusted odds ratios [aOR] = 0.83; 95% confidence interval [CI]: 0.74–0.92) and mortality (aOR = 0.70; 95% CI: 0.53–0.93), partly attributable to a lower risk of susceptibility to the virus (aOR = 0.91; 95% CI: 0.86–0.96) [121].
On the other hand, simvastatin was associated with a reduced mortality risk (aOR = 0.59, 95% CI: 0.40–0.87). The large degree of heterogeneity observed in the estimated OR of the different statins suggests that there was no class effect. In conclusion, the authors suggest that chronic use of ATO (and, to a lesser extent, simvastatin) is associated with a decreased risk of severe COVID-19 outcomes [121].6. Conclusions and Future Perspectives
The possibility of MET and ATO as therapeutic therapies for COVID-19 is highly promising. These medications, commonly used for treating diabetes and dyslipidemia, have shown notable immunomodulatory and antiviral effects that could be crucial against SARS-CoV-2. Ensuring effective, widely available, and safe treatments is especially critical during the current worldwide health emergency.
Notably, the cost-effectiveness of these treatments must not be disregarded. MET and ATO, being generic pharmaceuticals, represent a cost-efficient [124,125] substitute for more recent, trademarked anti-SARS-CoV-2 medications like Paxlovid® [126]. Their FDA and Cofepris (Mexico) approvals for diabetes management demonstrate their thorough examinations for safety and effectiveness [127,128], which increases confidence in their use for COVID-19 based on positive results from earlier clinical trials.
The role of MET extends beyond managing diabetes, as its antidiabetic actions can potentially reduce the severity and mortality of COVID-19. Through the partial inhibition of mitochondrial complex I and the activation of AMPK, MET enhances insulin sensitivity and has possible antiviral properties. Moreover, the capacity of ATO to reduce cholesterol levels and regulate immunological responses could be quite beneficial, particularly in severe instances of COVID-19 that are distinguished by an excessively aggressive immune response.
The available evidence, however varied, tends to favor optimism. Several research studies suggest that using MET and ATO can effectively reduce the severity and mortality of COVID-19, while some studies advise interpreting the results with caution. The documented advantages in specific patient cohorts, such as decreased hospitalizations and mortality rates, underscore their potential to impact patient outcomes effectively.
However, the journey from observation to clinical implementation is fraught with obstacles. The presence of diverse study approaches and patient demographics necessitates meticulous data analysis. Conducting prospective randomized controlled trials is crucial for confirming these results and finding the most efficient use of MET and ATO in treating COVID-19. Furthermore, considering the wide range of possible adverse effects, it is necessary to reevaluate these treatments’ widely recognized safety profiles in COVID-19.
Amidst the ongoing challenges posed by the COVID-19 pandemic, repurposing MET and ATO is a promising and innovative gesture. Due to their cost-effectiveness, wide availability, and extensive safety records, they are highly suitable for reapplication. Nevertheless, this endeavor necessitates thorough investigation, precise examination, and a steadfast commitment to comprehending their significance in the COVID-19 storyline. By following this road, we will be able to fully utilize the therapeutic capabilities of MET and ATO, providing a more promising future in this ongoing global health crisis.
Author Contributions
Conceptualization: L.A.D.J.-G., R.M.d.Á., S.N.P.-R., C.D.C.-R. and C.N.F.-M.; funding acquisition: L.A.D.J.-G. and R.M.d.Á.; investigation: A.R.-C., J.V.T.-P., C.N.F.-M., J.F.O.-R., J.M.R.-R., B.R.-S., M.L.-J. and A.C.G.-H.; supervision: L.A.D.J.-G., R.M.d.Á., S.N.P.-R., C.D.C.-R. and C.N.F.-M.; visualization: B.R.-S., M.L.-J., A.C.G.-H., A.C.R.-C., E.A.L.-G. and E.M.-R.; writing—review and editing: A.R.-C., J.V.T.-P., C.N.F.-M., J.F.O.-R., J.M.R.-R., B.R.-S., M.L.-J. and A.C.G.-H. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by grants Pronaii 302979 and A1-S-9005 CONAHCyT (México) from R.M.D.Á. Additionally, it was funded by FUNDACIÓN IMSS, AC (LADJG). However, the funders had no role in study design, data collection, analysis, publication decision, or article preparation.
Acknowledgments
L.A.D.J.-G., R.M.d.Á., A.R.-C., C.N.F.-M., J.F.O.-R., J.M.R.-R., B.R.-S. and M.L.-J. acknowledge their membership of the National System of Research (SNI CONAHCyT). SPR, CDCR, and JVTP appreciate the scholarship provided by CONAHCyT for doctoral or postdoctoral studies. We also thank the MDPI editorial board for their advice. The vatillos team.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Cascella, M.; Rajnik, M.; Aleem, A.; Dulebohn, S.C.; Di Napoli, R. Features, Evaluation, and Treatment of Coronavirus (COVID-19). In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2023. [Google Scholar]
- Reyes-Ruiz, J.M.; García-Hernández, O.; Martínez-Mier, G.; Osuna-Ramos, J.F.; De Jesús-González, L.A.; Farfan-Morales, C.N.; Palacios-Rápalo, S.N.; Cordero-Rivera, C.D.; Ordoñez-Rodríguez, T.; Ángel, R.M.d. The Role of Aspartate Aminotransferase-to-Lymphocyte Ratio Index (ALRI) in Predicting Mortality in SARS-CoV-2 Infection. Microorganisms 2023, 11, 2894. [Google Scholar] [CrossRef] [Scilit]
- Li, G.; Hilgenfeld, R.; Whitley, R.; De Clercq, E. Therapeutic Strategies for COVID-19: Progress and Lessons Learned. Nat. Rev. Drug Discov. 2023, 22, 449–475. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumari, M.; Lu, R.-M.; Li, M.-C.; Huang, J.-L.; Hsu, F.-F.; Ko, S.-H.; Ke, F.-Y.; Su, S.-C.; Liang, K.-H.; Yuan, J.P.-Y.; et al. A Critical Overview of Current Progress for COVID-19: Development of Vaccines, Antiviral Drugs, and Therapeutic Antibodies. J. Biomed. Sci. 2022, 29, 68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akkiz, H. Implications of the Novel Mutations in the SARS-CoV-2 Genome for Transmission, Disease Severity, and the Vaccine Development. Front. Med. 2021, 8, 636532. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- El-Mir, M.Y.; Nogueira, V.; Fontaine, E.; Avéret, N.; Rigoulet, M.; Leverve, X. Dimethylbiguanide Inhibits Cell Respiration via an Indirect Effect Targeted on the Respiratory Chain Complex I. J. Biol. Chem. 2000, 275, 223–228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hawley, S.A.; Ross, F.A.; Chevtzoff, C.; Green, K.A.; Evans, A.; Fogarty, S.; Towler, M.C.; Brown, L.J.; Ogunbayo, O.A.; Evans, A.M.; et al. Use of Cells Expressing Gamma Subunit Variants to Identify Diverse Mechanisms of AMPK Activation. Cell Metab. 2010, 11, 554–565. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Conde, K.; Pineda, G.; Newton, R.S.; Fernandez, M.L. Hypocholesterolemic Effects of 3-Hydroxy-3-Methylglutaryl Coenzyme A (HMG-CoA) Reductase Inhibitors in the Guinea Pig: Atorvastatin versus Simvastatin. Biochem. Pharmacol. 1999, 58, 1209–1219. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chong, P.H.; Seeger, J.D. Atorvastatin Calcium: An Addition to HMG-CoA Reductase Inhibitors. Pharmacotherapy 1997, 17, 1157–1177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reis, G.; Silva, E.A.d.S.M.; Silva, D.C.M.; Thabane, L.; Milagres, A.C.; Ferreira, T.S.; dos Santos, C.V.Q.; Neto, A.D.d.F.; Callegari, E.D.; Savassi, L.C.M.; et al. Effect of Early Treatment with Metformin on Risk of Emergency Care and Hospitalization among Patients with COVID-19: The TOGETHER Randomized Platform Clinical Trial. Lancet Reg. Health Am. 2022, 6, 100142. [Google Scholar] [CrossRef] [Scilit]
- Ventura-López, C.; Cervantes-Luevano, K.; Aguirre-Sánchez, J.S.; Flores-Caballero, J.C.; Alvarez-Delgado, C.; Bernaldez-Sarabia, J.; Sánchez-Campos, N.; Lugo-Sánchez, L.A.; Rodríguez-Vázquez, I.C.; Sander-Padilla, J.G.; et al. Treatment with Metformin Glycinate Reduces SARS-CoV-2 Viral Load: An in Vitro Model and Randomized, Double-Blind, Phase IIb Clinical Trial. Biomed. Pharmacother. 2022, 152, 113223. [Google Scholar] [CrossRef] [Scilit]
- Bramante, C.T.; Ingraham, N.E.; Murray, T.A.; Marmor, S.; Hovertsen, S.; Gronski, J.; McNeil, C.; Feng, R.; Guzman, G.; Abdelwahab, N.; et al. Metformin and Risk of Mortality in Patients Hospitalised with COVID-19: A Retrospective Cohort Analysis. Lancet Healthy Longev. 2021, 2, e34–e41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bramante, C.T.; Huling, J.D.; Tignanelli, C.J.; Buse, J.B.; Liebovitz, D.M.; Nicklas, J.M.; Cohen, K.; Puskarich, M.A.; Belani, H.K.; Proper, J.L.; et al. Randomized Trial of Metformin, Ivermectin, and Fluvoxamine for COVID-19. N. Engl. J. Med. 2022, 387, 599–610. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bramante, C.T.; Buse, J.B.; Liebovitz, D.M.; Nicklas, J.M.; Puskarich, M.A.; Cohen, K.; Belani, H.K.; Anderson, B.J.; Huling, J.D.; Tignanelli, C.J.; et al. Outpatient Treatment of COVID-19 and Incidence of Post-COVID-19 Condition over 10 Months (COVID-OUT): A Multicentre, Randomised, Quadruple-Blind, Parallel-Group, Phase 3 Trial. Lancet Infect. Dis. 2023, 23, 1119–1129. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davoodi, L.; Jafarpour, H.; Oladi, Z.; Zakariaei, Z.; Tabarestani, M.; Ahmadi, B.M.; Razavi, A.; Hessami, A. Atorvastatin Therapy in COVID-19 Adult Inpatients: A Double-Blind, Randomized Controlled Trial. Int. J. Cardiol. Heart Vasc. 2021, 36, 100875. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Investigators, I.-S. Atorvastatin versus Placebo in Patients with COVID-19 in Intensive Care: Randomized Controlled Trial. BMJ 2022, 376, e068407. [Google Scholar] [CrossRef] [Scilit]
- Nasri, H.; Rafieian-Kopaei, M. Metformin: Current Knowledge. J. Res. Med. Sci. 2014, 19, 658–664. [Google Scholar] [PubMed]
- Bailey, C.J.; Turner, R.C. Metformin. N. Engl. J. Med. 1996, 334, 574–579. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sum, C.F.; Webster, J.M.; Johnson, A.B.; Catalano, C.; Cooper, B.G.; Taylor, R. The Effect of Intravenous Metformin on Glucose Metabolism during Hyperglycaemia in Type 2 Diabetes. Diabet. Med. 1992, 9, 61–65. [Google Scholar] [CrossRef] [Scilit]
- Scarpello, J.H.B.; Howlett, H.C.S. Metformin Therapy and Clinical Uses. Diab. Vasc. Dis. Res. 2008, 5, 157–167. [Google Scholar] [CrossRef] [Scilit]
- DeFronzo, R.A.; Goodman, A.M. Efficacy of Metformin in Patients with Non-Insulin-Dependent Diabetes Mellitus. N. Engl. J. Med. 1995, 333, 541–549. [Google Scholar] [CrossRef] [Scilit]
- Giannarelli, R.; Aragona, M.; Coppelli, A.; Del Prato, S. Reducing Insulin Resistance with Metformin: The Evidence Today. Diabetes Metab. 2003, 29, 6S28–6S35. [Google Scholar] [CrossRef] [Scilit]
- Madiraju, A.K.; Erion, D.M.; Rahimi, Y.; Zhang, X.-M.; Braddock, D.T.; Albright, R.A.; Prigaro, B.J.; Wood, J.L.; Bhanot, S.; MacDonald, M.J.; et al. Metformin Suppresses Gluconeogenesis by Inhibiting Mitochondrial Glycerophosphate Dehydrogenase. Nature 2014, 510, 542–546. [Google Scholar] [CrossRef] [Scilit]
- LaMoia, T.E.; Shulman, G.I. Cellular and Molecular Mechanisms of Metformin Action. Endocr. Rev. 2021, 42, 77–96. [Google Scholar] [CrossRef] [Scilit]
- Xiao, B.; Heath, R.; Saiu, P.; Leiper, F.C.; Leone, P.; Jing, C.; Walker, P.A.; Haire, L.; Eccleston, J.F.; Davis, C.T.; et al. Structural Basis for AMP Binding to Mammalian AMP-Activated Protein Kinase. Nature 2007, 449, 496–500. [Google Scholar] [CrossRef] [Scilit]
- Hawley, S.A.; Boudeau, J.; Reid, J.L.; Mustard, K.J.; Udd, L.; Mäkelä, T.P.; Alessi, D.R.; Hardie, D.G. Complexes between the LKB1 Tumor Suppressor, STRAD Alpha/Beta and MO25 Alpha/Beta Are Upstream Kinases in the AMP-Activated Protein Kinase Cascade. J. Biol. 2003, 2, 28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hawley, S.A.; Pan, D.A.; Mustard, K.J.; Ross, L.; Bain, J.; Edelman, A.M.; Frenguelli, B.G.; Hardie, D.G. Calmodulin-Dependent Protein Kinase Kinase-Beta Is an Alternative Upstream Kinase for AMP-Activated Protein Kinase. Cell Metab. 2005, 2, 9–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shaw, R.J.; Lamia, K.A.; Vasquez, D.; Koo, S.-H.; Bardeesy, N.; Depinho, R.A.; Montminy, M.; Cantley, L.C. The Kinase LKB1 Mediates Glucose Homeostasis in Liver and Therapeutic Effects of Metformin. Science 2005, 310, 1642–1646. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fullerton, M.D.; Galic, S.; Marcinko, K.; Sikkema, S.; Pulinilkunnil, T.; Chen, Z.-P.; O’Neill, H.M.; Ford, R.J.; Palanivel, R.; O’Brien, M.; et al. Single Phosphorylation Sites in Acc1 and Acc2 Regulate Lipid Homeostasis and the Insulin-Sensitizing Effects of Metformin. Nat. Med. 2013, 19, 1649–1654. [Google Scholar] [CrossRef] [Scilit]
- Badr, D.; Kurban, M.; Abbas, O. Metformin in Dermatology: An Overview. J. Eur. Acad. Dermatol. Venereol. 2013, 27, 1329–1335. [Google Scholar] [CrossRef] [Scilit]
- Frid, A.; Sterner, G.N.; Löndahl, M.; Wiklander, C.; Cato, A.; Vinge, E.; Andersson, A. Novel Assay of Metformin Levels in Patients with Type 2 Diabetes and Varying Levels of Renal Function: Clinical Recommendations. Diabetes Care 2010, 33, 1291–1293. [Google Scholar] [CrossRef] [Scilit]
- Endo, A. The Discovery and Development of HMG-CoA Reductase Inhibitors. J. Lipid Res. 1992, 33, 1569–1582. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goldstein, J.L.; Brown, M.S. Regulation of the Mevalonate Pathway. Nature 1990, 343, 425–430. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Roglans, N.; Verd, J.C.; Peris, C.; Alegret, M.; Vázquez, M.; Adzet, T.; Díaz, C.; Hernández, G.; Laguna, J.C.; Sánchez, R.M. High Doses of Atorvastatin and Simvastatin Induce Key Enzymes Involved in VLDL Production. Lipids 2002, 37, 445–454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wierzbicki, A.S. Atorvastatin. Expert Opin. Pharmacother. 2001, 2, 819–830. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carro, A.C.; Damonte, E.B. Requirement of Cholesterol in the Viral Envelope for Dengue Virus Infection. Virus Res. 2013, 174, 78–87. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xun, Y.-H.; Zhang, Y.-J.; Pan, Q.-C.; Mao, R.-C.; Qin, Y.-L.; Liu, H.-Y.; Zhang, Y.-M.; Yu, Y.-S.; Tang, Z.-H.; Lu, M.-J.; et al. Metformin Inhibits Hepatitis B Virus Protein Production and Replication in Human Hepatoma Cells. J. Viral. Hepat. 2014, 21, 597–603. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hoppe-Seyler, K.; Herrmann, A.L.; Däschle, A.; Kuhn, B.J.; Strobel, T.D.; Lohrey, C.; Bulkescher, J.; Krijgsveld, J.; Hoppe-Seyler, F. Effects of Metformin on the Virus/Host Cell Crosstalk in Human Papillomavirus-Positive Cancer Cells. Int. J. Cancer 2021, 149, 1137–1149. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, R.; Feng, C.; Luo, D.; Zhao, R.; Kannan, P.R.; Yin, Y.; Iqbal, M.Z.; Hu, Y.; Kong, X. Metformin Hydrochloride Significantly Inhibits Rotavirus Infection in Caco2 Cell Line, Intestinal Organoids, and Mice. Pharmaceuticals 2023, 16, 1279. [Google Scholar] [CrossRef] [Scilit]
- Jiang, Z.; Liu, H. Metformin Inhibits Tumorigenesis in HBV-Induced Hepatocellular Carcinoma by Suppressing HULC Overexpression Caused by HBX. J. Cell Biochem. 2018, 119, 4482–4495. [Google Scholar] [CrossRef] [Scilit]
- Farfan-Morales, C.N.; Cordero-Rivera, C.D.; Osuna-Ramos, J.F.; Monroy-Muñoz, I.E.; De Jesús-González, L.A.; Muñoz-Medina, J.E.; Hurtado-Monzón, A.M.; Reyes-Ruiz, J.M.; del Ángel, R.M. The Antiviral Effect of Metformin on Zika and Dengue Virus Infection. Sci. Rep. 2021, 11, 8743. [Google Scholar] [CrossRef] [Scilit]
- Parthasarathy, H.; Tandel, D.; Siddiqui, A.H.; Harshan, K.H. Metformin Suppresses SARS-CoV-2 in Cell Culture. Virus Res. 2022, 323, 199010. [Google Scholar] [CrossRef] [Scilit]
- Curry, J.M.; Johnson, J.; Mollaee, M.; Tassone, P.; Amin, D.; Knops, A.; Whitaker-Menezes, D.; Mahoney, M.G.; South, A.; Rodeck, U.; et al. Metformin Clinical Trial in HPV+ and HPV- Head and Neck Squamous Cell Carcinoma: Impact on Cancer Cell Apoptosis and Immune Infiltrate. Front. Oncol. 2018, 8, 436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abdelmoneim, M.; Eissa, I.R.; Aboalela, M.A.; Naoe, Y.; Matsumura, S.; Sibal, P.A.; Bustos-Villalobos, I.; Tanaka, M.; Kodera, Y.; Kasuya, H. Metformin Enhances the Antitumor Activity of Oncolytic Herpes Simplex Virus HF10 (Canerpaturev) in a Pancreatic Cell Cancer Subcutaneous Model. Sci. Rep. 2022, 12, 21570. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Granato, M.; Gilardini Montani, M.S.; Romeo, M.A.; Santarelli, R.; Gonnella, R.; D’Orazi, G.; Faggioni, A.; Cirone, M. Metformin Triggers Apoptosis in PEL Cells and Alters Bortezomib-Induced Unfolded Protein Response Increasing Its Cytotoxicity and Inhibiting KSHV Lytic Cycle Activation. Cell. Signal. 2017, 40, 239–247. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, X.; Wang, H.; Yi, P.; Baker, C.; Casey, G.; Xie, X.; Luo, H.; Cai, J.; Fan, X.; Soong, L.; et al. Metformin Restrains ZIKV Replication and Alleviates Virus-Induced Inflammatory Responses in Microglia. Int. Immunopharmacol. 2023, 121, 110512. [Google Scholar] [CrossRef] [Scilit]
- del Campo, J.A.; García Valdecasas, M.; Gil Gómez, A.; Rojas Alvarez-Ossorio, M.A.; Gallego, P.; Ampuero Herrojo, J.; Gallego Durán, R.; Pastor, H.; Grande, L.; Padillo Ruiz, F.J.; et al. Simvastatin and Metformin Inhibit Cell Growth in Hepatitis C Virus Infected Cells via mTOR Increasing PTEN and Autophagy. PLoS ONE 2018, 13, e0191805. [Google Scholar] [CrossRef] [Scilit]
- Tsai, W.-L.; Chang, T.-H.; Sun, W.-C.; Chan, H.-H.; Wu, C.-C.; Hsu, P.-I.; Cheng, J.-S.; Yu, M.-L. Metformin Activates Type I Interferon Signaling against HCV via Activation of Adenosine Monophosphate-Activated Protein Kinase. Oncotarget 2017, 8, 91928–91937. [Google Scholar] [CrossRef] [Scilit]
- Lee, H.S.; Noh, J.Y.; Song, J.Y.; Cheong, H.J.; Kim, W.J. Metformin Reduces the Risk of Developing Influenza A Virus Related Cardiovascular Disease. Heliyon 2023, 9, e20284. [Google Scholar] [CrossRef] [Scilit]
- Planas, D.; Pagliuzza, A.; Ponte, R.; Fert, A.; Marchand, L.R.; Massanella, M.; Gosselin, A.; Mehraj, V.; Dupuy, F.P.; Isnard, S.; et al. LILAC Pilot Study: Effects of Metformin on mTOR Activation and HIV Reservoir Persistence during Antiretroviral Therapy. EBioMedicine 2021, 65, 103270. [Google Scholar] [CrossRef] [Scilit]
- Masich, A.M.; Thompson, L.; Fulco, P.P. Bictegravir and Metformin Drug-Drug Interaction in People with Human Immunodeficiency Virus (HIV). Infect. Dis. Rep. 2023, 15, 231–237. [Google Scholar] [CrossRef] [Scilit]
- Farfan-Morales, C.N.; Cordero-Rivera, C.D.; Reyes-Ruiz, J.M.; Hurtado-Monzón, A.M.; Osuna-Ramos, J.F.; González-González, A.M.; De Jesús-González, L.A.; Palacios-Rápalo, S.N.; del Ángel, R.M. Anti-Flavivirus Properties of Lipid-Lowering Drugs. Front. Physiol. 2021, 12, 749770. [Google Scholar] [CrossRef] [Scilit]
- Osuna-Ramos, J.F.; Farfan-Morales, C.N.; Cordero-Rivera, C.D.; De Jesús-González, L.A.; Reyes-Ruiz, J.M.; Hurtado-Monzón, A.M.; Palacios-Rápalo, S.N.; Jiménez-Camacho, R.; Meraz-Ríos, M.A.; Del Ángel, R.M. Cholesterol-Lowering Drugs as Potential Antivirals: A Repurposing Approach against Flavivirus Infections. Viruses 2023, 15, 1465. [Google Scholar] [CrossRef] [Scilit]
- Herrera-Moro Huitron, L.; De Jesús-González, L.A.; Martínez-Castillo, M.; Ulloa-Aguilar, J.M.; Cabello-Gutierrez, C.; Helguera-Repetto, C.; Garcia-Cordero, J.; León Juárez, M. Multifaceted Nature of Lipid Droplets in Viral Interactions and Pathogenesis. Microorganisms 2023, 11, 1851. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Owen, M.R.; Doran, E.; Halestrap, A.P. Evidence That Metformin Exerts Its Anti-Diabetic Effects through Inhibition of Complex 1 of the Mitochondrial Respiratory Chain. Biochem. J. 2000, 348 Pt 3, 607–614. [Google Scholar] [CrossRef] [PubMed]
- Fontaine, E. Metformin-Induced Mitochondrial Complex I Inhibition: Facts, Uncertainties, and Consequences. Front. Endocrinol. 2018, 9, 753. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Soto-Acosta, R.; Bautista-Carbajal, P.; Cervantes-Salazar, M.; Angel-Ambrocio, A.H.; Del Angel, R.M. DENV Up-Regulates the HMG-CoA Reductase Activity through the Impairment of AMPK Phosphorylation: A Potential Antiviral Target. PLoS Pathog. 2017, 13, e1006257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Honda, M.; Shirasaki, T.; Terashima, T.; Kawaguchi, K.; Nakamura, M.; Oishi, N.; Wang, X.; Shimakami, T.; Okada, H.; Arai, K.; et al. Hepatitis B Virus (HBV) Core-Related Antigen During Nucleos(t)Ide Analog Therapy Is Related to Intra-Hepatic HBV Replication and Development of Hepatocellular Carcinoma. J. Infect. Dis. 2016, 213, 1096–1106. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharma, T.; Abohashrh, M.; Baig, M.H.; Dong, J.-J.; Alam, M.M.; Ahmad, I.; Irfan, S. Screening of Drug Databank against WT and Mutant Main Protease of SARS-CoV-2: Towards Finding Potential Compound for Repurposing against COVID-19. Saudi J. Biol. Sci. 2021, 28, 3152–3159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, V.; Liu, H.; Wu, C. Drug Repurposing against SARS-CoV-2 Receptor Binding Domain Using Ensemble-Based Virtual Screening and Molecular Dynamics Simulations. Comput. Biol. Med. 2021, 135, 104634. [Google Scholar] [CrossRef] [Scilit]
- Duarte, R.R.R.; Copertino, D.C.; Iñiguez, L.P.; Marston, J.L.; Bram, Y.; Han, Y.; Schwartz, R.E.; Chen, S.; Nixon, D.F.; Powell, T.R. Identifying FDA-Approved Drugs with Multimodal Properties against COVID-19 Using a Data-Driven Approach and a Lung Organoid Model of SARS-CoV-2 Entry. Mol. Med. 2021, 27, 105. [Google Scholar] [CrossRef] [Scilit]
- Zapata-Cardona, M.I.; Flórez-Álvarez, L.; Zapata-Builes, W.; Guerra-Sandoval, A.L.; Guerra-Almonacid, C.M.; Hincapié-García, J.; Rugeles, M.T.; Hernandez, J.C. Atorvastatin Effectively Inhibits Ancestral and Two Emerging Variants of SARS-CoV-2 in Vitro. Front. Microbiol. 2022, 13, 721103. [Google Scholar] [CrossRef] [Scilit]
- Segatori, V.I.; Garona, J.; Caligiuri, L.G.; Bizzotto, J.; Lavignolle, R.; Toro, A.; Sanchis, P.; Spitzer, E.; Krolewiecki, A.; Gueron, G.; et al. Effect of Ivermectin and Atorvastatin on Nuclear Localization of Importin Alpha and Drug Target Expression Profiling in Host Cells from Nasopharyngeal Swabs of SARS-CoV-2-Positive Patients. Viruses 2021, 13, 2084. [Google Scholar] [CrossRef] [Scilit]
- Bryan-Marrugo, O.L.; Arellanos-Soto, D.; Rojas-Martinez, A.; Barrera-Saldaña, H.; Ramos-Jimenez, J.; Vidaltamayo, R.; Rivas-Estilla, A.M. The Anti-dengue Virus Properties of Statins May Be Associated with Alterations in the Cellular Antiviral Profile Expression. Mol. Med. Rep. 2016, 14, 2155–2163. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Palacios-Rápalo, S.N.; Farfan-Morales, C.N.; Cordero-Rivera, C.D.; De Jesús-González, L.A.; Reyes-Ruiz, J.M.; Meraz-Ríos, M.A.; Del Ángel, R.M. An Ivermectin—Atorvastatin Combination Impairs Nuclear Transport Inhibiting Dengue Infection in Vitro and in Vivo. iScience 2023, 26, 108294. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Españo, E.; Kim, J.-K. Effects of Statin Combinations on Zika Virus Infection in Vero Cells. Pharmaceutics 2022, 15, 50. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stoyanova, G.; Jabeen, S.; Landazuri Vinueza, J.; Ghosh Roy, S.; Lockshin, R.A.; Zakeri, Z. Zika Virus Triggers Autophagy to Exploit Host Lipid Metabolism and Drive Viral Replication. Cell Commun. Signal. 2023, 21, 114. [Google Scholar] [CrossRef] [Scilit]
- Wani, M.A.; Mukherjee, S.; Mallick, S.; Akbar, I.; Basu, A. Atorvastatin Ameliorates Viral Burden and Neural Stem/Progenitor Cell (NSPC) Death in an Experimental Model of Japanese Encephalitis. J. Biosci. 2020, 45, 77. [Google Scholar] [CrossRef] [Scilit]
- Ikeda, M.; Kato, N. Life Style-Related Diseases of the Digestive System: Cell Culture System for the Screening of Anti-Hepatitis C Virus (HCV) Reagents: Suppression of HCV Replication by Statins and Synergistic Action with Interferon. J. Pharmacol. Sci. 2007, 105, 145–150. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ikeda, M.; Abe, K.; Yamada, M.; Dansako, H.; Naka, K.; Kato, N. Different Anti-HCV Profiles of Statins and Their Potential for Combination Therapy with Interferon. Hepatology 2006, 44, 117–125. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Todorovska, B.; Caloska-Ivanova, V.; Dimitrova-Genadieva, M.; Trajkovska, M.; Popova-Jovanovska, R.; Grivceva-Stardelova, K.; Licoska-Josifovic, F.; Andreevski, V.; Curakova-Ristovska, E.; Joksimovic, N. Atorvastatin in Combination with Pegylated Interferon and Ribavirin Provided High Rate of Sustained Virological Response in Patients with Genotype 3 Hepatitis C Virus. Open Access Maced. J. Med. Sci. 2019, 7, 1641–1648. [Google Scholar] [CrossRef] [Scilit]
- Simon, T.G.; Bonilla, H.; Yan, P.; Chung, R.T.; Butt, A.A. Atorvastatin and Fluvastatin Are Associated with Dose-Dependent Reductions in Cirrhosis and Hepatocellular Carcinoma, among Patients with Hepatitis C Virus: Results from ERCHIVES. Hepatology 2016, 64, 47–57. [Google Scholar] [CrossRef] [Scilit]
- Guan, J.; Sun, X.; Liang, Y.; Dong, W.; Zhang, L.; Zhu, J.; Wang, G. Atorvastatin Attenuates Coxsackie Virus B3m-Induced Viral Myocarditis in Mice. J. Cardiovasc. Pharmacol. 2010, 56, 540–547. [Google Scholar] [CrossRef] [Scilit]
- Episcopio, D.; Aminov, S.; Benjamin, S.; Germain, G.; Datan, E.; Landazuri, J.; Lockshin, R.A.; Zakeri, Z. Atorvastatin Restricts the Ability of Influenza Virus to Generate Lipid Droplets and Severely Suppresses the Replication of the Virus. FASEB J. 2019, 33, 9516–9525. [Google Scholar] [CrossRef] [Scilit]
- Ianevski, A.; Yao, R.; Zusinaite, E.; Lysvand, H.; Oksenych, V.; Tenson, T.; Bjørås, M.; Kainov, D. Active Components of Commonly Prescribed Medicines Affect Influenza A Virus-Host Cell Interaction: A Pilot Study. Viruses 2021, 13, 1537. [Google Scholar] [CrossRef] [Scilit]
- Zhao, J.; Zeng, Z.; Chen, Y.; Liu, W.; Chen, H.; Fu, Z.F.; Zhao, L.; Zhou, M. Lipid Droplets Are Beneficial for Rabies Virus Replication by Facilitating Viral Budding. J. Virol. 2022, 96, e0147321. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mystakelis, H.A.; Wilson, E.; Laidlaw, E.; Poole, A.; Krishnan, S.; Rupert, A.; Welker, J.L.; Gorelick, R.J.; Lisco, A.; Manion, M.; et al. An Open Label Randomized Controlled Trial of Atorvastatin versus Aspirin in Elite Controllers and Antiretroviral-Treated People with HIV. AIDS 2023, 37, 1827–1835. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Overton, E.T.; Sterrett, S.; Westfall, A.O.; Kahan, S.M.; Burkholder, G.; Zajac, A.J.; Goepfert, P.A.; Bansal, A. Effects of Atorvastatin and Pravastatin on Immune Activation and T-Cell Function in Antiretroviral Therapy-Suppressed HIV-1-Infected Patients. AIDS 2014, 28, 2627–2631. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ganesan, A.; Crum-Cianflone, N.; Higgins, J.; Qin, J.; Rehm, C.; Metcalf, J.; Brandt, C.; Vita, J.; Decker, C.F.; Sklar, P.; et al. High Dose Atorvastatin Decreases Cellular Markers of Immune Activation without Affecting HIV-1 RNA Levels: Results of a Double-Blind Randomized Placebo Controlled Clinical Trial. J. Infect. Dis. 2011, 203, 756–764. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Negredo, E.; Clotet, B.; Puig, J.; Pérez-Alvarez, N.; Ruiz, L.; Romeu, J.; Moltó, J.; Rey-Joly, C.; Blanco, J. The Effect of Atorvastatin Treatment on HIV-1-Infected Patients Interrupting Antiretroviral Therapy. AIDS 2006, 20, 619–621. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Riestenberg, R.A.; Furman, A.; Cowen, A.; Pawlowksi, A.; Schneider, D.; Lewis, A.A.; Kelly, S.; Taiwo, B.; Achenbach, C.; Palella, F.; et al. Differences in Statin Utilization and Lipid Lowering by Race, Ethnicity, and HIV Status in a Real-World Cohort of Persons with Human Immunodeficiency Virus and Uninfected Persons. Am. Heart J. 2019, 209, 79–87. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Negredo, E.; Puigdomènech, I.; Marfil, S.; Puig, J.; Pérez-Alvarez, N.; Ruiz, L.; Rey-Joly, C.; Clotet, B.; Blanco, J. Association between HIV Replication and Cholesterol in Peripheral Blood Mononuclear Cells in HIV-Infected Patients Interrupting HAART. J. Antimicrob. Chemother. 2008, 61, 400–404. [Google Scholar] [CrossRef] [Scilit]
- Calza, L.; Trapani, F.; Bartoletti, M.; Manfredi, R.; Colangeli, V.; Borderi, M.; Grossi, G.; Motta, R.; Viale, P. Statin Therapy Decreases Serum Levels of High-Sensitivity C-Reactive Protein and Tumor Necrosis Factor-α in HIV-Infected Patients Treated with Ritonavir-Boosted Protease Inhibitors. HIV Clin. Trials 2012, 13, 153–161. [Google Scholar] [CrossRef] [Scilit]
- Zhang, J.; Dong, J.; Martin, M.; He, M.; Gongol, B.; Marin, T.L.; Chen, L.; Shi, X.; Yin, Y.; Shang, F.; et al. AMP-Activated Protein Kinase Phosphorylation of Angiotensin-Converting Enzyme 2 in Endothelium Mitigates Pulmonary Hypertension. Am. J. Respir. Crit. Care Med. 2018, 198, 509–520. [Google Scholar] [CrossRef] [Scilit]
- Simões e Silva, A.; Silveira, K.; Ferreira, A.; Teixeira, M. ACE2, Angiotensin-(1-7) and Mas Receptor Axis in Inflammation and Fibrosis. Br. J. Pharmacol. 2013, 169, 477–492. [Google Scholar] [CrossRef] [Scilit]
- Gheblawi, M.; Wang, K.; Viveiros, A.; Nguyen, Q.; Zhong, J.-C.; Turner, A.J.; Raizada, M.K.; Grant, M.B.; Oudit, G.Y. Angiotensin-Converting Enzyme 2: SARS-CoV-2 Receptor and Regulator of the Renin-Angiotensin System. Circ. Res. 2020, 126, 1456–1474. [Google Scholar] [CrossRef] [Scilit]
- Bian, J.; Li, Z. Angiotensin-Converting Enzyme 2 (ACE2): SARS-CoV-2 Receptor and RAS Modulator. Acta Pharm. Sin. B 2021, 11, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Chi, X.; Wang, S.; Huang, Y.; Stamnes, M.; Chen, J.-L. Roles of Rho GTPases in Intracellular Transport and Cellular Transformation. Int. J. Mol. Sci. 2013, 14, 7089–7108. [Google Scholar] [CrossRef] [Scilit]
- Marcianò, G.; Palleria, C.; Casarella, A.; Rania, V.; Basile, E.; Catarisano, L.; Vocca, C.; Bianco, L.; Pelaia, C.; Cione, E.; et al. Effect of Statins on Lung Cancer Molecular Pathways: A Possible Therapeutic Role. Pharmaceuticals 2022, 15, 589. [Google Scholar] [CrossRef] [Scilit]
- Wagstaff, K.M.; Sivakumaran, H.; Heaton, S.M.; Harrich, D.; Jans, D.A. Ivermectin Is a Specific Inhibitor of Importin α/β-Mediated Nuclear Import Able to Inhibit Replication of HIV-1 and Dengue Virus. Biochem. J. 2012, 443, 851–856. [Google Scholar] [CrossRef] [Scilit]
- Chen, L.Y.C.; Quach, T.T.T. Combining Immunomodulators and Antivirals for COVID-19. Lancet Microbe 2021, 2, e233. [Google Scholar] [CrossRef] [Scilit]
- Chen, X.; Guo, H.; Qiu, L.; Zhang, C.; Deng, Q.; Leng, Q. Immunomodulatory and Antiviral Activity of Metformin and Its Potential Implications in Treating Coronavirus Disease 2019 and Lung Injury. Front. Immunol. 2020, 11, 2056. [Google Scholar] [CrossRef] [Scilit]
- Foretz, M.; Guigas, B.; Bertrand, L.; Pollak, M.; Viollet, B. Metformin: From Mechanisms of Action to Therapies. Cell Metab. 2014, 20, 953–966. [Google Scholar] [CrossRef] [Scilit]
- Chaudhary, S.C.; Kurundkar, D.; Elmets, C.A.; Kopelovich, L.; Athar, M. Metformin, an Antidiabetic Agent Reduces Growth of Cutaneous Squamous Cell Carcinoma by Targeting mTOR Signaling Pathway†. Photochem. Photobiol. 2012, 88, 1149–1156. [Google Scholar] [CrossRef] [Scilit]
- Marcucci, F.; Romeo, E.; Caserta, C.A.; Rumio, C.; Lefoulon, F. Context-Dependent Pharmacological Effects of Metformin on the Immune System. Trends Pharmacol. Sci. 2020, 41, 162–171. [Google Scholar] [CrossRef] [Scilit]
- Huang, C.; Wang, Y.; Li, X.; Ren, L.; Zhao, J.; Hu, Y.; Zhang, L.; Fan, G.; Xu, J.; Gu, X.; et al. Clinical Features of Patients Infected with 2019 Novel Coronavirus in Wuhan, China. Lancet 2020, 395, 497–506. [Google Scholar] [CrossRef] [Scilit]
- Mills, C. M1 and M2 Macrophages: Oracles of Health and Disease. CRI 2012, 32, 463–488. [Google Scholar] [CrossRef] [Scilit]
- Kelly, B.; Tannahill, G.M.; Murphy, M.P.; O’Neill, L.A.J. Metformin Inhibits the Production of Reactive Oxygen Species from NADH:Ubiquinone Oxidoreductase to Limit Induction of Interleukin-1β (IL-1β) and Boosts Interleukin-10 (IL-10) in Lipopolysaccharide (LPS)-Activated Macrophages *. J. Biol. Chem. 2015, 290, 20348–20359. [Google Scholar] [CrossRef] [Scilit]
- Ding, L.; Liang, G.; Yao, Z.; Zhang, J.; Liu, R.; Chen, H.; Zhou, Y.; Wu, H.; Yang, B.; He, Q. Metformin Prevents Cancer Metastasis by Inhibiting M2-like Polarization of Tumor Associated Macrophages. Oncotarget 2015, 6, 36441–36455. [Google Scholar] [CrossRef] [Scilit]
- Saito, A.; Koinuma, K.; Kawashima, R.; Miyato, H.; Ohzawa, H.; Horie, H.; Yamaguchi, H.; Kawahira, H.; Mimura, T.; Kitayama, J.; et al. Metformin May Improve the Outcome of Patients with Colorectal Cancer and Type 2 Diabetes Mellitus Partly through Effects on Neutrophil Extracellular Traps. BJC Rep. 2023, 1, 20. [Google Scholar] [CrossRef] [Scilit]
- Li, J.; Zhang, K.; Zhang, K.; Zhang, Y.; Gu, Z.; Huang, C. Neutrophils in COVID-19: Recent Insights and Advances. Virol. J. 2023, 20, 169. [Google Scholar] [CrossRef] [Scilit]
- Sun, Y.; Tian, T.; Gao, J.; Liu, X.; Hou, H.; Cao, R.; Li, B.; Quan, M.; Guo, L. Metformin Ameliorates the Development of Experimental Autoimmune Encephalomyelitis by Regulating T Helper 17 and Regulatory T Cells in Mice. J. Neuroimmunol. 2016, 292, 58–67. [Google Scholar] [CrossRef] [Scilit]
- Liu, X.; Yu, P.; Xu, Y.; Wang, Y.; Chen, J.; Tang, F.; Hu, Z.; Zhou, J.; Liu, L.; Qiu, W.; et al. Metformin Induces Tolerogenicity of Dendritic Cells by Promoting Metabolic Reprogramming. Cell Mol. Life Sci. 2023, 80, 283. [Google Scholar] [CrossRef] [Scilit]
- Cortés, M.; Brischetto, A.; Martinez-Campanario, M.C.; Ninfali, C.; Domínguez, V.; Fernández, S.; Celis, R.; Esteve-Codina, A.; Lozano, J.J.; Sidorova, J.; et al. Inflammatory Macrophages Reprogram to Immunosuppression by Reducing Mitochondrial Translation. Nat. Commun. 2023, 14, 7471. [Google Scholar] [CrossRef] [Scilit]
- Wiklund, O.; Mattsson-Hultén, L.; Hurt-Camejo, E.; Oscarsson, J. Effects of Simvastatin and Atorvastatin on Inflammation Markers in Plasma. J. Intern. Med. 2002, 251, 338–347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al-Kuraishy, H.M.; Al-Gareeb, A.I.; Saad, H.M.; Batiha, G.E.-S. The Potential Therapeutic Effect of Statins in Multiple Sclerosis: Beneficial or Detrimental Effects. Inflammopharmacology 2023, 31, 1671–1682. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Blankier, S.; McCrindle, B.W.; Ito, S.; Yeung, R.S.M. The Role of Atorvastatin in Regulating the Immune Response Leading to Vascular Damage in a Model of Kawasaki Disease. Clin. Exp. Immunol. 2011, 164, 193–201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sorathia, N.; Al-Rubaye, H.; Zal, B. The Effect of Statins on the Functionality of CD4+CD25+FOXP3+ Regulatory T-Cells in Acute Coronary Syndrome: A Systematic Review and Meta-Analysis of Randomised Controlled Trials in Asian Populations. Eur. Cardiol. 2019, 14, 123–129. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fessler, M.B. Regulation of Adaptive Immunity in Health and Disease by Cholesterol Metabolism. Curr. Allergy Asthma Rep. 2015, 15, 48. [Google Scholar] [CrossRef] [Scilit]
- Sheridan, A.; Wheeler-Jones, C.P.D.; Gage, M.C. The Immunomodulatory Effects of Statins on Macrophages. Immuno 2022, 2, 317–343. [Google Scholar] [CrossRef] [Scilit]
- Pedrosa, A.R.; Martins, D.C.; Rizzo, M.; Silva-Nunes, J. Metformin in SARS-CoV-2 Infection: A Hidden Path—From Altered Inflammation to Reduced Mortality. A Review from the Literature. J. Diabetes Complicat. 2023, 37, 108391. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scheen, A.J. Metformin and COVID-19: From Cellular Mechanisms to Reduced Mortality. Diabetes Metab. 2020, 46, 423–426. [Google Scholar] [CrossRef] [Scilit]
- Petakh, P.; Griga, V.; Mohammed, I.B.; Loshak, K.; Poliak, I.; Kamyshnyiy, A. Effects of Metformin, Insulin on Hematological Parameters of COVID-19 Patients with Type 2 Diabetes. Med. Arch. 2022, 76, 329–332. [Google Scholar] [CrossRef] [Scilit]
- Moreno-Corona, N.C.; López-Ortega, O.; Pérez-Martínez, C.A.; Martínez-Castillo, M.; De Jesús-González, L.A.; León-Reyes, G.; León-Juárez, M. Dynamics of the Microbiota and Its Relationship with Post-COVID-19 Syndrome. Int. J. Mol. Sci. 2023, 24, 14822. [Google Scholar] [CrossRef] [Scilit]
- Petakh, P.; Kamyshna, I.; Nykyforuk, A.; Yao, R.; Imbery, J.F.; Oksenych, V.; Korda, M.; Kamyshnyi, A. Immunoregulatory Intestinal Microbiota and COVID-19 in Patients with Type Two Diabetes: A Double-Edged Sword. Viruses 2022, 14, 477. [Google Scholar] [CrossRef] [Scilit]
- Petakh, P.; Kamyshna, I.; Oksenych, V.; Kainov, D.; Kamyshnyi, A. Metformin Therapy Changes Gut Microbiota Alpha-Diversity in COVID-19 Patients with Type 2 Diabetes: The Role of SARS-CoV-2 Variants and Antibiotic Treatment. Pharmaceuticals 2023, 16, 904. [Google Scholar] [CrossRef] [Scilit]
- Rodriguez-Nava, G.; Trelles-Garcia, D.P.; Yanez-Bello, M.A.; Chung, C.W.; Trelles-Garcia, V.P.; Friedman, H.J. Atorvastatin Associated with Decreased Hazard for Death in COVID-19 Patients Admitted to an ICU: A Retrospective Cohort Study. Crit. Care 2020, 24, 429. [Google Scholar] [CrossRef] [Scilit]
- Kouhpeikar, H.; Khosaravizade Tabasi, H.; Khazir, Z.; Naghipour, A.; Mohammadi Moghadam, H.; Forouzanfar, H.; Abbasifard, M.; Kirichenko, T.V.; Reiner, Ž.; Banach, M.; et al. Statin Use in COVID-19 Hospitalized Patients and Outcomes: A Retrospective Study. Front. Cardiovasc. Med. 2022, 9, 820260. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Haji Aghajani, M.; Moradi, O.; Azhdari Tehrani, H.; Amini, H.; Pourheidar, E.; Hatami, F.; Rabiei, M.M.; Sistanizad, M. Promising Effects of Atorvastatin on Mortality and Need for Mechanical Ventilation in Patients with Severe COVID-19; a Retrospective Cohort Study. Int. J. Clin. Pract. 2021, 75, e14434. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schieffer, E.; Schieffer, B. The Rationale for the Treatment of Long-Covid Symptoms—A Cardiologist’s View. Front. Cardiovasc. Med. 2022, 9, 992686. [Google Scholar] [CrossRef] [Scilit]
- Visos-Varela, I.; Zapata-Cachafeiro, M.; Pintos-Rodríguez, S.; Bugarín-González, R.; González-Barcala, F.J.; Herdeiro, M.T.; Piñeiro-Lamas, M.; Figueiras, A.; Salgado-Barreira, Á. Outpatient Atorvastatin Use and Severe COVID-19 Outcomes: A Population-Based Study. J. Med. Virol. 2023, 95, e28971. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boulware, D.R.; Bramante, C.; Pullen, M.; Buse, J.; Odde, D.; Mehta, T.; Murray, T.A. Metformin Reduced SARS-CoV-2 Viral Load in a Phase 3 Randomized Clinical Trial. Top. Antivir. Med. 2023, 31, 70. [Google Scholar]
- Yu, J.-W.; Sun, L.-J.; Zhao, Y.-H.; Kang, P.; Yan, B.-Z. The Effect of Metformin on the Efficacy of Antiviral Therapy in Patients with Genotype 1 Chronic Hepatitis C and Insulin Resistance. Int. J. Infect. Dis. 2012, 16, e436–e441. [Google Scholar] [CrossRef] [Scilit]
- Lv, Z.; Guo, Y. Metformin and Its Benefits for Various Diseases. Front. Endocrinol. 2020, 11, 191. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tárraga López, P.J.; Celada Rodríguez, A.; Cerdán Oliver, M.; Solera Albero, J.; Ocaña López, J.M.; de Miguel Clavé, J. Análisis coste-efectividad de atorvastatina frente a simvastatina como tratamiento hipolipemiante en pacientes hipercolesterolémicos en atención primaria. Aten Primaria 2001, 27, 18–24. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pepperrell, T.; Ellis, L.; Wang, J.; Hill, A. Barriers to Worldwide Access for Paxlovid, a New Treatment for COVID-19. Open Forum Infect. Dis. 2022, 9, ofac174. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Corcoran, C.; Jacobs, T.F. Metformin. In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2023. [Google Scholar]
- DOF—Diario Oficial de La Federación. Available online: https://www.dof.gob.mx/nota_detalle.php?codigo=5588819&fecha=10/03/2020#gsc.tab=0 (accessed on 13 June 2023).

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).