


Abstract
Background Human African trypanocide resistance (HATr) is a challenge for the eradication of Human African Trypansomiaisis (HAT) following the widespread emergence of increased monotherapy drug treatment failures against Trypanosoma brucei gambiense and T. b. rhodesiense that are associated with changes in pathogen receptors. Methods: Electronic searches of 12 databases and 3 Google search websites for human African trypanocide resistance were performed using a keyword search criterion applied to both laboratory and clinical studies. Fifty-one publications were identified and included in this study using the PRISMA checklist. Data were analyzed using RevMan and random effect sizes were computed for the statistics at the 95% confidence interval. Results: Pentamidine/melarsoprol/nifurtimox cross-resistance is associated with loss of the T. brucei adenosine transporter 1/purine 2 gene (TbAT1/P2), aquaglyceroporins (TbAQP) 2 and 3, followed by the high affinity pentamidine melarsoprol transporter (HAPT) 1. In addition, the loss of the amino acid transporter (AAT) 6 is associated with eflornithine resistance. Nifurtimox/eflornithine combination therapy resistance is associated with AAT6 and nitroreductase loss, and high resistance and parasite regrowth is responsible for treatment relapse. In clinical studies, the TbAT1 proportion of total random effects was 68% (95% CI: 38.0–91.6); I2 = 96.99% (95% CI: 94.6–98.3). Treatment failure rates were highest with melarsoprol followed by eflornithine at 41.49% (95% CI: 24.94–59.09) and 6.56% (3.06–11.25) respectively. HATr-resistant phenotypes used in most laboratory experiments demonstrated significantly higher pentamidine resistance than other trypanocides. Conclusion: The emergence of drug resistance across the spectrum of trypanocidal agents that are used to treat HAT is a major threat to the global WHO target to eliminate HAT by 2030. T. brucei strains were largely resistant to diamidines and the use of high trypanocide concentrations in clinical studies have proved fatal in humans. Studies to develop novel chemotherapeutical agents and identify alternative protein targets could help to reduce the emergence and spread of HATr.
Keywords:
human African trypanosomiasis; trypanosomes; drug resistance; pentamidines; nifurtimox/eflornithine combination therapy; fexinidazole; NECT; TbAT1; amino-aquapurine transporters; amino acid transporters; trypanosoma brucei rhodesiense; trypanosoma brucei gambiense; neglected tropical diseases 1. Introduction
The World Health Organization (WHO) has set 2030 as a target for the elimination of human African trypanosomiasis (HAT) [1]; however, the development of drug-resistant phenotypes (see [2] on trypanocide resistance) in resource-poor countries affected by HAT presents a major challenge for HAT control. In Africa, HAT is caused by Trypanosoma brucei gambiense (TBG, chronic variant) and T. b. rhodesiense (TBR, acute variant), also referred to as gHAT and rHAT, respectively. Uganda has the misfortune to harbor both sub-species within its borders [3]. Trypanosomes are able to evade host immune defenses through a process of antigenic variation (while each genome contains over 103 distinct variable surface glycoprotein (VSG) genes, every trypanosome typically expresses a single VSG that rapidly switches [4], compromising any efforts to develop vaccines).
Globally, six major drugs are available for treatment of HAT depending on the stage of the infection: pentamidine, suramin, melarsoprol, eflornithine, nifurtimox/eflornithine combination therapy (NECT), and fexinidazole (see [2] on HAT pharmaceutics and limitations of current approved therapies). The emergence of human African trypanocide resistance (HATr) has undermined the use of monotherapy for HAT treatment.
Pentamidine was the first antiprotozoal diamidine to be routinely used for HAT treatment, its mode of action serving to disrupt the AATT-rich portions of Trypanosoma DNA and suppress mitochondrial activity [5]. Pentamidine resistance has been linked to changes in the transmembrane transport of the drug i.e., Trypanosoma brucei adenosine transporter 1/purine 2 (TbAT1/P2) and high-affinity pentamidine transporter 1 (HAPT1) [5,6,7]. Melarsoprol is an arsenical with which resistance has been associated with aquaglyceroporin transporters 2/3 (AQP2/3) in trypanosomes [8]. Resistance has led to the adoption of combination nifurtimox/eflornithine combination therapy (NECT), which has low toxicity and a shortened therapeutic period, although weekly intravenous infusions have proved challenging in resource-limited settings [9]. In early stages, pentamidine (TBG) and suramin (TBR) are used while melarsoprol (TBG and TBR) and eflornithine (TBG) are recommended for late-stage HAT [3]. New drugs, including pafuramidine maleate for early HAT, have failed, while acoziborole for stage 1 and 2 HAT is under continuous review [10], demonstrating the need to develop novel therapies; for example, fexinidazole is easier to administer since it is an oral medication [11,12]. The objective of the current study was to identify major parasitic markers in HATr associated with clinical studies (field surveys and clinical trials) and experimental (laboratory-based) studies.
2. Methods
2.1. Study Design
Multiple electronic databases were searched using the Ovid interface: AMED (Allied and Complementary Medicine) 1985 to March 2022, CAB Abstracts 1973 to 2022 Week 13, APA PsycInfo 1806 to March Week 4 2022, Books@Ovid 28 March 2022, Journals@Ovid Full Text 01 April 2022, Your Journals@Ovid, APA PsycArticles Full Text, CAB Abstracts 1910 to 1989, Embase Classic+Embase 1947 to 01 April 2022, Global Health 1910 to 2022 Week 13, Ovid MEDLINE(R), and Epub Ahead of Print, In-Process, In-Data-Review & Other Non-Indexed Citations, Daily and Versions 1946 to 01 April 2022. These searches generated a total of 172 publications and the Web of Science generated 111 publications using the following keywords as shown in Supplementary File S1.
ALL = ((african trypanosomiasis)) OR ALL = (trypanosoma brucei)) OR ALL = (‘tsetse fly-borne diseases’ OR ‘HAT’ or ‘human African trypanosomiasis’))) AND ALL = ((trypanosoma brucei gambiense) or (trypanosoma brucei rhodesiense))) AND ALL = ((suramin OR melarsoprol OR eflornithine OR nifurtimox OR pentamidine OR (NECT or (Nifurtimox Eflornithine Combination Therapy))))) AND ALL = (trypanocides resistance or drug resistance).
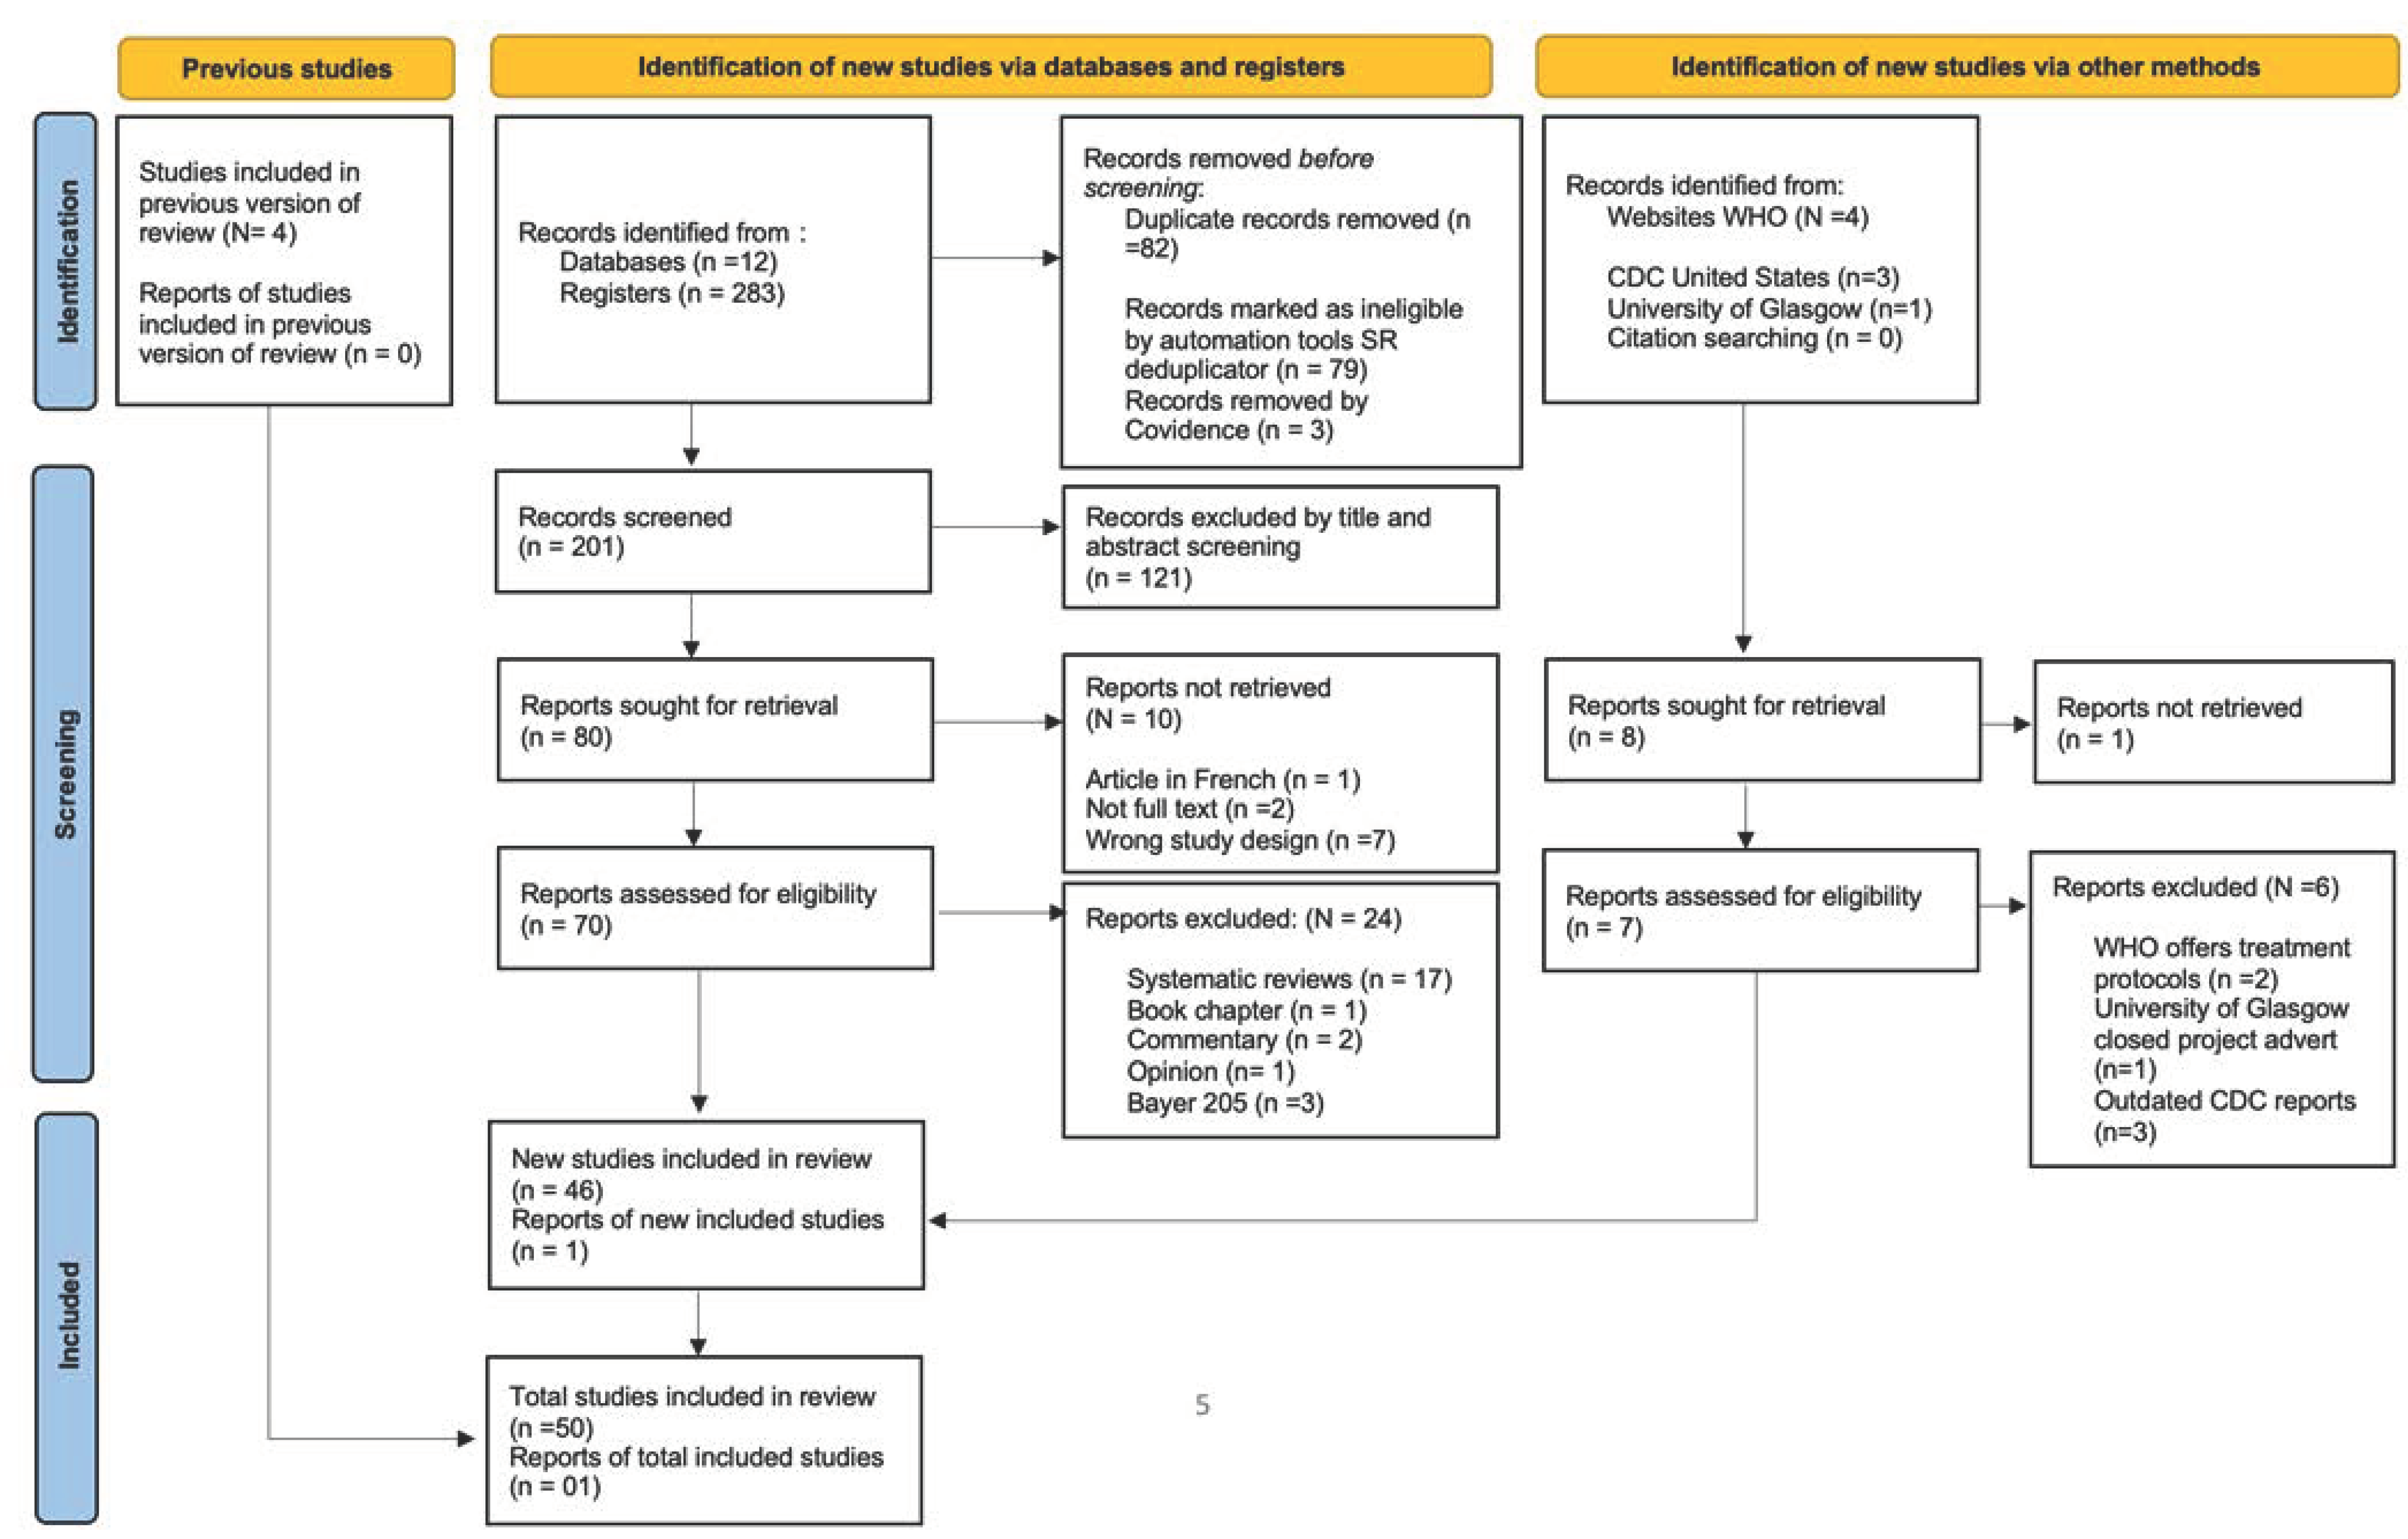
Grey literature was searched on Google using the WHO and CDC websites, and citations in systematic reviews were also searched for papers that might have been missed (Figure 1).
2.2. Article Screening on Inclusion and Exclusion
Data files were exported to EndNote 2020 and all papers were merged (N = 283). The SR depublicator removed 79 duplicates. A total of 204 papers were then exported to Covidence, which removed 3 additional duplicates, and these were confirmed by authors. Title and abstract screening removed 121 papers and only 80 papers were subjected to full-text review. After removing review articles, a total of 46 papers were acquired from the search and an additional 5 papers were added (i.e., 1 from Google search and 4 from review searches), as shown in Figure 1.
Figure 1.
PRISMA checklist showing studies from database, Google search, and citation review.
2.3. Statistical Analysis
Data were exported into MS Excel and categorized into laboratory studies (cell culture and rodents) and clinical studies (involving humans). These data were descriptively presented in tables while quantitative data were analyzed using RevMan® for meta-analysis using proportions and random effect sizes at 95% confidence interval. Data on the impact of resistance were analyzed using GraphPad Prism version 6 and posthoc Tukey’s tests were conducted and represented with different superscripts (a,b) being used to indicate significant differences (p < 0.05)
3. Results and Discussion
3.1. Description of Human African Trypanocide Resistance in the Study
Pentamidine/melarsoprol cross-resistance (PMXR) is associated with loss of and mutations in TbAT1/P2 genes [13], followed by mitochondrial, post translational activator XAC1, and flagellar genes [14]. The loss of TbAT1 alone does not effectively prevent endocytosis of pentamidine and melarsoprol (see [15], melarsoprol has other entry targets); however, a loss of aquaglyceroprotein (TbAQP, see [16], AQPs are important for viability and osmoregulation) has been associated with complete loss of trypanocide endocytosis [17]. In particular, the loss of TbAQP2/3 following point mutations in TbAT1 leads to a loss of the high-affinity pentamidine/melarsoprol transporter (HAPMT) [18,19]. In pentamidine diamidine resistance, HAPT1 and low-affinity pentamidine transporter 1 (LAPT1) are responsible for the residual uptake of melaninophenyl arsenic [20]. The presence of multiple resistance genes in single parasites contributes to a markedly resistant phenotype. For example, TbAT1 and T. brucei multidrug-resistant pentamidine-associated gene (TbMRPA) further complicate melarsoprol resistance [21] (Table 1).
These findings are important since pentamidine and melarsoprol have been the major trypanocides involved in HAT chemotherapy for over 60 years [22]. Cross-resistance between melarsoprol-pentamidine, diminazene aceturate, isometamidium chloride has been reported [23]. Although drugs used in HAT are different from those used for animal African trypanosomiasis, pentamidines/diamidines with similar pathogen targets (TbAT1/P2) contribute to this selection pressure [24]. This is important since TBR and TBG have been isolated from livestock species that have been recognized as maintenance hosts (see [25] in pigs, [26] in small ruminants, and [27] in cattle) and sources of re-infection and introduction of resistant phenotypes in humans [28].
Nifurtimox is metabolized rapidly and its metabolites are not effective against T. brucei s.l., thus reducing its therapeutical effect [29]. Similar results have been reported for TbAT1, where the loss of P2 favors trypanosome survival [30]. The loss of amino acid transporter (AAT) 6 leads to increased eflornithine resistance [24,25] while NECT resistance is associated with multiple loss of function of AAT6 and nitroreductase (NTR) [26,27]. Resistance to arsenicals and diamidine is associated with HAPT loss [31] while TbAT1 loss disrupts the uptake of diamidines [32]. In addition, cross-resistance in arsenical and suramin [33], arsenical/melarsoprol/pentamidine and diminazene aceturate [15] as well as isometamidium and diminazene aceturate, which are mainly used in livestock [34], raises major public health concerns since pentamidines and diminazene aceturate are used in both humans and animals [24]. Furthermore, the presence of putative nascent polypeptide associated complex (NAC) isoforms [35] presents a dilemma with opportunities for drug targets and challenges to address HATr (Table 1). Nifurtimox resistance has also been associated with TbAT1/P2 (contrary to previous assumptions [36] in which no relationship was made); however, AAT6 loss has been associated with eflornithine resistance. In NECT resistance, multiple loss of AAT6 and NTR is the hallmark of drug resistance. Nifurtimox–fexinidazole resistance is associated with the rapid metabolism of the sulfoxide and sulfone forms of this compound [22]. Since nifurtimox was first developed for use against American trypanosomiasis [37], it is apparent that further research exploring combination therapy could yield more efficient trypanocides.
Resistance to suramin (developed in 1916) has been associated with switching of VSG expression [31,38]. Furthermore, other mechanisms associated with ATP production, metabolism, cell cycle, and genome segregation [39] will continue to offer opportunities for continued research (Table 1). Although the cellular pathways involved in suramin resistance remain to be discovered (see [40] where resistance was postulated to develop after changes in the drug target by expression of drug extrusion mechanisms), since each parasite contains over 1000 VSG genes, expression switching to one particular VSGSur implies that it is close to impossible to eliminate suramin resistance in a population [41].
Table 1.
Characterization of pathogens, interventions used, and gene targets in human African trypanosome resistance in laboratory studies.
3.2. Human African Trypanocide Resistance in Clinical Studies
In clinical studies, relapse/cure rates have been used to study HATr (see [46] on using DL-α-difluoromethylornithine (DFMO, also referred to as eflornithine in most studies) with suramin against arsenical refractory HAT in mice). This is important since DFMO alone has been associated with resistance [47]. Combination of metronidazole and suramin were used to address arsenical resistance in HATr in Zambia [62], while high doses of nifurtimox have also been explored in the Democratic Republic of the Congo (DRC) [63,64]. Melarsoprol resistance in DRC has been associated with mutations in the AQP2/3 gene [48] and parasite regrowth [65]. Human samples from Tanzania and Ivory Coast showed cross-resistance to melarsoprol and suramin due to alterations in TbAT1 [33] or other transport mechanisms [15] (Table 2).
Melarsoprol resistance in Uganda and Tanzania has also been associated with mutations in the TbAT1 gene [66], and high minimum inhibition concentration (MIC) titers (see [49]) in Uganda). In DRC, melarsoprol alone is no longer used in late HAT [67] and eflornithine is now used at this stage [68]. The increasing levels of HATr has led to the promotion of combination therapy [69], as well as capital to invest in the discovery of more potent drugs better than the current drugs on the market.
Table 2.
Human African trypanosome resistance in human populations with location and drugs used during interventions.
3.3. Evidence of Human African Trypanocide Resistance of TbAT1 in Clinical Studies
Here, we provide evidence with a total random effect proportion of 68.0% (95% CI: 38.0–91.6) being reported from 2001–2014 (Table 3). Test for heterogeneity: Q (df) = 99.7 (3), p < 0.0001. I2 = 96.99% (95% CI: 94.6–98.3). The high I2 value indicates great variation, which could be associated with the different study designs, time scope, and geographical locations for these studies. Egger’s test (Intercept = −16.5, 95% CI: −30.8 to −2.1, p = 0.04), Begg’s test (Tau = −1.0, p = 0.04) showed publication bias. Pati [48] reported a further proportion of 4/6 (TbAT1) having mutations associated with the AQP2/3 genes.
Table 3.
Proportion of TbAT1 loss in human clinical studies.
3.4. Human African Trypanocide Treatment Relapse Rates
Treatment failure rates were highest with melarsoprol, followed by eflornithine, 41.49% (95% CI: 24.94–59.09) and 6.56% (3.06–11.25), respectively; however, the reliability of these findings may be biased due to the high I2 value associated with melarsoprol studies (Table 4). Furthermore, a high level of consistency was associated with nifurtimox studies (I2 = 0.0%) since this showed a low publication bias.
Table 4.
Human African trypanocide relapses following pentamidine, nifurtimox, eflornithine, and melarsoprol therapy in humans.
Treatment relapse rates have been used as indicators of resistance and combination therapies using DFMO-suramin against arsenical/melarsoprol resistance have been explored since eflornithine alone is ineffective [74]. This has continued as an alternative combination for use in late HAT cases because of melarsoprol resistance [75]. To overcome arsenical resistance, combination therapies of metronidazole and suramin have also been used since these are associated with mild side effects when compared with suramin monotherapy (in Zambia), while high doses of nifurtimox have also been used in DRC. Melarsoprol resistance in DRC has been associated with mutations in the AQP2/3 gene [35] and parasite regrowth[56]. Human samples from Tanzania and Ivory Coast have shown cross resistance to melarsoprol and suramin due to alterations in TbAT1 [30] or other transport mechanisms [15].
Melarsoprol resistance in Uganda and Tanzania has also been associated with mutations in the TbAT1 gene [57]. In DRC, melarsoprol alone is no longer used in late-stage HAT [58] and has been substituted with eflornithine for this stage [59]. The increasing levels of HATr have led to the promotion of combination therapy [60], as well as increased capital to invest in the discovery of more potent drugs superior those currently on the market. Furthermore, melarsoprol toxicity and decreasing efficacy has led to phasing out the drug as a frontline treatment against T. b. gambiense; this is now possible with the emergence of potent, safe combination chemotherapies, such as NECT, showing that eflornithine will continue to be around for decades to come. The TbAT1 genotype was the most prevalent marker, although few studies have been conducted in humans on the African continent exploring the genome diversity of HATr. This is important since melarsoprol has the highest treatment failure rates [66,73].
3.5. Drug Sensitivity Profiles on HATr Using Resistance Profiling
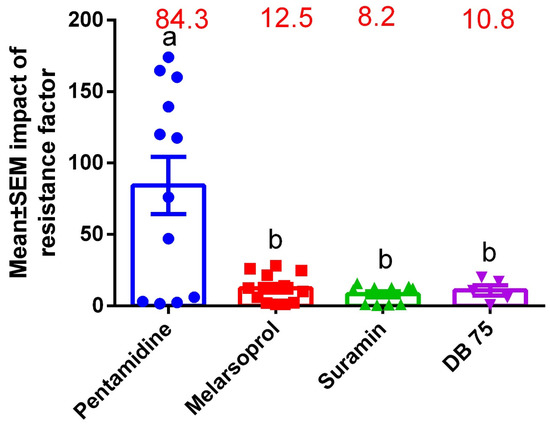
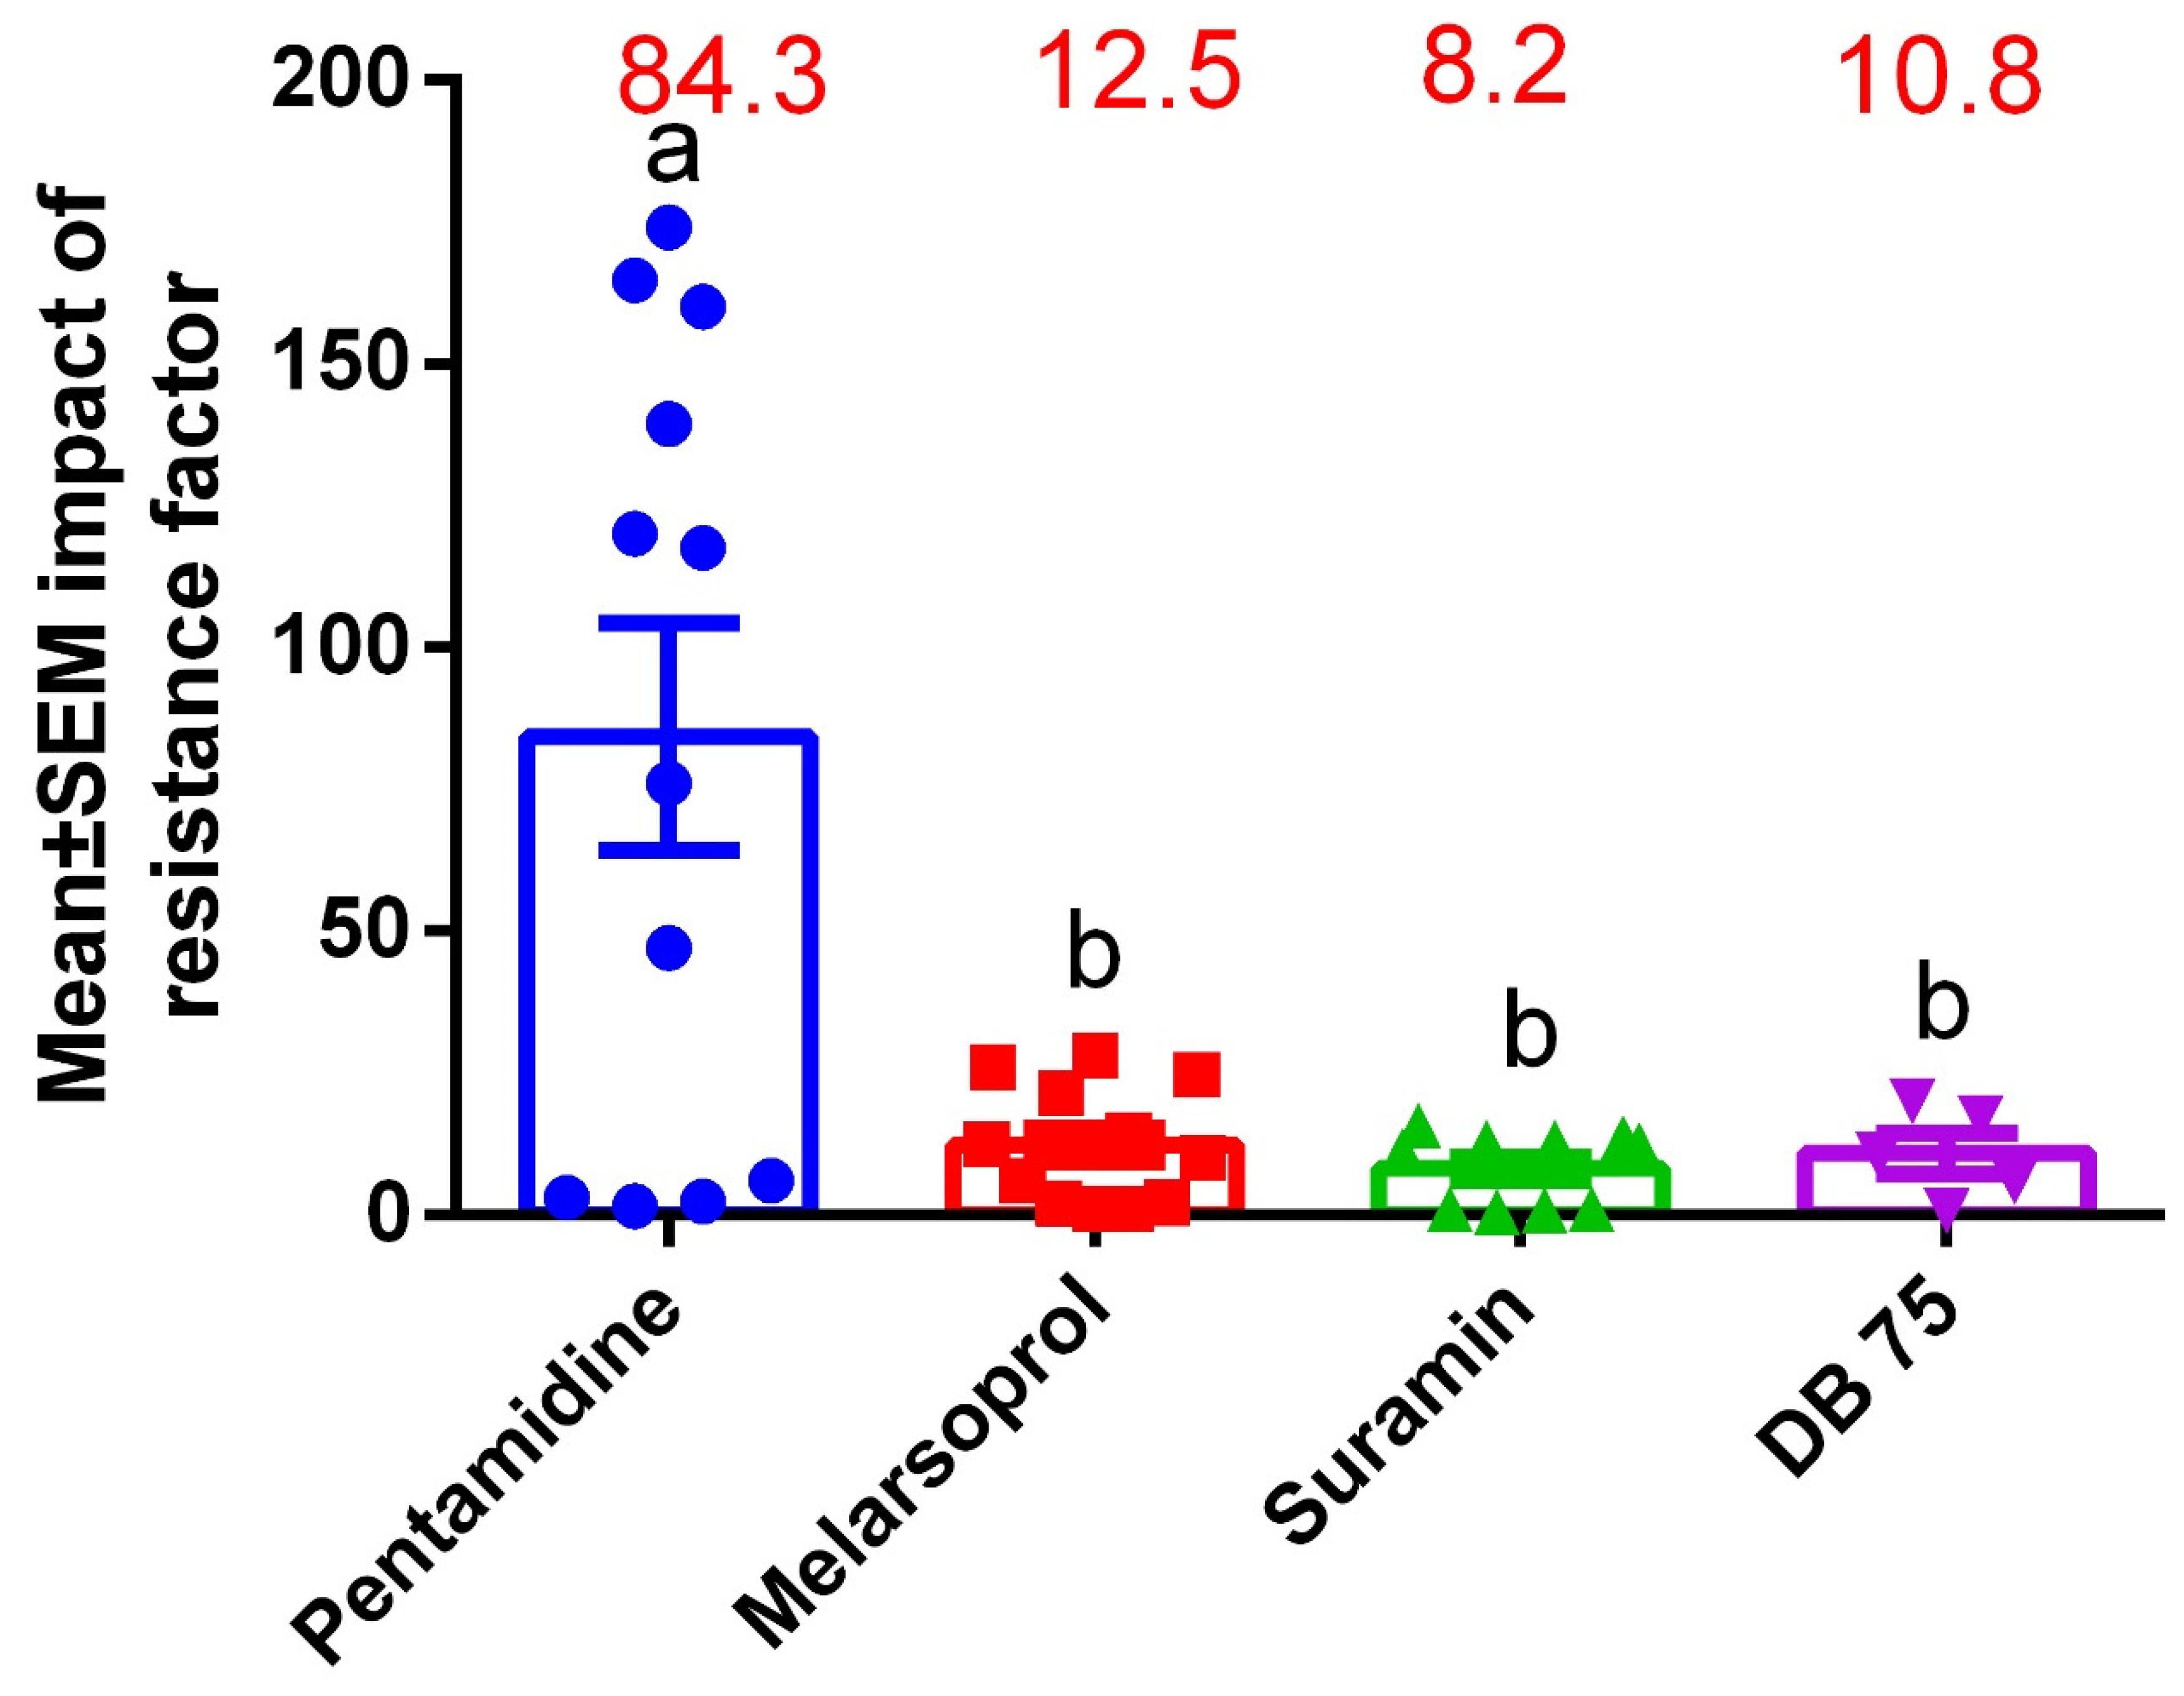
Some experimental laboratory studies have proved to be unreliable due to low reproducibility, especially when conducting clinical (field-based) studies [76]. This has subsequently given rise to speculative interpretations that make it hard to inform policy [77]. Here, we investigated the level of resistance induced in experimental studies for HATr. The resistance factor was calculated by dividing the IC50 of the resistant population by the IC50 of the wild-type in these studies [13,18,20,29,40]. The mean ± SEM for resistance factors of pentamidine, melarsoprol, suramin, and DB 75 were 84.3 ± 20.12, 12.5 ± 3.0, 8.2 ± 2.0, and 10.8 ± 3.5, respectively (Figure 2). Furthermore, most laboratory studies have continued to produce strains that are significantly resistant to pentamidines, demonstrating a shift in research direction for the next novel trypanocides.
Figure 2.
Resistance profiles of laboratory-developed HATr phenotypes. Generally, much emphasis has been placed on development of strains heavily expressing resistance to pentamidine compared with all other trypanocides. Different subperscripts in figure 2 are introduced under statistical analysis (i.e., different superscripts (a,b) signify significant differences).
4. Conclusions
Cross-resistance across trypanocides is a major threat to the development of novel monotherapy due to the targeting of similar molecules in the pathogen. TbAT1/P2 are the leading pathogenic transporter targets; however, total resistance is associated with the loss of TbAQ2/3, HAPT1, and LAPT1 in melarsoprol-pentamidine resistance, while AAT6 and NTRs are common in nifurtimox–eflornithine resistance. High treatment failure rates in humans have led to the implementation of high doses, which have proved fatal to patients, highlighting the desperate situation created by HATr in endemic communities.
Supplementary Materials
The following are available online at https://www.mdpi.com/article/10.3390/pathogens11101100/s1, File S1: keyword search criteria on HATr.
Author Contributions
K.I.K. and S.C.W. conceptualized the study; K.I.K., S.C.W. and E.T.M. conducted study design; K.I.K. collected the data; K.I.K. conducted data analysis. All authors have read and agreed to the published version of the manuscript.
Funding
This research was supported by the National Institute for Health Research (16/136/33) using UK aid from the UK Government. The views expressed in this publication are those of the author(s) and not necessarily those of the NIHR or the Department of Health and Social Care. This work was also supported by Zhejiang University Research Fund(SCW), The work was also funded by the Commonwealth Scholarship Commission (UGSC–2021–447) in the UK (KIK).
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data availability statement
All information used in the study is available in the manuscript.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Franco, J.R.; Cecchi, G.; Priotto, G.; Paone, M.; Diarra, A.; Grout, L.; Simarro, P.P.; Zhao, W.; Argaw, D. Monitoring the elimination of human African trypanosomiasis at continental and country level: Update to 2018. PLoS Negl. Trop. Dis. 2020, 14, e0008261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kasozi, K.I.; MacLeod, E.T.; Ntulume, I.; Welburn, S.C. An Update on African Trypanocide Pharmaceutics and Resistance. Front. Vet. Sci. 2022, 9, 828111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baker, C.H.; Welburn, S.C. The Long Wait for a New Drug for Human African Trypanosomiasis. Trends Parasitol. 2018, 34, 818–827. [Google Scholar] [CrossRef] [Scilit]
- Giordani, F.; Morrison, L.J.; Rowan, T.G.; De Koning, H.P.; Barrett, M.P. The animal trypanosomiases and their chemotherapy: A review. Parasitology 2016, 143, 1862–1889. [Google Scholar] [CrossRef] [Scilit]
- Lemke, T.L.; Williams, D. Foye’s Principles of Medicinal Chemistry, 7th ed.; Lippincott Williams & Wilkins: Philadelphia, PA, USA, 2013; ISBN 9781609133450. [Google Scholar]
- Barrett, M.P.; Vincent, I.M.; Burchmore, R.J.S.; Kazibwe, A.J.N.; Matovu, E. Drug resistance in human African trypanosomiasis. Future Microbiol. 2011, 6, 1037–1047. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bray, P.G.; Barrett, M.P.; Ward, S.A.; de Koning, H.P. Pentamidine uptake and resistance in pathogenic protozoa: Past, present and future. TRENDS Parasitol. 2003, 19, 232–239. [Google Scholar] [CrossRef] [Scilit]
- Fairlamb, A.H.; Horn, D. Melarsoprol resistance in African trypanosomiasis. Trends Parasitol. 2018, 34, 481–492. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Priotto, G.; Kasparian, S.; Mutombo, W.; Ngouama, D.; Ghorashian, S.; Arnold, U.; Ghabri, S.; Baudin, E.; Buard, V.; Kazadi-Kyanza, S.; et al. Nifurtimox-eflornithine combination therapy for second-stage African Trypanosoma brucei gambiense trypanosomiasis: A multicentre, randomised, phase III, non-inferiority trial. Lancet 2009, 374, 56–64. [Google Scholar] [CrossRef] [Scilit]
- Dickie, E.A.; Giordani, F.; Gould, M.K.; Mäser, P.; Burri, C.; Mottram, J.C.; Rao, S.P.S.; Barrett, M.P. New Drugs for Human African Trypanosomiasis: A Twenty First Century Success Story. Trop. Med. Infect. Dis. 2020, 5, 29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fairlamb, A.H. Fexinidazole for the treatment of human African trypanosomiasis. Drugs Today 2019, 55, 705. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mesu, V.K.B.K.; Mutombo Kalonji, W.; Bardonneau, C.; Valverde Mordt, O.; Ngolo Tete, D.; Blesson, S.; Simon, F.; Delhomme, S.; Bernhard, S.; Mahenzi Mbembo, H.; et al. Oral fexinidazole for stage 1 or early stage 2 African Trypanosoma brucei gambiense trypanosomiasis: A prospective, multicentre, open-label, cohort study. Lancet Glob. Health 2021, 9, e999–e1008. [Google Scholar] [CrossRef] [Scilit]
- Bernhard, S.C.; Nerima, B.; Maser, P.; Brun, R. Melarsoprol- and pentamidine-resistant Trypanosoma brucei rhodesiense populations and their cross-resistance. Int. J. Parasitol. 2007, 37, 1443–1448. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carter, M.; Gomez, S.; Gritz, S.; Larson, S.; Silva-Herzog, E.; Kim, H.; Schulz, D.; Hovel-Miner, G. A Trypanosoma brucei ORFeome-based gain-of-function library identifies genes that promote survival during melarsoprol treatment. mSphere 2020, 5, e00769-20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scott, A.G.; Tait, A.; Turner, C.M.R. Trypanosoma brucei: Lack of cross-resistance to melarsoprol in vitro by cymelarsan-resistant parasites. Exp. Parasitol. 1997, 86, 181–190. [Google Scholar] [CrossRef] [Scilit]
- Jeacock, L.; Baker, N.; Wiedemar, N.; Maser, P.; Horn, D. Aquaglyceroporin-null trypanosomes display glycerol transport defects and respiratory-inhibitor sensitivity. PLoS Pathog. 2017, 13, e1006307. [Google Scholar] [CrossRef] [Scilit]
- Graf, F.E.; Ludin, P.; Wenzler, T.; Kaiser, M.; Brun, R.; Pyana, P.P.; Buscher, P.; de Koning, H.P.; Horn, D.; Maser, P. Aquaporin 2 mutations in Trypanosoma brucei gambiense field isolates correlate with decreased susceptibility to pentamidine and melarsoprol. PLoS Negl. Trop. Dis. 2013, 7, e2475. [Google Scholar] [CrossRef] [Scilit]
- Graf, F.E.; Ludin, P.; Arquint, C.; Schmidt, R.S.; Schaub, N.; Renggli, C.K.; Munday, J.C.; Krezdorn, J.; Baker, N.; Horn, D.; et al. Comparative genomics of drug resistance in Trypanosoma brucei rhodesiense. Cell. Mol. Life Sci. 2016, 73, 3387–3400. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Graf, F.E.; Baker, N.; Munday, J.C.; de Koning, H.P.; Horn, D.; Maser, P. Chimerization at the AQP2-AQP3 locus is the genetic basis of melarsoprol-pentamidine cross-resistance in clinical Trypanosoma brucei gambiense isolates. Int. J. Parasitol. Drugs Drug Resist. 2015, 5, 65–68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matovu, E.; Stewart, M.L.; Geiser, F.; Brun, R.; Maser, P.; Wallace, L.J.; Burchmore, R.J.; Enyaru, J.C.; Barrett, M.P.; Kaminsky, R.; et al. Mechanisms of arsenical and diamidine uptake and resistance in Trypanosoma brucei. Eukaryot.Cell 2003, 2, 1003–1008. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luscher, A.; Nerima, B.; Maser, P. Combined contribution of TbAT1 and TbMRPA to drug resistance in Trypanosoma brucei. Mol. Biochem. Parasitol. 2006, 150, 364–366. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Koning, H.P. Ever-increasing complexities of diamidine and arsenical crossresistance in African trypanosomes. Trends Parasitol. 2008, 24, 345–349. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matovu, E.; Seebeck, T.; Enyaru, J.C.K.; Kaminsky, R. Drug resistance in Trypanosoma brucei spp., the causative agents of sleeping sickness in man and nagana in cattle. Microbes Infect. 2001, 3, 763–770. [Google Scholar] [CrossRef] [Scilit]
- Barrett, M.P. Veterinary link to drug resistance in human African trypanosomiasis? Lancet 2001, 358, 603–604. [Google Scholar] [CrossRef] [Scilit]
- Hamill, L.C.; Kaare, M.T.; Welburn, S.C.; Picozzi, K. Domestic pigs as potential reservoirs of human and animal trypanosomiasis in Northern Tanzania. Parasit. Vectors 2013, 6, 322. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kasozi, K.I.; Namayanja, M.; Gaithuma, A.K.; Mahero, M.; Matovu, E.; Yamagishi, J.; Sugimoto, C.; MacLeod, E. Prevalence of hemoprotozoan parasites in small ruminants along a human-livestock-wildlife interface in western Uganda. Vet. Parasitol. Reg. Stud. Rep. 2019, 87, 100309. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fèvre, E.M.; Coleman, P.G.; Odiit, M.; Magona, J.W.; Welburn, S.C.; Woolhouse, M.E.J. The origins of a new Trypanosoma brucei rhodesiense sleeping sickness outbreak in eastern Uganda. Lancet 2001, 358, 625–628. [Google Scholar] [CrossRef] [Scilit]
- Fyfe, J.; Picozzi, K.; Waiswa, C.; Bardosh, K.L.; Welburn, S.C. Impact of mass chemotherapy in domestic livestock for control of zoonotic T. b. rhodesiense human African trypanosomiasis in Eastern Uganda. Acta Trop. 2017, 165, 216–229. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sokolova, A.Y.; Wyllie, S.; Patterson, S.; Oza, S.L.; Read, K.D.; Fairlamb, A.H. Cross-resistance to nitro drugs and implications for treatment of human African trypanosomiasis. Antimicrob. Agents Chemother. 2010, 54, 2893–2900. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Geiser, F.; Luscher, A.; de Koning, H.P.; Seebeck, T.; Maser, P. Molecular pharmacology of adenosine transport in Trypanosoma brucei: P1/P2 revisited. Mol. Pharmacol. 2005, 68, 589–595. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bridges, D.J.; Gould, M.K.; Nerima, B.; Maser, P.; Burchmore, R.J.S.; Koning, H.P. de Loss of the high-affinity pentamidine transporter is responsible for high levels of cross-resistance between arsenical and diamidine drugs in African trypanosomes. Mol. Pharmacol. 2007, 71, 1098–1108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lanteri, C.A.; Stewart, M.L.; Brock, J.M.; Alibu, V.P.; Meshnick, S.R.; Tidwell, R.R.; Barrett, M.P. Roles for the Trypanosoma brucei P2 transporter in DB75 uptake and resistance. Mol. Pharmacol. 2006, 70, 1585–1592. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Scott, A.G.; Tait, A.; Turner, C.M.R. Characterisation of cloned lines of Trypanosoma brucei expressing stable resistance to MelCy and suramin. Acta Trop. 1996, 60, 251–262. [Google Scholar] [CrossRef] [Scilit]
- Matovu, E.; Iten, M.; Enyaru, J.C.K.; Schmid, C.; Lubega, G.W.; Brun, R.; Kaminsky, R. Susceptibility of Ugandan Trypanosoma brucei rhodesiense isolated from man and animal reservoirs to diminazene, isometamidium and melarsoprol. Trop. Med. Int. Health 1997, 2, 13–18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Foucher, A.L.; McIntosh, A.; Douce, G.; Wastling, J.; Tait, A.; Turner, C.M.R. A proteomic analysis of arsenical drug resistance in Trypanosoma brucei. Proteomics 2006, 6, 2726–2732. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Delespaux, V.; de Koning, H.P. Drugs and drug resistance in African trypanosomiasis. Drug Resist. Update 1368, 10, 30–50. [Google Scholar] [CrossRef] [Scilit]
- De Koning, H.P. Transporters in African trypanosomes: Role in drug action and resistance. Int. J. Parasitol. 2001, 31, 512–522. [Google Scholar] [CrossRef] [Scilit]
- Wyllie, S.; Foth, B.J.; Kelner, A.; Sokolova, A.Y.; Berriman, M.; Fairlamb, A.H. Nitroheterocyclic drug resistance mechanisms in Trypanosoma brucei. J. Antimicrob. Chemother. 2016, 71, 625–634. [Google Scholar] [CrossRef] [Scilit]
- Worthen, C.; Jensen, B.C.; Parsons, M. Diverse Effects on Mitochondrial and Nuclear Functions Elicited by Drugs and Genetic Knockdowns in Bloodstream Stage Trypanosoma brucei. PLoS Negl. Trop. Dis. 2010, 4, e678. [Google Scholar] [CrossRef] [Scilit]
- Wiedemar, N.; Graf, F.E.; Zwyer, M.; Ndomba, E.; Kunz Renggli, C.; Cal, M.; Schmidt, R.S.; Wenzler, T.; Mäser, P. Beyond immune escape: A variant surface glycoprotein causes suramin resistance in Trypanosoma brucei. Mol. Microbiol. 2018, 107, 57–67. [Google Scholar] [CrossRef] [Scilit]
- Zeelen, J.; van Straaten, M.; Verdi, J.; Hempelmann, A.; Hashemi, H.; Perez, K.; Jeffrey, P.D.; Halg, S.; Wiedemar, N.; Maser, P.; et al. Structure of trypanosome coat protein VSGsur and function in suramin resistance. Nat. Microbiol. 2021, 6, 392–400. [Google Scholar] [CrossRef] [Scilit]
- Burkard, G.S.; Jutzi, P.; Roditi, I. Genome-wide RNAi screens in bloodstream form trypanosomes identify drug transporters. Mol. Biochem. Parasitol. 2011, 175, 91–94. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vincent, I.M.; Creek, D.; Watson, D.G.; Kamleh, M.A.; Woods, D.J.; Wong, P.; Burchmore, R.J.S.; Barrett, M.P. A molecular mechanism for eflornithine resistance in African trypanosomes. PLoS Pathog. 2010, 6, e1001204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baker, N.; Alsford, S.; Horn, D. Genome-wide RNAi screens in African trypanosomes identify the nifurtimox activator NTR and the eflornithine transporter AAT6. Mol. Biochem. Parasitol. 2011, 176, 55–57. [Google Scholar] [CrossRef] [Scilit]
- Wiedemar, N.; Zwyer, M.; Zoltner, M.; Cal, M.; Field, M.C.; Maser, P. Expression of a specific variant surface glycoprotein has a major impact on suramin sensitivity and endocytosis in Trypanosoma brucei. FASEB BioAdv. 2019, 1, 595–608. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bacchi, C.J.; Nathan, H.C.; Yarlett, N.; Goldberg, B.; McCann, P.P.; Sjoerdsma, A.; Saric, M.; Clarkson, A.B., Jr. Combination chemotherapy of drug-resistant Trypanosoma brucei rhodesiense infections in mice using DL-alpha-difluoromethylornithine and standard trypanocides. Antimicrob. Agents Chemother. 1994, 38, 563–569. [Google Scholar] [CrossRef] [Scilit]
- Bacchi, C.J.; Garofalo, J.; Ciminelli, M.; Rattendi, D.; Goldberg, B.; McCann, P.P.; Yarlett, N. Resistance to DL-a-difluoromethylornithine by clinical isolates of Trypanosoma brucei rhodesiense. Role of S-adenosylmethionine. Biochem. Pharmacol. 1993, 46, 471–481. [Google Scholar] [CrossRef] [Scilit]
- Pati, P.P.; van Reet, N.; Ngoyi, D.M.; Lukusa, I.N.; Shamamba, S.K.; Buscher, P. Melarsoprol sensitivity profile of Trypanosoma brucei gambiense isolates from cured and relapsed sleeping sickness patients from the Democratic Republic of the Congo. PLoS Negl. Trop. Dis. 2014, 8, e3212. [Google Scholar] [CrossRef] [Scilit]
- Matovu, E.; Enyaru, J.C.K.; Legros, D.; Schmid, C.; Seebeck, T.; Kaminsky, R. Melarsoprol refractory T. b. gambiense from Omugo, north-western Uganda. Spec. Issue. Hum. Afr. Trypanos. Approaches Roll Back Sleep. Sick. 2001, 6, 407–411. [Google Scholar] [CrossRef] [Scilit]
- Brun, R.; Schumacher, R.; Schmid, C.; Kunz, C.; Burri, C. The phenomenon of treatment failures in human African trypanosomiasis. Trop. Med. Int. Health 2001, 6, 906–914. [Google Scholar] [CrossRef] [Scilit]
- Hawking, F. Drug Resistance acquired during the Treatment of Sleeping-Sickness with Tryparsamide and with Bayer 205. Am. J. Trop. Med. 1941, 21, 469–479. [Google Scholar] [CrossRef] [Scilit]
- Kagira, J.M.; Maina, N. Occurrence of multiple drug resistance in Trypanosoma brucei rhodesiense isolated from sleeping sickness patients. Onderstepoort J. Vet. Res. 2007, 74, 17–22. [Google Scholar] [PubMed]
- Kibona, S.N.; Matemba, L.; Kaboya, J.S.; Lubega, G.W. Drug-resistance of Trypanosoma b. rhodesiense isolates from Tanzania. Trop. Med. Int. Health 2006, 11, 144–155. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maina, N.; Maina, K.J.; Maser, P.; Brun, R. Genotypic and phenotypic characterization of Trypanosoma brucei gambiense isolates from Ibba, South Sudan, an area of high melarsoprol treatment failure rate. Acta Trop. 2007, 104, 84–90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mpia, B.; Pepin, J. Combination of eflornithine and melarsoprol for melarsoprol-resistant Gambian trypanosomiasis. Trop. Med. Int. Health 2002, 7, 775–779. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Munday, J.C.; Eze, A.A.; Baker, N.; Glover, L.; Clucas, C.; Aguinaga Andrés, D.; Natto, M.J.; Teka, I.A.; McDonald, J.; Lee, R.S.; et al. Trypanosoma brucei aquaglyceroporin 2 is a high-affinity transporter for pentamidine and melaminophenyl arsenic drugs and the main genetic determinant of resistance to these drugs. J. Antimicrob. Chemother. 2014, 69, 651–663. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Munday, J.C.; Tagoe, D.N.A.; Eze, A.A.; Krezdorn, J.A.M.; Rojas López, K.E.; Alkhaldi, A.A.M.; McDonald, F.; Still, J.; Alzahrani, K.J.; Settimo, L.; et al. Functional analysis of drug resistance-associated mutations in the T rypanosoma brucei adenosine transporter 1 (TbAT1) and the proposal of a structural model for the protein. Mol. Microbiol. 2015, 96, 887–900. [Google Scholar] [CrossRef] [Scilit]
- Mutuku, C.N.; Bateta, R.; Rono, M.K.; Njunge, J.M.; Awuoche, E.O.; Ndung’u, K.; Mang’era, C.M.; Akoth, M.O.; Adung’a, V.O.; Ondigo, B.N.; et al. Physiological and proteomic profiles of Trypanosoma brucei rhodesiense parasite isolated from suramin responsive and non-responsive HAT patients in Busoga, Uganda. Int. J. Parasitol. Drugs Drug Resist. 2021, 15, 57–67. [Google Scholar] [CrossRef] [Scilit]
- Nerima, B.; Matovu, E.; Lubega, G.W.; Enyaru, J.C.K. Detection of mutant P2 adenosine transporter (TbAT1) gene in Trypanosoma brucei gambiense isolates from northwest Uganda using allele-specific polymerase chain reaction. Trop. Med. Int. Health 2007, 12, 1361–1368. [Google Scholar] [CrossRef] [Scilit]
- Nnadi, C.O.; Ebiloma, G.U.; Black, J.A.; Nwodo, N.J.; Lemgruber, L.; Schmidt, T.J.; de Koning, H.P. Potent antitrypanosomal activities of 3-aminosteroids against African trypanosomes: Investigation of cellular effects and of cross-resistance with existing drugs. Molecules 2019, 24, 268. [Google Scholar] [CrossRef] [Scilit]
- Sanderson, L.; Dogruel, M.; Rodgers, J.; De Koning, H.P.; Thomas, S.A. Pentamidine Movement across the Murine Blood-Brain and Blood-Cerebrospinal Fluid Barriers: Effect of Trypanosome Infection, Combination Therapy, P-Glycoprotein, and Multidrug Resistance-Associated Protein. J. Pharmacol. Exp. Ther. 2009, 329, 967–977. [Google Scholar] [CrossRef] [Scilit]
- Foulkes, J.R. Metronidazole and suramin combination in the treatment of arsenical refractory Rhodesian sleeping sickness—A case study. Trans. R. Soc. Trop. Med. Hyg. 1996, 90, 422. [Google Scholar] [CrossRef] [Scilit]
- Pepin, J.; Milord, F.; Mpia, B.; Meurice, F.; Ethier, L.; DeGroof, D.; Bruneel, H. An open clinical trial of nifurtimox for arseno-resistant Trypanosoma brucei gambiense sleeping sickness in central Zaire. Trans. R. Soc. Trop. Med. Hyg. 1989, 83, 514–517. [Google Scholar] [CrossRef] [Scilit]
- Pepin, J.; Milord, F.; Meurice, F.; Ethier, L.; Loko, L.; Mpia, B. High-dose nifurtimox for arseno-resistant Trypanosoma brucei gambiense sleeping sickness: An open trial in central Zaire. Trans. R. Soc. Trop. Med. Hyg. 1992, 86, 254–256. [Google Scholar] [CrossRef] [Scilit]
- Richardson, J.B.; Evans, B.; Pyana, P.P.; van Reet, N.; Sistrom, M.; Buscher, P.; Aksoy, S.; Caccone, A. Whole genome sequencing shows sleeping sickness relapse is due to parasite regrowth and not reinfection. Evol. Appl. 2016, 9, 381–393. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matovu, E.; Geiser, F.; Schneider, V.; Maser, P.; Enyaru, J.C.K.; Kaminsky, R.; Gallati, S.; Seebeck, T. Genetic variants of the TbAT1 adenosine transporter from African trypanosomes in relapse infections following melarsoprol therapy. Mol. Biochem. Parasitol. 2001, 117, 73–81. [Google Scholar] [CrossRef] [Scilit]
- Balasegaram, M.; Harris, S.; Checchi, F.; Ghorashian, S.; Hamel, C.; Karunakara, U. Melarsoprol versus eflornithine for treating late-stage Gambian trypanosomiasis in the Republic of the Congo. Bull. World Health Organ. 2006, 84, 783–791. [Google Scholar] [CrossRef] [Scilit]
- Pepin, J.; Khonde, N.; Maiso, F.; Doua, F.; Jaffar, S.; Ngampo, S.; Mpia, B.; Mbulamberi, D.; Kuzoe, F. Short-course eflornithine in Gambian trypanosomiasis: A multicentre randomized controlled trial. Bull. World Health Organ. 2000, 78, 1284–1295. [Google Scholar]
- Scientific Working Group on African Trypanosomiasis. Proceedings of the Report of the Scientific Working Group meeting on African trypanosomiasis, Geneva, Switzerland, 4–8 June 2001; p. 96.
- Burri, C.; Keiser, J. Pharmacokinetic investigations in patients from northern Angola refractory to melarsoprol treatment. Spec. Issue. Hum. Afr. Trypanos. Approaches Roll Back Sleep. Sick. 2001, 6, 412–420. [Google Scholar] [CrossRef] [Scilit]
- Kazibwe, A.J.N.; Nerima, B.; de Koning, H.P.; Maser, P.; Barrett, M.P.; Matovu, E. Genotypic status of the TbAT1/P2 adenosine transporter of Trypanosoma brucei gambiense isolates from Northwestern Uganda following melarsoprol withdrawal. PLoS Negl. Trop. Dis. 2009, 3, e523. [Google Scholar] [CrossRef] [Scilit]
- Pyana, P.P.; Sere, M.; Kabore, J.; de Meeus, T.; MacLeod, A.; Bucheton, B.; van Reet, N.; Buscher, P.; Belem, A.M.G.; Jamonneau, V. Population genetics of Trypanosoma brucei gambiense in sleeping sickness patients with treatment failures in the focus of Mbuji-Mayi, Democratic Republic of the Congo. Infect. Genet. Evol. 2015, 30, 128–133. [Google Scholar] [CrossRef] [Scilit]
- Balasegaram, M.; Harris, S.; Checchi, F.; Hamel, C.; Karunakara, U. Treatment outcomes and risk factors for relapse in patients with early-stage human African trypanosomiasis (HAT) in the Republic of the Congo. Bull. World Health Organ. 2006, 84, 777–782. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Babokhov, P.; Sanyaolu, A.O.; Oyibo, W.A.; Fagbenro-Beyioku, A.F.; Iriemenam, N.C. A current analysis of chemotherapy strategies for the treatment of human African trypanosomiasis. Pathog. Glob. Health 2013, 107, 242–252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lutje, V.; Seixas, J.; Kennedy, A. Chemotherapy for second-stage human African trypanosomiasis. Cochrane Database Syst. Rev. 2013, 2013, CD006201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Begley, C.G.; Ioannidis, J.P.A. Reproducibility in science: Improving the standard for basic and preclinical research. Circ. Res. 2015, 116, 116–126. [Google Scholar] [CrossRef] [Scilit]
- Wolff, J.O. Laboratory studies with rodents: Facts or artifacts? Bioscience 2003, 53, 421–427. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).