


Abstract
Objective: The likelihood of timely treatment for cervical cancer increases with timely detection of abnormal cervical cells. Automated methods of detecting abnormal cervical cells were established because manual identification requires skilled pathologists and is time consuming and prone to error. The purpose of this systematic review is to evaluate the diagnostic performance of artificial intelligence (AI) technologies for the prediction, screening, and diagnosis of cervical cancer and pre-cancerous lesions. Materials and Methods: Comprehensive searches were performed on three databases: Medline, Web of Science Core Collection (Indexes = SCI-EXPANDED, SSCI, A & HCI Timespan) and Scopus to find papers published until July 2022. Articles that applied any AI technique for the prediction, screening, and diagnosis of cervical cancer were included in the review. No time restriction was applied. Articles were searched, screened, incorporated, and analyzed in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-analyses guidelines. Results: The primary search yielded 2538 articles. After screening and evaluation of eligibility, 117 studies were incorporated in the review. AI techniques were found to play a significant role in screening systems for pre-cancerous and cancerous cervical lesions. The accuracy of the algorithms in predicting cervical cancer varied from 70% to 100%. AI techniques make a distinction between cancerous and normal Pap smears with 80–100% accuracy. AI is expected to serve as a practical tool for doctors in making accurate clinical diagnoses. The reported sensitivity and specificity of AI in colposcopy for the detection of CIN2+ were 71.9–98.22% and 51.8–96.2%, respectively. Conclusion: The present review highlights the acceptable performance of AI systems in the prediction, screening, or detection of cervical cancer and pre-cancerous lesions, especially when faced with a paucity of specialized centers or medical resources. In combination with human evaluation, AI could serve as a helpful tool in the interpretation of cervical smears or images.
1. Introduction
Cervical cancer is the fourth most frequently diagnosed cancer and the fourth leading cause of cancer death in women [1], which accounts for 570,000 incident cases and 310,000 deaths each year worldwide [2]. Cervical cancer is the most commonly diagnosed cancer in 23 countries in the world and is the leading cause of cancer death in 36 countries, with the vast majority of these countries found in sub-Saharan Africa, Melanesia, South America, and South-Eastern Asia. The region with the highest incidence and mortality rates is sub-Saharan Africa, with rates particularly high in Eastern Africa (Malawi has the world’s highest incidence and mortality rate in the world), Southern Africa, and Middle Africa. In Northern America, Australia/New Zealand, and Western Asia (Saudi Arabia and Iraq), incidence rates are 7 to 10 times lower, while mortality rates can vary by up to 18 times [3].
Cervical cancer is almost fully preventable because of its long premalignant phase and is curable if the signs are identified and treated in the earliest stage [4,5,6]. Effective prevention strategies for cervical cancer include the use of screening tests for primary and secondary prevention, human papillomavirus (HPV) vaccination, and early detection and treatment of cervical intraepithelial neoplasia. [7,8,9,10,11,12,13,14]. The gold standard for the diagnosis of cervical cancer is still colposcopy-guided biopsy, which is then staged on the basis of the clinical examination and the outcome of imaging procedures [15,16]. Although this is an effective strategy in high-income nations, its execution requires a well-organized infrastructure, as well as skilled professionals, such as pathologists, cytopathologists, and colposcopy specialists [17,18,19]. Many efficient screening programs have been developed in recent times [20], but their implementation and maintenance are hindered by insufficient numbers of professionals [21] and the absence of an adequate health infrastructure [22]. Furthermore, manual screening is not always accurate [23], and may cause some lesions to escape detection for a certain period of time [16].
Artificial intelligence (AI) provides an automated diagnosis; its significant potential in resolving this issue is proven [24]. AI has been used to an increasing extent for the diagnosis of numerous diseases in recent years, including the classification of skin malignancies [25], imaging diagnosis of tumors [26], the detection and classification of retinal diseases [27], and gynecologic cancer [28]. With the use of sophisticated algorithms, AI has the ability to recognize images, learn classifications, extract features, and process data autonomously [16,29]. The research suggests that AI-assisted technology may be utilized for segmentation of cytoplasm and identification of cervical epithelial dysplasia; however, it is still unknown how well AI-assisted cytology will perform in population-based screening [30]. The application of AI in early screening and detection of cervical cancer has helped address the issue of scarce human resources and enhances diagnostic precision [16]. While most of the technologies supporting AI in pathology are either in the development stage or are in the observational study stage, they are not frequently used in routine large-scale screenings [31]. Considering the high demands and expectations of these tools in clinical practice, evidence supporting AI-based diagnosis needs to be systematically reviewed. The aim of the present review is to evaluate the diagnostic performance of AI technologies in cervical cancer and pre-cancerous lesions.
2. Materials and Methods
Published articles that developed or validated AI techniques for the prediction, screening, and diagnosis of cervical cancer were searched for a systematic review (PROSPERO registration ID: CRD42022352650).
2.1. Research Question
The review was based on the following research question: what do we know about AI, and what is the accuracy of AI techniques in detecting cervical cancer or pre-cancerous lesions?
2.2. Search Strategy and Information Sources
The Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) criteria were used to design the study [32]. We searched for relevant articles in the three databases PubMed/MEDLINE, Scopus, and Web of Science. The following keywords were used for the search in July 2022: “artificial intelligence”, combined with “cervical cancer”, “cervical intraepithelial neoplasia (CIN)”, “uterine cervical neoplasms”, “cervical neoplasm”, “atypical squamous cells of undetermined significance”, “high-grade squamous intraepithelial lesion (HSIL)”, “low-grade squamous intraepithelial lesion (LSIL)”, “atypical squamous cells of undetermined significance”, “Pap smear”, “Bethesda system”, “screening”, “prediction”, “cytology”, “colposcopy”, “detection”, and “diagnosis”. MeSH keywords and Boolean (AND, OR) operators were employed to enhance the selection of entries.
2.3. Inclusion and Exclusion Criteria
We included all types of observational studies dealing with cervical cancer screening, diagnosis, and prediction programs for early and appropriate detection, performed anywhere in the world and published exclusively in the English language.
Studies focused on animals, genomic and molecular studies, segmentation of nuclei, genomic profiles, biomarkers, chromosomal alteration progression, gene expression profiling, optoelectronic sensor, spectroscopy, mathematical model, and cervical cancer prognosis were excluded. Furthermore, studies addressing the segmentation of cancerous lesions on magnetic resonance imaging (MRI)/computed tomography (CT) images, non-full-text articles, case reports, reviews, commentaries, letters to editors, conference presentations, and reports were omitted. Two authors independently assessed the titles and/or abstracts of articles that were retrieved using the search method and those from additional sources to find studies that would fit the criteria of this systematic review. Discussion with a third (external) collaborator was used to settle any differences they had on the eligibility of specific articles.
2.4. Study Selection
Three authors reviewed, screened, and extracted the search results. The EndNote software (EndNote X9, Thomson Reuters) was used to list the studies and screen them on the basis of the inclusion criteria. The third expert author strategy was used for conflicts in the screening step. The studies were initially chosen according to the relevance of their titles and abstracts (LA and AMM). Then, the full texts were examined to validate their eligibility (LA and IA). We included articles that addressed any diagnosis of cervical cancer and pre-cancerous lesions.
2.5. Data Extraction and Synthesis
Details of all articles were extracted and reported from the studies using a pre-piloted customized standard form in order to ensure the consistency of this step for all investigations. Data such as the authors, year of publication, sample size, methods, and datasets were independently extracted by the two writers. Any disagreement was clarified through discussion (with a third external collaborator if necessary). Due to the diverse modes of reporting, we performed a narrative synthesis of the studies.
3. Results
3.1. Search Results
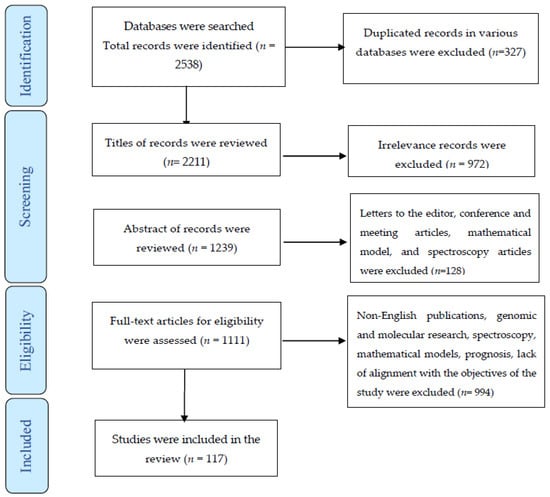
A total of 2538 publications, 327 of which were duplicate articles, were found in the various databases. After reviewing the titles and abstracts of the remaining papers, 1100 were excluded. Of the remaining articles, 994 were omitted for the lack of alignment with the objectives of the study. Finally, the systematic review comprised 117 studies (Figure 1).
Figure 1.
The process of screening and selecting relevant studies based on the Preferred Reporting Items for Systematic Reviews and Meta-Analyses.
3.1.1. Application of AI for Cervical Cancer and Its Cost-Effectiveness
From 1997—when cervical cancer screening was performed for the first time with AI—until today, various machine learning algorithms have been applied for the detection of cervical cancer [30,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47,48,49,50,51,52,53,54]. Common machine learning (ML) models included deep learning (DL), k-nearest neighbors (KNN), artificial neural network (ANN), decision tree (DT), random forest (RF), support vector machine (SVM), logistic regression (LR), synthetic minority oversampling technique (SMOTE), convolutional neural network (CNN), multilayer perceptron (MLP), deep neural networks (DNN), the PAPNET test, and ResNet (residual neural network or a combination of techniques) [36,39,45,46,55,56,57,58,59,60,61,62,63,64,65,66,67,68,69,70,71,72,73,74,75]. The time taken for training and for the prediction of cervical cancer by each algorithm varied markedly. In Kruczkowski et al.’s study, the time needed to train for the Naïve Bayes and CNN algorithms varied from 7.54 ms to 5320 ms. The prediction time for cervical cancer by the Naïve Bayes and RF algorithms varied from 1.81 ms to 15.5 ms, and the accuracies differed [76]. Elakkiya et al. reported an average of 0.2 s to classify the cervical lesion using a hybrid deep learning technique that combined small-object detection generative adversarial networks (SOD-GAN) and the fine-tuned stacked autoencoder (F-SAE). [77]. In recent years, the rapid progress of AI technologies and the use of combined features have significantly reduced costs, time, the cost of training, and the inference time [52,78,79]. These advancements have also improved the patient’s access to professional pathologists and the prompt delivery of cytology results [78].
However, the cost effectiveness of AI was questioned in some studies because the cost of AI techniques far exceeded that of manual screening. Additionally, commonly used techniques require a considerable database for training the application of models and this constitutes a barrier in the diagnosis of cervical cancer [80].
The following four groups were created from the 117 studies that were deemed suitable for the investigation: AI application in cervical cancer prediction (n = 22), AI application in cervical cancer screening (n = 25), AI application in cytology (n = 44), and colposcopy (n = 26) for the detection of cervical cancer.
3.1.2. Application of AI in Predicting Cervical Cancer
Identifying predictors is essential for making precise and meaningful predictions [81]. Multivariate adjustment and multiple-regression techniques were introduced for prediction (that is, for estimating the predicted value of a certain outcome as a function of given values of independent variables) [82]. AI studies using machine learning principles have focused on algorithms to predict cervical cancer [55,56,57,58,59,60,61,62,63,83,84,85,86,87,88,89,90,91,92,93,94,95]. The most important predictors of cervical cancer were age, age at first sexual intercourse, number of sexual partners, pregnancies, smoking, period of smoking (years), hormonal contraceptives, period of use of hormonal contraceptives (years), IUD, period of use of IUD (years), STDs, period of STDs (years), Schiller, Hinselmann, cytology, the presence of 15 high-risk HPV genotypes [55,56,57,58,60,84], social status, marital status, personal health level, education level, and the number of caesarean deliveries [63]. However, according to Mudawi et al., certain characteristics of the patient samples, including the quantity of alcohol consumed and the presence of HIV and HSV2, could not be regarded as reliable predictors [95]. Based on the data shown in Table 1, the accuracy of the algorithms in predicting cervical cancer varied from 70% to 100% [55,56,57,58,59,60,62,83,84,85,86,87,88,89,90,91,92,93,94,95]. The application of AI for the prediction of cervical cancer is shown in Table 1.
Table 1.
Characteristics of studies with AI for the prediction of cervical cancer.
3.1.3. Application of AI in Cervical Cancer Screening
Screening is a way of identifying apparently healthy people who may have an increased risk of a particular condition [97]. The screening test needs to be sensitive and precise. A screening test must have sensitivity exceeding 95% if the specificity is less than or equal to 95% and vice versa (specificity must be >95% if the sensitivity is 95%) in order to detect more true-positive cases than false-positive cases when the prevalence of the disease is less than or equal to 5% (which covers the majority of screening populations). Most screening tests do not meet this high standard, which means that the screening program must absorb the costs of many false-positive results [98].
The use of AI in screening for cervical cancer has produced contradictory results. In some studies, the use of artificial intelligence reduced false-negative outcomes compared to traditional methods [33]. Other studies reported an increase in false-negative outcomes [35]. Yet other investigations registered no difference between AI and conventional methods [37]. Michelow and coworkers [34] reported no significant difference between manual detection and PAPNET for invasive carcinoma and HSIL. Interestingly, these contradictions were observed in older studies as well [33,35,37]. In recent times, the performance of AI in cervical cancer screening was better than that of conventional and manual methods [38,42,53]. With equal sensitivity and much higher specificity compared to both Pap and manual DS, AI-based dual staining (DS) yielded lower positivity than cytology and manual DS [53]. The better performance of AI in recent studies may be attributed to the hybrid ensemble approach, combined algorithms and techniques, and the grade of squamous intraepithelial lesions [38,39,46]. Sarwar et al. [38] reported that the hybrid ensemble technique outperformed all other algorithms and demonstrated a screening efficiency of nearly 98%. According to Bao et al. [30], the overall agreement rate between manual reading and AI in CIN detection was 94.7% (95% confidence interval 94.5–94.8%), and the kappa coefficient was 0.92 (0.91–0.92). Furthermore, the performance of AI in the detection of CIN2+ increased with the severity of detected abnormalities on cytology. The accuracy of AI in screening for CIN 1–3 and adenocarcinoma in situ varies between 67% and 98.27% [39,40,41]. The application of AI in cervical cancer screening is shown in Table 2.
Table 2.
Characteristics of studies on the use of AI in screening for cervical cancer.
3.1.4. Application of AI in Cytology for the Detection of Cervical Cancer
Cervical cytology image analysis is a very time-consuming, challenging, and laborious task [99]. Computer-assisted diagnosis is believed to ease this situation because it can potentially lower the misdiagnosis rate and also reduce the workload of cytologists [100]. Therefore, several studies have addressed the subject of automatic cervical cancer diagnosis [64,65,66,67,68,74,75,80,101,102,103,104,105,106,107,108,109,110,111,112,113,114,115,116,117,118,119,120,121,122,123,124,125,126,127,128,129,130,131,132,133,134,135,136]. The investigations showed that AI-assisted methods were promising, and achieved a high sensitivity and specificity in clinical cervical cytological screening [66,126]. In a multicenter, clinical-based observational study by Bao et al., AI-assisted reading identified considerably more CIN 2 (92.6%) and CIN 3+ (96.1%) lesions than, or at a similar rate as, manual reading. Compared to expert cytologists, AI-assisted reading showed a similar sensitivity (relative sensitivity of 1.01) and greater specificity (relative specificity of 1.26) [66]. Cao and co-workers [130] compared the performance of AI-assisted reading with that of four pathologists. The first two pathologists had 4 years of work experience, and the third and fourth pathologist had 7 and 10 years of work experience, respectively. The proposed model achieved an area under the receiver operating characteristics (AUROC) of 0.99, and an accuracy of 98.0%, which was comparable to a pathologist with a decade of expertise (accuracy, 93.7%). Additionally, pathologists needed on average 14.83 s to diagnose each image, compared to the 0.04 s needed by the AI-assisted method. In fact, reading with AI assistance was approximately 380 times faster than reading by a typical pathologist. AI algorithms were able to distinguish between normal and cancerous Pap smears with an accuracy of 80–100% [68,110,111,113,115,116,119,120,125,127,130,131,135,137]. The application of AI in cytology for the detection of cervical cancer is shown in Table 3.
Table 3.
Characteristics of studies on the use AI in cytology to detect cervical cancer.
3.1.5. Application of AI in Colposcopy for the Detection of Cervical Cancer
AI-assisted tools appear to be very suitable for the cervical cancer diagnostic protocol, which recommends colposcopy in cases of an abnormal PAP smear and/or high-risk HPV and the collection of diagnostic tissue samples before initiating any potentially invasive treatment [138]. In response to this demand, a few notable studies were published on the use of AI in colposcopy for the detection of cervical cancer [69,70,71,72,73,77,79,137,138,139,140,141,142,143,144,145,146,147,148,149,150,151,152,153,154,155,156]. According to several investigations, the AI diagnostic approach could support or even potentially replace conventional colposcopy, permit more objective tissue specimen sampling, and reduce the number of cervical cancer cases in developing nations by offering an economical screening option in low-resource settings [137,141]. Some research suggests that AI could help less skilled clinicians to decide whether to perform a cervical biopsy [70,144,145,156]. In addition, AI helped gynecologists to accurately establish the presence of invasive cancer on cervical pathological images diagnosed by AI [156]. According to a large study (over 19,000 patients) performed in China by Xue et al., the agreement between pathology findings and colposcopic impressions graded by the Colposcopic Artificial Intelligence Auxiliary Diagnostic System (CAIADS) was higher than that of colposcopies interpreted by colposcopists (82.2% vs. 65.9%). Additionally, the CAIADS proved to be more accurate in predicting biopsy sites [147]. In published studies, the sensitivity and specificity of AI in colposcopy for the detection of CIN 2 or more severe lesions were reported at 71.9–98.22% and 51.8–96.2%, respectively [70,72,73,137,138,139,140,143,147,148,150,151,152,154]. The accuracy of AI in colposcopy for CIN 2+ detection varied from 40.5% to 98.3% [70,72,77,137,143,146,147,148,150,151,152,154,156]. The use of AI in colposcopy for the detection of cervical cancer is summarized in Table 4.
Table 4.
Characteristics of studies on the use of AI in colposcopy for the detection of cervical cancer.
4. Discussion
Despite tremendous progress in the treatment of cancer, cervical cancer cells are occasionally detected at a time when the disease has already caused distant metastasis [157]. This is a major problem in third-world countries with inferior health systems [5,8]. Furthermore, monetary and personal limitations increase the need for alternative tools as the number of people to be treated by professionals increases [158]. Thus, we need better diagnostic tools for cancer [157]. The application of AI not only in medicine but also other majors has grown significantly over the past ten years, particularly in the last five years [28,159,160] at three levels: for patients, by enabling them to process their own data to promote health; for health systems, by improving workflow and the potential for reducing medical errors; and for clinicians, predominantly via rapid, accurate image interpretation [161].
The aim of this systematic review is to evaluate the diagnostic performance of AI technologies in cervical cancer and pre-cancerous lesions. Estimating the prognosis of cervical cancer is one of the most difficult tasks because its management requires a variety of cancer treatment approaches [162,163], which may even impair quality of life to a significant extent [164,165].
The studies included in this systematic review employed models to identify a variety of predictors, including age, numbers of sexual partners, age at the first sexual intercourse, deliveries, smoking, hormonal and barrier contraceptives, STDs, marital status, personal health level, education level, social status, number of caesarean deliveries, and the presence of 15 high-risk HPV genotypes. The accuracy of different AI algorithms in predicting cervical cancer varies from 70% to 100%. More reliable predictions are achieved when the prediction models for cervical cancer are combined with the hybrid ensemble approach. Compared to studies focused on AI techniques, in a cohort study, Schulte-Frohlinde et al. [166] noted that cervical cancer could be predicted among high-risk HPV-positive women. Age at sexual debut was a significant modifier of the incidence of cervical cancer.
The prediction of cervical cancer on the basis of AI techniques has produced promising results. The findings of a study by Nsugbe showed how prediction machines can contribute towards early detection and prioritize the care of patients with cervical cancer, while also allowing for cost-saving benefits when compared with routine cervical cancer screening [167].
Cytology-based cervical cancer screening has poor accuracy [168]. In addition to the fact that the procedure needs clinical consultants who have undergone significant training, it is time consuming and susceptible to human interpretation and error [81,169]. The use of computer technologies may reduce the likelihood of misdiagnoses, analysis time, and assist in early diagnosis [169].
In the present systematic review, we reviewed studies investigating the performance of AI in screening and cytology for the detection of cervical cancer. The accuracy of AI in the detection of CIN 1–3 and adenocarcinoma in situ varied from 67% to 98.27%. However, we registered contradictory results regarding the performance of AI in cervical cancer screening, in terms of poor as well as better performance compared to traditional methods. The poor performance of AI appears to be limited to old methods of AI. Conversely, applying the hybrid ensemble approach and combined applied algorithms of new AI techniques performed better than traditional and manual approaches. We observed that AI techniques are able to distinguish between normal and cancerous Pap smears with 80–100% accuracy, and were 380 times faster than the typical pathologist. Pap smear testing is a fundamental procedure in protecting women from cervical cancer. However, the effort of a cytologist to detect morphologic changes in lesions with 20,000–50,000 cells on a single slide is tedious, arduous, and dependent on experience [67]. In a cross-sectional study by Wergeland Sørbye et al. [168], four pathologists at three hospitals in Norway evaluated one hundred Pap smears (20 cases normal, 20 cases LSIL, 20 cases HSIL, 20 cases atypical squamous cells of undetermined significance (ASC-US), and 20 high grade squamous intra-epithelial lesion (ASC-H)). The accuracy for CIN2+ varied from 74.1% to 83.8%. Therefore, the claim that AI improves the effectiveness of diagnosis, reduces the clinician’s workload, and even enhances the impact of treatment and prognosis would seem plausible [53,138]. Furthermore, AI was shown to be more adept than the human brain in recognizing specific patterns [138].
Currently, the two most common techniques used to diagnose precancerous cervical lesions are colposcopy and guided biopsy. However, numerous investigations have shown that even practitioners who are skilled in colposcopy struggle to make the right diagnosis [170]. Consequently, the standardized and less volatile diagnostic tools of AI might be useful [79]. Many studies included in the present review concluded that, in cervical cancer diagnosis, AI may be able to supplement or perhaps even replace current colposcopy procedures. The sensitivity and specificity of AI for the detection of CIN2+ were reported to be 71.9–98.22% and 51.8–96.2% respectively [70,72,73,137,138,139,140,143,147,148,150,151,152,154]. The accuracy of AI for the detection of CIN 2+ varied from 40.5% to 98.3%. These data demonstrate the potential of AI in reading colposcopic images. According to a meta-analysis by Mitchell et al. [171], the sensitivity of colposcopists in diagnosing CIN varies greatly compared to the performance of AI: the average weighted sensitivity of colposcopy in differentiating between normal and all cervix abnormalities (atypia, low-grade SIL, high-grade SIL, cancer) was 96%, and the average weighted specificity was 48%.
The threshold normal cervix has an area under the ROC curve of 0.80 when compared to other abnormalities. A gynecologist with little experience might overlook high-grade lesions [172]. AI technologies may serve as a practical aid for the inexperienced gynecologist or general physician in making a precise clinic diagnosis or a wise choice in terms of diagnostic intervention, such as whether to perform a punch biopsy or transfer the patient to a specialized center [79,144,171]. According to Kim et al. [79], the clinical interpretation of colposcopic images by AI had a higher AUC in identifying low- and high-risk lesions than the clinical interpretation of colposcopic images by humans. These findings imply that AI interpretations may be used in the clinical setting. A recent study that evaluated deep learning algorithms for automatic categorization of colposcopic images supports this notion [144]. Automated visual evaluation of cervical images had a higher AUC than the original interpretation of cervical images by human or conventional cytology [40].
Limitations and Recommendations
The limitations of the studies investigated for this systematic review are worthy of mention. First of all, the majority of the investigations were underpowered in regard of the primary outcome because of their small sample sizes. Some algorithms used in the studies are very unstable, which means that a slight change in the data will significantly change the layout of the best decision. Furthermore, some algorithms are slow and needed more memory to run, In fact, millions of observations may be needed for AI techniques to perform acceptably [173]. Second, AI-based models are not widely used in experimental and clinical settings on real datasets. The experimental results on some (small, intermediate and big) machine learning datasets can show the efficiency of the proposed methods, in terms of space, speed, and accuracy [174].
Experimental tests or prospective clinical trials are urgently needed to better highlight the differences between the investigated studies and validate the findings discussed in the present study. Considering the use of different techniques and algorithms in the published studies, it would be meaningful to design a review comparing each technique with others in order to obtain an accurate estimate of the effectiveness of the techniques and establish the potential superiority of the respective methods. According to several studies, the cost-effectiveness of the automated systems is limited, because they are not suitable for use in poorly and moderately developed nations [175]. Some researchers are still working to improve the use of artificial intelligence in cervical cytology. Since a reliable prediction of the clinical outcome would serve as a guide for treatment and the prediction of cervical cancer is most challenging [176], it would be appropriate to specifically address the role of AI in predicting cervical cancer outcomes.
5. Conclusions
Our systematic review highlights the acceptable performance of AI systems in the prediction, screening or detection of cervical cancer and pre-cancerous lesions. AI could aid clinicians in making decisions, reducing their workload as well as the likelihood of misdiagnoses. Indeed, AI interpretation of cervical smears or images could serve as an aid when combined with human evaluation. Further studies on prediction and detection are needed for making appropriate decisions about the treatment of cervical cancer. Eventually, this will help to devise programs for the eradication of cervical cancer on a worldwide basis. However, further work will be needed to make AI feasible, reliable, and less expensive for clinical use. The development of novel techniques and algorithms to reduce the impact of data scarcity in the evaluation and prediction of clinical outcomes, as well as the independent validation of machine learning algorithms, may be included in future studies.
Author Contributions
Conceptualization, L.A. and I.A.; methodology, L.A., A.M., H.S., I.A., data curation, L.A., A.M., S.K.G., M.M.G., I.A., writing-original draft preparation, L.A., A.M., H.S., S.K.G., M.M.G., I.A., writing—review and editing: L.A., A.S.L., V.G., V.C., A.R., Z.M., I.A., supervision. I.A. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The datasets analyzed for the current study are available from the corresponding author on reasonable request.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Sung, H.; Ferlay, J.; Siegel, R.L.; Laversanne, M.; Soerjomataram, I.; Jemal, A.; Bray, F. Global Cancer Statistics 2020: GLOBOCAN Estimates of Incidence and Mortality Worldwide for 36 Cancers in 185 Countries. CA Cancer J. Clin. 2021, 71, 209–249. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bray, F.; Ferlay, J.; Soerjomataram, I.; Siegel, R.L.; Torre, L.A.; Jemal, A. Global cancer statistics 2018: GLOBOCAN estimates of incidence and mortality worldwide for 36 cancers in 185 countries. CA Cancer J. Clin. 2018, 68, 394–424. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ferlay, J.; Ervik, M.; Lam, F.; Colombet, M.; Mery, L.; Piñeros, M.; Znaor, A.; Soerjomataram, I.; Bray, F. Global Cancer Observatory: Cancer Today; International Agency for Research on Cancer: Lyon, France, 2018; Volume 3. [Google Scholar]
- Takiar, R.; Nadayil, D.; Nandakumar, A. Projections of number of cancer cases in India (2010-2020) by cancer groups. Asian Pac. J. Cancer Prev. 2010, 11, 1045–1049. [Google Scholar]
- Salehiniya, H.; Momenimovahed, Z.; Allahqoli, L.; Momenimovahed, S.; Alkatout, I. Factors related to cervical cancer screening among Asian women. Eur. Rev. Med. Pharmacol. Sci. 2021, 25, 6109–6122. [Google Scholar]
- Bogani, G.; Sopracordevole, F.; Di Donato, V.; Ciavattini, A.; Ghelardi, A.; Lopez, S.; Simoncini, T.; Plotti, F.; Casarin, J.; Serati, M.; et al. High-risk HPV-positive and -negative high-grade cervical dysplasia: Analysis of 5-year outcomes. Gynecol. Oncol. 2021, 161, 173–178. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Canfell, K. Towards the global elimination of cervical cancer. Papillomavirus Res. 2019, 8, 100170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karimi-Zarchi, M.; Allahqoli, L.; Nehmati, A.; Kashi, A.M.; Taghipour-Zahir, S.; Alkatout, I. Can the prophylactic quadrivalent HPV vaccine be used as a therapeutic agent in women with CIN? A randomized trial. BMC Public Health 2020, 20, 274. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khan, M.J.; Werner, C.L.; Darragh, T.M.; Guido, R.S.; Mathews, C.; Moscicki, A.-B.; Mitchell, M.M.; Schiffman, M.; Wentzensen, N.; Massad, L.S.; et al. ASCCP Colposcopy Standards: Role of Colposcopy, Benefits, Potential Harms, and Terminology for Colposcopic Practice. J. Low. Genit. Tract Dis. 2017, 21, 223–229. [Google Scholar] [CrossRef] [Scilit]
- Smith, R.A.; Andrews, K.S.; Brooks, D.; Fedewa, S.A.; Manassaram-Baptiste, D.; Saslow, D.; Brawley, O.W.; Wender, R.C. Cancer screening in the United States, 2017: A review of current American Cancer Society guidelines and current issues in cancer screening. CA A Cancer J. Clin. 2017, 67, 100–121. [Google Scholar] [CrossRef] [Scilit]
- Valenti, G.; Vitale, S.G.; Tropea, A.; Biondi, A.; Laganà, A.S. Tumor markers of uterine cervical cancer: A new scenario to guide surgical practice? Updates Surg. 2017, 69, 441–449. [Google Scholar] [CrossRef] [Scilit]
- van den Helder, R.; Steenbergen, R.D.; van Splunter, A.P.; Mom, C.H.; Tjiong, M.Y.; Martin, I.; Rosier-van Dunné, F.M.; van der Avoort, I.A.; Bleeker, M.C.; van Trommel, N.E. HPV and DNA Methylation Testing in Urine for Cervical Intraepithelial Neoplasia and Cervical Cancer Detection. Clin. Cancer Res. 2022, 28, 2061–2068. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- John, J.H.; Halder, A.; Purwar, S.; Pushpalatha, K.; Gupta, P.; Dubey, P. Study to determine efficacy of Urinary HPV 16 &18 detection in predicting premalignant and malignant lesions of Uterine Cervix. Int. J. Gynecol. Obstet. 2022. [Google Scholar] [CrossRef] [Scilit]
- Sravani, A.B.; Ghate, V.; Lewis, S. Human papillomavirus infection, cervical cancer and the less explored role of trace elements. Biol. Trace Element Res. 2022, 1–25. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- WHO; IARC. Prevention of Cervical Cancer through Screening Using Visual Inspection with Acetic Acid (VIA) and Treatment with Cryotherapy. A Demonstration Project in Six African Countries: Malawi, Madagascar, Nigeria, Uganda, the United Republic of Tanzania, and Zambia. 2012; pp. 1–40.
- Hou, X.; Shen, G.; Zhou, L.; Li, Y.; Wang, T.; Ma, X. Artificial Intelligence in Cervical Cancer Screening and Diagnosis. Front. Oncol. 2022, 12, 851367. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Catarino, R.; Schäfer, S.; Vassilakos, P.; Petignat, P.; Arbyn, M. Accuracy of combinations of visual inspection using acetic acid or lugol iodine to detect cervical precancer: A meta-analysis. BJOG: Int. J. Obstet. Gynaecol. 2017, 125, 545–553. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meybodi, N.F.; Karimi-Zarchi, M.; Allahqoli, L.; Sekhavat, L.; Gitas, G.; Rahmani, A.; Fallahi, A.; Hassanlouei, B.; Alkatout, I. Accuracy of the Triple Test Versus Colposcopy for the Diagnosis of Premalignant and Malignant Cervical Lesions. Asian Pac. J. Cancer Prev. APJCP 2020, 21, 3501–3507. [Google Scholar] [CrossRef] [Scilit]
- Nazari, Z.; Torabizadeh, G.; Khalilian, A.; Ghadami, S.; Karimi-Zarchi, M.; Allahqoli, L.; Gharacheh, M.; Salehiniya, H.; Alkatout, I. Is cryotherapy effective in all women with low-grade cervical intraepithelial neoplasia? Eur. Rev. Med. Pharmacol. Sci. 2021, 25, 4211–4218. [Google Scholar]
- D’Oria, O.; Corrado, G.; Laganà, A.S.; Chiantera, V.; Vizza, E.; Giannini, A. New Advances in Cervical Cancer: From Bench to Bedside. Int. J. Environ. Res. Public Health 2022, 19, 7094. [Google Scholar] [CrossRef] [Scilit]
- Bao, H.; Zhang, L.; Wang, L.; Zhang, M.; Zhao, Z.; Fang, L.; Cong, S.; Zhou, M.; Wang, L. Significant variations in the cervical cancer screening rate in China by individual-level and geographical measures of socioeconomic status: A multilevel model analysis of a nationally representative survey dataset. Cancer Med. 2018, 7, 2089–2100. [Google Scholar] [CrossRef] [Scilit]
- Bedell, S.L.; Goldstein, L.S.; Goldstein, A.R.; Goldstein, A.T. Cervical Cancer Screening: Past, Present, and Future. Sex. Med. Rev. 2020, 8, 28–37. [Google Scholar] [CrossRef] [Scilit]
- Pollack, A.E.; Tsu, V.D. Preventing cervical cancer in low-resource settings: Building a case for the possible. Int. J. Gynaecol. Obstet. Off. Organ Int. Fed. Gynaecol. Obstet. 2005, 89 (Suppl. S2), S1–S3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- 24. Wang, A.C.; Wang, L.Q.; Li, J.; Li, M.X.; Tu, L.L.; Zhang, Y.X.; Liu, A.J. Artificial intelligence aided measurement of cervical squamous epithelial thickness and its correlation with cervical precancerous lesions. Zhonghua Bing Li Xue Za Zhi Chin. J. Pathol. 2021, 50, 339-43. [Google Scholar]
- Esteva, A.; Kuprel, B.; Novoa, R.A.; Ko, J.; Swetter, S.M.; Blau, H.M.; Thrun, S. Dermatologist-level classification of skin cancer with deep neural networks. Nature 2017, 542, 115–118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bi, W.L.; Hosny, A.; Schabath, M.B.; Giger, M.L.; Birkbak, N.; Mehrtash, A.; Allison, T.; Arnaout, O.; Abbosh, C.; Dunn, I.F.; et al. Artificial intelligence in cancer imaging: Clinical challenges and applications. CA A Cancer J. Clin. 2019, 69, 127–157. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schmidt-Erfurth, U.; Sadeghipour, A.; Gerendas, B.S.; Waldstein, S.M.; Bogunović, H. Artificial intelligence in retina. Prog. Retin. Eye Res. 2018, 67, 1–29. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akazawa, M.; Hashimoto, K. Artificial intelligence in gynecologic cancers: Current status and future challenges – A systematic review. Artif. Intell. Med. 2021, 120, 102164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shanthi, P.; Hareesha, K.; Kudva, R. Automated detection and classification of cervical cancer using pap smear microscopic images: A comprehensive review and future perspectives. Eng. Sci. 2022, 19, 20–41. [Google Scholar]
- Bao, H.; Sun, X.; Zhang, Y.; Pang, B.; Li, H.; Zhou, L.; Wu, F.; Cao, D.; Wang, J.; Turic, B.; et al. The artificial intelligence-assisted cytology diagnostic system in large-scale cervical cancer screening: A population-based cohort study of 0.7 million women. Cancer Med. 2020, 9, 6896–6906. [Google Scholar] [CrossRef] [Scilit]
- Holmström, O.; Linder, N.; Kaingu, H.; Mbuuko, N.; Mbete, J.; Kinyua, F.; Törnquist, S.; Muinde, M.; Krogerus, L.; Lundin, M.; et al. Point-of-Care Digital Cytology With Artificial Intelligence for Cervical Cancer Screening in a Resource-Limited Setting. JAMA Netw. Open 2021, 4, e211740. [Google Scholar] [CrossRef] [Scilit]
- Moher, D.; Shamseer, L.; Clarke, M.; Ghersi, D.; Liberati, A.; Petticrew, M.; Shekelle, P.; Stewart, L.A. Preferred reporting items for systematic review and meta-analysis protocols (prisma-p) 2015 statement. Syst. Rev. 2015, 4, 1. [Google Scholar] [CrossRef]
- Jenny, J.; Isenegger, I.; Boon, M.E.; Husain, O.N. Consistency of a Double PAPNET Scan of Cervical Smears. Acta Cytol. 1997, 41, 82–87. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Michelow, P.M.; Hlongwane, F.; Leiman, G. Simulation of Primary Cervical Cancer Screening by the PAPNET System in an Unscreened, High-Risk Community. Acta Cytol. 1997, 41, 88–92. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mango, L.J.; Valente, P.T. Neural Network–Assisted Analysis and Microscopic Rescreening in Presumed Negative Cervical Cytologic Smears. Acta Cytol. 1998, 42, 227–232. [Google Scholar] [CrossRef] [Scilit]
- Sherman, M.E.; Schiffman, M.; Herrero, R.; Kelly, D.; Bratti, C.; Mango, L.J.; Alfaro, M.; Hutchinson, M.L.; Mena, F.; Hildesheim, A.; et al. Performance of a semiautomated Papanicolaou smear screening system: Results of a population-based study conducted in Guanacaste, Costa Rica. Cancer 1998, 84, 273–280. [Google Scholar] [CrossRef]
- Nieminen, P.; Hakama, M.; Viikki, M.; Tarkkanen, J.; Anttila, A. Prospective and randomised public-health trial on neural network-assisted screening for cervical cancer in Finland: Results of the first year. Int. J. Cancer 2002, 103, 422–426. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sarwar, A.; Suri, J.; Ali, M.; Sharma, V. Novel benchmark database of digitized and calibrated cervical cells for artificial intelligence based screening of cervical cancer. J. Ambient Intell. Humaniz. Comput. 2016, 7, 593–606. [Google Scholar] [CrossRef] [Scilit]
- Kudva, V.; Prasad, K.; Guruvare, S. Andriod Device-Based Cervical Cancer Screening for Resource-Poor Settings. J. Digit. Imaging 2018, 31, 646–654. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hu, L.; Bell, D.; Antani, S.; Xue, Z.; Yu, K.; Horning, M.P.; Gachuhi, N.; Wilson, B.; Jaiswal, M.S.; Befano, B.; et al. An Observational Study of Deep Learning and Automated Evaluation of Cervical Images for Cancer Screening. JNCI J. Natl. Cancer Inst. 2019, 111, 923–932. [Google Scholar] [CrossRef] [Scilit]
- Sompawong, N.; Mopan, J.; Pooprasert, P.; Himakhun, W.; Suwannarurk, K.; Ngamvirojcharoen, J.; Vachiramon, T.; Tantibundhit, C. Automated Pap Smear Cervical Cancer Screening Using Deep Learning. In Proceedings of the 2019 41st Annual International Conference of the IEEE Engineering in Medicine and Biology Society (EMBC), Berlin, Germany, 23–27 July 2019; pp. 7044–7048. [Google Scholar] [CrossRef] [Scilit]
- Hu, L.; Horning, M.P.; Banik, D.; Ajenifuja, O.K.; Adepiti, C.A.; Yeates, K.; Mtema, Z.; Wilson, B.; Mehanian, C. Deep learning-based image evaluation for cervical precancer screening with a smartphone targeting low resource settings—Engineering approach. In Proceedings of the Annual International Conference of the IEEE Engineering in Medicine and Biology Society IEEE Engineering in Medicine and Biology Society Annual International Conference, Montreal, QC, Canada, 20–24 July 2020; pp. 1944–1999. [Google Scholar]
- Sahoo, G.R.; Dey, R.; Das, N.; Ghosh, N.; Pradhan, A. Two dimensional multifractal detrended fluctuation analysis of low coherence images for diagnosis of cervical pre-cancer. Biomed. Phys. Eng. Express 2020, 6, 025011. [Google Scholar] [CrossRef] [Scilit]
- Saini, S.K.; Bansal, V.; Kaur, R.; Juneja, M. ColpoNet for automated cervical cancer screening using colposcopy images. Mach. Vis. Appl. 2020, 31, 1–15. [Google Scholar] [CrossRef] [Scilit]
- Sanyal, P.; Ganguli, P.; Barui, S. Performance characteristics of an artificial intelligence based on convolutional neural network for screening conventional Papanicolaou-stained cervical smears. Med. J. Armed Forces India 2019, 76, 418–424. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Win, K.P.; Kitjaidure, Y.; Hamamoto, K.; Aung, T.M. Computer-Assisted Screening for Cervical Cancer Using Digital Image Processing of Pap Smear Images. Appl. Sci. 2020, 10, 1800. [Google Scholar] [CrossRef] [Scilit]
- Xiang, Y.; Sun, W.; Pan, C.; Yan, M.; Yin, Z.; Liang, Y. A novel automation-assisted cervical cancer reading method based on convolutional neural network. Biocybern. Biomed. Eng. 2020, 40, 611–623. [Google Scholar] [CrossRef] [Scilit]
- Xue, Z.; Novetsky, A.P.; Einstein, M.H.; Marcus, J.Z.; Befano, B.; Guo, P.; Demarco, M.; Wentzensen, N.; Long, L.R.; Schiffman, M.; et al. A demonstration of automated visual evaluation of cervical images taken with a smartphone camera. Int. J. Cancer 2020, 147, 2416–2423. [Google Scholar] [CrossRef] [Scilit]
- Cheng, S.; Liu, S.; Yu, J.; Rao, G.; Xiao, Y.; Han, W.; Zhu, W.; Lv, X.; Li, N.; Cai, J.; et al. Robust whole slide image analysis for cervical cancer screening using deep learning. Nat. Commun. 2021, 12, 5639. [Google Scholar] [CrossRef] [Scilit]
- Tan, X.; Li, K.; Zhang, J.; Wang, W.; Wu, B.; Wu, J.; Li, X.; Huang, X. Automatic model for cervical cancer screening based on convolutional neural network: A retrospective, multicohort, multicenter study. Cancer Cell Int. 2021, 21, 1–10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tang, H.; Cai, D.; Kong, Y.; Ye, H.; Ma, Z.; Lv, H.; Tuo, L.; Pan, Q.; Liu, Z.; Han, X. Cervical cytology screening facilitated by an artificial intelligence microscope: A preliminary study. Cancer Cytopathol. 2021, 129, 693–700. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, C.W.; Liou, Y.A.; Lin, Y.J.; Chang, C.C.; Chu, P.H.; Lee, Y.C.; Wang, C.H.; Chao, T.K. Artificial intelligence-assisted fast screening cervical high grade squamous intraepithelial lesion and squamous cell carcinoma diagnosis and treatment planning. Sci. Rep. 2021, 11, 16244. [Google Scholar] [CrossRef] [Scilit]
- Wentzensen, N.; Lahrmann, B.; Clarke, M.A.; Kinney, W.; Tokugawa, D.; Poitras, N.; Locke, A.; Bartels, L.; Krauthoff, A.; Walker, J.; et al. Accuracy and Efficiency of Deep-Learning–Based Automation of Dual Stain Cytology in Cervical Cancer Screening. JNCI J. Natl. Cancer Inst. 2020, 113, 72–79. [Google Scholar] [CrossRef] [Scilit]
- Fu, L.; Xia, W.; Shi, W.; Cao, G.-X.; Ruan, Y.-T.; Zhao, X.-Y.; Liu, M.; Niu, S.-M.; Li, F.; Gao, X. Deep learning based cervical screening by the cross-modal integration of colposcopy, cytology, and HPV test. Int. J. Med. Inform. 2022, 159, 104675. [Google Scholar] [CrossRef] [Scilit]
- Kahng, J.; Kim, E.-H.; Kim, H.-G.; Lee, W. Development of a cervical cancer progress prediction tool for human papillomavirus-positive Koreans: A support vector machine-based approach. J. Int. Med. Res. 2015, 43, 518–525. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al-Wesabi, Y.M.S.; Choudhury, A.; Won, D. Classification of cervical cancer dataset. arXiv 2018, arXiv:1812.10383. [Google Scholar]
- Ahmed, M.; Kabir, M.M.J.; Kabir, M.; Hasan, M. Identification of the Risk Factors of Cervical Cancer Applying Feature Selection Approaches. In Proceedings of the 2019 3rd International Conference on Electrical, Computer & Telecommunication Engineering (ICECTE), Rajshahi, Bangladesh, 26–28 December 2019; pp. 201–204. [Google Scholar] [CrossRef] [Scilit]
- Alam, T.M.; Milhan, M.; Atif, M.; Wahab, A.; Mushtaq, M. Cervical Cancer Prediction through Different Screening Methods using Data Mining. Int. J. Adv. Comput. Sci. Appl. 2019, 10, 388–396. [Google Scholar] [CrossRef] [Scilit]
- Chen, H.; Yang, L.; Li, L.; Li, M.; Chen, Z. An efficient cervical disease diagnosis approach using segmented images and cytology reporting. Cogn. Syst. Res. 2019, 58, 265–277. [Google Scholar] [CrossRef] [Scilit]
- Geetha, R.; Sivasubramanian, S.; Kaliappan, M.; Vimal, S.; Annamalai, S. Cervical Cancer Identification with Synthetic Minority Oversampling Technique and PCA Analysis using Random Forest Classifier. J. Med. Syst. 2019, 43, 1–19. [Google Scholar] [CrossRef] [Scilit]
- Nithya, B.; Ilango, V. Evaluation of machine learning based optimized feature selection approaches and classification methods for cervical cancer prediction. SN Appl. Sci. 2019, 1, 641. [Google Scholar] [CrossRef] [Scilit]
- Alsmariy, R.; Healy, G.; Abdelhafez, H. Predicting cervical cancer using machine learning methods. Int. J. Adv. Comput. Sci. Appl. 2020, 11, 173–184. [Google Scholar] [CrossRef] [Scilit]
- Asadi, F.; Salehnasab, C.; Ajori, L. Supervised Algorithms of Machine Learning for the Prediction of Cervical Cancer. J. Biomed. Phys. Eng. 2020, 10, 513–522. [Google Scholar] [CrossRef] [Scilit]
- Doornewaard, H.; van de Seijp, H.; Woudt, J.M.; van der Graaf, Y.; Tweel, J.G.V.D. Negative Cervical Smears Before CIN 3/Carcinoma. Acta Cytol. 1997, 41, 74–78. [Google Scholar] [CrossRef] [Scilit]
- Giovagnoli, M.R.; Cenci, M.; Olla, S.V.; Vecchione, A. Cervical False Negative Cases Detected by Neural Network–Based Technology. Critical review of cytologic errors. Acta Cytol. 2002, 46, 1105–1109. [Google Scholar] [CrossRef] [Scilit]
- Bao, H.; Bi, H.; Zhang, X.; Zhao, Y.; Dong, Y.; Luo, X.; Zhou, D.; You, Z.; Wu, Y.; Liu, Z.; et al. Artificial intelligence-assisted cytology for detection of cervical intraepithelial neoplasia or invasive cancer: A multicenter, clinical-based, observational study. Gynecol. Oncol. 2020, 159, 171–178. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, H.; Chen, H.; Wang, X.; Wang, Q.; Wang, L.; Heng, P.-A. Dual-path network with synergistic grouping loss and evidence driven risk stratification for whole slide cervical image analysis. Med. Image Anal. 2021, 69, 101955. [Google Scholar] [CrossRef] [Scilit]
- Sheela Shiney, T.S.; Rose, R.J. Deep Auto Encoder Based Extreme Learning System for Automatic Segmentation of Cervical Cells. IETE J. Res. 2021. [Google Scholar] [CrossRef] [Scilit]
- Bai, B.; Du, Y.; Liu, P.; Sun, P.; Li, P.; Lv, Y. Detection of cervical lesion region from colposcopic images based on feature reselection. Biomed. Signal Process. Control 2020, 57, 101785. [Google Scholar] [CrossRef] [Scilit]
- Miyagi, Y.; Takehara, K.; Nagayasu, Y.; Miyake, T. Application of deep learning to the classification of uterine cervical squamous epithelial lesion from colposcopy images combined with HPV types. Oncol. Lett. 2019, 19, 1602–1610. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nikookar, E.; Naderi, E.; Rahnavard, A. Cervical Cancer Prediction by Merging Features of Different Colposcopic Images and Using Ensemble Classifier. J. Med. Signals Sens. 2021, 11, 67–78. [Google Scholar] [PubMed]
- Peng, G.; Dong, H.; Liang, T.; Li, L.; Liu, J. Diagnosis of cervical precancerous lesions based on multimodal feature changes. Comput. Biol. Med. 2021, 130, 104209. [Google Scholar] [CrossRef] [Scilit]
- Viñals, R.; Vassilakos, P.; Rad, M.; Undurraga, M.; Petignat, P.; Thiran, J.-P. Using Dynamic Features for Automatic Cervical Precancer Detection. Diagnostics 2021, 11, 716. [Google Scholar] [CrossRef] [Scilit]
- Meng, Z.; Zhao, Z.; Li, B.; Su, F.; Guo, L. A Cervical Histopathology Dataset for Computer Aided Diagnosis of Precancerous Lesions. IEEE Trans. Med. Imaging 2021, 40, 1531–1541. [Google Scholar] [CrossRef] [Scilit]
- Diniz, D.N.; Vitor, R.F.; Bianchi, A.G.C.; Delabrida, S.; Carneiro, C.M.; Ushizima, D.M.; de Medeiros, F.N.S.; Souza, M.J.F. An ensemble method for nuclei detection of overlapping cervical cells. Expert Syst. Appl. 2021, 185, 115642. [Google Scholar] [CrossRef] [Scilit]
- Kruczkowski, M.; Drabik-Kruczkowska, A.; Marciniak, A.; Tarczewska, M.; Kosowska, M.; Szczerska, M. Predictions of cervical cancer identification by photonic method combined with machine learning. Sci. Rep. 2022, 12, 3762. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elakkiya, R.; Teja, K.S.S.; Deborah, L.J.; Bisogni, C.; Medaglia, C. Imaging based cervical cancer diagnostics using small object detection - generative adversarial networks. Multimed. Tools Appl. 2021, 81, 191–207. [Google Scholar] [CrossRef] [Scilit]
- Dong, Y.; Bai, J.; Zhang, Y.; Shang, G.; Zhao, Y.; Li, S.; Yan, N.; Hao, S.; Zhang, W. Automated Quantitative Cytology Imaging Analysis System in Cervical Cancer Screening in Shanxi Province, China. Cancer Clin. Oncol. 2017, 6, p51. [Google Scholar] [CrossRef] [Scilit]
- Kim, S.; Lee, H.; Lee, S.; Song, J.-Y.; Lee, J.-K.; Lee, N.-W. Role of Artificial Intelligence Interpretation of Colposcopic Images in Cervical Cancer Screening. Healthcare 2022, 10, 468. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ali, M.; Ahmed, K.; Bui, F.M.; Paul, B.K.; Ibrahim, S.M.; Quinn, J.M.; Moni, M.A. Machine learning-based statistical analysis for early stage detection of cervical cancer. Comput. Biol. Med. 2021, 139, 104985. [Google Scholar] [CrossRef] [Scilit]
- Luo, W. Predicting Cervical Cancer Outcomes: Statistics, Images, and Machine Learning. Front. Artif. Intell. 2021, 4. [Google Scholar] [CrossRef] [Scilit]
- Kannel, W.B.; McGee, D.; Gordon, T. A general cardiovascular risk profile: The Framingham study. Am. J. Cardiol. 1976, 38, 46–51. [Google Scholar] [CrossRef] [Scilit]
- Dillak, R.Y.; Manulangga, G.C.; Lalandos, J.L. Early warning system for cervical cancer diagnosis using ridge polynomial neural network and chaos optimization algorithm. J. Theor. Appl. Inf. Technol. 2018, 96, 1989–1998. [Google Scholar]
- Garg, S.K.; Kapil, M. A Cervical Cancer Prediction Model Using REPTree Classifier. J. Comput. Theor. Nanosci. 2019, 16, 4438–4442. [Google Scholar] [CrossRef] [Scilit]
- Kar, S.; Majumder, D.D. A Novel Approach of Mathematical Theory of Shape and Neuro-Fuzzy Based Diagnostic Analysis of Cervical Cancer. Pathol. Oncol. Res. 2019, 25, 777–790. [Google Scholar] [CrossRef] [Scilit]
- Tian, R.; Cui, Z.; He, D.; Tian, X.; Gao, Q.; Ma, X.; Yang, J.; Wu, J.; Das, B.C.; Severinov, K.; et al. Risk stratification of cervical lesions using capture sequencing and machine learning method based on HPV and human integrated genomic profiles. Carcinogenesis 2019, 40, 1220–1228. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hussain, E.; Mahanta, L.B.; Das, C.R.; Talukdar, R.K. A comprehensive study on the multi-class cervical cancer diagnostic prediction on pap smear images using a fusion-based decision from ensemble deep convolutional neural network. Tissue Cell 2020, 65, 101347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ijaz, M.F.; Attique, M.; Son, Y. Data-Driven Cervical Cancer Prediction Model with Outlier Detection and Over-Sampling Methods. Sensors 2020, 20, 2809. [Google Scholar] [CrossRef] [Scilit]
- Weegar, R.; Sundström, K. Using machine learning for predicting cervical cancer from Swedish electronic health records by mining hierarchical representations. PLoS ONE 2020, 15, e0237911. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Asaduzzaman, S.; Ahmed, R.; Rehana, H.; Chakraborty, S.; Islam, S.; Bhuiyan, T. Machine learning to reveal an astute risk predictive framework for Gynecologic Cancer and its impact on women psychology: Bangladeshi perspective. BMC Bioinform. 2021, 22, 1–17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ilyas, Q.M.; Ahmad, M. An Enhanced Ensemble Diagnosis of Cervical Cancer: A Pursuit of Machine Intelligence Towards Sustainable Health. IEEE Access 2021, 9, 12374–12388. [Google Scholar] [CrossRef] [Scilit]
- Jahan, S.; Islam, M.D.S.; Islam, L.; Rashme, T.Y.; Prova, A.A.; Paul, B.K.; Mosharof, M.K. Automated invasive cervical cancer disease detection at early stage through suitable machine learning model. SN Appl. Sci. 2021, 3, 1–17. [Google Scholar] [CrossRef] [Scilit]
- Khan, I.U.; Aslam, N.; Alshehri, R.; Alzahrani, S.; Alghamdi, M.; Almalki, A.; Balabeed, M. Cervical Cancer Diagnosis Model Using Extreme Gradient Boosting and Bioinspired Firefly Optimization. Sci. Program. 2021, 2021, 1–10. [Google Scholar] [CrossRef] [Scilit]
- Mehmood, M.; Rizwan, M.; Ml, M.G.; Abbas, S. Machine Learning Assisted Cervical Cancer Detection. Front. Public Health 2021, 9, 2024. [Google Scholar] [CrossRef] [Scilit]
- Mudawi, N.A.; Alazeb, A. A Model for Predicting Cervical Cancer Using Machine Learning Algorithms. Sensors 2022, 22, 4132. [Google Scholar] [CrossRef] [Scilit]
- Suman, S.K.; Hooda, N. Predicting risk of Cervical Cancer: A case study of machine learning. J. Stat. Manag. Syst. 2019, 22, 689–696. [Google Scholar] [CrossRef] [Scilit]
- Maxim, L.D.; Niebo, R.; Utell, M.J. Screening tests: A review with examples. Inhal. Toxicol. 2014, 26, 811–828. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Obuchowski, N.A.; Graham, R.J.; Baker, M.E.; Powell, K.A. Ten criteria for effective screening: Their application to multislice CT screening for pulmonary and colorectal cancers. Am. J. Roentgenol. (1976) 2001, 176, 1357–1362. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhan, A.; Sharma, D.; Mishra, S. (Eds.) Computer based automatic segmentation of pap smear cells for cervical cancer detection. In Proceedings of the 2018 5th International Conference on Signal Processing and Integrated Networks (SPIN), Delhi, India, 22–23 February 2018. [Google Scholar]
- Yang, L.; Tuzel, O.; Chen, W.; Meer, P.; Salaru, G.; Goodell, L.A.; Foran, D.J. PathMiner: A Web-based tool for computer-assisted diagnostics in pathology. IEEE Trans. Inf. Technol. Biomed. A Publ. IEEE Eng. Med. Biol. Soc. 2009, 13, 291–299. [Google Scholar] [CrossRef]
- Sherman, M.E.; Mango, L.J.; Kelly, D.; Paull, G.; Ludin, V.; Copeland, C.; Solomon, D.; Schiffman, M.H. PAPNET analysis of reportedly negative smears preceding the diagnosis of a high-grade squamous intraepithelial lesion or carcinoma. Mod. Pathol. 1994, 7, 578–581. [Google Scholar]
- Kok, M.R.; Boon, M.E. Consequences of neural network technology for cervical screening: Increase in diagnostic consistency and positive scores. Cancer 1996, 78, 112–117. [Google Scholar] [CrossRef] [Scilit]
- Cenci, M.; Nagar, C.; Giovagnoli, M.R.; Vecchione, A. The PAPNET system for quality control of cervical smears: Validation and limits. Anticancer Res. 1998, 17, 4731–4734. [Google Scholar]
- Kemp, R.A.; MacAulay, C.; Garner, D.; Palcic, B. Detection of Malignancy Associated Changes in Cervical Cell Nuclei Using Feed-Forward Neural Networks. Anal. Cell. Pathol. 1997, 14, 31–40. [Google Scholar] [CrossRef] [Scilit]
- Koss, L.G.; Sherman, M.E.; Cohen, M.B.; Anes, A.R.; Darragh, T.M.; Lemos, L.B.; McClellan, B.J.; Rosenthal, D.L.; Keyhani-Rofagha, S.; Schreiber, K.; et al. Significant reduction in the rate of false-negative cervical smears with neural network-based technology (PAPNET testing system). Hum. Pathol. 1997, 28, 1196–1203. [Google Scholar] [CrossRef] [Scilit]
- Keenan, S.; Diamond, J.; McCluggage, W.G.; Bharucha, H.; Thompson, D.; Bartels, P.H.; Hamilton, P.W. An automated machine vision system for the histological grading of cervical intraepithelial neoplasia (CIN). J. Pathol. 2000, 192, 351–362. [Google Scholar] [CrossRef] [Scilit]
- Dickman, E.D.; Doll, T.J.; Chiu, C.K.; Ferris, D.G. Identification of cervical neoplasia using a simulation of human vision. J. Low. Genit. Tract Dis. 2001, 5, 144–152. [Google Scholar] [PubMed]
- Parker, M.F.; Mooradian, G.C.; Okimoto, G.S.; O’Connor, D.M.; Miyazawa, K.; Saggese, S.J. Initial neural net construction for the detection of cervical intraepithelial neoplasia by fluorescence imaging. Am. J. Obstet. Gynecol. 2002, 187, 398–402. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boon, M.E.; Ouwerkerk-Noordam, E.; Suurmeijer, A.; Kok, L.P. Diagnostic Parameters in Liquid-Based Cervical Cytology Using a Coagulant Suspension Fixative. Acta Cytol. 2005, 49, 513–519. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dounias, G.; Bjerregaard, B.; Jantzen, J.; Tsakonas, A.; Ampazis, N.; Panagi, G.; Panourgias, E. Automated identification of cancerous smears using various competitive intelligent techniques. Oncol. Rep. 2006, 15, 1001–1006. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mat-Isa, N.A.; Mashor, M.Y.; Othman, N.H. An automated cervical pre-cancerous diagnostic system. Artif. Intell. Med. 2008, 42, 1–11. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Crookes, D.; Eldin, O.S.; Wang, S.; Hamilton, P.; Diamond, J. Assisted Diagnosis of Cervical Intraepithelial Neoplasia (CIN). IEEE J. Sel. Top. Signal Process. 2009, 3, 112–121. [Google Scholar] [CrossRef] [Scilit]
- Al-Batah, M.S.; Isa, N.A.M.; Klaib, M.F.; Al-Betar, M.A. Multiple Adaptive Neuro-Fuzzy Inference System with Automatic Features Extraction Algorithm for Cervical Cancer Recognition. Comput. Math. Methods Med. 2014, 2014, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Sokouti, B.; Haghipour, S.; Tabrizi, A.D. A framework for diagnosing cervical cancer disease based on feedforward MLP neural network and ThinPrep histopathological cell image features. Neural Comput. Appl. 2012, 24, 221–232. [Google Scholar] [CrossRef] [Scilit]
- Kim, S.H.; Oh, H.Y.; Kim, D.W. A study on development of automation diagnosis of liquid based cytology. Sains Malays. 2015, 44, 1729–1738. [Google Scholar]
- Kyrgiou, M.; Pouliakis, A.; Panayiotides, J.G.; Margari, N.; Bountris, P.; Valasoulis, G.; Paraskevaidi, M.; Bilirakis, E.; Nasioutziki, M.; Loufopoulos, A.; et al. Personalised management of women with cervical abnormalities using a clinical decision support scoring system. Gynecol. Oncol. 2016, 141, 29–35. [Google Scholar] [CrossRef] [Scilit]
- Hyeon, J.; Choi, H.-J.; Lee, B.D.; Lee, K.N. Diagnosing cervical cell images using pre-trained convolutional neural network as feature extractor. In Proceedings of the 2017 IEEE International Conference on Big Data and Smart Computing (BigComp) 2017, Jeju Island, Korea, 13–16 February 2017; pp. 390–393. [Google Scholar] [CrossRef] [Scilit]
- Abdoh, S.F.; Rizka, M.A.; Maghraby, F.A. Cervical Cancer Diagnosis Using Random Forest Classifier With SMOTE and Feature Reduction Techniques. IEEE Access 2018, 6, 59475–59485. [Google Scholar] [CrossRef] [Scilit]
- Arya, M.; Mittal, N.; Singh, G. Texture-based feature extraction of smear images for the detection of cervical cancer. IET Comput. Vis. 2018, 12, 1049–1059. [Google Scholar] [CrossRef] [Scilit]
- Aljakouch, K.; Hilal, Z.; Daho, I.; Schuler, M.; Krauß, S.D.; Yosef, H.K.; Dierks, J.; Mosig, A.; Gerwert, K.; El-Mashtoly, S.F. Fast and Noninvasive Diagnosis of Cervical Cancer by Coherent Anti-Stokes Raman Scattering. Anal. Chem. 2019, 91, 13900–13906. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhuvaneshwari, K.V.; Poornima, B. Cervical cancer cell identification & detection using fuzzy C mean and K nearest neighbor techniques. Int. J. Innov. Technol. Explor. Eng. 2019, 8, 1080–1084. [Google Scholar]
- Lasyk, L.; Barbasz, J.; Żuk, P.; Prusaczyk, A.; Włodarczyk, T.; Prokurat, E.; Olszewski, W.; Bidziński, M.; Baszuk, P.; Gronwald, J. An evaluation of the construction of the device along with the software for digital archiving, sending the data, and supporting the diagnosis of cervical cancer. Contemp. Oncol./Współczesna Onkol. 2019, 23, 171–177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ma, Y.; Xu, T.; Huang, X.; Wang, X.; Li, C.; Jerwick, J.; Ning, Y.; Zeng, X.; Wang, B.; Wang, Y.; et al. Computer-Aided Diagnosis of Label-Free 3-D Optical Coherence Microscopy Images of Human Cervical Tissue. IEEE Trans. Biomed. Eng. 2019, 66, 2447–2456. [Google Scholar] [CrossRef] [Scilit]
- Moscon, L.M.; Macedo, N.D.; Nunes, C.S.M.; Boasquevisque, P.C.R.; de Andrade, T.U.; Endringer, D.C.; Lenz, D. Automated detection of anomalies in cervix cells using image analysis and machine learning. Comp. Clin. Pathol. 2018, 28, 177–182. [Google Scholar] [CrossRef] [Scilit]
- Wang, H.; Jiang, C.; Bao, K.; Xu, C. Recognition and Clinical Diagnosis of Cervical Cancer Cells Based on our Improved Lightweight Deep Network for Pathological Image. J. Med. Syst. 2019, 43, 1–9. [Google Scholar] [CrossRef] [Scilit]
- Zhang, J.; He, J.; Chen, T.; Liu, Z.; Chen, D. Abnormal region detection in cervical smear images based on fully convolutional network. IET Image Process. 2019, 13, 583–590. [Google Scholar] [CrossRef] [Scilit]
- Konstandinou, C.; Kostopoulos, S.; Glotsos, D.; Pappa, D.; Ravazoula, P.; Michail, G.; Kalatzis, I.; Asvestas, P.; Lavdas, E.; Cavouras, D.; et al. GPU-enabled design of an adaptable pattern recognition system for discriminating squamous intraepithelial lesions of the cervix. Biomed. Eng./Biomed. Tech. 2019, 65, 315–325. [Google Scholar] [CrossRef] [Scilit]
- Ma, D.; Liu, J.; Li, J.; Zhou, Y. Cervical cancer detection in cervical smear images using deep pyramid inference with refinement and spatial-aware booster. IET Image Process. 2020, 14, 4717–4725. [Google Scholar] [CrossRef] [Scilit]
- Xia, M.; Zhang, G.; Mu, C.; Guan, B.; Wang, M. Cervical Cancer Cell Detection Based on Deep Convolutional Neural Network. In Proceedings of the 2020 39th Chinese Control Conference (CCC), Shenyang, China, 27–29 July 2020. [Google Scholar] [CrossRef] [Scilit]
- Cao, L.; Yang, J.; Rong, Z.; Li, L.; Xia, B.; You, C.; Lou, G.; Jiang, L.; Du, C.; Meng, H.; et al. A novel attention-guided convolutional network for the detection of abnormal cervical cells in cervical cancer screening. Med. Image Anal. 2021, 73, 102197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jia, D.; Zhou, J.; Zhang, C. Detection of cervical cells based on improved SSD network. Multimed. Tools Appl. 2021, 81, 13371–13387. [Google Scholar] [CrossRef] [Scilit]
- Li, X.; Xu, Z.; Shen, X.; Zhou, Y.; Xiao, B.; Li, T.-Q. Detection of Cervical Cancer Cells in Whole Slide Images Using Deformable and Global Context Aware Faster RCNN-FPN. Curr. Oncol. 2021, 28, 3585–3601. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liang, Y.; Pan, C.; Sun, W.; Liu, Q.; Du, Y. Global context-aware cervical cell detection with soft scale anchor matching. Comput. Methods Programs Biomed. 2021, 204, 106061. [Google Scholar] [CrossRef] [Scilit]
- Liang, Y.; Tang, Z.; Yan, M.; Chen, J.; Liu, Q.; Xiang, Y. Comparison detector for cervical cell/clumps detection in the limited data scenario. Neurocomputing 2021, 437, 195–205. [Google Scholar] [CrossRef] [Scilit]
- Pal, A.; Xue, Z.; Desai, K.; Banjo, A.A.; Adepiti, C.A.; Long, L.R.; Schiffman, M.; Antani, S. Deep multiple-instance learning for abnormal cell detection in cervical histopathology images. Comput. Biol. Med. 2021, 138, 104890. [Google Scholar] [CrossRef] [Scilit]
- Jia, D.; He, Z.; Zhang, C.; Yin, W.; Wu, N.; Li, Z. Detection of cervical cancer cells in complex situation based on improved YOLOv3 network. Multimedia Tools Appl. 2022, 81, 8939–8961. [Google Scholar] [CrossRef] [Scilit]
- Asiedu, M.N.; Simhal, A.; Chaudhary, U.; Mueller, J.L.; Lam, C.T.; Schmitt, J.W.; Venegas, G.; Sapiro, G.; Ramanujam, N. Development of Algorithms for Automated Detection of Cervical Pre-Cancers With a Low-Cost, Point-of-Care, Pocket Colposcope. IEEE Trans. Biomed. Eng. 2018, 66, 2306–2318. [Google Scholar] [CrossRef] [Scilit]
- Zimmer-Stelmach, A.; Zak, J.; Pawlosek, A.; Rosner-Tenerowicz, A.; Budny-Winska, J.; Pomorski, M.; Fuchs, T.; Zimmer, M. The Application of Artificial Intelligence-Assisted Colposcopy in a Tertiary Care Hospital within a Cervical Pathology Diagnostic Unit. Diagnostics 2022, 12, 106. [Google Scholar] [CrossRef] [Scilit]
- Park, S.Y.; Follen, M.; Milbourne, A.; Rhodes, H.; Malpica, A.; MacKinnon, N.B.; MacAulay, C.; Markey, M.K.; Richards-Kortum, R.R. Automated image analysis of digital colposcopy for the detection of cervical neoplasia. J. Biomed. Opt. 2008, 13, 014029. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, W.; Venkataraman, S.; Gustafsson, U.; Oyama, J.C.; Ferris, D.G.; Lieberman, R. Using acetowhite opacity index for detecting cervical intraepithelial neoplasia. J. Biomed. Opt. 2009, 14, 014020. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, S.Y.; Sargent, D.; Lieberman, R.; Gustafsson, U. Domain-Specific Image Analysis for Cervical Neoplasia Detection Based on Conditional Random Fields. IEEE Trans. Med. Imaging 2011, 30, 867–878. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bai, B.; Liu, P.-Z.; Du, Y.-Z.; Luo, Y.-M. Automatic segmentation of cervical region in colposcopic images using K-means. Australas. Phys. Eng. Sci. Med. 2018, 41, 1077–1085. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ramapraba, P.S.; Chitra, M.P.; Prem Kumar, M. Effective lesion detection of colposcopic images using active contour method. Biomed. Res. 2017, 28, S255-S64. [Google Scholar]
- Cho, B.-J.; Choi, Y.J.; Lee, M.-J.; Kim, J.H.; Son, G.-H.; Park, S.-H.; Kim, H.-B.; Joo, Y.-J.; Cho, H.-Y.; Kyung, M.S.; et al. Classification of cervical neoplasms on colposcopic photography using deep learning. Sci. Rep. 2020, 10, 1–10. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Chen, J.; Xue, P.; Tang, C.; Chang, J.; Chu, C.; Ma, K.; Li, Q.; Zheng, Y.; Qiao, Y. Computer-Aided Cervical Cancer Diagnosis Using Time-Lapsed Colposcopic Images. IEEE Trans. Med. Imaging 2020, 39, 3403–3415. [Google Scholar] [CrossRef] [Scilit]
- Luo, Y.-M.; Zhang, T.; Li, P.; Liu, P.-Z.; Sun, P.; Dong, B.; Ruan, G. MDFI: Multi-CNN Decision Feature Integration for Diagnosis of Cervical Precancerous Lesions. IEEE Access 2020, 8, 29616–29626. [Google Scholar] [CrossRef] [Scilit]
- Xue, P.; Tang, C.; Li, Q.; Li, Y.; Shen, Y.; Zhao, Y.; Chen, J.; Wu, J.; Li, L.; Wang, W.; et al. Development and validation of an artificial intelligence system for grading colposcopic impressions and guiding biopsies. BMC Med. 2020, 18, 1–10. [Google Scholar] [CrossRef] [Scilit]
- Yuan, C.; Yao, Y.; Cheng, B.; Cheng, Y.; Li, Y.; Li, Y.; Liu, X.; Cheng, X.; Xie, X.; Wu, J.; et al. The application of deep learning based diagnostic system to cervical squamous intraepithelial lesions recognition in colposcopy images. Sci. Rep. 2020, 10, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Yue, Z.; Ding, S.; Zhao, W.; Wang, H.; Ma, J.; Zhang, Y.; Zhang, Y. Automatic CIN Grades Prediction of Sequential Cervigram Image Using LSTM With Multistate CNN Features. IEEE J. Biomed. Health Inform. 2019, 24, 844–854. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adweb, K.M.A.; Cavus, N.; Sekeroglu, B. Cervical Cancer Diagnosis Using Very Deep Networks Over Different Activation Functions. IEEE Access 2021, 9, 46612–46625. [Google Scholar] [CrossRef] [Scilit]
- Chandran, V.; Sumithra, M.G.; Karthick, A.; George, T.; Deivakani, M.; Elakkiya, B.; Subramaniam, U.; Manoharan, S. Diagnosis of Cervical Cancer based on Ensemble Deep Learning Network using Colposcopy Images. BioMed Res. Int. 2021, 2021, 1–15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hunt, B.; Fregnani, J.H.T.G.; Brenes, D.; Schwarz, R.A.; Salcedo, M.P.; Possati-Resende, J.C.; Antoniazzi, M.; Fonseca, B.O.; Santana, I.V.V.; Matsushita, G.M.; et al. Cervical lesion assessment using real-time microendoscopy image analysis in Brazil: The CLARA study. Int. J. Cancer 2021, 149, 431–441. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Y.; Liu, Z.-H.; Xue, P.; Chen, J.; Ma, K.; Qian, T.; Zheng, Y.; Qiao, Y.-L. GRAND: A large-scale dataset and benchmark for cervical intraepithelial Neoplasia grading with fine-grained lesion description. Med. Image Anal. 2021, 70, 102006. [Google Scholar] [CrossRef] [Scilit]
- Yan, L.; Li, S.; Guo, Y.; Ren, P.; Song, H.; Yang, J.; Shen, X. Multi-state colposcopy image fusion for cervical precancerous lesion diagnosis using BF-CNN. Biomed. Signal Process. Control 2021, 68, 102700. [Google Scholar] [CrossRef] [Scilit]
- Yue, Z.; Ding, S.; Li, X.; Yang, S.; Zhang, Y. Automatic Acetowhite Lesion Segmentation via Specular Reflection Removal and Deep Attention Network. IEEE J. Biomed. Health Inform. 2021, 25, 3529–3540. [Google Scholar] [CrossRef] [Scilit]
- Ito, Y.; Miyoshi, A.; Ueda, Y.; Tanaka, Y.; Nakae, R.; Morimoto, A.; Shiomi, M.; Enomoto, T.; Sekine, M.; Sasagawa, T.; et al. An artificial intelligence-assisted diagnostic system improves the accuracy of image diagnosis of uterine cervical lesions. Mol. Clin. Oncol. 2021, 16, 1–6. [Google Scholar] [CrossRef] [Scilit]
- Bargahi, N.; Ghasemali, S.; Jahandar-Lashaki, S.; Nazari, A. Recent advances for cancer detection and treatment by microfluidic technology, review and update. Biol. Proced. Online 2022, 24, 1–20. [Google Scholar] [CrossRef] [Scilit]
- Li, Y.; Yi, J.; Chen, H.; Peng, D. Theory and application of artificial intelligence in financial industry. Data Sci. Financ. Econ. 2021, 1, 96–116. [Google Scholar] [CrossRef] [Scilit]
- Ahmad, Z.; Rahim, S.; Zubair, M.; Abdul-Ghafar, J. Artificial intelligence (AI) in medicine, current applications and future role with special emphasis on its potential and promise in pathology: Present and future impact, obstacles including costs and acceptance among pathologists, practical and philosophical considerations. A comprehensive review. Diagn. Pathol. 2021, 16, 1–16. [Google Scholar] [CrossRef] [Scilit]
- Tarawneh, A.S.; Hassanat, A.B.; Celik, C.; Chetverikov, D.; Rahman, M.S.; Verma, C. (Eds.) Deep face image retrieval: A comparative study with dictionary learning. In Proceedings of the 2019 10th International Conference on Information and Communication Systems (ICICS), Irbid, Jordan, 11–13 June 2019. [Google Scholar]
- Topol, E.J. High-performance medicine: The convergence of human and artificial intelligence. Nat. Med. 2019, 25, 44–56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Casarin, J.; Bogani, G.; Papadia, A.; Ditto, A.; Pinelli, C.; Garzon, S.; Donadello, N.; Laganà, A.S.; Cromi, A.; Mueller, M.; et al. Preoperative Conization and Risk of Recurrence in Patients Undergoing Laparoscopic Radical Hysterectomy for Early Stage Cervical Cancer: A Multicenter Study. J. Minim. Invasive Gynecol. 2020, 28, 117–123. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Di Donna, M.C.; Giallombardo, V.; Lo Balbo, G.; Cucinella, G.; Sozzi, G.; Capozzi, V.A.; Abbate, A.; Laganà, A.S.; Garzon, S.; Chiantera, V. Conventional Laparoscopy versus Robotic-Assisted Aortic Lymph-Nodal Staging for Locally Advanced Cervical Cancer: A Systematic Review and Meta-Analysis. J. Clin. Med. 2022, 11, 3332. [Google Scholar] [CrossRef] [Scilit]
- Laganà, A.S.; Garzon, S.; Raffaelli, R.; Ban Frangež, H.; Lukanovič, D.; Franchi, M. Vaginal Stenosis After Cervical Cancer Treatments: Challenges for Reconstructive Surgery. J. Investig. Surg. Off. J. Acad. Surg. Res. 2021, 34, 754–755. [Google Scholar] [CrossRef] [Scilit]
- La Rosa, V.; Laganà, A.; Fanale, D.; Vitale, S. Comment on: Survey of cervical cancer survivors regarding quality of life and sexual function. J. Cancer Res. Ther. 2017, 13, 598–599. [Google Scholar] [CrossRef] [Scilit]
- Schulte-Frohlinde, R.; Georges, D.; Clifford, G.M.; Baussano, I. Predicting Cohort-Specific Cervical Cancer Incidence From Population-Based Surveys of Human Papilloma Virus Prevalence: A Worldwide Study. Am. J. Epidemiol. 2021, 191, 402–412. [Google Scholar] [CrossRef] [Scilit]
- Nsugbe, E. Towards the use of cybernetics for an enhanced cervical cancer care strategy. Intell. Med. 2022. [Google Scholar] [CrossRef] [Scilit]
- Sørbye, S.W.; Suhrke, P.; Revå, B.W.; Berland, J.; Maurseth, R.J.; Al-Shibli, K. Accuracy of cervical cytology: Comparison of diagnoses of 100 Pap smears read by four pathologists at three hospitals in Norway. BMC Clin. Pathol. 2017, 17, 1–6. [Google Scholar] [CrossRef] [Scilit]
- Amorim, J.G.; Cerentini, A.; Macarini, L.A.B.; Matias, A.V.; von Wangenheim, A. Systematic Literature Review of Computer Vision-Aided Cytology; Federal University of Santa Catarina: Florianópolis, Brazil, 2020. [Google Scholar]
- Fan, A.; Wang, C.; Zhang, L.; Yan, Y.; Han, C.; Xue, F. Diagnostic value of the 2011 International Federation for Cervical Pathology and Colposcopy Terminology in predicting cervical lesions. Oncotarget 2018, 9, 9166–9176. [Google Scholar] [CrossRef] [Scilit]
- Mitchell, M.F.; Schottenfeld, D.; Tortolero-Luna, G.; Cantor, S.B.; Richards-Kortum, R. Colposcopy for the diagnosis of squamous intraepithelial lesions: A meta-analysis. Obstet. Gynecol. 1998, 91, 626–631. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wallace, M.B.; Sharma, P.; Bhandari, P.; East, J.; Antonelli, G.; Lorenzetti, R.; Vieth, M.; Speranza, I.; Spadaccini, M.; Desai, M.; et al. Impact of Artificial Intelligence on Miss Rate of Colorectal Neoplasia. Gastroenterology 2022, 163, 295–304.e5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Obermeyer, Z.; Emanuel, E.J. Predicting the Future - Big Data, Machine Learning, and Clinical Medicine. N. Engl. J. Med. 2016, 375, 1216–1219. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hassanat, A.B.A. Furthest-Pair-Based Decision Trees: Experimental Results on Big Data Classification. Information 2018, 9, 284. [Google Scholar] [CrossRef] [Scilit]
- Chankong, T.; Theera-Umpon, N.; Auephanwiriyakul, S. Automatic cervical cell segmentation and classification in Pap smears. Comput. Methods Programs Biomed. 2014, 113, 539–556. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alkatout, I.; Karimi-Zarchi, M.; Allahqoli, L. Gynecological cancers and the global COVID-19 pandemic. J. Turk. Ger. Gynecol. Assoc. 2020, 21, 272–278. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).