


Case presentation
A 76-year-old male patient was admitted to the emergency room for dyspnoea, cyanosis and chest discomfort. Dilated cardiomyopathy was diagnosed many years ago, with permanent atrial fibrillation and a very slow ventricular response necessitating pacemaker implantation in 1993. In 2005, an upgrade to biventricular pacing was performed with improvement in functional status and ejection fraction. Medical treatment included acenocoumarol, spironolactone 12.5 mg per day, enalapril 5 mg twice daily, and furosemide 40 mg per day.
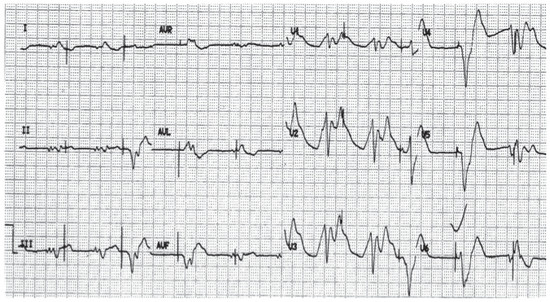
On admission, blood pressure was 90/60 mm Hg, pulse was irregular at a rate of 60 bpm, temperature was 38.1 degrees. Marked orthopnea with cyanosis was present, bilateral rales were present during pulmonary auscultation and peripheral oedema were obvious. A 12-lead resting ECG was performed on admission (Figure 1).
Figure 1.
Questions
- Is the pacemaker functioning?
- How can you describe the rhythm?
- What will you do in the emergency room?
The basic rhythm is impossible to assess but no P waves are present and no fibrillation waves can be seen… even if we know from the history that chronic atrial fibrillation has been present for more than 15 years. The ventricular complexes are broad, extremely broad (QRS width 270 ms), with multiphasic components, fragmentations and without left or right bundle branch block pattern. Major repolarisation abnormalities are also observed in the precordial leads. Stimulation artifacts are present with failure to sense and partial failure to capture with a major delay (latency) between the stimulus artifact and the ventricular depolarisation (complexes 3, 4, 9 and 10).
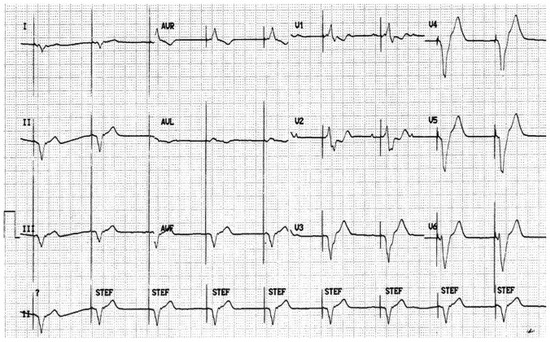
A diagnosis of bronchopneumonia with cardiac failure was rapidly established and the very strange ECG observed on admission was the consequence of severe hyperkaliaemia (7.6 mmol/l). Treatment included oxygen administration, immediate treatment of hyperkaliaemia, diuretics, antibiotics and reprogrammation of the pacemaker for better sensing and optimal capture of both ventricles. Figure 2 shows the ECG recorded two hours later when the potassium serum level was decreased to 5.6 mmol/l. There is 1:1 ventricular capture, latency has decreased, and, though the QRS complex is not narrow (QRS width 200 ms), positive forces are present in lead V1 compatible with biventricular pacing.
Figure 2.
Commentary
ECG modifications related to hyperkaliaemia are known for decades and include tall, peak and symetrical T waves, conduction disturbances (atrioventricular block, bundle branch block, nonspecific intraventricular conduction delays with very broad and funny QRS complexes) and lethal arrhythmias (ventricular tachycardia, ventricular fibrillation, extreme bradycardia, asystole…) [1]. ECG abnormalities may occur when the potassium level is above 5.0 mmol/l, but are essentially observed when the level is above 6.0 mmol/l. Failure to sense and failure to capture may be observed in patients with permanent pacemakers like in the present report [2,3,4].
In conclusion, hyperkaliaemia should be immediately suspected in the presence of a very broad and funny QRS complex, and when pacemaker dysfunction occurs in a previously stable patient.
Funding/potential competing interests
No financial support and no other potential conflict of interest relevant to this article were reported.
References
- Noble, K.; Isles, C. Hyperkaliemia causing profound bradycardia. Heart 2006, 92, 1063. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McVenes, R.; Hansen, N.; Lathinen, S.P.; Stokes, K. The salty dogs: serum sodium and potassium effects on modern pacing electrodes. Pacing Clin Electrophysiol 2007, 30, 4–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barold, S.; Leonelli, F.; Herweg, B. Hyperkaliemia during cardiac pacing. Pacing Clin Electrophysiol 2007, 30, 1–3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kahloon, M.U.; Aslam, A.K.; Aslam, A.F.; Wilbur, S.L.; Vasavada, B.C.; Khan, I.A. Hyperkaliemia induced failure of atrial and ventricular pacemaker capture. Int J Cardiol 2005, 105, 224–226. [Google Scholar] [CrossRef] [Scilit] [PubMed]
© 2012 by the author. Attribution - Non-Commercial - NoDerivatives 4.0.