


Highlights
Public health relevance—How does this work relate to a public health issue?
- Disability-adjusted life years (DALYs) quantify population health loss across diseases and regions, while DALY rates enable meaningful comparisons between populations of different sizes and age structures.
- This study uses these measures to analyse regional disease burden and identify population health priorities in the Grampian region of Scotland.
Public health significance—Why is this work of significance to public health?
- The analysis identifies leading contributors to disease burden (e.g., cancers, ischaemic heart disease, Alzheimer’s disease) and highlights worsening trends in drug use disorders and colorectal cancer.
- The study demonstrates how publicly available surveillance data can be systematically analysed to generate actionable, region-specific insights beyond national averages, including variations by sex, age group, and sub-regions.
Public health implications—What are the key implications or messages for practitioners, policy makers and/or researchers in public health?
- Finding support targeted prevention strategies (e.g., early interventions for drug use disorders from adolescence and colorectal cancer screening from early adulthood), particularly in areas with higher DALY rates, such as Aberdeen City.
- The study provides a reproducible analytical framework to guide resource allocation, research prioritisation, and integrated public health and healthcare planning.
Abstract
Burden of diseases measured as disability-adjusted life years (DALYs) per 100,000 people can be mined from public domain data, when they are made available by population health surveillance systems. This can be analysed to allow insightful comparisons with the national average, and to understand differences in trends between the sexes, age groups, time periods, geographic regions, and sub-regions. In this illustrative case study, we have analysed the Scottish burden of disease database to understand what ailed the population of the Grampian region before the COVID-19 pandemic. We have identified that selected cancers, ischaemic heart disease, Alzheimer’s disease and other dementias are amongst the highest contributors to the burden; that drug use disorders and colorectal cancer are showing worsening trends and require health promotion and disease prevention measures from ages 15 and 25, respectively, especially in Aberdeen City; and that males are more vulnerable to atrial fibrillation and flutter, diabetes mellitus, oesophageal cancer, and self-harm, while females are more vulnerable to cerebrovascular and chronic obstructive pulmonary diseases. We demonstrate the usefulness of our analysis and methodology for the wider health system, allowing targeted medical research investments and coordinated response from public health and health service delivery. We also show the need for up-to-date surveillance data, forecasts, and evidence on the impact of interventions to be made available widely.
1. Introduction
The origins of quality of life and cost-effectiveness analyses in healthcare can be traced back to a study on chronic renal disease published in 1968 [1], leading to quality-adjusted life years (QALYs) being formally defined in 1976 as the output of a utility function [2], c.f. Acknowledgements. This concept gained gradual acceptance over the next three decades for the economic evaluation of healthcare programmes [3], using metrics such as the incremental cost-effectiveness ratio developed at York [4], and the disability-adjusted life year (DALY) introduced in 1994 as a related term with age-weighting and discounting [5,6].
Disability-adjusted life year (DALY), the loss of equivalent of one year of full health, is a time-based measure that allows the burden of different diseases to be compared objectively. It is calculated as the sum of Years of Life Lost (YLL) due to premature mortality and Years Lived with Disability (YLD), i.e., DALY = YLL + YLD [5,6]. While DALYs quantify health loss at the population level, QALYs measure health gain by combining life expectancy with health-related quality of life [3]. In the United Kingdom (UK), QALYs are widely used in economic evaluation and health technology assessment by decision-making bodies such as the National Institute for Health and Care Excellence (NICE) to inform cost-effectiveness and resource allocation within the National Health Service (NHS) [7]. Thus, while QALYs support the evaluation of healthcare interventions, DALYs are particularly useful for identifying population health priorities.
DALY and DALY rate per 100,000 people in a given region can provide valuable insights to health service providers, public health departments, health economists, and policy makers if data are available to compare that region (for example, Grampian in Scotland) with others and the national average—as shown in this communication. Authentic and curated sources of such data in the UK include the Fingertips for England [8], the Scottish Burden of Disease [9], etc.
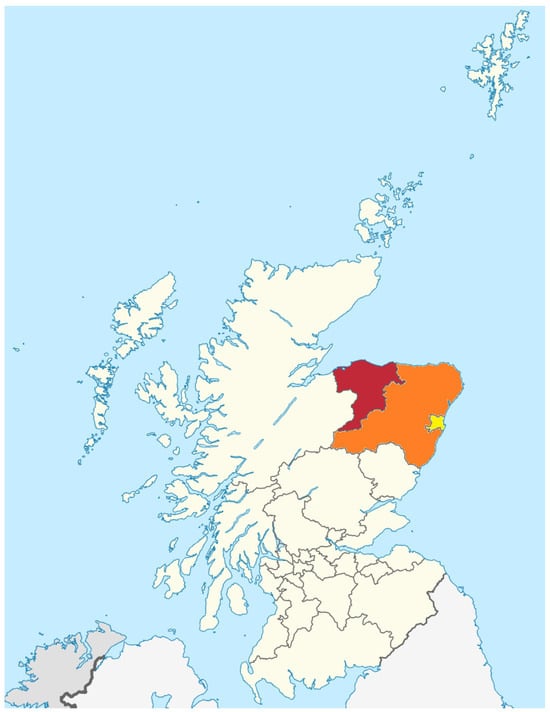
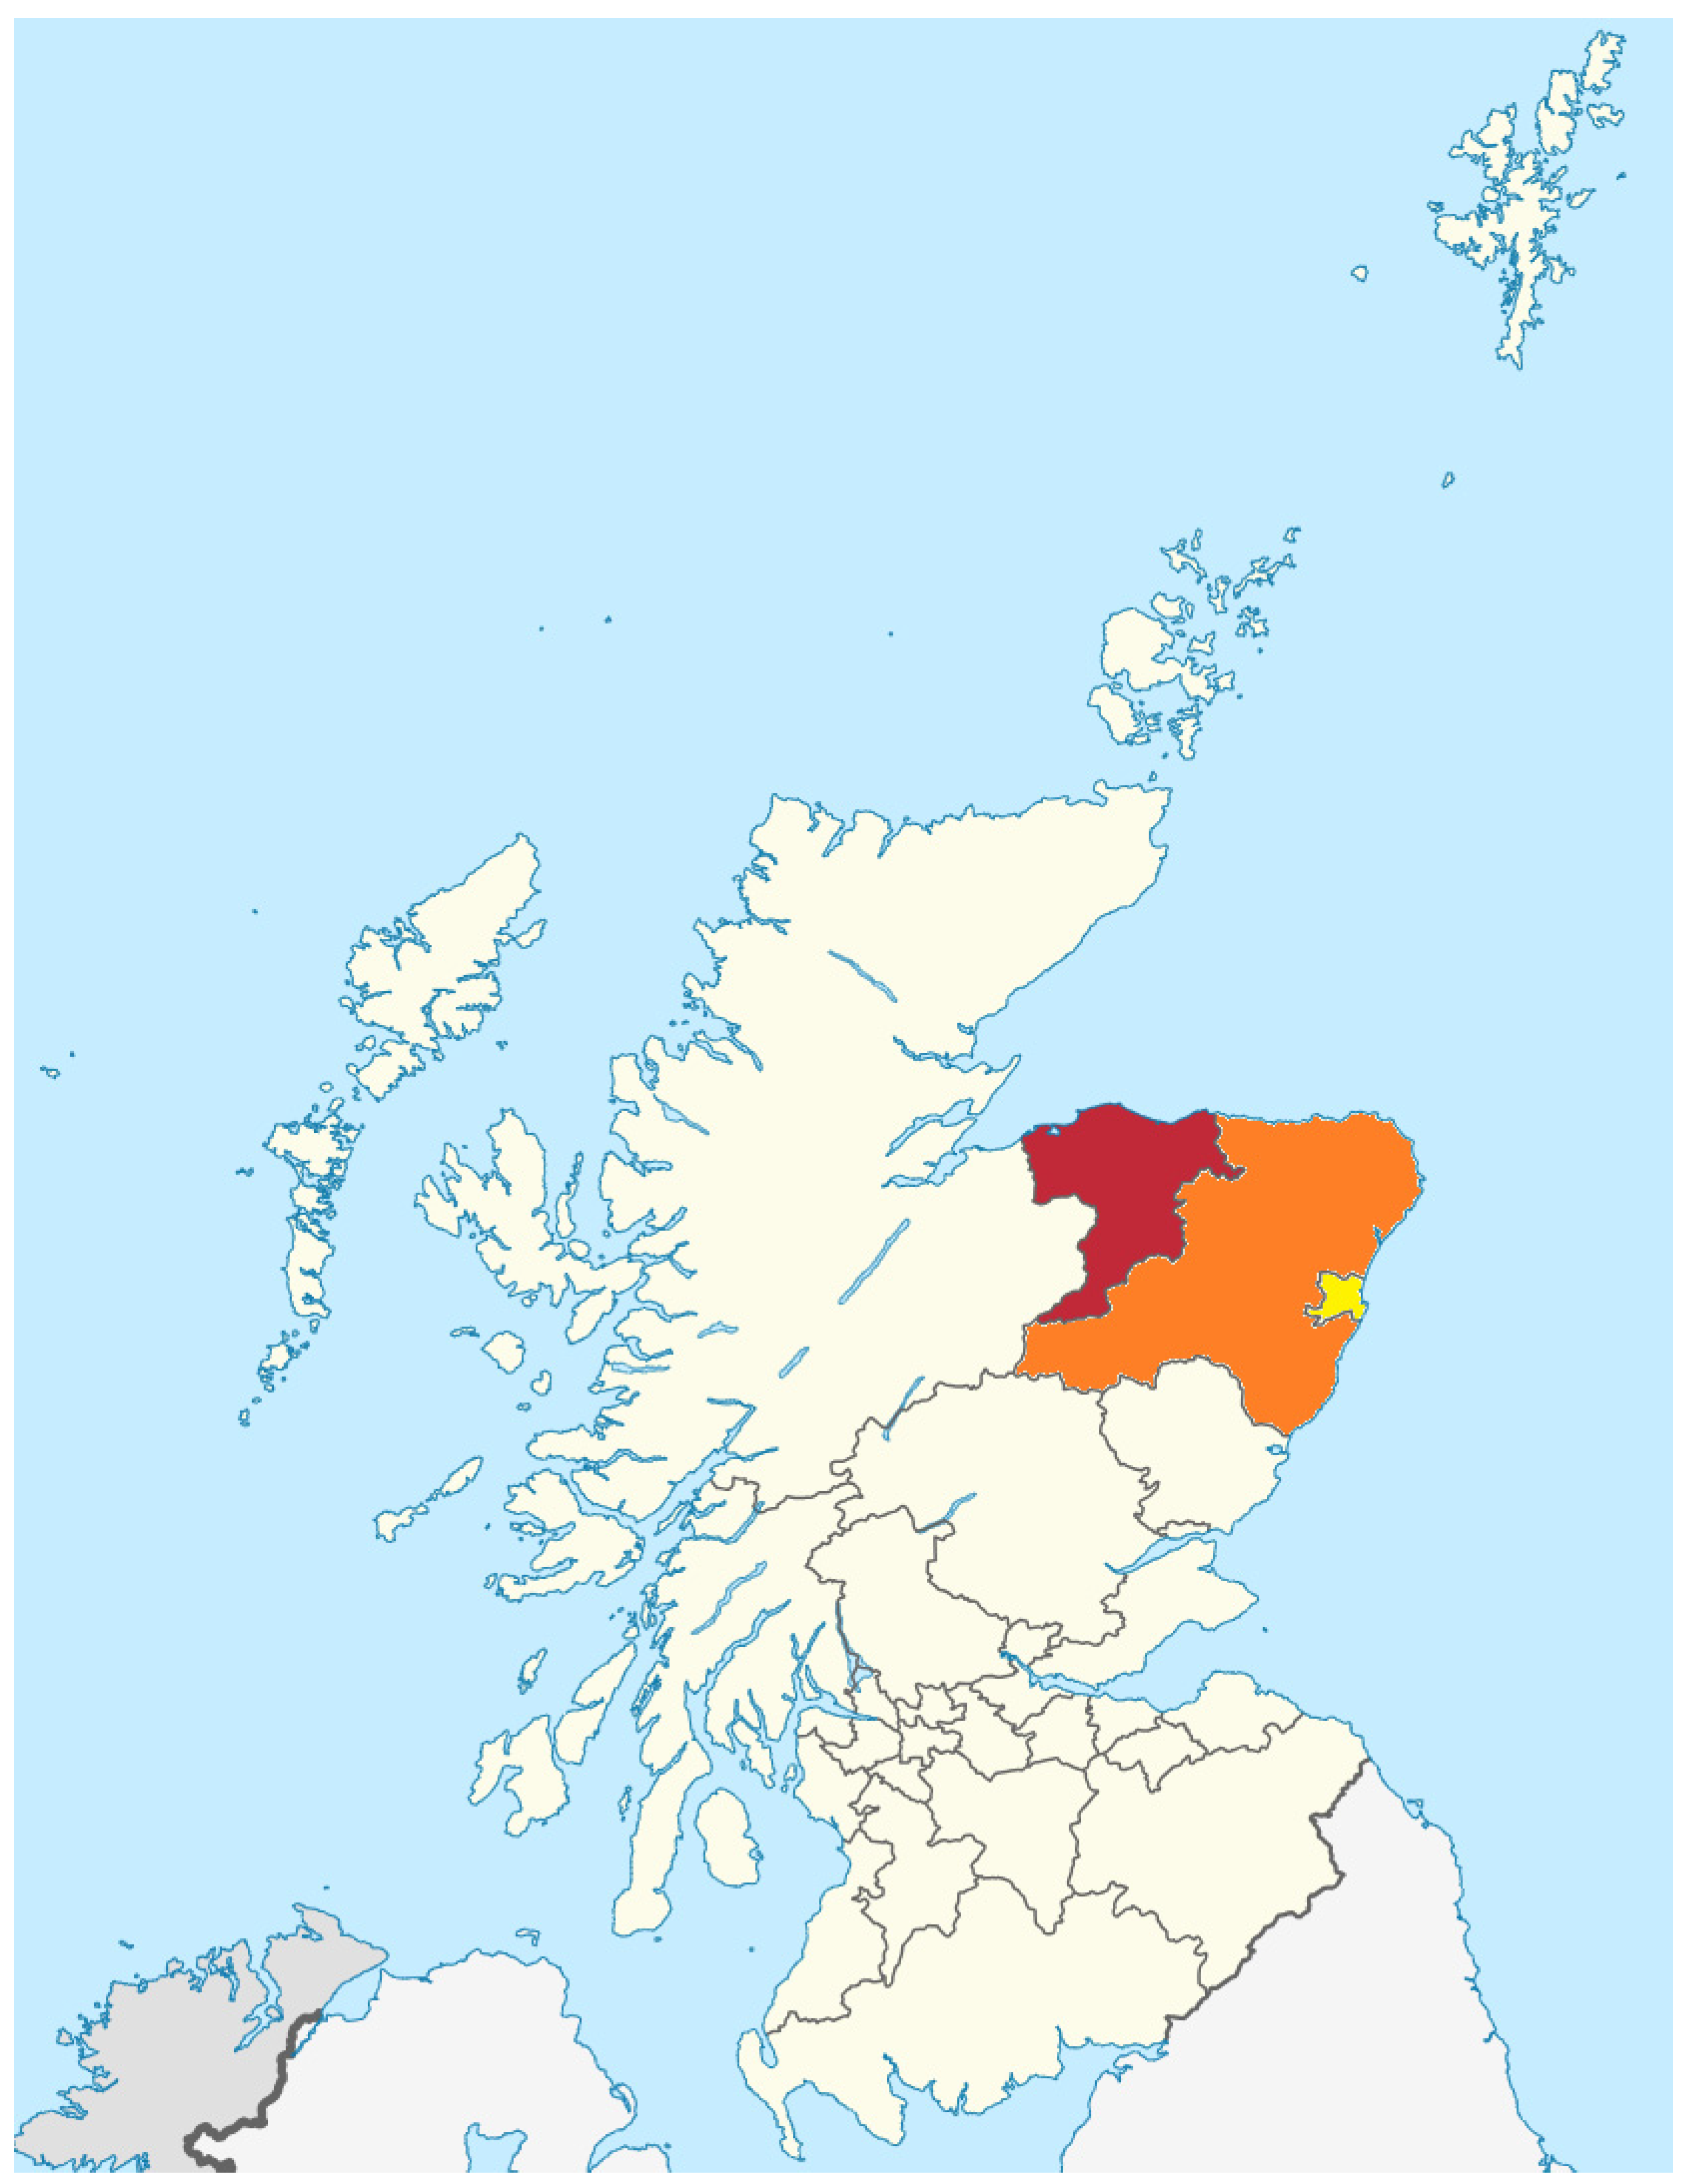
Such burden of disease estimates are also useful for identifying sub-populations with poorer outcomes (within the scope of this paper), which in turn can lead to further studies (not in the scope of this paper) on the underlying socio-economic determinants of health for each sub-population, and likely interventions by public health and local authorities. The reason for this is as follows: the NHS Research and Development department, with data scientists, can often produce the former analysis (as we have done); however, investigation of the wider socio-economic determinants of health and implementation of appropriate interventions typically fall within the remit of the Health and Social Care Partnerships in Scotland, Integrated Care Systems in England, and related regional bodies. Analysis, such as the one we have done, can help inform the work of organisations, including Aberdeen City, Aberdeenshire, and Moray Health and Social Care Partnerships within NHS Grampian (Figure 1).
Figure 1.
Grampian is a region in Scotland, and its constituent Health and Social Care Partnerships are shown in yellow (Aberdeen City), amber (Aberdeenshire), and red (Moray). Remixed image from Wikipedia released under the GNU Free Documentation License are highlighted for clarity.
Grampian was selected as an illustrative case study due to its heterogeneous population, encompassing urban (including Aberdeen City), rural, and remote communities. The region also has a distinctive demographic profile influenced by global migration to the North Sea oil and gas sector. With circa 1% of the population of the UK, Grampian provides a representative setting to demonstrate how regional burden of disease data can be analysed to inform local health priorities. This communication is a descriptive study of regional burden of disease patterns intended to inform health policy, service planning, research prioritisation, and resource allocation through a reproducible analytical approach that can be applied by other health service providers worldwide.
2. Methods
For this work, we have used the Scottish Burden of Disease (SBoD) dataset [9], c.f. eight references therein, a population health surveillance system which monitors how diseases, injuries, and risk factors prevent the Scottish population from living longer lives in better health. DALY rates per 100,000 population were extracted for Scotland and the Grampian region. Morbidity estimates within the SBoD framework were derived from multiple sources, including linked primary care records, secondary care records, disease registers, national surveys, and communicable disease surveillance systems. Most estimates were based on routine administrative datasets linked using Community Health Index (CHI) numbers, while some conditions additionally incorporated self-reported (depression and anxiety) or aggregate survey data. The SBoD methodology estimates prevalent ill-health rather than incident diagnoses; however, the publicly available methodology does not specify a universal requirement for active treatment status or a fixed diagnostic ascertainment period across all conditions [9,10,11]. Although socio-economic stratification was not presented explicitly in this analysis, the underlying SBoD methodology incorporates age-specific, sex-specific, and Scottish Index of Multiple Deprivation (SIMD)-specific morbidity modelling, whereby national morbidity rates stratified by deprivation decile are applied to local population structures to estimate expected burden [10,12].
Analyses were conducted by sex, age group, and time period. Data were initially analysed for the years 2016 to 2019 [13]; 2014 and 2015 were included in this analysis when data were made available. In addition to cross-sectional comparisons for the most recent year available (2019), temporal trends were assessed using compound annual growth rates (CAGR), calculated as:
where N is the number of years. CAGR was calculated for the periods of 2014–19 and 2016–19 to capture both longer-term and more recent trends. Differences between CAGR estimates across time intervals reflect both temporal changes and sensitivity to baseline selection, particularly for conditions with smaller absolute annual changes or non-linear trends. The use of two time windows, therefore, provides complementary insights into disease trends.
Our analysis is descriptive in nature, focusing on identifying patterns and relative differences across regions and population subgroups. Formal statistical hypothesis testing was not undertaken because the publicly available SBoD dataset does not provide uncertainty intervals or sufficiently granular raw data for robust inferential statistical analyses. The SBoD methodology notes that conventional confidence intervals would not fully capture uncertainties related to modelling assumptions and disability weights [10]. Therefore, observed differences between regions and sub-regions should be interpreted cautiously as descriptive indicators of variation rather than statistically confirmed differences.
The underlying raw Scottish burden of disease data used by this communication is available as Supplementary Material Table S1.
3. Results and Discussions
Burden of disease expressed as DALY rates per 100,000 population was calculated for Scotland versus Grampian for the latest year for which data are available (2019), separately for females (Table 1 and Table 2) and males (Table 3 and Table 4).
Table 1.
Disability-adjusted life year (DALY) rate per 100,000 people—females in Scotland versus Grampian (across time).
Table 2.
Disability-adjusted life year (DALY) rate per 100,000 people—females in Grampian 2019 (for selected diseases, age groups).
Table 3.
Disability-adjusted life year (DALY) rate per 100,000 people—males in Scotland versus Grampian (across time).
Table 4.
Disability-adjusted life year (DALY) rate per 100,000 people—males in Grampian 2019 (for selected diseases, age groups).
It is seen from Table 1 and Table 3 that the leading causes of disease burden for Grampian are also important for Scotland; however, their exact order may vary. Ischaemic heart disease, lung cancer, Alzheimer’s disease, and other dementias significantly affect both Grampian and Scotland (c.f. Figure 1), so it is important to focus on these national priorities.
We are able to identify those diseases where Grampian’s DALY rate exceeds the Scottish average as local priorities for the region. These include atrial fibrillation and flutter, diabetes, and oesophageal cancer for males; breast cancer, cerebrovascular disease, and other cardiovascular and circulatory diseases for females; colorectal cancer and drug use disorders that affect both sexes with worsening trends since 2014 (c.f. Table 1 and Table 3).
Age-stratified analyses (Table 2 and Table 4) identify the age groups for these diseases of concern where the burden is especially high. For example, Alzheimer’s disease and other dementias primarily affect those aged 65+, whereas drug use disorders and self-harm disproportionately impact younger and working-age populations. We assessed temporal trends using CAGR for 2014–19 as well as 2016–19 (as previously computed [13]) to identify diseases with significant temporal changes that warrant closer monitoring in future analyses. Application of CAGR across two time intervals (2014–2019 and 2016–2019) enabled the identification of additional priority conditions.
It is important to address these unmet needs through a combination of public health measures (e.g., health promotion, disease prevention) and interventions arising from life sciences, health, and medical research and innovation [14]. The latter is very important as demonstrated by, for example, the recent reviews of Australia’s Medical Research Future Fund [15,16], in which it was found that 231 grants were awarded during 2016–19 with a total value of AU$574.5 million [16], but when mapped against 17 disease groups in the Australian burden of disease study 2015 [17], only a weak association was observed with DALY (r2 = 0.4359) and no association was observed with disability burden YLD (r2 = 0.0009) [16]. Any life sciences, health, and medical research and innovation investments into Grampian by public, private, or non-profit sectors should take these considerations into account. Realistic medicine approaches [18] and regional investments should target the local burden of diseases, lest there could be higher opportunity costs and unintentional widening of inequalities. For the Grampian region, disease priorities are summarised under the mnemonic “CICADAS” (Table 5), with the worst-affected age groups identified from Table 2 and Table 4.
Table 5.
Selected disease conditions of concern to Grampian and the age groups worst affected.
As shown in Figure 1 and previously described, the Grampian region is in turn comprising three Health and Social Care Partnerships (viz. Aberdeen City, Aberdeenshire, and Moray), which are local authorities in Scotland responsible for planning and delivering health and social care services in partnership with the NHS. Examining sub-regional variations can provide valuable insights for these partnerships to identify relevant socio-economic determinants of health and devise appropriate interventions for each affected sub-population. For example, the Aberdeen City Health and Social Care Partnerships is one of the UK’s ‘Marmot Places’, an initiative focused on reducing health inequalities through action on the social determinants of health [19].
From Table 6, it is seen that Aberdeenshire is close to the Grampian average for diseases in females listed under Table 2; Aberdeen City has a higher DALY rate than Grampian for Alzheimer’s disease and other dementias, lung and colorectal cancers, and drug use disorders; while Moray has a higher DALY rate than Grampian for ischaemic heart disease, cerebrovascular disease, and other cardiovascular and circulatory diseases.
Table 6.
Disability-adjusted life year (DALY) rate per 100,000 people—females (2019, for selected diseases in Table 2, sub-regions).
From Table 7, it is seen that Aberdeenshire is below the Grampian average for diseases in males listed under Table 4 (except perhaps colorectal cancer, atrial fibrillation, and flutter); Moray has a higher DALY rate than Grampian for lung cancer, atrial fibrillation, and flutter; while Aberdeen has a higher DALY rate than Grampian for all but atrial fibrillation and flutter. Thus, we notice that while some trends are the same for both sexes, there are significant differences too, so we need a nuanced approach. Observed regional variations may partly reflect underlying socio-economic differences between urban, rural, and mixed populations across the Grampian region, including deprivation, occupational structure, environmental exposures, and differential access to healthcare and diagnostic services. In addition to these factors, broader contextual influences such as industrial activity, air quality, and natural environmental characteristics may also contribute to differences in disease burden, although these were not directly measured in this study.
Table 7.
Disability-adjusted life year (DALY) rate per 100,000 people—males (2019, for selected diseases in Table 4, sub-regions).
4. Conclusions, Limitations, and Future Work
With health services under increasing pressure across the world, it is important to ensure better alignment between the long-term plans for population health and integrated health and social care. In many developed countries, we have health surveillance data in the public domain. These, especially on the burden of diseases, can be mined and analysed by health service providers to serve their populations more effectively and in a targeted manner, as shown in this communication with the Grampian region case study. For example, we were able to identify which diseases have the highest DALY rate burden, which ones are of particular concern to Grampian, and those that are showing a worsening trend. We were also able to gain a nuanced understanding in terms of differences between males and females, age groups, and the three sub-regions that make up Grampian. This will allow targeted medical research investments and coordinated response from public health and health service delivery [14].
Importantly, while DALYs are well-suited for population health assessment and prioritisation, decision-making within the UK’s National Health Service is typically informed by cost-effectiveness frameworks based on QALYs, particularly in health interventions [7]. Although QALY-based analyses are beyond the scope of this study, our findings provide robust, region-specific burden of disease data that can inform policy and resource allocation. These quantitative results can be complemented by qualitative analyses, such as the recent Grampian participatory research on patient, public, and stakeholder perspectives, which identifies priority health areas from the viewpoint of those directly affected [14]. Together, such quantitative and qualitative evidence can strengthen local NHS planning, providing a foundation that can be expanded to inform broader decision-making in epidemiology and health policy.
We acknowledge that the public domain Scottish burden of disease data extends only to 2019, limiting direct applicability to post-pandemic health contexts. However, this communication does provide a useful pre-pandemic baseline for future comparisons. The methodological framework remains robust and can be readily applied to updated datasets as they become available.
Future work in Scotland, perhaps led by the relevant Health and Social Care Partnerships, should incorporate socio-economic stratification using measures such as SIMD deciles to enable a more detailed assessment of health inequalities within and between sub-regions, thereby supporting more targeted and equitable health planning. Finer-scale analyses within regions, alongside consideration of environmental, occupational, and healthcare access factors, may further help to explain observed variations in disease burden across sub-regions and what targeted interventions are needed.
There are several categories of public domain SBoD data published by Public Health Scotland, which researchers are unable to modify and therefore act as limiting factors for our analysis. For example, self-harm and interpersonal violence are distinct with very dissimilar causes, social outcomes, policies, and prevention programmes; however, these are only available to us as an aggregated line item. Several categories, such as “other cardiovascular” or “other cancers”, are too broad and less specific in the underlying dataset, highlighting the need for more granular categorisation in the public domain.
Crucially, this study provides a template that other regions can adapt using their own local data. It highlights the need for future analyses incorporating improved data granularity and socio-economic stratification that would enable more targeted and equitable health planning, and provide a more nuanced understanding of regional health inequalities. We further demonstrate the importance of up-to-date surveillance data being available to health service providers, as well as the need for predictive trends and evidence on the impact of interventions, and it is heartening to note that such forecasting could soon be made available “to offer insights into future public health challenges in Scotland” [9].
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/ijerph23060763/s1, Table S1: Scottish burden of disease underlying dataset.
Author Contributions
Conceptualization, S.S.V. and N.C.F.; methodology, S.S.V.; software, S.S.V. and S.A.; validation, S.S.V., S.A. and M.L.; formal analysis, S.S.V., S.A. and M.L.; investigation, S.S.V., S.A. and M.L.; resources, N.C.F.; data curation, S.S.V., S.A. and M.L.; writing—original draft preparation, S.S.V.; writing—review and editing, S.S.V., S.A., M.L. and N.C.F.; visualisation, S.S.V., S.A. and M.L.; supervision, N.C.F.; project administration, S.S.V.; funding acquisition, N.C.F. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Data supporting reported results can be downloaded from the Scottish burden of disease [9] or the Supplementary Materials.
Acknowledgments
S.S.V. is grateful for discussions with his past collaborator and co-author, Donald S. Shepard of Brandeis University (see, for instance, [20,21]) on QALYs versus DALYs. Donald preferred the term QALY to quality-adjusted citizen years as the latter acronym was felt to be quacky and fowl usage. The authors thank Shantini Paranjothy and are also grateful to Tara Shivaji and Grant Wyper of Public Health Scotland for their helpful guidance.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Klarman, H.E.; Francis, J.O.S.; Rosenthal, G.D. Cost-effectiveness analysis applied to the treatment of chronic renal disease. Med. Care 1968, 6, 48–54. [Google Scholar] [CrossRef] [Scilit]
- Zeckhauser, R.; Shepard, D.S. Where now for saving lives? Law Contemp. Probl. 1976, 40, 5–45. [Google Scholar] [CrossRef] [Scilit]
- Drummond, M.F.; Sculpher, M.J.; Torrance, G.W.; O’Brien, B.J.; Stoddart, G.L. Methods for the Economic Evaluation of Health Care Programmes; Oxford University Press: Oxford, UK, 2005; Available online: https://academic.oup.com/book/54294 (accessed on 20 November 2023).
- York Health Economics Consortium. Incremental Cost-Effectiveness Ratio. Available online: https://yhec.co.uk/glossary/incremental-cost-effectiveness-ratio-icer/ (accessed on 20 November 2023).
- Murray, C. Quantifying the burden of disease: The technical basis for disability-adjusted life years. Bull. World Health Organ. 1994, 72, 429–445. [Google Scholar] [PubMed]
- World Health Organization. Disability-Adjusted Life Years (DALYs). Available online: https://www.who.int/data/gho/indicator-metadata-registry/imr-details/158 (accessed on 20 November 2023).
- Ogden, J. QALYs and their role in the NICE decision-making process. Prescriber 2017, 28, 41–43. [Google Scholar] [CrossRef] [Scilit]
- Office for Health Improvement and Disparities. Fingertips (Public Health Data). Available online: https://fingertips.phe.org.uk (accessed on 20 November 2023).
- Public Health Scotland. Scottish Burden of Disease. Available online: https://scotland.shinyapps.io/phs-local-trends-scottish-burden-diseases (accessed on 20 November 2023).
- The Scottish Public Health Observatory. Burden of Disease: Archive. Available online: https://www.scotpho.org.uk/comparative-health/burden-of-disease/archive/ (accessed on 9 May 2026).
- Wyper, G. (Public Health Scotland, Edinburgh, UK). Personal communication, 2026. [Google Scholar]
- Wyper, G.; Grant, I.; Fletcher, E.; McCartney, G.; Stockton, D. Scottish Burden of Disease (SBOD) study: Developments and findings of local estimates. Int. J. Popul. Data Sci. 2019, 4, 1257. [Google Scholar] [CrossRef] [Scilit]
- Vasan, S.; Fluck, N. On Burden of Diseases, Prevention, Medical Research and Health Service Delivery: Grampian Case Study. Preprints 2023, 2023120361. [Google Scholar] [CrossRef]
- Lee, M.; Anderson, L.A.; Piltonen, E.; Maheshwari, A.; Griffin, J.L.; Vasan, S.S. Participatory development of innovation and implementation strategy—An action-oriented approach. BMC Health Serv. Res. 2026, 26, 626. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Australian National Audit Office. Department of Health’s Management of Financial Assistance Under the Medical Research Future Fund; Australian National Audit Office: Canberra, Australia, 2021. Available online: https://www.anao.gov.au/work/performance-audit/department-health-management-financial-assistance-under-the-medical-research-future-fund (accessed on 20 November 2023).
- Gilbert, S.E.; Buchbinder, R.; Harris, I.A.; Maher, C.G. A comparison of the distribution of Medical Research Future Fund grants with disease burden in Australia. Med. J. Aust. 2021, 214, 111–114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Australian Institute of Health and Welfare. Australian Burden of Disease Study 2015: Interactive Data on Disease Burden; Australian Institute of Health and Welfare: Canberra, Australia, 2019. Available online: https://www.aihw.gov.au/reports/burden-of-disease/abds-2015-interactive-data-disease-burden/data (accessed on 20 November 2023).
- Realistic Medicine. Available online: https://realisticmedicine.scot (accessed on 20 November 2023).
- Macgill, J. Scotland Can Be a Marmot Nation. Healthandcare.scot, 30 April 2025. Available online: https://healthandcare.scot/stories/4136/marmot-alliance-inequalities-aberdeen-lanarkshire-ayrshire-equity-collaboration (accessed on 13 May 2026).
- Lee, H.L.; Vasan, S.S.; Birgelen, L.; Murtola, T.M.; Gong, H.F.; Field, R.W.; Mavalankar, D.V.; Ahmad, N.W.; Hakim, L.S.; Murad, S.; et al. Immediate cost of dengue to Malaysia and Thailand: An estimate. Dengue Bull. 2010, 34, 65–76. [Google Scholar]
- Murtola, T.M.; Vasan, S.S.; Puwar, T.I.; Govil, D.; Field, R.W.; Gong, H.F.; Bhavsar-Vyas, A.; Suaya, J.A.; Howard, M.; Shepard, D.S.; et al. Preliminary estimate of immediate cost of chikungunya and dengue to Gujarat, India. Dengue Bull. 2010, 34, 32–38. [Google Scholar]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.