
Blood-Based Biomarkers for Post-Stroke Cognitive Impairment

Abstract
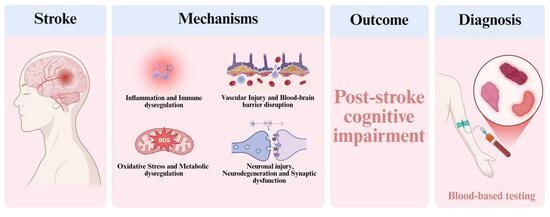
1. Introduction
2. Search Method
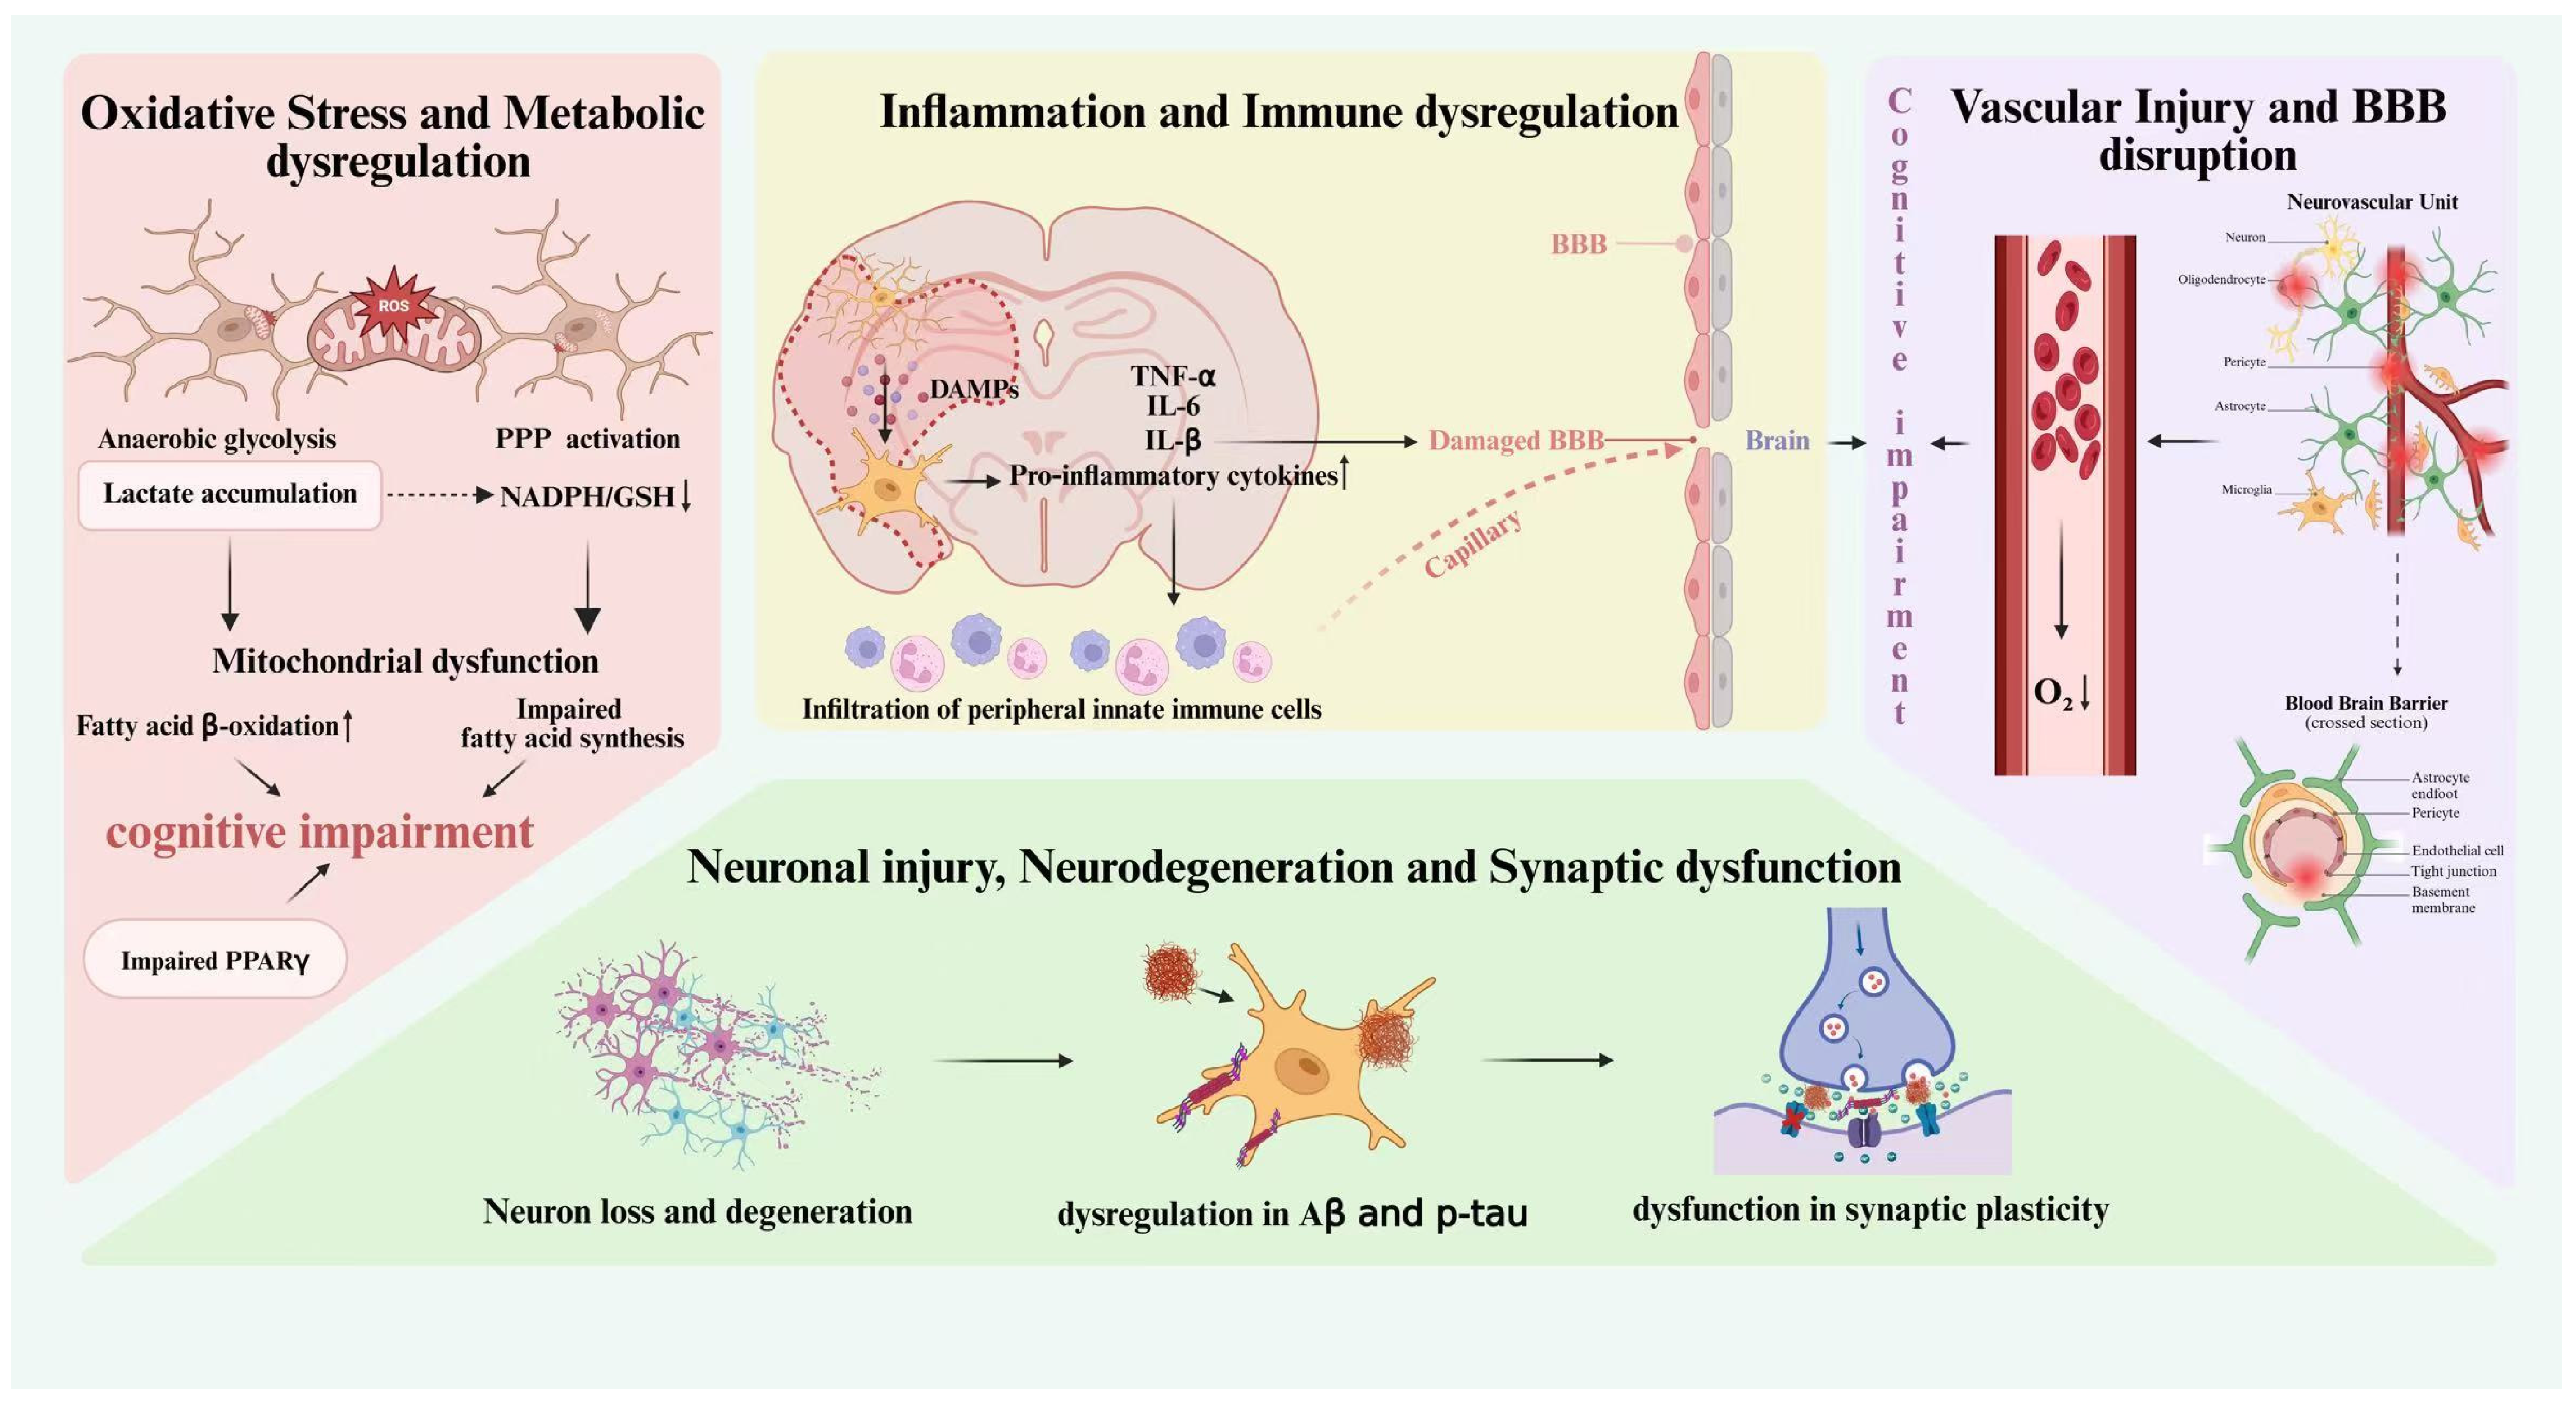
3. Pathophysiology of PSCI
3.1. Inflammation and Immune Dysregulation
3.2. Oxidative Stress and Metabolic Dysregulation
3.3. Vascular Injury and Blood–Brain Barrier Disruption
3.4. Neuronal Injury, Neurodegeneration and Synaptic Dysfunction
4. Blood-Based Biomarkers in PSCI
4.1. Inflammation and Immune Biomarkers
4.1.1. Classical Inflammatory Cytokines
4.1.2. Innate Immune Activation and Immunometabolism-Related Biomarkers
4.2. Oxidative Stress and Metabolic Biomarkers
4.2.1. Oxidative Stress-Related Biomarkers
4.2.2. Lipid and Energy Metabolism Biomarkers
4.2.3. Amino Acid Metabolism and Metabolic Regulatory Biomarkers
4.3. Vascular Injury and Endothelial Dysfunction Biomarkers
4.3.1. Blood–Brain Barrier Disruption-Related Biomarkers
4.3.2. Angiogenesis and Vascular Remodeling Biomarkers
4.3.3. Hemodynamic and Coagulation-Related Biomarkers
4.4. Neuronal Injury, Neurodegeneration and Synaptic Dysfunction Biomarkers
4.4.1. Markers of Neuronal Structural Injury
4.4.2. Synaptic Dysfunction and Neuroplasticity-Related Biomarkers
4.4.3. Neuroregulatory and Neurotransmitter-Related Biomarkers
4.5. Regulatory Molecules and Emerging Biomarkers
4.5.1. Circulating Non-Coding RNAs
4.5.2. Multi-Omics Biomarkers
4.6. Holistic Understanding and Clinical Implications of Blood Biomarkers in PSCI
5. Current Issues and Future Directions
6. Conclusions
Author Contributions
Funding
Data Availability Statement
Acknowledgments
Conflicts of Interest
References
- Feigin, V.L.; Abate, M.D.; Abate, Y.H.; Abd ElHafeez, S.; Abd-Allah, F.; Abdelalim, A.; Abdelkader, A.; Abdelmasseh, M.; Abd-Elsalam, S.; Abdi, P.; et al. Global, regional, and national burden of stroke and its risk factors, 1990–2021: A systematic analysis for the Global Burden of Disease Study 2021. Lancet Neurol. 2024, 23, 973–1003. [Google Scholar] [CrossRef] [Scilit]
- Feigin, V.L.; Owolabi, M.O. Pragmatic solutions to reduce the global burden of stroke: A World Stroke Organization-Lancet Neurology Commission. Lancet Neurol. 2023, 22, 1160–1206, Erratum in Lancet Neurol. 2023, 22, e13. [Google Scholar] [CrossRef] [Scilit]
- Levine, D.A.; Galecki, A.T.; Langa, K.M.; Unverzagt, F.W.; Kabeto, M.U.; Giordani, B.; Wadley, V.G. Trajectory of Cognitive Decline After Incident Stroke. JAMA 2015, 314, 41–51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pendlebury, S.T.; Rothwell, P.M. Prevalence, incidence, and factors associated with pre-stroke and post-stroke dementia: A systematic review and meta-analysis. Lancet Neurol. 2009, 8, 1006–1018. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, L.; Jiang, Y.; Xu, W.; Wang, L.; Li, L.; Zhang, C.; Huang, K.; Yang, Y.; Dai, J.; Zhou, F. Potential Inflammatory Biomarkers and Differential Gut Microbiota in Cognitive Impairment After Ischemic Stroke. Neuropsychiatr. Dis. Treat. 2025, 21, 965–972. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hilal, S.; Xu, X.; Ikram, M.K.; Vrooman, H.; Venketasubramanian, N.; Chen, C. Intracranial stenosis in cognitive impairment and dementia. J. Cereb. Blood Flow Metab. 2017, 37, 2262–2269. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Y.Q.; He, X.; Huang, X.L.; Qin, F.L.; Mao, F.L.; Cheng, Y.M.; Zeng, X.X.; Yang, Y.Y.; Xu, M.X. The role of serum albumin and albumin-related nutritional indices in predicting post-stroke cognitive impairment: A systematic review and meta-analysis. Front. Neurol. 2025, 16, 1641711. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mijajlović, M.D.; Pavlović, A.; Brainin, M.; Heiss, W.D.; Quinn, T.J.; Ihle-Hansen, H.B.; Hermann, D.M.; Assayag, E.B.; Richard, E.; Thiel, A.; et al. Post-stroke dementia—A comprehensive review. BMC Med. 2017, 15, 11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shi, D.; Chen, X.; Li, Z. Diagnostic test accuracy of the Montreal Cognitive Assessment in the detection of post-stroke cognitive impairment under different stages and cutoffs: A systematic review and meta-analysis. Neurol. Sci. 2018, 39, 705–716. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Crum, R.M.; Anthony, J.C.; Bassett, S.S.; Folstein, M.F. Population-based norms for the Mini-Mental State Examination by age and educational level. JAMA 1993, 269, 2386–2391. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wong, A.; Law, L.S.; Liu, W.; Wang, Z.; Lo, E.S.; Lau, A.; Wong, L.K.; Mok, V.C. Montreal Cognitive Assessment: One Cutoff Never Fits All. Stroke 2015, 46, 3547–3550. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Z.; Wang, R.; Li, Y.; Li, M.; Zhang, Y.; Jiang, L.; Fan, J.; Wang, Q.; Yang, D. Plasma Neurofilament Light Chain as a Predictive Biomarker for Post-stroke Cognitive Impairment: A Prospective Cohort Study. Front. Aging Neurosci. 2021, 13, 631738. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, M.; Zhang, M.; Chen, Z.; Bao, B.; Chen, Y.; Wang, F.; Jiang, M.; Wu, M.; Yin, X. Mechanisms and biomarkers of poststroke cognitive impairment. Neural Regen. Res. 2026, 21, 4642–4652. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Endres, M.; Moro, M.A.; Nolte, C.H.; Dames, C.; Buckwalter, M.S.; Meisel, A. Immune Pathways in Etiology, Acute Phase, and Chronic Sequelae of Ischemic Stroke. Circ. Res. 2022, 130, 1167–1186. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Q.; Tang, X.N.; Yenari, M.A. The inflammatory response in stroke. J. Neuroimmunol. 2007, 184, 53–68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jin, W.N.; Shi, S.X.; Li, Z.; Li, M.; Wood, K.; Gonzales, R.J.; Liu, Q. Depletion of microglia exacerbates postischemic inflammation and brain injury. J. Cereb. Blood Flow Metab. 2017, 37, 2224–2236. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oo, T.T. Ischemic stroke and diabetes: A TLR4-mediated neuroinflammatory perspective. J. Mol. Med. 2024, 102, 709–717. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, N.T.; Ong, L.K.; Gyawali, P.; Nassir, C.; Mustapha, M.; Nandurkar, H.H.; Sashindranath, M. Role of Purinergic Signalling in Endothelial Dysfunction and Thrombo-Inflammation in Ischaemic Stroke and Cerebral Small Vessel Disease. Biomolecules 2021, 11, 994. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Andjelkovic, A.V.; Situ, M.; Citalan-Madrid, A.F.; Stamatovic, S.M.; Xiang, J.; Keep, R.F. Blood-Brain Barrier Dysfunction in Normal Aging and Neurodegeneration: Mechanisms, Impact, and Treatments. Stroke 2023, 54, 661–672. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tsai, A.S.; Berry, K.; Beneyto, M.M.; Gaudilliere, D.; Ganio, E.A.; Culos, A.; Ghaemi, M.S.; Choisy, B.; Djebali, K.; Einhaus, J.F.; et al. A year-long immune profile of the systemic response in acute stroke survivors. Brain 2019, 142, 978–991. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Doyle, K.P.; Buckwalter, M.S. Does B lymphocyte-mediated autoimmunity contribute to post-stroke dementia? Brain Behav. Immun. 2017, 64, 1–8. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, P.; Zhang, G.; Wang, Y.; Wei, C.; Wang, Z.; Zhai, W.; Shen, Y.; Shi, L.; Sun, L. Peripheral immunity is associated with cognitive impairment after acute minor ischemic stroke and transient ischemic attack. Sci. Rep. 2024, 14, 16201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaur, M.; Sharma, S. Molecular mechanisms of cognitive impairment associated with stroke. Metab. Brain Dis. 2022, 37, 279–287. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gao, L.; Peng, L.; Wang, J.; Zhang, J.H.; Xia, Y. Mitochondrial stress: A key role of neuroinflammation in stroke. J. Neuroinflamm. 2024, 21, 44. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fanzhou, R.; Yuding, L.; Pingchuan, L.; Hai, X.; Xu, L.; Jian, W. The role of TNF signaling pathway in post-stroke cognitive impairment: A systematic review. Ann. Med. 2025, 57, 2543519. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kelly, P.J.; Morrow, J.D.; Ning, M.; Koroshetz, W.; Lo, E.H.; Terry, E.; Milne, G.L.; Hubbard, J.; Lee, H.; Stevenson, E.; et al. Oxidative stress and matrix metalloproteinase-9 in acute ischemic stroke: The Biomarker Evaluation for Antioxidant Therapies in Stroke (BEAT-Stroke) study. Stroke 2008, 39, 100–104. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lan, L.F.; Zheng, L.; Yang, X.; Ji, X.T.; Fan, Y.H.; Zeng, J.S. Peroxisome proliferator-activated receptor-γ agonist pioglitazone ameliorates white matter lesion and cognitive impairment in hypertensive rats. CNS Neurosci. Ther. 2015, 21, 410–416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, H.; Ke, X.; Feng, B.; Tian, H.; Cai, Z.; Zhang, A.; Man, Q. Research progress on the mechanism and markers of metabolic disorders in the occurrence and development of cognitive dysfunction after ischemic stroke. Front. Endocrinol. 2025, 16, 1500650. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thiel, A.; Cechetto, D.F.; Heiss, W.D.; Hachinski, V.; Whitehead, S.N. Amyloid burden, neuroinflammation, and links to cognitive decline after ischemic stroke. Stroke 2014, 45, 2825–2829. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rost, N.S.; Brodtmann, A.; Pase, M.P.; van Veluw, S.J.; Biffi, A.; Duering, M.; Hinman, J.D.; Dichgans, M. Post-Stroke Cognitive Impairment and Dementia. Circ. Res. 2022, 130, 1252–1271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Takemori, K.; Murakami, T.; Kometani, T.; Ito, H. Possible involvement of oxidative stress as a causative factor in blood-brain barrier dysfunction in stroke-prone spontaneously hypertensive rats. Microvasc. Res. 2013, 90, 169–172. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iadecola, C. The Neurovascular Unit Coming of Age: A Journey through Neurovascular Coupling in Health and Disease. Neuron 2017, 96, 17–42. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sweeney, M.D.; Ayyadurai, S.; Zlokovic, B.V. Pericytes of the neurovascular unit: Key functions and signaling pathways. Nat. Neurosci. 2016, 19, 771–783. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamazaki, Y.; Kanekiyo, T. Blood-Brain Barrier Dysfunction and the Pathogenesis of Alzheimer’s Disease. Int. J. Mol. Sci. 2017, 18, 1965. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huber, J.D. Diabetes, cognitive function, and the blood-brain barrier. Curr. Pharm. Des. 2008, 14, 1594–1600. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vestergaard, S.B.; Damsbo, A.G.; Pedersen, N.L.; Zachariassen, K.; Drasbek, K.R.; Østergaard, L.; Andersen, G.; Dalby, R.B.; Mortensen, J.K. Exploring vascular contributions to cognitive impairment and dementia (ENIGMA): Protocol for a prospective observational study. BMC Neurol. 2024, 24, 110. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Engedal, T.S.; Hjort, N.; Hougaard, K.D.; Simonsen, C.Z.; Andersen, G.; Mikkelsen, I.K.; Boldsen, J.K.; Eskildsen, S.F.; Hansen, M.B.; Angleys, H.; et al. Transit time homogenization in ischemic stroke—A novel biomarker of penumbral microvascular failure? J. Cereb. Blood Flow Metab. 2018, 38, 2006–2020. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alawieh, A.; Langley, E.F.; Tomlinson, S. Targeted complement inhibition salvages stressed neurons and inhibits neuroinflammation after stroke in mice. Sci. Transl. Med. 2018, 10, eaao6459. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, J.; Zhang, Y.; Xing, S.; Liang, Z.; Zeng, J. Secondary neurodegeneration in remote regions after focal cerebral infarction: A new target for stroke management? Stroke 2012, 43, 1700–1705. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakane, M.; Teraoka, A.; Asato, R.; Tamura, A. Degeneration of the ipsilateral substantia nigra following cerebral infarction in the striatum. Stroke 1992, 23, 328–332. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gemmell, E.; Bosomworth, H.; Allan, L.; Hall, R.; Khundakar, A.; Oakley, A.E.; Deramecourt, V.; Polvikoski, T.M.; O’Brien, J.T.; Kalaria, R.N. Hippocampal neuronal atrophy and cognitive function in delayed poststroke and aging-related dementias. Stroke 2012, 43, 808–814. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brodtmann, A.; Khlif, M.S.; Egorova, N.; Veldsman, M.; Bird, L.J.; Werden, E. Dynamic Regional Brain Atrophy Rates in the First Year After Ischemic Stroke. Stroke 2020, 51, e183–e192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Groen, T.; Puurunen, K.; Mäki, H.M.; Sivenius, J.; Jolkkonen, J. Transformation of diffuse beta-amyloid precursor protein and beta-amyloid deposits to plaques in the thalamus after transient occlusion of the middle cerebral artery in rats. Stroke 2005, 36, 1551–1556. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dong, D.W.; Zhang, Y.S.; Yang, W.Y.; Wang-Qin, R.Q.; Xu, A.D.; Ruan, Y.W. Hyperphosphorylation of tau protein in the ipsilateral thalamus after focal cortical infarction in rats. Brain Res. 2014, 1543, 280–289. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grilli, M.; Diodato, E.; Lozza, G.; Brusa, R.; Casarini, M.; Uberti, D.; Rozmahel, R.; Westaway, D.; St George-Hyslop, P.; Memo, M.; et al. Presenilin-1 regulates the neuronal threshold to excitotoxicity both physiologically and pathologically. Proc. Natl. Acad. Sci. USA 2000, 97, 12822–12827. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pluta, R.; Ułamek-Kozioł, M.; Januszewski, S.; Czuczwar, S.J. Tau Protein Dysfunction after Brain Ischemia. J. Alzheimers Dis. 2018, 66, 429–437. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sagare, A.P.; Bell, R.D.; Zlokovic, B.V. Neurovascular defects and faulty amyloid-β vascular clearance in Alzheimer’s disease. J. Alzheimers Dis. 2013, 33, S87–S100. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Raven, F.; Van der Zee, E.A.; Meerlo, P.; Havekes, R. The role of sleep in regulating structural plasticity and synaptic strength: Implications for memory and cognitive function. Sleep Med. Rev. 2018, 39, 3–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xia, D.; Yuan, J.; Wu, D.; Dai, H.; Zhuang, Z. Salvianolic acid B ameliorates neuroinflammation and neuronal injury via blocking NLRP3 inflammasome and promoting SIRT1 in experimental subarachnoid hemorrhage. Front. Immunol. 2023, 14, 1159958. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, X.W.; Zhou, J.P.; Bi, Y.L.; Wang, J.Y.; Yu, R.; Deng, C.; Wang, W.K.; Li, X.Z.; Huang, R.; Zhang, J.; et al. The role of MAPK signaling pathway in formation of EMT in oral squamous carcinoma cells induced by TNF-α. Mol. Biol. Rep. 2019, 46, 3149–3156. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pepys, M.B.; Baltz, M.L. Acute phase proteins with special reference to C-reactive protein and related proteins (pentaxins) and serum amyloid A protein. Adv. Immunol. 1983, 34, 141–212. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pepys, M.B.; Hirschfield, G.M. C-reactive protein: A critical update. J. Clin. Investig. 2003, 111, 1805–1812. [Google Scholar] [CrossRef] [PubMed]
- Yang, J.; Fan, C.; Pan, L.; Xie, M.; He, Q.; Li, D.; Wang, S. C-reactive protein plays a marginal role in cognitive decline: A systematic review and meta-analysis. Int. J. Geriatr. Psychiatry 2015, 30, 156–165. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rothenburg, L.S.; Herrmann, N.; Swardfager, W.; Black, S.E.; Tennen, G.; Kiss, A.; Gladstone, D.J.; Ween, J.; Snaiderman, A.; Lanctôt, K.L. The relationship between inflammatory markers and post stroke cognitive impairment. J. Geriatr. Psychiatry Neurol. 2010, 23, 199–205. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ran, F.; Liu, F.; Zhang, Y.; Chen, L. Serum Uric Acid and High-Sensitivity C-Reactive Protein as Predictors of Cognitive Impairment in Patients with Cerebral Infarction. Dement. Geriatr. Cogn. Disord. 2020, 49, 235–242. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Y.; Li, J.; Pan, Y.; Wang, M.; Lin, J.; Meng, X.; Liao, X.; Wang, Y. Interleukin-6 as Predictor of One-Year Cognitive Function After Ischemic Stroke or TIA. Neuropsychiatr. Dis. Treat. 2022, 18, 391–399. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carmichael, N.S.; Deijnen, H.R.; Wong, S.Y.; Williams, T.O.; Kontopantelis, E.; Cowie, L.; Jones, E.; Drag, L.; Buckwalter, M.S.; Grainger, J.R.; et al. Longitudinal plasma interleukin-6 and post-stroke cognitive outcomes: The Stroke-IMPaCT study. Alzheimers Dement. 2026, 22, e71261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kulesh, A.A.; Drobakha, V.E.; Nekrasova, I.V.; Kuklina, E.M.; Shestakov, V.V. Neuroinflammatory, Neurodegenerative and Structural Brain Biomarkers of the Main Types of Post-Stroke Cognitive Impairment in Acute Period of Ischemic Stroke. Vestn. Ross. Akad. Med. Nauk 2016, 71, 304–312. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sandvig, H.V.; Aam, S.; Alme, K.N.; Askim, T.; Beyer, M.K.; Ellekjær, H.; Ihle-Hansen, H.; Lydersen, S.; Mollnes, T.E.; Munthe-Kaas, R.; et al. Plasma Inflammatory Biomarkers Are Associated With Poststroke Cognitive Impairment: The Nor-COAST Study. Stroke 2023, 54, 1303–1311. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, P.; Zhao, M.; Zhang, G.; Zhai, W.; Wang, Y.; Shen, Y.; Sun, L. Plasma inflammatory cytokines are associated with cognitive impairment after acute minor ischemic stroke and transient ischemic attack. Front. Immunol. 2025, 16, 1445938. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Narasimhalu, K.; Lee, J.; Leong, Y.L.; Ma, L.; De Silva, D.A.; Wong, M.C.; Chang, H.M.; Chen, C. Inflammatory markers and their association with post stroke cognitive decline. Int. J. Stroke 2015, 10, 513–518. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, Z.; Zhong, C.; Guo, D.; Bu, X.; Xu, T.; Guo, L.; Liu, J.; Zhang, J.; Li, D.; Zhang, J.; et al. Multiple biomarkers covering several pathways improve predictive ability for cognitive impairment among ischemic stroke patients with elevated blood pressure. Atherosclerosis 2019, 287, 30–37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, Z.; Chen, L.; Guo, D.; Zhong, C.; Wang, A.; Bu, X.; Xu, T.; Zhang, J.; Ju, Z.; Guo, L.; et al. Serum Rheumatoid Factor Levels at Acute Phase of Ischemic Stroke are Associated with Poststroke Cognitive Impairment. J. Stroke Cerebrovasc. Dis. 2019, 28, 1133–1140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sack, G.H., Jr. Serum amyloid A—A review. Mol. Med. 2018, 24, 46. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, J.; Yang, C.; Xv, Q.; Wang, L.; Shen, L.; Lv, Q. Usefulness of Serum Translocator Protein as a Potential Predictive Biochemical Marker of Three-Month Cognitive Impairment After Acute Intracerebral Hemorrhage: A Prospective Observational Cohort Study. Int. J. Gen. Med. 2023, 16, 5389–5403. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, Z.; Yang, W.; Chen, J.; Wang, Q. Circulating HMGB1 in acute ischemic stroke and its association with post-stroke cognitive impairment. PeerJ 2024, 12, e17309. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muhammad, S.; Barakat, W.; Stoyanov, S.; Murikinati, S.; Yang, H.; Tracey, K.J.; Bendszus, M.; Rossetti, G.; Nawroth, P.P.; Bierhaus, A.; et al. The HMGB1 receptor RAGE mediates ischemic brain damage. J. Neurosci. 2008, 28, 12023–12031. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tang, S.C.; Yang, K.C.; Hu, C.J.; Chiou, H.Y.; Wu, C.C.; Jeng, J.S. Elevated Plasma Level of Soluble Form of RAGE in Ischemic Stroke Patients with Dementia. Neuromolecular Med. 2017, 19, 579–583. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, Z.; Yi, X.; Fu, W.; Wu, Y.; Zhong, X.; Fan, C.; Jiang, Y.; Zhou, Q.; Peng, J.; Liao, J.; et al. Higher soluble TREM-1 levels are associated with cognitive impairment after acute ischemic stroke. Front. Aging Neurosci. 2024, 16, 1463065. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, Y.; Zhao, Y.; Lu, Y.; Fang, C.; Zhang, Q.; Zhang, J.; Ju, Z.; Zhang, Y.; Xu, T.; Zhong, C. The association between plasma soluble triggering receptor expressed on myeloid cells 2 and cognitive impairment after acute ischemic stroke. J. Affect. Disord. 2022, 299, 287–293. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Q.; Wang, K.; Ma, Y.; Li, S.; Xu, Y. Serum Galectin-3 as a Potential Predictive Biomarker Is Associated with Poststroke Cognitive Impairment. Oxid. Med. Cell Longev. 2021, 2021, 5827812. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, M.; Lim, J.S.; Kim, C.H.; Lee, S.H.; Kim, Y.; Hun Lee, J.; Jang, M.U.; Sun Oh, M.; Lee, B.C.; Yu, K.H. High Neutrophil-Lymphocyte Ratio Predicts Post-stroke Cognitive Impairment in Acute Ischemic Stroke Patients. Front. Neurol. 2021, 12, 693318. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, W.; Liao, L.; Liu, Q.; Ma, R.; Hu, W.; Dai, Y.; Wang, L.; Sha, D. Predictive value of circulating inflammatory biomarkers for early-onset post-stroke cognitive impairment: A prospective cohort study. Front. Neurol. 2025, 16, 1565613. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gold, A.B.; Herrmann, N.; Swardfager, W.; Black, S.E.; Aviv, R.I.; Tennen, G.; Kiss, A.; Lanctôt, K.L. The relationship between indoleamine 2,3-dioxygenase activity and post-stroke cognitive impairment. J. Neuroinflamm. 2011, 8, 17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gorelick, P.B. Role of inflammation in cognitive impairment: Results of observational epidemiological studies and clinical trials. Ann. N. Y. Acad. Sci. 2010, 1207, 155–162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aletaha, D.; Neogi, T.; Silman, A.J.; Funovits, J.; Felson, D.T.; Bingham, C.O., 3rd; Birnbaum, N.S.; Burmester, G.R.; Bykerk, V.P.; Cohen, M.D.; et al. 2010 Rheumatoid arthritis classification criteria: An American College of Rheumatology/European League Against Rheumatism collaborative initiative. Ann. Rheum. Dis. 2010, 69, 1580–1588, Erratum in Ann. Rheum. Dis. 2010, 69, 1892. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Papadopoulos, V.; Baraldi, M.; Guilarte, T.R.; Knudsen, T.B.; Lacapère, J.J.; Lindemann, P.; Norenberg, M.D.; Nutt, D.; Weizman, A.; Zhang, M.R.; et al. Translocator protein (18kDa): New nomenclature for the peripheral-type benzodiazepine receptor based on its structure and molecular function. Trends Pharmacol. Sci. 2006, 27, 402–409. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dupont, A.C.; Largeau, B.; Santiago Ribeiro, M.J.; Guilloteau, D.; Tronel, C.; Arlicot, N. Translocator Protein-18 kDa (TSPO) Positron Emission Tomography (PET) Imaging and Its Clinical Impact in Neurodegenerative Diseases. Int. J. Mol. Sci. 2017, 18, 785. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, X.; Zhang, J.; Kim, B.; Jaitpal, S.; Meng, S.S.; Adjepong, K.; Imamura, S.; Wake, H.; Nishibori, M.; Stopa, E.G.; et al. High-mobility group box-1 translocation and release after hypoxic ischemic brain injury in neonatal rats. Exp. Neurol. 2019, 311, 1–14. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mazarati, A.; Maroso, M.; Iori, V.; Vezzani, A.; Carli, M. High-mobility group box-1 impairs memory in mice through both toll-like receptor 4 and Receptor for Advanced Glycation End Products. Exp. Neurol. 2011, 232, 143–148. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, Q.W.; Wang, J.Z.; Li, J.C.; Zhou, Y.; Zhong, Q.; Lu, F.L.; Xiang, J. High-mobility group protein box-1 and its relevance to cerebral ischemia. J. Cereb. Blood Flow Metab. 2010, 30, 243–254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alexiou, P.; Chatzopoulou, M.; Pegklidou, K.; Demopoulos, V.J. RAGE: A multi-ligand receptor unveiling novel insights in health and disease. Curr. Med. Chem. 2010, 17, 2232–2252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, W.; Hudson, B.I.; Moser, B.; Guo, J.; Rong, L.L.; Lu, Y.; Qu, W.; Lalla, E.; Lerner, S.; Chen, Y.; et al. Receptor for advanced glycation end products and its ligands: A journey from the complications of diabetes to its pathogenesis. Ann. N. Y. Acad. Sci. 2005, 1043, 553–561. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bouchon, A.; Dietrich, J.; Colonna, M. Cutting edge: Inflammatory responses can be triggered by TREM-1, a novel receptor expressed on neutrophils and monocytes. J. Immunol. 2000, 164, 4991–4995. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Colonna, M.; Facchetti, F. TREM-1 (triggering receptor expressed on myeloid cells): A new player in acute inflammatory responses. J. Infect. Dis. 2003, 187, S397–S401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, P.; Zhang, X.; Liu, Q.; Xie, Y.; Shi, X.; Chen, J.; Li, Y.; Guo, H.; Sun, R.; Hong, Y.; et al. Microglial TREM-1 receptor mediates neuroinflammatory injury via interaction with SYK in experimental ischemic stroke. Cell Death Dis. 2019, 10, 555. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jay, T.R.; von Saucken, V.E.; Landreth, G.E. TREM2 in Neurodegenerative Diseases. Mol. Neurodegener. 2017, 12, 56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhong, L.; Chen, X.F.; Wang, T.; Wang, Z.; Liao, C.; Wang, Z.; Huang, R.; Wang, D.; Li, X.; Wu, L.; et al. Soluble TREM2 induces inflammatory responses and enhances microglial survival. J. Exp. Med. 2017, 214, 597–607. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Almeida, F.; Wolf, J.M.; da Silva, T.A.; DeLeon-Rodriguez, C.M.; Rezende, C.P.; Pessoni, A.M.; Fernandes, F.F.; Silva-Rocha, R.; Martinez, R.; Rodrigues, M.L.; et al. Galectin-3 impacts Cryptococcus neoformans infection through direct antifungal effects. Nat. Commun. 2017, 8, 1968. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rahimian, R.; Béland, L.C.; Kriz, J. Galectin-3: Mediator of microglia responses in injured brain. Drug Discov. Today 2018, 23, 375–381. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dong, R.; Zhang, M.; Hu, Q.; Zheng, S.; Soh, A.; Zheng, Y.; Yuan, H. Galectin-3 as a novel biomarker for disease diagnosis and a target for therapy (Review). Int. J. Mol. Med. 2018, 41, 599–614. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Franke, M.; Bieber, M.; Kraft, P.; Weber, A.N.R.; Stoll, G.; Schuhmann, M.K. The NLRP3 inflammasome drives inflammation in ischemia/reperfusion injury after transient middle cerebral artery occlusion in mice. Brain Behav. Immun. 2021, 92, 223–233. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lan, T.; Wang, C.; Yan, Y.; Yang, T.; Cui, J.; Lei, R.; Luo, R.; Jiang, S.; Wu, B. Plasma GFAP and NLRP3 Associate with Cognitive Impairment After Recent Small Subcortical Infarct via Periventricular White Matter Hyperintensity. CNS Neurosci. Ther. 2026, 32, e70780. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kostulas, N.; Pelidou, S.H.; Kivisäkk, P.; Kostulas, V.; Link, H. Increased IL-1beta, IL-8, and IL-17 mRNA expression in blood mononuclear cells observed in a prospective ischemic stroke study. Stroke 1999, 30, 2174–2179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Widner, B.; Laich, A.; Sperner-Unterweger, B.; Ledochowski, M.; Fuchs, D. Neopterin production, tryptophan degradation, and mental depression--what is the link? Brain Behav. Immun. 2002, 16, 590–595. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fukai, T.; Ushio-Fukai, M. Superoxide dismutases: Role in redox signaling, vascular function, and diseases. Antioxid. Redox Signal 2011, 15, 1583–1606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, M.S.; Liang, J.H.; Yang, M.J.; Ren, Y.R.; Cheng, D.H.; Wu, Q.H.; He, Y.; Yin, J. Low Serum Superoxide Dismutase Is Associated With a High Risk of Cognitive Impairment After Mild Acute Ischemic Stroke. Front. Aging Neurosci. 2022, 14, 834114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wei, C.; Zhao, P.; Zhai, W.; Zhao, M.; Sun, L. Prediction of Post-Stroke Cognitive Impairment Based on Iron Metabolism Parameters: Results From A Prospective Study. Mol. Neurobiol. 2025, 62, 13352–13362. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, Z.; Liu, Y.; Tu, X.; Shen, H.; Qiu, H.; Chen, H.; He, J. High Serum Levels of Malondialdehyde and 8-OHdG are both Associated with Early Cognitive Impairment in Patients with Acute Ischaemic Stroke. Sci. Rep. 2017, 7, 9493. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, Y.; Jia, Y.; Liu, Y.; Chang, X.; Yang, P.; Shi, M.; Guo, D.; Peng, Y.; Chen, J.; Wang, A.; et al. High Plasma Polyamine Levels Are Associated With an Increased Risk of Poststroke Cognitive Impairment: A Multicenter Prospective Study From CATIS. J. Am. Heart Assoc. 2025, 14, e037465. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, S.; Liao, X.; Pan, Y.; Xiang, X.; Zhang, Y. Gamma-glutamyl transferase levels are associated with the occurrence of post-stroke cognitive impairment: A multicenter cohort study. BMC Neurol. 2022, 22, 65. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, X.; Zhu, Z.; Guo, D.; Zhong, C.; Xu, T.; Peng, Y.; Wang, A.; Peng, H.; Ju, Z.; Geng, D.; et al. Prognostic value of plasma fibroblast growth factor 21 among patients with acute ischemic stroke. Eur. J. Neurol. 2021, 28, 844–851. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, X.; Zhu, Z.; Zhong, C.; Guo, D.; Bu, X.; Peng, H.; Xu, T.; Zhang, Y. Plasma fibroblast growth factor 21 and risk of cognitive impairment among patients with ischemic stroke. Neuroscience 2024, 563, 129–135. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheng, Y.; Zhu, H.; Chen, J.; Li, L.; Liu, C.; Gao, Y.; Sun, D. Serum TG/HDL-C level at the acute phase of ischemic stroke is associated with post-stroke cognitive impairment. Neurol. Sci. 2022, 43, 5977–5984. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheng, Y.; Zhu, H.; Sun, D.; Li, L.; Liu, C.; Sun, S.; Guo, Y.; Gu, C.; Gao, Y.; He, G.; et al. High triglyceride-glucose index at admission is a predictor of post-stroke cognitive impairment in patients with acute ischemic stroke. J. Stroke Cerebrovasc. Dis. 2024, 33, 107510. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- You, S.; Bi, Y.; Miao, M.; Bao, A.; Du, J.; Xu, T.; Liu, C.F.; Zhang, Y.; He, J.; Cao, Y.; et al. Plasma sDPP4 (Soluble Dipeptidyl Peptidase-4) and Cognitive Impairment After Noncardioembolic Acute Ischemic Stroke. Stroke 2023, 54, 113–121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Che, B.; Chen, H.; Wang, A.; Peng, H.; Bu, X.; Zhang, J.; Ju, Z.; Xu, T.; He, J.; Zhong, C.; et al. Association Between Plasma L-Carnitine and Cognitive Impairment in Patients with Acute Ischemic Stroke. J. Alzheimers Dis. 2022, 86, 259–270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lan, C.; Huang, Z.; Luo, X.; Zhang, Y. The Correlations Between Serum Hcy Level and Seizures and Cognitive Function in Patients After Stroke. Am. J. Alzheimers Dis. Other Demen 2022, 37, 15333175221146738. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khedr, E.M.; Hamed, S.A.; El-Shereef, H.K.; Shawky, O.A.; Mohamed, K.A.; Awad, E.M.; Ahmed, M.A.; Shehata, G.A.; Eltahtawy, M.A. Cognitive impairment after cerebrovascular stroke: Relationship to vascular risk factors. Neuropsychiatr. Dis. Treat. 2009, 5, 103–116. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, J.; Lv, X.; Gao, X.; Chen, Z.; Wei, D.; Ling, Y.; Zhang, J.; Gu, Q.; Liu, J.; Chen, W.; et al. The association between serum uric acid level and the risk of cognitive impairment after ischemic stroke. Neurosci. Lett. 2020, 734, 135098. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, L.; Ouyang, Q.R.; Xiong, Q.; Huang, L.W.; Yu, M. Elevated serum uric acid is associated with cognitive impairment in acute minor ischemic stroke patients. Heliyon 2023, 9, e21072. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liao, L.; Huang, W.; Ma, R.; Hu, W.; Wu, H.; Su, M.; Sha, D. Serum uric acid to creatinine ratio in patients with early-onset post-stroke cognitive impairment: A retrospective cohort study. Front. Aging Neurosci. 2025, 17, 1580722. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, C.; Li, G.; Lv, Z.; Li, J.; Wang, X.; Kang, J.; Zhan, C. Association of plasma trimethylamine-N-oxide levels with post-stroke cognitive impairment: A 1-year longitudinal study. Neurol. Sci. 2020, 41, 57–63. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, Y.; Chen, Z.; Chen, K.; Xiong, F.; Gao, H. Spatiotemporal profiling of secondary neurodegeneration in a mouse model of cortical stroke: Role of N-acetylneuraminic acid. Neural Regen. Res. 2026, 21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sandvig, H.V.; Aam, S.; Alme, K.N.; Lydersen, S.; Magne Ueland, P.; Ulvik, A.; Wethal, T.; Saltvedt, I.; Knapskog, A.B. Neopterin, kynurenine metabolites, and indexes related to vitamin B6 are associated with post-stroke cognitive impairment: The Nor-COAST study. Brain Behav. Immun. 2024, 118, 167–177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cogo, A.; Mangin, G.; Maïer, B.; Callebert, J.; Mazighi, M.; Chabriat, H.; Launay, J.M.; Huberfeld, G.; Kubis, N. Increased serum QUIN/KYNA is a reliable biomarker of post-stroke cognitive decline. Mol. Neurodegener. 2021, 16, 7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chang, Y.T.; Chang, W.N.; Tsai, N.W.; Huang, C.C.; Kung, C.T.; Su, Y.J.; Lin, W.C.; Cheng, B.C.; Su, C.M.; Chiang, Y.F.; et al. The roles of biomarkers of oxidative stress and antioxidant in Alzheimer’s disease: A systematic review. BioMed Res. Int. 2014, 2014, 182303. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Newton, D.F.; Naiberg, M.R.; Goldstein, B.I. Oxidative stress and cognition amongst adults without dementia or stroke: Implications for mechanistic and therapeutic research in psychiatric disorders. Psychiatry Res. 2015, 227, 127–134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schibalski, R.S.; Shulha, A.S.; Tsao, B.P.; Palygin, O.; Ilatovskaya, D.V. The role of polyamine metabolism in cellular function and physiology. Am. J. Physiol. Cell Physiol. 2024, 327, C341–c356. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Koenig, G.; Seneff, S. Gamma-Glutamyltransferase: A Predictive Biomarker of Cellular Antioxidant Inadequacy and Disease Risk. Dis. Markers 2015, 2015, 818570. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Casolla, B.; Caparros, F.; Cordonnier, C.; Bombois, S.; Hénon, H.; Bordet, R.; Orzi, F.; Leys, D. Biological and imaging predictors of cognitive impairment after stroke: A systematic review. J. Neurol. 2019, 266, 2593–2604. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seo, J.A.; Kim, N.H. Fibroblast growth factor 21: A novel metabolic regulator. Diabetes Metab. J. 2012, 36, 26–28. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, M.; Chen, L.; Hu, Y.; Wu, J.; Wu, Z.; Yang, S.; Kang, W.; He, J.; Ren, W. The HALP (hemoglobin, albumin, lymphocyte, and platelet) score is associated with early-onset post-stroke cognitive impairment. Neurol. Sci. 2023, 44, 237–245. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Prajapati, K.D.; Sharma, S.S.; Roy, N. Current perspectives on potential role of albumin in neuroprotection. Rev. Neurosci. 2011, 22, 355–363. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nair, R.; Radhakrishnan, K.; Chatterjee, A.; Gorthi, S.P.; Prabhu, V.A. Serum Albumin as a Predictor of Functional Outcomes Following Acute Ischemic Stroke. J. Vasc. Interv. Neurol. 2018, 10, 65–68. [Google Scholar] [PubMed]
- Salazar, M.R.; Carbajal, H.A.; Espeche, W.G.; Leiva Sisnieguez, C.E.; Balbín, E.; Dulbecco, C.A.; Aizpurúa, M.; Marillet, A.G.; Reaven, G.M. Relation among the plasma triglyceride/high-density lipoprotein cholesterol concentration ratio, insulin resistance, and associated cardio-metabolic risk factors in men and women. Am. J. Cardiol. 2012, 109, 1749–1753. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Onat, A.; Can, G.; Kaya, H.; Hergenç, G. “Atherogenic index of plasma” (log10 triglyceride/high-density lipoprotein-cholesterol) predicts high blood pressure, diabetes, and vascular events. J. Clin. Lipidol. 2010, 4, 89–98. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, A.; Wang, G.; Liu, Q.; Zuo, Y.; Chen, S.; Tao, B.; Tian, X.; Wang, P.; Meng, X.; Wu, S.; et al. Triglyceride-glucose index and the risk of stroke and its subtypes in the general population: An 11-year follow-up. Cardiovasc. Diabetol. 2021, 20, 46. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Durinx, C.; Lambeir, A.M.; Bosmans, E.; Falmagne, J.B.; Berghmans, R.; Haemers, A.; Scharpé, S.; De Meester, I. Molecular characterization of dipeptidyl peptidase activity in serum: Soluble CD26/dipeptidyl peptidase IV is responsible for the release of X-Pro dipeptides. Eur. J. Biochem. 2000, 267, 5608–5613. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lambeir, A.M.; Durinx, C.; Scharpé, S.; De Meester, I. Dipeptidyl-peptidase IV from bench to bedside: An update on structural properties, functions, and clinical aspects of the enzyme DPP IV. Crit. Rev. Clin. Lab. Sci. 2003, 40, 209–294. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ma, M.; Hasegawa, Y.; Koibuchi, N.; Toyama, K.; Uekawa, K.; Nakagawa, T.; Lin, B.; Kim-Mitsuyama, S. DPP-4 inhibition with linagliptin ameliorates cognitive impairment and brain atrophy induced by transient cerebral ischemia in type 2 diabetic mice. Cardiovasc. Diabetol. 2015, 14, 54. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hermann, A.; Sitdikova, G. Homocysteine: Biochemistry, Molecular Biology and Role in Disease. Biomolecules 2021, 11, 737. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seshadri, S.; Beiser, A.; Selhub, J.; Jacques, P.F.; Rosenberg, I.H.; D’Agostino, R.B.; Wilson, P.W.; Wolf, P.A. Plasma homocysteine as a risk factor for dementia and Alzheimer’s disease. N. Engl. J. Med. 2002, 346, 476–483. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dufouil, C.; Alpérovitch, A.; Ducros, V.; Tzourio, C. Homocysteine, white matter hyperintensities, and cognition in healthy elderly people. Ann. Neurol. 2003, 53, 214–221. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amaro, S.; Llull, L.; Renú, A.; Laredo, C.; Perez, B.; Vila, E.; Torres, F.; Planas, A.M.; Chamorro, Á. Uric acid improves glucose-driven oxidative stress in human ischemic stroke. Ann. Neurol. 2015, 77, 775–783. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, A.; Zou, T.; Xiong, G.; Zhang, J. Association of uric acid with traditional inflammatory factors in stroke. Int. J. Neurosci. 2016, 126, 335–341. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Song, C.; Zhao, X. Uric acid promotes oxidative stress and enhances vascular endothelial cell apoptosis in rats with middle cerebral artery occlusion. Biosci. Rep. 2018, 38, BSR20170939. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Han, Y.-G.; Qin, X.; Zhang, T.; Lei, M.; Sun, F.-Y.; Sun, J.-J.; Yuan, W.-F. Electroacupuncture prevents cognitive impairment induced by lipopolysaccharide via inhibition of oxidative stress and neuroinflammation. Neurosci. Lett. 2018, 683, 190–195. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tang, W.H.; Wang, Z.; Fan, Y.; Levison, B.; Hazen, J.E.; Donahue, L.M.; Wu, Y.; Hazen, S.L. Prognostic value of elevated levels of intestinal microbe-generated metabolite trimethylamine-N-oxide in patients with heart failure: Refining the gut hypothesis. J. Am. Coll. Cardiol. 2014, 64, 1908–1914. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, C.; Li, C.; Zhao, W.; Xie, N.; Yan, F.; Lian, Y.; Zhou, L.; Xu, X.; Liang, Y.; Wang, L.; et al. Elevated trimethylamine N-oxide related to ischemic brain lesions after carotid artery stenting. Neurology 2018, 90, e1283–e1290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ulvik, A.; Midttun, Ø.; Pedersen, E.R.; Eussen, S.J.; Nygård, O.; Ueland, P.M. Evidence for increased catabolism of vitamin B-6 during systemic inflammation. Am. J. Clin. Nutr. 2014, 100, 250–255. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van den Steen, P.E.; Dubois, B.; Nelissen, I.; Rudd, P.M.; Dwek, R.A.; Opdenakker, G. Biochemistry and molecular biology of gelatinase B or matrix metalloproteinase-9 (MMP-9). Crit. Rev. Biochem. Mol. Biol. 2002, 37, 375–536. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gidday, J.M.; Gasche, Y.G.; Copin, J.C.; Shah, A.R.; Perez, R.S.; Shapiro, S.D.; Chan, P.H.; Park, T.S. Leukocyte-derived matrix metalloproteinase-9 mediates blood-brain barrier breakdown and is proinflammatory after transient focal cerebral ischemia. Am. J. Physiol. Heart Circ. Physiol. 2005, 289, H558–H568. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, X.; Jung, J.; Asahi, M.; Chwang, W.; Russo, L.; Moskowitz, M.A.; Dixon, C.E.; Fini, M.E.; Lo, E.H. Effects of matrix metalloproteinase-9 gene knock-out on morphological and motor outcomes after traumatic brain injury. J. Neurosci. 2000, 20, 7037–7042. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhong, C.; Bu, X.; Xu, T.; Guo, L.; Wang, X.; Zhang, J.; Cui, Y.; Li, D.; Zhang, J.; Ju, Z.; et al. Serum Matrix Metalloproteinase-9 and Cognitive Impairment After Acute Ischemic Stroke. J. Am. Heart Assoc. 2018, 7, e007776. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ge, J.; Li, R.; Yuan, P.; Che, B.; Bu, X.; Shao, H.; Xu, T.; Ju, Z.; Zhang, J.; Zhang, Y.; et al. Serum tissue inhibitor of metalloproteinase-1 and risk of cognitive impairment after acute ischaemic stroke. J. Cell. Mol. Med. 2020, 24, 7470–7478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Giesers, N.K.; Schaeff, V.; Gertz, K.; Endres, M.; Liman, T.G. Associations of Soluble Inflammatory and Endothelial Activation Biomarkers with Cognitive Function Over Three Years After Ischemic Stroke-PROSCIS-B. Transl. Stroke Res. 2025, 16, 2249–2257. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zuo, L.; Dong, Y.; Pan, Y.; Yan, H.; Meng, X.; Li, H.; Zhao, X.; Wang, Y.; Wang, Y.; Liao, X. Impact of Serum Cystatin C Level on Long-Term Cognitive Impairment After Acute Ischemic Stroke and Transient Ischemic Attack. Neuropsychiatr. Dis. Treat. 2023, 19, 1543–1554. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yan, X.; Chen, H.; Shang, X.L. Association between serum cystatin C level and post-stroke cognitive impairment in patients with acute mild ischemic stroke. Brain Behav. 2022, 12, e2519. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Prodjohardjono, A.; Vidyanti, A.N.; Susianti, N.A.; Sudarmanta; Sutarni, S.; Setyopranoto, I. Higher level of acute serum VEGF and larger infarct volume are more frequently associated with post-stroke cognitive impairment. PLoS ONE 2020, 15, e0239370. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qian, S.; Li, R.; Zhang, C.; Zhang, R.; Guo, D.; Bu, X.; Wang, A.; Peng, H.; Chen, J.; Zhang, Y.; et al. Plasma Endostatin Levels at Acute Phase of Ischemic Stroke Are Associated with Post-Stroke Cognitive Impairment. Neurotox. Res. 2020, 37, 956–964. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jia, H.; Li, H.; Liu, Y.; Liu, C.; Xue, M. Elevated serum alkaline phosphatase as a predictor of cognitive impairment in patients with acute ischaemic stroke: A retrospective cohort study. Arch. Gerontol. Geriatr. 2020, 89, 104104. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chang, X.; Yang, P.; Liu, Y.; He, Y.; Qin, X.; Song, B.; Yu, Q.; Fei, J.; Shi, M.; Guo, D.; et al. Plasma Osteoprotegerin and Cognitive Impairment after Ischemic Stroke. Curr. Neurovasc. Res. 2025, 21, 545–553. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, Y.; Chen, H.; Zhao, K.; He, W.; Lin, S.; He, J. High levels of plasma fibrinogen are related to post-stroke cognitive impairment. Brain Behav. 2019, 9, e01391. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pedersen, A.; Stanne, T.M.; Redfors, P.; Viken, J.; Samuelsson, H.; Nilsson, S.; Jood, K.; Jern, C. Fibrinogen concentrations predict long-term cognitive outcome in young ischemic stroke patients. Res. Pract. Thromb. Haemost. 2018, 2, 339–346. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, W.; Ruan, Y.; Yuan, C.; Luan, X.; He, J. Hemoglobin, anemia, and poststroke cognitive impairment: A cohort study. Int. J. Geriatr. Psychiatry 2020, 35, 564–571. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meng, F.; Zhang, S.; Yu, J.; Chen, Y.; Luo, L.; He, F.; Wei, R.; Yuan, H.; Ji, R.; Chen, H.; et al. Low Hemoglobin Levels at Admission Are Independently Associated with Cognitive Impairment after Ischemic Stroke: A Multicenter, Population-Based Study. Transl. Stroke Res. 2020, 11, 890–899. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jia, W.; Jia, Q.; Pan, Y.; Xiang, X.; Liao, X.; Zhao, X.; Wang, Y.; Zhang, Y. Relationship between baseline haemoglobin content and poststroke cognitive impairment. J. Clin. Neurosci. 2022, 101, 212–216. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- He, Y.; Chang, X.; Liu, Y.; Fei, J.; Qin, X.; Song, B.; Yu, Q.; Shi, M.; Guo, D.; Chen, J.; et al. High plasma thrombomodulin level is associated with a decreased risk of cognitive impairment after ischemic stroke. J. Stroke Cerebrovasc. Dis. 2025, 34, 108172. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rosenberg, G.A. Matrix metalloproteinases and their multiple roles in neurodegenerative diseases. Lancet Neurol. 2009, 8, 205–216. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, H.; Angert, M.; Nishihara, T.; Shubayev, I.; Dolkas, J.; Shubayev, V.I. Spinal Glia Division Contributes to Conditioning Lesion-Induced Axon Regeneration Into the Injured Spinal Cord: Potential Role of Cyclic AMP-Induced Tissue Inhibitor of Metalloproteinase-1. J. Neuropathol. Exp. Neurol. 2015, 74, 500–511. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Romero, J.R.; Vasan, R.S.; Beiser, A.S.; Au, R.; Benjamin, E.J.; DeCarli, C.; Wolf, P.A.; Seshadri, S. Association of matrix metalloproteinases with MRI indices of brain ischemia and aging. Neurobiol. Aging 2010, 31, 2128–2135. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, T.J.; Kang, M.K.; Jeong, H.G.; Kim, C.K.; Kim, Y.; Nam, K.W.; Mo, H.; An, S.J.; Ko, S.B.; Yoon, B.W. Cystatin C is a useful predictor of early neurological deterioration following ischaemic stroke in elderly patients with normal renal function. Eur. Stroke J. 2017, 2, 23–30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Helmersson-Karlqvist, J.; Ärnlöv, J.; Carlsson, A.C.; Härmä, J.; Larsson, A. Increased urinary cystatin C indicated higher risk of cardiovascular death in a community cohort. Atherosclerosis 2014, 234, 108–113. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, S.C.; Lee, K.Y.; Kim, Y.J.; Kim, S.H.; Koh, S.H.; Lee, Y.J. Serum VEGF levels in acute ischaemic strokes are correlated with long-term prognosis. Eur. J. Neurol. 2010, 17, 45–51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, Z.G.; Zhang, L.; Tsang, W.; Soltanian-Zadeh, H.; Morris, D.; Zhang, R.; Goussev, A.; Powers, C.; Yeich, T.; Chopp, M. Correlation of VEGF and angiopoietin expression with disruption of blood-brain barrier and angiogenesis after focal cerebral ischemia. J. Cereb. Blood Flow Metab. 2002, 22, 379–392. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Geiseler, S.J.; Morland, C. The Janus Face of VEGF in Stroke. Int. J. Mol. Sci. 2018, 19, 1362. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Slevin, M.; Krupinski, J.; Slowik, A.; Kumar, P.; Szczudlik, A.; Gaffney, J. Serial measurement of vascular endothelial growth factor and transforming growth factor-beta1 in serum of patients with acute ischemic stroke. Stroke 2000, 31, 1863–1870. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Reilly, M.S.; Boehm, T.; Shing, Y.; Fukai, N.; Vasios, G.; Lane, W.S.; Flynn, E.; Birkhead, J.R.; Olsen, B.R.; Folkman, J. Endostatin: An endogenous inhibitor of angiogenesis and tumor growth. Cell 1997, 88, 277–285. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Buchet, R.; Millán, J.L.; Magne, D. Multisystemic functions of alkaline phosphatases. Methods Mol. Biol. 2013, 1053, 27–51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moss, D.W. Physicochemical and pathophysiological factors in the release of membrane-bound alkaline phosphatase from cells. Clin. Chim. Acta 1997, 257, 133–140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Simonet, W.S.; Lacey, D.L.; Dunstan, C.R.; Kelley, M.; Chang, M.S.; Lüthy, R.; Nguyen, H.Q.; Wooden, S.; Bennett, L.; Boone, T.; et al. Osteoprotegerin: A novel secreted protein involved in the regulation of bone density. Cell 1997, 89, 309–319. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Collin-Osdoby, P. Regulation of vascular calcification by osteoclast regulatory factors RANKL and osteoprotegerin. Circ. Res. 2004, 95, 1046–1057. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tampubolon, G. Repeated systemic inflammation was associated with cognitive deficits in older Britons. Alzheimers Dement. 2016, 3, 1–6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zang, R.S.; Zhang, H.; Xu, Y.; Zhang, S.M.; Liu, X.; Wang, J.; Gao, Y.Z.; Shu, M.; Mei, B.; Li, H.G. Serum C-reactive protein, fibrinogen and D-dimer in patients with progressive cerebral infarction. Transl. Neurosci. 2016, 7, 84–88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schachtrup, C.; Ryu, J.K.; Helmrick, M.J.; Vagena, E.; Galanakis, D.K.; Degen, J.L.; Margolis, R.U.; Akassoglou, K. Fibrinogen triggers astrocyte scar formation by promoting the availability of active TGF-beta after vascular damage. J. Neurosci. 2010, 30, 5843–5854. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tan, B.; Venketasubramanian, N.; Vrooman, H.; Cheng, C.Y.; Wong, T.Y.; Chen, C.; Hilal, S. Haemoglobin, magnetic resonance imaging markers and cognition: A subsample of population-based study. Alzheimers Res. Ther. 2018, 10, 114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ito, T.; Maruyama, I. Thrombomodulin: Protectorate God of the vasculature in thrombosis and inflammation. J. Thromb. Haemost. 2011, 9, 168–173. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ito, T.; Thachil, J.; Asakura, H.; Levy, J.H.; Iba, T. Thrombomodulin in disseminated intravascular coagulation and other critical conditions-a multi-faceted anticoagulant protein with therapeutic potential. Crit. Care 2019, 23, 280. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wenzel, J.; Assmann, J.C.; Schwaninger, M. Thrombomodulin--a new target for treating stroke at the crossroad of coagulation and inflammation. Curr. Med. Chem. 2014, 21, 2025–2034. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, J.; Liem, R.K. α-Internexin and Peripherin: Expression, Assembly, Functions, and Roles in Disease. Methods Enzymol. 2016, 568, 477–507. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pekny, M.; Wilhelmsson, U.; Stokowska, A.; Tatlisumak, T.; Jood, K.; Pekna, M. Neurofilament Light Chain (NfL) in Blood-A Biomarker Predicting Unfavourable Outcome in the Acute Phase and Improvement in the Late Phase after Stroke. Cells 2021, 10, 1537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zetterberg, H. Neurofilament Light: A Dynamic Cross-Disease Fluid Biomarker for Neurodegeneration. Neuron 2016, 91, 1–3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tiedt, S.; Duering, M.; Barro, C.; Kaya, A.G.; Boeck, J.; Bode, F.J.; Klein, M.; Dorn, F.; Gesierich, B.; Kellert, L.; et al. Serum neurofilament light: A biomarker of neuroaxonal injury after ischemic stroke. Neurology 2018, 91, e1338–e1347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jiang, L.; Wang, Z.; Wang, R.; Li, M.; Zhang, Y.; Yang, D. Plasma Neurofilament Light Chain Is Associated with Cognitive Impairment after Posterior Circulation Stroke. Evid. Based Complement. Altern. Med. 2022, 2022, 2466982. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shaw, G.; Yang, C.; Ellis, R.; Anderson, K.; Parker Mickle, J.; Scheff, S.; Pike, B.; Anderson, D.K.; Howland, D.R. Hyperphosphorylated neurofilament NF-H is a serum biomarker of axonal injury. Biochem. Biophys. Res. Commun. 2005, 336, 1268–1277. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qiao, H.; Wang, S.; Tao, M.; Fan, H.; Zhao, T.; Du, Y.; Dong, M. Serum neurofilament heavy chain predicts post-stroke cognitive impairment. Sci. Rep. 2025, 15, 13556. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chi, N.F.; Chao, S.P.; Huang, L.K.; Chan, L.; Chen, Y.R.; Chiou, H.Y.; Hu, C.J. Plasma Amyloid Beta and Tau Levels Are Predictors of Post-stroke Cognitive Impairment: A Longitudinal Study. Front. Neurol. 2019, 10, 715. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, L.K.; Chao, S.P.; Hu, C.J.; Chien, L.N.; Chiou, H.Y.; Lo, Y.C.; Hsieh, Y.C. Plasma Phosphorylated-tau181 Is a Predictor of Post-stroke Cognitive Impairment: A Longitudinal Study. Front. Aging Neurosci. 2022, 14, 889101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tang, S.C.; Yang, K.C.; Chen, C.H.; Yang, S.Y.; Chiu, M.J.; Wu, C.C.; Jeng, J.S. Plasma β-Amyloids and Tau Proteins in Patients with Vascular Cognitive Impairment. Neuromolecular Med. 2018, 20, 498–503. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mao, L.; Chen, X.H.; Zhuang, J.H.; Li, P.; Xu, Y.X.; Zhao, Y.C.; Ma, Y.J.; He, B.; Yin, Y. Relationship between β-amyloid protein 1-42, thyroid hormone levels and the risk of cognitive impairment after ischemic stroke. World J. Clin. Cases 2020, 8, 76–87. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shan, W.; Jiang, R.; Wang, J.; Xu, G.; Zhao, J.; Zhai, G.; Shao, J. High serum glial fibrillary acidic protein levels are associated with increased risk of post-stroke cognitive impairment. Front. Aging Neurosci. 2025, 17, 1546270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gao, Y.; Wang, B.; Miao, Y.; Han, Y. Serum Neuroglobin as a Potential Prognostic Biomarker for Cognitive Impairment After Intracerebral Hemorrhage. Front. Neurol. 2022, 13, 885323. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chang, X.; You, J.; Yang, P.; He, Y.; Liu, Y.; Shi, M.; Guo, D.; Peng, Y.; Chen, J.; Wang, A.; et al. High-Serum Brain-Derived Neurotrophic Factor Levels Are Associated With Decreased Risk of Poststroke Cognitive Impairment. Stroke 2024, 55, 643–650. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, J.; Ma, W.; Gu, S. Exploring the Relationship Between Serum Neuronal Pentraxin 2 and Poststroke Cognitive Impairment in Patients With First-Episode Acute Ischemic Stroke. Brain Behav. 2025, 15, e70305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hou, L.; Ding, C.; Chen, Z.; Liu, Y.; Shi, H.; Zou, C.; Zhang, H.; Lu, Z.; Zheng, D. Serum Retinoic Acid Level and The Risk of Poststroke Cognitive Impairment in Ischemic Stroke Patients. J. Stroke Cerebrovasc. Dis. 2019, 28, 104352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qian, L.; Ding, L.; Cheng, L.; Zhu, X.; Zhao, H.; Jin, J.; Guan, D.; Zhang, B.; Chen, X.; Xu, Y. Early biomarkers for post-stroke cognitive impairment. J. Neurol. 2012, 259, 2111–2118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dong, W.; Lu, Y.; Zhai, Y.; Bi, Y.; Peng, Y.; Ju, Z.; Xu, T.; Zhong, X.; Zhang, Y.; Zhong, C. Plasma neuropeptide Y and cognitive impairment after acute ischemic stroke. J. Affect. Disord. 2022, 317, 221–227. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, J.; Zhi, W.; Wang, L. Role of Tau Protein in Neurodegenerative Diseases and Development of Its Targeted Drugs: A Literature Review. Molecules 2024, 29, 2812. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Nostrand, W.E.; Davis, J.; Previti, M.L.; Xu, F. Clearance of amyloid-β protein deposits in transgenic mice following focal cerebral ischemia. Neurodegener. Dis. 2012, 10, 108–111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goulay, R.; Mena Romo, L.; Hol, E.M.; Dijkhuizen, R.M. From Stroke to Dementia: A Comprehensive Review Exposing Tight Interactions Between Stroke and Amyloid-β Formation. Transl. Stroke Res. 2020, 11, 601–614. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, H.; Gu, S.; Liu, X.; Xie, A.; Wang, C. Association of Blood Amyloid Beta-Protein 1-42 with Poststroke Cognitive Impairment: A Systematic Review and Meta-Analysis. BioMed Res. Int. 2022, 2022, 6552781. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, M.; Wang, H.; Wang, M. The correlation of serum Aβ1-42 concentration and cognitive impairment after ischemic stroke. Mod. Med. J. China 2016, 18, 9–12. [Google Scholar]
- Fandos, N.; Pérez-Grijalba, V.; Pesini, P.; Olmos, S.; Bossa, M.; Villemagne, V.L.; Doecke, J.; Fowler, C.; Masters, C.L.; Sarasa, M. Plasma amyloid β 42/40 ratios as biomarkers for amyloid β cerebral deposition in cognitively normal individuals. Alzheimers Dement. 2017, 8, 179–187. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eng, L.F.; Ghirnikar, R.S.; Lee, Y.L. Glial fibrillary acidic protein: GFAP-thirty-one years (1969–2000). Neurochem. Res. 2000, 25, 1439–1451. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Middeldorp, J.; Hol, E.M. GFAP in health and disease. Prog. Neurobiol. 2011, 93, 421–443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Foerch, C.; Niessner, M.; Back, T.; Bauerle, M.; De Marchis, G.M.; Ferbert, A.; Grehl, H.; Hamann, G.F.; Jacobs, A.; Kastrup, A.; et al. Diagnostic accuracy of plasma glial fibrillary acidic protein for differentiating intracerebral hemorrhage and cerebral ischemia in patients with symptoms of acute stroke. Clin. Chem. 2012, 58, 237–245. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ciccone, L.; Nencetti, S.; Socci, S.; Orlandini, E. Neuroglobin and neuroprotection: The role of natural and synthetic compounds in neuroglobin pharmacological induction. Neural Regen. Res. 2021, 16, 2353–2358. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Y.; Li, F.; Qin, D.; Chen, H.; Wang, J.; Wang, J.; Song, S.; Wang, C.; Wang, Y.; Liu, S.; et al. The role of brain derived neurotrophic factor in central nervous system. Front. Aging Neurosci. 2022, 14, 986443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lu, B.; Nagappan, G.; Guan, X.; Nathan, P.J.; Wren, P. BDNF-based synaptic repair as a disease-modifying strategy for neurodegenerative diseases. Nat. Rev. Neurosci. 2013, 14, 401–416. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kapogiannis, D.; Mattson, M.P. Disrupted energy metabolism and neuronal circuit dysfunction in cognitive impairment and Alzheimer’s disease. Lancet Neurol. 2011, 10, 187–198. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chapman, G.; Shanmugalingam, U.; Smith, P.D. The Role of Neuronal Pentraxin 2 (NP2) in Regulating Glutamatergic Signaling and Neuropathology. Front. Cell Neurosci. 2019, 13, 575. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sia, G.M.; Béïque, J.C.; Rumbaugh, G.; Cho, R.; Worley, P.F.; Huganir, R.L. Interaction of the N-terminal domain of the AMPA receptor GluR4 subunit with the neuronal pentraxin NP1 mediates GluR4 synaptic recruitment. Neuron 2007, 55, 87–102, Erratum in Neuron 2007, 55, 533. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Brien, R.J.; Xu, D.; Petralia, R.S.; Steward, O.; Huganir, R.L.; Worley, P. Synaptic clustering of AMPA receptors by the extracellular immediate-early gene product Narp. Neuron 1999, 23, 309–323. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nohara, A.; Kobayashi, J.; Mabuchi, H. Retinoid X receptor heterodimer variants and cardiovascular risk factors. J. Atheroscler. Thromb. 2009, 16, 303–318. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Blomhoff, R.; Blomhoff, H.K. Overview of retinoid metabolism and function. J. Neurobiol. 2006, 66, 606–630. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tu, W.J.; Qiu, H.C.; Zhang, Y.; Cao, J.L.; Wang, H.; Zhao, J.Z.; Liu, Q.; Zeng, X. Lower serum retinoic acid level for prediction of higher risk of mortality in ischemic stroke. Neurology 2019, 92, e1678–e1687. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, H.; Wu, Y.; Huang, G.; He, W.; Lin, S.; Zhang, X.; He, J. Low Tri-iodothyronine Syndrome Is Associated With Cognitive Impairment in Patients With Acute Ischemic Stroke: A Prospective Cohort Study. Am. J. Geriatr. Psychiatry 2018, 26, 1222–1230. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Duarte-Neves, J.; Pereira de Almeida, L.; Cavadas, C. Neuropeptide Y (NPY) as a therapeutic target for neurodegenerative diseases. Neurobiol. Dis. 2016, 95, 210–224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Flood, J.F.; Hernandez, E.N.; Morley, J.E. Modulation of memory processing by neuropeptide Y. Brain Res. 1987, 421, 280–290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rangani, R.J.; Upadhya, M.A.; Nakhate, K.T.; Kokare, D.M.; Subhedar, N.K. Nicotine evoked improvement in learning and memory is mediated through NPY Y1 receptors in rat model of Alzheimer’s disease. Peptides 2012, 33, 317–328. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Borbély, E.; Scheich, B.; Helyes, Z. Neuropeptides in learning and memory. Neuropeptides 2013, 47, 439–450, Erratum in Neuropeptides 2014, 48, 107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- György, B.; Hung, M.E.; Breakefield, X.O.; Leonard, J.N. Therapeutic applications of extracellular vesicles: Clinical promise and open questions. Annu. Rev. Pharmacol. Toxicol. 2015, 55, 439–464. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reid, G.; Kirschner, M.B.; van Zandwijk, N. Circulating microRNAs: Association with disease and potential use as biomarkers. Crit. Rev. Oncol. Hematol. 2011, 80, 193–208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mitchell, P.S.; Parkin, R.K.; Kroh, E.M.; Fritz, B.R.; Wyman, S.K.; Pogosova-Agadjanyan, E.L.; Peterson, A.; Noteboom, J.; O’Briant, K.C.; Allen, A.; et al. Circulating microRNAs as stable blood-based markers for cancer detection. Proc. Natl. Acad. Sci. USA 2008, 105, 10513–10518. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhai, W.; Zhao, M.; Wei, C.; Zhang, G.; Qi, Y.; Zhao, A.; Sun, L. Biomarker profiling to determine clinical impact of microRNAs in cognitive disorders. Sci. Rep. 2024, 14, 8270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, S.; Zhan, X.; He, M.; Wang, J.; Qiu, X. miR-135b levels in the peripheral blood serve as a marker associated with acute ischemic stroke. Exp. Ther. Med. 2020, 19, 3551–3558. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Weng, Y.; Xue, C.; Guo, H.; Zhang, L.; Tang, X. Research progress of miRNA in post-stroke cognitive impairment. Brain Res. Bull. 2026, 237, 111796. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhai, Y.; Zhu, Z.; Li, H.; Zhao, C.; Huang, Y.; Wang, P. miR-195 and miR-497 in acute stroke and their correlations with post-stroke cognitive impairment. Int. J. Clin. Exp. Pathol. 2020, 13, 3092–3099. [Google Scholar] [PubMed]
- Sampath, D.; Branyan, T.E.; Markowsky, K.G.; Gunda, R.; Samiya, N.; Obenaus, A.; Sohrabji, F. Sex differences in cognitive impairment after focal ischemia in middle-aged rats and the effect of iv miR-20a-3p treatment. Neurobiol. Aging 2023, 129, 168–177. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yuan, M.; Guo, Y.S.; Zhang, X.X.; Gao, Z.K.; Shen, X.Y.; Han, Y.; Bi, X. Diagnostic performance of miR-21, miR-124, miR-132, and miR-200b serums in post-stroke cognitive impairment patients. Folia Neuropathol. 2022, 60, 228–236. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Burlacu, C.C.; Ciobanu, D.; Badulescu, A.V.; Chelaru, V.F.; Mitre, A.O.; Capitanescu, B.; Hermann, D.M.; Popa-Wagner, A. Circulating MicroRNAs and Extracellular Vesicle-Derived MicroRNAs as Predictors of Functional Recovery in Ischemic Stroke Patients: A Systematic Review and Meta-Analysis. Int. J. Mol. Sci. 2022, 24, 251. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, T.; Zhao, W.; Liu, Y.; Song, K.; Zeng, J.; Wang, Z. Differentially Expressed miR-511-3p in Stroke Patients Predicts the Presence of Post-Stroke Cognitive Impairment. Dement. Geriatr. Cogn. Disord. 2024, 53, 12–18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ma, Q.; Li, G.; Tao, Z.; Wang, J.; Wang, R.; Liu, P.; Luo, Y.; Zhao, H. Blood microRNA-93 as an indicator for diagnosis and prediction of functional recovery of acute stroke patients. J. Clin. Neurosci. 2019, 62, 121–127. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Z.Q.; Li, K.; Huang, J.; Huo, T.T.; Lv, P.Y. MicroRNA Let-7i Is a Promising Serum Biomarker for Post-stroke Cognitive Impairment and Alleviated OGD-Induced Cell Damage in vitro by Regulating Bcl-2. Front. Neurosci. 2020, 14, 215, Erratum in Front. Neurosci. 2021, 15, 648121. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Z.; Chen, Q.; Dou, C.; Sun, X. Biomarkers for diagnosis of acute ischemic stroke and prediction of post-stroke cognitive impairment: miR-93-3p. Biomark. Med. 2025, 19, 1211–1220. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, Y.; Xu, L.; Zhang, Y.; Zou, C. Prognostic Value of Elevated miR-502-3p in Patients With Post-Stroke Cognitive Impairment. Brain Behav. 2026, 16, e71208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, Y.; Wang, R.; Zeng, J.; Zhao, W.; Xiao, Y.; Jiang, H.; Wang, T. lncRNA six3os1 diagnoses acute stroke, predicts disease severity, and predicts post-stroke cognitive impairment. BMC Neurol. 2024, 24, 491. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, K.; Yang, L.; Zhang, C.; Xing, X.; Su, Z.; Gao, P.; Han, B. NEXN-AS1 Predicts the Occurrence of Post-Stroke Cognitive Impairment and Alleviates Inflammation and Oxidative Stress by Targeting the miR-92a-3p/NRF1 Axis: NEXN-AS1 Alleviates Inflammation and Oxidative Stress in PSCI. Neurochem. Res. 2025, 51, 14. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, C.; Liu, Q.; Wang, J.; Shen, X.; Cao, Z.; Zhang, X.; Chen, Q.; Yu, L.; Chu, Z.; Fang, Q. Circulating circular RNAs as novel biomarkers and functional prediction for the early diagnosis in post-stroke cognitive impairment: A single-center prospective study in China. J. Stroke Cerebrovasc. Dis. 2024, 33, 107945. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Duan, X.; Zhang, Z.; Jia, J.; Jiang, J.; Li, J.; Hu, K.; Niu, R. Histone Deacetylase 4 as a Potential Biomarker for Post-Stroke Cognitive Impairment. Tohoku J. Exp. Med. 2025, 266, 153–160. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Varesi, A.; Carrara, A.; Pires, V.G.; Floris, V.; Pierella, E.; Savioli, G.; Prasad, S.; Esposito, C.; Ricevuti, G.; Chirumbolo, S.; et al. Blood-Based Biomarkers for Alzheimer’s Disease Diagnosis and Progression: An Overview. Cells 2022, 11, 1367. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, Q.; Liu, X.; Zhao, J.; Zhu, R. Circular RNAs: Novel diagnostic and therapeutic targets for ischemic stroke. Expert Rev. Mol. Diagn. 2020, 20, 1039–1049. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cai, Z.; Li, S.; Yu, T.; Deng, J.; Li, X.; Jin, J. Non-Coding RNA Regulatory Network in Ischemic Stroke. Front. Neurol. 2022, 13, 820858. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, M.; Zhou, K.; Li, H.; Dong, X.; Tan, G.; Chai, Y.; Wang, W.; Bi, X. Potential of serum metabolites for diagnosing post-stroke cognitive impairment. Mol. Biosyst. 2015, 11, 3287–3296. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zeki, Ö.C.; Eylem, C.C.; Reçber, T.; Kır, S.; Nemutlu, E. Integration of GC-MS and LC-MS for untargeted metabolomics profiling. J. Pharm. Biomed. Anal. 2020, 190, 113509. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ding, L.; Zhang, M.; Fan, B.; Deng, F.; Li, Z.; Han, Y.; Wu, Y.; Zeng, J.; Lu, L. Metabolomics reveals key biomarkers for ischemic stroke: A systematic review of emerging evidence. Front. Neurol. 2025, 16, 1630390. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lu, Q.; Yu, A.; Pu, J.; Chen, D.; Zhong, Y.; Bai, D.; Yang, L. Post-stroke cognitive impairment: Exploring molecular mechanisms and omics biomarkers for early identification and intervention. Front. Mol. Neurosci. 2024, 17, 1375973. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cuttini, E.; Goi, C.; Pellarin, E.; Vida, R.; Brancolini, C. HDAC4 in cancer: A multitasking platform to drive not only epigenetic modifications. Front. Mol. Biosci. 2023, 10, 1116660. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fitzsimons, H.L.; Schwartz, S.; Given, F.M.; Scott, M.J. The histone deacetylase HDAC4 regulates long-term memory in Drosophila. PLoS ONE 2013, 8, e83903. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xu, Y.; Wei, S.; Zhu, L.; Huang, C.; Yang, T.; Wang, S.; Zhang, Y.; Duan, Y.; Li, X.; Wang, Z.; et al. Low expression of the intestinal metabolite butyric acid and the corresponding memory pattern regulate HDAC4 to promote apoptosis in rat hippocampal neurons. Ecotoxicol. Environ. Saf. 2023, 253, 114660. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, P.; Xin, Y.; Li, C.; Yao, L.; Su, Y. Blood-based biomarkers and neuroimaging for early detection of post-stroke cognitive impairment: Current evidence and synergistic prospects. Front. Neurol. 2025, 16, 1596940. [Google Scholar] [CrossRef] [Scilit] [PubMed]



| Mechanism | Biomarker | Expression Change | Sample Size | Blood Fraction | Cognitive Test | Method | Evidence Level | Ref. |
|---|---|---|---|---|---|---|---|---|
| Inflammation and Immune Biomarkers | CRP | Increase | 48 | Serum | MMSE | ELISA | Moderate | [54] |
| 197 | Serum | MoCA | ELISA | [55] | ||||
| IL-6 | Increase | 238 | Serum | MoCA | ELISA | High | [56] | |
| 190 | Plasma | MoCA | ELISA | [57] | ||||
| 72 | Serum | Unknown | ELISA | [58] | ||||
| 455 | Plasma | MoCA | ELISA | [59] | ||||
| IL-8 | Increase | 236 | Plasma | MMSE | ELISA | Moderate | [60] | |
| 243 | Serum | Unknown | ELISA | [61] | ||||
| IL-10 | Increase | 72 | Serum | Unknown | ELISA | Low | [58] | |
| IL-12 | Increase | 243 | Serum | Unknown | ELISA | Low | [61] | |
| IL-18 | Increase | 236 | Plasma | MMSE | ELISA | Low | [60] | |
| IL-1β | Increase | 72 | Serum | Unknown | ELISA | Low | [58] | |
| MIP-1α | Increase | 455 | Plasma | MoCA | ELISA | Low | [59] | |
| RF | Increase | 638 | Serum | MoCA | Immunological transmission turbidimetry | Moderate | [62] | |
| 582 | Serum | MoCA | Immunological transmission turbidimetry | [63] | ||||
| SAA | Increase | 80 | Serum | MoCA | ELISA | Low | [64] | |
| TSPO | Increase | 276 | Serum | MoCA | ELISA | Low | [65] | |
| HMGB1 | Increase | 192 | Serum | MoCA | ELISA | Moderate | [66] | |
| 16 | Serum | Unknown | ELISA | [67] | ||||
| RAGE | Increase | 172 | Plasma | MoCA | ELISA | Low | [68] | |
| TREM-1 | Increase | 291 | Serum | MoCA | ELISA | Low | [69] | |
| TREM-2 | Increase | 599 | Plasma | MMSE | ELISA | Low | [70] | |
| Galectin-3 | Increase | 416 | Serum | MoCA | ELISA | Low | [71] | |
| NLRP3 | Increase | 108 | Plasma | MoCA | ELISA | Low | [71] | |
| NLR | Increase | 345 | Whole blood | MMSE | Complete blood count | Moderate | [72] | |
| 146 | Whole blood | MoCA | Complete blood count | [73] | ||||
| GLR | Increase | 146 | Whole blood | MoCA | Complete blood count | Low | [73] | |
| CLR | Increase | 146 | Whole blood | MoCA | Complete blood count | Low | [73] | |
| LMR | Decrease | 146 | Whole blood | MoCA | Complete blood count | Low | [73] | |
| K/T | Increase | 41 | Plasma | MMSE | HPLC–MS | Low | [74] |
| Mechanism | Biomarker | Expression Change | Sample Size | Blood Fraction | Cognitive Test | Method | Evidence Level | Ref. |
|---|---|---|---|---|---|---|---|---|
| Oxidative Stress and Metabolic Biomarkers | SOD | Decrease | 187 | Serum | MoCA | Pyrogallol autoxidation | Low | [97] |
| TIBC | Decrease | 500 | Serum | Unknown | Colorimetric method | Low | [98] | |
| 8-OHdG | Increase | 193 | Serum | MMSE | ELISA | Low | [99] | |
| MDA | Increase | 193 | Serum | MMSE | Spectrophotometry | Low | [99] | |
| Polyamine | Increase | 619 | Plasma | MoCA and MMSE | UPLC-TQ-MS | Low | [100] | |
| GGT | Decrease | 1957 | Serum | MoCA | Unknown | Low | [101] | |
| FGF-21 | Increase | 3412 | Plasma | Unknown | ELISA | Moderate | [102] | |
| 600 | Plasma | MoCA and MMSE | ELISA | [103] | ||||
| Serum albumin | Decrease | 424 | Serum | MoCA and MMSE | Unknown | Low | [7] | |
| TG/HDL-C | Increase | 227 | Plasma | MoCA | Unknown | Low | [104] | |
| TyG index | Increase | 313 | Plasma | MoCA | Unknown | Low | [105] | |
| sDPP4 | Decrease | 600 | Plasma | MoCA | ELISA | Low | [106] | |
| L-carnitine | Decrease | 617 | Plasma | MoCA | UHPLC-MS/MS | Low | [107] | |
| Hcy | Increase | 638 | Plasma | MoCA | Enzymatic cycling assay | High | [62] | |
| 325 | Serum | MoCA | Unknown | [108] | ||||
| 81 | Serum | MMSE | ELISA | [109] | ||||
| UA | Increase | 274 | Serum | MoCA | Unknown | Moderate | [110] | |
| 318 | Serum | MoCA | Unknown | [111] | ||||
| SUA/SCr | Decrease | 130 | Serum | MoCA | Unknown | Low | [112] | |
| TMAO | Increase | 256 | Plasma | MMSE | ID-HPLC-MS/MS | Low | [113] | |
| Neu5Ac | Increase | 148 | Serum | Unknown | LC-MS/MS | Low | [114] | |
| PAr | Increase | 422 | Plasma | MoCA | LC-MS/MS | Low | [115] | |
| HKr | Increase | 422 | Plasma | MoCA | LC-MS/MS | Low | [115] | |
| HK | Increase | 422 | Plasma | MoCA | LC-MS/MS | Low | [115] | |
| QA | Increase | 422 | Plasma | MoCA | LC-MS/MS | Low | [115] | |
| QUIN | Increase | 20 | Serum | MoCA and MMSE | HPLC–MS | Low | [116] | |
| QUIN/KYNA ratio | Increase | 20 | Serum | MoCA and MMSE | HPLC–MS | Low | [116] |
| Mechanism | Biomarker | Expression Change | Sample Size | Blood Fraction | Cognitive Test | Method | Evidence Level | Ref. |
|---|---|---|---|---|---|---|---|---|
| Vascular Injury and Endothelial Dysfunction Biomarkers | MMP-9 | Increase | 236 | Plasma | MMSE | ELISA | High | [60] |
| 638 | Serum | MoCA | ELISA | [62] | ||||
| 558 | Serum | MoCA | ELISA | [145] | ||||
| TIMP-1 | Increase | 598 | Serum | MoCA and MMSE | ELISA | Low | [146] | |
| VCAM-1 | Increase | 570 | Serum | Unknown | Magnetic bead-based immunoassay | Low | [147] | |
| CysC | Increase | 1025 | Serum | MoCA | Immunoturbidimetric | Moderate | [148] | |
| 281 | Serum | MoCA | Immunoturbidimetric | [149] | ||||
| VEGF | Increase | 56 | Serum | MoCA | ELISA | Low | [150] | |
| Endostatin | Increase | 613 | Plasma | MoCA | ELISA | Low | [151] | |
| ALP | Increase | 1019 | Serum | MMSE | AMP | Low | [152] | |
| OPG | Increase | 613 | Plasma | MoCA and MMSE | ELISA | Low | [153] | |
| FIB | Increase | 210 | Plasma | MMSE | Coagulation assay | Moderate | [154] | |
| 268 | Plasma | BNIS | Automated clot rate assay | [155] | ||||
| Hb | Decrease | 326 | Whole blood | MMSE | Unknown | High | [156] | |
| 1081 | Whole blood | MMSE | Unknown | [157] | ||||
| 2240 | Whole blood | MoCA | Unknown | [158] | ||||
| Thrombomodulin | Decrease | 615 | Plasma | MoCA | ELISA | Low | [159] |
| Mechanism | Biomarker | Expression Change | Sample Size | Blood Fraction | Cognitive Test | Method | Evidence Level | Ref. |
|---|---|---|---|---|---|---|---|---|
| Neuronal Injury, Neurodegeneration and Synaptic Dysfunction Biomarkers | pNfL | Increase | 1694 | Plasma | MoCA | Simoa | Moderate | [12] |
| 264 | Plasma | MoCA | Simoa | [185] | ||||
| pNfH | Increase | 88 | Serum | MoCA | ELISA | Low | [187] | |
| Tau | Decrease | 55 | Plasma | MoCA | IMR assay | Low | [188] | |
| p-Tau181 | Increase | 136 | Plasma | MoCA | IMR assay | Low | [189] | |
| Aβ1-42 | Decrease | 55 | Plasma | MoCA | IMR assay | High | [188] | |
| 85 | Plasma | MoCA and MMSE | IMR assay | [190] | ||||
| 195 | Serum | MoCA | ELISA | [191] | ||||
| GFAP | Increase | 108 | Plasma | MoCA | ELISA | Moderate | [93] | |
| 336 | Serum | MMSE | ELISA | [192] | ||||
| Neuroglobin | Decrease | 353 | Serum | MoCA | ELISA | Low | [193] | |
| BDNF | Decrease | 660 | Serum | MoCA | ELISA | Low | [194] | |
| NPTX2 | Decrease | 134 | Serum | MoCA | ELISA | Low | [195] | |
| RA | Decrease | 261 | Serum | MoCA | ELISA | Low | [196] | |
| BACE1 | Increase | 152 | Serum | MoCA | ELISA | Low | [197] | |
| sRAGE | Decrease | 152 | Serum | MoCA | ELISA | Low | [197] | |
| T3 | Decrease | 195 | Serum | MoCA | CLIA | Low | [191] | |
| NPY | Increase | 593 | Plasma | MoCA | ELISA | Low | [198] |
| Mechanism | Biomarker | Expression Change | Sample Size | Blood Fraction | Cognitive Test | Method | Evidence Level | Ref. |
|---|---|---|---|---|---|---|---|---|
| Regulatory Molecules And Emerging Biomarkers | miR-195 | Increase | 108 | Serum | MoCA | RT-qPCR | Low | [229] |
| miR-497 | Increase | 108 | Serum | MoCA | RT-qPCR | Low | [229] | |
| miR-21 | Decrease | 77 | Serum | MMSE | RT-qPCR | Low | [231] | |
| miR-511–3p | Decrease | 169 | Serum | MoCA | RT-qPCR | Low | [233] | |
| miR-93 | Decrease | 33 | Plasma | Unknown | RT-qPCR | Low | [234] | |
| miR-let-7i | Increase | 74 | Serum | MoCA | RT-qPCR | Low | [235] | |
| miR-93-3p | Increase | 172 | Serum | MoCA | RT-qPCR | Low | [236] | |
| miR-502-3p | Increase | 273 | Serum | MoCA | RT-qPCR | Low | [237] | |
| SIX3OS1 | Increase | 138 | Serum | MoCA | RT-qPCR | Low | [238] | |
| NEXN-AS1 | Decrease | 159 | Serum | Unknown | RT-qPCR | Low | [239] | |
| hsa_circ_0089762 | Increase | 83 | Plasma | MoCA | RT-qPCR | Low | [240] | |
| hsa_circ_0089763 | Increase | 83 | Plasma | MoCA | RT-qPCR | Low | [240] | |
| hsa_circ_0064644 | Increase | 83 | Plasma | MoCA | RT-qPCR | Low | [240] | |
| HDAC4 | Decrease Or Increase | 139 | Whole blood | Unknown | RT-qPCR | Low | [241] |
| Biomarker Category | Representative Biomarkers | Evidence Level | Validation Status | Clinical Applicability |
|---|---|---|---|---|
| Neuronal Injury, Neurodegeneration and Synaptic Dysfunction Biomarkers | Aβ1-42 PNfL GFAP | High | Increasing evidence from prospective cohorts; PSCI-specific external validation is still needed | Among the most promising candidates due to the biological relevance and improved detection sensitivity |
| Inflammation and Immune Biomarkers | IL-6 IL-8 RF HMGB1 NLR | Moderate-High | Associations reported in multiple cohorts; however, external validation remains limited | High accessibility, low cost, and easy clinical implementation; however, insufficient specificity limits independent clinical use |
| Oxidative Stress and Metabolic Biomarkers | Hcy FGF-21 UA | Moderate | Evidence is mainly from small observational cohorts with limited replication | Evidence is mainly from small observational cohorts with limited replication |
| Vascular Injury and Endothelial Dysfunction Biomarkers | MMP-9 Hb CysC FIB | Moderate | Supported by several studies, standardized protocols and multicenter validation are lacking | Provide additional information for PSCI risk stratification when combined with clinical characteristics and neuroimaging findings |
| Regulatory Molecules And Emerging Biomarkers | miR-195 miR-497 | Low- Moderate | Mostly exploratory studies with limited independent replication | Provide novel insights into PSCI mechanisms and precision medicine approaches, but not currently ready for routine clinical use |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Pu, J.; Guo, W.; Li, H.; Wang, Z.; Mu, T.; Xie, F.; Chen, J.; Cao, J.; Zhong, C.; Li, H.; et al. Blood-Based Biomarkers for Post-Stroke Cognitive Impairment. Curr. Issues Mol. Biol. 2026, 48, 702. https://doi.org/10.3390/cimb48070702
Pu J, Guo W, Li H, Wang Z, Mu T, Xie F, Chen J, Cao J, Zhong C, Li H, et al. Blood-Based Biomarkers for Post-Stroke Cognitive Impairment. Current Issues in Molecular Biology. 2026; 48(7):702. https://doi.org/10.3390/cimb48070702
Chicago/Turabian StylePu, Jie, Wang Guo, Hongxin Li, Zhihao Wang, Tangda Mu, Fuli Xie, Jie Chen, Jiawei Cao, Chengfei Zhong, Hongyu Li, and et al. 2026. "Blood-Based Biomarkers for Post-Stroke Cognitive Impairment" Current Issues in Molecular Biology 48, no. 7: 702. https://doi.org/10.3390/cimb48070702
APA StylePu, J., Guo, W., Li, H., Wang, Z., Mu, T., Xie, F., Chen, J., Cao, J., Zhong, C., Li, H., & Tang, Q. (2026). Blood-Based Biomarkers for Post-Stroke Cognitive Impairment. Current Issues in Molecular Biology, 48(7), 702. https://doi.org/10.3390/cimb48070702